Experts Accuse CDC of ‘Cherry-Picking’ Data on Vaccine Immunity to Support Political Narrative
By Megan Redshaw | The Defender | September 16, 2021
There is now a growing body of literature showing natural immunity not only confers robust, durable and high-level protection against COVID, but also provides better protection than vaccine-induced immunity.
Yet, the Centers for Disease Control and Prevention (CDC) is ignoring the long-standing science of natural immunity when it comes to COVID — while acknowledging the benefits of natural immunity for other diseases — according to an expert who accused the agency of providing contradictory, ‘illogical’ COVID messaging.
Dr. Marty Makary, professor of surgery and health policy at John Hopkins University, on Tuesday accused the CDC of “cherry-picking” data and manipulating public health guidance surrounding vaccines and natural immunity to support a political narrative.
Makary joined the “Clay Travis and Buck Sexton Show” to discuss the clinical impact of natural immunity as it compares to the vaccine.
During the show, Travis pointed out the CDC’s guidance on COVID is inconsistent with its vaccine recommendations for other contagious viruses, like chickenpox.
The CDC’s current guidance for chickenpox, for example, does not encourage those who have contracted it to vaccinate themselves against the virus. The CDC only recommends two doses of chickenpox vaccine for children, adolescents and adults who have never had chickenpox.
“So why doesn’t the CDC say the same thing about those of us who already had COVID?” Travis asked.
Makary called the conflicting guidance “absolutely illogical,” and accused the agency of “ignoring natural immunity.”
“It doesn’t make sense with what they’re putting out on chickenpox,” Makary said. It’s like they have adopted the immune system for one virus, but not for another virus, he said, and “cherry-picking the data to support whatever they’ve already decided.”
“They salami slice it — something we call fishing in statistical techniques,” Makary said. “That is when you look for a tiny sliver of data that supports what you already believe.”
According to a Sept. 13 article in The BMJ, when the COVID vaccine rollout began in mid-December 2020, more than a quarter of Americans — 91 million — had been infected with SARS-CoV-2, according to CDC estimates.
As of this May, that proportion had risen to more than a third of the population, including 44% of adults between the ages of 18 and 59.
However, the CDC instructed everyone, regardless of previous infection, to get fully vaccinated as soon as they were eligible. On its website, the agency in January justified its guidance by stating natural immunity “varies from person to person” and “experts do not yet know how long someone is protected.
By June, a Kaiser Family Foundation survey found 57% of those previously infected got vaccinated.
Dr. Anthony Fauci, President Biden’s chief medical advisor, was asked Sept. 10 by CNN’s Dr. Sanjay Gupta whether people who have tested positive for the virus should still get a vaccine.
Gupta cited recent data from Israel suggesting people who recovered from COVID had better protection and a lower risk of contracting the Delta variant, compared to those with Pfizer-BioNTech’s two-dose vaccine-induced immunity.
“I don’t have a really firm answer for you on that,” Fauci said. “That’s something we’re going to have to discuss regarding the durability of the response.”
The research from Israel did not address the durability that natural immunity offers. Fauci said it is possible for a person to recover from COVID and develop natural immunity, but that protection might not last for nearly as long as the protection provided by the vaccine.
“I think that is something that we need to sit down and discuss seriously,” Fauci said.
Numerous studies, however, have shown people who recovered from COVID have robust, durable and long-lasting immunity.
Evidence of natural immunity
As early as November 2020, important studies showed memory B cells and memory T cells formed in response to natural infection — and memory cells respond by producing antibodies to variants at hand.
A study funded by the National Institutes of Health and conducted by the La Jolla Institute for Immunology, found “durable immune responses” in 95% of the 200 participants up to eight months after infection.
One of the largest studies to date, published in Science in February 2021, found that although antibodies declined over eight months, memory B cells increased over time, and the half-life of memory CD8+ and CD4+ T cells suggests a steady presence.
In a study by New York University published May 3, the authors studied the contrast between vaccine immunity and immunity from prior infection as it relates to stimulating the innate T-cell immunity — which is more durable than adaptive immunity through antibodies alone.
The authors concluded:
“In COVID-19 patients, immune responses were characterized by a highly augmented interferon response which was largely absent in vaccine recipients. Increased interferon signaling likely contributed to the observed dramatic upregulation of cytotoxic genes in the peripheral T cells and innate-like lymphocytes in patients but not in immunized subjects.”
The study further noted:
“Analysis of B and T cell receptor repertoires revealed that while the majority of clonal B and T cells in COVID-19 patients were effector cells, in vaccine recipients, clonally expanded cells were primarily circulating memory cells.”
This means natural immunity conveys much more innate immunity, while the vaccine mainly stimulates adaptive immunity — as effector cells trigger an innate response that is quicker and more durable, whereas memory response requires an adaptive mode that is slower to respond.
According to a longitudinal analysis published July 14 in Cell Medicine, most recovered COVID patients produced durable antibodies, memory B cells and durable polyfunctional CD4 and CD8 T cells –– which target multiple parts of the virus.
“Taken together, these results suggest broad and effective immunity may persist long-term in recovered COVID-19 patients,” the authors said.
In other words, unlike with the vaccines, no boosters are required to assist natural immunity.
In a May 12 study conducted by the University of California, researchers found natural immunity conveyed stronger immunity than the vaccine.
The researchers wrote:
“In infection-naïve individuals, the second [vaccine] dose boosted the quantity but not quality of the T cell response, while in convalescents the second dose helped neither. Spike-specific T cells from convalescent vaccinees differed strikingly from those of infection-naïve vaccinees, with phenotypic features suggesting superior long-term persistence and ability to home to the respiratory tract including the nasopharynx.”
According to The BMJ, studies in Qatar, England, Israel and the U.S. have found infection rates at equally low levels among people who are fully vaccinated and those who have previously had COVID.
As The Defender reported in June, the Cleveland Clinic surveyed more than 50,000 employees to compare four groups based on history of SARS-CoV-2 infection and vaccination status.
Not one of more than 1,300 unvaccinated employees who had been previously infected tested positive during the five months of the study. Researchers concluded the cohort “are unlikely to benefit from COVID-19 vaccination.”
In the largest real-world observational study comparing natural immunity gained through previous SARS-CoV-2 infection to vaccine-induced immunity afforded by the Pfizer vaccine, researchers in Israel found people who recovered from COVID were much less likely than never-infected, vaccinated people to get Delta, develop symptoms or be hospitalized.
“Our results question the need to vaccinate previously infected individuals,” they concluded.
Experts speak out on natural immunity
In a recent letter to the editor of The BMJ, Dr. Manish Joshi, a pulmonologist at UAMS Health; Dr. Thaddeus Bartter, a pulmonologist at UAMS Health; and Anita Joshi, BDS, MPH, said data demonstrate both adequate and long-lasting protection in those who have recovered from COVID, while the duration of vaccine-induced immunity is not fully known.
The authors of the letter said the “SIREN” study in the Lancet addressed the relationships between seropositivity in people with previous COVID infection and subsequent risk of severe acute respiratory syndrome due to SARS-CoV-2 infection over the subsequent seven to 12 months.
The study found prior infection decreased risk of symptomatic reinfection by 93%.
A large cohort study published in JAMA Internal Medicine which looked at 3.2 million U.S. patients, showed the risk of infection was significantly lower (0.3%) in seropositive patients compared to those who were seronegative (3%).
A recent study published in May in the journal Nature demonstrated the presence of long-lived memory immune cells in those who have recovered from COVID-19 suggesting durable and long-lasting immunity.
“This implies a prolonged (perhaps years) capacity to respond to new infection with new antibodies,” the authors wrote.
© [Sept. 2021] Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
The Meaning of the FDA Resignations

By Jeffrey A. Tucker | Brownstone Institute | September 14, 2021
How significant is it that the two top FDA officials responsible for vaccine research resigned last week and this week signed a letter in The Lancet that strongly warns against vaccine boosters? This is a remarkable sign that the project of government-managed virus mitigation is in the final stages before falling apart.
The booster has already been promoted by top lockdown advocates Neil Ferguson of Imperial College and Anthony Fauci of NIH, even in the face of rising public incredulity toward their “expert” advice. For these two FDA officials to go on record with grave doubts – and their perspective is certainly backed by the unimpressive booster experience in Israel – introduces a major break in the narrative that the experts in charge deserve our trust and deference.
What’s at stake here? It’s about more than the boosters. It’s about the whole experience of taking away the control of health management from individuals and medical professionals and handing it over to modelers and government officials with coercive power.
From the first week of March 2020, the US embarked on a wild experiment in virus mitigation, deploying a series of measures with a sweep and scope that had never previously been attempted, not in modern times and not even in ancient times. The litany of controls and tactics is long. Many of these measures survive in most parts of the US. The retail landscape is still filled with plexiglass. We are still invited to sanitize ourselves when going indoors. People still mask up in proximity to others. The “Karens” of the world are still actively shaming and denouncing anyone suspected of non-compliance.
The vaccine push has been particularly divisive, with President Biden actively encouraging “anger” at those who don’t get the jab, even as he refuses to acknowledge the existence of infection-induced immunities. In several cities, people who refuse vaccines are being denied active participation in civic life, and a populist movement is rising up that scapegoats the refuseniks as the only reason that the virus continues to be a problem.
All these measures were deployed in waves of controls. It all began with event cancellations and school closures. It continued with travel bans, most of which are still in place. Sanitization and plexiglass were next. Masks were rolled out and then mandated. The principle of forced human separation governed social interactions. Capacity limits indoors were a common feature. The US example inspired many governments around the world to adopt these NPIs (non-pharmaceutical interventions) and take away the liberties of the people.
At each stage of control, there were new claims that we’ve finally found the answer, the key technique that would finally slow and stop the spread of SARS-CoV-2. Nothing worked, as the virus seemed to follow its own course regardless of all these measures. Indeed there was no observable difference anywhere in the world based on whether and to what extent any of these measures were deployed.
Finally came the pharmaceutical interventions, voluntary at first but gradually mandatory, just as with each previous protocol began as a recommendation until it was mandated.
At no point in these 19 months have we seen a clear admission of failure on the part of government officials. Indeed, it’s mostly been the opposite, as the agencies double down, claiming effectiveness while citing no data or studies, while social media companies backed it all by taking down contrarian posts and brazenly deleting accounts of people who dare cite dissenting science.
The vaccine was the biggest gamble of all simply because the program was so expensive, so personal, and so wildly oversold. Even those of us who opposed every other mandate had hopes that the vaccines would finally end the public panic and provide governments a way to back out of all the other strategies that had failed.
That did not happen.
Most people believed that the vaccine would work like many others before them to block infection and spread. In this, people were merely believing what the head of the CDC said. “Our data from the C.D.C. today suggests that vaccinated people do not carry the virus, don’t get sick,” Rochelle Walinsky told Rachel Maddow. “And that it’s not just in the clinical trials, it’s also in real-world data.”
“You’re not going to get COVID if you have these vaccinations,”President Biden said, reflecting what was the common view in the summer of 2021.
That of course turned out not to be the case. The vaccines appear to have been helpful in mitigating against some severe outcomes but it did not achieve victory over the virus. Israel’s surge in infections in August was among the fully vaccinated. The same happened in the UK and Scotland, and that precise result began to hit the US in September. Indeed, we all have vaccinated friends who caught the virus and were sick for days. Meanwhile, team natural immunity has received a huge boost from a large study in Israel that demonstrated that recovered Covid cases gain far more protection than is conferred by the vaccine.
The fallback position then became the booster. Surely this is the answer! Israel was first to mandate them. Here again, the problems began to show, as yet another magic bullet of disease mitigation failed. Then the inevitable headline came: Israel preparing for possible fourth COVID vaccine dose. So think about this because there is a sense in which the vaccines rank among the biggest failures: in a matter of a few short months, we’ve gone from the claim that they fully protect to they are pretty okay provided you get regularly scheduled boosters forever.
Now to the striking resignation of two top officials at the FDA who were in charge of vaccine safety and administration. It was the Director and Deputy Director of the Office of Vaccines Research, Marion Gruber and Phillip Kause. They gave no reason for their departure, which is scheduled for October and November.
The case is fascinating because 1) people rarely resign cushy government jobs unless a higher-paying, higher-prestige job in the private sector awaits, or 2) they are being pushed out. It’s rare for anyone in a position like that to resign over a principled matter of science. When I first read that they were going, I figured something else was up.
These days, extremely weird things are going on within the Biden administration. Even though his approval ratings are sinking, the president has to pretend that he has all the answers, that the science behind his mandates and virus war is universally settled, that anyone who disagrees with him is really just a political enemy. He has gone so far as to denounce, demonize, and legally threaten red-state governors who disagree with him.
This is a deep problem for actual scientists working within the bureaucracy because they know for sure that all of this is a pretense and that the government cannot win this war on the virus. They simply cannot preside over more false promises, especially when the whole of their professional training is about assessing the safety and effectiveness of vaccines.
So what can they do? In this case, it appears they had to get away before they dropped a bombshell.
The bombshell is called “Considerations in boosting COVID-19 vaccine immune responses.” It appears in the prestigious British medical journal The Lancet. The two top officials are among the authors. The article recommends against the Covid booster shot that the Biden administration, following Fauci’s advice, is suggesting as the key to making the vaccines work better and finally fulfill their promise.
Fauci and company are pushing boosters because they know what is coming. Essentially we are going the way of Israel: most everyone is vaccinated but the virus itself is not being controlled. More and more among those hospitalized and dying are vaccinated. This same trend is coming to the US. The boosters are a means by which government can save face, or so many believe.
The trouble now is that the top scientists at the FDA disagree. Further, they think that the push for boosters is courting problems. They think the current regime of one or two shots is working as well as one can expect. Nothing is gained on net from a booster, they say. There just isn’t enough evidence to take the risk of another booster, and another and another.
The authors knew this article was appearing. They knew that signing it under the FDA affiliation would lead to a push for their resignations. Life would get very difficult for both of them. They got ahead of the messaging and resigned before it came out. Very smart.
The signed article goes even further to warn of possible downsides. They point out that boosters might seem necessary because “variants expressing new antigens have evolved to the point at which immune responses to the original vaccine antigens no longer protect adequately against currently circulating viruses.” At the same time, there are possible side effects that could discredit all vaccines for a generation or more. “There could be risks,” they write, “if boosters are widely introduced too soon, or too frequently, especially with vaccines that can have immune-mediated side-effects (such as myocarditis, which is more common after the second dose of some mRNA vaccines, or Guillain-Barre syndrome, which has been associated with adenovirus-vectored COVID-19 vaccines.”)
Bringing up such side effects is essentially a taboo topic. That this was written by two top FDA officials is nothing short of remarkable, especially because it comes at a time when the Biden administration is going all in on vaccine mandates. Meanwhile, studies are showing that for teenage boys, the vaccine poses a greater risk to them than Covid itself. “For boys 16-17 without medical comorbidities, the rate of CAE is currently 2.1 to 3.5 times higher than their 120-day COVID-19 hospitalization risk, and 1.5 to 2.5 times higher at times of high weekly COVID-19 hospitalization.”
From the beginning of these lockdowns – along with all the masks, restrictions, bogus health advice from plexiglass to sanitizer to universal vaccine mandates and so on – it was clear that there would someday be hell to pay. They wrecked rights and liberties, crashed economies, traumatized a whole generation of children and other students, ran roughshod over religious freedom, and for what? There is zero evidence that any of this has made any difference. We are surrounded by the carnage they created.
The appearance of The Lancet article by two top FDA vaccine scientists is truly devastating and revealing because it undermines the last plausible tool to save the whole machinery of government disease management that has been deployed at such enormous social, cultural, and economic cost for 19 months. Not in our lifetimes has a policy failed so badly. The intellectual and political implications here are monumental. It means that the real Covid crisis – the task of assigning responsibility for all the collateral damage – has just begun.
In 2006, during the early years of the birth of lockdown ideology, the great epidemiologist Donald Henderson warned that if any of these restrictive measures were deployed for a pandemic, the result would be a “loss of trust in government” and “a manageable epidemic could move toward catastrophe.” Catastrophe is exactly what has happened. The current regime wants to point the finger toward the noncompliant. That is no longer believable. They cannot delay the inevitable for much longer: responsibility for this catastrophe belongs to those who embarked on this political experiment in the first place.
Jeffrey A. Tucker is Founder and President of the Brownstone Institute and the author of many thousands of articles in the scholarly and popular press and ten books in 5 languages, most recently Liberty or Lockdown.
Local TV Asks for Stories of Unvaxxed Dying from COVID, Gets over 180K Responses of Vaccine Injured and Dead

Source.
By Brian Shilhavy | Health Impact News | September 15, 2021
The corporate media narrative that unvaccinated people are filling up the hospitals and dying from COVID is quickly falling apart, perhaps faster than they even expected.
WXYZ TV Channel 7 in Detroit asked their viewers on their Facebook Page last Friday to direct message them if they lost a loved one due to COVID-19 if they refused to get one of the COVID-19 vaccines.
This is a clear indication that they are getting desperate to find these stories, and are having a difficult time finding them.
I don’t know if they got any such stories through direct messaging, but the post on their Facebook Page, as of the time of publication today, had received over 182,000 comments, and they seem to be all comments of those who have lost loved ones after receiving a COVID shot, and comments asking them why they are not covering that story.
I paged through many dozens of the comments, and did not see a single one stating that they lost someone to COVID after refusing a COVID-19 shot.
People who have been silenced and censored on Facebook and other Big Tech platforms took advantage of the opportunity to share their stories instead. It is amazing that Facebook left these up, but after so many had commented, it would probably have been an even bigger story if they had taken down the post and comments.
I wonder what WXYZ will do now? Will they do what most corporate media companies do, fueled by almost unlimited resources from their billionaire Wall Street owners who are almost all connected to the pharmaceutical industry, and just go out and hire actors instead to do the story and make them up?
Here are a few screen shots of the comments that are representative of what people are posting, in case they do take this down.


35,000 Women Report Period Problems After Covid Jab
By Richie Allen | September 16, 2021
Around 35,000 women have come forward to report irregularities with their menstrual cycle, including abnormal period pain, after they received a covid jab.
Writing in the British Medical Journal (BMJ), Dr. Victoria Dale called for an investigation. She lectures on reproductive immunology at Imperial College London.
Incredibly, The Medicines and Healthcare Products Regulatory Agency (MHRA), the UK’s drug watchdog, has refused to accept that there is a link between the jabs and menstrual cycle problems.
According to the MHRA:
“The rigorous evaluation completed to date does not support a link between changes to menstrual periods and related symptoms and Covid vaccines.”
According to The Mail Online this morning:
Data on the number of period problems following vaccination was collected from the MHRA’s Yellow Card Scheme, which keeps a record of every case of a potential side effect. But this data is reliant on women coming forward, meaning nearly 35,000 figure could be the tip of the iceberg.
So-called experts were rushed onto UK TV and radio shows this morning to assure the public that even if there is a link between the jabs and period problems, the jabs do not affect fertility.
They’re lying. I am not saying that I know the jabs affect fertility. I do not know that. But equally they cannot know that the jabs do not affect fertility in males or females.
That’s because they have no long-term data on how the jabs affect fertility or anything else for that matter. I really hope this information is getting through to people. The jabs are unnecessary, untried, unsafe and the manufacturers have been indemnified against legal action from anyone injured by their products.
As BoJo prepares Britain for another winter of Covid restrictions, it’s still not enough for the hardliners
By Neil Clark | RT | September 15, 2021
The UK government’s ‘Winter Plan’ for Covid is likely to mean the attempted introduction of vaccine passports and more lockdowns. It’s all a far cry from the freedom we were promised would come with mass vaccination.
Suppose someone had told you back in March 2020, that, 18 months later, despite two-thirds of the population being double-vaccinated, Britain would be facing the prospect of another depressing autumn and winter of Covid restrictions and lockdowns?
Well, there were people back then who warned such things would happen, that life would never be allowed to get back to the ‘old’ normal and that the governing, globalist elite was working to a different plan that had little to do with countering a virus. These people were denounced as ‘conspiracy theorists’ and ‘crackpots’. Yet, after Prime Minister Boris Johnson’s unveiling of yesterday’s ‘Winter Plan’ for England, it seems the ‘conspiracy theorists’ and ‘crackpots’ have got it right once again.
Plan A is learning to live with Covid. But this doesn’t mean living totally normally. There will still be border restrictions. We’ll still be urged – some would say coerced – to get the booster jab and to have our kids vaccinated too (even though, less than a fortnight ago, the Joint Committee on Vaccination and Immunisation didn’t recommend it). We’ll still be encouraged to wear masks in certain settings.
Yet for all its downsides, life under Plan A is still better than the alternative, Plan B. This “toolkit” includes the return of mandatory masks, and the introduction of jab-only vaccine passports for large events, which could be extended to other gatherings too. And, most revealingly of all, further lockdowns are not ruled out, despite the disastrous impact they have had on both the economy and on society.
Let’s be clear what we are dealing with here: it’s psychological warfare on an industrial scale. The semblance of normality that Plan A gives us can be withdrawn at very short notice and Plan B – or parts of it – will be put into operation if ‘cases’ surge and the NHS comes under “unsustainable pressure.” But the NHS comes under pressure every winter, meaning Plan B is actually Plan A. Plan B is clearly what the government really wants to implement, but Johnson knows that, to keep disgruntled Tory backbenchers on side, he can’t do so straightaway.
Hospitals are nearly always close to capacity in December and January. Inevitably, once the flu/cold season starts up again in October, and with mass testing still in place, we’ll see a rise in ‘cases’, which will then see Johnson reach for his “toolkit.” That will be preceded by the usual doomladen and ludicrously over-the-top predictions from ‘modellers’ and ‘advisers’ of what will happen if the Prime Minister fails to ‘act’.
‘Something must be done!’ will be the cry from those who will lose nothing financially from another lockdown.
In fact, the calls for an immediate return of restrictions have already begun. A headline on the BBC News website reads, “Hospital Covid cases may see big jump, say experts.” The piece refers to how the Scientific Advisory Group for Emergencies (SAGE) committee modelling “suggested” hospitalisation could reach 2,000 to 7,000 per day next month.
We’ve been here before. Lots of times. Only a few months ago, there were dire predictions from ‘modellers’ and ‘experts’ of what would happen if restrictions were lifted in England in July. A member of Independent SAGE – which is even more hardline than SAGE – said the UK could face cases of more than 100,000 a day if lockdown easing went ahead. Well, lockdown easing did go ahead, and guess what? Cases fell. From 43,910 cases (on a seven-day average) on July 16 to 23,002 by the end of the month.
We’re meant, though, to have the memory of a gnat and to have forgotten how wrong the ‘modellers’ have consistently been, and to be terrified once again by their latest ‘predictions’, which make Private Frazer of 1970s sitcom ‘Dad’s Army’ fame – whose catchphrase was “We’re doomed!” – sound like the world’s greatest optimist.
With all the sensationalist ‘cases set to surge this autumn unless restrictions are re-imposed’ headlines, I expect that, straight after next month’s Tory Party conference – and after the Coronavirus Act has been renewed for another six months – Johnson will reach for his “toolkit” and bring back mandatory masks. Then, a few weeks after that, it’ll be ‘accept jab-only vaccine passports or we’ll have to do another lockdown’.
But hang on a minute… weren’t the vaccines meant to put an end to all of this? “15 million jabs to freedom” was the famous headline in the Daily Mail last 27 December. Yet with 66% of the population double-vaxxed – and around 90% of those deemed the most ‘vulnerable’ having had their jabs – we have more ‘cases’ and deaths with Covid than we did this time last year, when no one was vaccinated. How come?
On ‘Good Morning Britain’, Richard Madeley, a proper ‘old-school’ journalist asked this emperor’s new clothes question to Dr Hilary Jones. Jones struggled to answer and kept muttering about cases being higher this year. But if the vaccines work so well, and so many people have been vaccinated, why are we even talking of having more restrictions this autumn and winter? Either the vaccines work or they don’t. If they work, then there’s no need to discuss restrictions. If they don’t, then why push them?
The government line is we need more jabs and a “toolkit” of restrictions too. More lockdowns as a “last resort,” if cases surge, “to protect the NHS.” And vaccine passports too – without a negative-test or prior-infection option – even though we know the vaccines don’t prevent transmission.
Like the autumn and winter of 2020-21, this coming ‘winter of discontent’, of fear and dread, and restrictions being imposed or re-imposed at a moment’s notice, is meant to be our ‘new normal’. Which means this will only end when people realise it’s never meant to end.
Neil Clark is a journalist, writer, broadcaster and blogger. His award winning blog can be found at http://www.neilclark66.blogspot.com.
BBC chairman calls for crackdown on speech online
By Christina Maas | Reclaim The Net | September 15, 2021
Richard Sharp, BBC Chairman, is likely to back proposals to increase regulation of the world’s largest social networks and platforms to combat “fake news” and “disinformation.”
It is pertinent to ask “urgent questions” about these platforms, since platforms have allowed lies, conspiracy theories, and falsehoods to spread rapidly, the chairman claimed in a speech to the Royal Television Society convention.
Since assuming office in February, Sharp will make his first significant public statement, calling for an update to outdated Communications Act of 2003, calling for a crackdown on speech online.
He continued stating that he wants the BBC “to define itself globally as a pre-eminent purveyor of facts in the disinformation age.”
Sharp also claimed that “The pandemic and ‘infodemic’ that has spread alongside have left us in no doubt of how vulnerable we all are. But it has also suggested that some are more vulnerable than others…. The magnetic draw of conspiracy theories in our societies is getting stronger. And we can no longer pretend it doesn’t have real-life consequences – whether it’s pulling down 5G masts, driving down vaccine take up, or leaving the results of democratic elections in doubt, ” Televisual reported.
Even though the provision of fact-checking services and coordinating efforts between platforms and credible news organizations to detect misinformation is important, Sharp alleged more needed to be done.
“There are urgent questions to be answered about the future media world we want to live in. We need to rethink the regulatory environment in this country – and replace a Communications Act that predates Facebook with one that can deliver on a clear vision,” the chairman said.
“But we also need to look at where the digital world comes up against the fundamental rights, freedoms and privacies we sign up to as societies and individuals. Does the principle of media freedom need to be redefined and re-enshrined for the digital age? Do we need to claim our personal data as a human right, rather than an asset to be bought and sold?”
AMA issues mix of mindless propaganda & “Trust the SCIENCE” jargon to teach doctors to lie about Covid jabs
By Meryl Nass, MD | September 14, 2021
I am looking over the “AMA Covid -19 Guide. Winter 2021. It is not a guide. It only deals with Covid vaccines, not treatment. It’s raison d’etre is:
“To overcome vaccine hesitancy and ensure widespread vaccine acceptance among all demographic groups, physicians and the broader public health community must continue working to build trust in vaccine safety and efficacy, especially in marginalized and minoritized (this is not my misspelling–Nass) communities with historically well-founded mistrust in medical institutions. As COVID-19 vaccines become more widely available, it is critical that physicians continue to ensure they practice and encourage their patients to wear masks, physical distance and wash hands until a critical mass of the population is vaccinated.”
It is an extraordinary document. I wonder how much the AMA got paid to put their name on it. Probably a lot.
It is extraordinary because it would repel most doctors. It was obviously written by a non-doctor. I have an idea of one person who may have had a hand in creating it–John Grabenstein, a pharmacist and propagandist extraordinaire, who helped craft the fake science on the anthrax vaccine. He works for the Immunization Action Coalition now. He is a one man band who knows how to pull all the levers to push terrible vaccine policies.
It turns out that the current AMA President, Gerald Harmon, was instrumental in pushing the experimental and dangerous anthrax vaccine, and punishing refusers and truth tellers. This got him rapid promotions, and he retired as a Major General. No doubt he worked with Grabenstein back then, and probably now.
Whoever wrote the “Guide” did not know that whooping cough and pertussis were the same thing, or that the DTP vaccine includes tetanus. It is of interest that there is no name on it, no clue about how it came into existence.
All this business about “equity.” If the federal government cared about equity, why are they always bombing and droning people of color? What equity means to them is that a 25% acceptance of the Covid vaccine by Black people cannot be allowed to stand. And the refusal by blacks to participate in clinical trials is especially egregious.
The document is really kind of a hoot, it is so out of 1984. It shows you what the propagandists are really worried about, for example, the fact that too many people have learned the FDA “review” and the Pfizer preclinical tests were bogus:
On combating the spread of vaccine misinformation:
• With misinformation about the COVID-19 vaccine development process circulating widely, new AMA policy seeks to educate physicians on speaking with their patients about the vaccine and provide culturally appropriate education materials for all patients.
On vaccine development:
• To help physicians promote vaccine confidence among patients and the general public, we must continue to instill confidence in the information, education, and transparency around the FDA’s process for authorization or licensure, as well as the standards by which FDA will review future vaccine candidates and the clinical endpoints the FDA hopes to achieve.
• Physicians must be continuously updated about the review process for future COVID-19 vaccines. Any available safety and efficacy data must be in place as soon as possible so that any questions or concerns about the vaccine candidates can be addressed.
• The AMA has been talking to FDA officials about the role the agency needs to continue to play in alleviating vaccine concerns by ensuring the process is transparent and based on science.
• The widespread availability and adoption of a safe and efficacious vaccine will play an essential role in slowing transmission of COVID-19 and allow us to move safely and confidently toward the full re-opening of our businesses and schools, helping ease Americans back toward pre-pandemic life.
• Research shows growing levels of confidence in the safety and effectiveness of the COVID-19 vaccines, but there continues to be vacancy hesitancy among some individuals and in some communities, which we are striving to overcome.
• What’s clear is that the benefits of getting the vaccine to protect you from COVID-19 exceed the risks, which is why medical experts strongly recommend getting the vaccine.
• To improve the dialogue and provide opportunities for physicians to learn more about vaccine development, approval, and ongoing distribution plans and challenges, AMA has initiated a series of “town hall” type webinars with physicians and career staff at both the FDA and CDC. All events are archived on AMA’s website.
• To develop the most effective COVID-19 vaccine, U.S. clinical trials must include representation of all Americans to ensure treatments are studied in every population that may use it.
The AMA is pleased that efforts have been made by institutions to acknowledge the exclusion of Black and Latinx people from clinical trials historically.
Now there are many efforts underway to ensure Black and Latinx people, who have been disproportionately affected by the virus, are prioritized in clinical trials.
This not only provides better safety and efficacy data but is a more equitable strategy that will hopefully contribute to trust in the vaccine once available.
Shockingly, CDC Now Lists Vaccinated Deaths as Unvaccinated
By Dr. Joseph Mercola | September 15, 2021
While public health officials and mainstream media claim the COVID-19 pandemic is now “a pandemic of the unvaccinated,”1 we now know this claim is based on highly misleading statistics.
In a July 16, 2021, White House press briefing,2 U.S. Centers for Disease Control and Prevention director Dr. Rochelle Walensky claimed that “over 97% of people who are entering the hospital right now are unvaccinated.” A few weeks later, in an August 5, 2021, statement, she inadvertently revealed how that statistic actually came about.3
As it turns out, the CDC was looking at hospitalization and mortality data from January through June 2021 — a timeframe during which the vast majority of the U.S. population were still unvaccinated.4
But that’s not the case at all now. The CDC is also playing with statistics in other ways to create the false and inaccurate impression that unvaccinated people make up the bulk of infections, hospitalizations and deaths. For example, we now find out the agency is counting anyone who died within the first 14 days post-injection as unvaccinated.
Not only does this inaccurately inflate the unvaccinated death toll, but it also hides the real dangers of the COVID shots, as the vast majority of deaths from these shots occur within the first two weeks.5 Now their deaths are counted as unvaccinated deaths rather than being counted as deaths due to vaccine injury or COVID-19 breakthrough infections!
How CDC Counts Breakthrough Cases
According to the CDC,6 you’re not counted as fully vaccinated until a full 14 days have passed since your second injection in the case of Pfizer or Moderna, or 14 days after your first dose of Janssen. This is how the CDC defines a vaccine breakthrough case:
“… a vaccine breakthrough infection is defined as the detection of SARS-CoV-2 RNA or antigen in a respiratory specimen collected from a person ≥14 days after they have completed all recommended doses of a U.S. Food and Drug Administration (FDA)-authorized COVID-19 vaccine.”
In other words, if you’ve received one dose of Pfizer or Moderna and develop symptomatic COVID-19, get admitted to the hospital and/or die from COVID, you’re counted as an unvaccinated case. If you’ve received two doses and get ill within 14 days, you’re still counted as an unvaccinated case.
The problem with this is that over 80% of hospitalizations and deaths appear to be occurring among those who have received the jabs, but this reality is hidden by the way cases are defined and counted. A really clever and common strategy of the CDC during the pandemic has been to change the definitions and goalposts so it supports their nefarious narrative.
For example, the CDC has quietly changed the definition of “vaccine,” apparently in an attempt to validate calling the COVID mRNA gene therapies vaccines. In an August 26, 2021, archived version7 of vaccine, the CDC defines it as a “product that stimulates a person’s immune system to produce immunity to a specific disease, protecting the person from that disease.”
But a few days later, a new definition appeared on the CDC’s website,8 which now says a vaccine is a “preparation that is used to stimulate the body’s immune response against diseases.” The differences in the definitions are subtle but distinct: The first one defined a vaccine as something that will “produce immunity.”
But, since the COVID-19 vaccines are not designed to stop infection but, rather, to only lessen the degree of infection, it becomes obvious that the new definition was created to cover the COVID vaccines.
Different Testing Guidelines for Vaxxed and Unvaxxed
It’s not just the CDC’s definition of a breakthrough case that skews the data. Even more egregious and illogical is the fact that the CDC even has two different sets of testing guidelines — one for vaccinated patients and another for the unvaccinated.
Since the beginning of the pandemic, the CDC has recommended a PCR test cycle threshold (CT) of 40.9 This flies in the face of scientific consensus, which has long been that a CT over 35 will produce 97% false positives,10 essentially rendering the test useless.11,12,13
In mid-May 2021, the CDC finally lowered its recommended CT count, but only for patients who have received one or more COVID shots.14 So, if you have received a COVID injection, the CDC’s guidelines call for your PCR test to be run at a CT of 28 or less. If you are unvaccinated, your PCR test is to be run at a CT of 40, which grossly overestimates the true prevalence of infection.
The end result is that unvaccinated individuals who get tested are FAR more prone to get false positives, while those who have received the jab are more likely to get an accurate diagnosis of infection.
Only Hospitalization and Death Count if You’re COVID Jabbed
Even that’s not all. The CDC also hides vaccine failures and props up the “pandemic of the unvaccinated” narrative by only counting breakthrough cases that result in hospitalization or death.
In other words, if you got your second COVID shot more than 14 days ago and you develop symptoms, you do not count as a breakthrough case unless you’re admitted to the hospital and/or die from COVID-19 in the hospital, even if you test positive. So, to summarize, COVID breakthrough cases count only if all of the following apply:
- The patient received the second dose of the Pfizer or Moderna shot at least 14 days ago (or one dose in case of Johnson & Johnson’s single-dose injection)
- The patient tests positive for SARS-CoV-2 using a CT of 28 or less, which avoids false positives
- The patient is admitted to the hospital for COVID-19 and/or dies in the hospital
Vaccinated Probably Make Up Bulk of Hospitalizations
If vaccinated and unvaccinated were not treated with such varying standards, we’d probably find that the vaccinated now make up the bulk of hospitalizations, making the COVID pandemic one of the vaccinated. An August 30, 2021, exposé by The Epoch Times reveals what’s really happening on the front lines:15
“After a battery of testing, my friend was diagnosed with pancreatitis. But it was easier for the hospital bureaucracy to register the admission as a COVID case … The mainstream media is reporting that severe COVID cases are mainly among unvaccinated people … Is that what’s really going on?
It’s certainly not the case in Israel, the first country to fully vaccinate a majority of its citizens against the virus. Now it has one of the highest daily infection rates and the majority of people catching the virus (77 percent to 83 percent, depending on age) are already vaccinated, according to data collected by the Israeli government …
After admission, I spoke to the nurse on the COVID ward … The nurse told me that she had gotten both vaccines but she was feeling worried: ‘Two thirds of my patients are fully vaccinated,’ she said. How can there be such a disconnect between what the COVID ward nurse told me and the mainstream media reports?”
The heart of the problem is that the U.S. is not even trying to achieve an accurate count. As noted by The Epoch Times, “the Centers for Disease Control and Prevention have publicly acknowledged that they do not have accurate data.”
So, when you hear that cases are rising, and that most of them are unvaccinated, you need to ask: “Are these people who have had one vaccine and gotten sick, two vaccines and gotten sick, or no vaccines at all? Without more details, it is impossible to know what is really going on,” The Epoch Times says.16
All we do know, according to one doctor who spoke with The Epoch Times, is “the vaccines are not as effective as public health officials told us they would be. ‘This is a product that’s not doing what it’s supposed to do. It’s supposed to stop transmission of this virus and it’s not doing that.’”
Counting Non-COVID Illness as COVID Cases
On top of all of that, hospitals are still also reporting non-COVID related illnesses as COVID. As reported by The Epoch Times :17
“Health authorities around the world have been doing this since the beginning of the COVID crisis. For example, a young man in Orange County, Florida who died in a motorcycle crash last summer was originally considered a COVID death by state health officials …
And a middle-aged construction worker fell off a ladder in Croatia and was also counted as a death from COVID … To muddy the waters further, even people who test negative for COVID are sometimes counted as COVID deaths.
Consider the case of 26-year-old Matthew Irvin, a father of three from Yamhill County, Oregon. As reported by KGW8 News, Irvin went to the ER with stomach pain, nausea, and diarrhea on July 5, 2020. But instead of admitting him to the hospital, the doctors sent him home.
Five days later, on July 10, 2020, Irvin died. Though his COVID test came back negative two days after his death and his family told reporters and public health officials that no one Irvin had been around had any COVID symptoms, the medical examiner allegedly told the family that an autopsy was not necessary, listing his death as a coronavirus case. It took the Oregon Health Authority two and a half months to correct the mistake.
In an even more striking example of overcounting COVID deaths, a nursing home in New Jersey that only has 90 beds was wrongly reported as having 753 deaths from COVID. According to a spokesman, they had fewer than twenty deaths. In other words, the number of deaths was over-reported by 3,700 percent.”
No Need to Fear the Delta Variant if You’re Unvaccinated
In a June 29, 2021, interview,18 Fauci called the Delta variant “a game-changer” for unvaccinated people, warning it will devastate the unvaccinated population while vaccinated individuals are protected against it. Alas, in the real world, the converse is turning out to be true, as the Delta variant is running wild primarily among those who got the COVID jab.
In a June 30, 2021, appearance on Fox News, epidemiologist and cardiologist Dr. Peter McCullough pointed out that “It is very clear from the U.K. Technical Briefing19 that was published June 18 that the vaccine provides no protection against the Delta variant.”20
The reason for this is because the Delta variant contains three different mutations, all in the spike protein. This allows this variant to evade the immune responses in those who have received the COVID jabs, but not those who have natural immunity, which is much broader.
Even so, the Delta variant is far milder than previous variants, according to the U.K.’s June 18, 2021, Technical Briefing.21 In it, they present data showing the Delta variant is more contagious but far less deadly and easier to treat. As McCullough told Fox News:
“Whether you get the vaccine or not, patients will get some very mild symptoms like a cold and they can be easily managed … Patients who have severe symptoms or at high risk, we can use simple drug combinations at home and get them through the illness. So, there’s no reason now to push vaccinations.”
Contrast that with the following statement made by President Biden during a CNN town hall meeting in Cincinnati, Ohio, in late July 2021:22
“We have a pandemic for those who haven’t gotten a vaccination. It’s that basic, that simple. If you’re vaccinated, you’re not going to be hospitalized, not going to the ICU unit, and not going to die. You’re not going to get COVID if you have these vaccinations.”
However, Dr. Leana Wen, an emergency doctor and visiting professor of health policy and management at George Washington University’s Milken School of Public Health in Washington, D.C., contradicted the president, saying he had led the American astray by telling them you don’t need a mask if you’re vaccinated, or that you can’t get it or transmit it. As reported by CNN Health:23
“In particular, Wen took issue with Biden’s incorrect claims that you cannot contract Covid-19 or the Delta variant if you are vaccinated. ‘I was actually disappointed,’ Wen said. ‘I actually thought he was answering questions as if it were a month ago. He’s not really meeting the realities of what’s happening on the ground. I think he may have led people astray.’”
CNN added that Wen had told their political commentator Anderson Cooper that “many unknown answers remain related to Covid-19, and that it is still not known how well protected vaccinated individuals are from mild illness … [or] if you’re vaccinated, could you still be contagious to other people.”
Vaccinated Patients Flood Hospitals Around the World
The U.K. data showing the Delta variant is far milder than previous SARS-CoV-2 viruses deflates the claim that avoiding severe illness is a sign that the shots are working. Since the Delta variant typically doesn’t cause severe illness in the first place, it doesn’t make sense to attribute milder illness to the shot.
But if Delta is the mildest coronavirus variant yet, why are so many “vaccinated” people ending up in the hospital? While we still do not have clear confirmation, this could be a sign that antibody dependent enhancement (ADE) is at work. Alternatively, it could be that vaccine injuries are being misreported as breakthrough cases.
Whatever the case may be, real-world data from areas with high COVID jab rates show a disturbing trend. For example, August 1, 2021, the director of Israel’s Public Health Services, Dr. Sharon Alroy-Preis, announced half of all COVID-19 infections were among the fully vaccinated.24 Signs of more serious disease among fully vaccinated are also emerging, she said, particularly in those over the age of 60.
A few days later, August 5, 2021, Dr. Kobi Haviv, director of the Herzog Hospital in Jerusalem, appeared on Channel 13 News, reporting that 95% of severely ill COVID-19 patients are fully vaccinated, and that they make up 85% to 90% of COVID-related hospitalizations overall.25
In Scotland, official data on hospitalizations and deaths show 87% of those who have died from COVID-19 in the third wave that began in early July were vaccinated.26
In Gibraltar, which has a 99% COVID jab compliance rate, COVID cases have risen by 2,500% since June 1, 2021,27 and in Iceland, where over 82% have received the shots, 77% of new COVID cases are among the fully vaccinated.28
Data from the U.K. show a similar trend among those over the age of 50. In this age group, partially and fully “vaccinated” people account for 68% of hospitalizations and 70% of COVID deaths.29
A CDC investigation of an outbreak in Barnstable County, Massachusetts, between July 6, 2021, through July 25, 2021, found 74% of those who received a diagnosis of COVID19, and 80% of hospitalizations, were among the fully vaccinated.30,31 Most, but not all, had the Delta variant.
The CDC also found that fully vaccinated individuals who contract the infection have as high a viral load in their nasal passages as unvaccinated individuals who get infected.32 The same was found in a British study, a preprint of which was posted mid-August 2021.33,34 This means the vaccinated are just as infectious as the unvaccinated.
Interestingly, a Lancet preprint study35 that examined breakthrough infections in health care workers in Vietnam who received the AstraZeneca COVID shot found the “viral loads of breakthrough Delta variant infection cases were 251 times higher than those of cases infected with old strains detected between March-April 2020.”
What’s more, they found no correlation between vaccine-induced neutralizing antibody levels and viral loads or the development of symptoms. According to the authors:
“Breakthrough Delta variant infections are associated with high viral loads, prolonged PCR positivity, and low levels of vaccine-induced neutralizing antibodies, explaining the transmission between the vaccinated people.”
Not All Vaccinated Are Confirmed Vaccinated
As if all of that weren’t enough, there’s yet one more confounder. Just because you got the COVID shot does not mean you’ve been confirmed as having gotten the shot. You’re only confirmed “vaccinated” if your COVID injection is added to your medical record, and this sometimes doesn’t happen if you’re going to a temporary vaccination clinic, a drive-through or pharmacy, for example. As reported by CNN:36
“If you are among the countless people who didn’t get the doses at a primary care doctor’s office, there may not be any record of the vaccination on file with your doctor.”
To actually count as a “confirmed vaccinated” individual, you must send your vaccination card to your primary care physician’s office and have them add it to your electronic medical record. If you got the shot at a pharmacy, you’ll need to verify that they forwarded your proof of vaccination to your doctor. Primary care offices are then responsible for sharing their patients’ immunization data with the state’s immunization information system.
Patient-recorded proof of vaccination is only accepted for influenza and pneumococcal vaccines, not COVID-19 injections.37 What this all means is that, say you got the shot several weeks ago at a drive-through vaccination clinic and get admitted to the hospital with COVID symptoms. Unless your COVID shot status has actually been added into the medical system, you will not count as “vaccinated.”
This too can skew the statistics, because we know the CDC ascertains vaccination status by matching SARS-CoV-2 case surveillance and CAIR2 data using person-level identifiers and algorithms.38
As noted by John Zurlo, division director of infectious disease at Thomas Jefferson University, “the lack of reliable vaccine records complicates efforts to precisely understand vaccine effectiveness and determine how many local hospitalizations and deaths are resulting from COVID-19 breakthrough infections.”39
We’re in the Largest Clinical Trial in Medical History
In closing, it’s worth remembering that the COVID injection campaign is part and parcel of a clinical trial. As noted Dr. Lidiya Angelova in a recent Genuine Prospect article:40
“Many people are unaware that they are participating in the largest clinical trial test of our times. It is because World Health Organization, healthcare authorities, politicians, celebrities, and journalists promote the experimental medical treatments (wrongly called COVID-19 vaccines) as safe and efficient while in fact these treatments are in early clinical research stage.
It means that there is not enough data for such claims and that the people who participate are test subject.”
As shown in a graph on Genuine Prospect, under normal circumstances, clinical research follows a strict protocol that begins with tests on cell cultures. After that comes tests on animals, then limited human testing in four phases. In Phase 1 of human testing, up to 100 people are included and followed anywhere from one week to several months.
Phase 2 typically includes several hundred participants and lasts up to two years. In Phase 3, several hundred to 3,000 participants are tested upon for one to four years. Phase 4 typically includes several thousand individuals who are followed for at least one year or longer. After each phase, the data is examined to assess effectiveness and adverse reactions.
The timelines for these stages and phases were not followed for the COVID “vaccines.” Most Phase 3 trials concluded by the end of 2020, and everyone who got the shots since their rollout under emergency use authorization is part of a Phase 4 clinical trial, whether they realize it or not.41 And since the trials are not completed, you simply cannot make definitive claims about safety, especially long-term safety. As noted by Angelova:42
“When I worked at the National Institute of Allergy and Infectious Diseases (NIAID) … I went to the course Ethical and Regulatory Aspects of Clinical Research … The first rule we learnt was ‘Clinical research must be ethical’ … All ethical aspects of clinical research are dismissed with the COVID-19 vaccines.
People should know that nobody can require such to participate in everyday activities like using public transportation, shopping, going to school and even hospital. People should know that they should not be punished for refusing to take the experimental medical treatments.
COVID-19 vaccines mass use and COVID-19 measures are an infringe[ment] of the Articles 2, 3, 5, 9, 11, 12, 13, 18, 20, 25, 27, 28 of The Universal Declaration of Human Rights (UDHR).”
Sources and References
- 1 The New York Times July 16, 2021
- 2 WH.gov Press Briefing July 16, 2021
- 3 Fox News
- 4 Mayo Clinic COVID Vaccine Tracker
- 5 Twitter DX Foundation September 2, 2021
- 6 CDC August 25, 2021
- 7 Web Archive August 26, 2021
- 8 CDC September 1, 2021
- 9 FDA.gov CDC 2019-nCoV Real-Time RT-PCR July 13, 2020 (PDF) Page 35
- 10 Clinical Infectious Diseases September 28, 2020; ciaa1491
- 11 The Vaccine Reaction September 29, 2020
- 12 Jon Rappoport’s Blog November 6, 2020
- 13 YouTube TWiV 641 July 16, 2020
- 14 CDC.gov COVID-19 Vaccine Breakthrough Case Investigation Guidelines (PDF)
- 15, 16, 17, 28 The Epoch Times August 30, 2021
- 18 PBS June 29, 2021
- 19, 21 Public Health England, SARS-CoV-2 Variants Technical Briefing 16, June 18, 2021 (PDF)
- 20 Covidcalltohumanity.org July 5, 2021
- 22 CBS 8 News July 21, 2021
- 23 CNN Health July 22, 2021
- 24 Bloomberg August 1, 2021 (Archived)
- 25 American Faith August 8, 2021
- 26 The Daily Expose July 29, 2021
- 27 Big League Politics August 4, 2021
- 29 Evening Standard August 20, 2021
- 30 CDC MMWR July 30, 2021; 70
- 31 CNBC July 30, 2021
- 32 NBC News August 7, 2021
- 33 Impact of Delta on Viral Burden and Vaccine Effectiveness in the UK (PDF)
- 34 CBS News August 19, 2021
- 35 The Lancet Preprint August 10, 2021
- 36 CNN April 26, 2021
- 37 Immunize.org Documenting Vaccination
- 38 MMWR August 27, 2021; 70(34): 1170-1176
- 39 Philadelphia Enquirer August 31, 2021
- 40, 42 Genuine Prospect August 31, 2021
- 41 Red Voice Media June 22, 2021
Viral Reality Check – What’s going on, but with real logic and science
Ivor Cummins | September 13, 2021
Quick update on the evolving irrationality of our viral issue – couple of links below that were mentioned:
Revealing talk on one major reason WHY science died in early 2020: https://odysee.com/@IvorCummins:f/Ernst-Wolff—Uncovering-the-Corona-Narrative—Aug-2021:8
Also our Covid Chronicles movie latest update here: https://www.kickstarter.com/projects/capecrusaders/the-covid-chronicles/posts/3279184
NOTE: My extensive research and interviewing / video/sound editing and much more does require support – please consider helping if you can with monthly donation to support me directly, or one-off payment: https://www.paypal.com/donate?hosted_button_id=69ZSTYXBMCN3W
24,526 Deaths 2,317,495 Injuries Following COVID Shots Reported in EU Database of Adverse Reactions

By Brian Shilhavy | Health Impact News | September 14, 2021
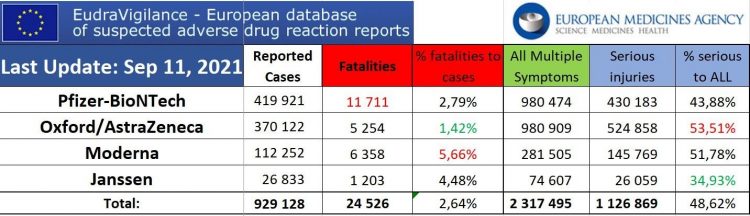
The European Union database of suspected drug reaction reports is EudraVigilance, and they are now reporting 24,526 fatalities, and 2,317,495 injuries, following COVID-19 injections.
A Health Impact News subscriber from Europe reminded us that this database maintained at EudraVigilance is only for countries in Europe who are part of the European Union (EU), which comprises 27 countries.
The total number of countries in Europe is much higher, almost twice as many, numbering around 50. (There are some differences of opinion as to which countries are technically part of Europe.)
So as high as these numbers are, they do NOT reflect all of Europe. The actual number in Europe who are reported dead or injured following COVID-19 shots would be much higher than what we are reporting here.
The EudraVigilance database reports that through September 11, 2021 there are 24,526 deaths and 2,317,495 injuries reported following injections of four experimental COVID-19 shots:
- COVID-19 MRNA VACCINE MODERNA (CX-024414)
- COVID-19 MRNA VACCINE PFIZER-BIONTECH
- COVID-19 VACCINE ASTRAZENECA (CHADOX1 NCOV-19)
- COVID-19 VACCINE JANSSEN (AD26.COV2.S)
From the total of injuries recorded, almost half of them (1,126,869) are serious injuries.
“Seriousness provides information on the suspected undesirable effect; it can be classified as ‘serious’ if it corresponds to a medical occurrence that results in death, is life-threatening, requires inpatient hospitalisation, results in another medically important condition, or prolongation of existing hospitalisation, results in persistent or significant disability or incapacity, or is a congenital anomaly/birth defect.”
A Health Impact News subscriber in Europe ran the reports for each of the four COVID-19 shots we are including here. It is a lot of work to tabulate each reaction with injuries and fatalities, since there is no place on the EudraVigilance system we have found that tabulates all the results.
Since we have started publishing this, others from Europe have also calculated the numbers and confirmed the totals.*
Here is the summary data through September 11, 2021.
Total reactions for the mRNA vaccine Tozinameran (code BNT162b2,Comirnaty) from BioNTech/ Pfizer – 11,711 deaths and 980,474 injuries to 11/09/2021
- 26,634 Blood and lymphatic system disorders incl. 156 deaths
- 26,940 Cardiac disorders incl. 1,745 deaths
- 253 Congenital, familial and genetic disorders incl. 21 deaths
- 13,005 Ear and labyrinth disorders incl. 9 deaths
- 728 Endocrine disorders incl. 5 deaths
- 15,314 Eye disorders incl. 28 deaths
- 87,239 Gastrointestinal disorders incl. 489 deaths
- 256,117 General disorders and administration site conditions incl. 3,330 deaths
- 1,098 Hepatobiliary disorders incl. 55 deaths
- 10,351 Immune system disorders incl. 64 deaths
- 32,834 Infections and infestations incl. 1,141 deaths
- 12,714 Injury, poisoning and procedural complications incl. 179 deaths
- 24,765 Investigations incl. 368 deaths
- 7,178 Metabolism and nutrition disorders incl. 210 deaths
- 130,077 Musculoskeletal and connective tissue disorders incl. 149 deaths
- 757 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 67 deaths
- 173,079 Nervous system disorders incl. 1,278 deaths
- 1,211 Pregnancy, puerperium and perinatal conditions incl. 36 deaths
- 168 Product issues incl. 1 death
- 17,756 Psychiatric disorders incl. 156 deaths
- 3,348 Renal and urinary disorders incl. 198 deaths
- 19,084 Reproductive system and breast disorders incl. 3 deaths
- 43,232 Respiratory, thoracic and mediastinal disorders incl. 1,376 deaths
- 47,012 Skin and subcutaneous tissue disorders incl. 105 deaths
- 1,805 Social circumstances incl. 14 deaths
- 887 Surgical and medical procedures incl. 31 deaths
- 26,888 Vascular disorders incl. 497 deaths
Total reactions for the mRNA vaccine mRNA-1273 (CX-024414) from Moderna – 6,358 deaths and 281,505 injuries to 11/09/2021
- 5,465 Blood and lymphatic system disorders incl. 59 deaths
- 8,364 Cardiac disorders incl. 687 deaths
- 113 Congenital, familial and genetic disorders incl. 2 deaths
- 3,466 Ear and labyrinth disorders incl. 1 death
- 221 Endocrine disorders incl. 2 deaths
- 4,302 Eye disorders incl. 18 deaths
- 24,595 Gastrointestinal disorders incl. 237 deaths
- 75,804 General disorders and administration site conditions incl. 2,461 deaths
- 458 Hepatobiliary disorders incl. 24 deaths
- 2,485 Immune system disorders incl. 11 deaths
- 8,436 Infections and infestations incl. 416 deaths
- 6,013 Injury, poisoning and procedural complications incl. 121 deaths
- 5,460 Investigations incl. 120 deaths
- 2,693 Metabolism and nutrition disorders incl. 145 deaths
- 35,728 Musculoskeletal and connective tissue disorders incl. 129 deaths
- 333 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 37 deaths
- 49,722 Nervous system disorders incl. 650 deaths
- 538 Pregnancy, puerperium and perinatal conditions incl. 6 deaths
- 59 Product issues incl. 1 death
- 5,316 Psychiatric disorders incl. 110 deaths
- 1,632 Renal and urinary disorders incl. 107 deaths
- 3,558 Reproductive system and breast disorders incl. 3 deaths
- 12,150 Respiratory, thoracic and mediastinal disorders incl. 614 deaths
- 15,102 Skin and subcutaneous tissue disorders incl. 57 deaths
- 1,188 Social circumstances incl. 25 deaths
- 905 Surgical and medical procedures incl. 69 deaths
- 7,399 Vascular disorders incl. 246 deaths
Total reactions for the vaccine AZD1222/VAXZEVRIA (CHADOX1 NCOV-19) from Oxford/ AstraZeneca: 5,254 deaths and 980,909 injuries to 11/09/2021
- 11,826 Blood and lymphatic system disorders incl. 221 deaths
- 16,641 Cardiac disorders incl. 603 deaths
- 158 Congenital familial and genetic disorders incl. 5 deaths
- 11,541 Ear and labyrinth disorders incl. 1 death
- 504 Endocrine disorders incl. 4 deaths
- 17,332 Eye disorders incl. 22 deaths
- 96,191 Gastrointestinal disorders incl. 270 deaths
- 257,766 General disorders and administration site conditions incl. 1,278 deaths
- 831 Hepatobiliary disorders incl. 51 deaths
- 3,987 Immune system disorders incl. 23 deaths
- 24,674 Infections and infestations incl. 330 deaths
- 11,183 Injury poisoning and procedural complications incl. 141 deaths
- 21,578 Investigations incl. 121 deaths
- 11,626 Metabolism and nutrition disorders incl. 73 deaths
- 148,195 Musculoskeletal and connective tissue disorders incl. 74 deaths
- 510 Neoplasms benign malignant and unspecified (incl cysts and polyps) incl. 16 deaths
- 204,423 Nervous system disorders incl. 840 deaths
- 439 Pregnancy puerperium and perinatal conditions incl. 11 deaths
- 158 Product issues incl. 1 death
- 18,501 Psychiatric disorders incl. 47 deaths
- 3,639 Renal and urinary disorders incl. 48 deaths
- 12,993 Reproductive system and breast disorders incl. 2 deaths
- 34,557 Respiratory thoracic and mediastinal disorders incl. 629 deaths
- 45,140 Skin and subcutaneous tissue disorders incl. 36 deaths
- 1,291 Social circumstances incl. 6 deaths
- 1,142 Surgical and medical procedures incl. 22 deaths
- 24,083 Vascular disorders incl. 379 deaths
Total reactions for the COVID-19 vaccine JANSSEN (AD26.COV2.S) from Johnson & Johnson: 1,203 deaths and 74,607 injuries to 11/09/2021
- 690 Blood and lymphatic system disorders incl. 31 deaths
- 1,201 Cardiac disorders incl. 120 deaths
- 25 Congenital, familial and genetic disorders
- 560 Ear and labyrinth disorders incl. 1 death
- 42 Endocrine disorders incl. 1 death
- 1,006 Eye disorders incl. 5 deaths
- 6,822 Gastrointestinal disorders incl. 56 deaths
- 19,539 General disorders and administration site conditions incl. 303 deaths
- 96 Hepatobiliary disorders incl. 9 deaths
- 302 Immune system disorders incl. 7 deaths
- 1,679 Infections and infestations incl. 66 deaths
- 694 Injury, poisoning and procedural complications incl. 16 deaths
- 3,861 Investigations incl. 72 deaths
- 431 Metabolism and nutrition disorders incl. 26 deaths
- 11,861 Musculoskeletal and connective tissue disorders incl. 30 deaths
- 31 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 2 deaths
- 15,493 Nervous system disorders incl. 142 deaths
- 26 Pregnancy, puerperium and perinatal conditions incl. 1 death
- 20 Product issues
- 988 Psychiatric disorders incl. 11 deaths
- 280 Renal and urinary disorders incl. 11 deaths
- 863 Reproductive system and breast disorders incl. 4 deaths
- 2,629 Respiratory, thoracic and mediastinal disorders incl. 136 deaths
- 2,296 Skin and subcutaneous tissue disorders incl. 5 deaths
- 212 Social circumstances incl. 4 deaths
- 546 Surgical and medical procedures incl. 38 deaths
- 2,414 Vascular disorders incl. 106 deaths
Featured Video

Get ready for the big Israeli false flag cyber-attack
or go to
Aletho News Archives – Video-Images
From the Archives
Some Call It Conspiracy Theory – Part 1
BY IAIN DAVIS | SEPTEMBER 25, 2023
There are certain assumptions that are applied to anyone labelled a “conspiracy theorist”—and all of them are fallacies. Indeed, the term “conspiracy theory” is nothing more than a propaganda construct designed to silence debate and censor opinion on a range of subjects. Most particularly, it is used as a pejorative to marginalise and discredit whoever challenge the pronouncements and edicts of the State and of the Establishment—that is, the public and private entities that control the State and that profit from the State.
Those of us who have legitimate criticisms of government and its institutions and representatives, who are therefore labelled “conspiracy theorists,” face a dilemma. We can embrace the term and attempt to redefine it or we can reject it outright. Either way, it is evident that the people who weaponise the “conspiracy theory” label will continue to use it as long as it serves their propaganda purposes.
One of the most insidious aspects of the “conspiracy theory” fabrication is that the falsehoods associated with the term have been successfully seeded into the public’s consciousness. Often, propagandists need do no more than slap this label on the targeted opinion and the audience will immediately dismiss that viewpoint as a “lunatic conspiracy theory.” Sadly, this knee-jerk reaction is usually made absent any consideration or even familiarity with the evidence presented by that so-called “lunatic conspiracy theorist.”
This was the reason why “conspiracy theorist” label was created. The State and its propagandists do not want the public to even be aware of inconvenient evidence, let alone to examine it. The challenging evidence is buried under the “wild conspiracy theory” label, thereby signalling to the unsuspecting public that they should automatically reject all of the offered facts and evidence.
There are a number of components that collectively form the conspiracy theory canard. Let’s break them down. … continue
Blog Roll
 Aletho News
- ‘Stop Putting Drugs in Our Food’: Scientists Link Folic Acid in Food to Rising Rates of Colorectal Cancer
- The 14 Things That Happen to Your Newborn in the First 48 Hours
- JFK’s Forgotten Confrontation with Israel
- Trump’s Cyber Director Pick Has Deep Ties To Israeli Intelligence
- Get ready for the big Israeli false flag cyber-attack
- The Ukrainian Reset experiment: A war and surveillance state blueprint for the EU
- Pentagon fails ninth financial audit in a row, unable to account for trillions in assets
- Russia rejects Danish plot claims, vows response to expulsion
- Study of 14,000 Children Links Vaccination to Higher Rates of Chronic Illness
- Strike Iran Again, Open Pandora’s Box | Brian McGlinchey
- If Americans Knew
- Reporting Raises Fresh Questions About Israeli Role in CNN’s ‘Preposterous’ Iranian Dirty Bomb Story
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- Under the West’s watch, genocide apologism has become entirely respectable
- Israeli Diplomat Offered Iowa Attorney General Free Trip, Then Asked for Favors
- On World Children’s Day, 350 Palestinian Children Remain in Israeli Prisons
- Why Is Israel Jailing a Palestinian Student Without Trial? Because It Can
- ICJ ruling on Rohingya genocide could strengthen South Africa’s case against Israel
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- Newly nominated House Speaker funded Gaza genocide
- Leaked: How Silicon Valley Elites Bankrolled an Anti-Migrant, Pro-Israel Propaganda Machine
- No Tricks Zone
- New Study: Modern Temps Are Among The Coldest Of The Last 10,000 Years In East Central Europe
- Germany’s Renewable Energies Lead to 1.4 Billion Euro Electric Power Trade Deficit
- Argentina’s Perito Moreno Glacier Joins Antarctica and Arctic In Defying Doomsday Melt Claims
- New Study: Barents Sea Temperatures Were Warmer And Sea Ice Less Extensive In The 1700s Than Today
- German Authorities Start Initiative To Evaluate Public Register For Climate “Disinformation” Spreaders!
- Zonal Asymmetry of Temperature Change in the Antarctic Circumpolar Current
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean

