Media outlets try to deflect from lab leak theory and censorship
By Didi Rankovic | Reclaim the Net | May 29, 2021
Mainstream media, now embarrassingly forced to follow President Biden’s policy and abruptly reverse course on the Wuhan lab leak theory – after branding and ridiculing it as a conspiracy theory for months – are working to downplay the importance of censorship around the topic that was enforced until just a few days ago.
One would think it would be hard to find a single person who has been through more than a year of lockdowns and myriads of restrictions who would not be interested to learn what the virus is and where it came from – but apparently, such people exist, in media outlets like The Verge.
An article that could easily be described as a distraction in its own right from the topic of why the lab leak theory was suppressed and censored so vigorously, now claims that the origin of coronavirus doesn’t really matter and suggests that it should be swept under the rug as a distraction from truly important topics.
While briefly paying lip service to the importance of discovering the origin of the virus, the article’s real goal is to convince its readers to change the topic. Forced to eat their own words, this class of media are no longer calling the Wuhan theory a fringe conspiracy, but “an extraordinary claim” that is “technically possible.”
But discussing the topic is discouraged as no less than “a distraction from the rest of the urgent work governments and health agencies around the world need to do in order to end this pandemic and prepare for the next one” – while at the same time calling for vaccination efforts to be doubled.
And as scientists who have tried to study the origin of coronavirus, including the possibility that it was artificially created, are finally getting a chance to speak after being censored and ostracized for a long time – mainstream media are scrambling to adjust to the new reality around the topic.
The New York Times has already done its U-turn, reporting on Friday that US intelligence agencies have a large amount of evidence concerning the Wuhan lab – but one of its reporters, Apoorva Mandavilli, didn’t get the memo immediately.
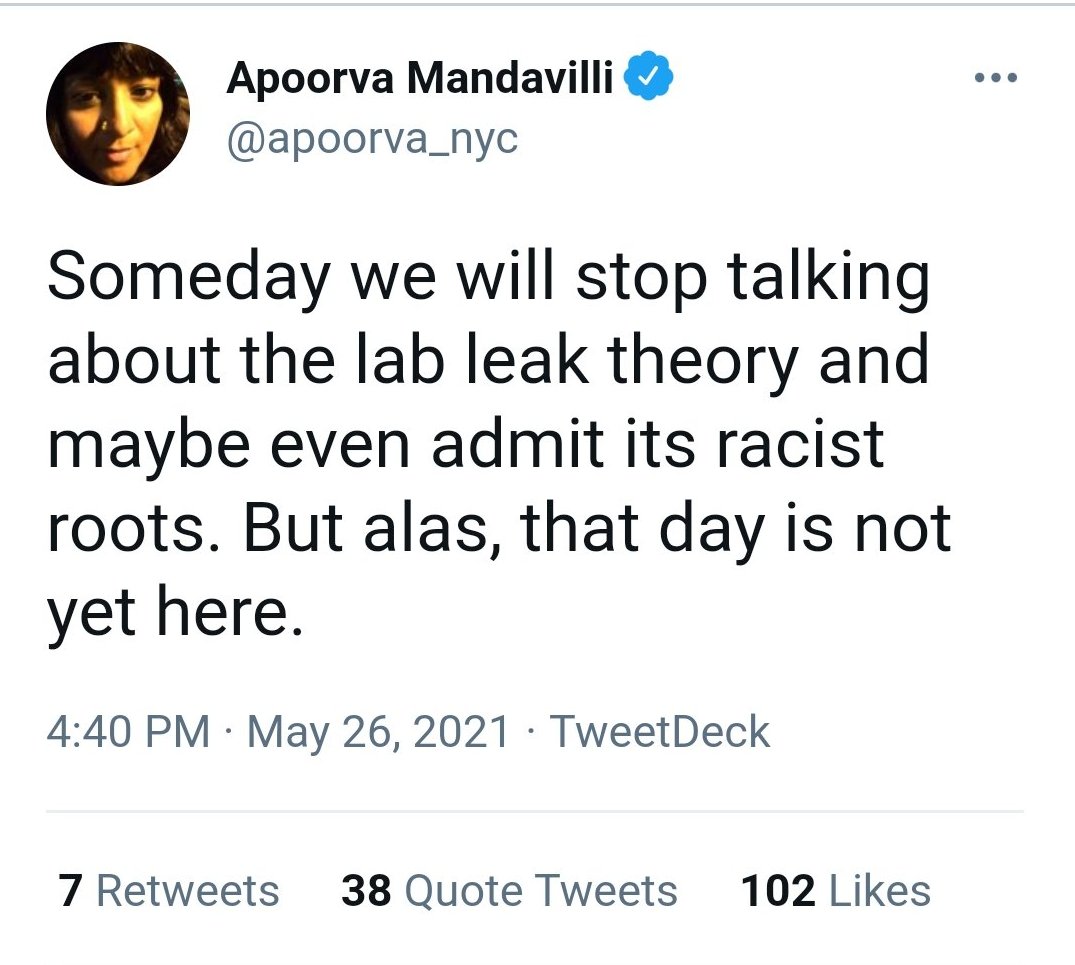
On the same day President Biden announced an investigation, Mandavilli tweeted, “Someday we will stop talking about the lab leak theory and maybe even admit its racist roots. But alas, that day is not yet here” – only to quickly delete the post after receiving backlash for making the claim that it was “racist” to consider the possibility that the virus was engineered by humans.
New Paper: Masks Achieve Nothing In Terms Of Spread
By Damian D. Guerra and Daniel J. Guerra | medrxiv.org | May 29, 2021
Latest analysis shows yet again – yet again – what we already knew from 40 years of published research. And also empirically from simply glancing over the past year’s real-world data. Masks don’t work!
Our main finding is that mask mandates and use are not associated with lower SARS-CoV-2 spread among US states. 80% of US states mandated masks during the COVID-19 pandemic.
Mandates induced greater mask compliance but did not predict lower growth rates when community spread was low (minima) or high (maxima). We infer that mandates likely did not affect COVID-19 case growth [15], as growth rates were similar on all days between actual or modeled issuance dates and 6 March 2021. Higher mask use (rather than mandates per se) has been argued to decrease COVID-19 growth rates [11].
While compliance varies by location and time, IHME estimates are robust (derived from multiple sources [17]) and densely sampled (day-level precision). Higher mask use did not predict lower maximum growth rates, smaller surges, or less Fall-Winter growth among continental states.
Mask-growth rate correlation was only evident at minima. This may be an artifact of faster growth at fewer normalized cases, as well as regional differences in case prevalence early in the pandemic. States in the high mask quintile grew at similar rates as states in the low mask quintile after maxima (when interstate total case differences were smaller than before minima).
In addition, mask use did not predict normalized cases at minima, and low mask growth curves trailed those of high mask (particularly Northeast) states before minima. Growth maxima and Fall-Winter surges did not differ between Northeast and other states. Northeast states exhibited the highest seroprevalence up to at least July 2020 [24] and constituted 80% of the top quintile of mask use, which may explain their comparatively lower Summer growth.
Overall, mask use appears to be an intra-state lagging indicator of case growth. There is inferential but not demonstrable evidence that masks reduce SARS-CoV-2 transmission. Animal models [25], small case studies [6], and growth curves for mandate-only states [16] suggest that mask efficacy increases with mask use [11]. However, we did not observe lower growth rates over a range of compliance at maximum Fall-Winter growth (45-83% between South Dakota and Massachusetts during maxima) [17] when growth rates were high.
This complements a Danish RCT from 3 April to 2 June 2020, when growth rates were low, which found no association between mask use and lower COVID-19 rates either for all participants in the masked arm (47% strong compliance) or for strongly compliant participants only [8].
Masks have generally not protected against other respiratory viruses. Higher self-reported mask use protected against SARS-CoV-1 in Beijing residents [26], but RCTs found no differences in PCR confirmed influenza among Hong Kong households assigned to hand hygiene with or without masks (mask use 31% and 49%, respectively) [27].
Medical and cloth masks did not reduce viral respiratory infections among clinicians in Vietnam [9] or China [10], and rhinovirus transmission increased among universally masked Hong Kong students and teachers in 2020 compared with prior years [28].
These findings are consistent with a 2020 CDC meta-analysis [29] and a 2020 Cochrane review update [30].
Our study has implications for respiratory virus mitigation. Public health measures should ethically promote behaviors that prevent communicable diseases. The sudden onset of COVID-19 compelled adoption of mask mandates before efficacy could be evaluated.
Our findings do not support the hypothesis that SARS-CoV-2 transmission rates decrease with greater public mask use.
As masks are required in public in many US states, it is prudent to weigh potential benefits with harms. Masks may promote social cohesion as rallying symbols during a pandemic [31], but risk compensation can also occur [32]. Prolonged mask use (>4 hours per day) promotes facial alkalinization and inadvertently encourages dehydration, which in turn can enhance barrier breakdown and bacterial infection risk [33].
British clinicians have reported masks to increase headaches and sweating and decrease cognitive precision [34]. Survey bias notwithstanding, these sequelae are associated with medical errors [35]. By obscuring nonverbal communication, masks interfere with social learning in children [36]. Likewise, masks can distort verbal speech and remove visual cues to the detriment of individuals with hearing loss; clear face-shields improve visual integration, but there is a corresponding loss of sound quality [37, 38].
Future research is necessary to better understand the risks of long-term daily mask use [30]. Conversely, it is appropriate to emphasize interventions with demonstrated or probable efficacy against COVID-19 such as vaccination [39] and Vitamin D repletion [40]. In summary, mask mandates and use were poor predictors of COVID-19 spread in US states. Case growth was independent of mandates at low and high rates of community spread, and mask use did not predict case growth during the Summer or Fall-Winter waves.
Strengths of our study include using two mask metrics to evaluate association with COVID-19 growth rates; measuring normalized case growth in mandate and non-mandate states at comparable times to quantify the likely effect of mandates; and deconvolving the effect of mask use by examining case growth in states with variable mask use. Our study also has key limitations. We did not assess counties or localities, which may trend independently of state averages.
While dense sampling promotes convergence, IHME masking estimates are subject to survey bias. We only assessed one biological quantity (confirmed and probable COVID-19 infections), but the ongoing pandemic warrants assessment of other factors such as hospitalizations and mortality. Future work is necessary to elucidate better predictors of COVID-19 spread. A recent study found that at typical respiratory fluence rates, medical masks decrease airway deposition of 10-20μm SARS-CoV-2 particles but not 1-5μm SARS-CoV-2 aerosols [41].
Aerosol expulsion increases with COVID-19 disease severity in non-human primates, as well as with age and BMI in humans without COVID-19 [42]. Aerosol treatment by enhanced ventilation and air purification could help reduce the size of COVID-19 outbreaks.
Widespread distribution of ivermectin proves effective in Mexico against COVID-19
By Juan Quintero | TrialSiteNews | May 28, 2021
One country that has had remarkable success in the war against the COVID pandemic, but has received little to no global media coverage, is Mexico. Like the rest of the world, COVID cases in Mexico exploded in April 2020, the first hot spots flaring up along the northern border with the United States, in Mexico City and Quintana Roo, a popular tourist destination in the Caribbean. At the beginning of the pandemic, Mexico took recommendations and followed protocol set forth by the World Health Organization (WHO) and watched the virus spread from state to state, engulfing the entire country.

First COVID Outbreak in Mexico
On June 10, the Spanish-speaking media began reporting on the success that Peru was having in controlling the virus using ivermectin as a treatment. Mexico was in the middle of its worst peak of cases and deaths with records breaking daily, and interest in the drug – as well as sales – rose dramatically.
On June 20, the pan-American WHO (OPS/OMS) issued a statement strongly opposing the use of ivermectin. Additionally, other media sources started publishing anti-ivermectin articles all over Mexico. And as the number of deaths slowly decreased, interest in ivermectin subsequently died down.

In October 2020, cases in Mexico began spiking again; the outbreak this time started in Chihuahua, the state on the border of Texas. Texas was also experiencing an outbreak at this time, so it’s likely that the cases in Mexico were sparked in the US. From Chihuahua, cases spread south and into Mexico City igniting the worst outbreak yet. Mexico City was an inferno of COVID cases and death, and health workers rushed to the capital city from all over the country to help.

Determined to stop the spread at any cost, Mexico City officials held a meeting at the end of December, 2020, and invited the Instituto Mexicano del Seguro Social (IMSS) among other groups of doctors. Together, they decided to begin distribution of ivermectin kits in Mexico City and Mexico State to anyone who tested positive for COVID and wanted to take the drug, and to closely monitor hospitalizations to keep tabs on ivermectin’s efficacy. The kits distributed included ivermectin, aspirin and paracetamol. Between the end of November 2020 and the end of January 2021, more than 200,000 people tested positive for COVID, and of these, nearly 80,000 used the ivermectin kits. Results showed up to 76% reduction in hospitalization in the group that was taking ivermectin.


https://osf.io/preprints/socarxiv/r93g4/
On January 22, 2021, the mayor of Mexico City, Claudia Scheinbaum, held a live televised press conference where she talked about the positive results from the ivermectin distribution from December. Following the press release, the kits were made available for everyone in the whole of Mexico, and nation-wide results of ivermectin use were monitored. Amazingly, after mass distribution of ivermectin, every single COVID indicator in Mexico improved. Over the course of 18 weeks, COVID cases, hospitalizations, and deaths continuously dropped, and on May 14, the mayor held another televised press conference sharing the positive results of the months’-long campaign.
What is astonishing, however, is that the media outlets in Mexico have not reported on this astounding result. They continued to report on the number of excess deaths from before the ivermectin intervention – and not one has covered the current situation of declining cases and deaths due to wide-spread ivermectin intervention.


Don’t Be Stupid – Inform Your Decisions
By Gillian Dymond | OffGuardian | May 28, 2021
Are you tired of having to watch everything you say, in case you’re accused of “hate speech”? Do you frequently have to bite back innocently-spoken words, when someone claims to be “offended” by them? Have you become used to avoiding lively debate or expressing frank opinions on social media, for fear of finding police officers on your doorstep?
If so, you’ll be glad to know that at last there is a whole class of people you may attack with impunity; people who may be derided, slandered and ostracised to your heart’s content; people so selfish and stupid that you are fully entitled to incite hatred against them with the full blessing of your government.
These are the Great Unclean: the “anti-vaxxers” who are not just nasty spoilsports, standing between you and the ever-deferred reopening of society, but who continue to waft death and disease through a world which can only be made safe by universal, and repeated, “jabbing”.
The opportunity to indulge in virtuous hate speech has been seized with zest by household names and obscure Twitterati alike.
“Love the idea of covid vaccine passports for everywhere,” enthuses Piers Morgan, “restaurants, clubs, football, gyms, shops etc. It’s time covid-denying, anti-vaxxer loonies had their bullshit bluff called and bar themselves from going anywhere that responsible citizens go.”
Edwina Currie has emerged from political oblivion to agree:
I hear what you say about someone exercising their freedom not to have a vaccination and they’re perfectly healthy. I don’t want them sitting next to me in the theatre. I don’t want them standing next to me at the theatre bar. I don’t want them next to me or anywhere near me or even in the same carriage on the train. So they can exercise their freedom by staying at home.”
As for the chorus of the immunologically saved on social media, here’s a sample meme:
If you’re antivax and you see me making fun of antivax people, I just want to say I’m talking about you personally and I hope you’re offended because you’re fucking stupid.”
Just try substituting one of a whole range of tenderly protected diversities for “antivax people” or “anti-vaxxers”, and watch the frisson of outrage creeping down any bien-pensant spine. But as the State extends its tolerance, even its encouragement, to our abusers, we covid sceptics, it seems, are fair game.
For there is no quarter from the government for those who are standing aloof from the stampede to get “shots into arms”, as believers in the WHO’s revised definition of herd immunity so crudely like to put it.
This is, after all, a government which, spurred on by behavioural psychologists and with malice aforethought, has industriously stirred up and exploited social disapproval as a potent means of shaming dissent and achieving maximum compliance.
Be kind, they urge you, and deprive yourself and your children of oxygen for your neighbour’s sake. Be responsible, and roll up your sleeve to receive the magic injection that will not only make you immortal but demonstrate your selfless concern for others. Don’t be stupid! Remember, having no symptoms doesn’t mean you’re not a silent super-spreader.
But do sceptics really deserve the contempt being dished out to them so freely?
Are they really so stupid?
Would any self-respecting “anti-vaxxer”, for instance, have been silly enough to come out with the nonsense spouted by the UK’s secretary of state for health, when he told us that:
If you think about it, the vaccine is a tiny bit of the virus in order to get your body to be able to respond.”
Really, Mr Hancock? Are you sure that’s what’s actually on offer here?
Perhaps Mike Yeadon, former head of respiratory research at Pfizer, can set you straight. As he pointed out to James Delingpole recently, “a tiny bit of the virus” is not what goes into these novel treatments – perhaps because, when it comes down to brass tacks, “no-one’s got any”.
What is actually being pumped into millions of arms throughout the world with such careless abandon is not, he says, “just a vaccine”. Although these gene-based medications do “ultimately raise an immune response … the way they do it is completely different from any vaccine we’ve used before … they induce the body, the cells of your body, to actually manufacture a piece of this pathogen, this infective agent. And you respond to that.”
“Anti-vaxxers” could have told you that, Mr Hancock, because they’ve done their own research, and they understand the difference between the traditional idea of a vaccine and what is currently being held up as the golden ticket to freedom. So please stop feeding us blatant untruths about what is actually being injected into all those trusting arms and making its insidious way around millions of bloodstream.
Let’s have the facts that would enable everyone to make a truly informed decision. It really doesn’t help when you fuel sectarian hatred by standing up in parliament and declaring that:
those who promulgate lies about the dangers of vaccines that are safe and have been approved … are threatening lives …”
The obvious response to that is, “those who promulgate lies about the safety of novel and incompletely tested gene therapies doled out on emergency approval only are threatening lives.”
The life of Peter Meadows, for instance: a superlatively healthy seventy-six-year-old, who, trusting government and NHS assurances that the “vaccines” were “safe and effective”, suffered an unprecedented heart attack within hours of receiving the Pfizer jab, and died a few days later: just one of over a thousand post-vaccine fatalities officially logged in the UK’s Yellow Card system to date – or perhaps, as the evidence is increasingly suggesting, of thousands of vaccine-related deaths which, unlike those ascribed to Covid, are not in line with natural mortality profiles.
It seems that those castigated for being “anti-vaxxers” are, in fact, far from stupid. On the contrary, they are the ones sensible enough to take the time and trouble to research and weigh up risks versus benefits before exposing their bodies to any of the novel gene therapies currently being hawked around as “vaccines”.
It is those who don’t search out the facts for themselves who are not using their intelligence, and who are thereby laying themselves open to the smooth sales talk of drug pushers in high places. Peter Meadows and his wife were apparently not handed even the minimal information supplied by the NHS regarding possible side effects they might suffer until after they had received their shots.
They had no idea that the “vaccines” so confidently touted by Matt Hancock were not fully tested for immediate, let alone medium- or long-term, safety, and were issued under the “black triangle” system – ie, were still “subject to intensive safety monitoring”, with the proviso that a record should be kept of all adverse reactions experienced by those acting effectively as human guinea pigs on behalf of the pharmaceutical companies.
What is more, a “high volume” of such adverse reactions were anticipated by the apparently unconcerned UK government before the roll-out began.
Although the Royal Pharmaceutical Society is quick to state that the black triangle label “does not indicate that the product is unsafe for use in patients”, the common-sense response to such a claim, after careful examination of the Yellow Card data, must surely be, “Oh yeah? And now pull the other one!”
In fact, a Pubmed paper advising the US as to whether or not the black triangle system does indeed promote “more judicious prescribing” of new medications, concludes that, “Accelerated drug approvals could cause more uncertainty about drug effectiveness and safety, but specific labeling of newly approved medicines is unlikely to promote more judicious prescribing.”
How much more accelerated could approval be, than the emergency approval accorded to the new coronavirus “vaccines”? And how much less judicious their prescribing, encompassing, as it does, the wholesale jabbing of populations throughout the world, including young people and children, who are at little to no risk of succumbing to the disease, let alone dying of it? It is depressing to learn that Peter Meadows’ daughters had understood enough about the uncertain nature of the hastily concocted “vaccines” to urge their parents not to have the jabs.
Unfortunately, like so many others, the couple were swayed by a longing to return to their old normal, and by peer pressure whipped up by the likes of Matt Hancock and SAGE, rather than by the reasonable concerns raised by their daughters after careful scrutiny of the facts.
So, once more: just how stupid are anti-vaxxers? Interestingly, a recent paper by a team at the Massachusetts Institute of Technology, Viral Visualizations: How Coronavirus Skeptics Use Orthodox Data Practices to Promote Unorthodox Science Online found that, contrary to their popular denigration as “covidiots”, and to the embarrassment of the researchers themselves, covid sceptics “practice a form of data literacy in spades”.
Many of them “express mistrust for academic and journalistic accounts of the pandemic, proposing to rectify alleged bias by ‘following the data’ and creating their own data visualisations.” What they value is “unmediated access to information” and they “privilege personal research and direct reading over ‘expert’ interpretations.” And “Most fundamentally,” say the MIT team, “the groups we studied believe that science is a process, and not an institution.”
Exactly.
In which case, their dismissal of the WHO’s presumption, in claiming to be custodians of “The Science”, is hardly surprising. Nonsense, say the sceptics. Science can never be above questioning. It is not a bundle of rubber-stamped, government-approved dogmas, handy for facilitating some political or commercial agenda.
Like all forms of human knowledge, science remains eternally incomplete, the evolving construction of many minds researching truth in a continuing process of discovery: forming hypotheses, and attempting by all means possible to disprove those hypotheses; seeking to explain or resolve anomalies, but never holding any theory sacrosanct which further investigation might yet prove false; adapting to the gradual unfolding of new perspectives, as fresh evidence shakes the foundations of old paradigms.
It is the alleged “covidiots” and “anti-vaxxers” who, while they may not be scientists themselves, understand the principles on which the scientific method is based. As the MIT study admits, to complain that these irritating people “need more scientific literacy is to characterize their approach as uninformed and inexplicably extreme. This study shows the opposite: they are deeply invested in forms of critique and knowledge production they recognise as scientific expertise.”
All the same, the authors of the study seem to find the concessions they are compelled to make disturbing. “(H)ow do these groups diverge from scientific orthodoxy,” they wonder, “if they are using the same data?” Since all right-minded facts should show decent respect for the statutory consensus, surely anyone inducing them to defect in support of alternative, unsanctioned conclusions must be employing underhand methods?
“We have identified a few sleights of hand that contribute to the broader epistemological crisis we identify between these groups and the majority of scientific researchers,” the defenders of the true faith plead: and they shake their heads at the way “these groups skillfully manipulate data to undermine mainstream science,” quoting as examples the sceptics’ “outsize emphasis on deaths versus cases” and their suspicion of the officially promoted confusion of deaths “with” and “of” covid: both very good reasons, less partial analysts might say, for questioning the figures being spewed out ceaselessly by the government-funded mainstream media, and taken by a terrorised public to be gospel truth.
Yet it’s not just annoying amateurs, with their absurd claims that actual facts should trump any institutionally-coerced consensus, who question the official “narrative” – and, indeed the very existence of a pandemic, as traditionally understood before the WHO decided to “re-imagine” the term, on 4th May 2009, in anticipation of the projected swine-flu apocalypse (in the event, a damp squib, but a useful practice-run for the present resounding success).
After accumulating hard evidence in interviews with over a hundred eminent scientists and other experts, the Corona Investigation Committee, a team headed by Dr Reiner Fuellmich, are likewise challenging the means – essentially, a fraudulent PCR test capable of manufacturing cases on demand and fuelling the myth of the “asymptomatic superspreader” – by which the global coup and its predestined outcome, the push to “get jabs into arms”, have been so artfully engineered.
Dr Fuellmich – a lawyer qualified to practise in both the States and Europe – has already taken on such giants as Deutschebank and Volkswagen. We can only hope that the evidence which he and the rest of the Committee have gathered so painstakingly over the past year and shared with lawyers all over the world will continue to result in court cases where facts will triumph over consensus, vindicating the unvaccinated of “stupidity” before they are forced by the uninformed to wear yellow stars and find themselves rounded up in camps for the unclean.
And that those behind the coup, along with all who enabled and enforced their unlawful actions by “just following orders”, are brought to justice before an international tribunal, to be charged with what the Corona Committee describes as “the greatest crime against humanity ever committed.”
Switch to Remote Learning Caused Large Increases in School Dropout and Learning Losses in Brazil
By Noah Carl • Lockdown Sceptics • May 28, 2021
Back in April, I wrote about a study published in Proceedings of the National Academy of Sciences, which found that Dutch students made “made little or no progress while learning from home”. Now researchers have reported a similar finding in Brazil.
As in the Dutch study, the researchers used rigorous methods to gauge the impact of remote learning on student outcomes. In other words, they didn’t just compare outcomes in 2020 to those the year before.
In São Paulo State (where the study was based) state schools switched to remote learning only at the end of the first quarter, and they continued to teach remotely thereafter. This allowed the researchers to compare the change in outcomes between the first and last quarters of 2020 to the change in outcomes between the same two quarters of 2019.
They looked at two different outcomes: high dropout risk (i.e., whether the student had any math and Portuguese grades on his school record in the relevant quarter), and standardised test scores.
When comparing the change in 2020 to the change in 2019, the researchers found large increases in school dropout and learning losses.
Furthermore, they exploited a natural experiment to gauge the impact of switching back to in-person learning. In the fourth quarter of 2020, some municipalities allowed high-schools but not middle-schools to switch back. This allowed the researchers to compare middle- and high-schools in those municipalities with respect to the change in 2020 versus the change in 2019.
Consistent with the previous result, they found that switching back to in-person learning was associated with higher standardised test scores.
In the authors’ own words, their results show that “the societal costs of keeping schools closed in the pandemic are very large”. As such, they argue that “the public debate should move from whether schools should be open or not to how to reopen them safely”.
Life Insurance and Covid-19; Something Doesn’t Make Sense
By Jeff Harris | Ron Paul Institute | May 26, 2021
You would think that during the worst Pandemic since the 1918 Spanish Flu life insurance companies would be hedging their bets to avoid major losses from Covid-19. I haven’t written a life policy for several years so I was wondering what was going on? I called one of the brokers I deal with that interacts with hundreds of big life insurers to get an inside look into how the Covid crisis has changed their business.
Imagine my surprise when she said it was pretty much business as usual! Last year when the hysteria was just getting ramped up she did say the companies temporarily tightened up underwriting and reduced the amount of coverage they would offer. But as time went by and the hard data came rolling in those same companies went back to business as usual.
I asked her specifically if life insurers wanted a Covid test as part of the underwriting process and she said none that she was aware of. Hmm, that’s pretty interesting isn’t it? The most lethal pandemic in decades descends on the globe with deadly mutations taking millions of innocent lives and the life insurance companies couldn’t care less.
I also asked if the cost per thousand of coverage had increased due to Covid and again she said no. Rates were pretty much the same as they were before the Covid Pandemic ravaged the earth. Life Insurance companies are very risk adverse. They don’t like losing money to unnecessary claims. The fact they’re treating Covid as a nonevent should be an indicator that something is very wrong with the whole narrative.
Copyright © 2021 by RonPaul Institute
MORE Flagrant Data Manipulation from the CDC
New report is further evidence the CDC is deliberately hiding post-vaccine “breakthrough cases”
By Kit Knightly | OffGuardian | May 26, 2021
A new report, published just yesterday, has provided yet more evidence that the CDC is manipulating data to conceal the number of “breakthrough infections”.
A “breakthrough infection” (or “breakthrough case”) is defined as a person who tests positive for Sars-Cov-2 infection, despite already being fully vaccinated. And this new report finds that the CDC’s official record of breakthrough cases is:
likely a substantial undercount.
Going on to explain:
The national surveillance system relies on passive and voluntary reporting, and data might not be complete or representative. Many persons with vaccine breakthrough infections, especially those who are asymptomatic or who experience mild illness, might not seek testing.
Which is partially accurate, but also a pretty major lie by omission.
It is probably true that vaccinated people with no symptoms are unlikely to seek testing, but it is also true that, on March 17th, the CDC updated their advice on testing policy to specifically exclude such people from testing protocols:

Screencap of CDC’s testing guidelines
So, while it’s certainly true that “breakthrough cases” are likely a substantial undercount, it is dishonest to pretend that this is just an accident of the system. Rather, the system is specifically designed to hide such cases.
Of course, this report only goes up to the end of April, the “undercount” will only have gotten worse since then, because the CDC changed their rules AGAIN to make it even harder to keep an accurate count of breakthrough cases.
As we wrote last week, as of May 1st the CDC will no longer be counting mild or asymptomatic cases as “breakthrough infections”, choosing to focus only on hospitalisations and deaths.
According to the CDC’s own report, though, over a quarter (27%) of breakthrough infections were asymptomatic, and a further 61% were only mildly ill. Conversely, only 10% of them were ever hospitalised, and only 2% died:
Based on preliminary data, 2,725 (27%) vaccine breakthrough infections were asymptomatic, 995 (10%) patients were known to be hospitalized, and 160 (2%) patients died.
So, the CDC has taken their “substantial undercount”, and then slashed it by 90%. The official figures, moving forward, will be so inaccurate as to be completely useless.
The CDC claims these changes “will help maximize the quality of the data collected on cases of greatest clinical and public health importance.” But that is an obvious and absurd lie.
Statistical studies have shown up to 86% of Covid “cases” never experience symptoms. To exclude such cases from your vaccine effectiveness studies is to poison your data in order to prop up a pre-determined conclusion. It is, at the very best, extremely poor science.
Of course, the truth is far more cynical even than that.
From the beginning of the so-called “pandemic”, waves of asymptomatic “cases” were deliberately created by running unreliable PCR tests on 100,000s of perfectly healthy people every day.
The entirely predictable false positives were called “cases”, and these manufactured “cases” of Covid19 were used to build up the illusion of a global plague.
This was a prolonged campaign of deception in order to bring about sweeping changes in the construction of our society.
To this point “asymptomatic cases” have been the backbone of the Covid narrative. But now the CDC has attempted to remove them from the reckoning by instructing medical labs and hospitals around the country to stop looking for them, but only in those who have had the “vaccine”.
This is a new prolonged campaign of deception, spinning the narrative that these untested, experimental “vaccines” truly are “effective” against a “pandemic” that was built on statistical smoke and mirrors.
In short: before the vaccine they needed “asymptomatic infections” to create a “problem”, after the vaccine they are actively hiding “asymptomatic infections”, because their existence undermines their “solution”.
“Breakthrough infections”, existing in anything approaching large numbers, effectively means one of three things is true: either the tests are unreliable, the “vaccines” are ineffective…or both.
To anyone interested in the truth, keeping an accurate count of these “breakthrough infections” is therefore vitally important.
The corollary of that, of course, is that anyone attempting to conceal, minimise or ignore them is NOT interested in the truth. Such behaviour is, in fact, a tacit admission of deception.
JHU Prof: Half Of Americans Have Natural Immunity; Dismissing It Is ‘Biggest failure Of Medical Leadership’
“Please, ignore the CDC guidance”
By Steve Watson | Summit News | May 26, 2021
A professor with the Johns Hopkins School of Medicine has said that there is a general dismissal of the fact that more than half of all Americans have developed natural immunity to the coronavirus and that it constitutes “one of the biggest failures of our current medical leadership.”
Dr. Marty Makary made the comments during a recent interview, noting that “natural immunity works” and it is wrong to vilify those who don’t want the vaccine because they have already recovered from the virus.
Makary criticised “the most slow, reactionary, political CDC in American history” for not clearly communicating the scientific facts about natural immunity compared to the kind of immunity developed through vaccines.
“There is more data on natural immunity than there is on vaccinated immunity, because natural immunity has been around longer,” Makary emphasised.
“We are not seeing reinfections, and when they do happen, they’re rare. Their symptoms are mild or are asymptomatic,” the professor added.
“Please, ignore the CDC guidance,” he urged, adding “Live a normal life, unless you are unvaccinated and did not have the infection, in which case you need to be careful.”
“We’ve got to start respecting people who choose not to get the vaccine instead of demonizing them,” Makary further asserted.
The professor’s comments come amid a plethora of media generated propaganda suggesting that natural immunity isn’t enough, and that those who do not choose to take the vaccine should be socially ostracised.
The likes of the World Health Organisation have even shifted the definition of ‘herd immunity’, eliminating the pre-COVID scientific consensus that it could be achieved by allowing a virus to spread through a population, and insisting that herd immunity comes solely from vaccines.
Google blocks ads from Italian author who suggested coronavirus could have originated in a lab
By Didi Rankovic | Reclaim the Net | May 26, 2021
Facebook, YouTube and other major social media platforms have been enforcing extremely strict rules around what their users can and cannot say about coronavirus and the pandemic for over a year now, to make sure only messages and narratives aligned with state authorities and the WHO made it through.
But at this point, it looks like those rules are even more stringent than what officials are saying, to the point that, if applied consistently, Facebook would have to ban Dr Fauci for not ruling out the possibility that the virus was engineered by humans.
This has so far been considered the type of “misinformation” that is sure to get posts deleted and accounts suspended, as Facebook says it prohibits any discussion around coronavirus possibly being man-made.
Facebook is not alone, since YouTube has a similar censorship policy. Only last week, Google prevented Italian journalist Fabrizio Gatti from advertising his book that explores much the same topic that Fauci did in his recent comments. Google said Gatti – whose book also criticizes China’s role – was guilty of creating content with “speculative intent.”
“Once the infection is overcome with vaccines, as I write in my book, we will have to defend our democracies from totalitarianism and the digital monopoly,” Gatti said, reacting to the blacklisting, and urged Google to reverse the decision.
Other contentious rules enforced by YouTube concern any questioning of the usefulness of masks, regardless of the fact official recommendations and guidelines on this topic have been changing throughout the pandemic.
Along the same line, saying that coronavirus vaccines might cause serious harm to people will get content and/or users banned on Facebook – even if medical authorities in Europe and in other places say that at least two of them – AstraZeneca and Johnson & Johnson – can cause blood clots, though rare.
Even though tech giants behind the largest social media sites defend their policies as a way to prevent misinformation and promote official sources, those who have been on the receiving end – everyday users, medical professionals, journalists – see this as unwarranted censorship that stifles any debate.
And as former New York Times journalist Alex Berenson observed, this vigorous suppression of opposing views around Covid is a cause for concern, but is also emblematic of the general direction we’re headed in.
“This isn’t about Covid, it’s about whether or not as a society we’re going to allow people who have views that are sort of outside what the mainstream media want you to believe, to present those views. It’s becoming harder and harder to have honest conversations,” said Berenson, whose book skeptical of lockdowns and masks Amazon had temporarily banned.
Featured Video

Ivermectin and iodine
or go to
Aletho News Archives – Video-Images
Book Review
UAE tortured, killed journalist for opposing Israel normalization
The Cradle | October 31, 2026
UAE security officers detained, tortured, and killed Emirati poet and news editor Habib al-Sayegh in August 2019, shortly after he published a column opposing UAE normalization with Israel, according to a newly published book.
“Princes and Thieves,” a book by investigative journalist Matthew Cole published on 25 October, alleges that UAE security officers raided Sayegh’s Abu Dhabi home shortly after the publication of the column, hooded him in front of his wife and took him to a detention facility where he was tortured to death.
His interrogators reportedly pulled out several of his teeth with pliers and beat him repeatedly with a sharp metal object.
On 11 August 2019, Sayegh criticized the UAE’s plan to normalize relations with Israel as part of the Abraham Accords in his weekly column for Khaleej newspaper. The column was titled “Israel Is Our Real Enemy and A Dangerous Project.”
Sayegh described Israel as “a real and natural enemy” while questioning “who authorized the normalizers to speak on behalf of everyone?”
Nine days after the column was published, Emirati state media announced his death, without stating a cause. … continue
Blog Roll
 Aletho News
- Ivermectin and iodine
- Congratulations climate skeptics — you are a ‘Hybrid weapon of war’ and a growing public health threat
- ‘The Arab Vote’: How Israeli Racism Has Ruined Their Elections
- Israel forces Palestinians in Gaza to choose between assassination alone or death with their families: Report
- US Approves Sale of 500 Patriot Missiles to Ukraine, Deliveries May Take Years
- German Imperialism: An Urgent Explainer
- Backed by AAP, West Virginia Proposal Would Allow Dental Hygienists to Give HPV Vaccine to 9-Year-Olds
- Poland Is the Symptom and Europe Is the Patient
- UAE security forces tortured, killed journalist for opposing Israel normalization: Report
- They Compared the Spice to the Drug. The Spice Won — Again. (Part 2)
- If Americans Knew
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- 1,300 will gather in Palo Alto on Nov. 1 for Z3 Conference on Zionism
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- The Long Arm of AIPAC
- Genocidal intent behind Hebron assault, rights group says
- This week, Israel killed 8-year-old who survived bombing that wiped out her family
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- Israeli soldier poses at damaged Lebanon church, sparking anger
- New Report. Manufacturing the Great Replacement: Is Israel behind one of the largest racist influence campaigns ever documented?
- ‘Arab voice doesn’t count’: Jewish Israeli blocs reject Palestinian support
- No Tricks Zone
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!

