Over a dozen U.S. cities and counties are now pro-freedom ‘sanctuaries’ against COVID measures
LifeSiteNews – May 5, 2021
More than a dozen cities and counties in the United States are fighting COVID-19 restrictions by designating themselves pro-freedom “sanctuaries” or by simply refusing to enforce emergency orders.
The counties are primarily located in highly regulated states – like Michigan and California – that have suffered catastrophic economic and mental health impacts amid months of business closures and mask mandates.
Late last year, county commissioners in Campbell County, Virginia passed a “First Amendment Sanctuary” resolution, declaring that “(n)o Campbell County funds will be used to restrict the First Amendment.” No funding “shall be expended to aid federal or state agencies in the restriction of said rights,” it added.
“We’re not going to utilize county resources to enforce the governor’s orders,” a district representative from the county told local news. “We’re not going to aid the Virginia Department of Health in shutting our businesses down.”
At least nine other cities and counties have passed similar “sanctuary” designations, including Burrillville, Rhode Island, Delta County, Michigan, Kosciusko County, Carroll County and the city of Mooresville in Indiana, and multiple jurisdictions in California and Texas.
In Michigan’s Baraga County earlier this year, the county sheriff and other officials approved the “Baraga Manifesto,” slamming Gov. Gretchen Whitmer’s “clearly unconstitutional measures that treat human beings like herd animals.”
“Since March 10, 2020, the People of the State of Michigan have endured restrictions on their freedom which have not been seen in North America since the days of King George III and the American Revolution,” the officials wrote. “Enough is enough.”
“Accordingly, we hereby put the State of Michigan on NOTICE that we have no intention of participating in the unconstitutional destruction of our citizens’ economic security and Liberty,” they continued. “We further declare our intention to take no action whatsoever in furtherance of this terribly misguided agenda.” The manifesto echoes defiant local resolutions approved in Nebraska and Colorado.
At least one conservative county also has signaled its resistance to coronavirus vaccine mandates.
Assemblymen in Kenai Peninsula Borough, Alaska, passed a resolution in December stressing that the county supports vaccination on an “optional basis.” The statement, which passed 8-1, says that “the best interests of the state” are not served by mandating a vaccine that “many people are concerned… could potentially have serious harmful effects on themselves.”
State legislatures have pushed back against COVID-19 rules as well, with more than nine states enacting new restrictions of executives’ emergency powers or advancing vaccine passport bans since the start of the crisis.
Government Documents reveal how Brits have been manipulated into complying with Medical Tyranny
THE DAILY EXPOSE • MAY 6, 2021
The ordinary hard working people of the United Kingdom have been played. They have been manipulated and coerced into complying with medical fascism, thanks to the psychological warfare unleashed by the UK Government and its Scientific advisors every waking hour since March 2020.
The authority’s weapons have included the television, the radio, the newspapers. But their most important weapon in ensuring the general public have complied with dictatorial tyranny and offered themselves up as lab rats in the largest experiment to ever be conducted in human history, is a weapon that everyone reading this will know personally. Because that weapon has been you.
To understand just how the authorities have managed to manipulate and coerce the British people into complying with medical fascism we must go back to March 2020. It was at this point that Boris Johnson had one simple instruction for the British people, that instruction being that “you must stay at home”. Stay at home in order to protect the NHS and save lives. This was sold to the British people by informing them that the authorities needed just “three weeks to flatten the curve”. But those three weeks turned into six weeks. Then those six weeks turned into twelve weeks. Then those twelve weeks turned into twelve months, and still to this day the freedoms that were taken for granted prior to March 2020 do not seem within reach.
But how on earth have they managed to get away with it? Well we only need to delve into government documents which are readily available to the public, if they know how to find them. The first document we discovered is titled ‘Options for increasing adherence to social distancing measures’ and was published on the 22nd March 2020, one day prior to the announcement that the British people “must stay at home”.
This is one of the problems they felt they has in persuading people to social distance –
A substantial number of people still do not feel sufficiently personally threatened; it could be that they are reassured by the low death rate.
They were quite right, and are still quite right to be reassured by the low death rate, as statistics show that just 0.2% of those who develop the alleged Covid-19 disease tragically die. And even then the vast majority who do die are over the age of 85 and also have underlying conditions.
But that wouldn’t help to create the illusion of a problem if they couldn’t get people to social distance so here’s what the behavioural insight team advised the UK Government to do in response to this problem –
The perceived level of personal threat needs to be increased among those who are complacent, using hard-hitting emotional messaging. To be effective this must also empower people by making clear the actions they can take to reduce the threat.

‘Perceived’ is probably the most key word within that advice given to the UK Government on how to manipulate the British people. As this entire charade has been entirely about perception. If there was any level of personal threat then there would be no need to use hard hitting emotional messaging as people would already genuinely feel threatened. If there was truly something for the British people to be wary of then it would not need a mass media advertising campaign to make them aware of it.
But here’s an example of some of the ‘hard hitting emotional messaging’ used to manipulate the British people into complying with medical fascism –

“Don’t kill granny with the virus” warns Matt Hancock who blames spike in Covid cases on middle-class youth. This is just one example of many that have been used to increase the perceived level of personal threat.
But propaganda messages via the media weren’t enough on their own so that’s where the most vital weapon up the authorities sleeve came in – you. The ‘Options for increasing adherence to social distancing measures’ document has within it a section titled ‘Coercion’. No we’re not making it up, and this was one of the points made within that section –
Social disapproval from one’s community can play an important role in preventing anti-social behaviour or discouraging failure to enact pro-social behaviour, (therefore) consideration should be given to the use of social disapproval.

Those who fell for the propaganda and lies broadcast on every mainstream TV channel and radio station, and published in every mainstream newspaper have been the glue that has kept the destruction of life as we knew it together. Because they have policed the introduction of medical fascism for the authorities, and they don’t even realise that they have and are being used.
The document lists every single tactic used to ensure the British people complied with the loss of their rights and freedoms and these have included –
- Using media to increase the sense of personal threat
- Using media to increase the sense of responsibility to others
- Using and promoting social approval for desired behaviors
- Using social disapproval for those who do not comply


The document explains in full how they have managed to manipulate and coerce the British public into complying with medical fascism using psychological warfare. But how exactly are authorities going to keep up this charade now that the “miraculous” experimental vaccines are being rolled out across the country? How are they going to ensure the British people continue to comply with medical fascism now that the most vulnerable to this alleged disease have been vaccinated?
Well another document found on the Government website helps us to find the answer to that. The document is titled ‘Behavioural and social considerations when reducing restrictions’ and was released on the 10th February 2021. A document which essentially confirms the writing is on the wall for a return to normality and that the introduction of vaccine passports (freedom passes) is inevitable.
One of the points made in the document describes the issues that may arise as some interventions are lifted. With complications on messaging due to “differences across tiers” and “immunity or vaccination certificates providing exemptions” for those who are vaccinated to carry out or take part in certain activities.

Tiers? But Boris Johnson said we were going back to normal on the 21st June, why on earth would we need tiers? Because he’s a liar.
Another line in the document explains that another problem for the authorities in getting the British public to continue to comply with medical fascism is that “as perceptions of immunity grow, messaging may need to explain why continued adherence to specific protective measures is important”.

Why exactly will the British people need to continue to adhere to restrictions if they now have a miraculous experimental vaccine that will “save” them from Covid-19? After all the Health Secretary, Matt Hancock is constantly reminding us that “vaccination is our route back to normal”.
Well maybe the next part of the document can explain why, and it’s a card they have kept up their sleeve and are yet to really play, but we all know it is coming.
he document states that “17% of adults expect life to return to normal in six months or less. Modelling from SPI-M suggests this is optimistic. Additionally, the challenge of new variants may call for sudden, strict reimposition of measures”.

If you thought life was going back to normal on the 21st June then think again, it’s not in the script, quite the opposite is going to happen and we’ve just shown you the evidence in black and white.
A Third of All Recent ‘Covid Deaths’ in England and Wales Not Caused by Coronavirus
21st Century Wire | May 6, 2021

After a year of incessant fearmongering, fraudulent PCR testing and generally inflating its Covid numbers, new data analysis reveals how the government’s rampant statistical fraud still continues unabated, as increasing numbers of people whose underlying cause of death was not due coronavirus – are still being included in the government’s hallowed ‘death count.’
Despite this exposure, the mainstream media and government officials seem unwilling to acknowledge how this fundamental deception has been used as the underlying basis for nearly every single ‘public health’ measure – coming at an incalculable cost for those countries and societies placed under the yoke of so-called ‘virus mitigation’ policies.
The inflated Covid death numbers are then used by the government and media as a ‘moral trigger’ to impose rolling lockdowns, as well as other repressive and needless policies such as mask mandates, business and school closures, deregulated emergency vaccine roll-outs, and arbitrary non-science-based “social distancing” rules.
The UK Telegraph reports…
Nearly one third of recently registered Covid deaths in England and Wales are people who died primarily from other causes, the latest figures show.
Weekly death data from the Office for National Statistics (ONS) shows that, for nearly 33 per cent of people included in the overall coronavirus death figures, Covid was not an underlying cause of death but was merely mentioned on the death certificate.
The number of people who are not principally dying from Covid but are still being included in the official figures has been creeping up steadily as the pandemic has declined.
It had been running at around 10 per cent for most of the crisis but had risen to nearly a quarter by mid-April and is continuing to increase.
In the latest data, published on Wednesday, which records death registrations in the week ending April 23, some 260 deaths from Covid were recorded in England and Wales, but only 67.7 per cent (176) of those had the virus as an underlying cause.
COVID Vaccines: Necessity, Efficacy and Safety
Doctors for Covid Ethics | OffGuardian | May 5, 2021
This paper was originally hosted on the Doctors for Covid Ethics Medium account, but the platform censored the expert group and removed the paper, claiming the post was “under investigation”:
An archived version is still available here.
*
Abstract: COVID-19 vaccine manufacturers have been exempted from legal liability for vaccine-induced harm. It is therefore in the interests of all those authorising, enforcing and administering COVID-19 vaccinations to understand the evidence regarding the risks and benefits of these vaccines, since liability for harm will fall on them.
In short, the available evidence and science indicate that COVID-19 vaccines are unnecessary, ineffective and unsafe.
- Necessity: Immunocompetent individuals are protected against SARS-CoV-2 by cellular immunity. Vaccinating low-risk groups is therefore unnecessary. For immunocompromised individuals who do fall ill with COVID-19 there is a range of medical treatments that have been proven safe and effective. Vaccinating the vulnerable is therefore equally unnecessary. Both immunocompetent and vulnerable groups are better protected against variants of SARS-CoV-2 by naturally acquired immunity and by medication than by vaccination.
- Efficacy: Covid-19 vaccines lack a viable mechanism of action against SARS-CoV-2 infection of the airways. Induction of antibodies cannot prevent infection by an agent such as SARS-CoV-2 that invades through the respiratory tract. Moreover, none of the vaccine trials have provided any evidence that vaccination prevents transmission of the infection by vaccinated individuals; urging vaccination to “protect others” therefore has no basis in fact.
- Safety: The vaccines are dangerous to both healthy individuals and those with pre-existing chronic disease, for reasons such as the following: risk of lethal and non-lethal disruptions of blood clotting including bleeding disorders, thrombosis in the brain, stroke and heart attack; autoimmune and allergic reactions; antibody-dependent enhancement of disease; and vaccine impurities due to rushed manufacturing and unregulated production standards.
The risk-benefit calculus is therefore clear: the experimental vaccines are needless, ineffective and dangerous. Actors authorising, coercing or administering experimental COVID-19 vaccination are exposing populations and patients to serious, unnecessary, and unjustified medical risks.
1. THE VACCINES ARE UNNECESSARY
1. Multiple lines of research indicate that immunocompetent people display “robust” and lasting cellular (T cell) immunity to SARS-CoV viruses [1], including SARS-CoV-2 and its variants [2]. T cell protection stems not only from exposure to SARS-CoV-2 itself, but from cross-reactive immunity following previous exposure to common cold and SARS coronaviruses [1,3-10]. Such immunity was detectable after infections up to 17 years prior [1,3]. Therefore, immunocompetent people do not need vaccination against SARS-Cov-2.
2. Natural T-Cell immunity provides stronger and more comprehensive protection against all SARS-CoV-2 strains than vaccines, because naturally primed immunity recognises multiple virus epitopes and costimulatory signals, not merely a single (spike) protein. Thus, immunocompetent people are better protected against SARS-CoV-2 and any variants that may arise by their own immunity than by the current crop of vaccines.
3.The vaccines have been touted as a means to prevent asymptomatic infection [11], and by extension “asymptomatic transmission.” However, “asymptomatic transmission” is an artefact of invalid and unreliable PCR test procedures and interpretations, leading to high false-positive rates[12-15]. Evidence indicates that PCR-positive, asymptomatic people are healthy false-positives, not carriers. A comprehensive study of 9,899,828 people in China found that asymptomatic individuals testing positive for COVID-19 never infected others[16].
In contrast, the papers cited by the Centre for Disease Control[17,18] to justify claims of asymptomatic transmission are based on hypothetical models, not empirical studies; they present assumptions and estimates rather than evidence. Preventing asymptomatic infection is not a viable rationale for promoting vaccination of the general population.
4. In most countries, most people now have immunity to SARS-CoV-2[19]. Depending on their degree of previously acquired cross-immunity, they will have had no symptoms, mild and uncharacteristic symptoms, or more severe symptoms, possibly including anosmia (loss of sense of smell) or other somewhat characteristic signs of the COVID-19 disease. Regardless of disease severity, they will now have sufficient immunity to be protected from severe disease in the event of renewed exposure. This majority of the population will not benefit at all from being vaccinated.
5. Population survival of COVID-19 exceeds 99.8% globally[20-22]. In countries that have been intensely infected over several months, less than 0.2% of the population have died and had their deaths classified as ‘with covid19’. COVID-19 is also typically a mild to moderately severe illness. Therefore, the overwhelming majority of people are not at risk from COVID-19 and do not require vaccination for their own protection.
6. In those susceptible to severe infection, Covid-19 is a treatable illness. A convergence of evidence indicates that early treatment with existing drugs reduces hospitalisation and mortality by ~85% and 75%, respectively[23-27]. These drugs include many tried and true anti-inflammatory, antiviral, and anticoagulant medications, as well as monoclonal antibodies, zinc, and vitamins C and D.
Industry and government decisions to sideline such proven treatments through selective research support[24], regulatory bias, and even outright sanctions against doctors daring to use such treatments on their own initiative, have been out of step with existing laws, standard medical practice, and research; the legal requirement to consider real world evidence has fallen by the wayside[28].
The systematic denial and denigration of these effective therapies has underpinned the spurious justification for the emergency use authorisation of the vaccines, which requires that “no standard acceptable treatment is available”[29]. Plainly stated, vaccines are not necessary to prevent severe disease.
2. THE VACCINES LACK EFFICACY
1. At a mechanistic level, the concept of immunity to COVID-19 via antibody induction, as per COVID-19 vaccination, is medical nonsense. Airborne viruses such as SARS-CoV-2 enter the body via the airways and lungs, where antibody concentrations are too low to prevent infection. Vaccine-induced antibodies primarily circulate in the bloodstream, while concentrations on the mucous membranes of lungs and airways is low.
Given that COVID-19 primarily spreads and causes disease by infecting these mucous membranes, vaccines miss the immunological mark. The documents submitted by the vaccine manufacturers to the various regulatory bodies contain no evidence that vaccination prevents airway infection, which would be crucial for breaking the chain of transmission. Thus, vaccines are immunologically inappropriate for COVID-19.
2. Medium to long-term vaccine efficacy is unknown. Phase 3, medium-term, 24-month trials will not be complete until 2023: There is no medium-term or long term longitudinal data regarding COVID-19 vaccine efficacy.
3. Short term data has not established prevention of severe disease. The European Medicines Agency has noted of the Comirnaty (Pfizer mRNA) vaccine that severe COVID-19 cases “were rare in the study, and statistically certain conclusion cannot be drawn” from it[30]. Similarly, the Pfizer document submitted to the FDA[31] concludes that efficacy against mortality could not be demonstrated. Thus, the vaccines have not been shown to prevent death or severe disease even in the short term.
4. The correlates of protection against COVID-19 are unknown. Researchers have not yet established how to measure protection against COVID-19. As a result, efficacy studies are stabbing around in the dark. After completion of Phase 1 and 2 studies, for instance, a paper in the journal Vaccine noted that “without understanding the correlates of protection, it is impossible to currently address questions regarding vaccine-associated protection, risk of COVID-19 reinfection, herd immunity, and the possibility of elimination of SARS-CoV-2 from the human population”[32]. Thus, Vaccine efficacy cannot be evaluated because we have not yet established how to measure it.
3. THE VACCINES ARE DANGEROUS
1. Just as smoking could be and was predicted to cause lung cancer based on first principles, all gene-based vaccines can be expected to cause blood clotting and bleeding disorders [33], based on their molecular mechanisms of action. Consistent with this, diseases of this kind have been observed across age groups, leading to temporary vaccine suspensions around the world: The vaccines are not safe.
2. Contrary to claims that blood disorders post-vaccination are “rare”, many common vaccine side effects (headaches, nausea, vomiting and haematoma-like “rashes” over the body) may indicate thrombosis and other severe abnormalities. Moreover, vaccine-induced diffuse micro-thromboses in the lungs can mimic pneumonia and may be misdiagnosed as COVID-19. Clotting events currently receiving media attention are likely just the “tip of a huge iceberg”[34]: The vaccines are not safe.
3. Due to immunological priming, risks of clotting, bleeding and other adverse events can be expected to increase with each re-vaccination and each intervening coronavirus exposure. Over time, whether months or years[35], this renders both vaccination and coronaviruses dangerous to young and healthy age groups, for whom without vaccination COVID-19 poses no substantive risk. Since vaccine roll-out, COVID-19 incidence has risen in numerous areas with high vaccination rates[36-38].
Furthermore, multiple series of COVID-19 fatalities have occurred shortly after the onset vaccinations in senior homes[39,40]. These cases may have been due not only to antibody-dependent enhancement but also to a general immunosuppressive effect of the vaccines, which is suggested by the increased occurrence of Herpes zoster in certain patients[41].
Immunosuppression may have caused a previously asymptomatic infection to become clinically manifest. Regardless of the exact mechanism responsible for these reported deaths, we must expect that the vaccines will increase rather than decrease lethality of COVID-19 — the vaccines are not safe.
4. The vaccines are experimental by definition. They will remain in Phase 3 trials until 2023. Recipients are human subjects entitled to free informed consent under Nuremberg and other protections, including the Parliamentary Assembly of the Council of Europe’s resolution 2361[43] and the FDA’s terms of emergency use authorisation[29]. With respect to safety data from Phase 1 and 2 trials, in spite of initially large sample sizes the journal Vaccine reports that, “the vaccination strategy chosen for further development may have only been given to as few as 12 participants”[32].
With such extremely small sample sizes, the journal notes that, “larger Phase 3 studies conducted over longer periods of time will be necessary” to establish safety. The risks that remain to be evaluated in Phase 3 trials into 2023, with entire populations as subjects, include not only thrombosis and bleeding abnormalities, but other autoimmune responses, allergic reactions, unknown tropisms (tissue destinations) of lipid nanoparticles[35], antibody-dependent enhancement [43-46] and the impact of rushed, questionably executed, poorly regulated[47] and reportedly inconsistent manufacturing methods, conferring risks of potentially harmful impurities such as uncontrolled DNA residues[48]. The vaccines are not safe, either for recipients or for those who administer them or authorise their use.
5. Initial experience might suggest that the adenovirus-derived vaccines (AstraZeneca/Johnson & Johnson) cause graver adverse effects than the mRNA (Pfizer/Moderna) vaccines. However, upon repeated injection, the former will soon induce antibodies against the proteins of the adenovirus vector. These antibodies will then neutralize most of the vaccine virus particles and cause their disposal before they can infect any cells, thereby limiting the intensity of tissue damage.
In contrast, in the mRNA vaccines, there is no protein antigen for the antibodies to recognize. Thus, regardless of the existing degree of immunity, the vaccine mRNA is going to reach its target — the body cells. These will then express the spike protein and subsequently suffer the full onslaught of the immune system.
With the mRNA vaccines, the risk of severe adverse events is virtually guaranteed to increase with every successive injection. In the long term, they are therefore even more dangerous than the vector vaccines. Their apparent preferment over the latter is concerning in the highest degree; these vaccines are not safe.
4. ETHICS AND LEGAL POINTS TO CONSIDER
Conflicts of interest abound in the scientific literature and within organisations that recommend and promote vaccines, while demonising alternate strategies (reliance on natural immunity and early treatment). Authorities, doctors and medical personnel need to protect themselves by evaluating the sources of their information for conflicts of interest extremely closely.
Authorities, doctors and medical personnel need to be similarly careful not to ignore the credible and independent literature on vaccine necessity, safety and efficacy, given the foreseeable mass deaths and harms that must be expected unless the vaccination campaign is stopped.
Vaccine manufacturers have exempted themselves from legal liability for adverse events for a reason. When vaccine deaths and harms occur, liability will fall to those responsible for the vaccines’ authorisation, administration and/or coercion via vaccine passports, none of which can be justified on a sober, evidence-based risk-benefit analysis.
All political, regulatory and medical actors involved in COVID-19 vaccination should familiarise themselves with the Nuremberg code and other legal provisions in order to protect themselves.
References:
[1] Le Bert, N.; Tan, A.T.; Kunasegaran, K.; Tham, C.Y.L.; Hafezi, M.; Chia, A.; Chng, M.H.Y.; Lin, M.; Tan, N.; Linster, M.; Chia, W.N.; Chen, M.I.; Wang, L.; Ooi, E.E.; Kalimuddin, S.; Tambyah, P.A.; Low, J.G.; Tan, Y. and Bertoletti, A. (2020) SARS-CoV-2-specific T cell immunity in cases of COVID-19 and SARS, and uninfected controls. Nature 584:457–462. [back]
[2] Tarke, A.; Sidney, J.; Methot, N.; Zhang, Y.; Dan, J.M.; Goodwin, B.; Rubiro, P.; Sutherland, A.; da Silva Antunes, R.; Frazier, A. and al., e. (2021) Negligible impact of SARS-CoV-2 variants on CD4+ and CD8+ T cell reactivity in COVID-19 exposed donors and vaccinees. bioRxiv -:x-x.[back]
[3] Anonymous, (2020) Scientists uncover SARS-CoV-2-specific T cell immunity in recovered COVID-19 and SARS patients. [back]
[4] Beasley, D. (2020) Scientists focus on how immune system T cells fight coronavirus in absence of antibodies. Reuters, 10/07/2020. [back]
[5] Bozkus, C.C. (2020) SARS-CoV-2-specific T cells without antibodies. Nat. Rev. Immunol. 20:463. [back]
[6] Grifoni, A.; Weiskopf, D.; Ramirez, S.I.; Mateus, J.; Dan, J.M.; Moderbacher, C.R.; Rawlings, S.A.; Sutherland, A.; Premkumar, L.; Jadi, R.S. and al., e. (2020) Targets of T Cell Responses to SARS-CoV-2 Coronavirus in Humans with COVID-19 Disease and Unexposed Individuals. Cell 181:1489–1501.e15. [back]
[7] Mateus, J.; Grifoni, A.; Tarke, A.; Sidney, J.; Ramirez, S.I.; Dan, J.M.; Burger, Z.C.; Rawlings, S.A.; Smith, D.M.; Phillips, E. and al., e. (2020) Selective and cross-reactive SARS-CoV-2 T cell epitopes in unexposed humans. [back]Science 370:89–94. [back]
[8] McCurry-Schmidt, M. (2020) Exposure to common cold coronaviruses can teach the immune system to recognize SARS-CoV-2. La Jolla Institute for Immunology. [back]
[9] Palmer, S.; Cunniffe, N. and Donnelly, R. (2021) COVID-19 hospitalization rates rise exponentially with age, inversely proportional to thymic T-cell production. J. R. Soc. Interface 18:20200982. [back]
[10] Sekine, T.; Perez-Potti, A.; Rivera-Ballesteros, O.; Strålin, K.; Gorin, J.; Olsson, A.; Llewellyn-Lacey, S.; Kamal, H.; Bogdanovic, G.; Muschiol, S. and al., e. (2020) Robust T Cell Immunity in Convalescent Individuals with Asymptomatic or Mild COVID-19. Cell 183:158–168.e14. [back]
[11] Drake, J. (2021) Now We Know: Covid-19 Vaccines Prevent Asymptomatic Infection, Too.[back]
[12] Bossuyt, P.M. (2020) Testing COVID-19 tests faces methodological challenges. Journal of clinical epidemiology 126:172–176. [back]
[13] Jefferson, T.; Spencer, E.; Brassey, J. and Heneghan, C. (2020) Viral cultures for COVID-19 infectivity assessment. Systematic review. Clin. Infect. Dis. ciaa1764:x-x. [back]
[14] Borger, P.; Malhotra, R.K.; Yeadon, M.; Craig, C.; McKernan, K.; Steger, K.; McSheehy, P.; Angelova, L.; Franchi, F.; Binder, T.; Ullrich, H.; Ohashi, M.; Scoglio, S.; Doesburg-van Kleffens, M.; Gilbert, D.; Klement, R.J.; Schrüfer, R.; Pieksma, B.W.; Bonte, J.; Dalle Carbonare, B.H.; Corbett, K.P. and Kämmer, U. (2020) External peer review of the RTPCR test to detect SARS-CoV-2 reveals 10 major scientific flaws at the molecular and methodological level: consequences for false-positive results. [back]
[15] Mandavilli, A. (2020) Your Coronavirus Test Is Positive. Maybe It Shouldn’t Be.[back]
[16] Cao, S.; Gan, Y.; Wang, C.; Bachmann, M.; Wei, S.; Gong, J.; Huang, Y.; Wang, T.; Li, L.; Lu, K.; Jiang, H.; Gong, Y.; Xu, H.; Shen, X.; Tian, Q.; Lv, C.; Song, F.; Yin, X. and Lu, Z. (2020) Post-lockdown SARS-CoV-2 nucleic acid screening in nearly ten million residents of Wuhan, China. Nat. Commun. 11:5917.[back]
[17] Moghadas, S.M.; Fitzpatrick, M.C.; Sah, P.; Pandey, A.; Shoukat, A.; Singer, B.H. and Galvani, A.P. (2020) The implications of silent transmission for the control of COVID-19 outbreaks. Proc. Natl. Acad. Sci. U. S. A. 117:17513–17515.[back]
[18] Johansson, M.A.; Quandelacy, T.M.; Kada, S.; Prasad, P.V.; Steele, M.; Brooks, J.T.; Slayton, R.B.; Biggerstaff, M. and Butler, J.C. (2021) SARS-CoV-2 Transmission From People Without COVID-19 Symptoms. JAMA network open 4:e2035057.[back]
[19] Yeadon, M. (2020). What SAGE got wrong. Lockdown Skeptics.[back]
[20] Ioannidis, J.P.A. (2020) Global perspective of COVID‐19 epidemiology for a full‐cycle pandemic. Eur. J. Clin. Invest. 50:x-x. [back]
[21] Ioannidis, J.P.A. (2021) Reconciling estimates of global spread and infection fatality rates of COVID‐19: An overview of systematic evaluations. Eur. J. Clin. Invest. -:x-x. [back]
[22] CDC, (2020) Science Brief: Community Use of Cloth Masks to Control the Spread of SARS-CoV-2. [back]
[23] Orient, J.; McCullough, P. and Vliet, E. (2020) A Guide to Home-Based COVID Treatment. [back]
[24] McCullough, P.A.; Alexander, P.E.; Armstrong, R.; Arvinte, C.; Bain, A.F.; Bartlett, R.P.; Berkowitz, R.L.; Berry, A.C.; Borody, T.J.; Brewer, J.H.; Brufsky, A.M.; Clarke, T.; Derwand, R.; Eck, A.; Eck, J.; Eisner, R.A.; Fareed, G.C.; Farella, A.; Fonseca, S.N.S.; Geyer, C.E.; Gonnering, R.S.; Graves, K.E.; Gross, K.B.V.; Hazan, S.; Held, K.S.; Hight, H.T.; Immanuel, S.; Jacobs, M.M.; Ladapo, J.A.; Lee, L.H.; Littell, J.; Lozano, I.; Mangat, H.S.; Marble, B.; McKinnon, J.E.; Merritt, L.D.; Orient, J.M.; Oskoui, R.; Pompan, D.C.; Procter, B.C.; Prodromos, C.; Rajter, J.C.; Rajter, J.; Ram, C.V.S.; Rios, S.S.; Risch, H.A.; Robb, M.J.A.; Rutherford, M.; Scholz, M.; Singleton, M.M.; Tumlin, J.A.; Tyson, B.M.; Urso, R.G.; Victory, K.; Vliet, E.L.; Wax, C.M.; Wolkoff, A.G.; Wooll, V. and Zelenko, V. (2020) Multifaceted highly targeted sequential multidrug treatment of early ambulatory high-risk SARS-CoV-2 infection (COVID-19). Reviews in cardiovascular medicine 21:517–530. [back][back]
[25] Procter, {.B.C.; {APRN}, {.C.R.{.; {PA}-C, {.V.P.; {PA}-C, {.E.S.; {PA}-C, {.C.H. and McCullough, {.{.P.A. (2021) Early Ambulatory Multidrug Therapy Reduces Hospitalization and Death in High-Risk Patients with SARS-CoV-2 (COVID-19). International journal of innovative research in medical science 6:219–221. [back]
[26] McCullough, P.A.; Kelly, R.J.; Ruocco, G.; Lerma, E.; Tumlin, J.; Wheelan, K.R.; Katz, N.; Lepor, N.E.; Vijay, K.; Carter, H.; Singh, B.; McCullough, S.P.; Bhambi, B.K.; Palazzuoli, A.; De Ferrari, G.M.; Milligan, G.P.; Safder, T.; Tecson, K.M.; Wang, D.D.; McKinnon, J.E.; O’Neill, W.W.; Zervos, M. and Risch, H.A. (2021) Pathophysiological Basis and Rationale for Early Outpatient Treatment of SARS-CoV-2 (COVID-19) Infection. Am. J. Med. 134:16–22. [back]
[27] Anonymous, (2020) Real-time database and meta analysis of 588 COVID-19 studies. [back]
[28] Hirschhorn, J.S. (2021) COVID scandal: Feds ignored 2016 law requiring use of real world evidence.[back]
[29] Anonymous, (1998) Emergency Use of an Investigational Drug or Biologic: Guidance for Institutional Review Boards and Clinical Investigators. [back] [back]
[30] Anonymous, (2021) EMA assessment report: Comirnaty. [back]
[31] Anonymous, (2020) FDA briefing document: Pfizer-BioNTech COVID-19 Vaccine. [back]
[32] Giurgea, L.T. and Memoli, M.J. (2020) Navigating the Quagmire: Comparison and Interpretation of COVID-19 Vaccine Phase 1/2 Clinical Trials. Vaccines 8:746. [back][back]
[33] Bhakdi, S.; Chiesa, M.; Frost, S.; Griesz-Brisson, M.; Haditsch, M.; Hockertz, S.; Johnson, L.; Kämmerer, U.; Palmer, M.; Reiss, K.; Sönnichsen, A.; Wodarg, W. and Yeadon, M. (2021) Urgent Open Letter from Doctors and Scientists to the European Medicines Agency regarding COVID-19 Vaccine Safety Concerns. [back]
[34] Bhakdi, S. (2021) Rebuttal letter to European Medicines Agency from Doctors for Covid Ethics, April 1, 2021. [back]
[35] Ulm, J.W. (2020) Rapid response to: Will covid-19 vaccines save lives? Current trials aren’t designed to tell us. [back][back]
[36] Reimann, N. (2021) Covid Spiking In Over A Dozen States — Most With High Vaccination Rates.[back]
[37] Meredith, S. (2021) Chile has one of the world’s best vaccination rates. Covid is surging there anyway.[back]
[38] Bhuyan, A. (2021) Covid-19: India sees new spike in cases despite vaccine rollout. BMJ 372:n854. [back]
[39] Morrissey, K. (2021) Open letter to Dr. Karina Butler. [back]
[40] Anonymous, (2021) Open Letter from the UK Medical Freedom Alliance: Urgent warning re Covid-19 vaccine-related deaths in the elderly and Care Homes. [back]
[41] Furer, V.; Zisman, D.; Kibari, A.; Rimar, D.; Paran, Y. and Elkayam, O. (2021) Herpes zoster following BNT162b2 mRNA Covid-19 vaccination in patients with autoimmune inflammatory rheumatic diseases: a case series. Rheumatology -:x-x. [back]
[42] Anonymous, (2021) Covid-19 vaccines: ethical, legal and practical considerations. [back]
[43] Tseng, C.; Sbrana, E.; Iwata-Yoshikawa, N.; Newman, P.C.; Garron, T.; Atmar, R.L.; Peters, C.J. and Couch, R.B. (2012) Immunization with SARS coronavirus vaccines leads to pulmonary immunopathology on challenge with the SARS virus. PLoS One 7:e35421. [back]
[44] Bolles, M.; Deming, D.; Long, K.; Agnihothram, S.; Whitmore, A.; Ferris, M.; Funkhouser, W.; Gralinski, L.; Totura, A.; Heise, M. and Baric, R.S. (2011) A double-inactivated severe acute respiratory syndrome coronavirus vaccine provides incomplete protection in mice and induces increased eosinophilic proinflammatory pulmonary response upon challenge. J. Virol. 85:12201–15. [back]
[45] Weingartl, H.; Czub, M.; Czub, S.; Neufeld, J.; Marszal, P.; Gren, J.; Smith, G.; Jones, S.; Proulx, R.; Deschambault, Y.; Grudeski, E.; Andonov, A.; He, R.; Li, Y.; Copps, J.; Grolla, A.; Dick, D.; Berry, J.; Ganske, S.; Manning, L. and Cao, J. (2004) Immunization with modified vaccinia virus Ankara-based recombinant vaccine against severe acute respiratory syndrome is associated with enhanced hepatitis in ferrets. J. Virol. 78:12672–6. [back]
[46]Czub, M.; Weingartl, H.; Czub, S.; He, R. and Cao, J. (2005) Evaluation of modified vaccinia virus Ankara based recombinant SARS vaccine in ferrets. Vaccine 23:2273–9 [back]
[47]Tinari, S. (2021) The EMA covid-19 data leak, and what it tells us about mRNA instability. BMJ 372:n627 [back]
[48] Anonymous, (2021) Interview with Dr. Vanessa Schmidt-Krüger, Hearing #37 of German Corona Extra-Parliamentary Inquiry Committee 30 January, 2021. [back]
Why I’m Removing All Articles Related to Vitamins D, C, Zinc and COVID-19

By Dr. Joseph Mercola | May 4, 2021
Over the past year, I’ve been researching and writing as much as I can to help you take control of your health, as fearmongering media and corrupt politicians have destroyed lives and livelihoods to establish global control of the world’s population, using the COVID-19 pandemic as their justification.
I’ve also kept you informed about billionaire-backed front groups like the Center for Science in the Public Interest (CSPI), a partner of Bill Gates’ Alliance for Science, both of whom have led campaigns aimed at destroying my reputation and censoring the information I share.
Other attackers include HealthGuard, which ranks health sites based on a certain set of “credibility criteria.” It has sought to discredit my website by ensuring warnings appear whenever you search for my articles or enter my website in an internet browser.
Well-Organized Attack Partnerships Have Formed
HealthGuard, a niche service of NewsGuard, is funded by the pharma-funded public relations company Publicis Groupe. Publicis, in turn, is a partner of the World Economic Forum, which is leading the call for a “Great Reset” of the global economy and a complete overhaul of our way of life.
HealthGuard is also partnered with Gates’ Microsoft company, and drug advertising websites like WebMD and Medscape, as well as the Center for Countering Digital Hate (CCDH) — the progressive cancel-culture leader with extensive ties to government and global think tanks that recently labeled people questioning the COVID-19 vaccine as a national security threat.
The CCDH has published a hit list naming me as one of the top 12 individuals responsible for 65% of vaccine “disinformation” on social media, and who therefore must be deplatformed and silenced for the public good. In a March 24, 2021, letter1 to the CEO’s of Twitter and Facebook, 12 state attorneys general called for the removal of our accounts from these platforms, based on the CCDH’s report.
Two of those state attorneys general also published an April 8, 2021, op-ed2 in The Washington Post, calling on Facebook and Twitter to ban the “anti-vaxxers” identified by the CCDH. The lack of acceptance of novel gene therapy technology, they claim, is all because a small group of individuals with a social media presence — myself included — are successfully misleading the public with lies about nonexistent vaccine risks.
“The solution is not complicated. It’s time for Facebook CEO Mark Zuckerberg and Twitter CEO Jack Dorsey to turn off this toxic tap and completely remove the small handful of individuals spreading this fraudulent misinformation,” they wrote.3
Pharma-funded politicians and pharma-captured health agencies have also relentlessly attacked me and pressured tech monopolies to censor and deplatform me, removing my ability to express my opinions and speak freely over the past year.
The CCDH also somehow has been allowed to publish4 in the journal Nature Medicine, calling for the “dismantling” of the “anti-vaccine” industry. In the article, CCDH founder Imran Ahmed repeats the lie that he “attended and recorded a private, three-day meeting of the world’s most prominent anti-vaxxers,” when, in fact, what he’s referring to was a public online conference open to an international audience, all of whom had access to the recordings as part of their attendance fee.
The CCDH is also partnered with another obscure group called Anti-Vax Watch. The picture below is from an Anti-Vax Watch demonstration outside the halls of Congress. Ironically, while the CCDH claims to be anti-extremism, you’d be hard-pressed to find a clearer example of actual extremism than this bizarre duo.5
Gates-Funded Doctor Demands Terrorist Experts to Attack Me
Most recently, Dr. Peter Hotez, president of the Sabin Vaccine Institute,6 which has received tens of millions of dollars from the Bill & Melinda Gates Foundation,7,8,9 — with funds from the foundation most recently being used to create a report called “Meeting the Challenge of Vaccine Hesitancy,”10,11 — also cited the CCDH in a Nature article in which he calls for cyberwarfare experts to be enlisted in the war against vaccine safety advocates and people who are “vaccine hesitant.” He writes:12
“Accurate, targeted counter-messaging from the global health community is important but insufficient, as is public pressure on social-media companies. The United Nations and the highest levels of government must take direct, even confrontational, approaches with Russia, and move to dismantle anti-vaccine groups in the United States.
Efforts must expand into the realm of cyber security, law enforcement, public education and international relations. A high-level inter-agency task force reporting to the UN secretary-general could assess the full impact of anti-vaccine aggression, and propose tough, balanced measures.
The task force should include experts who have tackled complex global threats such as terrorism, cyber attacks and nuclear armament, because anti-science is now approaching similar levels of peril. It is becoming increasingly clear that advancing immunization requires a counteroffensive.”
Why is Hotez calling for the use of warfare tactics on American citizens that have done nothing illegal? In my case, could it be because I’ve written about the theory that SARS-CoV-2 is an engineered virus, created through gain-of-function research, and that its release was anticipated by global elites, as evidenced in Event 201?
It may be. At least those are some of my alleged “sins,” detailed on page 10 of the CCDH report, “Disinformation Dozen: The Sequel.”13 Coincidentally enough, the Nature journal has helped cover up gain-of-function research conducted at the Wuhan Institute of Virology, publishing a shoddy zoonotic origins study relied upon by mainstream media and others, which was riddled with problems.14,15
So, it’s not misinformation they are afraid of. They’re afraid of the truth getting out. They’re all trying to cover for the Chinese military and the dangerous mad scientists conducting gain-of-function work.
You may have noticed our website was recently unavailable; this was due to direct cyber-attacks launched against us. We have several layers of protective mechanisms to secure the website as we’ve anticipated such attacks from malevolent organizations.
What This Means for You
Through these progressively increasing stringent measures, I have refused to succumb to these governmental and pharmaceutical thugs and their relentless attacks. I have been confident and willing to defend myself in the court of law, as I’ve had everything reviewed by some of the best attorneys in the country.
Unfortunately, threats have now become very personal and have intensified to the point I can no longer preserve much of the information and research I’ve provided to you thus far. These threats are not legal in nature, and I have limited ability to defend myself against them. If you can imagine what billionaires and their front groups are capable of, I can assure you they have been creative in deploying their assets to have this content removed.
Sadly, I must also remove my peer reviewed published study16 on the “Evidence Regarding Vitamin D and Risk of COVID-19 and Its Severity.” It will, however, remain in the highly-respected journal Nutrients’ website, where you can still access it for free.
The MATH+ hospital treatment protocol for COVID-19 and the iMASK+ prevention and early outpatient COVID-19 protocol — both of which are based on the use of vitamins C, D, quercetin, zinc and melatonin — are available on the Front Line COVID-19 Critical Care Alliance’s website. I suggest you bookmark these resources for future reference.
It is with a heavy heart that I purge my website of valuable information. As noted by Dr. Peter McCullough during a recent Texas state Senate Health and Human Services Committee hearing, data shows early treatment could have prevented up to 85% (425,000) of COVID-19 deaths.17 Yet early treatments were all heavily censored and suppressed.
McCullough, in addition to being a cardiologist and professor of medicine at the Texas A&M University Health Sciences Center, also has the distinction of having published the most papers of any person in the history of his field, and being an editor of two major medical journals. Despite that, his video, in which he went through a paper he’d published detailing effective early treatments, was summarily banned by YouTube in 2020.
“No wonder we have had 45,000 deaths in Texas. The average person in Texas thinks there’s no treatment!” McCullough told the senate panel.18 Indeed, people are in dire need of more information detailing how they can protect their health, not less. But there’s only so much I can do to protect myself against current attack strategies.
They’ve moved past censorship. Just what do you call people who advocate counteroffensive attacks by terrorism and cyberwarfare experts? You’d think we could have a debate and be protected under free speech but, no, we’re not allowed. These lunatics are dangerously unhinged.
The U.S. federal government is going along with the global Great Reset plan (promoted as “building back better”), but this plan won’t build anything but a technological prison. What we need is a massive campaign to preserve civil rights, and vote out the pawns who are destroying our freedom while concentrating wealth and power.
Sources and References
- 1 AG Letter to Tech CEOs March 24, 2021 (PDF)
- 2, 3 Washington Post April 8, 2021
- 4 Nature March 15, 2021
- 5 Twitter Mercola March 25, 2021
- 6 WHO Peter Hotez
- 7 PND July 1, 2011
- 8 Bill & Melinda Gates Foundation
- 9 Sabin Vaccine Institute February 11, 2019
- 10 Sabin Vaccine Institute June 2, 2020
- 11 Sabin Vaccine Institute May 28, 2020
- 12 Nature April 27, 2021
- 13 CCHD Disinformation Dozen: The Sequel
- 14 Monali Rahalkar Criticism for the Addendum: A pneumonia outbreak associated with a novel coronavirus of probable bat origin (Zhou et al 2020)
- 15 Monali Rahalkar Critique to the Addendum (Zhou et al 2020) and other contradictions in reporting the facts about RaTG13 and its history
- 16 Nutrients October 31, 2020;12, 3361; doi:10.3390/nu12113361
- 17, 18 Lifesitenews.com April 8, 2021
Why Is There No Correlation Between Masks, Lockdowns, and Covid Suppression?
In the past couple of months, our esteemed public health experts have had a rough go of defending the supposedly settled science behind lockdowns and mask mandates.
White House covid-19 advisor Andy Slavitt was first on the chopping block back in mid-February, when he was reduced to parroting empty platitudes about social distancing after failing to explain why a completely open Florida had numbers no worse than a strictly locked-down California. Then comes media darling Dr. Anthony Fauci, who has had a particularly embarrassing series of public appearances of late. During a recent MSNBC interview Fauci expressed confusion and wasn’t “quite sure” as to why Texas was experiencing falling cases and deaths an entire month after lifting its mask mandates and capacity restrictions. Moreover, during a hearing with Representative Jim Jordan, Fauci completely dodged Jordan’s question of why Texas has lower case rates than some of the most notable lockdown states. Fauci, refusing to answer the question, simply responded that having a lockdown is not the same thing as obeying lockdowns. Fauci was correct here, but he indirectly claimed that citizens of New York and New Jersey, two notorious lockdown states, were complying less with mitigation measures than a state that had, and still has, practically none. A quick check of Google’s covid-19 mobility reports lays this counterintuitive claim to rest.
The American Media’s Agenda
When governments and media outlets around the world have successfully captured audiences by stoking fear of covid-19, the data that should so easily assuage this fear become irrelevant, and interviews like those mentioned above are simply brushed aside in favor of a fear-born allegiance to the “morally superior” government-mandated lockdowns, curfews, mask mandates, and more. This “scared straight” approach, as Bill Maher correctly described it, is the state’s bludgeon of compliance.
As far as scaring citizens straight, Project Veritas has released footage showing CNN employees explaining how the network plays up the covid-19 death toll to drive numbers. Especially disgraceful was CNN technical director Charlie Chester’s admission that the network doesn’t like to report recovery rates because “[t]hat’s not scary…. If it bleeds it leads.”
CNN isn’t alone in the fearmongering business. Thanks to the surplus of United States media outlets willing to churn up a disproportionate amount of negative covid-19 headlines—roughly 90 percent of covid-19 news in the United States is negative compared to 51 percent internationally—is it any surprise that nearly 70 percent of Democrats, 51 percent of Republicans, and almost 50 percent of independents think the chances of being hospitalized with covid-19 range anywhere from 20 percent to over 50 percent?
Where’s the Correlation?
Government- and media-induced panic have blinded us to the data, which for the past thirteen months have consistently shown zero correlation between the timing, strength, and duration of mitigation measures and covid-19 incidence. Nowhere could this lack of correlation be more prevalent than among lockdowns and mask usage.
Leaving aside the disastrous and deadly consequences of government lockdowns—see here, here, and here—the evidence for lockdowns’ ability to mitigate covid-19 mortality remains scant.
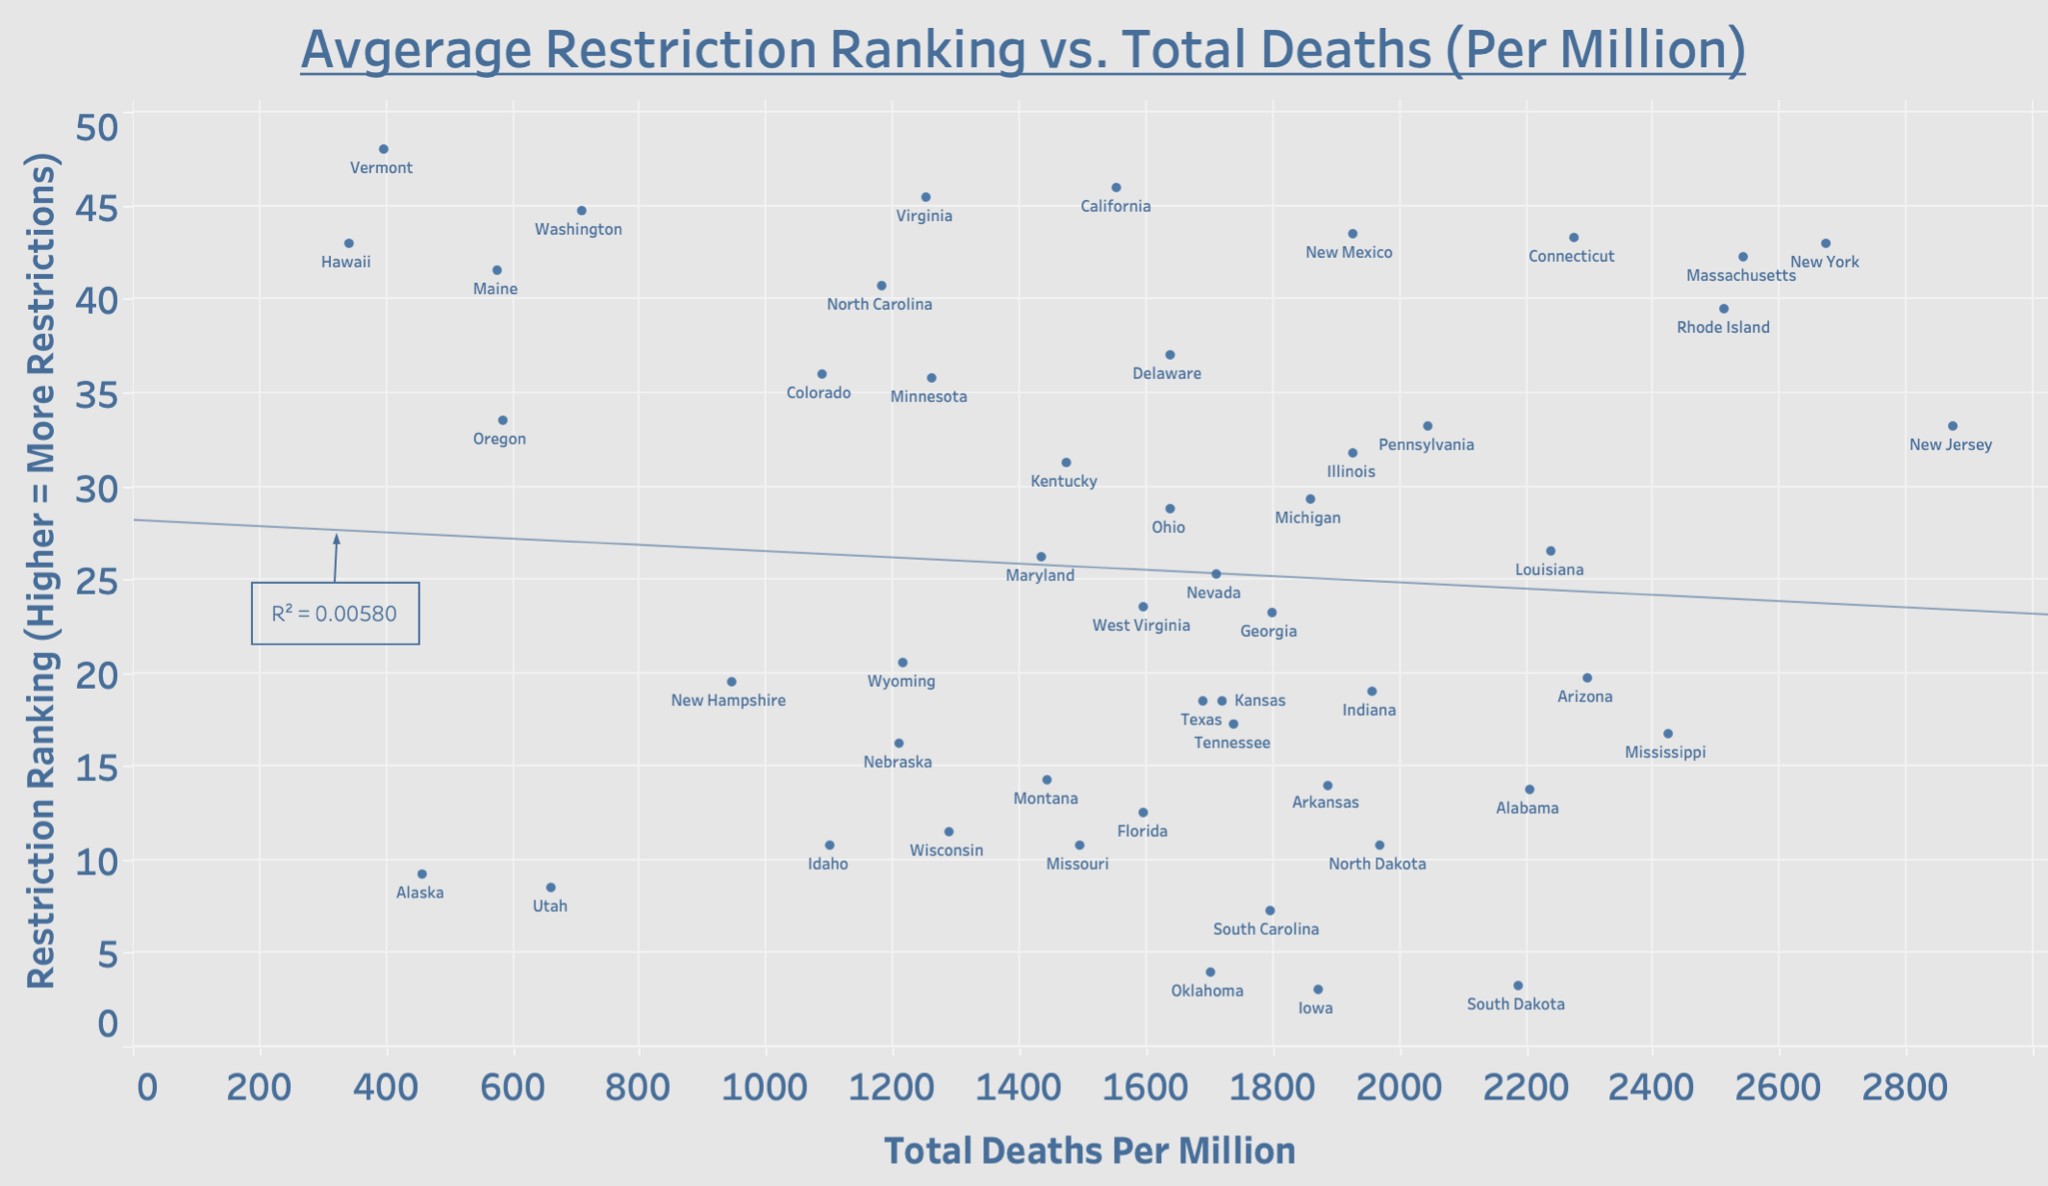
Looking at the United States, we can address the widely believed notion that states with more intense lockdowns will see fewer covid-19 deaths by plotting each state’s average restriction ranking over the past thirteen months against the total number of covid-19 deaths for each state. To get the average ranking, the author averaged data from Oxford University’s Blavatnik School of Government—this source ranked each state by the average time spent at a stringency index measure greater than sixty up until mid-December 2020—and WalletHub, which also ranked each state by stringency using a weighted average of various measures from January 2021 onward. Now, if the past year’s worth of sanctimonious lectures from public health experts have any scientific weight behind them, we should see a very strong negative correlation between the intensity of states’ restrictions and total covid-19 deaths.
Source: Data on deaths (as of Apr. 28, 2021) from the NYTimes Covid-19 Data Bot. Data on restriction rankings from the NYTimes Covid-19 Data Bot (through December 2020); Adam McCann, “States with the Fewest Coronavirus Restrictions,” WalletHub, Apr. 6, 2021 (since January 2021); and Laura Hallas, Ariq Hatibie, Saptarshi Majumdar, Monika Pyarali, and Thomas Hale, “Variation in US States’ Responses to COVID-19” (Blavatnik School of Government Working Paper No. BSG-WP-2020/034, December 2020).
Contrary to what the public health experts have been telling us for more than a year, there is no correlation between the strength of a state’s lockdown measures and total covid-19 deaths. In fact, notorious lockdown states such as New York and New Jersey have some of the worst mortality numbers to date. To blame noncompliance for these poor numbers is ridiculous on its face considering that states with no restrictions, such as Texas and Florida, have far fewer deaths than New York and New Jersey. In fact, you’ll find that every state that has either removed its mask mandate or all covid-19 restrictions entirely is outperforming New York and New Jersey in terms of deaths.
The same lack of correlation can be seen when comparing average lockdown stringency with the total number of patients hospitalized who have suspected or confirmed covid-19. As a point of clarification, the author summed the current number of patients hospitalized each day to arrive at the total number of patients hospitalized. This will result in slightly inflated total numbers, since patients may spend more than one day in the hospital, but having applied the same aggregation method across all states, the total hospitalization metric still provides an accurate assessment of covid-19 hospitalizations in each state.

Source: Data on hospitalizations (as of Apr. 24, 2021) from the US Department of Health and Human Services. Data on restriction rankings from the NYTimes Covid-19 Data Bot (through December 2020); Adam McCann, “States with the Fewest Coronavirus Restrictions,” WalletHub, Apr. 6, 2021 (since January 2021); and Laura Hallas, Ariq Hatibie, Saptarshi Majumdar, Monika Pyarali, and Thomas Hale, “Variation in US States’ Responses to COVID-19” (Blavatnik School of Government Working Paper No. BSG-WP-2020/034, December 2020).
Internationally speaking, the data continue to expose lockdowns as the single greatest public health failure in human history. Plotting lockdown stringency against total covid-19 death toll reveals, yet again, zero correlation between the two variables.

Source: Data on deaths (as of Apr. 28, 2021) and lockdown stringency (as of Apr. 28, 2021) from Our World in Data.
In light of a year’s worth of data showing wildly different mortality and hospitalization outcomes for fifty states with fifty very different lockdown stringencies, as well as drastically different mortality outcomes for 166 countries with 166 different lockdown stringencies, one can only marvel that such a deadly and ineffective policy can be recommended by public health experts.
If the lockdowns failed to mitigate the spread of covid-19 in the United States just as in dozens of countries around the world—remember, the lockdowns fail without even taking their costs into account—it’s possible that mask usage is the missing piece of the mitigation puzzle.
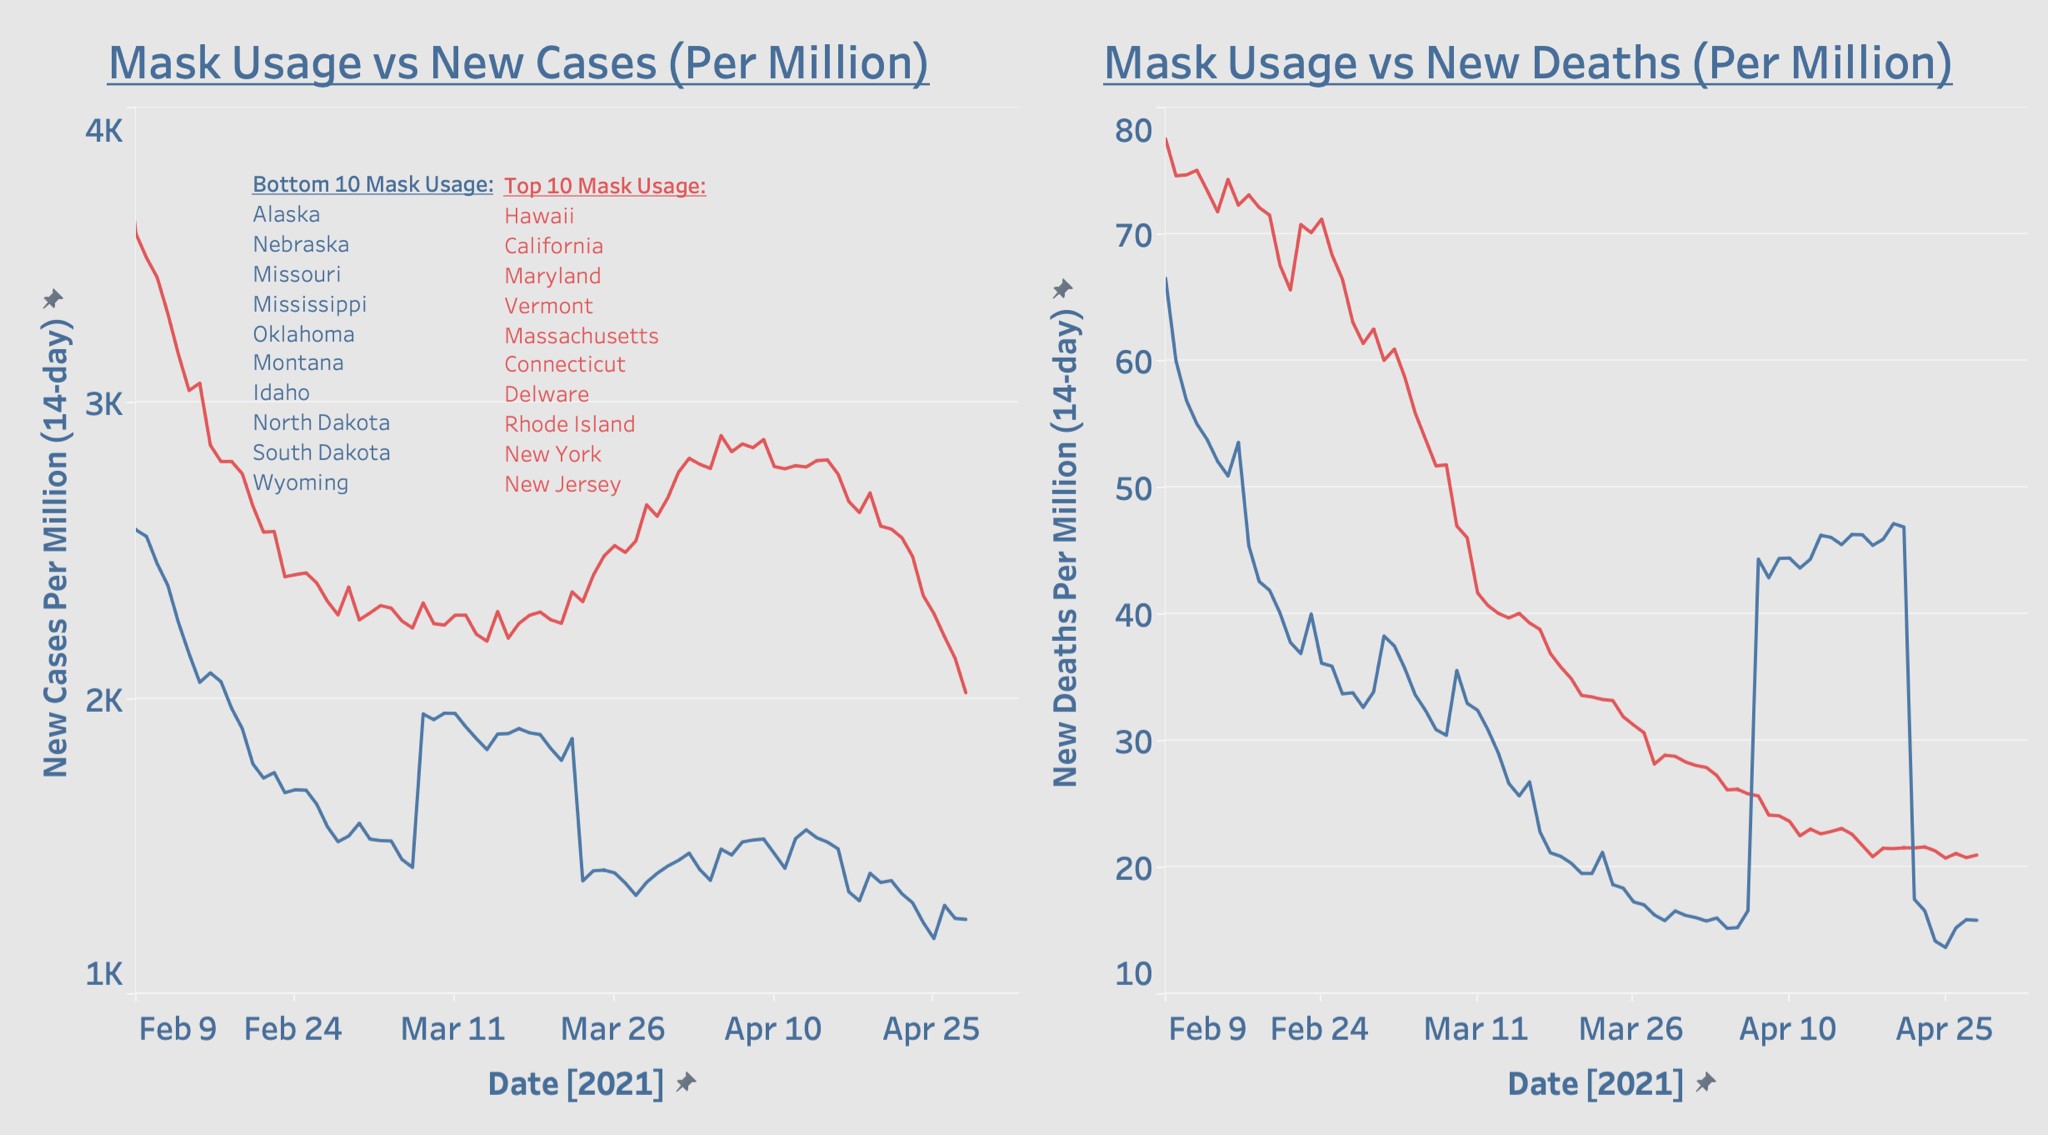
It wouldn’t be fair to the reader to post quite literally hundreds of charts that show the exact opposite outcomes the media would have one expect after regions remove or institute mask mandates—Ian Miller has done more work in this area than anybody else. It also wouldn’t be fair to claim that mask mandates and mask usage are synonymous. However, based on reactions to states lifting their mask mandates, I don’t think any proponent of mask wearing would seriously expect the same level of mask usage should mandates be lifted. Nevertheless, the claim that mask usage negatively correlates with cases and deaths is easily refuted with a quick look at the data. Given the data available, we’ll again only be looking at the fifty states.

Source: Data for cases and deaths (as of Apr. 28, 2021) from the NYTimes Covid-19 Data Bot. Mask usage data from the Delphi Group’s COVIDcast.
Even though the trend lines travel in the exact opposite direction of what our public health experts would have us expect, the correlations are statistically meaningless. Note that the above chart only covers the 2.5-month period starting February 9, 2021, which is when COVIDcast began reporting mask usage numbers for each state. Therefore, the author included only the cases and deaths that occurred during this 2.5-month period. Despite this truncated time period, 2.5 months should have been more than enough to have exposed any sort of meaningful correlation between mask usage and both cases and deaths.
It is worth noting that Rhode Island and New York, each with some of the highest mask usage rates and lockdown stringencies in the country, are leading the pack with some of the largest case increases since early February. What is more, in the 2.5 months since early February the ten states with the highest rate of mask usage have been doing worse in both cases and deaths than the ten states with the lowest rate of mask usage.
Source: Data for cases and deaths (as of Apr. 28, 2021) from the NYTimes Covid-19 Data Bot. Mask usage data from the Delphi Group’s COVIDcast.
Remember, we aren’t measuring the amount of rules that simply say you have to wear a mask. What’s being measured is the percentage of people actually wearing masks in public in each state. It’s quite difficult to look at the trends depicted above and make the case not only for continuing mask mandates, but wearing masks at all.
Some may have an issue with the fact that the trends above only cover the couple of months since February. Let’s assume, for the sake of a more complete picture, that mask usage trends were consistent for each state since the start of the pandemic. We can also expand our filter to the top and bottom fifteen states to account for some states’ movement in and out of the top and bottom ten states.

Source: Data for cases and deaths (as of Apr. 28, 2021) from the NYTimes Covid-19 Data Bot. Mask usage data from the Delphi Group’s COVIDcast.
In terms of cases, from April to around mid-June, states with the lowest rates of mask usage were outperforming states with the highest rates of mask usage. This trend reversed from mid-June through mid-January and then reversed again in favor of states with the lowest rate of mask usage.
In terms of deaths, states with the lowest rates of mask usage outperformed states with the highest rates of mask usage from April until mid-July. From mid-July to mid-February, death trends were more favorable to states with the highest rates of mask usage, but after mid-February death trends again became more favorable to states with the lowest rates of mask usage. Again, if we are assuming fairly consistent rates of mask usage across the entire duration of the pandemic while also assuming that the science behind masks is truly settled, it’s quite difficult to explain away any period of time in which states with the lowest rates of mask usage were outperforming states with the highest rates.
The supposedly settled science behind both lockdowns and mask mandates has always been in serious trouble but is even more so now. Completely leaving aside the incredible death toll of the lockdowns, their numerous social and psychological costs, the totalitarian denial of our most basic liberties, and the decimation of tens of thousands of small businesses, they would still be a miserable failure by nearly every covid-19 metric we have available. Though, to be fair, the lockdowns did make our cities quieter. But aside from that, the data continue to deny that either lockdowns or mask mandates are effective tools for mitigating the spread of covid-19.
This Biden Proposal Could Make the US a “Digital Dictatorship”

BY WHITNEY WEBB |
UNLIMITED HANGOUT| MAY 5, 2021
Last Wednesday, President Biden was widely praised in mainstream and health-care–focused media for his call to create a “new biomedical research agency” modeled after the US military’s “high-risk, high-reward” Defense Advanced Research Projects Agency, or DARPA. As touted by the president, the agency would seek to develop “innovative” and “breakthrough” treatments for cancer, Alzheimer’s disease, and diabetes, with a call to “end cancer as we know it.”
Far from “ending cancer” in the way most Americans might envision it, the proposed agency would merge “national security” with “health security” in such as way as to use both physical and mental health “warning signs” to prevent outbreaks of disease or violence before they occur. Such a system is a recipe for a technocratic “pre-crime” organization with the potential to criminalize both mental and physical illness as well as “wrongthink.”
The Biden administration has asked Congress for $6.5 billion to fund the agency, which would be largely guided by Biden’s recently confirmed top science adviser, Eric Lander. Lander, formerly the head of the Silicon Valley–dominated Broad Institute, has been controversial for his ties to eugenicist and child sex trafficker Jeffrey Epstein and his relatively recent praise for James Watson, an overtly racist eugenicist. Despite that, Lander is set to be confirmed by the Senate and Congress and is reportedly significantly enthusiastic about the proposed new “health DARPA.”
This new agency, set to be called ARPA-H or HARPA, would be housed within the National Institutes of Health (NIH) and would raise the NIH budget to over $51 billion. Unlike other agencies at NIH, ARPA-H would differ in that the projects it funds would not be peer reviewed prior to approval; instead hand-picked program managers would make all funding decisions. Funding would also take the form of milestone-driven payments instead of the more traditional multiyear grants.
ARPA-H will likely heavily fund and promote mRNA vaccines as one of the “breakthroughs” that will cure cancer. Some of the mRNA vaccine manufacturers that have produced some of the most widely used COVID-19 vaccines, such as the Pfizer/BioNTech vaccine, stated just last month that “cancer is the next problem to tackle with mRNA tech” post-COVID. BioNTech has been developing mRNA gene therapies for cancer for years and is collaborating with the Bill & Melinda Gates Foundation to create mRNA-based treatments for tuberculosis and HIV.
Other “innovative” technologies that will be a focus of this agency are less well known to the public and arguably more concerning.
The Long Road to ARPA-H
ARPA-H is not a new and exclusive Biden administration idea; there was a previous attempt to create a “health DARPA” during the Trump administration in late 2019. Biden began to promote the idea during his presidential campaign as early as June 2019, albeit using a very different justification for the agency than what had been pitched by its advocates to Trump. In 2019, the same foundation and individuals currently backing Biden’s ARPA-H had urged then president Trump to create “HARPA,” not for the main purpose of researching treatments for cancer and Alzheimer’s, but to stop mass shootings before they happen through the monitoring of Americans for “neuropsychiatric” warning signs.
For the last few years, one man has been the driving force behind HARPA—former vice chair of General Electric and former president of NBCUniversal, Robert Wright. Through the Suzanne Wright Foundation (named for his late wife), Wright has spent years lobbying for an agency that “would develop biomedical capabilities—detection tools, treatments, medical devices, cures, etc.—for the millions of Americans who are not benefitting from the current system.” While he, like Biden, has cloaked the agency’s actual purpose by claiming it will be mainly focused on treating cancer, Wright’s 2019 proposal to his personal friend Donald Trump revealed its underlying ambitions.
As first proposed by Wright in 2019, the flagship program of HARPA would be SAFE HOME, short for Stopping Aberrant Fatal Events by Helping Overcome Mental Extremes. SAFE HOME would suck up masses of private data from “Apple Watches, Fitbits, Amazon Echo, and Google Home” and other consumer electronic devices, as well as information from health-care providers to determine if an individual might be likely to commit a crime. The data would be analyzed by artificial intelligence (AI) algorithms “for early diagnosis of neuropsychiatric violence.”
The Department of Justice’s pre-crime approach known as DEEP was activated just months before Trump left office; it was also justified as a way to “stop mass shootings before they happen.” Soon after Biden’s inauguration, the new administration began using information from social media to make pre-crime arrests as part of its approach toward combatting “domestic terror.” Given the history of Silicon Valley companies collaborating with the government on matters of warrantless surveillance, it appears that aspects of SAFE HOME may already be covertly active under Biden, only waiting for the formalization of ARPA-H/HARPA to be legitimized as public policy.
The national-security applications of Robert Wright’s HARPA are also illustrated by the man who was its lead scientific adviser—former head of DARPA’s Biological Technologies Office Geoffrey Ling. Not only is Ling the main scientific adviser of HARPA, but the original proposal by Wright would have Ling both personally design HARPA and lead it once it was established. Ling’s work at DARPA can be summarized by BTO’s stated mission, which is to work toward merging “biology, engineering, and computer science to harness the power of natural systems for national security.” BTO-favored technologies are also poised to be the mainstays of HARPA, which plans to specifically use “advancements in biotechnology, supercomputing, big data, and artificial intelligence” to accomplish its goals.
The direct DARPA connection to HARPA underscores that the agenda behind this coming agency dates back to the failed Bio-Surveillance project of DARPA’s Total Information Awareness program, which was launched after the events of September 11, 2001. TIA’s Bio-Surveillance project sought to develop the “necessary information technologies and resulting prototype capable of detecting the covert release of a biological pathogen automatically, and significantly earlier than traditional approaches,” accomplishing this “by monitoring non-traditional data sources” including “pre-diagnostic medical data” and “behavioral indicators.”
While nominally focused on “bioterrorist attacks,” TIA’s Bio-Surveillance project also sought to acquire early detection capabilities for “normal” disease outbreaks. Bio-Surveillance and related DARPA projects at the time, such as LifeLog, sought to harvest data through the mass use of some sort of wearable or handheld technology. These DARPA programs were ultimately shut down due to the controversy over claims they would be used to profile domestic dissidents and eliminate privacy for all Americans in the US.
That DARPA’s past total surveillance dragnet is coming back to life under a supposedly separate health-focused agency, and one that emulates its organizational model no less, confirms that many TIA-related programs were merely distanced from the Department of Defense when officially shut down. By separating the military from the public image of such technologies and programs, it made them more palatable to the masses, despite the military remaining heavily involved behind the scenes. As Unlimited Hangout has recently reported, major aspects of TIA were merely privatized, giving rise to companies such as Facebook and Palantir, which resulted in such DARPA projects being widely used and accepted. Now, under the guise of the proposed ARPA-H, DARPA’s original TIA would essentially be making a comeback for all intents and purposes as its own spin-off.
Silicon Valley, the Military and the Wearable “Revolution”
This most recent effort to create ARPA-H/HARPA combines well with the coordinated push of Silicon Valley companies into the field of health care, specifically Silicon Valley companies that double as contractors to US intelligence and/or the military (e.g., Microsoft, Google, and Amazon). During the COVID-19 crisis, this trend toward Silicon Valley dominance of the health-care sector has accelerated considerably due to a top-down push toward digitalization with telemedicine, remote monitoring, and the like.
One interesting example is Amazon, which launched a wearable last year that purports to not only use biometrics to monitor people’s physical health and fitness but to track their emotional state as well. The previous year, Amazon acquired the online pharmacy PillPack, and it is not hard to imagine a scenario in which data from Amazon’s Halo wellness band is used to offer treatment recommendations that are then supplied by Amazon-owned PillPack.
Companies such as Amazon, Palantir, and Google are set to be intimately involved in ARPA-H’s activities. In particular, Google, which launched numerous health-tech initiatives in 2020, is set to have a major role in this new agency due to its long-standing ties to the Obama administration when Biden was vice president and to President Biden’s top science adviser, Eric Lander.
As mentioned, Lander is poised to play a major role in ARPA-H/HARPA if and when it materializes. Before becoming the top scientist in the country, Lander was president and founding director of the Broad Institute. While advertised as a partnership between MIT and Harvard, the Broad Institute is heavily influenced by Silicon Valley, with two former Google executives on its board, a partner of Silicon Valley venture capital firm Greylock Partners, and the former CEO of IBM, as well as some of its top endowments coming from prominent tech executives.
Former Google CEO Eric Schmidt, who was intimately involved with Obama’s 2012 reelection campaign and who is close to the Democratic Party in general, chairs the Broad Institute as of this April. In March, Schmidt gave the institute $150 million to “connect biology and machine learning for understanding programs of life.” During his time on the Broad Institute board, Schmidt also chaired the National Security Commission on Artificial Intelligence, a group of mostly Silicon Valley, intelligence, and military operatives who have now charted the direction of the US government’s policies on emerging tech and AI. Schmidt was also pitched as potential head of a tech-industry task force by the Biden administration.
Earlier, in January, the Broad Institute announced that its health-research platform, Terra, which was built with Google subsidiary Verily, would partner with Microsoft. As a result, Terra now allows Google and Microsoft to access a vast trove of genomic data that is poured into the platform by academics and research institutions from around the world.
In addition, last September, Google teamed up with the Department of Defense as part of a new AI-driven “predictive health” program that also has links to the US intelligence community. While initially focused on predicting cancer cases, this initiative clearly plans to expand to predicting the onset of other diseases before symptoms appear, including COVID-19. As noted by Unlimited Hangout at the time, one of the ulterior motives for the program, from Google’s perspective, was for Google to gain access to “the largest repository of disease- and cancer-related medical data in the world,” which is held by the Defense Health Agency. Having exclusive access to this data is a huge boon for Google in its effort to develop and expand its growing suite of AI health-care products.
The military is currently being used to pilot COVID-19–related biometric wearables for “returning to work safely.” Last December, it was announced that Hill Air Force Base in Utah would make biometric wearables a mandatory part of the uniform for some squadrons. For example, the airmen of the Air Force’s 649th Munitions Squadron must now wear a smart watch made by Garmin and a smart ring made by Oura as part of their uniform.
According to the Air Force, these devices detect biometric indicators that are then analyzed for 165 different biomarkers by the Defense Threat Reduction Agency/Philips Healthcare AI algorithm that “attempts to recognize an infection or virus around 48 hours before the onset of symptoms.” The development of that algorithm began well before the COVID-19 crisis and is a recent iteration of a series of military research projects that appear to have begun under the 2007 DARPA Predicting Health and Disease (PHD) project.
While of interest to the military, these wearables are primarily intended for mass use—a big step toward the infrastructure needed for the resurrection of a bio-surveillance program to be run by the national-security state. Starting first with the military makes sense from the national-security apparatus’s perspective, as the ability to monitor biometric data, including emotions, has obvious appeal for those managing the recently expanded “insider threat” programs in the military and the Department of Homeland Security.
One indicator of the push for mass use is that the same Oura smart ring being used by the Air Force was also recently utilized by the NBA to prevent COVID-19 outbreaks among basketball players. Prior to COVID-19, it was promoted for consumer use by members of the British Royal family and Twitter CEO Jack Dorsey for improving sleep. As recently as last Monday, Oura’s CEO, Harpeet Rai, said that the entire future of wearable health tech will soon be “proactive rather than reactive” because it will focus on predicting disease based on biometric data obtained from wearables in real time.
Another wearable tied to the military that is creeping into mass use is the BioButton and its predecessor the BioSticker. Produced by the company BioIntelliSense, the sleek new BioButton is advertised as a wearable system that is “a scalable and cost-effective solution for COVID-19 symptom monitoring at school, home and work.” BioIntelliSense received $2.8 million from the Pentagon last December to develop the BioButton and BioSticker wearables for COVID-19.
BioIntelliSense, cofounded and led by former Microsoft HealthVault developer James Mault, now has its wearable sensors being rolled out for widespread use on some college campuses and at some US hospitals. In some of those instances, the company’s wearables are being used to specifically monitor the side effects of the COVID-19 vaccine as opposed to symptoms of COVID-19 itself. BioIntelliSense is currently running a study, partnered with Philips Healthcare and the University of Colorado, on the use of its wearables for early COVID-19 detection, which is entirely funded by the US military.
While the use of these wearables is currently “encouraged but optional” at these pilot locations, could there come a time when they are mandated in a workplace or by a government? It would not be unheard of, as several countries have already required foreign arrivals to be monitored through use of a wearable during a mandatory quarantine period. Saint Lucia is currently using BioButton for this purpose. Singapore, which seeks to be among the first “smart nations” in the world, has given every single one of its residents a wearable called a “TraceTogether token” for its contact-tracing program. Either the wearable token or the TraceTogether smartphone app is mandatory for all workplaces, shopping malls, hotels, schools, health-care facilities, grocery stores, and hair salons. Those without access to a smartphone are expected to use the “free” government-issued wearable token.
The Era of Digital Dictatorships Is Nearly Here
Making mandatory wearables the new normal not just for COVID-19 prevention but for monitoring health in general would institutionalize quarantining people who have no symptoms of an illness but only an opaque algorithm’s determination that vital signs indicate “abnormal” activity.
Given that no AI is 100 percent accurate and that AI is only as good as the data it is trained on, such a system would be guaranteed to make regular errors: the question is how many. One AI algorithm being used to “predict COVID-19 outbreaks” in Israel and some US states is marketed by Diagnostic Robotics; the (likely inflated) accuracy rate the company provides for its product is only 73 percent. That means, by the company’s own admission, their AI is wrong 27 percent of the time. Probably, it is even less accurate, as the 73 percent figure has never been independently verified.
Adoption of these technologies has benefitted from the COVID-19 crisis, as supporters are seizing the opportunity to accelerate their introduction. As a result, their use will soon become ubiquitous if this advancing agenda continues unimpeded.
Though this push for wearables is obvious now, signs of this agenda were visible several years ago. In 2018, for instance, insurer John Hancock announced that it would replace its life insurance offerings with “interactive policies” that involve individuals having their health monitored by commercial health wearables. Prior to that announcement, John Hancock and other insurers such as Aetna, Cigna, and UnitedHealthcare offered various rewards for policyholders who wore a fitness wearable and shared that data with their insurance company.
In another pre-COVID example, the Journal of the American Medical Association published an article in August 2019 that claimed that wearables “encourage healthy behaviors and empower individuals to participate in their health.” The authors of the article, who are affiliated with Harvard, further claimed that “incentivizing use of these devices [wearables] by integrating them in insurance policies” may be an “attractive” policy approach. The use of wearables for policyholders has since been heavily promoted by the insurance industry, both prior to and after COVID-19, and some speculate that health insurers could soon mandate their use in certain cases or as a broader policy.
These biometric “fitness” devices—such as Amazon’s Halo—can monitor more than your physical vital signs, however, as they can also monitor your emotional state. ARPA-H/HARPA’s flagship SAFE HOME program reveals that the ability to monitor thoughts and feelings is an already existing goal of those seeking to establish this new agency.
According to World Economic Forum luminary and historian Yuval Noah Harari, the transition to “digital dictatorships” will have a “big watershed” moment once governments “start monitoring and surveying what is happening inside your body and inside your brain.” He says that the mass adoption of such technology would make human beings “hackable animals,” while those who abstain from having this technology on or in their bodies would become part of a new “useless” class. Harari has also asserted that biometric wearables will someday be used by governments to target individuals who have the “wrong” emotional reactions to government leaders.
Unsurprisingly, one of Harari’s biggest fans, Facebook’s Mark Zuckerberg, has recently led his company into the development of a comprehensive biometric and “neural” wearable based on technology from a “neural interface” start-up that Facebook acquired in 2019. Per Facebook, the wearable “will integrate with AR [augmented reality], VR [virtual reality], and human neural signals” and is set to become commercially available soon. Facebook also notably owns the VR company Oculus Rift, whose founder, Palmer Luckey, now runs the US military AI contractor Anduril.
As recently reported, Facebook was shaped in its early days to be a private-sector replacement for DARPA’s controversial LifeLog program, which sought to both “humanize” AI and build profiles on domestic dissidents and terror suspects. LifeLog was also promoted by DARPA as “supporting medical research and the early detection of an emerging pandemic.”
It appears that current trends and events show that DARPA’s decades-long effort to merge “health security” and “national security” have now advanced further than ever before. This may partially be because Bill Gates, who has wielded significant influence over health policy globally in the last year, is a long-time advocate of fusing health security and national security to thwart both pandemics and “bioterrorists” before they can strike, as can be heard in his 2017 speech delivered at that year’s Munich Security Conference. That same year, Gates also publicly urged the US military to “focus more training on preparing to fight a global pandemic or bioterror attack.”
In the merging of “national security” and “health security,” any decision or mandate promulgated as a public health measure could be justified as necessary for “national security,” much in the same way that the mass abuses and war crimes that occurred during the post-9/11 “war on terror” were similarly justified by “national security” with little to no oversight. Yet, in this case, instead of only losing our civil liberties and control over our external lives, we stand to lose sovereignty over our individual bodies.
The NIH, which would house this new ARPA-H/HARPA, has spent hundreds of millions of dollars experimenting with the use of wearables since 2015, not only for detecting disease symptoms but also for monitoring individuals’ diets and illegal drug consumption. Biden played a key part in that project, known as the Precision Medicine initiative, and separately highlighted the use of wearables in cancer patients as part of the Obama administration’s related Cancer Moonshot program. The third Obama-era health-research project was the NIH’s BRAIN initiative, which was launched, among other things, to “develop tools to record, mark, and manipulate precisely defined neurons in the living brain” that are determined to be linked to an “abnormal” function or a neurological disease. These initiatives took place at a time when Eric Lander was the cochair of Obama’s Council of Advisors on Science and Technology while still leading the Broad Institute. It is hardly a coincidence that Eric Lander is now Biden’s top science adviser, elevated to a new cabinet-level position and set to guide the course of ARPA-H/HARPA.
Thus, Biden’s newly announced agency, if approved by Congress, would integrate those past Obama-era initiatives with Orwellian applications under one roof, but with even less oversight than before. It would also seek to expand and mainstream the uses of these technologies and potentially move toward developing policies that would mandate their use.
If ARPA-H/HARPA is approved by Congress and ultimately established, it will be used to resurrect dangerous and long-standing agendas of the national-security state and its Silicon Valley contractors, creating a “digital dictatorship” that threatens human freedom, human society, and potentially the very definition of what it means to be human.
India’s “COVID outbreak” & the need for scientific integrity – not sensationalism
Reality versus hysteria in latest fear fest
By Colin Todhunter | OffGuardian | May 4, 2021
Western media outlets are currently paying a great deal of attention to India and the apparent impact of COVID-19. The narrative is that the coronavirus is ripping through the country – people are dying, cases are spiralling out of control and hospitals are unable to cope.
There does indeed seem to be a major problem in parts of the country. However, we need to differentiate between the effects of COVID-19 and the impacts of other factors. We must also be very wary of sensationalist media reporting which misrepresents the situation.
For instance, in late April, the New York Post ran a story about the COVID ‘surge’ in India with the headline saying, “footage shows people dead in the streets”. Next to it was an image of a woman lying dead. But the image was actually of a woman lying on the floor from a May 2020 story about a gas leak in Andhra Pradesh.
To try to shed some light on the situation and move beyond panic and media sensationalism, I recently spoke with Yohan Tengra, a political analyst and healthcare specialist based in Mumbai.
Tengra has carried out a good deal of research into COVID-19 and the global response to it. He is the co-author of a new report: ‘How the Unscientific Interpretation of RT-PCR & Rapid Antigen Test Results is Causing Misleading Spikes in Cases & Deaths’.
For India, he says:
We will never know statistically if the infections have really increased. To be certain, we would need data of symptomatic people who have tested positive with either a virus culture test or PCR that uses 24 cycles or less, ideally under 20.”
He adds that India is experiencing mainly asymptomatic cases:
For example, in Mumbai, they declared two days back that of total cases in the city, 85 per cent were asymptomatic. In Bangalore, over 95 per cent of cases were asymptomatic!”
In his report, Tengra offers scientific evidence that strongly indicates asymptomatic transmission is not significant. He asserts that as these cases comprise most of India’s case numbers, we should be questioning the data as well as the PCR tests and the cycles being used to detect the virus instead of accepting the figures at face value.
As in many countries across the globe, Tengra says people in India have been made to fear the virus endlessly. Moreover, they are generally under the impression that they need to intervene early in order to pass through the infection successfully.
He notes:
The medical system itself works to boost the number of positive cases. Even with a negative PCR test, they are using CAT scans and diagnosing people with COVID. These scans are not specific to SARS-CoV-2 at all. I personally know of people who have been asked to be hospitalised by their doctors just based on a positive test (doctors can get a cut of the total bill made when they refer a patient to a hospital). This also happened to a Bollywood celebrity, who was asked to be admitted by his doctors with no symptoms and just a positive PCR.”
Faulty PCR testing and misdiagnosis, says Tengra, combined with people who want to intervene early with the mildest symptoms, have been filling up the beds, preventing access to those who really need them.
Addressing the much-publicised shortage of oxygen, Tengra implies this too is a result of inept policies, with exports of oxygen having increased in recent times, resulting in inadequate back-up supplies when faced with a surge in demand.
According to Tengra, the case fatality rate for COVID-19 in India was over three per cent last year but has now dropped to below 1.5 per cent. The infection fatality rate is even lower, with serosurvey results showing them to be between 0.05 per cent to 0.1 per cent.
The directors of the All India Institute of Medical Science and the India Council of Medical Research have both come out and said that there is not much difference between the first and second wave and that there are many more asymptomatic cases this time than in the so-called ‘first wave’.
Tengra argues that the principle is the same for all infectious agents: they infect people, most can fight it off without even developing symptoms, some develop mild symptoms, a smaller number develop serious symptoms and an even smaller number die.
Although lives can be saved with the right prevention plus treatment strategies, Tengra notes that most of the doctors in India are using ineffective and unsafe drugs. As a result, he claims that mortality rates could increase due to inappropriate treatments.
As has occurred in many other countries, Tengra notes the way that death certificate guidelines are structured in India makes it easy for someone to be labelled as a COVID death just based on a positive PCR test or general symptoms. It is therefore often difficult to say who has died from the virus and who has been misdiagnosed.
And the issue of misdiagnosis should not be brushed aside lightly. In a recent article by long-term resident of India Jo Nash, ‘India’s Current ‘COVID Crisis’ in Context’, it is noted that the focus of the media’s messaging and the source of many of the horrifying scenes of suffering – Delhi – is among the most toxic cities in the world which often leads to the city having to close down due to the widespread effects on respiratory health.
Nash also argues that respiratory diseases like TB and respiratory tract infections such as bronchitis leading to pneumonia are always among the top ten killers in India. These conditions are severely aggravated by air pollution and often require oxygen which can be in short supply during air pollution crises as happens at this time of the year.
As a result, it is reasonable to state that all is not what it might seem to be with regard to media reporting on the current situation.
It is interesting that this ‘second wave’ has correlated with the vaccine rollout (Nash provides official sources to support this claim). Tengra feels this might not be coincidental. He says that the ‘aefi’ (adverse events following immunisation) data vastly underestimates how many vaccine adverse reactions are taking place in the country.
Tengra says that, based on ground surveys and data collected by himself, there is a tremendous number of people who have fallen ill post vaccination, many of them then testing positive for COVID and becoming hospitalised.
The financial incentive for doctors to diagnose people with COVID could also mean many of the people who are ill with other conditions are being placed as COVID patients, while beds are under occupied for people for non-COVID health issues.
Two months ago, there was a lot of vaccine hesitancy in India and many people were not taking the jabs. Tengra notes that the government has had to up the ante in order to get people scared.
He argues:
We are at a crossroads right now in terms of deciding the fate of our country and it will be interesting to see how this plays out.”
Tengra is working with lawyers and other concerned citizens to file legal cases to challenge the idea of asymptomatic transmission and the testing of healthy people. The aim is to also improve the testing in line with evidence-based protocols.
But that is not all:
We will also be challenging the current vaccine rollout, highlighting the issues with trials that have been conducted, adverse events, deaths, vaccine passports and other issues surrounding the subject.”
Tengra is not alone in challenging the mainstream narrative.
A recent article in India’s National Herald newspaper by clinical epidemiologist Professor Dr Amitav Banerjee argues that the current situation in India is not due to the lethality of the virus but by the numbers who are ending up in hospital, which are exposing cracks in India’s public health infrastructure and the inequitable distribution of health services. Even at the best of times, he argues, there is a mismatch of supply and demand. Little wonder, therefore, that we now see an emergency – not squarely due to COVID.
Like Yohan Tengra, Banerjee questions the scientific integrity of the responses to COVID and this includes the rollout of vaccines and the problems which this in itself could bring:
Going all out for mass vaccination with uncertain input on effectiveness is a big gambit. We have a vaccine against tuberculosis for decades which has zero effectiveness in preventing tuberculosis in the Indian population. Moreover, there are concerns that haphazard and incomplete vaccination of the population can trigger mutant strains.”
Referring to an editorial in the British Medical Journal by K. Abbasi (‘Covid-19, Politicisation, Corruption, and Suppression of Science’), Banerjee raises concerns about the suppression of science by politicians and governments and the conflicts of interest of academics, researchers and commercial lobbies.
He says:
In a global disaster, world leaders, their scientific advisers, including career scientists, are under tremendous pressure. They have to give the impression of being in control and may resort to authoritarian ways to camouflage their uncertainties. Such tactics deviate from the scientific approach. The present pandemic is full of such uncertainties and therefore a vicious cycle of repression has set in when the authorities and their advisers are faced with rising case numbers.”
None of what has been presented here is meant to deny the existence or impact of COVID-19. People in India are dying – some from the virus, others ‘with’ the virus but most likely mainly due to their pre-existing underlying conditions, and there are others who are being misdiagnosed.
Although excess mortality figures are currently unavailable, Yohan Tengra notes the average age of those who died in the first wave was 50. This time it is 49.
Professor Banerjee says that there is opacity and obfuscation instead of transparency. He calls for moral courage among scientists in advisory positions to the Indian government: scientific integrity is the need of the hour.
In finishing, let us place COVID and the global media reporting of the situation in India in context by returning to Jo Nash.
Even as the alleged COVID deaths reach their peak, more people die of diarrhoea every day in India and have done for years, mostly due to a lack of clean water and sanitation creating a terrain ripe for the flourishing of communicable disease.”
Readers can access the report How the Unscientific Interpretation of RT-PCR & Rapid Antigen Test Results is Causing Misleading Spikes in Cases & Deaths by Yohan Tengra and Ambar Koiri here.
Lockdowns are No Substitute for Focused Protection
By Paul E. Alexander | AIER | May 3, 2021
The most vulnerable groups in the US, which have been least able to afford the lockdowns and school closures, have been devastated by unscientific ineffective policies and have been hardest hit by Covid-19. The health of a nation is directly tied to the socioeconomic health of the nation, and the socioeconomic drivers that played a role in Covid-19’s severity cannot be ignored, particularly for the future burden of disease outcomes. Focused protection would have performed far better than lockdowns, which have not only been a distraction but actually enhanced the unequal impacts of severe outcomes of the virus.
In May 2020 the prevailing winds presciently suggested that there was a significant care-burden on the families in the future. The socioeconomic status of a person can negatively impact their lifestyle choices that are often unhealthy in nature, and this is complicated by the reality that often, this is not by choice, and rather based on ‘need.’ Often there is no other option but maladaptive ones.
The ineptness of the government leaders, public health officials and some television medical experts who have shown gross academic sloppiness and a depth of cognitive dissonance to all views not aligned with their failed ones, in retrospect is available to all for review. The evidence of the segments of the populace at greater risk emerged several months ago, included risk factors such as being elderly, being obese, and having comorbid conditions and has remained firm as a precursor of acquiring the ravages of the SARS-CoV-2 infection.
The failure to adopt appropriate public health measures to prevent the catastrophic disaster on the vulnerable and those at risk is laid at the feet of those officials and experts who were involved in the policy making process. The responsibility of the “Task Force” was protection and the safeguarding of all the citizens and they failed in their efforts. Not only did these experts resort to using political import as their guidance on decision-making, they have now resorted to groupthink and we have entered the age of Lysenkoism science where contrarians, dissenters, skeptics, and people who question their motives and underlying evidence for their ineffective policies, are attacked, slandered, and smeared.
All politicization aside, Covid-19 exploits our risk factors and age is the principle risk factor among them. This is understandable given that as we all age, our immune systems become less durable and there is a gradual deterioration of the immune system, called immune senescence. A focus on the other risk factors that Covid-19 exploits will help us prepare for future coronaviruses and other pathogens that also will exploit such risk factors. Covid-19 is a condition of disparity given its unequal force of mortality on lower SES populations. Minority populations in the US have been hit harder by Covid-19 in terms of severe outcomes due to a multiplicity of factors. The worldwide data suggests that this harm has occurred elsewhere and is not unique to the US. As an example, we are willing to discuss the elevated risk due to excessive body weight (obesity, morbid obesity) and this is a very serious issue that must be debated as a society. We argue that for many impoverished persons with depressed SES status, obesity is tied to economics. We have seen that Covid-19 gives away age to obesity in younger persons. Recent British research in near 7 million persons has shown that a body-mass-index (BMI) of greater than “23 kg/m2 was associated with a linear increase in risk of severe Covid-19 leading to admission to hospital and death, and a linear increase in admission to an ICU across the whole BMI range, which is not attributable to excess risks of related diseases. The relative risk due to increasing BMI is particularly notable in people younger than 40 years and of Black ethnicity.”
In confronting this pandemic in March 2020 and certainly by the summer of 2020, we had in our arsenal (yet failed to capitalize upon) a combination of i) strongly protecting (double- and triple-down protection) the elderly high-risk persons in nursing homes and similar congregated settings ii) use of effective public service announcements on who is at risk and how to mitigate the risk iii) allowing the low-risk portion of the population to live daily lives with sensible reasonable precautions, allowing them to get infected naturally and harmlessly given their low risk of severe illness or death and iv) use of early outpatient drug treatment (sequenced antivirals, corticosteroids, and anti-clotting drugs) in high risk populations, younger persons with comorbid conditions, and obese persons.
Unfortunately, we chose to ignore the signals from the pandemic. The fact remains that age and excess body weight/obesity, have accounted for almost 80% of the hospitalizations, intubations/ventilation, severe sequelae and deaths in Covid-19. A large number of persons who have died in nations such as the US have been overweight with some level of obesity.
The importance of educating the public on the risk factors and the need for such protective efforts can be enhanced by the people themselves. Had public health leaders used their platforms optimally, the geared messaging would have helped reduce the damage significantly. We could have cut deaths significantly had the options described above been used, especially early outpatient treatment.
As an example, the various US health agencies and their leaders have failed the minority and higher-risk African-American communities by neglecting to message the need for vitamin D supplements in persons with darker skin color. Evidence suggests that Vitamin D has an important immune function role and is a means to mitigate acute respiratory distress due to Covid-19, with patients revealing improved clinical recovery (shorter lengths of stay), lower oxygen requirements, and a reduction in inflammatory marker status.
So why have the public health agencies not messaged this to the high-risk minority groups, especially African-American and Asian-Americans? Why have the public health agencies or the Surgeon General not focused on public service messaging on the risk of excess body weight in Covid-19, as the right messaging could have saved tens of thousands of lives? We could have saved tens of thousands of lives had public health not been so politicized and done its rightful job.
We are responding to these failures by calling for a ‘social determinants of health’ approach to Covid-19 (a strong focus on the social aspects) and we find it is unacceptable that the public health agencies and television medical experts continued to use the platform to create fear rather than use their daily podium to address the potentially correctable catastrophic linkages.
US public health agencies such as the CDC appear to be 9 months to one year behind the science, routinely. The messaging, even at this late stage, continues to confuse the public as it waffles regarding masking, social distancing and vaccination, thus squandering the opportunity to help mitigate the impact of Covid-19 in their public health roles.
If the approach is mainly a therapeutic biomedical one to deal with Covid-19 (only to treat the disease or mitigate the epidemic/transmission), then this will end in failure each and every time. We must consider the socioeconomic ‘upstream’ fundaments of Covid-19 (and similar illnesses) and in an integrated manner. There is a certain level of personal responsibility in the decision-making on the part of the individual, as part of this discussion that must not be overlooked, but we would be ignorant to not recognize the direct association between poverty and health and the seemingly strong role that Covid-19 has in exploiting this link. Failure to understand this link between the SARS-CoV-2 virus and the SES of an individual thus fails to address an addressable and treatable issue.
In other words, had the US been a healthier population with a lower burden of noncommunicable chronic type diseases (diabetes, renal disease, hypertension, cardiovascular disease, respiratory illnesses etc.) and had the population been composed of less overweight and obese persons, then the force of severe morbidity and mortality would have been far lower from Covid-19.
If Covid-19 entered a population of 10,000 persons as an example, with a mean age of 40 (eldest being 60) and where all 10,000 persons were healthy, no underlying conditions, and a respectable health care system that could respond if there is need, then Covid-19 will likely (more certainly) severely impact no one and kill no one. At least the impact will be minimal. A strong argument could be made here and this is the approach we are taking. We make this clarion call not only for ‘Western’ richer nations plagued by these chronic conditions and risk factors, but also for poorer developing nations also struggling with these chronic conditions. Covid-19 has shown us that as a society, we must urgently heighten our resolve to combat hypertension, obesity, diabetes, cardiovascular, renal, and respiratory diseases, as well as cancer.
In addition, ‘stopping Covid at all costs’ (zero-Covid) has been a critically flawed approach that has proven to be harmful. The mindset of lockdowns continues unabated although the data suggests otherwise and some epidemiologists are voicing contrary opinions. This was indeed understandable in the first month (March/April 2020), but this may come back to haunt us as we have prolonged the fixation on Covid-19 at the loss of other equally and even more dangerous illnesses.
We already see warning signs of dramatic declines in vaccine-preventable disease vaccinations for children (declines in pediatric vaccine ordering and doses administered), and as such, anticipate a surge in such illnesses we usually control with vaccine programs. Yet we continue to fixate on Covid-19, ignoring other pressing conditions, when we know who the at-risk group is, and we know much better how to treat. Covid-19 in April/May 2021 is not Covid-19 in February and March 2020. Covid-19 is not a death sentence for we can manage and treat it and we do have early outpatient treatment that has proven effective, once given early in the sequelae when the patient has not yet worsened.
We continue to caution against the exploits of the politicians and their strong and deliberate inroads into the scientific community. This egregious intrusion is causing a grave harm on science itself. This includes the medical research community and the academic journal publishing and editors (peer-review process) whose roles have been politicized, and have contributed to the current failures. Covid-19 has revealed the political and corrupted underbelly of academic and medical scientific research and journal manuscript publishing with its steep conflicts of interest that will require many years if not decades to recover its reputation (if at all).
Understanding Covid-19 must therefore not involve the traditional unidimensional, dogmatic orthodoxy whereby we simply wish to control the spread of the pathogen or eradicate it. It remains an impossibility to eradicate a viral pathogen, especially if it is highly mutable like the flu virus. We as humanity have learned to live with such viruses. There is a greater severity and adverse sequelae in lower SES populations (socioeconomically disadvantaged populations), so we have to look at this and consider what is happening and focus here with a more nuanced finessed approach to pathology, as we address targeting the pathogen. This approach will help us now as well as in the future, as we deal with existing, emerging, and reemerging pathogens.
Importantly, (and a potential reason for the excessive burden of death in obese persons we have found this to be the case in African-American, minorities etc.), is the heightened expression of the ACE2 receptor in adipose tissue fat cells in obese persons (expression is higher in visceral and subcutaneous adipose tissue than that in lung tissue). A poor diet dominated by high-sugar, high-starch foods (predominantly rice, potatoes etc.) driven by affordability and the drive for satiety, contributes to obesity and the associated health conditions such as diabetes. The seeds of this are often planted in childhood. Is one at-risk group more differentially impacted and can obesity explain a substantial proportion of the severe sequelae? Do these social and economic factors (socioeconomic inequality) affect the severity sequelae differentially based on type of background condition e.g. will a socially disadvantaged person fare worse with diabetes or kidney disease versus cardiovascular illness?
The answers to some of these questions have been answered by the science community. The CDC posits a similar opinion that health disparities among minorities are real and related to the Covid illness. We applaud the CDC for this position. Yet even with a plethora of information available our policy makers still continue to punt on the issues that remain unaddressed and continue to harm people unnecessarily.
To end, we are arguing that the SES status with the social factors work to drive, perpetuate, prolong, and potentially worsen the emergence and clustering of pathogens and diseases. The above-mentioned comorbidities that exist in the vast majority of SARS-CoV-2 severe illness outcomes and death with Covid-19 especially among the poorer minority communities seem to drive Covid-19 and dramatically compromise a person’s ability to ward off the disease and escalate an infected individual’s susceptibility and vulnerability to harm or worsen their health outcomes. We need to study and understand this if we are to effectively shape prognosis and treatments. Good public health policy must reflect this interwoven relationship between pathogen, pathology, and social and economic equality, not merely impose the blunt and devastating “nonpharmaceutical interventions” indiscriminately on the whole of the population.
Contributing Authors
- Paul E Alexander MSc PhD, McMaster University and GUIDE Research Methods Group, Hamilton, Ontario, Canada elias98_99@yahoo.com
- Howard C. Tenenbaum DDS, Dip. Perio., PhD, FRCD(C) Centre for Advanced Dental Research and Care, Mount Sinai Hospital, and Faculties of Medicine and Dentistry, University of Toronto, Toronto, ON, Canada howard.tenenbaum@sinaihealth.ca
- Dr. Parvez Dara, MD, MBA, daraparvez@gmail.com
DC Mayor Bans Dancing & Standing At Weddings!
By Richie Allen | May 4, 2021
Washington DC Mayor Muriel Bowser has banned dancing at weddings. On Friday, Bowser said that weddings could go ahead but only at 25 per cent of a venues capacity. But she banned dancing and standing at receptions.
A spokesperson for the mayor’s office told FOX News on Friday that the measures were necessary to stop the spread of covid-19. The mayor said that people’s behaviour changes when they dance or stand around.
Meanwhile, Florida Governor Ron DeSantis lifted all local coronavirus emergency orders in his state yesterday. He also signed a bill that effectively bans the use of vaccine passports in Florida.
In New York, Governor Andrew Cuomo has announced that most restrictions will be removed from May 19th. However, Cuomo wants to retain social distancing and mask-wearing.
Will couples really ask wedding guests to remain seated at all times? Will they fence off the dance floor too?
Why is Muriel Bowser not being laughed out of town? Who are these people? Who are they taking advice from? Where do they get the balls to tell people who they can invite to weddings and how they must behave on the day?
You know this all goes away when people turn their backs on idiots like Bowser. Just ignore them. It really is that simple. Ignore them and carry on regardless. The only power they have is the power you give them. It’s time to take it back.
Featured Video

Ivermectin and iodine
or go to
Aletho News Archives – Video-Images
From the Archives
UN declares war on ‘dangerous’ conspiracy theories
‘World is not secretly run by elites’
Free West Media | August 5, 2022
UNESCO says it is seriously concerned about the increase in “disinformation” and “conspiracy theories”. And they plan to put an end to it through a network of informants.
“Conspiracy theories can be dangerous,” the UN agency warned. “Often they ignore scientific evidence and polarize society with dire consequences. This has to stop.”
Unesco’s director-general warned that “conspiracy theories” could cause damage to people as well as to their health. “They reinforce misconceptions about the pandemic, reinforcing stereotypes that can fuel violence and violent, extremist ideologies,” said Audrey Azoulay.
The UN agency has launched a campaign to help people identify, debunk and report “conspiracy theories” to prevent them from spreading further.
This campaign is being carried out in collaboration with the European Commission, Twitter and the World Jewish Congress. The UN has created a toolkit to “debunk” such theories and smear anyone who dares to claim that governments are not fair and transparent.
The UN also warned that George Soros, the Rothschilds and Israel should not be linked to “alleged conspiracies”.
World events “are not secretly manipulated behind the scenes by powerful players with malicious intent,” the UN agency maintained.
And if anyone therefore comes across someone who believes that the world elite is plotting to consolidate power or direct events, then that person needs to take action. According to the UN agency, when meeting a “conspiracy theorist”, under no circumstances should one enter into a discussion. … continue
Blog Roll
 Aletho News
- Russia shows Europe that prolonging the Ukraine war is pointless
- There is cautious optimism about ending the Ukraine War – Part 2
- Ukrainian air alert app hacked with fake nuclear warnings
- Ivermectin and iodine
- Congratulations climate skeptics — you are a ‘Hybrid weapon of war’ and a growing public health threat
- ‘The Arab Vote’: How Israeli Racism Has Ruined Their Elections
- Israel forces Palestinians in Gaza to choose between assassination alone or death with their families: Report
- US Approves Sale of 500 Patriot Missiles to Ukraine, Deliveries May Take Years
- German Imperialism: An Urgent Explainer
- Backed by AAP, West Virginia Proposal Would Allow Dental Hygienists to Give HPV Vaccine to 9-Year-Olds
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!

