The Shadowy CIA Data Firms Behind the Creation of Digital Vaccine Passport IDs
Daily Veracity | December 17, 2021
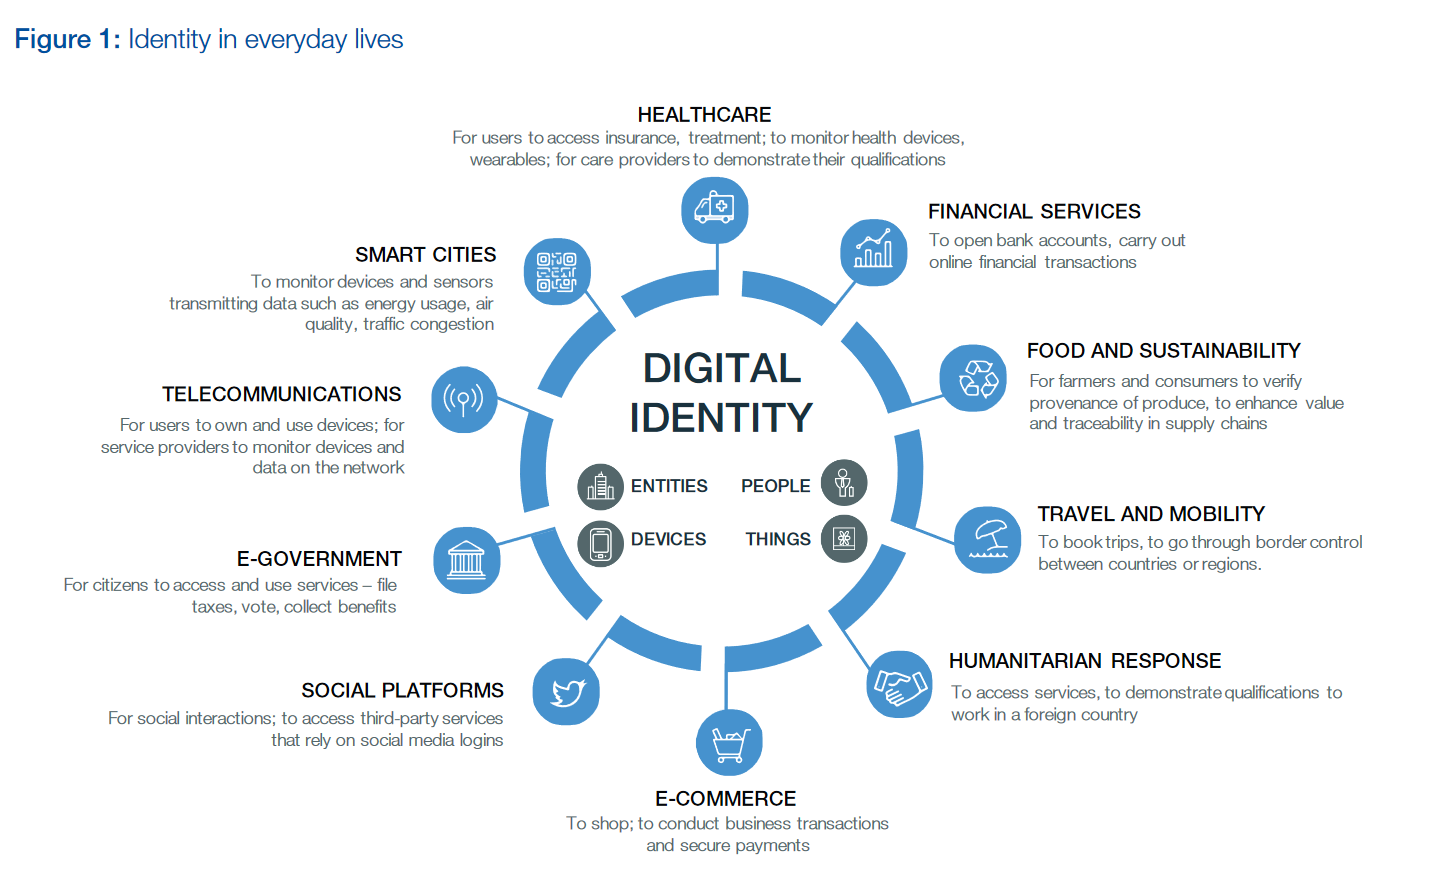
In January 2021, tech giants such as Microsoft, Oracle, and MITRE Corporation announced their launch of the Vaccination Credential Initiative (VCI) in partnership with healthcare companies.
On their website, the VCI describes itself as an alliance of private and public organizations dedicated to the development of the ‘issuance of verifiable health credentials’ bound to an individual digital identity.
The VCI idea depends upon a common platform from which digital wallets can be created, and on the VCI website they call for “participating organizations to commit to implementing, testing, and refining the SMART Health Cards Framework within their sphere of influence.”
According to VCI, their ‘SMART Health Cards’ are meant to “work across organizational and jurisdictional boundaries.”
SMART health cards as of now include a person’s name, gender, birth date, phone number, and email address, as well as vaccination status. Developers hope, however, that these cards will eventually become all-encompassing universal digital identities that reside within a universal digital wallet.
Josh Mandel, one of the main developers behind VCI’s SMART health cards system, said once that a complete universal digital identity is ‘essential’ to the effort of creating digital vaccination passes.
On their website, the group uses the term ‘digital wallet’ often and notes that SMART Health Cards could soon be used as digital IDs for all activities, including travel and every purchase an individual makes during commercial activity.
According to the ‘about’ section on their website, the group’s members section includes corporations like Amazon, Microsoft, Google, Apple, and the MITRE Corporation.
Along with the MITRE Corporation, one of the groups listed in the governance section on the website is the Commons Project Foundation, which is the main backer of the VCI and also hosts the VCI website.
The Commons Project Foundation also describes itself as a ‘private and public alliance.’
Listed on the leadership board of the Commons Project Foundation is the President of the Rockefeller Foundation, the Global Head of Performance at BlackRock, the senior managing director at the Blackstone Group, and Julie Gerberding, the former director of the CDC. Gerberding once wrote an op-ed in Time Magazine calling for an ‘International Pandemic Surveillance Network.’
There are many other heads of multilateral development banks (MDBs), former Goldman Sachs partners, UN advisers, and other multinational corporations listed on their assembly.

With the help of the World Economic Forum and the Rockefeller Foundation, the Commons Project Foundation runs the Common Trust Network. Like the Vaccination Credential Initiative and the Commons Project Foundation, the Commons Trust Network describes itself as a ‘private and public alliance.’
The World Economic Forum’s website lists the CEO and CMO of the Commons Project Foundation as Paul Meyer and Bradley Perkins respectively. Following his career at the US Center for Disease Control, Perkins was on the advisory board for the RAND Corporation, and his Partner Paul Meyer wrote President Clinton’s speeches while attending Yale.
In partnership with the World Economic Forum and the Rockefeller Foundation — as well as an almost endless list of corporations and government agencies — the Commons Project Foundation created the CommonPass.
According to the World Economic Forum’s website, just like the VCI, the Commons Project Foundation seeks to “develop and launch a standard global model to enable people to securely document and present their COVID-19 status to facilitate international travel and border crossing.”
The site states that their ‘CommonPass‘ is powered by their “CommonTrust Network™ Registry and VCI™ Directory.” and will allow individuals to document their “COVID-19 status to satisfy country or state entry requirements,” and “access lab results and vaccination records when you need it.”
Dutch Police Sick Attack Dogs On Anti-Lockdown Protesters
Is this what a ‘free’ country is supposed to look like?
By Steve Watson | Summit News | January 3, 2022
Shocking video emerged Sunday of police in Holland beating anti-lockdown protesters with batons and sending in dogs to maul the dissenters.
Massive amounts of people turned out to protest hard lockdown restrictions which were put back into place by the Dutch government before Christmas.
Everything except essential stores has been shut down in the country until at least Jan. 14.
The restrictions dictate that gatherings of more than two people are illegal, so the government sent in the riot police.
Watch:
Covid passport microchip developer says chipping humans is happening “whether we like it or not”
By Ken Macon | Reclaim The Net | January 3, 2022
Towards the end of last year, tech start-up Dsruptive Subdermals announced a microchip installed under the skin that can be scanned to reveal Covid vaccination status.
The technology was criticized, with many calling it “invasive.”
In an interview with Express, the company’s managing director doubled down on the technology and told critics the technology was here to stay.
The technology is a pre-programmed and scannable implant about the size of a grain of rice. It stores the vaccination information, displaying a person’s Covid-19 vaccine passport when scanned.
Speaking to Express, Hannes Sjobald, the company’s managing director, said: “This technology exists and is used whether we like it or not.
“I am happy that it is brought into the public conversation.
“New technologies must be broadly debated and understood.
“Smart implants are a powerful health technology.
“That is what we are building at Dsruptive and our goal is to transform healthcare on a global scale.”
Sjobald said the technology makes the vaccine passports more “accessible.”
“This means it is always accessible for me or for anyone else, really, who wants to read me.
“For example, if I go to the movies or go to a shopping center, then people will be able to check my status even if I don’t have my phone.”
Related:
Supreme Court to Hold Special Session on Legal Challenges to Biden Vaccine Mandates
By Michael Nevradakis, Ph.D. | The Defender | January 3, 2022
The U.S. Supreme Court on Jan. 7 will convene a special session to hear oral arguments in two cases related to the Biden administration’s COVID vaccine mandates.
The two cases pertain to the mandates imposed on private businesses with 100 or more employees, and healthcare facilities participating in the Medicare or Medicaid programs.
The Supreme Court announced Dec. 22, 2021, it would hold a special session to hear both cases, following a series of decisions in lower courts that successively implemented and lifted injunctions against the two mandates.
In both disputes, the formal legal question at hand pertains to whether the federal government can continue enforcing the mandates while legal challenges against them work their way through the judicial system.
In the first instance, the 6th Circuit Court of Appeals, in a 2-1 ruling Dec. 17, 2021, lifted an injunction against Biden’s vaccine mandate for private businesses previously issued by the 5th Circuit Court of Appeals.
The mandate is now set to come into force on Jan. 4, though the Occupational Safety and Health Administration (OSHA) announced it will not begin enforcement of the rule until Jan. 10. The mandate, if and when it is enforced, will impact an estimated 84 million U.S. workers.
Immediately following the 6th Circuit Court ruling, 27 states and several business groups, companies and ministries submitted applications to the Supreme Court seeking an emergency stay.
Two of these requests, one filed by a trade group and the other by a group of states led by Ohio, were formally accepted for oral argument.
These groups were joined by more than 170 Republican lawmakers who on Dec. 30, 2021, jointly filed an amicus brief with the Supreme Court arguing OSHA has no legal authority to impose a vaccine mandate on private businesses.
The Supreme Court, via Justice Brett Kavanaugh — whose jurisdiction includes the 6th Circuit — asked the Biden administration to submit a response to the legal challenges by Dec. 30, 2021.
In its response, Solicitor General Elizabeth B. Prelogar argued the Biden administration possesses the authority, under federal law, to impose the mandate and the Supreme Court should not block a program that will save thousands of lives.
The Supreme Court will also hear arguments pertaining to Biden’s vaccine mandate for healthcare workers at facilities that receive federal Medicare or Medicaid funding. This rule is estimated to impact more than 17 million workers across the U.S.
In this instance, it was the Biden administration that filed an emergency request with the court, requesting it be allowed to temporarily enforce the healthcare worker mandate, which is currently blocked in 24 states following a series of injunctions issued by lower courts.
A brief filed with the Supreme Court by 14 Republican-led states described the mandate as “plainly unlawful.”
The Centers for Medicare & Medicaid Service, which oversees the healthcare mandate, announced Dec. 29, 2021, it will begin enforcing the mandate in the 26 states where it is not blocked.
A modified enforcement timeline accompanied this announcement: Healthcare workers will now be required to receive the first dose of a COVID vaccine by Jan. 27, and the second dose by Feb. 28.
The Supreme Court’s move to hold oral arguments in deciding whether or not to issue an emergency stay is considered unusual. Typically, such cases are placed on the “shadow docket” and are decided without a full briefing or a presentation of oral arguments.
In this instance though, the Supreme Court may seek to alleviate the uncertainty which exists among employers and workers who remain unsure as to whether they are subject to a mandate or not.
It remains unclear whether a decision by the Supreme Court to uphold the injunctions against the healthcare worker mandate will impact all 50 states or only the 24 where the mandate is currently blocked.
Any emergency stay issued by the Supreme Court would not constitute a final ruling regarding either case, but would freeze the enforcement of the two mandates until legal challenges make their way through the federal appeals courts before, most likely, ending up in the Supreme Court for a full hearing.
Separate Biden administration mandates pertaining to such categories as federal contractors and military personnel also have been challenged legally.
In the most recent such example, Judge James “Wesley” Hendrix of the U.S. District Court for the Northern District of Texas ruled against a mask and vaccine mandate for participants in federal Head Start programs. The rules were set to take effect by the end of January.
Texas Attorney General Ken Paxton described the ruling as “a win for the children of Texas.”
However, the Supreme Court will not examine any of these other Biden administration mandates in the Jan. 7 special session.
While the Supreme Court previously rejected requests for emergency stays against state-level vaccine mandates, the court is also viewed as one that is skeptical of the power of federal agencies to issue mandates relating to COVID countermeasures.
This stance was evident, for instance, when the court lifted a moratorium on evictions imposed by the Centers for Disease Control and Prevention, on the basis it was outside the agency’s authority.
Notably, a well-known Supreme Court decision from 1905, Jacobsen v. Massachusetts, which, according to proponents of vaccine mandates, sets a legal precedent for their legality, actually pertains to state-level mandates.
This argument was made by the state of Arizona in its lawsuit against the OSHA mandate, as previously reported by The Defender.
The lack of a federal-level precedent may therefore weigh into the justices’ decision.
Michael Nevradakis, Ph.D., is an independent journalist and researcher based in Athens, Greece.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
UK plans to test EVERY school child TWICE this week
… so what happens when you run 7 million lateral flow tests in five days? And are you ready for the “new wave” of “cases” it will likely produce?
OffGuardian | January 3, 2022
New plans, announced before Christmas, will require every secondary school pupil in the UK to take an on-site Covid test when school resumes after the Christmas break.
The government plans, allegedly to “monitor” Covid infection in students, go on to suggest that every child should receive a follow-up test 3-4 days later.
The tests being used are lateral flow tests, which have repeatedly been shown to be completely unreliable, and can test positive using apple juice or coca-cola.
There are roughly 3.5 million school pupils aged 11-16 in the UK and they plan to test them all twice.
If just 2% of them test positive just once, the media will scream about 140,000 new “cases” of Covid in children.
Further, the “recommendations” suggest children should then continue to be tested twice a week, every week, or “more frequently if asked to do so”:
Secondary, college and university students and education staff and early years staff should then continue to test themselves twice a week, and more frequently if they are specifically asked to do so, such as in the event of an outbreak.
At least 7 million lateral flow tests per week, every week.
It’s not hard to see where it goes from there, with the headlines blaring that lack of social distancing over the holidays gave rise to a “fourth wave” (or would it be fifth? I’ve lost count).
I would start preparing for a new lockdown, if I were you.
Lukashenko Told You It Was a Psychosis TWO YEARS Ago

Anti-Empire | January 3, 2022
The entire interwebs are ablaze with the term “mass formation psychosis”. Since a smart Ph.D. visited Joe Rogan everyone and their grandmother are now reading up on it, and emitting into the ether how the COVID panic (hysteria) is nothing but a mass psychosis. That is great. Except that it is January freaking 2022.

It has been a psychosis for nearly TWO YEARS now. It has been evident it is nothing but brain rot in the heads of excitable idiots this whole time. Aleksandr Lukashenko, a Belarusian potato farmer, and a much less educated man than Dr. Robert Malone, diagnosed it as a “psychosis” and an “info-demic” way back in March 2020.
“Despite some criticism on my part, I call this coronavirus nothing other than a psychosis, and I will never deny that, because I’ve gone through many situations of psychosis together with you, and we know what the results were.
“Coronavirus is yet another psychosis, which will benefit some people and will harm others.”
Doesn’t it seem to you that the powerful forces of the world would like to remake the world, without a ‘war’(Emmanuel Macron has already called it a war), through this so-called ‘corona-psychosis’, or ‘info-demic’? Many people are asking: ‘what will happen after the pandemic?’”
Some need the permission of a PhD to start thinking, preferably a PhD they saw on a massive media outlet like Rogan.* Others, like Lukashenko have their common sense.

*Who is on record as saying that without lockdowns you would have had more COVID deaths.
Former Ontario privacy chief says never trust the government with coronavirus cell phone tracking
By Ken Macon | Reclaim The Net | December 31, 2021
Ontario’s former privacy commissioner Ann Cavoukian has warned that the government cannot be trusted with cellphone tracking amid the pandemic. The warning came after it was revealed last week that a federal agency has been using cellphone data to track the movements of Canadians since the beginning of the pandemic.
“It concerns me enormously that this would enable the government to collect more and more information,” Ann Cavoukian told The Epoch Times.
“I do not want to [see] a trend where the government is consistently doing this and starting now. You can’t trust the government.”
Last week, the Public Health Agency of Canada (PHAC) confirmed it has been using cellphone data to analyze movements for the purposes of pandemic policies. The agency plans to continue with the data analysis until 2026, expanding it to other health issues.
“In March 2020, [Prime Minister Justin] Trudeau said that tracking cell phone users was not being considered. Well, they did it, PHAC’s been doing it, and they want to do it even more,” Cavoukian said.
“[Officials] say ‘as soon as the emergency is over, we’re going to return to privacy.’ They don’t. The privacy invasive measures that are introduced during emergencies, pandemics, etc., often continue well after the emergency is over,” she added.
According to the former privacy commissioner, who served from 1997 to 2014, PHAC kept the data collection a secret because “they know people do not want their mobile devices tracked.”
Cavoukian was particularly concerned with the PHAC partnering with other unknown data providers, like the Communications Research Center (CRC).
“In partnership with CRC, PHAC has been producing report summaries to look at how movement trends of the Canadian population have changed over the course of the pandemic, including identifying new patterns to help direct public health messaging, planning and policy development,” PHAC said in a statement to The Epoch Times.
The agency insisted that it did not “receive or collect any individual mobility data” and that it has not stored or acquired individual level data.
On December 16, the PHAC posted a Research for Proposal for a contractor that could “provide it with a steady flow de-identified cell phone data,” reported The Epoch Times.
In a statement, the agency said it “requires access to cell-tower/operator location data that is secure, processed, and timely in addition to being adequately vetted for security, legal, privacy and transparency considerations to assist in the response to the COVID-19 pandemic.”
According to Cavoukian the language in the RFP “reflects an intention to collect this data and retain it.”
She is concerned that the de-identification of data could be done so poorly that it could easily be re-identified.
“At the very least, the Privacy Commissioner’s Office should be all over this, and saying we need to examine exactly what measures you introduced to do this and how you’re going to protect privacy and de-identify data such that it cannot be re-identified,” she said.
“Examine this from end to end. Look under the hood.”
Facts about Covid-19
Swiss Policy Research | Updated: December 2021
Fully referenced facts about covid-19, provided by experts in the field, to help our readers make a realistic risk assessment.
“The only means to fight the plague is honesty.” (Albert Camus, 1947)
Overview
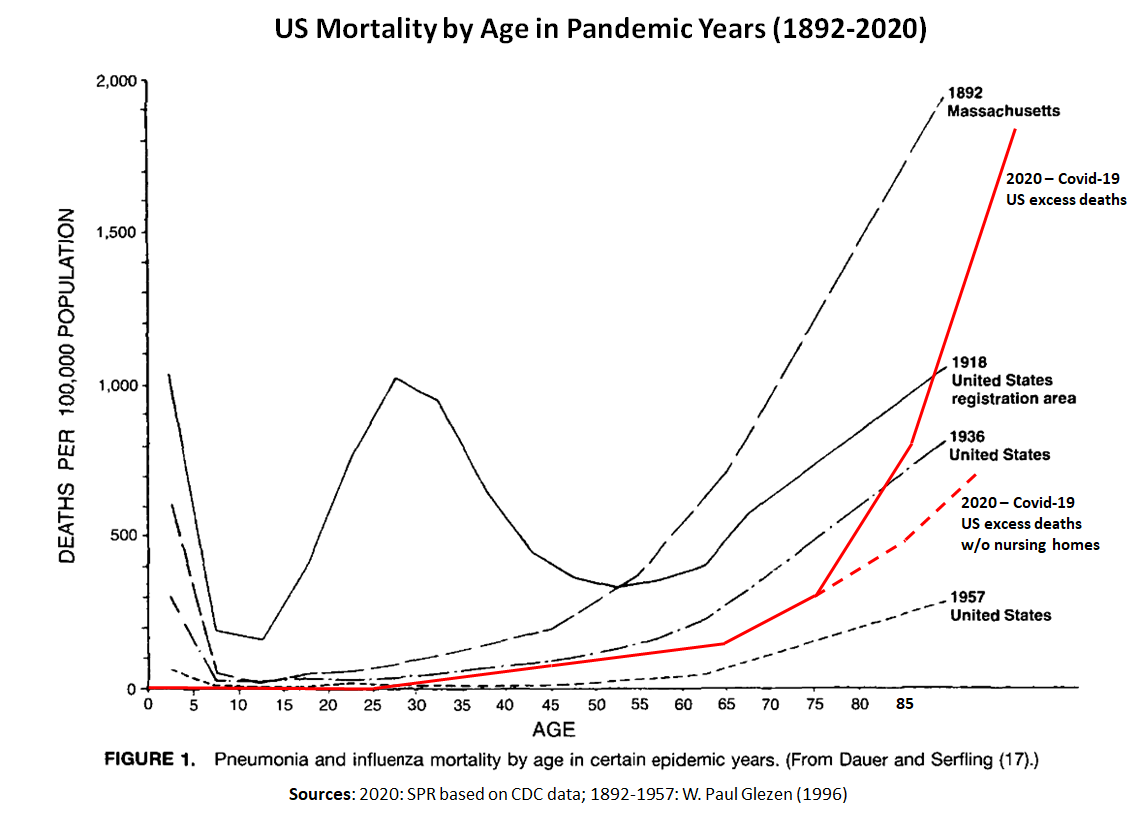
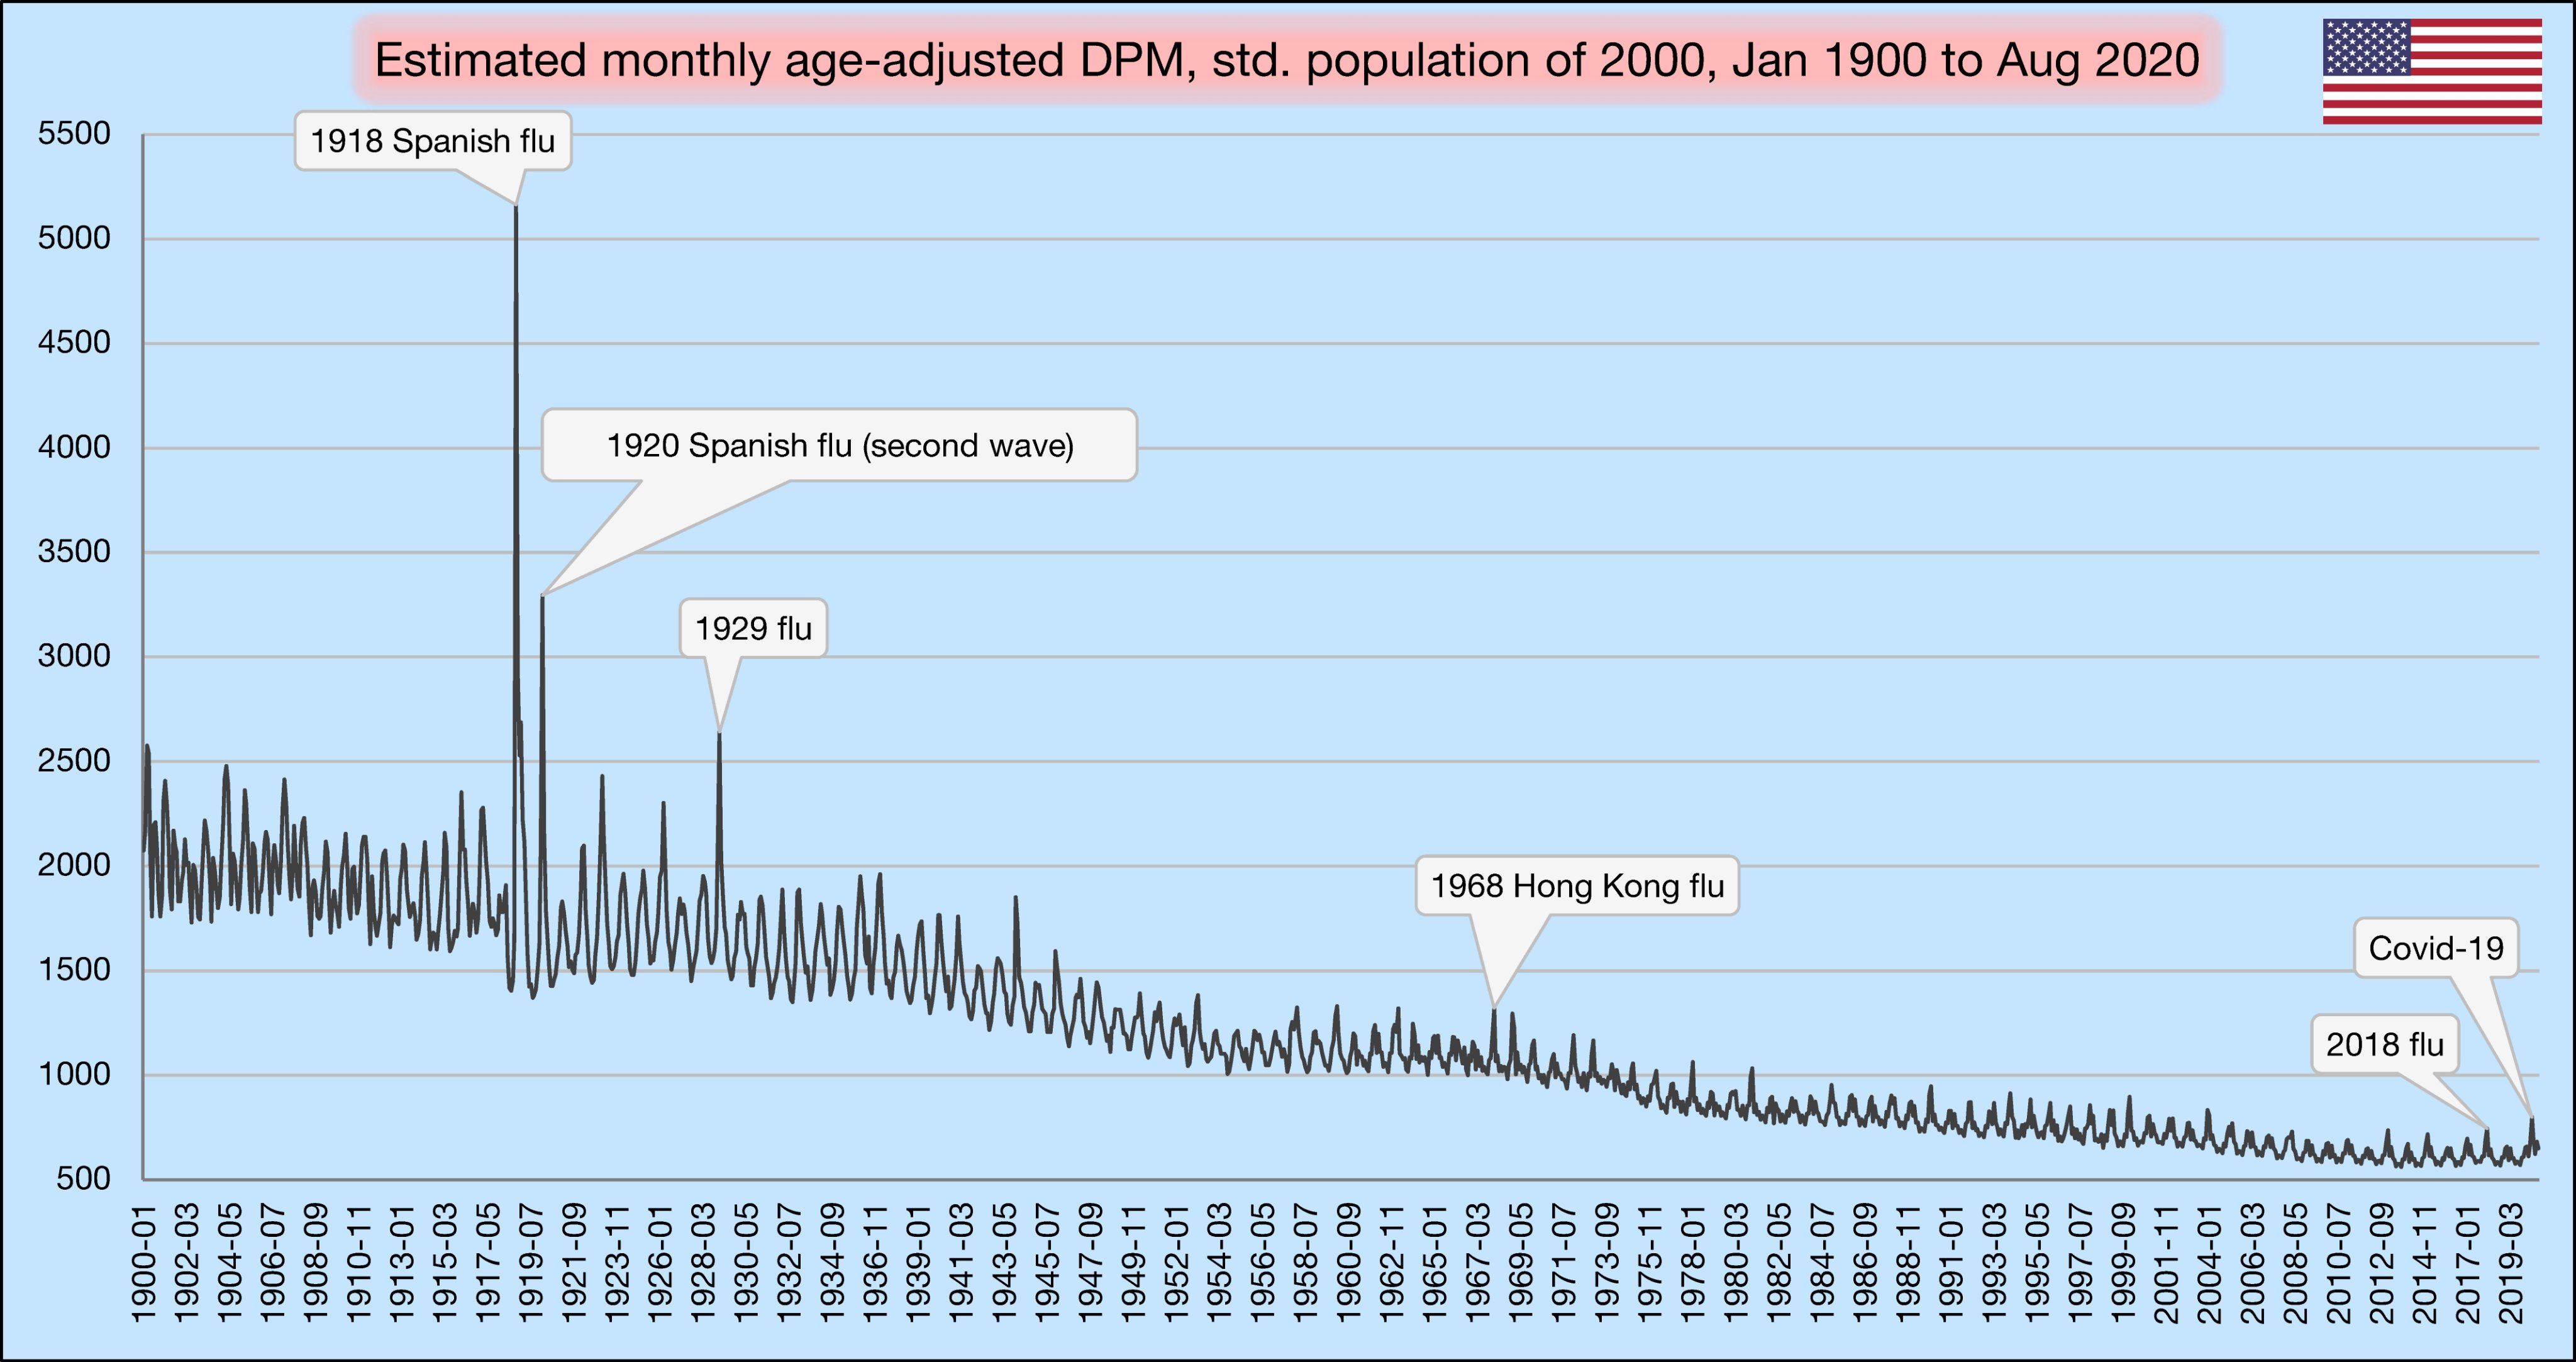
- Lethality: According to the latest immunological studies, the overall infection fatality rate (IFR) of covid in the general population is about 0.1% to 0.5% in most countries, which is most closely comparable to the medium influenza pandemics of 1936, 1957 and 1968.
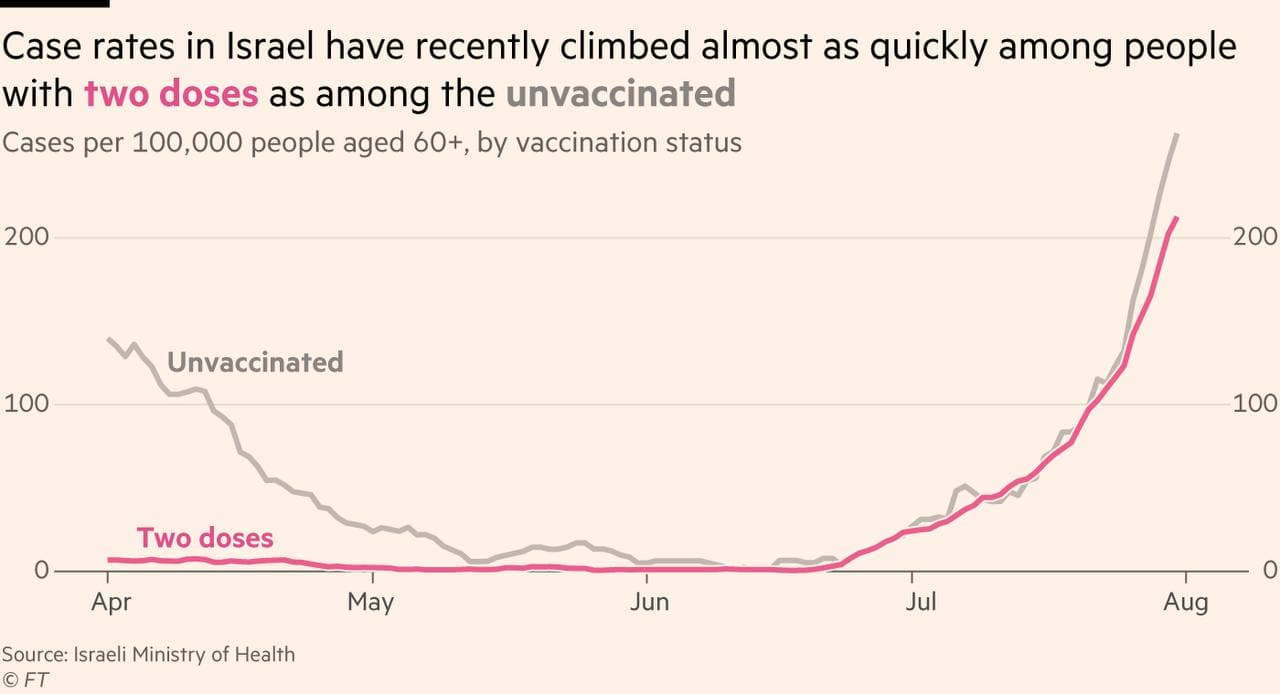
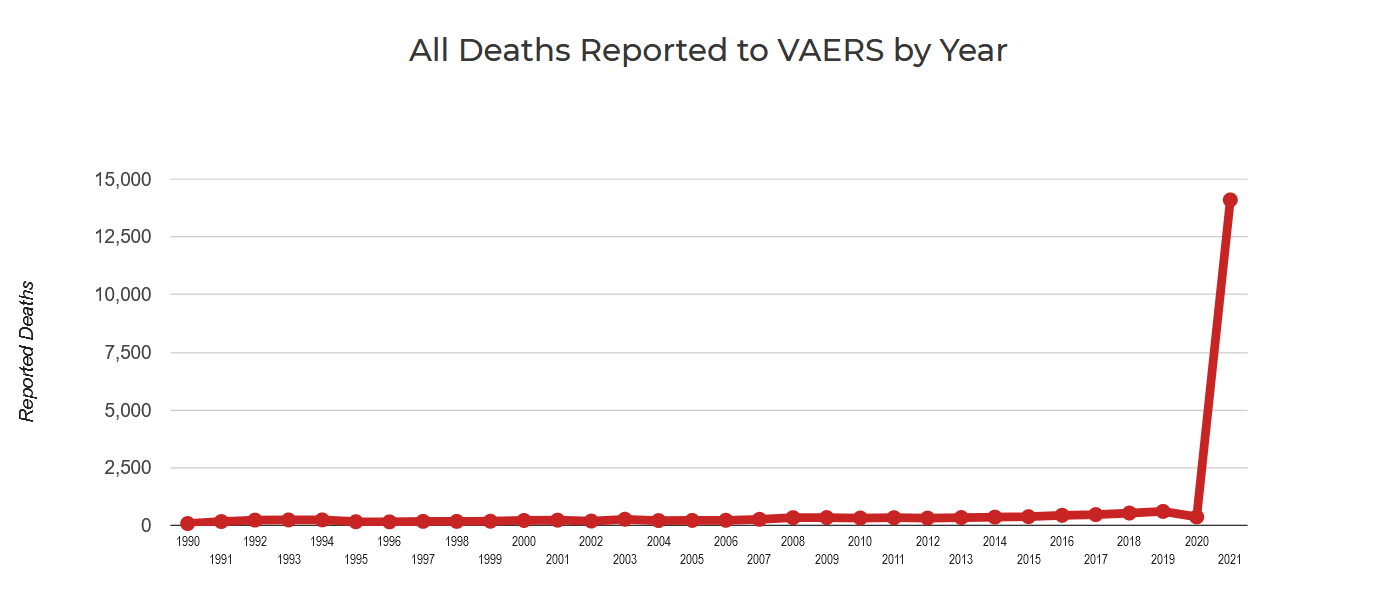
- Vaccines: Real-world studies have shown a very high, but rapidly declining covid vaccine effectiveness against severe disease. Vaccination cannot prevent infection and transmission. Various severe and fatal vaccine adverse events have been reported, including in young people. A prior infection generally confers superior immunity compared to vaccination.
- Treatment: For people at high risk or high exposure, early or prophylactic treatment is essential to prevent progression of the disease. According to numerous international studies, early outpatient treatment of covid may significantly reduce hospitalizations and deaths.
- Age profile: The median age of covid deaths is over 80 years in most Western countries (78 in the US) and about 5% of the deceased had no serious preconditions. The age and risk profile of covid mortality is therefore comparable to normal mortality, but increases it proportionally.
- Nursing homes: In many Western countries, about 50% of all covid deaths have occurred in nursing homes, which require targeted and humane protection. In some cases, care home residents died not from the coronavirus, but from weeks of stress and isolation.
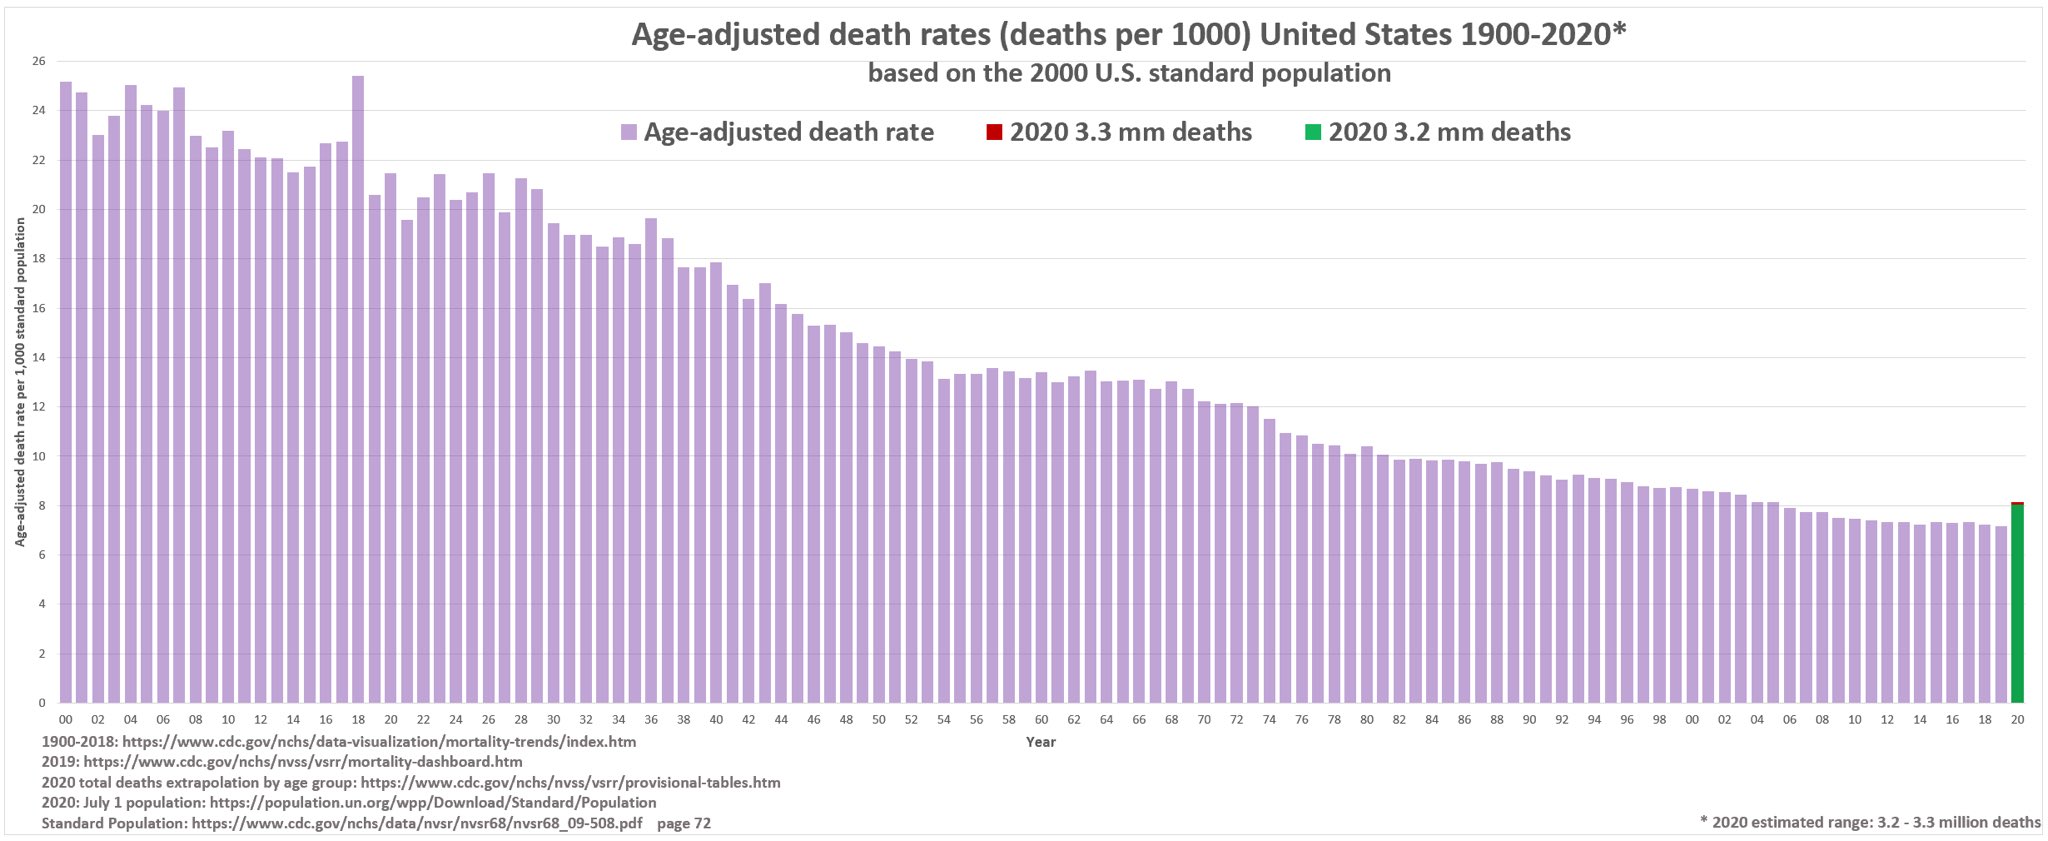
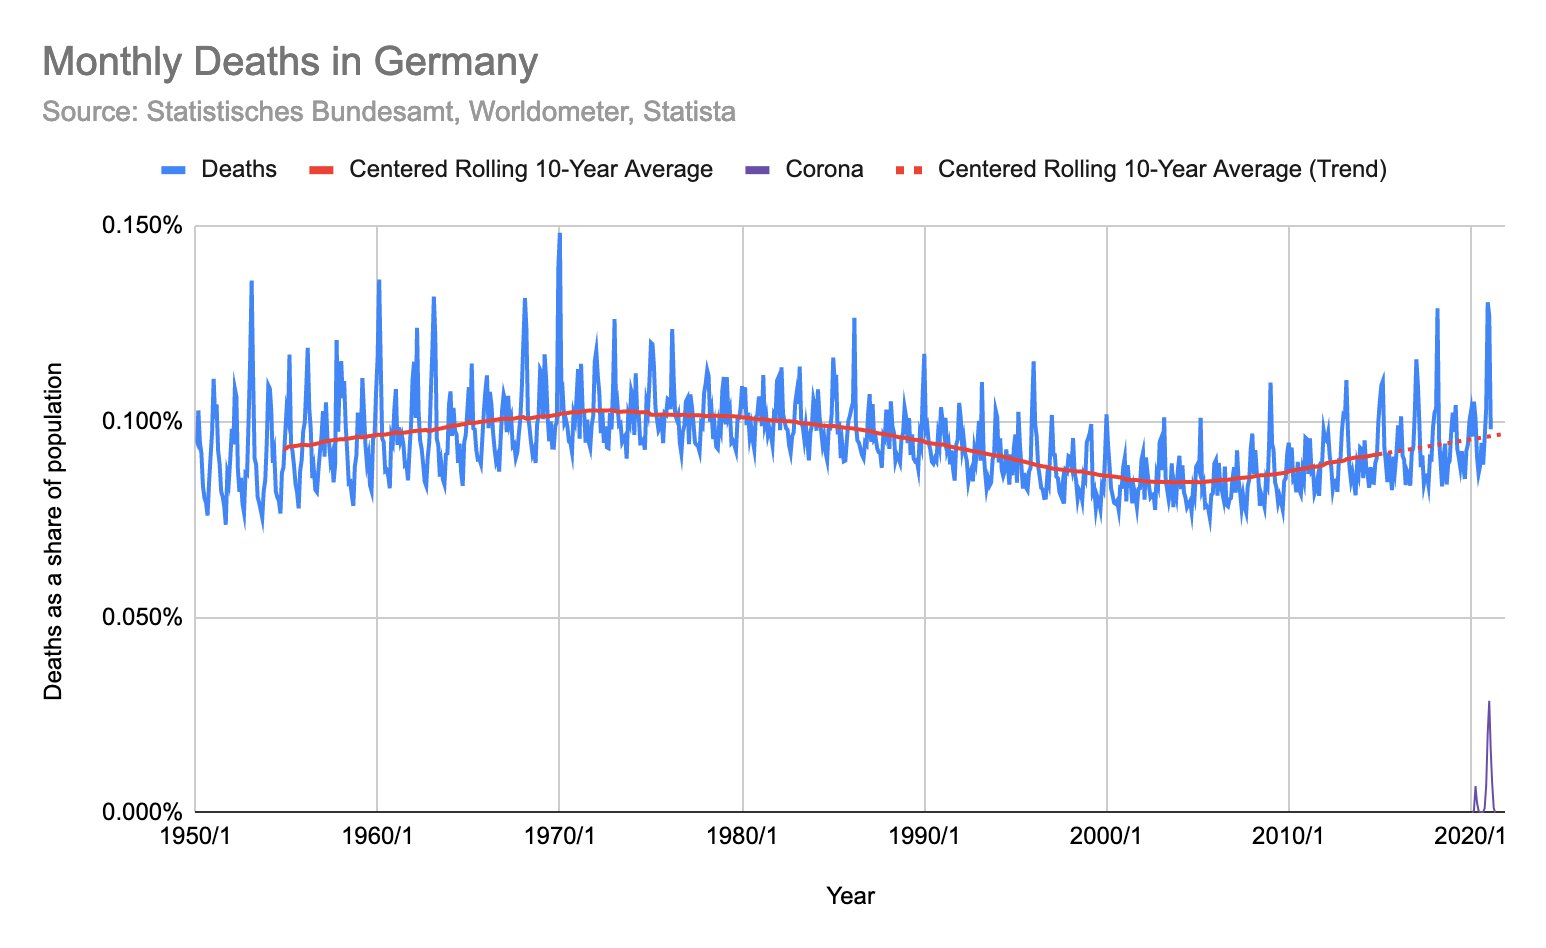
- Excess mortality: Overall, the pandemic has increased mortality by 5% to 25% in most Western countries. In some countries, up to 30% of additional deaths have been caused not by covid, but by indirect effects of the pandemic and lockdowns (including drug overdose deaths).
- Antibodies: By the end of 2020, between 10% and 30% of the population in most Western countries had coronavirus antibodies. In India and some Latin American countries, coronavirus infection prevalence reached up to 75% by the summer of 2021.
- Symptoms: About 30% of all infected persons show no symptoms. Overall, about 95% of all people develop at most mild or moderate symptoms and do not require hospitalization. Early outpatient treatment may significantly reduce hospitalizations.
- Long covid: Up to 10% of symptomatic people experience post-acute or long covid, i.e. covid-related symptoms that last several weeks or months. Long covid may also affect younger and previously healthy people whose initial course of disease was rather mild.
- Transmission: Indoor aerosols appear to be the main route of transmission of the coronavirus, while outdoor aerosols, droplets, as well as most object surfaces appear to play a minor role. The coronavirus season in the northern hemisphere usually lasts from November to April.
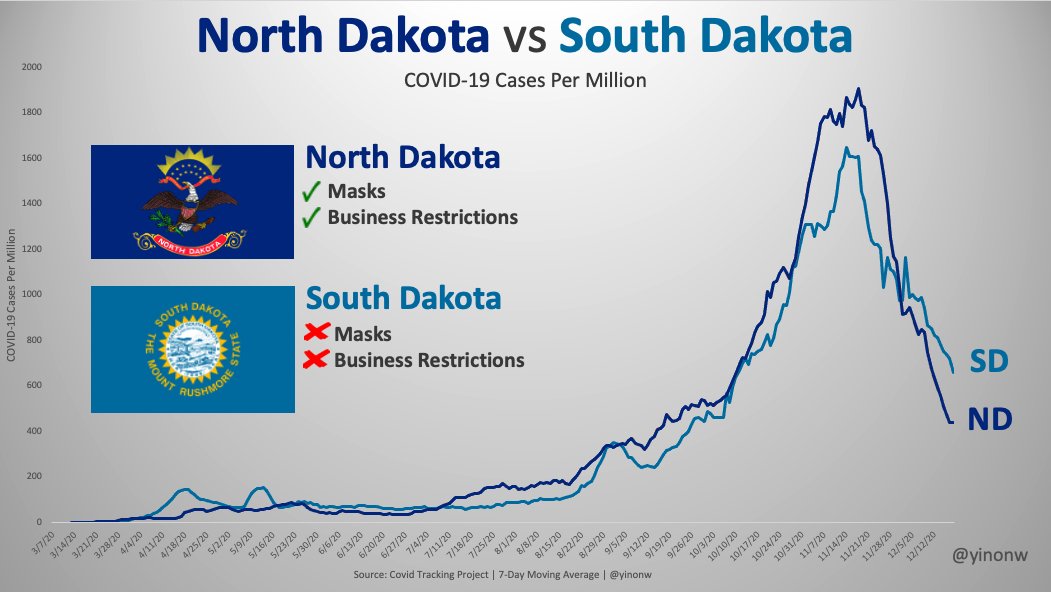
- Masks: There is still little to no scientific evidence for the effectiveness of face masks in the general population, and the introduction of mandatory masks couldn’t contain or slow the epidemic in most countries. If used improperly, masks may increase the risk of infection.
- Children and schools: In contrast to influenza, the risk of disease and transmission in children is rather low in the case of covid. There was and is therefore no medical reason for the closure of elementary schools or other measures specifically aimed at children.
- Contact tracing: A WHO study of 2019 on measures against influenza pandemics concluded that from a medical perspective, contact tracing is “not recommended in any circumstances”. Contact tracing apps on cell phones have also proven ineffective in most countries.
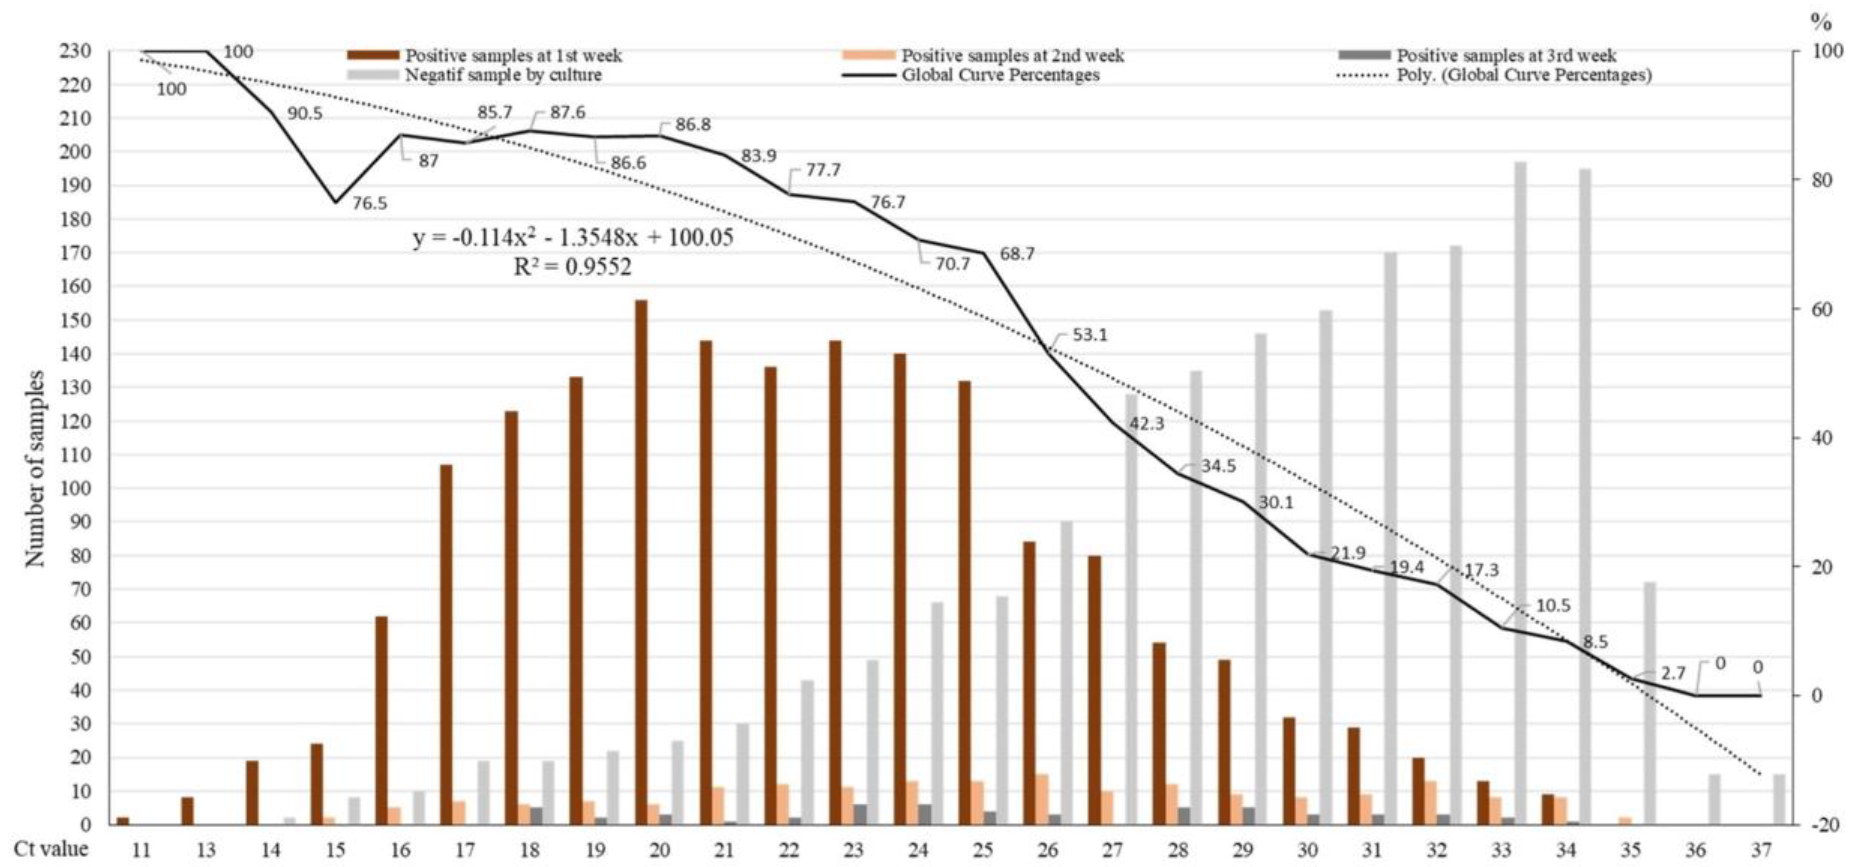
- PCR tests: The highly sensitive PCR test kits may in some cases produce false positive or false negative results or react to non-infectious virus fragments from a previous infection. In this regard, the so-called cycle threshold or ct value is an important parameter.
- Virus mutations: Similar to influenza viruses, mutations occur frequently in coronaviruses. Most of these mutations are insignificant, but some of them may increase the transmissibility, virulence or immune evasion of the virus to some extent.
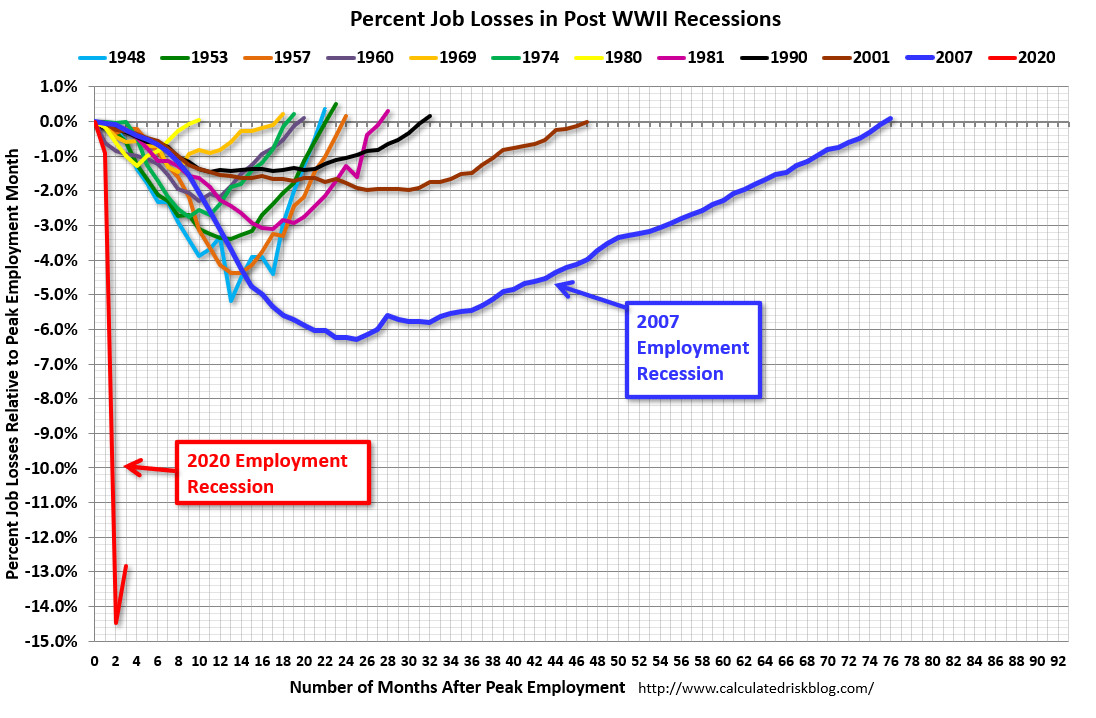
- Lockdowns: In contrast to early border controls, lockdowns have had no significant effect on the pandemic. According to the UN, lockdowns may put the livelihood of 1.6 billion people at acute risk and may push an additional 150 million children into poverty.
- Sweden: In Sweden, covid mortality without lockdown has been comparable to a strong influenza season and somewhat below the EU average. About 50% of Swedish deaths occurred in nursing homes and the median age of Swedish covid deaths was about 84 years.
- Media: The reporting of many media has been unprofessional, has increased fear and panic in the population and has led to a hundredfold overestimation of the lethality of the coronavirus. Some media even used manipulative pictures and videos to dramatize the situation.
- Virus origin: The origin of the new coronavirus remains unknown, but the best evidence currently points to a covid-like pneumonia incident in a Chinese mine in 2012, whose virus samples were collected, stored and researched by the Wuhan Institute of Virology (WIV). Due to cooperations, some US labs may also have had access to these viruses.
- Surveillance: NSA whistleblower Edward Snowden warned that the coronavirus pandemic may be used to expand global surveillance. Many governments have restricted fundamental rights of their citizens and announced plans to introduce digital biometric vaccine passports.
Overview diagrams





Latest updates
Basics
General
- The Covid Vaccine War (December 2021)
- The Return of the Flu (November 2021)
- The WEF and the Pandemic (October 2021)
- Global Covid Mortality (September 2021)
- Variants: What’s next? (July 2021)
- Obesity and the pandemic (June 2021)
- The failure of PCR mass testing (June 2021)
- Pre-symptomatic transmission (June 2021)
- Covid versus the flu, revisited (March 2021)
- Lockdowns in China in 2021 (February 2021)
- Why Covid-19 is a “strange pandemic” (Sept. 2020)
Vaccines
- Covid Vaccines: A Reality Check (December 2021)
- Covid vaccine adverse events (December 2021)
- Israel: Highest infection rate in the world (Sept. 2021)
- Israel: Why is all-cause mortality increasing? (April 2021)
- Videos: Vaccines: Successes and Controversies (Dec. 2020)
Early Treatment
- The Ivermectin Debate (July 2021)
- Covid and anti-androgens (July 2021)
- Molnupiravir: Caution (October 2021)
- Severe covid: An autoimmune attack (July 2021)
- Is budesonide really effective against covid? (April 2021)
- Remdesivir: An Epidemic Failure (October 2020)
Face masks
- The Mask Folly in Retrospect (August 2021)
- Danish Mask Study: No Benefit (November 2020)
- WHO Mask Study Seriously Flawed (September 2020)
Other topics
- Judgment day: Sweden vindicated (Dec. 2021)
- Omicron Hits the Mutation Jackpot (Nov. 2021)
- Meanwhile in Australia (June 2021)
- The Censorship Pandemic (May 2021)
- On the “people collapsing in Wuhan” (April 2021)
- Lockdowns: Fewer Suicides in 2020? (April 2021)
Featured Video

The American Retreat from Vietnam
or go to
Aletho News Archives – Video-Images
From the Archives
Secret document reveals plans for civil war in Lebanon, Israeli false flags, and invasion
By Randi Nord | Geopolitics Alert | April 5, 2019
Beirut – During his visit with US Secretary of State, Mike Pompeo, Lebanese President Michael Aoun reportedly received a US-Israeli document detailing plans for creating a civil war in Lebanon with covert false flag operations and possible Israeli invasion.
Although the source of the document is Israeli and created in partnership with Washington, no one knows who presented it to Aoun. The Lebanese TV station, Al-Jadeed, initially reported the document on Lebanese TV and a video on its website. Geopolitics Alert translated the report for this article. … continue
Blog Roll
 Aletho News
- There Is A Drought in Academia: A Drought in Honest Research on the Subject of Drought and Other Weather Extremes
- Department of War Awards $20.7 Billion Contract to Raytheon for Air-to-Air Missiles
- ‘Distance yourselves from Israel’: IRGC urges US population to question govt policies
- America’s Greenland deal has a radioactive backstory
- The RAF Fairford ‘terror plot’: Unpacking escalation in the UK echo-chamber
- EU Council Advances Chat Control 2.0 Scanning Proposal
- Ex-Greek MEP files complaint against Israeli spyware firm over alleged Pegasus surveillance
- Troubling ideas throughout the Torah, Talmud, Mishneh Torah and Tanya
- ‘Grave, alarming’: Iran mission on Trump’s UNGA ‘annihilation’ threats
- Najaf airport to reopen to Iranian flights within 24 hours: Ambassador
- If Americans Knew
- New Report: “Scholasticide and Genocide in Gaza: Assessment, Testimonies and Legal Analysis”
- Ex-Biden officials are desperate for a Gaza scapegoat
- Israeli “settlers” Invade Al-Aqsa; Pour Boiling Water on 75-Year-Old
- Israel Has Kidnapped Another American Teenager
- US arms sales to Israel worth $21.6 billion in 20 months
- Three Palestinians Killed in Israeli Attacks on Gaza
- Revealed: German “Anti-Semitism Expert” Driving Crackdown on Palestine Solidarity is Former Israeli Spy
- Egypt’s Warning to Israel Before Oct 7
- Israel’s siege signals another cruel winter for 1.8 million Gazans – Daily Update
- Netanyahu Asked UAE Leader to Deny Report on Oct. 7 Warning in Secret Visit, Sources Say
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

