CDC Gives Incoming Refugees Nobel Prize-Winning Ivermectin
By Kelen McBreen | InfoWars | September 3, 2021
All Middle Eastern, Asian, North African, Latin American, and Caribbean refugees entering the U.S. since 2019 have been prescribed ivermectin.
The CDC recommendation advises doctors working for the International Organization for Migration (IOM), who screen refugees in their home countries, and American doctors who treat them when they arrive to prescribe both ivermectin and albendazole.
Since the CDC guidance was released pre-Covid, naysayers will point out the ivermectin was prescribed for parasites and not for Covid-19, and presume the drug probably doesn’t work against viral infections.
Ivermectin’s creators won a Nobel Prize in Medicine in 2015 for the drug’s ability to battle infections caused by roundworm parasites.
As Tokyo, Japan’s top health official Dr. Haruo Ozaki recently explained, “In Africa, if we compare countries distributing ivermectin once a year with countries which do not give ivermectin… I mean, they don’t give ivermectin to prevent Covid, but to prevent parasitic diseases… but anyway, if we look at Covid numbers in countries that give ivermectin, the number of cases is 134.4 per 100,000, and the number of death is 2.2 in 100,000.”
He continued, “Now, African countries which do not distribute ivermectin: 950.6 cases per 100,000 and 29.3 deaths per 100,000. I believe the difference is clear.”
Several studies show ivermectin actually is effective at treating Covid-19, but what this information truly exposes is the current media and government demonization campaign against it.
Despite media cries of “people eating horse paste” and several stories about an increase in poison control calls from people misusing the drug, the CDC has been giving it to refugees for at least two years.
By the way, a Fox 9 Minnesota story lists possible symptoms of an ivermectin “overdose” as “nausea, vomiting, diarrhea, decreased consciousness, hallucinations, seizures, coma, and death.”
However, not a single person in the United States has died from a Covid-related ivermectin overdose.
Plus, the majority of people resorting to the horse version of ivermectin are doing so because the attacks on the drug have convinced many doctors and pharmacies not to prescribe or carry it.
The establishment is even upset that celebrities like top podcast host Joe Rogan and “Cheers” star Kirstie Alley have touted the drug as helping them defeat Covid.
The CDC is obviously aware that the drug is safe for people to use as its physicians prescribe it to refugees just as tens of thousands of doctors across the U.S. are now giving it to patients for Covid.
So, why is mainstream media and a government agency like the FDA scaring Americans out of a treatment that could help them with the virus?
The FDA’s website explains, “Certain animal formulations of ivermectin such as pour-on, injectable, paste, and ‘drench,’ are approved in the U.S. to treat or prevent parasites in animals. For humans, ivermectin tablets are approved at very specific doses to treat some parasitic worms, and there are topical (on the skin) formulations for head lice and skin conditions like rosacea.”
Well, no doctors are prescribing ivermectin animal formulations to their patients, and the government and media both know this.
Perhaps it’s because the FDA, which is “virtually controlled by Pfizer” according to President Trump, is currently developing their own Covid drug to be taken twice a day alongside their vaccine.
Merck, the company that produces ivermectin, is also developing a drug to treat Covid which will make them much more money than the cheap antiviral ivermectin.
On June 9, Merck revealed that the U.S. government is paying the company $1.2 billion to supply 1.7 million courses of the new drug to federal government agencies.
Or, it could be that the Covid vaccines still being used under Emergency Use Authorization would no longer have that emergency approval if a legitimate low-risk treatment were available.
Follow the money and stop paying attention to establishment media.
Why all the fuss about Ivermectin?
By Brian C. Joondeph | American Thinker | September 3, 2021
First hydroxychloroquine, now ivermectin, is the hated deadly drug de jour, castigated by the medical establishment and regulatory authorities. Both drugs have been around for a long time as FDA-approved prescription medications. Yet now we are told they are as deadly as arsenic.
As a physician, I am certainly aware of ivermectin but don’t recall ever writing a prescription for it in my 30+ years’ medical career. Ivermectin is an anthelmintic, meaning it cures parasitic infections. In my world of ophthalmology, it is used on occasion for rare parasitic or worm infections in the eye.
Ivermectin was FDA approved in 1998 under the brand name Stromectol, produced by pharmaceutical giant Merck, approved for several parasitic infections. The product label described it as having a “unique mode of action,” which “leads to an increase in the permeability of the cell membrane to chloride ions.” This suggests that ivermectin acts as an ionophore, making cell membranes permeable to ions that enter the cell for therapeutic effect.
Ivermectin is one of several ionophores, others including hydroxychloroquine, quercetin, and resveratrol, the latter two available over the counter. These ionophores simply open a cellular door, allowing zinc to enter the cell, where it then interferes with viral replication, providing potential therapeutic benefit in viral and other infections.
This scientific paper reviews and references other studies demonstrating antibacterial, antiviral, and anticancer properties of ivermectin. This explains the interest in this drug as having potential use in treating COVID.
Does ivermectin work in COVID? I am not attempting to answer that question, instead looking at readily available information because this drug has been the focus of much recent media attention. For the benefit of any reader eager to report this article and author to the medical licensing boards for pushing misleading information, I am not offering medical advice or prescribing anything. Rather, I am only offering commentary on this newsworthy and controversial drug.
What’s newsworthy about ivermectin? A simple Google search of most medications describes uses and side effects. A similar search of ivermectin provides headlines of why it shouldn’t be taken and how dangerous it is.

YouTube screen grab
The Guardian describes ivermectin as horse medicine reminding readers considering taking the drug, “You are not a horse. You are not a cow”, saying it’s a medicine meant for farm animals. The FDA echoed that sentiment in a recent tweet, adding “Seriously, y’all. Stop it,” their word choice making it obvious who the tweet was directed to.
Perhaps the FDA didn’t realize that Barack and Michelle Obama often used the term “y’all” and that some might construe the FDA tweet as racist.
The FDA says ivermectin “can be dangerous and even lethal,” yet they approved it in 1998 and have not pulled it from the market despite it being “dangerous and lethal.” Any medication can be “dangerous and lethal” if misused. People have even overdosed on water.
It is true that ivermectin is also used in animals, as are many drugs approved for human use. This is a list of veterinary drugs with many familiar names of antibiotics, antihypertensives, and anesthetics commonly used by humans. Since these drugs are used in farm animals, should humans stop taking them? That seems a rather unscientific argument against ivermectin, especially coming from the FDA.
And healthcare professionals are not recommending or prescribing animal versions of ivermectin as there is an FDA-approved human formulation.
Does ivermectin work against COVID? That is the bigger question and worthy of investigation, rather than reminding people that they are not cows.
A study published several months ago in the American Journal of Therapeutics concluded,
Meta-analyses based on 18 randomized controlled treatment trials of ivermectin in COVID-19 have found large, statistically significant reductions in mortality, time to clinical recovery, and time to viral clearance. Furthermore, results from numerous controlled prophylaxis trials report significantly reduced risks of contracting COVID-19 with the regular use of ivermectin. Finally, the many examples of ivermectin distribution campaigns leading to rapid population-wide decreases in morbidity and mortality indicate that an oral agent effective in all phases of COVID-19 has been identified.
To my knowledge, these 18 studies have not been retracted, unlike previous studies critical of hydroxychloroquine which were ignominiously retracted by prestigious medical journals like The Lancet and the New England Journal of Medicine.
Yet the medical establishment refuses to even entertain the possibility of some benefit from ivermectin, castigating physicians who want to try it in their patients. 18 studies found benefit. Are they all wrong?
Podcaster Joe Rogan recently contracted COVID and recovered within days of taking a drug cocktail including ivermectin. Was it his drug cocktail, his fitness, or just good luck? Impossible to know but his experience will keep ivermectin in the news.
Highly unvaccinated India had a surge in COVID cases earlier this year which abruptly ended following the widespread use of ivermectin, over the objections and criticism of the WHO. In the one state, Tamil Nadu, that did not use ivermectin, cases tripled instead of dropping by 97 percent as in the rest of the country.
This is anecdotal and could have other explanations but the discovery of penicillin was also anecdotal and observational. Good science should investigate rather than ignore such observations.
The Japanese Medical Association recently endorsed ivermectin for COVID. The US CDC cautioned against it.
There is legal pushback as an Ohio judge ordered a hospital to treat a ventilated COVID patient with ivermectin. After a month on the ventilator, this patient is likely COVID free and ivermectin now will have no benefit, allowing the medical establishment to say “see I told you so” that it wouldn’t help.
By this point, active COVID infection is not the issue; instead, it is weaning off and recovery from long-term life support. The early hydroxychloroquine studies had the same flaw, treating patients too late in the disease course to provide or demonstrate benefit.
These drugs have been proposed for early outpatient treatment, not when patients are seriously ill and near death. Looking for treatment benefits in the wrong patient population will yield expected negative results.
Given how devastating COVID can be and how, despite high levels of vaccination in countries like the US, UK, and Israel, we are seeing surging cases and hospitalizations among the vaccinated, we should be pulling out all the stops in treating this virus.
Medical treatment involves balancing risks and benefits. When FDA-approved medications are used in appropriate doses for appropriate patients, prescribed by competent physicians, the risks tend to be low, and any benefit should be celebrated. Instead, the medical establishment, media, and regulatory authorities are taking the opposite approach. One has to wonder why.
No Animal Studies for the Vaccines
By Martin Armstrong | ArmstrongEconomics | September 2, 2021
I find it extremely unbelievable that nobody will investigate this entire scam for what it is. The people behind the vaccines should be dragged in to testify what is going on. Moderna has admitted it took them only 2 days to create the vaccine. In Texas, they are trying to launch a criminal investigation. The FDA is no longer trustworthy, for the normal time to get anything approved is 12 years. What has been released in less than one year with no animal studies? There has been NO TESTING to determine side effects on pregnancy, fertility, or lactation.
It is just stunning that we have politicians REFUSING to look at anything, probably because they are too busy counting their bribes. The White House said under NO condition would they ever fire Fauci, meaning under NO condition will they investigate anyone.
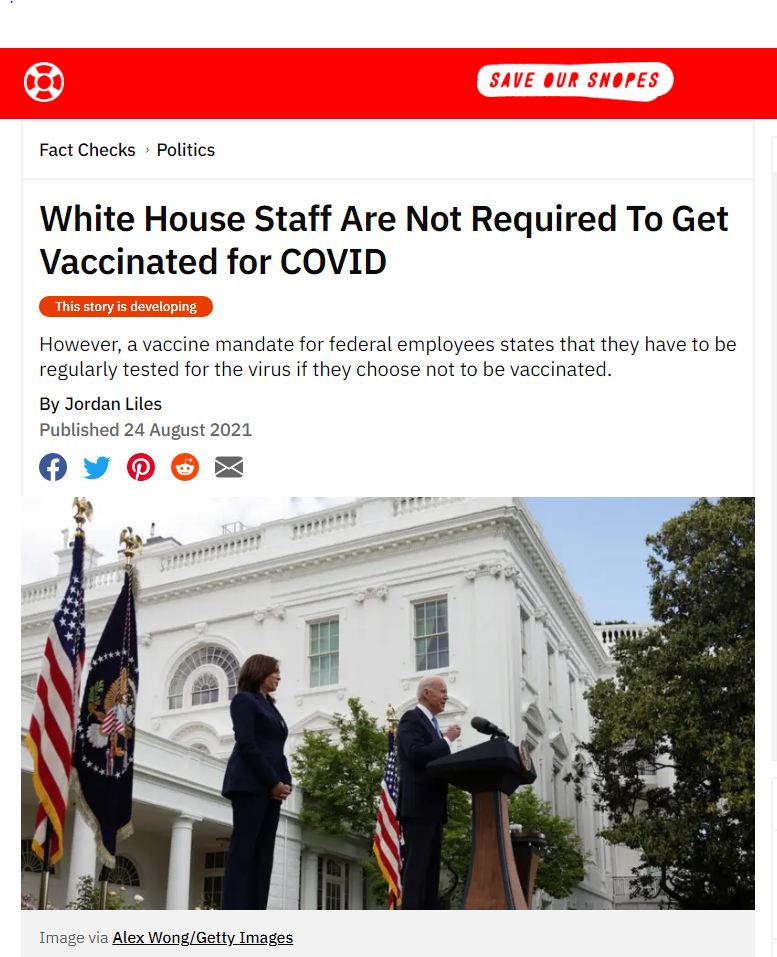
Meanwhile, even the notorious corrupt Snopes had to admit this is TRUE. Despite demanding everyone gets vaccinated, the White House said its own staff DOES NOT need to be vaccinated provided they are routinely checked. So why is the White House the entire exception? Even the military is demanding 100% compliance. Meanwhile, the White House has demanded everyone else receive vaccinations or lose their job.

The fact that they have skipped animal trials is very disturbing. When the government is part of the conspiracy against the public, we will NEVER know the truth about anything. Jack Dorsey has been especially protective of the narrative. Nobody is allowed to question the government no matter what.
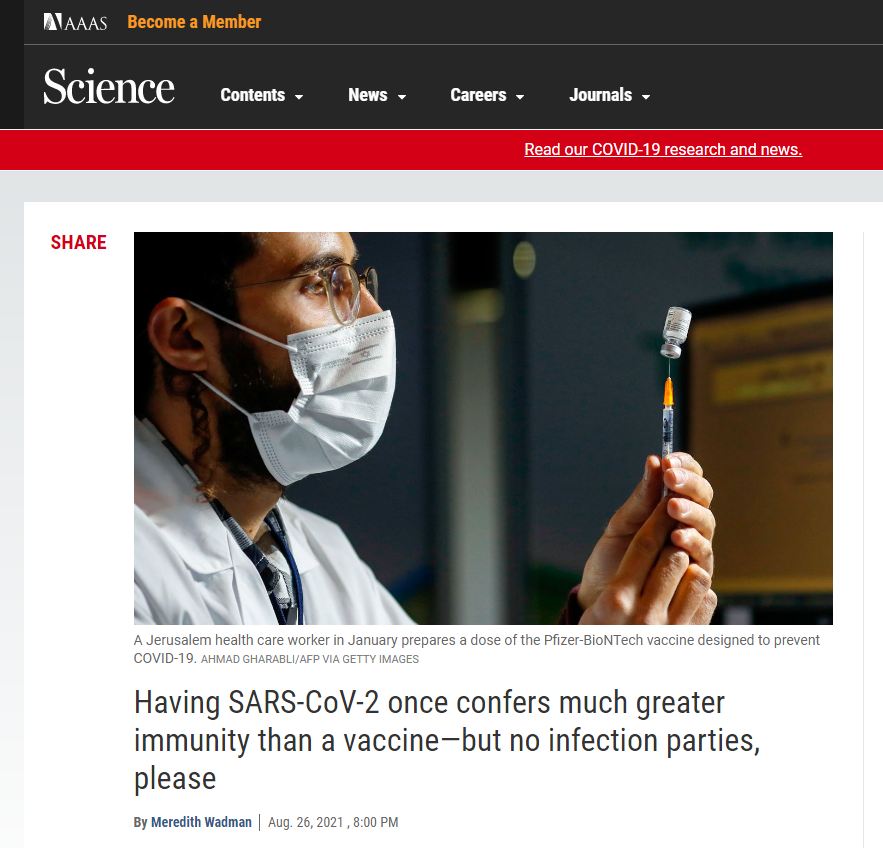
Then there are studies revealing that natural immunity to COVID is 13 times better than the vaccines. They try to bury such studies, and they also try to ensure that they are not peer-reviewed in order to discredit them. The Science journalist Alex Berenson was permanently suspended from Twitter one day after his tweets that reported an Israeli study that making this finding that natural immunity from a prior Covid-19 infection is 13 times more effective than vaccines against the delta variant. Twitter is now acting against the very basis of free speech, which is threatening people’s lives. I would love to see Twitter taken down, for they are clearly now responsible for the deaths of many people from vaccine injuries.

To show that this is one giant cover-up, OSHA has instructed employers NOT TO REPORT vaccine injuries suffered by employees if they only “recommend” the shots. Many employers with more than 10 employees are required to keep a record of serious work-related injuries and illnesses. Nobody should volunteer to be vaccinated to satisfy an employer, for you will not be covered for any injury or loss of pay, and you could be fired for not showing up to work for a period of time. However, if employers mandate vaccines to work, then the vaccine injuries should become subject to reporting, lawsuits, and workman’s comp claims.
UK Schoolchildren To Be Covid Vaxxed With Or Without Parental Consent
ALERT: ALL PARENTS IN U.K. WITH CHILDREN AGED 12 – 15 years
By Dr. Mike Yeadon | Health Impact News | August 26, 2021
I’ve just been informed via someone senior in the vaccination authorities that they will begin VACCINATING ALL SCHOOL CHILDREN AGED 12 – 15 years old STARTING SEPTEMBER 6th 2021.
WITH OR WITHOUT YOUR CONSENT.
Children are at no measurable risk from SARS-CoV-2 & no previously healthy child has died in U.K. after infection. Not one.
The vaccines are NOT SAFE. The USA reporting system VAERS is showing around 13,000 deaths in days to a few weeks after administration. A high % occur in the first 3 days. Around 70% of serious adverse events are thromboembolic in nature (blood clotting- or bleeding-related).
We know why this is: all of the gene-based vaccines cause our bodies to manufacture the virus spike protein & that spike protein triggers blood coagulation.
The next most common type of adverse events are neurological.
Death rates per million vaccinations are running everywhere at around 60X more than any previous vaccine.
Worse, thromboembolic events such as pulmonary embolisms, appear at over 400X the typical low rate after vaccination.
These events are serious, occur at a hideously elevated level & are at least as common in young people as in elderly people. The tendency is that younger people are having MORE SEVERE adverse events than older people.
There is literally no benefit whatsoever from this intervention. As stated, the children are unquestionably NOT AT RISK & vaccinating them WILL ONLY RESULT IN PAIN, SUFFERING, LASTING INJURIES AND DEATH.
Children rarely even become symptomatic & are very poor transmitters of the virus. This isn’t theory. It’s been studied & it pretty much doesn’t happen that children bring the virus into the home. In a large study, on not one occasion was a child the ‘index case’ – the first infected person in a household.
So if you’re told “it’s to protect vulnerable family members”, THAT IS A LIE.
The information emerging over time from U.K. & Israel is now showing clearly that the vaccines DO NOT EVEN WORK WELL. If there’s any benefit, it wanes.
Finally, the vaccines ARE NOT EVEN NECESSARY. There are good, safe & effective treatments.
IF YOU PERMIT THIS TO GO AHEAD I GUARANTEE THIS: THERE WILL BE AVOIDABLE DEATHS OF PERFECTLY HEALTHY CHILDREN, and severe illnesses in ten times as many.
And for no possible benefit.
KNOWING WHAT I KNOW FROM 40 years TRAINING & PRACTISE IN TOXICOLOGY, BIOCHEMISTRY & PHARMACOLOGY, to participate in this extraordinary abuse of innocent children in our care can be classified in no other way than MURDER.
It’s up to you. If I had a secondary school age child in U.K., I would not be returning them to school next month, no matter what.
The state is going to vaccinate everyone. The gloves are off. This has never been about a virus or public health. It’s wholly about control, totalitarian & irreversible control at that, and they’re nearly there.
PLEASE SHARE THIS INFORMATION WIDELY.
With somber best wishes,
Mike
ACIP vote yesterday, after deceitful CDC briefings, removes liability from Comirnaty and opens door to mandates
By Meryl Nass, MD | August 31, 2021
In a nutshell: Yesterday CDC asked its advisory committee to “recommend” the Comirnaty vaccine for 16 and 17 year olds. And it agreed, unanimously. Or pusillanimously.
The vote may seem silly or superfluous, because it had already been recommended for this age group as an EUA.
But this vote was anything but superfluous. This seemingly minor recommendation, which did not get headlines, moves the licensed Comirnaty vaccine from a place where the manufacturer is legally liable for injuries, to a berth within the Childhood Vaccine Injury Compensation Program, for which there is no manufacturer liability. Instead a $0.75 excise tax is charged per dose, which goes into a fund administered by DHHS to pay for injuries, if one is lucky enough to convince the special masters (judges) in the program that a vaccine caused your injury. Once a vaccine is recommended for children, its liability is waived no matter who receives it.
But the important part is that once this process is complete (which I expect to be only a very few weeks), Pfizer can roll out stocks of the licensed vaccine while still having its liability waived. That means that the loophole I told you about last week is being backfilled by the USG, with the help of the supine and spineless ACIP committee members, and will soon disappear.
I say spineless with true conviction, because the briefings they received yesterday were a load of fraud and hogwash. Yet no one challenged the data nor the conclusions. It is hard to believe that the lot of them are really that stupid that they believed what they heard. It is also hard to believe that none of them had a conflict of interest, which they all asserted along with their vote.
Furthermore, no one ever actually said why the vote was held: which was for liability purposes, nor that the vote would lead to mandates, which could not be implemented under the EUA.
So, it is disappointing.
Children’s Health Defense went to court today in Tennessee to challenge the FDA on issuing both a license and EUA for the same product. AFLDS also went to court today in Colorado challenging the mandate. More on these cases later.
The Greatest Scientific Fraud Of All Time — Part XXVIII
By Francis Menton | Manhattan Contrarian | August 26, 2021
What I refer to as the “Greatest Scientific Fraud Of All Time” is the systematic alteration of historical world temperatures to make it appear, falsely, that the most recent months and years are the “warmest ever.” The basic technique of the fraud is the artificial lowering of previously-reported data as to world temperatures in earlier years, in order to erase earlier warmth and amplify the apparent warming trend. This is the 28th post in this series. The previous post in the series appeared on October 5, 2020. To view all 27 prior posts, you can go to this composite link.
The deliverable products of the temperature fraudsters are purported charts of world temperatures derived from a thermometer-based surface record (called GHCN, or Global Historical Climate Network), generally going back to about 1880. The charts are engineered to appear in an iconic “hockey stick” shape, with relatively flat earlier years followed by a sharply rising “blade” in the most recent years.
Every few years the government (this is a joint effort of NASA and NOAA) comes out with a new version of these data. The latest version is called GHCN version 4, which began in 2018. Here is a chart from the Columbia University website (the NASA branch involved in this project, known as the Goddard Institute of Space Studies, is located on the Columbia campus in uptown Manhattan) showing a side-by-side comparison of the version 3 and version 4 GHCN data. Both show the famous hockey stick shape, although version 4 increases the recent uptick somewhat.

My October 5, 2020 post mainly summarized a piece by Tony Heller that had appeared on October 1 of that year. Heller’s piece focused specifically on alterations to the temperature record of the U.S., as opposed to the entire world. Heller provided links to earlier and later NASA/GISS data reports, clearly showing that temperatures originally reported for earlier years had subsequently been lowered to enhance the warming trend and to make the most recent years appear to be the “warmest” — in spite of the fact that if temperatures previously reported had been correct, then earlier years including 1953, 1934, and 1921 had actually been warmer than the most recent years.
Heller also noted, as I have many times, that NASA and NOAA make no secret of the fact that they are systematically altering and lowering earlier-year temperatures,
Reality is that the data alterations are no secret, and that NOAA and NASA acknowledge that they do it.
The problem is not that the alterations are a secret, but that they are opaque. You would think that it would be impossible for earlier-year temperatures to change at all, let alone that they would systematically change in a way that just happens to enhance the desired narrative of the promoters of the global warming scare. The justifications for the alterations appear to be just so much bafflegab, completely lacking in specific rationales for each change that you would think would be required — particularly given that these temperature charts are being used as a basis for a multi-trillion dollar fundamental transformation of the world energy economy.
Anyway, into this mix now comes a young Japanese woman named Kirye, who has taken up the Heller tradition of compiling and publishing instances of government alteration of the data that underlie the NASA/NOAA temperature charts. Kirye posts periodically on Heller’s website, known as RealClimateScience, and also at the NoTricksZone site. A couple of days ago (August 24) Kirye had a post at NoTricksZone titled “Adjusting To Warm, NASA Data Alterations Change Cooling To Warming In Ireland, Greece.” Adding to Heller’s work, this post goes outside the U.S. to look at two European countries that ought to have good and reliable temperature data. The post specifically focuses on the period 1988 to present, which is the period of the supposed sharp uptick in temperatures represented by the “blade” of the hockey stick in the NASA/NOAA charts above.
What Kirye finds is that in both Ireland and Greece, NASA and NOAA have altered the data to turn a cooling trend into a warming trend for the 1988-2020 period. Here is her comparison of the “unadjusted” data for Ireland compared to the “GHCN version 4” currently being reported:

Kirye gives a link for these graphs to the NASA/GISS website. That is where she got the information. The NASA/GISS site has a map of the world with a little dot for each station, and if you click on any station you can get a plot courtesy of NASA that shows both the “unadjusted” and “version 4” temperature series for that station. Kirye has taken both versions straight from NASA itself. It’s just that only when you combine and present the data the way Kirye does do you realize that the bureaucrats have systematically altered the temperature trend for an entire country from down to up. Suddenly you clearly see that the entire apparent upward trend consists of unspecified “adjustments.” The same applies for both Ireland and Greece.
Can they even attempt to justify what they have done? At the same NASA/GISS page linked by Kirye, I find a further link saying “For details see FAQ.” Maybe I can find the answer here? So I followed that link, and another, and come to the end of my road at this document titled “FAQs on the Update to Global Historical Climatology Network–Monthly Version 3.2.0.” This document specifically relates to the version of GHCN just preceding version 4, but I have no reason to think that the basic methodology has changed. Here is an extremely revealing “FAQ” with the relevant part of its answer:
Why is the century‐scale global land surface trend higher in version 3.2.0?
The PHA software is used to detect and account for historical changes in station records that are caused by station moves, new observation technologies and other changes in observation practice. These changes often cause a shift in temperature readings that do not reflect real climate changes. When a shift is detected, the PHA software adjusts temperatures in the historic record upwards or downwards to conform to newer measurement conditions. In this way, the algorithm seeks to adjust all earlier measurement eras in a station’s history to conform to the latest location and instrumentation. The correction of the coding errors greatly improved the ability of the PHA to find these kinds of historic changes. As a result, approximately twice as many change points (inhomogeneities) were detected in v3.2.0 than in v3.1.0. . . .
Study that a little bit and think about what they are saying. There can be “station moves” or “new observation technologies” that can cause a “shift in temperature readings.” Fair enough. So has anybody contacted any of the Irish stations to find out if they have had a “station move” or “new observation technology” or anything like that since 1988? Absolutely not! Instead, they have a computer algorithm detect these things — or maybe invent them. The algorithm supposedly looks for “shifts.” So suppose readings at a particular station have somehow shifted to lower temperatures. Could it be that temperatures are reading lower because it got cooler? Obviously that does not fit the narrative. Time to declare a “shift.” Now, instead of reporting the cooling trend that is coming from the thermometers, you can adjust the earlier temperatures downward to reflect “new observation technology” or some such never-specified thing.
Note on Kirye’s dynamic graph that every single one of the stations in Ireland has had its trend adjusted from down to up by these computer algorithms. Did they all have station moves and/or “new observation technologies”? NASA doesn’t even pretend to have checked.
Take a look also at the “unadjusted” Irish plots on Kirye’s graph. Can you spot the supposed “shifts” that support having some computer come in and re-write the earlier temperatures to make the overall trend change from down to up?
At the end of the linked NASA document is a further link where you can supposedly get the computer code used for making what they call the “homogeneity corrections.” However, when I try that I don’t get anything I can open.
Anyway, this is what passes for “science” in the field of climatology.
Now they tell us … repeat Covid shots for the forseeable future
By Meryl Nass, MD | August 29, 2021
Extraordinary admissions. Extraordinary facial expressions. I typed exactly what she said:
“Booster doses, repeat doses will be part of it… I can assure you that the Commonwealth government has purchased large quantities of vaccine into 2022 and this will be a regular cycle of vaccination and revaccination as we learn more aabout when immunity wanes”
— Razorback1111 (@razorback11111) August 30, 2021
The Latest Paper From Neil Ferguson et al. Defending the Lockdown Policy is Out of Date, Inaccurate and Misleading

By Mike Hearn • The Daily Sceptic • August 24, 2021
Neil Ferguson’s team at Imperial College London (ICL) has released a new paper, published in Nature, claiming that if Sweden had adopted U.K. or Danish lockdown policies its Covid mortality would have halved. Although we have reviewed many epidemiological papers on this site, and especially from this particular team, let us go unto the breach once more and see what we find. The primary author on this new paper is Swapnil Mishra.
The paper’s first sentence is this:
The U.K. and Sweden have among the worst per-capita Covid mortality in Europe.
No citation is provided for this claim. The paper was submitted to Nature on March 31st, 2021. If we review a map of cumulative deaths per million on the received date then this opening statement looks very odd indeed:
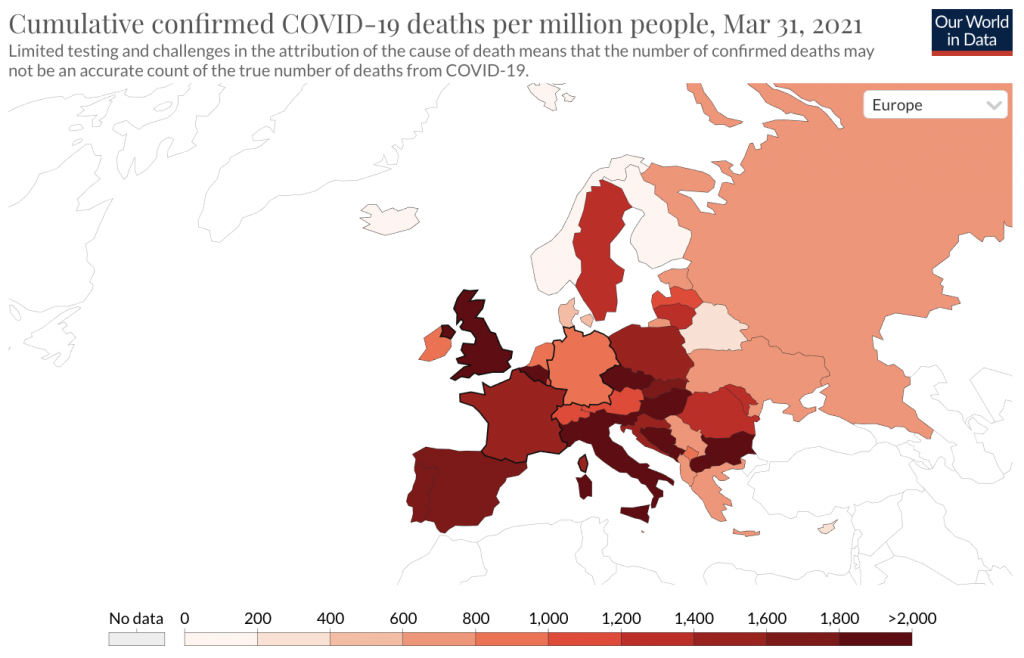
Sweden (with a cumulative total of 1,333 deaths/million) is by no means “among the worst in Europe” and indeed many European countries have higher totals. This is easier to see using a graph of cumulative results:
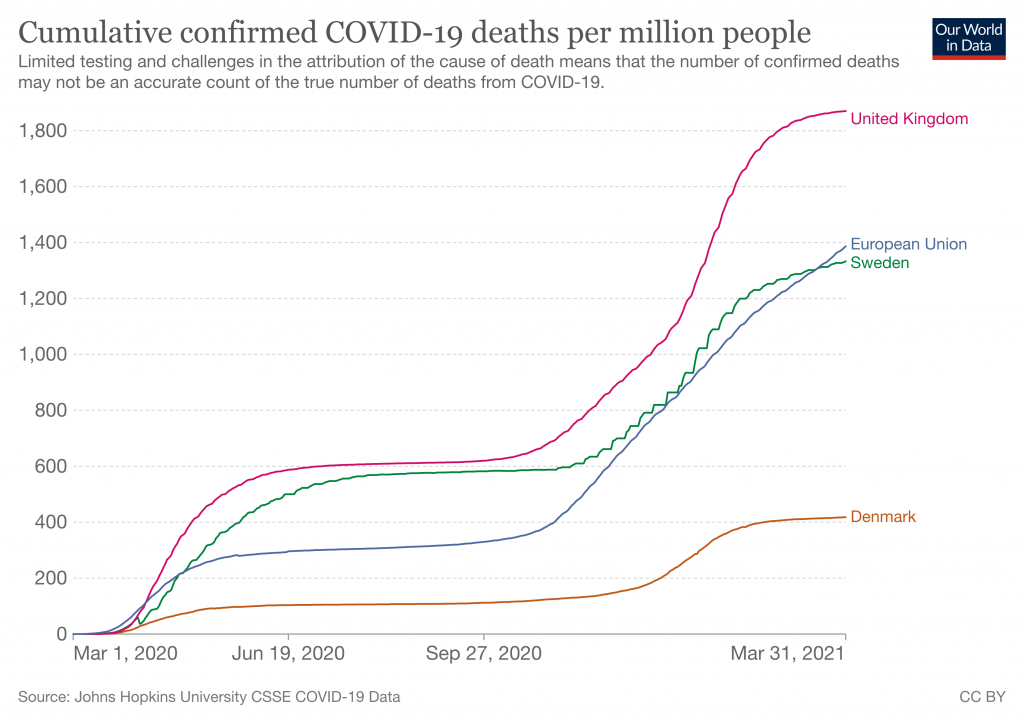
But that was in March, when the paper was submitted. We’re reviewing it in August because that’s when it was published. Over the duration of the journal’s review period this statement – already wrong at the start – became progressively more and more incorrect:
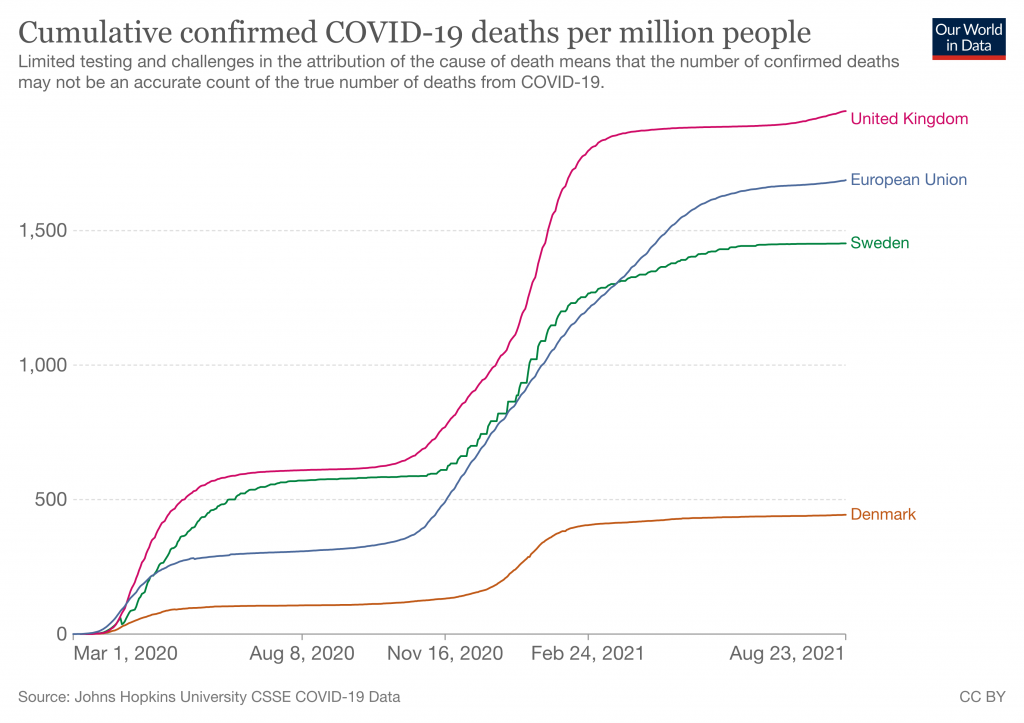
As always, we must note that these ‘death’ graphs can be heavily affected by testing levels, because Covid deaths are defined as any death within 28 days of a positive test. The U.K. tests much more than Sweden does. But putting that to one side, Sweden by now has significantly better results than the rest of the E.U. What’s going on here? A likely explanation is that although the paper was submitted in March it was actually written some time last year, probably starting around the end of the summer and finishing up in August. There then followed a strange many month gap before they submitted it, and then many more months were added by the glacial peer review process journals use. We can see evidence of this timeline in the abstract, where they say:
We use two approaches to evaluate counterfactuals which transpose the transmission profile from one country onto another, in each country’s first wave from March 13th (when stringent interventions began) until July 1st, 2020.
More evidence comes from the upload dates on the released code, which is from 10 months ago. In other words, Nature is publishing a paper about the fast-moving coronavirus situation that builds its entire case on obsolete data more than a year old, without explicitly noting that anywhere. In July 2020, Sweden and the U.K. did indeed have worse results than the rest of the E.U. However as we now know, this meant nothing and a year on the data looked very different.
Why did ICL wait so long before submitting this paper to Nature? No obvious explanation occurs. And why didn’t anyone notice that the claims were no longer true? Not for the first time, it appears nobody can actually be reading these papers adversarially before publication. Time and again we see that at major scientific journals the lights are on, but nobody’s home.
Seeing this made me wonder if they were once more engaging in a favourite trick of this team, by using Verity et al.‘s obsolete infection:fatality ratio estimates from January 2020. And indeed they are:
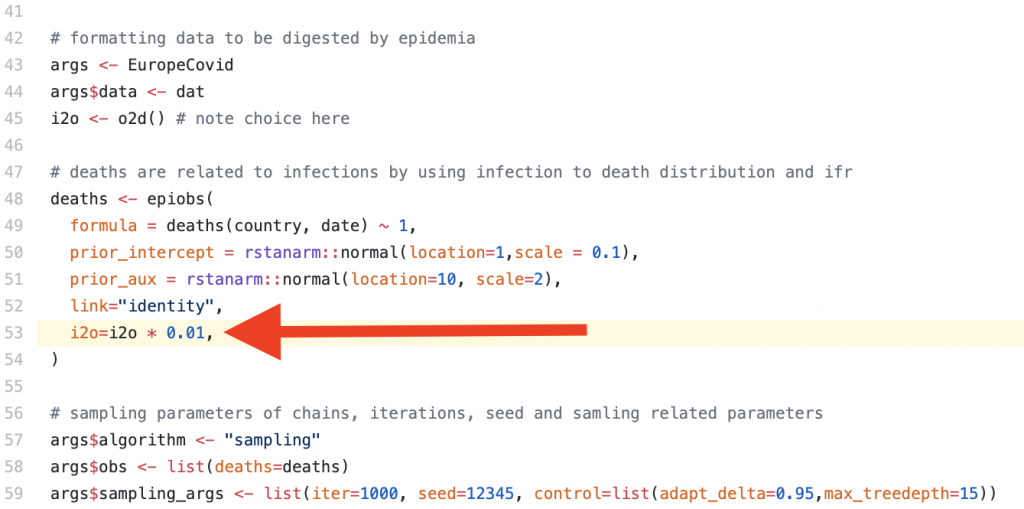
The idea that 1% of all SARS-CoV-2 infections would lead to death was later disputed as being ~4x too high by a meta-study of seroprevalence data published by the WHO. This newer estimate was based on far larger sample sizes, and serosurveys give an ability to detect people who recently had mild disease without getting tested or reporting it at the time. It’s thus a much more scientifically robust method of IFR estimation than Verity’s paper, which being written very early on had to rely on media reports and questionably reliable information coming out of China. As the authors discuss in the supplementary material, using a lower IFR (they try 0.5) means that the U.K.’s predicted mortality from adopting the Swedish strategy drops significantly due to the changed impact of herd immunity.
Who is responsible for this situation? Nature appears to be knowingly publishing a paper on Covid that makes claims in the present tense, but which is in reality so out of date that the very first sentence is factually false. This is not merely useless but actively damaging because non-academic readers (i.e., politicians and public health officials) will reasonably assume that claims published by scientists about Covid in August 2021 were actually written in August and have some relevance to the current situation. Nowhere is it explicitly stated at what time the analysis was believed to be accurate: it must instead be inferred from the choice of datasets and audit trails left on the source code hosting site they use.
Overall approach
Moving on. What does the model actually do?
The core concept is to try and calculate the changing infectiousness of SARS-CoV-2 for each of the U.K., Sweden and Denmark over time, then ‘graft’ the generated timeseries for R(t) onto the other countries. As is typical for this team, the authors assume that changes in Rt are driven only by government interventions or voluntary behavioural changes, and thus by transposing Rt onto other countries they claim to be calculating what would have happened if different countries had adopted each other’s policies. They try two different approaches to this, an ‘absolute’ and a ‘relative’ approach.
There are many problems with this methodology.
The study of only the U.K., Sweden and Denmark has no scientific basis. Why Denmark and not, say, France? This selection is very obviously politically motivated. In fact, the entire paper is basically a policy paper designed to influence politicians, not answer any question about viruses that a real scientist might ask.
With the benefit of 2021 hindsight we can argue persuasively that lockdowns had no real impact on Covid. The most recent and effective demonstration of that was the U.K.’s ‘Freedom Day’ in which cases dropped off a cliff just days after restrictions were relaxed, in defiance of the warnings of “international health leaders” that this would be “foolish” and “unethical”, a “threat to the world”, etc. There have been many other such events and analyses of global datasets show no correlation between lockdowns and health outcomes. Thus their underlying assumption that social policy is responsible for different outcomes is wrong. In fact, although they are well aware that there must be many factors influencing mortality outcomes, they explicitly disregard all of them: “While we cannot fully encompass the myriad of differences between each country, our analysis is nonetheless informative on best practice for control of future waves of the Covid pandemic.”
Despite asserting that their analysis can tell lawmakers what to do in future epidemics, they later admit that “our counterfactual scenarios should be interpreted as a exchange of both population behaviour and government policy between donor and recipient countries“. This is important for them to admit because they tried to explain why Covid has varying infectiousness in different countries by reference to “cultural differences“, which they boil down to a single statistic about the proportion of single person households in each country. But this is illogical nonsense. Even if we (wrongly) assume that all differences in observed outcomes are to do with policy and culture, governments cannot magically make the U.K. population become Danish or vice-versa. Any analysis that assumes this and claims to be “informative on best practice” is wrong and should have been dropped during peer review.
The paper has another difficulty with being “informative“. Although the authors propose two different approaches to try and answer the same underlying question, the two approaches give totally different answers. For example: “If Denmark followed U.K. policies, our relative approach estimates that mortality would not have been markedly different, although our absolute approach implies that mortality would have been more than twice that observed.” Their calculations aren’t even consistent with each other, yet the paper provides no specific recommendation on which approach is supposed to yield the best answer.
Other problems include an inability to actually calculate Rt from death data (“the high variance of this distribution leads to high uncertainty in Rt estimates“), even though their entire analysis is based on the presumed integrity of that calculation, and an implausibly high sensitivity to the exact starting date of policy changes (“a three-day difference in the introduction of measures can lead to twofold differences in mortality“). The strength of this connection in their model is absurd and would appear to be strongly motivated by ICL’s attempted rewriting of history to one of: “If only the Government had listened to us sooner everything would have been far better.”
Conclusion
Given the history of this department, it’s no surprise that ICL is still churning out delusional and misleading epidemiology papers. They will continue doing so for as long as they’re funded. Analysing each and every one is a futile effort due to the sheer scale at which academia operates (e.g. this paper alone has 19 authors). But we can nonetheless learn some more about bad science by reading them. This paper shows all the usual hallmarks of an academic sector that’s gone off the rails:
- A grotesque level of data cherry picking.
- A publishing process so slow that the claims are entirely wrong on the date of publication, and wrong from literally the first sentence.
- A delusional belief that their work is “informative” to policy makers, despite implicitly arguing that entire societies can be transplanted from one country to another.
Who is ultimately responsible for stopping this? It must be the funders, who for this paper include:
- The National Institute for Health Research
- The Bill and Melinda Gates Foundation
- The U.K. Medical Research Council
- Community Jameel (a Saudi family foundation)
- Microsoft, who donated free compute time on Azure
- And finally, universities and other institutions who subscribe to Nature despite its history of publishing misleading papers
The theme here is that none of these organisations is paying close attention to what’s actually being written, apparently including the journals and peer reviewers. For funders, giving away money is not the means but the end. Until research is funded by people who actually care about the utility of the results our society will continue to be flooded with highly evolved scientism, of which the output of the ICL Epidemiology Department is a textbook example.
Mike Hearn is a former Google software engineer. You can read his blog here.
Featured Video

Broke Princes: Saudi Arabia’s Powder Keg
or go to
Aletho News Archives – Video-Images
From the Archives
Registered Israeli foreign agent driving contrived campus antisemitism crisis
By Wyatt Reed | The Grayzone | December 17, 2023
Lawsuits accusing top US universities of harboring antisemitism all originate from one source: a corporate law firm that fielded the pro-settler ex-US ambassador to Israel, and which was registered as a foreign agent of an Israeli principal as recently as 2021.
The firm now represents professional Israel lobby activists posing as victimized “Jewish students” and seeking to crush the free speech rights of Palestine solidarity activists. … continue
Blog Roll
 Aletho News
- Ukraine arrests woman who exposed Azov battalion’s ‘torture chamber’
- Did Israel lose the midterms?
- How Iran defeated Trump’s Israel First GOP
- De-escalating the conflict: What the OSCE, the UN, and Europe are (not) doing to prevent war
- Desperate For A Renewed Iran War, Israel Dusts Off The WMD Deception.
- US Elections Offer Choice Between ‘Bad and Worse’ as Both Parties Serve War Lobby – ex-UN Expert
- Ghalibaf warns US government not to betray voters who rejected war
- Broke Princes: Saudi Arabia’s Powder Keg
- Albania’s Crisis: Rama, Israeli Investments and the Demand for Accountability
- Hezbollah Categorically Denies Syrian Accusations: We Aim at Confronting Israeli Enemy, Not Undermining Syria’s Stability
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago

