The Political Agenda of the IPCC

BY ROGER PIELKE JR. | THE HONEST BROKER | MAY 15, 2023
The Intergovernmental Panel on Climate Change (IPCC) was established as a scientific assessment process more than 35 years ago. Scientific assessments are of critical importance in many areas to help policy makers and the public to identify what is known, what is uncertain, as well as where there is contestation, uncertainties and areas of fundamental ignorance. Such assessments can also help us to understand policy options and expectations for how different choices might lead to different outcomes.
Regular readers of The Honest Broker will know that I have taken issue with the recent IPCC Sixth Assessment (AR6) based on an unacceptable number of errors and omissions in my areas of expertise, as well as its over-reliance on the most extreme climate scenarios. Today I take a look at the IPCC’s self-described political agenda and argue that the institution finds itself at a fork in the road.
Before proceeding, I want to be clear about what I mean when I talk about “the IPCC.” In one sense there is really no such thing as “the IPCC.” The organization’s assessment process includes many hundreds of people who do their work across three Working Groups to produce many dozens of chapters covering a wide range of topics. The Working Groups are largely independent of each other and even chapters within the same Working Group can be written largely independently of other chapters.
In another sense there is indeed such a thing as the IPCC — Specifically, its leadership and most engaged participants. These core participants represent a kind of climate in-group with a shared sense of purpose and an overarching commitment to a shared political agenda. For some people, their entire career is centered on the IPCC. These core participants do have a shared political agenda which can be seen in varying degrees within the reports.
So what is the political agenda of the IPCC in-group? Transformational change
When the IPCC released its Synthesis Report in March, it announced:
Taking the right action now could result in the transformational change essential for a sustainable, equitable world
It would be easy to write this sentence off as containing consultant-like and empty buzzwords. But the notion of “transformational change” has been widely employed in the academic literature on climate and the IPCC clearly defines what it means by “transformational change.”
In its AR6 Working Group 3 report the IPCC explains that transformation involves more than simply transitioning from one type of technology to another (emphasis added):
While transitions involve ‘processes that shift development pathways and reorient energy, transport, urban and other subsystems’ (Loorbach et al. 2017) (Chapter 16), transformation is the resulting ‘fundamental reorganisation of large-scale socio-economic systems’ (Hölscher et al. 2018). Such a fundamental reorganisation often requires dynamic multi-stage transition processes that change everything from public policies and prevailing technologies to individual lifestyles, and social norms to governance arrangements and institutions of political economy
Transformational change means that everything changes.
What are examples of these sorts of changes? The IPCC identifies “the potential for virtuous cycles of individual level and wider social changes that ultimately benefit the climate.”
The IPCC continues (emphasis added):
The starting point for this virtuous circle are inner transitions. Inner transitions occur within individuals, organisations and even larger jurisdictions that alter beliefs and actions involving climate change (Woiwode et al. 2021). An inner transition within an individual (see e.g., Parodi and Tamm 2018) typically involves a person gaining a deepening sense of peace and a willingness to help others, as well as protecting the climate and the planet . . .”
What are examples of such “inner transitions”? The IPCC explains:
Examples have also been seen in relation to a similar set of inner transitions to individuals, organisations and societies, which involve embracing post-development, degrowth, or non-material values that challenge carbon-intensive lifestyles and development models . . .
The IPCC discusses the importance of “degrowth” to its vision of transformation in its AR6 Working Group 2 report:
Consumption reductions, both voluntary and policy-induced, can have positive and double-dividend effects on efficiency as well as reductions in energy and materials use . . . a low-carbon transition in conjunction with social sustainability is possible, even without economic growth (Kallis et al. 2012; Jackson and Victor 2016; Stuart et al. 2017; Chapman and Fraser 2019; D’Alessandro et al. 2019; Gabriel and Bond 2019; Huang et al. 2019; Victor 2019). Such degrowth pathways may be crucial in combining technical feasibility of mitigation with social development goals (Hickel et al. 2021; Keyßer and Lenzen 2021).
These views are no doubt legitimate and sincerely held. But I seriously doubt that a climate agenda focused on changing everything, grounded in inner transitions to support degrowth is going to get very far in Peoria, much less anywhere else. More broadly, why are they being used to frame a scientific assessment?
I’m far from the first to recognize that the IPCC has adopted a political agenda focused on transformational change. Writing in 2022, Lidskog and Sundqvist explain:
Transformation has become a buzzword within scientific and political discourses in which “transformative change” is stated to be the solution to many severe environmental challenges. Expert organizations such as the IPCC and IPBES have stressed that transformative change is necessary to meet environmental challenges (IPCC, 2018; IPBES, 2019). . . While transformative change is seen as the way forward and as an uncontroversial ambition—it is difficult to find anyone who is critical of it—its meaning is nevertheless unclear.
The adoption of transformational change as an overriding political objective in the IPCC AR6 (and in the IPCC 1.5 report before that) represents a departure from a more politically neutral use of the concept in the IPCC Fifth Assessment Report (AR5). In 2014, the AR5 described “transformation pathways” to refer to technological alternatives for mitigation, not to demand that everything must change across society:
Stabilizing greenhouse gas (GHG) concentrations at any level will require deep reductions in GHG emissions. Net global CO2 emissions, in particular, must eventually be brought to or below zero. Emissions reductions of this magnitude will require large-scale transformations in human societies, from the way that we produce and consume energy to how we use the land surface. The more ambitious the stabilization goal, the more rapid this transformation must occur. A natural question in this context is what will be the transformation pathway toward stabilization; that is, how do we get from here to there?
The IPCC AR5 acknowledged that there were many ways to address accumulating greenhouse gases (GHGs) in the atmosphere:
[T]here is no single pathway to stabilization of GHG concentrations at any level. Instead, the literature elucidates a wide range of transformation pathways. Choices will govern which pathway is followed . . .
This expansive view of policy possibilities is far removed from “processes that change everything” and a “deepening sense of peace.” The IPCC AR5 and AR6 have been rightly criticized for not considering a larger set of possibilities for mitigation (notably, equity), which also reflects a political orientation.
The IPCC – or to be more precise, influential elements of the IPCC – appears to have been captured by an in-group with shared political views related to climate. These views embrace concepts like degrowth and planetary boundaries and turn climate policy on its head such that ends become means.
Transformational change views climate policy as a lever through which to “change everything.” The expressed need for such momentous changes across society are grounded in a frightening, even apocalyptic, perspective on the future. As the head of the IPCC exhorted in March, the IPCC “underscores the urgency of taking more ambitious action and shows that, if we act now, we can still secure a liveable sustainable future for all.”
The political agenda of the IPCC reads as if it was developed by wealthy American and Europeans academics. The billions of people around the world who may lack energy services or enough food probably would welcome an agenda of change. Instead, the IPCC emphasizes transformational changes in the lifestyles of ordinary people in rich countries, for instance, the recent Synthesis Report explained: “Many mitigation actions would have benefits for health through lower air pollution, active mobility (e.g., walking, cycling), and shifts to sustainable healthy diets.”
I have little doubt that many who have worked on the IPCC AR6 might read this post and say, “Hmmm, I never saw any of that,” others might say, “Yup, that’s our agenda, so what?” and still others might say, “I have a different political or professional agenda that I inserted into the report.” Further, one can surely dive into the almost 10,000 pages of the AR6 reports and selectively construct a different political narrative. However, I argue that “transformational change” is what in the jargon of symbolic politics is called the “master symbol” — the dominant political framing of the AR6.
The IPCC has clearly departed from its role as a scientific assessment and is now much more deeply engaged in political advocacy. Trying to simultaneously engage in assessment and advocacy is never a good idea. I hypothesize that the IPCC’s political agenda of transformational change plays more than a small role in its stubborn reliance on implausibly extreme scenarios and its multiple errors and omissions related to the science of extreme weather and disasters — both of which help to underscore the demand for urgent and large-scale societal change.
The IPCC finds itself at a fork in the road and should be reformed. It needs to either operate as a trustworthy scientific assessment or alternatively, to fully embrace its current role as an environmental advocacy group pushing transformational change. There is no middle ground.
Dutch-Led Network Of International Experts Finds “Serious Errors” In Latest IPCC Report
By P Gosselin | No Tricks Zone | May 12, 2023
The UN Intergovernmental Panel On Climate Change (IPCC) is misleading policy makers by focusing on an implausible worst-case emissions scenarios, concludes a new analysis report published by the Clintel Foundation: “The Frozen Climate Views of the IPCC“

The IPCC is hiding the good news about disaster losses and climate-related deaths and wrongly claims the estimate of climate sensitivity is above 2.5°C. Also errors in the AR6 report are worse than those that led to the IAC Review in 2010, concludes the report by The Climate Intelligence Foundation (Clintel), which was founded in 2019 by emeritus professor of geophysics Guus Berkhout and science journalist Marcel Crok.
Opposite of IPCC claims likely true
Another result: The IPCC ignored crucial peer-reviewed literature showing that normalized disaster losses have decreased since 1990 and that human mortality due to extreme weather decreased by more than 95% since 1920.
Clintel accuses the IPCC of cherry picking from the literature to claim increases in damage and mortality due to anthropogenic climate change, when in fact the opposite is likely true.
Rewrote climate history
The Clintel report is 180 pages long and the first serious international ‘assessment of the IPCC’s Sixth Assessment Report. In 13 chapters the Clintel report shows the IPCC rewrote climate history, and emphasizes an implausible worst-case scenario, favoring bad news and ignoring good news.
“The strategy of the IPCC seems to be to hide any good news about climate change and to hype anything bad,” reported the Clintel press release.
The errors and biases that Clintel documents in the report are far worse than those that led to the investigation of the IPCC by the Interacademy Councel (IAC Review) in 2010. Clintel believes that the IPCC should reform, or be dismantled.
Clintel is a network of international scientists who analyzed several claims from the Working Group 1 (The Physical Science Basis)
and Working Group 2 (Impacts, Adaptation and Vulnerability) reports. This led to the latest report: “The Frozen Climate Views of the IPCC”.
IPCC ignores 97% of all papers
Clintel explains how the IPCC ignored 52 out of 53 peer reviewed papers dealing with “normalized disaster losses” and found no increase in harms that could be attributed to climate change. Yet, the IPCC highlighted the single paper that claimed an increase in losses.
Cherrypicking, rewriting history
The IPCC also has tried to rewrite climate history by erasing the existence of the so-called Holocene Thermal Maximum (or Holocene Climate
Optimum), a warm period between 10,000 and 6000 years ago, and has introduced a new hockey stick graph, which is the result of cherry-picked proxies. The IPCC ignores temperature reconstructions that show more variability in the past, such as the well-documented Little Ice Age.
In its recent report, the IPCC also has grossly exaggerated sea level rise and CO2’s ability to warm the earth’s atmosphere and thus appears to have remained ‘addicted’ to its highest emissions scenario, so-called RCP8.5, which in recent years has been shown by several published papers to be implausible and thus should not be used for policy purposes.
Severely biased
“We are sorry to conclude that the IPCC has done a poor job of assessing the scientific literature,” the Clintel scientists report. “In our view the IPCC should be reformed, and should include a broader range of views. Inviting scientists with different views, such as Roger Pielke Jr and Ross McKitrick, to participate more actively in the process is a necessary first step.”
If the inclusion of other views does not permitted, then the IPCC should be dismantled, the scientists say.
Reality: Future is far less bleak
“Our own conclusions about climate – based on the same underlying literature – are far less bleak. Due to increasing wealth and advancing technology, humanity is largely immune to climate change and can easily cope with it. Global warming is far less dangerous to humanity
than the IPCC tells us.”
Clintel also published the World Climate Declaration, which has now been signed by more than 1500 scientists and experts. Its central message is “there is no climate emergency”.
Clintel press release here.
Autopsy of Fatal Delta Variant in a Fully Vaccinated Man
Findings Suggest Complete Failure of Pfizer-BioNTech COVID-19 Vaccine Induced Antibodies
By Peter A. McCullough, MD, MPH | Courageous Discourse | May 18, 2023
Autopsies have played a critical role in the history of medicine. The novel coronavirus pandemic is a period of time where autopsies have been particularly helpful in advancing our understanding of COVID-19 disease. So the question on the table is: if the mRNA COVID-19 vaccines raised antibodies against the ancestral wild type Wuhan strain of SARS-CoV-2, would they cover the Delta variant? The only real way to know is to find a case who is fully vaccinated with “protective” antibodies in the bloodstream who contracts COVID-19. Recently such a patient has been reported from Catania, Italy.
Esposito, et al, published an autopsy of an 83 year old man who was admitted to the hospital with heart failure and was later diagnosed with acute COVID-19 and succumbed 18 days later. There is no mention of treatment with lifesaving medications in the McCullough protocol such as ivermectin, corticosteroids, or anticoagulants. Sadly his lungs were ravaged with SARS-CoV-2 despite having adequate antibody titers for the Spike protein generated from the Pfizer-BioNTech COVID-19 Vaccine.

Esposito, M.; Cocimano, G.; Vanaria, F.; Sessa, F.; Salerno, M. Death from COVID-19 in a Fully Vaccinated Subject: A Complete Autopsy Report. Vaccines 2023, 11, 142. https://doi.org/10.3390/vaccines11010142
The important points of this paper are: 1) the original Pfizer-BioNTech COVID-19 Vaccine failed to stop the Delta variant, 2) antibodies are an invalid surrogate of protection and should have never been used 8 times by the US FDA in EUA approvals for extended use of COVID-19 vaccines.
Biden’s New NIH Head Solidify’s America’s Breakaway Health Agency Crisis
By Jefferey Jaxen | May 18, 2023
American health agencies are in a crisis of their own making. The pandemic response has both amplified and spotlighted the classic shortcomings and limitations of agencies like the U.S. Food and Drug Administration (FDA), the Centers for Disease Control and Prevention (CDC), and the National Institutes of Health (NIH).
News this week reports Biden has chosen Dr. Monica Bertagnolli, formerly National Cancer Institute Director, to lead the NIH. Bertagnolli fills the absence left by Dr. Francis Collins.
In a post-Covid world, much of the public-facing legacy of agency directors is written by their actions during the failed pandemic response. History will show it as a doomed era where no leadership escaped without tarnished careers from their unified actions to viciously mandate Covid shots, mask kids, keep schools closed and lockdown society causing irreparable harm to the American economy – all without the science to back up their decisions.
Former NIH head Collins will be forever known as the man who shut down scientific debate at a time when open dialogue about the already known, published research could have saved lives, the economy, and the mental health of our current population. Purposely ignored warnings, which came in the form of the Great Barrington Declaration, that internal emails show Collins and Fauci colluded to publish a ‘devastating takedown’ of its premise using the full weight of their agencies and media power.
Dr. Bertagnolli’s deep funding by Pfizer, and to a lesser extent from Johnson & Johnson subsidiary Janssen, is chronicled by The Daily Signal :
From 2015 through 2021, Bertagnolli received more than 116 grants from Pfizer, totaling $290.8 million. This amount made up 89% of all her research grants, according to Open Payments, a national transparency program under the Center for Medicare & Medicaid Services that collects and publishes information about financial relationships between drug and medical device companies and certain health care providers.
Her extensive background in cancer research and ties to Pfizer and other pharma companies raises questions about the timing of her placement at the head of NIH, the largest single public funder of biomedical and behavioral research in the world at more than $40 billion.
The Covid vaccine gold rush has come to an end for companies like Pfizer and Moderna. A brief look at headlines tells of the next profit push on the horizon being mRNA cancer vaccine therapies.

Meanwhile, an epidemic surge of cancers of unknown causes is also grabbing headlines.

Bertagnolli appears well-positioned to streamline an injectable pharmaceutical ‘answer’ to a growing cancer question while obscuring further investigation into its root cause(s).
Meanwhile, Walensky’s abrupt departure from a badly damaged CDC has public trust in the agency racing for the doors at breakaway speeds.
The FDA has done no better. After Trump’s director, Stehpan Hahn stepped down as the administration changed hands, Biden kept the agency without a presidential nomination for commissioner for the maximum time allowed by law – nearly one year.
In that time, the FDA pushed through emergency use authorizations for J&J’s Covid shot, expanded Pfizer’s EUA to 12-15 yr-olds and 5-11 yr-old, added EUA booster doses and mishandled massive warnings about increases in myocarditis, Guillain-Barre syndrome and thrombocytopenia after Covid shots. The agency’s authoritarian booster push also saw infighting due to a lack of data to inform the decision culminating in two of the FDA’s top, longtime vaccine regulators [Kruse & Gruber] departing in disgust.
A recent BMJ article titled The decline of science at the FDA has become unmanageable states, … the corruption of the FDA’s scientific culture remains the primary culprit driving the deterioration of safety and effectiveness standards.”
By all measures, America’s health agencies are in rapid decline as a litany of historical issues like Big Pharma’s revolving door influence, an outward mission-directed posture of mandates and censorship, a continued doubling down on bad policy, and an imbalance focusing on liability-free injectable products as the answer has left American marooned.
The path forward for American health, suffering in many categories, has challenges ahead. Yet the many failures and outright censorship of the medical and research communities during the failed pandemic response have created a new space being rapidly populated by medical professionals, experts, and citizen journalists who see the value and desperate need to investigate and report on reality, expose bad science and maximize open debate surrounding key health issues. It is the best of times and it is the worst of times.
FDA not fit for purpose – the Makena® fiasco
For years, the FDA allowed a drug to be injected into pregnant women that was neither safe, nor effective. Finally, it has been withdrawn.
BY MARYANNE DEMASI, PHD | MAY 15, 2023
Previously, I wrote about Makena, a synthetic hormone given to millions of pregnant woman, to prevent premature birth. It was highly controversial because there was no robust proof that it was safe or effective, despite having FDA-approval.
Last month, after many years of use, the FDA finally decided to withdraw Makena from the market.
Adam Urato, a maternal-foetal medicine specialist at MetroWest Medical Centre, Massachusetts welcomed the decision, but said it took the FDA far too long.
“I cannot believe we’ve been injecting this hormone into pregnant women for 20 years, all the leading medical organisations recommended it, the FDA approved it – and it took this long to finally acknowledge the drug did not work,” he said.
Urato opposed the use of Makena from the start. He testified before the FDA, he wrote in the media and in medical journals, and helped petition the FDA to withdraw the drug from the market.

Adam Urato, maternal-foetal medicine specialist, MetroWest Medical Centre, Massachusetts.
Preterm birth is a major issue in obstetrics. In the US, one in 10 babies are born prematurely, and accounts for most of the neonatal morbidity and mortality.
Physicians were desperate for a solution, and Makena seemed to hold promise.
It wasn’t cheap though. Makena was 5,200% more expensive than generic versions of the same medication.
Large amounts of public money in the Medicaid program and other health insurance dollars were used to pay for the weekly shots at a total cost of $30,000 per pregnancy.
How it began
The drug maker sought fast-track approval of Makena, citing a 2003 study that was so flawed, the FDA’s own statistical reviewer commented that the drug was not worth approving.
The FDA approved it anyway on the basis that the drugmaker conduct more in-depth research into the medication’s effectiveness.
Then, in 2019 a confirmatory trial found the drug did not work. And by this stage, there were documented harms including gestational diabetes, depression, blood clots and a non-statistical doubling in stillbirths.
But instead of pulling the drug off the market, the FDA allowed Makena to be licensed for another four years.
“It should’ve been pulled immediately,” said Urato. “There were substantial profits for the drug company even after a confirmatory trial found it did not work, so it’s no wonder it was dragging its feet.”
It begs the question…
How is it even possible that a drug, which was neither safe nor effective for pregnant women, was allowed to be on the market for so long?
Urato says it’s a direct symptom of the medical-industrial complex – an entanglement of big pharma, medical organisations, and regulatory agencies – that creates an underlying motive to bolster profits, over health.
“For two decades the drug brought in billions in profits, and that money was used to fund physicians, researchers, professional medical societies, and academic institutions,” said Urato.
This makes it exceedingly difficult, if not impossible, for patients to navigate the healthcare system and know who to trust.
“We need elected officials that are going to put the interests of patients and the public first, and not be tainted, or corrupted by industry. We need to separate our politics and our regulatory bodies from industry funding,” he added.
Lesson learned?
Urato feels vindicated for his work, but says it’s no time for a victory lap. Instead, the Makena fiasco should provide us with tangible lessons to safeguard us against such scientific transgressions in the future.
“We must ‘first do no harm’ and follow the precautionary principle,” insisted Urato.
“When you’re exposing developing babies to synthetic chemical compounds, you can’t just assume it’s safe, until harm is proven. You must assume that the chemicals are having chemical effects on the foetus, because that’s what chemicals do.”
The Diethylstilbestrol (DES) disaster should have been a reminder to all obstetricians about the harms of giving synthetic hormones to pregnant women without sufficient data. But once Makena was rolled out, Urato said, “it was like everyone forgot the past.”
“I counselled my patients on my concerns about exposing them and their babies to a synthetic hormone with unknown short and long-term effects, so I guess I could have been accused of peddling ‘misinformation’,” said Urato cognisant that he was going against medical consensus.
“But what is considered misinformation today, may be scientific fact tomorrow. I helped to prevent a generation of mums and babies in my community from being exposed to a useless drug. That’s why it’s so important that doctors have freedom of speech to express their views,” said Urato.
It’s estimated that hundreds of thousands of pregnant mothers and babies were exposed to the ineffective and risky synthetic hormone over the past 2 decades.
“Time and time again, drugs and devices are pulled off the market for safety issues. If the FDA approves a drug, it does not mean that it will be proven to be safe and effective over time. The FDA has lost the public’s trust,” Urato said.
Missed Bacterial Pneumonia Cases Left Untreated Were the Majority of COVID-19 Hospital Deaths
In April 2020, I warned about that the false positive-prone non-quantitative RT-PCR was deadly. Now we know, again, I was (sadly) correct.
By James Lyons-Weiler | Popular Rationalism | May 17, 2023
Hospital protocolists sticking to the strict hand-me-down highly profitable “COVID protocol” may have doomed a majority of admitted COVID-19 patients to death due to a perfect storm of institutional failure.
I first warned FDA in early 2020 that because the commercial kits did not use internal negative controls there would be arbitrarily high COVID-19 false positive rates due to the abuse of non-quantitative PCR. The majority of “cases”, I pointed out, would be false because the test was to be used as a screening device – and when you screen with an imperfect test when prevalence is low, you end up with more false positives than negatives in the set of positives.
Knowing that people who were symptomatic for respiratory infections would be among the most tested population and that Fauci’s medical approach to COVID-19 was to tell people to go home and get as sick as possible, it was readily clear that people would be dying due to lack of treatment for treatable conditions, like bacterial pneumonia and fungal infections in the lung.
Now a study from NIH-funded researchers in Chicago, IL has found that unresolved respiratory infections – not necessarily those involved in SARS-CoV-2 – were present in people who failed to “respond” to mechanical ventilation.
The authors wrote:
“Recent data suggest that secondary pneumonia is present in up to 40% and pneumonia or diffuse alveolar damage is present in over 90% of autopsy specimens obtained from patients with acute SARS-CoV-2 infection (18). Consistent with these observations, we and others found high rates of ventilator-associated pneumonia (VAP) in patients with SARS-CoV-2 pneumonia requiring mechanical ventilation, suggesting that bacterial superinfections such as VAP may contribute to mortality in patients with COVID-19 (7, 19–22). These findings prompt an alternative hypothesis that a relatively low mortality rate directly attributable to primary SARS-CoV-2 infection is offset by a greater risk of death attributable to unresolving VAP (23).”
They concluded:
“These data suggest mortality associated with severe SARS-CoV-2 pneumonia is more often associated with respiratory failure that increases the risk of unresolving VAP and is less frequently associated with multiple-organ dysfunction.”
Unsurprisingly, the study found that people with bacterial pneumonia who were on ventilators had the highest mortality. Although their analysis restricted consideration to bacterial pneumonia cases detected 48 hours after ventilation, they did not distinguish between undiagnosed cases of bacterial pneumonia upon admission and those acquired in-hospital (nosocomial infection). The rate of co-infection is not clear either, due to insufficient testing for bacterial pneumonia in patients once diagnosed with COVID-19.
The study leads to the stunning potential that perhaps 58% of “COVID” cases were respiratory issues other than COVID (43% bacterial pneumonia, 16% non-pathogen causes of respiratory failure). Treated as “COVID”, these patients were doomed to a fate of non-treatment due to mis- or under-diagnosis.
It is unclear what percentage of deaths attributed to COVID-19 could have been prevented via a standard therapy for bacterial pneumonia, but it is potentially very high. Fauci’s prescription – sending patients home to do nothing – no corticosteroids, no antibiotics just in case it was bacterial – drove the COVID-19 death rate up far higher than it had to be.
Gao et al., 2023. Machine learning links unresolving secondary pneumonia to mortality in patients with severe pneumonia, including COVID-19, Journal of Clinical Investigation (2023). DOI: 10.1172/JCI170682
Her Father Got COVID and Died — But She Believes the CDC, NIH and Hospital Protocols Are What Really Killed Him

By Michael Nevradakis, Ph.D. | The Defender | May 16, 2023
Ralph Marxen Jr. had just turned 70 and was enjoying life with his wife of 49 years, Lynda, and his adult children and grandchildren. The Minnetonka, Minnesota, native was in good health and, according to his daughter, Nicole Riggs, walked long distances daily and wasn’t on any medications.
In August 2021, several members of Riggs’ household contracted COVID-19, including, presumably, her parents. A week later, while most family members were recovering, Marxen’s condition deteriorated leading him to be admitted to Abbott Northwestern Hospital in Minneapolis on Aug. 23, 2021.
Marxen would never leave the hospital — he died there on Sept. 7, 2021.
During his stay, Marxen, who had not received a COVID-19 vaccine, was administered more than 50 medications, including remdesivir, vancomycin, fentanyl and midazolam, and in the days prior to his death, he was placed on a ventilator.
At the time of his death, Marxen had “multiple organ system failure including renal failure, endocarditis, hyperkalemia, MRSA [methicillin-resistant Staphylococcus aureus] pneumonia, MRSA bacteremia and sepsis,” Riggs said.
Riggs told The Defender the treatments she and her family requested for Marxen, including ivermectin, monoclonal antibodies and vitamins, were refused.
She said she did not believe her father’s refusal of the COVID-19 vaccines played a role in his illness — in fact, she argued that her father’s non-vaccinated status — and the COVID-19 protocols prescribed by the Centers for Disease Control and Prevention (CDC) and the National Institutes of Health (NIH) — were factors in the treatment he received from the hospital and its medical staff.
‘Is this a hospital or a prison?’
“My dad went to the ER seeking help for dizziness and nausea,” Riggs said. “He was 70 years old and took no daily meds. He was unvaccinated and refused to take their unreliable PCR tests.”
In a separate interview with Minnesota’s Alpha News, Riggs said that two of her father’s friends had gotten vaccinated “and they both got vax-injured.” As a result, “He was adamant that he was not going to get the vaccine.”
“I think this played a part in him not getting good care,” Riggs told The Defender.
Riggs recounted the chain of events that led her father to end up in the hospital.
“In the middle of August 2021, my household of four, plus my parents, became ill with fever and fatigue, and a few of us had chest congestion,” Riggs said. “Myself, my husband and my two boys were spit-tested for COVID and were all told we were positive for COVID. We assumed my parents had the same.”
But after a week of being sick, she said they noticed that her father “didn’t seem to be bouncing back like the rest of us. He was having trouble walking to the bathroom because he was so weak and dehydrated.”
Due to his older age, his family “decided to call the ambulance and get him checked out,” Riggs said. Paramedics recommended Marxen go to the hospital for further evaluation, so he was admitted on Aug. 23, 2021, after an ER visit.
“From the beginning, the medical records indicate they wanted to get him on remdesivir even though they couldn’t get him to PCR test,” Riggs said.
“Within a day, a friend of the family who had been working with COVID patients for the past year told us to call the hospital and request that my dad be given monoclonal antibodies (a.k.a. Regeneron),” Riggs said. However, the nurse treating her father said he “had never heard of that before, and that was the end of that discussion.”
“That seemed strange to me, but I still trusted them at that time,” Riggs said.
The day after her father was admitted to the hospital, her mother also was admitted, after her oxygen levels dropped to the low 90s.
“My parents were soon hospital room neighbors,” Riggs said. “COVID medications were started, which we later learned was hospital protocol with remdesivir and dexamethasone.”
Despite being in neighboring rooms though, Riggs’ parents could not visit each other. “My mom wanted to go see my dad since he was in the room right next door, but she realized that her bed had an alarm that sounded when she tried to get up. She also learned that both of them were locked in their rooms as well,” Riggs said.
She added:
“My mom’s nurse thought ‘it wasn’t appropriate,’ and refused to let her go see my dad. They had to wait until that nurse was off her shift before the doctor would OK my mom to go into my dad’s room for a short visit.
“Is this a hospital or a prison?”
It wasn’t long before Riggs began to receive more disturbing updates about the treatment her parents were receiving in the hospital.
She told The Defender :
“My brother started a CaringBridge site to keep our whole family updated. It wasn’t long before I started to receive unsettling messages from people I knew and trust. One was from my dad’s old neurological chiropractor, saying ‘no remdesivir and no ventilator, that’s asking to die.’ He also sent me information on how to get a lawyer involved.
“It was then that I started to research and realize the dangers of the deadly hospital protocols put in place by the NIH and CDC, especially for those on Medicare, as the hospital is given a 20% bonus payment if certain steps are followed with those patients, starting with a positive COVID PCR test.”
According to Riggs, this was evident in her father’s medical records.
“One of the doctors actually wrote this in the medical records: ‘I don’t think it’s impossible to use remdesivir without a PCR positive,’” Riggs said, adding, “My dad initially refused a nasal PCR test because he knew they could be inaccurate and wanted to be treated by symptoms, not a PCR positive COVID test result.”
However, the hospital told Marxen and his family this was not possible. According to Riggs, the doctor said, “Certain treatments may not be available without PCR-proven COVID, and that if his condition worsened such that he required intubation, we would run the nasopharyngeal swab.”
“Basically, my dad was told he wouldn’t get access to ‘certain treatments’ until he submitted to their request to be PCR tested,” Riggs said. “And if he got bad enough, they would test him anyway.”
The hospital also told them if Marxen’s condition deteriorated enough that they needed to put him on a ventilator, they would do the test without his permission.
Her father finally “relented” and tested positive for COVID-19. That’s when the hospital administered remdesivir “and many other harmful drugs,” Riggs said, and denied their request for safer alternatives.
‘It all happened so fast’
From this point forward, “It all happened so fast,” Riggs said. Her father was transferred to progressive care on Aug. 26, 2021, and to the ICU the next day.
“My dad was denied visitation by anyone under the guise of ‘COVID isolation,’” Riggs said. “Even my mom, who was in the same hospital with COVID.”
Marxen’s condition quickly deteriorated. “My dad was told he needed to get on the ventilator so he could get relief and a feeding tube,” Riggs said. “By this time, my dad hadn’t slept in two days and hadn’t eaten in five days.”
“After two days in the ICU, he was freaking out, pulling off his mask and pulling out his IV,” Riggs said. “They got him ‘reoriented’ and brought in the doctor. If you knew my dad, you would know that this was totally out of character for him. He was the kindest, most loving man and father. He was one of my best friends.”
“Soon, he felt he had no other option but to be put on a ventilator,” Riggs said. “A decision he had to make scared and alone because we were kept from him … They had finally got him desperate enough to submit to getting on a ventilator.”
Marxen was intubated on Aug. 29, 2021, and placed on fentanyl and propofol, Riggs said, “even though, reading the records, they knew that wasn’t the solution, but they did it anyway.”
Riggs said she and her family again requested monoclonal antibodies be administered, “but were denied because it was too late in the progression of the disease to be a benefit.”
They also requested “vitamin C, vitamin D, zinc, hydroxychloroquine, ivermectin,” but were denied “and told they refused to go off of protocol, ‘because the one time we did that, the patient died,’” Riggs added.
“My dad’s medical records indicate vitamin D was ‘deemed not appropriate during this admission,’” Riggs noted. “We asked them to take him off vancomycin because that can make you retain fluid and he was already doing that. They told us no, and that the drug was ‘the gold standard.’”
‘He was kept from everyone that truly loved him’
According to Riggs, she would call the hospital every day at 6 p.m. for updates, and her brother would do so daily at 6 a.m. This continued until Sept. 7, 2021, the day her father would be placed “off quarantine” and allowed to see family members again.
However, “on Sept. 7, we were told that the ‘infectious disease team’ said he needed another seven days of quarantine,” Riggs said. “This decision was not even made by his ICU doctor.”
Instead, Riggs and her family were told “the nurses would set up a Facetime for us for the evening of Sept. 7,” Riggs said. “After that call, I was crying and pacing in my house. My thoughts were, ‘Are we going to just leave him in there to die alone?’ I needed to actually do something.”
Riggs said she decided to request her father’s medical records from the hospital, “so I could see exactly what was going on there.” However, she was told the records could not be released “unless he signed the release form” — even though her father was sedated and on a ventilator “and it wasn’t possible for him to sign anything.”
In response, the hospital told Riggs that she “would need to provide his death certificate for the records if we hadn’t already set up power of attorney.”
“So, he had to die before I could access his records?” Riggs asked. “How did this nightmare become our reality?”
Within a few hours of this exchange, Riggs received a call that her father was “actively dying” and if they wanted to see him, they needed to do it soon, because he would pass away during that night.
“Now that he was dying, we were able to come see him — but hours before we couldn’t? This made zero sense to me,” Riggs said.
On arriving at the hospital, she and other family members “were required to wear space-like soft helmets, which made it impossible to even kiss my dad goodbye.”
According to Riggs, she and her family “gave the OK to remove him from the ventilator so we could pray scripture over him through his transition.”
“I thought removing him from the ventilator would cause him to pass away because he couldn’t live without it,” Riggs said. “But I can’t help but wonder if that’s really how it went down. His records show that he was given fentanyl at 5:10 p.m. and midazolam at 5:32 p.m. He passed away at 6:22 p.m.”
Riggs said the “official” cause of death was determined to be “respiratory failure with underlying COVID-19.”
When her father died, he had multi-system organ failure. Riggs said she did not believe her father died of COVID-19, but instead due to the CDC- and NIH-approved protocols.
“He was isolated and kept from everyone that truly loved him for 16 days,” Riggs said. “Then, under the guise of ‘palliative care,’ he was finished off with fentanyl and midazolam.”
According to Alpha News, the price tag from the hospital for the treatment her father received during those 16 days was $1.2 million.
A statement provided by Abbott Northwestern to Alpha News said the following:
“Allina Health respects the privacy of its patients and is unable to comment on specific patient care.
“We have great confidence in the exceptional care our medical teams provide to our patients, which is administered according to evidence-based practices by our talented and compassionate care teams.”
‘To honor my dad, I have put my grief into action’
Riggs said her father’s death had knock-on effects on her and her family.
“Now my mom, who survived remdesivir, can’t afford to keep their home,” Riggs said. “She had to sell almost all of their possessions accumulated over 50 years to move into one of the bedrooms of my two-bedroom home. Two of my boys … now share a bedroom in our living room.”
“She can hardly make the bed without being out of breath and she struggles mentally with what they endured and getting a grasp on her new life without my dad in it,” Riggs added.
Despite these challenges, Riggs said that “to honor my dad, I have put my grief into action,” getting involved in activism for victims of hospital protocol deaths.
Riggs is now the Minnesota chair of the FormerFedsGroup Freedom Foundation, a national coalition that has documented cases involving COVID-19 care protocols at hospitals.
“I don’t want the families … to be isolated and alone in their pain of losing their loved one,” Riggs said, adding that she has launched weekly Zoom calls for Minnesota families and survivors of hospital protocols, and is also launching in-person meetups.
Riggs also recently attended the Halt Hospital Homicide rally, which she described as the “first national rally for hospital protocol deaths.”
She drew parallels with those who died of COVID-19 vaccine injuries. “The vax-injured are ignored and not believed, just like those of us who have had a family member die or get injured by the hospital protocols,” she said.
“My dad, Ralph, will go on in our memories as a wonderful husband of 50 years, dad, grandpa and great-grandpa, as well as a fun fisherman and the best homemade French fry maker around.”
Michael Nevradakis, Ph.D., based in Athens, Greece, is a senior reporter for The Defender and part of the rotation of hosts for CHD.TV’s “Good Morning CHD.”
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Farewell Questions for Rochelle Walensky An open letter to Congress
BY EL GATO MALO | BAD CATTITUDE | MAY 15, 2023
The history of the CDC during covid has been, at best, a checkered one.
Given what we now know about the complete failure of covid vaccines to provide sterilizing immunity, stop infection, or stop spread as well as the fact that such issues were not even tested for in the drug trials that approved them, certain questions would seem overdue in the asking:
Just what was this “Data from the CDC today” that suggested that “Vaccinated people do not carry the virus?”
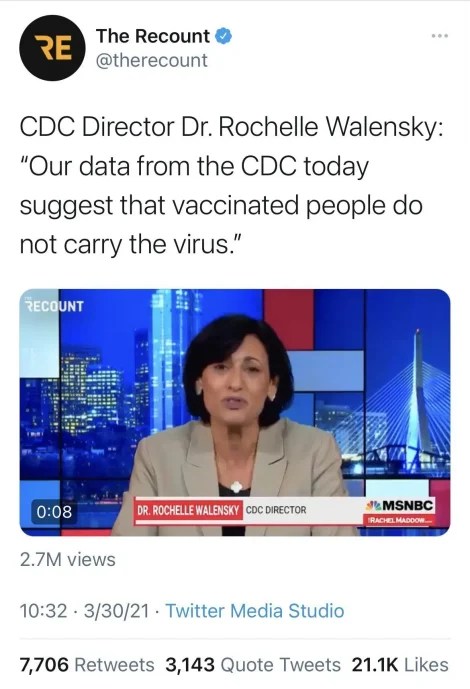
Was there, in fact, any data at all?
Or was this a completely fabricated claim used to underpin the mass rollout of a product that failed so spectacularly right out of the gates and:
- Where the sorts of safety and inefficacy signals that would have pulled any other vaccine in history off the market were ignored.
- Where the data collection was rigged to make known adverse events difficult to find, report, and aggregate in the V-safe system by removing them from searchable database fields and placing them in free text response.
- And where the mandated safety assessments were not being performed until long after problems were evident, allowing the CDC to miss the most blatant safety signal in history.
There seems to be an awfully large body of claims made by CDC that appear to have lacked foundation in fact or data. Both Dr Walensky and her predecessor Robert Redfield would seem to have a great deal to answer for here.
“The covid vaccine will make the vaccinated a dead end for the virus.”
This talking point was simply everywhere all at once.
Pfizer CEO Albert Bourla certainly pushed this narrative. Presumably, the fact that he was allowed to do so (itself quite an exceptional situation) implies the acquiescence of FDA, CDC, and other regulators.
Upon what was this seemingly widespread consensus based?
The matter appears to have never even been studied at the time the claims were made.
Why were the usually strict and fastidious US regulators so sanguine about such unusually aggressive and certain statements?
This is a most unusual situation and such an extraordinary outcome would seem to demand an extraordinary explanation.
Yet none seems forthcoming.
“The mRNA and the spike protein do not last long in the body” constitutes another key early safety claim similarly rooted in opaque or absent evidence or perhaps simply assumed or invented. (before being quietly retracted later).
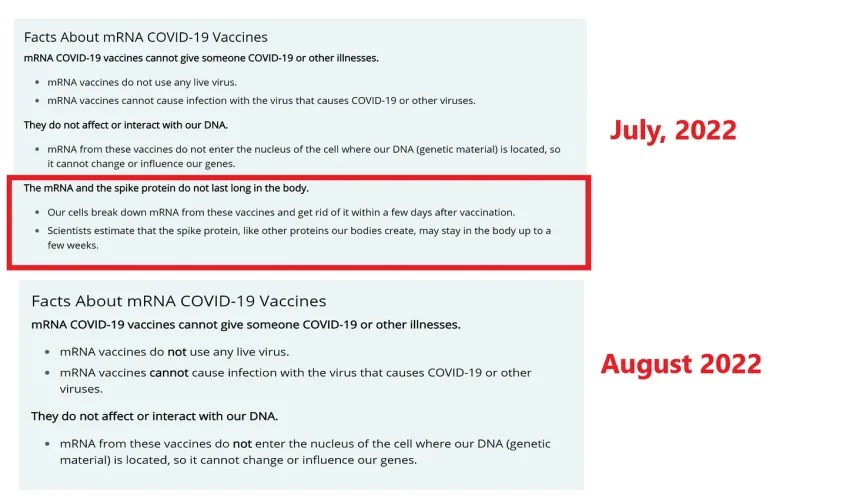
This claim also proved extravagantly incorrect.
Wherever one looks, it seems one finds that these grand claims of safety and efficacy were underpinned by a paucity or utter absence of supporting evidence.
Even the definitions themselves such as “Any positive for trace covid from a PCR test at a 40 Cycle Threshold is covid” or “No disease outcomes from vaccines are to be counted until 2 weeks after the second (or third) dose” which left a large window (4-6 weeks) during a period of known immune suppression from the jabs uncounted or even, in many cases, attributed to the unvaccinated in a manner that can make placebo look like high efficacy preventative are so unusual and inconsistent with past practice or sound science as to demand the most pointed of questions as to how such practices came to be and who the decision makers who put them in place were.
This series of unfounded claims and distortionary definitions seems both a poor and a deeply dangerous practice for Public Health.
If we are to have any hope of restoring faith in this field, we must ask and answer the pointed questions of “How did this happen?” and “At whose behest?”
Someone made these choices for some reason. Who and why would seem to be the bare minimum of post mortem here.
It is oft opined that a bad map is worse than no map at all and in this, I must wholeheartedly agree. The public health agencies in America have become the most calamitous of cartographers.
If we would seek to have the agents of public health act as something other than a marketing arm and apologist for the revolving door of Pharma with whom they seem to so regularly swap staff and sinecure then it must once more be turned to serve the public. It may do so only if it regains the public trust and such trust, once lost, may only be restored by asking the hard questions and diligently following the answers wherever so they may lead until we may understand what went wrong, hold the malefactors to account, and effect the means to prevent this from happening again.
Please make no mistake, if nothing is done and this is swept beneath some august Congressional rug or societal memory hole, it will happen again. And soon. This is not a choice I would have for America and one I do not believe you should countenance.
Public health runs on public trust.
I ask you to restore it.
Featured Video

The Truth About the Trump Shootings with Ken Silva
or go to
Aletho News Archives – Video-Images
From the Archives
The Geopolitics behind the War in Yemen (I)
By Mahdi Darius NAZEMROAYA | Strategic Culture Foundation | 30.03.2015
The United States and the Kingdom of Saudi Arabia became very uneasy when the Yemenese or Yemenite movement of the Houthi or Ansarallah (meaning the supporters of God in Arabic) gained control of Yemen’s capital, Sanaa/Sana, in September 2014. The US-supported Yemenite President Abd-Rabbuh Manṣour Al-Hadi was humiliatingly forced to share power with the Houthis and the coalition of northern Yemenese tribes that had helped them enter Sana. Al-Hadi declared that negotiations for a Yemeni national unity government would take place and his allies the US and Saudi Arabia tried to use a new national dialogue and mediated talks to co-opt and pacify the Houthis.
The truth has been turned on its head about the war in Yemen. The war and ousting of President Abd-Rabbuh Manṣour Al-Hadi in Yemen are not the results of «Houthi coup» in Yemen. It is the opposite. Al-Hadi was ousted, because with Saudi and US support he tried to backtrack on the power sharing agreements he had made and return Yemen to authoritarian rule. The ousting of President Al-Hadi by the Houthis and their political allies was an unexpected reaction to the takeover Al-Hadi was planning with Washington and the House of Saudi. … continue
Blog Roll
 Aletho News
- IRGC air defenses destroy another US MQ-1 drone over Strait of Hormuz
- Imran Khan’s entire immediate family detained in Pakistan ahead of mass protest demanding his release
- EU nation detains former presidential frontrunner
- Leaked: Britain’s Sham Conviction Of Hashim Thaci
- Seyed M. Marandi: U.S. Strike Imminent – Toward Total War in the Middle East
- Russia Voted Under Fire. Washington Is Loading the Tankers.
- 12 Things Your Oncologist Was Trained Not to Tell You
- Anthrax Attacks Paved Way for COVID-Era ‘Junk Drugs and Vaccines’
- How Real Is the Impact of Western Sanctions on Israel?
- France, You Are Guilty: How Paris Turned Western Sahara into the Maghreb’s Powder Keg
- If Americans Knew
- Israeli president pardons soldier convicted for killing wounded Palestinian
- Singer Ed Sheeran says his ‘heart broken’ by Gaza devastation, addresses Macklemore controversy
- Israel Has Imprisoned Female Journalist Bushra Al-Tawil Without Trial Or Charge In Solitary Confinement For Past Month
- Israel poised to teach West Bank a lesson after one Israeli killed – Daily Update
- Salah Sarsour’s Legal Team Says DHS Has Not Met Its Burden to Prove He Is Deportable
- An analysis of tax forms by The Intercept show Kraft’s charity and LLC have donated to Friends of the IDF and AIPAC’s super PAC.
- Israeli attacks kill four Palestinians in Gaza – Daily Update
- Inside Gaza’s death trap of collapsing, bombed-out buildings
- The everyday items Israel bans from Gaza every day
- Inside the siege, the ruined buildings of Gaza – Daily Update
- No Tricks Zone
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
- Fear Of Debate: Alarmist German Climate Scientist Calls On Mainstream Media To Discredit Skeptic Voices
 Aletho News
