GMC Blinks First: Regulator Declines to Investigate Dr Aseem Malhotra Over Vaccine Warnings in BBC Interview

BY NIALL MCCRAE | THE DAILY SCEPTIC | JANUARY 21, 2023
To paraphrase the Sound of Music song, “How do we solve a problem like Malhotra?” After receiving several complaints, the General Medical Council has decided not to investigate cardiologist Dr. Aseem Malhotra, who has become a thorn in the side of the medical profession.
Professional regulators have been at the forefront of pandemic discipline, contributing to a culture of fear among practitioners. Severe action has been taken against registrants who criticise or do not comply with the official narrative. I know this from my experience as an officer of the Workers of England Union, representing members brought before the Nursing and Midwifery Council on charges of bringing the profession into disrepute. Apparently the public must be protected against nurses who don’t believe that masks stop airborne respiratory viruses, or who believe in informed consent for novel mRNA vaccines.
A significant strike against this censorial tyranny was by general practitioner Sam White last year. Dr. White was ordered, as a condition of maintaining his clinical licence, to delete his social media posts about COVID-19 and to refrain from making similar comments. Dr. White took the GMC to the High Court and won. The condition was overturned as a breach of his rights to freedom of expression under the Human Rights Act 1998.
Whereas White was an early critic of COVID-19 policy, Malhotra is a relatively recent convert. Initially he promoted the vaccine, but when his fit and healthy father died shortly after receiving the injections, Malhotra changed his mind and began speaking out against the mass vaccination programme. His personal loss came alongside his observation in clinical practice of a marked increase in myocarditis cases (as well as blood clots and other cardiac complications). Malhotra had a review paper published on this phenomenon, and his findings of iatrogenic harm are corroborated by other medical scientists.
Malhotra has repeatedly urged suspension of the vaccination programme until the risks are better understood. He became a darling of vaccine sceptics, with his charismatic and compassionate voice doing the rounds of alt media channels and independent-minded broadcasters working for more mainstream channels (such as Tucker Carlson’s show on Fox News, and Neil Oliver on GB News ). However, he was ignored by the legacy media, and it was not until two weeks ago, when he took the opportunity of a BBC interview on statins, that his call was more widely heard.
The context for Malhotra’s BBC appearance was a claim by Chief Medical Officer Chris Whitty that cardiac morbidity had increased as a result of limited access to statins during lockdown. Malhotra disagreed, explaining that myocarditis is unrelated to cholesterol level, which statins are meant to control. He instead blamed the vaccines, telling the BBC presenter that this radical medical intervention should be halted. Cue outrage.
The Guardian did a particularly nasty report on Malhotra, smearing him as a peddler of an ‘anti-vax’ conspiracy theory. Numerous doctors expressed their outrage on social media, angered by the BBC giving a platform to this known sceptic, who they accused of hijacking an interview on a different topic. Some reported Malhotra to the GMC.
The GMC’s decision not to act against Malhotra is a victory for science, ethics and common sense, but we should not get ahead of ourselves. This was a reluctant decision by the regulator, as the wording of their response to the referrals shows:
We recognise that Dr Malhotra has views on the COVID-19 mRNA vaccines that are at odds with the national and international scientific and medical communities. We also recognise that his words are strong and there is a question around the accuracy of his statements. There is currently no evidence that Dr. Malhotra has engaged in the type of Covid conspiracy related conduct that has to date justified regulatory action.
Note here the emphasis on consensus, as if that amounts to truth. It seems that if Malhotra had followed the likes of James Delingpole or Maajid Nawaz down the rabbit hole of globalist conspiracy, he would have been in big trouble. The GMC continued:
We also feel it is relevant that Dr. Malhotra started expressing his concerns about the vaccines in late 2021 and by this time the vaccine programme was well underway with the vast majority of vaccines delivered before this time. We would suggest that Dr. Malhotra’s impact on the COVID-19 vaccination programme in the U.K. could only have been negligible.
This is the most worrying line in the GMC response. If Malhotra is right about the risks of these vaccines, the GMC should be concerned that doctors were inhibited from speaking out earlier, thereby potentially saving lives. Instead, the GMC assumes that Malhotra is wrong, and that his remarks have not stopped the biggest vaccination drive in history.
The GMC acknowledged that Malhotra has a right to freedom of expression under Article 10 of the Human Rights Act, although that is not an absolute right for a medical practitioner. His outspoken opinions on the vaccines, according to the GMC, are “not so egregious as to justify a public hearing and a forum for further scepticism to be aired as to aspects of the COVID-19 pandemic and response”.
This, I believe, is the real reason why the GMC has decided not to take any further action. Any proceedings would inevitably attract publicity and give Dr. Malhotra a platform to air his sceptical views. Ultimately, the truth will get out, and those who tried to hide it will be judged by history.
Dr. Niall McCrae is a former university lecturer who now works for the Workers of England Union.
New Study Shows Respiratory Syncytial Virus Not a Hospitalization Threat to Frail Adults
Media Hype Died as Data Show Ambulatory Management is Sufficient
By Peter A. McCullough, MD, MPH | Courageous Discourse | January 21, 2023
I have noticed on occasion over the past three years that media hype can well up over an infectious disease threat and then for unexplained reasons the story is dropped without follow-up or resolution. Examples include a global hepatitis outbreak in children, monkeypox, group A strep, and the “tripledemic” of COVID-19, influenza, and respiratory syncytial virus (RSV). Some of these news stories escalate to a frenzy and in the case of monkeypox, President Biden declared a national emergency.
Americans are wondering to this day where is the monkeypox emergency? How has it impacted our lives? Most doctors including myself have never seen a case!
Last fall the fervor over RSV, largely a mild infantile illness was amplified to a point where some doctors were pushing for a third national emergency declaration (SARS-CoV-2, monkeypox, RSV). We were told new vaccines would be needed in every human being. Like the other stories, the RSV scare seems to have disappeared in the media cycle.
Concerns may be allayed in some part by a recent paper from Juhn et al of N=2325 adults including frail seniors that demonstrated a negligible risk (1 hospitalization, 0 deaths) with adult RSV usually manageable with outpatient nebulizer treatments for a few days.
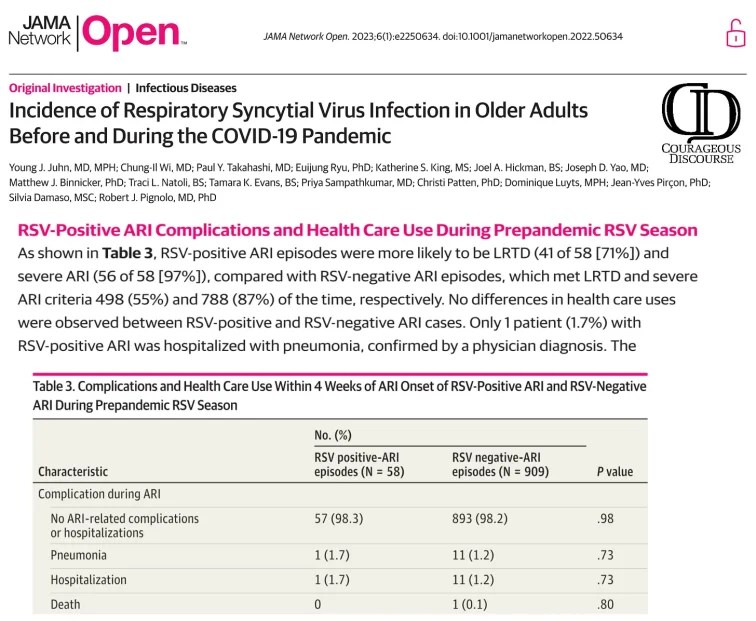
If it occurs in infants and small children, a few hours in an urgent care or emergency department may be needed for breathing treatments, but again the outcomes are very favorable and certainly do not warrant vaccination, frightening news stories, or calls for national emergencies.
Pediatricians Call for National Emergency as Flu, RSV Surge Written by Lisa O’Mary Nov 17 2022
PR firm CEO tells Davos: businesses need to starve platforms that spread “disinformation” of revenue
Demonetizing non-conformity
By Cindy Harper | Reclaim The Net | January 20, 2023
During a panel discussion on “disrupting distrust” at the World Economic Forum in Davos, Switzerland, it was posited that combating the spread of “disinformation” by “right-wing groups” is a crucial step in restoring trust in non-governmental organizations (NGOs) that collaborate with governments and other entities on initiatives aimed at ameliorating global issues.
The CEO of global communications firm Edelman, Richard Edelman, noted with regret the decline in trust towards NGOs in recent years and attributed this shift to the influence of right-wing groups, while noting that companies are now viewed as more trustworthy in addressing matters pertaining to civil society.
“My hypothesis on that is right-wing groups have done a really good job of disenfranchising NGOs,” he said. “They’ve challenged the funding sources. They’ve associated you with Bill Gates and George Soros. They’ve said that you’re world people, as opposed to actually what you are, which is local.”
Edelman said that platforms that allow “disinformation” need to be stripped of advertising, saying that what “business needs to do is deprive platforms that spread disinformation of oxygen, stop advertising, pull your promotion money, make sure that they understand that they have a consequential impact on society.”
The Re-education of Dr Sally Price
A culture of fear and censorship in the Australian medical profession
By Rebekah Barnett | Dystopian Down Under | January 14, 2023
On a Friday in August 2021, Dr Sally Price received a phone call from the Australian Health Practitioner Regulation Agency (AHPRA). There had been an anonymous complaint against her, and AHPRA was to follow up with an investigation.
“So of course, I was checking my email all afternoon,” says Dr Price, who describes the ensuing investigation as, “destructive” and “very stressful.”
At the time, Dr Price was a practicing GP in Perth, with additional qualifications in nutritional medicine and Ayurveda. In over 30 years of practice, Dr Price had never received a complaint, and she was mystified as to which of her patients could possibly have complained to AHPRA.
When the email from AHPRA finally arrived in her inbox, Dr Price was surprised to find that the complaint was not from a patient, but from a social media follower who, to the best of her knowledge, she has never met or had any contact with.
The complaint centred around five Facebook story posts, four of which were reposted content from a non-partisan, pro-choice activist group called Reignite Democracy Australia (RDA). Two of the posts referenced efforts of politicians (in Australia and Italy) to resist vaccination mandates. Another story was a repost offering insight into the physiological effects of the fear response.
The complainant characterised the reposts as “anti-vaccination,” though none of the posts gave advice on vaccination or stated any opinion on the Covid vaccines. This was all that was required for AHPRA to launch an official investigation into Dr Price’s conduct.
AHPRA’s position statement on the Covid vaccination rollout (March 2021) set the bar for such vague complaints to trigger investigations, when they specifically barred doctors from expressing messages that could be construed as anti-vaccination on their social media:
”There is no place for anti-vaccination messages in professional health practice, and any promotion of anti-vaccination claims including on social media, and advertising may be subject to regulatory action.”
Dr Price was given two weeks to respond, during which time she engaged with her indemnity organisation in a highly stressful back-and-forth, knowing that her reputation, and maybe even her licence were on the line. Dr Price was strongly advised to offer to undergo ‘re-education’ at her own cost, so as to avoid more serious consequences, such as suspension, or having conditions imposed.
AHPRA agreed that Dr Price should undergo 10 hours of re-education and submit a letter of reflection detailing what she had learned from the process. “What you have to do is pull your forelock and tell AHPRA that you’ve been a very naughty girl,” says Dr Price.
As part of her re-education, Dr Price was required to study the Australian Medical Association’s (AMA) Code of Ethics (2017). Ironically, this firmly established in Dr Price’s mind that the AMA’s Code of tehics and AHPRA’s position statement on the Covid vaccination rollout were at odds with each other. “As I studied the AMA Code of Ethics, I was struck by how AHPRA’s position statement overrode our professional ethics, and that had me more deeply concerned,” says Dr Price. “It highlighted to me that none of this was ok.”
The AMA’s Code of Ethics states that doctors must, “consider first the well-being of the patient,” (Article 2.1.1) and that they must provide full informed consent before undertaking any tests, treatments or procedures (Article 2.1.4). Dr Price says that AHPRA’s position statement and hawkish regulatory behaviour put the public health agenda before the patient and made it “impossible” for doctors to provide valid informed consent to patients.
AHPRA’s unilateral decision that all doctors must fall in line with the vaccination rollout was also in conflict with the AMA Code’s provision that doctors may conscientiously object to providing certain treatments or procedures (Article 2.1.13), and that they may publicly state opinions contrary to the status quo (Article 4.3.3). Further, the Code requires that doctors “practise effective stewardship, the avoidance or elimination of wasteful expenditure in health care…” (Article 4.4.1), and that they use their “knowledge and skills to assist those responsible for allocating health care resources, advocating for their transparent and equitable allocation.” (Article 4.4.3) These articles imply a responsibility for doctors to speak out and take action when they believe that public health policy could be improved upon.
Feeling conflicted about how to practice good medicine under these conditions, Dr Price decided to take some leave to reflect and regroup. She lodged a complaint with Ahpra and the Ombudsman, requesting either a waiver to excuse her from the requirements of AHPRA’s position statement, or that AHPRA explain how she might be able to practice under their conditions whilst also keeping to the AMA’s Code of Ethics. No waiver or explanation was provided, and so Dr Price determined that continuing to practice as a GP was untenable. Her registration has since lapsed.
Dr Price says that, as it stands, the system has strayed from its primary purpose of letting doctors be doctors, and putting patients first. She speaks to a culture of fear within the medical profession. “The thing to understand is that doctors feel like someone is always behind them waiting to stab them in the back or put a bag over their head. That’s how it feels being under AHPRA,” she says.
The censorial nature of AHPRA’s regulatory practices was brought into the national spotlight several weeks ago by former AMA president Dr Kerryn Phelps, who recently revealed that she is Covid vaccine injured. In a submission to the federal government’s Long Covid Inquiry (Submission #510), Phelps wrote, in reference to the aforementioned AHPRA position statement,
“Regulators of the medical profession have censored public discussion about adverse events following immunisation, with threats to doctors not to make any public statements about anything that ‘might undermine the government’s vaccine rollout’ or risk suspension or loss of their registration.”
This is a view also held by cardiologist and Australian Medical Professionals’ Society (AMPS) founder, Dr Chris Neil, who warned in a recent article for Spectator Australia, that many medical professionals believe that not only is the AHPRA position statement unlawful, but that “it is at the root of a dangerous shift in Australian Medicine.” Neil points to the changes to the National Law for Health Practitioner Regulation introduced last October in the Queensland Parliament.
The changes, which the AMA strongly opposed, will further compel doctors to fall in line with public policy decided by bureaucrats, and will create a culture of ‘guilty until proven innocent’ by way of publicly naming and shaming medical professionals who are under investigation. AMPS has gone on the defensive with a Stop Medical Censorship national tour, on which medical, legal and other professionals gather to speak to audiences about the implications of censorship in medicine.
Dr Price says she feels damaged by the experience of being investigated by AHPRA, and she may not return to the profession. “I’m not sure that I want to come back. If medicine were to return to its ethical code, I will reconsider.”
Florida Governor Ron DeSantis’ “Prescribe Freedom” plan bans vaccine passports, supports doctors’ free speech

By Cindy Harper | Reclaim The Net | January 19, 2023
Florida’s Republican Gov. Ron DeSantis plans to introduce legislation that will, among other things, stop Florida from being a “biomedical security state.” The legislation will ban all vaccine passport mandates.
DeSantis said the purpose of the legislation is to “prescribe freedom.”
“When the world lost its mind, Florida was a refuge of sanity, serving strongly as freedom’s linchpin,” the Republican governor said on Tuesday. “These measures will ensure Florida remains this way and will provide landmark protections for free speech for medical practitioners.”
“It required us over the past few years to stand against major institutions in our society: The bureaucracy, the medical establishment, legacy media, and even the President of the United States who, together, were working to impose a biomedical security state on society,” he added.
DeSantis’ surgeon general Dr. Joseph Ladapo said he supports the bill because it would protect the free exchange of ideas between medical professionals.
“As a health sciences researcher and physician, I have personally witnessed accomplished scientists receive threats due to their unorthodox positions,” Ladapo said. “However, many of these positions have proven to be correct, as we’ve all seen over the past few years. All medical professionals should be encouraged to engage in scientific discourse without fearing for their livelihoods or their careers.”
The legislation would protect medical professionals’ freedom of speech by protecting their religious views and their right to disagree with the preferred narrative. The bill would also protect medical freedom of choice by banning discrimination based on vaccination status, testing, and mask-wearing.

Related:
California’s chilling medical misinformation law is an affront to the US constitution
Germany, “standing atop a billion-dollar mountain of masks,” begins to incinerate the rapidly expiring surplus
eugyppius: a plague chronicle | January 20, 2023
From Welt :
Authorities have come up with a term that sounds at least halfway sane. They’re calling it “thermal reprocessing.” Four federal states now claim to have thermally reprocessed – or, in plain language, to have incinerated – a total of 17.25 million expired Corona masks.
Baden-Württemberg has destroyed 6.1 million masks, Saxony 5.5 million, North Rhine-Westphalia 5 million, and Mecklenburg-Vorpommern 656,000 …
The Federal Ministry of Health (BMG) in Berlin has also “thermally recycled” masks in recent months. The number so far is “less than one million units,” a spokesperson said … The destroyed masks were purchased during the peak of the pandemic, and have exceeded their expiration date …
The federal and state governments are currently standing atop a billion-dollar mountain of masks. According to information provided by the Ministry of Health in September, there are a total of 3.7 billion masks in the federal inventory … The federal states have have an additional 180 million Corona masks at their disposal …
The states want to burn even more masks, but for the moment they’re not allowed, because much of the surplus in their possession is technically federal property. Thus they’ve begun begging the government to take the masks back:
“The Interior ministry of Hesse, together with many ministries of other states, have turned to the federal government with an urgent request to either take back their unusable masks … or grant permission for their destruction…” says a spokesperson. Unfortunately, the federal government has not yet agreed. “The Federal Ministry of Health has referenced uncertainties in customs law that the government has not yet been able to clarify.”
I’m going to go out on a limb here, and say the Scholz government is reluctant to write off the masks purely because of the negative publicity it’ll generate. I can’t imagine how customs regulations would prevent the Health Ministry from destroying its own expiring property.
Karsten Klein, chairman of the FDP faction in the Bundestag Budget Committee, has criticised the previous government’s over-procurement: “The coalition has inherited a hugely expensive mask mountain [Merkel health minister] Jens Spahn. As important as federal support for procuring masks was in 2020, under Spahn it led to literal frenzied buying that completely lost sight of actual demand” …
But we haven’t even gotten to the best part. The idiot pandemicists are still hoarding masks, even as they’re burning them:
… Additionally, the “National Health Protection Reserve is still stockpiling masks. The Reserve was established in mid-2020 by the Merkel government to prevent future shortages. According to the Ministry of Health, there are currently 245 million masks in the reserve, part of which will expire at the end of 2023.
Doubts about the usefulness of the Reserve are growing. In November, the Budget Committee called on the government to … examine “whether a federal physical stockpile for the health system is at all necessary or economical” …
For the taxpayer, mask procurement is very expensive. The costs at the federal level alone have totalled 5.8 billion Euros since the beginning of the pandemic.
It’s just so astounding, this entirely pointless and still ongoing mass delusion. Masks do nothing to stop infection, we have spent three years learning in excruciating detail that they do nothing to stop infection, we are now setting fire to millions of masks heedlessly purchased at the height of pandemic hysteria when there was every reason to expect that masks would do nothing to stop infection, and still we’re pouring millions of Euros into some kind of retarded national strategic mask reserve that will also surely be incinerated in the coming years because masks do nothing to stop infection. Even more unfathomable is this ridiculous fiction that useless products which do nothing can ever “expire.” What is the fear, that expired masks will do even more of nothing than new masks?
Everything about Corona is such a multifaceted ridiculous farce.
MHRA Passes the Buck: “All the Covid Vaccine Authorisation Decisions Were Taken by the Government Minister”
The Blame Game Begins
BY NICK DENIM | THE DAILY SCEPTIC | JANUARY 19, 2023
I have just received a very interesting MHRA reply to an FOI request about whether the Healthy Secretary delegated Covid vaccine decisions to the MHRA.
MHRA said “All the Covid vaccines and therapeutics authorisation decisions were taken by the Licensing Minister and were not delegated.”
What makes this so interesting is the wider context. Under the Human Medicines Regulations, the Licensing Authority is the Secretary of State for Health. He or she delegates to MHRA all the work associated with that – licensing of medicines, pharmacovigilance, inspection of manufacturers, enforcement and so on.
But for the Covid vaccines, MHRA is saying that the Secretary of State personally took all the decisions.
I read that as the blame game having started. I’ll explain why.
Back in 2020, MHRA would have known only too well that the clinical trials had been rushed (10 months compared with typical time to market of 5-10 years), had not been comprehensive (e.g. limited pharmacokinetics/pharmacodynamics) and wouldn’t finish until 2024. There were many warnings from experts around the world. MHRA’s line about ‘rolling review’ was, and remains, bunkum.
MHRA scientists and officials would have known about the problems (with all medicines) of scaling up production from small-scale, laboratory-based production for trials purposes to full-scale production. For example, larger quantities of ingredients can be more difficult to mix. They wouldn’t therefore have been surprised to have seen batch problems with the Covid vaccines around the world. One batch resulted in the hospitalisation of 120 children in Vietnam. One batch caused ocular injury to nurses when a vial was broken. In Japan, 1.63 million doses were recalled due to metallic contamination. Probably just the tip of the iceberg.
MHRA then saw adverse event reporting starting to reveal serious safety issues in the U.K. and around the world. First, myocarditis and blood clots, in March 2021, a few weeks after approval of the AstraZeneca vaccine (now effectively withdrawn) and later other heart issues, neurological problems and immunosuppression with Pfizer and Moderna.
MHRA knew in 2020 that the risk to younger age groups from Covid was very low and after rollout it would have seen assessments of vaccine effectiveness falling month on month. It wriggled hard against the evidence in the UKHSA weekly surveillance reports that vaccine effectiveness was even negative for younger age groups.
Since then the Covid vaccine narrative has continued to take a pounding as more clinicians around the world speak up, the research evidence about cardiac, neurological and immunosuppression problems continues to pile up, and the 1,000 per week excess deaths have still not been explained.
MHRA might have been criticised by Baroness Cumberlege for being “unresponsive and defensive”, but its staff aren’t all deaf, blind or stupid. They knew.
So my inference is that the blame game has started.
Mind you, MHRA is on a sticky wicket in any blame game. There are serious shortfalls in its own safety management:
- It doesn’t have a process for investigating individual Yellow Card reports. It says it tries to investigate individual fatal and serious Yellow Card reports but it doesn’t have a process so it doesn’t know how many it has investigated (FOI 21/1109);
- It’s never had a safety audit (FOI 22/562);
- It doesn’t actively seek out real-world data – for example, real-world population-level data such as hospitalisation for ‘adverse events of special interest’ segmented by vaccination status and age. In January 2022, MHRA did not hold such data (CSC 88243) and in August 2022, UKHSA (FOI 22/472) only held population level info on thrombosis with thrombocytopenia syndrome (TTS). Instead, it waits for signal detection from Yellow Card reports of adverse events, which are massively under-reported;
- It doesn’t (or can’t) define the quantitative level of risk which is ‘acceptable’ as the basis of “acceptably safe” (FOI 22/390);
- It lost 20% of posts in 2021 due to funding cuts and has 20% vacancies below that new baseline (FOI 22/1007);
- It doesn’t have a process for delegating the authority to approve medicines for public use (FOI 22/1002) or governance of individuals competence (qualification, experience and training) (FOI 22/1007) to MHRA officers;
- It has hidden safety data (FOI 22/1083), redacting numbers in tables on the pretext of maintaining patient confidentiality;
- It appears quietly to have dropped a key strand of its Covid vaccine surveillance: Targeted Active Monitoring. FOI 22/1083 asked for a copy of the latest report but it was 15 months old (August 2021).
But back to “All the Covid vaccines and therapeutics authorisation decisions were taken by the Licensing Minister and were not delegated.” I’m left wondering what safety advice MHRA gave to Chris Whitty and ministers about the Covid vaccines back in late 2020 and early 2021 and subsequently as the serious safety issues started to emerge. And I wonder what briefings MHRA gave to the Commission on Human Medicines Expert Working Group on Covid Vaccine Benefits and Risks and to the COVID-19 Vaccines Safety Surveillance Methodologies Expert Working Group – neither publishes minutes.
It’s high time MPs and the Covid Inquiry started to ask some searching questions.
Until Nick retired a few years ago, he was a Senior Civil Servant in a Government Department.
The WHO wants to control everyone and everything, everywhere, in the name of health, equity and global solidarity
By Libby Klein | Reclaim Ethical Medicine | January 18, 2023
I’ve gone through the “Conceptual Zero Draft” of the proposed pandemic treaty, line by line, trying to figure out what it means. It wasn’t that much fun. But it sure had my eyes out on stalks more than once. Like the bit where WHO can decide what is a fact. And what is a “falsified” treatment. And appropriate money from member States and use it to foist vaccines on people in developing countries. And set aside protections in other treaties if they are inconvenient. And dictate what “social measures” are required in addition to “public health measures”.
My summary of the proposed pandemic treaty is set out below. Notice how broad the scope is. How comprehensively the WHO will be in control of everyone, everything, everywhere, all in the name of health, equity and global “solidarity”.
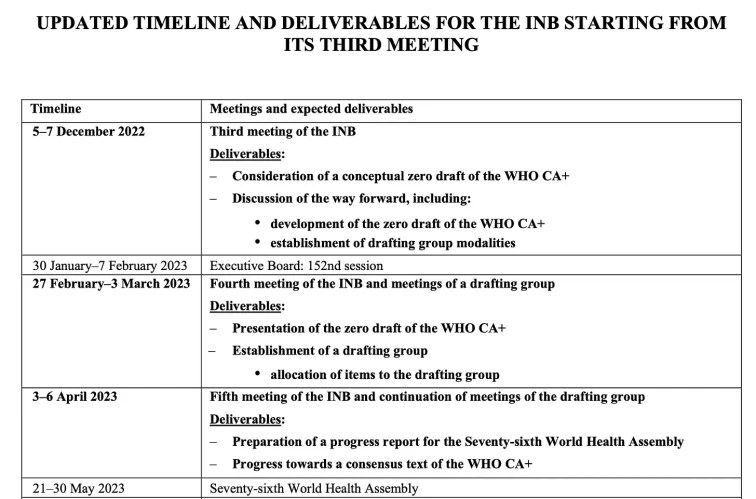
It’s urgent to oppose this before it rolls over us like a steamroller. The World Health Organisation is working hard on the next draft, for consideration by the “Intergovernmental Negotiating Body” in February, and the World Health Assembly in May 2023 (see timeline below)
(Is the treaty a furphy? A decoy to take our eye off the proposed amendments to the International Health Regulations, which are being negotiated in parallel with the treaty? Maybe, but there’s no way I want to take that risk and assume we can ignore it…)
MUST DO BEFORE FEBRUARY:
- Have a read of this amazing summary of everything the WHO is up to. There is also my summary of the treaty below. If you’re keen also read this plain English translation of the treaty.
- Pick out your 3 favourite horror-story highlights. Which 3 things are the most egregious, in your view?
- Tell your friends and your politicians we need to pull out of the WHO, before it’s too late.
Summary of the proposed pandemic treaty
The WHO is to control everyone and everything, everywhere, in the name of health, equity and global solidarity
Because of climate change and the likely increase in diseases crossing over from animals to humans, and increasing resistance to antibiotics, we are likely to have more pandemics in the future.
If we centralise decision-making about pandemics right across the globe, and if everyone falls into line, everyone can be healthier. Vaccines and other new medical products are the solution to pandemics and the proposed treaty.
The proposed treaty will make sure everyone can access vaccines and other new pandemic products. The WHO is the right body to control everything centrally, because it is the directing and coordinating authority for:
- international health work;
- convening and generating scientific evidence; and
- fostering international cooperation in global health governance.
Everything can impact health, so WHO has to be in charge of everything.
The world needs WHO to control and oversee:
- a global system for production and distribution of medical products
- stockpiling of medical products
- fast-tracking of research and development, and licensing of new products
- sharing of pathogen samples, genetic sequences, and benefits arising from those things being shared
- increased surveillance of diseases
- implementation of digital health
- a system of peer reviews and table-top exercises
- public health and social measures necessary for dealing with pandemics and situations that might give rise to pandemics
- censorship
- All must cooperate with the WHO in relation to all of the above measures.
- Wealthy nations must provide funding for the WHO and for developing countries
- Nations maintain their sovereignty – except where that means other nations are at risk
- Communities must be primed to accept public health measures and social measures
Tho WHO reckons this treaty is urgent and important, so:
- Start date is fast-tracked
- Once in, you can’t get out for 3 years
- The treaty can be amended by majority vote and amendments will apply to everyone.
- No adjudication by a court of law if parties are in dispute.
A “Consensus draft” draft will be considered at the May 2023 World Health Assembly. In other words: by May 2023, the content of the treaty already have been agreed in the backrooms.
Tony Blair calls for WEF and WTO to introduce “digital infrastructure” that monitors vaccination status
By Tom Parker | Reclaim The Net | January 19, 2023
Former United Kingdom (UK) Prime Minister Tony Blair has called for global organizations such as the World Trade Organization (WTO) and World Economic Forum (WEF) to push national governments to introduce “digital infrastructure” that monitors who has been vaccinated and who hasn’t.
Blair pushed for this government-controlled digital vaccine database during an appearance at the World Economic Forum’s 2023 annual meeting — a yearly event where powerful business leaders, politicians, and other influential figures meet in Davos, Switzerland to discuss the agendas they want to advance.
The former Prime Minister emphasized the importance of “technology and digital infrastructure” and data collection for surveilling the status of the vaccinated and unvaccinated.
“You need the data,” Blair said. “You need to know who’s been vaccinated and who hasn’t been. Some of the vaccines that will come on down the line will be multiple, there’ll be multiple shots. So you’ve got to have, the reasons to do with the healthcare more generally, but certainly, for a pandemic or for…vaccines, you’ve got to have a proper digital infrastructure, and many countries don’t have that. In fact, most countries don’t have that.”
Blair continued by suggesting that his digital vaccination status surveillance dragnet should be pushed through by the WTO (an intergovernmental organization that regulates international trade), the WEF (an unelected global organization that seeks to “shape global, regional and industry agendas”), and intergovernmental forums such as the Group of Twenty (G20) and the Group of Seven (G7).
“Who are the people that can make this happen?” Blair said. “How do you get the right partnerships in place?…That should happen in the G20 particularly, I think, which is… G7 is an important forum, but the G20 is the broader forum… You’ve got to work out what is it that you want to achieve in order to make sure that any future pandemic is properly handled and what are the partnerships that you’re going to create in order to ensure that the answers you get are the right answers. And then you’re going to have the mechanisms of implementation. And those mechanisms will be partly through the formal institutions that you have, like the WTO, and they’ll also be through organizations like yours [the WEF] which… I think… have many advantages because they don’t get landed with the same bureaucracy and frankly small pea politics around them.”
Blair’s call is the latest of several that he and his nonprofit, The Tony Blair Institute for Global Change, have made for an expansion of mandatory digital surveillance infrastructure.
His institute has called for digital IDs and said increased surveillance is a “price worth paying.” Blair himself has also called for mandatory vaccine passports.
And two of the global groups that Blair wants to help push through this digital surveillance system, the WTO and the WEF, are also huge advocates of digital surveillance systems.
The WEF and the WTO have previously pushed “global digital identity of persons and objects.” And the WEF regularly advocates for digital ID programs around the world. This year’s WEF 2023 annual meeting subjected journalists to some of the surveillance technologies it advocates for including digital IDs and biometric scanning.
Not only do these surveillance systems reduce individual privacy but vaccine passports discriminate against citizens and restrict their access to businesses and services.
And the WEF wants to expand this surveillance and discrimination via digital ID. It has proposed a system that monitors online behavior, biometrics, purchases, and more to determine access to a wide range of services.
Related:
How Big Government and Big Tech used COVID to accelerate the adoption of digital ID
Davos Leaders Collude to Force Permanent Global Vaccine Infrastructure
By Jefferey Jaxen | January 19, 2023
What is Davos? The World Economic Forum’s (WEF) annual meeting happens each year in the alpine Swiss ski resort town. Each year global leaders, elected and unelected, gather to collude on policy initiatives and hot button topics concerning humanity overwhelmingly without the consent of the people.
Intel coming out of this year’s meeting has had a more pressing, alarmist nature from the self-proclaimed global elite minders. Don’t worry, the meeting was still filled with the annual hypocrisy we are used to. Squadrons of ‘unsustainable,’ carbon-emitting private jets still flew in at will. Fleets of non-electric cars openly chauffeured the climate alarmist around while they preached about the end of gas vehicles and individual car ownership… for the planet of course. But lets turn to moves by the medical–industrial complex.
Coming off the back of a rushed Covid shot that failed to stop transmission and whose harms and shortcomings are still unraveling in the public conversation, the ‘global leaders’ of Davos used the forum to do what they always do in the uncomfortable spotlight – double down on agendas.
After some of the biggest, concerted global protests in a century against lockdowns and the digital Covid vaccine passports used by governments to enforce them, a call was made to expand such tools of restriction.
Former UK PM Tony Blair of Iraq war criminal fame apparently received his new marching orders speaking passionately at Davos for the implementation of a ‘national digital infrastructure.’
For ‘the vaccines coming down the line [that] will be multiple shots,’ for ‘vaccines [in general]’ and for ‘a pandemic’ Blair stated you need a proper digital infrastructure to know ‘who’s been vaccinated and who hasn’t.’
Founded in Davos by the Gates Foundation, the UK-based Wellcome Trust, the WEF and other governments, the Coalition for Epidemic Preparedness Innovations or CEPI was a central player in global Covid vaccine development efforts.
They now have a new ‘100 day goal’ which has been embraced by the G7 and G20 nations according to a Davos speech attended by Pfizer’s CEO Bourla, Blair and others.
To ‘accelerate vaccine development over and above what was achieved in 2020’ and to be able to deliver vaccines for new threats within 100 days.
So the idea again would be to sidestep proper safety testing to put massive mutation pressure on a new circulating virus or pathogen by vaccinating in a middle of an ongoing pandemic – something Dr. Geert Vanden Bossche has continually warned against.
CEPI’s goal to take Covid’s fast tracking vaccine development precedent and fast track it further has been aided, intentionally or unintentionally, by the newly enacted FDA Modernization Act 2.0 which allows drug and vaccine developers to rely upon computer modeling and testing with virtual patients in their safety assessments of new products to convince regulators they’ve been ‘de-risked.’
While the Davos crowd, along with many others in the public, like Neil DeGrasse Tyson, still believe the official narrative that the rushed Covid shot was a wild, safe and effective success, a growing critical mass continues to expose the truth.
Meanwhile, the FDA still doesn’t have ‘robust’ data from Pfizer or Moderna on their mRNA Covid shot product’s ability to cause potentially deadly heart inflammation.
A 2021 letter by the FDA to Pfizer gave the company until October 2025 to turn in their study looking at that piece which public health leaders and agencies will take, at face value, as the final word on the subject. Despite the foot-dragging by regulators, members of the public and medical community have filled the vacuum with actual data and warnings.
Top UK cardiologist Dr. Aseem Malhotra made history becoming one of the BBC’s most watched segments of the last two years [27.1M view on Twitter] warning about the myocarditis risk live on-air along with its role in the soaring number of excess deaths – the highest in 50 years according to the BBC.
Will the public accept digital restrictions on their life again in the form of vaccine passports?
Will the public accept new, multi-dose vaccines unpinned by even less safety testing and transparency than the mRNA Covid shots?
Are vaccine deaths being disguised as virus deaths?
By Professor Roger Watson and Dr Niall McCrae | TCW Defending Freedom | January 18, 2023
A new Covid-19 variant has appeared: XBB.1.5 (or ‘Kraken’, for the fear factor). This could explain why deaths are surging again, with Japan recording about 400 daily, and Australia (despite being in the height of summer) in the dozens. But are people really dying from the latest strain of coronavirus?
Excess mortality is highest in countries with the highest rates of Covid-19 vaccination. Correlation is not causation, but only the wilfully blind are describing this human toll as ‘baffling’. Ordinary people do not need scientific expertise to join the dots. At the very least, the authorities should be investigating this unprecedented rise in mortality as a possible iatrogenic disaster (ie caused by medical treatment, like thalidomide).
While there is growing public awareness of the lethality of the mRNA injections, the scientific orthodoxy is continuing to suppress the truth. In reports showing an increased incidence of cardiovascular disease after vaccination, researchers always moderate the message by stating that the benefits overwhelmingly outweigh the risks. However, many publications do not even consider the vaccines as a cause of illness or death.
Our editor alerted us to the article Covid Leading Cause of Death Among Law Enforcement for Third Year in Medscape. The data for this study of police officers across the US were taken from an annual report issued by the National Law Enforcement Officers Memorial Fund, titled 2022 End-Of-Year Preliminary Law Enforcement Officers Fatalities Report.
The report claims that in the past year 70 officers died in the line of duty of causes related to Covid-19. The good news is that this is ‘down dramatically from 2021, when 405 officer deaths were attributed to Covid’, but this was still a significant loss of front-line personnel, surpassing the number of deaths from firearms-related incidents.
The authors of the original report attribute the decline in deaths to ‘reduced infection rates and the broad availability and use of vaccinations’. However, this putative triumph of the Covid-19 vaccine needs more scrutiny than afforded by Medscape writer Lisa O’Mary.
In the original report we were keen to know how many law enforcement officers had died of other deadly infections. We anticipated influenza, meningitis, gastroenteritis and septicaemia among other potential killers, but none of these are mentioned in the report despite exposure on duty. We also wondered what the ‘background noise’ was in terms of how many law enforcement officers had died in total during the preceding years whether in the line of duty or not. Sadly, this figure was not reported either.
Covid-19, uniquely amongst infectious diseases, is being recorded as a cause of death in the line of duty but it is not clear why. We do not have any doubts about the bona fides of the National Law Enforcement Officers Memorial Fund and we do not, at face value, question their use of the numbers with which they have been provided. What is clear is that, like most of the public sector in the US (and the UK) they have fallen for the Covid-19 narrative and been willing participants in the ‘fear porn’ that has gripped so many otherwise well-meaning organisations.
We see several problems with the researchers’ claim that low Covid-19 mortality in officers was due to the vaccine. The first problem is the distinction between the definition of deaths ‘with’ as opposed to ‘of’ Covid-19 and the possible attenuation of the Covid-19 virus over time. Then, we are not informed in the report, and data seem unavailable, about the extent to which Covid-19 testing was or is still being carried out. If there was a significant reduction in Covid-19 testing between 2021 and 2022 that would be a significant confounding factor.
A bold claim about the success of the vaccine rollout would need, at least, to show how many law enforcement officers were vaccinated. Even then the outcome would not provide much insight into cause (vaccination) and effect (death from Covid-19).
It is not clear how many US law enforcement officers are vaccinated. There were indications that compulsory vaccination was going to be introduced for law enforcement officers. But there was also evidence that the law enforcement unions ‘pushed back’ against the idea. In fact, uptake of Covid-19 vaccines was so low amongst law enforcement officers that hundreds were reported to be dying and that, according to the Washington Post, they were a danger to the public. Therefore, it seems incongruous that, on the one hand, law enforcement officers are a public hazard due to their low Covid-19 vaccination status, and on the other hand have their own lives saved ‘dramatically’ as a result of the Covid-19 vaccines.
There is a more serious question that the researchers failed to ask themselves. Is it possible that some of the 70 officers dying in 2022, and some of the 405 in the year of the initial vaccine rollout, were victims of the Covid-19 vaccine? Consider, for example, an officer who is hospitalised for breathlessness, and is discovered to have dangerous blood clots. On admission he tests positively on a PCR test, which is notoriously prone to false positives. If this officer were to die, he would be added to the Covid-19 mortality figures. This is not fantasy, but the reality of how the pandemic has been perpetuated over the last three years – with the collusion of the scientific community.
Featured Video

Seyed M. Marandi: Toward Total War in the Middle East
or go to
Aletho News Archives – Video-Images
From the Archives
The Geopolitics behind the War in Yemen (I)
By Mahdi Darius NAZEMROAYA | Strategic Culture Foundation | 30.03.2015
The United States and the Kingdom of Saudi Arabia became very uneasy when the Yemenese or Yemenite movement of the Houthi or Ansarallah (meaning the supporters of God in Arabic) gained control of Yemen’s capital, Sanaa/Sana, in September 2014. The US-supported Yemenite President Abd-Rabbuh Manṣour Al-Hadi was humiliatingly forced to share power with the Houthis and the coalition of northern Yemenese tribes that had helped them enter Sana. Al-Hadi declared that negotiations for a Yemeni national unity government would take place and his allies the US and Saudi Arabia tried to use a new national dialogue and mediated talks to co-opt and pacify the Houthis.
The truth has been turned on its head about the war in Yemen. The war and ousting of President Abd-Rabbuh Manṣour Al-Hadi in Yemen are not the results of «Houthi coup» in Yemen. It is the opposite. Al-Hadi was ousted, because with Saudi and US support he tried to backtrack on the power sharing agreements he had made and return Yemen to authoritarian rule. The ousting of President Al-Hadi by the Houthis and their political allies was an unexpected reaction to the takeover Al-Hadi was planning with Washington and the House of Saudi. … continue
Blog Roll
 Aletho News
- HE SAVED LIVES. NOW HE FACES PRISON.
- Israeli lobby seeks to bind US fate to ‘Israel’: Araghchi
- Pakistan-Iran talks secure LNG shipment to Islamabad through Hormuz
- Black Sea grain crisis puts global wheat supplies under pressure
- IRGC air defenses destroy another US MQ-1 drone over Strait of Hormuz
- Imran Khan’s entire immediate family detained in Pakistan ahead of mass protest demanding his release
- EU nation detains former presidential frontrunner
- Leaked: Britain’s Sham Conviction Of Hashim Thaci
- Seyed M. Marandi: U.S. Strike Imminent – Toward Total War in the Middle East
- Russia Voted Under Fire. Washington Is Loading the Tankers.
- If Americans Knew
- Israeli Attacks in Gaza Kill at Least Seven Palestinians Over Three Days, including Woman and Child
- Trump’s militarization of Washington DC as he pursues Israel’s war against Iran
- Why Israel Fears This Searing New Documentary
- Huckabee aide solicited cash gifts from Israelis
- This isn’t sci-fi, AI is already killing people
- ‘The Most Brutal Thing’: Investigation Reveals Execution of Elderly Woman in Rafah
- Inside Israel’s ‘soft’ ethnic cleansing plan for Gaza through the eyes of its victims
- New online database tracks pro-Israel political donations in the United States
- Israeli president pardons soldier convicted for killing wounded Palestinian
- Singer Ed Sheeran says his ‘heart broken’ by Gaza devastation, addresses Macklemore controversy
- No Tricks Zone
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
- Fear Of Debate: Alarmist German Climate Scientist Calls On Mainstream Media To Discredit Skeptic Voices
 Aletho News
