Unvaccinated Students Told to Wear Different Coloured Wristbands So They Can be Identified
By Paul Joseph Watson | Summit News | September 29, 2021
First year students at the University of Bath have been given armbands by authorities to signal whether they’ve been double-vaccinated, with unvaxxed students having to wear a different colour.
“Freshers have been given wristbands to signal whether they are vaccinated against coronavirus amid anger at emerging “two-tier” university campuses,” reports the Telegraph.
“Students arriving this week at the University of Bath have been given a different coloured wristband on club nights if they can prove in advance they are double jabbed, or have Covid-19 immunity.”
Those who cannot prove they’ve been vaccinated are forced to enter a different queue in a clear example of segregation.
Bath is a notoriously left-wing city, as is its main university.
Vaccine passports are being enforced on campuses despite the government’s inability to impose them on the country after studies found they would be discriminatory and ethically unsound.
Students at Sheffield University must also present a COVID pass to gain access to enter freshers events or union nights out, meaning those who fail to comply will miss out on a social life altogether, with one student revealing how he felt “excluded” and feared being “shamed in front of friends.”
Students at Oxford and Cambridge are also being asked to disclose their vaccination status.
“We are worried that some universities appear to have implemented what amounts to a vaccine passport via stealth,” said Arabella Skinner, the director of parents group UsForThem.
“The idea of making students display their private medical information in such a public way is unacceptable. This echoes examples of discrimination we have seen in schools through the pandemic and raises concerns of a two-tier system for students to access education.”
Vaccine passports have largely proven to be ineffective everywhere they’ve been adopted, including in France where in many cases they are not even enforced.
After Israel set up one of the world’s first vaccine passport schemes, it experienced a record new wave of COVID infections.
The Vaccine Death Report
By Dr David John Sorenson & Dr Vladimir Zelenko MD | Principia Scientific | September 29, 2021
The purpose of this report is to document how all over the world millions of people have died, and hundreds of millions of serious adverse events have occurred, after injections with the experimental mRNA gene therapy.
We also reveal the real risk of an unprecedented genocide.
F A C T S
Our aim is to only present solid facts, and stay away from unfounded claims. The data is clear and verifiable. References can be found with all presented information, which is provided as a starting point for further investigation.
C O M P L I C I T Y
The data shows that we are currently witnessing the greatest organized mass murder in the history of our world. The severity of this situation compels us to ask this critical question: will we rise up to the defense of billions of innocent people? Or will we permit personal profit over justice, and be complicit?
Networks of lawyers all over the world are preparing class action lawsuits to prosecute all who are serving this criminal agenda. Hundreds of millions of people worldwide are rising up against this criminal operation. To all who have been complicit so far, we say: There is still time to turn and choose the side of truth. Please make the right choice.
W O R L D W I D E
Although this report focuses on the situation in the United States, it also applies to the rest of the world, as the same type of experimental injections with similar death rates – and comparable systems of corruption to hide these numbers – are used worldwide. Therefore we encourage everyone around the world to share this report. May it be a wake up call for all of humanity.
AT LEAST 5 TIMES MORE DEATHS
VACCINE DEATHS ARE SEVERELY UNDERREPORTED
VAERS data from the American CDC shows that as of August 26, 2021 already half a million people suffered severe side effects, including stroke, heart failure, blood clots, brain disorders, convulsions, seizures, inflammations of brain & spinal cord, life threatening allergic reactions, autoimmune diseases, arthritis, miscarriage, infertility, rapid-onset muscle weakness, deafness, blindness, narcolepsy and cataplexy.
Besides the astronomical number of severe side effects, the CDC reports that approx. 16,000 people died as a result of receiving the experimental injections. However, according to a CDC whistleblower who signed a sworn affidavit, the actual number of deaths is at least five times higher. This is what the CDC healthcare fraud detection expert Jane Doe officially stated in a sworn affidavit:1
‘I have, over the last 25 years, developed over 100 distinct healthcare fraud detection algorithms, both in the public and private sector. (…) When the COVID-19 vaccine clearly became associated with patient death and harm, I was inclined to investigate the matter. It is my professional estimate that VAERS (the Vaccine Adverse Event Reporting System) database, while extremely useful, is under-reported by a conservative factor of at least 5 (…) and have assessed that the deaths occurring within 3 days of vaccination are higher than those reported in VAERS by a factor of at least 5.’
The CDC is also vastly underreporting other adverse events, like severe allergic reactions (anaphylaxis). The Informed Consent Action Network (ICAN) reported that a study showed that the actual number of anaphylaxis is 50 to 120 times higher than claimed by the CDC. 2, 3
On top of that, a private researcher took a close look at the VAERS database, and tried looking up specific case-ID’s. He found countless examples where the original death records were deleted, and in some cases, the numbers have been switched for milder reactions. He says:
‘What the analysis of all the case numbers is telling us right now is that there’s approximately 150,000 cases that are missing, that were there, that are no longer there. The question is, are they all deaths?’4
How criminal the CDC is, was also revealed a few years ago, when researchers investigated the link between vaccines and autism. They found that there indeed is a direct connection. So what did the CDC do?
All the researchers came together and a large dustbin was placed in the middle of the room. In it they threw all the documents that showed the link between autism and vaccinations. Thus, the evidence was destroyed.
Subsequently, a so-called ‘scientific’ article was published in Pediatric, stating that vaccinations do not cause autism. However, a leading scientist within the CDC, William Thompson, exposed this crime. He publicly admitted:
‘I was involved in misleading millions of people about the possible negative side effects of vaccines. We lied about the scientific findings.’ 5
Maybe the worst example of criminal methodology used to hide vaccine deaths is the incredible fact that the CDC doesn’t consider a person vaccinated until two weeks after the injection.
Therefore everyone who dies within the first two weeks after being injected, is not considered a vaccine death, further skewing the data. 6,7
MODERNA: 300,000 ADVERSE EVENTS
HUNDREDS OF THOUSANDS IN THREE MONTHS TIME
A whistleblower from Moderna made a screenshot of an internal company notice labeled “Confidential – For internal distribution only”, showing there were 300,000 adverse events reported in only three months time.” This is a quote from this confidential notice:
‘This enabled the team to effectively manage approximately 300,000 adverse event reports and 30,000 medical information requests in a three month span to support the global launch of their COVID-19 vaccine.’
https://alexberenson.substack.com/p/some-actual-news
LESS THAN 1% IS BEING REPORTED
STUDY SHOWS REAL NUMBER OF ADVERSE EVENTS IS 100X HIGHER
All this information already shows us that the number of adverse events and deaths is a multitude of what is being told to the public. The situation is however still far worse, than most of us can even imagine.
The famous Lazarus report from Harvard Pilgrim Health Care inc. in 2009 revealed that in general only 1% of adverse events from vaccines is being reported:
‘Adverse events from drugs and vaccines are common, but underreported. Although 25% of ambulatory patients experience an adverse drug event, less than 0.3% of all adverse drug events and 1-13% of serious events are reported to the Food and Drug Administration (FDA). Likewise, fewer than 1% of vaccine adverse events are reported.’
LESS THAN 1% IS BEING REPORTED
STUDY SHOWS REAL NUMBER OF ADVERSE EVENTS IS 100X HIGHER
All this information already shows us that the number of adverse events and deaths is a multitude of what is being told to the public. The situation is however still far worse, than most of us can even imagine.
The famous Lazarus report from Harvard Pilgrim Health Care inc. in 2009 revealed that in general only 1% of adverse events from vaccines is being reported:
‘Adverse events from drugs and vaccines are common, but underreported. Although 25% of ambulatory patients experience an adverse drug event, less than 0.3% of all adverse drug events and 1-13% of serious events are reported to the Food and Drug Administration (FDA). Likewise, fewer than 1% of vaccine adverse events are reported.’
REASONS FOR UNDERREPORTING
THE POPULATION IS UNAWARE AND MISINFORMED
The reason that less than 1% of adverse events is reported, is first of all because the vast majority of the population is not aware of the existence of official reporting systems for vaccine adverse events.
Secondly, the pharmaceutical industry has been waging an unrelenting media war the past decades against all medical experts, who attempted to inform the public about the dangers of vaccines.
One deployed strategy is name calling, and the negative label ‘anti-vaxxer’ was chosen to shame and blame all scientists, physicians and nurses who speak truth.
Because of this criminal campaign of aggressive suppression of adverse events data, the majority of the population is clueless that vaccines can cause any harm at all.
The message the general public constantly hears and sees, couldn’t be further from the truth: ‘Vaccines are safe and the best way to protect yourself from disease.’ The thousands of books, scientific studies, and reports documenting the devastating effects of vaccines in general, have been suppressed by all possible means. The undeniable fact that children (and people of all ages, for that matter) are far more ill today than ever before in history, while at the same time they are the most vaccinated population in all of history, is flatly denied.
The widespread propaganda by the vaccine companies, who use government agencies as their main carrousel, simply told humanity for decades that adverse events are a very rare occurrence.
When vaccinated people therefore suffer from serious adverse events, it doesn’t even occur to them that this could be from previous injections, and therefor don’t report it as such.
During the current world crisis the attacks on medical experts who are warning about vaccines, have gone to an even higher level. Medical experts are now being completely deplatformed from all social media, their websites are deranked by Google, entire YouTube channels are deleted, many have lost their jobs, and in some countries medical experts have been arrested, in an attempt to suppress the truth about the experimental covid injections.
Scientists who speak out against vaccines are even labeled ‘domestic terrorists’. All means are deployed by the criminal vaccine cartel to suppress the truth.
As a result countless medical professionals are afraid to report adverse events, which further contributes to the underreporting of these side effects. Additionally, the amount of scientific information warning for these dangerous biological agents, and the number of medical experts warning humanity, is so overwhelming and almost omnipresent – despite the aggressive attempts to silence them – that it is virtualy impossible for any medical professional to not be at least somewhat aware of the risk they are taking, by administering an untested DNA altering injection, without even informing their patients of what is being injected into their body.
If they then see their patients suffer or die, they are naturally afraid of being held accountable, so they refuse to report it.
Lastly: many medical professionals receive financial incentives to promote the vaccines. In the United Kingdom for example nurses get ₤10 per needle they put into a child. That again is a reason for them to not report adverse events.
They see large numbers of patients come in with serious adverse reactions, like heart failure, and they notice how the authorities of their hospitals are not reporting any of these vaccine injuries. Dr. Maria Gonzales, ER doctor from the U.S. Dept. of Health and Human Services, expresses her outrage about this in the Phoenix Indian Medical Center.
She discusses with a colleague how a patient was vaccinated and as a result got heart failure:
‘They’re not going to blame the vaccine. But he has an obligation to report that, doesn’t he? They are not reporting!’ – ‘Right!’ – ‘Because they want to shove it under the mat. The government doesn’t want to show that the vaccine is full of shit.’
PROJECT VERITAS WHISTLEBLOWERS
DOCTORS AND NURSES SPEAK OUT: ‘THEY ARE NOT REPORTING!’
Project Veritas is a journalistic organization that has been exposing crime and corruption in our world for years. They often receive video footage from hidden cameras, that reveal what is going on behind closed doors. They were contacted by several federal doctors and nurses, who can no longer be silent.
In an interview with James O’Keefe from Project Veritas, the nurse Jodi O’Malley testifies:
‘I’ve seen dozens of people come in with adverse reactions.’
She adds that none of these are being reported. When asked if she isn’t afraid for repercussions for speaking the truth, she answers:
‘I am not afraid, because my faith is in God. This is evil at the highest level.’
The video also shows nurse Jodi talking to a doctor, who is desperate to break the silence:
‘It is bullshit. I am about tired of it. So what we’re going to have to do, cause we’re on the inside… I’ve been thinking about it.’ – ‘And, what do we do?’ – ‘I don’t know, but there’s so much I want to blow up.’ – ‘So much. How do we do that?’ – ‘You know Project Veritas?’
There are thousands of doctors and nurses like this, whose hearts are burning to speak out, but who are afraid. I have personally been contacted by different groups of hundreds of medical professionals. If you are a medical professional and want to speak out, please contact Project Veritas veritastips@protonmail.com or Stop World Control: network@stopworldcontrol.com
You will be not be alone, but you will find a vast army of freedom fighters, worldwide, who will stand with you. Please come forward and share your story. Humanity needs you!
Watch the videos from Project Veritas with the medical whistleblowers here:
THOUSANDS OF STORIES
FACEBOOK POST REVEALS TSUNAMI OF ADVERSE EVENTS
A local ABC News Station posted a request on Facebook for people to share their stories of unvaccinated loved ones that died. They wanted to make a news story on this. What happened was totally unexpected. In five days time over 250,000 people posted comments, but not about unvaccinated beloved ones. All the comments talk about vaccinated loved ones that died shortly after being injected, or that are disabled for life. The 250,000 comments reveal a shocking deathwave among the population, and the heartwrenching suffering these injections are causing. The post was already shared 200,000 times, and counting…


Notice in the last comment how the lady says that everybody in the hospital is afraid to report this as a vaccine reaction, and another person says ‘the doctors can’t report it’. That is proof of what I explained earlier: Most medical professionals are terrified to report adverse events, which causes the true prevalence of vaccine injuries to remain hidden from the world.
The 250,000+ comments show that once people find a safe place to report their suffering caused by the injections, we see a tsunami… This is only one single Facebook post, that is getting no media attention whatsoever. What would we see if this was announced on the news, and everyone was allowed to report their stories?
https://www.facebook.com/80221381134/posts/10158207967261135/?d=n
VACCINE DEATHS SUMMARY
WHAT IS HAPPENING IS FAR WORSE THAN WE THINK
- VAERS published 16,000+ deaths and 450,000+ adverse events, as of August 28, 2021
- CDC fraud expert says that number of deaths is at least five times higher 150,000 reports have been rejected or scrubbed by the VAERS system.
- The actual number of anaphylaxis is 50 to 120 times higher than claimed by the CDC
- Vaccinated people who die within two weeks, are not listed as vaccine deaths
- Moderna received over 300,000 reports of adverse events in only three months-time
- The Lazarus Report shows that only 1% of adverse events is being reported by the public
- The majority of the population is not aware of the existence of systems where they can report vaccine adverse events
- Aggressive censorship and propaganda told the public that adverse events are rare, causing people to not understand how their health problems stem from past injections
- The shaming and blaming of medical professionals who say anything against the vaccines, cause many in the medical community to avoid reporting adverse events
- The fear of being held accountable after administering an injection that killed or disabled patients, further prevents medical personnel from reporting it
- Having accepted financial incentives to promote, and administer the covid vaccines, also stops medical personnel from reporting adverse events
- Profit driven vaccine manufacturers have every reason not to report the destruction their untested experimental products are causing 250,000+ Facebook users comment about vaccine deaths and serious injuries
- Nurses and doctors testify how their hospitals are hiding vaccine injuries.

WORLD EXPERTS WARN HUMANITY
LEADING SCIENTIFIC VOICES ISSUE GRAVE WARNINGS
This alarming data leads world experts, like the Nobel Prize Winner in Medicine, Dr. Luc Montagnier, to issue a grave warning that we are currently facing the greatest risk of worldwide genocide, in the history of humanity. Even the inventor of the mRNA technology, Dr. Robert Malone, warns against these injections that are using his technology.
The situation is so severe that former Pfizer vice president and chief scientist Dr. Mike Yeadon came forward to warn humanity for these extremely dangerous injections. One of his best known videos is titled ‘A Final Warning’.
Another world renown scientist, Geert Vanden Bossche, former Head of Vaccine Development Office in Germany, and Chief Scientific Officer at Univac, also risks his name and career, by bravely speaking out against administration of the covid shots. The vaccine developer warns that the injections can compromise the immunity of the vaccinated, making them vulnerable for every new variant.
WWII holocaust survivors wrote to the European Medicines Agency demanding the injections to be stopped, which they consider to be a new holocaust.
REFERENCES:
1: https://renzlaw.godaddysites.com/45k-whistleblower-suit
2: https://www.icandecide.org/wp-content/uploads/2021/03/Letter-to-Dr.-Walensky-re-anaphylaxis.pdf1: https://renzlaw.godaddysites.com/45k-whistleblower-suit
3: https://jamanetwork.com/journals/jama/fullarticle/2777417
4: https://centipedenation.com/first-column/150k-records-deleted-from-vaers-covid-database/
tempest-in-a-trashcan/?sh=47819f145396
6: https://rumble.com/vm1yrt-wow-vaccine-caused-deaths-reported-as-un-vaxxed-covid-deaths.html
7: https://dissident.one/2021/08/29/18311/
To Download The Full PDF Of The Above Report Please Visit: Https://Www.Stopworldcontrol.Com/Report
New York Governor Declares Self-Inflicted State of Emergency
By Stephen Lendman | September 29, 2021
Monday was D-day in New York —the deadline imposed by Gov. Kathy Hochul for state healthcare workers and staff to take at least one kill shot or face unemployment without benefits mandated by law.
Staff of home care, hospice, diagnostic treatment centers, school-based clinics and adult care facilities must be jabbed by October 7.
Last week, a statement by Hochul’s office said sacked or suspended state healthcare staff won’t be eligible for unemployment benefits without a physician-approved medical exemption.
Her draconian, health-destroying, mandate applies to out-of-state and contract medical staff employed in New York.
On Monday by executive order, she declared a state of emergency — of her own making — in response to the imminent sacking or suspension of tens of thousands of state healthcare professionals and staff.
They justifiably refused to sacrifice their health and well-being as a draconian condition for employment.
If tens of thousands lose jobs, a state healthcare crisis will follow — no matter how much coverup lipstick is applied to what’s going on.
Like Biden regime officials and other Dem governors, Hochul is going all-out to ensure maximum numbers of casualties throughout New York from health-destroying jabs, including many thousands of deaths.
It’s unclear how many state healthcare workers and staff are unjabbed.
Official numbers of inoculated state residents are artificially inflated to encourage refuseniks to join them.
On Tuesday, the New York Times dubiously claimed that as Monday’s deadline approached, “thousands of holdouts (got) last-minute shots (sic).”
Healthcare professionals are on the frontlines of treating and otherwise serving the needs of ill patients.
They’ve witnessed the effects of health-destroying jabs firsthand.
It’s why countless thousands nationwide abstained from getting them, knowing their toxic effects.
It’s highly unlikely that many thousands in New York agreed to sacrifice their health at the 11th hour to stay employed.
Healthcare whistleblowers are going public on widespread harm from toxic jabs.
Project Veritas is on the frontlines of reporting on what they said verbatim — discussed in an earlier article.
On Tuesday, Health Impact News headlined the following:
“Attorney (Thomas Renz) Files Lawsuit Against CDC Based on ‘Sworn Declaration’ from Whistleblower Claiming 45,000 Deaths… Within 3 Days of (flu/covid) Shots
As explained in a days earlier article, independent analysis by Jessica Rose, PhD (in computational biology), MSc (in immunology), and BSc (in applied mathematics) and researcher Matthew Crawford said the following:
“Analysis of the Vaccine Adverse Event Reporting System (VAERS) database can be used to estimate the number of excess deaths caused by (flu/covid jabs).”
“A simple analysis shows that it is likely that over 150,000 Americans have been killed by (jabs) as of August 28, 2021.”
Official CDC VAERS reported adverse events, including deaths, reflect a minuscule tip of an infinitely greater human health toll.
Many US hospitals have become hazardous to the health of flu/covid patients by mistreating them with toxic protocols, denying them what’s safe and effective based on orders from higher authorities.
A previous article discussed “fraud, negligence and greed” that whistleblower nurse Erin Maria Olzewski witnessed firsthand at New York City’s Elmhurst Hospital, saying:
“The very first day (at Elmhurst) I was shocked. It was something I’ve never seen before.”
“Patients were alone in the rooms on ventilators (with) no family allowed in” for support and advocacy.
“People were just dying from gross negligence, medical malpractice, (and) mismanagement.”
“(T)hat was really difficult to swallow. Everything made sense to me at that moment of why there were so many deaths in New York.”
“There was such mismanagement, and we knew it.”
“A lot of nurses and doctors, half of them looked away because the pay checks were good, and the other half were scared to say anything.”
“And if you did say anything, you ended up in my situation. I was fired for advocating for my patients.”
In its latest edition, WaPo reported that New York is “brac(ing)” for what follows after “(t)ens of thousands (of state) healthcare workers (who) refused” to be jabbed are fired or suspended, adding:
Dismissing them will “exacerbat(e) an already existing (healthcare) labor shortage” in the state and elsewhere in the US.
Earlier this year, a Washington Post-Kaiser Family Foundation survey found that nearly 30% of healthcare workers may quit because of what’s gone on since last year.
Nearly 60% of respondents said they’ve been physically and emotionally drained.
According to the American Hospital Association (AHA), hiring of least 200,000 nurses is required annually in the US to meet increased healthcare demands, adding:
Critical shortages of staff already exist in parts of the US, especially in what AHA called “vulnerable rural and urban communities.”
Under normal conditions, the AHA expects a “shortage of up to 122,000 physicians by 2032.”
If widespread sacking or suspension of healthcare workers occurs in numerous US communities for unwillingness to take toxic jabs, a crisis of monumental proportions could follow.
Is this what US dark forces planned all along?
Is depopulation by toxic jabs — and/or unavailable or inadequate treatment for lack of enough staff — what their diabolical healthcare-destroying plan is all about?
The world’s wealthiest nation that’s able to provide universal state-of-the-art healthcare is spending tens of billions of dollars for irreversible harm on countless unwanted millions instead.
A nation at war with its own people and others abroad poses an unparalleled threat to humanity.
That’s the ugly reality of what’s ongoing and likely to worsen ahead.
It’s why mass resistance against the diabolical scheme is crucial — by whatever it takes to turn things around before it’s too late to matter.
Despite 95% Vaccination Rate, Harvard Experiences “Substantial Outbreak” of COVID
By Paul Joseph Watson | Summit News | September 28, 2021
Despite having a vaccination rate higher than 95 per cent, Harvard Business School has been forced to move its first and second year students to remote learning after a “substantial” outbreak of COVID.
“In recent days, we’ve seen a steady rise in breakthrough infections among our student population, despite high vaccination rates and frequent testing,” Mark Cautela, head of communications for HBS, told Poets&Quants.
Despite the claim that the outbreak “is not occurring in classrooms or other academic settings on campus,” authorities have “decided to move all first-year MBA students, and some in the second year, to remote learning for the week of 9/27 to 10/03.”
According to Howard Foreman, a professor in the practice of management at Yale School of Management and a medical doctor, the situation represents a “substantial outbreak” that continues to worsen with “11 new graduate students testing positive in the last batch of tests.”
According to Harvard’s official coronavirus dashboard, 95% of students and 96% of employees are vaccinated against the virus.
“Is Harvard therefore implicitly admitting that vaccine effectiveness has waned to the point of total ineffectiveness?” asks Zero Hedge.
“So, despite all the promises of a ‘return to normal’ if only everyone were vaccinated (which in this case they are), it appears elite higher education in 2021 is no different from elite higher education in 2020… and certainly not any cheaper.”
Group activities and meetings have now all been moved online, with Harvard asking students to limit in-person interactions with others outside their household.
This again underscores how people will be mandated to get constant booster shots, with all the attendant health risks, because the longevity of protection the vaccine offers is minimal.
Meanwhile, natural immunity, which studies show offers 27 times more protection, is completely discredited by the media, with VICE recently denying its existence altogether.
Note also that Joe Biden said yesterday life in America won’t return to normal until 98% of the population is vaccinated.
Harvard almost reached that level and life is very much not back to normal.
Community Masking: Where did ‘The Science’ Come From?

By Noah Carl • The Daily Sceptic • September 28, 2021
Before 2020, evidence for the efficacy of community masking – that is, asking ordinary members of the public to wear cloth or surgical masks when going about their business – was shaky at best.
This evidence was reviewed in detail by Jeffrey Anderson, a former director of the Bureau of Justice Statistics. He notes that:
of the 14 RCTs that have tested the effectiveness of masks in preventing the transmission of respiratory viruses, three suggest, but do not provide any statistically significant evidence in intention-to-treat analysis, that masks might be useful. The other eleven suggest that masks are either useless—whether compared with no masks or because they appear not to add to good hand hygiene alone—or actually counterproductive.
In another piece that’s well worth reading, Professor Steve Templeton provides a list of quotations from what he calls “the BP era” (Before Things Got Political). Each quotation, taken from one or other expert, testifies to the lack of evidence that community masking works against respiratory pathogens.
For example, in a systematic review published early last year, Jingyi Xiao and colleagues “did not find evidence that surgical-type face masks are effective in reducing laboratory-confirmed influenza transmission, either when worn by infected persons… or by persons in the general community to reduce their susceptibility”.
This is presumably why, at the start of the COVID-19 pandemic, health authorities in both the U.K. and the U.S. advised against community masking.
For example, on 4th March 2020, Chris Whitty told Sky News that “wearing a mask if you don’t have an infection reduces the risk almost not at all”. And as late as 3rd April, Jonathan Van Tam said “there is no evidence that general wearing of face masks… affects the spread of the disease”.
Likewise, in a tweet sent on 27th February, the CDC said that it “does not currently recommend the use of facemasks”. And two days later, the U.S. Surgeon General urged people to “STOP BUYING MASKS” because they are “NOT effective” at preventing the general public from catching coronavirus.
In a video interview from May of 2019, Anthony Fauci actually laughed at the notion of wearing a face mask. The interviewer asks him, “The best way for me to prevent getting an infectious disease… is what? Wearing a mask?” To which Fauci replies, “No, no no… you avoid all the paranoid aspects.”
Yet by the summer of 2020, the health authorities in both countries had done an about-face, and were now recommending face masks to the public. These recommendations subsequently became mandates.
‘The Science,’ in other words, had changed. But what prompted this change? The charitable answer is that new evidence emerged suggesting that community masking does work against SARS-CoV-2. However, this new evidence looks just as shaky – if not shakier – than the pre-Covid evidence.
I suspect that something else happened. Back in the spring of 2020, all Western countries were on the same upward trajectory, with cases doubling every few days. Meanwhile, Japan, Korea, Hong Kong and Singapore had all manged to ‘flatten the curve’, despite eschewing draconian lockdowns.
Commentators were searching around for an explanation, and ‘masks’ seemed like a good one. After all, Western health authorities had advised against masks. Yet many East Asians had been wearing them for years.
If you were on social media at that time, you probably remember seeing a version of this chart, which went viral numerous times:
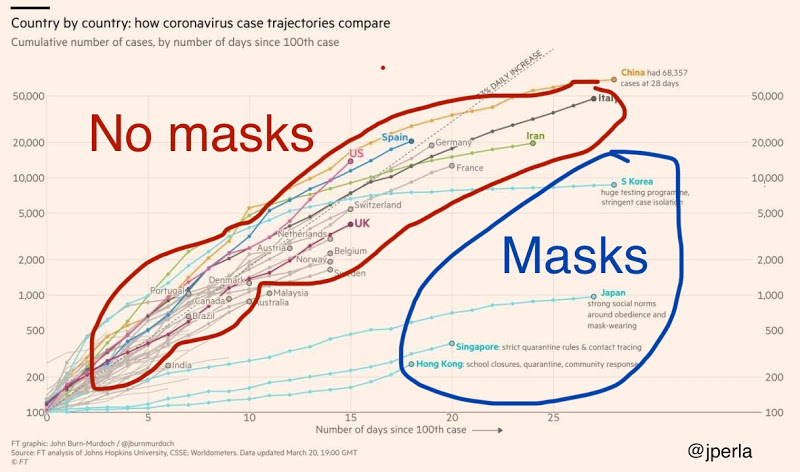
Putting ‘correlation doesn’t equal causation’ aside, it appears to suggest that masks are the crucial factor for bringing COVID under control. Of course, the subsequent imposition of mask mandates in Western countries didn’t forestall large winter outbreaks, which rather undermines the mask theory.
Nonetheless, it seemed plausible enough at the time. And articles began appearing in major news outlets that questioned the West’s reluctance to wear face masks. On social media, commentators asked why we shouldn’t follow the East Asian countries, given their far greater success in handling the pandemic.
I suspect this pressure had more to do with the health authorities’ about-face than any fundamental change in the quality of evidence. It was another case of ‘politician’s logic’. ‘Something must be done; mask-wearing is something; therefore we must do it.’
In a matter of weeks, ‘The science’ went from ‘don’t do X’ to ‘do X’. And yet it took another whole year for the first RCT of community masking to be published. The theory I’ve outlined is speculative, of course. But I don’t see what else can account for such a sudden shift in public health advice.
Blame Doctors And Hospitals, Not The Virus, For COVID Deaths
By Joel S. Hirschhorn | Principia Scientific | September 28, 2021
Very, very few physicians are courageous enough to stand up against the vaccine-but-not-early treatment with generics tyranny pushing mass COVID vaccination.
Few will prescribe ivermectin. Few acknowledge the many vaccine risks that for most people outweigh the benefits.
Few accept the science that natural immunity is better than vaccine immunity and people with it should not get the jab.
When Americans see the data on COVID deaths of over 600,000 who or what should they blame? The truth is this: Better than blaming the virus they should blame hospitals and the vast majority of physicians. Why?
Because the medical establishment has never had the courage to stand up to the medical tyranny engineered by Fauci and implemented by the CDC and FDA.
People still are dying from COVID because their physicians refuse to genuinely follow the science and prescribe cheap, safe and proven generics like ivermectin.
Of course, there have always been a minority of doctors who have since March 2020 been curing their patients of COVID by using a variety of protocols that hospitals and their doctors refuse to use.
Why are so many nurses and physicians refusing to be vaccinated? Because they have seen on a daily basis large numbers of patients suffering and dying not from the virus but from the COVID vaccines.
Now one of the most respected physicians and medical researchers, Dr. Robert Malone, has spearheaded a movement to combat medical tyranny by organizing physicians from all over the world and creating just days ago a Physicians Declaration. Here are some key highlights from this historic action.
— There is an unprecedented assault on our ability to care for our patients.
— Public policy [think Fauci] has chosen to ignore fundamental concepts of science, health and wellness, instead embracing a “one size fits all” treatment strategy [think COVID vaccines] that results in too much illness and death when the individualized, personalized approach to health care is safe and equally or more effective.
–Thousands of physicians are being denied the right to provide treatment to their patients [think ivermectin], as a result of barriers put up by pharmacies, hospitals, and public health agencies, rendering the vast majority of healthcare providers helpless to protect their patients in the face of disease. Physicians are now advising their patients to simply go home (allowing the virus to incubate) and return when their disease worsens, resulting in hundreds of thousands of unnecessary patient deaths, due to failure-to-treat [other than using vaccines].
— Physicians must defend their right to prescribe treatment, observing the tenet FIRST, DO NO HARM. Physicians shall not be restricted from prescribing safe and effective treatments [other than vaccines]. These restrictions continue to cause unnecessary sickness and death. The rights of patients, after being fully informed about the risks and benefits of each option [especially vaccines], must be restored to receive those treatments [such as ivermectin].
— We invite patients, who believe in the importance of the physician-patient relationship and the ability to be active participants in their care, to demand access to science-based medical care.
That last point is where you the reader must join this revolt and demand from your physicians and hospitals your right to get access to generic medicines like ivermectin. Print the Declaration and give it to your doctor.
If this Declaration simply remains words but not profound changes in the practice of medicine in this pandemic, then all hope for saving lives will be lost.
We are rapidly approaching the point where more people will die from COVID vaccines than the virus.
Fauci and his allies will not easily admit their many evil wrong actions. If you want to examine extensive medical science details on the emerging Vaccine Dystopia, then read this truth-telling article.
Nothing They’ve Tried Has Worked: The Story In Four Charts
By Tom Woods | Principia Scientific | September 28, 2021
I send a lot of charts, as you know. But these are especially interesting. What story are the charts below — which cover four different regions of the United States — telling us about the Covid virus?
The dark line represents 2020. The lighter line represents 2021.
I get that the curves are not absolutely identical. But they’re not altogether different, either. The same trajectories are evident in both years, in each chart.


What do these charts mean?
Do they mean that the virus is regional and seasonal, and that despite our feeble interventions it does what it will?
I won’t attempt to draw any sweeping conclusions for you. But look at the charts and make up your own mind.
Meanwhile, much of the public continues to believe the standard story.
Someone inside the Tom Woods Show Elite, my private group for normal people, put it this way: “Most people believe that masks work, that kids are dying in droves due to Covid, and that the vaccines stop the spread. If you go up to people in public at random and ask them basic questions about Covid, they will not know these basic things.”
It reminds me of when 70 percent of Americans thought Saddam Hussein had been responsible for 9/11.
Most Americans don’t trust Biden and US government on Covid-19 information – poll
RT | September 28, 2021
The Axios/Ipsos poll, released Tuesday, shows 53% of Americans have not very much trust or no trust at all in the president to provide accurate information on the coronavirus.
Biden has retained the trust of a minority, with 45% saying they either trust the Democrat a great deal or a fair amount.
The survey was taken among more than 1,100 adults and has a margin of error of 3.2% points.
The president has continued pushing vaccines onto the American public, though some recent efforts have faced scrutiny, including his support of a third booster shot ahead of any Food & Drug Administration (FDA) decision and a vaccine mandate for employers with staff totaling over 100.
The public’s trust in Biden has slipped a fair amount since January, according to the survey data, as 58% of respondents questioned then said they supported the president on the pandemic, not long after his inauguration.
As is typical for Biden, his support is almost entirely among Democrats and Independents. Broken down by party lines, only 11% of Republicans trust Biden, while 42% of Independents and 81% of Democrats trust him.
This lack of trust extends beyond Biden and to the entire federal government, with only 49% saying they trust the government to provide accurate information on Covid-19. That number has continually been slipping and sat at 54% in data published two weeks ago.
The polling found a rise in trust among health officials. Over 60% said they trust the Centers for Disease Control and Prevention (CDC) and ‘national public health officials’ to provide accurate coronavirus information to the public. Those numbers, however, have also slipped from previous polling.
Survey data also found a growing majority seeing the coronavirus as a major health risk. Less than 15% said gatherings with friends and family or dining in a restaurant pose a large health risk, which is a decrease from two weeks ago. Only 27% think that air travel poses a risk because of Covid-19, which is also a drop from 35% since the last poll.
Gagged Australian Nurses Form Whistleblower Group to Expose What’s Really Happening with COVID-19 Vaccine Injuries

By Brian Shilhavy | Health Impact News | September 27, 2021
Reignite Democracy Australia, which was started by journalist Monica Smit, an outspoken critic on authoritarian lockdowns in Australia who was just released from jail on bond last week, has started a group called “Nurses Speak Out” where gagged nurses are speaking out about the truth of what is currently going on inside of hospitals with people suffering from vaccine injuries.
They are posting these stories on their Telegram channel as well.
This is an Anonymous whistleblowing channel for Nurses & Healthcare workers in Australia. We will share verified experiences from frontline workers who see firsthand the damage caused by COVID-19 vaccinations.
These submissions have been vetted by a collective of health professionals. Some details may be omitted, your identity will be protected. AHPRA has gagged, coerced and threatened anyone who comes forward – let’s save some lives.
This channel is dedicated to all frontline workers around the world. This is Australia. This is for you.
Here are some of their stories that have just been published.
Hi,
I’m a community RN on the —— , Qld.
I am seeing and caring for adversely affected clients who have had the vaccines and are quite literally dying. Our palliative care is increasing at an exponential rate, people are getting diagnosed with terminal conditions and dying quickly. We (community nurses) are seeing 2-3 palliative clients per day each, this is a massive increase from 1-2 each per week. Other palliative clients who haven’t been vaxxed, then their families talk them into the vax, die more quickly than expected.
Have noted that those who are vaxxed that their clinically ‘weak’ areas are being exacerbated. Appears to be at 3, 5 then 12 week patterned intervals. Not one of them associate with the C19vax.
Had one man in his 70’s in very stable remission with leukemia for years. Within 3 weeks of having ‘the vaccine’ his white cell count dropped so he had neutropenia. He suddenly developed in 24 hours bilateral cellulitis to both legs up to thighs. 9 weeks later, he is dead.
Those with rheumatoid arthritis who have been jabbed experiencing related consistency of flare ups. Getting all sorts of skin infections for no obvious reasoning. They’re having constant medication reviews and increasing analgesia.
3 x clients with healing venous ulcers, all 3 had the jab, 3 weeks later all developed septicemia all with hard to treat bacteria.
Those with cardiac conditions who were clinically stable on medication for years, suddenly no longer stable. Arrhythmias, unstable blood pressure, syncope, falls, increased hospitalisations.
Cancers: seeing massive increase in skin cancers. They’re growing very quickly and aggressively.
Cognition: clients who have been vaxxed and predisposed to some memory issues, increasing episodic bouts of confusion with accompanying amnesia and increasing STML.
Of my nursing colleagues who have been vaxxed, noticing increasing sick leave being taken.
Sincerely,
Veronica
Community RNTriage Admin, Emergency Department.
Hi,
I work in Emergency Department as an admin clerk at triage and I can tell you the reason I will not be having this vaccine is that every third or fourth patient is coming in with an adverse reaction.
Some complaining that their heart is beating so hard and is squeezing out of their chest, I’ve seen vision changes, numbness , skin problems , cellulitis young men and women diagnosed with pericarditis myocarditis, clots , tumors even my colleagues have had Bell’s palsy there is so much more.
What amazes me with all this is that no one can see it! Young patients being told it’s just anxiety 😥, nurses at triage rolling their eyes saying things like “can’t they just stay home and take a panadol” !
Then to top it all off our double jabbed nurses at triage test positive to Covid and are admitted and are sick but they are saying “at least I’m vaccinated I could have been a lot worse”, there are 5 unvaccinated clerks at the front desk at triage and we have worked through this pandemic but now we are a danger to the other other staff
UNBELIEVABLE! So we now have received the letter saying no jab no job we’ve got till the 30th 😟 Also would like to add the influx of nursing home patients that are coming in is ridiculous, falls vertigo generally declining quickly after jab, I’m not a medical person but I can see what’s going on it’s very sad 😞
Hi,
I am a Physiotherapist with 40 years of Private Practice experience – Some of the clients I see I have been seeing them and their families for different things for decades.
On Thursday I had four of the jabbed ones in. They all had the same set of symptoms.
Their original injury that I treated them for occasionally — maybe once every few years over the last few decades has returned with a vengeance and is excruciatingly painful. Additionally all four of them had pain all over in ankles, wrists, knees, hips, backs all over… and they all had a severe headache.
They are not relating this to the jab.
I have been seeing this new presentation of pain over the last couple of weeks.
However, on Thursday with them all coming in on the same day with the same symptoms I now KNOW it is a pattern of pain for the jabbed.
This evening I went out with a Nurse friend who is jabbed and she has the same thing happening to her. Neck, arm and wrist pain, swollen feet and foot pain, and she kept saying she felt old, and her body was breaking down… She is 15 years younger than me and could barely walk home from dinner.
These people are my friends and long term clients — it is difficult to watch them suffer.
(Response to #0003)
25/09/2021
Private Practice PhysiotherapistsHi,
We’re also a group of private practice physios of similar vintage and have seen this pattern of presentation in the jabbed ones.
Headaches feature prominently. In addition, we’ve noticed discoloured feet (purple-red), swollen joints (one young patient with Crohn’s disease resorted to a walking stick), swollen and tight calves, recurrence of old injuries as well as new joint aches snd pains.
When dry needling, our acupuncture needles are now “swimming” in tissue because there’s just so much generalised inflammation of the muscles. Patients are reluctant to report these symptoms because they’re doctors have told them “the shots are safe”!
Student Nurse, Rural.
Hi,
I’m a student nurse working in a rural hospital.
I’ve had several people walk into the hospital with flaring pains all over their body, on my last shift there were 9 patients who whispered to me that they were sure that their condition was caused by the COVID vaccine they got but they were afraid to tell the registered nurse for fear of being ostracised. They got the jab because everyone else was getting it rather then making the decision for medical treatment.
I have seen many nurses and doctors laughing about these people in the break room. Calling these patients Anti-vaxers and wishing they could kick them out for the real patients in need. I told my student supervisor and the nurses stopped talking about it when I was on break but I have the feeling they still had those conversations behind my back.
RN. Aged Care, NSW.
Hi,
I am (was) a Registered Nurse in Aged Care in NSW.
I was terminated from my job there over a week ago now for declining the jab.The facility had a covid clinic where the masses received Pfizer.
On the day as they had left over stock the staff were then offered jabs which many of them didn’t feel comfortable but got because the management where there on the day saying things like “come on just get it, don’t be ridiculous, if you can’t trust the science what can you trust” one staff member declined twice, the third time she was pushed into getting it (all on the same day) I seen this as pure bullying and coercion, she submitted and got the jab.
The next day a resident died (nobody batted an eyelid) within three days post jab another two residents died.
Over the course of the next three weeks we lost in total 6 residents all who had significantly declined overall and not to mention a lot of other residents declining overall and becoming unwell.
The second jab clinic, within the first week, we had five people end up in hospital who then died, shortness of breath, heart issues, others the residence getting rashes not being able to lift their arm up, acting as delirious state, within the next week after that another 5 residents died.
In total within the 3 months roll out of the jab, we had 14 deaths of vaccinated residents.
In a nursing home with 90 residents most of the staff are commenting on how unheard of this amount of death was but when questioned in relation to the jab many were in denial stating it couldn’t be from that.
Over the course of three months watching the staff who had been injected so many staff off on sick leave a few staff members ended up in the hospital one for heart reasons the other one had blistering rashes all over her body she ended up being admitted twice, mass reports of headaches lasting days to weeks, dizziness, just generally reporting to not feeling right since having it. The fear in the eyes of the staff is something I will never forget. Other staff feeling completely deflated as they could lose there jobs and had to submit to the jab, In which some after were crying to me at how much they just felt defeated. I have many things to say in relation to this, I could write a novel.
I know just within the week and a half of not being there they are struggling to fill shifts, which sadly impacts on everyone, residents and staff the only people it doesn’t effect is the management.
I love being a nurse but I just can’t do it in this current situation it no longer aligns with what I believe health to be. It is a sad and devastating time.
RN, Emergency Department. NSW.
I am a Registered Nurse from NSW,
I have a young colleague, also a nurse who did not want the vaccine.
Due to the mandate she got the shots. After her first shot she had searing pain down her arm. Unrelenting pain. After her second shot, she was bedridden for an entire week. She could not sit up straight. She was so sick, unable to move and constant chest pain.
After the week of being bedridden she returned to work with chest pain. She finally has been admitted to hospital with myocarditis.
She is early 20’s. Before the vaccines she was healthy with nil health issues. Now she has cardiac issues and may need medication for the rest of her life.Each day we are seeing the emergency department full of patients with stroke, Pulmonary embolisms, cardiac arrhythmias, Myocarditis, endocarditis. The increase of strokes is exponentially growing. Patient after patient with PE’s, cardiac issues. Most in previously healthy patients. Doctors are denying connections to the vaccines.
RN, 40years. Palliative Care.
AHPRA Verified ✅Hi,
I am an RN of 40 years, presently my work is in Palliative care where I have worked for 8.5 years permanently in ——-.
I am seeing patients developing increased effects from Palliative radiation, which is commonly prescribed for reducing various conditions arising from cancers. Our patients are deteriorating more quickly with increasing weaknesses, breathlessness (?PEs) facial droops (Palsy or stroke), neuropathys in hands or feet.
The cancers some only recently diagnosed, seem to have metastisised very rapidly. This needs to be looked into carefully. We as nurses are commenting those going for radiation are very much at risk; a death sentence which hastens their deterioration towards death. As Palliative patients, their downturns are passed as expected, while we see them as alarming.
I have many colleagues took the jab out of sheer fear of losing their job and incomes. Also one other colleague after she recieved her 1st pfizer jab was off work with encephalitis and remains very unwell having diffuculty with headaches and dizzy spells.
I am ordered to leave from September 30th, a job I am passionate about and feel have been valued. While now 61 years old I hoped to continue my work for 5 more years and feeling very sad to be forced to leave.
I think the radiation perhaps is accentuating the vaccinations, namely the graphene components.
Sincerely.
EN. Brisbane, QLD.
Hi, Enrolled Nurse from Brisbane…
I work in Private health, so don’t often get to see initial reason for presentation to emergency, as they are usually transferred from public to us later.
I nursed a man in his 60’s recently that got vaxed…he had a knee replacement 3 months prior (fully healed).
Came in to hospital again due to severe bleeding and needing surgery… post-surgery his knee haemorrhaged quite badly… then got a vacc dressing…ended up nursing him again in a Rehab ward a week later… told me it happened after vaccination but surgeon didn’t report it or link it with vaccine.
Another older lady presented as very disordered after vaccination.. couldn’t walk properly, ended up 2 assist with a FASF… on Lyrica 150 BD for nerve pain… frequently complained of headaches and chronic ear ache.. ended up going home after a long rehab stint..
I won’t be getting the jab so will probably be unemployed in the next month or so… One of our Doctors is very over the draconian crap..his words.. he is fully vaxed and furious we are still wearing masks.
Remedial Massage Therapist, QLD.
Part 1 of 2.
Hello,
I am a Remedial Massage Therapist operating out of Wellness Clinic in an exclusive seaside town in —— Qld, Australia.
Over the past 12months the majority of my regular clients have received both shots of either AZ or Pzizer and I have observed and felt the changes in their bodies. I will also add that not only have the changes happened in their bodies but also their personalities.
Over the past 2 months I have also listened to them telling me of their sudden medical issues that are happening to them. This has been so disturbing for me that I am closing my business and am taking the time to heal myself both physically and mentally.
Their bodies over the past 12months have changed. They have no movement, elasticity anymore. It is like they are turning to lead. I have 3 clients, all retirees and golfers who now have tears in their supraspinatus. This is on their left hand side from swinging the golf club.
(1) One client, male retiree who has been rushed to hospital 4 times last week unable to urine or make bowel release. The Doctors have told him that he has kidney stones. Hmmm… He also had a large burning and itchy rash all over his back. He said it was that painful he had his wife put metho on his back to ease the pain as nothing else was working.
(2) One retired lady advised me that she had a cyst forming behind her knee and when she would have a shower it would burst and the blood that came out was uncontrollable. This happened twice within a couple of weeks. She went to the Doctors he said it was a bakers cyst. She returned saw another Doctor who said it was a BCC. The third time she came to me her leg is now swollen all the way and she is in a lot of pain.
(3) Another lady, a Doctor herself advised that she had an electrical like pain run across her back. She couldn’t quite explain it. Never had anything like it before and now has a sore neck and headaches. I felt her neck and there was a pulsing feeling at the rear. She couldn’t feel it. I went back to that site 2 more times and I could feel it. She couldn’t.
Cont…
Part 2 of 2.
… (4) A retired lady told me she had burning and itching skin on her chest and that she was in a lot of pain. I asked her if I could see it. It covers a large area between her breasts and underneath her bra line. She said it is getting worse each day. It was very red and raw.
(5) Another regular client has markings all through her lower back on the left side. She was unaware. I took a pic and showed her. She said that she had been putting an electric heat pack in that location at night to warm her up. She went to the Doctors and the skin clinic and they didn’t know what it was. She came back to see me 5 weeks later and the markings are still there.
I have attached the pics (redacted) for you to view. and the list goes on..I have regularly massaged these clients over the past 2-3 years and I find it extremely troubling. These haven’t happened straight after their shots but over the 3, 4 , 5 months following so they are not connecting it to their shots. I am unable to say anything to them as their once friendly personalities have also changed. They are more aggressive and talk at you, not to you and will defend these shots.
The man I mentioned above even said to me that he will be getting the booster shot if and when it comes out next year. When you hear from your clients all day, every client, not 1 or 2 then this is a concern for all people who have had this shot. They are not the same people, on any level anymore. Like I mentioned above this has traumatised me to the point that I am now unable to continue my passion for the foreseeable future and I am now focusing on healing me, physically, mentally and spiritually. Take care everyone and be safe.
Radiographer, Private Practice, Rural.
Hi,
I work as a Sonographer for a private rural practice. We mostly see outpatients but the occasional patient via ED.
I work three days a week and I would say I see at least one patient per shift with an injury directly related to the vaccine. Some examples:
89 yo F haemathrosis to left shoulder at injection site one week post vaccine.
No blood thinners. Healthy72 yo F (mother in law)
Very healthy, fit. No medical problems.
Profoundly deaf in both ears over a period of days. Had vax 10 months ago. No cause found.56 yr old M
Testicular ultrasound showed epididymis one week post vax.Lots of unexplained abdominal pain, headaches, shoulder pain and inability to use arm at injection site.
Hope that’s helpful.
Regards. ——RN, 39years.
Hi,
I am an RN with almost 40years experience.
We looked after one of the first AZ blood clot patients
Male, 45yo. 8 days post his 1st AZ shot he complained of dreadful stomach pains. Went to ED.
Scans showed a massive blood clot in his bowel.
It took 3-4 days before they could operate, as his Coags were all over the place.The clot was finally removed along with almost 2 metres of necrotic bowel.
When out of ICU, he came to our ward. A beautiful man, who was black and blue all over with bruising. He was on an anti-coagulant drip, with a drug I’d never heard of (still can’t remember the name).
He was transferred to our Haematology ward, and unsure what happened to him.
Admitted a pt yesterday, who had been in ED for 10 hrs. Quite casually he told me that he couldn’t believe the numbers of young guys coming in with side effects from the vaccine. I asked him how he knew this, and he said he could hear the conversations.
I asked re the side effects and he said chest pains, breathing problems!Nursed a female pt, fully vaxxed, with pancreatic issues, but she’s had increasing weakness in her legs?? All Neuro tests are NAD. She can no longer weight bear, and has been told it’s because she’d been in ICU and was deconditioned???
I’m not so sure….Will no doubt lose my job end of October, as no jab for me!😥😥
RN. Emergency Department, Melbourne, VIC.
Hi,
I am an Emergency Department RN based in Melbourne’s east and have similar experiences to the other whistleblowers.
We have young, healthy men in their 20’s-30’s coming in every single day due to chest pain after the vaccine. Pathology is usually fairly normal (Trops and d-Dimer) and doctors write it off as either psychological or unrelated to the vaccine. Even when they admit it’s probably vaccine related, it is never reported. Ever.
I have looked after a young, healthy female who felt coerced in to getting it due to her job in healthcare, who suffered from severe headaches ever since, and nothing seemed to help. She was sent home basically left to hope that it resolves eventually. Doctors did not report it.
Another patient came in with multiple blood blisters, and petechiae on his arms. He was diagnosed with ITP which is a known adverse effect of the Pfizer vaccine. His platelets were literally completely wiped out. Doctors did not think it was linked to the vaccine he had 3 days earlier, and so it was not reported.
If science was being respected, people would be followed up properly, and the cause of the chest pain for example would be getting investigated, but it isnt.
None of these things were discovered during the purportedly thorough and complete clinical trials. None of the patients were made aware of the possibility of these effects, which means they could not give proper informed consent.
Now they want to force us to take it or lose our job? Who knows what other problems will be uncovered in the future?
No risk/reward analysis is being done in regards to age demographics. Many experts are saying young adults have greater risk from the vaccine than the virus. No formal studies have been done that I’m aware of, but I suspect that is true. And it is definitely true for children. The government now wants to vax all children despite their risk of harm from covid being almost zero, and the risk from the vax being comparatively high.
Medical treatment is supposed to have a favourable risk/benefit analysis, and it absolutely does not in this case.
The medical field is about to lose staff who are capable of thinking for themselves and standing up for themselves, and healthcare for patients will be much worse because of it.
RN. Brisbane Hospital, QLD.
AHPRA Verified ✅Hi there,
I am a nurse at one of the major hospitals in Brisbane. Had my first Pfizer shot back in April – suffering pericarditis, numbness and tingling in both arms, ceased menstruation, elevated insulin levels.
Will not get second.
No Covid at our hospital. Have seen many adverse reactions from Covid vaccine. Mainly block clots, strokes, heart problems.
AIN. Aged Care, NSW.
AHPRA Verified ✅I work as an AIN (Assistant in Nursing) in aged care in rural NSW.
One of my colleagues in her mid 30s went home sick the day after her second Pfizer shot. She went white and nauseaus and faint. This was in March and she has not been back to work since (its September now). After ages of going to Doctors etc she was diagnosed with myocarditis, she says she can hardly do anything. She was fine and healthy before, slim, physically active and on a good diet. Whenever the other staff talk about it, the narrative goes: oh she must have had something else before that, surely it’s not from the vaccine.
Two residents died within 2-3 weeks after first Astra-Zeneca shots, however were overall in bad condition before.
Residents are not allowed to leave the facility and nobody is allowed to see them except on compassionate grounds (basically if someone becomes really unwell). This causes some of the people to be really mentally unwell. There has not been one Covid Case in our town for the whole course of the pandemic since 2020.
We are told we have a “choice” to either get the flu and covid shot or we can’t work here. Another colleague had 40 years experience in emergency nursing and refused the flu shot, she was subjected to sitting at the door doing covid checks for about six months (even when there was no flu season) until she gave up and resigned. She had never had a flu shot for her entire career.
RN. Clinical Call Handler, COVID Vaccine Adverse Events, VIC.
AHPRA Verified ✅Hi,
I am a registered nurse in Melbourne with almost 33 years experience.
I currently have a role as a clinical call handler for people that are experiencing side effects from covid vaccines.
The adverse events that have been reported to me are extremely concerning in both the types of reactions and the frequency of them.
Apart from the usual expected side effects of over, pain etc for 1 to 2 days, some of the reactions that have been reported to me multiple times include
*Delayed anaphylactic reactions involving respiratory distress, facial and tongue swelling, usually a rash, but not always , with onset occurring usually around 2 days after vaccine, but has been up to 4 days post vaccine.
* Chest heaviness, stabbing chest pains, palpitations and shortness of breath is reported to me several times a day every day usually in young people (male and female) post Pfizer 1st and 2nd dose.
* Heart palpitations are very commonly reported across all age groups( usually Pfizer)
* ongoing shortness of breath for 6 plus weeks post vaccination with no explanation
* unusual rashes that appear days to weeks after vaccination
* unexplained bruising that appear days to weeks after vaccination with both Pfizer and AZ ( commonly reported extensive bruising on legs)
* swollen, painful varicose veins
* persistent headaches for weeks after vaccination, sometimes severe but usually just annoyingly persistent
* heavy vaginal bleeding in post menopausal women ( mid to late 50’s) and menstrual disruption/ irregularities in younger women
* Blood noses post Pfizer is extremely common
* Burning pain in limbs, in several cases the pain is so severe that the person is unable to walk.
* numbness and tingling in arms and legs is very commonly reported up to 6 weeks post vaccination with both Pfizer and AZ
* leg / foot pain and swelling( symptoms strongly suggestive of DVT however I don’t get to follow up)
* severe vertigo and tinnitus ( Pfizer)
* numbness down one side of face (this is surprisingly common)
* uncontrollable muscle twitching/ spasms
* extreme lethargy that persists for months after vaccine.
* Exacerbation of old injuries such as previously broken or sprained joints flare up or old scars become red and inflamed again.
* older Australians that have had Astrazeneca vaccine and have been ok but then had flu vaccine and have been extremely unwell since. I do believe there is a correlation between the 2 given within weeks of each other that is causing significant health decline in older people.
* people that have had stable auto immune disease but then once vaccinated their symptoms are markedly exacerbated or others with no previous history of immune disorders, I suspect develop an immune disorder post vaccine
I am certain that these vaccines are causing immune, neurological and blood clotting disorders resulting in significant harm to an unacceptably large amount of people.
There is more specific cases that I am aware of but for anominity I will not disclose them here. I am aware of ICU admissions post Pfizer vaccination in 3 different people as well as deaths of elderly nursing home residents within 24 hours of vaccination.
I am both concerned and frustrated that the medical profession is either unaware that these side effects are happening, or in many cases, not prepared to admit that they are in fact a result of the covid vaccines, (often medically gaslighting and putting down to anxiety), leaving these poor affected people desperately seeking help and answers, that in most cases, they probably won’t get either. I have tried to raise this issue on more than one occasion, but it falls on deaf ears.
RN/Critical Care Nurse. Rural, NSW.
Hi,
Love your idea by the way! It’s too hard for us to speak out and keep our jobs 😔
I watched many of my fellow colleagues suffer side effects. I was one of them too! When you talk about it so many stories come out and quite a few of us have ongoing issues to this day.
Within my workplace in a rural Emergency department I find myself as a team leader at times. I have been overwhelmed with patients post vaccination suffering side effect. Some short term such as chest pain amongst 20 -40yr olds to abdominal pain. Then the more serious long term stokes, heart attacks, guillian barre and pulmonary embolism.
For those nurses around me that have not had their vaccination yet, they are terrified!! For us that have had a reaction…..never again!Very little are reported and knowing how a proper clinical trial is conducted for my many years at university…this roll out is terribly wrong!
I understand COVID can make you quite sick (even if I have never seen it in my nursing career) but I believe this vaccination is no better! We need to go back to the drawing board and admit defeat instead of pushing forward.
The politics running this with no medical knowledge should be ashamed!
RN. Palliative Care Ward, Melbourne. VIC. AHPRA Verified ✅
.I’m a RN working on a Palliative Care ward in a major Melbourne hospital.
We never had Covid patient as they stay on the acute wards, obviously we need to protect our non-Covid patients.However we have had a number of patients coming to our ward and subsequently dying with sudden onset of unusual symptoms. Of course no connection has been made to the jab what so ever.
One male 70-something had his second AZ jab and a few days later suddenly collapsed with seizures. He was brought into hospital, ICU, had a number of CT’s, MRI’s and other investigations done, was intubated for a number of weeks. Everytime he was extubated, he was having seizures despite being on high doses of anticonvulsant (anti-seizer medication). The medical team decided he might have Autoimmune encephalitis (=autoimmune brain inflammation) eventhough the EEG and blouds did not confirm this conclusively.
(1). A man in that age group suddenly having an autoimmune disease? Eventually the decision was made to palliate him, which is when he was transferred to our ward. He somehow stabilised on our ward but was bedbound and definetly not like himself. Now here’s the twist. All along in his medical history the diagnoses was documented as “autoimmune encephalitis vs. vaccine injurie post AZ”. At one stage during the weekly meeting I actualy asked if he was going to be a Coroners case, since it’s unclear what his cause of death would be.
I was looked at realy strange, my concern was dismissed, I was told no it’s clear that he suffers from Autoimmune Encephalitis. After that the above comment was removed and his diagnoses remained Autoimmune encephalitis. To me this was a trigger to start looking at each patients history deeper.
(2). Female 65 years old and healthy was transferred to us after she’d suddenly collapsed at home for unknown reasons. ICU, intubated, again seizures from unkown reasons. They had done all the tests available under the sun(whole body MRI, CT, EEG, Autoimmune tests, etc). Medical team unable to find a cause of her severe deterioration. Decision was made to palliate. Transferred to us and then died after a couple of weeks. At least this one was a Coroners, as the cause of death was unclear.
A number of other patients were transferred to us, mostly with some sort of seizure that led to a collapse, or Stroke that led to more strokes and collapses. Sometimes one has to dig a bit to find info of recent vaccination with Covid vaccine!
I am genuenly concerned for every single person that had or will have the jab! Please don’t take it!
Physiotherapist, Private Practice.
Hi.
Thanks for giving us somewhere safe to speak out. I am a physio in private practice and previously contracted to aged care.
I have seen several deaths in aged care facilities in 12-24hours following the vaccination in people who were previously stable. Each time the entire file has been completely removed from the system and any notes by staff related to vaccine were deleted prior to the file being returned.
I actually retained proof of this from the first time I saw it happen as I could not believe what I had seen happen given how strict they are on no modification of record keeping being made in ANY other circumstance. This was not normal protocol when a death occurred in the facilities.
In private practice I have seen and heard of many side effects – similar to all those listed in the other accounts (persistent sharp headaches, increased previous injury flares, auto-immune disorder flares)
Probably the worst 2 were a patient with Parkinsons who I have been seeing for several years and had been symptomatically stable the entire time despite other health challenges. Post second vaccination they had a debilitating increase in freezing episodes and pain through their lower limbs. Their specialist denied this would have any connection to the vaccination so they did not question it any further.
Another client attended an appointment reporting they were completely bedridden for 3 weeks with extreme dizziness, lack of appetite and fatigue post initial vaccine (AZ). They were still breathless and very fatigued on the day they saw me. They are normally very well and active with no history of prior health issues. Again when they contacted the GP regarding the issues following the vaccine they were informed that what they had experienced the equivalent of “mild” symptoms of COVID and that was all to be expected with the vaccine. When I queried if they were going to return for their second dose, they reported they were so afraid as the GP had told them catching COVID would be much worse than what they were currently going through so they definitely needed to ensure they returned for their second dose. 😥😥
RN, Cardiology Ward, Major Hospital.
27/09/2021 AHPRA Verified ✅Hi,
I work on a busy cardiology ward.
Overall in the medical notes Doctors aren’t connecting the dots and not even considering the jab as a reason for the illness. Whether that is intentional or not I don’t know.
I have seen young adults come onto the ward for cardiac monitoring after collapsing after the jab.
(1). A lady with an autoimmune disease came in with a pericardial effusion after her jab.
(2). One lady had chest pain for weeks after the second astrazeneca dose, she had myocarditis. She was quite sick when she was on the ward, she had fevers, and all of her face was swollen, her eyelids were that swollen she could barely open them and inside her eyes were all glassy.
(3). Another was a young guy, healthy as, post jab had severe cellulitis to one side of his face, his ear was Triple the size.
(4). Another guy in his 20s had his first pfizer and the day after was febrile, and after a TOE was diagnosed with infective endocarditis. He also developed acute kidney injury to the point of needing dialysis. All kidney scans came back normal but still his kidneys were failing. In his notes when he was in ED it was mentioned that this started post jab but then on the ward after being reviewed by multiple specialists (infectious disease, renal, cardiac) not once was the jab mentioned.
What I am finding disturbing in my area is that it’s not even being considered as a potential cause. Even though problems start after the jab.
RN, Community GP Practice, Former Vaccinator. AHPRA Verified ✅
Part 1 of 2..
Hi,
I’m an RN who was working in a GP clinic and guilty of being a covid vaccinator.
I had raised concerns on a number of occassions and could no longer give it when I started to see what was happening. During this time I have seen and heard things which lead me to believe the vaccines are not safe.
I have heard many people saying they were spaced out and dizzy for days.I can’t count how many times I heard “spaced out”. Older people coming back and saying they were off balance and having falls when this hasn’t happened to them before.
Also heard people say loss of bladder control, arthritis flare ups, eczemea and skin rashes, strange blister, out of control diabetes, unhealing wounds and enhanced pain of old injuries. A man reported that he had visual problems and thought he almost went blind for a month but went to the optometrist instead of a dr and he said he had reported it to the report link provided which he said they had “pretty much dismissed it”.
I have sent a man off in the ambulance with anaphylaxis reaction, uncontrollable shaking and tingling around his mouth, unable to walk. I have had 40y old man crying half hr post vaccination saying he didnt feel right, was dizzy, headache, heart palpatations and jitters, he did not believe it was anxiety as they said.
I’ve since realised there was an older man who didnt come back for second jab and I had reported this to the report line. I remember he had walked back into the treatment room the day after his jab and he was anxious, glassy eyed, said he was sick and had been falling over that night. I did his obs and his ecg wasnt right, offered for him to go in ambulance but he declined. He missed his second appointment I wouldn’t be surprised if he died.
I have seen a man with cancer go down hill very quickly after his jab.
I have heard patients tell me there family has told them they have to get the shot or they wont pay for a ventilator. Also a pt tell me that her old neighbour told her he thinks he has killed himself getting the jab and he hasnt been the same since.Cont…
I have heard of a nurse pressured to get the jab who had diabetes under control is now on insulin. Another nurse I know didn’t want it but said she has brain fog and memory loss and sudden onset of menopause..she also admits to seeing patients at a seperate clinic she works at go down hill since getting the shots.
I have a nurse friend who has 2 family members, 1 with bells palsy and the other with myocarditis. She also knows a fit healthy 30yr old who had a heart attack.
My sisters 60yr old neighbour is in a coma after second shot. Her mother in law keeps passing out and her father in law has been showing aggression.
My brother in law also knows a guy in a coma and somebody else with blood clots in his bowel.
My sister in law had kidney stones the day after her second shot.Another thing I have noticed is personality changes in patients and people I know or have worked with where a number of them seem to become aggressive, lack empathy and logical sense.
In comparing my findings with other nurses we have all noticed similiar patterns where we agree that comorbidities seem to become worsened and mortality is being sped up.
We are very concerned and worried sick, especially that they want to give these to our children who will be at much greater risk from the jab than the virus.
We disagree with the mandates, we believe the cases of injuries and deaths to be under reported and the jabs are unsafe and unethical and should be ceased immediately.
RN, Major Hospital.
27/09/21 AHPRA Verified ✅I work on a rehab ward
I know of 3 patients who had a stroke 7-8 days post jab.
(1). 1 Pt with bell’s palsy.
(2). 1 Pt with Guillain-Barré syndrome.
(3). 1 man experienced an unresponsive episode following his 2nd jab. Diagnosed with hypo delirium and pneumonia! 3 weeks in hospital so far and at what financial cost?
Nothing documented in notes. Family told it was nothing to do with the jab.Also possibly seeing vac shedding too.
Bels palsy, shingles causing encephalitis, lots of falls.Lots of PE’s, but unsure of vac status.
Interesting that recently the federal gvt was trying to amend the NDIS Act! It would be interesting to see the statistics of new NDIS applications.
And, what happened to influenza?? Vanished?
Reported by REGISTERED NURSE from Regional NSW:
(1). 62 year old with blood clot on lung post AstraZeneca- ICU admission
(2). 35 year old with severe headaches and blood clot on brain- ICU admission 2 weeks- sent home to have MRIs every 2 weeks as followup
(3). 27 Year old Male- Pericarditis following Pfizer
(4). 19 Year old female- cardiac arrest 3 days post pfizer (deceased)
…and many others.V status not being consistently asked or documented in eMR- medical team not looking to make correlation. Medical team worried about AHPRA and their careers if they speak out.
This is not what we signed up for!
MD. RN. 46years.
27/09/2021. AHPRA Verified ✅
Part 1 of 2.Hi,
Im an RN of 46 yrs practicing as an acute peri/post operative care nurse.
I no longer practice. The following is an account of a close nursing colleague. She experienced: Pfizer x no1 jab- “headache from hell”.
No 2 pfizer jab- awoke in the night totally paralysed for 4-6 hrs(estimated as time unknown on waking). She could not move a muscle, cough, speak, take a deep breath or nudge her husband to call ambulance until it resolved. Only eyes would open and blink..at one point she wished she would die she felt so terrible.On return to duty when recovered much later, she reported incident in writing to hear similar affects with 6 other nurses in total at her hospital. Date 2/6/21. Still has not been interviewed face to face as normal protocol, 10 weeks later.
What is going on? We must all ask ourselves and our superiors?
The Hippocratic oath- to do no harm? Are the medicos brain dead? Is it mind control? Surely no one could need the $ that badly. That is only one example…Cont…
MD. RN. 46years.
27/09/2021. AHPRA Verified ✅
Part 1 of 2.Hi,
Im an RN of 46 yrs practicing as an acute peri/post operative care nurse.
I no longer practice. The following is an account of a close nursing colleague. She experienced: Pfizer x no1 jab- “headache from hell”.
No 2 pfizer jab- awoke in the night totally paralysed for 4-6 hrs(estimated as time unknown on waking). She could not move a muscle, cough, speak, take a deep breath or nudge her husband to call ambulance until it resolved. Only eyes would open and blink..at one point she wished she would die she felt so terrible.On return to duty when recovered much later, she reported incident in writing to hear similar affects with 6 other nurses in total at her hospital. Date 2/6/21. Still has not been interviewed face to face as normal protocol, 10 weeks later.
What is going on? We must all ask ourselves and our superiors?
The Hippocratic oath- to do no harm? Are the medicos brain dead? Is it mind control? Surely no one could need the $ that badly. That is only one example…Cont…
No 2 this is anecdotal from a jab victims daughter-in-law:
An 80 r yr old independant lady, no comorbidities in nursing home. Family expressly forbade- face to face with 2 staff members, her having the jab( I can’t call it a vaccine as it isnt). The army turned up to jab the residents. When they came to this 80 yr old, the residential nurse on duty told the army nurse the said woman was not to have the injection. She ignored the nurse and gave it (az) anyway- that was on a Thursday.On the Friday the relative came to see her mother in law, having been informed via phone of the misdeed. She found the woman in an unusually hyped up state- as if high on something- unusual for this quiet woman.
On the Saturday, the injected woman asked her nurse to return her to her room as she felt unwell. According to the relative who had been told the following, as she walked down the hallway she collapsed and died instantly. This was day 2 after first az.
The attending physician refused to sign the death certificate as he thought his now deceased patient had NOT died of a cardiac arrest as staff assumed. Deceased was sent to coroner in a large city nearby. The coroner only scanned the body, decided it was heart attack and declined to perform a full post mortem. The lady has since been cremated so no body to exume? We all know what to call such an incident!
Life should never be this cheap!
Enough is enough. This must be stopped.
We all know there is power in numbers. Everyone, seem to be impotent to act on this critical and existential crisis in the making.In fact this is threatening humanity’s very survival.
Childless Gladys should read these ‘testimonials’. She is some one else’s child too! Unwitting guilt abounds. The people responsible including medico’s, who ignore what they must be re-cognising, cannot plead ” I didn’t know” for too much longer, surely?? Bring on Nuremberg!
M. D. RN
Senior Clinical Nurse Specialist, Metropolitan Hospital, NSW.
27/09/21.Hi there,
I am a senior Nurse (CNS2) in a metropolitan hospital, NSW.My usual role is in Cardiology.
My lengthy career is ending this week, after decades in the acute sector.I have seen many patients both in ED and Cardiology with vaccine SE’s .
These are LARGELY under-recognised, and RARELY reported. I have told relatives to make their own TGA reports as reporting in the acute sector is NOT HAPPENING.Doctors are RARELY attributing the various conditions to vaccination, but when you take a history it is very easy to join the dots.
Heart attacks (all ages), acute myocarditis / pericarditis, DRASTIC deterioration in EF (ejection fraction – index of heart’s pumping strength), ie worsening in heart failure.
I understand that many are presenting with strokes, and other neurological complications.
Diabetes has been far more unstable in some, and difficult to manage, with very labile BSLs.
I have seen colleagues with gastrointestinal SE, recurrent pneumonias
Many non- injected, including myself have experienced symptoms from spike protein transmission (shedding).
GI pain (severe), headaches, migraines, sleep disturbance.
I have seen bizarre changes in pathology, huge drops in haemaglobin, and derangements in biochemistry (Na, kidney function).I had a secondment in Aged Care and after the vaccination was rolled out in Facilities, saw MANY acute deteriorations, with increases in death rates above normal
Loss of speech, loss of mobility, chest infections.My sister in law works in community aged care, and has seen MANY SE as well. Renal Failure, siezures, acute loss of mobility with resultant falls.
Many of the elderly she has cared for and knows well have had their death hastened, or had to move into residential care as they now cannot manage at home.Thanks for helping us to get our stories out there.
RN, 40 years experience, NSW.
27/09/21. AHPRA Verified ✅Hello,
I am an RN with over 40 years experience, mostly in the public sector.I am currently employed on a casual basis.
I received a letter from NSW Health last week stating I “ must have” my first “ vaccination” by the 30th September to continue to work.
If I don’t I will not be able to work for NSW Health and will be placed on unpaid leave.All of the nurses in my ward( except a pregnant one) acquiesced to the “ vaccine” even though some were
dead against it.One nurse experienced loss of sensation in both legs below the knees which eventually resolved.
Another staff member( clerical) had a mini stroke and ended up in ED.
Both these episodes were not reported as vaccine injury.Indeed, one Physician said it definitely is not vaccine related.
I will now be forced not to work as I do not want the “vaccine”.
I believe NSW Health system will be in dire straights after 30th September and beyond as very experienced staff leave.I am a Registered Nurse working for a large public hospital in Melbourne.
A significant amount of our patients have had the covid vaccine and are presenting to us as transfers from ED, presenting with chest pain, shortness of breath, neurological symptoms , headaches and fevers. These patients are being found to have confirmed mini strokes (TIA), Pulmonary Embolisms, neurological disorders, severe headaches and deranged pathology resulting particularly often in acute kidney injury.
The most concerning of these presentations is the fact that majority of these patients range from 20-70 years old. One female patient in her 30’s presented with a body temperature of 40 degrees and has since been found to have multiple bilateral PE’s.
There has been no documentation or discussion from Doctors linking these patients symptoms with their recent covid vaccination. These patients were healthy and fully functioning people pre vaccination.
We’re also having to palliate patients at a concerning rate due to acute deterioration. Most of these patients are dying from respiratory failure or suffering a massive stroke.
All nurses in my clinical area have now been vaccinated besides myself. Some have told me they were coerced into getting it by management.
I am counting down the days now until I’m fired for not wanting the vaccine.Our current staffing is awful, I hate to think how bad it will be after October 15th when unvaccinated nurses are mercilessly terminated from employment. I feel for the patients who will fall through the gaps of our already stressed healthcare system.
Registered Midwife, WA.
28/09/2021
AHPRA Verified ✅Hello, Thank you so much for the work you are doing.
I’m a Registered Midwife in W.A. and until I resigned on Wednesday Sep 21, I had been working at the biggest hospital in the South West region. When RANZCOG and the ACM came out with their guidelines stating the c19 vax was safe for pregnancy, the directive from the hospital was to promote it hard.
At the hospital clinic I know of 2 women that received their first doses and they subsequently lost their babies;
1st dose at 34 weeks and 2 days, fetal death in utero at 36 weeks
1st dose 28+2, fetal death in utero 29 weeks I know of other women in the community under 20 weeks as reported to me by midwives that work with General Practice obstetricians;
1st dose 12+6, miscarriage 13 weeks
1st dose 17 +5, miscarriages 18 weeks
1st dose 12 weeks, miscarriage 12+2
Now, I know correlation does not mean causation, but it certainly should be investigated. Only one of the above cases have been reported. I fear many won’t be and they will be lumped into the 1:4 pregnancy loss statistic.
It’s not something that is asked (vaccine status) when women come to the hospital with a loss, so many may fall through and be missed.
I mentioned it to a doctor and they didn’t see the connection. I’m so sad to leave a job I love, but this isn’t health. This is something entirely different.
Registered Midwife, Small Rural Hospital.
28/09/21. AHPRA Verified ✅Hi,
I’m a Midwife in a small rural hospital.
We recently admitted a woman who’s baby had unfortunately died in utero and was subsequently stillborn. She was in her third trimester and she’d had her 2nd dose of Pfizer just 3 days before she stopped feeling the baby moving.
When I questioned my manager if this was going to be reported to the TGA she talked to the doctor and he said no, because there was no evidence of the two being linked.
I can’t help but wonder…what if nobody else is reporting events like this either because they all think there is no evidence?
contact us: nursesspeakout@pm.me
COVID-19: Vaccinating kids – the debate heats up
By Maryanne Demasi, PhD | September 23, 2021
5- to 11-year-olds
This week, the Australian Federal Health Minister announced a commitment to COVID-19 vaccines for kids aged 5 to 11 years pending TGA-approval, after Pfizer claimed, in a press release, that it had obtained “favourable” results.
Pfizer’s ongoing Phase 2/3 trial apparently showed the vaccine “was safe, well tolerated and showed robust neutralising antibody responses”. However, the results were not submitted to the drug regulator, nor were they published in a medical journal, so for now, we must take their word for it.
Pfizer registered the trial plan, showing that it tested a lower dose (10µg) as well as two higher doses (20µg and 30µg) in 5- to 11-year-olds. Whether the vaccine can provide protection against symptomatic disease or severe COVID-19 remains to be seen.
The manufacturer also claimed that the vaccine had a “favourable safety profile”, however, it is important to note that the trial has not enrolled enough children (2,268) to detect any rare but serious harms that might arise from the vaccine
Only healthy kids were recruited in the trial – children with known or suspected immunodeficiency, a history of autoimmune disease, any condition associated with prolonged bleeding, anyone receiving treatment with immunosuppressive therapy or corticosteroids were excluded from the trial.
Notably, these are the same cohort of children who have been prioritised for the vaccine.
Despite little to no data available for its safety and efficacy, the Israeli Ministry of Health gave the green light to start vaccinating high risk 5- to 11-year olds with the lower-dose (10µg) of the vaccine.
Pfizer senior vice-president Dr Bill Gruber said he felt “a great sense of urgency” in the process, and Pfizer’s CEO Albert Bourla said trial data would be submitted to the various international drug regulators for “immediate authorisation.”
The language of Pfizer executives, the frenzied press coverage, and the political will of Governments, is all designed to pressure drug agencies to fast-track authorisations.
Younger than 5 years old?
Pfizer announced that trial data involving children under 5 are expected later this year.
Last week, Cuba began vaccinating toddlers as young as 2, using its homegrown vaccine, the Soberana 02, from the Finlay Vaccine Institute administered at adult doses. To my knowledge, there has been no data from Phase III trials published in the peer-reviewed literature in children as young as 2 with this vaccine.
China’s drug agency has cleared three COVID-19 vaccines produced by Sinopharm and Sinovac and is vaccinating children aged 3 years and older, under emergency use authorisation.
12- to 15-year-olds
Most major western nations have authorised COVID-19 vaccines for those aged 12 years and older.
In Australia for example, children aged 12 to 15 years began receiving the mRNA vaccines last week. According to the NSW Premier, 20% of children in the state of NSW have already had their first jab.
They require a two-dose regimen, the same dose given to adults, which aligns with the US FDA and Health Canada advisories on vaccines for this age group. (See my previous analysis for 12-15yr olds)
This does not align with the UK’s more cautious approach. After significant political and media pressure, UK chief medical officers recommended a single dose of the Pfizer vaccine, because of concerns about rare side effects such as heart inflammation.
Brazil appears to be an outlier at the moment. It was reported that the Minister for Health called for the suspension of the COVID-19 immunisation of people aged 12 to 17 after the death of a 16-year old girl named Isabelli Borges Valentim, eight days after she received the Pfizer shot. Authorities are still investigating the incident but the drug regulator denies any link to the vaccine.
Myocarditis/Pericarditis
This issue has stirred up some heated debate.
Now that real world data is becoming widely available, myocarditis (inflammation of the heart muscle) and pericarditis (inflammation of the membrane surrounding the heart) are being reported as rare harms related to the Pfizer & Moderna mRNA vaccines.
Israel, because of its fast vaccine roll-out, was first to raise the alarm – 148 cases of myocarditis were reported within 30 days of immunisation, more commonly after the second jab. It prompted the Israeli Ministry of Health to launch an investigation into any possible link between these cases of myocarditis and vaccination.
Since then, other countries such as the UK, the US and Canada have corroborating data.
In June, the US FDA decided that the link between the mRNA vaccines and myocarditis, particularly in young males, was sufficiently clear that it revised its vaccine fact sheets to include a warning.
The CDC released data showing the incidence of “expected” versus “observed” incidences of myocarditis and pericarditis and found a significant increase in the observed rates. The graph shows the higher rates in red (see table numbers circled in red).

Another study, published in JAMA which looked at data from 40 hospitals in the US showed a similar pattern to the CDC, although at higher incidences, suggesting that the vaccine’s adverse events were being underreported.
Researchers then took a more granular look at the database for reported adverse events (VAERS database) between 1 January and 18 June, and found boys aged 12-15 years vaccinated with their second shot of the mRNA vaccine, with no underlying medical conditions were 4 to 6 times more likely to develop a cardiac adverse event, than ending up in hospital with COVID-19.
The study was published as a pre-print online but it ignited a twitter storm, with critics claiming the study ‘over-estimated’ the risk and it was biased because one of the authors belonged to a group that did not support making vaccines compulsory.
Sceptics say that most of the myocarditis cases are mild, and that children recover quickly from hospitalisation. Others are not so quick to dismiss the potential risk of ‘sub-clinical disease’ (myocarditis without symptoms) in children.
Notably, a retrospective multi-centre study across 16 US hospitals including patients <21 years of age with a diagnosis of myocarditis following COVID-19 vaccination, found concerning abnormalities in heart tissue (the left ventricle) (See image with yellow arrows).
Jain SS, et al doi: 10.1542/peds.2021-053427.
Careful monitoring is required to see if these abnormalities lead to fibrosis, which can have long-term implications for young patients.
Early findings suggest that post-vaccination myocarditis could be mediated by the toxicity of ‘spike protein’ on heart muscle cells or from circulating spike proteins in plasma after vaccination.
The risk of myocarditis associated with contracting COVID-19 infection may be higher than that after vaccination, but more research is needed to weigh harms against benefit.
If we don’t vaccinate kids, what about long COVID?
The fear of long-COVID has been a major impetus behind vaccinating kids.
A recent review by Monash University, analysing 14 international studies on long COVID in children and adolescents, found no difference in the symptoms reported by those who had experienced COVID-19 and those who had not.
Lead researcher on the study, Professor Nigel Curtis told newsGP the review’s findings should be reassuring for parents and carers.
Similarly, a webinar hosted by The BMJ revealed the results of the largest citizen-scientist participation study to date in young children. It used a smartphone app to monitor the illness and symptoms of children after testing positive to COVID-19.
The researchers found that the median duration of illness was 6 days. Only 4.4% of children had illness duration >28 days and 1.8% had symptoms >56 days. Encouragingly, their symptom ‘burden’ was greatly reduced by this time (none became worse) with the most common symptoms being headache and fatigue.
The researchers looked at neurological symptoms such as epileptic seizures, convulsions, impaired attention and concentration, but none were reported.
Lead investigator on the study, Prof Emma Duncan from Kings College in London concluded “Long illness duration of COVID-19 in children is uncommon.”
Vaccine Mandates for kids
Despite COVID-19 vaccine mandates for teachers in places such as New York and Australia (Victoria and New South Wales), no Federal government has announced plans to make the vaccines compulsory for children (yet).
Canadian and English professors have argued that making COVID-19 vaccines mandatory for children, will “encourage uptake”.
U.S. Surgeon General Vivek Murthy has also suggested that COVID-19 vaccine mandates for students could happen at the state and local level in the US, once they have been approved for paediatric use by the US FDA.
In a surprise announcement this week, the Los Angeles public school system said students aged 12 and older will now have to be double-vaccinated by the end of the year, to attend classes on campus or take part in sports and other extracurricular activities. It remains to be seen whether other school districts will follow.
Consent from kids
Before the age of 14, minors are generally thought to lack the cognitive capacity and maturity to make rational judgments about their health.
In fact, most US state laws presume that minors lack medical decision-making capacity and therefore require parental consent for most health care decisions, including vaccination, with some exceptions.
However, in the case of COVID-19, under what is termed ‘Gillick competency’, those under 16 years can make independent decisions about a medical treatment if they can demonstrate they have the capacity to consent, even if their parent withholds consent.

This applies to every Australian state and territory as part of the ‘common law’ and in the UK.
The Victorian government has produced ‘communication packs’ for teachers and educators on how to ‘promote’ COVID-19 vaccines to minors.
Hopefully, the conversations about COVID-19 vaccines, between health professionals and minors, are conducted without coercion, pressure or judgment.
Not surprisingly, this has raised the age-old question about who is better placed to determine the best medical treatment for a child – a parent or a Government minister?
The debate will continue and experts will need to wade through muddy waters to find a balance between protecting children’s health and the uncertainty over the long-term harms of the vaccine.
Featured Video

Death Spikes & Rising Cancer In Our Youth Explained
or go to
Aletho News Archives – Video-Images
From the Archives
Politicians lie
By Mazin Qumsiyeh | Popular Resistance | August 18, 2013
There is no way to say this truth nicely: Politicians lie. That includes Japanese, American, Egyptian, Israeli, and Palestinian politicians! Is there something more common sense than that? Yet, so many citizens around the world believe their own politicians or wistfully acknowledge lies but think it is part of the job needed to run things. They believe even when politicians contradict themselves blatantly. This phenomenon is rather remarkable. It is a dissonance and disconnect from reality that many seem oblivious to. It is very dangerous because it can lead to accepting rationales for going to war. These can be deadly wars that lead to millions of lives lost as happened in what was called World War 1 and WW2. Even when incredible and declassified evidence abound, politicians continue to lie and old mythologies refuse to die. Here are just a few of the countless lies told to us over the past few decades… continue
Blog Roll
 Aletho News
- RSF military group defects, joins Sudanese army: State media
- Ireland goalkeeper refuses to play ‘Israel’ as squad weighs boycott
- China pushes back against US on Cuba, Iran
- Ukrainian Soldiers, Potential Mercenaries: Have Gun, Will Travel!
- Burnham’s UN debut… A masterclass in British disinformation
- Iran flights continue despite US aviation sanctions
- Global Tipping Points Lead the World Into a State of Entropy
- The day-after at the White House: USA and Xi Jinping
- The Geopolitical Balance in the Red Sea: The UAE Being Displaced by New Players
- Iraqi resistance group vows to stage airport sit-ins over Iran aerial blockade
- If Americans Knew
- Deconstructing Netanyahu’s pants-on-fire UN rant – Daily Update
- Trump betrayed voters with his campaign lies and prioritized a foreign country once he took office
- Netanyahu calls Israel’s war in Gaza ‘opposite of genocide’ in UN speech to near-empty hall
- Settler Kidnappings: Torture, Sexual Abuse and Terrorisation of Palestinian Abductees as Israel Deepens Annexation of West Bank
- Gaza winter nears as 162,000 tents become unusable, raising fears of humanitarian crisis
- Netanyahu says, “It’s the opposite of genocide”; UN says Gaza economy is world’s ‘most severe crisis on record’ – Daily Update
- Israel’s US-Backed Assault on Gaza Has Created the ‘World’s Most Severe Economic Crisis on Record’: UN
- ‘Protecting U.S. Citizens’… From Israel
- ‘This is where I live now, the back of a truck’: a day in the life of a grandmother in Gaza
- In UN Speech, Iran’s President Displays Pictures of Children Killed by US, Brings Attention to Israel’s Nuclear Arsenal
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

