Hypocritical Gospel according to the Covidians
By Elephant City | The Conservative Woman | June 28, 2021
THE recent spectacle of the G7 leaders in Cornwall posing for photos in masks and then ripping them off to party down with no social distancing is only the latest and most blatant example of double standards from the Covidians. For anyone paying attention, they have been giving us a daily masterclass in advanced hypocrisy.
The Covidian faith is strongest among Left-leaning elite managerial types. Safetyism is a huge part of their religion. These are people who slather sunblock on their kids before they step out the door and monitor them with tracking apps on their phones. And then they allow their kids to be shot up with an experimental ‘vaccine’ (gene therapy) that was tested on only 1,131 children who were followed up for less than six months.
The Covidians tremble in their homes like gutless cowards because of a disease that has an average survival rate of at 99.8 per cent for the general population and nearly 100 per cent for the healthy population. And then they allow themselves to be injected with an experimental gene therapy with less than a year of safety data, authorised by regulatory agencies fully corrupted by Big Pharma money. So much for ‘stay safe’!
Covidianism is a branch of wokism. The woke take every opportunity to manufacture status by loudly proclaiming their concern for ‘social justice’. They seized on the pandemic as a chance to flaunt their shining virtue to the world by hanging out of windows and lustily banging pots and clapping. They conveniently ignored the fact that the lockdown policies they so eagerly supported crushed the working class. They considered it completely natural that a class of workers should have to deliver their food, work in the grocery stores, take their garbage and clean their streets, while they hid behind their computer screens and called for ever harsher lockdowns. Their idea of social justice consists of forcing others to face the risks of Covid while they attend Zoom meetings in their sweatpants.
As card-carrying members of the woke, the Covidians surely spent the last four or five years eagerly mouthing the central tenet of the faith: that the ‘patriarchy’ is the root of all evil; that a gang of Western white men has spent the last few centuries brutally oppressing everyone else in the world. And then, without any irony, they slavishly follow every command of Western white men such as Boris Johnson, Chris Whitty, Matt Hancock, Anthony Fauci and Joe Biden.
Likewise, as good wokesters, they no doubt eagerly signed up to the campaign to ‘defund STEM’ (because science itself is a tool of the dreaded patriarchy). Now, without the slightest tinge of shame, they angrily insist that we must ‘follow The Science.’ Of course, what they mean by ‘The Science’ is the institutional narrative favourable to Big Pharma.
The Covidians profess tremendous faith in the vaccine. Yet they find it almost impossible to let go of their precious masks, their flag of tribal identity. Likewise, despite their faith in the vaccine, the Covidian faithful insist that everyone else on earth be forced to take the vaccine (though presumably, if the vaccine works, they are protected so it doesn’t matter whether others take it).
As members of the elite managerial class, they obsess about the quality of their food, scrutinising food labels to be sure that anything they put into their bodies is organic, artisanal and free from chemicals. And then they queue to have a syringe full of unknown, barely tested, industrial genetic products shot directly into their bloodstream.
No doubt most Covidian women are strident feminists who mouth the slogan ‘my body, my choice’. Yet they eagerly support a national campaign of coerced ‘consent’ wherein the state forces the people to accept injection of unknown and potentially dangerous genetic material into their bodies. They are supporting the penetration of the state into their physical beings – mechanical rape on an industrial scale.
Likewise, these feminists have no doubt spent the last few decades working their way into every boardroom, professorship and political office. Now they vocally support being locked in their homes by the state. They gladly accept limits on their freedom that would make Saudi Arabian women look like liberated hippie chicks.
The Covidians claim that black lives matter, and yet they support policies that damage the working class, in which people of colour are disproportionately represented. Likewise, they support the regime that actively suppresses knowledge and use of ivermectin, a drug that would eliminate Covid. Thus they perpetuate a pandemic that disproportionately affects people of colour.
If you look closely at the words and actions of the Covidians, you will see nothing but contradiction and hypocrisy. This indicates an appalling lack of principles, because principles would demand some consistency across words and actions. Rather, for the Covidians, it’s all about obedience to the diktats of the mainstream media and government agencies. These people are reeds bending in the wind, incapable of thinking for themselves and only concerned with appearing virtuous. They have stood for nothing and fallen for everything.
These are just a few examples: please add more in the comments section. We have a duty to history to document the full depths of the mind-boggling hypocrisy of the Covidians.
Re-Evaluating Mask Mandates Part II: Exposing the “Assumption-Led Claim”
By Masha Krylova | C2C Journal | June 25, 2021
This two-part review is not meant to cast doubt on the seriousness of the SARS-CoV-2 infection, but to hold up to scientific and logical scrutiny the dominant narrative that has frantically promoted mandatory face coverings for the general public as an effective means of protection against the viral spread. Open-minded inquiry quickly uncovered evidence that this narrative is not only skewed, but unscientific, as we will see in even greater clarity. One of its noticeable features has been to denounce anyone who questions the dominant view as ignorant, deluded, a conspiracy theorist or a deliberate purveyor of misinformation. This is deeply disturbing in a free and democratic society. It also raises the question, if the pro-mask forces are unwilling to debate the issue on substance, just how strong their case really is. If they are truly “following the science,” why won’t they discuss the issue on exactly those terms?
In Part I, Science Gives Way to the Talisman, we noted the previous longstanding scientific and public health consensus against ubiquitous masking as an infection-control method, a view that was initially maintained by public health leaders when Covid-19 hit – but then abandoned. Following this came a blizzard of several hundred studies that appeared to prove the efficacy and benefits of wearing masks in reducing viral transmission (but with no mention of any potential harms). These studies seemed to “seal the deal” regarding masking, ending any need for further discussion.
Strangely, however, none of these studies were randomized controlled trials (RCT), the gold-standard of reliability in scientific testing and the only research method that can establish causal relationships between a selected behaviour or intervention and an outcome. The pro-mask studies were of an observational type and could demonstrate at best only a temporal association (i.e., correlation) between mask-wearing and infection rates – but were nonetheless hailed as definitive. Yet there was still room for doubt, because large-scale RCTs had been performed examining mask-wearing in relation to influenza viruses. And the bulk of these high-quality studies in the pre-Covid era failed to support the efficacy of mask-wearing to stop the spread of viral infection.
Why does this matter today? Because even as countries around the world reopen, the conflict over mask-wearing appears fated to continue. Even though mask mandates are being discarded or even outlawed in many U.S. states, and are soon to be dropped in Alberta, there is widespread resistance to allowing people once again to show their faces wherever they go and whatever they do.
Other Canadian provinces, left-leaning big-city mayors and various groups of medical experts are all demanding that mask mandates remain in place until some utopian goal is reached – such as zero recorded Covid-19 cases (as unrealistic an idea as, say, fully eradicating influenza). If we are to be subjected to prolonged political conflict over mask-wearing – and if many of us continue to feel a lingering urge to mask up just in case – then surely it is worth understanding whether masks even work, or whether wearing them might present health risks of their own, unrelated to Covid-19.
Randomized Controlled Trials (RCT) of Masking During Covid-19
A search by C2C Journal of the scientific literature since early 2020 has found two RCTs specific to mask wearing during the Covid-19 pandemic.
The first was a large Danish study, approved by an ethics committee and published in March 2021 in Annals of Internal Medicine. It tracked over 6,000 participants across the country, divided roughly equally between people who wore surgical masks and those who did not, from April to June 2020. Universal mask wearing was not yet recommended by the Danish authorities and mask use remained generally uncommon, thereby avoiding ethical concerns that otherwise might have been raised by the need to persuade a control group not to wear masks, and freeing the study results from the impact of governmental regulation.
Another strength is that this study used not only the results of the common PCR test as its primary outcome to measure infection results, but also the participant’s antibody count, an arguably more reliable measure than nasal swab sampling. Importantly, all participants spent at least three hours per day outside their homes, i.e., were not isolated from social interaction with potentially infected individuals.
As with previous RCTs testing the efficacy of facemasks against influenza virus (discussed in Part I), the Danish scientific team found no statistically significant difference in the spread of SARS-CoV-2 between the experimental and control groups. Specifically, the researchers reported: “SARS-CoV-2 infection occurred in 40 participants (1.8%) in the mask group and 53 (2.1%) in the control group.” These results, it stated, were “compatible with a possible 46% reduction to 23% increase in infection among mask wearers,” which, as the researchers concluded, makes their findings practically inconclusive. Such low precision of the detected impact of mask wearing, varying from being beneficial against the infection to making it worse, impedes drawing a more definite conclusion. Among the study’s limitations was the reliance on self-reported data, but that seems inevitable in population-based studies.
The other RCT is a micro study performed in a laboratory setting. It used four participants whose saliva, captured on a petri dish, was analyzed following exposure to the virus. It found no difference in the median viral emission between the mask-free individuals and the mask wearers. That study, however, was ultimately retracted after the researchers admitted they had misinterpreted part of their findings but were, rather strangely, denied the customary opportunity to correct and update their paper.
Clearly then, despite claims that RCTs are inappropriate for studying mask effectiveness against Covid-19, it is both possible and would be of incalculable benefit to the public and policy-makers to perform just such studies – as was done with influenza. And the fact that the two conducted RCTs, one in a community setting and the other in a laboratory setting, were found inconclusive should only elevate the urgency of running additional and even better RCTs. Instead, and very strangely again, RCTs seem to be under a general halt in the scientific community.
The final point on the epidemiological evidence is the odd juxtaposition between the fact that most RCTs do not find facemasks to be beneficial against other respiratory illnesses while nearly all observational studies concerning Covid-19 do. That is why in reviews such as this, where accumulative data from both RCTs and observational studies are analyzed, the evidence for mask effectiveness is generally said to be “inconclusive.”

Despite claims that randomized controlled trials are inappropriate for studying mask effectiveness against Covid-19, such studies have been done with influenza.
To rationalize this observation, some have suggested that experimental epidemiological studies might underestimate the benefits of mask-wearing whereas observational studies overestimate them. If that is the case, then because the pre-Covid-19-era RCTs have been roundly ignored and virtually no Covid-era RCTs were conducted at all, the world has been subjected to a seriously skewed view of what masks can accomplish against this viral pandemic.
Looking broadly, the Covid-19 crisis has generated literally tens of thousands of scientific papers on nearly all aspects of the disease in question. This should certainly appear to justify more than two RCTs evaluating the efficacy of one of the most heavily relied-upon, onerous and contentious public health measures. The fact that this has not been done is a matter of considerable curiosity, to say the least.
The Microscopic Mechanics of Masks
There is, further, a common pro-mask argument based on “mechanistic” evidence of masks’ protective properties (see again this review). Covid-19 is said to propagate both through small respiratory aerosols, with a diameter of less than 5 micrometers (μm, one-millionth of a metre) and larger droplets, 5-10 μm in size. Technically, any kind of mask can impede the spread of aerosols and droplets, with various masks providing different degrees of protection. Although leakage is possible due to poor fit of certain mask types (reducing protective capacity by up to 30 percent), it is generally established that masks provide a physical barrier against splashes and sprays of fluids.
Masks do not, however, function as a “strainer” but rather as a filter, meaning there is far more to a mask than its pore size. Various mask fibres perform different types of filtration (such as gravitational sedimentation, inertial impaction or interception) and these processes play a role in catching airborne particles. The review cited above notes that N95 masks have the best so-called particle filtration efficiency, with surgical masks having a lower degree of such efficiency. Cloth facemasks, which are not regulated, are “expected” to be even less efficient. That was why the CDC recommended using masks with two or more layers to limit the spread of Covid-19.
This, too, seems like strong, if not decisive, evidence in favour of facemasks. And yet the conclusions provided by mechanical studies have not been supported by RCTs. On the contrary, several RCTs have shown no advantage of wearing N95 versus surgical masks in protecting individuals against clinical respiratory illness, including coronaviruses (see this systematic review of RCTs). This seemingly makes no sense given the assertions of the N95 type’s filtration advantage over surgical masks – unless of course the mechanistic studies were focused on the wrong variable, i.e., filtration efficiency is not determinative, or masks in general are not especially useful.
Moreover, recall that the studies discussed above merely state that cloth masks are “expected” to have less particle filtration efficiency. But just how much less is unknown, because to date there has been no known scientific study describing and evaluating the mechanical properties and effectiveness of cloth masks or facial coverings in reducing the transmission of droplets and aerosols containing Covid-19.
This in itself is remarkable if not shocking, since hundreds of millions of people worldwide – possibly billions – habitually wear those cloth coverings and expect them to be life-protecting. So it is fair to say that the body of mechanics-focused research that is meant to provide further evidence in favour of masking does little but cast even greater doubt on the rationale for universal public masking.
The Serious Adverse Effects of Mask Wearing
Public health decisions are not intended to be based solely on scientific evidence. Science aims to observe, explain and predict as many natural phenomena as possible, yet it is not absolute and its models frequently fail to be verified. Hence, in the realm of policy making, especially regarding public health-related issues, it is commonly understood that any proposed medical intervention should undergo thorough cost-benefit analysis prior to implementation.
Enforcement of masks on the general public should not have been an exception. Yet – again astoundingly – no known cost-benefit analysis has ever been done on the issue anywhere worldwide. Nor, until two months ago, was a comprehensive investigation conducted to evaluate the adverse effects of mask wearing in the context of the Covid-19 pandemic. This should be considered a stunning omission since, in the pre-Covid-19 era, convincing evidence had been accumulated that the wearing of masks carries risks and can be harmful (see, for example, this and this study). And recall the WHO’s earlier warning about self-contamination (discussed in Part I).
The new literature review of April 2021 is devastating to the common view of masking as all-benefit, no-risk. Prepared by eight German scientists, it includes 31 RCTs and 13 observational studies, was published by the International Journal of Environmental Research and Public Health and is entitled Is a Mask That Covers the Mouth and Nose Free from Undesirable Side Effects in Everyday Use and Free of Potential Hazards? Notably, the review provided quantitative evaluation of all types of masks including unregulated cloth masks. It reports undesired side effects across no fewer than 14 medical disciplines, including neurology, psychology, sports medicine, pediatrics and microbiology.
The review leaves very little room for doubt that prolonged mask wearing by the general public can be unsafe. In fact, it is claimed to lead to “psychological and physical deterioration” with a “negative effect on the basis of all aerobic life, external and internal respiration, with an influence on a wide variety of organ systems and metabolic processes with physical, psychological and social consequences for the individual human being.”
The overarching negative consequences of mask wearing include an increase in dead space volume (by 80 percent in one study), a reduction in the user’s blood oxygen levels, a 30-fold increase in carbon dioxide retention and greater average breathing resistance (by 128 percent) due to excessive moisturization of masks.
In essence, wearing a mask induces changes in the person’s physiology of breathing – one of the most basic and critical biological functions. In particular, it leads to expansion of dead space volume, which is the amount of the inhaled air that does not participate in gas exchange. It’s normal to have some 150 millilitres of dead space per inhalation (out of 500 ml that is typically inhaled and exhaled in each respiratory cycle), but an increase of 80 percent greatly diminishes the effectiveness of gas exchange in lungs.
Such breathing-related changes, in turn, lead to a host of other negative medical effects: increased heart rate, elevated blood pressure and irritation of the respiratory tract which could lead to asthmatic reactions. While these may strike many people as minor irritants to be endured during a pandemic, they are medically serious. In the long run, the effects are expected to be illness-provoking and include vascular damage, coronary heart disease (metabolic syndrome) and neurological diseases such as epileptic seizures. The review states: “Even slightly but persistently increased heart rates encourage oxidative stress with endothelial dysfunction, via increased inflammatory messengers, and finally, the stimulation of arteriosclerosis of the blood vessels has been proven.”
This summary of the previous findings is distressing enough, yet is not exhaustive. The initial physiological effects of mask wearing are also recognized to lead to non-physical consequences, including the impairment of the wearer’s brain function. The view that wearing a mask, especially for a long period of time, quite simply compromises one’s ability to think is among the review’s most firmly stated conclusions and is worth quoting at length:
“Confusion, disorientation and even drowsiness… and reduced motoric abilities… with reduced reactivity and overall impaired performance… as a result of mask use have also been documented…
The scientists explain these neurological impairments with a mask-induced latent drop in blood gas oxygen levels O2 (towards hypoxia) or a latent increase in blood gas carbon dioxide levels CO2 (towards hypercapnia). In view of the scientific data, this connection also appears to be indisputable.
In a mask experiment from 2020, significant impaired thinking (p < 0.03) and impaired concentration (p < 0.02) were found for all mask types used (fabric, surgical and N95 masks) after only 100 min of wearing the mask. The thought disorders correlated significantly with a drop in oxygen saturation (p < 0.001) during mask use.” (Emphasis added.)
In addition to covering these grave cognitive harms, the German review also discusses the psychological dimension, finding that habitual mask wearing can cause a combination of exhaustion, discomfort, anxiety, panic, anger, distraction and a feeling of imprisonment.
The idea that experiencing difficulty breathing and a needlessly elevated heart rate while inhaling one’s own C02 for hours or days on end is bad for one’s health and wellbeing seems like unassailable logic and sheer common sense. Yet it was ignored, if not actively suppressed, by the political class, public health officials, widely quoted medical professionals and the news and social media in the frenzied campaign to impose and then sustain public mask mandates. And some scientists in joining this moralistic crusade cast aside their professional impartiality, even-handedness and intellectual curiosity.
Dissenting scientific voices were silenced and even cancelled by their peers. Among those are Denis Rancourt, a former tenured Full Professor of Physics at the University of Ottawa. The prolific researcher had amassed a publication record of over 100 papers in leading peer-reviewed journals in physics, chemistry, geology, materials science, soil science and environmental science. Rancourt’s scientific “h-index” of 39 placed him just one point short of the international rating for “outstanding scientist” in the Nobel Prize category. But all of that would count for nothing once Rancourt concluded that the orthodoxy on masking was wrong.

For speaking up against the imposed pro-mask narrative, former tenured University of Ottawa Full Professor of Physics Denis Rancourt was silenced and cancelled – not by government, but by his peers.
In April 2020, Rancourt wrote Masks Don’t Work: A Review of Science Relevant to Covid-19 Social Policy. The article was published by ResearchGate, a popular networking site for academics, gathering an unprecedented 400,000 reads – but was later taken down. Since then Rancourt has written another dozen articles opposing the general narrative around the Covid-19 virus and pandemic while ResearchGate has all-but erased his existence, leaving only the remnants of his publicly presented lab on its website and moving his original profile into “archives.”
On his personal blog, Rancourt explained the censorship he suffered. The note he received from ResearchGate’s two managing directors stated that he was de-platformed because his widely read paper “goes against the public health advice and/or requirements of credible agencies and governments” which they “thought… had the potential to cause harm.” In other words, instead of free-wheeling scientific inquiry like Rancourt’s stimulating broader debate, aimed at informing and strengthening public policy, the people in charge of a major scientific website appear to believe that it is current public policy orthodoxy which must dictate the bounds of science itself. And that a nebulous and entirely unsupported (i.e., unscientific) worry about the “potential” for harm must outweigh and shut down the search for truth.
On balance, it is Rancourt who evidently has truth on his side for, as we have seen, the risks of mask-wearing are extensively documented. These harmful effects are particularly evident – bluntly starring into people’s faces – in sports. There have been several vivid recent accounts of young athletes forced to wear masks during competitions falling into distress, events that were captured on video and covered by local TV stations.
Earlier this spring, for example, a young cross-country runner collapsed at a New Mexico state championship. The teenager, who had never suffered a collapse in his five-year running experience, was taken to hospital and was reported to have excessive C02 in his lungs, a lack of oxygen, elevated liver enzymes and high red blood count. Recalling the last minute of the race, the runner said, “I realized I’m going to fall, I got super dizzy, I was losing my balance and I could feel my legs almost giving out from under me every step,” and then, “I don’t feel like I’m getting enough air under the mask.” This was not the only time when masked school-age athletes needed emergency care.
Indeed, the German review makes it very clear that mask wearing has long been recognized as a destructive practise for athletes – and as much or more so for children. Respiratory problems are especially severe in children due to the high oxygen demand associated with their early developmental stages. In one of the studies cited by the German team, masks in children were shown to trigger headaches in 50 percent of cases, difficulty concentrating in 50 percent, joylessness in 49 percent, learning difficulties in 38 percent, fatigue in 37 percent, anxiety in 25 percent and even nightmares in 25 percent.

That masks and athletics are a toxic combination was considered incontrovertible until Covid-19 came along. It has required masked athletes falling into medical distress during competitions to rediscover this obvious truth.
Finally, wearing masks may actually increase the risk of catching other diseases. The surfaces and interior fibres of warm and humid masks provide an ideal environment for the accumulation of germs. As was shown in the reviewed experimental studies, after only two hours of wearing masks the pathogen density can increase ten-fold and after six hours the following viruses can be detected: adenovirus, bocavirus, respiratory syncytial virus and influenza viruses. And these are consequences observed in medical personnel who are conscious of avoiding self-contamination. While the WHO is by now likely to be discredited in the eyes of many people, its original caution about masks is evidently well-founded.
After its exhaustive scientific enterprise, the German review team arrived, in effect, back at the beginning: reiterating the longstanding skepticism towards mass-masking that prevailed until March 2020. Opening with a pointed reminder of the World Medical Association’s 1948 Geneva Declaration (revised in 2006), the German team’s conclusion can only be read as a full-throated denunciation of the mask frenzy of the past 15 months:
It is worth repeating three devastating words from the German review: “assumption-led claim.” In the researchers’ considered opinion, that is the crux of the entire campaign to subject billions of people to the burdens and harms of habitual mask-wearing.
It Is Time to Unmask
Perhaps upon finishing this read there will still be some facemask proponents who maintain that mask wearing is warranted because, even if they are not as effective as first hoped, they might still do some good – perhaps saving even one life. They can point out that in a public health crisis, with thousands dying and hundreds of thousands infected, anything even marginally beneficial, especially something inexpensive and simple to use by anyone, is surely worth doing. Objections based on human rights, freedom and individual responsibility, as often argued, can be dismissed as frivolous or irrelevant, or set aside until normality returns.
Nonetheless, as we have seen, the risks of this practice on a broad population scale are substantially greater and more palpable than their benefits, which turn out to be largely assumed and remain unsupported by gold-standard scientific evidence. And these risks are not merely transient but of potentially life-shortening or life-threatening consequence.
If the benefits themselves are exaggerated or even chimerical – if masks are more like a “talisman” (in the words of a prominent WHO physician quoted in Part I) than a plausible means to control the spread of infection – then the case for masking weakens further. Once it is clearly seen that masks are harmful – and not just in one or two ways, but in a dozen or more – then the “where’s the harm” and “even one life” arguments collapse and the failure to clearly establish the net benefits of masking becomes unconscionable. If masks are bad for you and don’t even protect you, they shouldn’t be worn. At that point, the message becomes clear: it is time to unmask.
It is time to unmask because the facemask mandate for the general public – which was always an egregious assault on civil liberties – is unsupported by either the highest-quality science or a rational evaluation of the relevant risks (not only the risk of transmitting Covid-19). It is time to unmask because masks have not been shown to be effective at preventing people from catching Covid-19. It is time to unmask because the negative health consequences of wearing masks are so detrimental that continuing to wear them (especially at a time when the risks of Covid-19 have been driven down to immaterial) is not merely irrational but borders on self-destruction.

For children in particular, mask wearing is nothing less than a grave health hazard – a conclusion that also “follows the science”. Yet the dominance of the “narrative” during Covid-19 has highlighted the vulnerability of the scientific community to concurrent political ideology and the propensity towards false prediction.
As for the scientific community’s role, the public and policy-makers should insist on having more Covid-19-related experimental studies – prominently to include RCTs – and cost-benefit analyses around the imposed public health measures. The public deserves to know in tangible terms the price attached to employing either approach. This reflects the basis of any decision-making, at both personal and societal levels.
It is obvious that scientists are faced with some serious challenges with regard to this pandemic; there’s no doubt that the infamous and ever-growing cancel culture has penetrated their métier and is actively carrying out its destructive work. Arguably science has always been vulnerable to political influence, or even manipulation by the ruling class, yet the pandemic crisis has either greatly exacerbated this trend or illuminated it more starkly – perhaps both.
Had scientists remained professionally impartial, while the political and public health establishment were actually true to their unapologetic motto to “just follow science,” it is likely that we would not have seen ubiquitous mask mandates. Or, if we had, that they would have been discarded in the face of countervailing evidence – like the studies and reviews cited above.
The failure of science and government regulators to develop any kind of standard for an effective, practical and low-cost mask type to be universally used during this pandemic further undermines the integrity of the imposed mask rules. The notion that Covid-19 transmission can be halted by – to take just one of many real-world examples – pulling a mucous-laden bandana over one’s face while standing in a ski area lift lineup seems ludicrous. Yet that practice last winter satisfied government and corporate rules in B.C., Alberta and much of the U.S.
Canada is not the only country that remains largely oblivious to the truth about masks; governments around the world are maintaining the same shroud of ignorance. Yet some countries have proved more willing than others to unmask and return to normal. The United States is the most prominent example. And while the increasing vaccination rates are frequently regarded as the main or even sole ground for relaxing or discarding mask wearing, it should not be so. Because, at bottom, masks just do not work.
Maria (Masha) V. Krylova is a Social Psychologist and writer based in Calgary, Alberta who has a particular interest in the role of psychological factors affecting the socio-political climate in Russia and Western countries.
GP with the courage to say No to vaccines
By Sally Beck | The Conservative Woman | June 28, 2021
A GP who resigned his ‘job for life’ as a partner with a Hampshire practice because of his doubts about Covid-19 vaccines has been suspended by NHS England for questioning coronavirus protocol.
Dr Sam White received a letter on Friday informing him that he was suspended with immediate effect, which stops him practising as a doctor within the NHS. On Saturday he was telephoned by a senior clinical adviser to NHS England, who condescendingly called him ‘poppet’.
In a soothing manner, she told him she was concerned for his welfare. ‘I’m worried about whether you’re well,’ she said, the undercurrent of the conversation being the suggestion that Dr White is suffering mental health issues.
In fact, Dr White has never felt saner even though he has pressed the nuclear button on his professional life. The two main reasons for detonation involved the Covid-19 vaccine roll out, an initiative that he fundamentally disagrees with because vaccines are not needed if there’s an effective treatment; and the mandatory wearing of masks, a theme introduced by psychologists not scientists, which Stanford University research shows is nothing more than theatre.
He said: ‘It’s hard to go against the grain like this, but when I found out they were going to start testing the vaccine on children, I couldn’t sleep. I knew it didn’t matter what the results of the trials were, negative or positive, they would begin injecting children regardless. A healthy child is more likely to be struck by lightning than die of Covid. They don’t need an experimental vaccine that has no proven benefit.
‘The risks from the vaccine are completely unknown because it’s barely been tested. But reactions are beginning to come to light. Adolescent boys seem to be developing myocarditis – heart inflammation – which can permanently damage the heart. The risks could be potentially devastating compared with them contracting Covid and surviving it.
‘I began waking up in a cold sweat. I was so anxious that I ended up calling in sick. That was back in March, and I never went back.’ He now fears this anxiety will be used to question his mental health.
The second dig in his ribs came when someone in the Twitter community posted in the wake of apocalyptic stories about the vaccine-injured: ‘What are all the doctors doing about this crime against humanity?’ It struck a chord, and it was then he knew he had to reveal how he’d taken a stand.
Dr White explained in a heartfelt resignation video that went viral after he posted it to Twitter on Friday June 4. ‘I had to go because of all the lies. They’re so vast it’s been impossible to stomach.
‘I became a doctor because I wanted to help people and make a difference.
‘Since the pandemic was announced, I’ve had my hands tied behind my back. There are safe treatments that I have researched and there is good science behind them, proven treatments, but we’re not allowed to use them.’
During our interview, Dr White explained that the ‘vaccine cure’ was worse than the ‘disease’. He said: ‘After the vaccine programme began, I started to see more people with vaccine damage than with Covid.
‘I effectively left my practice three months after the rollout but before I left, I saw eight vaccine injured patients, they felt feverish and short of breath post-vaccination, and one was hospitalised in his 50s. He’d had Covid-19 so he didn’t need the vaccine, but no one had checked his medical notes. When I got his discharge letter back from A&E, it just said Covid-19, not that he’d had a reaction to the injection.’
The lack of information available about the vaccine worried him, as did his contract to be complicit in potentially causing harm. He said: ‘A lot of doctors don’t know that this is not a vaccine, but genetic manipulation.
‘When you sign up to become a GP you sign a contract with the NHS who tell you what to do. Essentially you can’t refuse to do what you’re told. I was hoping in December that the General Practitioners’ Committee (GPC), our governing body, would say, “Hang on, we haven’t got enough data here, we need to hold off doing this”, but that didn’t happen.’
Now, he wonders how many of his elderly Covid patients would not have died if he’d been allowed to prescribe ivermectin, the medication recommended by Dr Tess Lawrie from British Ivermectin Recommendation Development (BIRD), a group of health researchers who say research shows it can cure and prevent Covid.
On Wednesday afternoon last week, Dr White had a call from a woman claiming to be a doctor from NHS England who expressed concerns that he’d discussed drugs such as the malaria prevention medicine hydroxychloroquine which research says could increase Covid survival rates by 200 per cent. She also did not want him to mention the steroid inhaler budesonide, talked about by a doctor in the US.
A clean getaway was too much to hope for, especially as he’d made his feelings known so publicly. Since that video flew around the world it’s had close to a million views, and Dr White has paid dearly for his outspoken departure. His bank account has been hacked and a five-figure sum removed. He has no idea if it’s connected but according to the International Women’s Media Foundation (IWMF) it’s a ‘thing’: thieving people’s identities and stealing their money is a tactic used to intimidate the outspoken.
It has affected his personal relationships and is a divisive subject within his family, who all have their roots in healthcare.
As painful as the response from his family has been, the outpouring of support from strangers on social media has been phenomenal. He said: ‘Before I posted the video, I had 100 followers on Instagram which increased to 37.5k after my video. I had 11 followers on Twitter and now I have over 8k, but Instagram are taking down my posts. I put up a list of vitamins I take for boosting immunity. I didn’t even mention Covid, and they labelled it: “Covid-19 misinformation. False treatments. WARNING”.’
Dr White, 41, is not a naïve rookie. He qualified in 2004, worked as a GP for 11 years and was invited to become a partner in the Hampshire practice where he’d worked as a popular locum in February 2020. He’s worked in A&E, and he helped to run a palliative care unit for a while.
Initially, he turned down their offer of a partnership because he said: ‘Being a GP is a mill, you’re seeing 40 patients a day, a third of your day is spent doing paperwork, a lot of it is meaningless. It’s what we call tick-box medicine. What I felt was that I was, if I can be frank with you, a bitch for Big Pharma.
‘If you take someone coming in with newly diagnosed type 2 diabetes, the agenda is to get them on a drug for the diabetes, get them on a different drug for their blood pressure, it’s not about reversing type 2 diabetes which you can do by changing their diet.’
Since he walked away from general practice, he feels lighter and is excited for the future. Dr White is now focusing on functional medicine, from which he is not suspended – a biology-based approach to healthcare that identifies and addresses the root cause of disease, for example poor diet and lifestyle.
He wants to cure people, not just control their symptoms with drugs with side effects that can potentially harm.
The vaccines, and the Armageddon he, and many other doctors and scientists, fear they could cause, are never far from his thoughts though. He has this advice for people undecided about whether to have a Covid vaccination or not: ‘Please don’t have this because you think they will let you go on holiday. Your ability to travel should not be impeded for a virus with a survival rate of 99.7 per cent. It makes no sense.’
Fauci and the Biden Admin are purposely deceiving us about the ‘Delta variant’ threat
By Jordan Schachtel | June 24, 2021
Prominent actors within the U.S. government have been lying to the American people about COVID-19 for 18 months and counting, and their latest behavior shows that the individuals in charge of U.S. Government Science have no intention of stopping the charade anytime soon. Over time, their lies have evolved to become so common and so reckless to the point that someone with even the most rudimentary understanding of viruses can instantly debunk the lies. The latest “Delta variant” paranoia peddling has put their incompetence, deliberate spreading of falsehoods, and perpetual gaslighting of their own citizens on display for the world to see.
The Biden Administration, through lifelong government bureaucrat Anthony Fauci, is making a hard push to fear monger about the supposed dangers posed by the “Delta variant” of the virus that causes COVID-19.
A video posted from the White House account made the rounds Thursday morning, stating:
“Here’s the deal: The Delta variant is more contagious, it’s deadlier, and it’s spreading quickly around the world – leaving young, unvaccinated people more vulnerable than ever. Please, get vaccinated if you haven’t already. Let’s head off this strain before it’s too late.”
Fauci has been on a media tear this week hyping up the threat of the Delta variant.
Sometimes it’s easy to reflexively dismiss these warnings of doom and gloom as total nonsense, especially when they are in fact total, bald-faced nonsense.
(Check out this video from Ivor Cummins breaking down how the Delta variant, previously referred to as the Indian variant, is nothing more than a “political scariant.”)
First of all, it goes against all understanding of 101 concepts for a virus to mutate to become both more contagious and more deadly. If a virus becomes more contagious, it spreads faster but does not kill off its host. If a virus becomes more deadly, it doesn’t spread as fast because it has taken out its host. In fact, the best evidence we have on the Delta variant shows that it is probably less deadly than previous mutations. And it’s always good to remember that we’re talking about a disease that sports an original recovery rate well over 99%.
Second, the idea that human intervention can “head off” a strain is an idea straight out of the “COVID Zero” (the idea that you can eliminate the virus from this earth) pseudoscience playbook. Fauci and the gang are by no means brilliant minds, but they are well aware that they cannot eliminate a virus from circulation. This makes it obvious that there are several ulterior motives in play, none of which have anything to do with our health.
Outside of academic models (we all know how well those held up in the past with lockdowns, masks, etc), there is no hard evidence anywhere in the world that this Delta variant is any more or less dangerous than any other mutation of the virus. In fact, the statistics on this variant shows no particular reason for alarm. Yet the government is — let me know if this sounds familiar — baselessly making stuff up about a virus based on absolutely zero real world data.
Since the beginning of COVID Mania, the government has never been on the side of science, evidence, and data. From the infamous Gates-funded panic models and fraudulent Chinese government “science” that encouraged the world to lock down indefinitely, to the absurd mannequin “studies” about the efficacy of masks, this latest Delta variant scaremongering has once again put their lies on display for the world to see. Given the almost two years of immunity building related to the virus, the threat posed by COVID-19 at this point in time is virtually nonexistent. There never was a legitimate reason for a single restriction on our liberties, and today, the “delta variant” argument to curb our rights and transform our society is more baseless than ever before.
Re-Evaluating Mask Mandates – Part I: Science Gives Way to the “Talisman”
By Masha Krylova | C2C Journal | June 13, 2021
The health of my patient will be my first consideration; I will not use my medical knowledge to violate human rights and civil liberties, even under threat.
—World Medical Association: Declaration of Geneva, 2006
Where all men think alike, no one thinks very much.
—Walter Lippmann, 1937
We all remember when it was natural to strike up a conversation with a stranger on a street, in a mall or in a café. Sharing a smile would often start the enjoyable process from which mutual trust and understanding could flow. Seeing other people’s open faces and hearing them laugh felt contagious and energizing. A spontaneous encounter had a chance to turn into something long-lasting and meaningful.
Those times were pre-Covid-19; the pandemic has brought great upheaval to social norms. Rarely do many of us talk to strangers in public places. Communication is largely transactional – aiming a few words at a clerk behind a plexiglass shield and straining to hear the muffled reply. Laughter has become a rarity. And even if others smile at us, we hardly can tell – or know when to smile back. All we see are faces largely hidden behind masks and staring, shifting or downcast eyes.
Happily, that is beginning to change. Mask mandates are dropping left and right across the United States. As of June 8, 35 U.S. states had removed these requirements in indoor or outdoor public settings. A few U.S. governors have even prohibited local governments and school boards from countermanding such state policy. At the same time, the exposure of Anthony Fauci’s serial contradictions has loosened his grip on the American psyche – weakening the entire pro-mask side. Gathering limits are disappearing as well; the recent Indy 500 was packed with mostly unmasked auto race enthusiasts and fans are once again jamming stadiums for pro sports.
In Canada, a number of provinces are also reopening – led in speed by Alberta, where all provincial restrictions will be dropped within two weeks of 70 percent of the population receiving one dose of vaccine. That pointedly includes the mask mandate. If this occurs, and much of the rest of Canada follows suit, the summer of 2021 could end up being, if not exactly the “best summer ever” in the previous hopeful words of Alberta Premier Jason Kenney, then at least one to rekindle normal life and, perhaps, look back upon as the time when the Covid-19 pandemic was put in its grave.
These lovely sentiments – surely shared by millions of Canadians – could be dashed, however. Reopening is threatened by a number of political leaders, urged on by an entrenched medical/scientific faction, who appear almost terrified of normality’s return and whose default position is to lock down, prohibit and prevent. Ontario, for example, only re-authorized camping last Friday and recently extended its state of emergency until December. Premier Doug Ford, wrote Matthew Lau in the Financial Post, “has turned the presumption of liberty completely on its head. In Ontario there is now a presumption of government control.”
Even in Alberta, big-city mayors are suggesting they might defy the province’s mask mandate lifting. They are egged on by vocal medical experts who have formally demanded that masks remain in place until 70 percent of the population has had two vaccine doses. This may amount to something like “forever,” since vaccination curves in other countries to date have gone nearly flat at approximately 55-65 percent with even one dose. Alberta, it was reported last week, is having trouble achieving the last several percentage points leading to 70 percent with one dose.
In short, if some have their way, it could be masks for a long time. Should further new Covid-19 variants or new infectious diseases come along in the meantime, it might be masks forever.
If Canada is to enter a major political struggle over the possibility of long-term masking, then surely it is worth revisiting the basic question of whether masks actually work. And, even if masks are shown to be useful in slowing the transmission of Covid-19, the public has a right to understand whether habitual mask-wearing carries negative health effects, in order to weigh the costs against the benefits of such an intrusive long-term policy.
With those questions in mind, C2C Journal brings you this exclusive, carefully researched two-part analysis. In Part I, we review the recent history of mask requirements and discuss the initial evidence around widespread mask-wearing.
When it Began: The WHO Mask Guidance
On April 6, 2020, the World Health Organization (WHO) issued Interim Guidance on the use of facemasks against Covid-19. The organization advised only health professionals to wear medical masks or respirators and to avoid non-medical masks because the effectiveness of the latter, it stated, was not established.
Significantly for the wider population – or seemingly so – it also cautioned that “the wide use of masks by healthy people in the community setting is not supported by current evidence and carries uncertainties and critical risks.” Among these were potential self-contamination by frequent touching and re-wearing of single-use masks, breathing difficulties and a “false sense of security, leading to potentially less adherence to other preventive measures such as physical distancing and hand hygiene.”
The WHO’s April guidance was consistent with the statements of numerous public health officials worldwide. It was, for example, preceded by the official statement by Canada’s Chief Public Health Officer Theresa Tam who suggested that “putting a mask on an asymptomatic person is not beneficial, obviously if you’re not infected.”
The official advice should have been unsurprising, even though by this time millions of individuals were rushing to scour store shelves for any and all mask varieties, while others rigged up bizarre contraptions out of old diving helmets or even fish bowls, and a few were seen shuffling down aisles in full hazmat suits (real or home-fashioned). But the official advice was consistent with decades of established international guidance for the management of disease outbreaks, in which masks are recommended for those who are sick – to protect the healthy – but not ubiquitously (see, for example, the WHO’s guide of 2018, or Public Health England Principles of 2015, or the Association of Faculties of Medicine of Canada Primer on Population Health).
Physician Margaret Harris, a member of the WHO’s coronavirus response team, was quoted saying that “the mask is almost like a talisman,” making “people feel more secure and protected.” An official scientist appeared to say that mask-wearing was no longer about science, but about sorcery and emotion.
Regardless of how sound these recommendations are, they soon were thrown overboard as fears spread of “asymptomatic spreaders,” many doctors and scientists started asserting benefits to the public wearing almost any sort of mask, and governments and international organizations sought to reassure jittery populations they were taking “crucial steps” to “save lives” – which now included requiring people to wear masks in a variety of settings.
The WHO subsequently updated its mask guidance, with the most recent document issued on December 1, 2020. Citing a number of studies, this one advised the general public to wear either medical or three-layer fabric facemasks in indoor and outdoor settings where ventilation is inadequate and physical distancing is less than 1 metre. It asserted several pandemic control benefits to such practice, including reduced spread of viral respiratory droplets and reduced stigmatization towards mask-wearers (a transient phenomenon early in the pandemic). Further stated benefits included making people feel that “they can play a role in contributing to stopping spread of the virus,” encouraging proper hygiene and, finally, reducing transmission of other respiratory illnesses such as tuberculosis and influenza.

Caution to the wind: The WHO’s explicit list of negative effects from ubiquitous mask wearing was ignored by all.
The WHO’s list of disadvantages, however, had grown significantly and now also included potential headaches, facial skin problems, difficulties communicating, discomfort, improper mask disposal, poor compliance among young children and difficulties for people with developmental challenges, with chronic respiratory problems or those living in hot and humid conditions. Nor should this have been surprising either, for as we shall see it too was consistent with longstanding scientific understanding. None of these mask-associated risks, however, received a thorough airing in news and social media.
On the contrary, many governments imposed even more stringent and often duplicative requirements, like requiring masks and distancing even outdoors where ventilation was good, or masks and plexiglass barriers, or masks, face shields and distancing. Masks, meanwhile, took on novel roles as political statements or articles of faith employed by political leaders, organizations, public health figures and much of the population. People were even seen swimming with paper masks. Physician Margaret Harris, a member of the WHO’s coronavirus response team, was quoted in an NPR column saying that “the mask is almost like a talisman,” making “people feel more secure and protected.” An official scientist appeared to say that mask-wearing was no longer about science, but about sorcery and emotion.
Meanwhile, no one in the public sphere seemed willing to peruse the WHO’s December 2020 guideline in detail. Had they done so, they might have noticed two statements eerie in their juxtaposition. First, the WHO clearly recognized the serious limitations of the studies it cited about the efficacy of masking to reduce viral spread: “[The] studies differed in setting, data sources and statistical methods and have important limitations to consider notably the lack of information about actual exposure risk among individuals, adherence to mask wearing and the enforcement of other preventive measures.” Second, the WHO nonetheless insisted on universal mask usage: “Despite the limited evidence of protective efficacy of mask wearing in community settings, in addition to all other recommended preventive measures, the [guidelines development group] advised mask wearing.”
The WHO’s categorical recommendation, then, rested on admittedly shaky foundations. Over half a year has passed. One would expect there to be an ever-growing number of studies dedicated to Covid-19 and related issues, including masking. And so there has been.
Current Evidence on Mask Effectiveness
More than 300 scientific papers have been published specifically on masking during the pandemic. The best way to evaluate such a vast body of research without losing the forest for the trees is to focus primarily on literature reviews and systematic reviews (special types of scientific analysis that summarize up-to-date knowledge on a particular issue). This narrows the search to some 20 review studies (as of May 2021). Six of these provide support for universal mask wearing using epidemiological data (1, 2, 3, 4, 5 and 6). Six others offer mechanical evidence by describing material and filtration properties of masks. Two reviews are inconclusive (this and this), while the rest are less relevant (comparing medical masks to N95 masks in a healthcare setting, for example, this).
The most recent and comprehensive review is by researchers from the University of Hawaii at Manoa, Honolulu, published in April 2021. This interdisciplinary report outlines the “state-of-the-art understanding of mask usage against Covid-19” by covering the most important epidemiological data, face mask filtration mechanisms and mask recontamination and reuse.
In their epidemiological evidence the researchers cite eight publications that report a positive association between mask wearing and a reduced risk of Covid-19 infection. These studies were conducted in China, Thailand, the U.S., Germany and Canada. The Canadian evidence notably encompassed both provincial data from Ontario and nationwide data analyzing the effect of mask wearing on Covid-19 case numbers over the course of eight months. “In the first few weeks after their introduction, mask mandates are associated with an average reduction of 25 to 31% in the weekly number of newly diagnosed COVID-19 cases in Ontario,” the study concluded. It also speculated that had indoor masking been mandated by early July, there would have been 25-45 percent fewer weekly cases across the country than actually occurred.
The other studies were different in methodology and reported varying strengths of the association between mask wearing and risk reduction, ranging from 15 percent to 80 percent. The University of Hawaii team’s conclusion appears decisive: “All available epidemiologic evidence suggests that community-wide mask-wearing results in reduced rates of COVID-19 infections.”
Not All Science Is Created Equal: RCTs vs. Observational Studies
The take-home message from the above research appears unequivocal: masks work. The factual conclusion provides scientific support for the political decision to impose a public mask mandate. But for one fact: nearly all Covid-19-related epidemiological studies are either observational analyses (such as this or this), simulation studies (such as this), or a combination thereof (like the Canadian study described above). Almost none involved randomized controlled trials (RCTs).
Why does that matter?
The distinction between study types is imperative for it speaks of the quality and not simply the quantity of the available scientific evidence. Setting aside simulation studies that are hypothetical and therefore of lesser empirical value, it is important to understand the differences between RCTs and observational studies (case-control and cohort studies are two types).
The RCT facilitates an objective comparison between various types of intervention, or between treatment and non-treatment. The RCT achieves this by using the process of randomization, assigning participants randomly either to experimental or control groups. The goal of such studies is to prevent manipulation of the results and to draw, as accurately as possible, a causal relationship between an intervention, or a behaviour, and the subsequent outcome.
The link of causality cannot be achieved in observational research, which involves analyzing data gathered in natural conditions without researchers’ intervention. Although observational studies are illuminating and useful in various scenarios, they are inevitably biased. The bias occurs because such studies do not allow for direct control over confounding variables that may have an impact on the study results. For example, for one to say that “A causes B” requires ensuring that the effects of all other important variables on B have been removed or cancelled through randomization.

Through the process of randomization, RCTs are able to establish a causal link between a treatment or behaviour and an outcome. Observational studies are limited to showing correlation, or association – and thereby can be misunderstood.
This is impossible in observational studies, always leaving a chance that the observed outcome B might have been caused by a variable, or variables, other than A. Thus, observational studies, even those employing advanced statistical analyses, cannot reach conclusions stronger than establishing temporal associations between one thing and another. But association, or correlation, does not demonstrate causation. (The Canadian study cited above, for example, notes that mask mandates are “associated” with a reduction in the rate of Covid-19 infection; it does not assert a causal relationship.)
The Odd Reluctance to Conduct RCTs in Regard to Public Health Matters
Which brings us back to the 300-odd mask-related studies conducted in the Covid-19 era. Many, indeed, found associations or correlations between widespread adoption of masks and a reduction in Covid-19 case counts, or a slowing of acceleration in case counts. In an observational study like this one, however, it is reasonable to ask whether the detected reduction in Covid-19 transmission was caused by mask wearing. Could it not have been due to other preventative health measures adopted around the same time, such as improved hand hygiene, limited social interaction, physical distancing in public settings or even individuals’ general health regimen? And what about the impact of other variables such as age or race on the risk of catching the virus? Finally, could there be other, as-yet overlooked confounders that affect virus spread? Randomization is required to negate the effects of the confounding variables, known or unknown.

Correlation does not show causation: Masks may be associated with a reduced rate of Covid-19 infection, as frequently documented in observational studies, but a host of other factors could also be at work.
Because of these known limitations of observational studies, the RCT is recognized as the gold standard of clinical research practice, a rigorous tool of cause-and-effect analysis. One of the world’s leading experts in medical standards and statistics, Dr. Janus Christian Jakobsen, who is frequently cited for her systematic reviews of meta analyses, authoritatively stated:
“Clinical experience or observational studies should never be used as the sole basis for assessment of intervention effects – randomized clinical trials are always needed…Observational studies should primarily be used for quality control after treatments are included in clinical practice.” (Emphasis added.)
It is thus clear that in health-related contexts, researchers should rely on RCTs whenever possible and use observational studies to gather supplementary evidence.
The most common arguments against RCTs are that they are expensive, time-consuming and impractical for population-wide interventions. There are also understandable ethical objections against exposing healthy control groups to contagious and potentially fatal infections, in this instance attempting to determine whether unmasked people are more likely to catch Covid-19. In fact, some have asserted, in reference to the WHO, that “we should not generally expect to be able to find controlled trials” in the context of population health measures.
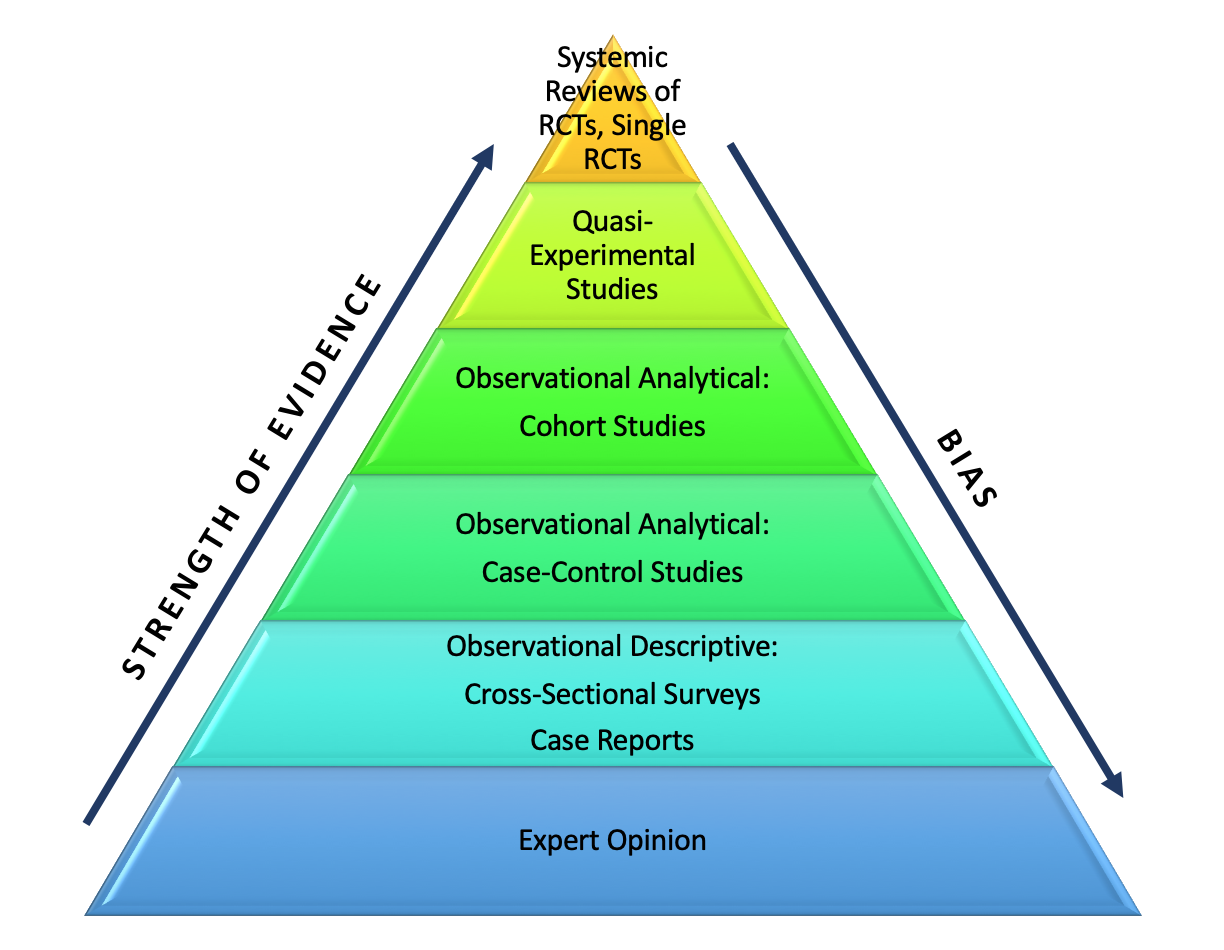
Maximum strength of evidence, minimum degree of bias: Not for nothing is the randomized controlled trial considered the “gold standard” of clinical practice. (Graphic by Masha Krylova/ C2C Journal)
Unethical and impractical? It is claimed that RCTs should not be used to study the effects of health measures on Covid-19 infection – yet numerous RCTs have examined influenza on a community-wide scale.
Still, it has been over a year since mask mandates were first imposed in many countries. Given the prodigious effort poured into seemingly anything to do with Covid-19, this should be ample time for researchers to gather resources and test mask effectiveness in a controlled experimental setting. Nor was it unheard-of prior to the pandemic to perform RCTs in healthcare and wider-population settings to evaluate the effect of mask wearing on the transmission of respiratory illnesses such as influenza (see this review of 2010) and influenza-like illness (also see this scoping review of 2020). These studies clearly overcame objections related to practicality and ethics. Why should Covid-19 be different?
The cited reviews present intriguing details: with respect to influenza, five out of six RCTs conducted in healthcare settings found no significant difference between mask-wearing and control groups. Even more important from the standpoint of the current pandemic, none of four RCTs performed in broader community settings found a significant difference between masking and remaining bare-faced. For influenza-like illnesses, the pooled data from five other RCTs as well showed a non-significant protective effect of mask wearing for avoiding either primary or secondary infection. These results appear substantial and would seem of some relevance to the current pandemic. But there is more.
End of Part I.
Coming next in Part II: Should you care whether masks are more like a sieve or a filter? Is there really no RCT-generated “gold standard” evidence regarding whether wearing masks reduces the spread of Covid-19? And is there any basis to concerns of ill effects from wearing masks?
Maria (Masha) V. Krylova is a Social Psychologist and writer based in Calgary, Alberta who has a particular interest in the role of psychological factors affecting the socio-political climate in Russia and Western countries.
Doctor fired from University of Saskatchewan after posting online statement asking for “informed consent” on vaccines

By Christina Maas | Reclaim the Net | June 25, 2021
Dr. Francis Christian was fired from his position at the University of Saskatchewan and is being investigated by the College of Physicians and Surgeons of Saskatchewan for an online statement calling for informed consent when it comes to vaccines.
Dr. Christian has been a surgeon for over 20 years. In 2018, he was appointed to the position of Director of Surgical Humanities Program and Director of Quality and Patient Safety at the University of Saskatchewan. He also co-founded the Surgical Humanities Program and is an editor of the Journal of The Surgical Humanities.
On June 23, Dr. Christian was suspended from all teaching responsibilities, and will no longer be an employee of the University of Saskatchewan from September 2021. The College of Physicians and Surgeons of Saskatchewan is also investigating him after receiving a complaint about a statement he released last week.
In a statement to over 200 doctors, released on June 17, Dr. Christian recommended informed consent when administering COVID-19 vaccines to children. The statement made it clear that he is pro-vaccine, does not represent any group, the University of Saskatchewan, or the Saskatchewan Health Authority.
“I speak to you directly as a physician, a surgeon, and a fellow human being,” Dr. Christian said in the statement before going on to recommend the principle of informed consent so that the patient is “fully aware of the risks of the medical intervention, the benefits of the intervention, and if any alternatives exist to the intervention.”
“This should apply particularly to a new vaccine that has never before been tried in humans… before the vaccine is rolled out to children, both children and parents must know the risks of m-RNA vaccines,” he added.
The surgeon noted that he was yet to hear of “a single vaccinated child or parent who has been adequately informed” about the risks of COVID vaccines in children.
His statement argued that m-RNA vaccines are experimental. Dr. Christian further argues that the vaccines do not qualify for “emergency use authorization” in kids because “Covid-19 does not pose a threat to our kids. The risk of them dying of Covid is less than 0.003% – this is even less than the risk of them dying of the flu. There is no emergency in children.”
Dr. Christian also noted the vaccines have caused “serious medical problems for kids” around the globe, such as “a real and significantly increased risk” of heart inflammation and myocarditis.
The College of Physicians and Surgeons sent him a letter stating that it has “received information that you are engaging in activities designed to discourage and prevent children and adolescents from receiving Covid-19 vaccination contrary to the recommendations and pandemic-response efforts of Saskatchewan and Canadian public health authorities.”
The Litigation Director of The Justice Center for Constitutional Freedoms, the organization representing Dr. Chrisitian in the complaint made against him, expressed his concerns over medical professionals getting censored and punished for expressing views contradicting the government’s narrative.
“We are seeing a clear pattern of highly competent and skilled medical doctors in very esteemed positions being taken down and censored or even fired, for practicing proper science and medicine,” said Cameron.
“Censoring and punishing scientists and doctors for freely voicing their concerns is arrogant, oppressive and profoundly unscientific,” he added.
“Both the western world and the idea of scientific inquiry itself is built to a large extent on the principles of freedom of thought and speech. Medicine and patient safety can only regress when dogma and an elitist orthodoxy, such as that imposed by the Saskatchewan College of Medicine, punishes doctors for voicing concerns,” Cameron concluded.
There is no Covid third wave in Africa
Alarmist reporting is getting basic facts wrong
By Toby Green | Unherd | June 24, 2021
The last few days have seen an avalanche of reports that a third wave of Covid-19 is underway in Africa. Seasoned coronavirus watchers will not be surprised that the alarm was raised in Geneva. WHO Central issued alarming press releases on June 7th and 17th, with the Regional Director for Africa, Dr Matshidiso Moeti, stating in the latter that “Africa is in the midst of a full-blown third wave”. So what’s happening?
Since the June 7th press release, there have been 1,651 new deaths reported from Covid-19 across the entire continent in 17 days, less than 100 per day. In a continent where 9 million people die annually (roughly 25,000 per day), reported Covid deaths in this “full-blown” third wave thus currently account for roughly 0.4% of daily mortality in Africa. Certainly, there are mortality increases from Covid reported in some countries such as Cape Verde and the Democratic Republic of Congo, but they are not anything like on the scale of what has happened elsewhere.
Moreover, the vast majority of these fatalities have occurred in temperate zones: South Africa, Morocco, Egypt, Algeria, Libya and Tunisia account for 105,000 of the 139,500 deaths reported from Covid-19 across the continent.
Many of the reports on this “third wave” point to the failure to count deaths accurately, and suggest that these figures mask the true problem. Reports from the BBC and the New York Times have pointed to a continent-wide lack of systemic mortality figures. But running at 0.4% of current mortality, and touching a small area of the continent as a whole, even if this was an underestimate by 1000%, Covid would still only be a minor concern to most Africans. In fact, a recent paper disputes these accusations of undercounting: the authors note that “while only 34.6% of countries [in Africa] have complete death registration data… all countries have a system in place, and there is no evidence that COVID-19 mortality data is less accurately reported in Africa than elsewhere”.
What certainly does go under-reported are cases. This is good news, as it indicates that much of the continent’s population has already developed antibodies to Covid-19 through mild infections. In a study from July to October 2020 of mineworkers tested in Ivory Coast, 25.1% had Covid antibodies; meanwhile, a February study in South Africa based on blood donors found antibody levels of 63% in Eastern Cape, 46% in Free State, and 52% in KwaZulu Natal, while a study from Cameroon just published found antibody levels of 32%. These figures far outstrip recorded cases, suggesting that many Africans already have protection from Covid.
However the WHO redefined herd immunity last year as only achievable through vaccination, so it may not want to publicise this. The Guardian last week added to the clamour, reporting on research that had not been peer-reviewed and which claimed that Covid infection did not provide immunity. Ironically, a series of studies published in Nature the week before had found that “the evidence thus far predicts that infection with SARS-CoV-2 induces long-term immunity in most individuals”.
The evidence from Africa is quite clear, in fact. Large sections of the population have now developed Covid antibodies, and death rates are low compared to other chronic illnesses. Herd immunity does not have to be achieved through vaccination, either in Africa or elsewhere. But none of these conclusions fit with the catastrophic decisions taken by global policy elites over the past year, so they won’t be coming to a television news channel near you any time soon.
Toby Green is the author of The Covid Consensus: The New Politics of Global Inequality (Hurst).
Why Hasn’t the Government Published a Cost-Benefit Analysis of Lockdown?
By Noah Carl • Lockdown Sceptics • June 24, 2021
When considering a policy as unprecedented and far-reaching as a nationwide lockdown, you’d assume the Government would carry out a cost-benefit analysis. After all, such analyses are routine in policy-making.
For example, the Treasury maintains a document called ‘The Green Book’, which gives detailed guidance on how to compute the costs and benefits of particular actions. It refers to concepts such as opportunity cost, discount factors and adjusting for inflation.
You might say there wasn’t much time to carry out a detailed cost-benefit analysis before the first lockdown last March. (Though the Government could have provided a few rough numbers for the public to scrutinise.) However, it’s now more than a year later, and there still hasn’t been any attempt to weigh the costs and benefits.
In a report for the Institute of Economic Affairs published last December, the economist Paul Ormerod argued that the Government’s refusal to crunch the numbers reflects a general overreliance on epidemiological expertise, at the expense of economic expertise.
As Russ Roberts, another economist, has observed, “Knowing a lot about the human body does not make you an expert in risk analysis, tradeoffs, or unintended consequences.” Note: this is not to imply that all or even most economists are opposed to lockdowns, but simply that key insights from that discipline have been overlooked during the course of the pandemic.
Several cost-benefit analyses of the UK lockdowns have been published by persons outside the Government, and each one has concluded that the costs almost certainly outweighed the benefits.
Since the NHS typically pays up to £30,000 to extend a patient’s life by one quality-adjusted life-year, a reasonable estimate of the benefits of lockdown can be obtained by multiplying the expected number of life-years saved by 30,000.
For example, if we assume (generously) that lockdowns saved 50,000 lives and prevented 500,000 people from getting long COVID, then the total benefits would be about £16.5 billion. This figure then has to be weighed against some measure of the costs (including effects on the economy, health, education and civil liberties). Given that the fall in GDP alone last year was over £220 billion, it seems very unlikely that lockdowns would pass a cost-benefit test.
The Government’s lack of interest in cost-benefit analysis was highlighted in a recent LinkedIn post by Daniel Fujiwara – an expert in policy evaluation. Fujiwara was apparently invited to “meet with senior Government officials to discuss the pros and cons of lockdown”. However, despite offering his advice and input pro-bono, he “never heard back from them”.
In the post, Fujiwara goes on to say, “Lockdowns should have stopped at the point where an additional day of #lockdown causes more damage to our society than it benefits us… My analysis of the impacts of lockdown last year suggests that we have gone well beyond this threshold.”
One can only assume that the Government’s failure to publish even basic estimates of the costs and benefits of lockdown is due to fear of what those estimates might show…
So Matt Hancock groped his assistant…. who cares?
By Catte Black | OffGuardian | June 25, 2021
Oh gosh, Matt Hancock is being outed as a sleazebag.
Who knew, right?
The Sun published pics purporting to be of him and his girlfriend kissing in an elevator and even the BBC thinks this is newsworthy.
So this is serious now. You can sign off on mass murder all you like, Matt, but when you start breaking social distancing rules by groping married ladies in elevators that’s a step too far.
His lies and hypocrisy are puke-inducing of course. Some people who actually thought the ruling elite really believed in their social distancing, triple masking, hand-sanitizing rules may well be deeply shocked. Many of the more clued in are cheering the humiliation fest. Fair enough I guess. It’s certainly gratifying to see some psychopathic creep suddenly shamed or called to account.
And it’s probably harmless. Isn’t it?

Or then again maybe not.
What actually are these periodic ‘outings’ we witness?
What does it actually mean when an establishment billionaire-owned media outlet somewhere on the permitted and phony spectrum of Left/Right ‘leaks’ some grainy footage, or a clumsily revealing email, that ends up shaming some erstwhile pillar of the prevailing narrative?
Is the system finally getting a conscience? Are things gonna be ok, now [insert hate figure here] is gone?
Of course not. No one seriously thinks that, do they?
The establishment is essentially amoral. A psychopathic hive mind entity without conscience or ethics. It doesn’t expose or reject one of its own unless it sees advantage to itself in doing so. When one of them is publicly humiliated and cast out it’s because he/she has failed in a power play, or been ousted in a palace coup, or is earmarked as a good sacrifice to appease the restless mob.
You see, to the 1%, the 99% are caged dogs. Our masters need to gauge the frustration and make sure it doesn’t spill over. Being thrown a ‘victim’ to rend every now and again is a nice way of venting tension while also giving us the impression the system self-regulates.
It keeps us distracted occupied and works off our aggression and represents NO THREAT to vested interests.
Even the supposed ‘victim’ will likely just ride out the storm or, if fired from his job, get a fat fee and ‘retire’ happily, only to be readmitted to the fold after a short exile.
Ok, maybe in very extreme cases, they’ll occasionally get ‘suicided’, though that’s usually reserved for genuine outsiders with an inconvenient conscience.
Whatever way it plays out, it’s a show. We are groundlings gawping at the painted actors on the stage. Our reaction is anticipated, manipulated, catered for and ultimately despised.
And anyhow we know, don’t we, that rending one of these Ringwraiths is missing the point. They are all replaceable servants of the Machine. Well paid, cosily ensconced – but ultimately expendable.
While we’re tearing the latest ‘victim’ with our teeth we’re forgetting all that and forgetting the real enemy.
And the real enemy is laughing at us.
I hope to see us become more sophisticated. Ignore these staged witch hunts, these hate sessions, these deliberately seeded water-cooler controversies about what Fauci knew or whether Hancock should go…yada y yada y pues yada.
If we are falling for this every time we need to get to know our enemy and its tricks a lot better, or we don’t have much chance of winning in this latest and most important struggle.
Johnson’s govt taken to court by theatre bosses to force release of Covid-19 trial data
RT | June 24, 2021
A group of concert and theatre bosses led by Andrew Lloyd Webber has launched legal action against the British government in a bid to force it to publish data from a trial assessing the safety of indoor events during the pandemic.
The concert managers and theatre producers are demanding that the government provide data from its Events Research Programme – a trial assessing the safety of indoor events – so that they can plan to finally reopen their institutions.
In a statement on Thursday, they said the government had “refused to publish the results from the first phase of the Events Research Programme, despite saying that it would do so on numerous occasions.”
The statement adds that, in addition to not publishing the data from the trial, the government has not provided any form of insurance scheme to safeguard the industry against any further delays following 15 months of closures due to Covid curbs.
The entertainment bosses claim that, according to the government, the trial has been a huge success, which in turn has contributed to the increasing frustration within the entertainment sector concerning the industry’s continuing dormant state.
Pilot events under the programme, which the industry participated in, included the BRIT Awards at the O2 Arena, an outdoor festival event in Liverpool for 5,000 people, a snooker tournament at the Crucible Theatre in Sheffield, and the Download festival for 10,000 people last weekend.
The reopening of the theatre industry in England has been pushed back from its anticipated late June date until July 19, following the spread of the more infectious Delta variant.
Speaking later on Thursday, a spokesman for Prime Minister Boris Johnson said the government had made £2 billion available via a major arts funding package. He added that the government understands “the necessary delay to step four is challenging for live events.”
The impresarios note in their statement that live entertainment and theatre generate £11.25 billion for the UK economy each year, supporting just under one million jobs.
Featured Video

AIDS Inc. by Gary Null (2007)
or go to
Aletho News Archives – Video-Images
From the Archives
Clash of Civilization, Iran Part II
By Jamal Kanj – Intifada-Palestine.com – January 14, 2011
Israel’s survival kit is: perpetuate conflict, insecurity to rationalize collective hate and finally playing victim.
Devoid of conflict, Israel implodes internally; without hate, Zionism loses its justification; and playing eternal victim to continue blackmailing the West. Absence of this holy trinity, Israel ceases to exist.
From its inception, the house of Zion has mastered exploiting adversarial powers to advance Israel’s cause. For instance, their influence over the Democratic Party in the US began with President Truman’s bid for 2nd term election in 1948.
Responding to strong opposition from Secretary of State General George Marshall and Department experts urging against recognition of Israel, President Truman replied: “I’m sorry gentlemen but I have to answer to hundreds of thousands [Jewish voters] who are anxious for the success of Zionism. I do not have hundreds of thousands of [voting] Arabs among my constituents”
Zionists influence over liberal American politics was matched with the doctrinal school of Conservative theoreticians aligning the Republican Party’s platform with Israel’s objectives. The Neoconservative Zionists, coined Zioncons, invented the “Clash of Civilization” concept to fight Israel’s wars. … continue
Blog Roll
 Aletho News
- 12 Things Your Psychiatrist Was Trained Not to Tell You
- From Unipolar Universalism to Multipolar Civilizational Distinctiveness
- RSF military group defects, joins Sudanese army: State media
- Ireland goalkeeper refuses to play ‘Israel’ as squad weighs boycott
- China pushes back against US on Cuba, Iran
- Ukrainian Soldiers, Potential Mercenaries: Have Gun, Will Travel!
- Burnham’s UN debut… A masterclass in British disinformation
- Iran flights continue despite US aviation sanctions
- Global Tipping Points Lead the World Into a State of Entropy
- The day-after at the White House: USA and Xi Jinping
- If Americans Knew
- Israel forces Gazans to live in constant peril – Daily Update
- Deconstructing Netanyahu’s pants-on-fire UN rant – Daily Update
- Trump betrayed voters with his campaign lies and prioritized a foreign country once he took office
- Netanyahu calls Israel’s war in Gaza ‘opposite of genocide’ in UN speech to near-empty hall
- Settler Kidnappings: Torture, Sexual Abuse and Terrorisation of Palestinian Abductees as Israel Deepens Annexation of West Bank
- Gaza winter nears as 162,000 tents become unusable, raising fears of humanitarian crisis
- Netanyahu says, “It’s the opposite of genocide”; UN says Gaza economy is world’s ‘most severe crisis on record’ – Daily Update
- Israel’s US-Backed Assault on Gaza Has Created the ‘World’s Most Severe Economic Crisis on Record’: UN
- ‘Protecting U.S. Citizens’… From Israel
- ‘This is where I live now, the back of a truck’: a day in the life of a grandmother in Gaza
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

