Now you see it, now you don’t
The popular narrative of plucky little Israel prevailing over hordes of bloodthirsty Arabs has captured the Western imagination even though it is manifestly false in almost every detail. But Israel’s greatest accomplishment might well be something else, it’s ability to make things disappear. It plausibly all began in June 1967 when Israel attacked the USS Liberty, a lightly armed but well identified US naval vessel cruising in international waters under a large American flag. Fighter bombers and torpedo boats sought to sink the ship, destroying the lifeboats so no one would escape. In the engagement, 34 American military personnel were killed and a further 171 wounded, before a heroic defense by the crew managed to save the vessel. President Lyndon Johnson, who said he would rather see the ship sink than embarrass his friend Israel, started a cover-up which has lasted to this day. There has been no legitimate court of inquiry into the attack and when the ship’s captain received a Medal of Honor for his heroism, it was awarded secretly in the Washington Navy Yard rather than openly at the White House. Israel and its legion of apologists certainly know how to make potential embarrassments disappear.
Last week on this site I posted an article that I thought would prove to be extremely interesting to those who have been expressing concern about foreign interference in our government. It included a link to a series of computer screen texts provided by a credible independent source demonstrating that an employee of the Israeli Consulate General was deeply involved in what appears to be extorting millions of dollars from the father of a congressman based on assisting that congressman through some legal difficulties. The scheme being concocted also included discussion of arrangements for a commando raid on Iran to free a prisoner. The information conveyed in the screenshots that were provided of the texts has not been disputed by anyone involved in the venture, but as I thought the accompanying article was timid in its willingness to draw any conclusions, I wrote my piece attempting to connect the dots.
The Congressman involved was, of course, Matt Gaetz of Florida, who is now facing the House Ethics Committee, surely an oxymoron if there ever was one, concerning his primarily sexual exploits. To my surprise, however, there has been hardly a word in the mainstream media about looking deeper into the possible Israeli connection. One would have thought the copied texts would be newsworthy due to the extortion angle but even more due to the fact that an armed attack on a nation with which the US is not at war was being funded and planned by a foreign government’s diplomatic mission in New York.
To be sure my article did very well both on Unz and even Facebook, though I had to cut and paste it in the latter site due to its blocking of Unz. I did a bit more checking and noted something that has been occurring for some time: the piece, like others relating to Israel, was not coming up on search engines like Google, which means it was not getting the exposure that it merited. I search daily by my name assuming that my pieces if replayed elsewhere will be displayed. In the past I would sometimes get scores of hits on a popular article, but during the past year hardly anything has been appearing. I have to assume that deliberate and widespread censorship of articles critical of Israel is taking place, which was no surprise as friends of Israel are not exactly rare in the social media. Facebook’s censorship board, for example, includes a former Israeli government minister.
It all comes down to the power of the Israeli/Jewish lobby and its ability to make things that it does not like go away. And sometimes it can make things happen that are manifestly not in the interest of the United States. Jonathan Pollard, the most damaging spy ever in the history of the United States, was recently allowed to return to Israel. In an interview on March 26th he said that any American Jews working for US intelligence agencies must do their duty and spy for Israel because one’s real loyalty is to the Jewish state and one’s co-religionists.
Clearly Pollard is not alone and it was shocking to learn that outgoing president Donald Trump pardoned the Israeli agent who recruited and presumably helped “run” Pollard when he was stealing US secrets. Aviem Sella received a full pardon from Trump as part of hundreds of last minute pardons, many of which had been arranged through two Orthodox Jewish agencies favored by presidential son-in-law Jared Kushner.
Sella was a retired Israeli air force officer doing graduate studies and living in the US when he enlisted Pollard to spy for Israel. He fled the country after Pollard was arrested in 1985 and was charged in absentia on three espionage counts but Israel refused to extradite him to the US to stand trial. A White House statement noted that Sella’s request for clemency received support from Israeli Prime Minister Benjamin Netanyahu, the Israeli ambassador in Washington Ron Dermer, the American ambassador to Israel David Friedman, and Miriam Adelson, the widow of the Republican Party’s top donor and Trump supporter Sheldon Adelson. Would anyone expect otherwise?
The Sella pardon should be seen for what it is. It was a gift to the corrupt Netanyahu, who was at the time facing another national election. It served no US national interest at all and in fact sent the message to those who might be tempted a la Pollard that spying for Israel might be regarded as consequence free, in fact desirable and the right thing to do. Of course, the special “exemption” when dealing with Israel should also be regarded as a tribute to Jewish power in the United States, which relies on the corruption of those in leadership positions, using financial inducements or even blackmail backed up by smears of anti-Semitism and holocaust denial for those who cannot be bought.
And the power to corrupt governments and media is not limited to the United States. Nearly everyone in public office or who relies on the media for an income understands one does not cross the Israel Lobby. In Britain, former Foreign Office Minister Sir Alan Duncan has written a memoir that accuses pro-Israel lobbyists of “the most disgusting interference” in British politics while also distorting the country’s foreign policy in the Middle East to favor the Jewish state.
Duncan also claimed that Conservative Friends of Israel (CFI) went “ballistic” and blocked him from becoming the Middle East minister at the Foreign Office. Duncan has long been a major target for the Israel lobby. In 2017, an Al Jazeera documentary exposed the maneuvering of pro-Israel groups working together with the Israeli Embassy in London to “take down” Duncan and also Labour Party leader Jeremy Corbyn.
Per Duncan, Conservative Friends of Israel, which openly promotes the interests of a foreign country, had successfully promoted a “Netanyahu-type view of Israeli politics into our foreign policy.” In one chapter Duncan criticized Conservative MPs’ fawning over Benjamin Netanyahu during his visit to Britain, a performance apparently similar to the time when Bibi addressed the US Congress and received 27 standing ovations.
The Duncan book appeared when another story broke about how a group called “UK Lawyers for Israel” acting on behalf of the Israeli government has been altering the material included in secondary school text books. Per a statement issued by Pearson, the largest publisher of school books in the UK, the company has suspended publication of two textbooks responding to “an eight-page report, by Middle East specialists Professors John Chalcraft and James Dickins, which found hundreds of changes to the textbooks overwhelmingly favoring an Israeli narrative and removing or replacing passages that support Palestinian narratives.”
Censorship of course materials as well as textbooks by Jewish groups to depict Israel in a certain way has certainly been going on in the United States for many years. And the corruption of our institutions to favor Israel and protect it from criticism is incessant. It will be interesting to see if the Gaetz story in all its aspects will ever be allowed to surface or whether the congressman will be offered some inducement to allow him to quietly resign. Somehow, it reminds one of the still unresolved Jeffrey Epstein case in which Epstein and his accomplice Ghislaine Maxwell obtained blackmail material relating to world leaders and celebrities having sex with young girls, somewhat similar to the claims regarding Gaetz.
Many including myself believe that Epstein was part of an Israeli intelligence operation, similar in scale to what was being run on 9/11, which sought to “influence” key figures on issues regarded as important by the Jewish state. Clearly, the game goes on with no one in Washington caring much about the damage being done. Do corrupted and intimidated Congressmen over their morning coffee ponder whether certain activities are “Good for Israel” and therefore not subject to further scrutiny? Judging from Epstein and Gaetz, one would have to believe that to be the case.
Philip M. Giraldi, Ph.D., is Executive Director of the Council for the National Interest, a 501(c)3 tax deductible educational foundation (Federal ID Number #52-1739023) that seeks a more interests-based U.S. foreign policy in the Middle East. Website is councilforthenationalinterest.org, address is P.O. Box 2157, Purcellville VA 20134 and its email is inform@cnionline.org
April 13, 2021
Posted by aletho |
Ethnic Cleansing, Racism, Zionism, Full Spectrum Dominance | Israel, UK, United States, Zionism |
Leave a comment
According to the UK Government, as of 27 March 2021, 126,515 people have died as a result of contracting Covid-19, and an additional 21,610 people have died with COVID-19 on their death certificates.
The government alleges, therefore, that a total of 148,125 people in the UK have died as a result of COVID-19. As we shall see, this claim is not credible.
Justifiable Policy?
Claims about mortality have been used by both the government and the mainstream media to justify the policy response.
The pace of change driven by that policy response has been astonishing. With Health Secretary Matt Hancock’s recent announcement of the creation of the UK Health Security Agency and its commitment to take “action to mitigate infectious diseases and other hazards to health before they materialise,” it is clear the government’s new (ab)normal is here to stay.
There is clearly an agenda; one entirely founded upon the idea that COVID-19 presents a significant threat. The primary evidence offered to substantiate this claim is suggested COVID-19 mortality.
Age Standardised Mortality
Just like nearly every other mortality cause, COVID-19 risks increase proportionately with age. Statistics for those of working age show a population mortality risk of between 0.0166% and 0.0046%, depending upon who you believe. The COVID-19 risk to the working age population is statistically insignificant. For the under 18’s it is statistically zero.
Mortality risk disproportionately impacts men. In 2018 the average age of death for men was approximately 80, and 83 for women in England and Wales.
The average age of COVID-19 death is just over 82. When we look at standard mortality distribution, there is no observable impact from COVID-19.
UK all cause mortality doesn’t suggest any need to panic either.
The ONS released data estimating a total of 607,173 deaths from all causes in England and Wales for 2020. Given demographic changes over time, the ONS use Age Standardised Mortality Rates (ASMR’s) to calculate relative death rates. The ASMR showed that 2020 was the worst year for mortality in the last decade.
ASMR’s were in continual decline throughout the post war period. That decline stopped abruptly in 2009 as the economic impact of the global financial crisis took its toll on public health. Thereafter it showed a marginal rise to 2019. Mortality in 2020 and 2021 should be seen in the context of a global financial crisis that dwarfs the credit crunch of 2008.
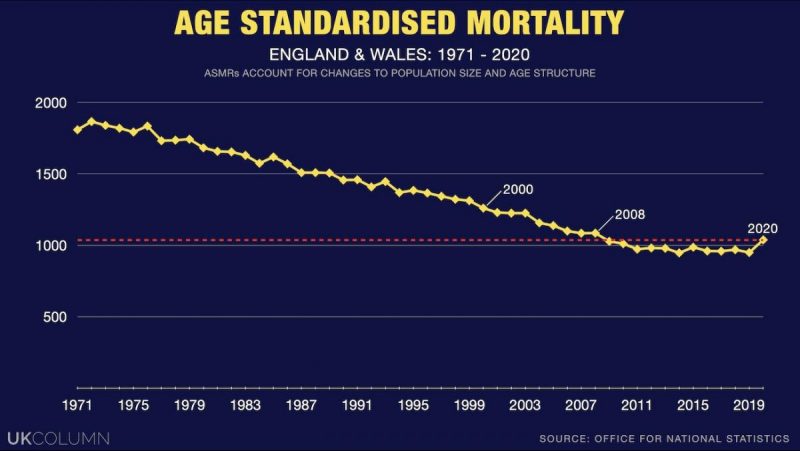
ASMR’s fluctuate annually and 2020 showed a significant increase above the 5 year average mortality rate. This was higher than most rises but by no means “unprecedented.” ASMR’s in England since 1938 show similar increases in 1947, 1949, 1951, 1958, 1963, 1970, 1972, 1976, 1985, 1993 and 2014.
Most of these spikes in ASMR’s were in the region of 35 to 45 points. For example, in 2014 the ASMR rose by 40.2, in 1993 by 38.4 and in 1985 by 46.3 points. It rose by 90.5 in 1947, by 83.5 in 1963, it went up by 104.9 in 1970 and in 1951 by 216.3. So the 2020 rise of 118.5 is by no means the worst.
The death toll in 1951 was attributed to the the influenza epidemic which struck some parts of the UK (most notably Liverpool) but left others relatively unscathed. To this day science has struggled to account for this.
2020 not only didn’t have the highest mortality rate in the post war period, it didn’t have the highest mortality rate in the 21st century either. 2020 ranked 9th, out of 20 consecutive years, for all cause mortality in England and Wales. It was the 11th least dangerous year in the last 50.
While there is no statistical evidence of an unprecedented global pandemic in England and Wales (nor in Scotland and Northern Ireland) this tells us little about how many deaths were genuinely attributable to COVID-19. Nor does it indicate at which point we should sacrifice our rights, freedoms, children’s educations and economy in the service of public health.
We certainly didn’t sacrifice them in 1947, 1963, 1970, nor even in 1951. Why was 2020 different?
PCR Does Not Mean COVID
For the purposes of this analysis, we will use the government’s higher claim of 148,000 deaths. The vast majority of these deaths were attributed based upon a positive RT-PCR test. The UK Coronavirus Act makes a clear distinction between the virus and the disease. It states:
Coronavirus means severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2); coronavirus disease means COVID-19 (the official designation of the disease which can be caused by coronavirus).
SARS-CoV-2 and COVID-19 are not the same thing. The detected presence of SARS-CoV-2 does not mean the person has or will develop COVID-19.
Therefore the attribution of mortality based solely upon a positive test result in no way proves the person died of COVID-19. The extent to which the disease caused or contributed towards a death is a precise medical assessment. The UK government created a death certification and registration process where this did not occur in an unknown number of cases. We need to know what that number is.
COVID-19 has a distinct presentation that requires careful diagnosis. The unique symptoms are severe hypoxemia (low blood oxygen levels), hypercapnia (elevated blood Co2 saturation) and unusually no corresponding loss of respiratory system compliance.
Measurement of gaseous exchange and fluid retention in the lungs appears normal, meanwhile the patient, in serious cases, struggles to breath. This is unlike other influenza like illnesses (ILI’s).
Yet the NHS describe a list of COVID-19 symptoms that could be attributable to any ILI. A high temperature, continuous cough and loss of taste and smell are associated with many. While this is public information, intended to guide our decision to seek medical advice or a test, the list of possible causes expands further given that the NHS state just one of these symptoms possibly indicates COVID-19.
Without precise symptomatic diagnosis, it is difficult to distinguish COVID-19 from a range of other respiratory illnesses. A study from the University of Toronto found:
The symptoms can vary, with some patients remaining asymptomatic, while others present with fever, cough, fatigue, and a host of other symptoms. The symptoms may be similar to patients with influenza or the common cold.
A Cochran Review meta analysis of available studies looked for a clear definition of COVID-19 symptoms. Published in June 2020, the reviewers noted:
The individual signs and symptoms included in this review appear to have very poor diagnostic properties … Based on currently available data, neither absence nor presence of signs or symptoms are accurate enough to rule in or rule out disease.
Even using advanced diagnostics, such as a computer tomography (CT) scan, won’t always provide a clear result. A study attempting to improve differential diagnosis using CT scans found:
Although typical and atypical CT image findings of COVID-19 are reported in current studies, the CT image features of COVID-19 overlap with those of viral pneumonia and other respiratory diseases. Hence, it is difficult to make an exclusive diagnosis.
Regardless of their SARS-CoV-2 test status, without a very accurate diagnosis of symptoms, suspected COVID-19 patients could be suffering from one among a range of ILI’s. Again, a positive test result does not mean the patient died from COVID-19, even if they had corresponding symptoms.
Notifications of Infectious Diseases
In England and Wales it is a legal requirement for all registered medical practitioners to notify their local health authority of any suspected cases of notifiable diseases. The list of Notifiable Infectious Diseases (NOIDS) includes COVID-19. This is not optional.
All diagnosing doctors must complete a NOIDS report upon making a diagnosis. Testing laboratories are also required to notify Public Health England (PHE) of positive tests for notifiable diseases.
According to the fact checker FullFact there were 18,152 COVID-19 notifications made by doctors in the whole of 2020.
Yet the government claim that there were 70,853 COVID-19 deaths, never mind cases, in England and Wales in the same year.
Fullfact offered an explanation for this apparent huge discrepancy:
People with Covid symptoms are advised to get a test, but not to visit their doctor, which may be part of the reason why doctors reported so few cases of the disease through NOIDS. Since Covid became widespread in the UK, and began to be monitored in other ways, it is also possible that doctors felt there was little need to continue notifying PHE about each case.
This is not credible. While it is true that people were told not to go to a doctor if they suspected they had COVID-19, a diagnosis by a doctor was still necessary at some point. Self diagnosis doesn’t usually afford access to hospital treatment. The suggestion by FullFact that doctors unilaterally decided not to bother with their statutory obligations is ridiculous.
What this massive difference between claimed cases, subsequent COVID-19 mortality and NOIDS indicates, is that Doctors were largely reliant upon laboratory testing to fulfil the duty to notify the authorities. This adds considerable weight to the notion that laboratory testing was the leading determinant in the overwhelming majority of COVID-19 diagnosis.
Until mid August 2020, a UK COVID-19 death was reported if the decedent had tested positive at any point during the preceding months. An individual may have have tested positive for SARS-CoV-2 in March, have died of cancer in August and subsequently have been recorded as a COVID-19 statistic.
The scientific rationale for this did not exist. Research conducted by scientists at Oxford University analysed the COVID-19 Hospitalisation in England Surveillance System (CHESS) and calculated the average time between infection (positive test) and mortality to be 26.8 days.
And so, in response to public and scientific pressure this approach changed to only recording a COVID-19 death within 28 days of a positive test. Still the UK government would not let go of its inflated number system, adding nothing but statistical confusion, they announced:
In England, a new weekly set of figures will also be published, showing the number of deaths that occur within 60 days of a positive test. Deaths that occur after 60 days will also be added to this figure if COVID-19 appears on the death certificate.
The August methodological change reduced claimed COVID-19 deaths by 5,377 in England alone. This didn’t make any difference to the number of people who had died from COVID-19, it just changed the number of people who had reportedly died from COVID-19.
This wasn’t the only notable change to the data gathering process. Just before the significant spring spike in mortality, on the 30th March 2020, the MSM reported that the government had instructed the ONS to change the way they record COVID-19 deaths. Hitherto the ONS only reported a COVID-19 death if it was recorded as the direct or underlying cause. This was changed to recording “mentions” of COVID-19. A spokesperson for the ONS said:
It will be based on mentions of Covid-19 on death certificates. It will include suspected cases of Covid-19 where someone has not been tested positive for Covid-19.
The reporting of COVID-19 comorbidity rates was“paused” in July and has yet to resume. The final published ONS analysis that directly reported the number of pre-exiting conditions for deaths “with” COVID-19 mentioned on the death certificate, was released for the period ending 30 June 2020.
From this we learned that 91.1% of alleged COVID deaths had at least 1 serious additional comorbidity. The mean number of comorbidities for a those under 70 was 2.1 and for the vast majority over 70 it was 2.3.
It is preposterous to claim that a decedent who had cancer, pneumonia and had just had surgery, but tested positive for SARS-CoV-2 four weeks earlier, could reasonably be categorised as a COVID-19 death. Yet that is precisely what happened, and continues to happen to this day.
Covid-19 Cures the Flu
COVID-19 also cured influenza and other respiratory disease, such as adenovirus. Early January is always a period of notable influenza outbreaks, resultant hospital admissions and mortality. This is evident if we look at PHE’s Weekly Influenza Report for week 2 in any year prior to 2020.
In 2020, according to the newly combined PHE Weekly Influenza and COVID Report, there have been virtually no cases of influenza, treatment or related deaths.
The ONS note all the details on a death certificate. In their mortality roundup for the January to August 2020 period they stated:
Influenza and pneumonia was mentioned on more death certificates than COVID-19, however COVID-19 was the underlying cause of death in over three times as many deaths between January and August 2020.
How can flu and pneumonia possibly be on more death certificates than COVID-19 if, as the media and PHE allege, it has been wiped out? It seems the medical profession didn’t get the memo.
A Systemic Catch-22
A positive SARS-CoV-2 test appears to be the primary reason for attribution of mortality. Only the most fastidious diagnosis can differentiate between COVID-19 symptoms and other ILI’s. Is it credible to believe that flu and pneumonia are on more death certificates but that COVID-19 is deemed the cause of death on three times as many Medical Certificates of Cause of Death (MCCD’s)?
These are somewhat rhetorical questions. The reason why bizarre anomalies like this occurred is because recording COVID-19 as the cause of death was practically unavoidable.
The Coronavirus Act overhauled the MCCD and death registration processes. In addition, World Health Organisation Coding changes and guidance issued by the NHS and other medical authorities combined to create a systemic Catch-22.
In England and Wales an MCCD is completed online using the WHO’s recommended coding. The MCCD is split into sections. Part 1. a) “Disease or condition directly leading to death”; b) “Other disease or condition, if any, leading to (a)”; and c) “Other disease or condition, if any, leading to (b)”.
Part 2 records “Other significant conditions contributing to the death, but not related to the disease or condition causing it.” For example, a person may have died from heart failure caused by pneumonia but obesity, though not directly related to the immediate cause of death, could have contributed and would therefore be recorded in Part 2.
In the case of respiratory disease, the direct cause of death could be Acute Respiratory Distress Syndrome (ARDS). This may be brought on by, for example, pneumonia which was caused by influenza. In this instance the direct cause of death would be recorded in Part 1. a) as ARDS, prompted by pneumonia in Part1. b), and the underlying cause would be set as influenza in Part 1. c).
The WHO Family of International Classifications (WHOFIC) Network Classification and Statistics Advisory Committee (CSAC) created new International Classification of Diseases codes (ICD-10 codes) for COVID-19. If the decedent had tested positive, or had been in contact with anyone else who had, a recorded COVID-19 death was practically a fait accompli.
A “confirmed case” was dependent solely upon a positive test result and was given the code U07.1. Observable symptoms were not necessary for U07.1 code to be recorded on a death certificate.
A suspected COVID-19 case was coded as U07.2. A decedent known to have had contact with a SARS-CoV-2 positive person who, while neither testing positive nor having any symptoms themselves, was deemed a suspected/probable COVID-19 case and given the code U07.2.
Neither the U07.1 nor the U07.2 codes required any evidence that the decedent had COVID-19.
As the U07.1 code indicated a “confirmed case,” unless the decedent passed away from something obviously unrelated, such as head trauma, a SARS-CoV-2 positive test would almost automatically confirm COVID-19 as the underlying cause of death.
The WHO clearly described this process in their International MCCD coding guidelines. They defined what death “due” to COVID-19 was:
A death due to COVID-19 is defined for surveillance purposes as a death resulting from a clinically compatible illness, in a probable or confirmed COVID-19 case, unless there is a clear alternative cause of death that cannot be related to COVID disease (e.g. trauma). There should be no period of complete recovery from COVID-19 between illness and death. A death due to COVID-19 may not be attributed to another disease (e.g. cancer).
A clinically compatible illness could be any ILI. Even if the individual died from cancer, as long as they tested positive for SARS-CoV-2, or the Doctor suspected respiratory distress, the death would be registered as “due to” COVID-19. COVID-19 would again be the reported as the underlying cause.
Additional WHO guidance stated:
COVID-19 should be recorded on the medical certificate of cause of death for ALL decedents where the disease caused, or is assumed to have caused, or contributed to death. Although both categories, U07.1 … and U07.2 … are suitable for cause of death coding … it is recommended, for mortality purposes only, to code COVID-19 provisionally to U07.1 unless it is stated as probable or suspected.
If a doctor was uncertain and merely suspected a probable COVID-19 case, they were clearly advised to record it on the MCCD as a confirmed case (U07.1 and not U07.2). Again, ensuring it would be reported as the “underlying cause.”
The Office of National Statistics stated:
Deaths involving the coronavirus (COVID-19) include those with an underlying cause, or any mention, of U07.1 (COVID-19, virus identified) or U07.2 (COVID-19, virus not identified) …
If the Doctor held firm and coded COVID-19 as U07.2 on Part 2 of the MCCD, the ONS (and the NRS and NISA) would still report it as a COVID-19 death.
In the Clear
The Coronavirus Act indemnified all NHS doctors against any claims of malpractice or negligence. It removed the need for a second medical opinion (Medical Examiner), it effectively ruled out both post-mortem examinations and jury-led coroner’s inquests, allowed virtually anyone to act as the qualified informant and facilitated rapid cremation.
In response to the Coronavirus Act and WHO IC10 coding, the NHS issued guidance to doctors for the completion of the Medical Certificate of Cause of Death (MCCD). The COVID-19 death certification and registration process they produced beggars belief. Under the guidance, acting on their own without any corroborating opinion:
Any medical practitioner with GMC registration can sign the MCCD, even if they did not attend the deceased during their last illness.
Attend doesn’t mean examine either. Checking in with the decedent via Zoom is sufficient. Failing that, if the MCCD signing doctor has only seen the decedent after death, providing they have tested positive, a review of their notes is still sufficient to record a COVID-19 death. The NHS stated COVID-19 could be recorded wherever:
A medical practitioner has attended the deceased (including visual/video consultation) within 28 days before death, or viewed the body in person after death.
In keeping with the WHO coding guidelines, there isn’t even any need for a positive test result. The NHS guidance added:
If before death the patient had symptoms typical of COVID-19 infection, but the test result has not been received, it would be satisfactory to give ‘COVID-19’ as the cause of death … In the circumstances of there being no swab, it is satisfactory to apply clinical judgement.
The NHS then created a system of remote death certification:
During periods of excess deaths due to COVID-19, healthcare providers are encouraged to redeploy medical practitioners whose role does not usually include direct patient care, such as some medical examiners, to provide indirect support by working as dedicated certifiers, completing MCCDs.
These dedicated certifiers, though medically qualified, are tasked with signing off COVID-19 MCCD’s. GP’s and hospital physicians gather reports, perhaps from a review of the deceased’s medical notes or a video conference with a care home provider, and pass that information to the dedicated COVID-19 certifier for MCCD completion.
The NHS advised that no proof was required for the attribution of a COVID-19 death. They stated:
Without diagnostic proof, if appropriate and to avoid delay, medical practitioners can circle ‘2’ in the MCCD (information from post-mortem may be available later)
This suggestion that a post mortem may be available is implausible.
Additional guidance issued by the Royal College of Pathologists states:
If a death is believed to be due to confirmed COVID-19 infection, there is unlikely to be any need for a post-mortem examination to be conducted and the Medical Certificate of Cause of Death should be issued.
Bearing in mind that the WHO had instructed suspected U07.2 deaths to be coded as confirmed U07.1 deaths, the chance of anything other than confirmed COVID-19 death reaching a pathologist is extremely remote. Any MCCD signed “without diagnostic proof” would almost certainly be agreed by the pathologist without further scrutiny. The mere act of putting COVID-19 anywhere on the MCCD was enough to negate the need for a post mortem.
This new death certification system, specifically designed for COVID-19, has understandably caused confusion. The British Medical Association’s verification of death guidance advises that if no signing doctor has seen the decedent prior to completing the MCCD they should refer it to the coroner. However, this was only a policy recommendation not a legal requirement.
Contradicting this, the Chief Coroner advised:
COVID-19 is a naturally occurring disease and therefore is capable of being a natural cause of death … The aim of the system should be that every death from COVID-19 which does not in law require referral to the coroner should be dealt with via the MCCD process.
This means that even if a coroner receives a referral from a doctor, they will be highly likely to automatically approve the MCCD without further inquiry. Since a post mortem has already effectively been ruled out, there will be little point in the coroner investigating further.
NHS staff and carers who may have been uncomfortable with all this have been under no illusions. The use of draconian Hospital Trust gagging orders (non disclosure agreements) are widely reported. Carers who have spoken out have been sacked.
To finalise this unbelievable COVID-19 death registration system, the Coronavirus Act also withdrew the standard second opinion required prior to cremation. The need to complete Cremation form 5 was suspended for all COVID-19 deaths.
Alleged COVID-19 decedents can be cremated without any clear evidence that they ever had the disease, regardless of their family’s wishes, swiftly ending any chance of any investigation by sceptical family members.
What was the Cause of Death?
SAGE assessed the UK mean operational false positive rate (FPR) for RT-PCR to be 2.3% of all conducted tests. The government say they have conducted just over 118M tests of which 4.3M were positive. This includes an unknown number of multiple tests of the same individual. A mean FPR of 2.3% suggests 2.7M of those 4.3M positive tests were false positives. This equates to 62.7% of all positive test results.
As we have already discussed it is highly likely that laboratory testing was the primary determinant for a diagnosis of COVID-19. Therefore it is not unreasonable to surmise that at least 50% of claimed COVID-19 deaths were attributed on the basis of false positives. We can halve the claimed 148,000 to 74,000 COVID-19 deaths.
The 2020 ONS mortality data for England showed a reduction in deaths from a number of other causes.
Deaths from Ischaemic heart diseases were 1,450 below the 5 year average. Cerebrovascular disease was down by 2,276, malignant respiratory neoplasm by 1,537, chronic lower respiratory disease by 2,764 and influenza and pneumonia deaths were 7,313 below the 5 year average. An apparent reduction of 15,340 deaths from other causes.
It seems highly likely that these deaths were wrongly recorded as COVID-19.
As we have seen above, approximately 90% of supposed COVID-19 decedents had at least one other comorbidity. Using the Government’s 148,125 figure, we might claim, therefore that only something like 15,000 of these died of, rather than with.
Is this claim justifiable? Well, consider this:
The Department of Health and Social Care published a study of residents in care homes which purported to show the total number of confirmed cases. Among this number they claimed:
80.9% of residents who tested positive were asymptomatic.
A meta analysis by the Oxford Centre for Evidence Based Medicine found that asymptomatic rates among those who tested positive varied between 5% – 80%. If there are no symptoms, then the disease cannot have contributed towards a death.
Taking everything into account, from high rates of comorbidity, to low rates of symptomatic individuals, the impact of false positives on testing and a death certification regime heavily biased towards recording COVID-19 as the underlying cause, then it is reasonable to conclude that the total number of deaths from Covid-19 is not 148,000, nor 126,000, but much closer to 15,000.
April 10, 2021
Posted by aletho |
Civil Liberties, Deception, Economics | Covid-19, Human rights, UK |
Leave a comment
IN THE early stages of the ongoing ‘war on terror’, which started twenty years ago, a nebulous conception of the enemy, non-existent victory conditions and the consistent dishonesty of warmongering politicians such as Blair led some to wonder if the threat of the global ‘Axis of Evil’ had been exaggerated to achieve some other set of goals.
Today, in similar circumstances of unanswered questions and ambiguous realities underpinned by systematic deception, reinforced by Boris Johnson on Monday as he launched the new phase of the psychological and economic war he is waging on the British people – vaccine passports (and after that?) – this question is being asked:
Is there a pandemic? Was there ever a pandemic?
Perhaps the most important point to grasp is that a pandemic is a construct, not an object. There is nothing you can point at which is the pandemic, only various data points indicating that one exists.
The World Health Organisation changed its definition in 2008 to exclude the criterion of ‘enormous numbers of deaths and illness’. In other words, the definition of a pandemic is ultimately a matter of interpretation. There is no data that currently supports the claim there is a pandemic in Britain at this moment, and whether any data ever did is doubtful..
The scientific process has happened in reverse. Starting in January last year, the existence of a deadly new pandemic, unlike anything previously confronted, was conjectured on the basis of terrifying rumours and unreliable reports from China, not scientifically established facts.
Once the existence of an extraordinary pandemic was assumed, extraordinary measures were justified to fight it, including the rapid deployment of highly unreliable PCR protocols developed by the Gates Foundation-funded Christian Drosten, shock propaganda messaging, a massive and drastic reduction in health care provision (which has functionally destroyed the NHS in order to ‘protect’ it) and de facto euthanasia policies in care homes, based on Neil Ferguson’s Gates Foundation-funded models.
Compromised administrative procedures recorded deaths as lives lost to the pandemic, providing further evidence for its existence.
As is now well known, an overwhelming majority of pandemic casualties also suffered from other conditions and the average age of victims tracks life expectancy in every country.
If the pandemic had not been assumed to exist, and the reckless and cynical interventions against it had not taken place, how would anyone know there was one?
Data clearly demonstrates that lockdowns and related policies were never necessary or effective. Experimental therapies have been deployed which are unreliable and potentially dangerous. Vaccination may or may not prevent contagion or transmission. The fact that governments and their paid experts are unable or unwilling to incorporate these matters into their thinking testifies either to their sinister intentions or the extent to which their mental processes have been corrupted.
Either they believe that some clandestine end justifies repressive and deceptive means, or else they are insane, or mindless through conformism: there is no other explanation.
Phenomenologically, the most important evidence for the existence of the pandemic is its external signifiers, especially face masks, this mass psychological theatre.
Here again, the conjecture of the pandemic itself justified the imposition of the mandate, and nothing else: no evidence supports the thesis that masks have any positive medical effect and the more plausible scenario is their medical effect is negative. Nonetheless the Gates Foundation-funded behavioural psychologists of Sage and their equivalents in other countries argued that mandating them was necessary (‘because most people still did not feel sufficiently threatened’).
The vague objective of an incomprehensible ambition, opposed against a nightmare, discloses a more concrete aim: control.
Why the authors of this initiative want control presents a complex question. Either they just want it without even knowing why, or they want it for another reason. Perhaps they have a broader plan which demands dramatically upgraded repression.
Either way, what they seem to desire is control over the bodies of their populations. In the idea of vaccine passports, what is being implemented is a political and legal climate in which experimental genetic therapies on human populations are normalised and inescapable. Armed with vaccine passports, global governments and their corporate allies would be able to establish the foundations of a global surveillance state, with the power to monitor every social interaction.
Vaccine passports are the gateway to the most radical slavery the world has ever seen. It now seems likely that creating a psychological and social climate in which to impose them was always the aim behind the engineered pandemic. The pandemic was needed to impose the vaccinations, and the vaccinations are needed to impose the passport.
This transformation of one part of the population into the vaccinated simultaneously invents the unvaccinated, a problem which could eventually be resolved through liquidation, but meanwhile offering opportunity for politically profitable stigmatisation. The vaccinated (via vaccine passports) are granted ‘privileges’ that the unvaccinated are denied in order to compel compliance.
Like accepting being forced to wear a government mandated gimp mask, for no reason whatsoever, a person accepting vaccination implicitly accepts the terms of the new normal. At the same time, vaccination is a ritual, substantiating membership in a psychological community.
Anyone who supposes the vaccine passport could lead to discrimination fails to grasp that this is the whole purpose of this document. The entire point is to divide society, to rule it. By creating checkpoints everywhere, power flows to the authority controlling access, in this case Johnson and his faction: a criminal cartel.
Accepting vaccination does not automatically imply a happy ending. The privilege to resume the semblance of a normal life (a ’new normal’ life) is linked to vaccination status now, but the reasoning behind this privilege is contingent on the existence of the non-vaccinated. Once non-vaxxers vanish, the reason for continuing to offer privileges is also gone. At this point a new status category can be introduced, and the same selective sequence played again. In this way, it would be possible progressively to eliminate a significant percentage of the population.
So far the theatre of the pandemic has been organised as a campaign of psychological manipulation with policies conceived to ‘nudge’ compliance by alternately dangling rewards (which are usually snatched away) and making threats. This campaign has also featured systematic censorship and intimidation directed against some of the most accomplished scientists in the world.
Although these tactics make a mockery of the principle of informed consent, they are of the ‘softer’ variety. Ultimately, more aggressive tactics will be deployed. The intensifying lawlessness of the police now points in this direction.
What can be done? The government is ruling via a threadbare fraud. When that disintegrates what will remain is force, but the real command authority of Johnson and his collaborators over the monopoly of violence that defines the British state has barely been tested.
Would British police or soldiers open fire on peaceful protesters on Johnson’s, Gove’s or Starmer’s orders? The question may arise. So far, the Territorial Support Group have been used by Johnson to attack protesters, and a strategy of tension is being used to increase antagonism between the people and the police, but further escalation would be risky.
What is needed in the meantime is urgently to unwind the cycle of compliance, beginning with the mass removal of the mask, extending to the deconstruction of the narrative, and culminating in total disobedience against the tyranny now represented by this illegitimate and shameful government.
April 10, 2021
Posted by aletho |
Civil Liberties, Corruption, Deception, Science and Pseudo-Science, Timeless or most popular | Covid-19, Human rights, UK |
Leave a comment
Former Foreign Office Minister Sir Alan Duncan has accused pro-Israel lobbyists of “the most disgusting interference” in British politics, and of negatively influencing the country’s foreign policy in the Middle East. The veteran politician has also claimed that Conservative Friends of Israel (CFI) went “ballistic” and blocked him from taking on a new post covering the region’s affairs.
Duncan, a former Conservative MP and government minister, makes the sensational claims in his newly published memoir, In The Thick of It: The private diaries of a minister (published by William Collins, 2021). Speaking to journalist Michael Crick about his book for the MailPlus website, the 64 year-old blasted CFI and its undue influence in British politics.
Conservative Friends of Israel, he said, had injected a “Netanyahu-type view of Israeli politics into our foreign policy,” referring to Israel’s right-wing prime minister. He claimed that it had applied pressure on Theresa May’s government to prevent him becoming Middle East minister at the Foreign Office.
In his book, Duncan claims that his new role was agreed until the then Foreign Secretary Boris Johnson alerted him to the fact that CFI “are going ballistic”. He insists that he was blocked from taking the post because he believes in the rights of the Palestinians.
In one diary entry Duncan is scathing about Conservative MPs’ fawning over Benjamin Netanyahu during his visit to Britain. He was “ashamed” of the British government, accusing officials of allowing Netanyahu to “peddle pro-settlement propaganda”.
Duncan described to Crick the culture of fear created by CFI. “A lot of things do not happen in foreign policy or in government for fear of offending them because that’s the way it’s put to them by the CFI.”
He warned: “It’s a sort of buried scandal that has to stop… they will interfere at a high level in British politics in the interests of Israel on the back of donor power in the UK.” Ultimately, he pointed out, the influence of the pro-Israel lobby group came at the expense of the Palestinians.
Duncan has been a major target for the pro-Israel lobby. In 2017, an Al Jazeera documentary sensationally exposed the operations of pro-Israel lobbyists working with the Israeli Embassy in London to “take down” a minister of the Crown. Duncan, fellow Conservative MP Crispin Blunt and former Labour leader Jeremy Corbyn were marked out as targets. Writing for Al Jazeera at the time, Robert Grenier, a retired, 27-year veteran of the CIA’s Clandestine Service, warned against what he called the “insidious threats” of the pro-Israel lobby.
Read also: Conservative Friends of Israel urge UK to oppose ICC’s war crimes investigation
April 10, 2021
Posted by aletho |
Book Review, Ethnic Cleansing, Racism, Zionism | Human rights, Israel, Palestine, UK, Zionism |
Leave a comment
The WEF’s promotion of a Chinese ‘smart face mask’ that tracks every breath its wearer takes is further evidence that the changes to Western society over the last 12 months of Covid are intended to be permanent.
“It’s only for when you pop into Tesco’s to do your weekly shop, what‘s your problem with that, you selfish ‘right-wing’ libertarian?” That’s how the introduction of mandatory face-masks was sold to us in Britain last summer, by its virtue-signalling, “Look at me, I’m such a good citizen” supporters.
Masks would be temporary – restricted to shops – and as soon as the Covid threat had passed they would be dispensed with, like social distancing. Anyone who said these measures were designed to be permanent – and were part of the global elite’s plan to keep the plebs muzzled up forever – was dismissed as a ‘crank’ and ‘a conspiracy theorist’.
Well, nine months on, and where are we?
The UK government has issued a ‘road map’ for taking us – with the speed of a 150-year-old Galapagos Island tortoise on sleeping tablets – out of lockdown. But there’s no mention of when masks and social distancing will be dispensed with.
Could that be because there’s no intention of masks and social distancing ever being dispensed with? It certainly appears that way.
Since last July, we’ve seen the mask mandate expanded. You are now asked to wear them not just in shops, but in all indoor areas, unless exempt. Even school children have to wear them in class. That decision was supposed to be reviewed at Easter, and, guess what, the government has just extended the school mask mandate until the summer. In addition, football fans will be expected to wear masks when they’re finally allowed back into grounds this spring at ‘trial’ events.
‘Following the science’? Hardly. We shouldn’t forget that in the week that masks were first introduced last summer, deaths with Covid literally reached zero.
The BBC’s Health Correspondent Deborah Cohen asked the World Health Organisation if their change of advice on masks had been due to political lobbying, and they did not deny.
Why, if masks were so important in preventing transmission, weren’t we told to wear them last March and April? In fact, government scientists advised us not to wear them.
Now, it seems not only must we wear them, but we need to get used to them being a permanent part of daily life in the ‘New Abnormal’. In their recent paper, ‘Evaluating England’s Road Map out of Lockdown‘, published on the UK government’s website, the Imperial College Covid-19 Response team state: “Whilst the impact of Test Trace Isolate, mask wearing, hand hygiene and COVID security on ‘R‘ is difficult to quantify it will be vital to emphasise the importance of normalising and ensuring adherence to all measures even after ‘full lifting’ is achieved.” Got that? Masks need to stay even after Boris Johnson says ‘Lockdown is over‘.
It’s in this context that the World Economic Forum’s (WEF) enthusiastic promotion of the Chinese ‘smart face mask’ needs to be seen. It apparently reminds users when to wash it and checks if they’re wearing it properly. If too much carbon dioxide builds up inside, a phone alert reminds the wearer to catch a few breaths of fresh air. If the user forgets to put it on, the same phone app sends them a reminder to mask up.
This is not about public health, but all about making sure that measures introduced ostensibly to stop the spread of Covid-19 become permanent. Yes, once again the much-derided ‘crackpot conspiracy theorists’ of 2020 have been proved right.
Remember how last summer, the WEF was promoting a ‘Common Pass‘ health passport scheme, not just for international travel but for access to domestic events too? It would never happen, we were told. That’s ‘David Icke stuff’, was the condescending brush-off. Well, that too has come to pass – no pun intended.
To find out why all this is happening, all we have to do is to follow the money trail. All the way to Davos. What does the pro-permanent mask Imperial College have in common with the pro-permanent mask WEF? Answer: the pro-permanent mask Bill Gates.
Last month, Gates himself likened putting on a face mask to putting on a pair of trousers. “I just don’t think wearing a mask is such a deep inconvenience. I mean we ask people to wear pants. You know, why was this politicised?” Back in November, he made the same comparison. “We ask you to wear pants and, you know, no American says — or very few Americans say — that that’s, like, some terrible thing.”
But is masking up whenever we go out really the same as putting on a pair of trousers, to use the English term?
Of course it isn’t. Unless you’re Batman or The Lone Ranger, or another Saturday morning cinema superhero, or indeed a bank-robber, wearing a mask in public isn’t normal, and no amount of WEF-spin makes it so. But what walking about with pieces of black cloth over our mouths and noses does do, is maintain the levels of fear in the community.
If cases and deaths with Covid have plummeted to zero, but we want to make people live as if there is a permanent pandemic, to keep control over them, and to introduce ‘Covid-certification’ to restrict where they can and cannot go, how else can we keep Project Fear going without masks? It’s the only way we’d know that these were not ‘normal’ times. Which is, of course, precisely why they were introduced when deaths had dwindled to very low numbers.
Smart masks? The really smart thing is to get wise to the WEF’s dystopian agenda.
Neil Clark is a journalist, writer, broadcaster and blogger. His award winning blog can be found at http://www.neilclark66.blogspot.com.
April 9, 2021
Posted by aletho |
Civil Liberties, Science and Pseudo-Science | Covid-19, Human rights, UK |
Leave a comment
The leader of the pro-independence Alba Party, Alex Salmond, has steadfastly refused to toe the British government’s line on the alleged poisoning of a Russian double agent in England in 2018.
Former Russian military intelligence officer, Segei Skripal, who betrayed his country by working for the UK’s MI6, was allegedly poisoned, alongside his daughter Yulia, with what the British government says was the Novichok nerve agent.
The alleged attack took place in the medieval cathedral city of Salisbury on March 04, 2018. Both Skripal and his daughter survived the alleged attack.
Speaking to BBC Good Morning Scotland on April 07, Salmond refused no less than four times to blame Russia for the alleged attack.
Faced by Salmond’s defiance, the show’s presenter, Gary Robertson, tried to undermine the former First Minister’s position by pointing out that he produces a show for the Russian TV network RT.
But Salmond hit back by saying: “I produce, along with Tasmina Ahmed-Sheikh, a program for Slainte Media which is then broadcast on the RT platform, as they’re perfectly entitled to do”.
“I can tell you from personal experience – I don’t know what your experience at the BBC is – not a single word of editorial instruction or even suggestion has been made to me from anyone at RT and the program stands on its own merits”, the former leader of the Scottish National Party (SNP) added.
Salmond and fellow Alba Party candidate Ahmed -Sheikh (who is a former SNP MP), host “The Alex Salmond Show” each week on RT.
On another subject, Salmond suggested that evidence of Russian interference in recent US elections was “very slight”.
Salmond’s position on these sensitive issues will alarm the British establishment which has identified Russia as an “active threat” to UK national security in its newly-released Integrated Review of Security, Defense, Development and Foreign Policy.
Both the Alba Party and the SNP are committed to closing down the headquarters of the Royal Navy in Scotland.
The Faslane naval base, formally called Her Majesty’s Naval Base, Clyde, hosts the UK’s nuclear weapons capability.
April 7, 2021
Posted by aletho |
Mainstream Media, Warmongering, Militarism, Russophobia | Scotland, UK |
Leave a comment
The Medical Director of a hospital in the United Kingdom has bravely spoken out against the failure to report the reality of morbidity caused by the Covid-19 vaccination roll-out across the United Kingdom to NHS staff.
Dr Polyakova, who is the Medical Director of a hospital in Kent has said that the “levels of sickness after vaccination is unprecedented” among NHS staff, confirming that some are even suffering neurological symptoms which is having a “huge impact on the health service functioning”.
The doctor, who progressed into medical management of the hospital over the past three years says that she is struggling with the “failure to report” adverse reactions to the Covid vaccines among NHS staff, and clarified that the young and healthy are missing from work for weeks after receiving a dose of either the Pfizer or AstraZeneca experimental vaccine.
“Some even require medical treatment” Dr Polyakova said, “Whole teams are being taken out as they went to get the vaccine together”.
In response to the arising question of making Covid-19 vaccination compulsory for NHS staff, Dr Polyakova said –
“Mandatory vaccination in this instance is stupid, unethical and irresponsible when it comes to protecting our staff and public health. We are in the voluntary phase of vaccination, and staff are being encouraged to take an unlicensed product that is impacting on their immediate health.
“I have direct experience of staff contracting Covid after vaccination and probably transmitting it. It is clearly stated that these vaccine products do not offer immunity or stop transmission.
“So why are we doing it? There is no longitudinal safety data available and these products are only under emergency licensing. What is to say that there are no longitudinal adverse effects that we may face that may put the entire health sector at risk?”
Both the Pfizer and AstraZeneca jab are only licensed for emergency use, as confirmed by Dr Polyakova. This means that the manufacturer of the vaccine, in this case either Pfizer or AstraZeneca, are not liable for any injury or ill-effect that may occur in the recipient of their product.


The Medical Director didn’t stop their though as she went on to attack the coercion and mandating of experimental medical treatments for NHS staff, comparing it to a Nazi dystopia –
“Flu is a massive annual killer, it inundates the health system, it kills young people, the old the comorbid, and yet people can chose whether or not they have that vaccine (which had been around for a long time). And you can list a whole number of other examples of vaccines that are not mandatory and yet they protect against diseases of higher consequence.
“Coercion and mandating medical treatments on our staff, of members of the public especially when treatments are still in the experimental phase, are firmly in the realms of a totalitarian Nazi dystopia and fall far outside of our ethical values as the guardians of health.
“I would never debase myself and agree, that we should abandon our liberal principles and the international stance on bodily sovereignty, free informed choice and human rights and support unprecedented coercion of professionals, patients and people to have experimental treatments with limited safety data. This and the policies that go with this are more of a danger to our society than anything else we have faced over the last year.
“What has happened to “my body my choice?” What has happened to scientific and open debate? If I don’t prescribe an antibiotic to a patient who doesn’t need it as they are healthy, am I anti-antibiotics? Or an antibiotic-denier? Is it not time that people truly thought about what is happening to us and where all of this is taking us?”
We couldn’t have said it better ourselves.
April 6, 2021
Posted by aletho |
Civil Liberties | COVID-19 Vaccine, Human rights, UK |
Leave a comment

Once again, the UK government has been shown to have used ‘covert tactics’ in order to scare UK residents into staying at home for lockdown by increasing the ‘perceived threat’ of COVID’ rather than genuine science-backed risk assessment data, and also used ‘hard-hitting emotional messages’ designed to cower the public into complying with the government’s arbitrary diktats.
Due to the heightened level of public outrage, mainstream media outlets are finally being forced to admit what they have been systematically covering-up now for 12 months – that Government have been involved in active psychological and information warfare measures against their own population.
In a document presented to the UK government’s ‘SAGE’ confab, a scientific group meant to advise government on pandemic policies, it was revealed how technocrats sought to increase the ‘perceived threat’ of COVID-19 using aggressive psychological ‘hard-hitting emotional messages’ in order to brainwash the public into compliance.
Upon hearing the official admission, some psychology professionals have turned their sights on Downing Street, accusing bureaucrats of using “covert psychological strategies” in order to hype-up the threat of the virus, and offering no context as to the actual risk posed to the general public.
Government officials are accused of creating ‘a state of heightened anxiety’ which led to many people becoming ‘too frightened to attend hospital’.
This rebuke of the government’s active measures is given further credence by the fact that the majority of hospital beds in the UK remained largely empty in 2020, especially during the first few months of the ‘pandemic.’ This is especially relevant because it was at this same time when the government and mainstream media were relentlessly pushing out the idea that health services were ‘under threat’ of being overrun by Covid, only it never happened.
As a result of the government’s fear campaign, along with the overall throttling of the NHS, there have been an estimated 4.66 million people left waiting many months to begin even routine treatment, as well as thousands of pre-cancer screening appoints abandoned or pushed back – all because of the constant ramping-up of the fear of Covid.
The question still remains: will cabinet ministers be held to account for this unprecedented over-reach of state power?
The Mail Online reports…
Experts fear Britons have been the subject of an experiment in the use of tactics which operate ‘below their level of awareness,’ it was said.
They have now made a formal complaint to an organisation which will rule on whether Government advisers are guilty of a breach of ethics.
Downing street denies this, claiming it simply presented the facts.
Complainants point to a document handed to the Scientific Advisory Group for Emergencies last March, when the pandemic began to rapidly grow in Britain.
The paper, written by Scientific Pandemic Influenza Group on Behaviours, said: ‘A substantial number of people still do not feel sufficiently personally threatened; it could be that they are reassured by the low death rate in their demographic group, although levels of concern may be rising.
‘The perceived level of personal threat needs to be increased among those who are complacent, using hard-hitting emotional messaging. To be effective this must also empower people by making clear the actions they can take to reduce the threat.’
The document, seen by the Telegraph, allegedly then gave 14 options for improving compliance including ‘use media to increase sense of personal threat’, which they said would be highly effective but runs the risk of ‘negative’ side effects.
SAGE members have since claimed the British public have been ‘subjected to an unevaluated psychological experiment without being told that is what’s happening.’
They added that SPI-B reports are often not ‘challenged’ by SAGE because many of those involved are ‘not very well equipped to evaluate it.’
‘When someone from SPI-B is saying we need to ramp up the fear and keep it ramped up – there wasn’t much questioning of that at the beginning and most of the questioning came from external sources, not from within.’
SPI-B is described as providing behavioural science advice aimed at anticipating and helping people adhere to interventions that are recommended by medical or epidemiological experts.
(…) Last November, Sir Patrick Vallance admitted he had ‘regrets’ over frightening people with a doomsday dossier that forecasted as many as 4,000 Covid-19 deaths a day over winter and was used to justify a second national lockdown.
Number 10’s top scientific adviser made the comments alongside Professor Chris Whitty, England’s chief medical officer, after the pair were hauled before MPs to defend SAGE’s modelling that also predicted hospitals would be overrun with virus patients by the end of this month.
During the grilling by members of the House of Commons Science and Technology Committee, Labour MP Graham Stringer asked Sir Patrick if he believed he had frightened people with the bleak deaths data presented during Saturday night’s press briefing.
The Chief Scientific Adviser said: ‘I hope not and that’s certainly not the aim… I think I positioned that as a scenario from a couple of weeks ago, based on an assumption to try and get a new reasonable worst-case scenario. And if that didn’t come across then I regret that.
Continue this story at the Mail Online
April 6, 2021
Posted by aletho |
Deception, Fake News, Mainstream Media, Warmongering, Science and Pseudo-Science | Covid-19, UK |
Leave a comment
The British public’s widespread compliance with lockdown restrictions and the subsequent vaccine rollout has been the most remarkable aspect of the coronavirus crisis.
The removal of our basic freedoms — in the form of lockdowns, travel bans and mandatory mask wearing — have been passively accepted by the large majority of people. Furthermore, the proportion of the general public expressing a willingness to accept the Covid-19 vaccines has been greater in the UK than almost anywhere else in the world. But has the government achieved this widespread conformity through the unethical use of covert psychological strategies — “nudges” — in their messaging campaign?
A major contributor to the mass obedience of the British people is likely to have been the activities of government-employed psychologists working as part of the “Behavioural Insights Team” (BIT). The BIT was conceived in 2010 as “the world’s first government institution dedicated to the application of behavioural science to policy.” In collaboration with governments and other stakeholders, the team aspire to use behavioural insights to “improve people’s lives and communities”. Several members of BIT, together with other psychologists, currently sit on the Scientific Pandemic Insights Group on Behaviours (SPI-B), a subgroup of SAGE, which offers advice to the government about how to maximise the impact of its Covid-19 communications.
A comprehensive account of the psychological approaches deployed by BIT is provided by an Institute of Government document titled MINDSPACE: Influencing behaviour through public policy, where it is claimed that these strategies can achieve “low cost, low pain ways of ‘nudging’ citizens … into new ways of acting by going with the grain of how we think and act”. Several interventions of this type have been woven into the Covid-19 messaging campaign, including fear (inflating perceived threat levels), shame (conflating compliance with virtue) and peer pressure (portraying non-compliers as a deviant minority) – or “affect”, “ego” and “norms”, to use the language of behavioural science.
Behavioural scientists know that a frightened population is a compliant one, so this was exploited as a way of compelling us to abide by the coronavirus restrictions. The minutes of the SPI-B meeting on 22 March 2020 stated: “The perceived level of personal threat needs to be increased … using hard-hitting emotional messaging.” Aided by the mainstream media, the British public were subsequently bombarded with fear-inducing information, images and mantras: Covid-19 daily death counts reported without context; inflated predictions of future casualties; recurrent footage of dying patients in Intensive Care Units; and scary slogans like, “If you go out you can spread it”, or “People will die”, often accompanied by images of emergency personnel wearing PPE.
We all strive to maintain a positive view of ourselves. Utilising this human tendency, behavioural scientists have recommended messaging that equates virtue with adherence to the Covid-19 restrictions, so that following the rules preserves the integrity of our egos while any deviation evokes shame. Examples of these nudges in action include: slogans such as, “Stay home, Protect the NHS, Save lives” and “Protect yourselves, Protect your loved ones”; TV advertisements where an actor tells us, “I wear a face covering to protect my mates”; the pre-orchestrated Clap for Carers ritual; ministers telling students not to “kill your gran”; and close-up images of acutely unwell hospital patients with the voice-over, “Can you look them in the eyes and tell them you’re doing all you can to stop the spread of coronavirus?”
And then there’s what the psychologists euphemistically refer to as “normative pressure”: awareness of the prevalent views and behaviour of our fellow citizens — through peer pressure and scapegoating — can prise us into compliance. The simplest example is ministers repeatedly telling us that the vast majority of people are “obeying the rules”. But normative pressure is less effective in changing the behaviour of the deviant minority if there is no visible indicator of pro-social conformity rooted in communities. The mandating of masks in summer 2020 — in the absence of strong evidence that they reduce viral transmission in the community — enabled the rule breakers to be instantly distinguished from the followers. Appearing unmasked in public places now felt comparable to failing to display the icon of a dominant religion while being among devout followers; even if no explicit challenge ensues, the implicit demand to conform is palpable.
The same covert strategies are now being used to promote the uptake of the Covid-19 vaccines. The tactic of fear inflation is evident in a recent NHS England document that recommends healthcare staff “leverage anticipated regret” on the over-65s cohort by telling them they are “over three times more likely to die”. The recommended follow-up statement is, “Think about how you will feel if you do not get vaccinated and end up with Covid-19?” For young people — who are at vanishingly small risk of suffering serious illness should they contract Covid-19 — shame is the selected tool from the behavioural-science armoury; the recommendation is that they should be told “normality can only return, for you and others, with your vaccination.” As for the healthcare staff who will administer the jabs, the psychological experts suggest an ego boost from being hailed as the, “latest ‘NHS Heroes’”.
So, what’s wrong with using these covert psychological strategies to improve compliance with public health policy?
In comparison to the government’s traditional tools of persuasion (such as information provision and rational argument) these methods of influence differ in their nature and subconscious mode of action. Consequently, three sources of ethical concern emerge: problems with the methods per se; problems with the goals to which they are applied; and problems with the lack of consent.
It is questionable whether a civilised society should knowingly increase the emotional discomfort of its citizens as a means of gaining their compliance. State scientists deploying fear, shame and scapegoating to change minds is an ethically dubious practice that in some respects resembles the tactics used by totalitarian regimes such as China, where the state inflicts pain on a subset of its population in an attempt to eliminate beliefs and behaviour they perceive to be deviant.
Another ethical issue associated with the methods of covert nudging used in the Covid-19 communications campaign concerns the unintended consequences. Shaming and scapegoating has emboldened some people to harass those unable or unwilling to wear a face covering. More disturbingly, fear inflation has led to many people being too scared to attend hospital with non-Covid illness, while many old people, rendered housebound by fear, will have died prematurely from loneliness. Collateral damage of this sort is likely to be responsible for many of the tens of thousands of excess non-Covid deaths in private homes. In a civilised society, is it morally acceptable to use psychological strategies that are associated with this level of collateral damage?
The perceived legitimacy of using covert psychological strategies to influence people may also depend upon the behavioural goals that are being pursued. It seems likely that a higher proportion of the general public would be comfortable with the government resorting to subconscious nudges to reduce violent crime – for example, to discourage young men from stabbing each other – as compared to the purpose of imposing unprecedented and non-evidenced public-health restrictions. Would British citizens have agreed to the furtive deployment of fear, shame and peer pressure as a way of levering compliance with lockdowns and mask mandates? Maybe they should be asked before the Government considers any future imposition of these techniques.
In 2010, the authors of the MINDSPACE document — one of whom is Dr David Halpern, a member of SAGE and the SPI-B — recognised the significant ethical dilemmas arising from the use of influencing strategies that impact subconsciously on the country’s citizens and emphasised the importance of consent. Indeed, they could not be clearer: “policymakers wishing to use these tools … need the approval of the public to do so.” They go on to suggest some practical ways of acquiring this consent, including the facilitation of “deliberative forums” where a representative sample of several hundred people are brought together for a day or more to explore an issue and reach a collective decision. I am unaware of any public consultation of this type being conducted to gain the public’s permission to use covert psychological strategies.
At an individual level, obtaining a recipient’s permission prior to an intervention is a long-established principle of ethical clinical practice. Informed consent is an essential precursor to any medical procedure, including vaccination. To ensure ethical integrity, healthcare staff should be encouraging each potential recipient to, consciously and rationally, weigh up the pros and cons of accepting the Covid-19 vaccine rather than nudging them towards compliance.
The covert psychological strategies incorporated into the state’s coronavirus information campaign have achieved their aims of inducing a majority of the population to obey the draconian public health restrictions and accept vaccination. The nature of the tactics deployed — with their subconscious modes of action and the emotional discomfort generated — do, however, raise some pressing concerns about the legitimacy of using these kinds of psychological techniques for this purpose. The government, and their expert advisors, are operating in morally murky waters. An open, public-wide debate about the ethical integrity of these approaches — and the extensive collateral damage associated with them — is urgently required.
Dr Gary Sidley is a retired clinical psychologist with over 30 years’ experience working for the NHS. He is a member of the Health Advisory and Recovery Team (HART).
April 4, 2021
Posted by aletho |
Deception, Timeless or most popular | Covid-19, UK |
Leave a comment
Two UK school textbooks on the Middle East have been “significantly altered” following intervention from leading advocates of the Zionist state in favour of the Israeli narrative. The alterations, slammed as “propaganda under the guise of education” and “not fit for purpose” have raised serious concerns over the textbook, prompting a pause in further distribution.
Details of the extensive “biased” and “misleading” alterations were exposed by a report, by Professors John Chalcraft and James Dickins, Middle East specialists in History and in Arabic, respectively, and members of the British Committee for the Universities of Palestine (BRICUP).
Their eight-page report uncovered” dangerously misleading” changes to the books published by Pearson, titled Conflict in the Middle East and The Middle East: Conflict, Crisis and Change, both by author Hilary Brash and are read by hundreds of thousands of GCSE students annually. GCSEs are the academic qualifications studied for by UK high school students to the age of 16.
The alterations were made last year following intervention by the Board of Deputies of British Jews (BoD) working together with UK Lawyers for Israel (UKLFI). Both are amongst the most vocal pro-Israeli groups in the UK.
Describing the scale of the alterations the report noted that there are changes on almost every page, often multiple changes. “In CME (with 84 pages of history) we have counted 294 changes, in MECCC (with 104 pages of history) over 360,” said the report. “There are thus on average more than three changes per page, and the re-writing on some pages is particularly extensive. Alterations have been made to text, timelines, maps and photographs, as well as to sample student essays, and to the questions that students are asked to answer”.
Multiple examples of the changes are highlighted in the report. In one example the original version says that “international law states that a country cannot annex or indefinitely occupy territory gained by force”. This is the overwhelming international legal consensus. The revised version replaces this with: “Some argue that international law states that a country cannot annex or indefinitely occupy territory gained by force”. This change, according to the report’s authors “clearly replaces an accurate and unambiguous description of the internationally accepted legal position by a ‘fudge’ that implicitly throws doubt on that position”.
In the original version of the domestic GCSE textbook there are 10 references to Jewish terrorism and 32 to Palestinian terrorism (in each case including use of ‘terror’, ‘terrorist’ or ‘terrorism’). After revision there are 4 references to terrorism by Jewish groups, and 61 references to terrorism by Palestinian ones.
Concluding the report, the authors said that they had “found the process to have been biased and the outcome misleading. The outcome is two textbooks that distort the historical record, failing to offer students a balanced view of the conflict. These books, we conclude, are not fit for purpose. School children should not be supplied with propaganda under the guise of education”.
Leading experts on the Middle East have raised serious concerns over the alterations. Eugene Rogan FBA, Professor of Modern Middle Eastern History at the University of Oxford said: “Given Britain’s historical responsibility, it is particularly important that the subject be taught in a way that is impartial and objective. It is a betrayal of such objectivity to allow Israel advocates the opportunity to edit teaching materials without giving Palestine advocates an equal opportunity to provide input. The result can only undermine confidence in the impartiality of the teaching of an intensely complex and sensitive issue.”
Neve Gordon, Professor of International Law and Human Rights at Queen Mary University of London, said: “Through their rigorous analysis of two GCSE text books, Professors John Chalcraft and James Dickins uncover how hundreds of revisions have been inserted in order to modify and distort historical and political facts relating to Israel/Palestine. Their report suggests that when accredited publishing houses allow lobbying groups to help develop high-school curriculum, knowledge is replaced by indoctrination and our children are encouraged to adopt biased thinking.”
Khaled Fahmy FBA, Professor of Arabic Studies at the University of Cambridge, said: “While it is laudable that Middle Eastern history books are regularly revised and updated, the manner in which these two school textbooks have been revised is shocking and unacceptable. School textbooks should be revised based on the advice and expertise of academics and scholars, not by reviewers selected by an organisation of lawyers whose rationale is advocating for a foreign country.”
In a statement to Middle East Eye, Pearson said “We stand by our texts but had already taken the decision to pause further distribution while we discuss further with stakeholders.”
April 3, 2021
Posted by aletho |
Ethnic Cleansing, Racism, Zionism, Full Spectrum Dominance | Israel, Palestine, UK, Zionism |
Leave a comment
A bizarre Covid-19 conspiracy theory appears to have taken root among the epidemiologists and public health officials who still support lockdowns. According to their claims, the UK government’s pandemic response was secretly captured at some point in the fall of 2020 by lockdown critics including Great Barrington Declaration co-author Sunetra Gupta, her Oxford colleague Carl Heneghan, and Sweden’s state epidemiologist Anders Tegnell.
Seizing on an article in the Times of London, supporters of this theory allege that Gupta and her colleagues convinced UK Prime Minister Boris Johnson and Chancellor Rishi Sunak to abandon a so-called “circuit breaker” lockdown during an audience in late September. Had the UK gone back into lockdown around the beginning of October instead of a month later – proponents of this theory maintain – it would have avoided its disastrous second wave over the fall and winter months.
Even the basic narrative flies in the face of empirical reality. In November 2020 and again in January 2021, the UK went through two successive rounds of draconian lockdowns of the exact type that Gupta and her colleagues advised against. Championed by Johnson as a way to avert the second wave, these policies utterly failed at their stated purpose. On November 5th, the date the second lockdown took effect, the UK’s death toll stood at 48,000. Over the next four months, three of them spent under recurring lockdowns, the UK’s fatality numbers exploded to over 120,000.
Equally telling, the timing of the UK’s fall/winter wave almost perfectly matched that of Sweden, which remained open throughout the same period – except the UK’s results under lockdowns were visibly worse. As a growing body of scientific literature attests, lockdowns did practically nothing to contain the pandemic. Instead, the performance of this policy shows no discernible advantage over states and countries that opted against suspending the basic operations of daily life, and in many cases lockdown countries actually did worse than those that remained open.
Still, proponents of the newest UK conspiracy theory hold that something very different would have happened if only Johnson had enacted an earlier lockdown around the beginning of October instead of November 5th. Its underlying narrative has gained an unusually intense following among public health activists and pundits in the UK.
Deepti Gurdasani, an epidemiologist at Queen Mary University in London and a principal organizer of the pro-lockdown John Snow Memorandum, has aggressively promoted the alleged wresting of pandemic policy away from the lockdowners as an explanation for why the UK’s second and third lockdowns failed. As early as December, Gurdasani blasted Downing Street for supposedly listening to the “dangerous ideology” of Gupta, Heneghan, and Tegnell, which “has cost thousands of lives” and sought to replicate the “dangerous” Swedish strategy. Never mind that Sweden, without lockdowns, has a much lower deaths-per-million residents total (1,303 as of April 1st) than the UK (1,890) under three harsh lockdowns.
The same narrative has become a favorite of Devi Sridhar, an anthropologist and Snow Memorandum co-signer who frequently appears in the UK media to advocate the fringe “Zero Covid” strategy (the same one that claims we need more lockdowns to prevent future lockdowns, apparently unaware of the contradiction that entails). Attempting to explain why her own lockdown approach did not work, Sridhar wrote on January 5th that “Chancellor Sunak invited Heneghan, Gupta & Tegnell to advise on strategy. That says it all.”
Other variants of the same conspiracy theory permeate the UK’s pundit ranks. Far-left Guardian columnist Owen Jones repeated it in a December column targeting Sunak and the scientists for allegedly delaying the lockdowns until it was “too late to bring coronavirus rates down to anywhere near the level needed to suppress the virus.”
A little over a month later, Sam Bowman, a right-leaning self-described “neoliberal,” penned an almost identical argument to Jones in the same newspaper, writing “Sunak was reported as having been the decisive voice in government against an autumn lockdown that might have brought cases low enough to make things like test-and-trace viable,” all because of “Sunetra Gupta, Carl Heneghan and Anders Tegnell being invited to speak via Zoom at Downing Street.”
Note that none of these commentators are even willing to consider the possibility that lockdowns do not deliver on their promises, or that Britain’s dismal performance under the policies they advocated is a direct testament to their failure as public health measures. The validity of lockdowns has become an axiom to them, and the only conceivable reason they do not work must be some form of malfeasance preventing them from working the way the epidemiology models claim they should. Sunak and the three dissenting scientists accordingly became a natural scapegoat for Britain’s dismal public health performance over the winter months.
Is there even a kernel of truth behind the lockdowner’s UK conspiracy theory? Gupta, Heneghan, and Tegnell did meet with Downing Street via Zoom on September 20th to voice their opposition to lockdowns in general – a position they have consistently held throughout the pandemic. Unfortunately, as Gupta has explained and as the next four months repeatedly demonstrated, the Prime Minister largely ignored their advice.
The conspiracists’ alleged “smoking gun” is a series of minutes from the UK government’s SAGE advisory committee on September 21st, which included a “circuit-breaker lockdown” among a “short-list” of policies “that should be considered” in response to rising Covid-19 cases. Apparently in their minds, being “considered” equates to adoption, and the fact that Johnson did not lock down the very next day is proof that the dissenting scientists had wrested the reins of the UK’s pandemic policy from those who advocated lockdowns, delaying the necessary response until November 5th after which it was too late.
There are multiple immediate problems with this narrative. First off, Wales tried a “circuit breaker” lockdown that almost exactly followed the proposal being considered by the SAGE committee, announcing it on October 19 and implementing it a few days later. Although it had a lead of almost two weeks before the rest of Britain went into lockdown in November, Wales’s per capita case numbers followed the same trajectory as the rest of the country, including the sharp spike in late December and early January. Far from working as intended, Wales’s “circuit breaker” lockdown only slightly shifted the timing of this pattern. Its maximum daily peak of 87 cases per 100,000 residents nearly matched England’s peak of 96, and its curve for Covid-19 fatalities followed the same pattern as the rest of Britain.
Equally telling, a number of the conspiracy theory adherents themselves were singing a very different tune when these events were unfolding. Gurdasani, Sridhar, and other lockdown advocates of the John Snow Memorandum crowd want you to believe that they were patiently counseling the government to adopt an early lockdown between the end of September and mid-October, only to see their advice deflected by Downing Street due to the interference of Gupta and the other dissenting scientists. The record reveals a very different story.
On September 24, only three days after the SAGE meeting minutes, an interesting editorial appeared in the leading British medical journal. Written by Karl Friston, a frequent collaborator with Gurdasani and fellow John Snow Memorandum organizer, the editorial advocated a “third way beyond lockdown or herd immunity” premised on implementing a contact tracing regime over the next few weeks. Far from raising alarms about the immediate need for another lockdown, Friston attempted to assure calm.
“We have already developed a substantial population immunity (around 8% in the UK) and our physical distancing policies remain adaptive and effective,” he explained, arguing that a contact tracing regime could synergistically harness and augment their effectiveness. As far as the fall case surge went, he predicted a comparatively mild trajectory: “When one models what is likely to happen…in terms of viral spread and our responses to it—a plausible worst-case scenario is a peak in daily deaths in the tens (e.g., 50 to 60) not hundreds, in November.” As it happens, the UK topped 400 deaths per day during the November lockdown, and surged to 1,200 deaths per day at the peak of the January lockdown.
Just over two months later, Friston joined Gurdasani and several other Snow Memorandum signers in an letter to the Lancet that blamed the UK’s second wave on failing to heed pro-lockdown advice that they now claimed as their own, even as it conflicted with their public messaging from September that downplayed the very same recommendation. Writing in hindsight and with a liberal amount of revisionism, they recast themselves as proponents of an earlier lockdown all along: “On Sept 21, 2020, the Scientific Advisory Group for Emergencies (SAGE) advised the UK Government to institute a circuit breaker in England to suppress the epidemic. Instead, the government opted for several weeks of ineffective local tiered restrictions, and cases continued to rise exponentially.”
A similar messaging came from the “Independent SAGE” group – a private organization of scientists who now generally support the lockdown approach, but also spent the early fall advocating less-restrictive measures that would supposedly avoid another lockdown. On September 20th, the same day that Gupta and the other scientists met with Downing Street, the Independent SAGE group (not to be confused with the official SAGE group despite their shared name) released a 10-point plan “to avoid a national lockdown.”
The scheme warned of a point “when the situation is so far out of control that the only possible response will be a second national lockdown,” but advised “we can only avoid it if we take urgent action” as recommended by the group. They sought a variety of restaurant restrictions limited to outdoor dining, plus the same testing and contact tracing programs espoused by Friston. Six months later, Independent SAGE member Kit Yates is now faulting the anti-lockdown scientists for Johnson’s failure to implement a policy last September that his own group purported to oppose and sought to forestall.
Indeed, what we see when we look to the words of these lockdowner scientists and pundits is nothing short of a conscious attempt to rewrite their own positions from the time period when the conspiracy theory that they’ve now adopted was allegedly playing out. As I documented last fall, the overwhelming media narrative from late September and early October explicitly deflected attention away from the prospect of a second lockdown. Scientists such as Gupta, Heneghan, and the Great Barrington Declaration (GBD) signers, they vigorously maintained, were arguing with a “strawman” of renewed lockdowns that nobody was seriously proposing or considering anymore.
A typical version of this narrative appeared inWired UKon October 7th as part of a media attack on the GBD. “The kind of lockdown that the Great Barrington Declaration seems to be railing against hasn’t been in place in the UK since mid-June,” argued the magazine’s science editor Matt Reynolds. Even in UK cities that were under local restrictions, “pubs, restaurants and schools are still open and it’s hard to find people who are advocating for a return to the lockdown we saw in March.” Reynolds continued: “When the Great Barrington Declaration authors declare their opposition to lockdowns, they are quite literally arguing with the past.”
Similar messages appeared throughout the UK media at the time, each insisting that lockdowns were no longer on the table. On October 11th, Guardian columnist Sonia Sodha wrote “The [Great Barrington] declaration sets itself up against a straw proposal that nobody is arguing for – a full-scale national lockdown until a vaccine is made available.” By October 30th, Sodha was already contradicting herself and revising her own history, tweeting “Wish we’d had a circuit breaker lockdown when SAGE first recommended it.” By mid-December, she was touting the conspiracy theory about Gupta, Heneghan, and Tegnell’s Zoom meeting with Downing Street. More recently, she’s become an advocate of de-platforming the same scientists from British media channels for their anti-lockdown heresies.
Sridhar’s own navigation of the lockdown question followed a similar course. Although she now chastises opponents of the “circuit breaker” lockdown proposal from the events of September 20-21 and faults them for Britain’s second wave, Sridhar wrote a bizarre op-ed in the Guardian on October 10th purporting to oppose “continual lockdowns.” Much like the Zero Covid messaging she would later adopt, its argument is confused and self-contradictory, meandering from touting the model of Taiwan, which never locked down, to New Zealand, which continues to use aggressive lockdowns to suppress even the slightest outbreak. But it also sought to signal her opposition to the specter of renewed lockdowns, which could be avoided – she insisted – by adopting less-stringent localized restrictions and an extensive contact tracing regime.
Sridhar would doubtless insist that her own re-adoption of lockdown advocacy about a month later arose from a failure to heed her earlier advice, as opposed to a more fundamental error with the lockdown approach. Even then, it’s difficult to square her mid-October position with her newfound claim to have recognized the wisdom of a national lockdown some 2 to 3 weeks earlier than the October 10th op-ed, only to see it derailed by the scientists who spoke to Downing Street. Like the Independent SAGE group’s September 20th manifesto, Sridhar was either far less attached to a second lockdown at that point in time than she now insists, or she was engaging in deception about her intentions.
The most astounding attempt at revisionism, however, came from Gurdasani – the Snow Memorandum organizer who has since tried to scapegoat the UK’s Covid failures on Gupta, Heneghan, and Tegnell over the September Zoom conference. She now depicts herself as an early lockdown advocate whose advice from September was shoved aside and ignored. Yet as late as October 26, Gurdasani was still pushing the same “lockdowns are a strawman” line that had dominated the previous month of UK media coverage.
Writing for the Byline Times, a London-based blog that has pushed multiple unhinged conspiracy theories of its own about the Great Barrington Declaration, Gurdasani described lockdowns as “a strawman that the science is not only not advocating for, but very keen to avoid.”
Gurdasani was in the middle of a publicity campaign for the John Snow Memorandum at the time, its own language having been carefully crafted to present its recommendations as a strategy “to prevent future lockdowns” by relying on nondescript localized “restrictions” and a contact tracing regime. As Gurdasani and another Snow Memorandum signer told the Byline Times’ readership, “Unfortunately, the proponents of herd immunity have had a huge impact on responses to the pandemic, effectively creating the lockdown strawman,” insisting that this presented a “dangerous false dichotomy.”
With Gurdasani stressing that she was keen to avoid future lockdowns – a “strawman” in her own words – as late as October 26th, one begins to wonder how she could have supported the very same “strawman” over a month earlier on September 20th, the date on which the dissenting scientists allegedly wrested control of the UK’s pandemic response. Perhaps the lockdowners’ latest conspiracy theory has another as of yet undisclosed twist to it, this one involving a time machine.
April 2, 2021
Posted by aletho |
Deception, Mainstream Media, Warmongering, Science and Pseudo-Science | Covid-19, UK |
Leave a comment


