Fact checking the Radio New Zealand fact check
COVID Plan B | November 17, 2021
Radio New Zealand has recently criticized a Facebook live conversation between former National MP Matt King and epidemiologist Dr Simon Thornley. While people should undertake their own research, we provide some comments related to the media’s critique. The evidence related to covid-19 policy continues to change and be updated.
In the interview, Professor Rod Jackson made several claims, decrying Thornley personally during the interview. Let’s examine them in turn.
- “There is no trial evidence that ivermectin [an anti-parasitic drug used as early treatment for covid-19 in some parts of the world] works in people with Covid – it doesn’t exist.”
Trials do exist. In fact a meta-analysis or summary study of six such trials exist. The pooled effect of these trials is a 79% decline in all-cause mortality (95% confidence interval: 89% to 58%). These trials are from Iraq, Iran, Bangladesh, Egypt, Turkey and India, places less reticent about its use. But they are trials, and the reduction in all-cause mortality is stark, an endpoint which is generally considered clinically important and free of error and bias. Another trial points to effective treatment, such as from vitamin D supplementation, which reduced intensive care admissions to 1/50 (2%) in the treated from 13/26 (50%) in the untreated in Spanish covid-19 patients.
We’re not advocating ivermectin at all. But we are prepared to look at the evidence. The fact that Jackson didn’t know there were trials invalidates his point.
- “Professor Jackson also said claiming Covid-19 was no worse than the flu was nonsense”.
In the interview, Thornley claimed the infection fatality rate of covid-19 was as bad as a ‘severe flu’. A summary study of many countries indicates that the average global infection fatality rate of covid-19 is 0.15% or 1/667 people.
The fatality rate for H1N1 influenza is variable, but this figure from covid-19 is well within the range of estimates presented from a similar summary study.
The comparison between covid-19 and flu is therefore fair and accurate. Jackson’s claim is misinformation.
We should note that many fatality studies take the definition of a covid-19 death at face value but it does not mean the individual died exclusively from the virus. This was exemplified by the counting a recent covid-19 death in a man who was actually shot and killed, yet tested positive for SARS-CoV-2 during the autopsy. This was defended by the Ministry of Health, as it conformed with World Health Organization policy.
We are able to test the accuracy of Jackson’s claimed fatality risk. In May 2020, Jackson admonished Sweden for its lax approach. He said the fatality rate of covid-19 was 1/100 people infected, so predicted 56,000 deaths from covid-19 in the country, assuming 60% of the population would be infected. To date, there have been about 15,000 covid-19 deaths, with an age distribution similar to that of background deaths (figure). In fact, by all accounts, Sweden has fared through the epidemic particularly well compared to other European countries.
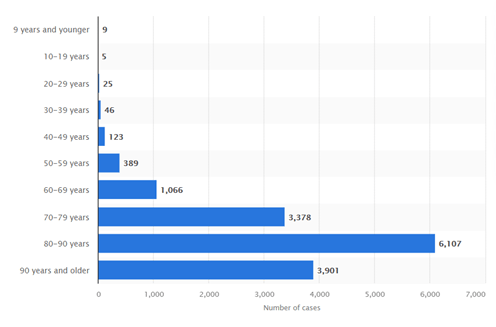
Figure. Deaths with covid-19 in Sweden, by age at November 3, 2021. Source: statistica.com
- “This is a severe disease and we have a evidence-based treatment [the vaccine] where there is definitive evidence that it reduces the risk of severe disease and death by 95 percent, in that order.”
This is an extraordinary claim for several reasons. First, the original Pfizer trial reported about the same number of overall deaths in the treated and the untreated groups (14 in the treated and 13 in the untreated). In the six-month trial results, only three covid-19 deaths occurred, one in the treated and two in the untreated group. This is not consistent with Jackson’s assertion of a 95% reduction in risk of severe disease and death.
Given the numbers of deaths in the original trial, it is possible to work out whether the trial would have picked up a 95% reduction as Jackson claims. The trial would have been expected to have only one death in the treated group, and would have detected a difference more than expected by chance with 96% certainty.
There is observational evidence from Sweden of reduced covid-19 hospitalisations and deaths (not from all-causes), however, the vaccine effect diminished to zero for all three outcomes eight months after the date that the vaccine was administered.
To compound the confusion about the effect of the vaccine, the original Pfizer trial now is marred by whistle-blowers who have given the British Medical Journal evidence of fraud occurring during its conduct. Sixteen Swedish doctors have now called for the injection to be suspended as a result of these revelations.
Both Jackson and RNZ use extensive use of ad hominem attacks, which are considered an invalid, and lowest, form of argument.
Examples include:
- “anti-vax”
- “discredited academic”
- “And we have someone who is questioning that evidence, who doesn’t know what they’re talking about, talking to an epidemiologist who doesn’t know what he’s talking about.”
- “outlier in his field”.
The purveyors and writers of such ‘argument’ appear to have no embarrassment at the anti-intellectualism and inhumanity of their conduct.
We’ll stick to the contest of ideas by again considering Jackson’s accuracy. Back in August 2020, Jackson and his colleagues claimed that elimination was still the best strategy for New Zealand to tackle covid-19. That article has not dated well, yet the personalised tirade and arguments are familiar.
“He [Thornley] is the only dissenter in the epidemiological community,”
“It’s not like this is a discussion like a boxing match with two equal partners. What you’ve got is every experienced epidemiologist in the country supporting the Government’s elimination approach.”
“We are all advising the Government, and we speak with one voice. And you have got a junior epidemiologist who is presenting a different case.”
Jackson has made increasingly inaccurate claims during the pandemic, claiming, unchallenged that one in five infected people will be hospitalised after infection with covid-19. No media have ever fact checked this.
New Zealand’s own government data shows Jackson overestimated by at least a factor of ten, since the proportion of cases (rather than infections) hospitalised is 2% (table).
Table. Counts of cases of covid-19 in New Zealand (16 November 2021).
| Count | % | |
| Self-isolation | 2058 | 56% |
| Isolation Complete | 969 | 26% |
| Managed Isolation | 396 | 11% |
| Hospital | 73 | 2% |
| Other | 198 | 5% |
As sailing great Russell Coutts has recently pointed out, it is questionable how “media entities can maintain objectivity when they have accepted a government grant that is conditional on them promoting certain government policies”.
It is prudent to check all sources of information, not only those who dare to question the what is coming from the Beehive.
More people died in the key clinical trial for Pfizer’s Covid vaccine than the company publicly reported
By Alex Berenson | November 16, 2021
On July 28, Pfizer and its partner BioNTech posted a six-month data update from their key Covid vaccine clinical trial, the one that led regulators worldwide to okay the shot.
At a time when questions about vaccine effectiveness were rising, the report received worldwide attention. Pfizer said the vaccine’s efficacy remained relatively strong, at 84 percent after six months.
It also reported 15 of the roughly 22,000 people who received the vaccine in the trial had died, compared to 14 of the 22,000 people who received placebo (a saline shot that didn’t contain the vaccine).
These were not just Covid deaths. In fact, they were mostly not from Covid. Only three of the people in the trial died of Covid-related illnesses – one who received the vaccine, and two who who received the saline shot. The other deaths were from other illnesses and diseases, mostly cardiovascular.
Researchers call this datapoint “all-cause mortality.” Pfizer barely mentioned it, stuffing the details of the deaths in an appendix to the report.
But all-cause mortality is arguably the MOST important measure for any drug or vaccine – especially one meant to be given prophylactically to large numbers of healthy people, as vaccines are.

(Appendix to “Six Month Safety and Efficacy of the BNT162b2 mRNA COVID-19 Vaccine,” SOURCE https://www.medrxiv.org/content/10.1101/2021.07.28.21261159v1.supplementary-material)
Although the researchers released their update in July, the data was already more than four months old. They had stopped collecting information about deaths as of March 13, the “data cut-off.”
But even at the time, their figures were somewhat troubling.
In their initial safety report to the FDA, which contained data through November 2020, the researchers had said four placebo recipients and two vaccine recipients died, one after the first dose and one after the second. The July update reversed that trend. Between November 2020 and March 2021, 13 vaccine recipients died, compared to only 10 placebo subjects.
Further, nine vaccine recipients had died from cardiovascular events such as heart attacks or strokes, compared to six placebo recipients who died of those causes. The imbalance was small but notable, considering that regulators worldwide had found that the Pfizer and Moderna mRNA vaccines were linked to heart inflammation in young men.
(I reported accurately on this study on Twitter on July 29, and the next day Twitter suspended me for a week for doing so, the fourth of my five defamatory “strikes” for Covid “misinformation.”)
At best, the results suggested that the Pfizer/BioNTech vaccine – now pushed on nearly a billion people worldwide at a cost of tens of billions of dollars and ruinous and worsening civil liberties restrictions – did nothing to reduce overall deaths.
Worse, Pfizer and BioNTech had vaccinated almost all the placebo recipients in the trial shortly after the Food and Drug Administration okayed the vaccine for emergency use on Dec. 11, 2020.
As a result, they had destroyed our best chance to compare the long-term health of a large number of vaccine recipients with a scientifically balanced group of people who had not received the drug. The July 28 report appeared to be the last clean safety data update we would ever have.
But now the FDA has given us one more.
On November 8, the agency released its “Summary Basis for Regulatory Action,” a 30-page note explaining why on August 23 it granted full approval to Pfizer’s vaccine, replacing the emergency authorization from December 2020.

SOURCE: https://www.fda.gov/media/151733/download
And buried on page 23 of the report is this stunning sentence:
From Dose 1 through the March 13, 2021 data cutoff date, there were a total of 38 deaths, 21 in the COMIRNATY [vaccine] group and 17 in the placebo group.
Pfizer said publicly in July it had found 15 deaths among vaccine recipients by mid-March. But it told the FDA there were 21 – at the same data cutoff end date, March 13.
21.
Not 15.
The placebo figure in the trial was also wrong. Pfizer had 17 deaths among placebo recipients, not 14. Nine extra deaths overall, six among vaccine recipients.
Could the discrepancy result from some odd data lag? Maybe, but the FDA briefing book also contains the number of Covid cases that Pfizer found in vaccine recipients in the trial. Those figures are EXACTLY the same as those Pfizer posted publicly in July.
Yet the death counts were different.
Pfizer somehow miscounted – or publicly misreported, or both – the number of deaths in one of the most important clinical trials in the history of medicine.
And the FDA’s figures paint a notably more worrisome picture of the vaccine than the public July numbers. Though the absolute numbers are small, overall deaths were 24 percent higher among vaccine recipients.
The update also shows that 19 vaccine recipients died between November and March, compared to 13 placebo recipients – a difference of almost 50 percent.
Were the extra deaths cardiac-related? It is impossible to know. The FDA did not report any additional details of the deaths, saying only that none “were considered related to vaccination.”
But with tens of thousands of post-vaccine deaths now reported in the United States and Europe – and overall non-Covid death rates now running well above normal in many countries – a fresh look at that vague reassurance cannot happen soon enough.
Alex Berenson is a former New York Times reporter and the author of 13 novels, two non-fiction books and the Unreported Truths booklets.
Why is the US Hyping Up the Threat of ISIS in Afghanistan?
By Valery Kulikov – New Eastern Outlook – 16.11.2021
To justify its interventionist actions in the Middle East, the United States, following the now cliched example, actively uses its alleged commitment to fighting against terrorism, focusing on countering such well-known terrorist formations as Al Qaeda and ISIS. The same goes for the actions of the USA in Afghanistan. However, Washington didn’t take any accountability before the rest of the world about the results of this fight against terrorists in Afghanistan during its 20 years of abysmal military intervention.
At the same time, the Russian presidential envoy to Afghanistan Zamir Kabulov and foreign ministry spokeswoman Maria Zakharova mentioned several times that Russia has sufficient facts backing the claims about the USA’s cooperation with the ISIS militants in the northern part of Afghanistan. In particular, since 2017, unmarked helicopter flights have been recorded within areas of ISIS militant activity, not without the explicit knowledge of US and NATO forces in their area of responsibility, especially in northern Afghanistan… According to Afghan sources, these aircraft have been used to deliver manpower, weapons, and ammunition to ISIS militants. Moreover, there were recorded instances of surgical strikes by the US Air Force not against terrorists, but positions of radical Taliban fighters engaged in combat against ISIS.
After the termination of the US military intervention in Afghanistan in August this year under the pressure of the international public and Americans themselves, certain American politico-military circles, clearly dissatisfied with this step, started to spin the propaganda campaign about the allegedly intensified in recent months “danger of ISIS activity in Afghanistan” through their lackey media. With the apparent hope of triggering a new international armed aggression in Afghanistan, again under “US patronage.”
Thus, on September 28 this year, General Mark A. Milley, Chairman of the Joint Chiefs of Staff, announced the supposedly obvious danger of strengthening of Al-Qaeda and ISIS positions in Afghanistan: “And we must remember that the Taliban was and remains a terrorist organization, and they still have not broken ties with al-Qaeda. I have no illusions about who we are dealing with.” “A reconstituted al-Qaeda or Daesh/ISIS with aspirations to attack the US is a very real possibility,” General continued.
The allegedly growing threat of ISIS in Afghanistan has recently been actively picked up by the American media, handy to the current military and political elite. In particular, recently The New York Times began to scare the world with stories that, since the Taliban came to power, ISIS militants in Afghanistan have intensified, their terrorist attacks are exhausting the new government and raising fears among Western powers of a potential revival of the group. During his speech in Congress, US Undersecretary of Defense for Policy Colin Kahl admitted that the ability of Afghan authorities to combat the Islamists “has yet to be determined.” However, he did not say anything about who and when will determine the results of 20 years of fighting them by the United States itself.
The New York Times acknowledged that, after its disgraceful flight from Afghanistan in August, Washington had lost reliable access to intelligence. Limited drone flights now provide only partial information given the distance they need to travel to reach Afghanistan, and its established network of informants has been destroyed.
However, the real reason behind Washington’s new propaganda wave regarding the allegedly heightened threat of ISIS from Afghanistan becomes apparent in one of the final paragraphs of the article published by this newspaper. It states that the Taliban “refuse to cooperate with the United States in fighting ISIS by fighting the war on their terms.”
As for the organization of today’s fight against ISIS, Dr. Bashir, head of the Taliban’s intelligence services, has directly pointed out that such work is constantly being done, and his men have adopted the methods of this fight from their predecessors. Moreover, they even rely on Western equipment to intercept messages and radio communications. He insists, however, that the Taliban have something the past government and the Americans did not have: widespread local support that can alert authorities to attacks and militant positions, something that has always been hard to detect in the past.
As for some Western propagandists who attempt to use the thesis about the alleged merger of the Taliban with ISIS terrorists at the instigation of Washington, keep in mind that ISIS does not have such a strong influence in Afghanistan as the Taliban, and they are seen as antagonists in the country. The fact is that ISIS relies on Salafi ideology, while most Afghans identify themselves with the Hanafi school of fiqh. Therefore, the organization is a foreign body in the structure of Afghan society, which undoubtedly limits its growth of influence and popularity in the country.
As you know, ISIS announced the formation of the group in Iraq in 2014. Then came the ISIS affiliate in Pakistan. As for Afghanistan, a branch of ISIS emerged here in January 2015 under the Islamic State – Khorasan Province, which later the Tehrik-e Taliban Pakistan joined with. In 2015, several regional media reports revealed that the National Directorate of Security (NDS), under complete US control, had helped ISIS gain a foothold in Nangarhar province. There have also been reports that some leaders of the Afghan branch of ISIS, including Sheikh Abdul Rahim Muslim Dost (a former Guantanamo Bay detainee!), traveled in Afghan intelligence vehicles and lived in guesthouses belonging to Afghan intelligence agencies. Therefore, some analysts accuse US intelligence services of involvement in creating and strengthening ISIS in Afghanistan.
At a certain point, the Taliban viewed ISIS as temporary “allies” fighting against US intervention within Afghanistan. However, after ISIS demanded that Taliban leaders swear allegiance to Abu Bakr al-Baghdadi, clashes broke out between the Taliban and ISIS, especially in Nangarhar province. Notably, after such clashes broke out, government helicopters rescued ISIS fighters besieged by the Taliban in some areas, such as Jawzjan province. In particular, Afghan army helicopters supported by US forces evacuated ISIS fighters and their families and housed them in guesthouses in Sheberghan, Jawzjan province, belonging to Afghan intelligence. Afghan intelligence agencies implicitly acknowledged this.
The estimated number of ISIS fighters in Afghanistan is 5,000. A UN report released in mid-July said the number of ISIS fighters in Afghanistan ranges from 500 to 1,500. Currently, ISIS does not possess heavy weapons, guns, and tanks, even though such equipment was abandoned in large numbers by the US army after fleeing Afghanistan, and has no centers, headquarters, or open fronts on Afghan soil. In these circumstances, ISIS can gain a foothold in Afghanistan only if some foreign patrons support it with people, arms, and money to use this organization to weaken the Taliban’s power and turn Afghanistan into a new breeding ground for terrorism. And here, one cannot rule out such actions precisely on the part of the United States and its Western allies. For example, Washington has done it before by supporting al-Qaeda in Afghanistan in its confrontation with the Soviet Union.
In a sense, former Afghan army and Afghan intelligence officers trained in the United States, who had already joined ISIS in Afghanistan in August after the US fled Afghanistan, could be used by the United States to manipulate ISIS. Their numbers, as admitted by The Wall Street Journal, “are still relatively small, but they are growing, according to those who know these people, and also according to Afghan and Taliban intelligence agencies.”
Today, the Taliban control the entire country and view ISIS as a foreign group to be fought and wholly expelled from Afghanistan. As for the restraints the Taliban has towards carrying out joint counter-terrorist actions against ISIS, confirmed by the Taliban on October 11 at the meeting with the Americans in Doha, one cannot rule out that it was Washington’s former ties with ISIS that could lie behind such a position of the current rulers of Afghanistan.
False imagery and data hallmarks of COP26

By Vijay Jayaraj | CNS News | November 12, 2021
Mainstream media is infamous for its exaggeration of everyday events. When it comes to the issue of climate change, it rarely misses an opportunity to promote fear. True to form, during the COP26 climate conference in Glasgow, media promoted incorrect information spewed by politicians and famous personalities.
Special attention was drawn to the assertion that rising sea levels are threatening island nations by none other than Barack Obama, who incongruously has purchased a multi-million-dollar ocean front property on the New England coast.
Catching the attention of millions was the image of a Tuvalu minister standing in knee-high sea water. But there is a problem with this: Most islands in the South Pacific nation of Tuvalu have gained surface area and are in no danger of being inundated.
Despite sea-level rise that has been underway since the end of the last ice age, Tuvalu’s land area has increased recently by 2.9 percent. A peer-reviewed research paper which studied four decades of shoreline change in all 101 islands in theTuvalu atolls categorically proves this. The paper notes that “…change is analyzed over the past four decades, a period when local sea level has risen at twice the global average (~3.90 ± 0.4 mm.yr−1). Results highlight a net increase in land area in Tuvalu of 73.5 hectares (2.9%) despite sea-level rise and land area increase in eight of nine atolls.”
The case of Tuvalu is not unique. Various island nations have gained landmass in recent decades, including Maldives which increased by 37 square kilometers since 2000.

(Getty Images)
The climate doomsday machine has been using this image-based propaganda for a while now. National Geographic circulated an image of a starving polar bear and falsely claimed that the bear’s condition was a direct result of man-made climate change. However, polar bear populations are relatively healthy and have increased in recent decades. When exposed, the famous media channel issued a statement saying that the reason for the dismal condition of the bear is unknown and that it had exaggerated the climate impact.
At COP26, Bill Gates joined climate elites who resorted to a false representation of reality to promote climate fear. “Farmers in low-income countries are at high risk from the impacts of climate change,” said Gates. But a closer look at weather data and the state of global agriculture reveals a different picture.
The United Nations makes clear that there is no strong evidence that climate change is having a significant influence on the frequency of extreme weather events. IPCC AR5 WGI Chapter 2 states, “In summary, there continues to be a lack of evidence and thus low confidence regarding the sign of trend in the magnitude and/or frequency of floods on a global scale.” When it comes to droughts, the report states that “… there is not enough evidence at present to suggest more than low confidence in a global-scale observed trend in drought or dryness (lack of rainfall) since the middle of the 20th century.”
Consider India, a country with world’s largest number of low-income farmers. More than 500 million people depend either on agriculture or allied products. Of that total, 150 million depend only on agriculture — the equivalent of 40 percent of the U.S. population.
These farmers — with an average monthly income of less of $120 — depend on monsoon rainfall and there has been no climate signature on the monsoon rainfall trend. Nor has there been any increase in cyclones. In other words, there has not been any increased risk from climate change for India’s farmers. Another indicator of the absence of heightened risk is crop production. For four consecutive years, India has produced record food crops, higher than ever before in its history.
You would think that Gates would know something about agriculture and climate given that he owns 242,000 acres of U.S.farmland and said to be the largest private owner of such acreage. However, it appears that the billionaire is at best ill-informed.
Though fancying themselves to be noble defenders of nature, these purveyors of doomsday scenarios are more akin to a cult’s priesthood offering commoners salvation in exchange for prosperity and freedom.
Vijay Jayaraj is a Research Associate at the CO2 Coalition, Arlington, Va., and holds a Master’s degree in environmental sciences from the University of East Anglia, England. He resides in Bengaluru, India.
Here’s the real reason Comirnaty is not available
It’s all about liability. It will magically become available when the vaccine for children is fully approved, not before.
By Steve Kirsch | November 3, 2021
The reason Comirnaty isn’t available is because those shots would expose the company to liability since the fully-licensed product doesn’t have the liability waiver of the EUA product.
But once the Pfizer vaccine is fully approved in kids, then Pfizer gets liability waiver on all age groups due to a “feature” in federal law for child vaccines (NCVIA). At that time, they are done. They can market the COVID vaccine products under full approval for all age groups and face no liability when it kills or disables you.
This is why they are focused on the kids. This is why there is a reformulation at a 1/3 dose and they changed the buffer and the storage conditions (low temperatures not required). All of these will weaken the protection, but result in a safer vaccine (since it is ineffective).
But for the clinical trials on the 5-11 year olds, they did not use the formulation they approved in the meeting. This is known as bait and switch. So they used a more effective vaccine to show efficacy (in the trials they completed), then they get the FDA to approve the drug but with a change in formulation, then the product with the new buffer will go out to the public with the lower efficacy, but better safety. This is because they don’t want to jeopardize any adverse events happening until they are fully approved. So they basically use formula 1 for safety, get approval for formula 2 (safer, less effective), then roll out formula 2 under EUA.
They also arrange with the FDA and CDC to make sure no early treatment drugs get approved or recommended. This is why there is no movement on fluvoxamine, ivermectin, etc. since that would blow the EUA. Fluvoxamine is the best drug ever for COVID with a mortality reduction of 12X when taken early. It’s the best drug to date for COVID, but the CDC and NIH are deliberately burying it until the vaccines are fully approved. Then they’ll say, “ok, we have all the data.”
So at the end, Pfizer gets a fully approved vaccine with full liability protection. At that time, then the NIH can recognize other treatments.
This is how it is wired to go. Let’s be honest about it.
This is why nobody wants to debate our team about what is going on.
CDC Redefined Vaccine to Support Deficient Fake Vaccines Sold by Drug Companies
By Joel S. Hirschhorn | November 14, 2021
The CDC once was a federal agency that nearly everyone respected. That no longer is the case. Now there are many reasons why the CDC should be widely disrespected. Its latest debacle is how it changed the definition of vaccine.
Just imagine this: The entire push for COVID “vaccines” was based on a lie – they did not meet the official CDC definition of a vaccine. By doing this, the government could coerce the entire population to get the shot. Calling them “vaccines” was the biggest lie from Fauci and the key to drug companies making many billions of dollars.
Why would the government’s key public health agency change the definition of what a vaccine is in the midst of a pandemic? After millions of Americans have taken the shot? And millions more are being beaten into taking it for the first time and others to get booster shots.
Words matter
Here is the key point. It became widely recognized by medical experts and informed citizens that COVID vaccines clearly did not fit the official CDC vaccine definition. The CDC thought the answer was not to fix what was deficient with the COVID vaccines or stop their use by most people as so many medical experts advised. Their response was to change the vaccine definition to fit the so-called vaccines.
This was done so that vaccine mandates could keep getting pushed by the government. Of course, the COVID “vaccines” should be referred to as gene therapy products, even better than calling them experimental vaccines.
To see how corrupt this action by the CDC was, it is necessary to examine the details of the vaccine definition debacle.
Prior to September 1, 2021 here is how CDC defined vaccine:
A product that stimulates a person’s immune system to produce immunity to a specific disease, protecting the person from that disease. Vaccines are usually administered through needle injections, but can also be administered by mouth or sprayed into the nose.
This definition had been used for years and it makes sense. No expert or sensible citizen would find fault with it. But did it honestly apply to the COVID vaccines?
Then this is what the CDC concocted:
A preparation that is used to stimulate the body’s immune response against diseases. Vaccines are usually administered through needle injections, but some can be administered by mouth or sprayed into the nose.
Here is what the CDC also said:
Immunity: Protection from an infectious disease. If you are immune to a disease, you can be exposed to it without becoming infected.
Think about that last sentence: You can be exposed to COVID without being infected; but we know that is not true for fully vaccinated people who still get infected.
This is the key language in the original definition:
“stimulates a person’s immune system to produce immunity to a specific disease, protecting the person from that disease.”
How rational to invoke the purpose of a vaccine to stimulate an immune system to produce immunity to a specific disease that protects the recipient from that disease. Exactly what everyone for years thought was the correct way to think about a vaccine. People want permanent protection from the COVID infection disease.
But now the CDC has taken out the language referring to getting immunity for a specific disease and getting protection from that disease.
Now, COVID vaccines do not have to directly produce immunity. No, now they only have to stimulate the body’s immune system.
You don’t get immunity because COVID vaccines do not directly produce immunity. They do not directly kill the COVID virus. Vaccinated people can still have high viral loads and also transmit the virus to others. While some individuals may get some health benefits from COVID shots, they do not necessarily protect the entire population. This is why mandates to get everyone the shots really do not make sense from a public health perspective, that Dr. Paul Alexander has well substantiated.
Apparently, the only logical way to understand what the CDC has done is to accept the truth belatedly seen by the CDC that COVID vaccines do not, in fact, produce effective immunity for COVID infection and do not provide effective protection, once vaccinated, from that infection.
Much of the public surely does not yet know what the CDC has acknowledged for the COVID vaccines. Odds are that everyone who depends on mainstream media for good information about the pandemic has not been informed about what the CDC has done and its implications.
The new vaccine definition, if publicly known, would reduce public confidence in current COVID vaccines. You don’t have to be a medical expert to see how the new definition has been created to accommodate COVID shots.
In fact, these definition changes reflect what is now known about the limitations of the COVID vaccines.
Fully vaccinated people can still get COVID disease, referred to as breakthrough infections that, contrary to what the government says, can be very serious, often requiring hospitalization and sometimes causing death, as was the case for Colin Powell. Such serious effects have been well discussed by Dr. Günter Kampf. Other times, breakthrough infections greatly disrupt lives, as recently described by Madrigal, a strong proponent of COVID shots.
Moreover, the COVID vaccines are now widely known from considerable clinical evidence to lose their effectiveness typically in about six months. And even worse, they do not provide hardly any protection against variants like the delta variant. Same disease but from a different virus in terms of its complex genetic makeup. So, befitting the new CDC definition the COVID shots really do not have long lasting effective immunity to the specific COVID infection caused by all variants.
Elsewhere on the CDC website is a glossary of many terms; here is what is especially relevant to the debate about COVID vaccines:
Attenuated vaccine: A vaccine in which a live microbe is weakened (attenuated) through chemical or physical processes in order to produce an immune response without causing the severe effects of the disease. Attenuated vaccines currently licensed in the United States include measles, mumps, rubella, varicella, rotavirus, yellow fever, smallpox, and some formulations of influenza, and typhoid vaccines.
Most people would read this and find that it fits with what they think of as vaccines that have been routinely taken by most people, especially children. Clearly, COVID vaccines do not fit this definition. But seeing this established view of vaccines helps explain why so many people resist and reject the COVID shots. They are so fundamentally different than long accepted and used vaccines.
Natural immunity
One of the biggest pandemic scandals is that the government refuses to give full credit to natural immunity that people get from once being infected by the COVID virus. It should be officially recognized as equivalent to “vaccine” immunity.
The following CDC glossary definition is especially relevant:
Active immunity: The production of antibodies against a specific disease by the immune system. Active immunity can be acquired in two ways, either by contracting the disease or through vaccination. Active immunity is usually permanent, meaning an individual is protected from the disease for the duration of their lives.
This CDC definition of active immunity recognizes that you can get it by contracting the disease versus through vaccination. In other words, it recognizes what today is commonly called natural immunity achieved by once being infected by the COVID virus. And that such immunity is likely permanent and better than vaccine immunity, as recent clinical studies substantiate. But it also infers that active immunity obtained through vaccination is also permanent, which clearly is not the case for COVID shots, as evidenced by breakthrough infections.
Also note that it has recently been revealed that the CDC has not been able to provide any proof of at least one instance of an unvaccinated, naturally immune individual transmitting the COVID-19 virus to another individual.
And a new study found that almost 60 percent of the people with antibodies had no idea they had even had COVID at all. But they would have natural immunity. Quite consistent with the reality that most people suffer no significant health impacts from being infected with the COVID virus, regardless of all the fear mongering by Fauci and others.
Conclusions
To sum up, a close look at what the CDC has done lately reinforces the thinking of millions of people who have reservations and concerns about getting COVID genetic therapy shots that pose myriad adverse impacts and sometimes death.
There is a rational, science basis for thinking that the limited benefits of those shots do not adequately offset their risks. This is true for the vast majority of healthy people, especially children, who have extremely low risk from COVID infection for serious illness, hospitalization or death.
Mandates that do not recognize natural immunity are merely a sham tactic to make money for drug companies.
How interesting it would be, in the context of informed consent, if people were shown the original and new CDC vaccine definitions as a means to stimulate productive discussion with medical providers of COVID shots.
Dr. Joel S. Hirschhorn, author of Pandemic Blunder and many articles, podcasts and radio shows on the pandemic, worked on health issues for decades. As a full professor at the University of Wisconsin, Madison, he directed a medical research program between the colleges of engineering and medicine. As a senior official at the Congressional Office of Technology Assessment and the National Governors Association, he directed major studies on health-related subjects; he testified at over 50 US Senate and House hearings and authored hundreds of articles and op-ed articles in major newspapers. He has served as an executive volunteer at a major hospital for more than 10 years. He is a member of the Association of American Physicians and Surgeons, and America’s Frontline Doctors.
Featured Video

AIDS Inc. by Gary Null (2007)
or go to
Aletho News Archives – Video-Images
From the Archives
Clash of Civilization, Iran Part II
By Jamal Kanj – Intifada-Palestine.com – January 14, 2011
Israel’s survival kit is: perpetuate conflict, insecurity to rationalize collective hate and finally playing victim.
Devoid of conflict, Israel implodes internally; without hate, Zionism loses its justification; and playing eternal victim to continue blackmailing the West. Absence of this holy trinity, Israel ceases to exist.
From its inception, the house of Zion has mastered exploiting adversarial powers to advance Israel’s cause. For instance, their influence over the Democratic Party in the US began with President Truman’s bid for 2nd term election in 1948.
Responding to strong opposition from Secretary of State General George Marshall and Department experts urging against recognition of Israel, President Truman replied: “I’m sorry gentlemen but I have to answer to hundreds of thousands [Jewish voters] who are anxious for the success of Zionism. I do not have hundreds of thousands of [voting] Arabs among my constituents”
Zionists influence over liberal American politics was matched with the doctrinal school of Conservative theoreticians aligning the Republican Party’s platform with Israel’s objectives. The Neoconservative Zionists, coined Zioncons, invented the “Clash of Civilization” concept to fight Israel’s wars. … continue
Blog Roll
 Aletho News
- 12 Things Your Psychiatrist Was Trained Not to Tell You
- From Unipolar Universalism to Multipolar Civilizational Distinctiveness
- RSF military group defects, joins Sudanese army: State media
- Ireland goalkeeper refuses to play ‘Israel’ as squad weighs boycott
- China pushes back against US on Cuba, Iran
- Ukrainian Soldiers, Potential Mercenaries: Have Gun, Will Travel!
- Burnham’s UN debut… A masterclass in British disinformation
- Iran flights continue despite US aviation sanctions
- Global Tipping Points Lead the World Into a State of Entropy
- The day-after at the White House: USA and Xi Jinping
- If Americans Knew
- Israel forces Gazans to live in constant peril – Daily Update
- Deconstructing Netanyahu’s pants-on-fire UN rant – Daily Update
- Trump betrayed voters with his campaign lies and prioritized a foreign country once he took office
- Netanyahu calls Israel’s war in Gaza ‘opposite of genocide’ in UN speech to near-empty hall
- Settler Kidnappings: Torture, Sexual Abuse and Terrorisation of Palestinian Abductees as Israel Deepens Annexation of West Bank
- Gaza winter nears as 162,000 tents become unusable, raising fears of humanitarian crisis
- Netanyahu says, “It’s the opposite of genocide”; UN says Gaza economy is world’s ‘most severe crisis on record’ – Daily Update
- Israel’s US-Backed Assault on Gaza Has Created the ‘World’s Most Severe Economic Crisis on Record’: UN
- ‘Protecting U.S. Citizens’… From Israel
- ‘This is where I live now, the back of a truck’: a day in the life of a grandmother in Gaza
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

