The 5 signs you DON’T have “Omicron”… you have a cold & a PCR test
By Kit Knightly | OffGuardian | December 15, 2021
They are determined to make the “Omicron Variant” appear as frightening as possible, that means getting as many cases as possible, which means flipping all the way to the front of the Covid playbook.
Enter “The 5 Signs You May Have Omicron Covid”, an article in the Metro yesterday, and repeated in spirit across dozens of other outlets.
For those of you feeling morbidly curious, here are the five signs of Omicron:
- scratchy throat
- Fatigue
- mild muscle aches
- dry cough
- night sweats
The astute reader will no doubt pick up that these are the symptoms of every single one of the common cold viruses that infect millions of people all over the world every single year.
It’s just the old Simpsons joke about “mild hunger, occasional thirst and tiredness at night”, only they expect us to take it seriously.
The odds are you’ve experienced these symptoms at least once or twice in the last year or so. This does not mean you had Omicron. It does not mean Omicron even exists.
Rather, it’s just a ploy to get you to follow government guidance and, in the words of the article:
“order a free PCR test as soon as possible”.
The government site for ordering PCR tests has already shut down due to millions of requests. We have repeated, ad infinitum, that these tests are scientifically meaningless, and return huge numbers of false positives.
Nevertheless, hundreds of thousands of PCR tests are being done on people with nothing but mild cold symptoms as we speak, and in these nasal swabs lies the incipient “Omicron wave”.
That is why Sajid Javid is going on TV saying he expects cases of Omicron to “dramatically increase” in the run-up to Christmas, because they are going to make it happen.
Then they’ll probably have the Prime Minister announce new restrictions… just after Parliament adjourns for the Christmas break, so they can’t be reviewed or voted on.
It’s the same old trick, again and again and again. Hopefully, people will stop falling for it soon.
RFK Jr. as America’s #1 HIV/AIDS Denier and the Sounds of Media Silence
BY RON UNZ • UNZ REVIEW • DECEMBER 15, 2021
Robert F. Kennedy, Jr.’s book attacking Anthony Fauci and the medical establishment has become a publishing sensation, spending more than a full week as the #1 Amazon bestseller and racking up over 2,600 reviews, 94% of them five-star.
Now after nearly a month of stunned silence, the American media is finally taking belated notice. This morning the Associated Press released a 4,000 word hit-piece harshly attacking the most prominent public figure in America’s much-vilified anti-vaxxing movement.
- How a Kennedy Built an Anti-Vaccine Juggernaut Amid COVID-19
Michelle R. Smith • The Associated Press • December 15, 2021 • 4,000 Words
A great deal of effort had obviously been invested in this attack, and the byline of the named author was shared by five additional AP writers and researchers, underscoring the journalistic resources devoted to damaging the reputation of an individual who has obviously made such powerful enemies. But in reading the article, the phrase that came to my mind was “the Sounds of Silence” or perhaps the famous Sherlockian clue of “the Dog That Didn’t Bark.”
Almost half of the entire book under attack—around 200 pages—is devoted to the presenting and promoting the astonishing claim that everything we have been told about HIV/AIDS for more than 35 years probably amounts to a hoax. As I wrote last week:
Yet according to the information provided in Kennedy’s #1 Amazon bestseller, this well-known and solidly-established picture, which I had never seriously questioned, is almost entirely false and fraudulent, essentially amounting to a medical media hoax. Instead of being responsible for AIDS, the HIV virus is probably harmless and had nothing to do with the disease. But when individuals were found to be infected with HIV, they were subjected to the early, extremely lucrative AIDS drugs, which were actually lethal and often killed them. The earliest AIDS cases had mostly been caused by very heavy use of particular illegal drugs, and the HIV virus had been misdiagnosed as being responsible. But since Fauci and the profit-hungry drug companies soon built enormous empires upon that misdiagnosis, for more than 35 years they have fought very hard to maintain and protect it, exerting all their influence to suppress the truth in the media while destroying the careers of any honest researchers who challenged that fraud. Meanwhile, AIDS in Africa was something entirely different, probably caused mostly by malnutrition or other local conditions.
I found Kennedy’s account as shocking as anything I have ever encountered.
By any reasonable standard, Robert F. Kennedy, Jr. has now established himself as America’s #1 “HIV/AIDS Denier,” and prior to the Covid outbreak, AIDS had probably spent almost four decades as the world’s highest-profile disease, reportedly absorbing some two trillion dollars in research and treatment costs. So for someone to essentially claim that the disease doesn’t actually exist would seem the height of utter lunacy, on a par with Flat Earthism. Yet not a single word of this astonishing situation appears in the long AP article, that attacks Kennedy on almost all other possible grounds, fair or unfair. Did all six of the AP writers and researchers somehow skip over those 200 pages in Kennedy’s bestseller?
That large team of AP journalists seems to have spent at least ten days working on their lengthy article, mining Kennedy’s record for almost everything controversial they could possibly find, even highlighting a photograph that merely shows him standing next to Trump allies Roger Stone and Michael Flynn.

Surely these reporters consulted numerous leading figures in the medical establishment on the HIV/AIDS issue, yet not a single word on that incendiary topic was included in their 4,000 word denunciation.
Although ferocious attacks against Kennedy’s HIV/AIDS claims might naturally have been expected, perhaps certain aspects of the book caused the senior editors of the Associated Press to draw back and decide that discretion on this matter was the better part of valor. As I had explained:
However, the first endorsement on the back cover is from Prof. Luc Montagnier, the medical researcher who won a Nobel Prize for discovering the HIV virus in 1984, and he writes: “Tragically for humanity, there are many, many untruths emanating from Fauci and his minions. RFK Jr. exposes the decades of lies.” Moreover, we are told that as far back as the San Francisco International AIDS Conference of June 1990, Montagnier had publicly declared “the HIV virus is harmless and passive, a benign virus.”
Perhaps this Nobel Laureate endorsed the book for other reasons and perhaps the meaning of his striking 1990 statement has been misconstrued. But surely the opinion of the researcher who won a Nobel Prize for discovering the HIV virus should not be totally ignored in assessing its possible role.
I went on to note:
And he was hardly alone. Kennedy explains that the following year, a top Harvard microbiologist organized a group containing some of the world’s most distinguished virologists and immunologists and they issued a public statement, endorsed by three additional science Nobel Laureates, that raised the same questions:
It is widely believed by the general public that a retrovirus called HIV causes a group of diseases called AIDS. Many biomedical scientists now question this hypothesis. We propose a thorough reappraisal of the existing evidence for and against this hypothesis, to be conducted by a suitable independent group. We further propose that the critical epidemiological studies be designed and undertaken.
As Kennedy tells the story, by that point AIDS researchers and the mainstream media were completely in thrall to the ocean of government funding and pharmaceutical advertising controlled by Fauci and his corporate allies, so these calls by eminent scientists were almost entirely ignored and unreported. According to one journalist, some two trillion dollars has been spent on HIV/AIDS research and treatment over the decades, and with so many research careers and personal livelihoods dependent upon what amounts to an “HIV/AIDS industrial-complex,” few have been willing to critically examine the basic foundations of that empire.
Until a couple of weeks ago, I had never given any thought to questioning AIDS orthodoxy. But discovering the longstanding scientific skepticism of so many knowledgeable experts, including four Nobel Laureates, one of them the actual discoverer of the HIV virus, has completely shifted my perspective. I cannot easily ignore or dismiss the theories Kennedy presents… And in basic fairness to the author, he himself also repeatedly emphasizes that he can “take no position on the relationship between HIV and AIDS” but is simply disturbed that Fauci has successfully used his government funding and media clout to suppress an ongoing and perfectly legitimate scientific debate. According to Kennedy, his book is intended “to give air and daylight to dissenting voices.”
So the total silence of the article does certainly raise certain obvious suspicions. As I previously wrote:
Robert F. Kennedy, Jr. is a top figure in America’s much-vilified anti-vaxx movement and his book is becoming a major element of that cause. His strident attacks against pharmaceutical companies, medical orthodoxy, and Fauci have earned him numerous, powerful enemies. If his AIDS claims were really as ridiculous as they might seem, would they not have already become a lightning rod for attacks against him? Suppose that his anti-vaxx tome had devoted 200 pages to arguing that our world was secretly controlled by invisible 12-foot-tall Reptilians from another dimension. Surely Kennedy’s enemies would have unleashed a huge storm of media ridicule against him for that lunacy, thereby discrediting his critique of vaccination campaigns. Yet instead complete silence has greeted his AIDS claims, raising questions in my mind of whether the medical establishment suspects that it has a great deal to hide and that many of Kennedy’s accusations might be correct.
As an outside observer with no special expertise in these areas of medicine, I was impressed by much of the material that Kennedy marshaled in support of his unorthodox views on vaccines and Covid treatments, but found that the evidence he provided on HIV and AIDS was vastly more comprehensive and persuasive, while being backed by far more authoritative experts. But if as he argues, the truth about HIV and AIDS has been successfully suppressed for decades by the entire medical industry, we must necessarily become very suspicious about other medical claims, including those regarding Covid and vaccinations.
Unless the medical and media establishments swiftly and forthrightly challenges Robert F. Kennedy, Jr. on the issue of HIV/AIDS, any fair-minded observers must necessarily conclude they recognize that he is substantially correct. And if he is correct about AIDS, any shreds of remaining credibility in our public health authorities will surely be destroyed, while the longstanding theories of Berkeley Prof. Peter Duesberg will have been vindicated:
- The chemical bases of the various AIDS epidemics: recreational drugs, anti-viral chemotherapy and malnutrition
Peter Duesberg, Claus Koehnlein, and David Rasnick • Journal of Bioscience • June 2003 • 24,000 Words
So as some have suggested, HIV/AIDS might very well become the Achilles’ Heel of our corrupt and incompetent medical establishment.
UK approves vaccine passes and mandatory jabs for healthcare workers
OffGuardian | December 15, 2021
Last night the UK Parliament voted through a bill forcing NHS workers to either get vaccinated or lose their jobs, as well bringing in “vaccine passports” for some events and venues.
Over 70,000 NHS workers are officially counted as “unvaccinated”, if you trust government numbers. Considering the NHS employs well over a million people, I wouldn’t be surprised if that number were actually much higher.
If just half of the unvaccinated workers resign it could put a lot of pressure on the always-over-burdened healthcare system.
The government wouldn’t mind that, of course, because it will make it easier to claim the NHS is being “overwhelmed” with Covid patients, and this will be blamed on the unvaccinated and used to justify further mandates and coercion.
Any deaths resulting from the under-staffed health system can be PCR tested and added to the “died with Covid” tally.
It’s a win-win.
The vaccine passport element of the bill is likewise concerning, even if it currently only applies to nightclubs and venues with a capacity of more than 10,000. That’s the thin edge of a rapidly-expanding wedge.
An interesting aspect of the vote was that it passed entirely thanks to the Labour party. Labour leader Sir Keir Starmer announced on Tuesday, in a bizarre-looking televised speech, that his party would support the government.
As a result all but eight “opposition” MPs voted with the government, whilst Tory rebel votes counted an even 100. If Labour had opposed the bill, it would not have passed.
Jeremy Corbyn, now an independent, voted against the government and emerged from his Covid hibernation to (finally) make a statement.
Much too little, and far too late, but it does illustrate why they needed to get rid of him in December 2019, just before the Covid roll-out, and why they so obviously rigged that election.
If he, as leader of the opposition, had been offering even this small amount of resistance from the beginning, the Covid narrative would never have made it this far.
Labour voting with the government, without even asking for concessions on sick pay or pay rises for NHS workers, is a sign that a changing of the guard may be on the horizon, with Keir Starmer being groomed to be the next PM, perhaps in the very near future.
That would explain the sudden emergence of the Christmas party scandal, which had further fuel added to its fire just today by yet another leak.
That, combined with the massive rebellion by his own MPs, is a massive knock on his authority.
Official polls, always a tool for controlling opinion rather than a scale for measuring it, are already putting Starmer 13 points ahead as the nations “most capable Prime Minister”.
Don’t be surprised if there are calls for another election, probably sometime soon. And they won’t be rigging this one for Boris.
Forget China, was it CEPI’s bio-spooks who locked down the West?
By Paula Jardine | TCW Defending Freedom | December 15, 2021
IT is nearly two years since the world turned upside down and a sequence of unprecedented lockdowns and quarantines in the name of public health and safety were imposed across the West.
The narrative of the still unfolding story of Covid-19 is familiar to all of us, with China the chief bogeyman of the tale. But is that right?
In this drama has something really important been overlooked? Namely, the role of a powerful, self-appointed supranational organisation, set up 2017, called the Coalition for Epidemic Preparedness Innovations (CEPI).
Members of CEPI’s board and scientific advisory committee have been, and still are, key actors in global and national responses to the Covid-19 virus. Its mission? To ‘create a world in which epidemics are no longer a threat to humanity’.
At the start of 2020, all eyes were glued on China. The communist government had dutifully notified the World Health Organisation (WHO) on New Year’s Eve 2019 of its concerns over a small cluster of cases of ‘pneumonia of unknown origin’.
Three weeks later, when the death toll stood at 17, the CCP was sufficiently alarmed to order the home confinement of nearly 12 million mostly healthy people who were unfortunate enough to reside in the outbreak city, Wuhan.
Having fingered as the culprit a relative of the SARS virus that claimed 774 victims in 2003, the Chinese determination to contain the self-evidently nastier 2019 co-variant at all costs was made plain to the world.
The scenes broadcast out of China nightly on the TV news were surreal, but strangely familiar to anyone with a passing familiarity with vintage sci-fi. A nightmare amalgamation of The Andromeda Strain and The Hamburg Syndrome was unfolding in real life, right before our eyes.
Here, a man falling down dead in the street. There, men in white hazmat suits walking through empty Chinese thoroughfares equipped with Ghostbuster-esque backpacks blowing smoke in a desperate attempt to fumigate the invisible peril out of existence.
Knowing that the Queen’s own men at the Porton Down chemical and biological defence establishment long ago discovered that fresh air and sunlight, two commodities already in short supply in Chinese cities, are the most potent of disinfectants, it seemed a strangely futile spectacle. What on Earth were they trying to do? Death apparently lurked around every corner.
As the Wuhan lockdown was being imposed on January 23, 2020, the global elite were busy congregating at their annual networking fest, the World Economic Forum, in Davos, Switzerland (where CEPI had been founded three years earlier by the governments of Norway and India, the Bill & Melinda Gates Foundation, the Wellcome Trust global charity organisation, and the World Economic Forum).
Next day, a little-noticed press conference was convened in Davos to discuss the SARS-like, closely-related, but definitely novel, SARS Wuhan coronavirus.
Appearing in front of about 30 reporters were Sir Jeremy Farrar, Director of the Wellcome Trust and board member of CEPI; Richard Hatchett, chief executive of CEPI, and Stephane Bancel, chief executive of Moderna, one of three companies being funded to develop a coronavirus vaccine. A Chinese reporter asked the panel if there was any historical precedent for the lockdown.
Hatchett said: ‘One thing that is important to understand, is that when you don’t have treatments and you don’t have vaccines, non-pharmaceutical interventions are literally the only thing that you have, and it’s a combination of isolation, containment, infection prevention and control and then these social distancing interventions.
‘There is historical precedent for their use. We looked intensively and did an historical analysis of the use of non-pharmaceutical interventions in US cities in 1918 and what we found was that cities that introduced multiple interventions, early in an epidemic, had much better outcomes.
‘The challenge of course is that it is very difficult to sustain these interventions, as they impose enormous cost and they also can produce enormous anxiety among the affected population.’
The ‘we’ Hatchett was referring to was the US Department of Homeland Security where, as an official, he had helped develop the US pandemic preparedness plan in 2005 and 2006 during the H5N1 avian influenza outbreak, which Farrar had discovered in Vietnam.
Hatchett continued: ‘At that time, we looked at how could you have those interventions implemented in a way that maximised their benefit and minimised the cost and we developed an approach that we called “community mitigation” interventions and CDC (the US Centres for Disease Control and Prevention) published guidance on this several years ago.
‘There is a literature which I would certainly encourage Chinese authorities to review and certainly I would be happy to talk to them about that, although that’s not my current job.’
There was no need to encourage the Chinese authorities to review the literature. CEPI already had a man in Beijing, Dr George Gao, the director of China’s Centre for Disease Control, but also member of the CEPI scientific advisory panel. The community mitigation approach the Chinese adopted in Wuhan was straight out of the 2006 US Homeland Security pandemic playbook.
Gao, like Farrar, completed his PhD at Oxford University before conducting post-doctoral work under Sir John Bell, the controversial Regius Professor of Medicine at Oxford, holder of several extranumerary positions and multiple interests, not least as chair of the global health scientific advisory board of the Bill & Melinda Gates Foundation.
An expert on coronaviruses, Gao served on CEPI’s first scientific advisory committee in 2016 and was a player in Event 201, the pandemic simulation hosted in October 2019 by the World Economic Forum, Bill & Melinda Gates Foundation and the Johns Hopkins Bloomberg School of Health – discussed here by Robert F Kennedy Jr.
In all probability, Gao is the old friend Farrar was referring to when he said on Desert Island Discs that he had had a phone call on December 31, 2019 – the day the Chinese authorities reported the Wuhan pneumonia outbreak to the WHO – to alert him that China would release the genome of the new virus on January 10. As things stood on New Year’s Eve, the virus had yet to cause any deaths, although it was making a few people very ill.
By January 17, another CEPI scientific adviser, Dr Christian Drosten, had conveniently developed a PCR test from the genetic sequence posted online by the Chinese, which the WHO advised laboratories could be used as a diagnostic test for Covid-19.
This was almost two months before the WHO declared the novel coronavirus a pandemic on March 11, 2020. Following a visit to Wuhan by the WHO in February 2020, led by its assistant director-general Dr Bruce Aylward, the world was being encouraged to adopt what were now being called Chinese measures.
‘China didn’t approach this new virus with an old strategy for one disease or another disease,’ said Aylward. ‘It developed its own approach to a new disease and extraordinarily has turned around this disease with strategies most of the world didn’t think would work.’
The Chinese government, with its own Big Brother infrastructure, had its own reasons for going along with that. But the response plan is in reality far more complex, and has a much darker background in the West.
The Yellow Brick Road that passes through CEPI and Beijing leads right back to the US Department of Homeland Security, and its 1998 Pentagon strategy paper.
The response plan is in reality an American scheme, with its origins more than decade and a half earlier and against a backdrop of bioterrorism concerns. Uncle Sam is the wizard behind the curtain, not acting in the West’s interests at all.
Is Vaccine Effectiveness Against Death Mostly a Statistical Illusion?

By Will Jones | The Daily Sceptic | December 12, 2021
One of the big challenges in analysing the data on Covid has been definitions. What is a Covid death, what is a Covid case or infection? What the data appears to say can change radically depending on the definitions adopted.
This has been a particular issue with vaccination, as vaccination status is subject to a variety of conflicting definitions. In particular, when does someone count as vaccinated? Is it as soon as they have the needle in their arm, or do they remain ‘unvaccinated’ after that for a period of time, say seven, 14 or 21 days?
For instance, the recent ICNARC report stated the number of ICU admissions by vaccination status. But it also clarified that ‘unvaccinated’ includes those who received a jab less than 14 days prior to testing positive. This means that some (an unknown number) who were counted as unvaccinated had in fact received a dose.
This may be more than just a minor problem. For one thing, there is now a lot of evidence that people are more vulnerable to infection in the days following their jab, likely due to temporary immune suppression. This means a significant proportion of the vaccinated who are susceptible to infection with the current dominant variant are infected in the immediate post-jab period when in many studies and reports they don’t count as vaccinated. This creates a ‘survivorship bias‘ in the remaining vaccinated group that exaggerates vaccine efficacy. For instance, in a study of the U.S. nursing home population published in NEJM, once the post-jab period was included – when the vaccinated experienced higher incidence than the unvaccinated – the overall proportion of vaccinated and unvaccinated groups testing positive was the same at 6.8%. This makes it essential that all the data is presented, including for past-jab periods, and definitions are clear.
A similar problem occurs with the classification of deaths as vaccinated and unvaccinated. New analysis led by Norman Fenton, Professor in Risk Information Management, and Martin Neil, Professor in Computer Science and Statistics, both at Queen Mary, University of London, has highlighted a strange anomaly in the ONS deaths data that may be indicative of a deeper problem. They noticed that if non-Covid deaths in the unvaccinated were plotted against time over the course of the vaccine rollout then a strange spike appeared during the rollout in which the mortality rate among the unvaccinated shot up to well above the background level. The same thing happened with the non-Covid mortality rate in the single-dosed as second doses were rolled out, and the phenomenon was repeated in each age group as vaccines were administered.
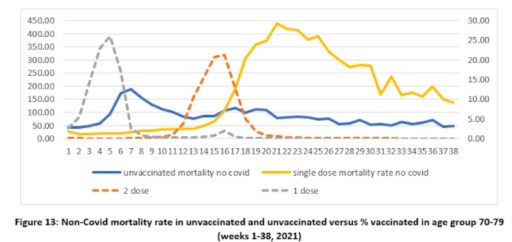
Since there is no obvious reason that vaccination should impact on non-Covid mortality in this way, Prof Fenton, Prof Neil and team argue that this is evidence of a problem in the way the data is recorded or defined. In particular, if it is assumed that the unvaccinated in fact continue to die of non-Covid causes at the background rate and that the additional non-Covid deaths above that are deaths that are actually in the vaccinated but have been misclassified (owing, say, to not counting those who die within 14 days of their jab) then, they argue, a more realistic pattern emerges (see below).
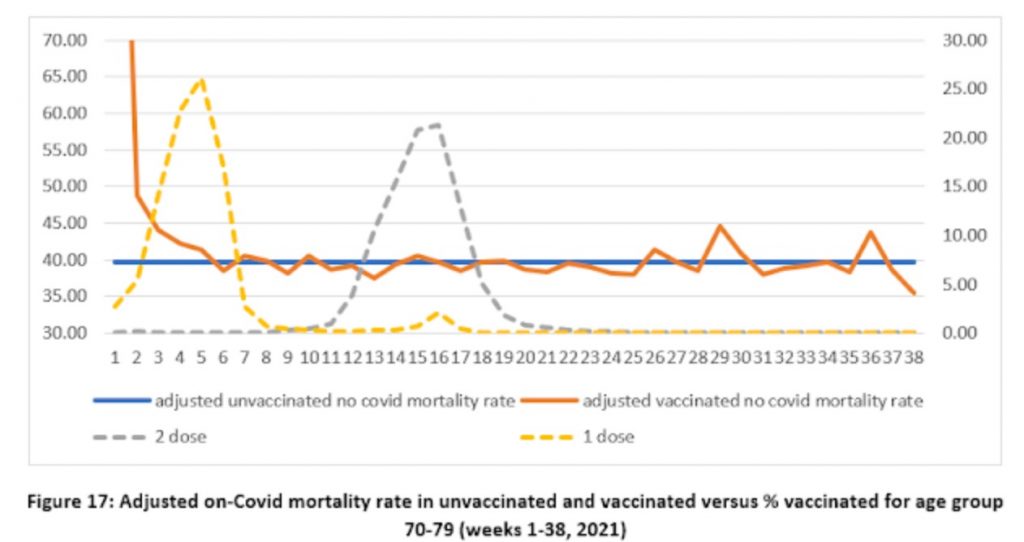
In each age group there is now a spike in non-Covid deaths in the vaccinated right at the start of the rollout, which the team argue makes sense as vaccination was prioritised for the most vulnerable who are more likely to die of any cause. Indeed, it was confusing in the original data that this initial spike was absent and the vaccinated died of non-Covid causes at a lower rate than the unvaccinated despite the most vulnerable being prioritised for vaccination.
The team discovered a different problem when they looked at Covid deaths by vaccination status. Here, the vaccines appear to be highly efficacious, but there is an anomaly that may again be indicative of deeper problems in the data.
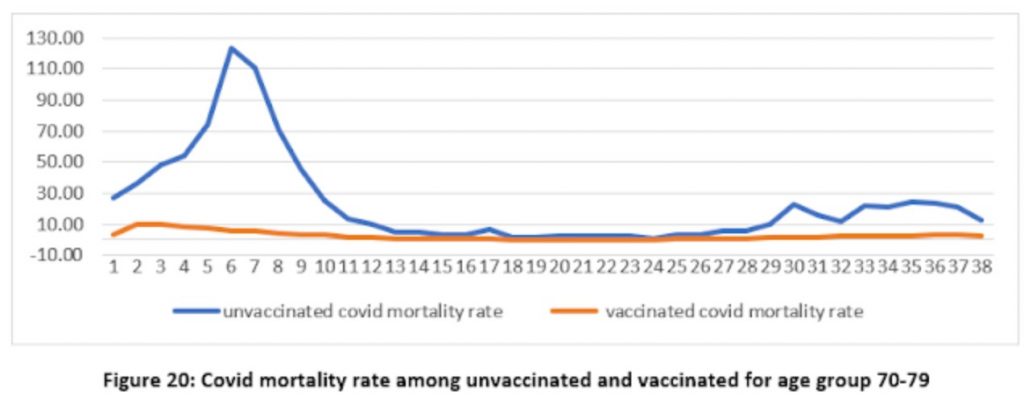
Again a spike appears in the unvaccinated mortality rate where there is none in the vaccinated. Fair enough, you might think, as the vaccines are protecting the vaccinated. However, it’s important to remember that the vaccines are not expected to work until 21 days after the first jab, yet here we have a spike in unvaccinated Covid mortality in the middle of the rollout before most of the vaccines should take effect – referring to figure 17 above we can see that the vaccine rollout in the age group peaked in week five, around the same time as the mortality rate in the unvaccinated peaked (week six), which all seems much too early.
Prof Fenton, Prof Neil and team suggest that the problem here may be in the denominator, that is to say, in how many people are supposed to be in the vaccinated and unvaccinated populations when calculating the mortality rate each week. It’s important to realise that the populations here are changing fast as tens of thousands of people get vaccinated each week. Using the right figure for the right week therefore makes a big difference to the mortality rate reported. Could this anomalous spike in unvaccinated Covid deaths be an artefact of this kind of problem?
Professor Fenton thinks so. He and his team suggest that the problem may be that the relevant denominator or number of people vaccinated for each week is not how many are vaccinated in the week a person dies but in the week they were infected, which is around three weeks earlier on average. What happens if the denominators are shifted by three weeks to allow for this? (Prof Fenton demonstrates the effect of shifting denominators in a short video of a hypothetical example here.)
The effect is remarkable, as shown below (note the change of scale on the y-axis).
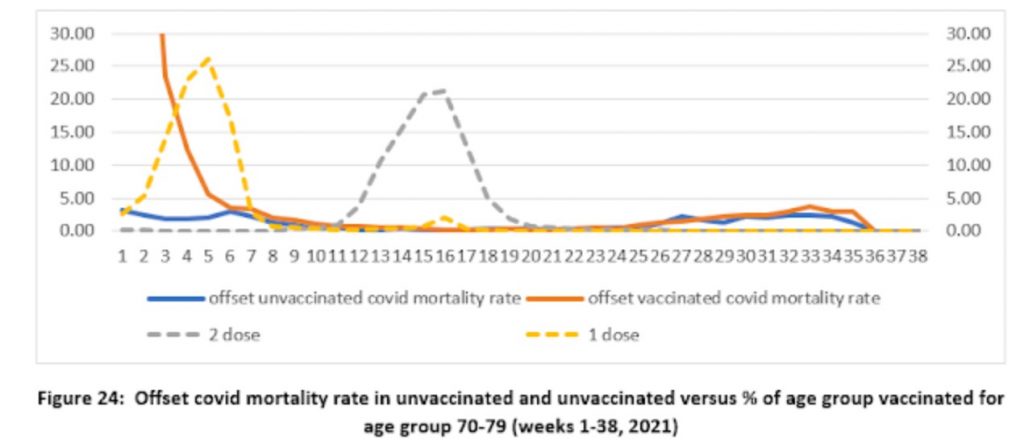
Shifting the population denominator estimates by three weeks means that the number of vaccinated for calculating the vaccinated mortality rate becomes much smaller, making the mortality rate much higher, while the denominator for the unvaccinated becomes much larger, making the mortality rate much lower. This massively reduces the mortality rate in the unvaccinated to low levels – to under five deaths per 100,000 people throughout the period, rather than as many as 125 per 100,000 in week six previously. Instead, a mortality spike appears in the vaccinated at the start of the vaccine rollout (though note that the scale is smaller so it only reaches 30 per 100,000 people), which makes some sense as the vulnerable were prioritised for vaccination and at this point the population of vaccinated was small, so contained a high proportion of vulnerable people. Prof Fenton and team remark that it also tallies with what we know of the increased vulnerability of the recently-vaccinated to infection, as noted above.
The shift in population estimates also greatly reduces the implied effectiveness of the vaccines in the autumn wave, where the lines are now much closer to one another, which is in line with findings from Sweden and elsewhere as vaccine efficacy wanes. Prof Fenton and team suggest that once you take into account the initial spike in the vaccinated, then this new analysis suggests there is “no reliable evidence that the vaccines reduce all-cause mortality”.
So is this what’s going on? There are certainly anomalies that need to be explained, and the analysis by Professor Fenton, Professor Neil and team makes a lot of sense. It deserves to be taken seriously by the ONS and UKHSA.
Stop Press: Watch Prof Fenton discussing his team’s findings with Maajid Nawaz on LBC radio.
Comirnaty, liability, and how the HHS lies, cheats and steals
By Meryl Nass, MD | December 12, 2021
I checked the Federal Register and there has been no notice that Comirnaty has been added to the National Childhood Vaccine injury Program (NVICP). I confirmed this by checking whether Comirnaty had been added to the childhood schedule, and according to the HRSA, which manages both compensation programs, it has not.
So, if you receive the licensed Comirnaty vaccine, correctly labeled as the brand-name product and not the vaccine being fobbed off as licensed product, and you are injured, you are free to sue the manufacturer for your injury. Could this be why Pfizer wrote, “Pfizer does not plan to produce any product with these new [Comirnaty National Drug Codes] and labels over the next few months while EUA authorized product is still available and being made available for U.S. distribution.”
If, however, you receive the Pfizer-BioNTech vaccine under Emergency Use Authorization, or the Moderna or J and J vaccine, you can’t sue anyone. You have the right to beg HRSA for compensation of lost wages and unpaid medical bills, period. So far, HRSA and the Countermeasures Injury Compensation Program it administers have not paid out one dime for the approximately one million injuries and 20,000 deaths reported to VAERS for any COVID vaccine.
In other words, the federal government (DHHS) has not admitted a single injury was caused by a COVID vaccine. CDC says it has not linked a single death to a COVID vaccine–not even when the patient walked into the vaccination center but got carried out to the morgue. FDA doesn’t know much about myocarditis, Bell’s Palsy, thrombosis, thrombocytopenia, pulmonary emboli, etc. There are no black box warnings on any of the COVID vaccines.
HRSA, FDA, CDC and NIH are all agencies within the federal Department of Health and Human Services. They have all gotten their stories straight. They know nothing and they are just following orders. Heil HHS!
They can’t find a doggone problem in the 20 or so databases they are spending many $millions of your money to “study.”
Want to know the biggest conspiracy in the US right now? It is the HHS.
FDA has access to a bunch of electronic databases it has termed the “BEST” Initiative, and it published a plan to use them to study heart attacks, pulmonary embolism, thrombocytopenia, etc. back in July. Where are the results, FDA? What are you waiting for? (According to CDC, “More than 459 million doses of COVID-19 vaccines were administered in the United States from December 14, 2020, through November 29, 2021.”). It seems clear that we aren’t supposed to be informed of FDA’s findings until everyone possible has been vaccinated, at which point the results will be irrelevant.
In October 2020, FDA’s Steve Anderson told us there were even more databases that would be studied.
On August 23, 2021, FDA announced its databases were inadequate to assess myocarditis, so BioNTech would have to do it for them. Here is what FDA wrote about its inability to use VAERS and its many other databases:
- As noted above, the FDA acknowledges that “We have determined that an analysis of spontaneous postmarketing adverse events reported under section 505(k)(1) of the FDCA [in other words, VAERS–Nass] will not be sufficient to assess known serious risks of myocarditis and pericarditis and identify an unexpected serious risk of subclinical myocarditis.
- Furthermore, the pharmacovigilance system that FDA is required to maintain under section 505(k)(3) of the FDCA [in other words, FDA’s many other databases that cost the taxpayer zillions–Nass] is not sufficient to assess these serious risks.”
NOT SUFFICIENT???
Unsaid, but implied, is that if FDA is incapable of studying thousands of reported cases of myocarditis, it probably cannot study the other serious adverse events that have been reported in conjunction with COVID vaccines.
VAERS has operated for 30 years, collecting reports of vaccine adverse events. It averaged under 100 cases of myocarditis reported yearly until this year. Through November, CDC reports it received 1949 reports of myocarditis and pericarditis, in those under 30. CDC didn’t say what the total number of reports for all ages was.
Somehow, these HHS don’t seem all that concerned that the admitted reporting rate of myocarditis is over 20 times the average during the past 30 years. Why?
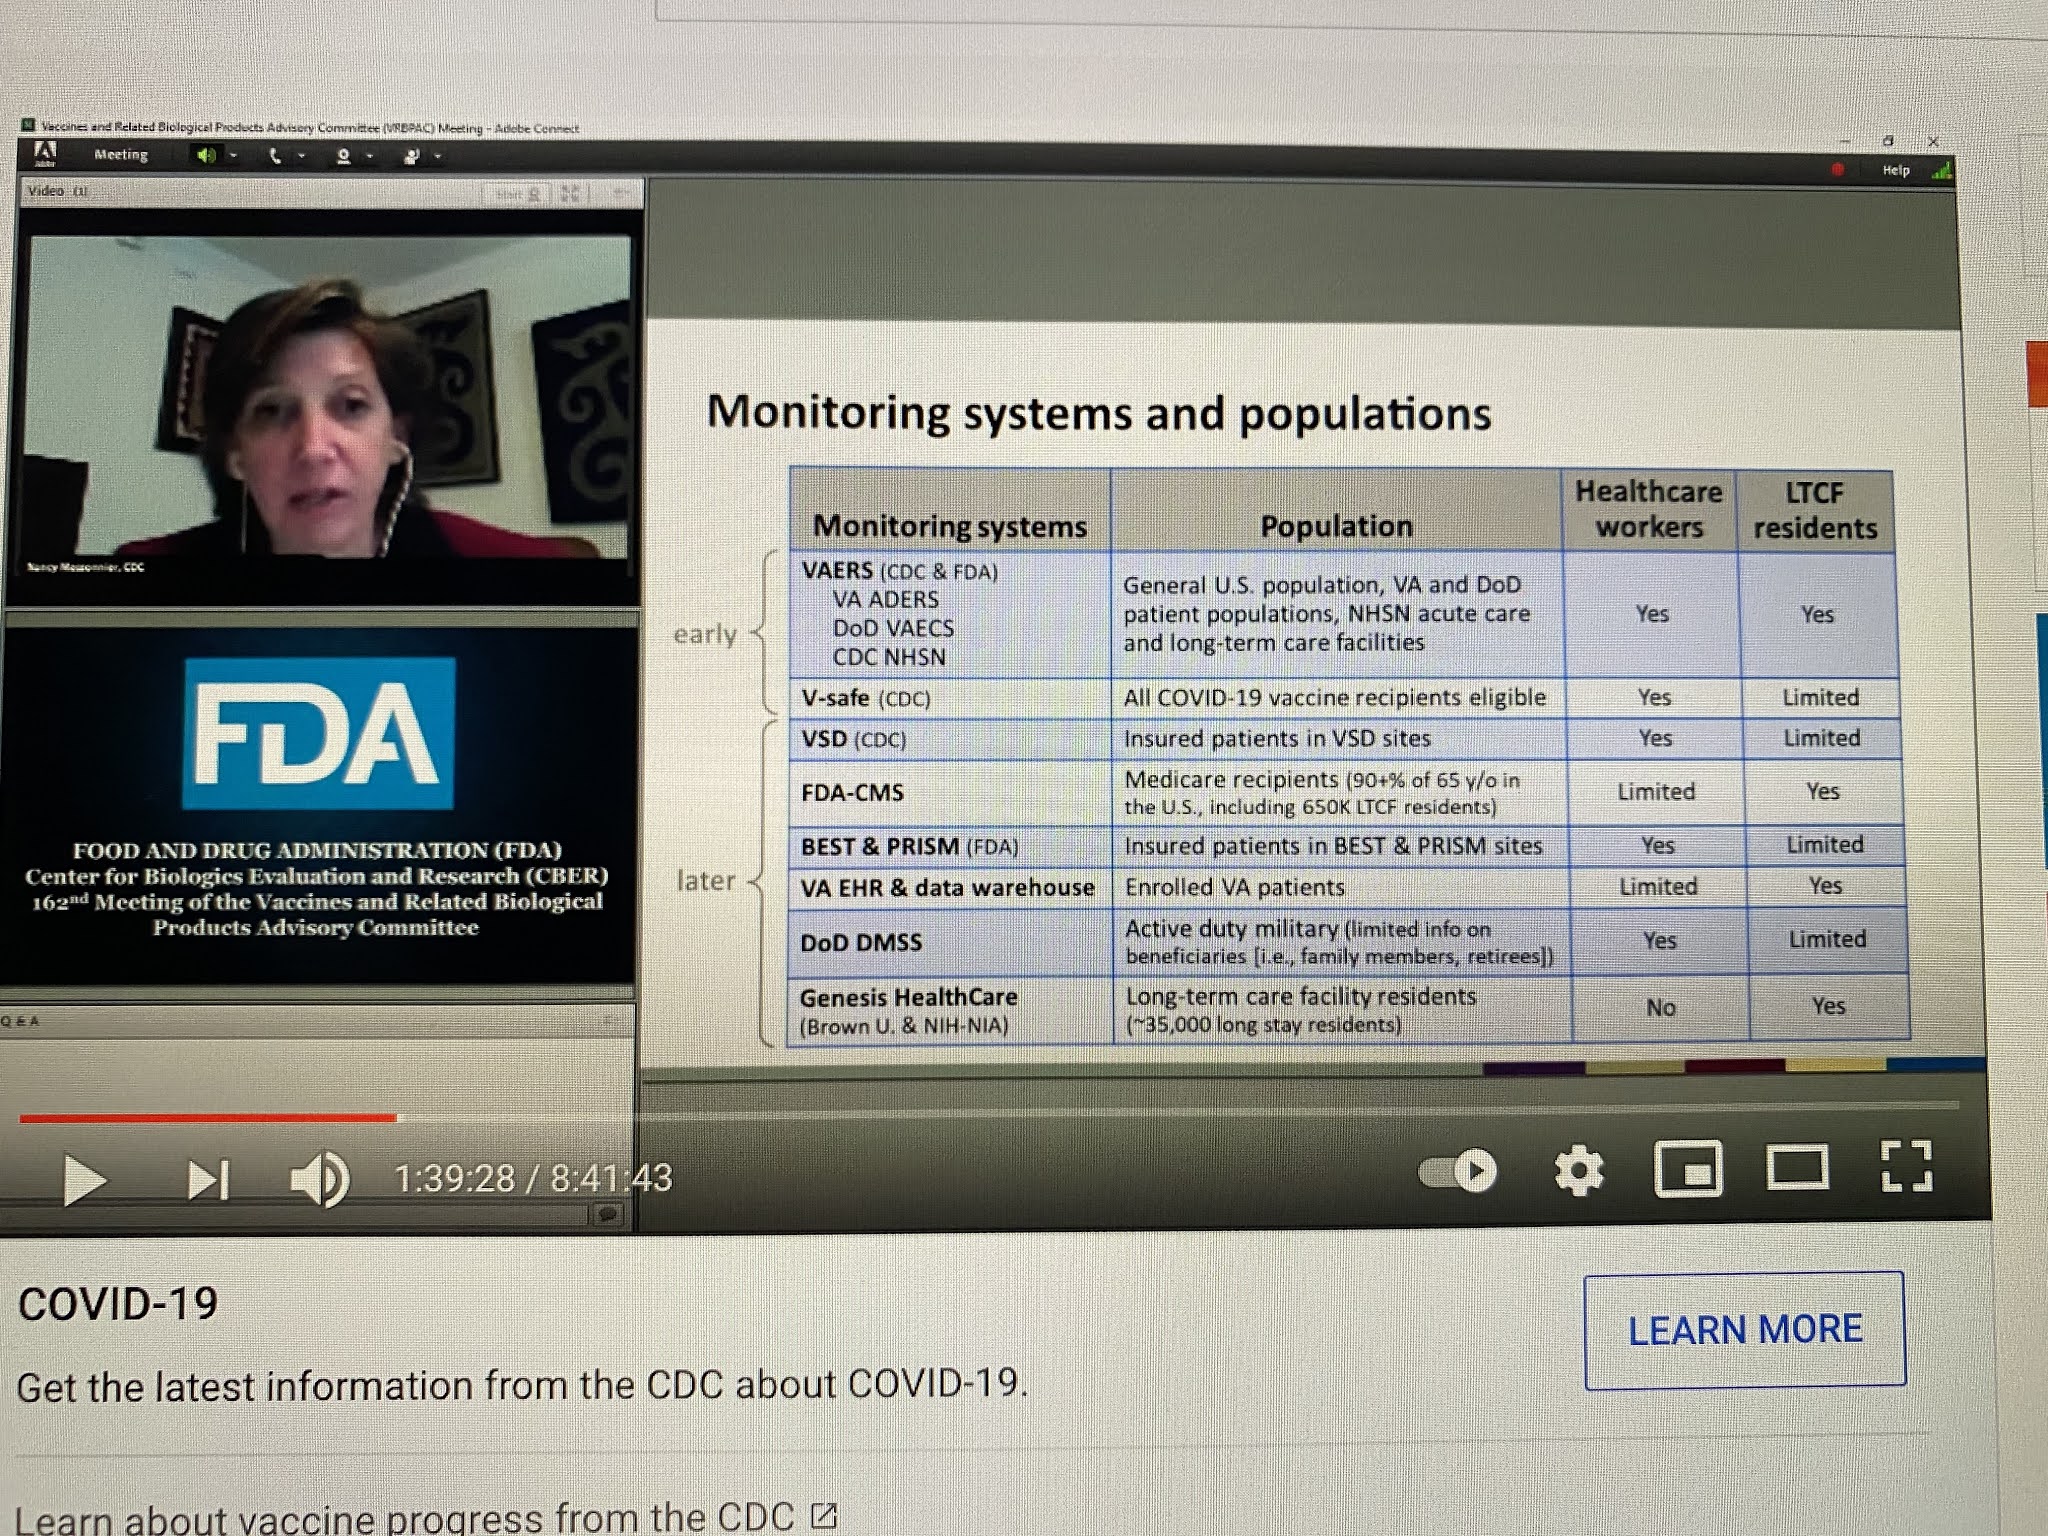
CDC has been even more shady in its analyses of safety as FDA, if that is even possible. Below, Nancy Messonier, then head of Immunizations and Respiratory Diseases at CDC, presented this list of databases that CDC would be using in the evaluation of COVID vaccine safety, on December 10, 2020. Apart from the V-safe (which they stopped talking about last January), VSD (which somehow can’t find any problems, not even myocarditis) and VAERS, all these other databases have been MIA.
NIH, whose job has never been to issue treatment guidelines, but instead to do and fund research, suddenly took over the treatment guidelines for COVID early in 2020. It formed a committee of internal and eternal “experts” to make up the guidelines. How were they chosen? That is not clear, but what is clear is that 16 of these so-called experts had current or recent financial entanglements with Gilead, the maker of remdesivir. NIH and the US Army also owned pieces of remdesivir. A number of other had financial conflicts with Merck. While NIH is the biggest single funder of medical research in the world, I cannot recall seeing a single study it funded on the safety of COVID vaccines. But somehow vaccines are its number one recommendation.
But it is not even clear that the committee is functional. The NIH has been sued to learn whether a vote was even taken by the committee regarding its ivermectin guidelines, which fly in the face of the evidence on ivermectin. How was NIH somehow authorized to issue guidelines in the first place?
Here is what has obviously occurred. All these agencies were told they had to keep quiet on vaccine problems (and perhaps problems of other COVID treatments), and they had to fiddle with their data or their analytic methods, or both, to get the required results. And there was to be NO BAD NEWS, no matter what. And no good news regarding generic treatments.
As we have seen, the so-called scientists and physicians working as bureaucrats in these agencies all caved, sucked it up, did the dirty work, kept their jobs, and betrayed their oaths and the trust of the people of the USA and the world.
Joe Biden spins tornado misinformation
By Gregory Wrightstone | CO2 Coalition | December 12, 2021
President Joe Biden wasted no time in politicizing the recent tornado tragedy that claimed nearly 100 lives in Kentucky, Illinois, Arkansas, Tennessee, and Missouri. Speaking less than 24 hours after the devastation of communities and lives, Biden linked the storms to man-made climate change.
“All I know is that the intensity of the weather across the board has some impacts as a consequence of the warming of the planet and climate change,” Biden said. “The fact is that we all know everything is more intense when the climate is warming. Everything. And obviously it has some impact here.”
Is that really the case? Have violent tornadoes been increasing? The answer to that question is clear, but you won’t find the answer at the agency most responsible for monitoring such things. It appears that the National Oceanic and Atmospheric Administration (NOAA) is playing games with tornado data. In 2017, while researching tornado data, I archived the NOAA site’s page on tornadoes and data. At the time, NOAA specifically warned that pre-Doppler radar records of tornadoes (before 1995) are unreliable:
“One of the main difficulties with tornado records is that a tornado, or evidence of a tornado, must have been observed. Unlike rainfall or temperature, which may be measured by a fixed instrument, tornadoes are short-lived and very unpredictable. A tornado in a largely unoccupied region is not likely to be documented. Many significant tornadoes may not have made it into the historical record since Tornado Alley was very sparsely populated during the early 20th Century.”
Because of this, NOAA recommended (at the time) only using the strongest tornadoes as a measure of pre-Doppler numbers and provided this chart that documented an overall decrease in the number of strong and violent storms that were categorized as >EF 3 (I have added the carbon emissions to the chart).

Figure 1 – Tornadoes: NOAA (2017) NCEI Historical Records and Trends, https://www.ncdc.noaa.gov/climate-information/extreme-events/us-tornado-climatology/trends CO2: Boden 2016 Global Regional and National Fossil-Fuel CO2 Emissions. CDIAC
Accessing the very same link for NOAA today takes one to their latest iteration, which showcases a chart of ALL tornadoes dating back to 1950 and shows a steady and significant rise in the number of tornadoes from 1950 to the late 1990s. Bear in mind, that just a few years ago, NOAA specifically warned against using exactly this data because it would under-count the numbers before 1995.

Figure 2 – Tornadoes: NOAA (2017) NCEI Historical Records and Trends, https://www.ncdc.noaa.gov/climate-information/extreme-events/us-tornado-climatology/trends
Updated data on tornadoes through 2020 is available at ustornadoes.com and showcases just why using pre-Doppler data is misleading. Figure 3 shows the pre-Doppler numbers of tornadoes reported. Importantly, this is not capturing increasing actual numbers of tornadoes that occurred, but rather increased reporting.

Figure 3 – US Pre-Doppler Tornadoes https://www.ustornadoes.com/annual-tornadoes/
Figure 4, below, is a chart of all Doppler-era tornadoes showing no increase at all.

Figure 4 – US pre-Doppler Tornadoes https://www.ustornadoes.com/annual-tornadoes
All of this begs the question: Why would a government agency promote flawed data? The answer is simple: It “confirms” their preconceived notion of increasing severe weather and provides support for alarming claims of ever-increasing death and destruction.
You can be sure that Joe Biden will not be the last to use these deaths and this tornado deception to spread fear and alarm to support their plans to spend trillions of dollars to solve a non-existent climate crisis. The Biden administration should “follow the science” and get to the business of helping the victims and stop spreading misinformation.
Gregory Wrightstone is a geologist, executive director of the CO2 Coalition, Arlington, Va., and author of “Inconvenient Facts: The science that Al Gore doesn’t want you to know.”
Whilst you were distracted by a Christmas Party the UK Gov. released a report confirming the Fully Vaccinated account for 4 in every 5 Covid-19 Deaths in England since August
THE EXPOSÉ | DECEMBER 11, 2021
Serious questions need to be answered as to why Boris Johnson’s Government have decided to restrict the freedoms of the unvaccinated population through the introduction of Vaccine Passports, when the latest official data shows that the vaccinated population have accounted for 3 in every 5 Covid-19 cases, 3 in every 5 Covid-19 hospitalisations, and 4 in every 5 Covid-19 deaths, in England since August 16th 2021.

During a national Covid-19 briefing that took place on Tuesday December 8th, the Prime Minister of the United Kingdom announced that ‘Plan B’ would be implemented in England from Wednesday December 15th, which would entail ‘working from home’ (if you can) orders, and the introduction of Vaccine Passports.
The reason given for the commencement of ‘Plan B’ is that it has to be done to protect the public from the alleged new Omicron variant of the Covid-19 virus. A variant which as of December 11th, has failed to cause a single fatality in the UK, with just several hundred cases allegedly being confirmed.
A new law will come into effect from Wednesday December 15th, which will state that Vaccine Passports will become mandatory for entry to nightclubs and other large venues, including Premier League football matches and concerts. We’re told they will be required for indoor settings of 500 people or more, outdoor settings of 4,000 people or more, and any setting with 10,000 attendees or more.
There will be many in England who believe Vaccine Passports are the answer to their prayers. Two years of misinformation, and disinformation mixed with propaganda published by the mainstream media can do that to people. But unfortunately the official data published by the UK Government proves that they are far from it, and suggests Vaccine Passports have absolutely nothing to do with protecting public health, and instead everything to do with controlling the nation.

The UK Health Security Agency (PHE) is an executive agency of the Department of Health and Social Care and recently replaced Public Health England. The Chief Executive of the agency is Dr Jenny Harries OBE, who you may recognise from the television as she has served as Deputy Chief Medical Officer for England throughout the pandemic.
The UKHSA publish a weekly ‘Vaccine Surveillance’ report which contains data on Covid-19 cases, hospitalisations, and deaths by vaccination status over a period of four weeks, and unfortunately for the vaccinated population, the official data shows that they have accounted for the majority of Covid-19 cases, hospitalisations, and deaths for at least the past four months.
We have used the following official reports for our analysis –
- COVID-19 vaccine surveillance report – Week 37 (Covers Week 33-36)
- COVID-19 vaccine surveillance report – Week 41 (Covers Week 37-40)
- COVID-19 vaccine surveillance report – Week 45 (Covers Week 41-44)
- COVID-19 vaccine surveillance report – Week 49 (Covers Week 45-48)
Covid-19 Cases
Table 8 of the latest report shows the number of Covid-19 cases by vaccination status in England. The table may have been attributed a different number in previous reports published by the UKHSA, but the following chart shows cases by vaccination status over a period of 16 weeks from 16 Aug 21 to 05 Dec 21.

The chart shows that between August and early September, the vaccinated population accounted for the majority of Covid-19 cases. However, between the middle of September and early October this switched to the not-vaccinated population accounting for the majority of cases. This is most likely due to children returning to school in September and being “encouraged” to test on a regular basis.
But between October 11th and December 5th the roles reversed again, and it is the fully vaccinated population that have accounted for the majority of Covid-19 cases in England.
This data alone puts an end to the myth that it is selfish to not be vaccinated, because it’s quite clear the jabs do not prevent infection or transmission. Which begs the question as to why Boris Johnson has decided to implement Vaccine Passports in England?

The above chart shows the cumulative number of cases by vaccination status between 16 Aug 21 and 05 Dec 21, and illustrates quite clearly that the fully vaccinated have accounted for the majority of cases since August.
What we can see from the above is that the unvaccinated had accounted for the majority of cases up to October 10th, however since this date there has been a switch with the fully vaccinated taking the lead, hitting a cumulative total of 1.5 million confirmed cases by Dec 5th.
When including the 258,387 confirmed cases among the partly vaccinated during this period, the total cases among the vaccinated population rises to 1,757,444. Whilst the number of cases among the unvaccinated population during this period of 16 weeks has amounted to 1,403,100.
Covid-19 Hospitalisations
Table 9 of the latest report shows the number of Covid-19 hospitalisations by vaccination status in England. The table may have been attributed a different number in previous reports published by the UKHSA, but the following chart shows cases by vaccination status over a period of 16 weeks from 16 Aug 21 to 05 Dec 21.

You may have heard several times this week on national television from people such as Dr Hilary, Lorraine Kelly, and Martin Kemp that “90% of the people currently in hospital with Covid-19 have not been vaccinated”.
Well it looks like they have been lying to you because the official UK Government data the fully vaccinated population have accounted for the majority of Covid-19 hospitalisation every month since at least August.

The above chart shows the cumulative number of hospitalisations by vaccination status between 16 Aug 21 and 05Dec 21, and shows just how bad things have actually been for the vaccinated population compared to the unvaccinated.
Between Aug 16 and Dec 05, the unvaccinated population accounted for 11,767 Covid-19 hospitalisations. But the vaccinated population have accounted for nearly double the amount, recording 19,730 hospitalisations, with 18,406 of those being among the 2/3 dose vaccinated population. This means the vaccinated population have accounted for 63% of Covid-19 hospitalisations since August 2021.
Covid-19 Deaths
Table 10 (b) of the latest report shows the number of Covid-19 hospitalisations by vaccination status in England. The table may have been attributed a different number in previous reports published by the UKHSA, but the following chart shows cases by vaccination status over a period of 16 weeks from 16 Aug 21 to 05 Dec 21.

The above chart proves that the fully vaccinated population have accounted for the majority of Covid-19 deaths every single month since August 2021, with things really taking a turn for the worse in October.
The highest number of Covid-19 deaths in single four week period among the fully vaccinated population has been 3,284, whereas the highest number of Covid-19 deaths among the unvaccinated population in a four week period has been just 850. That’s a 286% difference.

The above chart shows the cumulative number of deaths by vaccination status between 16 Aug 21 and 05 Dec 21, and illustrates quite clearly that this is very much a pandemic of the fully vaccinated.
Between 16 Aug 21 and 05 Dec 21 there were 3,070 Covid-19 deaths among the unvaccinated population in England, compared to 12,058 deaths among the vaccinated population during the same time frame. That is a 293% difference.
Covid-19 Fatality Rates by Vaccination Status
The official data shows the the vaccinated population have accounted for 56% of Covid-19 cases, 63% of hospitalisations, and 80% of deaths over the past 16 weeks in England.

It’s quite clear that the jabs do not prevent infection or transmission, but they are alleged to reduce the risk of hospitalisation and death. However, if this were the case then should we not be seeing a graph that looks more like this?

So why aren’t we?
It could have something to do witht he fact that the data suggests the Covid-19 injections are actually increasing the risk of death due to Covid-19 rather than reducing it by the claimed 95%.
The following graph shows the case-fatality rate among the not-vaccinated population, and the case-fatality rate among the 2/3 dose vaccinated population over the past 16 weeks.

The case-fatality rate is calculated by dividing the number of known deaths by the number of known cases among the population. As we can see from the above the case-fatality rate among the not-vaccinated population is just 0.2%, which is what is in line with the average case-fatality rate in 2020 before a Covid-19 injection was introduced to the masses.
However, the case-fatality rate among the fully vaccinated population is much higher, equating to 0.8%. Therefore the fully vaccinated are 4 times / 300% more likely to die if exposed to the Covid-19 virus based on official UK Government figures.
The following graph shows the hospitalisation-fatality rate among the not-vaccinated population, and the hospitalisation-fatality rate among the 2/3 dose vaccinated population over the past 16 weeks.

The hospitalisation-fatality rate is calculated by dividing the number of known deaths by the number of known hospitalisations among the population. As we can see from the above the hospitalsiation-fatality rate among the not-vaccinated population is 26%.
But the hospitalisation-fatality rate among the fully vaccinated population is frighteningly higher equating to a shocking 63%. This means the fully vaccinated population are 2.4 / 142% more likely to die once hospitalised with Covid-19.
So now that you know that the double / triple jabbed population have accounted for 3 in every 5 cases, 3 in every 5 hospitalisations, and 4 in every 5 Deaths over the past 4 months in England, and that the UK Government has been laughing at you since at least Christmas 2020 through their alleged Christmas parties, are you going to allow them to take away your freedom yet again in response to an alleged variant that has so far caused zero fatalities, or are you going to stand up, carry on living, and say “no” this time around?
Because this will not end until we all say it does.
Latest Modelling on Omicron Ignores All Evidence of Lower Severity, Among Numerous Other Problems
By Mike Hearn | The Daily Sceptic | December 11, 2021
Today the Telegraph reported that:
Experts from the London School of Hygiene and Tropical Medicine (LSHTM) predict that a wave of infection caused by Omicron – if no additional restrictions are introduced – could lead to hospital admissions being around twice as high as the previous peak seen in January 2021.
Dr Rosanna Barnard, from LSHTM’s Centre for the Mathematical Modelling of Infectious Diseases, who co-led the research, said the modellers’ most pessimistic scenario suggests that “we may have to endure more stringent restrictions to ensure the NHS is not overwhelmed”.
As we’ve come to expect from LSHTM and epidemiology in general, the model forming the basis for this ‘expert’ claim is unscientific and contains severe problems, making its predictions worthless. Equally expected, the press ignores these issues and indeed gives the impression that they haven’t actually read the underlying paper at all.
The ‘paper’ was uploaded an hour ago as of writing, but I put the word paper in quotes because not only is this document not peer reviewed in any way, it’s not even a single document. Instead, it’s a file that claims it will be continually updated, yet which has no version numbers. This might make it tricky to talk about, as by the time you read this it’s possible the document will have changed. Fortunately, they’re uploading files via GitHub, meaning we can follow any future revisions that are uploaded here.
Errors
The first shortcoming of the ‘paper’ becomes apparent on page 1:
Due to a lack of data, we assume Omicron has the same severity as Delta.
In reality, there is data and so far it indicates that Omicron is much milder than Delta:
Early data from the Steve Biko and Tshwane District Hospital Complex in South Africa’s capital Pretoria, which is at the centre of the outbreak, showed that on December 2nd only nine of the 42 patients on the Covid ward, all of whom were unvaccinated, were being treated for the virus and were in need of oxygen. The remainder of the patients had tested positive but were asymptomatic and being treated for other conditions.
The pattern of milder disease in Pretoria is corroborated by data for the whole of Gauteng province. Eight per cent of Covid-positive hospital patients are being treated in intensive care units, down from 23% throughout the Delta wave, and just 2% are on ventilators, down from 11%.
Financial Times, December 7th
The LSHTM document claims to be accurate as of today, but just ignores the data available so far and replaces it with an assumption; one that lets them argue for more restrictions.
What kind of restrictions? The LSHTM modellers are big fans of mask wearing:
All scenarios considered assume a 7.5% reduction in transmission following the introduction of limited mask-wearing measures by the U.K. Government on November 30th 2021, which we assume lasts until April 30th 2022. This is in keeping with our previous estimates for the impact of increased mask-wearing on transmission.
I was curious how they arrived at this number given the abundant evidence that mask mandates have no impact at all (example one, example two). But no such luck – a reference at the end of the above paragraph points to this document, which doesn’t contain the word “mask” anywhere and “7.5%” likewise cannot be found. I wondered if maybe this was a typo but the claim that the relevant reference supports mask wearing appears several times and the word “mask” isn’t mentioned in references before or after either.
There are many other assumptions of dubious validity in this paper. I don’t have time today to try and list all of them, although maybe someone else wants to have a go. A few that jumped out on a quick read through are:
- An assumption that S gene drop-outs, i.e. cases where a PCR test doesn’t detect the spike protein gene at all, are always Omicron. That doesn’t follow logically given the very high number of mutations and given that theoretically PCR testing is very precise, meaning a missing S gene should be interpreted as “not Covid”. Of course, in reality – as is by now well known – PCR results are routinely presented in a have-cake-and-eat-it way, in which they’re claimed to be both highly precise but also capable of detecting viruses with near arbitrary levels of mutation, depending on what argument the user wishes to support.
- “We use the relationship between mean neutralisation titre and protective efficacy from Khoury et al. (7) to arrive at assumptions for vaccine efficacy against infection with Omicron” – The cited paper was published in May and has nothing to say on the topic of vaccine effectiveness against Omicron, which is advertised as being heavily mutated. Despite not citing any actual measured data on real-world vaccine effectiveness, the modelling team proceeds to make arguments for widespread boosting with a vaccine targeted at the original 2019 Wuhan version of SARS-CoV-2.
- They make scenarios that vary based on unmeasurable variables like “rate of introduction of Omicron”, making their predictions effectively unfalsifiable. Regardless of what happens, they can claim that they projected a scenario that anticipated it, and because such a rate is unknowable, nobody can prove otherwise. Predictions have to be falsifiable to be scientific, but these are not.
- Their conclusion says “These results suggest that the introduction of the Omicron B.1.1.529 variant in England will lead to a substantial increase in SARS-CoV-2 transmission” even though earlier in the ‘paper’ they say they assume anywhere between a 5%-10% lower transmissibility than Delta to 30%-50% higher (page 7), or in other words, they have no idea what the underlying difference in transmissibility is – and that’s assuming this is actually something that can be summed up in a single number to begin with.
Analysis
If you’re new to adversarial reviews of epidemiology papers some of the above points may seem nit-picky, or even made in bad faith. Take the problem of the citation error – does it really matter? Surely, it’s just some sort of obscure copy/paste error or typo? Unfortunately, we cannot simply overlook such failures. The phenomenon of apparently random or outright deceptive citations is one I’ve written about previously. This problem is astoundingly widespread in academia. Most people will assume that a numerical claim by researchers that has a citation must have at least some level of truth to it, but in fact, meta-scientific study has indicated the error rate in citations is as high as 25%. A full quarter of scientific claims pointing to ‘evidence’ turn out when checked to be citing something that doesn’t support their point! This error rate feels roughly in line with my own experiences and that’s why it’s always worth verifying citations for dubious claims.
The reality is that academic output, especially in anything that involves statistical modelling, frequently turns out to not merely be unreliable but leaves the reader with the impression that the authors must have started with a desired conclusion and then worked backwards to try and find sciencey-sounding points to support it. Inconvenient data is claimed not to exist, convenient data is cherry picked, and where no convenient data can be found it’s just conjured into existence. Claims are made and cited but the citations don’t contain supporting evidence, or turn out to be just more assumptions. Every possible outcome is modelled and all but the most alarming are discarded. The scientific method is inconsistently used, at best, and instead scientism rules the day; meanwhile, universities applaud and defend this behaviour to the bitter end. Academia is in serious trouble: huge numbers of researchers just have no standards whatsoever and there are no institutional incentives to care.
Some readers will undoubtably wonder why we’re still bothering to do this kind of analysis given that there’s nothing really new here. On the Daily Sceptic alone we’ve covered these sorts of errors here, here, here, here, here and here – and that’s not even a comprehensive list. So why bother? I think it’s worth continuing to do this kind of work for a couple of reasons:
- Many people who didn’t doubt the science last year have developed newfound doubts this year, but won’t search through the archives to read old articles.
- The continued publication of these sorts of ‘papers’ is itself useful information. It shows that academia doesn’t seem to be capable of self-improvement and despite a long run of prediction failures, nobody within the institutions cares about the collective reputation of professors. The appearance of being scientific is what matters. Actually being scientific, not so much.
Majority of Covid ICU Patients in October and November Were Vaccinated
By Will Jones – The Daily Sceptic – December 11, 2021
Contrary to the claims made by Dr Rachel Clarke and Professor Stephen Powis last month and used to blame the unvaccinated for the mounting troubles of the NHS, new data out this week shows that the majority of Covid ICU admissions in October and November were among the vaccinated, not the unvaccinated.
The latest report from ICNARC shows that of Covid ICU patients in England, Wales and Northern Ireland, 50.5% in October and 50.7% in November were double vaccinated. Add to that the 2.8% in October and 1.8% in November who were single-vaccinated and you get overall vaccinated proportions of 53.3% in October and 52.5% in November. That compares to 46.7% unvaccinated in October and 47.5% in November. Note that the unvaccinated here includes people who received a vaccine less than 14 days prior to the positive Covid test, so includes some (an unknown number) who are actually single vaccinated.
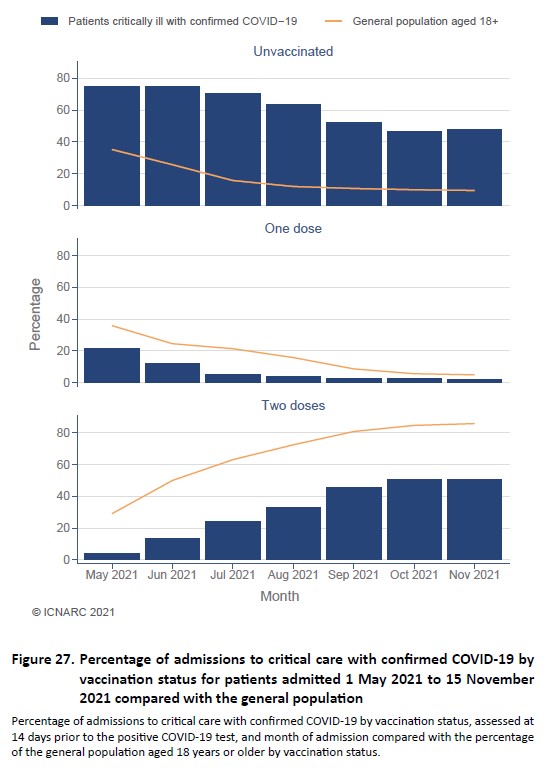
This is not what the public has been led to believe by some prominent medics and newspapers.
Two weeks ago, Professor Stephen Powis, the National Medical Director of NHS England, was quoted in the Sunday Times saying: “Data shows that the overwhelming majority of people admitted to intensive care with Covid are not fully vaccinated.” A source was not provided for this claim but the article implied that it meant right now, with an opening paragraph stating: “Hundreds of intensive care beds that could be used for life-saving surgery are instead occupied by unvaccinated Covid patients, one of NHS England’s top officials has said.”
The same day the Sunday Times also printed an article by Dr. Rachel Clarke with the subheading: “Some 75% of those suffocating in intensive care with the coronavirus are unvaccinated.” In it she states: “Of the Covid patients treated in intensive care in recent months, the majority – nearly 75% according to the latest data – have chosen not to be vaccinated.”
The Guardian published a piece in November headlined “ICU is full of the unvaccinated – my patience with them is wearing thin”, written by an anonymous medic who claimed that the ICU patient population “consists of a few vulnerable people with severe underlying health problems and a majority of fit, healthy, younger people unvaccinated by choice”.
Now that the data has been released it’s clear that the claim that ICUs are “full of” the unvaccinated is highly misleading. While the unvaccinated do currently appear to be over-represented (depending how many of them are misclassified), no one now can claim that ICUs are “full of” the unvaccinated or that the unvaccinated constitute the “overwhelming majority” of Covid ICU admissions. If you spot any newspapers still peddling this misinformation, particularly it if is being used to stigmatise and pressure the unvaccinated, you can complain to IPSO here.
Featured Video

Broke Princes: Saudi Arabia’s Powder Keg
or go to
Aletho News Archives – Video-Images
From the Archives
Registered Israeli foreign agent driving contrived campus antisemitism crisis
By Wyatt Reed | The Grayzone | December 17, 2023
Lawsuits accusing top US universities of harboring antisemitism all originate from one source: a corporate law firm that fielded the pro-settler ex-US ambassador to Israel, and which was registered as a foreign agent of an Israeli principal as recently as 2021.
The firm now represents professional Israel lobby activists posing as victimized “Jewish students” and seeking to crush the free speech rights of Palestine solidarity activists. … continue
Blog Roll
 Aletho News
- How Iran defeated Trump’s Israel First GOP
- De-escalating the conflict: What the OSCE, the UN, and Europe are (not) doing to prevent war
- Desperate For A Renewed Iran War, Israel Dusts Off The WMD Deception.
- US Elections Offer Choice Between ‘Bad and Worse’ as Both Parties Serve War Lobby – ex-UN Expert
- Ghalibaf warns US government not to betray voters who rejected war
- Broke Princes: Saudi Arabia’s Powder Keg
- Albania’s Crisis: Rama, Israeli Investments and the Demand for Accountability
- Hezbollah Categorically Denies Syrian Accusations: We Aim at Confronting Israeli Enemy, Not Undermining Syria’s Stability
- Trump claims funding to Israel ending in 2026 as merger of Israeli–US armies looms
- Iran Weathering The Storm, But Saudi Arabia Is Sinking
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago

