Memo to the Guardian: Have you muzzled the facts on masks?
By David Seedhouse | TCW Defending Freedom | November 27, 2021
This is an open letter to Andrew Gregory, Health Editor of the Guardian.
Dear Andrew,
We are a group of citizens dedicated to promoting a more open, democratic society. We have tried to contact you on several occasions without success, so we have published this open letter in the hope you will see it and reply.
On November 18, you published a story with the headline: ‘Mask-wearing cuts Covid incidence by 53%, says global study.’
The sub-heading was: ‘Researchers said results highlight the need to continue with face coverings, social distancing and handwashing alongside vaccine programmes’.
We were struck by this, since it goes against a substantial body of evidence that concludes that mask-wearing offers little if any protection against viruses, for example these studies https://swprs.org/face-masks-evidence/ https://www.professorhinkley.com/blog/sorry-oregon-your-mask-is-useless-according-to-the-science; https://www.city-journal.org/do-masks-work-a-review-of-the-evidence.
You did not reference the paper on which you base your article but an internet search reveals it. (Stella Talic corresponding author). You paraphrase uncritically: ‘Vaccines are safe and effective and saving lives around the world. But … it is not yet known if jabs will prevent future transmission of emerging coronavirus variants …
‘Results from more than 30 studies from around the world were analysed in detail, showing a statistically significant 53 per cent reduction in the incidence of Covid with mask wearing …’
We find it puzzling that you did not mention that ten days earlier the CATO Institute (an American libertarian think-tank) published a 61-page working paper entitled: Evidence for Community Cloth Face Masking to Limit the Spread of SARS-CoV 2: A Critical Review.
It tentatively concluded: ‘Of 16 quantitative meta-analyses, eight were equivocal or critical as to whether evidence supports a public recommendation of masks, and the remaining eight supported a public mask intervention on limited evidence, primarily on the basis of the precautionary principle.’
Given this striking incongruity, we have ten questions:
1. Have you read the Talic paper?
2. Do you agree that it is an exaggeration to describe it as a ‘global study’?
3. Have you read the associated British Medical Journal editorial?
4. Do you agree that your headline: ‘Mask-wearing cuts Covid incidence by 53%, says global study’ is misleading?
5. Were you aware of this when you chose the heading?
6. Why has the Guardian not published the results of the many studies which say there is no evidence of benefit and some evidence of harm?
7. Do you agree that professional journalism requires balance, in the public interest?
8. Would a more accurate headline be: ‘The majority of randomised controlled trials fail to establish that wearing face masks protects anyone against viruses’?
9. Is the Guardian’s policy to publish only information that supports a particular set of beliefs?
10. Are you prepared publicly to debate this matter?
Here is a little more detail about our concerns. The CATO meta-analysis states: ‘In non-healthcare settings, of the 14 RCTs (randomised control trials) identified by the authors that evaluated face mask efficacy compared to no-mask controls in protecting against respiratory infections other than Covid-19, 13 failed to find statistically significant benefits … of eight RCTs that evaluated face mask efficacy against respiratory illness transmission in non-healthcare household settings, all eight failed to find a statistically significant benefit for the use of face masks alone …’
This gives a very different picture from the one your newspaper article presented.
Talic et al claim to have screened 36,729 papers, but found only six on masks they considered eligible for inclusion. Yet an internet search reveals numerous relevant research articles. How can the authors have overlooked this, and how can their conclusion be true given the many other conflicting studies?
We dug a little deeper and found that several of the papers cited by Talic et al are telephone surveys covering multiple variables, with questionable methodology.
For example, one study investigated the effectiveness of mask-wearing in families in their homes of laboratory-confirmed Covid-19 cases in Beijing and concluded that face mask use was ’79 per cent effective in reducing transmission’.
Strangely, the paper contains a passage that seems to undermine the whole study: ‘As the compliance of UFMU (universal face mask use) would be poor in the home, there was difficulty and also no necessity for everyone to wear masks at home …’
This seems to imply that the use of face masks by family members in their households included in the study was sporadic and that therefore the study has no scientific merit.
Equally strange, one of six papers referenced in the Talic paper is the Danish RCT mask study, which the authors presumably included to support their conclusions, even though it doesn’t. In fact, the study was inconclusive (a difference of between 1.8 per cent and 2.1 per cent)
Even more peculiar, the Talic article is linked in the BMJ to an editorial published simultaneously which directly refutes the claim of a 53 per cent reduction in Covid incidence.
It says: ‘Face masks seem to have a real but small effect for wearer and source control, although final conclusions should await full reports of the trials from Bangladesh and Guinea-Bissau.
‘However, the quality of the current evidence would be graded – by GRADE (Grading of Recommendations, Assessment, Development and Evaluations) criteria – as low or very low, as it consists of mainly observational studies with poor methods (biases in measurement of outcomes, classification of PHSM – Public Health and Social Measures – and missing data), and high heterogeneity of effect size. More and better research are needed.’
How can such inconsistencies be overlooked by a senior editor of a quality broadsheet?
Signed
Professor David Seedhouse, BSc (Hons), PhD
Bruce Luffman
Sarah Goode, PhD
Alex Thorn
Simon Fletcher
Sandy French
Fiona Swan, LLB, Solicitor (Rtd.)
Monica Coyle
Daphne Havercroft, Project Management Professional (PMP)®
Phil Button, BSc, MBCS
Professor Chris Jesshope, BSc Hons (Mathematics), MSc (computer science), PhD (electronics)
Philip Morkel, Managing Director Engineering Services, Law Degree, MBA, S/W Project management
Tony Woodcock
Dr Damien Bush, MA, VetMB, Cert. SAS, MRCVS, RCVS, Recognised Advanced Practitioner Small Animal Surgery
Neil Sherry
Michael Welby
Shirley Dudfield
Maddy Conway
Peter Whitehead
Vanessa Peutherer, Author, Learning & Development Consultant (Health Care Ethics), RGN, ENG, ENB (Rtd)
Michael Philips, BSc (Hons) Mathematics
Edina Atkinson
Adam Mockett, BA (Hons)
Mike Davies, Project Manager (Rtd)
Alex Camm MPhil, CQSW
Susan James, FCILEX
Myra Forster-van Hijfte, DVM, CertVR CertSAM, DipECVIM, FRCVS
Dr. Jo-Ann van Eijck, Ph.D, Former Associate Professor at University of Hong Kong
Helen Myles, BSc (Hons) Maths and Psychology
How to escape Google
Do you belong to the 94% of Internet users who have no clue?
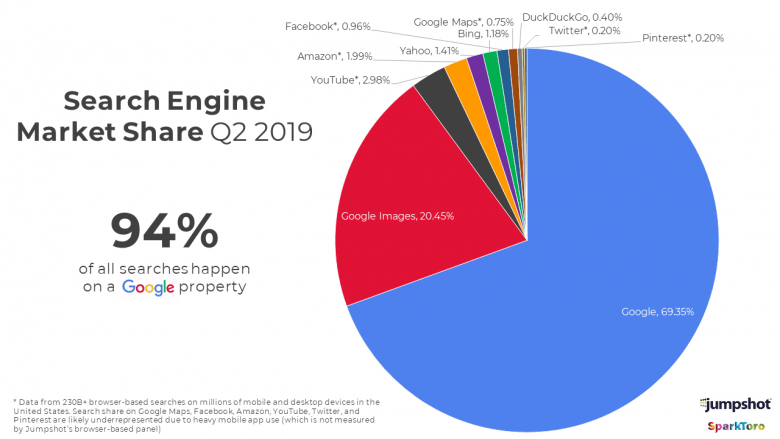
The US search engine market in 2019 (SparkToro)
Swiss Policy Research | November 25, 2021
Google Search has a US online search market share of about 70%, or even 94% if Google Images, Google Maps and Google-owned YouTube are added (see chart above).
If you belong to these 94%, there is some bad news for you.
As a well-known US podcaster recently discovered, Google is indeed “hiding information” from its users. This has actually been known for many years, but it has become especially obvious and serious during the coronavirus pandemic.
In fact, censorship by Google has become so bad that nowadays, advanced Internet users are using Google primarily to monitor the current extent of censorship, not to actually search for anything. US researcher Dr. Robert Epstein termed it the Search Engine Manipulation Effect (SEME).
Of note, Google censorship affects not just search results, but even search suggestions. In other words, Google is first manipulating what you search for, only to then additionally manipulate what results you will get. It is well worth trying this out yourself to appreciate the effect (see below).
What is Google hiding from you? In short, they are hiding “non-authoritative sources”. In other words, they are hiding stuff those in power don’t want you to know or to even think of.
This is not all that surprising, given that Google initially was a research and startup project funded and supported by US intelligence and the military to “retain information superiority”.
Essentially, Google Search has become an online prison library.
Fortunately, there are a few alternatives to Google Search, although not as many as one might think. In fact, there are currently only two real alternatives to Google Search.
These two alternatives are Microsoft Bing and Russian Yandex.
The fact that Microsoft as a monopolistic corporation and Yandex as a Russian provider are offering more or less uncensored search results is somewhat ironic, and both of them may have their own reasons for doing so. But these are currently the only real alternatives to Google.
What about the many other, independent search engines, though? The truth is, most of them are neither independent, nor even actual search engines, as most of them simply rely on results provided by Google or Bing.
For instance, Startpage is simply providing Google search results.
DuckDuckGo, Yahoo, Qwant, Ecosia, Swisscows, MetaGer and other search engines are primarily relying on Microsoft Bing, although some of them may be adding a few other contextual sources or important privacy features. But with most searches, you will simply get Bing results.
If Microsoft Bing, one day, should decide to apply Google-style censorship (or get forced to do so), sophisticated Western Internet users will either have to rely on Russian Yandex, or will finally have to create an independent, real and uncensored search engine.
Otherwise, the Internet is going to become a pretty dark place, literally.
(Update: In June 2021, independent browser developer Brave beta-launched its own search engine, Brave Search, which is creating and using its own search index. If successful, Brave Search may become the first true, non-Russian alternative to Google Search and Microsoft Bing.)
One more thing: YouTube. YouTube belongs to Google, too (since 2006).
This is why it has become increasingly difficult to find YouTube videos on “controversial topics”. In many cases, what you are looking for may already have been deleted by YouTube, but even if not, it may not be displayed in the highly censored YouTube search results and recommendations.
Instead, one has to use an alternative search engine based on Bing – which is indexing YouTube videos independently – and then search for the topic by adding “site:youtube.com”.
Or, better still, use an alternative video platform from the outset, like Odysee, Bitchute, Rumble, Brighteon, DTube, or even Archive.org.
Independent video producers, too, increasingly have to switch to these alternative platforms, as creating videos on YouTube nowadays is like building a sandcastle too close to the water.
To learn more about online media sources, search engines, ad blockers, bypassing paywalls and censorship, see Advanced Online Media Use: Seven Recommendations.
Google vs. Yandex
Russian Yandex seems to be manipulating search suggestions in the opposite way of Google. For instance, when searching for “Pfizer vaccine”, the first two search suggestions currently are “Pfizer vaccine deaths” and “Pfizer vaccine side effects”. Meanwhile, on Google, “Pfizer vaccine” is being auto-completed to “near me”, “booster”, “FDA approval”, “for kids”, or “efficacy”.
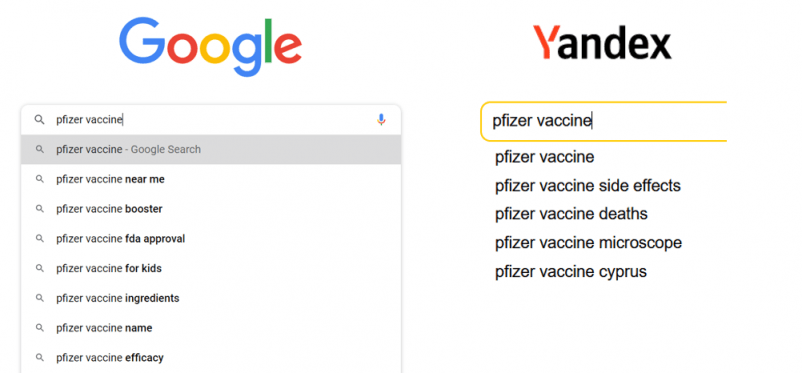
“Pfizer vaccine”: Yandex vs. Google
Google vs. Bing
Coronavirus: a “planned pandemic” (Bing) or “planning tools” (Google)?
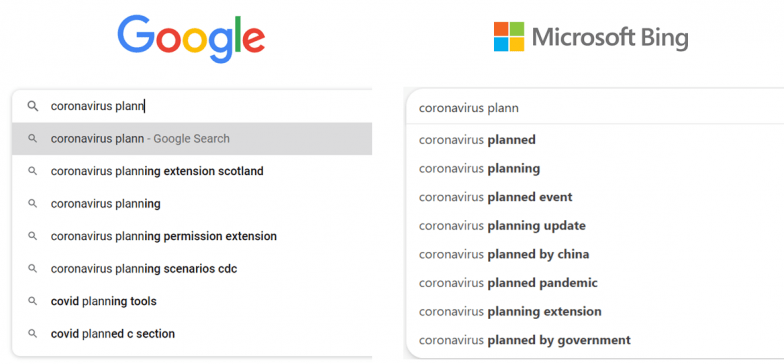
Coronavirus: Google vs. Bing
Literature
- The new mind control (Dr. Robert Epstein, Aeon, 2016)
- How the CIA made Google (Nafeez Ahmed, Medium, 2015)
- Google is not what it seems (Julian Assange, Wikileaks, 2014)
- The Military Origins of Facebook (Whitney Webb, Unlimited Hangout, 2021)
- Surveillance Valley: The Secret Military History of the Internet (Yasha Levine, 2018)
See also:
COVID-19: Moderna Gets Its Miracle

BY WHITNEY WEBB |
UNLIMITED HANGOUT| OCTOBER 28, 2021
COVID-19 erased the regulatory and trial-related hurdles that Moderna could never surmount before. Yet, how did Moderna know that COVID-19 would create those conditions months before anyone else, and why did they later claim that their vaccine being tested in NIH trials was different than their commercial candidate?
In late 2019, the biopharmaceutical company Moderna was facing a series of challenges that not only threatened its ability to ever take a product to market, and thus turn a profit, but its very existence as a company. There were multiple warning signs that Moderna was essentially another Theranos-style fraud, with many of these signs growing in frequency and severity as the decade drew to a close. Part I of this three-part series explored the disastrous circumstances in which Moderna found itself at that time, with the company’s salvation hinging on the hope of a divine miracle, a “Hail Mary” save of sorts, as stated by one former Moderna employee.
While the COVID-19 crisis that emerged in the first part of 2020 can hardly be described as an act of benevolent divine intervention for most, it certainly can be seen that way from Moderna’s perspective. Key issues for the company, including seemingly insurmountable regulatory hurdles and its inability to advance beyond animal trials with its most promising—and profitable—products, were conveniently wiped away, and not a moment too soon. Since January 2020, the value of Moderna’s stock—which had embarked on a steady decline since its IPO—grew from $18.89 per share to its current value of $339.57 per share, thanks to the success of its COVID-19 vaccine.
Yet, how exactly was Moderna’s “Hail Mary” moment realized, and what were the forces and events that ensured it would make it through the FDA’s emergency use authorization (EUA) process? In examining that question, it becomes quickly apparent that Moderna’s journey of saving grace involved much more than just cutting corners in animal and human trials and federal regulations. Indeed, if we are to believe Moderna executives, it involved supplying formulations for some trial studies that were not the same as their COVID-19 vaccine commercial candidate, despite the data resulting from the former being used to sell Moderna’s vaccine to the public and federal health authorities. Such data was also selectively released at times to align with preplanned stock trades by Moderna executives, turning many of Moderna’s highest-ranking employees into millionaires, and even billionaires, while the COVID-19 crisis meant economic calamity for most Americans.
Not only that, but—as Part II of this three-part series will show, Moderna and a handful of its collaborators at the National Institutes of Health (NIH) seemed to know that Moderna’s miracle had arrived—well before anyone else knew or could have known. Was it really a coincidental mix of “foresight” and “serendipity” that led Moderna and the NIH to plan to develop a COVID-19 vaccine days before the viral sequence was even published and months before a vaccine was even considered necessary for a still unknown disease? If so, why would Moderna—a company clearly on the brink—throw everything into and gamble the entire company on a vaccine project that had no demonstrated need at the time?
The Serendipitous Origins of Moderna’s COVID-19 Vaccine
When early January 2020 brought news of a novel coronavirus outbreak originating in Wuhan, China, Moderna’s CEO Stéphane Bancel immediately emailed Barney Graham, deputy director of the Vaccine Research Center at the National Institutes of Health, and asked to be sent the genetic sequence for what would become known as SAR-CoV-2, allegedly because media reports on the outbreak “troubled” him. The date of that email varies according to different media reports, though most place it as having been sent on either January 6th or 7th.
A few weeks before Bancel’s email to Graham, Moderna was quickly approaching the end of the line, their desperately needed “Hail Mary” still not having materialized. “We were freaked out about money,” Stephen Hoge would later remember of Moderna’s late 2019 circumstances. Not only were executives “cutting back on research and other expenditures” like never before, but – as STAT News would later report – “cash from investors had stopped pouring in and partnerships with some drug makers had been discontinued. In meetings at Moderna, Bancel emphasized the need to stretch every dollar and employees were told to reduce travel and other expenses, a frugality they were advised would last several years.”
At the tail end of 2019, Graham was in a very different mood than Bancel, having emailed the leader of the coronavirus team at his NIH lab saying, “Get ready for 2020,” apparently viewing the news out of Wuhan in late 2019 as a harbinger of something significant. He went on, in the days before he was contacted by Bancel, to “run a drill he had been turning over in his mind for years” and called his long-time colleague Jason McLellan “to talk about the game plan” for getting a head start on producing a vaccine the world did not yet know it needed. When Bancel called Graham soon afterward and asked about this new virus, Graham responded that he didn’t know yet but that “they were ready if it turned out to be a coronavirus.” The Washington Post claimed that Graham’s apparent foreknowledge that a coronavirus vaccine would be needed before anyone officially knew what type of disease was circulating in Wuhan was a fortunate mix of “serendipity and foresight.”

Dr. Barney Graham and Dr. Kizzmekia Corbett, VRC coronavirus vaccine lead, discuss COVID-19 research with Sen. Chris Van Hollen, Sen. Benjamin Cardin and Rep. Jamie Raskin, March 6, 2020; Source: NIH
A report in Boston magazine offers a slightly different account than that reported by the Washington Post. Per that article, Graham had told Bancel, “If [the virus] is a coronavirus, we know what to do and have proven mRNA is effective.” Per that report, this assertion of efficacy from Graham referred to Moderna’s early stage human-trial data published in September 2019 regarding its chikungunya vaccine candidate, which was funded by the Defense Advanced Research Projects Agency (DARPA), as well as its cytomegalovirus (CMV) vaccine candidate.
As mentioned in Part I of this series, the chikungunya vaccine study data released at that time included the participation of just four subjects, three of whom developed significant side effects that led Moderna to state that they would reformulate the vaccine in question and would pause trials on that vaccine candidate. In the case of the CMV vaccine candidate, the data was largely positive, but it was widely noted that the vaccine still needed to pass through larger and longer clinical trials before its efficacy was in fact “proven,” as Graham later claimed. In addition, Graham implied that this early stage trial of Moderna’s CMV vaccine candidate was somehow proof that an mRNA vaccine would be effective against coronaviruses, which makes little sense since CMV is not a coronavirus but instead hails from the family of viruses that includes chickenpox, herpes, and shingles.
Bancel apparently had reached out to Graham because Graham and his team at the NIH had been working in direct partnership with Moderna on vaccines since 2017, soon after Moderna had delayed its Crigler-Najjar and related therapies in favor of vaccines. According to Boston magazine, Moderna had been working closely with Graham specifically “on [Moderna’s] quest to bring a whole new class of vaccines to market” and Graham had personally visited Moderna’s facilities in November 2019. Dr. Anthony Fauci, the director of the NIH’s infectious-disease division NIAID, has called his unit’s collaboration with Moderna, in the years prior to and also during the COVID-19 crisis, “most extraordinary.”
The year 2017, besides being the year when Moderna made its pivot to vaccines (due to its inability to produce safe multidose therapies, see Part I), was also a big year for Graham. That year he and his lab filed a patent for the “2P mutation” technique whereby recombinant coronavirus spike proteins can be stabilized in a prefusion state and used as more effective immunogens. If a coronavirus vaccine were to be produced using this patent, Graham’s team would financially benefit, though federal law caps their annual royalties. Nonetheless, it would still yield a considerable sum for the named researchers, including Graham.
However, due to the well-known difficulties with coronavirus vaccine development, including antibody dependent enhancement risk, it seemed that commercial use of Graham’s patent was a pipe dream. Yet, today, the 2P mutation patent, also known as the ’070 patent, is not just in use in Moderna’s COVID-19 vaccine, but also in the COVID-19 vaccines produced by Johnson & Johnson, Novavax, Pfizer/BioNTech, and CureVac. Experts at New York University School of Law have noted that the 2P mutation patent first filed in 2016 “sounds remarkably prescient” in light of the COVID crisis that emerged a few years later while later publications from the NIH (still pre-COVID) revealed that the NIH’s view on “the breadth and importance of the ’070 patent” as well as its potential commercial applications was also quite prescient, given that there was little justification at the time to hold such a view.
On January 10, three days after the reported initial conversation between Bancel and Graham on the novel coronavirus outbreak in Wuhan, China, Graham met with Hamilton Bennett, the program leader for Moderna’s vaccine portfolio. Graham asked Bennett “if Moderna would be interested in using the new [novel coronavirus] to test the company’s accelerated vaccine-making capabilities.” According to Boston, Graham then mused, “That way . . . if ever there came a day when a new virus emerged that threatened global public health, Moderna and the NIH could know how long it would take them to respond.”
Graham’s “musings” to Bennett are interesting considering his earlier statements made to others, such as “Get ready for 2020” and his team, in collaboration with Moderna, would be “ready if [the virus then circulating in Wuhan, China] turned out to be a coronavirus.” Is this merely “serendipity” and “foresight”, as the Washington Post suggested, or was it something else? It is worth noting that the above accounts are those that have been given by Bancel and Graham themselves, as the actual contents of these critical January 2020 emails have not been publicly released.
When the genetic sequence of SARS-CoV-2 was published on January 11, NIH scientists and Moderna researchers got to work determining which targeted genetic sequence would be used in their vaccine candidate. Later reports, however, claimed that this initial work toward a COVID-19 vaccine was merely intended to be a “demonstration project.”
Other odd features of the Moderna-NIH COVID-19 vaccine-development story emerged with Bancel’s account of the role the World Economic Forum played in shaping his “foresight” when it came to the development of a COVID-19 vaccine back in January 2020. On January 21, 2020, Bancel reportedly began to hear about “a far darker version of the future” at the World Economic Forum (WEF) annual meeting in Davos, Switzerland, where he spent time with “two [anonymous] prominent infectious-disease experts from Europe” who shared with him data from “their contacts on the ground in China, including Wuhan.” That data, per Bancel, showed a dire situation that left his mind “reeling” and led him to conclude, that very day, that “this isn’t going to be SARS. It’s going to be the 1918 flu pandemic.”

Stéphane Bancel speaks at the Breakthroughs in Cancer Care session at WEF annual meeting, January 24, 2020; Source: WEF
This realization is allegedly what led Bancel to contact Moderna cofounder and chairman, as well as a WEF technology pioneer, Noubar Afeyan. Bancel reportedly interrupted Afeyan’s celebration of his daughter’s birthday to tell him “what he’d learned about the virus” and to suggest that “Moderna begin to build the vaccine—for real.” The next day, Moderna held an executive meeting, which Bancel attended remotely, and there was considerable internal debate about whether a vaccine for the novel coronavirus would be needed. To Bancel, the “sheer act of debating” pursuing a vaccine for the virus was “absurd” given that he was now convinced, after a single day at Davos, that “a global pandemic was about to descend like a biblical plague, and whatever distractions the vaccine caused internally at Moderna were irrelevant.”
Bancel spent the rest of his time at the Davos annual meeting “building partnerships, generating excitement, and securing funding,” which led to the Moderna collaboration agreement with the Coalition for Epidemic Preparedness Innovations—a project largely funded by Bill Gates. (Bancel and Moderna’s cozy relationship with the WEF, dating back to 2013, was discussed in Part I as were the Forum’s efforts, beginning well before COVID-19, to promote mRNA-based therapies as essential to the remaking of the health-care sector in the age of the so-called Fourth Industrial Revolution). At the 2020 annual meeting attended by Bancel and others it was noted that a major barrier to the widespread adoption of these and other related “health-care” technologies was “public distrust.” The panel where that issue was specifically discussed was entitled “When Humankind Overrides Evolution.”
As also noted in Part I of this series, a few months earlier, in October 2019, major players in what would become the Moderna COVID-19 vaccine, particularly Rick Bright and Anthony Fauci, had discussed during a Milken Institute panel on vaccines how a “disruptive” event would be needed to push the public to accept “nontraditional” vaccines such as mRNA vaccines; to convince the public that flu-like illnesses are scarier than traditionally believed; and to remove existing bureaucratic safeguards in the vaccine development-and-approval processes.
That panel took place less than two weeks after the Event 201 simulation, jointly hosted by the World Economic Forum, the Bill & Melinda Gates Foundation, and the Johns Hopkins Center for Health Security. Event 201 simulated “an outbreak of a novel zoonotic coronavirus” that was “modeled largely on SARS but . . . more transmissible in the community setting by people with mild symptoms.” The recommendations of the simulation panel were to considerably increase investment in new vaccine technologies and industrial approaches, favoring rapid vaccine development and manufacturing. As mentioned in Part I, the Johns Hopkins Center for Health Security had also conducted the June 2001 Dark Winter simulation that briefly preceded and predicted major aspects of the 2001 anthrax attacks, and some of its participants had apparent foreknowledge of those attacks. Other Dark Winter participants later worked to sabotage the FBI investigation into those attacks after their origin was traced back to a US military source.
It is hard to imagine that Bancel, whose company had long been closely partnered with the World Economic Forum and the Gates Foundation, was unaware of the exercise and surprised by the closely analogous event that transpired within three months. Given the accounts given by Bancel, Graham, and others, it seems likely there is more to the story regarding the origins of Moderna’s early and “serendipitous” push to develop a COVID-19 vaccine. In addition, given that Moderna was in dire financial circumstances at the time, it seems odd that the company would gamble everything on a vaccine project that was opposed by the few investors that were still willing to fund Moderna in January/February 2020. Why would they divert their scant resources towards a project born only out of Barney Graham’s “musings” that Moderna could try to test the speed of its vaccine development capabilities and Bancel’s doomsday view that a “biblical plague” was imminent, especially when their investors opposed the idea?
Moderna Gets to Bypass Its Long-Standing Issues with R & D
Moderna produced the first batch of its COVID-19 vaccine candidate on February 7, one month after Bancel and Graham’s initial conversation. After a sterility test and other mandatory tests, the first batch of its vaccine candidate, called mRNA-1273, shipped to the NIH on February 24. For the first time in a long time, Moderna’s stock price surged. NIH researchers administered the first dose of the candidate into a human volunteer less than a month later, on March 16.
Controversially, in order to begin its human trial on March 16, regulatory agencies had to allow Moderna to bypass major aspects of traditional animal trials, which many experts and commentators noted was highly unusual but was now deemed necessary due to the urgency of the crisis. Instead of developing the vaccine in distinct sequential stages, as is the custom, Moderna “decided to do all of the steps [relating to animal trials] simultaneously.” In other words, confirming that the candidate is working before manufacturing an animal-grade vaccine, conducting animal trials, analyzing the animal-trial data, manufacturing a vaccine for use in human trials, and beginning human trials were all conducted simultaneously by Moderna. Thus, the design of human trials for the Moderna vaccine candidate was not informed by animal-trial data.

Lt. Javier Lopez Coronado and Hospitalman Francisco Velasco inspect a box of COVID-19 vaccine vials at the Naval Health Clinic in Corpus Christi, TX, December 2020; Source: Wikimedia
This should have been a major red flag, given Moderna’s persistent difficulties in getting its products past animal trials. As noted in Part I, up until the COVID-19 crisis, most of Moderna’s experiments and products had only been tested in animals, with only a handful able to make it to human trials. In the case of the Crigler-Najjar therapy that it was forced to indefinitely delay, toxicity concerns related to the mRNA delivery system being used had emerged in the animal trials, which Moderna was now greenlighted to largely skip. Given that Moderna had subsequently been forced to abandon all multidose products because of poor results in animal trials, being allowed to skip this formerly insurmountable obstacle was likely seen as a boon to some at the company. It is also astounding that, given Moderna’s history with problematic animal trials, more scrutiny was not devoted to the regulatory decision to allow Moderna to essentially skip such trials.
Animal studies conducted on Moderna’s COVID-19 vaccine did identify problems that should have informed human trials, but this did not happen because of the regulatory decision. For example, animal reproductive toxicity studies on the Moderna COVID-19 vaccine that are cited by the European Medicines Agency found that there was reduced fertility in rats that received the vaccine (e. g., overall pregnancy index of 84.1% in vaccinated rats versus 93.2% in the unvaccinated) as well as an increased proportion of aberrant bone development in their fetuses. That study has been criticized for failing to report on the accumulation of vaccine in the placenta as well as failing to investigate the effect of vaccine doses administered during key pregnancy milestones, such as embryonic organogenesis. In addition, the number of animals tested is unstated, making the statistical power of the study unknown. At the very least, the 9 percent drop in the fertility index among vaccinated rats should have prompted expanded animal trials to investigate concerns of reproductive toxicity before testing in humans.
Yet, Moderna declined to further investigate reproductive toxicity in animal trials and entirely excluded reproductive toxicity studies from its simultaneous human trials, as pregnant women were excluded from participation in the clinical trials of its vaccine. Despite this, pregnant women were labeled a priority group for receiving the vaccine after Emergency Use Authorization (EUA) was granted for the Moderna and Pfizer/BioNTech vaccines. Per the New England Journal of Medicine, this meant that “pregnant women and their clinicians were left to weigh the documented risks of Covid-19 infection against the unknown safety risks of vaccination in deciding whether to receive the vaccine.”
Moderna only began recruiting for an “observational pregnancy outcome study” of its COVID-19 vaccine in humans in mid-July 2021, and that study is projected to conclude in early 2024. Nevertheless, the Centers for Disease Control recommends the use of Moderna’s COVID-19 vaccine in “people who are pregnant, breastfeeding, trying to get pregnant now, or might become pregnant in the future.” This recommendation is largely based on the CDC’s publication of preliminary data on mRNA COVID-19 vaccine safety in pregnant women in June 2021, which is based on passive reporting systems in use within the United States (i. e., VAERS and v-safe).
Even in the limited scope of this study, 115 of the 827 women who had a completed pregnancy during the study lost the baby, 104 of which were spontaneous abortions before 20 weeks of gestation. Of these 827 pregnant women, only 127 had received a mRNA vaccine before the 3rd trimester. This appears to suggest an increased risk among those women who took the vaccine before the 3rd trimester, but the selective nature of the data makes it difficult to draw any definitive conclusions. Despite claims from the New England Journal of Medicine that the study’s data was “reassuring”, the study’s authors ultimately stated that their study, which mainly looked at women who began vaccination in the third trimester, was unable to draw “conclusions about spontaneous abortions, congenital anomalies, and other potential rare neonatal outcomes.” This is just one example of the problems caused by “cutting corners” with respect to Moderna’s COVID-19 vaccine trials in humans and animals, including those conducted by the NIH.
Meanwhile, throughout February, March and April, Bancel was “begging for money” as Moderna reportedly lacked “enough money to buy essential ingredients for the shots” and “needed hundreds of millions of dollars, perhaps even more than a billion dollars” to manufacture its vaccine, which had only recently begun trials. Bancel, whose tenure at Moderna had long been marked by his ability to charm investors, kept coming up empty-handed.
Then, in mid-April 2020, Moderna’s long-time cooperation with the US government again paid off when Health and Human Services Biomedical Advanced Research and Development Authority (BARDA) awarded the company $483 million to “accelerate the development of its vaccine candidate for the novel coronavirus.” A year later, the amount invested in Moderna’s COVID-19 vaccine by the US government had grown to about $6 billion dollars, just $1.5 billion short of the company’s entire value at the time of its pre-COVID IPO.
BARDA, throughout 2020, was directly overseen by the HHS Office of the Assistant Secretary for Preparedness and Response (ASPR), led by the extremely corrupt Robert Kadlec, who had spent roughly the last two decades designing BARDA and helping shape legislation that concentrated many of the emergency powers of HHS under the Office of the ASPR. Conveniently, Kadlec occupied the powerful role of ASPR that he had spent years sculpting at the exact moment when the pandemic, which he had simulated the previous year via Crimson Contagion, took place. As mentioned in Part I, he was also a key participant in the June 2001 Dark Winter exercise. In his capacity as ASPR during 2020, Kadlec oversaw nearly all major aspects of the HHS COVID-19 response and had a key role in BARDA’s funding decisions during that period, as well as in the affairs of the NIH and the Food and Drug Administration as they related to COVID-19 medical countermeasures, including vaccines.
On May 1, 2020, Moderna announced a ten-year manufacturing agreement with the Lonza Group, a multinational chemical and biotech company based in Switzerland. Per the agreement, Lonza would build out vaccine production sites for Moderna’s COVID-19 vaccine, first in the US and Switzerland, before expanding to Lonza’s facilities in other countries. The scale of production discussed in the agreement was to produce 1 billion doses of Moderna’s COVID-19 vaccine annually. It was claimed that the ten-year agreement would also focus on other products, even though it was well known at the time that other Moderna products were “nowhere close to being ready for the market.” Moderna executives would later state that they were still scrambling for the cash to manufacture doses at the time the agreement with Lonza was made.
The decision to forge a partnership to produce that quantity of doses annually suggests marvelous foresight on the part of Moderna and Lonza that the COVID-19 vaccine would become an annual or semiannual affair, given that current claims of waning immunity could not have been known back then because initial trials of the Moderna vaccine had begun less than two months earlier and there was still no published data on its efficacy or safety. However, as will be discussed Part III of this series, Moderna needs to sell “pandemic level” quantities of its COVID-19 vaccine every year in order to avoid a return of the existential crises it faced before COVID-19 (for more on those crises, see Part I). The implications of this, given Moderna’s previous inability to produce a safe product for multidosing and lack of evidence that past issues were addressed in the development of its COVID-19 vaccine, will also be discussed in Part III of this series.
It is also noteworthy that, like Moderna, Lonza as a company and its leaders are closely affiliated with the World Economic Forum. In addition, at the time the agreement was reached in May 2020, Moncef Slaoui, the former GlaxoSmithKline executive, served on the boards of both Moderna and Lonza. Slaoui withdrew from the boards of both companies two weeks after the agreement was reached to become the head of the US-led vaccination-development drive Operation Warp Speed. Moderna praised Slaoui’s appointment to head the vaccination project.
By mid-May, Moderna’s stock price—whose steady decline before COVID-19 was detailed in Part I —had tripled since late February 2020, all on high hopes for its COVID-19 vaccine. Since Moderna’s stock had begun to surge in February, media reports noted that “nearly every progress update—or media appearance by Moderna CEO Stephane Bancel—has been gobbled up by investors, who seem to have an insatiable appetite for the stock.” Bancel’s tried-and-tested method of keeping Moderna afloat on pure hype, though it was faltering before COVID-19, was again paying off for the company thanks to the global crisis and related panic.
Some critics did emerge, however, calling Moderna’s now $23 billion valuation “insane,” especially considering that the company had posted a net loss of $514 million the previous year and had yet to produce a safe or effective medicine since its founding a decade earlier. In January 2020, Moderna had been worth a mere $5 billion, $2 billion less than its valuation at its December 2018 IPO. If it hadn’t been for the onset of the COVID crisis and a fresh injection of hype, it seems that Moderna’s valuation would have continued to shrink. Yet, thankfully for Moderna, investors were valuing Moderna’s COVID-19 vaccine even before the release of any clinical data. Market analysts at the time were forecasting Moderna’s 2022 revenue at about $1 billion, a figure based almost entirely on coronavirus vaccine sales, since all other Moderna products were years away from a market debut. Yet, even with this forecasted revenue, Moderna’s stock value in mid-May 2020 was trading at twenty-three times its projected sales, a phenomenon unique to Moderna among biotech stocks at the time. For comparison, the other highest multiples in biotech at the time were Vertex Pharmaceutical and Seattle Genetics, which were then trading at nine and twelve times their projected revenue, respectively. Now, with the implementation of booster shot policies around the world, revenue forecasts for Moderna now predict the company will make a staggering $35 billion in COVID-19 vaccine sales through next year.
Moderna’s surging stock price went into overdrive when, on May 18, 2020, the company published “positive” interim data for a phase 1 trial of its COVID-19 vaccine. The results generated great press, public enthusiasm, and a 20 percent boost in Moderna’s stock price. Just hours after the press release, Moderna announced a new effort to raise $1.3 billion by selling more stock. It has since been revealed that Moderna had hired Morgan Stanley to manage that stock sale on May 15.
However, left largely unmentioned by the press or Moderna itself was that the ostensibly “scientific study” only provided data from 8 of the 45 volunteers—4 volunteers each from the 15- and 100-microgram dose cohorts—regarding the development of neutralizing antibodies. The age of these mysteriously selected 8 volunteers was also not published, and other key data was missing, making it “impossible to know whether mRNA-1273 [Moderna’s COVID-19 vaccine] was ineffective [in the remaining 37 volunteers whose antibody data was not disclosed], or whether the results were not available at this point.” Meanwhile, in the highest-dose cohort, in which volunteers received 250 micrograms, 21 percent of volunteers experienced a grade 3 adverse event, which is defined by the FDA as “preventing daily activity and requiring medical intervention.”
STAT published a report the next day that was skeptical of Moderna’s press release and seemed to imply the data release was aimed at boosting the company’s stock valuation, which hit $29 billion after the news. STAT reporter Helen Branswell called this jump in valuation “an astonishing feat for a company that currently sells zero products.” Branswell’s report noted several things, including that several vaccine experts had noted that “based on the information made available [by Moderna], there’s really no way to know how impressive—or not—the vaccine may be.” Moderna later defended its withholding of key data in the press release, claiming that it was done to respect “federal securities laws and the rules of scientific journals” and to prevent a potential leak of the data from insiders at the NIH. Moderna executives have more recently claimed that the “timely” release of these selective data had been linked to their “desperate” fundraising efforts at the time and ultimately prevented them from “losing” the COVID-19 vaccine race.
The STAT report also noted that the National Institute of Allergy and Infectious Diseases (NIAID), which was running the trial referenced by Moderna in the press release, was completely silent on the matter, declining to put out a press release that day and declining to comment on Moderna’s announcement. This was described as uncharacteristic for NIAID, especially considering they were the part of the NIH co-developing the vaccine with Moderna and running the trial. STAT noted that, normally, “NIAID doesn’t hide its light under a bushel. The institute generally trumpets its findings.” In this case, however, they declined to do so. It emerged in early June 2020 that Dr. Anthony Fauci, who leads NIAID, had been displeased with Moderna’s decision to publish incomplete data on the trial, telling STAT that he would have preferred “to wait until we had the data from the entire Phase 1 . . . and publish it in a reputable journal and show all the data.”

Tal Zaks, Chief Scientific Officer at Moderna; Source: The Forward
It subsequently emerged that Moderna’s top executives, including chief financial officer Lorence Kim and chief scientific officer Tal Zaks, had used their insider knowledge of the coming press release to trade company stock that netted them several million each following the jump in Moderna’s stock that resulted from the press release’s positive buzz. A little over a week after the press release had been published, STAT reported that the top five Moderna executives had cashed out $89 million in shares since the company’s stock price had begun to soar earlier in the year. Per that report, the amount of trades by these five executives alone between January and May 2020 was “nearly three times as many stock transactions than in all of 2019.” By September 2020, the amount of stock shed by Moderna executives amounted to $236 million. Less criticized or even mentioned by the press was Moderna’s move, less than a month later, to create a tax haven in Europe for its European COVID-19 vaccine sales.
Though the trades were deemed slimy but legal, mainstream media reports essentially confirmed that the early release of the interim data was planned to “raise the share price of Moderna’s stock so that executives could cash in during the period of euphoria” that followed. Some watchdog groups called on the SEC to investigate Moderna executives for manipulating the stock market. The critical reporting on executive stock trades and Moderna’s release of incomplete data led the company’s stock to temporarily trend downward throughout the rest of May. As previously mentioned, Moderna has repeatedly attempted to explain away the timing of this particular press release, offering new explanations as recently as this week.
Moderna’s Shocking Claim about Its Vaccine Candidate
In mid-June 2020, researchers at the NIH and Moderna published a manuscript preprint of preclinical data for Moderna’s COVID-19 vaccine. This preprint described the vaccine as employing a delivery system covered in a patent owned by the company Arbutus Biopharma and described the results of that vaccine in tests on mice. As discussed in Part I, Moderna has long been locked in a bitter legal dispute with Arbutus, which has threatened Moderna’s ability to ever turn a profit on any product that relies on Arbutus-patented technology regarding lipid nanoparticle (LNP) delivery systems for its mRNA products. Moderna has claimed for years it was no longer using the Arbutus-derived system on which it once entirely relied, with Bancel even going so far as to publicly call it “not very good.” However, Moderna has provided no real evidence that it no longer relies on the technology covered in the Arbutus patents. The June 2020 manuscript preprint from the NIH and Moderna provided evidence indicating that the same Arbutus-derived technology that had caused major toxicity issues in multidose products Moderna had previously attempted to develop was also being used in Moderna’s COVID-19 vaccine candidate.
Yet, when Moderna’s chief corporate affairs officer, Ray Jordan, was challenged on this point by Forbes, Jordan asserted that the preprint’s data had been generated using a formulation of a COVID-19 vaccine that is not the same as the vaccine itself, stating, “While the authors of the preprint used the term ‘mRNA-1273’ for convenience of the reader, the preprint does not describe the cGMP process by which we make our messenger RNA and LNP or the final drug product composition in our commercial candidate (mRNA-1273).” When Forbes asked Jordan if he could provide any specifics, including the LNP molar ratio of the new LNP technology to prove that the LNPs in use in the COVID-19 vaccine were in fact different from those covered by the Arbutus patent, Jordan flat out refused.

Arbutus Biopharma’s office in Warminster, Pennsylvania; Source: Philadelphia Business Journal
Despite Jordan’s claims, a Moderna preclinical study regarding its COVID-19 vaccine was published a month later, and that July study noted that the Moderna vaccine used LNPs as described in a 2019 paper, which in turn reveals that the LNPs in question were the same as those used in the June study. This paper included the results from the study originally promoted by Moderna in May that led to a jump in Moderna’s stock price. Now published in full, the study generated lots of positive press, including a statement from the NIAID’s Fauci that “no matter how you slice this, this is good news.” A jump in US government funding of Moderna’s COVID-19 vaccine also shortly followed the study’s publication. At the time, CBS News remarked that Moderna’s stock price, which had been sliding since its late 2018 IPO, had been essentially rescued by the COVID-19 crisis, as “shares of Moderna—which has never brought a product to market over its ten-year existence—have soared as much as 380 percent since the start of the year as news emerged [in January] of its promising potential for producing a vaccine. [Moderna’s] stock price was less than $20 in early January and around $95 on Friday [July 17, 2020].” Today, by comparison, Moderna has consistently been trading above $300 a share.
Yet, if we take Ray Jordan at his word with respect to the preprint published in June, Moderna appears to have been engaged in rather slimy behavior. If Jordan was telling the truth, it appears that this July study, which appears to use the vaccine candidate containing the same LNPs as those described in the June 2020 preprint, also used a formulation not consistent with the company’s commercial vaccine candidate. If so, given that the July study was the same study referenced by Moderna’s controversial May press release tied to insider stock trades, Moderna appears to have used “positive” data generated by a vaccine candidate other than its commercial vaccine candidate to boost stock prices and ameliorate the company’s financial situation while also generating millions for executives. This, of course, says nothing about the separate but critically important issue that the vaccine candidate used in these studies, including the NIH study, is not necessarily the same as the commercial candidate used in clinical trials.
It seems that the only reason that Moderna would make such an outrageous claim to Forbes would be to distance its COVID-19 vaccine from its past controversies that largely have their root in Moderna’s LNP-related problems, which it had claimed to have already resolved. It is not clear if the motive behind such a gambit is principally related to the legal dispute with Arbutus or the past safety issues Moderna encountered with multidose therapies.
Adding to the confusion about the LNPs in use in Moderna’s products is that, a few days earlier in July, Moderna had published results on a separate vaccine candidate, this one for HIV, that appeared to use the exact same LNP technology that is covered by the Arbutus patent. The LNPs described in that study included the same components as those described in the Arbutus patent and the same molar ratio. Moderna appeared to be referencing this issue in their August 6, 2020, SEC filing, which states: “There are many issued and pending third-party patents that claim aspects of oligonucleotide delivery technologies that we may need for our mRNA therapeutic and vaccine candidates or marketed products, including mRNA-1273, if approved.”
By the end of 2020, Moderna claimed in a December filing with the SEC that, while it had “initially used LNP formulations that were based on known lipid systems,” that is, the Arbutus LNPs, it had “invested heavily in delivery science and ha[s] developed LNP technologies, as well as alternative nanoparticle approaches.” Despite the claims it made in this filing, however, it remained unclear as to whether the company’s COVID-19 vaccine was using Arbutus technology or the technology it purported to have developed on its own without infringing on Arbutus’s intellectual property.
Moderna’s claims that it now uses a different LNP system than the one that caused such major issues is based on the company’s development and implementation of a lipid structure now known as SM-102. This lipid structure was first revealed by Moderna in a 2019 publication under the name Lipid H, and, in that paper and since, Moderna has claimed that its LNP system is now superior to that which it previously used because it is using SM-102 instead of the original Arbutus lipids. However, it is critical to note that Moderna’s use of SM-102 does not necessarily mean the company is not violating the Arbutus patents, which cover the use of LNPs that combine cationic and PEGylated lipids in specific proportions.
Despite claims from Moderna that SM-102 resolved both the company’s patent-related and toxicity issues with its LNP system (as discussed in Part I), Moderna has declined to disclose SM-102’s exact structure or whether it carries a net positive charge at physiological pH, the latter of which could lead to proof of continued infringement on the Arbutus patent. In addition, there are no studies on the distribution, degradation, and/or elimination of SM-102 from the body, meaning that the accumulation of the lipids or their capacity to damage organs is not documented. The obvious lack of study of SM-102’s properties and effects on the human body was largely circumvented by public health authorities during the emergency approval process by using the same criteria for the Moderna vaccine candidate that is used for traditional vaccines that do not utilize the novel mRNA approach. These “traditional” criteria therefore do not include any requirements for data on LNP safety.
Overall, the evidence seems to point toward Moderna’s claims that its COVID-19 vaccine doesn’t use Arbutus-derived LNPs as being false. The other possibility is that Moderna attempted to modify the LNP system but only slightly so that potential identifiers, such as the molar ratio, remained the same. In this case, Arbutus could still claim that the LNPs currently in use by Moderna and in its COVID-19 vaccine infringe on their patent. It is also thus likely that the safety issues Moderna had acknowledged with this LNP system were largely unaffected if the potential modifications were indeed minor. Yet, if either of these scenarios is correct, the question becomes – Why wouldn’t Arbutus challenge Moderna once again to obtain royalty payments stemming from its COVID-19 vaccine?
The answer seems to lie mostly in optics and public relations. As STAT wrote last July, were Arbutus to sue Moderna over patent infringement in the midst of the COVID-19 crisis, “that would mean taking the substantial risk that it would be perceived as a company holding up a desperately needed medicine out of concern for its bottom line.” This also seemed to be part of the motive behind Moderna’s altruistically framed promise not to enforce its own COVID-19–related patents until the pandemic is declared over. Observers have noted that this move by Moderna was not only a public relations boon for the company but also “set a disarming tone in the space that may serve to deter others in the space [e. g., Arbutus] from acting too defensively or aggressively,” largely due to “fear of the potential public relations backlash.”
While July 2020 brought a surge in valuation and positive press for Moderna and its COVID-19 vaccine candidate, it also brought an unfavorable ruling for Moderna in its long-running dispute with Arbutus, one that opened the door for Arbutus to file an injunction against Moderna’s COVID-19 vaccine, if they chose, to force the negotiation of a license with Moderna. The news led to Moderna’s stock price falling by 10 percent, wiping out $3 billion in value. However, most likely for the reasons outlined above, Arbutus ultimately declined to jump on the decision to block Moderna’s COVID-19 vaccine from advancing in the hopes of securing royalties. Yet, they reserve the ability to do so, if and when the perceived urgency of the COVID-19 crisis fades.
Moderna has asserted that the decision would not affect its COVID-19 vaccine as the company was “not aware of any significant intellectual property impediments for any products we intend to commercialize.” Thus, Ray Jordan’s assertions and the lack of “clear and convincing” evidence that Moderna’s COVID-19 vaccine relies on Arbutus-patented technology appears to have been sufficient for Moderna to make this claim. This seems to be due to a lack of interest by the mainstream media or federal agencies/regulators in demanding concrete evidence that Moderna’s LNP system used in its COVID-19 vaccine does not rely on Arbutus-patented technology.
Despite the issues raised above in relation to the vaccine study data published in June and July, the positive press attention—particularly after the July publication—translated just a month later into the US government entering into a significant supply agreement with Moderna on August 11, 2020. Per that agreement, the government would pay $1.525 billion for 100 million doses with the option to purchase an additional 400 million doses in the future, all of which it has since purchased. Per Moderna’s press release, the agreement meant that the US government had, by that point, paid $2.48 billion for “early access” to Moderna’s COVID-19 vaccine.
Roughly a month later, it was revealed that the US government had been paying for much more. On September 10, 2020, BARDA joined long-time Moderna funder and “strategic ally” DARPA in scrutinizing contracts that had been awarded to the company due to Moderna’s failure to disclose the role government support had played in its numerous patent applications. The announcement came after Knowledge Ecology International (KEI), which advocates for protecting taxpayer investments in patents, found that none of the patents or applications assigned to Moderna in the company’s entire history had disclosed the considerable US government funding it had received at the time those patents were filed, which is required by the 1980 Bayh-Doyle Act and by the regulations of the Patent and Trademark Office. Per KEI, this translates into the US government owning certain rights over the patents, and thus US taxpayers may have an ownership stake in vaccines made and sold by Moderna.
Despite the clear evidence that Moderna failed to disclose the considerable amount of US government funding prior to and during the COVID crisis in its patent applications, Moderna responded to KEI and the BARDA/DARPA “scrutiny” by stating that it was “aware of and consults with our agency collaborators regarding our contractual obligations under each of these agreements, including those with respect to IP [intellectual property], and believe we comply with those obligations.” As of the writing of this article, BARDA and DARPA have taken no action against Moderna for their illegal omission about having received substantial government funding in their patent applications and filings. Instead, a month after DARPA claimed to be “scrutinizing” Moderna’s patent applications, it awarded the company up to $56 million to develop small-scale mobile means of manufacturing its products—namely, its COVID-19 vaccine and its personalized cancer vaccine.
Moderna: “Just Trust Us”
What quickly stands out about Moderna’s COVID-19 vaccine candidate over the course of its rapid development in 2020 was the willingness of federal agencies like NIH, BARDA, and others, as well as the mainstream press, to take Moderna at its word concerning critical aspects of its vaccine and its development, even when the evidence appeared to contradict its claims. This is particularly evident in Moderna claiming that it resolved its LNP issues, both in terms of toxicity and patent infringement, and those claims—despite the company’s refusal to release clear supporting evidence—being taken at face value. This is even more striking when one considers the multiple factors that Moderna was facing before COVID-19 and how the company faced collapse without the success of its COVID-19 vaccine, as this means Moderna was under considerable pressure to have its vaccine succeed.
While the controversial simultaneous conducting of animal and human trials was publicly justified in the name of the urgency of the COVID-19 crisis, can the other examples explored in this article be similarly justified in the name of urgency? Instead, several issues explored above appear to have been driven by conflicts of interest and corruption.
Adding to the ridiculousness is that Moderna got away with claiming that the NIH was conducting safety tests on a COVID-19 vaccine product different from their commercial candidate, without causing a major backlash in either the mainstream media or from the NIH itself. This is particularly telling as the May 2020 press release and suspiciously timed stock trading by Moderna executives and insiders did garner negative press attention. However, the subsequent revelation, per Moderna, that its press release was based on the study of a vaccine candidate that was not “necessarily the same” as their commercial COVID-19 vaccine candidate received essentially no coverage, despite raising the unsettling possibility that Moderna could have used another product to essentially rig preliminary data to be positive in order to advance their product to market and make millions through insider stock sales. How can the claims made by such a company be trusted at face value without independent verification? Furthermore, how can NIH studies of Moderna be trusted when Moderna has claimed that some of the studies that were ultimately factors in the vaccine’s emergency use authorization approval by the FDA utilized a different product than that which Moderna later successfully commercialized?
Moderna and the NIH were, nevertheless, taken at their word in November 2020 when they said that their COVID-19 vaccine candidate was 94.5 percent effective. At the time, the main promoters of this claim were Moderna’s Bancel and NIAID’s Fauci. The claim came shortly after Pfizer’s press release claiming its COVID-19 vaccine candidate was 90 percent effective. Not to be outdone by Moderna, Pfizer revised the reported efficacy of its vaccine just two days after Moderna’s November press release, stating that their vaccine was actually 95% effective to Moderna’s 94.5%. In the case of these claims, it was indicative of the now-established yet troubling practice of “science by press release” when it comes to touting the benefit of certain COVID-19 vaccines currently on the market. Since then, real-world data has shattered the efficacy claims that were used to secure emergency use authorization, for which Moderna applied at the end of November 2020 and received only a few weeks later in mid-December of that year.
As Part III of this series will explore, the EUA for the Moderna vaccine got around the issues raised in this article by treating the entire Moderna formulation as a traditional vaccine, which it is not, as traditional vaccines do not utilize mRNA for inducing immunity, and their safety and efficacy depend on several criteria that are entirely different from those of the more novel mRNA. Thus, the LNP issue, a perpetually sticky one for Moderna that it struggled to circumvent before the onset of the COVID-19 crisis, was largely evaded when it came down to, not just research and development, but receiving EUA. It appears that this sleight-of-hand by federal regulators was necessary for Moderna, after ten years, to finally get its first product on the market. As noted in Part I, were it not for the COVID-19 crisis and its fortuitous timing, Moderna might not have survived the severe challenges that threatened its entire existence as a company.
Part III will also examine how Moderna’s “Hail Mary” moment in the COVID-19 crisis was only the beginning of its miraculous rescue from a Theranos-like fate, as the company has not only expanded its partnership with the government but now with a CIA-linked firm. This shows that Moderna and key power players in Big Pharma and the US national-security state envision Moderna’s COVID-19 vaccine being sold in massive quantities for several years to come. As previously noted, without annual or semiannual sales of booster doses, Moderna’s pre-COVID crisis will inevitably return. The push for Moderna booster-dose approval has advanced despite real-world data not supporting Moderna’s past claims of safety and efficacy for its COVID-19 vaccine, the recent decision of several European governments to halt the vaccine’s use, and the FDA’s own infighting and recent admissions that the Moderna COVID-19 vaccine is one of the more dangerous currently in use, particularly in terms of adverse effects on the cardiovascular system. The obvious question here then becomes – How costly will Moderna’s “Hail Mary” save ultimately be, not just in terms of the $6 billion US taxpayer money already spent on it, but also in terms of public health?
Family of Capitol rioter who died by ‘overdose’ demands autopsy review
RT | November 24, 2021
The family of a woman whose death during the pro-Trump riot on Capitol Hill was ruled a drug overdose is crowdfunding an autopsy review, after Washington, DC police refused to release body camera footage of her final moments.
Rosanne Boyland was 34 when she traveled in January from her home in Georgia to Washington, DC to protest the certification of Joe Biden’s electoral victory. After crowds of Trump supporters took their rowdy protest to the US Capitol, Boyland would later be found dead among them, with her death ruled an amphetamine overdose by the DC medical examiner’s office several months later.
Her family aren’t buying the story, and have launched a crowdfunding campaign to finance a review of her autopsy.
“There are still many questions about exactly what happened to her,” the family wrote on GiveSendGo this month. “Videos show her being beaten by a female officer after being crushed by protesters pushed by police. Yet the DC Medical Examiner said Rosanne’s body showed no signs of trauma, and attributed her death to the prescription medication she took every day for years.”
In an update to the campaign posted on Tuesday, they added that Boyland was not abusing amphetamines. Rather she was taking adderall, a prescription drug containing four kinds of amphetamine used to treat ADHD and narcolepsy. “The only drugs in Rosanne’s body were her prescription medications,” they wrote.
Thousands of hours of video footage – from both surveillance cameras and police body cameras – captured during the Capitol protest remain unreleased, with authorities citing the importance of this footage to ongoing criminal investigations. Boyland’s family filed a Freedom of Information Act (FOIA) request with the DC Metropolitan Police to obtain body camera footage from officers who handled her unconscious body, but their request was denied.
Some of this footage allegedly shows Boyland being carried into a space beneath the House majority leader’s office, where lawyers for other defendants claim that their clients were assaulted by Capitol Police officers. Conservative journalist Julie Kelly reported on the story last week, after seeing legal documents alleging a series of brutal beatings taking place in the tunnels under the Capitol.
Three other protesters died in the Capitol on January 6. Air Force veteran Ashli Babbitt was shot dead by a Capitol Police officer. Two other Trump supporters in their 50s – Benjamin Philips and Kevin Greeson – died of medical emergencies.
Capitol Police officer Brian Sicknick, whose death was initially blamed on the pro-Trump mob, passed away of a stroke the day after the riot.
Lethal Injection; Frontline E.R. Doctor Gives Chilling Account of Unusual Vaccine-Induced Illness
BY MIKE WHITNEY • UNZ REVIEW • NOVEMBER 20, 2021
“Americans are scared to death… People are walking off the job, not because they want to lose their jobs, but they don’t want to die from the vaccine! … They say, ‘Listen, I don’t want to die. That’s the reason I’m not taking the vaccine.’ It’s that clear.” Dr. Peter McCullough
A report in the U.K. Telegraph explains how the Covid-19 vaccine has led to a sharp rise in excess deaths. Here’s an excerpt from the article:
“Nearly 10,000 more people than usual have died in the past four months from non-Covid reasons, as experts called for an urgent government inquiry into whether the deaths were preventable…
Latest figures from the Office for National Statistics showed that England and Wales registered 20,823 more deaths than the five-year average in the past 18 weeks. Only 11,531 deaths involved Covid.” (“Alarm grows as mortuaries fill with thousands of extra non-Covid deaths,” UK Telegraph )
Mortality is rising because more people are dying. And more people are dying because more people have been vaccinated. There’s a link between rising mortality and the Covid-19 vaccine. Naturally, the media wants to shift responsibility for the fatalities to “delayed treatments” and “the lack of preventable care”. But this is just a diversion. The primary cause of death is the injection of a toxic pathogen into the bloodstreams of roughly 70% of the population. That’s what’s causing the clotting, the bleeding, the pulmonary embolisms, the heart attacks, the strokes, and the premature deaths. It’s the vaccine. Here’s more
“Weekly figures for the week ending November 5 showed that there were 1,659 more deaths than would normally be expected at this time of year. Of those, 700 were not caused by Covid.
The excess is likely to grow as more deaths are registered in the coming weeks.
Data from the UK Health Security Agency show there have been thousands more deaths than the five-year average in heart failure, heart disease, circulatory conditions and diabetes since the summer.
The number of deaths in private homes is also 40.9 per cent above the five-year average, with 964 excess deaths recorded in the most recent week, which runs up to November 5.” (“Alarm grows as mortuaries fill with thousands of extra non-Covid deaths“, UK Telegraph )
The sudden surge in mortality is not a meaningless blip on the radar. It’s a red flag indicating a significant break in the five-year trend. Something has gone terribly wrong. Mass vaccination was supposed to reduce the number of cases, hospitalizations and deaths. Instead, the fatalities continue to rise.
Why?
The answer to that question can be found in the data itself. As the author admits, there has been a sharp uptick in heart failure, heart disease, circulatory conditions and strokes. (Diabetes is the outlier) These are precisely the ailments one would expect to see if one had just injected millions of people with a clot-generating biologic that triggers a violent immune response that attacks the inner lining of the blood vessels inflicting severe damage to the body’s critical infrastructure. So, yes, all-cause mortality is up, and it is certain to climb even higher as more people are vaccinated and gradually succumb to the (frequently) delayed effects of a hybrid concoction that is the cornerstone of a malign plan to dramatically reduce global population. Check out this chart followed by a brief comment by diagnostic pathologist, Dr Claire Craig:
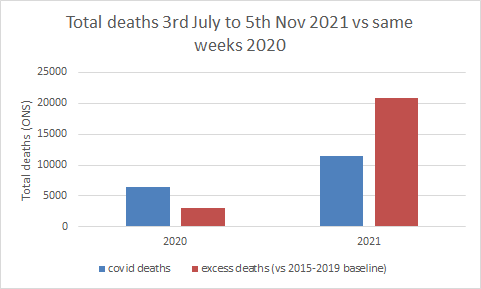
Dr Clare Craig @ClareCraigPath
“Since summer there have been twice as many covid deaths, but seven times as many excess deaths as last year.” (Twitter)
And here’s another blurb from Craig:
“If you start at week 22 and add up all the deaths since for each year, then something very abnormal is happening this year among 15-19 yr old males.”
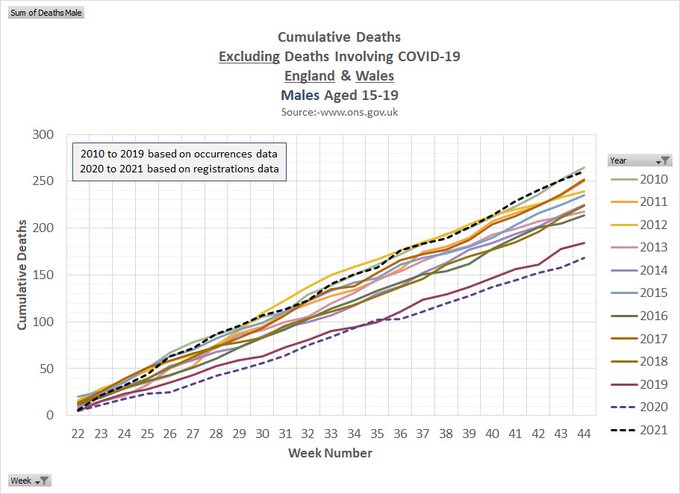
So, not only are more people dying, but the demographic has shifted downwards as younger and younger people are drawn into the vaccine vortex. Simply put, the number of young people dying from vaccine-inflicted cardiac arrest and myocarditis continues to increase with no end in sight.
Not surprisingly, all-cause mortality is higher among the vaccinated than the unvaccinated which, again, makes it easier to trace the problem back to its root, a cytotoxic “poison-death shot” that suppresses the innate immune system, damages vital organs and shaves years off the lives of normal, healthy people.
Perhaps, you’ve seen one of the many short videos of fit, young athletes who suddenly have dropped dead on the field of play or been rushed to hospital shortly after getting injected. If not, here’s a link to two of them. (Athletes collapse following vaccination: See here and here)
According to Israeli Real-Time News, there has been a “500% increase in deaths of players in 2021… Since December, 183 professional athletes and coaches have suddenly collapsed! 108 of them died!”
“500% increase in the deaths” of athletes?!? What are we to make of this?
For starters; the Covid-19 vaccine is not a medication. It is the essential component in the elitist plan for industrial-scale extermination. It is designed to inflict severe physical injury on the people who take it. It’s shocking that people are so deep in denial that they can’t see what’s going on right before their eyes. (Please, watch the video clips of the athletes. These are the fittest people on the planet and, yet, they are being struck down by the mystery substance in the vaccine.) Here’s how South African doctor Shankara Chetty summed it up in a recent video posted on Bitchute:
“The pathogen that is causing all the deaths from the illness is the spike protein. And the spike protein is what the vaccine is supposed to make in your body. … Spike protein is one of the most contrived poisons that man has ever made. And, the aim of this toxin, is to kill billions of people without anyone noticing it. So it is a poison with an agenda.” (“South African Physician Dr. Shankara Chetty Talks about “The Bigger Plan”, Bitchute)
There it is in a nutshell. And Chetty is not alone in linking the vaccine to the agenda of the globalist elites who plan to use the cover of a pandemic to implement their “population management” scheme. Former Pfizer vice president, Mike Yeadon, offered a similar view just days ago on his website. He said:
“We are in the midst of the biggest depopulation program the world has ever seen, where most of humanity are acting as useful idiots to it and to their own demise.”
Indeed, and we have tried to provide as much information as possible on the biologic agent that is being used to pursue this malign agenda, the spike protein. In early reports we passed along the research of Dr. Patrick Whelan who grasped the danger of the spike protein before anyone else. Here’s a brief recap of his analysis from a letter he submitted to the FDA on December 8, 2020:
“I am concerned about the possibility that the new vaccines aimed at creating immunity against the SARS-CoV-2 spike protein have the potential to cause microvascular injury to the brain, heart, liver, and kidneys in a way that does not currently appear to be assessed in safety trials of these potential drugs.
… Meinhardt et al…. show that the spike protein in brain endothelial cells is associated with formation of microthrombi (clots)… In other words, viral proteins appear to cause tissue damage without actively replicating virus…. The Pfizer/BioNTech vaccine (BNT162b2) is composed of an mRNA that produces a membrane-anchored full-length spike protein. The mouse studies suggest that an untruncated form of the S1 protein like this may cause a microvasculopathy in tissues that express much ACE2 receptor.
… it appears that the viral spike protein… is also one of the key agents causing the damage to distant organs that may include the brain, heart, lung, and kidney. Before any of these vaccines are approved for widespread use in humans, it is important to assess in vaccinated subjects the effects of vaccination on the heart…. As important as it is to quickly arrest the spread of the virus by immunizing the population, it would be vastly worse if hundreds of millions of people were to suffer long-lasting or even permanent damage to their brain or heart microvasculature as a result of failing to appreciate in the short-term an unintended effect of full-length spike protein-based vaccines on these other organs. (“FDA shrugs off dire warning about lethal spike protein“, Truth in the Age of Covid)
From the very beginning, government regulators and their allies in the public health establishment have ignored (or censored) the warnings of capable physicians and researchers. They also waved-off career immunologist and vaccinologist, Dr Byram Bridle who was the first in his profession to identify the spike protein as “a specific causative agent of disease”; aka–“a pathogen”. Here’s Bridle:
“‘We have known for a long time that the spike protein is pathogenic… It is a toxin. It can cause damage in our body if it’s in circulation. Now, we have clear-cut evidence that . . . the vaccine itself, plus the protein, gets into blood circulation.’”
Once that happens, the spike protein can combine with receptors on blood platelets and with cells that line our blood vessels. This is why, paradoxically, it can cause both blood clotting and bleeding. ‘And of course the heart is involved, as part of the cardiovascular system… That’s why we’re seeing heart problems. The protein can also cross the blood-brain barrier and cause neurological damage…
‘In short,… we made a big mistake. We didn’t realize it until now. We didn’t realize that by vaccinating people we are inadvertently inoculating them with a toxin.”… (“Vaccine scientist: ‘We’ve made a big mistake’“, TCW Defending Freedom )
Here again, we have a highly-regarded immunologist, with more than 3 decades of experience under his belt, who offered his informed and evidence-based research on an issue that should have been of great interest to the regulators that were making decisions about the long-term safety of the experimental drug they were foisting on millions of people across the country. But there was no interest at all. Despite the fact that the science supported his conclusions, Bridle was viciously attacked, censored, dragged through the mud, and forced to leave his place of employment.
Why?
Because he drew the same conclusions as Dr. Patrick Whelan. There’s really no substantive difference between the two except that Bridle’s comments attracted more attention in the media which made him a greater threat to the “universal vaccination” strategy. That was his real crime; he discovered the truth and made his findings available to the public, basically alerting them to the dangers of the “poison-death shot”. For that he was crushed.
Bridle has since made other claims that should concern anyone whose cancer might be in remission. Here’s what he said in a recent interview:
“What I’ve seen way too much of is people who had cancers that were in remission, or that were being well controlled; their cancers have gone completely out of control after getting this vaccine. And we know the vaccine causes a drop in T-cell numbers, and those T-cells are part of our immune system and they are part of the critical weapons our immune system has to fight off cancer cells; so there’s a potential mechanism there. All I can say, is I’ve had way too many people contact me with these reports for me to feel comfortable. I would say that is my newest major safety concern, and it’s also the one that’s going to be the most under-reported in the adverse data base, because if someone has had cancer before the vaccine, there’s no way public health officials will ever link it to the vaccine.” (“Dr Byram Bridle speaks”, Bitchute, :55 second-mark)
So, the vaccine suppresses the immune system?
Yes, it does, and author Alex Berenson provided evidence of this just recently in an article he posted on Substack. Here’s an excerpt:
“… the British government… admitted today, in its newest vaccine surveillance report, that:
“N antibody levels appear to be lower in people who acquire infection following two doses of vaccination.” (Page 23)
What’s this mean?…
What the British are saying is they are now finding the vaccine interferes with your body’s innate ability after infection to produce antibodies against not just the spike protein but other pieces of the virus…
This means vaccinated people will be far more vulnerable to mutations in the spike protein EVEN AFTER THEY HAVE BEEN INFECTED AND RECOVERED ONCE…
… it probably is still more evidence the vaccines may interfere with the development of robust long-term immunity post-infection.” (“URGENT: Covid vaccines will keep you from acquiring full immunity EVEN IF YOU ARE INFECTED AND RECOVER”, Alex Berenson, Substack)
Berenson’s observations square with research that was compiled earlier in the year by scientists in The Netherlands and Germany who:
“… warned that the … (COVID-19) vaccine induces complex reprogramming of innate immune responses that should be considered in the development and use of mRNA-based vaccines… the research team from Radboud University Medical Center and Erasmus MC in the Netherlands… showed that the vaccine altered the production of inflammatory cytokines by innate immune cells following stimulation with both specific (SARS-CoV-2) and non-specific stimuli.
Following vaccination, innate immune cells had a reduced response to toll-like receptor 4 (TLR4), TLR7 and TLR8 – all ligands that play an important role in the immune response to viral infection…. an unexplored area is whether BNT162b2 vaccination has long-term effects on innate immune responses …
This could be very relevant in COVID-19, in which dysregulated inflammation plays an important role in the pathogenesis and severity of the disease,” writes the team. “Multiple studies have shown that long-term innate immune responses can be either increased (trained immunity) or down-regulated (innate immune tolerance) after certain vaccines or infections.” (Research suggests Pfizer-BioNTech COVID-19 vaccine reprograms innate immune responses, new-medical-net)
Berenson’s finding also align with with cutting-edge research showing that the spike protein greatly “impedes adaptive immunity” by preventing DNA from repairing damaged cells. The paper suggests that the spike protein does in fact “impact on the nucleus of the cell, where we store our DNA, our core genetic material.” Here’s more from Berenson’s breakdown of the paper:
“… our cells have mechanisms to repair their own DNA.
But – at least in the experiments these two scientists ran – the spike protein appeared to interfere with our own DNA repair proteins: “Mechanistically, we found that the spike protein localizes in the nucleus and inhibits DNA damage repair by impeding key DNA repair protein BRCA1 and 53BP1 recruitment to the damage site.”
To be clear, the scientists did NOT prove the spike protein was causing these problems in people, or even animals… Nonetheless, at a time when advanced countries that have high mRNA (and DNA/AAV) vaccination rates are seeing unusually full hospitals and higher-than-normal death rates, they are yet more cause for concern. As the authors explained:
“Our findings reveal a potential molecular mechanism by which the spike protein might impede adaptive immunity and underscore the potential side effects of full-length spike-based vaccines.” (“URGENT: Worrisome paper about the spike protein’s impact on DNA and DNA repair”, Alex Berenson, Substack)
Bottom line: If the vaccine does in fact inhibit the body’s innate immune response, then people are going to get alot sicker from seasonal infections that routinely spread through the population. Their path to recovery will also be alot more difficult.
But rather than belabor the immunity angle, let’s move on to the research of Dr Charles Hoffe who was the first physician to provide hard evidence that the vaccines generate blood clots by triggering an immune response in which the body attacks the thin layer of cells lining the walls of the blood vessels. Hoffe found that 62% of his patients that had been vaccinated tested positive for blood clots on a D-dimer test. Naturally, he was alarmed by what he found, particularly since the vaccine “was causing serious neurological events, and even death. When he raised his concerns with the BC College of Physicians, they immediately implemented a gag order, and reprimanded him in an attempt to intimidate, and silence him.”
Hoffe has been interviewed a number of times and always provides a detailed and riveting account of his findings. In a recent interview, he predicted that some vaccinees suffering from clot-related issues would likely die in just three years. Here’s what he said:
“… once you block off a significant number of blood vessels to your lungs, your heart must pump at a much greater resistance to get the blood through your lungs. That causes a condition called pulmonary artery hypertension, which is high blood pressure in your lungs because so many of the blood vessels in your lungs are blocked. And the terrifying thing about this is that people with pulmonary artery hypertension usually die of right-sided heart failure in three years… And not only is the long-term outlook very grim, but with each successive shot, the damage will add and add and add. It’s going to be cumulative because you are getting more and more damaged capillaries.” (“Shock: Doctor Warns That Majority Of Vaccinated Patients Could HavePermanent Heart Damage, Some May Die Within Three Years”Permanent Heart Damage, Some May Die Within Three Years”, Infowars; Minute 6:10)
Once again, there is no discrepancy between the analysis of Whelan, Bridle and Hoffe. And while the focus of their attention might vary slightly, their conclusions are the same. These experimental injections pose serious risks for anyone who allows himself to be inoculated.
Now check out how similar Hoffe’s analysis is to Dr. Rochagne Kilian who was an Emergency Room physician at the GBHS hospital until she resigned in protest. This is a particularly important video as it describes the “oddball” symptoms and exceedingly rare conditions that are now presenting in emergency rooms everywhere following the mass vaccination of millions of people with the “poison-death shot”. (I transcribed the video myself, so there could be errors.)
Dr Rochagné Kilian – Blows the Whistle on Covid-19 Vaccines and D-Dimer Levels
“What I was seeing in my ER department especially in the last 8 to 9 months is related to the D-Dimer levels. We use D-Dimers specifically related to pulmonary embolisms as well as Deep Vein Thrombosis. D-Dimer detects any thrombosis (clots) in the body but it doesn’t give you a diagnosis it gives you a basis for going further and doing an ultrasound and CT scan to either confirm or deny the presence of a pulmonary embolism or Deep Vein Thrombosis.
The first part of 2020 was probably the slowest ever in the emergency department, but when we went into 2021 and the vaccination rollout started, we ended up seeing an increase in stroke, transient ischemic attacks and stroke like presentations. (There were) definitely significant larger numbers of those people coming in. I ended up doing D-dimer tests on these people and never before in my clinical experience had I seen D-dimers and the amount of people with positive D-dimers higher than 2,000, higher than 3,000 and higher than 5,000. My clinical experience told me a needed to go look for a large clot either in their legs or their lungs. And I ended up doing a CT scan on these people. Most of them, and I will say almost all of them, had negative scans which started making me think that if there was not a significant clot in their lungs, but my D-dimer was so much higher than what I was usually seeing, it might not be concentrated in one clot. But that it is multiple micro-thrombi extended throughout the body, and that is so easy to miss because the CT scan is not going to pick it up.
“These people coming into the ER were all people anywhere from about a week to four months after receiving their 2nd injections. There are certain factors that can influence a D-dimer test that can give you a sense of a higher level than would be expected in the body. That said, the patients I was doing D-Dimer tests on did not have a level of maybe a positive 500 or 400 reading. It was more than 3500, more than 5000 ng/ml. So those are significantly positive without any proof of having a pulmonary embolism. If I was seeing high levels of D-dimer without a definite diagnosis, I needed to ask more questions.
One study said, never ignore extremely elevated D-dimer levels. They are specific for serious illness, including venous thrombosis, sepsis, and/or cancer. Even if sharply elevated D-dimer are a seemingly solitary finding, clinical suspicion of severe underlying disease should be maintained.
There were two conditions that stood out and the first one was disseminated intravascular coagulation also known as DIC. The second one is antiphosphlipid syndrome. Both of these conditions are related to an abnormality in either the initiation or the feedback of the coagulation pathway as well as thrombosis or the thrombosis cycle where clots are being broken down. DIC is a serious sometimes life threatening situation in which the proteins in the blood involved in blood clotting become overactive. It’s a cascade that’s difficult to stop once it’s reached a certain level. There are certain conditions that trigger DIC; significant sepsis, underlying viruses, trauma, major surgery, pregnancy and childbirth. And less common causes toxic drug reaction, blood transfusion reaction, and organ transplants. So there was a connection with intravascular products and a possible DIC.
Most cases of DIC are diagnosed rapidly and suddenly which is the acute presentation. But there are cases where it develops gradually, occurring over a longer period of time. This is known as a chronic form of DIC and I would go as far to say a subacute form of DIC that is very easy to miss. Simultaneous clotting and bleeding can occur with chronic DIC. The bleeding part comes in blood in the urine, headaches and other symptoms associated with brain bleeds, bruising, inflammation of red, small dots on the limbs, bleeding at sites of wounds and mucosal bleeding. which means bleeding out of the gums and nose. I definitely saw an increase in nose bleeds and bleeding from previous wound sites. ulcers, as well as rashes that couldn’t be explained. Blood clotting symptoms and signs were symptoms like chest pains, heart attacks, strokes, TIAs, and headaches either related to bleeding or not. As well as symptoms related to kidney failure, because of the clotting of those smaller blood vessels that go to the kidneys. Antiphosphlipid syndrome is a very similar type of condition. But the basis of the antiphosphlipid syndrome is an autoimmune disorder meaning that the body’s immune system makes proteins–known as antibodies–that mistakenly attacks its own body or tissues. That gives the skin the cascading effect of clotting disorder but it is linked to an autoimmune trigger. Basically, it presented in exactly the same way; high blood pressure which I was seeing alot of; first diagnosis of high blood pressure, heart attacks, strokes, TIAs, heart valve problems, repeated headaches or migraines, vision loss, balance and mobility problems, difficulty concentrating or thinking clearly,
The astute listener would start forming a picture of what we’ve been told about Covid-19, and there are research papers connecting Covid 19 with an underlying vascular disease. One of these was a study called “Covid 19; unraveling the clinical progression of Nature’s Virtually perfect Biological weapon.”
“SARS-Cov-2, presenting as Covid-19 syndrome, was not a respiratory basis, but an underlying vascular basis. which had certain phases of incubation, pulmonary phase, pro inflammatory phase, (which once again comes into a cytotoxic inflammation process) then moves into a protothrombic phase . Covid-19 is a thrombotic disease. implications for prevention, antithrombotic therapy and follow up…
This picture shows us certain risk factors, Homeostatic Abnormalities, as well as clinical outcomes. It indicates increased D-dimer levels. It also mentions Venous Thromboembolism, Myocardial Infarction, and Disseminated Intravascular Coagulation that is connected to postulated mechanisms of coagulathopy as well as parthenogenesis of thrombosis in Covid-19…
I started asking the question, if we are able to detect certain connections between vascular abnormalities and Covid-19, and we based our proposed treatment on the spike protein, which includes the Pfizer and Moderna injections, shouldn’t we be looking for similar side effects or complications from that same injection?
If we are mandating certain treatments, we do need to do the due diligence to make sure what the side effects and complications especially in a time where there has not been long term studies.”And that’s what led me to focusing on D-dimers.” (“Dr Rochagné Kilian – Blows the Whistle on Covid-19 Vaccines and D-Dimer Levels“, Bitchute)
Kilian’s statement should be read over and over again. It is the most detailed description we have of the mysterious and deeply sinister machinations of a laboratory-engineered bioweapon that, in effect, turns the vascular and immune systems against the person who was vaccinated. Disseminated intravascular coagulation and antiphosphlipid syndrome are names that are entirely unknown to the American people, and yet, these freakish conditions are now responsible for a growing number of patients that are experiencing bleeding, clotting, headaches, rashes, bruising, high blood pressure, and inflammation . And– in more extreme cases– chest pains, heart attacks, strokes, heart-valve problems, and brain bleeds. One can only guess how the media will try to cover-up these extraordinarily-rare and potentially life-threatening conditions??
When Kilian asks:
“If we are able to detect certain connections between vascular abnormalities and Covid-19… shouldn’t we be looking for similar side effects or complications from that same injection?”
Bingo! If the spike protein produced by the vaccines, inflicts the same internal damage as Covid-19, then shouldn’t doctors expect to see the same symptoms?
Yes, they should. And if the symptoms are the same, then there’s a good chance that vaccine-induced injuries are being misdiagnosed as Covid-19.
Think about that for a minute. That would be the perfect scenario for the pandemic managers and their billionaire backers who’d love to see the impending mountain of carnage blamed on the waning virus instead of on their own poison-death shot.
And that is the evil-genius of the globalist strategy; to remove the fingerprints from the smoking gun before the investigators even arrive at the scene of the crime.
The amount of planning that must have gone into this scam, is simply breathtaking.

This perverse ban on ivermectin, cheap and proven to work
By Kathy Gyngell | TCW Defending Freedom | November 23, 2021
GIVEN the feared winter resurgence of Covid infection despite, or because of, the government’s mass vaccination programme, the continued ban on ivermectin in this country becomes ever more perverse.
It beggars belief that the British public is still denied access to this proven prophylactic and treatment. If the public health authorities are genuinely worried about pressure on hospitals, why have not the Medicines and Health products Regulatory Agency (MHRA), Public Health England, the NHS and Department of Health all gone flat out over this last year to approve ivermectin with the same zeal they gave emergency authorisation to the limited trialled, novel gene therapy, Covid vaccines?
The answer is widespread misinformation from the top down. Put ‘ivermectin’ into the Google search box and what do you come up with? Topping the list is a warning from the US Food and Drug Administration (FDA) why it should NOT be used to treat or prevent Covid-19. Their reason? It’s as simple as the fact that they have not approved it and, because they have not approved, it cannot be used. Trials are ongoing they say. Maybe some are. But plenty have been completed, as Dr Pierre Kory’s paper (he was the lead author) ‘Review of the Emerging Evidence Demonstrating the Efficacy of Ivermectin in the Prophylaxis and Treatment of Covid-19’, published by the American Journal of Therapeutics earlier this year, made quite clear.
By contrast with this detailed review of the evidence the FDA’s substantive concern appears to rest on random reports of harms deriving from self-medication with ivermectin.
The BBC not to be behindhand entered the fray with its customary selective and biased take on ‘the science’. Its recent report entitled ‘How false science created a Covid ‘miracle’ drug‘ made not even the most minimal of checks on the veracity of their assertions, which are pulled apart here. A letter sent to a programme journalist in response to their request for information (in advance of transmission) by Dr Tess Lawrie, the Director of the British Ivermectin Recommendation Development Group (BIRD), an advocacy group of clinicians and scientists from around the world, setting out the science behind the case for authorising it, was completely ignored. Her letter can be found here.
How the BBC came not to ask how it was that remdesivir – a standard medication for Covid in the UK – was approved on the basis of one study when ivermectin, with 63 studies, of them 31 Randomised Controlled Trials (RCT), 7 meta-analyses, 32 Observational Controlled Trials (OCT), multiple country case studies, expert opinion, patient testimony ALL pointing in favour of the medication, was not, is inexplicable.
This is the news source the public is still told to trust.
A blog posted on BIRD last week asked whether there are indeed any genuine gripes about the quality of the evidence, as the FDA and others suggest?
No, there are not. The author argues it is down to a misinformation campaign based on misleading information produced by high profile public health agencies, like the World Health Organisation, itself a victim of disinformation tactics, that has been ‘perpetrated by a minority of corporations to manipulate and delay government action on matters that would adversely affect their income and profit’. Speculation of course. But every indication points that way.
As reported extensively in TCW Defending Freedom, for example here, the WHO is subject to the huge financial influence of the Bill and Melinda Gates Foundation, the organisation’s second biggest donor. Since one of the BMGF’s long-term interest is in delivering vaccines, why would they show any interest in promoting the use of cheap, old repurposed medications in the treatment and prevention of Covid-19? It’s for the very same reason that ivermectin has proved of so little interest to Big Pharma -it’s hardly the money spinner that indemnified world-wide vaccination is.
Worse perhaps than what these big interests have not done is what they have actively done to discredit ivermectin. The BIRD blog relays an analysis by Dr Kory setting out what the WHO ‘did’ with the ivermectin evidence. He says it:
· Failed to publish a pre-established protocol for data exclusion
· Excluded two ‘quasi-randomised’ controlled trials (RCTs) with lower mortality
· Excluded two RCTs that compared ivermectin to or gave it together with other medications, all reporting lower mortality
· Excluded seven other available ivermectin RCT results
· Excluded all RCTs and observational controlled trials (OCTs) investigating ivermectin in the prevention of Covid-19
· Excluded 13 OCTs, more than 5,500 patients, that showed reductions in mortality
· Excluded numerous published and pre-print epidemiologic studies.
The bottom line, however, remains – if ivermectin is good enough and provenly effective for the more than 20 lower-income countries which do distribute it and also benefit from lower Covid rates, why are the populations of wealthier nations and individuals still being denied?
It’s a point that clearly has bothered the chairman of the Tokyo Medical Association, Dr Haruo Ozaki, who would recommend ivermectin for Covid patients, noting that the parts of Africa that use ivermectin to control parasites have a Covid death rate of just 2.2 per 100,000 population, compared with 13 times that death rate among African countries that do not use ivermectin.
‘I would like,’ said Dr Ozaki, ‘the government to consider treatment at the level of the family doctor’ with the informed consent of the patient. So would we.
Featured Video

Broke Princes: Saudi Arabia’s Powder Keg
or go to
Aletho News Archives – Video-Images
From the Archives
Registered Israeli foreign agent driving contrived campus antisemitism crisis
By Wyatt Reed | The Grayzone | December 17, 2023
Lawsuits accusing top US universities of harboring antisemitism all originate from one source: a corporate law firm that fielded the pro-settler ex-US ambassador to Israel, and which was registered as a foreign agent of an Israeli principal as recently as 2021.
The firm now represents professional Israel lobby activists posing as victimized “Jewish students” and seeking to crush the free speech rights of Palestine solidarity activists. … continue
Blog Roll
 Aletho News
- Did Israel lose the midterms?
- How Iran defeated Trump’s Israel First GOP
- De-escalating the conflict: What the OSCE, the UN, and Europe are (not) doing to prevent war
- Desperate For A Renewed Iran War, Israel Dusts Off The WMD Deception.
- US Elections Offer Choice Between ‘Bad and Worse’ as Both Parties Serve War Lobby – ex-UN Expert
- Ghalibaf warns US government not to betray voters who rejected war
- Broke Princes: Saudi Arabia’s Powder Keg
- Albania’s Crisis: Rama, Israeli Investments and the Demand for Accountability
- Hezbollah Categorically Denies Syrian Accusations: We Aim at Confronting Israeli Enemy, Not Undermining Syria’s Stability
- Trump claims funding to Israel ending in 2026 as merger of Israeli–US armies looms
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago

