Oblivion: the best cure?
The effects of lockdown, now becoming clearer by the day, should never be forgotten.
By Tom Jefferson | Trust the Evidence | November 29, 2022
My grandfather was a decorated WWI veteran. He was lucky and got back home minus a hand. My dad participated in the Battle of Britain, North African and Italian campaigns. He got home apparently unscathed. However, both had one thing in common: they would not speak of what they had done and seen. What they had been through was too terrible to describe, and people were not interested; it was all in the past. That is one of the reasons why we have wars: few people have any idea what it’s like.
It’s going that way with the most traumatic experience in this lifetime: lockdowns.
Looking at the media, you would think nothing extraordinary has happened since 2020.
Well, let me remind you.
Our civil liberties were severely curtailed, drones were sent after lone runners on deserted moorland, children could see but not touch toys in stores (if they were let in at all), our elders died abandoned in nursing homes or their own homes, governments spurted gibberish on the advice of modellers and overnight experts. The media ran a wall-to-wall campaign to get the populace to toe the line. Crooks were allowed to run away with billions of public money while massive amounts were spent on useless tests. That is why the Chancellor has a large hole in his books. While patients likely to be infected were moved around hospitals, in some casualties, separation consisted of taped bin bags stretched across walls, GPs were not accessible, and the police were checking people’s movements and compliance with government policies. Children were confined to home; people stopped exercising and took to drinking. People with serious illnesses did not get treated, partly because they were rightly scared of catching the plague when in hospital. Few people questioned what was going on.
Data, real data on which momentous decisions were made, were absent. We do not know how many real infectious cases or deaths attributable to SARS-CoV-2 there were. Even deceased who tested negative were wrapped up in the Covid death tally. So we cannot separate the impact of the agent from the self-inflicted devastation.
The current economic crisis has its genesis in the demented and wasteful response to an unknown unquantified threat, then came the war in Ukraine, but the lockdown came first. Remember how many businesses stopped paying taxes because they had gone bust or could not trade?
Parliament had little say in what went on while large swathes of politicians were trying to outdo each other in demanding more restrictions and closures.
Scientific evidence, when available, was used as a political weapon regardless of its quality and credibility.
So now that I have refreshed your memory and now we know that no one will ever be held responsible for the greatest catastrophe in our generation, I ask you, when will the next round be? There is ample precedent, so it’s only a matter of time.
The government is now bending over backwards it seems to address four problems: cancer, obesity, addiction and mental health, throwing more money at four problems which its policy magnified and worsened. I will save you the effort of searching. In the glossy press release, I failed to find any mention of restrictions, isolation or lockdown.
Perhaps my grandfather and father should have spoken about the war and reminded those who wanted to forget that oblivion is the road to perdition. For our democracy, our society and our families.
Twitter quietly changes Covid-19 policy
RT | November 29, 2022
Twitter has said it will no longer enforce its coronavirus misinformation policy, according to an update on the platform’s Covid-19 transparency page that went largely unnoticed since it was posted last week. The move came as its new owner Elon Musk announced a “general amnesty” for previously suspended accounts.
The misinformation policy was initially developed in 2020 amid the outbreak of Covid-19 and was meant to combat “harmful” misleading posts about the coronavirus, government policies aimed at curbing its spread, and related vaccines.
Users who violated the rule received strikes. After two or three strikes, their accounts were suspended for 12 hours. After four, they would be locked out for a week, while offenders with more than five strikes were permanently banned from the platform.
According to statistics published by Twitter itself, between January 2020 and September 2022, the platform’s moderators challenged over 11.72 million accounts and suspended more than 11,000 for violating the rule. They also scrubbed nearly 100,000 pieces of content worldwide under the policy.
The extensive moderation policy became a topic of heated debate. Some called for more censorship of posts deemed to be harmful, while others argued this constituted suppression of free speech.
Since Musk acquired Twitter for $44 billion last month, he has made a number of dramatic changes at the company, including laying off nearly two-thirds of its staff and significantly cutting the site’s moderation and management teams.
Ahead of Thanksgiving, the billionaire also vowed to extend a “general amnesty” to an unspecified number of suspended accounts after holding a Twitter poll, in which more than 72.4% out of 3.1 million respondents supported the move.
Critics have argued that the social networking service could soon become a hotbed for misinformation, right-wing extremism and hate speech. Musk, however, has insisted that he wants Twitter to become a level playing field and a bastion of free speech where people can peacefully exchange their views on a wide range of topics.
Pfizer CEO, who said online “misinformation” is criminal, is found guilty of “misleading” vaccine statements

By Cindy Harper | Reclaim The Net | November 27, 2022
Pfizer CEO Albert Bourla, last year at the Atlantic Council, called people who spread COVID-19 vaccine misinformation “criminals,” in his calls for censorship of misinformation online.
However, this year, Dr. Bourla is himself found responsible by the UK’s pharmaceutical regulator of making “misleading” statements about vaccination of children.
Last December, in an interview with the BBC, Dr. Bourla said that “there is no doubt in my mind that the benefits, completely, are in favor of” vaccinating children between the ages of five and 11.
He continued to say that “Covid in schools is thriving.”
“This is disturbing, significantly, the educational system and there are kids that will have severe symptoms.”
The interview was conducted before the vaccine was approved for children between the ages of five and 11 in the UK.
After the interview was published, parent campaign group UsForThem filed a complaint with the Prescription Medicines Code of Practice Authority (PMCPA). The complaint accused Dr. Bourla of making “disgracefully misleading” comments about vaccinating children and that the comments were “extremely promotional in nature,” and that he violated several clauses of the code of practice by the Association of the British Pharmaceutical Industry (ABPI).
“There is simply no evidence that healthy schoolchildren in the UK are at significant risk from the SARS COV-2 virus and to imply that they are is disgracefully misleading,” the complaint said.
PMCPA convened a code of practice panel that found that Dr. Bourla had indeed violated the code of practice in a few ways, including failure to present information to the public in a factual and balanced manner, misleading the public, and making claims that cannot be substantiated.
The Telegraph reported Pfizer appealed against the findings of the panel and strongly disagreed with UsForThem’s claims that the CEO violated the code of practice. The company argued that Dr. Bourla’s remarks were based on “up-to-date scientific evidence” and they could be proven through “publicly available independent benefit-risk assessments.”
An appeal board upheld that Dr. Bourla misled the public, made claims that were unbalanced, and made unsubstantiated claims.
However, it ruled against claims that Pfizer discredited the industry, encouraged reckless use of a treatment, and did not maintain high standards.
As an Oncologist I Am Seeing People With Stable Cancer Rapidly Progress After Being Forced to Have a Booster
BY DR ANGUS DALGLEISH | THE DAILY SCEPTIC | NOVEMBER 26, 2022
There follows a letter from Dr. Angus Dalgleish, Professor of Oncology at St George’s University of London, to Dr. Kamran Abbasi, the Editor in Chief of the BMJ. It was written in support of a colleague’s plea to Dr. Abbasi that the BMJ make valid informed consent for Covid vaccination a priority topic.
Dear Kamran Abbasi,
Covid no longer needs a vaccine programme given the average age of death of Covid in the U.K. is 82 and from all other causes is 81 and falling.
The link with clots, myocarditis, heart attacks and strokes is now well accepted, as is the link with myelitis and neuropathy. (We predicted these side effects in our June 2020 QRBD article Sorensen et al. 2020, as the blast analysis revealed 79% homologies to human epitopes, especially PF4 and myelin.)
However, there is now another reason to halt all vaccine programmes. As a practising oncologist I am seeing people with stable disease rapidly progress after being forced to have a booster, usually so they can travel.
Even within my own personal contacts I am seeing B cell-based disease after the boosters. They describe being distinctly unwell a few days to weeks after the booster – one developing leukaemia, two work colleagues Non-Hodgkin’s lymphoma, and an old friend who has felt like he has had Long Covid since receiving his booster and who, after getting severe bone pain, has been diagnosed as having multiple metastases from a rare B cell disorder.
I am experienced enough to know that these are not the coincidental anecdotes that many suggest, especially as the same pattern is being seen in Germany, Australia and the USA.
The reports of innate immune suppression after mRNA for several weeks would fit, as all these patients to date have melanoma or B cell based cancers, which are very susceptible to immune control – and that is before the reports of suppressor gene suppression by mRNA in laboratory experiments.
This must be aired and debated immediately.
Angus Dalgleish MD FRACP FRCP FRCPath FMedSci
Angus Dalgleish is a Professor of Oncology at St George’s, University of London.
The Doctor Who Can Rebuild Trust: Joseph Ladapo
By Jeffrey A. Tucker | Brownstone Institute | November 22, 2022
If you are like me, you are exhausted of the lies. Every day seems to bring new revelations about how our lives came to be upended. The connections are becoming clearer between the pandemic response and the growing economic crisis, the ballooning debt, the growth of the surveillance state, the corruption and scams, chilling absence of integrity in public life, and, with the failure of FTX, the way in which an outright financial scam was integral to the calamity.
While we await new revelations, depositions, coverups, pleas for amnesty, and bad economic news, whom can we trust? Is anyone telling the truth?
Today was Anthony Fauci’s last White House press conference, and he spoke as if life is all normal and everything is fine. It’s as if the whole disaster never happened. He never locked anyone down, he says. He is happy for any investigations, he says, because he has nothing to hide. And then he ended with a final push for everyone to get booster #5 or whatever number we are on.
It’s like we live in two universes: our own lives in which we read true things in some places, and official life, in which shills and publicists keep repeating the same nonsense over and over without flinching or providing anything like an honest account of these last three years.
Perhaps for this reason – and also because by any historical standard this is a tremendous autobiography – reading Dr. Joseph Ladapo’s Transcend Fear is a welcome relief from the nonsense of our times. It is brutally honest. It is emotionally affecting. It is careful and precise but also deeply radical in its observations. If what’s called the “public health world” has lost touch with both the public and health, this book provides a path to restoring it. In short, it is a beautiful and inspiring experience.
Dr. Ladapo is the Surgeon General of the State of Florida, picked by Governor Ron DeSantis to forge and explain the state’s health decisions and priorities to the public in the midst of a grave crisis. He has faced down the national press time and time again with Zen-like wisdom. He seems emotionally unflappable while also sticking to the science as he understands it. He is the only public health official in the country who has been upfront about the limits of the vaccines and warned healthy young people that they don’t need them.
What we learn from this book is that he has been a warrior against pseudoscience from the very beginning of this pandemic and the government response. After the lockdowns, most scientists and health professionals fell silent, fearing reputational and financial loss. Dr. Ladapo was different, On March 24, 2020, still within the window of “15 Days to Flatten the Curve,” he wrote in USA Today:
We are fretting and we are fuming. As a country, we have been caught miserably flat-footed after receiving warnings about what lay ahead when cases of Covid-19 began exploding in Wuhan, China. Messages from local and state leaders about how to respond to the pandemic change almost daily—a sure sign they have no idea what they are doing. Shutdowns are happening here in California and in New York, and will probably spread to the rest of the nation….
Here’s the problem: Because of the (understandable) fear and hysteria of the moment, few US leaders are seriously talking about the endgame. The epidemiologic models I’ve seen indicate that the shutdowns and school closures will temporarily slow the virus’ spread, but when they’re lifted, we will essentially emerge right back where we started. And, by the way, no matter what, our hospitals will still be overwhelmed. There has already been too much community spread to prevent this inevitability.
We don’t have a totalitarian government like China, and we value our civil liberties too much to take the measures (i.e., total lockdown) that would be needed to rapidly decrease the infection rate to zero. This means that, even with shutdowns, the virus will still spread. Unfortunately, this also means that rates of “community immunity,” often referred to as “herd immunity,” will slow. As a result, we will always be vulnerable to the virus spreading rapidly again as soon as shutdown measures are lifted, unless they are immediately reimplemented—over and over and over again.
Was he the first post-lockdown voice from public health profoundly to object in a public forum of this magnitude? Perhaps so. Consider the bravery and presence of mind it required to write those sentences. The entire country was on a wartime footing with unprecedented horribles taking place. The media was screaming “Run for your lives” but most of us weren’t even allowed out of our homes to do that.
These were utterly crazy times. The whole world was going bonkers. And yet this man kept his cool.
This book explains where his cool comes from. You see, he is the son of an immigrant from Nigeria, born 1979. A math and science whiz, he attended Wake Forest and then entered Harvard Medical School. While he was involved in his studies, he noted the existence of the Kennedy School of Government and enrolled there too. On graduation day, he was granted a MD plus a PhD in public policy. So essentially: the highest credentials in two fields that this country offers. He became professor of medicine at New York University and then the University of California, Los Angeles.
The trouble was that none of his training had prepared him to deal with medical issues closer to home, namely his wife’s unrelenting migraines that often landed her in the hospital and his own underlying psychological fears of social interaction. The details are very painful and told in this book with disarming detail. Long story short: his search for answers led him toward alternative medical paths that eventually fixed both issues, and burned a lesson in his mind. Health is individual, and the right path is not the same for everyone and not always found in expertise as codified in the textbooks and institutions.
It was soon after these difficult times that the pandemic broke and, along with it, the claims that the experts had all the answers in lockdowns and eventual universal mandates for vaccination.
Dr. Ladapo had meanwhile developed the self-confidence to speak about such matters truthfully and fearlessly. And he never stopped. He wrote for every venue he could, month after month, urging an end to the lockdowns, a focus on therapeutics, attention to the science we had, and genuine concern for the health of actual individuals, who are not lab rats but people with human rights and freedom.
Even though Dr. Joseph Ladapo is obviously a hero (and one for the ages, so far as I’m concerned), the prose here is remarkably lucid, humble, and precise. That’s why I say that the humane concern in this book is an inspiration. Moreover, reading it is a form of therapy because he connects with a common sense that we all had in 2019 before the world descended into utter madness.
What’s more, this book shows a path forward not only for public health but for all of us as individuals. He urges personal reflection as the first step in recovery, overcoming whatever hidden fears we had that caused too many among us to go along with the preposterous parade of dangerous nonsense that controlled our lives for so long.
In my own view, this book is a classic of our times. Its value added is not only the author’s credentials, though he has them galore, or even how it speaks so directly to issues that have profoundly affected all our lives. Its real value is as a model of autobiography that offers lessons for all of us without exception.
I write as Dr. Fauci just finished his last press conference without offering so much as a hint of apology for what has happened. Meanwhile, I’m sure Dr. Ladapo is tending to his work in Florida where he has been charged with dealing with public health policy with honesty, truth, and wisdom. I know who gets my vote for hero of the pandemic.
Jeffrey A. Tucker, Founder and President of the Brownstone Institute, is an economist and author. He has written 10 books, including Liberty or Lockdown, and thousands of articles in the scholarly and popular press.
Courage to Face COVID-19: Book Trailer
https://rumble.com/embed/v1uk8xs/?pub=4
Written by John Leake and produced by Daniel Hancock | November 25, 2022
At the beginning of 2020, Dr. Peter McCullough was a highly regarded practicing physician, program director, teacher, and clinical investigator at a major academic medical center in Dallas, TX. When COVID-19 arrived in March, he felt a duty to find a treatment for the disease. He wasn’t alone. Other doctors all over the world were also searching for a cure. They followed the longstanding principle that it’s best to tackle a sickness early, before it becomes life threatening. This is the story of how Dr. McCullough and his colleagues developed an early treatment protocol of generic, repurposed drugs and supplements that has saved millions of COVID-19 patients from hospitalization and death.
In spite of their success, their early treatment protocol was not welcomed by public health officials. On the contrary, the news of their promising results was dismissed as soon as it was reported. At first this seemed like conventional skepticism, but then fraudulent papers maligning the protocol’s repurposed drugs were published in academic medical journals. This and other acts of fraud revealed that a coordinated smear campaign against early treatment was being waged. Dr. McCullough and his colleagues soon found themselves censured, censored, vilified in the media, and fired from their jobs. The greatest victims of the smear campaign were COVID-19 patients who were consequently deprived of early treatment. Hundreds of thousands needlessly died of the disease.
At the same time early treatment was suppressed, the US government and mainstream media proclaimed that the cure to COVID-19 lay in a new generation of vaccines that were being developed at warp speed. These were heralded as a forthcoming panacea that would save mankind and restore normalcy. As soon as they were mass deployed, public health officials would lift the restrictions on social and economic life.
While many observers were thunderstruck by this turn of events, there were historical precedents. In his 1961 Farewell Address, President Eisenhower warned, “We must guard against the acquisition of unwarranted influence, whether sought or unsought, by the military-industrial complex. The potential for the disastrous rise of misplaced power exists and will persist. We must never let the weight of this combination endanger our liberties or democratic processes”. As Dr. McCullough and his colleagues learned, Eisenhower’s warning has become equally applicable to the Bio-Pharmaceutical Complex of multinational drug companies, the NIH and other federal agencies, research and virology labs, and the Gates Foundation. Since COVID-19 arrived, this Complex has obtained misplaced power over every aspect of our lives and taken our liberties. The Courage to Face Covid-19 recounts how Dr. McCullough and his colleagues began their work by fighting a novel infectious disease, and then became leaders in fighting the tyrannical regime that endangers our American way of life.
One for the Enquiry: Test and Trace to bankruptcy
How the Test and Trace policy based on shaky science has helped bankrupt the UK
By Tom Jefferson and Carl Heneghan | Trust the Evidence | November 24, 2022
We plan to write up a series of short notes on topics that, in our view, should be addressed by the Covid enquiry. So, we are calling these One, Two, Three etc., for the enquiry. But, as always, we rely on our readers to suggest other topics.
Here’s the first one.
In public health, identifying symptomatic subjects and their subsequent isolation is proposed and used for infectious diseases to slow outbreaks and, in some instances, stop them.
The conceptual nub of the issue is that in the vast majority of cases, an infectious disease is contagious for a short time. During that period, the source of infection (known as the index case) may infect other people (contacts). Therefore, if you stop contact from the index case and/or their secondary cases (family, acquaintances, colleagues), you will interrupt or disrupt the chain of transmission of the agent.
Cases are only of interest if they are contagious, i.e. producing so-called replication-competent viruses that can be passed on from A to B and so on, which need to be identified and traced, then isolated to prevent onward transmission.
In the explosive phase of an acute respiratory viral epidemic, testing, tracing, and isolation are incredibly labour-intensive as cases multiply exponentially to then level out and fall as the contagion curve obeys Farr’s law.
In Lombardy, by the second week in March, public health had given up testing and tracing as the numbers of supposed cases rapidly overwhelmed public health resources. Tracing, you see, needs to be done based on history taking. It is time-consuming, and the window of contagiousness is sometimes very short, lasting as little as two days.
No problem, enter PCR as a tool for diagnosis. If applied in large numbers in what amounts to mass testing of whole populations, it can quickly tell you who is “positive”. No need to use those old rusty tools of clinical investigation and history-taking, considered old fuddy-duddy stuff in this age.
So in a very short time, PCR capacity went from niche testing in a few laboratories to people waving swabs at motorists in drive-ins – the way out of the pandemic and the return to normal was imminent, we were told.

Except, as discussed in the third instalment of our transmission riddles, qualitative PCR (positive/negative) on its own without recourse to clinical history and an estimate of viral burden cannot distinguish between contagious, convalescent and spurious cases, i.e. due to environmental contamination. If you then set arbitrary cut-offs for positivity, as has been done in most UK laboratories, you increase the number of “cases” by an unknown factor.
The consequence, apart from the cost of setting up a programme not founded on science and clinical medicine, is the lengthy isolation of those who never came into contact with SARS-CoV-2 or those who are convalescing, regardless of whether they knew they had been infected. Convalescents can still test positive for PCR as the technique is so sensitive that in the presence of an arbitrary cut-off, the test is picking up viral debris, which is of little interest.
So, we have an expensive programme with no clear, evidence-based objectives. The initial budget was £15 billion; by November 2020, this rose to £22bn; by the time the service was halted in February 2022, it cost £37bn. At its height, over 700 UK testing sites were open seven days a week, including Xmas and New Year’s day.
In the digital era – phone technologies were considered the answer – the dreaded ‘pings’ went unanswered, that’s if you downloaded or switched it on in the first place. But yet again, interventions were untried and untested; however, this didn’t stop them from being rolled out at speed.
But at any point, did anyone ask if there is evidence for such an approach that had never been tried before on such a scale worked or, once rolled out, evaluated its effectiveness?
Although contact tracing has a clear logic, its effects depend on the characteristics of the organism, how it is transmitted, the duration of the asymptomatic phase before symptoms manifest, the time the agent is transmissible, the size of the outbreak and the behaviour of the population.
By the time it shut down in February 2022, 16 million cases had been detected in England, whereas the ONS infection survey estimated 67.6 million had tested positive for covid-19. Therefore, only about one in four “cases” were detected, and of those testing positive, there was no indication of whether they were infectious at the time.
Given the scale of the outbreak and the nature of the SARs-COV-2 agent, it was clear early on that Test and Trace would be an expensive waste of resources. But at the outset, those in power extolled its virtues.

One of the arguments is that Test and Trace was rolled out too late. Early on, Germany was praised for its Test and Trace strategy. Some advisors incorrectly extolled their strategy; however, Germany equally struggled and ended up gripped by panic. As a result, it was late in coming out of covid measures in 2022.
The Test and Trace program ignored the basic rules of infectious disease epidemiology leading to massive disruption of society. Models are insufficient evidence to support £37bn of expenditures – lacking evidence, no other area of healthcare would tolerate such waste.

But you don’t need to take our word for it: in October 2021, The House of Commons Committee of Public Accounts, in its Test and Trace update, similarly considered the program a waste of resources.
- ‘In March this year, we reported NHS Test and Trace Service’s (NHST&T) failure to deliver on its central promise of averting another lockdown.‘
- ‘In addition, most of the testing and contact tracing capacity that NHST&T paid for has not been used, and despite previous commitments to reduce dependency on consultants, it employed more in April 2021 than in December 2020.’
- ‘NHST&T’s overall goal is to help break the chains of COVID-19 transmission and enable people to return to a more normal way of life, but there have been two national lockdowns since October 2020 and at the time of our evidence session cases were increasing again.’
Despite all the resources thrown at it, Test and Trace did not show one measurable difference in the outcomes of the pandemic – it did not avoid further lockdowns as promised. Instead, the £37 Billion could have paid for roughly a million nurses for the year, or a year and a half of social care cost for everyone that needed it. In October 2020, the PM announced £3.7 billion for 40 hospitals in the biggest hospital-building programme in a generation – He could have nearly rebuilt the whole NHS estate with £37bn. We’ll leave you to consider what you may have better spent the money on.
The budget for Test and Trace now seems unthinkable in the face of a deep recession where every penny counts. Effective healthcare is built on solid evidence of what works, not on opinions of what we think might work. The fact it made no measurable difference is now clear.
The Questions for the enquiry are
- What was the Test and Trace program’s aim?
- What evidence was the Test and Trace built on?
- How was the quality of the evidence assessed?
- What were the metrics for effectiveness? These should not be process measures such as number tested as these do not measure the spread of the agent.
- Why wasn’t the Test and Trace program terminated after the damming PAC report?
- How can the government prevent such a massive waste of resources on ineffective interventions in the future?
Who is Dr. Asish Jha (President Biden’s Covid Czar)?
Top public health empty suit is a pandemic planner and propagandist

Dr. Ashish Jha
By John Leake · Courageous Discourse · November 25, 2022
At at press briefing on November 22, White House COVID-19 Response Coordinator, Dr. Ashish Jha, reiterated that God gave us two arms in order to receive multiple vaccines and boosters. I write “reiterated” because he made the same stupid remark at a press briefing back in September.
I wasn’t surprised when the Biden Administration appointed Dr. Jha to serve as its Covid Czar. As we recount in our book, Dr. Jha was the minority witness at Senator Ron Johnson’s November 19, 2020 hearing on Early Outpatient Treatment. This hearing began with testimony from Drs. Peter McCullough, Harvey Risch, and George Fareed on the safety and efficacy of repurposed, FDA-approved drugs for treating COVID-19—especially in the disease’s early stage—to prevent hospitalization and death.
Following their testimony, Dr. Jha testified that their observations and findings were erroneous. In fact, he claimed, there were no effective early treatments for COVID-19, and that our best and only hope was the vaccine that was then in development.
An especially dramatic and somewhat comical moment in the hearing occurred when Dr. George Fareed said, “I wonder if Dr. Jha actually treats patients by the way he talks.” Senator Johnson took this remark as a cue for querying Dr. Jha.
“Have you treated any Covid patients,” Senator Johnson asked.
“I have not, sir,” Dr. Jha replied. We recount this scene in the following excerpt from The Courage to Face COVID-19: Preventing Hospitalization and Death While Battling the Bio-Pharmaceutical Complex:
Dr. Jha had splendid academic credentials to match his splendid manners, but at this moment he lost a lot of credibility. It was perhaps the equivalent of an aeronautical engineer admitting that he’d never flown in a plane, or a marital counselor admitting he’d never been married.
He implied that Professor Risch—a distinguished epidemiologist twenty years his senior—was categorically wrong in his interpretation of the data. Then he implied that Dr. Fareed’s observations as a treating physician were an illusion—that the high-risk patients who received the Zelenko Protocol would have recovered in the same dramatic way without the intervention.
This was probably the most notable moment in the hearing. Since graduating from medical school in 1970, Dr. Fareed had logged fifty years as a medical researcher and treating physician. It would be hard to find a doctor in the entire country with more clinical experience. He testified to the U.S. Senate that he’d successfully treated 1,000 high-risk COVID-19 patients. A few minutes later, a doctor 25 years his junior—one who’d never treated a single COVID-19 patient—asserted that “there is now clear consensus in the medical and scientific community” that a key ingredient of Dr. Fareed’s treatment protocol doesn’t work. In effect, Dr. Jha told Dr. Fareed to reject the evidence of his own eyes and ears.
Shortly after the hearing, Dr. Jha published an opinion piece for the November 24, 2020, edition of the New York Times titled “The Snake-Oil Salesman of the Senate.” He opened with likening the event to a contagion.
There was a super-spreader event last week in the United States Senate. It wasn’t the coronavirus, however, that was spreading, but misinformation. … The Senate Homeland Security and Governmental Affairs Committee held a hearing about early treatment for COVID-19. Yet instead of a robust discussion about promising emerging therapies or what Congress might do to accelerate such treatments, the conversation was all about the malaria drug hydroxychloroquine. … Neither Ron Johnson, the Wisconsin Republican senator nor his chosen witnesses—three doctors who have pushed hydroxychloroquine—displayed more than a passing interest in evidence. Intuition and personal experiences of individual doctors were acclaimed as guiding principles.[i]
Dr. Jha didn’t mention that he himself had focused his Senate remarks on hydroxychloroquine and hadn’t mentioned any “promising emerging therapies” apart from vaccines. He also didn’t state the names or credentials of the hearing’s witnesses or a summary of their findings or experiences. He compared them to the snake oil salesmen from the frontier past with their advocacy of the drug that President Trump had touted in the spring, implying they were equally lacking in medical sophistication.
“I was called reckless because I pointed to facts that could prevent people from getting the treatment,” he wrote, but he didn’t state these facts. The online version of his essay hyperlinked the word “reckless” to a similar hatchet job report on the hearing in the Washington Post. He claimed the witnesses had expressed a distrust of science and had even “suggested that scientists were part of a ‘deep state’ conspiracy to deny Americans access to lifesaving therapies.” This was, he asserted, “a powerful reminder that not even Congress is immune to toxic conspiracy theories…”
Dr. Jha’s New York Times opinion was, itself, evidence that early treatment of COVID-19 was the subject of a well-orchestrated smear campaign. Why else would such a distinguished academic pen such rank propaganda against his colleagues and their work? That he was personally stung by the revelation that he’d never treated a single COVID-19 patient could only partly account for it.
A possible answer to this question may be gleaned from Dr. Jha’s remarks at a January 10, 2017, Georgetown University conference titled “Pandemic Preparedness in the Next Administration.”
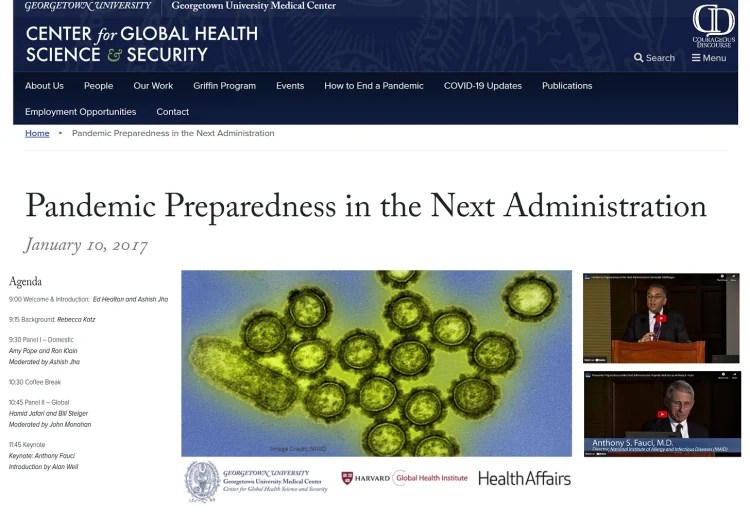
Like the participants at the October 2019 Pandemic Simulation Exercise at Johns Hopkins, Dr. Jha predicted that a devastating pandemic “is going to come at some point.” Dr. Fauci, the keynote speaker, made a more precise prediction.
“There is no question that there will be a challenge to the coming administration in the arena of infectious diseases,” he proclaimed. “The thing we’re extraordinarily confident about is that we’re going to see this in the next few years.”[ii]
As psychiatrist and author Peter Breggin, MD, remarked in his extraordinary book COVID-19 and the Global Predators: We Are the Prey, Dr Jha did not speak in a somber tone about the coming devastation. On the contrary, he emphasized that he was excited about the ambitious project of helping the U.S. and other governments, and equally excited about the many pandemic preparation events in Georgetown and Cambridge that lay ahead. The conference was, he said, the “beginning of a journey.”[iii]
Dr. Jha and his colleagues were animated with the same excitement that denizens of the military-industrial complex would feel at the prospect of a coming war in which they would assume leadership positions. At last, they would be able to deploy all of their forces. With the recognition that the coming war was inevitable, they could call upon the government to allocate far more resources for new technologies, weapons systems, bases, and military organizations. In an atmosphere of such heady excitement, the suggestion of defusing the coming war with diplomacy wouldn’t be received with much enthusiasm.
The irony of Dr. Jha’s excitement is that, when the pandemic he predicted arrived three years later, he didn’t attempt to treat patients or scramble to find consultants to intervene against the disease before it wrecked bodies and imprisoned people in hospitals. Instead, he penned propaganda against hydroxychloroquine and against Drs. McCullough, Risch, and Fareed. Why was the New York Times Editorial Board compelled to publish his misleading account of the Senate hearing? Did the editors even watch the C-SPAN recording of it?
It’s not plausible that their motive was a concern about hydroxychloroquine’s safety. Dr. Jha himself conceded in his testimony that he wasn’t particularly concerned about safety, so why the vast and ceaseless quibbling about whether its efficacy for outpatients had been proven? As Senator Johnson had said in the hearing, this makes no sense.
[i] Jha, Ashish, MD. The Snake Oil Salesmen of the Senate. New York Times, Nov. 24, 2020. https://www.nytimes.com/2020/11/24/opinion/hydroxychloroquine-covid.html
[ii] Georgetown University Center for Global Health Science & Security, Pandemic Preparedness in the Next Administration. January 10, 2017. https://ghss.georgetown.edu/pandemicprep2017/
[iii] Breggin, Peter R, MD and Ginger Ross Breggin, COVID-19 AND THE GLOBAL PREDATORS: WE ARE THE PREY. Ithaca: Lake Edge Press, 2021, p. 259.
Time to come clean about Covid’s lab origins
By Neville Hodgkinson | TCW Defending Freedom | November 24, 2022
More than two years ago, an Anglo-Norwegian team of scientists demonstrated unique ‘fingerprints’ of laboratory manipulation in the Covid virus. They argued that the evidence as good as proved that the virus had originated in a lab rather than evolving naturally. The manipulation, which made a bat virus a danger to humans, was exactly as envisaged by American and Chinese researchers who had been working on a vaccine aimed at reducing the impact of any such future outbreaks.
A paper describing these findings, co-authored by London University vaccines expert Professor Angus Dalgleish, was suppressed in both the US and UK. Internationally, the World Health Organisation, leading science journals and others made a huge effort to persuade us that Covid was a natural occurrence – and that we should spend a lot more money to fight any such future threats.
However the paper was uploaded by the Norwegian website Minerva in July 2020, and an update appeared on the website in May 2021 which I reported here.
Now an American expert in the field, who previously dismissed the lab-origin theory, has reached exactly the same conclusion. ‘The body of evidence supporting a lab origin of SARS-CoV-2 is overwhelming, far more so than most realise,’ says biologist and analyst Dr Alex Washburne in a newly published ten-page report.
He studied transmission of infections from bats to people for many years before Covid. ‘Pathogen spillover is common,’ he writes, ‘and so for much of the pandemic I kept an open mind about a laboratory origin yet remained firmly entrenched in my prior belief of a zoonotic [animal] origin. However . . . the totality of evidence has completely changed my mind.’
Before Covid, Dr Washburne was working with a team funded by a US Defense Department grant aimed at pre-empting pandemics by studying whether some strains of animal viruses were more likely to cause human disease than others.
He says it takes a lot of effort to find and examine naturally occurring viruses, and so ‘there is a clear temptation to make new viruses, such as chimeric viruses or viruses passaged in human cells. If we made a virus more capable of infecting people, it might reveal the essence of human-infective viruses and help us prepare vaccines before a pandemic ever happens.
‘Engineer and evolve a novel pandemic-capable virus to create a vaccine against the virus before it causes a pandemic, and you might win a Nobel Prize . . . provided nothing goes wrong.’
He describes how in March 2018 a proposal to do just that was drawn up by EcoHealth Alliance (a global non-profit with the slogan ‘Standing Between You and the Next Pandemic’) with the Wuhan Institute of Virology in China and other international collaborators.
The plan was to sample bat coronaviruses, assemble cloned copies of the viruses in the lab, introduce genes that might make them a threat to humans, and test the resulting chimeric viruses in the lab at Wuhan.
‘Find, engineer, and evolve human-infectious viruses capable of causing a pandemic, develop a vaccine against them, and pre-empt a pandemic . . . provided nothing goes wrong.’
DARPA, the US Defense Advanced Research Projects Agency, turned down the proposal on safety grounds.
But the group had alternative sources of funding, including a biodefence grant from the US National Institute of Allergy and Infectious Diseases. The fact that SARS-CoV-2 emerged in Wuhan, with an exact fingerprint of the proposed manipulation, and a geographic pattern inconsistent with its having emerged from animal trade, ‘ought to tilt the scales towards a laboratory origin’, Washburne says.
He adds that ‘as a scientist, I can’t tell you how badly I want scientists to have not opened Pandora’s Box. It took enormous amounts of self-examination and self-criticism to question my own cherished belief in the theory of a zoonotic origin’.
He might have been able to change his mind sooner if the findings of the Anglo-Norwegian team had been examined at the pandemic’s outset.
The team’s findings were exactly in line with those now highlighted by Washburne. They found that the virus’s so-called spike protein had six inserts, ‘unique fingerprints . . . indicative of purposive manipulation’, which allowed it to infect and damage a wide range of human cells. They showed how these and other features of the virus were linked to laboratory work published by the Chinese and American researchers.
The authors wrote: ‘Since, regrettably, international access has not been allowed to the relevant laboratories or materials, since Chinese scientists who wished to share their knowledge have not been able to do so and indeed since it appears that preserved virus material and related information have been destroyed, we are compelled to apply deduction to the published scientific literature, informed by our own biochemical analyses.
‘We refute pre-emptively objection that this methodology does not result in absolute proof by observing that to make such a statement is to misunderstand scientific logic. The longer the chain of causation of individual findings that is shown, especially converging from different disciplines, the greater the confidence in the whole.’
The team also warned that vaccine-makers who failed to acknowledge the chimeric nature of the virus, and the toxicity of the spike protein, might unwittingly put the public at risk.
We now know that wittingly or not the vaccine-makers put out products which present an even bigger threat to health for some than the virus itself, and have been linked to tens of thousands of deaths and millions of adverse events. But because of the obstacles put in the way of a genuine understanding of the virus’s nature, regulators continue to assure the public that the products are ‘safe and effective’.
I believe there was high-level knowledge from the very start that this was not a naturally evolved virus, but a chimera – originally native to Chinese bats but manipulated in the laboratory to see if it could become a threat to humans.
If Covid really was a straightforward zoonosis – an infectious disease of animal origin – why was a global panic button pressed, leading to the ruinous lockdowns and other crisis measures which were to cost the UK £500billion over the next two and a half years?
Why did top scientists and public health officials persist in demanding panic measures long after it was clear that the threat from Covid was not as bad as had been feared?
Why did the G20 countries at their recent meeting in Bali sing the praises of Covid immunisation as a ‘global public good’, and flag up digital and non-digital ‘proof of vaccinations’ to facilitate ‘seamless international travel’?
Is it because of fears that another, more dangerous genetically engineered pathogen is in the pipeline?
Chinese scientists and public health officials are said to have predicted that World War Three will be fought with ‘a new era of genetic weapons’ which can be ‘artificially manipulated into an emerging human disease virus, then weaponised and unleashed in a way never seen before’.
This is clearly a subject with which governments and their intelligence agencies worldwide must be familiar. May I suggest that if that is the real fear, they should come clean about it, and stop treating us like idiots? That would do a lot to improve understanding, and help end a damaging crisis of confidence in science that could prove a lot more damaging than SARS-CoV-2 itself.
Four Myths about Pandemic Preparedness

By David Bell | Brownstone Institute | November 24, 2022
We are assured by the World Health Organization (WHO), the World Bank, the G20, and their friends that pandemics pose an existential threat to our survival and well-being. Pandemics are becoming more common, and if we don’t move urgently we will have ourselves to blame for more mass death of the ‘next pandemic.’
The proof of this is the catastrophic harm done to the world by COVID-19, a repeat of which can only be prevented by transferring unprecedented funds and decision-making power to the care of public health institutions and their corporate partners. They have the resources, experience, knowledge and technical know-how to keep us safe.
This is a no-brainer, all of it, and only a fool who desires mass death would oppose it. But there are still people who claim that the link between the public health establishment and large corporations appears to be the only part of this narrative that withstands scrutiny.
If true, this would imply that we are being systematically deceived by our leaders, the health establishment, and most of our media; a ludicrous allegation in a free and democratic society. Only a fascist or otherwise totalitarian regime could run such a broad and inclusive deception, and only people with truly bad intent could nurture it.
So let’s hope such ‘appearances’ are deceptive. To believe that the premise behind our leaders’ Pandemic Preparedness and Response agenda is knowingly based on a set of complete fabrications would be a conspiracy theory too far. It would be too uncomfortable to accept that we are being deliberately misled by people we elected and the health establishment we trust; that the assurances of inclusivity, equity and tolerance are mere facades hiding fascists. We should examine the key claims supporting the pandemic agenda carefully and hope to find them credible.
Myth #1: Pandemics are becoming more common
In its 2019 pandemic influenza guidelines, the WHO listed 3 pandemics in the century between the 1918-20 Spanish flu and COVID-19. The Spanish flu killed mainly through secondary bacterial infections at a time before modern antibiotics. Today we would expect most of these people, many relatively young and fit, to survive.
The WHO subsequently recorded pandemic flu outbreaks in 1957-58 (‘Asian flu’) and 1968-69 (‘Hong Kong flu’). The Swine flu outbreak that occurred in 2009 was classed by WHO as a ‘pandemic’ but caused just 125,000 to 250,000 deaths. This is far less than a normal flu year and so hardly deserving of the pandemic label. Then we had COVID-19. That’s it for a whole century; one outbreak the WHO classifies as a pandemic per generation. Rare, or at least highly unusual, events.
Myth #2: Pandemics are a major cause of death
The Black Death, the Bubonic Plague that swept Europe in the 1300s, killed perhaps a third of the entire population. Repeat outbreaks over the following centuries caused similar harm, as had plagues known from Greek and Roman times. Even the Spanish flu did not compare with these. Life changed prior to antibiotics – including nutrition, accommodation, ventilation and sanitation – and these mass-mortality events subsided.
Since the Spanish flu we have developed an array of antibiotics that remain extremely effective against community-acquired pneumonia. Fit young people still die from influenza through secondary bacterial infection, but this is rare.
The WHO tells us there were 1.1 million deaths from the 1957-58 ‘Asian flu,’ and a million from the 1968-69 Hong Kong flu. In context, seasonal influenza kills between 250,000 and 650,000 people every year. As the global population was 3 to 3.5 billion when these two pandemics occurred, they classify as bad flu years killing about 1 in 700 mostly elderly people, with little influence on total deaths. They were treated as such, with the Woodstock Festival proceeding without super-spreader panic (regarding the virus, at least…).
COVID-19 has a higher associated mortality, but at an old average age equivalent to that of all-cause mortality, and is nearly always associated with comorbidities. Much mortality also occurred in the presence of the withdrawal of normal supportive care such as close nursing and physiotherapy, and intubation practices may have played a role.
Of the 6.5 million that the WHO records as dying from COVID-19, we don’t know how many would have died anyway from cancer, heart disease or the complications of diabetes mellitus and just happening to have a positive SARS-CoV-2 PCR result. We don’t know because most authorities decided not to check, but recorded such deaths as being due to COVID-19. The WHO records about 15 million excess deaths throughout the COVID-19 pandemic, but this includes lockdown deaths (malnutrition, rising infectious disease, neonatal death etc).
If we take the 6.5 million toll as likely, we can understand its context by comparing it with tuberculosis, a globally endemic respiratory disease that few worry about in their day-to-day lives. Tuberculosis kills about 1.5 million people every year, which is almost half the annual COVID-19 toll in 2020 and 2021. Tuberculosis kills far younger on average than COVID, removing more potential life-years with each death.
So based on normal metrics for disease burden, we could say they are roughly equivalent – COVID-19 has had an impact on life expectancy overall fairly similar to TB – worse in older populations in Western countries, far less in low-income countries. Even in the US COVID-19 was associated with less (and older) deaths in 2020-21 than normally occur from cancer and cardiovascular disease.
COVID-19 has not therefore been an existential threat to the life of many people. The infection mortality rate globally is probably around 0.15%, higher in the elderly, much lower in healthy young adults and children. It is not unreasonable to think that if standard medical knowledge had been followed, such as physiotherapy and mobility for frail elderly people and micronutrient supplementation for those at risk, the mortality rate may have been even lower.
Whatever one’s views on COVID-19 death definitions and management, it is unavoidable that death is rare in healthy younger people. Over the past century all pandemic deaths have been very low. Averaging less than 100,000 people per year inclusive of COVID-19, they are a small fraction of that caused by seasonal flu.
Myth #3: Diversion of resource to pandemic preparedness makes public health sense
The G20 has just agreed with the World Bank to allocate $10.5 billion annually to its pandemic prevention and response Financial Intermediary Fund (FIF). There is, in their view, about $50 billion needed in total per year. This is the annual, holding budget for pandemic preparedness. As an example of their preferred response when an outbreak occurs, Yale University modelers estimate that to vaccinate people in low and middle income countries with just 2 doses of COVID-19 vaccine would cost about $35 billion. Adding one booster would total $61 billion. Over $7 billion has thus far been committed to COVAX, the WHO’s Covid vaccine financing facility, vaccinating most who are already immune to the virus.
To put these sums in context, the annual budget of the WHO is normally below $4 billion. The entire world spends about $3 billion annually on malaria – a disease that kills well over half a million young children each year. The largest financing facility for tuberculosis, HIV/AIDS and malaria, the Global Fund, spends less than $4 billion per year on these three diseases combined. Other and larger preventable killers of children, – such as pneumonia and diarrhea, receive still less attention.
Malaria, HIV, tuberculosis and diseases of malnutrition are all increasing, while economies globally – the main long-term determinant of life expectancy in lower-income countries – decline. Taxpayers are being asked, by institutions that themselves will benefit, to spend vast resources on this problem rather than on diseases that kill more and younger people. The people pushing this agenda do not appear to be dedicated to reducing annual mortality or improving overall health. Alternatively, they either cannot manage data or have a window on the future that they are keeping to themselves.
Myth #4: COVID-19 caused massive harm to health and the global economy
The age-skewing of COVID mortality has been unmistakable since early 2020, when data from China demonstrated almost no mortality in healthy young to middle-aged adults and children. This has not changed. Those contributing to economic activity, working in factories, farms and transport, were never at great risk.
The economic and personal harm arising from the restrictions on these people, unemployment, destruction of small businesses and supply-line disruption, was a choice made against orthodox policy of the WHO and public health in general. The prolonged school closures, locking in generational poverty and inequality on both a sub-national and international level, was a choice to perhaps buy months for the elderly.
The 2019 WHO pandemic guidelines advised against lockdowns due to the inevitability that they would increase poverty, and poverty drives illness and reduces life expectancy. The WHO noted this disproportionately harms poorer people. This is not complicated – even those at the center of the lockdown and future digital ID agenda such as the Bank of International Settlements (BIS) acknowledge this reality. If the aim of poverty-promoting measures had been to reduce elderly death, the evidence for success is poor.
There seems little reasonable doubt that growing malnutrition and long-term poverty, rising endemic infectious disease, and the impacts of education loss, increased child marriage and increased inequality will far outweigh any possible mortality reduction achieved. UNICEF’s estimation of a quarter-million child deaths from lockdowns in South Asia in 2020 provides a window into the enormity of the harm lockdowns wrought. It was the novel public health response that caused the massive harm associated with this historically mild pandemic, not the virus.
Facing truth
It seems unavoidable that those advocating for the current pandemic and preparedness agenda are intentionally misleading the public in order to achieve their aims. This explains why, in the background documents of the WHO, the World Bank, G20 and others, detailed cost-benefit analyses are avoided. The same absence of this basic requirement characterized the introduction of Covid lockdowns.
Cost-benefit analyses are essential for any large-scale intervention, and their absence reflects either incompetence or malfeasance. Prior to 2019, the resource diversion being contemplated for pandemic preparedness would have been unthinkable without such analysis. We can therefore reasonably assume that their continued absence is based on fear or certainty that their outcomes would scupper the program.
A lot of people who should know better are going along with this deceit. Their motives can be surmised elsewhere. Many may feel they need a good salary, and the resultant dead and impoverished will be far enough away to be considered abstract. The media, owned by the same investment houses who own the Pharma and software companies sponsoring public health, are mostly silent. It is hardly a conspiracy to believe that investment houses such as BlackRock and Vanguard work to maximize return for their investors, using their various assets to do so.
A few decades of our elected leaders trooping off for closed-door sessions at Davos, together with a steady concentration of wealth with the individuals they were meeting, could not really have landed us anywhere else.
We knew this 20 years ago, when the media still warned of the harm that increasing inequality would bring. When individuals and corporations richer than medium-sized countries control major international health organizations such as Gavi and CEPI, the real question is why so many people struggle to acknowledge that conflicts of interest define international health policy.
The subversion of health for profit runs contrary to the entire ethos of the post-World War Two anti-fascist, anti-colonialist movement. When people across politics can acknowledge this reality, they can put aside the false divisions that this corruption has sown.
We are being deceived for a reason. Whatever that is, going along with a deception is a poor choice. Denial of truth never leads to a good place. When public health policy is based on a demonstrably false narrative, it is the role of public health workers, and the public, to oppose it.
David Bell, Senior Scholar at Brownstone Institute, is a public health physician and biotech consultant in global health. He is the former Program Head for malaria and febrile diseases at the Foundation for Innovative New Diagnostics (FIND) in Geneva, Switzerland.
Biden endorses G20 Declaration to censor “disinformation”
By Christina Maas | Reclaim The Net | November 24, 2022
During the summit held in Bali, Indonesia, the G20 Leaders signed a declaration endorsing the censorship of “disinformation.” The Biden administration endorsed the declaration by publishing it on the White House website.
The G20 Bali Leaders’ Declaration mainly focused on climate change, including Sustainable Development Goals (SGDs). However, the leaders have linked SDGs with online censorship.
Section 24 of the declaration says there is a need to censor online disinformation.
“The COVID-19 pandemic has accelerated the transformation of the digital ecosystem and digital economy,” the section began. “We recognize the importance of digital transformation in reaching the SDGs.”
It adds that for there to be “trust in the digital economy,” they should “create an enabling, inclusive, open, fair and non-discriminatory digital economy that fosters the application of new technologies, allows businesses and entrepreneurs to thrive, and protects and empowers consumers.”
The G20 leaders believe there is a need to censor “false” information for digital infrastructure to thrive: “We acknowledge the importance to counter disinformation campaigns, cyber threats, online abuse, and ensuring security in connectivity infrastructure.”
The White House endorsing a declaration that calls for more censorship is not surprising considering it is the subject of the lawsuit filed by Missouri’s and Louisiana’s Attorneys General alleging collusion between the government and social media companies to censor viewpoints surrounding Covid and more.
Featured Video

HE SAVED LIVES. NOW HE FACES PRISON.
or go to
Aletho News Archives – Video-Images
From the Archives
The Geopolitics behind the War in Yemen (I)
By Mahdi Darius NAZEMROAYA | Strategic Culture Foundation | 30.03.2015
The United States and the Kingdom of Saudi Arabia became very uneasy when the Yemenese or Yemenite movement of the Houthi or Ansarallah (meaning the supporters of God in Arabic) gained control of Yemen’s capital, Sanaa/Sana, in September 2014. The US-supported Yemenite President Abd-Rabbuh Manṣour Al-Hadi was humiliatingly forced to share power with the Houthis and the coalition of northern Yemenese tribes that had helped them enter Sana. Al-Hadi declared that negotiations for a Yemeni national unity government would take place and his allies the US and Saudi Arabia tried to use a new national dialogue and mediated talks to co-opt and pacify the Houthis.
The truth has been turned on its head about the war in Yemen. The war and ousting of President Abd-Rabbuh Manṣour Al-Hadi in Yemen are not the results of «Houthi coup» in Yemen. It is the opposite. Al-Hadi was ousted, because with Saudi and US support he tried to backtrack on the power sharing agreements he had made and return Yemen to authoritarian rule. The ousting of President Al-Hadi by the Houthis and their political allies was an unexpected reaction to the takeover Al-Hadi was planning with Washington and the House of Saudi. … continue
Blog Roll
 Aletho News
- Finland’s Stubb tells European leaders to calm down
- Defeating Russia on battlefield impossible – Fico
- Finland’s Gender Clinic Reversal
- Massachusetts Wants Mental Health Visits, Why Does Government Use ‘Health’ to Enter Our Homes & Families?
- US lawmaker admits American people footing bill for Trump’s failed aggression against Iran
- Pfizer Gave $500,000 to Groups That Lobbied to End Religious Exemption in Massachusetts
- HE SAVED LIVES. NOW HE FACES PRISON.
- Israeli lobby seeks to bind US fate to ‘Israel’: Araghchi
- Pakistan-Iran talks secure LNG shipment to Islamabad through Hormuz
- Black Sea grain crisis puts global wheat supplies under pressure
- If Americans Knew
- Israel Is Expanding and Upgrading Compounds for Palestinian Militias in Gaza
- The Palestinian-American Residents of This West Bank Town Are Wondering: Where Is Trump?
- Gaza desperately needs tents, wheelchairs, fuel… and everything else (Israel blocks it all) – Daily Update
- Israeli Attacks in Gaza Kill at Least Seven Palestinians Over Three Days, including Woman and Child
- Trump’s militarization of Washington DC as he pursues Israel’s war against Iran
- Why Israel Fears This Searing New Documentary
- Huckabee aide solicited cash gifts from Israelis
- This isn’t sci-fi, AI is already killing people
- ‘The Most Brutal Thing’: Investigation Reveals Execution of Elderly Woman in Rafah
- Inside Israel’s ‘soft’ ethnic cleansing plan for Gaza through the eyes of its victims
- No Tricks Zone
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
- Fear Of Debate: Alarmist German Climate Scientist Calls On Mainstream Media To Discredit Skeptic Voices

