As a truth-seeking journalist writing on Covid policies surrounding the young, I have been bewildered by the scientific establishment’s failure to have an honest, rational discussion of the data. Being an ordinary, critical-thinking person with no prior scientific expertise, my impression was always that the costs and benefits of an medical intervention must be carefully weighed before making a decision. Moreover, I assumed there is no “one-size-fits-all” medicine — everything from Tylenol, prescription drugs, to novel psychedelic therapies — that can be universally recommended.
According to the foremost public health “experts”, I was wrong.
This suddenly dawned on me when I watched CNN’s Dr. Sanjay Gupta refuse to acknowledge the risk of vaccine myocarditis in young boys on Joe Rogan’s podcast, then appear on CNN shortly after doubling-down on his assertions by presenting a study finding infection-induced myocarditis poses a greater risk compared to the vaccine (across the population, as opposed to young men specifically).
Publication after publication have printed articles quoting medical experts “debunking” concerns of vaccine myocarditis in young males using flawed CDC data or aggregate population-level data which shows the risk of Covid myocarditis exceeding that from the vaccine.
This is incredibly dishonest. The conversation from the start has always oriented around the specific risk in young men.
Among the most rigorous, comprehensive data we have on vaccine myocarditis is from Katie Sharff who analyzed a database from Kaiser Permanente. She found a 1/1,862 rate of myocarditis after the second dose in young men ages 18 – 24. For boys ages 12 – 17, the rate was 1/2,650. Active surveillance monitoring in Hong Kong shows virtually identical figures.
After failing the Joe Rogan test, Dr. Gupta decided to promote his one-size-fits-all vaccine advocacy on a less questioning and critical-thinking platform: Sesame Street. “The second vaccine dose gives you stronger, longer, and wider protection,” he stated on the kids program. “Hopefully the protection lasts a long time!”
Leading public health officials who do honestly discuss vaccine risks are immediately punished. Last week, after Ontario’s Chief Medical Officer of Health conceded the possible 1/5,000 risk of myocarditis for healthy young people at a conference promoting the fourth dose, a number of top “doctors” in the province rebuked his remarks.
“The incidence of myocarditis after vaccination is much lower than 1 in 5000,” cardiac radiologist Dr. Kate Hanneman stated, referring to the risk in the wider population.
City News: ‘Much lower than 1-in-5,000’, doctors take issue with Dr. Moore’s myocarditis claim
As a result of the mainstream medical community’s failure to weigh the age-specific cost and benefits of vaccination, young people across North America have been coerced, misinformed, and marginalized. Virtually all across Canada, anyone unvaccinated between 15-30 (and over) was barred from exercising at a gym, dining in at restaurants, and attending large gatherings.
In the United States, a number of school districts are now bizarrely mandating the primary vaccine series for the fall, despite newer variants and a seroprevalence rate indicating prior covid infection in children of 75% (pre-Omicron).
ABC News DC to require students 12 and older to be vaccinated against COVID-19 this fall
As Megyn Kelly recently lamented, her kids are now not only facing exclusion from sports and after school activities, but expulsion if they don’t get double vaccinated at their school in Connecticut.
The institutional push to mandate and coerce vaccination in the young is not only pushed in schools and public health centers, but by journalists as well. As a pro-vaccine writer reporting on vaccine myocarditis in a specific demographic (arguing only for personal choice and no mandates), I have been stunned by a number of reputable outlets refusing to publish anything that acknowledge the risks.
After pitching one editor, she replied:
“The _____ is a pro-vaccine publication. We don’t run any pieces that discourage the public from getting vaccinated.”
Another editor:
“Rav, I don’t know why you’re still writing about this. I personally think everyone should get vaccinated already and stop making this a big deal for everyone. The risks for young men are still incredibly small.”
One editor I had a very close relationship with:
“I think the risk of vaccine myocarditis has been vastly exaggerated. It comprises a minuscule fraction of vaccinations. Please pitch this to another outlet.”
The scientific community’s misleading claims have also permitted the violation of informed consent and a number of preventable vaccine-induced myocarditis incidents.
In a recent long-form investigative article (rejected by several publications), I interviewed a 33-year-old previously healthy and incredibly fit man who unwillingly got double-vaccinated to keep his job in law-enforcement.
He didn’t hear the term “vaccine-induced myocarditis” till the doctor told him his diagnosis when he ended up in the hospital after almost dying from heart failure (210 beats per minute) following the second Pfizer dose.
Or take the recent viral story of a triple-vaccinated mother who followed the advice of public health authorities and got her 14-year-old son double-vaccinated, resulting in vaccine myocarditis:
Mom Whose 14-Year-Old Son Developed Myocarditis After Pfizer Vaccine No Longer Trusts CDC, Public Health Officials
We’ve known that teenage boys are at two to three times higher risk of vaccine myocarditis than Covid hospitalization. We’ve known men under the age of 40 remain at elevated risk of vaccine myocarditis (Oxford analysis).
Yet, the government — as informed by “top epidemiologists” — has not created any public awareness surrounding this issue. Perhaps they are worried this would discourage some people from getting vaccinated, and they want as many people vaccinated as possible.
Instead of making careful, age-stratified recommendations, they now strongly encourage everyone to get three doses. Hardly day goes by without a Canadian government advertisement popping up on YouTube prompting teenagers and young adults get boosted to “prevent serious illness.”
Many in the media and medical establishment promote vaccination to prevent serious illness or death in the elderly, but react to any information that questions the safety and efficacy of vaccination in children with a kind of religious opposition.
Supporting the vaccine means judiciously recommending it to those who have more to gain and less to lose and being transparent about the real risks of vaccination in specific demographics — without either agenda-driven minimization or exaggeration. Obfuscating, downplaying, and misleading the public, on the other hand, undermines trust in public health recommendations.
November 14, 2022
Posted by aletho |
Full Spectrum Dominance, Science and Pseudo-Science, Timeless or most popular | COVID-19 Vaccine |
Leave a comment
The lords of lockdown barely escaped their worst possible fate, namely that the topic would become the national and international source of scandal that it should be. And let’s add the vaccine mandates here too: even if such had been morally justified, which they were not, there is absolutely no practical reason for them at all.
To have imposed both of these within the course of one year – with zero evidence that they achieved anything for public health and vast amounts of unfolding evidence that they ruined life quality for countless millions – qualifies as a scandal for the ages. It was in the US but also in nearly every country in the world but a few.
Might that have huge political implications? One would suppose so. And yet today it appears that truth and justice are further off than ever. The most passionate of the anti-lockdown governors – those who never locked down or opened earlier than the rest of the country – won on their record. Most of the rest joined the entire political establishment in pretending that all of this is a non-issue. Tragically, this tactic seems to have worked better than it should have.
Meanwhile, a few points to consider:
The US government, through the Transportation Safety Administration, has signed yet another order extending the ban on unvaccinated international visitors until January 8, 2023. This means that no person who has managed to refuse the shot is allowed to come to the US for any reason. This is 30% of the world’s population, banned even to enter the US on their own dime. Something like this would have been inconceivably illiberal three years ago, and been a source of enormous controversy and outrage. Today, the extension hardly made the news.
The Biden administration has once again extended the Covid emergency declaration another 90 days, which continues to grant government vast powers without Congressional approval. Under a state of emergency, the Constitutional structure of the US is effectively suspended and the country remains on a wartime footing. This announcement was not controversial, and, like the above, it barely made the news.
Many colleges and universities, and also other schools and public agencies, continue to enforce the vaccine mandate even without any solid science behind the approval of the bivalent shots or any real rationale behind the push, given that most people have long ago been exposed and acquired natural immunity, and, moreover, it is very well established that the shots do not protect anyone from infection nor stop transmission. They just keep doing this anyway.
Masking is not in disrepute because we never really obtained anything like an honest admission of their failure to control the spread. Even today, there is a percentage of people out there permanently traumatized. On travels, I’m seeing perhaps 10-20% but in some Northeastern cities, regular wearing of masks is also very common. Once they became a symbol of political compliance and virtue, that sealed the deal and the culture was changed. Now we face the threat of mask mandates whenever government deems it necessary because the Transportation Safety Authority has been given the go-ahead by the courts.
The end of vaccine mandates in most areas of life, and hence also the drive for a passport to distinguish between clean and unclean people, is a good sign. But the infrastructure is still in place and becoming more sophisticated. It is hardly a final victory. It might only be a temporary respite, while all the ambitions are still extant.
More than that, the Biden administration (and all that it represents, including the World Economic Forum, the World Health Organization, and everything else called the establishment) has its own pandemic plans in place. The idea is not to dial back the mandates or cool it on them. It’s the reverse: centralize all pandemic planning to make a South Dakota, Georgia, and Florida experience impossible the next time. Also, spend tens of billions in more money.
The principle seems to have emerged among the agencies, intellectuals, and politicians who did this. Whatever you do, never admit to having made any major mistakes. And never connect the economic, cultural, health, and educational disasters all around us to anything the govenrment did in 2020 or 2021! That would be nothing but a conspiracy theory.
The pandemic racket is so huge at this point that it is even embroiled in the FTX meltdown over the weekend. Sam Bankman-Fried’s brother Gabe actually founded a nonprofit solely for the purpose of providing “support” for the $30 billion that the Biden administration has allocated to pandemic planning. The institution “Guarding Against Pandemics” is very obviously a honeypot for such funding, complete with on-the-record endorsements from many Democrat Party candidates who won election.
Meanwhile, yes, there have been many successful court challenges to many features of the pandemic response. But not enough. The main machinery that took away liberty and property in the name of virus control is still in place in all its essentials. The CDC to this day brags of its awesome quarantine powers that it can deploy any time government deems it necessary. Nothing about that has changed.
In the big picture and rendered in a philosophical sense, humanity seems to have lost its ability to learn from its own errors. Put in more gritty terms, too many people among ruling-class interests gained financially and in terms of the lust for power during the pandemic to prompt any serious rethinking and reform.
In any case, that rethinking and reform is now put off for another day. Anyone seriously concerned about the future of humanity and the civilizations it built must throw themselves into the long-term battle for truth and reason. That will require that we use every bit of what remains of free speech and what remains of the longing for integrity and accountability in public life. The group we have come to call “they” want a demoralized population and a silent public square.
We cannot allow that to happen.
Jeffrey A. Tucker, Founder and President of the Brownstone Institute, is an economist and author. He has written 10 books, including Liberty or Lockdown, and thousands of articles in the scholarly and popular press.
November 14, 2022
Posted by aletho |
Civil Liberties, Corruption, Science and Pseudo-Science, Timeless or most popular | Covid-19, COVID-19 Vaccine, Human rights, United States |
Leave a comment
World leaders have been taking energy advice from people like Michael Mann and Greta Thunberg, who have no experience or expertise related to energy. Simultaneously, governments have been refusing to listen to the people who provide the world’s energy.
November 14, 2022
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular, Video |
Leave a comment
There’s been an interesting follow up to BBC’s recent story about the Pakistan floods at the end of August.
Readers will recall that the claim that one third of the country was under water immediately set off my BS detector, and I did a full analysis here, totally debunking it.
But just a couple of days after my piece, the BBC’s More or Less radio programme also looked at the claim, after some viewers had complained.
They interviewed an environmental scientist who checked out what the various satellite records indicated. His conclusion was that the true figure was that about 10% of the country had been affected by floods, and much of this was short term.
In fact, all the BBC had to do was what I did in a few minutes, and check what NASA were reporting.
It was plainly evident that nothing like a third of the country had flooded. Indeed a simple look at the map would have shown them that much of Pakistan is either mountainous or desert, which would be impossible to flood.
They could also have checked with the UN disaster agency, OCHA, who were publishing regular reports on the flooding.
According to them, the area affected was 75000 sq km, or 9% of the country.
In fact, these are precisely the sort of checks the BBC should have carried out before making their absurd claim. One which anybody with an ounce of common sense, or integrity, would have immediately suspected was wrong.
It is doubly ironic that the BBC’s defence was that the one third claim had been widely reported across the media. This shows just how utterly corrupt most of the media is nowadays.
November 13, 2022
Posted by aletho |
Fake News, Mainstream Media, Warmongering, Science and Pseudo-Science | BBC |
Leave a comment
History shows that hiding clinical trial data can be deadly.
Vioxx is a well-known example of how the US drug regulator withheld important information about the harms of the drug for over three years, before it was withdrawn from the market and tens of thousands of people died as a consequence.
Numerous initiatives have been launched over the past two decades to improve access to trial data after it became evident that what was reported in peer-reviewed journals was often cherry-picked and misleading.
Eminent scientists have succeeded in gaining access to trial data from the European and Canadian drug regulators, but a recent analysis published in the Journal of Law, Medicine, & Ethics, found that the US FDA still lags behind others when it comes to data transparency.
Drug regulators have traditionally been the guardians of a treasure trove of trial data which they kept hidden from the public. But, over a decade ago, the efforts of Danish professor Peter Gøtzsche turned that on its head.
Gøtzsche and his PhD student were studying the effects of an anti-obesity drug and requested the trial data held by the European Medicines Agency (EMA).
“We already had good evidence that the efficacy and harms of drugs were incompletely reported in the medical journals, so by asking for the regulatory data for the anti-obesity pills, we were convinced it would get us closer to the truth”, said Gøtzsche.
At first, EMA denied their request, saying that it needed to protect commercially confidential information, but Gøtzsche was undeterred. He made a formal complaint to the European Ombudsman.
After an arduous 3-year process, the Ombudsman accused EMA of “maladministration” for refusing to share its data – it was a serious and embarrassing charge, so EMA had no choice but to capitulate.
In 2013, EMA announced that it would provide public access to regulatory data – which included study reports, protocols and the raw anonymised patient data in statistical programmes enabling anyone to independently scrutinise the data for all new drugs that it approved.
It was a bitter-sweet moment for Gøtzsche.
“I was satisfied with the outcome, but I also felt a bit betrayed. When EMA praised itself for being transparent, it conveniently omitted telling the public that it was basically forced to make the decision because of my efforts and that of the Ombudsman,” said Gøtzsche.
“I’ve been around a while to know that this is exactly how the drug industry operates. They cover up their failures while praising themselves for what others force them to do,” he added.
Millions of pages containing trial data have since been released. Interestingly though, this remarkable feat has gone largely unrecognised and the response from the research community has been rather tepid.
Gøtzsche suspects it’s because analysing regulatory documents is complex and requires experience to decipher regulatory data – skills that few researchers have.
“It is a huge job to do systematic reviews of clinical study reports held by drug regulators, but it is the difference between producing reliable reviews or merely “garbage-in, garbage-out” reviews,” said Gøtzsche.
Since then, Gøtzsche’s group showed this was the case for reviews of antidepressant drug trials.
When they compared data from medical journals to that from regulatory documents, they found major discrepancies such as underreporting of harms, including suicide attempts and aggressive behaviour.
Following the landmark policy change in Europe, researchers believed it would help unlock regulatory documents elsewhere that were historically kept hidden from the public.
In 2016, Peter Doshi, professor at the University of Maryland and senior editor of The BMJ requested the release of unpublished clinical trial data relating to antivirals for the treatment of influenza (Tamiflu, Relenza) and three human papillomavirus vaccines from the Canadian drug regulator, Health Canada.
After some resistance, Health Canada agreed to allow Doshi access to the documents but imposed a confidentiality agreement that would prevent him from making his findings public.
When Doshi refused to sign the confidentially agreement, his request for access to the trial data was denied, so he filed a lawsuit in a federal court seeking a judicial review of the regulator’s decision.
Remarkably, in 2018, in the case of Peter Doshi v. Attorney General of Canada, a federal court judge ruled in favour of Doshi and in the public’s interest, ordering Health Canada to hand over the trial data for independent scrutiny.
It was hailed a “major victory” for transparency and after the win, Doshi told The BMJ, “For me this case has always been about something larger than my specific request. It is about the principle of transparency. If my case sets a precedent and Health Canada begins making clinical trial data available to others—promptly, and without imposing confidentiality agreements—that will be the real victory.”
Notably, the Canadian drug regulator has gone one step further than EMA by proactively releasing data for not only approved drug submissions, but also “unapproved, and withdrawn drug and biologic submissions… Class III and IV medical device applications.”
The US FDA houses the largest known repository of clinical trial data in the world, but it doesn’t proactively share it.
In 2018, the FDA launched a new pilot program to proactively publish clinical study reports from the pivotal studies of nine recently approved drugs – but the agency put an end to that program in March 2020.
“It is just so typical of the FDA, which is very beholden to industry, and which some have dubbed the Foot Dragging Agency when it comes to the public interest,” said Gøtzsche.
Now, the only mechanism to ascertain regulatory data for FDA-approved drugs is to submit Freedom of Information Act (FOIA) requests, a lengthy process which often results in heavily redacted documents of limited value.
A study by US researchers, analysed the FDA’s willingness to release data, compared to other regulators, EMA and Health Canada.
They found that between 2016 and April 2021, EMA released data for 123 unique medical products, while Health Canada released data for 73 unique medical products between 2019 and April 2021.
In stark contrast, the FDA only proactively disclosed data supporting one single drug that was approved in 2018, clearly demonstrating that the agency has failed to keep pace with the European and Canadian regulatory bodies.
The problem of data secrecy within the FDA has been especially evident during the pandemic. Recently, I reported in The BMJ that the agency had failed to disclose covid-19 vaccine ‘safety signals’ derived from post-marketing data.
Also, the non-profit group, Public Health and Medical Professionals for Transparency had to sue the FDA for access to trial documents used as the basis for licensing Pfizer’s covid-19 mRNA vaccine. Initially, the agency wanted 75 years to release all the data but a Federal Court Judge rejected its request, ordering the release of the documents at a rate of 55,000 pages per month, taking approximately 8 months.
Given the widespread use of this important public health intervention, and the billions of dollars in public funds used to conduct vaccine research and development, these data should have been made publicly available immediately.
Data secrecy has undermined the health care system by subverting the allocation of scare resources and eroding public trust. The damage done to people’s confidence in vaccines, and medicines more broadly, will be felt for generations and likely to harm public health.
November 13, 2022
Posted by aletho |
Deception, Science and Pseudo-Science, Timeless or most popular | EMA, FDA, Health Canada |
Leave a comment
Dr. Rochelle Walensky Tweeting Counterfactuals with Intent
CDC Director, Rochelle Walensky, MD, MPH, for the record, continues to make false claims about the COVID-19 vaccine boosters with the apparent motivation of getting more Americans “fully vaccinated.” This is in the backdrop of an 8.4% rate of Americans over age 5 taking one of them.[i]
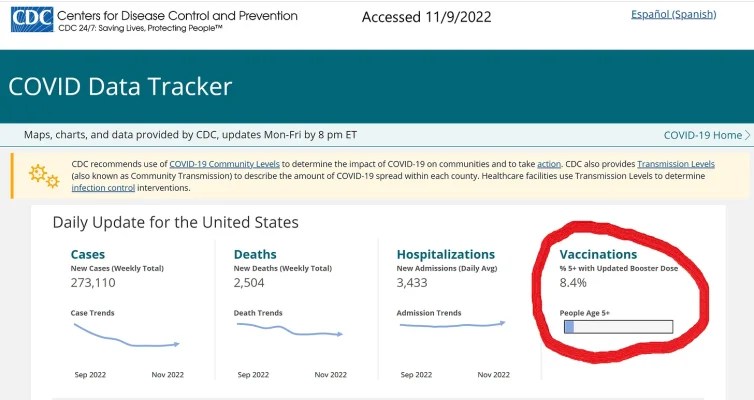
No matter how hard the internal pressure is at the CDC to get a “needle in every arm,” what would be such a strong motivation for Walensky to blatantly deceive Americans with such obvious counterfactual information?
She states “COVID-19 vaccines may not prevent every infection (as apparent in her personal case), but they do provide us important protection against severe illness, hospitalization, and death…”

In order for that claim to be valid by US regulations, a COVID-19 vaccine would need to reduce the risk of adjudicated COVID-19 hospitalization and death as a primary endpoint in a prospective, double blind, randomized, placebo-controlled trial. The benefit would need to be meaningful, e.g., ~20% relative risk reduction, and statistically significant, e.g., p<0.05. The conclusive study should have no significant threats to validity such as loss to follow-up. There has been no pivotal randomized trial, and no one can claim COVID-19 vaccines reduce hospitalization and death. The shortest section on the FDA Pfizer Fact Sheet is the “Benefits” section! This is given with the consent form and makes no claims about severity, hospitalization, and death.[ii]

She goes on to promote a two-month period between the last injection (presumably legacy mRNA) and the new bivalent vaccine. This schedule has never been tested and demonstrated to be safe in human beings. Even more shocking, the bivalent boosters which failed in animal studies to stop Omicron, have never been tested for safety or efficacy in human RCTs with clinical outcomes. In academic medicine and the pharmaceutical regulatory community, the question is WHY does Walensky cross the line into making false claims, an illegal act for fully FDA approved and marketed drugs/vaccines? Only senate or congressional hearings with direct questions will get the truth out of her.
Here are some possibilities: 1) she is following orders from higher governmental authorities, 2) she knows the claims are false but truly believes the only way for vaccination to work is to keep everyone vaccinated on a continuous basis no matter what the costs, 3) she is in a form of a trance or psychological state driven by fear in herself and for humanity where COVID-19 vaccination has become like a talisman with special powers and cannot be challenged. Indeed, Walensky has never comprehensively discussed safety of COVID-19 vaccination, and she has not disclosed who should NOT take a COVID-19 vaccine. So, the next time someone in your circles claims you or your loved one should take a COVID-19 vaccine to be “safe” or “protected” from serious outcomes, ask them to take a look at the consent fact sheet and read the tiny benefit section.
[i] CDC COVID Tracker, Accessed November 9, 2022
[ii] VACCINE INFORMATION FACT SHEET FOR RECIPIENTS AND CAREGIVERS ABOUT COMIRNATY (COVID-19 VACCINE, mRNA), THE PFIZER-BIONTECH COVID-19 VACCINE, AND THE PFIZER-BIONTECH COVID-19 VACCINE, BIVALENT (ORIGINAL AND OMICRON BA.4/BA.5) TO PREVENT CORONAVIRUS DISEASE 2019 (COVID-19) FOR USE IN INDIVIDUALS 12 YEARS OF AGE AND OLDER, August 22, 2022
November 13, 2022
Posted by aletho |
Deception, Science and Pseudo-Science, War Crimes | COVID-19 Vaccine, United States |
Leave a comment
One novel feature of the pandemic, from the standpoint of public debate, is the fact that so much name-calling, ‘fact-checking’ and censorship was aimed not just at random dissidents but at credentialed scientists.
Academics who’d reached esteemed positions within their field were denounced as ‘Covid deniers’, accused of spreading ‘misinformation’, and subjected to multiple forms of censorship.
Renowned scholars had warning labels attached to their tweets, and found their articles blacklisted on sites like Facebook and LinkedIn. In one particularly egregious case, the Great Barrington Declaration was downranked by Google, so that when users searched for it, articles critical of the Declaration appeared above the Declaration itself.
Somehow, Big Tech firms felt they were in position to adjudicate complex scientific debates. This would be like two scientists having an argument at speaker’s corner in Hyde Park, but the groundskeeper keeps blasting an airhorn every time one of them speaks.
And it wasn’t just Big Tech that restricted one side’s freedom of speech. Academics who questioned the mainstream view on Covid faced sanctions from their universities, journals and professional associations.
In a recent paper, Yaffa Shir-Raz and colleagues analysed the tactics that were used against dissenting scientists, based on semi-structured interviews with some of the targets. Their findings have already been summarised by Carl Heneghan and Tom Jefferson, but it’s worth pulling out a few anecdotes from the paper.
One interviewee recounted that he/she was even censored on Google docs – a program for creating documents and spreadsheets (like Microsoft Office):
Google Docs started restricting and censoring my ability to share documents… This is not Twitter throwing me off like they did. This is an organisation telling me that I cannot send a private communication to a colleague or to a friend, or to a family member.
Another interviewee explained that his/her employment contract was re-written after he/she deviated from the narrative:
They offered me a new contract… we got some new terms for you, because my old contract was not restricted. The new one basically had like seven or eight restrictions of my First Amendment rights… basically I couldn’t talk to the press, I couldn’t speak in public… unless I said, these are my opinions not that of my employer… It was a relatively short conversation. I said that’s never going to happen, I’m never going to sign that thing.
A third interviewee described how he/she was cancelled by several organisations without any due process:
There was a whole series of actions taken again with no due process and no explanation… I received a notice from the [medical association] that I was being stripped from a committee position… I received a letter from a journal…where I was the Editor-in-Chief, being stripped of the editorship, again with no due process, no phone calls no, tractable explanation… I received a letter from the National Institutes of Health being stripped from a longstanding committee position.
Remember, these were all “established doctors and scientists”, not foreign spies engaged in subversion.
The point isn’t that dissenting scientists were right about everything (although they were right about a lot). It’s that we can’t have a proper debate if one side faces a barrage of name-calling, ‘fact-checking’ and censorship. Enforcing a narrative around Covid shouldn’t be the role of Big Tech companies. And it certainly shouldn’t be the role of academic institutions.
November 13, 2022
Posted by aletho |
Civil Liberties, Full Spectrum Dominance, Science and Pseudo-Science, Timeless or most popular | Covid-19, COVID-19 Vaccine, Facebook, Google, Human rights, LinkedIn |
Leave a comment
In my research into “early spread,” one oddity that’s jumped out at me is how some people with antibody evidence of early infection seem to intuitively know this information is taboo or controversial. Some people clearly sense when they’re saying something that “goes against the narrative” … and this makes them very nervous.
On one level, this has always bothered me. What’s wrong with simply telling the truth? For an investigative journalist, it’s frustrating that some people with important information won’t go on the record and provide such information.
On the other hand, I get why some people would prefer to remain anonymous or not be mentioned in any story at all. Fear rules the thinking of just-about everyone (a maxim that also explains how those who create said fear effectively rule the world).
Many people with important information clearly fear some type of reprisals even if they are simply telling the truth. The disturbing point is that many of these people aren’t being paranoid. They probably would suffer some kind of negative blowback if they told the truth. This could be as extreme as losing a job or as prosaic as having friends or family members treat them differently because they said something others don’t agree with.
I started thinking about this topic when I went back and re-read a couple of stories published by The Seattle Times that document two residents of Snohomish County who almost certainly had Covid in December 2019.
One of these two residents was not named. However, the other resident did exhibit some level of courage by allowing a reporter to interview her. But the lady was only identified in the story by her middle name. So “Jean,” a 64-year-old retired nurse from a rural area of Washington state, thinks she had Covid.
My hunch is Jean intuitively knew her story might upset some powerful people – people who did not want to “confirm” any evidence that Americans were coming down with this illness before the Wuhan Outbreak in China.
Or maybe Jean thought her claims might bother some of her friends and neighbors, friends who always trust the experts and authorities and don’t like it when anyone goes against, say, the pronouncements of Anthony Fauci … or CNN.
For whatever reason, Jean settled on a compromise. She’d share her story, but she wouldn’t use her full name.
After researching the case of another “early spread” candidate, I understand why Jean might have wanted to be identified only by her middle name.
Michael Melham happens to be the mayor of Belleville, New Jersey. Along with Jean and the other unknown person from Washington, Melham is among the 17 Americans I’ve identified in previous articles as Americans who almost certainly had Covid weeks or months before the virus was supposed to be circulating in our country.
Michael Melham did go public with his story. Among the news organizations covering his claim was NJ.com.
The headline from the “straight news” piece makes this news organization’s point, as well as my point:
“N.J. mayor makes unfounded claim that he had coronavirus in November.”
One piece of yellow journalism apparently wasn’t enough so the news organization also published a scathing opinion column the next day.
Wrote columnist Jeremy Schneider:
“It needs to be said. Again. This is not the time for voluntary stupidity. If you have something to say about the coronavirus that is not supported by proven truths presented by experts, you should really, really just keep it to yourself. People are dying and you are almost certainly not an epidemiologist. Be quiet and listen.”
Schneider also called the people who suspect they may have had Covid before the experts said was possible, “a sub-sect of well-meaning dopes on social media.”
And although readers had already gotten the author’s unsubtle point – our official guidance – the writer made it again in the smear piece he was happy to pen: “Stay safe, listen to the experts.”
Basically, Schneider is calling Mayor Melham, and anyone else who believes they had Covid before mid-January 2020, idiots. It never occurs to the author he might be the real idiot. Nor does it occur to him that the experts he thinks are infallible may be using people like himself to advance their misery-producing agendas.
Why don’t more people come forward as whistleblowers? Here we probably have part of our answer.
But the sociology and psychology component that really fascinates me is how so many people quickly accept the authorized “narrative” and then have a visceral reaction to people who do not happen to subscribe to this thinking.
This evidence of mass “groupthink” can also be seen from reading the 1,600 reader comments that followed a Fox News story on Michael Melham’s claim.
As I was doing my “due diligence” on early spread, I think I read every one of these comments. I would say that 95 percent of commenters thought Melham was simply wrong in thinking he had Covid or, like the NJ.com columnist, were angered the mayor had the temerity to share his own story and personal opinions.
What I’m really trying to understand is why so many people are so quick to share their disgust with individuals who don’t think like they do.
People with important information like Jean who are afraid to use their full name (or those who won’t come forward at all) must conclude that the potential wrath of their peers is not worth the benefits … and/or that there are no benefits from going against the narrative.
Due to this dynamic, the public is unlikely to learn important, narrative-changing information. The only thing that might change some harmful and false narratives is if people did come forward and expose this. However, in the “home of the brave” very few people are bold enough to do this.
And as we saw above, even when people like Mayor Melham do come forward, their revelations are dismissed or ridiculed by the people who matter – the watchdog press and authorities. That is, everything works to “protect the narrative.”
Which leads me to my final depressing point: If 99 percent of the people posting in Reader Comments sections happen to be dead wrong, this wouldn’t matter if, say, 10 percent of the country’s journalists were real skeptics and did the job of real journalists.
If this was the case, truth-seeking journalists would write important stories that might influence the 90 percent of the population who’ve been sold a bill of goods. That is, journalists – if they did their most important job – could maybe change a few bogus or dubious narratives.
But this isn’t going to happen because, at least regarding Covid narratives, the group think is 100 percent.
So what we have is some kind of “Catch-22” self-protecting loop of WrongThink. In such a world, the probability any taboo truths could break through the barricades erected by our “gatekeepers of the news” is probably zero. No false narratives will ever be de-bunked.
The journalists who are supposed to challenge narratives won’t do it because they always believe authorities and experts. As most people get their information from mainstream journalists, it’s a case of the dumb leading the …. ah, non-critical thinkers.
Anyway, all of this probably explains, at least in part, why so many would-be whistleblowers are afraid to blow any whistles.
In summary, many people intuitively sense when they posses information that contradicts the official narrative. This Sixth Sense makes many people leery of coming forward or attaching their name to revelations that go against conventional wisdom .
While this is a small observation, the implications which flow from it are probably large. For example, the quality of life of our children and grandchildren will be lower because important truths were not previously acknowledged, because rotten leaders were not previously exposed.
It might be counter-intuitive, but it’s not the false opinions of the masses that matter. It’s the views of a very small minority of truth-revealing contrarians, a group that’s too often afraid to come forward and reveal what they know.
Those who smear, bully or dismiss such people know not what they do … nor the harm they are really causing.
November 13, 2022
Posted by aletho |
Full Spectrum Dominance, Mainstream Media, Warmongering, Science and Pseudo-Science, Timeless or most popular | Covid-19 |
Leave a comment

Southern California’s Orange County Health Department this month declared a local health emergency over concerns around the rising number of pediatric cases of Respiratory Syncytial Virus (RSV).
County officials also declared a Proclamation of Local Emergency, allowing them to access state and federal resources in response to the spread of RSV.
The news came amid media warnings of a looming “tripledemic” of RSV, influenza and COVID-19 and news that Pfizer and GlaxoSmithKline (GSK) are close to securing regulatory approval for their RSV vaccine candidates — including Pfizer’s RSV vaccine for pregnant women.
RSV was first identified in 1956, and frequently affects children, with a majority of childhood cases occurring before age 2. For most children, symptoms are similar to those of the common cold, according to the Centers for Disease Control and Prevention (CDC).
It can, however, cause serious symptoms in the very young and the elderly, although childhood deaths are infrequent, according to CDC data.
According to California attorney Rita Barnett-Rose, there’s no evidence to support claims that Orange County hospitals are overextended, or to justify a state of emergency.
In an interview with The Defender, Barnett-Rose drew parallels between Orange County’s emergency declaration for RSV and other state, local and federal emergency declarations for COVID-19:
“One of the other alarming things that happened with COVID is when [Gov. Gavin] Newsom declared the state of emergency in COVID. He also waived the 30 and 60-day review periods for all local governing boards.
“So, yeah, so that’s what everyone is concerned about, this perpetual state of emergency.
“And the other thing that it triggers is it asks, once they declare a state of emergency, aside from getting the funding, it also triggers a request to Governor Newsom to declare a statewide state of emergency and then also to have Newsom ask President Biden to declare a national state of emergency.”
That could lead to Emergency Use Authorization (EUA) of RSV vaccines, according to Barnett-Rose, who told The Defender there may be an avenue to challenge the legality of the latest Orange County emergency declaration.
Is pharma using the COVID playbook to push RSV vaccines?
Dr. Regina Chinsio-Kwong, Orange County’s health officer, said in a press release county officials issued the declaration due to “rapidly spreading virus infections causing record numbers of pediatric hospitalizations and daily emergency room visits.”
The declaration will allow the county to access state and federal resources and to allow non-pediatric hospitals to offer beds to sick children, Chinsio-Kwong said.
Children’s Health Defense (CHD) California Chapter notes that this declaration was unanimously ratified “over the objections by members of the public who showed up to speak against the declarations.”
Dr. Melaine Patterson, chief nursing officer for Children’s Health Orange County, said area hospitals are seeing an “unprecedented” volume of children visiting their emergency rooms — approximately 400 per day, with wait times of “four to 12 hours.”
She also said that, as of Nov. 1, there were 285 patients in her hospital, compared to 188 on that date last year, adding that 11 of those current patients were placed in ICU as a result of RSV infections. RSV cases also are on the rise nationally.
Chinsio-Kwong advised the public to remain “up to date with other vaccinations such as flu and COVID-19” to “reduce the burden on hospitals this fall and winter.”
“Our best shot at protecting ourselves and our children from respiratory illnesses continues to be the same things we practiced throughout the pandemic including the use of masks when indoors around others and staying home when you are sick,” Chinsio-Kwong said.
However, Barnett-Rose said hospitals in Orange County may be overextended not due to an unusually high number of admissions, but due to unvaccinated staff having been let go.
She told The Defender :
“I do think that has a big role in it, and a lot of people pointed that out during the hearings and public comments were made about that.
“They were trying to claim … there were not enough pediatric experts or pediatric-trained doctors and medical professionals, so they needed to go outside of the county. And I do think a big part of that is that they did let go of many pediatric nurses and pediatric physicians that refused to take the vaccines. So I do think that this is a crisis of their own making … if there is even a crisis.”
San Diego County also issued a warning to its residents Nov. 4 over rising RSV cases but stopped short of declaring an emergency.
CHD California questioned why Orange County would declare a “Local Health Emergency” now — even though local COVID-19 states of emergency haven’t been lifted.
Despite claims that the purpose of these new declarations is exclusively meant to help county hospitals, CHD California said, “the language of the emergency Resolutions says something else entirely”:
“Both the Resolution to ratify the Local Health Emergency under Health & Safety Code section 101080 and the Proclamation of a Local Emergency under Government Code section 8630 declare the need for these local emergencies not only based on the asserted need to handle allegedly rising cases of RSV — but also because of other unnamed ‘other respiratory illnesses’ that were not discussed during the special meeting or otherwise disclosed to the public.”
Barnett-Rose provided insights into the legal meaning underlying these declarations. She told The Defender :
“There’s a local health emergency, which is declared by the public health officer as opposed to the [county] board … and that is when the health officer says … ‘I’ve been talking to the hospitals and we’ve done some assessments and there’s an increasing rate of respiratory illnesses and the children’s hospitals, and so, because of this, I am asking to declare a local health emergency.’ …
“But her authority to declare a local health emergency only lasts for seven days unless it’s ratified by our board of supervisors. And so, on Nov. 2, our board ratified that, which means now it’s in place and it needs to be renewed or looked at every 30 days, unless Governor Newsom waives that condition.”
CHD California argued that the “overly broad language used in these emergency declarations should be deeply concerning to anyone wary of a repeat of the “public health” measures ordered under COVID-19,” noting that adding the vague statement referring to “other respiratory viruses” creates “plenty of room for further abuse.”
Barnett-Rose told The Defender that, during the Nov. 2 meeting, Chinsio-Kwong said, “No restrictions are currently [emphasis added] in place,” a statement that “caused … a little bit of an uproar during the hearing because of her wording, which suggests that indeed they may end up rolling out mask mandates or some other mandates.”
Under this type of “slippery language,” argued CHD California, even the common cold could be used to issue an emergency declaration.
Barnett-Rose agreed:
“How do you measure that? How do you dispute it? How do you examine it? How do you end it?
“If you’re going by one infectious disease, at least you can try to find some data on hospitalizations or cases or deaths or ICU beds. But when it’s everything, it can still include COVID, flu, cold, COPD, a whole bunch of things that would qualify as respiratory illnesses.”
Barnett-Rose said that attempts will be made to legally challenge these declarations as “overbroad,” noting, however, that while case law precedent exists to challenge overbroad legislation, there is no such precedent in place for states of emergency.
Barnett-Rose she’s looking into whether there’s some way to litigate against these broad states of emergency.
When statutes are overbroad, she said, sometimes you can challenge them for being overley broad or too vague, but she’s not sure if there’s a similar precedent for challenging an overly broad state of emergency.
Declaring a local state of emergency at the county level could trigger a chain of events leading all the way to a national declaration of emergency, according to CHD California:
“By ratifying and/or declaring these local emergencies, the Board has now triggered an official request to Governor Newsom that he also declare a state-wide state of emergency on the same overly broad basis — and to ask the President of the United States to declare a national state of emergency.”
“A nationally declared state of emergency may trigger all of the same measures that have already deeply divided our country: masks on airplanes, business and school closures, and coercive school and employee mandates for experimental ‘vaccines’ offered as the ‘only solution’ back to Freedom,” CHD California argued.
Barnett-Rose said the emergency declaration in Orange County may be tied to the fact that there are multiple RSV vaccines already in the pipeline:
“The reason this is becoming really huge news is because this is what happened with the COVID state of emergency, too, it kind of went like that in dominoes.
“Once Biden declares a national state of emergency, then that triggers all of the emergency use authorizations that allowed the so-called vaccines for COVID. And I’m sure you already know that there’s vaccines in the works now for RSV that they’re floating out there in the news as well.”
Recounting events that occurred in relation to COVID-19, Barnett-Rose told The Defender that Orange County and some other counties in California declared a state of emergency, “then it went to the state, then it went national, and then, of course, once there’s a national emergency, you can go into Iowa.”
“So I do think that this is very suspicious timing, the articles that we are seeing in the news about being close to this RSV vaccine,” Barnett-Rose said. “And so, I do think that they’re trying to repeat the same playbook.”
Up to 30 RSV vaccine candidates already in pipeline
Pharmaceutical industry publication FiercePharma reported that Pfizer and GSK “moved closer to regulatory approvals” in the past week, and “could each see the first-ever approvals for an RSV vaccine in 2023.”
GSK’s candidate will be reviewed May 3, 2023, while Pfizer is “eyeing an approval filing by year-end.”
In all, up to 30 RSV candidate vaccines have been identified by the National Institutes of Health (NIH).
GSK has secured priority review status for its RSV vaccine following the submission of data from its AReSVi-006 phase 3 trial. The candidate vaccine exclusively targets adults 60 and older, and the data reportedly “showed high overall vaccine efficacy against RSV lower respiratory disease” at a rate of 82.6%, Fierce Biotech reported.
GSK initially intended to develop an RSV vaccine for older adults and for infants, but plans for the latter were shelved due to a “safety concern.” Nevertheless, GSK CEO Emma Walmsley in a call last week with investors described GSK’s new vaccine as “a very significant scientific achievement.”
Previous efforts to develop an RSV vaccine have failed because they “had a persistent tendency to cause worse disease,” due to “a phenomenon known as antibody-dependent enhancement (ADE).”
Dr. Ruth Karron, a pediatrician and professor of international health at the Johns Hopkins Bloomberg School of Public Health, said, “The difference this year is the general public for the first time is probably eagerly awaiting an RSV vaccine, because they’re seeing firsthand just how much of a problem RSV can be,” in a statement drawing a clear connection with the reported increase in RSV cases this year.
Pfizer announced Nov. 1 that its own candidate RSV vaccine wrapped up its phase 3 trial for efficacy early. Unlike GSK’s candidate vaccine, Pfizer’s vaccine targets pregnant women. The vaccine is designed to be administered early in the third trimester with the intent that the vaccine-induced antibodies be passed from the mother to her newborn.
Pfizer, in its Nov. 1 announcement, claimed that its bivalent RSV prefusion vaccine candidate RSVpreF, also known as PF-06928316, delivered “broadly positive” results — namely, a significant reduction in the rate of respiratory illness in newborns and their mothers.
Pfizer claimed 81.8% efficacy against severe cases of RSV for babies up to three months, and 69.4% efficacy after six months.
Pfizer’s MATISSE (MATernal Immunization Study for Safety and Efficacy) trial involved 7,400 pregnant women and their newborns, tracking the infants for one year following birth, and some for two years. It was conducted in 18 countries beginning in June 2020.
Pfizer’s vaccine trial did not deliver statistically significant results regarding the prevention of infant medical visits caused by RSV, including for non-severe cases.
Nevertheless, Pfizer said there are “no major safety concerns” with its product, adding:
“At the recommendation of the DMC [Data Monitoring Committee], and in consultation with the U.S. Food and Drug Administration (FDA), Pfizer has stopped enrollment in the study.
“Based on these positive results Pfizer plans to submit a Biologics License Application (BLA) to the FDA by the end of 2022 for the vaccine candidate followed by other regulatory authorities in the coming months.”
Pfizer’s phase 3 trial data has not yet been vetted by independent experts, and has not been peer-reviewed or published.
On March 2, 2022, Pfizer’s candidate vaccine received a Breakthrough Therapy Designation from the FDA, while previously, in November 2018, the FDA granted it Fast-Track status, according to the Pfizer release.
“Pfizer’s investigational RSV vaccine candidate builds on foundational basic science discoveries including those made at the National Institutes of Health (NIH),” the vaccine maker said in its press release.
The NIH research in question also was “key to the hugely successful COVID-19 vaccines,” according to ABC 7 Los Angeles.
Others looking to develop an RSV vaccine include Moderna and AstraZeneca and Sanofi, in a joint initiative. Moderna received fast-track designation from the FDA on Aug. 3, 2021, for its mRNA-1345 RSV vaccine for older adults, while AstraZeneca and Sanofi are developing a viral vector RSV vaccine by the name of “nirsevimab.”
An August 2021 article in The Defender predicted that RSV would represent the “new frontier for vaccine development,” as pharmaceutical companies would be “lured by the prospect of a large untapped global RSV vaccine market,” leading to a vaccine development “gold rush.”
Media tout benefits, ignore safety concerns
Online news portal Vox described the development of new RSV vaccines as “very, very good news” in a recent article.
Coupled with media coverage about “rising” RSV cases nationwide, it appears the stage is being set to create an emergency in the public consciousness, which could lead to EUAs being granted to the new vaccines and a rush to get the public vaccinated.
Blogger James Roguski, however, called into question the results of the Pfizer phase 3 trial, raising many safety concerns that are indicated in the company’s own data but were downplayed by Pfizer in its public proclamations. In a recent post, he wrote:
“In the Phase II study, researchers found that women who received RSVpreF vaccine containing aluminum hydroxide had a higher incidence of local reactions than those who received RSVpreF vaccine without aluminum hydroxide.
“It seems like 1 of the 117 infants in the placebo group suffered fetal death and 6 infants in the ‘vaccinated’ group are unaccounted for.”
Roguski also highlighted the many adverse events that were recorded for both infants and pregnant mothers who participated in the study, none of which were recorded for the placebo group.
For infants, some of these adverse events included acute respiratory failure, bronchiolitis, cardiac murmur, chordee (bent penis), conjunctival hemorrhage, hypoglycemia, jaundice, low birth weight, neonatal hypoxia, neonatal respiratory failure, seizure, sepsis, upper respiratory tract infection and vascular malformation.
Pregnant women, in turn, experienced adverse events including fetal growth restriction, fetal tachycardia, gestational diabetes, nonreassuring fetal heart rate pattern, premature labor, premature separation of placenta, vaginal hemorrhage and thrombocytopenia.
For some, these safety concerns are conjuring up memories of previously failed attempts to develop an RSV vaccine.
A vaccine tested in 1966 led to the deaths of two toddlers as a result of “enhanced disease symptoms,” while many infants “suffered worse symptoms than usual, and needed to be hospitalized.”
As previously reported by The Defender, RSV itself originated in monkeys housed in a Maryland facility where they were used to conduct polio vaccine research. Remarking on this and the connection to RSV vaccine development today, Brian Hooker, CHD’s chief scientific officer, told The Defender, “It is incredible that the vaccine industry can create a disease — RSV from the polio vaccine — and then create another vaccine to ‘prevent’ that disease. Talk about a business proposition!”
Michael Nevradakis, Ph.D., based in Athens, Greece, is a senior reporter for The Defender and part of the rotation of hosts for CHD.TV’s “Good Morning CHD.”
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
November 12, 2022
Posted by aletho |
Science and Pseudo-Science | California, Covid-19, COVID-19 Vaccine, RSV, United States |
Leave a comment
Dr. Paul Marik and his fellows in the FLCCC fight for patients’ rights. All have paid a heavy price for taking care of patients and telling the truth.
Part I in a series on Dr. Paul Marik—a magnificent doctor who was fired from his job and professorship because he successfully treated his COVID-19 patients with FDA-approved drugs and high-dose Vitamin C.
The following post is from The Courage to Face COVID-19: Preventing Hospitalization and Death While Battling the Bio-Pharmaceutical Complex, by John Leake and Peter A. McCullough. MD, MPH.
Dr. Paul Marik is to critical care medicine what Dr. McCullough is to cardio-renal medicine. The 65-year-old native of South Africa has published over 500 peer-reviewed papers and books, which made him the second most published critical care doctor in the history of medicine.

Dr. Paul Marik with Dr. Peter McCullough and John Leake at the Nurses Freedom Network Conference in Franklin, TN, June 12, 2022
Upon meeting Dr. Marik, one is overwhelmed by the impression of his vast physical stature. His gentle manners and elegant South African accent conjure accounts of 19th century British gentleman explorers. Since the early days of his career, he’d been keenly interested in discovering how to treat sepsis—the body’s extreme, life-threatening response to an infection. Well into the 21st century, sepsis continued to be a major cause of death. According to the CDC, approximately 1.7 million American adults fall ill with sepsis every year, of which approximately 270,000 die in hospital. Globally, the sepsis burden is estimated at 15 to 19 million cases annually, with a mortality rate approaching 60% in low-income countries.
Dr. Marik knew the literature on sepsis treatment. Several studies had indicated that large doses of IV-administered Vitamin C and Vitamin B1 (thiamine) showed some benefit. Other studies indicated that hydrocortisone showed promise. Dr. Marik reasoned that combining the three into a cocktail could amplify their benefit. As had often been observed in medicine, combining agents seems to affect multiple pathways, causing an overlapping and synergistic effect.
In 2016, he and his colleagues conducted a study in which they compared 47 sepsis patients who received the cocktail to a control group of 47 patients who received sepsis standard of care at the time. The mortality rate of the treatment group was 8.5% compared to 40.4% of the control group—a stunning difference. Skeptics claimed the study was too small and nonrandomized. Nevertheless, what became known as the “Marik Cocktail” was adopted by critical care units all over the world, which reported excellent results with the therapy.
When COVID-19 struck and Dr. Marik’s critical care unit at the Sentara Norfolk General Hospital received its first patients, he observed they were suffering from an inflammatory lung reaction, and he suspected this could be treated with a corticosteroid. He contacted four other critical care specialists—Professor Joseph Varon at United Memorial Medical Center in Houston (who, in the year 2020, would work 268 days straight treating COVID-19 patients in his ICU) Professor Gianfranco Umberto Meduri at the University of Tennessee Health Science Center in Memphis, Professor Jose Iglesias at the Hackensack Meridian School of Medicine in Seton Hall, New Jersey, and Professor Pierre Kory at the University of Wisconsin-Madison. As author Michael Capuzzo pointed out in his marvelous story about these doctors, it would be hard to imagine a more experienced and scholarly team of pulmonary critical care doctors.
Together they formed the Frontline COVID-19 Critical Care Consortium (FLCCC) and got to work on a protocol for saving hospitalized patients. They started their work by focusing on the extreme inflammation they were observing. Often called “cytokine storm” after the proteins produced by the immune system, this was an extreme and maladaptive immune response that had often been observed in other viral illnesses, including virulent influenza. It was this inflammation of the lungs, kidneys, and other organs that killed the patient, and not the virus itself. Thus, the key to treating the syndrome was reducing this inflammation.
Professor Meduri was a leading expert on corticosteroid therapy in critical illness. He conducted an exhaustive review of corticosteroid use against SARS-CoV-1, MERS, and H1N1 and found significant evidence that these agents had been lifesaving in their reduction of extreme inflammation. For decades the corticosteroid methylprednisolone had been the standard medication for suppressing cytokine storm. And yet, despite this glaring fact, every US federal health agency recommended against using corticosteroids against COVID-19 from the outset of the pandemic.
Unlike these agencies, the FLCCC concluded that their best bet for tackling the disease in hospitalized patients was a combination of Methylprednisolone and the antioxidant Ascorbic acid (Vitamin C). To these they added Thiamine (Vitamin B1) to optimize cellular oxygen utilization and energy consumption, and the anticoagulant Heparin to prevent and help in dissolving blood clots that appear with high frequency.
There is nothing experimental about these drugs. Methylprednisolone and heparin had long been FDA-approved for treating inflammation and blood clotting. Vitamin C and B1 were available over the counter, though in the hospital setting they were IV-administered in high doses. The FLCCC doctors began giving this “MATH Protocol” to ICU patients and tracked their progress for a case study. By the end of April, they had treated 100. Of these, 98 survived. The two who died were in their eighties and had other advanced chronic illnesses. None of the patients had long durations on ventilators, were ventilator dependent, and or had long hospital stays.
During this period, Dr. Pierre Kory was in daily communication with ICU doctors in his native New York City, where he’d worked in multiple hospitals. His colleagues reported that they turned the tide in the ICUs as soon as they started using methylprednisolone. Other ICU doctors in hard hit New Orleans reported the same. Kory and colleagues therefore sent letters to the White House, the CDC, and the NIH, presenting their real-world evidence of the corticosteroid’s efficacy—all to no avail.
Dr. Kory’s efforts were drawn to the attention of Wisconsin Senator Ron Johnson, who was chairman of the Senate Homeland Security Committee. Since his daughter had been born with a congenital heart defect—successfully corrected by an innovative operation—Senator Johnson had believed that if citizens were faced with a life-threatening condition for which there was no proven treatment, they should have the right to try drugs or operations that seem to offer some benefit, even if these had not yet passed the conventional FDA-approval process. The alternative was to do nothing and accept the high probability of death.
Critics of the right to try claim that unless procedures and medications are carefully regulated by the FDA, unscrupulous doctors will create false hope by offering them to desperate patients, even if there is little trial data to prove their efficacy. Senator Johnson did not find this argument persuasive and he introduced his federal right to try bill in 2017. A companion bill was introduced in the House, ultimately passed in both houses, and was signed into law by President Trump in 2018.
Upon Senator Johnson’s invitation, Professor Kory addressed the Senate Homeland Security Committee on May 6, 2020. Speaking via WebEx, Kory stated the credentials of the FLCCC doctors, and then explained the rationale for using their protocol. He then reported the success they and other doctors were having with it. This was excellent news, and a naive viewer would likely assume that it would be welcomed by the entire medical profession.
And yet, despite the FLCCC’s well-founded rationale for their therapy, broad consensus for the efficacy of its components in related conditions, and their success with it, they continued to get pushback from the CDC and NIH, which refused to change their advisory against using corticosteroids to treat COVID-19. On four occasions, the FLCCC tried to notify the White House of their favorable results, but they received no reply.
November 12, 2022
Posted by aletho |
Book Review, Full Spectrum Dominance, Science and Pseudo-Science, Timeless or most popular | Covid-19, Human rights |
Leave a comment
On Monday, October 24th a debate on vaccine safety took place in Parliament. Three MPs, Danny Kruger, Sir Christopher Chope and Andrew Bridgen, discussed a number of issues the mainstream media have not been reporting on. The health concerns raised appear to be receiving very little, if any, serious recognition by the Government. It was the safety of children and young adults that concerned me most in this debate and in this article I want to explore whether the medical profession is being as cautious and conscientious as it should be in the administration of medication, including but not limited to Covid vaccines, to children. How well are children and young adults being monitored following medical interventions?
A few days ago it was reported that dozens of children between the ages of five and 11 were given higher doses of the Covid vaccine “by mistake”. Solent NHS Trust operated the ‘pop-up’ vaccine clinic (see later) and one mother was told that “she shouldn’t expect anything significant” to happen to her daughter following the mistake but that any reaction to the jab “would last longer”. The Chief Medical Officer for the Trust said that this was an isolated occurrence.
In other news, the Indonesian Health Ministry said on Thursday, October 20th that it had found traces of three hazardous chemicals in children with acute kidney injury, two of which are present in Indian-manufactured syrups suspected to be linked to dozens of deaths in Gambia. According to the Ministry, at least 70 cases of children under the age of five years with acute kidney failure are being detected every month with a mortality rate of about 50%.
This type of news is always disturbing to hear, not only because innocent young lives are involved but also because these children had little, if any, choice in the administration of a treatment that might not even have been necessary. It seems all too easy to reach out to the medicine cabinet for just about any ailment, no matter how mild or trivial these days. Likewise, it seems too easy for parents to be made to believe that Covid vaccinations offered to their child are essential for their health and wellbeing.
Errors in paediatric doses are not in fact uncommon. Research shows that potential adverse drug events occur three times more frequently among paediatric patients than among adults. Some of these differences in error rates are due to:
- larger volumes of stock solution for adults;
- greater variability in weight and body surface area of children;
- differences in pharmacokinetics and pharmacodynamics;
- children’s kidneys, liver and immune systems are still developing;
- children not being able to communicate what they are feeling;
Monitoring of adverse events in children is also much more difficult than for adults and conducting and monitoring long term drug trials for children is even more problematic. The conclusion of a 2019 medical study was that: “Paediatric clinical trials designed to sufficiently investigate drug safety and efficacy to support approval are of relatively limited duration. Given the potential long-term exposure of patients to these drugs, the clinical community should consider whether new approaches are needed to better understand the safety of long-term use of these drugs.”
An example of a recent attempt to monitor the effect (and therefore safety) of Covid vaccines on children has been the reliance on testing for antibody production against the disease. A recent JAMA study suggests that these trials have been inadequate and inappropriate. It found that such antibody production provides children with little or no protection against infection. The main determinant is actually cellular immunity (i.e., T Cells). The study even found that having antibodies to Omicron increased the infection risk, which may help to explain the negative vaccine effectiveness seen in a number of studies where infection rates are higher in the vaccinated than the unvaccinated.
Whilst evidence of the adverse reactions and immediate harms of Covid vaccines on young people is building at an alarming rate, it is easy to overlook the possible unknown long term consequences. History has taught us that medical experts can fail to see harms in both pre-licensed and post-licensed pharmaceuticals and in non-licensed or non-prescription drugs for dangerously long periods. There are too many examples to list here, but in the early 1900s concern about smoking was considered alarmist. There was no definitive evidence that smoking was bad for you. By the 1930s, tobacco companies had an army of doctors ready to debunk you as a quack for even suggesting something as benign as a cigarette could give you cancer. By the 1960s, the evidence against smoking was more than damning. By then, the debate over smoking’s deadly impact had been raging around the world for more than a generation and medical experts were slowly reaching the same conclusion.
In July 1956, medical authorities in West Germany licensed a drug for sale without a prescription. Thalidomide had been developed as a sedative or tranquiliser, but people were soon taking it for a range of conditions, including pneumonia, colds and the flu, as well as to relieve nausea in early pregnancy. Six years later, more than 10,000 babies had been born with physical abnormalities caused by the drug. It wasn’t until 1962 that Thalidomide was banned in most countries in which it was sold – and this for a drug with such early and devastating side effects. In the U.K., the MHRA Yellow Card adverse event reporting system was introduced partly as a result of Thalidomide, but we know that average reporting rates are estimated to be around 10% of actual adverse events under this system.
Scandals are often associated with a failure to learn from history. In the early 50’s a Dr. Krugman wanted to create a vaccine for hepatitis. He deceptively coerced carers and parents into forcing 50 children from a home for developmentally challenged kids to be injected with the virus itself or by making them drink chocolate milk mixed with faeces from other infected children. Dr. Paul Offit, a paediatrician, said that “Krugman certainly did speed up the development of a hepatitis B vaccine but I don’t think you’re ever justified to inoculate a child with an infectious virus that might kill them”. In 1979 the Belmont Report was published in an effort to learn from this and provide a comprehensive guideline of basic ethical principles.
Augmenting the hoped for protections of the Belmont Report, a 2004 article described the main ways in which the risk of medication errors for children could be minimised. It said it is critical to have
- personnel trained in paediatrics to prescribe, prepare, dispense and administer medications;
- a quality review system in place to review drug use and medication errors, and;
- to implement computerised physician order entry with decision support and other tools in the next decade to improve pharmacologic therapy for paediatric patients.
It is concerning therefore, in relation to the above, that the ‘pop-up’ Covid vaccine clinics in the U.K. are often staffed by volunteers who may have had no prior medical, nursing or any type of clinical experience. The BMA paper on the recruitment of these Covid vaccination volunteers lists the minimal qualifications. The volunteer has to:
- be between the age of 18 and 69;
- have at least two or more A-levels or equivalent;
- be at low risk of COVID-19;
- be prepared to undergo a reference check.
How can we be sure that the Solent NHS Trust incident was an “isolated occurrence” and how can we be sure that nothing “significant” will happen to the children (estimated to have received three times the correct dose)?
Surely this cannot be right, 70 years on from the days of Krugman? Is it also acceptable for parents to have been pressured (in the case of Covid, through fear from Government, scientists and the media) into providing consent for a novel ‘vaccine’, without long term data, on behalf of their healthy offspring? This fear was instilled through overstating the risk of Covid to healthy children, misinforming the public that the vaccines prevented transmission and describing vaccine effectiveness in a misleading way by claiming up to 95% effectiveness (relative risk) instead of the actual or absolute reduction in risk which in the trial was less than 1% in adults and is now possibly less than nil for children (see above).
I try to put myself in the shoes of these children when, possibly some time later in their lives, they are told of their participation in the administration of a not yet fully licensed medication. Or not told. They were possibly too young to comprehend the personal risk and bodily infringement inflicted. Andrew Bridgen MP reported one study alone involving several thousand vaccinated children showing that one in 500 under five years of age who received a Pfizer Covid vaccine were hospitalised with a vaccine injury and one in 200 had symptoms ongoing for weeks or months afterwards.
Why has the Government, the medical profession and media not allowed the public to be informed that the Yellow Card reports, and those of the American equivalent, VAERS, show up more adverse Covid vaccine incidents in young people than all other known vaccinations combined? Around 6,000 doctors, scientists and professionals in more than 34 countries have declared an international medical crisis due to “diseases and death associated with the COVID-19 vaccines”. Their report highlights the large number of sudden deaths in previously healthy young people who were inoculated with these ‘vaccines’, and the high incidence of miscarriages and perinatal deaths which have not been investigated.
Danny Kruger MP said: “The MHRA is funded by the pharmaceutical companies that produce the drugs and vaccines that it regulates. There might be some universe in which that makes sense, but this is not it.”
In 1995, the comedienne Mrs Merton famously asked Debbie McGee (unfairly I thought): “So what attracted you to the millionaire Paul Daniels?” Similar could be asked of Government and others involved in the rollout of experimental mRNA Covid vaccinations: “So why were healthy children and young adults coerced into receiving unnecessary multiple Covid vaccinations from a $1.4 trillion global pharmaceutical industry?”
Dr. Mark Shaw is a retired dentist.
November 12, 2022
Posted by aletho |
Deception, Science and Pseudo-Science, Timeless or most popular, War Crimes | COVID-19 Vaccine, Human rights, UK |
Leave a comment

 Aletho News

