Flawed paper behind Covid-19 testing faces being retracted, after scientists expose its ten fatal problems
By Peter Andrews | RT | December 9, 2020
A publisher admitted it is urgently re-investigating research, following revelations that the PCR test it extols is defective, giving too many false-positives. The news comes as a new group plans a legal challenge over the checks.
Last week I reported on an astonishing review conducted by a group of senior scientists on a paper on which most Covid testing is based. It comprehensively debunked the science behind the Corman-Drosten paper, which described a protocol for using the polymerase chain reaction (PCR) technique to detect Covid, finding 10 fatal flaws, including major failings in the operating procedure and potential conflicts of interest among its authors.
The team behind the review demanded that Eurosurveillance, the journal that published the original research, retract it at once, as in their view it clearly failed to meet proper standards. This is of vital importance because the Corman-Drosten paper laid the path for mass PCR testing as the main source of data on the coronavirus. Almost all case numbers, infection rates and even deaths attributed to Covid are based on PCR tests (and all the attendant lockdowns and restrictions on people), and a huge amount of them use the method set out in the Corman-Drosten paper.
But now, the organisation Retraction Watch have reported that Eurosurveillance is considering retracting the paper. In a statement, Eurosurveillance said that they were “seeking further expert advice and discussing the current correspondence in detail. We will, according to our existing procedures, evaluate the claims and make a decision as soon as we have investigated in full.’’ So no retraction yet, but it would not be surprising if one came soon.
Call up Guinness World Records
One of the 10 fatal flaws in the original Corman-Drosten paper was that it was unclear whether it had ever been subjected to proper peer review – before, that is, the panel of experts took it upon themselves to do so. The paper had been submitted on January 22 and published the very next day. Peer review, when it takes place, is normally a long, drawn out process with plenty of back-and-forth, even when it is being rushed as much as possible. That it could be done in a single day beggars belief.
But that is what the authors are asking us to believe, as they are still claiming that their article was “peer-reviewed by two experts on whose recommendation the decision to publish was made.’’ Eurosurveillance may want to consider submitting this feat to Guinness World Records as the fastest peer review of all time – it may not be too late to get into the 2021 edition.
Taking the government to court
It is clear that the wars over PCR tests are hotting up, and the stakes couldn’t be higher. A new organisation in the UK, calling itself PCR Claims, has been set up to challenge in the courts the British government’s handling of PCR testing for Covid-19.
The organisation describes itself as a pro bono network of lawyers, life scientists, and business advisers led by Jo Rogers, a lawyer who runs Navistar Legal.
Rogers told RT.com: “The intention is to expose the controversy of the inappropriate use of PCR in the context of pillar 2 community testing and private sector lighthouse labs.
“PCR was not designed for mass testing because of the sensitivity and risk of contamination. There are serious flaws in many of the protocols employed, which were hurriedly put together, some without peer review. The operational false positive rate is unknown and therefore every positive test could be false, unless accompanied by clinical examination.”
As an example of errors with PCR, the group points to a recent case from Cambridge University. “Our first priority is to gather evidence of the harms from restrictions to life whose policies were driven by PCR test modelling and/or ‘case’ results,” Rogers said. “We believe the cases are a pseudo epidemic, as seen in other places around the world using PCR testing.
“Legal action is progressing and further instances will follow as we receive the evidence of harms. The gathering of that evidence is ongoing nationwide, as well as our raising awareness of errors and negligence.”
As someone who shares their deep concerns over these PCR tests, this is good news. At last, there is somewhere to go for expert legal counsel on the government’s persecution of free-born citizens. And thank heavens also for the stellar work of the entire peer review team for holding this bad science to account. If indeed it is retracted, it will be a major victory for those of us who can see through what Dr Mike Yeadon, one of the paper’s debunkers, rightly calls a “false positive pseudo-epidemic.”
Peter Andrews is an Irish science journalist and writer based in London. He has a background in the life sciences, and graduated from the University of Glasgow with a degree in genetics.
Canadian Health Ministry Exploring “Immunity Passports,” Vaccine “Tracking And Surveillance”

By Steve Watson | Summit News | December 9, 2020
The Health Minister of Ontario in Canada has stoked controversy by suggesting that people who do not take the coronavirus vaccine will face restrictions on where they can travel and spend time.
When asked by reporters about how the government intends to go about convincing people to get the vaccine, Health Minister Christine Elliott warned that those who refuse it will face difficulties reintegrating into society.
“That’s their choice, this is not going to be a mandatory campaign. It will be voluntary,” Elliot said, but adding that “There may be some restrictions that may be placed on people that don’t have vaccines for travel purposes, to be able to go to theatres and other places.”
When another reporter asked if the government would be introducing ‘immunity passports’, or proof of vaccination cards, Elliot said “Yes, because that’s going to be really important for people to have for travel purposes, perhaps for work purposes, for going to theatres or cinemas or any other places where people will be in closer physical contact.”
Following up on Elliot’s comments, The Toronto Sun spoke to her press secretary, who confirmed that the government is exploring several options for vaccine “tracking and surveillance.”
“This includes exploring developing tech-based solutions while also providing for alternative options to ensure equitable access to any potential ‘immunity passport,’” Alexandra Hilkene said.
Sun reporter Brian Lilley notes “That phrase will set off alarm bells and it should, not just for anti-vaxxers, but for anyone who is concerned about Charter rights and governments running roughshod over them.”
Ontario Chief Medical Officer of Health Dr. David Williams has also said that a COVID-19 vaccine may be required for “freedom to move around”.
“What we can do is to say sometimes for access, or ease, in getting into certain settings, if you don’t have vaccination then you’re not allowed into that setting without other protection materials,” Williams said.
The comments of these Canadian officials add to the litany of other government and travel industry figures in both the US, Britain and beyond who have suggested that ‘COVID passports’ are coming, in order for ‘life to get back to normal’
In an essay in The Wall Street Journal on Saturday, former Centers for Disease Control and Prevention director Tom Frieden noted that he expects the so called ‘immunity passports’ will come into widespread use despite any ethical, legal or operational challenges, and despite the fact that it hasn’t at all been determined whether the vaccine equates to immunity.
Everyone is already wearing a mask. They just don’t work.
By Jordan Schachtel | December 7, 2020
One of the most common pro-mask arguments I’ve heard over the course of the past year, both from “public health experts” and your average citizen, sounds similar to the following statement:
“If only everyone would just wear a mask, we would be able to crush the virus and end the pandemic.”
This line of reasoning is frequently espoused by lockdown governors and “public health experts.” You see, the problem isn’t them, it’s you, the citizen, we’re told. Wear a mask, peasant. You’re the problem! You’re the reason why the pandemic is still a problem in this country.
Deaths up? Why aren’t you wearing a mask. Cases up? Wear a mask. Hospitals crowded? The problem is that not enough people are wearing masks, they claim.
The idea that not enough Americans are wearing masks is detached from reality. And we have the data to prove it.
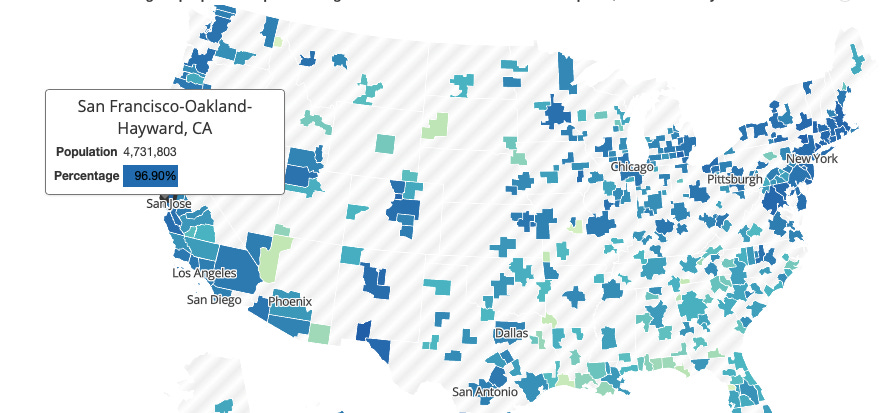
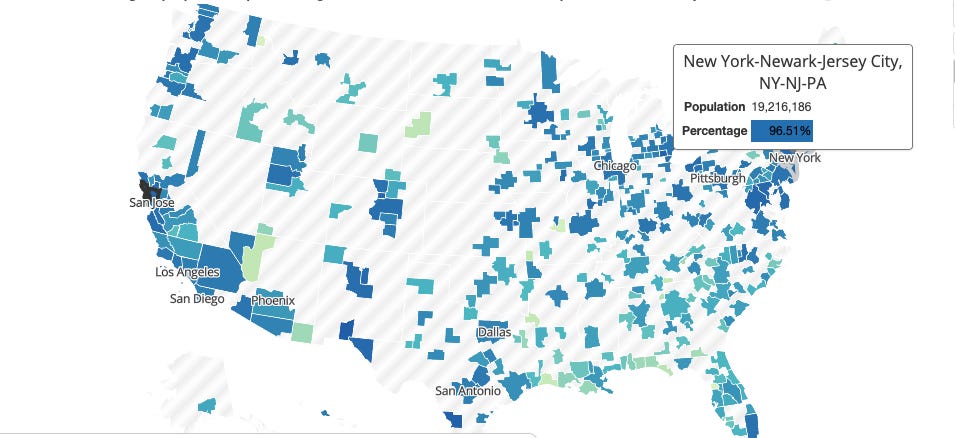
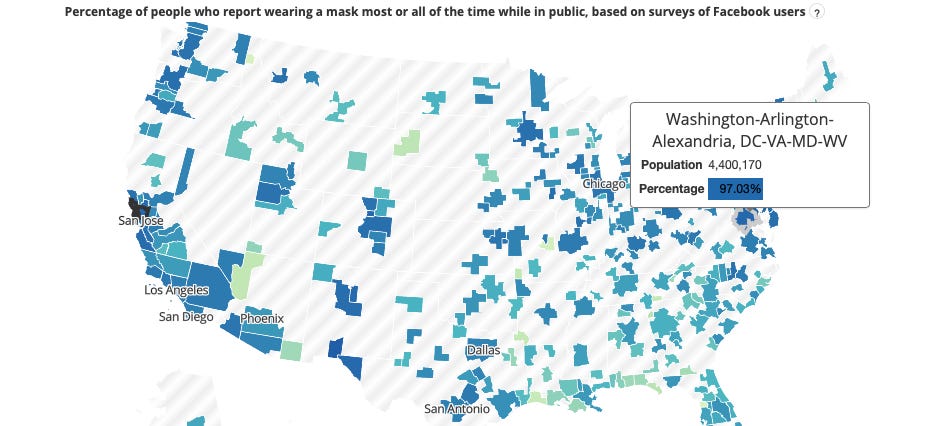
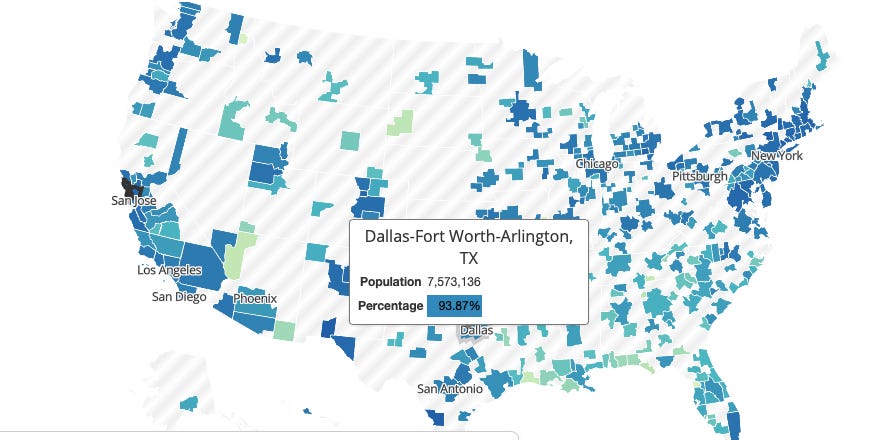
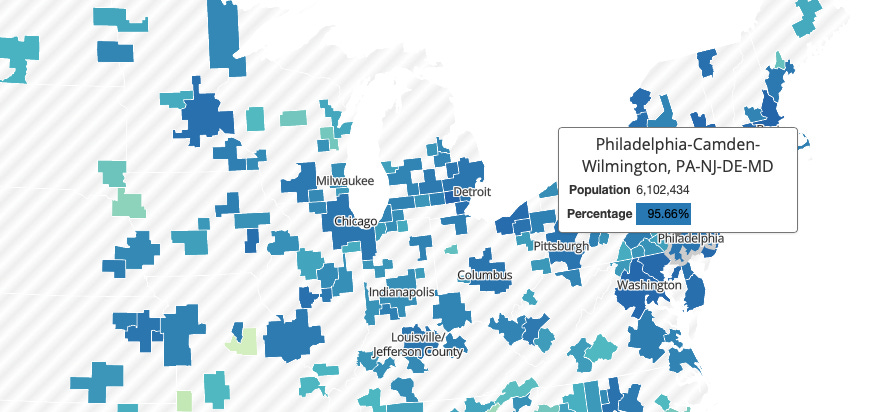
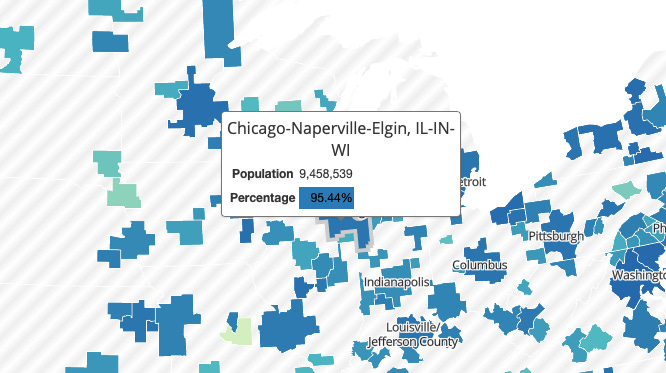
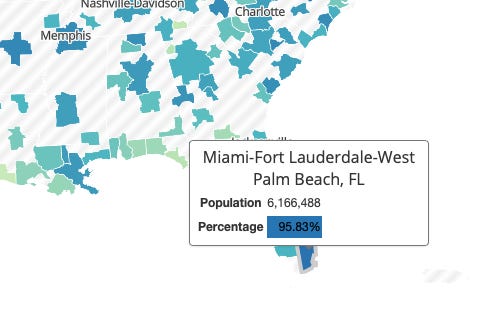
The Delphi group at Carnegie Mellon University has developed a very informative, consistently updated mask compliance tracker. It shows that the overwhelming majority of Americans across the nation are wearing masks. And in virtually every major population center in the United States, especially in areas where COVID-19 cases are rising, mask compliance levels are off the charts high, with most major metro areas registering well over 90 percent compliance.
Early on in the pandemic, when the “new science” told us that masks could stop the virus in its tracks (after the science of early 2020, espoused by the likes of Fauci and many others, rightly pointed to the reality that masks are useless outside of a controlled setting), the CDC and other “public health agencies” claimed that we could essentially eliminate transmission if a large percentage of the population adopted universal masking.
When lockdowns failed to “stop the spread,” masking up at over 80% was hyped as a way to “do more to reduce COVID-19 spread than a strict lockdown.”
“Universal masking at 80 [percent] adoption flattens the curve significantly more than maintaining a strict lockdown,” a much-hyped, highly publicized study, which was treated by many in the scientific community as the gospel, proclaimed.
“We will not only be able to flatten the curve, we will be able to significantly reduce the spread of the virus and return to life as normal sooner rather than later,” De Kai, a research scholar at Berkeley who helped develop the COVID-19 universal masking model, proclaimed.
With the help of the CMU mask compliance tracker, let’s take a look at the current COVID-19 hotspots in the United States and the level of mask compliance within these areas.
San Francisco metro area: 97% mask compliance
New York City metro area: 97% mask compliance
DC metro: 97%
Dallas-Fort Worth-Arlington: 94%
Philly area: 96%
Chicago: 95%
Miami-Ft Lauderdale: 96%
Seattle: 96%
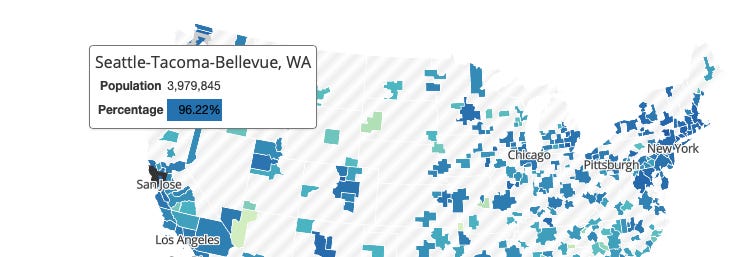
The data demonstrates very clearly that Americans have overwhelmingly exceeded the masking compliance percentages needed to supposedly “flatten the curve” and reduce transmission of the virus. The problem, of course, is that the models have not matched reality. Americans are wearing masks, but the hypothesis behind universal masking has not worked to stop the spread of COVID-19.
Americans have adopted the recommendations of the “public health experts,” but the “public health experts” have failed to follow the science, which now shows that masks are useless when it comes to stopping the spread of COVID-19. Now we’re left with an overwhelming majority of Americans wearing masks for no science-based reason whatsoever.
New Study Claims Vaccinated Children Appear To Be “Significantly Less Healthy” Than Unvaccinated
By Arjun Walia | Collective Evolution | December 4, 2020
A new study published in the International Journal of Environmental Research and Public Health has, according to the authors, discovered that vaccinated children require far more healthcare than unvaccinated children. At least that’s what they found from the group of children used to collect the data.
This type of study is interesting to see given the fact that studies comparing unvaccinated children to vaccinated children are lacking, there aren’t many of them. These studies are, as the authors state, “rarely conducted.”
None of the post licensure-vaccine safety studies have included comparisons to groups completely unexposed to vaccines.
The study concludes that “the unvaccinated children in this practice are not, overall, less healthy than the vaccinated and that indeed the vaccinated children appear to be significantly less healthy than the unvaccinated.
The data source for this study was all billing and medical records of Integrative Pediatrics, a private pediatric practice located in Portland, Oregon.
The study emphasizes the need for more research given the fact that, again, there is hardly any in this area. They concur with Mawson et al., 2017 , who reported: “Further research involving larger, independent samples is needed to verify and understand these unexpected findings in order to optimize the impact of vaccines on children’s health” and with Hooker and Miller 2020, who wrote: “Further study is necessary to understand the full spectrum of health effects associated with childhood vaccination.”
These studies mentioned above also had similar findings.
According to the authors,
Vaccines are widely regarded as safe and effective within the medical community and are an integral part of the current American medical system. While the benefits of vaccination have been estimated in numerous studies, negative and nonspecific impact of vaccines on human health have not been well studied. Most recently, it has been determined that variation exists in individual responses to vaccines, that differences exist in the safety profile of live and inactivated vaccines, and that simultaneous administration of live and inactivated vaccines may be associated with poor outcomes. Studies have not been published that report on the total outcomes from vaccinations, or the increase or decrease in total infections in vaccinated individuals.
This is important because, although vaccinations in some cases may protect against the target disease, what else might they be doing not only on the short term, but in the long term? It’s also important to point out that in other cases, like the HPV vaccine, there is no evidence that they do protect against the target disease.
Another great example comes from a study published in 2017 that examined the introduction of the diphtheria-tetanus-pertussis vaccine (DTP) in an urban community in Guinea-Bissau in the early 1980s. They found that the DTP vaccine was associated with 5-fold higher mortality than being unvaccinated. The authors state the following:
All currently available evidence suggests that DTP vaccine may kill more children from other causes than it saves from diphtheria, tetanus or pertussis. Though (this) vaccine protects children against the target disease it may simultaneously increase susceptibility to unrelated infections.
This new study points out,
Pre-licensure clinical trials for vaccines cannot detect long-term outcomes since safety review periods following administration are typically 42 days or less. Long-term vaccine safety science relies on post-market surveillance studies using databases such as the US Food and Drug Administration (FDA) and Centers for Disease Control and Prevention (CDC’s) Vaccine Adverse Events Reporting System (VAERS) and the Vaccine Safety Datalink. VAERS is a passive reporting system in which, according to Ross 2011, “fewer than 1% of vaccine adverse events are reported.” The Vaccine Safety Datalink (VSD) can, in principle, according to the Institute of Medicine (IOM, 2013), be used to compare outcomes of vaccines and unvaccinated children. Based on the IOM’s recommendation, in 2016, the CDC published a white paper (CDC, 2016; Glanz et al., 2016) on studying the safety of their recommended pediatric vaccine schedule. Unfortunately, to date, no studies have been published comparing a diversity of outcomes of vaccinated and unvaccinated children.
Below is one of many interesting graphs from the study. The orange line represents the vaccinated children, and the blue one represents the unvaccinated.
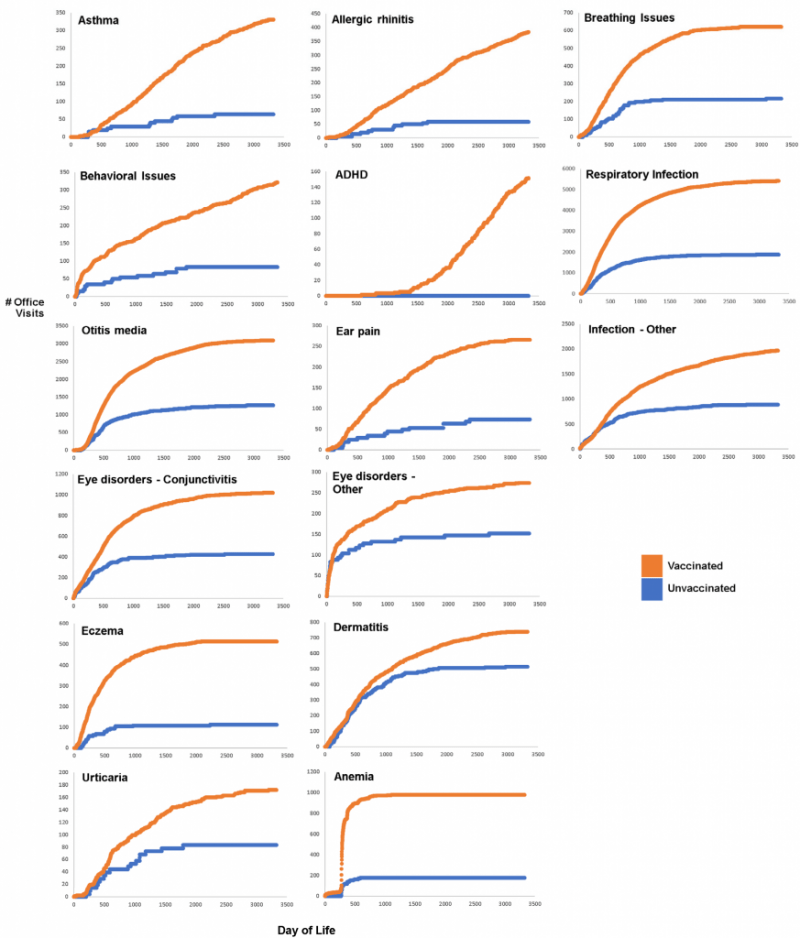
For methods used, limitations, and more please refer to the study.
The parents that I work with in New York, that I see around the country are very concerned that their rights are being taken away, that their knowledge about the science is being pushed away by an agenda that only says, unvaccinated children are a problem.
No study has every been done in this country, appropriately, to address the health outcomes of children who are vaccinated versus the children who are unvaccinated. I have been seeing families in my practice for over 20 years, that have opted out of vaccination, they are the healthiest children I’ve ever seen. – Dr. Lawrence Palevsky, a NY licensed paediatrician
Why This Is Important: Given the fact that the National Childhood Vaccine Injury Act (NCVIA) has paid out approximately $4 billion dollars to families of vaccine injured children, there are clearly, in my opinion, some valid points here, especially against compulsory vaccinations. Again, as mentioned above, VAERS only accounts for an estimated 1 percent of vaccine injuries, this one percent is what is recorded.
A 2010 HHS pilot study by the Federal Agency for Health Care Research (AHCR) found that 1 in every 39 vaccines causes injury, a shocking comparison to the claims from the CDC of 1 in every million.
Take the MMR vaccine for example, if you search on VAERS, as of 2/5/19, the cumulative raw count of adverse events from measles, mumps, and rubella vaccines alone was: 93,929 adverse events, 1,810 disabilities, 6,902 hospitalizations, and 463 deaths. Again, don’t forget about that 1% figure cited in the study.
There are a number of legitimate concerns about vaccine safety that would require quite a long and very in-depth article, but I just wanted to let the reader know here briefly. Aluminum for example, is another concern I’ve written quite a lot about.
These are a few reasons as to why vaccine hesitancy is at an all time high, even among many physicians and scientists. This has actually been observed for a while. For example, one study published in the journal EbioMedicine in 2013 outlines this point, stating in the introduction:
Over the past two decades several vaccine controversies have emerged in various countries, including France, inducing worries about severe adverse effects and eroding confidence in health authorities, experts and science. These two dimensions are at the core of vaccine hesitancy (VH) observed in the general population. VH is defined as delay in acceptance of vaccination, or refusal, or even acceptance with doubts about its safety and benefits, with all these behaviours and attitudes varying according to context , vaccine and personal profile, despite the availability of vaccine services VH presents a challenge to physicians who must address their patients’ concerns about vaccines and ensure satisfactory vaccination coverage.
At a 2019 conference on vaccines put on by the World Health Organization this fact was emphasized by Professor Heidi Larson, a Professor of Anthropology and the Risk and Decision Scientist Director at the Vaccine Confidence Project. She is referenced, as you can see, by the authors in the study above. At the conference, she emphasized that safety concerns among people and health professionals seem to be the biggest issue regarding vaccine hesitancy.
She also stated,
The other thing that’s a trend, and an issue, is not just confidence in providers but confidence of health care providers, we have a very wobbly health professional frontline that is starting to question vaccines and the safety of vaccines. That’s a huge problem, because to this day any study I’ve seen… still, the most trusted person on any study I’ve seen globally is the health care provider…
Is there not enough information here alone to warrant informed consent? I have a hard time understanding how someone who would take the new COVID-19 vaccine, for example, would be worried about me contracting the virus if they are protected?
Why have we given governments the ability to mandate such actions? Why have we given them so much power to dictate what we do and how we want to live? Is this really how we want to live, is this really the kind of world we want to create?
A Deeper Discussion. What Do We Do About The Increasing Vaccine Pressure?
So many are concerned about mandatory vaccination. Further, many are starting to see that mandated vaccines may not be the future, but that services and options will be denied unless you can prove you have been vaccinated. Is it still the time to point the blame? Or is there a radical new approach we must take? A shift in our worldview, re-examining who we think we are, why we are here and what world we want to create is where we will begin to find the answers we are looking for. Has the dualistic fight the enemy method worked in the past? Are we not still here regardless of having used this method in the past? Maybe it’s time for a new conversation, one that looks at ourselves in a whole new light. This perhaps is how we will solve our ongoing challenges at their core.
Below is a deeper discussion about it from CE Founder Joe Martino. You can follow me, Arjun, here on Instagram.
Ex-Pfizer Exec Demands EU Halt COVID-19 Vaccine Studies Over ‘Indefinite Infertility’ And Other Health Concerns
By Tyler Durden – Zero Hedge – 12/06/2020
Former Pfizer vice president and scientific director Dr. Michael Yeadon and German lung specialist and parliamentarian Dr. Wolfgang Wodarg have filed an urgent application with the European Medicine Agency calling for the immediate suspension of all SARS-CoV-2 vaccine studies – particularly the BioNtech/Pfizer study on BNT162b (EudraCT number 2020-002641-42).

Yeadon and Wodarg say the studies should be halted until a design study is available which addresses a host of serious safety concerns expressed by a growing body of renowned scientists who are skeptical of how quickly the vaccines are being developed, according to Germany’s 2020 News.
On the one hand, the petitioners demand that, due to the known lack of accuracy of the PCR test in a serious study, a so-called Sanger sequencing must be used. This is the only way to make reliable statements on the effectiveness of a vaccine against Covid-19. On the basis of the many different PCR tests of highly varying quality, neither the risk of disease nor a possible vaccine benefit can be determined with the necessary certainty, which is why testing the vaccine on humans is unethical per se. –2020 News
The pair also point to concerns raised in previous studies involving other coronaviruses – including (via 2020 News):
- The formation of so-called “non-neutralizing antibodies” can lead to an exaggerated immune reaction, especially when the test person is confronted with the real, “wild” virus after vaccination. This so-called antibody-dependent amplification, ADE, has long been known from experiments with corona vaccines in cats, for example. In the course of these studies all cats that initially tolerated the vaccination well died after catching the wild virus.
- The vaccinations are expected to produce antibodies against spike proteins of SARS-CoV-2. However, spike proteins also contain syncytin-homologous proteins, which are essential for the formation of the placenta in mammals such as humans. It must be absolutely ruled out that a vaccine against SARS-CoV-2 could trigger an immune reaction against syncytin-1, as otherwise infertility of indefinite duration could result in vaccinated women.
- The mRNA vaccines from BioNTech/Pfizer contain polyethylene glycol (PEG). 70% of people develop antibodies against this substance – this means that many people can develop allergic, potentially fatal reactions to the vaccination.
- The much too short duration of the study does not allow a realistic estimation of the late effects. As in the narcolepsy cases after the swine flu vaccination, millions of healthy people would be exposed to an unacceptable risk if an emergency approval were to be granted and the possibility of observing the late effects of the vaccination were to follow. Nevertheless, BioNTech/Pfizer apparently submitted an application for emergency approval on December 1, 2020.
Wodarg Yeadon EMA Petition Pfizer Trial FINAL 01DEC2020 en Unsigned With Exhibits
Dr. Yeadon made headlines last month when he said “There is no science to suggest a second wave should happen,” and that false positive results from inherently flawed COVID-19 tests are being used to ‘manufacture’ a second wave.
As Ralph Lopez write at HubPages, Yeadon warns that half or even “almost all” of tests for COVID are false positives. Dr. Yeadon also argues that the threshold for herd immunity may be much lower than previously thought, and may have been reached in many countries already.
In an interview last month (see below) Dr. Yeadon was asked:
“we are basing a government policy, an economic policy, a civil liberties policy, in terms of limiting people to six people in a meeting… all based on, what may well be, completely fake data on this coronavirus?”
Dr. Yeadon answered with a simple “yes.”
He then lamented the lives lost as a result of lockdown policies, and of the “savable” countless lives which will be further lost, from important surgeries and other healthcare deferred, should lockdowns be reimposed.
Watch the full discussion below:
Rich People & Journalists Made Exempt From Having to Enter COVID Quarantine
“High value business travellers” won’t have to self-isolate
By Paul Joseph Watson | Summit News | December 3, 2020
Journalists and rich people defined as “high value business travellers” will be made exempt from having to enter a 2 week COVID quarantine when they return to the UK under new rules announced by the government.
“From 4am on Saturday, people in a number of categories will no longer have to self-isolate upon returning to England, even if they are travelling from a country not on the travel corridors list,” reports Sky News.
Those categories include journalists, “high value business travellers,” performing arts professionals and wealthy sports stars.
Under current rules, anyone returning from a country not on the UK’s “travel corridor” list has to self-isolate at home for 14 days or face escalating fines.
Public Health England said the new measures will not raise the risk of domestic transmission of coronavirus.
The rule change is being pitched as a way to help boost the economy, but many responded by framing it as a classic example of elitist privilege.
“We are being governed by absolute fools, clowns and charlatans. If I’m rich enough to afford Business Class I’m immune to Covid?” asked one Twitter user.
“Ah! One rule for “us” and another for all the “little people”. Shrewd move just when trust and social cohesion is needed,” remarked another.
“What a load of rubbish. You mean those well off don’t need to follow “quarantine measures,” said another.
“There will be some big businesses that are able to take advantage of it,” said Paul Charles, chief executive of travel consultancy The PC Agency, underscoring once again how the rules favor large transnational corporations while small businesses continue to go bust.
Featured Video

New positive ivermectin evidence
or go to
Aletho News Archives – Video-Images
From the Archives
Fanatical Followers of the Covid Regime: A Jim Jones-Style Cult?
By Professor Roger Watson and Dr. Niall McCrae | The Daily Sceptic | November 15, 2021
As scholars at leading British universities over recent decades, we witnessed the replacement of critical thinking and debate by narrative: facts are discrimination and scientific method is imperialism; truth, instead, is derived from ‘progressive’ values. This educational trend may be a major contributory factor to the ease in which society has been inculcated to the Covid ‘new normal’ of masking, testing, and repeated doses of vaccines for a disease of similar risk to severe influenza.
One doesn’t need much critical reasoning to observe the flawed logic of some vaccination enthusiasts, such as people who respond to experiencing any side effects, however debilitating, by saying “at least I know it’s working”, or, after contracting the disease despite their promised inoculation (over 90% effective, according to initial drug company claims), “I’d have been worse off without the jab.” … continue
Blog Roll
 Aletho News
- EU Council Advances Chat Control 2.0 Scanning Proposal
- Ex-Greek MEP files complaint against Israeli spyware firm over alleged Pegasus surveillance
- Troubling ideas throughout the Torah, Talmud, Mishneh Torah and Tanya
- ‘Grave, alarming’: Iran mission on Trump’s UNGA ‘annihilation’ threats
- Najaf airport to reopen to Iranian flights within 24 hours: Ambassador
- From ‘How Will This End For Iran’ to ‘When America Walks Away’: A tale of two Economist covers
- Tehran blasts ‘baseless’ speculation linking Iran to alleged bomb plot at UK air base
- The Rise And… Rise Of ‘Color Revolutions’
- The Coming GOP Bloodbath?
- Arctic Scare Stories Melt Away
- If Americans Knew
- Netanyahu Asked UAE Leader to Deny Report on Oct. 7 Warning in Secret Visit, Sources Say
- CNN Chief Int’l Correspondent Clarissa Ward on Journalists in Gaza
- Democratic Party Consultants Surround Troy Jackson with Pro-Israel Donors
- Christian Leader Responds To Netanyahu’s Claims Regarding Palestinian Christians
- In Gaza, ‘Whoever Survives the Bombing Won’t Survive the Rubble’
- Israel kills more Palestinians, amid push to resettle Gaza – Daily Update
- Israel forces Gazans to live in constant peril – Daily Update
- Deconstructing Netanyahu’s pants-on-fire UN rant – Daily Update
- Trump betrayed voters with his campaign lies and prioritized a foreign country once he took office
- Netanyahu calls Israel’s war in Gaza ‘opposite of genocide’ in UN speech to near-empty hall
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

