South Carolina Legislation Looks To BAN Mandatory Vaccines
By Steve Watson | Summit News | January 6, 2021
Lawmakers in South Carolina have pre-filed a bill proposing a ban on mandatory coronavirus vaccines.
WCNC News reports that four state reps. have proposed the legislation to ensure that people may opt out of vaccination and not be discriminated against for doing so.
The proposal states that those refusing the vaccine would not face “adverse employment action” or any form of societal restrictions for doing so.
The legislation will also state that vaccines “may be provided only to those individuals who agree to vaccination.”
Currently in the state it is legal for employers to mandate vaccinations. This legislation would overturn that.
The proposed bill, which has been referred to the Committee on Medical, Military, Public and Municipal Affairs, is being sponsored by one Democratic representative, and three Republicans. They are Reps. Steven Long, R-Spartanburg, Leola Robinson, D-Greenville, Mike Burns, R-Greenville, and Sandy McGarry, R-Lancaster.
Rep. Burns told reporters “We want people to be able to go to their jobs, go to schools, go about their business, and not be mandated to do something that they feel is not in the best interest health-wise for themselves.”
“There should be no negative consequences for those opting out of the vaccine,” Rep. Burns added.
Representative Stephen Long said that the legislation was proposed following concerns from multiple constituents that “vaccine cards” could be introduced, effectively segregating society.
“Taking a vaccine should be a personal, private choice, and requiring ‘vaccine cards’ to board planes, attend school, etc is a very dangerous idea,” Rep. Long urged.
“I encourage everyone to speak with a physician about the benefits and risks of taking a vaccine, but it should never be mandatory,” Long added.
The proposal could progress through to committee next week, according to reports.
There has been much hype around potential ‘COVID passports’, especially concerning the fact that employers are currently allowed to mandate vaccination in many states.
Last week, Dr. Anthony Fauci, director of the National Institute of Allergy and Infectious Diseases stated that mandatory vaccinations are still ‘on the table’, and that he is “sure” that institutions such as hospitals and schools will mandate all who work there to be vaccinated.
32-Year-Old Mexican Doctor Suffers Seizures and is Paralyzed After Receiving the Pfizer Experimental Vaccine

Dr. Karla Cecilia Pérez Osorio (right)
By Brian Shilhavy | Health Impact News | January 5, 2021
The Mexican Press is reporting that a 32-year-old female doctor in Coahuila has suffered seizures and become paralyzed after receiving the Pfizer experimental COVID mRNA vaccine on December 30, 2020.
Dr. Karla Cecilia Pérez Osorio reportedly was working as an internist at the General Hospital of Zone No. 7, in the municipality of Monclova. She was subsequently transferred to the High Specialty Medical Unit No. 25 of the IMSS, in Monterrey, Nuevo León.
She was reportedly evaluated by a neurologist and diagnosed with transverse myelitis, a known side effect of vaccines, and specifically of the COVID experimental mRNA vaccines as this injury was observed in some of the vaccine trials of the various COVID19 experimental trials being conducted around the world.
According to the Mayo Clinic, transverse myelitis:
“can cause pain, muscle weakness, paralysis, sensory problems, or bladder and bowel dysfunction… Other conditions, such as a stroke of the spinal cord, are often confused with transverse myelitis.”
Medical authorities in Mexico are downplaying the adverse reaction as “mild,” but relatives reported yesterday (January 4, 2021) that although she is conscious, she has difficulties speaking and moving her legs and arms.
Her husband, Ángel Palestino Gallardo, and her cousin, Carolina Rivas Gallardo, confirmed that she had tingling in her lips and extremities just after receiving the experimental vaccine, so they gave her medication and she returned to work. But 20 minutes later she experienced paralysis of her arms and legs and suffered several seizures until she was unconscious.
This incident follows a report out of Portugal that a “perfectly healthy” 41-year-old Pediatric Assistant and mother of 2 died suddenly after receiving the experimental Pfizer COVID vaccine. See:
In the U.S., there appears to be a public cover-up in place to try and conceal these injuries and deaths, as the CDC received a lot of negative reactions to their first report following the FDA emergency use authorization (EUA) for the Pfizer experimental vaccine.
The CDC’s own report showed that in the first week alone in the U.S. 3150 injuries occurred, serious enough to prevent the healthcare workers from performing their jobs and performing their normal activities, requiring medical treatment. See:
This report was provided during the Advisory Committee on Immunization Practices (ACIP) meeting on December 22, 2020, and no further reports or meetings have been published since then.
One has to wonder why?
It doesn’t help when a nurse in Tennessee, Tiffany Dover, passes out on live camera just after receiving the Pfizer experimental COVID vaccine, and then disappears, leading the hospital to fake a video of her supposedly appearing alive, when Internet sleuths uncovered records of her death. See:
Is the Tennessee Nurse Who Passed Out on Live Camera After the COVID Vaccine Still Alive?
These deaths and injuries to medical personnel being reported so far are primarily occurring in young, child-bearing ages of female hospital staff.
See also:
Doctors Around the World Issue Dire WARNING: DO NOT GET THE COVID VACCINE!!
Trouble getting subscription content? How to Beat Internet Censorship and Create Your Own Newsfeed

Health Impact News has been labeled “Fake News” by Corporate Media and Big Tech allies such as Facebook and Twitter even when we report government-verified statistics on vaccine injuries and deaths
By Brian Shilhavy | Health Impact News
Back in January of this year (2020) we reported about Event 201, a pandemic simulation which was hosted by the Johns Hopkins Center for Health Security in partnership with the World Economic Forum and the Bill and Melinda Gates Foundation.
This event took place about 6 weeks BEFORE the first cases of COVID-19 were reported in Wuhan China. See:
As I have previously written, almost everything that was predicted at this pandemic simulation event has now occurred, except one: an Internet blackout.
The most likely reason that an Internet blackout has not occurred yet, is because the American public, and indeed the world population, was very compliant and voluntarily locked themselves down in their own homes – something that has never before happened.
With a compliant public, an Internet blackout would have done more harm than good, as the bandwidth on the Internet was pushed to its limits with everyone suddenly working from home via the Internet, and entertainment streaming services seeing a record high demand as people voluntarily complied and stayed home.
Shutting off the Internet would have been counterproductive, as it would have made people angry and quite possibly led them out their homes back on to the streets to start protesting sooner.
As a result, more and more people were able to research what was really going on, and find alternative accounts of the news different from what was being spoon fed to them through the corporate media and television networks.
This has increased the corporate news organizations and their Big Tech alliances with companies such as Facebook, Twitter, and Google to increase their efforts to censor dissenting voices, such as what we publish here at Health Impact News.
A group funded by the Corporate Media giants called “Newsguard” is at the forefront in determining what websites are publishing information contrary to what they want the public to hear, and they have published a list here (Health Impact News is on the list, of course): Coronavirus Misinformation Tracking Center
I have previously exposed this group called “Newsguard” by publishing my own correspondence with them. See:
Self-Appointed Internet Police Declare MedicalKidnap.com and DOJ Vaccine Court Reports Fake News
As a result, many of our articles are now censored and not allowed on Facebook, Twitter, Google (who owns YouTube) and Pinterest (Pinterest has banned us completely). In addition, emails from the domains of our news sites, like healthimpactnews.com, are also being suppressed, and many of the larger Big Tech “free” emails like hotmail.com and yahoo.com no longer allow us to email our newsletters or respond to inquiries.
So how do you beat this Internet censorship?
First, stop using their free email services, including the popular Gmail. Everything you communicate via Gmail is owned by Google, and they index all your emails on their servers. It seems they are now marking our newsletters as “SPAM” and not delivering them into inboxes.
Two free email services that value privacy are located outside of the U.S. but available to people residing within the U.S., and they are Protonmail (Switzerland), and Tutanota (Germany). So unless you have your own private email service on your own email server, it is best to use a service like this so you can continue receiving emails and newsletters such as what we publish here at HealthImpactNews.com.

Universal icon used for RSS feeds
However, there is a way to bypass email completely, and be able to instantaneously get all the news you want from all of your favorite websites and bypass censorship efforts by using an older technology that still exists today: RSS feeds.
RSS stands for Really Simple Syndication (or sometimes Rich Site Summary.) It was developed back in the 1990s during the infancy of the Internet, and was originally called RDF (Resource Description Framework).
Almost all websites publishing content still use this technology today by using an XML file format that is included with each new article published, that can then be retrieved by an RSS feed reader as soon as that content is published, which bypasses third parties such as email and social media postings.
All of the Health Impact News websites have an RSS icon that one can click on to get the XML file URL that one can then add to any standard RSS feed reader. [Aletho News’ RSS icon is at the top of the blogroll] In addition, one can just type: /feed/ at the end of the URL for any of our websites and get the same link to our XML file.
So it would look like this: https://healthimpactnews.com/feed/
This should work for most websites that have an XML file. For those sites that do not have an RSS icon, or do not provide a an XML feed by simply appending /feed/ to the end of the homepage URL, you can usually right click with your mouse and choose to look at the page “source”, and then search (usually CTR “F” in most browsers) for “RSS” to find the link you need to use to collect the XML file that you can then add to your RSS Feed Reader.
There are many RSS Feed Readers to choose from, including apps for Apple and Android. Most of them will operate basically the same, so just search for the more popular ones.
As Editor of Health Impact News, my entire news feed these days is in my RSS Feed Reader. I use the desktop version of Mozilla’s Thunderbird (free), which is mainly known as an email client, but has powerful features for listing RSS feeds that can be quickly used to look at new articles from as many sources as you want to add.
And it doesn’t have to just be sites you like. You can include corporate news sites also, if you want to stay on top of what they are publishing as well. Here is how my news feed in Thunderbird looks:

Click to enlarge
My list of news feeds lets me know if there are new articles I have not yet checked, and how many I have not yet read.
Once you locate a website’s RSS feed URL, it is easy to add it to your own custom news feed in basically a 4-step process:
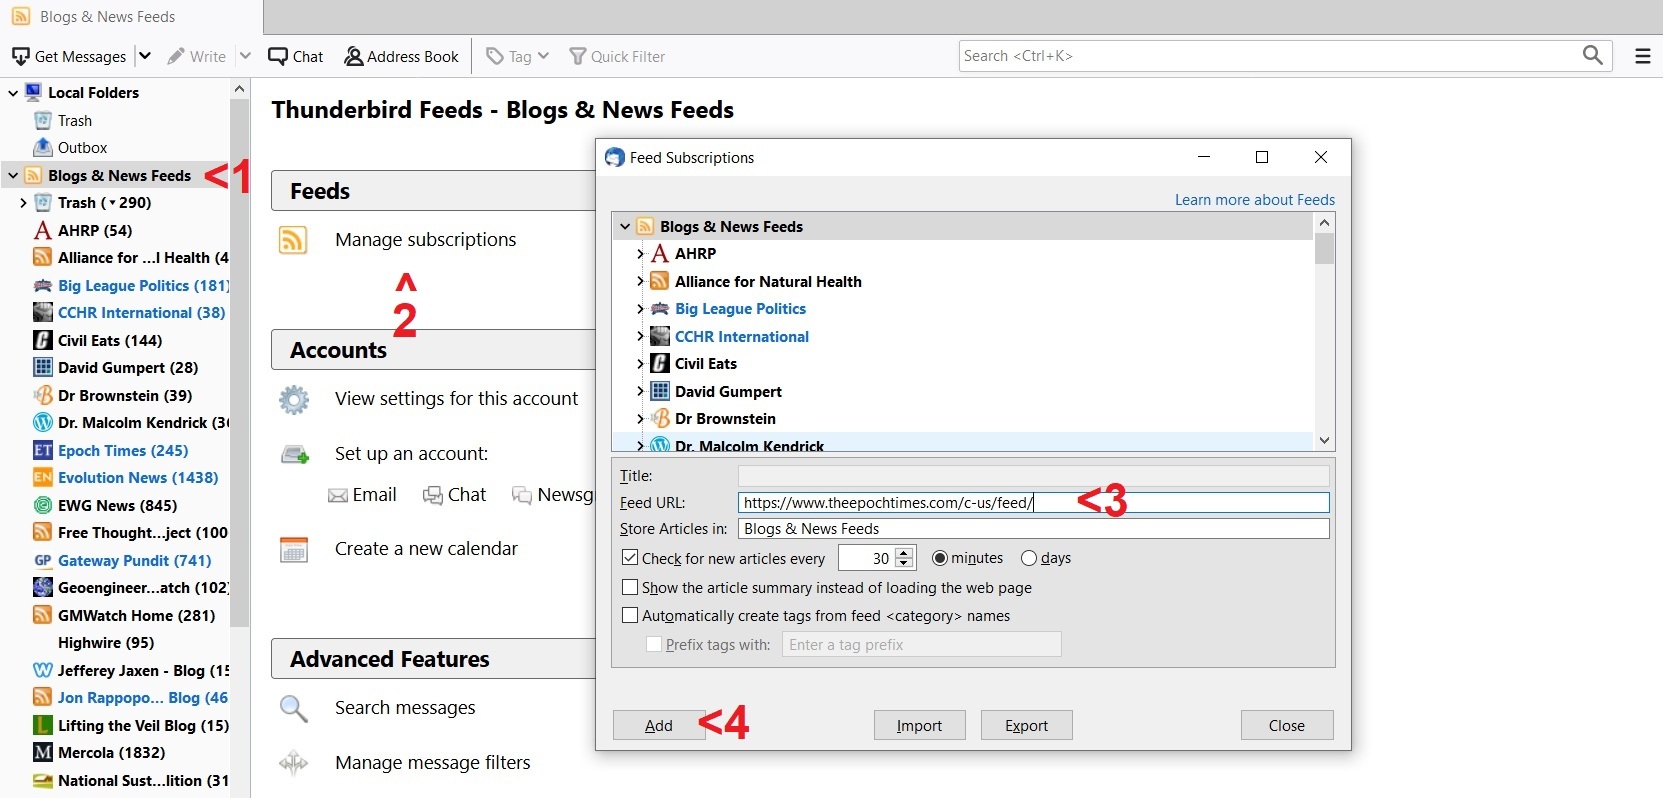
Click to enlarge
Once your news feed is collecting your own custom list of articles for a while, you can also now take advantage of your own custom search engine by searching your news feed!
This is increasingly more important these days as Google owns Internet searches, and even if you use a more private search engine that does not track your searches (recommended) such as duckduckgo.com, these sites are still using data compiled by Google, and Google now filters their search results so that only the relevant results they believe you should have access to shows up in their searches.
To understand this censorship Google is dominating in, read what they did to one of the oldest Alternative Health websites on the Internet, Mercola.com :
Google and Wikipedia Team Together To Suppress Alternative Health Information
By using an RSS Feed Reader, YOU have the freedom to beat censorship by grabbing new articles as they are published without first going through Social Media or email where they can be censored, and you get to develop your own collection of data over time that can be searched.
Which websites should you add to your news feed? That is entirely up to you, but the list we linked to above from Newsguard that lists websites they claim are publishing “misinformation” about the coronavirus that they are so desperately trying to censor, might be a good place to start!
Knowledge is powerful, and ignorance is dangerous, especially in these dark days where those in power calling the shots want to take away your freedoms and keep you in the dark, so that they can better control you.
UPDATE 10/28/20:
I am going to update this article and publish my own current newsfeed, with the list of RSS links.
Please note this is a constant developing newsfeed, and the presence of a publication in my newsfeed does NOT mean I endorse that publication.
As an editor, I want to be informed about ALL sides of an issue, even those I do not agree with, or maybe only partially agree with, etc. So you will see some “left-leaning,” some “right-leaning,” and some “libertarian-leaning” sources, along with some that do not fit any particular category and just practice good journalism.
Many of these sources have been banned by Big Tech in places like Facebook, Twitter, and YouTube.
There are not many corporate sites in my newsfeed, because you can get all of those in one place: https://news.google.com/
If you keep Google News open in a tab in your browser and refresh throughout the day, you see exactly what the corporate media’s main message is that day, which is primarily the Liberal Left, with a few Fox News stories thrown in from time to time to make them look “balanced.”
I have found over the past couple of years that Google particularly likes the Washington Post, now owned by their fellow Technocrat, Jeff Bezos, founder of Amazon.com, and who today is rumored to be interested in buying CNN.
With that said, here is the list of RSS feeds currently in my own, custom newsfeed (in alphabetical order) that can be loaded into any RSS feed reader where you will get their articles or videos into your RSS feeder almost as soon as they are published.
Last Update: 11/29/20
Activist Post – https://feeds.feedburner.com/ActivistPost
AHRP – http://ahrp.org/feed/
Alliance for Natural Health – https://feeds.feedburner.com/TheAllianceForNaturalHealthPulseOfNaturalHealth
Amazing Polly – https://www.bitchute.com/feeds/rss/channel/99freemind/
Behind The News Network – https://behind-the-news.com/feed/
Ben Swann – https://www.youtube.com/feeds/videos.xml?channel_id=UC1h3bqESVdqkwm123Ce4ZmA
Big League Politics – https://bigleaguepolitics.com/feed/
CCHR International – https://www.cchrint.org/feed/
Children’s Health Defense – https://childrenshealthdefense.org/feed/
Civil Eats – http://feeds.feedburner.com/civileats/
Conscious Resistance Network – https://theconsciousresistance.com/feed/
The Corbett Report – http://feeds.feedburner.com/CorbettReportRSS
Coreysdigs.com – https://www.coreysdigs.com/feed
David Icke – https://davidicke.com/feed
Dr Brownstein – https://www.drbrownstein.com/feed/ (Currently inactive due to FTC censorship)
Dr. Malcolm Kendrick – https://drmalcolmkendrick.org/feed/
Evolution News – http://www.evolutionnews.org/atom.xml
EWG News – http://www.ewg.org/rss.xml
FiercePharma – https://www.fiercepharma.com/rss/xml
Free Thought Project – https://thefreethoughtproject.com/feed/
From the Trenches World Report – https://fromthetrenchesworldreport.com/feed/
garydbarnett.com – https://www.garydbarnett.com/feed/
Gateway Pundit – https://www.thegatewaypundit.com/feed/
Geoengineering Watch – https://geoengineeringwatch.org/?feed=rss2
Global Research – https://www.globalresearch.ca/feed
GMWatch Home – http://gmwatch.org/index.php?format=feed&type=rss
GreenMedInfo – https://www.greenmedinfo.com/rss.xml
Health Impact News – https://healthimpactnews.com/feed/
henrymakow.com – https://www.henrymakow.com/index.xml
Highwire – https://thehighwire.com/feed/
Jefferey Jaxen – Blog – http://www.jeffereyjaxen.com/1/feed
Jennifer Margulis – https://www.jennifermargulis.net/feed/
Jon Rappoport’s Blog – https://blog.nomorefakenews.com/feed/
Larken Rose – https://www.youtube.com/feeds/videos.xml?channel_id=UCFeK8ZdHbCqAq3gekWs8aEQ
LewRockwell – https://www.lewrockwell.com/feed/
Lockdown Sceptics – https://lockdownsceptics.org/feed/
London Real – https://londonreal.tv/feed/
Mercola – https://articles.mercola.com/sites/articles/rss.aspx
Millennial Millie – https://www.youtube.com/feeds/videos.xml?channel_id=UCglVbeKF9JGMCt-RTUAW_TQ
MintPress News – https://www.mintpressnews.com/feed/
MuchAdoAboutCorona.ca – https://muchadoaboutcorona.ca/feed/
National Sustainable Agriculture Coalition – http://feeds.feedburner.com/SustainableAgricultureCoalition
Natural Blaze – https://feeds.feedburner.com/naturalblaze
Natural News – https://www.naturalnews.com/rss.xml
NCCPR Child Welfare Blog – https://www.nccprblog.org/feeds/posts/default
New American – https://www.thenewamerican.com/component/obrss/rss
OffGuardian – https://off-guardian.org/feed/
Organic Prepper – https://www.theorganicprepper.com/feed/
ProPublica – http://feeds.propublica.org/propublica/main
pubmed: coconut – http://www.ncbi.nlm.nih.gov/entrez/eutils/erss.cgi?rss_guid=1h9kEWSfxImVd1oVVxNXs-QhLQ2Mqgf3akksz6grrdBSI4mkKM
pubmed: coconut oil – http://www.ncbi.nlm.nih.gov/entrez/eutils/erss.cgi?rss_guid=1jo74WIY5-k9p6Znkrwo_QPaAx3vca4yHPRf0HdXALXdzbQMSx
pubmed: glyphosate – https://eutils.ncbi.nlm.nih.gov/entrez/eutils/erss.cgi?rss_guid=1jcCSTNs5ufOgat_YC3U4VwOtfhRjg-1yrF8FFk40eULTu5gHm
pubmed: ketogenic – http://www.ncbi.nlm.nih.gov/entrez/eutils/erss.cgi?rss_guid=1X19VF0tT62AGY7YJfny8dqLi72ihaiV9mT7Ci-IkSxQtiZcSu
pubmed: lauric acid – http://www.ncbi.nlm.nih.gov/entrez/eutils/erss.cgi?rss_guid=1Z3442Lm0S4hVLy6FnedjUqQRvq3xpeURXmyVzxvBi-al7eQg1
pubmed: nigella sativa – http://www.ncbi.nlm.nih.gov/entrez/eutils/erss.cgi?rss_guid=1FGsvIM_Qr9wkQgjpiOwj3WknRPW1Kki5WG-g8Z8VKNBurM9nD
pubmed: vaccine induced auto... – http://www.ncbi.nlm.nih.gov/entrez/eutils/erss.cgi?rss_guid=1JsSDwnbM1SRzT1Uf_bWEVfmljEtsuQ8fPVHItFJg_u6p_w5fu
Q (We) Are The News – https://wearethene.ws/rss
reallygraceful – https://www.youtube.com/feeds/videos.xml?channel_id=UCY-UU3bN4FkMILC-CMd8N5w
Rethinking Foster Care – https://rethinkingfostercare.blogspot.com/feeds/posts/default
Rise Magazine – http://www.risemagazine.org/feed/
Ron Paul Institute for Peace And Prosperity – http://ronpaulinstitute.org/archives/peace-and-prosperity/rss.aspx?blogid=5
SaneVax, Inc. – http://sanevax.org/feed/
Sarah Westall – https://sarahwestall.com/feed/
Sharyl Attkisson – http://feeds.feedburner.com/SharylAttkisson
Spiro Skouras – https://www.youtube.com/feeds/videos.xml?channel_id=UCkKOQNYoZjaa_8V0uPOueeQ
Stand for Health Freedom – https://standforhealthfreedom.com/feed/
StopTheCrime – http://stopthecrime.net/wp/feed/
Strategic Culture Foundation – https://www.strategic-culture.org/feed/
Summit News – https://summit.news/feed/
Sustainable Pulse – https://sustainablepulse.com/feed/
Technocracy News – https://www.technocracy.news/feed/
The Appeal – https://theappeal.org/feed/
The Burning Platform – https://www.theburningplatform.com/feed/
The Freedom Articles – https://thefreedomarticles.com/feed/
The Last American Vagabond – https://www.thelastamericanvagabond.com/feed/
The Vaccine Reaction – https://thevaccinereaction.org/feed/
True Pundit – https://truepundit.com/feed/
unlimitedhangout.com – https://unlimitedhangout.com/feed/
U.S. Right to Know – https://usrtk.org/feed/
Vaxxter – https://vaxxter.com/feed/
Vernon Coleman – https://www.youtube.com/feeds/videos.xml?channel_id=UCd6F39mg7LPUkw1BfiJDibw
Volatility – https://attempter.wordpress.com/feed/
Winter Watch – https://www.winterwatch.net/feed/
ZeroHedge News – http://feeds.feedburner.com/zerohedge/feed
HHS Launches $250M Propaganda Campaign to Convince People to Take Experimental COVID Vaccines as Current Doses Sit Unused

By Brian Shilhavy | Health Impact News | January 4, 2021
Reporter Zachary Stieber of the Epoch Times is reporting today that President Trump’s Operation Warp Speed program for distributing COVID experimental vaccines is lagging way behind schedule.
Operation Warp Speed’s chief scientific adviser on Monday defended the federal government’s rollout of COVID-19 vaccines, but acknowledged there is a “lag” in getting the vaccines administered.
Officials with President Donald Trump’s administration said late last year that 20 million Americans would be vaccinated by the end of 2020. Instead, under 3 million people received vaccinations, out of some 12 million doses distributed to states, as of Dec. 30.
Moncef Slaoui, the operation’s adviser, said on CNN’s “New Day” that “nothing has gone wrong.” He was then played a snippet of what he said last year, when he said officials expected 40 million doses to be shipped and 20 million Americans to be vaccinated by the time 2021 hit.
“So obviously, I did say that, and, you know, that was our hope,” Slaoui said.
The operation, a federal government effort, distributes vaccine doses to states, which are then in charge of administering them.
According to a Centers for Disease Control and Prevention tracker, most states haven’t come close to administering half of the doses they’ve received.
So why haven’t states “come close to administering half of the doses they’ve received”?
Surgeon General Jerome Adams said the delay in vaccinations stems from states not being fast enough to administer them, and hesitancy among a broad swath of the public in getting the new vaccines.
Read the full article at The Epoch Times.
America Divided Between those Who Watch and Read the Pharma-funded Corporate Media, and Those who Do Not
So what is the U.S. Government and Big Pharma going to do about all these unused experimental vaccines that Americans don’t want to take?
They are going to do the same thing they have been doing for decades: They are going to lie to the American people by giving the media $250 MILLION to produce propaganda using the “appeal to authority” technique by having “doctors” tell you how safe the vaccine is, and that it is your duty to get the vaccine for the good of humanity.
As FiercePharma reports:
Half of Americans remain skeptical about COVID-19 vaccines. The U.S. Department of Health and Human Services (HHS) calls that group the “movable middle,” and it plans to spend $250 million to convince them otherwise.
The first phase of the campaign, already underway in December, is an online video and radio effort to prep the market. The bulk of the effort aimed at promoting vaccinations—the “Building Vaccine Confidence” campaign—will officially kick off in late January in a bid to convince people to get the vaccine when it’s their turn.
The plans from HHS and the contracted Washington, D.C., consultancy Fors Marsh Group include paid and unpaid media elements. National and local TV, radio, print and social media buys will run concurrently with co-marketing partnership efforts with a variety of associations, nonprofits and corporations, including Google, with which HHS is currently in discussions. (Source.)
So who is the Liar in Chief that will be first up to convince the American public they should risk an experimental vaccine?
The man who has admitted to lying about herd immunity to try and trick people into getting the COVID vaccine for the “greater good,” Anthony Fauci.
As FiercePharma reports, this is a risky “double-edge” sword approach, since Fauci is so polarizing. People either love him, or hate him, and that reflects the division within America today among those who consume the pharma-funded corporate media and their watch dogs, Big Tech, and those who do not, but make the extra effort to research the truth for themselves.
The Ad Council video leads with Anthony Fauci, M.D., director of the National Institute of Allergy and Infectious Diseases, who says: “My primary message to healthcare professionals is please get vaccinated. It’s important to protect yourselves, to protect your family, but as important symbolically as healthcare providers to show confidence in the vaccine so that other people in this country follow suit and get vaccinated.”
It’s a likely to be a tough sell. Even HHS’ own data point to that. In pre-campaign surveys asking a wide cross-section of people whose advice they would trust to get a vaccine, HHS said half claimed they would get a vaccine if Fauci and the Centers for Disease Control and Prevention (CDC) said to do so, while the other half said they specifically wouldn’t get a vaccine if told by Fauci and the CDC. (Source.)
Here is the first video produced by the Ad Council on YouTube. It is geared towards healthcare professionals, of whom up to 60% are refusing the vaccine.
After Anthony Fauci makes an appeal to guilt for healthcare workers, it is no accident that the doctors and nurses who speak next represent the next segments of society that the Globalists are targeting with these experimental vaccines: Blacks, Asians, and Latinos.
As FiercePharma reports:
The Fors Marsh strategy includes a plan to “heavy-up in vulnerable communities” of people disproportionately affected by COVID-19, including senior citizens with comorbid conditions, front-line workers and Black, American Indian and Alaska Native, Hispanic and American Pacific Islander populations. (Source.)
Here is a list of the lies that are being told to the American people through this video:
LIE #1: “It’s important to note that none of these vaccines can give you COVID19 since they only express a protein from the virus that allows your body’s immune system to generate antibodies.”
FALSE. The fact is, the COVID19 SARS virus has never been fully identified, and the PCR test to test for COVID19 is inaccurate. Even if what they say is true about there not being a COVID19 virus in the vaccine, since they can only at this point identify fragments from the faulty PCR test, who is to say that a “protein” from the virus that affects the body’s immune system would not produce symptoms of COVID19 and test positive?
Also, in Israel, which at the time of publication of this article has had the largest amount of people vaccinated with the experimental COVID vaccines, has reported that 240 people have come down with COVID right after being vaccinated. See:
So to say that “none of these vaccines can give you COVID19” is scientifically inaccurate, because the truth is these vaccines have not been studied long enough, and we just do not know.
LIE #2: “Because vaccines are given to millions of healthy people to prevent serious diseases, they’re held to very high safety standards. Both the FDA and the CDC have to ensure the safety and efficacy of the vaccines before they are recommended for use in the United States. The COVID19 vaccine, just like all others, are undergoing a rigorous process...”
FALSE. The COVID19 vaccines are NOT approved by the FDA like every other vaccine currently in the market, and the typical time it takes to bring a vaccine to market is 5-7 years. (Source.)
The experimental COVID vaccines should NOT be compared to vaccines that have full FDA approval, but to other times a vaccine was rushed to market under emergency use authorization, and the last time that happened was in 1976 with the Swine Flu “epidemic.”
But the “epidemic” never panned out. Only one death and 13 cases were attributed to the Swine Flu, while 25 people died from the vaccine and another 500 or so developed Guillain-Barre syndrome. The vaccine was withdrawn from the market after 10 weeks. See:
LIE #3: “So far, we haven’t seen any trends of serious side effects.”
FALSE. They are trying to be clever by using the word “trends” so that specific cases of serious side effects, including DEATH, can be excused as “abnormal” or not a result of the vaccine.
But they got caught in their own lie here, as even the FDA has stated that they are investigating why so many people are experiencing anaphylactic shock after receiving the vaccine, focusing on the polyethylene glycol component of the vaccine. (Source.)
Not to mention that several people have now died after receiving the experimental vaccines, including one healthcare worker in Portugal, and apparently Nurse Tiffany Dover from Tennessee as well.
There were deaths in the vaccine trials as well, before the FDA EUA was issued. (Source.)
Facts About the Experimental COVID Vaccines they Do NOT Tell You
In addition to their lies, the people in this video are failing to give full disclosure about all the facts regarding these experimental COVD vaccines.
1. These vaccines are NOT approved by the FDA.
This is stated multiple times in the vaccine guidelines that are supposed to be given to everyone. Therefore, it is illegal to require anyone to take them. They are 100% voluntary, because you are basically participating in the last part of their vaccine trials in order to get FDA approval.
2. Emergency Use Authorization was issued by the FDA illegally, because other therapeutics to treat COVID19 are available.
Hydroxychloroquine and Ivermectin are two older drugs already approved by the FDA that tens of thousands of doctors have used successfully to treat and cure COVID19.
In addition, the experimental COVID19 vaccines used the faulty PCR test in their trials, and therefore should never have been approved until accurate testing was used. An Administrative Stay of Action was filed against the FDA, but they simply ignored it. See:
3. Warnings of Potential Infertility due to These Experimental Vaccines are NOT Being Issued by the FDA
The UK guidelines for the Pfizer vaccine warn of potential infertility of women and also do NOT recommend pregnant women receive the vaccine, while neither warnings are issued for the same vaccine for Americans. See:
Unlike UK, U.S. FDA Allows Pregnant and Nursing Women to Receive Experimental Pfizer COVID Vaccine
Also, the University of Miami is investigating the effects of the COVID-19 vaccines on male fertility. See:
Study investigates effects of COVID-19 vaccine on male fertility
The other thing that the U.S. Government and Big Pharma never disclose, is the revolving door between both. Former FDA Chief Scott Gottlieb, for example, now sits on the Board of Directors for Pfizer. See:
Former FDA Director Gottlieb Now Pfizer Board Member Secures $1.95 BILLION for COVID Vaccine
The CDC, FDA, and HHS have become primarily marketing branches of Big Pharma.
The Corporate Media is Owned by Big Pharma
While in years past the primary advertisers funding the corporate media were Wall Street conglomerates heavily invested in tobacco and the oil industry, today it is Big Pharma.
See:
Protecting their financial interest in the pharmaceutical trade is Big Tech, as now even Google is a pharmaceutical company, and they filter their search results to censor anything that challenges pharmaceutical products like vaccines. See:
And now, the U.S. Government is going to give the corporate media and Big Tech a quarter of a million dollars to try and brainwash you into getting the unapproved experimental COVID vaccine, which is a mere drop in the bucket of the $TRILLIONS of American wealth that has been transferred to Big Pharma in 2020 all in the name of the “pandemic.”
Don’t be fooled by their lies! Turn off your TVs and stop watching these Hollywood-style actors and actresses posing as journalists spew forth this dangerous propaganda.
What Vaccine Trials?
The most important, meaningful phase of CV-19 vaccine trials has barely begun, let alone been completed
By Iain Davis | OffGuardian | January 3, 2021
COVID 19 vaccine trials appear to have caused some confusion. Hopefully, this article might help clear things up a bit. People genuinely appear to believe that the COVID 19 vaccines have undergone clinical trials and have been proven to be both safe and effective. That belief is simply wrong.
The main point is this. If you decide to have Pfizer and BioNTechs experimental mRNA-based BNT162b2 (BNT) vaccine, or any other claimed COVID 19 vaccine for that matter, you are a test subject in a drug trial.
The mRNA in the BNT vaccine was sequenced from the 3rd iteration of the original WUHAN published Genome SARS-CoV-2 (MN908947.3). However, the WHO protocols Pfizer used to produce the mRNA do not appear to identify any nucleotide sequences that are unique to the SARS-CoV-2 virus. When investigator Fran Leader questioned Pfizer they confirmed:
The DNA template does not come directly from an isolated virus from an infected person.
Nor are there any completed clinical trials for these vaccines. Trials are ongoing. If you are jabbed with one, you are the guinea pig. This may be fine with you but it’s not a leap of faith I or my loved ones wish to take. However, everyone is different.
On December the 8th the BBC reported a study in the Lancet and categorically stated:
The Oxford/AstraZeneca Covid vaccine is safe and effective, giving good protection, researchers have confirmed
The BBC had no justification to make this claim. The study in the Lancet did not confirm anything of the sort. The researchers wrote:
ChAdOx1 nCoV-19 has an acceptable safety profile and has been found to be efficacious against symptomatic COVID-19 in this interim analysis of ongoing clinical trials.
This was an interim analysis funded by, among others, CEPI and the Bill and Melinda Gates Foundation. The analysis was based upon trials which are years from completion and haven’t reported anything. The researchers also stated:
There were no peer-reviewed publications available on efficacy of any severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) vaccines…
There is no clear scientific evidence establishing either the safety or efficacy of proposed COVID 19 vaccines. The BBC and other MSM reports that this evidence exists are false.
We are going to focus on Pfizer and BioNTech’s BNT vaccine but all the manufacturers have essentially exploited the same trick. The regulators and governments have worked with the pharmaceutical corporations to conflate the limited data from the initial, or phase one, trials with the incomplete and ongoing data collection from the substantially larger phase two and three trials. The MSM have then falsely claimed the 1,2,3 phase trials are complete and insinuated that the untested data demonstrates vaccine efficacy and safety.
In reality, not only has the reporting of existing data been manipulated to show efficacy that isn’t evident in the raw data itself, the most important and meaningful phases of the trials have barely begun, let alone been completed.
Recently the UK Financial Times reported that the UK regulators (the MHRA) are due to approve Astrazeneca/Oxfords AZD1222 [ChAdOx1] COVID 19 Vaccine. The FT revealed an anonymous statement from the UK Department of health:
The medicines regulator is reviewing the final data from the University of Oxford/AstraZeneca phase 3 clinical trials to determine whether the vaccine meets their strict standards of quality, safety and effectiveness.
Thus giving the public the impression that the trials are complete and that the regulators have strict safety standards. The 1,2,3 phase trial for AZD1222 was registered with the U.S. Centre for Disease Control as clinical trial NCT04516746 [Archived 29th December 2020]. It is incomplete and the estimated end date is February 21st 2023. The CDC state:
No Study Results Posted
Astrazeneca are years away from reporting any “final data.” It is impossible for the UK Department of Health to review it, because it doesn’t exist.
NCT04516746 is one of four trials of AZD1222. Another Russian arm of the AZD1222 trial was suspended after a Suspected Unexpected Serious Adverse Reaction (SUSAR) event occurred. The SUSAR supposedly happened in the United Kingdom after a 37 year old women developed inflammation of the spinal chord. It appears the Russian Ministry of Health have yet to reinstate their arm of the Astrazeneca/Oxford trial while it has resumed in the UK and elsewhere.

Clinical Trial NCT04516746: [Archived 29.12.2020], [Contemporary Link]
What Vaccine Trials?
On November 18th Pfizer and BioNTech announced they had concluded their phase three trial of BNT. They had demonstrated efficacy of 95% and U.S. Food and Drug Administration’s (FDA’s) Emergency Use Authorization (EUA) safety data milestone had been met.
The only part of this claim that was true was compliance with FDA emergency safety data milestones. They have not concluded their phase three trials. They haven’t even fully completed phase one.
Under section 564 of the Federal Food, Drug, and Cosmetic Act (FD&C Act) so called “unapproved” drugs are allowed on the market in emergencies. Similarly, in the UK, authorisation under Regulation 174 of the Human Medicine Regulations 2012 (as amended) permits the same.
Having also been approved in the UK, this is why the Medicines and Healthcare products Regulatory Agency (MHRA) state:
This medicinal product does not have a UK marketing authorisation
The fact that there are no completed clinical trials for the Pfizer and BioNTech BNT vaccine also explains why the FDA State:
Additional adverse reactions, some of which may be serious, may become apparent with more widespread use of the Pfizer-BioNTech COVID-19 Vaccine.
The FDA also noted:
[There is]…currently insufficient data to make conclusions about the safety of the vaccine in sub-populations such as children less than 16 years of age, pregnant and lactating individuals, and immunocompromised individuals…..[the] risk of vaccine-enhanced disease over time, potentially associated with waning immunity, remains unknown.
Yet the first people to receive this vaccine are the most vulnerable in society, many of whom are immunocompromised. The precautionary principle appears to have been abandoned. The notion that the purpose of the BNT vaccine roll out is to save life appears untenable.
The Pfizer announcement enabled politicians to pretend to cry on national television while others were really excited. UK Prime Minister Boris Johnson said it was “fantastic news,” and the BBC said it was “good news” and “really encouraging.” Everyone was thoroughly impressed with the 95% effective claim.
However, this was based upon relative risk reduction. That is the declared percentage difference between the vaccinated group’s 8/18310 chance (0.00044%) of developing COVID 19 against a 162/18319 (0.0088%) chance of COVID 19 symptoms without the vaccine. As this larger group of 43,000 people have yet to be trialled, there is no basis for this claimed outcome. But it is what it is, and we can use these reported figures here.
It should be noted this only refers to an alleged reduction of COVID 19 symptoms among those who have the virus. The tested endpoints do not demonstrate that the vaccine will either reduce the spread of infection or save lives. It should also be noted that these figures suggest the threat from COVID 19 is vanishingly small.
Using Pfizer’s figures, the relative risk reduction is 100(1 – (0.00044/0.0088)). Which is 95%. Voila!
This sounds fantastic and is a much better marketing strategy than reporting the absolute risk reduction. The absolute risk of developing COVID 19 symptoms without the vaccine is supposedly 0.0088% and with the vaccine 0.00044%. In absolute terms, the effectiveness of the vaccine is 100(0.0088-0.00044).
A risk reduction of 0.84%. Oh! A barely perceptible “efficacy.”
By using the relative instead of absolute risk reduction, the mainstream media (MSM) were free to market the mRNA vaccine for Pfizer and BioNTech (and other interested parties) with impressive sounding claims. These weren’t remotely truthful, not only because they relied upon statistical manipulation but because no one had a clue about BNT’s safety or efficacy. To this day, there are no clinical trial results.
The Clinical Trials That Don’t Exist
An analysis of available positive RT-PCR tests and mortality results led the Oxford Centre for Evidence Based Medicine estimated a very tentative COVID 19 Case Fatality Rate (CFR) of around 1.4%. Based upon the figures reported to the FDA by Pfizer and BioNTech, this indicates a broad population based mortality risk from COVID 19 of 1.4(0.0088/100) which is 0.00012%.
Please bear this incredibly remote risk in mind as we discuss the early indication of the apparent threat to public health presented by the mRNA vaccine.
It is reasonable to work in terms of population risk because, while the chance of COVID 19 mortality seemingly increases with age, with the average age of death being 82 and a mortality distribution indistinguishable from standard mortality, the intention is to give the vaccine to everybody.
If we look at the “V-Safe Active Surveillance for COVID 19 Vaccines” reported by the U.S. Center For Disease Control (CDC), early indications of the recorded “Health Impact Events” (HIE) reveal a worrying level of adverse reactions from the mRNA vaccine. The CDC define an HIE as:
Unable to perform normal daily activities, unable to work, required care from doctor or health care professional
On December the 18th 112,807 people were injected with the Pfizer/BioNTech vaccine in the U.S. Of these, 3,150 were subsequently unable to perform normal daily activities, unable to work, required care from doctor or health care professional. This is an HIE rate of 2.8%.
This suggests that among the first 10 million people to receive the vaccine in the UK, around 280,000 may find themselves unable to perform normal daily activities, unable to work and require medical care as a result. As it is the most vulnerable who are the first to receive this vaccine, given the tiny risk of mortality from the COVID 19 disease, it is by no means clear that this is a risk worth taking.

CDC Presentation: [Archived 19.12.2020],[Original]
Not that any of the other vaccines seem any better. So far the CDC have noted more than 5,000 HIE’s for all vaccine being trialled on the population. Clearly, the potential exists that the vaccines will contribute to more deaths than the disease they allegedly protects vulnerable people against.
The Pfizer/BioNTech trial was registered as clinical trial number NCT04368728 with the CDC. Having recently discussed what I am about to share with you with people who simply refused to believe the evidence of their own eyes, I think it is important to stress that this is the Phase 3 Clinical Trial which Pfizer claimed they had concluded in their press release. There isn’t another one. This is it.
The CDC state:
When available, study results information is included in the study record under the Study Results tab…….After study results information has been submitted to ClinicalTrials.gov, but before it is posted, the results tab in the study record is labeled “Results Submitted.
At the time of writing (21st December 2020) as can be seen by date of the archived ClinicalTrials.gov web-page, the Study Results tab reads “No Results Posted.” That is because there are no posted or submitted results from the Pfizer BioNTech trial of the BNT162b2 vaccine:
No Study Results Posted on ClinicalTrials.gov for this Study
Mainstream media reports, giving the impression that these vaccines have been found to be effective and safe are not evidence and they are not based on science. They are based on political policy and they report dangerous pseudo-scientific babble, masquerading as science journalism.
There will of course be mindless anti-rationalists who will call this dangerous antivaxxer nonsense. All the time insisting that it is perfectly safe to give a vaccine with a questionable safety profile, for which there are no completed clinical trials, to the most vulnerable people in our society.
I am running out of patience with these people.
Vaccine Safety?
The start date for NCT04368728 was April 29th and the estimated trial completion date is January 27th 2023. The estimated end date of the primary or phase one of a three phase trial is June 13th 2021.
According to the “Current Primary Outcome Measures,” the minimum time frame for Pfizer to assess serious adverse events (SAE’s) is “6 months after last dose.” This is the minimum term for assessing SAE’s in phase one of the trial.
Phase one is the only part of the NCT04368728 trial to have been completed and published. It was published on the 14th October, 5 months and two weeks after the start date. Most of that period was taken up with recruitment an allocation. The minimum term for assessing SAE’s has not been met during Phase One.
During Phase One, 195 participants were split into 13 groups of 15 people. In each group 12 received one of two potential mRNA vaccine candidates (either BNT162b1 or BNT162b2) and 3 a placebo.
39 people aged between 18-55 and another 39 people aged between 65-85 received the BNT vaccine, now approved for global distribution. The threat of COVID 19, though tiny overall, is statistically zero for those aged 18-55. Those with any measurable risk from COVID 19 were in the older age group.
Of the 39 older people who received 2 doses of BNT about half of them experienced “fatigue,”roughly 15% had “chills” and 3 of them had a fever. The common side effects of BNT included nausea, headache (a very common BNT induced nervous system disorder) arthralgia and myalgia (very common), fatigue, chills and fever (again very common.) Other than fatigue, no one in the placebo group suffered these problems.
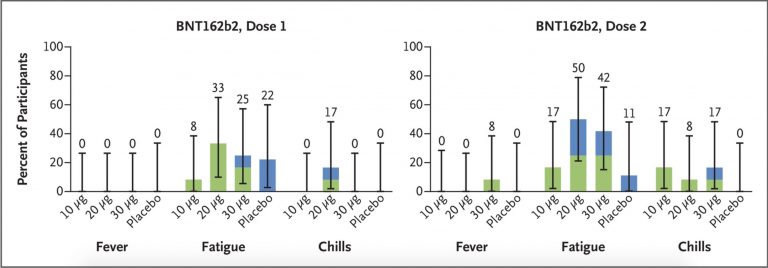
Safety and Immunogenicity of Two RNA-Based Covid-19 Vaccine Candidates: Figure 3, ‘Participants 65 – 85 yr of age’ [Archived 29.10.2020], [Original]
The study states:
Pfizer was responsible for the trial design; for the collection, analysis, and interpretation of the data; and for the writing of the report.
Therefore, it is reasonable to conclude that while Pfizer see the side effects of their vaccine as fatigue, chills and fever, the CDC refer to them as people who can’t work and need medical care.
The UK Medical and Healthcare products Regulatory Agency (MHRA) approved the BNT vaccine, to be given to vulnerable British people, based upon a study of 39 older people. This study reported a pretty high adverse reaction rate. It was produced exclusively from the R&D of the vaccine manufacturer. The MHRA questioned nothing.
They “approved” BNT in the certain knowledge that there were no completed clinical trials for this vaccine. In their Public Assessment Report they state:
At the time of writing, the main clinical study is still on-going….It was concluded that BNT162b2 has been shown to be effective in the prevention of COVID-19. Furthermore, the side effects observed with use of this vaccine are considered to be similar to those seen with other vaccines. Therefore, the MHRA concluded that the benefits are greater than the risks.
This conclusion and approval not only lacks supporting evidence it is utterly at odds with what little is known about BNT. While Pfizer and BioNTech only completed trials of the vaccine on 39 relevant test subjects, the results, even from this practically inconsequential effort, suggest the risk from the vaccine is greater than the risk presented by COVID 19. By a considerable margin.
This undoubtedly explains why the MHRA ordered software from European suppliers to deal with the slew of vaccine adverse reaction they presumably anticipate. They stated:
The MHRA urgently seeks an Artificial Intelligence (AI) software tool to process the expected high volume of Covid-19 vaccine Adverse Drug Reaction (ADRs)….it is not possible to retrofit the MHRA’s legacy systems to handle the volume of ADRs that will be generated by a Covid-19 vaccine.
From the way the manufacturers, politicians, regulators and the MSM have approached vaccine safety, it is clear that they collectively have at total disregard for the welfare of vulnerable people. We really must put aside this infantile notion that “the authorities” care about us or our loved ones. We mean nothing to them.
COVID 19 is only an appreciable risk for the most vulnerable in society. It is a risk to the infirm elderly and people with existing life threatening conditions.
If we look at the exclusion criteria for Phase One, these people were not in the cohort tested. Anyone with high blood pressure, asthma, diabetes or a high BMI were excluded from the alleged safety trial. But the vaccine is being given to the most vulnerable first.
Of the 39 older people at most risk in the phase one study, none of them had the serious comorbidities which the overwhelming majority of those who die “with” COVID 19 possess. The people actually at risk from COVID 19 nominally entered the BNT trials at phase 2 and 3. However, it appears every effort has been made to limit, if not completely remove, their number too. “Immunocompromised or individuals with known or suspected immunodeficiency,” were excluded.
Immunodeficiency is caused by a wide range of health conditions. Conditions such as undernutrition, polytrauma, stress after surgery, diabetes and cancer lead to immunodeficiency. The people with the comorbidities associated with so called COVID 19 deaths were practically ruled out from the BNT vaccine trials.
NCT04368728 was designed as a 1,2,3 trial with all phases running concurrently. With regards to assessing safety Pfizer described systemic events as:
Fever, fatigue, headache, chills, vomiting, diarrhea, new or worsened muscle pain, and new or worsened joint pain as self-reported on electronic diaries.
The first 360 subjects randomised into the phase 2 and 3 trials underwent monitoring for systemic events for less than a week, following each dose:
In the first 360 participants randomized into Phase 2/3, percentage of participants reporting systemic events [ Time Frame: For 7 days after dose 1 and dose 2 ]
The same cohort of 360 test subjects were also monitored for Serious Adverse Events (SAE’s) for up to 6 months in phase 2 and 3:
In the first 360 participants randomized into Phase 2/3, percentage of participants reporting serious adverse events [ Time Frame: From dose 1 through 6 months after the last dose]
Pfizer also intend to report the percentage of all test subjects who suffer SAE’s:
Percentage of participants in Phase 2/3 reporting adverse events [ Time Frame: From dose 1 through 6 month after the last dose ]
But there are no reported results from either phase 2 or 3. No one has the faintest idea what the health risks of BNT are, especially for those it is supposedly designed to protect, and no one in authority gives a damn. Phase 2/3 clinical trials are now a moot point anyway.
The regulatory agencies have already approved the vaccine and health services have started injecting people with BNT. They do so after the manufacturers failed to properly test its safety on a 39 people who were in the at risk group but did not have the comorbidity that leads to claimed COVID 19 deaths.
The degree to which people have been misled into believing that these vaccines are known to be either safe or effective is almost beyond imagination.
Sadly, we don’t need imagination. The evidence is clear.
***
You can read more of Iain’s work at his blog In This Together
Even While It Was Happening, It Wasn’t Happening
Was there really such a year as 2020?
By Michael Lesher | OffGuardian | December 31, 2020
You know how it goes: if a tree falls in the forest and no one hears it, et cetera…?
Suppose an entire society goes to smithereens, while our media elites stubbornly refuse to notice. What then?
Suppose the reporters and the pundits and the “experts” ignore the coup that has trampled our basic freedoms since last March.
Suppose they all assure us that defending democracy is “anti-science,” and preach to us that civil rights (except for Black Lives Matter protests) are nothing but a “death cult.”
Suppose, after an “election” conducted mainly in the press, on the basis of a torrent of worthless propaganda, a notorious corporate whore is about to be installed in the White House as carnival-barker-in-chief for scantily-tested vaccines – drugs being peddled by a gang of profiteers who wouldn’t even make the stuff until they were promised complete legal immunity for whatever they do to their victims.
Well? Does the murder of our liberties even make a sound?
Was there really such a year as 2020?
In his Nobel Prize acceptance speech in 2005, the playwright Harold Pinter had this to say about every atrocity concealed by the Western press:
It never happened. Nothing ever happened. Even while it was happening it wasn’t happening. It didn’t matter. It was of no interest.
And so much never happened this past year!
Four-fifths of the United States of America suspended democracy and declared the Bill of Rights obsolete. The United Kingdom unleashed a new sort of “police” – faces masked, truncheons in their paws – to maul peaceful protesters for the crime of breathing. In parts of Australia, it became a criminal offense to tell other people the time and place of a political demonstration. Germany outlawed political protest.
But none of that happened. It wasn’t reported in the mainstream press. It was of no interest.
In just over nine months, economies in once-wealthy countries were reduced to ruin. Social media reeled under systematic thought-policing. Following a wave of “executive orders” that shuttered small businesses across the United States, an unprecedented number of Americans began to steal food to survive. In the U.K., UNICEF is distributing food to hungry children for the first time in more than 70 years. Around the world, people in need still can’t get medical treatment. Cultural institutions have been shattered. The performing arts have been banned. Singing was deemed a public health risk.
It didn’t matter.
This year, for the first time in history, more than 40 governors in the U.S. awarded themselves quasi-dictatorial powers – on the strength of laws hastily designed less than 20 years ago for massive bioterrorism attacks, pressed into service to counter a medical “emergency” that was never an emergency. By the end of 2020, most of the American population was still living under dictatorial rule.
That was of no interest.
Huge numbers of people, in Europe as in America, were placed (without a court order) under virtual house arrest. This was called a protective measure – and it was reported as such, though the practice violated civil-rights rulings going back nearly a century. Tens of millions of people saw their livelihoods snatched from them by officials they never even had the opportunity to confront.
Yes, a handful of states that did not imprison their populations or wreck their economies claimed to have medical results as good as – if not better than – neighboring states that did both. Arkansas Governor Asa Hutchinson went so far as to assert all this on May 5 in the editorial pages of the Washington Post, a main purveyor of coronavirus propaganda. But those claims were never investigated in the mainstream press. They didn’t matter.
Now the mega-corporations that supported the “lockdowns” are sucking the life out of the small-business economy that was once the mainstay of the free world. For restaurants, the picture is so bleak that chef and author Edward Lee calls it “the end of the independent restaurant era,” and warns that…
we will lose the culture of all of our American cities…. [W]e will become a nation of corporate chain restaurants that will look and taste the same in every city.
Culture is under attack from other directions as well. London’s theatres, heirs to one of the proudest dramatic traditions in the world, are closed for the first time in modern history – and whether they will ever open again depends upon the whims of politicians. Musicians and other artists have been devastated by “social distancing” rules that never made any sense and have never been obeyed by the powerful.
That doesn’t matter, either.
In respectable society, it can’t even be talked about.
The U.K. Labour Party’s Angela Rayner – last seen threatening to expel “thousands and thousands” of members who don’t think their country should be governed by Israel – is now grousing that…
[o]ur children should not have to rely on humanitarian charities that are used to operating in war zones and in response to natural disasters.
You’d never guess that the self-righteous Rayner actually supported the economy-wrecking madness that caused this deepening poverty – in fact, back in May, she wanted even stricter police-state tactics than those the government imposed.
Governments lied to us throughout the year about the nature of the medical threat we faced, about what they planned to do about it, and about what it was going to cost us.
Formerly-esteemed scientists tried to tell us that the hype made no sense. “We’re falling into a trap of sensationalism,” Stanford University’s John Ioannidis said as early as March 23. “We have gone into a complete panic state.” The interview containing those comments was soon banned by Youtube, even though Ioannidis is universally recognized as “one of the world’s foremost epidemiologists.”
Prominent scientists who signed the Great Barrington Declaration suffered a similar fate, smeared as fringe elements promoting “craven lunacy” and a “brutal” attempt to “let people die” – in other words, as Nazis.
But that wasn’t name-calling. And it wasn’t censorship, either – even though Reddit’s moderators promptly banned the Declaration. Such facts mustn’t be mentioned. Breathe the word “censorship” and you’re a right-wing fanatic.
Speaking of fanaticism, though: an 18-year-old American college student is behind bars at this moment in the Cayman Islands. Her crime? Watching – by herself – as her boyfriend competed in his last jet-skiing race of the year, after she had received not one but two negative tests for COVID19. It seems other people attending the race snitched on the woman, resulting in a four-month prison sentence for cutting short a fourteen-day “quarantine” – one that was issued without a court order, of course.
Once upon a time, we would have called those snitches “collaborators,” if not “heartless fanatics.” Now their actions are praised by newspapers and prosecutors alike: after all, they were protecting the public “health” by putting a young woman in prison.
New vaccines for COVID19 are another way of protecting the public health, of course – they have nothing whatsoever to do with the billions of dollars pharmaceuticals companies are likely to make from selling them.
Never mind that the Food and Drug Administration had to short-circuit its own rules in order to authorize their use. Never mind that the manufacturers had to be promised that “for the next four years, [they] cannot be sued for money damages in court over injuries related to the administration or use” of their new vaccines – a blanket legal immunity that is “very rare,” according to a prominent labor attorney. (Oh, and you can’t sue the FDA either.)
None of that matters. None of that is of interest.
That’s why CNN’s “political analyst,” Joe Lockhart, could recently insist that the government ought to prevent Tucker Carlson from stating inconvenient facts about those vaccines on his Fox News program. The First Amendment doesn’t matter any more, you see. Joe Lockhart says so. He’s a representative of a press outlet calling for government censorship of another press outlet – for expressing an opinion he doesn’t agree with.
And? Has anyone in the “free press” complained about Lockhart’s breathtaking treachery – attacking the Constitution’s press protections while handing over a colleague to the Thought Police? Not as far as I know.
Because, you see, none of it happened.
Just like the rest of the coronavirus coup. Even while it was happening, it wasn’t happening.
It didn’t matter that all the recent hysteria about COVID19 “cases” was based on the results of a manifestly unreliable testing procedure. It didn’t matter that inexpensive and effective treatment for the disease may already be available, with no serious side effects, from drugs like ivermectin and hydroxychloroquine. When the highly-credentialed Dr. Pierre Kory tried to interest Congress in the use of these medications – from which no one stands to benefit except those suffering the worst cases of COVID19 – he was the target of an astonishing smear by the ranking Democrat on the Senate Homeland Security Committee.
That was typical of official reaction, though: after a group of physicians announced the promising results of the same drugs on December 4…
no major U.S. media outlets reported [their] pleas for help from the federal government to act… Nor did any representative from the CDC, the NIH or the World Health organization contact them,
… according to one of the rare alternative news sources that bothered to report the story.
So the unproven vaccines will roll out everywhere; Big Pharma will get even richer; poor people will be allowed to die. As manufactured claims of rising “case” numbers stoke renewed hysteria, government after government will subject its citizens to further mass house arrests, even though the experience of Belarus – which did not impose “lockdowns” – strongly suggests that the mass-incarceration strategy does more harm than good.
To those in power, all this is of no interest. It didn’t matter. It never happened.
And to the rest of us?
That will depend, I suppose, on the steadfastness of people who care more about the truth than about conformity.
Those for whom words still have meaning, and facts still matter.
Those who are not ashamed to touch, nor afraid to stand up.
Those who will not swallow lies nor ingest a fraud.
Those to whom the word “freedom” isn’t an insult.
Those are the ones who have truly survived the ghastly year 2020 – and on whom our future depends.
The criminal WHO blows its own cover: fake PCR test
By Jon Rappoport | December 31, 2020
In early 2020, the WHO accepted a PCR test for “SARS-CoV-2” that was designed without having possession of the virus. Yet the test is meant to detect… the missing virus. This is evidence of deep criminal intent. [1]
But as of December 14, 2020, WHO has made a correction [2]. Thereby blowing its own cover. Why?
Two reasons. Huge numbers of people have caught on to the PCR test scam. And by their correction, WHO paves the way for “declining COVID case numbers”—thereby making it appear the new vaccine is a roaring success. I predicted this development. [3] [4]
A brief review. The PCR test (a complete fraud for several reasons) is run in “cycles.” Each cycle is a giant magnification of a tiny portion of the swab sample taken from the patient.
As I’ve reported, even Tony Fauci readily asserts that if the PCR is run at 35 cycles or higher, it’s meaningless. [5] [6]
Every positive result—indicating “infection with the virus”—occurring at 35 cycles or higher is meaningless.
BUT, as I’ve also pointed out, public health agencies recommend running the PCR test at up to 40 cycles. Therefore, labs comply.
Therefore, millions upon millions of PCR tests results, over the last nine months, which indicate “infection,” are a vast lie.
Therefore, the COVID case numbers are a vast lie, and the lockdowns, which are based on those numbers, are absurd, insane, criminal, and predatory.
NOW, the WHO is walking back their stance on how the PCR should be run, for the reasons I mentioned above.
The WHO document is titled, “WHO Information Notice for IVD Users/Nucleic acid testing (NAT) technologies that use real-time polymerase chain reaction (RT-PCR) for detection of SARS-CoV-2.” [2]
Here are the money quotes. The language is mealy-mouthed, intentionally confusing, cautious, and sterile. Nevertheless, we can see the intent to lower the number of test cycles.
“Users of RT-PCR reagents should read the IFU [Information for Use] carefully to determine if manual adjustment of the PCR positivity threshold is necessary to account for any background noise which may lead to a specimen with a high cycle threshold (Ct) value result being interpreted as a positive result.”
Translation: Using too many test cycles—aka “high cycle threshold (Ct) value”—has resulted in patients being told they’re infected, which is a lie.
“In some cases, the IFU will state that the cut-off should be manually adjusted to ensure that specimens with high Ct values are not incorrectly assigned SARS-CoV-2 detected due to background noise.”
Translation: Running the test with a high number of cycles yields “background noise”—aka a false positive result. The patient is told he’s infected but he’s not.
“The design principle of RT-PCR means that for patients with high levels of circulating virus (viral load), relatively few cycles will be needed to detect virus and so the Ct value will be low. Conversely, when specimens return a high Ct value, it means that many cycles were required to detect virus. In some circumstances, the distinction between background noise and actual presence of the target virus is difficult to ascertain.”
Translation: When the test is run with a high number of cycles, we can’t tell the difference between “irrelevant” and “meaningful.”
A frank and honest translation of the WHO message: “We’re changing the way we’re doing PCR tests. We were running them with a high number of cycles and getting millions of false positives, and those numbers were deployed to justify the lockdowns—but NOW we’re moving to a lower number of cycles. This change, all on its own, will result in fewer positive results, fewer case numbers, making the vaccine look VERY GOOD.”
The WHO is still crazy, still criminal, but not entirely stupid. They know what they’re doing and why.
SOURCES:
[1] https://blog.nomorefakenews.com/2020/12/25/you-thought-the-pcr-test-detects-an-actual-virus-wrong/
[2] https://www.who.int/news/item/14-12-2020-who-information-notice-for-ivd-users
[4] https://blog.nomorefakenews.com/2020/11/13/how-theyll-fake-the-success-of-the-covid-vaccine/
[6] https://blog.nomorefakenews.com/2020/12/08/florida-forces-labs-to-report-number-of-pcr-test-cycles/
10 Facts From the UK Government Pfizer Vaccine Guidance that Promote “Vaccine Hesitancy”
By Johnny Vedmore |
Unlimited Hangout| December 29, 2020
Official government guidance has been released in the United Kingdom to assist healthcare professionals in administering the Pfizer/BioNTech vaccine BNT162b2. While the UK government goes to war against supposed misinformation, the official narrative is clearly based on very little to no supporting data from incomplete clinical trials. This article examines the document “Reg 174 Information for UK Healthcare Professionals” and narratives being pushed in the mainstream media that directly contradict that document.
Healthcare professionals globally have begun the controversial campaign to vaccinate large swathes of their respective populations with various experimental medical products. The vanguard of the mainstream pro-vax extremists have been busy enacting mass censorship tactics and committing blatant acts of digital book burning on a scale never before seen in the internet era. So-called “trusted sources” have become indistinguishable from the state-run media apparatus of your bog-standard dictatorship with the usual MSM outlets working non-stop to skew any information that threatens their hyper-aggressive official narrative. Throughout 2020, our basic civil liberties have been quickly stripped away by countless unelected officials from a wide array of unaccountable global power structures, all of them connected to a small group of elites who are sitting aloft the COVID-19 money train and using the heavily exaggerated epidemic to achieve their own long term goals.
Any useful data, scientific paper, or other credible research contradicting the official narrative is being purposely hidden from view. Too many uncomfortable, yet ultimately necessary, questions for vaccine companies such as Moderna, AstraZeneca, Pfizer, and their many collaborators, are being heavily censored by those pushing their own various COVID-related agendas. The promised “war on truth” is in full swing throughout all nations globally and their respective state media machines are nearly all towing their official government lines. Mainstream talk shows and podcasts worldwide are also in lockstep, and have often been caught publicly guilt-tripping their easily swayed audiences to help push them deeper into queues for mass medical trials for vaccines and other products that lack research studies on their long term effects. This inconvenient lack of completed research will not stop the money men from pumping this milky white liquid into the arms of hundreds of millions of people worldwide.
At this point in the process, the medical professionals who are administering these heavily rushed vaccines are being given the opportunity to defer responsibility and accountability for their actions to the government’s vaccine-related guidance. As the Stanley Milgram experiments have proven, when the option to defer responsibility is present, then roughly 65% of participants will follow the orders they have received regardless of the risk to their subjects. In 1974, Stanley Milgram detailed the behaviour of his participants in his famous study and suggested that people have two basic states of behaviour when they are in a social situation: “The autonomous state”, where people direct their own actions and ultimately take responsibility for the results of those actions and “the agentic state”, where people allow others to direct their actions and then pass off the responsibility for the consequences to the person giving orders, in essence acting as agents of another person’s will.
The majority of the people who are injecting these experimental drugs into their trusting patients are not likely to question the official guidance, as the overwhelming majority will often simply be in an agentic state. Thus, it should be in the best interest of anyone thinking of receiving an mRNA vaccine to first study the guidance offered by the various government sources. And, when one does study the official guidance given to healthcare professionals, one will find many different glaring contradictions and shocking admissions.
While all official bodies are attacking any inconvenient fact as misinformation, they are all busy defrauding the global population with their own misinformation campaigns that surely would have inspired awe in the likes of Joseph Stalin. So, let’s study their own words and examine the NHS guidance given to the medical professionals in the UK for the administration of the recently approved Pfizer-BioNTech vaccine.
An Introduction to Reg 174 Information for UK Healthcare Professionals (#1-4)
The short ten page official guidance being given to UK healthcare professionals contains many interesting admissions. In fact, the document, released in early December 2020 to accompany the vaccine rollout, appears to advise healthcare practitioners not to risk giving the experimental injection to the majority of the people who are due to receive the vaccine, particularly “prioritized” populations. Those in charge are pushing to vaccinate as much of the population as possible, before any critical public questions can be asked and answered, a situation that has left the safety and ethics of the vaccination campaign questionable at best and inhumane at worst.
In going through the Reg 174 document, it becomes very clear that there are many issues and recommendations that are being hidden from the general public. Here are ten of the most notable causes for concern contained within the official UK guidance document.
The authorisation to produce and supply this experimental vaccine in the UK was given by the UK Department of Health and Social Care, led by Matt Hancock – the UK Secretary of Health, and also by the Medicines & Healthcare products Regulatory Agency (MHRA). While the MHRA is part funded by the Department of Health and Social Care for the regulation of medical devices, the costs of medicine regulations are met through fees paid by the pharmaceutical industry. The agency’s financial reliance on Big Pharma has led to suggestions by some Members of the UK Parliament that the MHRA is not actually independent. Being in associated roles at the MHRA since 1985, June Raine was officially appointed as CEO in September 2019 and had previously been the Director of Vigilance and Risk Management in the Medicines Division.
2. The official Phase III safety trials will not be completed until 2023
Section 1 of the medical guidance clearly states that this vaccine guidance refers specifically to the “Pfizer/BioNTech COVID-19 mRNA Vaccine BNT162b2 concentrate for solution for injection.” On 2 December 2020, the MHRA became the first medicines regulator in history to approve an mRNA vaccine for human use, granting emergency authorisation for BioNTech and Pfizer’s BNT162b2 COVID-19 vaccine for widespread use only a week after its first Phase III eight-week trial had finished. However, the Phase III trials for BNT162b2 will not actually be fully completed until January 2023 meaning that, if you’re ready to take the vaccine now, then you should be informed that the safety trials for these experimental vaccines have at least two more years before the results are in. Regardless of that fact, Raine told reporters “no corners have been cut in approving it” and that “the benefits outweigh any risk”.
3. Will you be truly “protected” from COVID-19?
The official guidance clearly states that individuals may not be protected until at least 7 days after their second dose of the vaccine. This fact has again been ignored by various reckless pro-vax media campaigns where powerful elites such as Tony Blair have contradicted this specific recommendation, suggesting recently in an interview that people should only be given a single dose of any vaccine. Mr Blair told BBC Radio 4’s Today programme that “Does the first dose give you substantial immunity, and by that I mean over 50 percent effectiveness? If it does, there is a very strong case for not, as it were, holding back doses of the vaccine.” Blair, writing in the Independent, stated that the current vaccination strategy needed to be “altered and radically accelerated”. In responding to Blair’s call for radical acceleration, Professor Wendy Barclay, chair of virology at Imperial College London and member of the UK government’s NERVTAG, said: “I think that the issue with [Mr Blair’s suggestion] is that the vaccine is on the basis of being given in two doses, and the efficacy is on that basis.” Barclay went on to point out that “To change at that point, one would have to see a lot more analysis coming out from perhaps the clinical trial data.”
It is very important to pay attention to the wording of Reg 174 because the Pfizer vaccine purportedly boosts the immune system, rather than stopping the transmission of the virus. This would suggest that you will not be fully “protected” from COVID-19 and that you will still be able to catch the virus and could still suffer complications. The official guidance also states that “Immunocompromised persons, including individuals receiving immunosuppressant therapy, may have a diminished immune response to the vaccine,” with the guidance admitting “No data are available about concomitant use of Immunosuppressants.”
Reg 174 goes on to make this most pertinent of points when it states “As with any vaccine, vaccination with COVID-19 mRNA Vaccine BNT162b2 may not protect all vaccine recipients.” The guidance also states clearly that “administration of COVID-19 mRNA Vaccine BNT162b2 should be postponed in individuals suffering from acute severe febrile illness and that individuals receiving anticoagulant therapy or those with a bleeding disorder that would contraindicate intramuscular injection, should not be given the vaccine unless the potential benefit clearly outweighs the risk.”
4. The complicated multistage dilution and thawing process of the vaccine vials opens the major possibility of human error
In investigating the official instructions for the vaccine’s administration, we can clearly see that there are plenty of opportunities for potential human error. Section 2 of this document describes the distributed vaccine as coming in “a multidose vial and must be diluted before use.” Confirming that each vial contains 0.45 ml (which equates to 5 doses of 30 micrograms) of BNT162b2 RNA embedded in lipid nanoparticles. The delicate preparation process will be repeated 100s of millions of times globally and the multidose vial will be stored frozen and must be thawed prior to dilution. The guidance describes the process for preparing the frozen vials stating that they should be transferred to temperatures of between 2 °C to 8 °C to thaw or, alternatively, the frozen vials may also be thawed for 30 minutes at temperatures up to 25 °C for immediate use. Once thawed, the undiluted vaccine can be stored for up to 5 days at 2 °C to 8 °C, and up to 2 hours at temperatures up to 25 °C. The thawed vial must then come to room temperature and be gently inverted 10 times prior to dilution.

Some of the featured diagrams and instructions found in Reg 174
The complicated thawing and dilution process will obviously leave room for individual error. Healthcare practitioners are also warned not to shake the vials and instead to gently turn them 10 times. Prior to dilution, the vaccine should present as an off-white solution with no particulates visible. The guidance states that you must discard the vaccine if particulates or discolouration are present. The thawed vaccine must be diluted in its original vial with 1.8 mL sodium chloride 9 mg/mL (0.9%) solution for injection, using a 21 gauge or narrower needle and aseptic techniques and this complex, multistage process isn’t completed there.
The healthcare professional should then equalise vial pressure before removing the needle from the vial by withdrawing 1.8 mL of air into the empty diluent syringe. Then they should gently invert the diluted solution 10 times, again being careful not to shake the solution. The official guidance continues: “The diluted vials should be marked with the dilution date and time and stored between 2 °C to 25 °C. After dilution, the vial contains 5 doses of 0.3 mL.” The healthcare professionals are then told to “withdraw the required 0.3 mL dose of diluted vaccine using a sterile needle and syringe and discard any unused vaccine within 6 hours after dilution.”
The instructions must be followed precisely to safely administer the mRNA vaccine; there are no data available on potential consequences for the vaccine recipient if anything goes wrong during this tedious and complex multistage process. On 19 December 2020, video emerged of an official drive-thru vaccination hub which had begun operating out of a car park of Hyde Leisure Centre in Greater Manchester. The video in question, shared by No Comment TV on YouTube, shows people being vaccinated outdoors at Hyde Leisure Centre by gloveless staff and in less than sterile conditions. In an article in the Manchester Evening News four days prior to the videos release the local news site stated that “The first batch of the Pfizer/BioNTech vaccine arrives in the borough on Tuesday, with vaccinations starting at Hyde Leisure Centre on Wednesday, December 15.”
No Data Available (#5-10)
When reading Reg 174, you will soon notice a recurring theme throughout the document. The guidance clearly states on multiple occasions that there are no data available concerning some of the most important questions surrounding the mRNA vaccine. As previously noted, the actual Phase III section of the safety trials will not be completed until January 2023, meaning that two years of trials are still to be run before the vaccine can be confirmed as safe, effective and ethical.
5. The safety and efficacy of COVID-19 mRNA Vaccine BNT162b2 in children under 16 years of age have not yet been established
Although the guidance states that the safety and efficacy of the COVID-19 vaccine has not been established in children, it doesn’t mean that children have not been included within the studies. In fact, in the official Pfizer study entitled “Protocol C4591001”, one of the two main study groups included children as young as 12 years old. The inclusion of children in trials but not the guidance raises the important question, why were children included in the trial? If the vaccine is not to be given to those under the age of 16 years old, then why include children as young as 12 in the trials for an experimental vaccine technology never before authorised for use in humans?
The mainstream media, instead of raising concerns about the involvement of children in the Pfizer clinical trials, have been fully supportive of the move to test experimental pharmaceuticals on minors. CNN reported on children as young as 12 being involved in trials in an October 2020 article entitled “This 12-year-old is happy to be testing a Covid-19 vaccine” while Microsoft News recently announced that “China begins Covid test trials on children as young as age three.”
6. No data are available on the use of COVID-19 mRNA Vaccine BNT162b2 in persons that have previously received a full or partial vaccine series with another COVID-19 vaccine
We are currently witnessing the very first of many tailor-made vaccines being rolled out for general use, so don’t expect the COVID-19 jabs to be the only vaccines coming our way. With a 20 to 1 return on investment on many of these new technologies, most pharmaceutical giants will surely be lobbying governments across the globe for the next “necessary” vaccination program. The idea of multiple COVID-19 vaccinations throughout the year is already being presented as a very possible outcome for the future of humanity. Yet, no studies have been completed showing the risk of taking different types of vaccines. There have also been suggestions that people will have to have the same vaccine that they had previously taken every six months or so. This will leave Astrazeneca, Pfizer and Moderna picking up repeat vaccine contracts worth billions in secured future revenue before there are any real data on the results of the vaccines.
7. No interaction studies have been performed and there are no, or a limited amount of, data from the use of COVID-19 mRNA Vaccine BNT162b2
Admissions like these should be a cause for concern for anybody reading the official guidance. While officials and carefully chosen “trusted sources” are telling you that “no corners have been cut” in the race to approve these vaccines, it is also true that no full length studies have been completed either. These two facts are juxtaposed and obviously contradict the official narrative that is being thrust upon the general public by all of those involved.
It is clear that the officials have no real data on what will happen next and that there is a tsunami of ethical questions that are not being answered. In the absence of data, there will be speculation.
8. It is unknown whether COVID-19 mRNA Vaccine BNT162b2 is excreted in human milk and It is unknown whether COVID-19 mRNA Vaccine BNT162b2 has an impact on fertility
It is vital to note the potential dangers posed by the BNT162b2 to unborn and newborn babies as well as the reproductive organs in general. There are so many parts of the Pfizer/BioNTech clinical trials that have not yet been completed. Dr. Peter Klatsky, the Director of Fertility Preservation at the Bay Area’s Spring Fertility, talking about the coming animal trials which are to be performed over the coming months was quoted in SFGate as saying, “It will reassure me an awful lot if the protein expression is not seen on the placenta. That the mRNA isn’t making it to the placenta in animals,” he said. “I don’t expect to see any.” The article goes on to explain that it will be about another 9 months until the data has been collected and analyzed.

Section 4.6 of the official guidance recommends pregnant women should not recieve the BNT162b2 vaccine
Big names in mainstream media have also been caught recklessly promoting the vaccine to pregnant women, such as Karen Weintraub writing for USA Today, whose recent article quickly states, “Although there are very little data on how pregnant and nursing mothers will respond to a COVID-19 vaccine, professional organizations and individual doctors say the benefits are very likely to outweigh the risks.” Even though the clinical trials intentionally excluded pregnant women, Weintraub went on to state that “23 women in the Pfizer-BioNTech trial and 13 in Moderna’s became pregnant during the trial.”
While the UK’s official guidance is left sounding ambiguous, on the European continent, the European Medicines Agency (EMA) states that “the Pfizer vaccine should be considered on a case by case basis for pregnant women”, but they also reserve the right to alter the guidance if more data becomes available. It seems there is no longer any erring on the side of caution with some regulators when it comes to the COVID-19 vaccinations.
9. Non-clinical data reveal no special hazard for humans based on a conventional study of repeat dose toxicity but animal studies into potential toxicity to reproduction and development have not been completed
Animal studies have not been completed and, as referred to in the previous section, the data on those animal trials will not be available for another 9 months. It is, of course, a very rare decision to approve an experimental medical technology before any animal studies have been completed. This should be a great cause for concern for any free thinking man or woman. The fact that they have had to use what they refer to as “non-clinical” data in these studies is also in conflict with the idea that the trials were conducted to the highest professional standard. The document also fails to clearly define what non-clinical data actually means.
10. In the absence of compatibility studies, this medicinal product must not be mixed with other medicinal products
Possibly the most fascinating admission in the entire document is the absence of any compatibility studies when somebody is given the vaccine while on any other medication or medical treatment. The guidance clearly states “this medicinal product should not be mixed with other medical products.” This completely jaw dropping sentence will lead many to assume that if you are on any medication at all, then you shouldn’t be given the vaccine. Whether this refers to the mixing of other medical properties directly together with the vaccine, or simultaneous dosing of any other medical product is unclear from the official guidance.
The Mail Online and The Guardian reported in 2019 that a staggering 1 in 4 people in England – nearly 12 million people – were taking what was described as “addictive” prescription medicines such as antidepressants, sleeping pills and opioid painkillers, saying that “the NHS must take action”. Those statistics throw into question the mass rollout of a vaccination with no compatability studies. This makes the fact that elderly care home residents, followed by those aged over 80, will be the first to recieve the experimental Pfizer vaccine an extremely risky strategy. Also in 2019, Age UK reported that nearly 2 million older people were on more that 7 prescription medicines and were at “risk of side effects that are severe in some cases, and occasionally even life threatening.” This worrying issue has been barely reported by the “trusted news sources”.
A Conclusive Lack of Real Data
After examining the official guidance, one fact becomes glaringly obvious — there is little to no data on the official Pfizer vaccine in key areas. In the clinical trials, children as young as 12 years old were used as unnecessary guinea pigs. There also wasn’t enough care taken to avoid pregnant women being involved in the initial clinical trials and under the cover of unyielding and uneducated mainstream propaganda, the safety of some of the most vulnerable people involved in the vaccine trials have been ignored by Pfizer and the politicians who have successfully pushed for the public vaccination campaign to essentially replace mass clinical trials. The stage has been set for a potential disaster on an unimaginable scale. It isn’t only the participants of the trials who are risking their health for the sake of big pharmaceutical companies’ hyperinflated profit margin, but it is also the medical professionals who could be risking their futures by collaborating in these risky experimental trials, which will certainly see many people dead and irreversibly injured.
In one section of Reg 174, the Big Pharma giant lays out the risk to people’s health from the Pfizer/BioNTech vaccine. The most common adverse reaction in participants 16 years of age and older was pain at the injection site, which affected a massive 80% of those taking part in the Pfizer trials. Fatigue came a close second with 60% of trial participants becoming sluggish and tired. Half of those involved in the studies suffered from a headache as the experimental vaccine went to work while myalgia was experienced by 30% of vaccine recipients, though the results do not indicate whether the myalgia was acute (short-term) or chronic (long-term). Almost a third of participants came down with chills, while just under 1 in 5 people suffered from arthralgia (joint pain) and 1 in 10 from pyrexia (increased body temperature).
Adverse reactions reported in clinical trials are listed in the study in decreasing order of frequency and seriousness. Just under 1 in 10 people who take the vaccine will suffer from the very common and common adverse reactions referred to in the latter paragraph, such as headaches, myalgia and chills, but the more serious issues are classified as uncommon – including Lymphadenopathy (which causes swollen or enlarged lymph nodes) and nervous system disorders – which may affect up to 1 in 100 people. Rare adverse reactions that could affect up to 1 in 1000 people and very rare adverse reactions that would affect less than 1 in 10,000 of the vaccine recipients were not included in Pfizer’s self-reported safety information. It has obviously been decided that this information should be kept out of the public domain as much as possible to avoid any further vaccine hesitancy.
Not only does the official guidance actively hide the types of rare and very rare adverse effects, but they have also been leaving out some of the adverse reactions reported during the clinical trials. As I write this, the Reg 174 guidance for healthcare professionals is on version 10.1 of the document and, since its release, they have yet to admit to the potential of a certain uncommon adverse reaction to the vaccine being a specific nervous system disorder. Structural nervous system disorders include brain or spinal cord injury, Bell’s palsy, cervical spondylosis, carpal tunnel syndrome, brain or spinal cord tumors, peripheral neuropathy, and Guillain-Barré syndrome. However, previous versions of the guidance gives no clue as to what type of nervous system disorders they were referring to. However, recent articles in the USA Today, heavily promoted by the Microsoft Network, suggested that the Bell’s palsy some people came down with in the vaccine trials wasn’t related to the Pfizer jab. The article states that on Dec. 10, the FDA’s Center for Biologics Evaluation and Research held the 162nd meeting of the Vaccines and Related Biological Products Advisory Committee to discuss the emergency use authorization of the Pfizer-BioNTech COVID-19 vaccine. The USA Today piece even goes on to admit that , “a 53-page briefing noted that there had been four cases of Bell’s palsy among the vaccinated group and none among the placebo group.”

Bell’s palsy causes drooping facial muscles similar to the effects of a stroke, image source PTHealth.com
Even though Miriam Fauzia, who wrote the USA Today piece, claims that the Bell’s palsy was not related to the experimental Pfizer vaccine, the 53-page briefing she sources clearly states, “Among non-serious unsolicited adverse events, there was a numerical imbalance of four cases of Bell’s palsy in the vaccine group compared with no cases in the placebo group, though the four cases in the vaccine group do not represent a frequency above that expected in the general population.” While it is true that 1 to 4 people in 10,000 will develop Bell’s palsy within the general population, it should be noted that the 4 cases in the vaccine trials and none in the placebo group makes for a statistical anomoly that must be examined more thoroughly. Instead, the mainstream media moved quickly to discredit the Bell’s palsy links to the Pfizer vaccine using various misleading tactics to achieve their aims.
Many mainstream outlets were caught spouting the same misleading information with articles entitled “Why you shouldn’t worry about a connection between Bell’s palsy and COVID-19 vaccines,” from Business Insider and a Reuters article from 14 December 2020 entitled, “Fact check: Photo does not show three recipients of Pfizer’s COVID-19 vaccine that developed Bell’s palsy.”
In the case of the Reuters article, which is described as written by “Reuters Staff” rather than a specific journalist, the focus was not on the four Pfizer clinical trial participants who developed Bell’s palsy but instead the article discredits a random post on social media of three people with Bell’s palsy unconnected to the Pfizer vaccine. These type of misinforming mainstream media articles are commonly found to be using obvious fallacies to mislead their readership and with no individual taking responsibility for writing the misinforming piece, a trick repeated by many other media companies complicit with the official narrative. The Reuters article even goes on to admit that: “According to the FDA’s briefing document dated December 10, Bell’s palsy was reported in four vaccine participants and none in the placebo group, out of the 44,000 total participants of the late-stage vaccine trial.” However, the title of the Reuters article would mislead even some of the most keen eyed observers.
The mainstream media has been creating a flood of misleading stories, but it appears as though they have been given carte blanche to continue to do so, probably because they are sticking so tightly to the official narrative. It’s a narrative that is thick with irony, for it is the “trusted sources” who are being caught systematically misleading the general population again and again while also declaring a propaganda war against “fake news”.
The official guidance noted in Reg 174 doesn’t only highlight the serious lack of real data gained from Pfizer’s clinical trials for its Covid-19 vaccine so far, but it also exposes the wealthy medical professionals involved in these experimental vaccine development programs as complacent, reckless and very naive. It’s no secret that children are, more often than not, incapable of giving informed legal consent for such a risky and unethical enterprise. But the pro-vax extremists are using every tactic to coerce and manipulate children and their guardians into becoming human guinea pigs for Big Pharma. Pregnant women are also treated as acceptable collateral damage to advance the new science of gene, mRNA and DNA manipulation, a science and technology that pushes a sinister transhumanist agenda.
Don’t be fooled by the carefully worded vacuous celebrities, self-serving politicians, Big Pharma, and the mainstream medias authoritarian style misinformation campaigns. Keep your humanity intact and read their own words. The government guidance to healthcare professionals clearly states on multiple occasions that there are “no data available”.
Johnny Vedmore is a completely independent investigative journalist and musician from Cardiff, Wales. His work aims to expose the powerful people who are overlooked by other journalists and bring new information to his readers. If you require help, or have a tip for Johnny, then get in touch via johnnyvedmore.com or by reaching out to johnnyvedmore@gmail.com
Major Covid Vaccine Glitch Emerges: Most Europeans, Including Hospital Staff, Refuse To Take It
By Tyler Durden | Zero Hedge | December 27, 2020
All is not going according to plan in the biggest global rollout of what is arguably the most important vaccine in a century, and it is not just growing US mistrust in the covid injection effort that was rolled out in record time: an unexpected spike in allergic reactions to the Pfizer/BioNTech vaccine (and now, Moderna too) may prove catastrophic to widespread acceptance unless scientists can figure out what is causing it after the FDA’s rushed approval, and is also why as we reported yesterday, scientists are scrambling to identify the potential culprit causing the allergic reactions.
Making matters worse, Europe rolled out a huge COVID-19 vaccination drive on Sunday to try to rein in the coronavirus pandemic but even more Europeans than American are sceptical about the speed at which the vaccines have been tested and approved and reluctant to have the shot.
While the European Union has secured contracts [with] drugmakers including Pfizer, Moderna and AstraZeneca, for a total of more than two billion doses and has set a goal for all adults to be inoculated next year, this is looking increasingly like a pipe dream: according to recent surveys, the local population has expressed “high levels of hesitancy” towards inoculation in countries from France to Poland, with many used to vaccines taking decades to develop, not just months.
“I don’t think there’s a vaccine in history that has been tested so quickly,” Ireneusz Sikorski, 41, said as he stepped out of a church in central Warsaw with his two children.
“I am not saying vaccination shouldn’t be taking place. But I am not going to test an unverified vaccine on my children, or on myself.”
Smart: why take the risk of getting vaccinated when others will do it, resulting in the same outcome.
Surveys in Poland, where distrust in public institutions runs deep, show that fewer than 40% of people planning to get vaccinated. Worse, according to Reuters on Sunday, only half the medical staff in a Warsaw hospital where the country’s first shot was administered had signed up. And if the doctors don’t trust the vaccine, one can be certain that the broader population will refuse to take it.
The situation is similar in Spain, one of Europe’s hardest-hit countries, where 28-year-old singer and music composer German summarizes the skepticism of a broad range of the population, and plans to wait for now.
“No one close to me has had it (COVID-19). I’m obviously not saying it doesn’t exist because lots of people have died of it, but for now I wouldn’t have it (the vaccine).”
A Christian Orthodox bishop in Bulgaria, where 45% of people have said they would not get a shot and 40% plan to wait to see if any negative side effects appear – meaning only 15% of the population will actually volunteer for a vaccine in the near future – is in the tiny minority when it comes to taking the vaccine.
“Myself, I am vaccinated against everything I can be,” Bishop Tihon told reporters after getting his shot, standing alongside the health minister in Sofia. He spoke about anxiety over polio before vaccination became available in the 1950s and 1960s.
To be sure, the establishment is pounding the table on why the vaccines are safe despite the record short time in development (even though not even the “scientists” can explain what is behind the spike in vaccine allergic reactions), and claiming that the new technology behind the mRNA vaccine is all one needs to know… when it is precisely this new technology that is sparking the skepticism.
“We’ll look back on the advances made in 2020 and say: ‘That was a moment when science really did make a leap forward’,” said Jeremy Farrar, director of the Oxford University Clinical Research Unit, which is backed by the Wellcome Trust. Oxford also received $750MM from Bill Gates in June in the billionaire’s quest to vaccinate the world against Covid.
Only problem: nobody in Europe seems to care about these “scientific” justifications. Independent pollster Alpha Research said its recent survey suggested that fewer than one in five Bulgarians from the first groups to be offered the vaccine – frontline medics, pharmacists, teachers and nursing home staff – planned to volunteer to get a shot.
An IPSOS survey of 15 countries published on Nov. 5 showed then that 54% of French would have a COVID vaccine if one were available. The figure was 64% in Italy and Spain, 79% in Britain and 87% in China.
Since then things have gone far worse, and a more recent IFOP poll showed that only 41% people in France would take the shot. This means that a vast majority will not.
Not even in Sweden, where public trust in authorities is absurdly and inexplicably high, is there a universal trust in the vaccine, with at least one in three saying they won’t get the shot: “If someone gave me 10 million euro, I wouldn’t take it,” Lisa Renberg, 32, told Reuters on Wednesday.
Meanwhile, in a paradoxical attempt to force more to sign up – not realizing that it will only have the precisely opposite effect – Polish Prime Minister Mateusz Morawiecki urged Poles on Sunday to sign up for vaccination, saying the herd immunity effect depended on them. Critics have accused Warsaw’s “nationalist leaders” of being too accepting of anti-vaccination attitudes in the past in an effort to garner conservative support. Well… let’s check back on said attitude in 10 years and see if perhaps it was the right one.
For now, however, the more European governments pressure their populations to get immunized, the fewer the people who will actually sign up and the worse the vaccine rollout will be, that much we can be 100% sure of.
Developers of Oxford-AstraZeneca Vaccine Tied to UK Eugenics Movement
By Jeremy Loffredo and Whitney Webb |
Unlimited Hangout| December 26, 2020
The developers of the Oxford-AstraZeneca vaccine have previously undisclosed ties to the re-named British Eugenics Society as well as other Eugenics-linked institutions like the Wellcome Trust.
On April 30th, AstraZeneca and Oxford University announced a “landmark agreement” for the development of a COVID-19 vaccine. The agreement involves AstraZeneca overseeing aspects of the development as well as manufacturing and distribution while the Oxford side, via the Jenner Institute and Oxford Vaccine Group, researched and developed the vaccine. Less than a month after this agreement was reached, the Oxford-AstraZeneca partnership was awarded a contract from the US government as part of Operation Warp Speed, the public-private COVID-19 vaccination effort dominated by the US military and US intelligence.
Though the partnership was announced in April, Oxford’s Jenner Institute had already begun developing the COVID-19 vaccine months before, in mid-January. According to a recent BBC report, it was in January that the Jenner Institute first became aware of how serious the pandemic would soon become, when Professor Andrew Pollard, who works for both the Jenner Institute and heads the Oxford Vaccine Group, “shared a taxi with a modeler who worked for the UK’s Scientific Advisory Group for Emergencies.” During the taxi ride, “the scientist told him data suggested there was going to be a pandemic not unlike the 1918 flu.” Due to this sole encounter, we are told, the Jenner Institute then began to pour millions into the early development of a vaccine for COVID-19 well before the scope of the crisis was clear.
For much of 2020, the Oxford-AstraZeneca vaccine was treated as an early front-runner, though its lead would later be marred by scandals related to its clinical trials, including the death of participants, sudden trial pauses, the use of a problematic “placebo” with its own host of side effects and the “unintentional” mis-dosing of some participants that skewed its self-reported efficacy rate.
The significant issues that emerged during trials have provoked little concern from the vaccine’s two lead developers, despite critical attention from even mainstream media of its complications. The lead developer of the Oxford-AstraZeneca vaccine, Adrian Hill, told NBC on December 9th that the experimental vaccine should be approved and distributed to the public before the conclusion of the safety trials, saying,”to wait for the end of the trial would be the middle of next year. That’s too late, this vaccine is effective, available at large scale and easily deployed.”
Sarah Gilbert, the other lead researcher on the vaccine, seemed to believe that pre-mature safety approval was likely, telling the BBC on December 13 that the chances of rolling out the vaccine by the end of the year are “pretty high.” Now, the UK is expected to approve the Oxford-AstraZeneca vaccine shortly after Christmas, with India also set to approve the vaccine next week.
While the controversies surrounding the vaccine’s trials did ultimately undermine its previous frontrunner status, the Oxford-AstraZeneca vaccine remains heavily promoted as the vaccine of choice for the developing world, as it is cheaper and has much less complicated storage requirement than its main competitors, Pfizer and Moderna.
Earlier this month, Dr. Richard Horton, the editor-in-chief of the Lancet medical journal, told CNBC that “The Oxford AstraZeneca vaccine is the vaccine right now that is going to be able to immunize the planet more effectively, more rapidly than any other vaccine we have” in large part because it is a “vaccine that can get to lower middle-income countries.” CNBC also quoted Andrew Baum, global head of health care for Citi Group, as saying that the Oxford-AstraZeneca vaccine “is really the only vaccine that is going to suppress or even eradicate SARS-CoV-2, the virus that causes COVID-19, in the many millions of individuals in the developing world.”
In addition to longstanding claims that the Oxford-AstraZeneca vaccine will be the vaccine of choice for the developing world, this vaccine candidate has also been treated by several outlets in the mainstream and even independent media as “good for people, bad for profits” due to the partnership’s “explicit intention of supplying [the vaccine] around the world on a not-for-profit basis, meaning that the poorest nations on the planet will not have to worry about being shut out of a cure due to lack of funds.”
However, investigation into the vaccine’s developers and the realities of their “no-profit pledge” reveals a very different story than that which has been spun for most of the year by corporate press releases, experts and academics tied to the vaccine and the mainstream press.
For instance, mainstream media has had little, if anything, to say about the role of the vaccine developers’ private company – Vaccitech – in the Oxford-AstraZeneca partnership, a company whose main investors include former top Deutsche Bank executives, Silicon Valley behemoth Google and the UK government. All of them stand to profit from the vaccine alongside the vaccine’s two developers, Adrian Hill and Sarah Gilbert, who retain an estimated 10% stake in the company. Another overlooked point is the plan to dramatically alter the current sales model for the vaccine following the initial wave of its administration, which would see profits soar, especially if the now obvious push to make COVID-19 vaccination an annual affair for the foreseeable future is made reality.
Yet, arguably most troubling of all is the direct link of the vaccine’s lead developers to the Wellcome Trust and, in the case of Adrian Hill, the Galton Institute, two groups with longstanding ties to the UK Eugenics movement. The latter organization, named for the “father of eugenics” Francis Galton, is the re-named UK Eugenics Society, a group notorious for its promotion of racist pseudoscience and efforts to “improve racial stock” by reducing the population of those deemed inferior for over a century.
The ties of Adrian Hill to the Galton Institute should raise obvious concerns given the push to make the Oxford-AstraZeneca vaccine he developed with Gilbert the vaccine of choice for the developing world, particularly countries in Latin America, South and Southeast Asia and Africa, the very areas where the Galton Institute’s past members have called for reducing population growth.
In the final installment of this series on Operation Warp Speed, the US government’s vaccination effort, and race, the Oxford-AstraZeneca vaccine’s ties to Eugenics-linked institutions, the secretive role of Vaccitech, and the myth of the vaccine’s sale being “non-profit” and altruistically motivated are explored in detail.
GlaxoSmithKline and the Jenner Institute
The Edward Jenner Institute for Vaccine Research was initially established in 1995 in Compton in Berkshire as a public-private partnership between the UK government, via the Medical Research Council and the Department of Health, and the pharmaceutical giant GlaxoSmithKline. Following a “review by the [institute’s] sponsors,” it was relaunched in 2005 in Oxford under the leadership of Adrian Hill, who—prior to that appointment—held a senior position at the Wellcome Trust’s Centre for Human Genetics. Hill, the lead developer of the Oxford-AstraZeneca COVID-19 vaccine, still leads a research group at Wellcome aimed at “understand[ing] the genetic basis of susceptibility to different infectious diseases, especially. . . severe respiratory infections,” which conducts most of its studies in Africa. The UK’s Medical Research Council has also become a collaborator with the Wellcome Trust, specifically on vaccine-related initiatives. The Wellcome Trust, discussed at greater length later in this article, was originally created with funding from Henry Wellcome, who founded the company that later became GlaxoSmithKline.
Hill’s partner at the Jenner Institute and the other co-developer of the Oxford COVID-19 vaccine is Sarah Gilbert. Gilbert also hails from the Wellcome Trust, where she was a “program director,” and is a student of Hill’s. Together, Gilbert and Hill have worked to position the institute to be the center of all future vaccination efforts undertaken in response to global pandemics.

Professor Sarah Gilbert at Oxford, Photo by John Cairns
The Jenner Institute’s relocation to Oxford was largely facilitated by the Medical Research Council, which donated £1.25 million between 2005 and 2006, after the decision was made to replace the institute’s original sponsors (GlaxoSmithKline, the Medical Research Council, the Department of Health) with the University of Oxford and the Institute for Animal Health, now called the Pirbright Institute. The involvement of Pirbright meant that the relaunched Jenner Institute became unique in developing vaccines for both humans and livestock.
The relaunched Jenner Institute has come to dominate publicly funded vaccine development in the UK as well as the testing of vaccines produced by the world’s largest pharmaceutical companies via clinical trials and has overseen prominent safety trials for vaccines of high media interest in recent years. Some of the Jenner Institute–conducted trials later drew controversy, such as those using South African infants in 2009 in which seven infants died.
An investigation conducted by the British Medical Journal found that the Hill-led Jenner Institute had, in the South African instance, knowingly misled parents about the negative results of and questionable methods used in animal studies as well the vaccine being known to be ineffective. The vaccine in question, an experimental tuberculosis vaccine developed jointly by Emergent Biosolutions and the Jenner Institute, was scrapped after the controversial study in infants confirmed what was already known, that the vaccine was ineffective. The trial, largely funded by Oxford and the Wellcome Trust, was subsequently praised as “historic” by the BBC. Hill, at the time the study was conducted, had a personal financial stake in the vaccine.
Similar instances of dodgy practices in efficacy trials and the effects of increased dosages have led vaccine experts to criticize the COVID-19 vaccine developed by Hill and Gilbert. Hill and Gilbert hold a considerable financial stake in the Oxford-AstraZeneca COVID-19 vaccine. While the vaccine reportedly has an efficacy of over 90 percent, those figures—often cited in mainstream reports—are self-reported by the vaccine’s developers and manufacturers (i.e., the Oxford team and AstraZeneca), which is significant given that Hill and other Jenner Institute scientists have previously been caught manipulating trial results to benefit a vaccine product in which they were personally invested.
The prominence of the Jenner Institute in vaccine development and testing has largely come through Hill’s additional leadership role at the UK’s Vaccines Network, which chooses what vaccines to develop, how to develop them, and which firms should receive “targeted investments” from the UK government. The Vaccines Network also plays a key role in identifying “what vaccine technologies could play an important role in future outbreaks.” Two of the main backers of the UK’s Vaccines Network are the Wellcome Trust and GlaxoSmithKline.
Unsurprisingly, the Vaccines Network has steered many millions of pounds toward the Hill-run Jenner Institute, with completed projects including a “plug and display” virus-like particle platform for rapid-response vaccination. Also funded by the Vaccines Network were the Jenner Institute’s initial studies of novel chimpanzee adenovirus vaccines for coronavirus (in this case, MERS), the same viral vector used for the Oxford-AstraZeneca vaccine. In addition to the Vaccines Network, the Jenner Institute also coordinates the efforts of the EU’s Vaccines Network equivalent, MultiMalVax.

Professor Adrian Hill at the Jenner Institute, Photo by John Cairns
The Jenner Institute also has a close relationship with GlaxoSmithKline and the Italian biotech Okairos, which was acquired by GlaxoSmithKline in 2014. Soon after it was acquired, Okairos, and its new owner GlaxoSmithKline, became key players in the 2014 experimental Ebola vaccine push, an effort that mirrors the current COVID-19 vaccine development rush in many key ways. The rushed safety trials for that vaccine were overseen by Adrian Hill and the Jenner Institute and funded by the UK government and the Wellcome Trust. GlaxoSmithKline and Okairos are the only firms represented on the Jenner Institute’s Scientific Advisory Board.
The Jenner Institute, along with GlaxoSmithKline-Okairos and a small French biotech called Imaxio, have been developing an experimental malaria vaccine since 2015, with human trials of that vaccine announced on December 12, 2020. Those trials will be conducted on 4,800 children in Africa over the course of 2021, in many of the same countries where Hill’s research group at the Wellcome Center for Human Genetics has been studying genetic susceptibility to several diseases. “A lot more people will die in Africa this year from malaria than will die from Covid,” Hill recently said in regard to the soon-to-begin trials.
Currently, the Jenner Institute is funded by the Jenner Vaccine Foundation, but the foundation’s documents note on several occasions a considerable influx of money from Wellcome Trust Strategic Awards. A “special review panel” from the Wellcome Trust actually lobbied the Jenner Institute to apply for further “strategic core funding” from the trust after visiting the institute and appraising its work. The Jenner Institute frames its funding from Wellcome as the key guidance behind its development decisions, which are made “based on the successful model of Wellcome Trust Strategic Award support.”
The Jenner Institute’s foundation, however, is not the only source of income for its lead researchers. Hill and Gilbert have been working to commercialize many of the institute’s vaccines through their own private company, Vaccitech. Though media reports often describe the vaccine as being a joint effort between AstraZeneca and the University of Oxford, Vaccitech is a key stakeholder in that partnership, given that the vaccine candidate relies on technology developed by Hill and Gilbert and owned by Vaccitech. A deeper look into Vaccitech offers a clue as to why the company’s name has been absent from nearly all media reports on the Oxford-AstraZeneca vaccine, as it demolishes the much-touted claim that the vaccine is “nonprofit” and offered at low cost for charitable reasons.
Vaccitech: doing well by going “good”?
The official reason Sarah Gilbert and Adrian Hill created Vaccitech in 2016 per The Times is because “Oxford’s researchers [are] encouraged to form companies to commercialize their work.” Vaccitech, like other “commercialized” Oxford research enterprises, was spun out of the Jenner Institute via the university’s commercialization arm, Oxford Science Innovations, which is currently Vaccitech’s largest stakeholder at 46 percent. Hill and Gilbert are reported to maintain a 10 percent stake in the company.
The largest investor in Oxford Science Innovations, and by extension one of the largest shareholders in Vaccitech, is Braavos Capital, the venture-capital firm started in 2019 by Andrew Crawford-Brunt, Deutsche Bank’s long-time global head of equity trading at its London branch. Through its stake in Oxford Science Innovations, Braavos owns about 9 percent of Vaccitech.
Prior to COVID-19, Vaccitech’s main focus, especially last year, was the development of a universal vaccine for the flu. Vaccitech’s efforts in this regard were praised by Google, which is also invested in Vaccitech. At the same time, the Bill & Melinda Gates Foundation was funding research to develop a universal flu vaccine, reportedly because the field of influenza vaccinology was not yet able “to design a flu vaccine that would protect broadly against the strains of flu that infect people every winter and those in nature that could emerge to trigger a disruptive and deadly pandemic,” according to a STAT News report from last year. The Gates Foundation effort originally partnered with Google’s cofounder Larry Page and his wife Lucy.
To fully finance Hill and Gilbert’s Vaccitech, and specifically its quest to develop a universal flu vaccine, Oxford Science Innovations sought £600 million from “outside investors,” chief among them the Wellcome Trust and the venture-capital arm of Google, Google Ventures. This means that Google is poised to make a profit from the Oxford-AstraZeneca vaccine at a time when its video platform YouTube has moved to ban COVID-19 vaccine–related content that shines a negative light on COVID-19 vaccines, including the Oxford-AstraZeneca candidate. Other investors in Vaccitech include Sequoia Capital’s Chinese branch and the Chinese pharmaceutical company Fosun Pharma. In addition, the UK government has put an estimated £5 million into the company and is also expected to make a return on the Oxford-AstraZeneca vaccine.
Vaccitech’s homepage showing company co-founders Adrian Hill and Sarah Gilbert. From vaccitech.co.uk
Information on the profit motive behind the Oxford-AstraZeneca vaccine has been muddied due to the extensive media promotion of the claim that Hill and Gilbert will not be collecting royalties on the vaccine and that AstraZeneca is not making a profit off the vaccine. However, this is only true until the pandemic is “officially” declared over, and the virus is labeled a persistent or seasonal condition that will require the mass administration of COVID-19 vaccines at regular intervals and possibly annually. Sky News reported that the determination of when the pandemic is over “will be based on the views of a range of [unspecified] independent bodies.” At that point, both Vaccitech and Oxford will obtain royalties from AstraZeneca’s sales of the vaccine.
Those tied to the vaccine have been at the center of promoting the idea that the COVID-19 vaccine will soon become an annual affair. For instance, in early May, John Bell—an Oxford medical professor and an “architect” of the Oxford-AstraZeneca partnership—told NBC News, “I suspect we may need to have relatively regular vaccinations against coronaviruses going into the future,” adding that the vaccine would likely be needed every year like the flu vaccine. NBC News failed to note that the Oxford-AstraZeneca vaccine in which Bell is involved stands to significantly benefit financially if that does come to pass.
More recently, Bell told The Week that, “should there prove to be a market for regular vaccinations against coronavirus in the future, ‘there is some money to be made.’” Such sentiments have been echoed by Pascal Soriot, the CEO of AstraZeneca, who told Bloomberg last month that the company stood to make a “reasonable profit” once the pandemic was declared over and COVID-19 deemed a seasonal illness requiring regular vaccinations. On this matter, Vaccitech’s CEO, Bill Enright, stated that Vaccitech investors would receive a “big chunk of the royalties from a successful vaccine as well as ‘milestone’ payments” if and when the pandemic is declared over and COVID-19 vaccines become a seasonal event.
Vaccitech, in particular, appears quite certain that this possibility is slated to become reality. For all subsequent iterations of the Oxford-AstraZeneca vaccine, Vaccitech will reacquire a much larger percentage of rights to the vaccine, rights it is currently splitting with Oxford for the first iteration. Sky News has noted that the technology that Vaccitech owns “could drive the second generation of COVID-19 vaccines” and that it “has [already] received £2.3 million of public funding to develop it.”
US government officials such as Anthony Fauci have also signaled that the COVID-19 vaccine will require annual shots. Notably, the government, through Health and Human Service’s BARDA, has poured over $1 billion into the Oxford-AstraZeneca vaccine development. In addition to government officials, several recently published mainstream media reports have claimed that the “expert” consensus “seem[s] to be leaning toward an annual shot like the flu vaccine” with regards to the COVID-19 vaccine. For instance, Dr. Charles Chiu, a professor of infectious diseases at the University of California–San Francisco, recently told Salon, “This may end up being a vaccine that’s not a one-time thing or even a two-time thing. . . it may end up being what we call either a seasonal vaccine, or vaccine that needs to be administered every couple of years.”
Such hints about an annual COVID-19 vaccine from 2021 onward have recently become commonplace from the leading COVID-19 vaccine manufacturers themselves. For instance, on December 13th, Pfizer CEO Albert Bourla was quoted by the Telegraph as saying, “How long this [vaccine] protection lasts is something we don’t know … I think it is a likely scenario that you will need periodical vaccinations.” Pfizer also recently issued a statement that noted that “we don’t know how the virus will change, and we also don’t know how durable the protective effect of any vaccination will be,” adding that its vaccine would be suitable “for repeated administration as booster shots” in the event that the vaccine only induces an immune response for a few months.
Then, this past Tuesday, Moderna released information that suggested immunity from its COVID-19 vaccine would only last several months, with Forbes writing that “the duration of neutralizing antibodies from the Moderna vaccine will be relatively short, potentially less than a year,” an outcome that would favor the push for an annual COVID-19 shot. The developer of the Pfizer COVID-19 vaccine, Ugur Sahin of BioNTech, also stated on Tuesday that “The virus will stay with us for the next 10 years… We need to get used to the fact there’ll be more outbreaks.” He later added that “if the virus becomes more efficient… we might need a higher uptake of the vaccine for life to return to normal,” implying that these regular outbreaks he foresees occurring over the next ten years would be correlated with increased vaccine administration.
Quotes from the developers of the Oxford-AstraZeneca vaccine themselves also point to a pandemic-dominated future and a desire for the crisis to be prolonged so that the vaccine can be widely distributed. Gilbert told the UK Independent in August that she believes COVID-19 is just the beginning and that COVID-like pandemics will become more frequent in the near future. The Jenner Institute vaccine team seems so determined to create the COVID vaccine that, in June, Hill was quoted by the Washington Post in June as stating that he wanted the pandemic to stick around, saying, “We’re in the bizarre position of wanting COVID to stay, at least for a little while. But cases are declining.” He also stated that his team was in “a race against the virus disappearing.”
With the vaccine developers, “medical experts,” government officials, and the CEOs of major vaccine manufacturers all agreeing that a seasonal COVID-19 vaccine is an increasingly likely outcome, it is worth considering a possible ulterior motive regarding the initial “nonprofit” model being used by the Jenner Institute/Vaccitech and AstraZeneca for their joint COVID-19 vaccine.
Given that vaccine guidance in several countries states that each dose of the multidose COVID-19 vaccine must be produced by the same manufacturer as previous doses, the implication is that in the event of a need for periodic COVID-19 vaccine variants, those who initially received the Oxford-AstraZeneca vaccine would likely be required to receive that same “brand” of vaccine seasonally. In other words, those who initially received the Oxford-AstraZeneca vaccine would likely be required, not just to receive a second dose of the same “brand,” but continue receiving that same “brand” of vaccine every year. Notably, no interaction studies have yet been conducted on the interactions between the COVID-19 vaccines and other medications as well as other vaccines.
If this turns out to be the case, it would certainly behoove the Oxford-Vaccitech-AstraZeneca team to want their vaccine to be the most widely used one in the first year in order to guarantee the largest market for subsequent annual COVID-19 vaccines. This could be a possible motive behind the efforts of the Oxford-AstraZeneca partnership “to supply the entire world with the Oxford jab” and to supply the vaccine “to the most vulnerable groups to COVID-19.” This vaccine has already been purchased, even before regulatory approval, by governments around the world, including in Europe, North America, Australia and most Latin American countries.
The Wellcome Trust
Adrian Hill currently holds a senior position at the Wellcome Trust’s Centre for Human Genomics. The Wellcome Trust is a scientific charity based in London, established in 1936 with funds from pharmaceutical magnate Henry Wellcome. As previously mentioned, Wellcome founded the pharmaceutical company that eventually became the industry giant GlaxoSmithKline. Today, the Wellcome Trust has a $25.9 billion endowment and engages in philanthropic endeavors, including funding clinical trials and research.
Hill has been closely tied to Wellcome for decades. In 1994, he participated in the founding of the Wellcome Centre for Human Genetics and was awarded a Wellcome Trust Principal Research Fellowship the following year. He became a Wellcome professor of human genetics in 1996.
The Wellcome Centre for Human Genetics website boasts of the large-scale genetic mapping they’ve conducted in Africa. The center also publishes papers that explore genetic dispositions in relation to male fertility and “reproductive success.” The crossroads between race and genes is important in the center’s work, as an entire working group at the center, the Myers Group, is dedicated to mapping the “genetic impacts of migration events.” The center also funded a paper that argued that so long as eugenics is not coercive it’s an acceptable policy initiative. The paper asks, “Is the fact that an action or policy is a case of eugenics necessarily a reason not to do it?” According to Hill’s page on the Wellcome Trust site, race and genetics have long played a central role in his scientific approach, and his group currently focuses on the role genetics plays in African populations with regard to susceptibility to specific infectious diseases.

The Wellcome Genome Campus, which houses the Wellcome Centre for Human Genetics, is located on the grounds of Hixton Hall, in Cambridgeshire, England.
Of even greater concern, last year Science Mag reported that Wellcome was accused by both a whistleblower and the University of Cape Town South Africa of illegally exploiting hundreds of Africans by “commercializing a gene chip without proper legal agreements and without the consent of the hundreds of African people whose donated DNA was used to develop the chip.” Jantina de Vries, a bioethicist at the University of Cape Town South Africa told the journal that it was “clearly unethical.” Since the controversy, other African institutions and peoples such as the indigenous Nama peoples of Namibia have demanded that Wellcome return the DNA it collected.
The Wellcome Centre regularly co-funds the research and development of vaccines and birth control methods with the Gates Foundation, a foundation that actively and admittedly engages in population and reproductive control in Africa and South Asia by, among other things, prioritizing the wide-spread distribution of injectable long-acting, reversible contraceptives (LARCs). The Wellcome Trust has also directly funded studies that sought to develop methods to “improve uptake” of LARCs in places such as rural Rwanda.
As researcher Jacob Levich wrote in the Palgrave Encyclopedia of Imperialism and Anti-Imperialism, LARCs afford women in the Global South “the least choice possible short of actual sterilization.” Some LARCs can render women infertile for as long as five years, and, as Levich argues, they “leave far more control in the hands of providers, and less in the hands of women, than condoms, oral contraceptives, or traditional methods.”
One example is Norplant, a contraceptive implant manufactured by Schering (now Bayer) that can prevent pregnancy for up to five years. It was taken off the US market in 2002 after more than fifty thousand women filed lawsuits against the company and the doctors who prescribed it. Seventy of those class action suits were related to side effects such as depression, extreme nausea, scalp-hair loss, ovarian cysts, migraines, and excessive bleeding.
Slightly modified and rebranded as Jadelle, the dangerous drug was promoted in Africa by the Gates Foundation in conjunction with USAID and EngenderHealth. Formerly named the Sterilization League for Human Betterment, EngenderHealth’s original mission, inspired by racial eugenics, was to “improve the biological stock of the human race.” Jadelle is not approved by the FDA for use in the United States.
Another scandal-ridden LARC is Pfizer’s Depo-Provera, an injectable contraceptive used in several African and Asian countries. The Gates Foundation and USAID have collaborated to fund this drug’s distribution and introduce it into the health-care systems of countries including Uganda, Burkina Faso, Nigeria, Niger, Senegal, Bangladesh, and India.
Andrew Pollard, director of the Oxford Vaccine Group, where Hill’s Jenner Institute resides, is enmeshed with the Gates Foundation. His employer, the University of Oxford, has received $11 million for vaccine development research from the foundation over the past three years and $208 million in grants over the past decade. In 2016, the Gates Foundation gave $36 million to a team of researchers that was headed by Pollard for vaccine development. In addition, Pollard’s private laboratory is funded by the Gates Foundation. Given this, it should come as no surprise that the Global Alliance for Vaccine Initiative (GAVI), a public-private partnership founded and currently funded by the Bill & Melinda Gates Foundation, plans to distribute the Oxford-AstraZeneca COVID-19 vaccine to low-income, predominantly African and Asian, countries once it’s approved.
The Galton Institute: Eugenics for the Twenty-First Century
Both the Wellcome Trust and Adrian Hill share a close relationship with the most infamous eugenics society in Europe, the British Eugenics Society. The Eugenics Society was renamed the Galton Institute in 1989, a name that pays homage to Sir Francis Galton, the so-called father of eugenics, a field that he often described as the “science of improving racial stock.”
In the case of the Wellcome Trust, the Trust’s library is the guardian of the Eugenics Society historical archives. When the Wellcome Trust first set up its Contemporary Medical Archive Center, the first organizational archive it sought to acquire was tellingly that of the Eugenics Society-Galton Institute. Wellcome’s website describes the Eugenics Society’s original purpose as “to increase public understanding of heredity and to influence parenthood in Britain, with the aim of biological improvement of the nation and mitigation of the burdens deemed to be imposed on society by the genetically ‘unfit’.” It also states the interests of the society’s members “ranged from the biology of heredity, a subject that developed rapidly during the first half of the 20th century, to the provision of birth control methods, artificial insemination, statistics, sex education and family allowances.” Lesley Hall, Wellcome’s senior archivist, has referred to Francis Galton, a racist eugenicist, as an “eminent late nineteenth century polymath” in her discussion of the Eugenics Society archive held at Wellcome.

A poster published by the Eugenics Society-Galton Institute in the 1930S, from the Wellcome Library
Several top governance positions at the former British Eugenics Society, now the Galton Institute, include individuals who originally worked at The Wellcome Trust, including the Galton Institute’s president Turi King. Dr. Elena Bochukova, a current Galton Council Member and Galton lecturer, previously worked under the direction of Adrian Hill at the Wellcome Trust Center for Human Genetics. The Galton Institute’s Senior Genetics Researcher, Dr. Jess Buxton, was previously a ‘genetics researcher’ at the Wellcome Trust and then went on to carry out independent research financed by Wellcome. Her research, which is particularly race oriented, includes creating the first genetic sequence map of a native Nigerian. Moreover, Adrian Hill himself spoke at the Eugenics Society-Galton Institute at the celebration of their 100th anniversary in 2008.
The Galton Institute publishes what they now call the Galton Review, previously titled the Eugenics Review, where various members of the self-proclaimed “learned society” publish papers focused on population issues, genetics, evolutionary biology, and fertility.
A look at early issues of the Eugenics Review shines a light on Galton’s original ambitions. In the 1955 issue titled “The Immigration of Colored People,” an author asks, “What will become of our national character, good workmanship etc. in the course of a few decades if this immigration of negroes and negroids continues unchecked?” The article ends with an appeal to readers to write their parliamentary representatives and urge them that in view of “racial betterment or deterioration” something must be done urgently to “check the present influx of africans and other negroids.”
Today, it appears that the Galton Institute continues to see the immigration of racial minorities into European cities as an unchecked threat. Mike Coleman, an Oxford professor of demographics and a fellow at the institute runs an anti-immigration organization and advocacy group called MigrationWatch—whose mission is to preserve the European culture of the UK by lobbying the government to stem legal immigration and publishing data that supposedly demonstrates the biological and cultural threat of increasing immigration.
A 1961 issue of the Eugenics Review titled “The Impending Crisis” claims the function of the institute’s upcoming conference is “to honor Margaret Sanger” and describes the population crisis as “quantity threatening quality.”
Sanger, known as the “pioneer of the American birth control movement,” was a staunch advocate for promoting “racial betterment” and the key architect of the Negro Project, which she claimed “was established for the benefit of the colored people.” But as medical ethics fellow at Harvard Medical School, Harriet Washington, argues in her book Medical Apartheid, “The Negro Project sought to find the best way to reduce the black population by promoting eugenic principals.” Sanger was an American member of the British Eugenics Society.
Another early member of the Galton Institute was John Harvey Kellogg, prominent business man and eugenicist. Kellogg founded the Race Betterment Foundation and argued that immigrants and nonwhites would damage the American gene pool. Yet another example is Charles Davenport, a scientist known for his collaborative research efforts with eugenicists in Nazi Germany and his contributions to Nazi Germany’s brutal racial policies, who was vice president of the Galton Institute in 1931.
Another more recent member of the Galton Institute was David Weatherall, for whom the Weatherall Institute of Molecular Medicine at Oxford is named. Weatherall was a member of the Galton Institute when it was still named the Eugenics Society and he remained a member until his death in 2018. Weatherall, who was knighted by the British monarch in 1987 for his contributions to science, addressed the Galton Institute on numerous occasions and gave a senior lecture on genetics at the institute in 2014, of which no transcript or video is available. As an Oxford professor, Weatherall was Adrian Hill’s doctoral adviser and eventually his boss when Hill began working at the Weatherall Institute conducting immunogenic research in Africa. A key fixture of the Weatherall Institute of Molecular Medicine since its founding is Walter Bodmer, a former president of the Galton Institute.
While the Galton Institute has attempted to distance itself from its past of promoting racial eugenics with surface-level public relations efforts, it has not stopped family members of the infamous racist from achieving leadership positions at the institute. Emeritus professor of molecular genetics at the Galton Institute and one of its officers is none other than David. J Galton, whose work includes Eugenics: The Future of Human Life in the 21st Century. David Galton has written that the Human Genome Mapping Project, originally dreamt up by Galton’s former president Walter Bodmer, had “enormously increased . . . the scope for eugenics . . . because of the development of a very powerful technology for the manipulation of DNA.”
This new “wider definition of eugenics,” Galton has said, “would cover methods of regulating population numbers as well as improving genome quality by selective artificial insemination by donor, gene therapy or gene manipulation of germ-line cells.” In expanding on this new definition, Galton is neutral as to “whether some methods should be made compulsory by the state, or left entirely to the personal choice of the individual.”
Who gets the safest vaccines?
Considering the degree to which the players and institutions behind the Oxford-AstraZeneca vaccine (including the lead developer) are tied and connected to institutions that have been instrumental in the rise and perpetuation of racial eugenics, it’s concerning that this particular vaccine is being portrayed by scientists and media alike as the COVID-19 vaccine for the poor and the Global South.
The Oxford-AstraZeneca vaccine sells at a fraction of the cost of its COVID-19 vaccine competitors—running between 3 and 5 dollars per dose. Moderna and Pfizer cost 25 to 37 dollars and 20 dollars per dose, respectively. As CNN recently reported, the Oxford-AstraZeneca vaccine will “be far easier to transport and distribute in developing countries than its rivals,” several of which require complicated and costly cold supply chains. When the Thomson Reuters Foundation asked several experts which COVID-19 vaccine could “reach the poorest soonest,” all declared a preference for the Oxford-AstraZeneca candidate.
There is also the added fact that a host of safety issues have come to surround the vaccine. Recently, on November 21, a forty-year-old participant in AstraZeneca’s clinical trial who lives in India sent a legal notice to the Serum Institute of India alleging that the vaccine caused him to develop acute neuroencephalopathy, or brain damage. In the notice, the participant said he “must be compensated, in the least, for all the sufferings that he and his family have undergone and are likely to undergo in the future.”
In response, the Serum Institute claimed the participant’s medical complications are unrelated to the vaccine trial and said it would take “legal action” against the brain-damaged participant for maligning the company’s reputation, seeking damages in excess of $13 million. “This is the first time I have ever heard of a sponsor threatening a trial participant,” Amar Jesani, editor of the Indian Journal of Medical Ethics, said of the incident. The Serum Institute has received at least $18.6 million from the Bill & Melinda Gates Foundation and has a deal with AstraZeneca to manufacture a billion doses of the vaccine.
Other manufacturers chosen by Oxford-AstraZeneca to produce their vaccine are also no strangers to controversy. For instance, their manufacturing partner in China, Shenzhen Kangtai Biological Products, has been at the center of controversy for years, especially after 17 infants died from its Hepatitis B vaccine in 2013. The New York Times cited Yanzhong Huang, a senior fellow for global health at the Council on Foreign Relations, as saying: “Imagine if a similar scandal is reported again in China… It’s not just going to undermine the confidence of the company manufacturing the vaccine, it’s also going to hurt the reputation of AstraZeneca itself and their vaccine, too.”
In another example, the manufacturing partner chosen to produce the vaccine in the US is the scandal-ridden company with ties to the 2001 anthrax attacks, Emergent Biosolutions. Emergent Biosolutions, previously known as BioPort, has a long track record of knowingly selling and marketing products that were never tested for safety and efficacy, including its anthrax vaccine BioThrax and its biodefense product Trobigard. The current head of quality control for Emergent Biosolutions’ lead manufacturing facility in the US has no expertise in pharmaceutical manufacturing and is instead a former high-ranking military intelligence official who operated in Iraq, Afghanistan and beyond.
The issues raised by their decision to partner with manufacturers with dark histories of product safety issues are compounded by the adverse reactions reported in the Oxford-AstraZeneca trials as well as the ways in which those trials have been conducted. In September, AstraZeneca was forced to pause its experimental COVID-19 vaccine trial after a woman in the UK developed a “suspected serious reaction” that the New York Times reported was consistent with transverse myelitis. TM is a neurological disorder characterized by inflammation of the spinal cord, a major element of the central nervous system. It often results in weakness of the limbs, problems emptying the bladder, and paralysis. Patients can become severely disabled, and there is currently no effective cure.
Concern over an association between TM and vaccines is well established. A review of published case studies in 2009 documented thirty-seven cases of TM associated with various vaccines, including hepatitis B, measles-mumps-rubella, diphtheria, pertussis, tetanus, among others in infants, children, and adults. The researchers in Israel noted, “The associations of different vaccines with a single autoimmune phenomenon allude to the idea that a common denominator of these vaccines, such as an adjuvant, might trigger this syndrome.” Even the New York Times article on the AstraZeneca trial pause notes past “speculation” that vaccines might be able to trigger TM.
In July, an Oxford-AstraZeneca trial participant developed symptoms of TM, and the vaccine trial was paused at that time. An “independent panel” ultimately concluded the illness was unrelated to the vaccine, and the trial continued. Yet, as Nikolai Petrovsky from Flinders University told the Australian Broadcasting Corporation, these panels are typically made up of “biostatisticians and also medical representatives from the sponsor drug company running the trial.” Then, in October, a trial participant in Brazil died, though in that case, AstraZeneca suggested that the person was part of the control group and thus hadn’t received the COVID-19 vaccine.
According to Forbes, the AstraZeneca vaccine was ineffective at stopping the spread of coronavirus in their animal trials. All six monkeys injected with AstraZeneca’s COVID-19 vaccine became infected with the disease after being inoculated. All the monkeys were put to death, which means that it will remain unknown whether those monkeys would have suffered other adverse effects.
Another concern is that trial administrators gave the trial control group (for both human and animal trials) Pfizer’s Nimenrix, a meningitis vaccine, as opposed to a saline solution, which is regarded as the gold standard for controls because researchers can be sure the saline solution won’t cause any adverse reactions. Using Pfizer’s meningitis vaccine as the control placebo allows AstraZeneca to downplay any adverse reactions in its COVID-19 vaccine group by showing that the control group suffered adverse reactions as well. “The meningitis vaccine in the AstraZeneca trial is what I would call a ‘fauxcebo,’ a fake control whose real purpose is to disguise or hide injury in the vaccine group,” said Mary Holland, general counsel at Children’s Health Defense.
Eugenics under another name
Despite these safety concerns and clinical trial scandals, close to 160 countries have purchased the Oxford-AstraZeneca vaccine, and now reports are suggesting that India, the country with the second largest population on Earth, is likely to approve this vaccine by next week.
As documented here, while the vaccine may be heralded as “vital for lower-income countries,” the Oxford-AstraZeneca project is no mere philanthropic pursuit. Not only is there a significant profit motive behind the vaccine, but its lead researcher’s connection to the British Eugenics Society adds another level of warranted scrutiny.
For those encountering stories of eugenicists, it’s common to dismiss such activity as that of “conspiracy theories.” However, it’s undeniable that several prominent individuals and institutions that remain active today have clear ties to eugenicist thinking, which was not so taboo just a few decades ago. Unfortunately, this holds true for the individuals and institutions associated with the Oxford-AstraZeneca COVID vaccine, who, as demonstrated in this article, immerse themselves in studies of race science and population control – primarily in Africa while working closely with institutions that have direct and longstanding links to the worst of the Eugenics movement.
As this series has shown, there are many concerns regarding the points where race and the COVID-19 vaccination campaign in the US and abroad intersect, both publicly and privately. Part I of this series raised questions about the policy-shaping role of the Johns Hopkins Center for Health Security, which suggested that the US government make COVID-19 vaccines available to ethnic minorities and the mentally challenged first. Part II explained how in order to allocate COVID-19 vaccines in the US, health agencies are using a program created by Palantir, a company with a record of helping the US agencies target ethnic minorities through immigration policy and racist policing.
Furthermore, there are plans in place to exercise what could reasonably be described as economic coercion to pressure people to “voluntarily” get vaccinated. Such coercion will be obviously be more effective on poor and working communities, meaning communities of color will be disproportionately affected as well.
Considering these facts, and the case for scrutinizing the safety of Oxford-AstraZeneca’s “affordable” vaccine option made above, any harm caused by vaccine allocation policy in the US and beyond is likely to disproportionately affect poor communities, especially communities of color.
As such, the public should take all vaccine rollout policy with a grain of salt, even when they come cloaked in language of inclusion, racial justice, and public health preservation. As the co-founder of the American Eugenics Society (later renamed “Society for the Study of Social Biology”) Frederick Osborn put it in 1968, “Eugenic goals are most likely to be attained under a name other than eugenics.”
Featured Video

Get ready for the big Israeli false flag cyber-attack
or go to
Aletho News Archives – Video-Images
From the Archives
Chocolate Gives Statins a $29 Billion Run For Their Money
By Sayer Ji · GreenMedInfo · April 17, 2012
With the blockbuster cholesterol-lowering class of drugs known as statins being widely promoted for the primary prevention of cardiovascular disease, despite their having over 300 documented adverse health effects (including heart failure!), how does chocolate sound as a viable, heart-friendly alternative?
We already connect amorously with chocolate (to the tune of 6 billion lbs of cocoa consumed annually worldwide), revealing in heart-felt expressions like “I love it,” and “this is to die for!” how comfortable we are with publicly declaring our affection. But did you know that while it makes our emotional hearts sing, it may actually keep our physical hearts happy, alive and ticking longer, as well?
Indeed, back in 2006, researchers found that for elderly men, eating cocoa was inversely associated with blood pressure and 15-year cardiovascular and all-cause mortality. … continue
Blog Roll
 Aletho News
- China warned Trump not to touch Iran’s oil tankers: Larry Johnson
- EU Central Banker Plans To Plant Barren AI Crops Across The Continent
- Macron’s Strategic Autonomy Paradox: France Rearms on Debt and Depends on Foreign Fuel
- Nigel Farage vs Tucker Carlson: Who is right about Hitler and Britain?
- Chocolate Gives Statins a $29 Billion Run For Their Money
- Hypotheses on the collapse of U.S. computer systems
- Discover Iran: North Khorasan’s medicinal plants, spices, and sustainable economic potential
- ‘Stop Putting Drugs in Our Food’: Scientists Link Folic Acid in Food to Rising Rates of Colorectal Cancer
- The 14 Things That Happen to Your Newborn in the First 48 Hours
- JFK’s Forgotten Confrontation with Israel
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- New Study: Modern Temps Are Among The Coldest Of The Last 10,000 Years In East Central Europe
- Germany’s Renewable Energies Lead to 1.4 Billion Euro Electric Power Trade Deficit
- Argentina’s Perito Moreno Glacier Joins Antarctica and Arctic In Defying Doomsday Melt Claims
- New Study: Barents Sea Temperatures Were Warmer And Sea Ice Less Extensive In The 1700s Than Today
- German Authorities Start Initiative To Evaluate Public Register For Climate “Disinformation” Spreaders!
- Zonal Asymmetry of Temperature Change in the Antarctic Circumpolar Current
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean

