CDC REFUSING TO PUBLISH DATA
And:
RT | February 28, 2022
The Russian Defense Ministry has called on Ukrainian civilians to evacuate from Kiev. They can do so by taking the highway towards Vasilkov, a city located 20km southwest of the capital, it said in a statement on Monday, claiming that “this direction is open and safe.”
The ministry added that Russia “only attacks military objects” and insisted that the civilian population will not be at risk.
The call came on Monday as the Ukrainian and Russian delegations are set to start peace talks in Belarus. President Volodymyr Zelensky said in a public address, from Kiev, that he had low expectations for the negotiations. His country does not intend to surrender, he added.
Kiev Mayor Vitali Klitschko told AP on Sunday that the city was fully encircled by Russian troops, but backtracked on the claim later.
The Ukrainian government earlier distributed firearms to civilians, released felons with military experience from prison, and called on the people to prepare firebombs to fight Russian troops.
Russia attacked Ukraine on Thursday, claiming that the country had to be demilitarized and “denazified” to protect the breakaway regions of Donetsk and Lugansk, as well as Russia.
By Kit Knightly | OffGuardian | February 28, 2022
Some of the UK’s “temporary” measures intended to help “deal with the pandemic” are going to be added to future legislation and made permament laws by the spring of this year.
Of course, the truth is that many of the “temporary” Covid measures were already permanent.
As we detailed in fact check in the spring of 2020, although defenders claimed the Coronavirus Act was “temporary” and “only for two years”, this was completely untrue.
To quote ourselves…
Section 89 of the Coronavirus Act 2020 details just how many sections and sub-sections are not subject to the expiry clause. As well as all the “conditions” which, if met, would enable Ministers to waive the expiry clause on certain other sections and regulations.
The list is hugely long: Sections 1, 2, 5, 6, 11, 12, 13, 17, 19(11), 21(7), 59-70, 72-74, 75(1) and 76. As well as parts of Schedules 1, 4, 5, 7, 8 and 10 through 13.
These non-temporary measures included section 11, which guarantees legal indemnity for any public sector employee if they kill or injure a patient whilst attempting to treat Covid.
In total, over a quarter of the “temporary measures” were never actually temporary. And now, as Covid segues into war, the government are seeking to add a few more clauses to the non-temporary list.
It’s all detailed in the government’s “Living with Covid” planning document, released last week.
Among the double-think, back-pedalling and revisionism the document claims that the sections 30, 53, 54 and 55 of the Coronoavirus Act have “enabled revolutions in the delivery of public services” and should be made permanent.
They propose a sixth month extension now, while the sections are copied-and-pasted into legislation expected to pass later this year.
Section 30 gave coroners the right to have an inquest without a jury when Covid19 was a suspected cause of death, why they want this to be permanent I can’t see as yet. Except maybe to further erode the ideas behind the Jury system they’ve been attempting to undermine throughout the “pandemic”. Of course, it could also be amended to include any other disease they wish.
That is expected to be passed into law as part of the Judicial Review and Courts Bill.
Sections 53-55, though, empowered the justice system to hold trials over the internet, via audio or video link. Making this permanent has massive implications for human rights moving forward, not to mention leaving the system wide open for abuse and fakery (pre-recordings, deep fakes or other digital manipulation).
These will be added to the Police, Crime, Sentencing and Courts Bill
It was a terrible precedent to set, and now its here forever. We did warn you it wouldn’t be “just two years”.
By Dr. Malcolm Kendrick | February 27, 2022
My last blog discussed the possibility that mRNA COVID19 vaccines significantly increase the risk of myocarditis. Following this, a fellow doctor reached out to tell me about what has happened to them. They too, had questioned some aspects of the safety and efficacy of the vaccines.
As a result, they have been sent two threatening letters, which are both of the ‘iron fist in a velvet glove’ variety. I asked their permission to reproduce them here. One is from the General Medical Council (GMC). The other from their responsible officer – I shall explain what this title means a bit further on.
Below is the letter from the GMC:
Dear Dr….
The GMC have received several complaints regarding your recent social media posts.
All doctors have a right to express their personal opinion regarding the Covid-19 vaccine, and while the GMC in no way supports this opinion, we don’t consider your comments are sufficiently strong to open a fitness to practice investigation at this stage.
However, we are referring this matter to your Responsible Office for your reflection through the appraisal process.
We ask that you consider what implications this complaint might have for your practise when you are discussing this with your appraiser. We would also like to remind you of GMC guidance, in particular ‘Doctors’ use of social media, and of the requirement of doctors to act with honesty and integrity to justify the public’s trust in them
What we will do now
We will share the complaint with your responsible officer for them to consider in the wider context of your practice and revalidation.
‘The wider context of your practice and revalidation.’ Which means what, exactly? I sometimes wonder if there a special training scheme where you learn to write creepy and threatening phrases that can later be denied as being creepy and threatening? ‘I was only trying to be nice. They just took it the wrong way.’
‘Your children look charming. However, you may want to consider their continued existence on the planet in the wider context of your practice.’
The GMC, as mentioned before, have the powers to investigate complaints made against doctors in the UK, and impose various punishments (they call them sanctions, which sounds far prettier). Ranging from nothing very much to permanent erasure from the medical performers list.
The latter means that you cannot work as a doctor ever again. Anywhere in the world. The GMC will communicate your erasure to other national statutory bodies, upon request. They do it gladly… and speedily.
On the face of it, in this case, the GMC have decided to do nothing. ‘We don’t consider your comments are sufficiently strong to open a fitness to practice investigation at this stage.’
Jolly good.Nothing to see here, move along. Although they add the rider … ‘at this stage.’ Well, what other stages are left, after deciding to take no action? The … I have changed my mind and I am going to have you guillotined, stage?
However, in reality they have not done nothing – have they dear reader? The GMC have decided to refer the complaint to this doctor’s responsible officer. A responsible officer is a doctor who is ‘responsible’ for ensuring that other doctors working in their area have met the necessary requirement for revalidation.
Revalidation is a five-year cycle whereby a doctor has to meet various requirements. A few hundred hours of medical education, keeping up do date with mandatory training. Carrying out an audit, and a patient satisfaction questionnaire, getting sufficient colleague feedback, and suchlike.
There is also a need to have a yearly appraisal. Which is a meeting with an allocated appraiser, to discuss how things have gone. A look through any complaints about you, work you have done, audits that have been completed, actions to take in the next year to improve your practice – a personal development plan. Release of thumbscrews – or a tightening.
If all this is done successfully, over a five-year period, the responsible officer ‘signs you off’ and you are now able to continue work. If not, you are removed from the performers list, and you cannot work as a doctor until you are successfully re-validated. No-one has ever explained to me how you actually do get revalidated. In fact, there is no system in place for this to happen.
If you manage to fulfil the re-validation cycle, and attend appraisals, in theory there can be no grounds for removal. You cannot actually ‘fail’ an appraisal. You simply have to turn up, and ‘reflect’ on your practice. I have never heard of a responsible officer stepping in to remove a doctor from the performers list any time they so wish.
Bearing all that in mind, here is the follow up letter from the responsible officer.
Dear Dr….
I have today received a communication from the GMC regarding an ‘incident that occurred on social media.’ The GMC have advised that they have reviewed the complaint and that it does not meet the threshold for investigation.
However, I understand that you have been asked to consider what implications this complaint may have for your practise and there is a requirement for you to reflect on this matter at your next appraisal meeting.
As your Responsible Officer I have a statutory duty to ensure that any concern or complaint about your practise is responded to and dealt with appropriately.
I would be grateful if you could let me have your views on this issue, by completing the attached form and returning it as a matter of urgency.
Can you also complete the attached Monitoring of Clinical Practise for your file, please.
Your co-operation with this process is vital in order for us to come to an acceptable resolution as soon as possible, minimising impact to your practice and cost in time and money.
If you have any questions regarding this process, please to contact me to discuss further.
Kind regards
Dr X
Responsible Officer for X region.
I love the ‘Kind regards’ sign off. For this is a letter dripping with unspoken menace. Just to highlight one phrase ‘An incident that occurred on social media…’ An ‘incident’. You mean, someone wrote something that someone didn’t like, they then complained about it. This was not an incident, in the sense that anyone would normally choose to use this word.
[I also note that the GMC spells practice, practice. The responsible officer spells it practise – maybe they need to reflect on their spelling between them].
If you look up the word ‘incident’ on the Cambridge Dictionary it gives an example of its use:
‘A youth was seriously injured in a shooting incident on Saturday night.’1
It does not say. ‘Someone wrote a blog post that upset someone, somewhere, for a bit. But it’s alright now, they are looking at pictures of kittens to recover.’
Words. Words, words, words. They can be used in so many different ways. Their true meaning hidden behind layers of sophistry. But we all know what the word ‘incident’ means in this case. Someone was badly damaged by your actions on that day – do not attempt to deny it, comrade.
Then we move on to the real threat. The responsible officer wants to ensure an acceptable resolution, thus … ‘minimising impact to your practise and cost in time and money.’
What the responsible officer here is saying is that I have the powers to stop you practising medicine in the UK. If I find that your answer to this complaint – which was not strong enough to open a fitness to practice investigation by the GMC – does not satisfy me. Indeed (subtext), I do not actually care what answer you give, I may remove you anyway. This will certainly maximise the impact on this doctor’s ‘practise and cost in time and money’.
If you think this is not what is being threatened. Then ask yourself what else it could mean? There is nothing that needs to be ‘resolved’. A complaint has been made, but the GMC didn’t think it was serious enough to take forward. No patient was harmed, no laws broken … no wrecks and nobody drowned, in fact nothing to laugh at, at all. (small prize for who knows where that came from).
At this point you may have begun to allow the thought to enter your mind that the GMC have quite deliberately handed this complaint down to the responsible officer to carry out the required sentence and execution. Whatever the accused doctor says, the responsible officer can simply respond. ‘Sorry, not satisfied with your answer. I am now going to stop you working – for as long as I wish.’ No hearing, no possibility of review, no accountability. Bosh.
In truth I have always known that responsible officers possess this amazing and unrestrained power. I tried, and failed, to stop this happening years ago – when I was on various British Medical Association (BMA) committees. I found it incredible that the legislation in this area was going to hand over, to one individual, the ability to destroy someone’s career, with no regard to anyone else, or anything else.
Yes, we live in a democracy that has created a form of local tyranny.
Tyranny (noun) def: government by a ruler or small group of people who have unlimited power of the people in their country or state and use it unfairly, and cruelly.
You could say that this situation suits the GMC very well … Very well indeed. Because, you see, the GMC has tried to remove other doctors from the medical register for criticising vaccination. [The medical register is not quite the same thing as the performer’s list, but you need to be on both of them to work as a doctor in the UK].
These punishments were quashed in the High Court. Here from a legal firm that works in this area:
‘On Friday, the High Court handed down a judgment quashing the GMC interim order of conditions previously imposed on a GP, Dr Samuel White, as a result of his actions arising from the pandemic. Dr White came to the GMC’s attention as a result of “spreading misinformation and inaccurate details about the Coronavirus and how it is diagnosed and treated”. His comments have included assertions that the COVID-19 vaccine “inserts a code”, masks do “absolutely nothing” and hydroxychloroquine, budesonide inhalers and ivermectin are “safe and proven treatments”.
The interesting point arising from Dr White’s High Court appeal is the technical point on which he won. The High Court found that the Medical Practitioners Tribunal Service (MPTS – the adjudication wing of the GMC) panel made an error of law in not properly considering the test required by section 12(3) of the Human Rights Act 1998 when deciding whether to impose an interim order.’2
As this company also says:
As time goes on, we’re seeing more fitness to practise cases arising from COVID-19-related activities. We’ve previously posted about the Irish GP interim suspended after describing COVID-19 as a hoax and the first UK nurse struck off by the Nursing and Midwifery Council (NMC) as a result of COVID-19 denial activities.
‘COVID denial activities’ – what a deliciously Soviet phrase.
I have to say that I very much enjoyed the lawyers’ assertion that the GMC interim order was quashed on a ‘technical point’. Namely that the GMC had failed to consider the small matter of the Human Rights Act 1998. Riding roughshod over someone’s human rights is now a technical point of law. How quaint.
However, undeterred, the GMC have not been deterred from their vital work in punishing COVID-19 vaccine deniers – to ensure that they can never work again. They have just found another, simpler, far cheaper, and far quicker route to obliterate a doctor’s career. Call the responsible officer. No-one expects the responsible officer.
Who needs time consuming and costly hearings, where you might have to bear in mind the Human Rights act 1998 – and other such woolly liberal nonsense? When you can alert the local ‘tyrant’ to a doctor’s non-comradely Soviet ‘denial’ activities. Sorry, COVID19 ‘denial’ activities.
They will know precisely what to do, and they have the powers to do it. Why on earth did the GMC not think of this of this before? I could have told them about the ridiculous, frightening, and untrammelled powers of a responsible officer, but they never asked me.
Of course, you could argue the following. If the local responsible officer does obliterate someone’s medical career and does this without paying any heed to such things as well, the law, for example, then their actions will be over-turned in court. Well, I certainly hope so, in fact I would expect so. This may act as a deterrent … maybe.
However, during the months, or years, that it takes to get such a case to court, the doctor will be out of work and unable to earn. They will almost certainly end up bankrupt, and their reputation (have been struck off the performers’ list) will lie shattered in the gutter.
As for the responsible officer. Their punishment ‘please don’t do it again,’ would just about cover it. This is very much asymmetric warfare. I can punish you, terribly, but you can do absolutely nothing to me in return.
In the financial world they call this moral hazard. A banker can bankrupt you, and your family, and half the country, making stupid and risky decisions – that will earn them huge short-term bonuses. If, as a result, their bank goes bust, the Government simply bails them out and they keep their job, and their bonus. All gain, no pain.
As a sign off, the responsible officer (washing his hands of any personal responsibility of course) wrote this ‘I have a statutory duty to ensure that any concern or complaint about your practise is responded to and dealt with appropriately.’ Kind regards … Pontius.
However, one thing that has not happened, so far, is to actually take the time and effort to forward a copy of the complaints to the doctor concerned. Still, they must be guilty of something or other. So, it is clearly critical that they respond to these unknown complaints, of some sort or another, in some-way or other. ‘Here is a bottle of whisky, and a revolver…. You know what you must do.’
What a world this has become. I had hoped I would not live to see such a time in this country, but I have.
1: https://dictionary.cambridge.org/dictionary/english/incident
BY JEFFREY A. TUCKER | BROWNSTONE INSTITUTE | FEBRUARY 26, 2022
One day I’m reading an internal memo commissioned by the Democratic Party to provide advice to dealing with Covid policy. The next day I’m reading headlines about how the CDC has drastically altered its advice on how to deal with Covid.
Is there a relationship? At this point, only the hopelessly naive would think otherwise.
Let’s look at the memo produced by Impact Research. Some excerpts:
A few points.
This memo is not epidemiology but politics, most strongly illustrated by the idea that polling should make the difference as to whether a pathogen is pandemic or endemic. The constant incantation of “vaccines” here has nothing to do with the known data: they have nowhere stopped infection or spread, a point which the memo obscures with the line about how they “minimize illness.” They minimize serious outcomes for some strains so long as they last.
From a policy point of view, there are two main features that stand out: Covid is here to stay and “most people in the US will eventually get COVID-19” (thereby hinting at the reality that vaccines are not effective in the way that Biden/Fauci/Walensky promised) and therefore the focus should be on protecting the vulnerable.
There is nothing new about this. It was always true! You can shout “Omicron” all day but it was also true with Alpha and Delta as well. The virus should have been treated rationally the entire time and policies that have wrecked public health should have been off the table from 2020. The memo writers did not cite the Great Barrington Declaration but they might as well have.
As for how the Democrats somehow prevented an economic freefall, the worst economic outcomes are very clearly in Democratic-controlled states that retained restrictions for nearly two years in some places, including keeping schools closed. There is a reason for the mass migration that this has inspired.
If we are looking for thriving economies, look to the states that never closed up or opened earliest: South Dakota, Florida, Texas, Georgia, and so on. So none of this is remotely true but, hey, this is politics, right?, so it doesn’t have to be true.
The real problem that the Democrats need to solve is revealed in this chart:

Now, let us consider the dramatic turnaround at the CDC that came out the very next day. The full PDF is embedded below.
Here are the talking points handed to the director. It’s not just about masking, which is being relaxed. The CDC says there needs to be a dramatic shift away from endless monitoring of cases that are overwhelmingly mild and instead focus only on actual sickness that lands people in the hospital and threatens life. We need to stop obsessing about cases and start looking mainly at “medically significant disease.” The focus should be on “protecting the most vulnerable.”
This makes all of us want to say, shout, scream: THANK YOU!
In order to justify this change, the CDC posts four sets of charts on Covid prevalence during episodes of the pandemic. The last chart illustrates the point that an exclusive focus on controlling the spread is utterly preposterous at this point. Under the old protocols, the whole country should be back in lockdown. It’s unimaginable what attempting this now would cause.
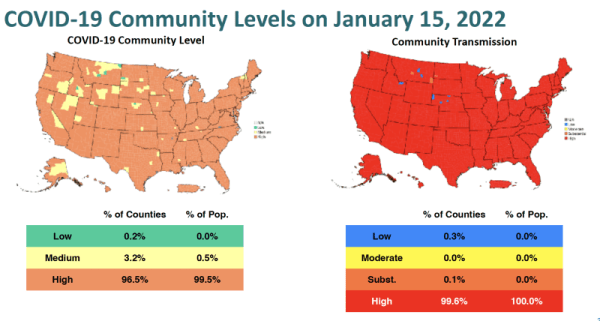
To be sure, all of this is enormously frustrating for those of us engaged in this battle for two years. Instead of focusing on getting sick people well, the CDC experimented with wild guidelines that imagined some kind of society-wide solution that seemed designed to crush the virus while vast amounts of social and economic activity were shut down by law. This necessitated a crushing of freedoms, including of travel, association, commerce, religion, and, eventually even speech.
The CDC nowhere admits this much less apologizes for it. Two years in, the CDC seems to have rediscovered the traditional practice of public health, and has justified this new wisdom based on changed conditions, while never even bothering to claim that its previous measures and guidelines achieved anything along the way.
We’ve seen a massive collapse in public health, economic vitality, and essential rights, while closing schools and wrecking education and so much more, all in the name of virus control, even as the evidence is now overwhelming that the entire enterprise was not only a distraction from what should have happened (therapeutics and protecting the vulnerable) but also an astonishing failure.
Why the change? It had to happen at some point. The entire machinery of lockdowns and mandates were destined to fail. As to the timing of the reversal, it’s hard to resist the speculation that it is entirely political. See the memo above.
Still, there is a worrisome aspect to the CDC’s announcement. They reserve the right to do it all over again. “We want to give people a break from things like mask-wearing, when these metrics are better, and then have the ability to reach for them again should things worsen,” she said.
No one should be satisfied with a politically motivated change in the messaging. We need fundamental regime change to make sure that nothing like this can ever happen again.
Jeffrey A. Tucker is Founder and President of the Brownstone Institute and the author of many thousands of articles in the scholarly and popular press and ten books in 5 languages, most recently Liberty or Lockdown.
The Highwire with Del Bigtree | February 24, 2022
Freedom Convoy USA 2022 Organizer, Kyle Sefcik, went viral this week with his video message to President Biden to end the mandates, and his plan for peaceful protest of the draconian measures.
Convoy updates.
#FreedomConvoyUSA #KyleSefcik #TruckerConvoy #FreedomConvoyUSA2022
See also:
BY IAN MILLER | BROWNSTONE INSTITUTE | FEBRUARY 26, 2022
An infuriatingly consistent aspect of the mainstream media’s COVID coverage was their determination to prematurely credit a country with a wildly successful set of policy interventions.
While there has been no track record of universally accurate predictions or expectations, the desire to claim victory as far back as spring 2020 has led to subsequent embarrassments as trends change.
Naturally, New Zealand is no stranger to such untimely praise, with the BBC in July 2020 doing an in-depth look at how New Zealand became “COVID free.”
Of course, it was because New Zealand “… locked down early and aimed for elimination” and achieved “effective communication and public compliance.”
This is really the whole problem in a nutshell, isn’t it?
Assuming that elimination was possible through effective communication, compliance and early lockdowns ignores the inevitably that COVID will eventually spread throughout the population, whenever you “open up.”
Elimination of COVID throughout the world is and always was impossible, and therefore Fauci’s assertion that COVID could be “eliminated in certain countries” was inane and virtually impossible.
So how successful has New Zealand been in eliminating COVID in the long term through effective communication, public compliance and early lockdowns?
Well. The numbers speak for themselves.
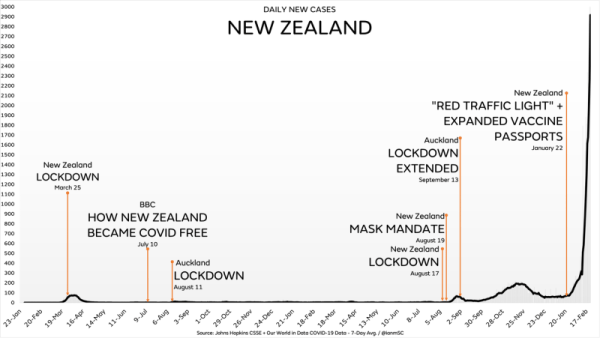
When the BBC wrote the article explaining New Zealand’s remarkable success in eliminating the virus, they were averaging 1.5 cases each day. It’s now 2,918 cases each day.
That’s an increase of nearly 195,000%.
Elimination is a pipe dream.
No matter what policy interventions they’ve added, no matter how many early lockdowns they’ve tried, COVID has not been eliminated.
Remember how New Zealand’s amazing tracking and tracing system allowed them to identify transmission that could have only occurred via aerosols? And recall how all of the pre-pandemic guidance on masking suggested that masks could not stop aerosols? Did that stop New Zealand from using mask mandates to try and continue their elimination goals?
Of course not!
The following are the currently enforced rules on face masks in New Zealand:
We know New Zealanders are complying because the BBC assured us that their success was due to population compliance, but the survey data backs that up as well:
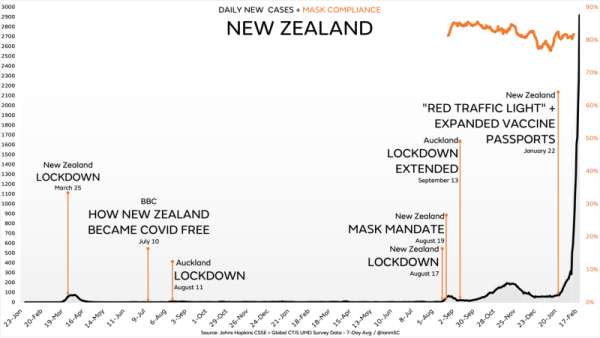
Mask wearing has been consistently high since the mandate came into effect in August, yet cases have exploded anyway.
None of it has mattered.
And this isn’t an insignificant increase. New Zealand’s now reporting more new cases adjusted for population than the United States, and identical numbers to the United Kingdom:
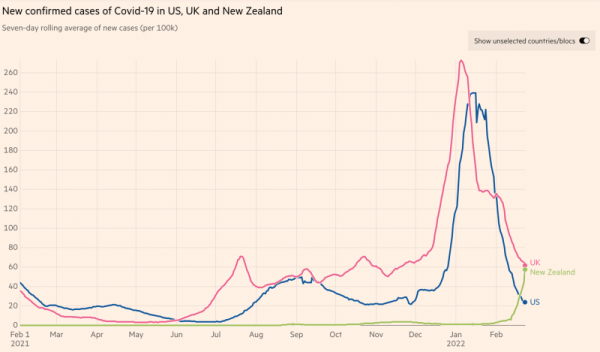
Working perfectly!
Elimination Through Vaccination
In the previously referenced interview, Fauci said that the most successful way to “eliminate” COVID was to reach extraordinary levels of vaccination uptake in the population.
While the Our World in Data download hasn’t been updated in the past week, over 88% of the population had received at least one vaccination dose in New Zealand by February 15th.
The numbers are even more impressive when considering only those over 12 years of age. 95% of everyone over in that demographic has been at least partially vaccinated or booked their appointment. 94% are fully vaccinated:
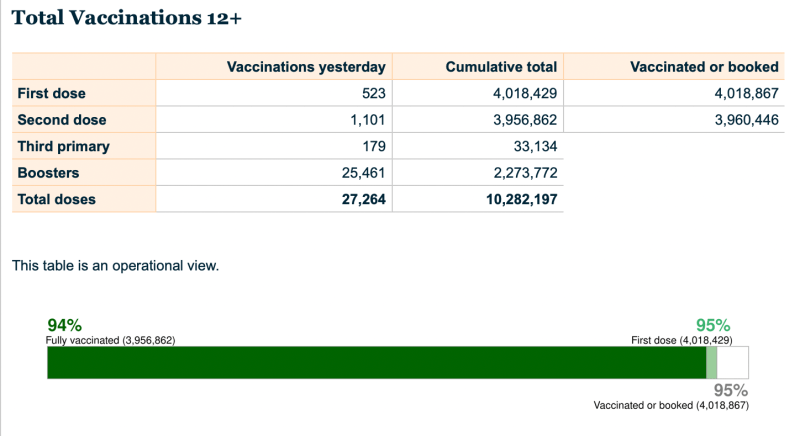
Nearly 2.3 million people over 12 have been given boosters, roughly 53% of that entire population.
Clearly those incredible rates of uptake must have been enough to maintain the “blanket of herd immunity” that Fauci claimed would be achievable with 75-85% of the population vaccinated.
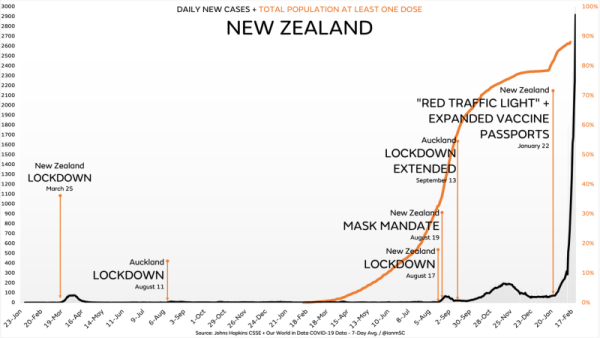
Not exactly!
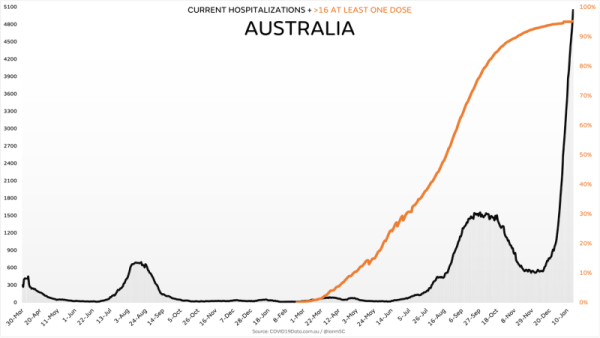
Whenever you reference the dramatic failure of Australia or New Zealand to maintain “zero COVID” lockdowns and “elimination” strategies, adherents to the cult of inaccurate expertise will respond by claiming their goal was only to eliminate cases until widespread vaccination.
By allowing for vaccines to blunt the impact of cases, these countries would prevent surges in hospitalizations. We already saw that this was wildly off in Australia:
But what about New Zealand? Maybe they’ve been able to successfully stave off any surge in severe cases due to their exceptional vaccination rate:
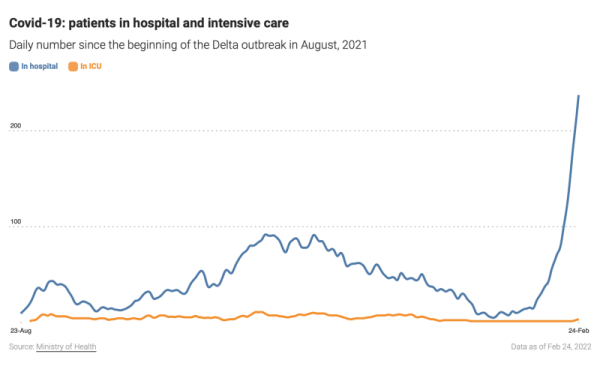
Well. Not exactly.
Hospitalizations have risen dramatically since January and continue to rise significantly each day.
News reports from New Zealand sound like those from any generic location in the US where local doctors report concerns of hospitals being overwhelmed:
Authorities anticipate Omicron will become the predominant Covid-19 variant in New Zealand within just two to four weeks of it being introduced into the community – and hospitals are bracing to be “swamped”.
Dr John Bonning, a frontline emergency department doctor and immediate past president of the Australasian College for Emergency Medicine, said EDs were already under “enormous duress”.
So their elimination strategy did not prevent a dramatic increase in cases, nor a concerning, overwhelming surge of hospitalizations.
And deaths, while thankfully still low, have increased in recent months as well:
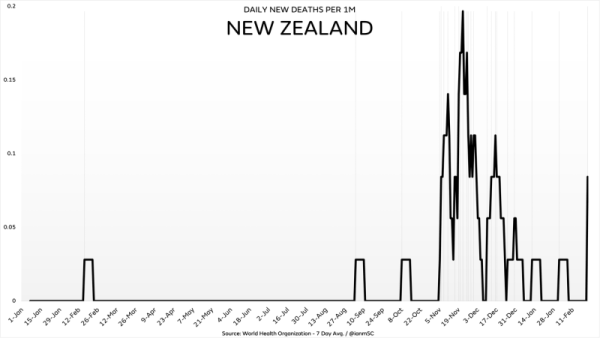
New Zealand’s supposed “elimination” through their zero COVID policy has completely collapsed.
Mask mandates, as their own research indicated, have not prevented surges. Elimination until vaccination has not prevented surges. Zero COVID has been an unmitigated failure, as any rational person would have known and suggested as far back as summer 2020.
They’ve maintained an unearned sense of superiority, exemplified in this quote from the BBC’s story:
He says it is “a bit of a puzzle for us at a distance to understand why” with the UK’s extensive scientific expertise and health care, “you haven’t looked at the evidence and worked out a pattern like New Zealand’s”.
The UK government has previously defended its coronavirus strategy, saying its approach was “being guided by the science.”
That undeserved attitude can no longer be maintained.
The policies that never had the slightest possibility of long term success, the policies that Fauci claimed could be successful in “certain countries,” have turned into yet another example of the delusions of hubris.
While many areas are lifting mandates, they’re doing so without acknowledging the underlying flaws in their strategy. Iceland’s health ministry summed up the inescapable reality of COVID while announcing an end to all restrictions:
“Widespread societal resistance to COVID-19 is the main route out of the epidemic,” the ministry said in a statement, citing infectious disease authorities.
“To achieve this, as many people as possible need to be infected with the virus as the vaccines are not enough, even though they provide good protection against serious illness,” it added.
Until they understand and accept those sentiments, there will always be excuses for politicians and public health officials to bring back their prized, ineffectual interventions.
New Zealand is the latest in a long list of countries to be hailed as showing the world the “right” way to prevent surges; to keep COVID under control.
But as with masks, vaccine passports and “early” lockdowns, zero COVID never had a chance of working — despite the endless media and expert praise.
As always, Eric Feigl-Ding had absolutely no idea what he was talking about:

It is time for a taste of its own medicine
By Vinay Prasad MD MPH | February 26, 2022
Just yesterday, I read that NYC public schools will remove the OUTDOOR mask mandate starting Monday. How Brave!
Let’s reflect on this for a moment. NYC school district has been requiring children wear masks OUTSIDE all this time. Years after we knew the virus almost never spreads outside. During recess when kids play, forced to wear a mask while exerting themselves. Wow!
Whoever made the policy is an idiot. No way around it. They are not fit for policymaking. They abused the power of government to coerce children (at incredibly low risk of bad outcomes) to wear a mask in a setting where the virus simply does not spread. In other words, they participated in something done in the name of public health, which actually made human beings worse off. Worse, they used coercive force to do it.
Post-COVID we need to seriously talk about setting restrictions. But not on people. We need to place restrictions on public health and things done in the name of public health. We cannot allow individuals who are poor at weighing risk and benefit and uncertainty to coerce human beings, disproportionately the young and powerless (waiters/ servers) to participate in interventions that have no data supporting them, for years on end.
Public health be the subject of restrictions; a taste of its own medicine. Some of those restrictions should be placed on governments, but others on private actors who are appealing to public health. Here is what that might look like:
Cal Academy is a museum in Golden Gate Park. Do they have any business nor ability to mandate boosters in adolescents? No, it is absurd. Two senior officials with the FDA— Gruber and Krause- resigned over this decision. Paul Offit and Luciano Boro and others have been publicly critical of boosters for young people, and Cal Academy mandates it? Cal Academy is not qualified to make this decision.
These are just a few examples of where governments or institutions have overreached in the name of public health, but there are many more. Post COVID, the group that needs to face the strongest restrictions is public health itself. We must careful remove the power we have granted public health, which has often been misused.
Vinay Prasad MD MPH is a hematologist-oncologist and Associate Professor in the Department of Epidemiology and Biostatistics at the University of California San Francisco. He runs the VKPrasad lab at UCSF, which studies cancer drugs, health policy, clinical trials and better decision making. He is author of over 300 academic articles, and the books Ending Medical Reversal (2015), and Malignant (2020).
The Naked Emperor’s Newsletter | February 24, 2022
Whilst many countries have been making noises about removing Covid passes, they still remain for a lot of international travel. It has been obvious from the beginning, with the amount of money and effort spent on them, that vaccine passes wouldn’t disappear without a fight.
 Today, this concern has been reinforced with the World Health Organization (WHO) signing a contract with T-Systems (a Deutsche Telecom subsidiary) for the production of a global QR system to make digital vaccination certificates easier to introduce in the future. The press release in TotalTelecom says that the WHO is setting up a gateway to enable QR codes on electronic vaccination certificates to be checked across national borders.
The head of WHO’s Digital Health and Innovation Department, Garrett Mehl said that they would be “supporting member states in building national and regional trust networks and verification technology. The WHO’s gateway service also serves as a bridge between regional systems. It can also be used as part of future vaccination campaigns and home-based records”.
T-Systems have already developed the EU’s Digital Covid Certificates which are used by more than 60 countries already. They also developed the German tracing app which had event check-ins and universal certificate storage. With WHO membership comprising of 194 Member States, this Covid certification scheme looks to be massively expanded.
Furthermore, even if Covid won’t allow them to roll-out their certification scheme, the WHO already states that it wants the system to serve as a standard procedure for other vaccinations such as polio or yellow fever.
Now is not the time to let one’s guard down. Freedoms are being returned with one hand whilst being further curtailed with the other. Instead of celebrating the return of freedoms that should never have been removed in the first place, a continued effort should remain to ensure all restrictions are gone and can never be reinstated in the future. This new global vaccination passport should be the next thing to be scrapped, how every much money it wastes.
By David Charbonneau, Ph.D. | The Defender | February 23, 2022
Before the U.S. Supreme Court last month blocked the Biden administration’s COVID-19 vaccine mandates for large employers and allowed the mandate for healthcare workers to stand, all eyes were on the feds when it came to COVID-related policies.
But state lawmakers also have been busy drafting bills in an effort to shape COVID policies closer to home.
The California Assembly, for example, introduced over the past six months a flurry of bills designed to strengthen vaccination mandates and regulate treatment options for patients.
For example, Sen. Richard Pan (D-Sacramento) last month introduced legislation proposing COVID vaccine mandates for all K-12 students in California schools.
And this month, Assembly Member Evan Low (D-Campbell) introduced legislation (AB 2098) that, according to the Los Angeles Times, would “make it easier for the Medical Board of California to discipline doctors who promote COVID-19 misinformation by classifying it as unprofessional conduct.”
The bill defines “unprofessional conduct” as any action a physician or surgeon takes “to disseminate or promote misinformation or disinformation related to COVID-19, including false or misleading information regarding the nature and risks of the virus, its prevention and treatment; and the development, safety, and effectiveness of COVID-19 vaccines.”
Under the bill, disciplinary action could be brought against a physician for disseminating information that “resulted in an individual declining opportunities for COVID-19 treatment or prevention that was not justified by the individual’s medical history or condition.”
Additionally, doctors could be disciplined for “misinformation or disinformation” that is contradicted by contemporary scientific consensus to an extent where its dissemination constitutes gross negligence” by the physician.
Commenting on the criteria, Dr. Meryl Nass, an expert in epidemiology and vaccine injury and member of the Children’s Health Defense scientific advisory committee, said:
“I think this is clearly an attempt to legislate that the government of California or the Medical Board of California will define what is truth and what is misinformation, and medical providers will have to follow lockstep with that definition.
“This, of course, is the same thing as the Ministry of Truth in George Orwell’s “1984,” and if the California legislature actually votes for this bill, the intent of the action will be to enforce a one and only truth.
“Nowhere does this legislature define what is misinformation and disinformation. They do talk about contemporary scientific consensus but as we know in the last two years, the so-called scientific consensus — or the public health agency consensus — on masks, on vaccination, on boosters, etc. has flip-flopped all over the place. So we have adequate examples that the concept of “contemporary scientific consensus” is basically meaningless in this context.”
Contrary to typical board practice, under AB 2098, physicians could also be disciplined for public speech, including social media posts, unrelated to the actual treatment of patients.
Supporters of Low’s bill insist the legislation does not impinge on doctors’ freedom of speech.
“This isn’t a call for a policing of free speech,” Nick Sawyer, an emergency room doctor who founded a group called No License for Disinformation, told the LA Times. “This is a call for protecting the public against dangerous misinformation, which patients are parroting back to us in our emergency room departments every day.”
Nass disagreed:
“The result is removing options from doctors and patients. And the longer-term consequence is that doctors will become irrelevant if they are not needed to assess each individual’s personal risks and benefits from each type of medical care.
“The government and its partners in the healthcare industries can simply prescribe one-size-fits-all healthcare for everyone.”
Low’s bill, introduced as part of a larger effort by a group of Democratic state legislators to strengthen vaccination laws, set off a contentious debate over how far the state should go in pursuing COVID mandates.
Other COVID-related bills introduced in California include:
Other states pursue efforts to support alternative treatments
In contrast to California, several state legislatures are moving to provide legal support for off-label prescriptions and alternative approaches supported by physicians.
In New Hampshire, legislators last month held public hearings on a bill that would allow for over-the-counter dissemination of ivermectin at pharmacies, provided certain treatment plan requirements were met.
New Hampshire HB 1022 would permit pharmacists to dispense the ivermectin by means of a standing order entered into by licensed healthcare professionals.
Sponsors of the bill argued many healthcare workers are unable to prescribe ivermectin, either because of hospital politics or outside professional pressures.
The bill has support from Dr. Paul Marik, who traveled from Virginia to testify at the public hearing.
A former professor of medicine and chief of pulmonary and critical care medicine at Eastern Virginia Medical School, Marik sued the hospital he worked for after it banned physicians from prescribing ivermectin for COVID patients.
Marik resigned late last year in protest of the ban.
During his testimony in New Hampshire, Marik described ivermectin as “cheap, exceedingly safe and exceedingly effective.”
“If ivermectin had been promoted at the beginning of this pandemic, we would not be sitting here today,” Marik said.
Kansas lawmakers last month advanced a bill supporting the prescribing of ivermectin and hydroxychloroquine. The model legislation, also introduced in Tennessee, would require pharmacists to fill prescriptions for the off-label use of ivermectin and hydroxychloroquine.
In direct contrast to the California legislation, the Kansas bill also would mandate that doctors not be subject to disciplinary action for any “recommendation, prescription, use or opinion … related to a treatment for COVID-19, including a treatment that is not recommended or regulated by the licensing board,” Kansas Department of Health and Environment or the U.S. Food and Drug Administration.
“Such actions,” the bill states, “could not be considered unprofessional conduct.”
Kansas lawmaker Sen. Mark Steffen (R-Hutchinson) supports the bill. Steffen, an anesthesiologist, said he’s under investigation by the University of Kansas Health System with which he is affiliated for prescribing ivermectin to COVID patients.
Dr. Festus Krebs III, a physician representing the Catholic Medical Association of Kansas City, also spoke in favor of the bill:
“With ivermectin and hydroxychloroquine, we now have 76 ivermectin COVID-19 controlled studies which show 66 percent overall improvement and 57 percent decreased mortality.”
Meanwhile, in Florida, legislation that would extend protection for hospitals against patient lawsuits over COVID care sits on the desk of Gov. Ron DeSantis, awaiting signature or a veto.
And in New York, the state’s comptroller — citing the investment of the state’s public pension plan in Spotify — sent a letter to the company asking it to increase its screening of “misinformation” on their platform.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.

or go to
Aletho News Archives – Video-Images
By SASAN FAYAZMANESH | March 17, 2008
It is now nearly three decades since the Unites States adopted the policy of dual containment of Iran and Iraq. While much has been written about the containment of Iraq, there has been very little in-depth analysis of this policy when it comes to Iran. In a book that is going to be released on March 31, 2008, entitled The United States and Iran: Sanctions, Wars and the Policy of Dual Containment (Routledge), I attempt to address this shortcoming by investigating when and why the US policy of containment of Iran came about, how it evolved, and where it stands today.[1] To the extent that Israel has been involved in US policy making, the study will also include the role that Israel has played in the containment of Iran. Also, since the fate of Iran has been inextricably linked to that of Iraq, occasionally the investigation will overlap with the containment of Iraq.
The policy of dual containment of Iran and Iraq originated during the Carter Administration, but it was not until the Clinton Administration that the expression “dual containment” became popular. … continue
 Aletho News If Americans Knew No Tricks Zone

