The crushing of dissent throughout the covid era
Orwellian parallels worsen by the week
Health Advisory & Recovery Team | October 8, 2022
The recent actions of the financial technology company, PayPal, to close the accounts of subscribers expressing political opinions of which they disapprove, represents the latest example of censorship within so-called liberal democracies. Their strategic decisions to block the online monetary activities of the Free Speech Union, the Daily Sceptic website and the Us For Them campaign group – although later reversed – signal the willingness of powerful global big-tech companies to collude with governments in the crushing of activities that challenge the dominant narratives. But no one should be surprised; we have all been manipulated by top-down censorship and state propaganda for many years, a dystopian process that accelerated during the covid era.
Since the emergence of the novel coronavirus in early 2020, there has been widespread censorship of views that do not support the two mantras of covid-19 orthodoxy: namely that, ‘Lockdowns and other restrictions were appropriate responses’ and ‘The mRNA vaccines are safe and effective’. Indeed, the unprecedented and non-evidenced covid restrictions could not have been so successfully imposed without propaganda in all its forms. Contrary to popular opinion, techniques of manipulation do not only characterise recognised totalitarian regimes, but are now endemic within contemporary liberal democracies. And three, overlapping, forms of non-consensual persuasion have been widely deployed throughout the covid era to control the narrative and subsequent behaviour of citizens:
1. Control through emotional manipulation
The covert influencing of people’s emotions via use of behavioural-science ‘nudges’ has been well documented. Based on the advice of state-employed psychological experts, the covid-19 communication strategy has relied heavily on evoking uncomfortable feelings in the populace as a way of inducing them to ‘do the right thing’, where what is ‘right’ is solely determined by government-appointed officials. In particular, the manipulation of fear, shame and scapegoating – or ‘affect’, ‘ego’ and ‘norms’, to use the euphemisms of behavioural science – has been conducted for this purpose via the broadcasting of selective statistics, alarming images and emotional messaging. Furthermore, the decision to impose mask mandates was most likely informed by the knowledge that face coverings enhance the power of each of these three nudges, thereby increasing people’s compliance with government diktats.
Despite escalating concerns about the ethical basis of the state’s deployment of behavioural science, there has been a stark reluctance of anyone in authority to accept responsibility for this form of manipulation. The British Psychological Society (the formal guardians of ethical application of psychological interventions) is of the view that covertly inflicting emotional distress on people so as to promote compliance with covid restrictions and the vaccine rollout is acceptable as it is encouraging ‘social responsibility’, thereby colluding – along with other professional bodies – with the state’s mission to silence dissent and eliminate contrary behaviour. Meanwhile the Government show a reluctance to explore the ethics underpinning their deployment of nudges as evidenced by their ‘Public Administration and Public Affairs Committee’ ignoring a request for an independent inquiry and the omission of any mention of behavioural science in the draft terms of reference for the Inquiry into the covid-19 pandemic.
2. Control through modulating the flow of information
A second way of controlling dissent – used at unprecedentedly high levels throughout the covid event – has been via the regulation of information flow within our TV, radio, newspaper and social media outlets. Ease of access to facts, data and opinion (including that of scientific experts) has been mainly determined by the degree to which the information corresponds with the dominant narratives: write or speak words supportive of lockdowns, masking and vaccination and they will typically receive preferential treatment within the media’s editorial processes, gaining prominence and ease of access; in contrast, say or print something contrarian and it will most likely be submerged in the quagmire of daily media output.
The seeds of this system of selective information flow had been sown prior to 2020 with the formation of the ‘Trusted News Initiative’ (a coalition of mainstream media, publishers and big-tech companies) aspiring to ‘create a global alliance of integrity in news’ by countering ‘misinformation’ and ‘bias’. Furthermore, at the start of the pandemic, Ofcom – the UK’s communications regulator – instructed broadcasters not to cover anything that went against the Government’s narrative. This censorial alliance ensured that voices expressing dissent about covid restrictions and the vaccine rollout were disadvantaged, displaced to the inaccessible fringes of media output.
In the UK, there has even been military involvement in the form of the 77th Brigade with their explicit mission to create and spread material ‘in support of designated tasks’ while also ‘supporting counter-adversarial information activity’. Internationally, the WHO has effectively modulated the flow of information via the use of fact-checking organisations and collaborations with Facebook, Twitter, WhatsApp and YouTube, so as to guarantee that ‘science-based health messages from official sources’ (aka the dominant narrative) appear first when one searches for covid information.
Specific examples of the impact of this – seemingly global – operation to control information flow are numerous. They include: Professor Gupta (an epidemiological expert) being instructed not to mention the Great Barrington Declaration prior to appearing on a BBC discussion programme about lockdowns; academic journals blocking the peer-reviewed covid research of Dr Peter McCullough and the suppression of trial findings that had concluded that Ivermectin was an effective treatment; the removal of Dr Robert Malone (the inventor of mRNA technology) from Twitter; and the removal of MPs Sir Christopher Chope and David Davies from YouTube for, respectively, raising concerns about vaccine damage and vaccine effectiveness.
One fundamental consequence of this selective regulation of information was that our Western media – a supposed pillar of democracy – failed us all in their refusal to scrutinise and evaluate the actions of public officials.
3. Control through erasing dissenting voices
Presumably based on the assumption that eliminating people before dissent is expressed is a more effective censorial method than controlling their information output, throughout the covid era there appears to have been a systematic state-driven attempt to discredit or cancel those brave individuals expressing views that are inconsistent with the dominant restrict-and-jab narrative.
Since March 2020, anyone who has expressed a contrarian covid opinion in a public space will likely have attracted criticism involving accusations of being ‘right wing’, fascist or a ‘conspiracy theorist’. Efforts by powerful players to destroy reputations and livelihoods through smearing and character assassination have been commonplace. Arguably the most high-profile example of this egregious practice is in regards to the targeting of the main authors of the Great Barrington Declaration, a multi-signatory document arguing for an alternative to the blanket lockdowns. In leaked emails between Anthony Fauci (Chief Medical Advisor to the US president) and Francis Collins (the Director of the US National Institute of Health), these powerful state officials refer to the illustrious authors of the document as ‘fringe epidemiologists’ while describing the need for a ‘quick and devastating public takedown’ of their arguments. Furthermore, the extremely popular US podcaster, Joe Rogan, was smeared as a transphobe and racist in the aftermath of him giving a platform to experts expressing views at odds with the dominant covid narrative.
A threat of imminent loss of earnings – actual or implied – is another tactic that has been commonly deployed to cancel those criticising the approach of Western governments to pandemic management. Many academics have suffered in this way, including Canadian professor Julie Ponesse who lost her job after she challenged the vaccine mandates. Of course, such a draconian sanction serves as a warning to many other university scholars who might also be considering expressing dissent.
The recent actions of PayPal suggest that our medico-technocratic powerhouses are not satisfied with inflicting emotional distress, censorship and character assassination on the Western population, but now seek to control how we spend our money. Manipulation by means of regulating access to our finances may be the new front in the war on freedom of verbal and behavioural expression. It raises the spectre of the imposition of a totalitarian social credit system, mediated via a Central Bank Digital Currency, a world where unelected global bureaucrats determine our monthly spend based on the degree to which our behaviour conforms to their version of what constitutes the ‘greater good’.
In the words of Piers Robinson (an expert on global propaganda), ‘That the censorship, smearing and coercion … has come to be tolerated is a clear indicator of how far our democracies have slipped into an authoritarian abyss’. And the imminent Online Harms Bill, with its ‘legal but harmful’ category, may further restrict our basic human right to freedom of expression. But there is still hope. As more and more people become aware of the associated collateral damage, the dominant narratives on the benefits of lockdowns, school closures, masks and ‘safe-and-effective’ covid vaccines are beginning to crumble. As awareness of ubiquitous state-funded manipulation and censorship grows, increasing numbers of citizens are turning to independent sources of expert information – such as HART and PANDA – for reliable covid updates. The basic human right of freedom of expression within Western democracies must be protected; once lost, it is unlikely to be restored within our lifetimes.
No balanced coverage of covid vaccines in legacy media, says Peter Doshi
By Maryanne Demasi, PhD | October 16, 2022
Peter Doshi, associate professor at the University of Maryland School of Pharmacy and senior editor at The BMJ, has spoken out about how the mainstream media has ignored important data on covid-19 vaccines.
In a recent interview with German TV, Doshi said, “Our legacy media has not done a good job in providing balanced coverage about the vaccines.”
He said there has been “a lot of nervousness” about how to communicate vaccine harms to people and is concerned that “we’re not getting the information we need to make better choices and to have a more informed understanding of risk and benefit.”
Doshi’s concerns extended to the over-confidence of public health authorities engaged in promoting the covid-19 vaccines.
“It was very unfortunate, that from the beginning, what was presented to us by public health officials was a picture of great certainty… but the reality was that there were extremely important unknowns,” said Doshi who has written and spoken about these unknowns, highlighting that even public health officials were aware of these limitations.
“We entered a situation where essentially the stakes became too high to later present that uncertainty to people.” He added, “I think that’s what set us off on the wrong foot. Public officials should have been a lot more forthright about the gaps in our knowledge.”
Doshi was part of an international group of eminent academic researchers and physicians who went back and re-analysed the safety data from the original randomised clinical trials that underpinned the FDA’s decision to authorise the mRNA vaccines in December 2020.
I reported on the pre-print study, but since then, it has been published in the peer-reviewed journal, Vaccine.
The authors focused on serious adverse events that occurred in the Moderna and Pfizer vaccine trials, events the sponsors classified as “serious” generally because they resulted in hospitalisation.
In short, their analysis showed that mRNA vaccines were associated with 1 additional serious adverse event for every 800 people vaccinated, which Doshi said is “much more common” than what we’ve traditionally observed for other vaccines where the adverse event rate is in the range of 1 to 2 per million vaccinees.
“Just to put that in some perspective, a rate like that in past years has had vaccines taken off the market. In 1976, we saw Guillain Barre Syndrome after influenza vaccines that were then withdrawn.”
The authors of the study also found the trial data showed that the increase in serious adverse events following mRNA vaccination surpassed the reduction in risk of ending up hospitalised with covid-19.
Despite public assurances that covid-19 vaccines would save lives and protect the community by preventing transmission, Doshi knew from the outset that it was never properly tested. In Oct 2020, Doshi published an article in The BMJ:
Hospital admissions and deaths from covid-19 are simply too uncommon in the population being studied for an effective vaccine to demonstrate statistically significant differences in a trial of 30 000 people. The same is true of its ability to save lives or prevent transmission: the trials are not designed to find out [emphasis added]
It was, therefore, unsurprising to Doshi that the vaccines failed to stop the spread.
“One of the big reasons is that it’s an intramuscular vaccine, and this doesn’t produce mucosal immunity. Infections of covid, influenza and other acute respiratory infections, start in the mucosal membranes, a place where these vaccines are not particularly good, historically, at producing immunity antibodies” said Doshi.
Doshi and his colleagues have called on public health authorities and drug manufacturers to release the raw data so that we can better understand who is most at risk of a serious adverse event.
“There’s no reason to think that these risks are going away and if it’s in the low-risk population, that’s very bad news, because low-risk people have much less to potentially gain from covid vaccines, so the side effect profile in such people has to be extremely low,” said Doshi, pointing out that Denmark now recommends against routine covid-19 vaccination for people under 50.
The FDA and the vaccine manufacturers have the raw ‘patient level’ data, but they have not released it and we’re now almost 2 years into the roll out of the product.
“They should immediately be warning people about this safety signal that we found, and they should immediately be replicating our analysis — the data are indicating there’s increased risk at a level that is much higher than has previously been realised,” said Doshi.
Throughout the pandemic, we’ve been told to “trust the science” but Doshi says, “How can one recommend responsibly that these products are based on science if the data are not available? Science is about sharing data. We’re in an era of open science, not secret science.”
Doshi and colleagues have penned an open letter to the CEOs of the vaccine companies asking for the raw data, but as yet, they have not received a reply.
See the full interview on mdr.de
ACIP committee approves mRNA vaccines for the childhood schedule 15-0
By Steve Kirsch | October 20, 2022
The ACIP committee voted on Thursday, as predicted, to add the COVID vaccines to the childhood vaccination schedule so that the manufacturers will now get full liability protection for the authorized product forever.
Here’s the Reuters story that was just published:
U.S. CDC advisers approve adding COVID shots to vaccine schedules
The last of the public commenters was cut off because they were talking about Nuremberg. They were asking why do you even have a public comment section because nobody listens to the comments.
The ACIP committee voted 15-0 to approve the mRNA COVID shots for the childhood immunization schedule, just as I and others predicted they would.
See Meryl Nass’s writeup on her prediction which just came true a few minutes ago.
This means several things:
- The “emergency” can now end. They needed the emergency to be able to create EUA approval which gave them liability protection as long as the emergency existed. The emergency is no longer needed.
- The vaccine makers can now manufacture fully “approved” vaccines and have complete liability protection forever.
- The ACIP vote is just a recommendation. The CDC must add it to the schedule, but that’s a slam dunk.
These people do not want to see any data that shows the vaccines are not safe.
I tried to ask the Chair of the ACIP committee, Grace Lee, if she wanted to see the Israeli safety data showing the vaccines aren’t safe. She refused to answer my Yes or No question on this important data and called the cops on me (even though I didn’t violate any laws). I have it all on video.
That is the level of corruption we are dealing with here: “scientists” who simply look the other way when asked if they want to see the safety data.
My video erases all doubt that they could be honest. The cop handed her my note so I know she got it. She never responded to the offer. They don’t want to look at any negative data.
The Reuters article contained this statement:
“Adding the COVID-19 vaccine to the recommended childhood immunization schedule does not constitute a requirement that any child receive the vaccine,” said Dr. Nirav Shah, an ACIP member and Director of Maine’s Center for Disease Control and Prevention.
What Dr. Shah failed to point out is that there are many states which adopt the entire childhood schedule as a requirement to attend public school. So sure, the vote doesn’t force anyone to follow it, but the reality is that it will be mandated in those states that require the entire vaccine schedule. That point was conveniently left out.
We all knew this was going to happen. I still don’t know of a single healthy kid who died from COVID. We do know of healthy kids who die from the shot. This is insanity and few members of Congress have the guts to speak out about this.
If you haven’t supported Senator Ron Johnson in the past, this would be a very good time to donate to his campaign. It is imperative he win. Please read this article and make a donation using the link in the article. Thanks!
Spike Protein Triggers Coronary Plaque Destabilization and Thrombosis
By Dr. Peter McCullough & John Leake | Courageous Discourse | October 20, 2022
As a cardiologist, I have received many reports of cardiovascular events (unstable angina, myocardial infarction) occurring after COVID-19 vaccination. Each vignette is different from an explosive fatal heart attack to rapid progression of coronary disease and the need for stenting or bypass surgery. A study by Gundy, who measured multiple biomarkers before and after vaccination was presented as an abstract at the American Heart Association; it predicted heart attacks would happen with COVID-19 vaccination based upon indicators that atherosclerotic plaque within coronary arteries would destabilize with circulatory Spike protein and cytokines.[i] This inflammatory milieu in combination with the thrombogenic nature of the Spike protein is a recipe for fatal and nonfatal heart attacks in patients with existing coronary disease.
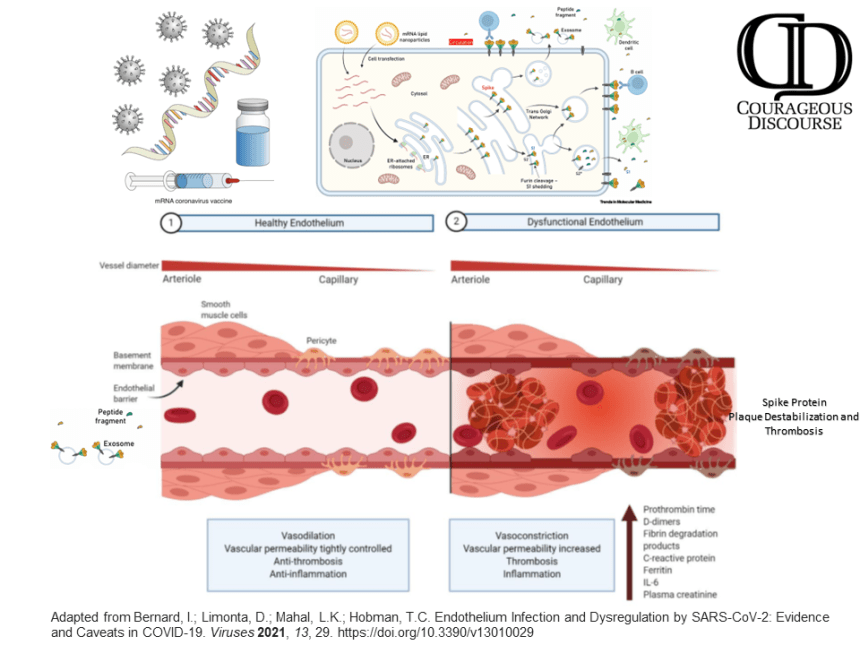
This is different from myocarditis which is direct heart inflammation that can occur in younger people with normal coronary arteries. To the casual observer if a man over age 50 years drops dead a few weeks or a few months after a COVID-19 vaccine, it is possible the mechanism of death may have been a fatal myocardial infarction and thrombotic blockage of a coronary artery to heart muscle as depicted in the figure. The only way to tell if the cause of death was coronary heart disease or myocarditis would be to obtain a limited autopsy. Baronti et al reported on four fatal myocardial infarction cases occurring shortly after COVID-19 vaccination.[ii] All of the patients underwent autopsies and were found to have predisposing factors to blood clots. Patients with prior heart attacks, stents, and bypass surgery are at unacceptably high risk for progression of disease after COVID-19 vaccination and despite the fearful fervor of their cardiologists, they should respectfully decline the shots to keep their cardiovascular system safe. COVID-19 is always treatable and so many heart patients have already had the illness so the next episode will be characteristically mild. Because SARS-CoV-2 respiratory illness can trigger cardiovascular events in the months after hospitalization, recovering patients should consider themselves at equal risk to those who have taken the vaccine and report new heart symptoms to their cardiologist.[iii] Probably the highest risk patients are those who have had severe COVID-19 and have taken multiple injections either before or after the respiratory infection. In these cases, multiply loading the body with long-lasting Spike protein is highly likely to be an ongoing danger to the cardiovascular system and the only way to navigate out of the storm is to decline any further injections and let the body slowly recover.
Agree with Us or Hold your Tongue
BY RAMESH THAKUR | BROWNSTONE INSTITUTE | OCTOBER 19, 2022
Every crisis, they say, is an opportunity. Governments, health bureaucrats and drug regulators all over the world have exploited the Covid-19 crisis to grab power and gain control over our lives. Predictably, rather than to most people’s surprise, many are proving singularly resistant to relinquishing their extraordinary powers, instead extending the emergency and broadening its scope to embrace other issues.
Efforts to control the pandemic narrative began with a systematic suppression of any suggestion that it might have originated in a research lab of the Wuhan Institute of Virology, then moved on to denigrate, silence and smear critics of lockdowns, masks and vaccine efficacy and mandates.
Australia’s Amended Health Practitioner Regulation National Law
The latest iteration in Australia occurred on October 13 when the Queensland Parliament amended the Health Practitioner Regulation National Law Act to fundamentally reshape the relationship between doctors, patients and health regulators. As per an existing intergovernmental agreement, the Queensland change will be replicated in cascading legislative amendments in other states and territories to ensure a uniform National Law.
On February 22, Australian federal and state health ministers had approved the Health Practitioner Regulation National Law Amendment Bill. The updates to the guiding principles included “an increase in the regulatory responses available to protect public safety.” At best, this is vague and ambiguous.
At worst, it shifts the balance decisively from the individual-centric in liberal democracies to the collective safetyism of technocrats and experts, justifying restrictions on individual rights and agency for the greater good as determined by government agencies. Doctors will be prohibited from expressing their opinion and using their experience, training, education and knowledge of the patient, if this contradicts what the health bureaucrats say is in the interests of “public confidence in safety.” The latter will remote-control how doctors should approach treatment recommendations for patients.
There were several submissions arguing against various elements of the amendment. The Australian Medical Association queried what a “main guiding principle” means “in practice” and argued that the “concept of public confidence is not always clear cut.” The Royal Australian College of General Practitioners submitted that the amendments would imbalance the system even further away from the protection of patient safety and toward “the prosecution of practitioners,” to the detriment of doctors’ confidence in the National Law.
The most substantial submission came from the Australian Medical Professionals Society and the Nurses Professional Association of Australia representing more than 10,000 health professionals. They expressed concern that “the broad and discretionary nature of claims to ‘public safety and confidence’” can be abused “as a mechanism to enforce compliance with government directives.” On the one hand, these could be disconnected from science and evidence.
On the other, they could be used to control health practitioners in direct “conflict with their ethical duties and code of conduct obligations.” They weren’t confident that the provisions for public health and safety would in fact either “improve public protection from clinical misconduct” or “increase confidence in the public health system.” Instead the proposed powers would “serve to conveniently silence voices of expertise that wish to correct health authorities” and prove counterproductive by preventing “necessary information and communication from entering the public sphere.”
Everything done by health bureaucrats and regulators since March 2020, in the name of ensuring public safety and stopping disinformation, indicates we should fear the worst and would be naive to hope for the best. This includes psychological manipulation of emotions and feelings to nudge people into compliance with health directives.
Long-standing principles that have guided Australian doctors and ensured its health system is second to none will be undermined: the Hippocratic Oath’s duty of “Do no harm,” informed consent of the patient based on a harm-benefit evaluation of different treatment options, the risks associated with them in the best professional judgment of the doctor, and the sanctity of the doctor-patient relationship.
People’s faith in their GPs could collapse once they realize doctors are barred from questioning putative benefits or pointing to possible risks of recommended treatments. Instead, they must stay within the boundaries laid down by bureaucrats and regulators, the latter often subject to industry capture.
California has passed a similar law empowering the state’s medical board to revoke the license of physicians who express opinions “contradicted by contemporary scientific consensus to the standard of care.” Or, as helpfully translated by the New York Post sub-editors: “California makes it illegal for doctors to disagree with politicians.”
The Debate on the Harm-Benefit Balance of Covid Vaccines
For health bureaucrats and regulators, the latter often with compromising links to industry, to claim a monopoly on scientific truth is scandalous. The effort to shut down legitimate debates on pain of excommunication from the medical profession represents a clear and present danger to public health.
Having overturned a hundred years of science and policy orthodoxy on pandemic management with Covid, we are intent on revolutionizing the everyday practice of medicine by subordinating the professional judgment of doctors on the best treatment options for their patients, to the directives of bureaucrats and health regulators. With public esteem for politicians at all-time lows, this is not likely to inspire confidence in the health service.
Consider globally contested opinion on the benefit-harm balance of Covid vaccines for children. Their risk of severe illness or death from Covid is tiny, of serious adverse reactions is higher and the long-term effects are unknown. On October 7, Florida issued a press release recommending against mRNA Covid vaccines for 18–39 year-old males. Their analysis had found an 84 percent higher risk of cardiac-related death within 28 days of vaccination in this group. Over-60s have a 10 percent increased risk.
This complements Florida’s guidance on paediatric vaccine guidance issued in March which recommends against Covid vaccines for healthy under-18s. They note the limited risk to infants and children of severe illness due to Covid, the high prevalence of existing immunity among them, reduced vaccine efficacy and “higher than anticipated” severe adverse events, including myocarditis.
Florida thus joins Denmark, Norway and Sweden in ending vaccine recommendations for 12–17 year-olds and also, in two of these, for under 50s and 65s. Albeit contested, there is a substantial and growing body of scientific studies that support their skepticism toward the net benefits of Covid vaccines for infants, children and adolescents.
Florida’s guidance includes three recommendations that are directly relevant to Australia’s National Law:
- People are encouraged to discuss all potential vaccine benefits and risks with their health care provider.
- The risk associated with mRNA vaccination should be weighed against that with Covid infection.
- Doctors should inform patients of the possible cardiac complications that can arise after receiving an mRNA vaccine.
Yet Australia’s Therapeutic Goods Administration has approved vaccines for children aged 6 months-5 years. Meanwhile, many of the claims advanced in support of the vaccines – they stop infection and transmission and prevent severe illness and death – have had to be abandoned one after another but were never “fact-checked” by social media platforms, while the early critics of these claims were assessed by the self-styled fact-checkers to be spreading disinformation and promoting conspiracy theories – until they aren’t any longer.
Moreover, people who die inside 14 days of a vaccine dose are wrongly classified as “unvaccinated.” This distorts the statistics on the net harm-benefit balance to an indeterminate degree. In a particularly egregious example, an article in Nature on September 23 explained that the authors (1) had classified unvaccinated and single-dose vaccinated into the one catch-all category of unvaccinated, and (2) unvaccinated individuals with previous infection had been classified as “fully vaccinated” (Supplementary Table 2).
This in a study whose main objective was to assess the comparative susceptibility to infection by the Omicron variant of the vaccinated versus the unvaccinated within Danish households in December 2021. They concluded that the vaccinated are less susceptible. I can empathize with the reaction of Julian Conradson that after such analytical legerdemain in a leading peer-reviewed journal, “Academia Is Dead.” Little wonder that a poll by the Pew Research Center in February mapped falling confidence in medical scientists since 2020.
Examples of Off-Limits Topics
Examples of studies that doctors could not discuss without fear of investigation and repercussions include:
- In a new study in preprint that looked at 31 pre-vaccination national seroprevalence studies to estimate the infection fatality rate (IFR) stratified by age, John Ioannidis and his team found that the average IFR was 0.0003% at 0-19 years, 0.003% at 20-29 years, 0.011% at 30-39 years, and 0.035% at 40-49 years. The median for 0-59 year-olds was just 0.035%. These are well within and often lower than the seasonal flu range for the under-60s. The last sentence would be ruled out as disinformation, or misleading, or at the very least missing context.
- In the weekly report for August 14–20, NSW Health said: “The minority of the overall population who have not been vaccinated are significantly overrepresented among patients in hospitals and ICUs with Covid-19” (p. 2). Two pages later, the same report gives us the data for hospital and ICU admissions by vaccination status. The number of unvaccinated is exactly zero for both. Now, this makes it mathematically impossible for the unvaccinated to be “overrepresented” among hospital and ICU Covid patients. There is an important conceptual distinction between the statement on page 2 and the statistics in Table 1 two pages later. The first is part of public messaging by the health department of Covid vaccines being “safe and effective.” The second is actual data. The way I read the amended National Law, and therefore the way that some AHPRA (Australian Health Practitioner Regulation Agency) official could read it at some time in the future against any doctor, the latter must conform to the public message and not mention the actual data.
- Imagine a family of 45-year-old parents with three young children aged 5-12 who visit their family doctor to discuss vaccination for their kids and boosters for themselves, both to protect themselves and their parents in turn as they take the kids to spend quality time with grandparents. In the name of public safety, will Australian doctors have to promote the mRNA vaccines to children, boosters to grown-ups and be forbidden to mention advice to the contrary in Scandinavia and Florida? In New South Wales, of the 2,311 Covid-related deaths since May 22, only 3 have been under 20 and 34 under 50. Has any healthy under-20 died of Covid in Australia through the pandemic? If children are at virtually no risk and vaccines don’t stop transmission, why expose children to the risk of serious adverse events?
- What of the startling revelation that Pfizer had never tested its vaccines for transmissibility and therefore the entire vaccine passport requirement was built on a conspiracy of lies? In an NBC interview on February 26, 2021 Pfizer CEO Albert Bourla clearly says “there are a lot of indications right now that are telling us that there is a protection against transmission of the disease” provided by the vaccine. In a CBS interview on May, 26, 2021, Anthony Fauci said: “when you get vaccinated, you not only protect your own health, that of the family, but also you contribute to the community health by preventing the spread of the virus throughout the community … you become a dead end to the virus.” Australian data too confirm that while vaccines and boosters continue to provide protective benefits against severe disease and deaths, despite 95 percent adult vaccination they do not provide immunity against infection, hospitalization, ICU admission or even death (Figure 1).
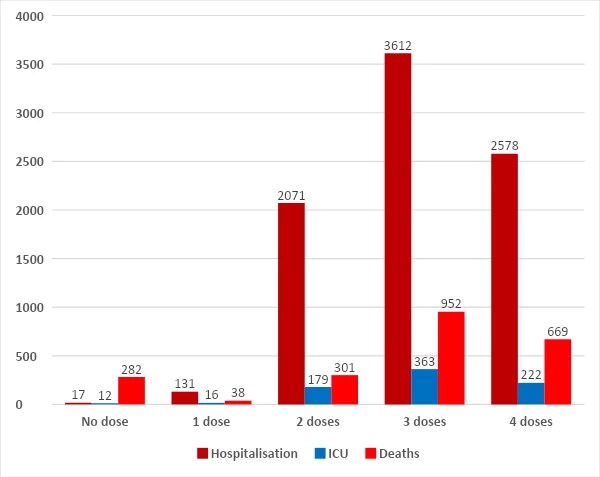
Figure 1: Covid-19 statistics for New South Wales (NSW) by vaccination status, May 22–October 10, 2022. Source: NSW Health, Weekly Surveillance Reports.
In an article on news.com.au, Frank Chung has done Australians a great service by compiling a list of statements from Australian ministers and health bureaucrats repeatedly stating their firm conviction that vaccines stop transmission. Michael Senger has done us all a service with a similar look back at the demonization of the unvaccinated by various public authorities, only too eagerly amplified by the media, and all predicated in the false belief that vaccines stop transmission.
For readers with an interest in Australia, Richard Kelly provides a review of many head-shaking edicts and enforcement actions – such as fining a delivery man for washing his van at an empty car wash at 1.15 a.m. and a teenage learner driver for going for a lesson with her mum – that were issued by public health officials. Their ignorance about the disease was exceeded only by their arrogance and hubris about their ability to control the behavior of a coronavirus. Would Australian doctors be at risk of deregistration for mentioning any of this?
Oliver May of News UNCUT wrote an open letter to 20 British news editors on October 12, asking them to explain why they had failed to run a story either on the powerful documentary on vaccine injuries called Safe and Effective: A Second Opinion, or on Dr. Aseem Malhotra’s painfully honest peer-reviewed study calling for a pause in Covid vaccination because of serious adverse events until all the raw data has been subjected to fully independent scrutiny. Both would be interesting to the public and both are very much in the public interest. We shouldn’t hold our breath for an answer. Maryland School of Pharmacy’s Peter Doshi, senior editor of the British Medical Journal, is right to call out the legacy media for their lack of balanced coverage of Covid vaccines.
Remarkably, the Pfizer admission has been studiously ignored by the Australian MSM. In case I had missed the coverage of the bombshell interview in the Australian media, I did a search on the website of ABC (Australia’s version of the BBC), Age, Australian and Sydney Morning Herald papers. I got zero hits for Robert Roos, the Dutch MEP who asked the question in the European Parliament of Pfizer director Janine Small, and for the latter who confessed to lack of testing for transmissibility. Fading trust in our principal institutions is contributing to the multipronged global crisis of democracy.
The lack of media interest and coverage means there is little pressure for public accountability. Absent that, there will not be any punishment meted out to ministers and bureaucrats for the extensive range of malfeasance in inflicting cruel and inhumane harms on millions of their citizens; no prospect of emotional closure for the people for the trauma they have suffered, including deaths of despair and desolation born of loneliness; delayed prospects of the masses shedding their sheer dread of a virus that for most healthy people under 70 or 65 is not really a severe illness; and a refusal to institute the most powerful deterrent of all for any repeats of public criminality on a grand scale.
Instead we can all look forward to endless cycles of rinse and repeat of surveillance, compulsion and coercion of the masses on the whims of their technocratic betters.
Ramesh Thakur, a Brownstone Institute Senior Scholar, is a former United Nations Assistant Secretary-General, and emeritus professor in the Crawford School of Public Policy, The Australian National University.
mRNA in your food
NSW fast tracks vaccines for cattle
The Naked Emperor’s Newsletter | October 19, 2022
The NSW Department of Primary Industries have partnered with the Queensland Government, the Federal Department of Agriculture, Fisheries and Forestry and Meat and Livestock Australia. These will be the first mRNA vaccines for these diseases and will be created by US biotech company, Tiba Biotech.
Deputy Premier and Minister for Regional NSW, Paul Toole wants to prepare for a potential outbreak and so has written to vaccine manufacturers to develop both vaccines by 1 August 2023.
Cattle are currently vaccinated for FMD using traditional live attenuated virus vaccines and there is no LSD vaccine in use in Australia. Therefore, Minister for Agriculture, Dugald Saunders, wants mRNA vaccines quickly because they are “cheaper and quicker to produce, highly effective and very safe.”
Except for there haven’t been any trials to see if these vaccines are highly effective and very safe because they haven’t been designed yet.
Meat and Livestock Australia managing director Jason Strong said “This type of vaccine technology may not require the longer testing and approval processes required for conventional vaccine development and importation as it does not use animal products”.
Sounds reassuring?
The NSW Government has spent 229 million Australian Dollars (144 million USD) on biosecurity so far this year.
I’ve said it before and I’ll say it again, mRNA technology is an exciting development but it is relatively new and needs far more extensive testing.
Fact checkers from last year said vaccinated Mothers didn’t have mRNA in their breast milk. Studies this year contradict those fact checks and say they do. Before mRNA is pumped into every animal on the planet, I want long term studies showing what happens to that mRNA, whether it transfers via milk and meat, how long it takes for the mRNA to degrade and most importantly how it interacts with humans if it passes to them.
For all we know, the mRNA could transfer to humans, where our cells start producing proteins from the FMD and LSD viruses.
It’s opening a whole can of worms to not test these things and to fast track approval is ridiculous.
Looks like I will be eating bugs after all!
Organized Chaos in South Central, Los Angeles
BY DANIEL NUCCIO | BROWNSTONE INSTITUTE | OCTOBER 19, 2022
The LAPD’s 77th Division in South Central serves what some officers consider “pretty much the most violent area of the entire city and county of Los Angeles,” explained Officer Charles Simmering in a phone interview. “You’re just running and gunning all night. You’re just running. There’s never a dull moment. You’re just going from one call to the next to the next. ‘Organized chaos’ is the best way we describe it.”
Each night, he explained, the 77th Division puts out a minimum of 12 cars, usually two officers per car, all 24 officers feeling “beyond overwhelmed.” The 77th Division can’t afford to lose people, Simmering said. But, he continued, that’s exactly what’s happening.
“Last year at my division alone I think we lost roughly 40 officers – and that’s putting a hurt, putting a strain on everybody,” said Simmering.
“People are leaving,” he stated. “They’re tired. They’re fed up.” Their reasons vary according to Simmering’s account. Lack of support. Lack of trust on the part of the city. Frustrations over not being allowed to make their own decisions out on the job. Nonetheless, the departure of these officers only exacerbates some of the problems that drove them to leave.
“If you need a particular day off for something family-related, your mother’s birthday or kid’s birthday, or something important,” Simmering explained, “They deny you and say, ‘No, you can’t have the day off. Sorry. We’re undermanned. We need people here.’”
That is, they need people, assuming they are vaccinated for Covid-19 because to the city bureaucracy Covid-19 remains the greatest threat to the citizens of South Central, as well as the rest of Los Angeles. Hence, officers such as Simmering, who remain unvaccinated for Covid-19, are considered dispensable.
The Parallel Reality of LA’s City Workers
Announced in July of 2021 and later passed and approved that August at the height of the Pandemic Era’s mandate madness, Los Angeles’ vaccine mandate for city employees still remains in effect. Predicated on the continued threat of Covid-19 to public health, the effectiveness of Covid vaccines, and the danger posed by the unvaccinated, the mandate comes off as a relic from a bygone era, as do the protracted Byzantine processes to which employees seeking exemptions must submit and the testing protocols such employees must agree to follow.
According to the anti-mandate organization Roll Call 4 Freedom, the ordinance and the system it established are illegal. According to the unvaccinated employees living under the ordinance, the system often seems random and arbitrary. Yet, in October of 2022, when there appears to be little doubt that Covid vaccines do little to stop the spread of Covid and that the vaccinated can spread the disease as easily as the unvaccinated, vaccine mandates are alive and well in the city of LA.
By the account of James Greenfield, a manager in the sanitation department, “It’s like we’re living in a parallel universe… [we’re] just in a parallel reality.”
Looking back on the past year, Greenfield, who is unvaccinated for Covid due to religious reasons, described life under the ordinance in a phone interview, saying requirements for compliance are always changing, “the goal post is always moving.”
“It was originally, you know, submit an exemption…” he stated. “It later developed into like this four-page, unconstitutional questionnaire on your religious beliefs.”
The city also wanted employees to “have a pastor answer questions.” Greenfield added. “I mean it [was] just over the top on violating your, you know, your religious freedom.”
Greenfield said he filed for a religious exemption, but refused to fill out the four-page form.
As a condition of remaining employed while working through the exemption process, Greenfield said, he and other unvaccinated city employees were initially required to test twice per week, but that was later reduced to once per week. The city, he said, also threatened to deduct the cost of the tests from people’s paychecks. However, before the city could charge anyone’s paycheck, they first needed them to fill out paperwork giving them permission to charge their paychecks.
“I didn’t fill out the paperwork,” Greenfield said. “I’m not going to give [the city] permission to take money out of my paycheck.”
But, he noted, he believes “a lot of people were coerced” and the city managed to bill at least a couple of people before they had to stop.
More recently, said Greenfield, they tried to bill the tests to the insurance of unvaccinated employees but backed off from those attempts within a couple of weeks.
Yvette Smith, an animal control officer at the City of Los Angeles’ Harbor Animal Shelter in the San Pedro neighborhood, stated, “We just didn’t give our insurance information and then [the city] pulled away.”
Like Greenfield, Smith has been required to test for Covid for nearly a year as she works her way through the exemption process. During the past year, Smith said, she had submitted a request for a religious exemption, was informed that it was denied, and appealed the decision. Now, in October of 2022, she awaits a decision regarding her appeal.
In some ways, although frustrated and inconvenienced, she believes people in her department (or at least her corner of her department), have gotten lucky. “As long as you have submitted a religious exemption that [the city has] denied and it’s in some imaginary nebulous area and you agree to test, they’re pretty much leaving us alone. So I’m grateful for that.”
However, Smith noted, “Every department is treating [the ordinance] differently.”
The Autumn Purge
Currently, the Los Angeles Department of Transportation appears to be one of the departments in which a purge of the unvaccinated is in full swing.
Navy veteran and former wildland firefighter, Rene Ochoa, has been a traffic officer with the Los Angeles Department of Transportation for the past 19 years. “I’ve been grateful for my job,” he said in a phone interview. “It’s helped me to have a lifestyle [I wanted], permitted me to have my home and provide for my wife and my children.”
Last year, he said, he filed a request for a religious exemption due to concerns about potential side effects and the use of aborted fetal cell lines in the development of the Covid vaccines. After his request was denied in May 2022, Ochoa said he appealed the denial. That appeal, he explained, was denied in July.
“Then, September 13 of this year…” he said, “I was walked off the job, locked out of my station in front of all my fellow coworkers…”
“I am currently on administrative leave,” stated Ochoa. “I have a Skelly hearing scheduled for Friday November 4 at 10:00 am.”
Amongst city employees working their way through the process of attaining a religious exemption from the Covid vaccine mandate, Skelly hearings are generally seen as the final step prior to termination.
Reflecting on the strong likelihood that he will lose his job on November 4, Ochoa said, “I’m in a much better position than a lot of other people I know that are younger than me and with maybe say half the time [in a city job].”
Because of his time working other positions with the city and with LA County, Ochoa is eligible for retirement, although with an early retirement penalty if he takes it before he turns 55; Ochoa is currently 53.
Smith expressed similar sentiments, commenting on the possibility she might be terminated. “I’m in a different position than most people. I’m pretty close to retirement [in June 2023] and kind of don’t give a shit at this point. So, you know, I’ll just keep jumping through the hoops until it bothers me too much and then I just won’t do it any more.”
If the City of Los Angeles does try to proceed with her termination, Smith is optimistic that she can work within the system to delay its finalization through a strategic use of vacation time, family leave, and possibly agreeing to unpaid leave until she can retire at least sort of on her terms. She admitted she is morally conflicted about having to resort to these kinds of tactics, but will do what she needs to do.
Yet, most Los Angeles city employees do not find themselves in positions where they can retire early or maneuver their way through the system until they can run out the clock and retire on terms they find acceptable.
Pearl Pantoja, for example, an employee with the Los Angeles Department of Transportation, who was interviewed previously for an article published by Brownstone Institute about the troubles faced by LA city workers, has five children, one of whom has special needs. She also serves as the caregiver for her disabled mother. She and her family depend on her paycheck and the benefits that come with her job.
However, she said, “Friday, September 16, I was in effect placed on, my supervisor used the word suspension. I know the city’s calling it administrative leave without pay.”
“They gave me a notice with an appointment…” she stated. “It says you’re being placed off for non-compliance.”
But, Pantoja holds, “I was compliant, except they refused to accept my religious exemption.”
“They also did not… attempt to see if there were any reasonable accommodations that could be made so that I could continue to work.” Pantoja claims these are “parts of the process [that were] just simply ignored.”
Currently, Pantoja, like her colleague, Ochoa, awaits her Skelly hearing. Based on what she has seen happen to other unvaccinated colleagues, she is not optimistic about the future. “I have a colleague who lost his job and he is now homeless…I have another colleague who is expecting his first child and he’s now out of work and [has] no healthcare.”
“I’m really worried,” she said. “I almost know with certainty that I’m going to lose my job.”
What Lies Behind the Curtain
Perhaps the City of Los Angeles’ mandate, exemption process, and the personal and professional devastation they wrought can best be described as a form of organized chaos.
Part of what makes this all so frustrating and demoralizing, according to Greenfield, is the way the whole system is set up. No one is really accountable for any of the decisions made regarding exemptions, testing, appeals, or terminations. Everything is done through third parties and anonymous emails.
“You’ll get an email… with no name,” he explained. “Nobody attached to it. Nobody personally to talk to about it.”
“It’s like they’re just hiding,” he said. “They’re hiding behind a shroud. You know, supposedly there’s this committee that’s reviewing and coming up with these policies except who would know who’s on this committee. Who the names are? When they meet? It’s just a blind process like the wizard behind the curtain. The Wizard of Oz behind the curtain. You know, and that’s the process.”
Moreover, Greenfield noted, he and other unvaccinated city employees live with this feeling that “the hammer can drop anytime.”
“So, you’re just living under this uncertainty,” he said. “When’s the carpet going to get pulled out from beneath you?”
Simmering, who is currently on medical leave due to an injury sustained on the job, said the decision regarding his exemption has been placed on hold until he can return to work, at which point he said he’ll have to “play the Russian roulette with whether not they’re going to approve [his] exemption.”
“It’s like so much of the country is going in a different direction and maybe backtracking,” Greenfield said. “You know, maybe they thought [mandates were] a good decision. But [in LA], there’s no backtracking. It’s like they’re doubling down. [They’re] sticking to [their] guns here even though nobody else is.”
“Until Proven Otherwise, it is Likely Covid mRNA Vaccines Played a Significant Role in All Unexplained Heart Attacks Since 2021”
BY WILL JONES | THE DAILY SCEPTIC | OCTOBER 18, 2022
“Until proven otherwise, it is likely that Covid mRNA vaccines played a significant or primary role in all unexplained heart attacks, strokes, cardiac arrhythmias and heart failure since 2021.”
That’s according to Dr. Aseem Malhotra, a renowned British cardiologist who once endorsed the vaccines on TV but is now raising awareness of their dangers. In September his two–part, peer-reviewed analysis of vaccine efficacy and safety was published in the Journal of Insulin Resistance.
Dr. Malhotra made the comments in a new interview with James Freeman Wells, a former Head of U.K. Trade and Business Inflation Statistics at the Office for National Statistics, the U.K.’s Government statistics agency. James has tweeted a link to the full interview here.
Dr. Malhotra’s comments come ahead of a meeting of the All-Party Parliamentary Group on COVID-19 Vaccine Damage, where he will speak to MPs and Peers about the evidence of the risks from the vaccines, putting it in the context of wider problems with the way medicine is regulated and marketed globally. The meeting was originally planned for September but was delayed due to the Queen’s death and will now take place this coming Thursday, October 20th in the House of Commons of the U.K Parliament.
Referring to the worrisome influence of large pharmaceutical companies in the regulation of drugs – whom he describes as “immoral” and “psychopathic” because he says they are constitutionally unable to put people before profits – he proclaims:
“It’s time to put patients before profits, to put truth before money, to put human needs ahead of the needs of an immoral, psychopathic entity. Let’s do this.”
James Wells has posted a link to a template letter to encourage your MP to attend here.
Let’s hope this delivers another hammer blow to the wall of silence that has thus far met the growing clamour for recognition of the extraordinary level of injuries associated with these experimental genetic vaccines.
Those Demonising the Unvaccinated Need to Look in the Mirror

BY NICK RENDELL | THE DAILY SCEPTIC | OCTOBER 17, 2022
It’s been known since the outbreak of Covid that obesity leads to higher rates of hospitalisations and deaths. Despite this, very few resources were deployed to encourage healthier eating and lifestyles. This article argues that this was a disastrous decision for the long term health of the nation and the short to medium term capacity of the NHS.
Boris Johnson (BMI 34; healthy is under 25) in his New Year message broadcast on December 31st 2020 said: “Get a vaccine, it’s far easier than losing weight” (see video from two minutes in). Well, the people of the U.K. took him at his word: we’ve had 30 months to galvanise the population into losing weight and getting fitter, 30 months entirely squandered.
First, let’s just look at how effective spending £25bn injecting 150 million vaccines into the U.K. population has been. As the NHS continues to struggle to meet demand, perhaps Covid hospital admissions are the key metric. For the vaccine programme to have been a success we should expect the unvaccinated to be disproportionately admitted to hospital. They’re not. These figures come from the latest UKHSA Weekly Vaccine Surveillance Report; table 12a on page 49 gives us the figures for hospital admissions between March 21st and August 28th of this year. In each age cohort the unvaccinated are proportionately less likely to be hospitalised than the vaccinated. As an example, in the 50-64 year-olds, 129 of the 1,342 admissions were unvaccinated, that’s 9.6%. Yet, about 14% of that age group are unvaccinated. If the unvaccinated were more likely to be hospitalised we would expect the figures to be reversed, to see a higher proportion of the unvaccinated hospitalised than the total proportion of people unvaccinated.
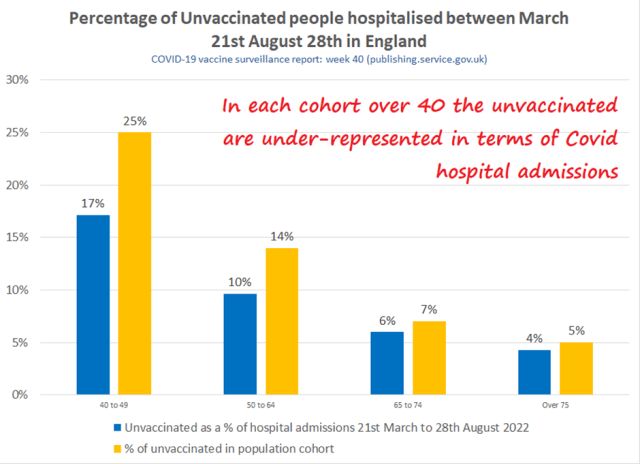
Demonstrably, despite the Government’s claims that vaccines have reduced hospital admissions, this can’t be true. Something has reduced hospital admissions from the peaks in the first two waves, but if the rate of admission is much the same for the vaccinated and the unvaccinated I struggle to see how vaccines can explain it. Surely, far more likely are the twin benefits of immunity brought about by prior infection and a less virulent variant. Figure 2 shows the peaks and troughs of Covid hospital admissions since the start of the pandemic.
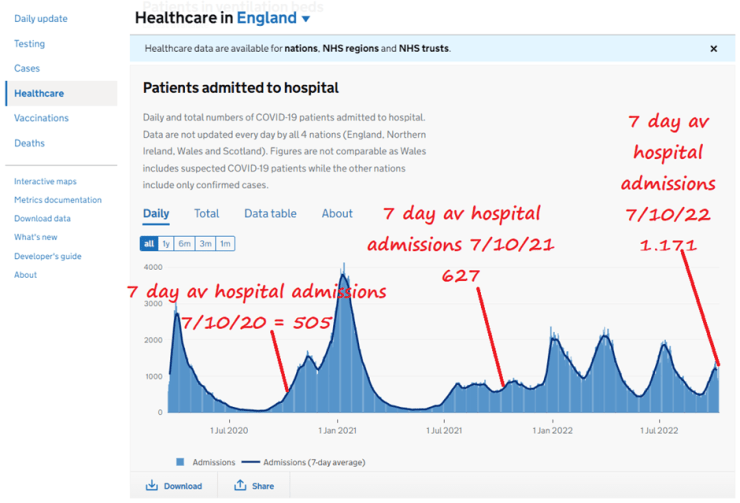
Also worth noting, the seven-day average number of hospital admissions for Covid is currently 132% higher than it was on October 7th 2020, before anyone anywhere had been vaccinated, and 86% higher than on October 7th 2021 when most people had been vaccinated – though it should be noted that over half of Covid hospital admissions since Omicron have been primarily being treated for something else.
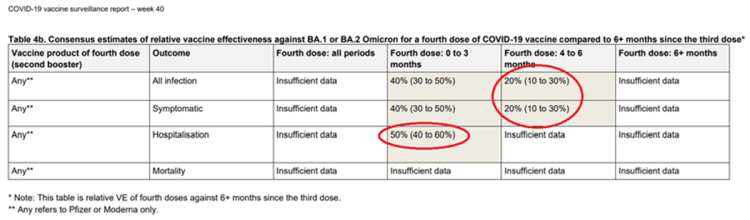
Despite my deep scepticism of the efficacy of the mRNA vaccines and the real world evidence presented above, to avoid any accusations of dogmatism I’m going to indulge the vaccine zealots’ figures for vaccine effectiveness. Again, with the data taken from the Government’s week 40 vaccine surveillance report, figure 3 suggests that the UKHSA thinks that the best protection a fourth dose of vaccine can offer is about 50%, soon falling to 20%.
Now let’s compare that vaccine efficacy with the impact of obesity on severe Covid outcomes by turning to a fascinating study published in June in the Lancet that looked at how BMI affects Covid outcomes. What made this latest study particularly interesting was that it used real, though anonymised, data from about 20% of the U.K. population. The data, from QResearch had over 12 million patient records but about 3 million couldn’t be used, mainly because BMI data were missing, but that still left 9,171,524 patient records to be analysed. So, again, we’re looking at real-world evidence whereas the UKHSA vaccine efficacy rates are estimates.
The data related to the period from December 2020 to November 2021. This was the period covering the initial rollout through to booster doses in older people. Part of the summary table is reproduced in Figure 4. I’ve highlighted in red hospital admissions.
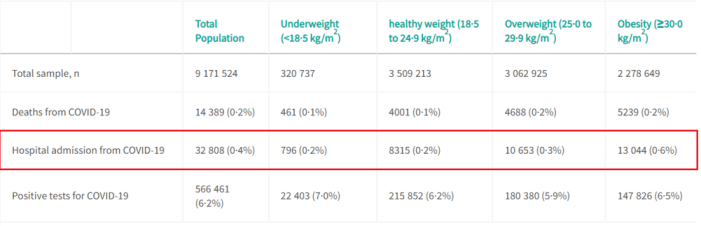
There were 3,509,213 people of a healthy weight in the study, of whom 8,315 were hospitalised with Covid, that’s 0.23%. Of the 3,062,925 overweight people, 10,653 or 0.35% were hospitalised. That means the overweight were 50% more likely to end up in hospital than those classed as healthy weight.
Of the 2,278,649 obese people 13,044 or 0.57% were hospitalised. This means they were 150% more likely require hospital treatment than the healthy weight group.
Let’s now compare the relative risk of being vaccinated with that of being obese. The obese get hospitalised at a rate 150% greater than those of a healthy weight while the best you can hope for from your fourth vaccine is a 50% reduction in the likelihood of being admitted to hospital, dropping to 20% after about four months. And that’s another key point, keep the weight off and that risk reduction remains in contrast to any benefit from vaccination that soon wanes to nothing (assuming it ever existed in the first place).
But of course, it’s not just Covid where the overweight and obese have worse outcomes. The Lancet study goes on to list some of the other health outcomes for other conditions. The obese are almost six times more likely to have type 2 diabetes, more than twice as likely to suffer cardiovascular disease and over three times more likely to suffer hypertension.
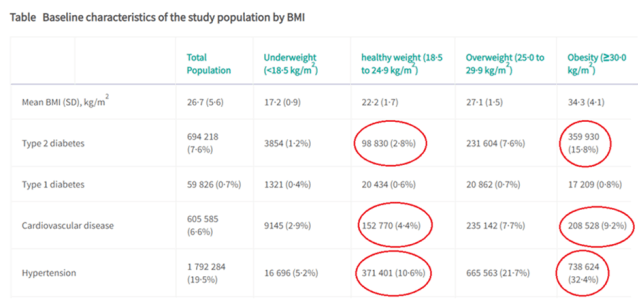
Lose weight and many of these rates of disease would fall. The burden on the NHS would be reduced, the people losing weight, in most cases, would feel better and no doubt their mental health would, in the round, be improved.
I was interested in a piece by Michael P. Senger in the Daily Sceptic on October 14th 2022 highlighting the demonisation of the unvaccinated. I really don’t recall anyone in the mainstream media or in Government objecting to this vilification at the time yet it was evident from the Week 35 2021 Vaccine Surveillance Report that in each of the age groups from 40 to 80 the double dosed were testing positive for the virus at a higher rate than the unvaccinated (see an article I wrote back in June that goes into some detail on this point), so it was evident that the unvaccinated represented less of a threat than the vaccinated. Likewise, it’s been known since the Covid outbreak on the Diamond Princess back in February 2020 that obesity was a risk factor. However, can you imagine the furore that would result if people were to suggest that the obese were denied hospital treatment?
It’s not the unvaccinated who are clogging up the NHS, it’s disproportionately the obese and overweight – some of whom have been particularly vocal in vilifying the unvaccinated or in failing to promote healthier lifestyles:
- Andrew Neil (estimated BMI 32) argued for restrictions on the freedoms of the unvaccinated.
- Piers Morgan (estimated BMI 29) argued for the unvaccinated to be denied NHS care if they caught Covid.
- Boris Johnson (estimated BMI 34) attempted to bring in vaccine passports.
- Michael Gove (estimated BMI 28) was a keen advocate of vaccine passports.
- Therese Coffey (estimated BMI 30), the new Health Minister appears to be far keener on promoting vaccines rather than healthy lifestyles.
The Government spent about £12bn vaccinating the under 50s, largely a pointless exercise. As an advocate of lower taxes and a smaller state I don’t argue that this money should have been spent on schemes to subsidise healthier living. Such schemes invariably fail. What’s more, I would object just as fiercely to coercing people to lose weight as I do to coercing people to get vaccinated. However, I would like to see them campaign to raise people’s awareness of the risks associated with a high BMI. In rough terms, there appears to be about a 10% Covid hospitalisation risk reduction for each BMI point reduction and associated risk reductions for various cancers, diabetes, heart conditions, muscular/skeletal problems and mental health.
Body positivity is all well and good but being overweight is neither risk or cost free. If Andrew Neil, Piers Morgan, Boris Johnson et al. want target a group to be censorious of perhaps they should follow Jordan Peterson’s advice and go tidy their own room first.
Featured Video

Thomas Fazi: NATO’s Hybrid Warfare – Deception & Permanent War
or go to
Aletho News Archives – Video-Images
Book Review
The Zeolite Book — First Edition, 2026, Paperback
The volcanic mineral medicine will not patent — for the toxic burden medicine will not name
Lies are Unbekoming – October 30, 2026
 Zeolite is old. It is in Roman concrete that has held for two thousand years. It’s in the water filters of ancient cisterns. It’s in the stomachs of Pacific livestock whose keepers knew, somehow, that this grey crumbling rock made the animals healthier. It’s in Soviet clinical protocols from the 1960s. It’s in the standard emergency response to the Chernobyl explosion.
In 1986, after the Chernobyl reactor failure, the Soviet Union manufactured and distributed natural zeolite at industrial scale — for soil remediation, for livestock feed, for human consumption, for the cleanup itself. Karl Hecht, who had been director of the Institute for Experimental and Clinical Pathophysiology at the Charité of Humboldt University Berlin, spent the six decades after that building the clinical research base — on silicon’s role in human health, on zeolite’s clinical safety, on its applications in ageing. In 2018, Pavelić and colleagues published a comprehensive clinical safety review of natural clinoptilolite in Frontiers in Pharmacology. In 2019, Mastinu analysed its binding affinities. In the Western medical literature, these works sit largely uncited.
What has not been treated at book length, until now, is how a volcanic mineral with six decades of Soviet clinical work behind it, two major peer-reviewed Western reviews, and ongoing clinical use across the former Eastern Bloc, remains almost entirely absent from Western medical practice — and what the toxic burden it’s meant to address actually is.
The Zeolite Book gathers the Soviet clinical record, the Western peer-reviewed studies, three contemporary practitioner voices, and three serious counterviews into one honest treatment. That’s why the book runs to seven appendices. 288 pages, four parts, three practitioner voices, three counterviews, seven appendices. The honest treatment is the argument.
Blog Roll
 Aletho News
- UAE security forces tortured, killed journalist for opposing Israel normalization: Report
- They Compared the Spice to the Drug. The Spice Won — Again. (Part 2)
- Thomas Fazi: NATO’s Hybrid Warfare – Deception & Permanent War
- Wrong, AP and NPR: Europe’s 50,000 Heat Deaths Are a Computer-Model Estimate, Not a Real Body Count
- Questioning Your Doctor Is Now Considered A Psychological Problem (Seriously)
- London tourism expo promotes Israeli agency linked to theft of Palestinian land
- Dockworkers launch global strike against Israeli and US military shipments
- Europe facing gas price shock – Gazprom chief
- Ukraine continues recruiting people with disabilities
- Weaponized Journalism: 2021 Sayer Ji Interview with NPR
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!

