CDC’s Ludicrous Makeover
BY HARVEY RISCH | BROWNSTONE INSTITUTE | AUGUST 18, 2022
CDC announced that the institutes have done an external/self-study and proposed a makeover “to restore public trust.” Dr. Walensky said that she “plans to remake the culture to help the agency move faster when it responds to a public health crisis. She also wants to make it easier for other parts of the government to work with the CDC, and wants to simplify and streamline the website to get rid of overlapping and contradictory public health guidance.”
The CDC’s announcement covers everything except the fundamental problem to which the director and the external reviewer are blind: industry subservience and epidemiologic incompetence.
CDC has published numbers of fatally flawed study reports over the last two years in MMWR, its captive journal. No amounts of “moving faster” will fix this problem. It took CDC two years to figure out that the vaccines are not an effective public health tool for reducing infection spread, something that I and numerous colleagues have been saying for more than a year.
CDC has still not recognized that for Covid, masks are useless, that distancing is useless, that general population testing is virtually useless for managing the population pandemic.
That the CDC has reviewed itself and only found trivialities and not the systematic problems that caused it to produce repeatedly failing policies shows that this review exercise was only window dressing. It was not a serious review.
The CDC needs a completely different independent external review to understand how it as a public health agency with MD and PhD epidemiologists could get so much science wrong for so long. The current makeover plans are ludicrous, will fool no one, and will not restore any of the large amount of public trust that has been lost by its poor performance over the last 2.5 years.
Harvey Risch is Professor of Epidemiology in the Department of Epidemiology and Public Health at the Yale School of Public Health and Yale School of Medicine. Dr. Risch received his MD degree from the University of California San Diego and PhD from the University of Chicago. After serving as a postdoctoral fellow in epidemiology at the University of Washington, Dr. Risch was a faculty member in epidemiology and biostatistics at the University of Toronto before coming to Yale.
(Yet) more worrying data on myocarditis in children
Thai data shows alarming signal
Health Advisory & Recovery Team | August 18, 2022
HART recently published an article summarising the results of a study performed in the US military which found that nearly 3% of those vaccinated with smallpox vaccine developed subclinical myocarditis (defined by an increased troponin level – which was prospectively measured in all subjects).
It should be emphasised that no “safe” level of increased troponin has been identified. Any increase is a potential cause for concern in any age group, let alone young people.
In that article, we expressed alarm that – given the worrying data regarding myocarditis and Covid mRNA vaccination – a simple prospective before and after study of troponin levels had never been performed in any age group.
It turns out that we weren’t the only people suggesting such a study needs performing. The FDA thought so too.
As Vinay Prasad writes – apparently the FDA made it a condition of the Emergency Authorisation.

The agreed dates for such a study are frankly bizarre, given how simple and quick such a study would be to perform and how many billions of doses of this product have / are being injected into people of all ages, with no (official) abatement in enthusiasm yet apparent.
However, such a study has in fact now been performed. Not by any investigators in the wealthy Western world, for whom carrying out such an exercise would have been like a proverbial “cake-walk”.
No, instead we have had to rely on a publication out of Thailand, which can be found here. In this study, they measured troponin levels in ~300 teenagers aged 13 to 18 in 2 schools, both before and after their second dose of Pfizer mRNA vaccine.
A lot has now been written about this study already, and we will therefore refer you to the best summaries published to date, which are those from Vinay Prasad and Brian Mowery although the former analysis is, in our opinion, far too muted given the gravity of the situation.
The bottom line is that troponin elevation or cardiac symptoms indicative of myocarditis/pericarditis were identified in 7 (3.5%) of 200 boys, 5 of whom (2.5%) had elevated troponin levels.
(Troponin is a substance released from heart cells which is indicative of damage to heart muscle cells, which have no repair mechanism. Testing for its presence is commonly performed when patients present with chest pain suggestive of a possible heart attack.)
There was a zero signal (for either symptoms or raised troponin) in girls.
John Campbell – who has around 2.5m followers and had previously been extremely enthusiastic about the mRNA covid vaccines – appears visibly shocked by this data in his video covering it.
He points out that anyone with a raised troponin level would ordinarily be ordered to rest due to the association between myocardial damage and fatal arrhythmia on exertion. The implication must surely be that the administration of these agents to children and young people must cease, since the notion that all will routinely be troponin-tested is clearly ridiculous.
Worse still: this 2.5% (which is bad enough) only represents the cases where the troponin levels exceeded a specific threshold of 13 pc/mg. The authors have not provided the raw data and it is perfectly possible that there were many more boys (and possibly girls) in whom some clinically relevant elevated troponin might have been evident but not to this level.
It is to be noted that as described here the cut-off of 13 pc/ml (based on the 99th percentile for a normal reference population) appears to relate to the use of troponin levels to determine a differential diagnosis of chest pain when a myocardial infarction (“heart attack”) is suspected – ie to answer the typical question facing ER doctors (and one which is not as easy to answer merely based on symptoms as many might imagine): “has there been cardiac involvement, or is this just indigestion?”
Because of the mechanism of a typical heart attack (blockage of an artery) you’d actually expect a heterogeneous response – either an amount of heart muscle has been damaged sufficient to result in high troponin elevation, or not (resulting in no elevation). Hence the use of a certain cut-off can reasonably reliably rule out an incident such as heart attack.
However, with myocarditis, we should surely be concerned with identifying any myocardial damage at all, not screening for MI as a differential diagnosis. In this context, a completely safe level is unknown. It may be that any elevation means there has been myocardial damage. Depending on where this is, it may be associated with an increased chance of suffering a fatal arrhythmia.
We don’t know the answers to these questions. Given where we are, that’s alarming.
In the absence of comorbidities, young people were never at risk from covid and certainly are not at risk from omicron. Most have been infected and have natural immunity. The mass administration of these agents to the young was always completely unjustifiable; this latest data brings the decision to continue with this program into the more serious realm of malfeasance.
What to Know Before Deciding to Take The Novavax Injection
Accepting an injection of spike protein hoping it is safe or effective is absurd. Yet, many are again forced to make a decision threatening their health and ability to support their family.
By Pierre Kory, MD, MPA | August 17, 2022
A subscriber asked me to write a post about my thoughts on Novavax because she “really trusts my judgement.” Flattered, I felt like I should share what they are. So here goes.
Before any medical intervention, but especially in the case of a novel or barely tested one, a long standing practice of medical ethics is that informed consent must be obtained. The emphasis should be on the informed part and not the consent part. Note that informed consent has been one of the foundations of medical ethics, essentially an inviolable standard, or at least it used to be before this “emergency” came along where now you have pharmacists injecting children with barely a mention of the risks, “because they might be too scared to take the shot.”
Informed consent discussions are simple in structure but often complex and time-consuming to conduct. It relies on providing the patient with as detailed and comprehensive a knowledge of the risks, benefits, and alternatives to the intervention.
So, should we go through an informed consent discussion with the novel Novavax injection? Actually, I would not. Why? Because I don’t hold informed consent discussions for interventions I do not recommend or would not want my patient to consider. I instead tell them not to consider and give them my reasons for that recommendation. Thus, I only conduct informed consent discussion for interventions that I feel would bring about greater benefits than risks (generally much greater), and I would only do so for patients with active illness in order to get them better. A vaccine is a much different proposition as they are given to patients without disease.
Why would I not even consider Novavax as a reasonable option? Simple:
- There has never been a successful or safe coronavirus vaccine. The last 18 months have shown that COVID vaccines lead to increased chances of getting ill, equal or increased chances of transmitting, and higher likelihood of entering hospital and dying. And that is leaving unmentioned the lethality and toxicity of the mRNA platform ones. See my “Vaccine Exemption Letter” post for the data to support these statements. The coronavirus is a rapidly mutating virus, thus vaccines will always be non-neutralizing because by the time they are manufactured and ready for injection, the virus has mutated into forms poorly responsive to older, narrower antibodies.
- Novavax is still formulated with a two and a half year-old protein for this rapidly mutagenic coronavirus, so it would be like giving a two and a half year old flu shot for this years flu (worse actually). Yet our health system, including every single academic medical center in the country is still mandating and eager to adopt use of an outdated viral protein. I would love to say this is beyond belief, but this is the world we live in now.
- We now have the omicron variant circulating, which is generally well tolerated by most, particularly those who are healthy or young (and even the old), and especially those with natural immunity.
- The country now has abundant natural immunity, which even the CDC now admits offers equal protection (actually, natural immunity offers better protection but let’s give the CDC some credit for telling at least a partial truth). So why are we still vaccinating and/or mandating in those who have recovered from COVID?
- Vaccinating against respiratory viruses works very poorly as the antibodies do not reach high concentrations in the nasal and respiratory mucosa which is where the virus enters. The flu vaccine is almost completely ineffective, even when you get this years flu shot. Not known by most.
- Vaccinating against respiratory viruses with non-neutralizing vaccines actually weakens and warps the immune system such that you are more likely to get other respiratory viruses or illnesses as well (this has been well reported after flu vaccinations given that those vaccinated against the flu are more susceptible to other respiratory viral infections).
- Proposing a novel and barely tested product coming out of the pharmaceutical industry to a patient is a wicked proposition in modern times. Note the pharmaceutical industry is a documented criminal industry which has repeatedly put out unsafe and ineffective products (even deadly, i.e opioids, Avandia, Vioxx, Bextra, the list goes on), followed by burying the adverse event data while pushing their wares through control of professional societies, federal/state legislation, and captured agencies. They have paid over $12 billion in criminal fines and over $16 billion in civil fines, just in the last 20 years across the 20 largest settlements. Their history of these actions stretches even longer.
- The history of criminality around the COVID vaccines dwarfs any actions the industry has done in the past. The Pfizer documents that the PFDA (the P is not a typo) tried to hide for 75 years reveal insane amounts of manipulations to try to show they work and are safe. They didn’t and weren’t. Further the testimony from the Ventavia/Pfizer whistleblower Brook Jackson reveals that the studies were so poorly done with such little follow-up of patients that they are simply not credible. Remember, Pharma. Does. Not. Care. About. Your. Health. Just your wallet (actually the government’s wallet, which I suppose is also your wallet).
So, conceptually, I think the idea of getting any coronavirus vaccine at this point is preposterous. However, let’s try to do a more traditional informed consent using the structure of risks/benefits/alternatives. The following is what I think other providers (or pharmacists egads) should be telling people prior to offering them Novavax, or more accurately, in order to get them to avoid it.
Yes, Novavax is a “non-mRNA” vaccine and is designed more along the line of a traditional vaccine in that an amount of viral protein is injected into the arm, it is then recognized as a “foreign” protein by our immune system which then makes antibodies against it. These antibodies are then thought (“hoped” remember) to help clear the virus rapidly and efficiently after exposure such that we avoid illness. Sounds good on paper. Not. Just ask Geert Vanden Bossche, one of the worlds top immunologists and vaccine experts.
RISKS
Novavax delivers the spike protein. As a self-described clinical expert in spike-protein induced disease, the spike protein is a pathogen. A pathogen is a substance or organism that is capable of inducing illness. Note that I call myself an expert because there are very few of us out here studying it’s pathogenicity, however I would argue Professor Paul Marik has taken the lead across the globe in amassing all the basic science and clinical research underlying the knowledge of the mechanisms and treatments of spike-protein induced diseases. That scholarly document is in evolution, and has over 300 scientific references at this point, with rapid evolutions and additions each week. Note that it appears to be the world’s sole “comprehensive” scholarly work on spike protein pathogenicity and empirically proposed treatments.
Another great sadness about the US COVID response is that almost the entire health system and all of academia have yet to recognize the spike as a pathogen or formulate any approach to treating Long-Haul or Post-Vaccine Injury. Until they do, they will continue to fail to recognize the causes or mechanisms of these syndromes as well as to offer effective treatments. And, it goes without saying, they will not be able to discuss this in thier ill-informed consent discussions. Their deplorable failure at treating these disabling diseases is astounding and will continue for the foreseeable future. Remember, the system docs won’t treat because they are all members of the Church of RCT Fundamentalism (a.k.a “evidence based medicine.”) You know, where they will sit there paralyzed until some massive randomized controlled trial is published in a high-impact medical journal and then is recommended by a federal agency or national medical society. You know what that system produces by now if you read my Substack. Not only will it leave patients untreated for months to years, but while the docs sit around waiting, Pharma, via the agencies and media, will suppress or attack any generic medicines or supplements that front-line doctors and patients have found effective. They will do this with ferocity and depravity until such a time they can “save the day” with the massive promotion of a novel, pricey Big Pharma pill which they will get our government to pay for at a price they set. Think about what happened to ivermectin and hydroxychloroquine until Pharma saved the day with the pathetic and poisonous Paxlovid using our government coffers. Rinse repeat here.
The two major and complex diseases unleashed by the spike are what we call “long haul” and “post-vaccine injury” syndromes. I probably should differentiate post-vaccine into two subtypes, with one being an acute, sudden death syndrome caused by massive heart attacks, myocarditis (which can cause lethal arrhythmias or pump failure), and/or massive strokes. Excess mortality amongst the vaccinated in 2021 skyrocketed and is showing up in Life Insurance industry data in both the U.S and other countries. However I don’t see those events in my practice because they are sudden deaths occurring in asymptomatic patients (who are often swimming or running or doing something else fun until they suddenly drop dead). My practice instead sees patients who suffer with the more chronic subtype consisting of myriad, disabling symptoms across multiple organ systems. Now, whether there is enough spike in Novavax to produce similar deadly events or chronic syndromes in the future, who knows. More on that below.
SHORT TERM RISK DATA
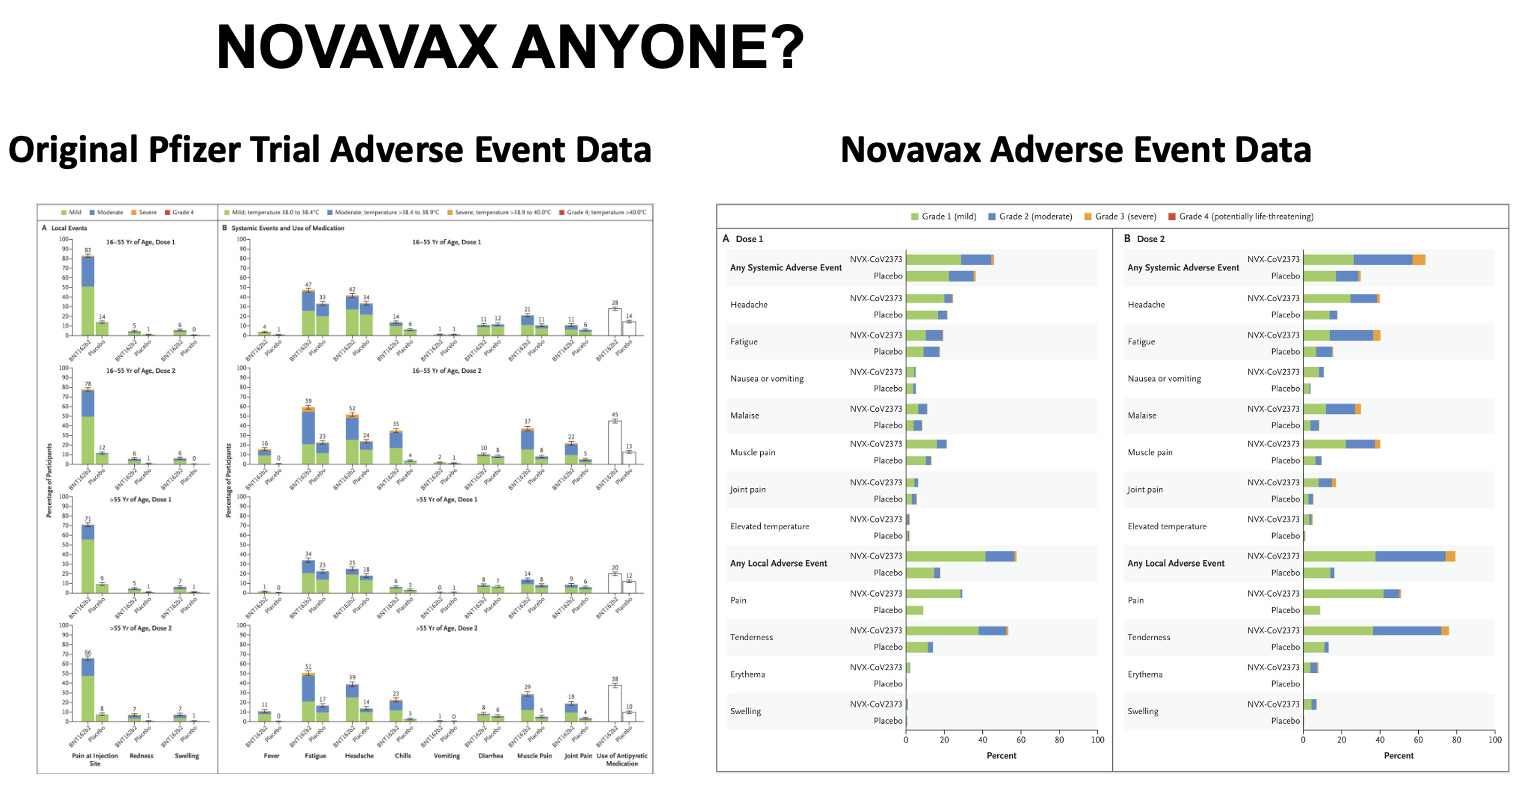
Not looking good here folks. Let’s take a look at the actual published trial of Novavax, and their chart detailing the “side effects.” Then let’s compare it to Pfizers mRNA “vaccine” trial published in December 2020. Look carefully. I will interpret these charts below.
Click for full size
Here is how I interpret the data:
- The “local” and “systemic” adverse events are absurdly high in both. I remember thinking back in December 2020 when I was reading the Pfizer trial, I said to myself, “Wow, that does NOT look friendly!” Not just the wickedly high frequency of really sore arms with redness and swelling, but the very high rates of “systemic symptoms” of fatigue, headache, chills, vomiting, muscle pain. Very high rates of those. Ouch.
- Next, look at the “dose response,” meaning look at the incidence of adverse events after the 2nd shot compared to the 1st shot. If it is higher after the 2nd, it indicates a “dose-response relationship,” which, when we are talking about a therapeutic, is a pillar of evidence to support the efficacy of the drug. For instance, ivermectin in COVID has a strong dose response relationship, meaning the higher the dose, the more effective it is (that is why all the high impact trials tried as much as they could to limit the dose of ivermectin, in particular during history’s most fraudulent trial called the TOGETHER trial).
Conversely, a dose-response in terms of side effects is a pillar of the measure of toxicity. The more you give, the sicker you get. Not cool. Now take a look at Pfizers published chart above, keeping in mind, these are only the short term systemic side effects.
- Pfizer: fatigue goes from 47% after the 1st to 59% after the 2nd in young folks and 34% up to 51% in older folks. Chills: 14% to 35% in young, 6% to 23% in old. Same pattern and increases with muscle pains and also joint pains and use of anti-pyretic medications.
- Now, take a look at Novavax. Note how they don’t give you the numeral percentages and instead make you crane your neck and use a ruler to estimate the actual incidences and increases. But just looking at the height of the bars from shot 1 to shot 2 and the increases in the yellow at the tops of the bars (yellow = “Grade 3” reactions – i.e. more severe), you see again what looks like a scary shot to me with some of the local and systemic events reported even higher than with Pfizer’s mRNA shot! So, is Novavax safer?
LONG TERM SIDE EFFECTS. Unknown. Remember the famous, “I guess we will just have to give it to see how safe it is” by one of the nations top vaccine experts. I swear, again, and I say this often, you just cannot make this stuff up. So, an informed consent discussion should relate that long term side effects are unknown. Remember as well, we are not in a supposed “emergency” anymore, despite the fact our government keeps renewing its emergency powers. If the person conducting this discussion tries to argue that in terms of long term effects, it is safe and effective because the mRNA vaccines were safe and effective, that is so categorically ridiculous it does not even bare addressing. Again, read my “Vaccine Exemption Letter” post for the data on toxicity and lethality of those vaccines. Do not proceed. My caution would be that spike protein is a pathogen with sequences that we know generate antibodies that then are capable of attacking many tissues (what are called autoantibodies which cause a category of diseases called “auto-immune” diseases). Also, spike protein, when broken down by the body is known to generate amyloid like fragments which are highly thrombogenic (i.e. cause clotting). Spike protein also stimulates immune cells called monocytes and macrophages which disturb numerous organ functions. Spike protein is also toxic to mitochondria which are the energy producing parts of each cell. In summary, don’t sign up for any more spike protein than is already circulating in the world.
Also, Novavax, like the mRNA vaccines uses “nanoparticles” in a “saponin-based adjuvant” solution which is novel and proprietary, patented only in 2020. Well, thats reassuring no? Their published paper states that the adjuvant and the vaccine was found to be “safe and immunogenic” in Phase 1 and 2 trials. Then I found this in the supplementary appendix from one of the earlier trials, ”the mechanism of Matrix-M1 (the adjuvant) is not well defined, but it has been associated with a potent induction of leukocyte activation and migration into the draining lymph nodes in their previous study.” Not reassuring.
EFFICACY
Unknown, but likely ineffective as it has not been tested against Omicron, or any of its sub-variants or whatever future variant will be circulating when it rolls out. Plus, as we know now, all the predicted efficacy reported from COVID-19 vaccine trials were never observed in the real-world, again likely due to trial shenanigans and data manipulations and removal and/or miscategorization of those who fell ill during the trial or simply due to the fact the virus is rapidly mutating. Even if it were effective, we know from the past two years, it would be short lived. I again have to mention natural immunity. It already protects against severe disease and reasonably well from re-infection, and there is no credible data to suggest adding an even older spike protein vaccine using a newly patented adjuvant will better protect you or make you healthier.
ALTERNATIVES TO VACCINATION
For readers of my Substack, you all know that you can always just skip the vaccine and instead just rely on early treatment which has been shown to be near perfectly effective in achieving rapid recovery and avoidance of hospitalization and death, especially when given in synergistic combinations like the FLCCC’s or the AAPS’s protocols. In fact, as you know, no vaccine would ever get an EUA or approval if effective treatments were available. Further, there are now over three dozen effective treatments supported by controlled trials, with many of them repurposed and/or over the counter. I suppose you could also just rely on Paxlovid given its demonstration of such incredible efficacy in treating President Biden and Dr. Fauci.
Hope this helps.
P.S. I opened a tele-health clinic providing care not only in the prevention and treatment of acute COVID, but with a specialized focus on the study and treatment of both Long-Haul and Post-Vaccination injury syndromes. If anyone needs our help, feel free to visit our website at www.drpierrekory.com.
P.P.S. I am getting professional help (hah!) to write a book about what I have personally witnessed and learned during Pharma’s historic Disinformation war on ivermectin. Pre-order here for:

RNA for Moderna’s Omicron Booster Manufactured by CIA-Linked Company
BY WHITNEY WEBB |
UNLIMITED HANGOUT| AUGUST 17, 2022
Since late last year, messenger RNA for Moderna’s COVID-19 vaccines, including its recently reformulated Omicron booster, has been exclusively manufactured by a little known company with significant ties to US intelligence.
Earlier this week, the United Kingdom became the first country to approve Moderna’s reformulated version of its COVID-19 vaccine, which claims to provide protection against both the original form of the virus and the significantly less lethal but more transmissible Omicron variant. The product was approved by the UK’s Medicines and Healthcare Products Regulatory Agency (MHRA) with the support of the UK government’s Commission on Human Medicines.
Described by UK officials as a “sharpened tool” in the nation’s continued vaccination campaign, the reformulated vaccine combines the previously approved COVID-19 vaccine with a “vaccine candidate” targeting the Omicron variant BA.1. That vaccine candidate has never been previously approved and has not been the subject of independent study. The MHRA approved the vaccine based on a single, incomplete human trial currently being conducted by Moderna. The company promoted incomplete data from that trial in company press releases in June and July. The study has yet to be published in a medical journal or peer reviewed. No concerns have been raised by any regulatory agency, including the MHRA, regarding Moderna’s past history of engaging in suspect and likely illegal activity in past product trials, including for its original COVID-19 vaccine.
The approval comes shortly before several Western countries, including the UK, plan to conduct a massive COVID-19 booster vaccination campaign this fall. Moderna has also noted that approval for its Omicron booster vaccine are pending in the US, EU, Australia and Canada – all of which are also planning fall vaccination campaigns focused on COVID-19. The company’s CEO, Stéphane Bancel, has called the reformulated vaccine “our lead candidate for a Fall 2022 booster.”

Moderna CEO Stéphane Bancel, Source: ClockworkOrange
However, unlike the company’s original COVID-19 vaccine, the genetic material, or messenger RNA (mRNA), for this new vaccine, including the newly formulated genetic material meant to provide protection against the Omicron variant, is being manufactured, not by Moderna, but by a relatively new company that has received hardly any media attention, despite its overt links to US intelligence. Last September, it was quietly announced that a company called National Resilience (often referred to simply as Resilience) would begin manufacturing the mRNA for Moderna COVID-19 vaccine products. Under the terms of the multi-year agreement, “Resilience will produce mRNA for the Moderna COVID-19 vaccine at its facility in Mississauga, Ontario, for distribution worldwide.”
“Reinventing Biomanufacturing”
National Resilience was founded relatively recently, in November 2020, and describes itself as “a manufacturing and technology company dedicated to broadening access to complex medicines and protecting biopharmaceutical supply chains against disruption.” It has since been building “a sustainable network of high-tech, end-to-end manufacturing solutions with the aim to ensure the medicines of today and tomorrow can be made quickly, safely, and at scale.” It further plans to “reinvent biomanufacturing” and “democratize access to medicines,” namely gene therapies, experimental vaccines and other “medicines of tomorrow.”
In pursuit of those goals, the company announced it would “actively invest in developing powerful new technologies to manufacture complex medicines that are defining the future of therapeutics, including cell and gene therapies, viral vectors, vaccines, and proteins.” It was founded with the reported intention “to build a better system for manufacturing complex medicines to fight deadly diseases” as a way to improve post-COVID “pandemic preparedness.”
The company initially marketed its manufacturing capabilities as “the Resilience platform”, and offers principally “RNA Modalities”, including RNA development for vaccines, gene editing and therapeutics; and “Virus Production”, including viral vectors, oncolytic viruses (i.e. a virus engineered to preferentially attack cancer cells), viruses for use in vaccine development and gene-edited viruses for unspecified purposes. It is worth noting that, to date, many controversial “gain-of-function” experiments have justified modifying viruses for the same purposes as described by National Resilience’s Virus Production capabilities. In addition, National Resilience offers product formulations and other modalities, such as biologics and cell therapies, to its clientele and the “Virus Production” of its website has since been removed.

Resilience CEO Rahul Singhvi, Source: Resilience
National Resilience, being such a young company, has very few clients and there is little publicly available information on its manufacturing capabilities aside from the company’s website. The firm only acquired its first commercial manufacturing plant in March 2021, located in Boston, MA and purchased from Sanofi, followed shortly thereafter by the acquisition of another separate plant located in Mississauga, Ontario, Canada. Makeovers were announced for the plants, but little is publicly known about their progress. Prior to the acquisitions, the company had been subleasing a Bay area facility in Fremont, California. Reporters were puzzled at the time as to why a company with roughly 700 employees at the time had acquired a total of 599,00 square feet of manufacturing space after having only emerged from stealth less than 6 months prior.
In April 2021, National Resilience acquired Ology Bioservices Inc., which had received a $37 million contract from the US military the previous November to develop an advanced anti-COVID-19 monoclonal antibody treatment. This acquisition also provided National Resilience with its first Biosafety Level 3 (BSL-3) laboratory and the ability to manufacture cell and gene therapies, live viral vaccines and vectors and oncolytic viruses.
Despite being in the earliest stages of developing its “revolutionary” manufacturing capabilities, National Resilience entered into a partnership with the Government of Canada in July of last year. Per that agreement, the Canadian government plans to invest CAD 199.2 million (about $154.9 million) into National Resilience’s Ontario-based subsidiary, Resilience Biotechnologies Inc. Most of those funds are destined for use in expanding the Ontario facility that Resilience acquired last March and which is now manufacturing the mRNA for Moderna’s COVID-19 products. Canada’s Minister of Innovation, Science and Industry, François-Philippe Champagne, asserted at the time that the investment would “build future pandemic preparedness” and help “to grow Canada’s life science ecosystem as an engine for our economic recovery.” More recently, in 2022, the company has announced a few new clients – Takeda, Opus Genetics and the US Department of Defense.
According to National Resilience’s executives, the company’s ambitions apparently go far beyond manufacturing RNA and viruses. For instance, Resilience CEO Rahul Singhvi has claimed that the company is seeking to build “the world’s most advanced biopharmaceutical manufacturing ecosystem.” Yet, Singhvi has declined to offer much in the way of specifics when it comes to exactly how the company plans to become the planet’s most elite biomanufacturing company.
In an interview with The San Francisco Business Times, Singhvi states that Resilience is looking to fill its massive manufacturing plants with “technologies and people that can set and apply new standards for manufacturing cell therapies and gene therapies as well as RNA-based treatments.” Prior to Resilience, Singhvi was CEO of NovaVax and an operating partner at Flagship Pioneering, which played a major role in the creation and rise of Moderna.
Singhvi has further insisted that National Resilience is “not a therapeutics company, not a contractor and not a tools company” and instead aims “to boost production using the new therapeutic modalities” such as RNA-based treatments, which have become normalized in the COVID-19 era. Whereas contract manufacturers “are like kitchens, with pots and pans ready for any recipe,” “what we’re trying to do is fix the recipes,” Singhvi has explained. One member of Resilience’s board of directors, former FDA Commissioner and Pfizer Board member Scott Gottlieb, has described the company as seeking to act as the equivalent of Amazon Web Services for the biotechnology industry.
Essentially, Resilience bills itself as offering solutions that will allow “futuristic” medicines, including mRNA vaccines, to be produced more quickly and more efficiently, with the apparent goal of monopolizing certain parts of the biomanufacturing process. It also appears poised to become the manufacturer of choice for mRNA vaccines and experimental therapeutics in the event of a future pandemic, which some public health “philanthropists” like Bill Gates have said is imminent.
Perhaps the company’s most noteworthy ambition relates to their claims that they support clients through the government regulatory process. Given the company’s emphasis on speedy mass production of experimental gene therapies, its stated intention of getting the “futuristic” medical products it manufactures to market as quickly as possible seems at odds with the slower, traditional regulatory processes. Indeed, one could easily argue that the approvals of mRNA vaccines for the first time in human history during the COVID-19 crisis were only possible because of the major relaxing of regulatory procedurse and safety testing due to the perceived urgency of the situation.
Resilience seems intent on seeing that phenomenon repeat itself. As previously mentioned, the company claims to allow for the setting and application of “new standards for manufacturing cell therapies and gene therapies” and also says it plans to become a “technology-aggregating standards bearer that helps therapies come to market more efficiently.” It previously offered on its website “regulatory support” and “strategy consulting” to clients, suggesting that it would seek to mediate between clients and government regulators in order to fulfill its goal of having the products it manufactures taken to market more quickly. In addition, upon launch, the company claimed it planned to obtain unspecified “regulatory capabilities.” If so, it is certainly notable that former top Food and Drug Administration (FDA) officials are either on the company’s board or, as will be noted shortly, played a major role in the company’s creation.
The People Behind Resilience
Resilience was co-founded by Biotech venture capitalist Robert Nelsen, who is known for listening “to science’s earliest whispers, even when data are too early for just about anyone else.” Nelsen was one of the earliest investors in Illumina, a California-based gene-sequencing hardware and software giant that is believed to currently dominate the field of genomics. As mentioned in a previous Unlimited Hangout investigation, Illumina is closely tied to the DARPA-equivalent of the Wellcome Trust known as Wellcome Leap, which is also focused on “futuristic” and transhumanist “medicines.” Nelsen is now chairman of National Resilience’s board, which is a “Who’s Who” of big players from the US National Security State, Big Pharma and Pharma-related “philanthropy.”

Bob Nelsen of ARCH Venture Partners, Source: ARCH Venture Partners
However, while Nelsen has been given much of the credit for creating Resilience, he revealed in one interview that the idea for the company had actually come from someone else – Luciana Borio. In July of last year, Nelsen revealed that it was while talking to Borio about “her work running pandemic preparedness on the NSC [National Security Council]” that had “helped lead to the launch of Nelsen’s $800 million biologics manufacturing startup Resilience.”
At the time of their conversation, Borio was the vice president of In-Q-tel, the venture capital arm of the CIA that has been used since its creation in the early 2000s to found a number of companies, many of which act as Agency fronts. Prior to In-Q-Tel, she served as director for medical and biodefense preparedness at the National Security Council during the Trump administration and had previously been the acting chief scientist at the FDA from 2015 to 2017.
Borio is currently a senior fellow for global health at the Council on Foreign Relations, a consultant to Goldman Sachs, a member of the Bill Gates-funded vaccine alliance CEPI, and a partner at Nelsen’s venture capital firm ARCH Venture Partners, which funds Resilience. Nelsen’s ARCH previously funded Nanosys, the company of the controversial scientist Charles Lieber. Around the time of her conversation with Nelsen that led to Resilience’s creation, Borio was co-writing a policy paper for the Johns Hopkins Center for Health Security that recommended linking COVID-19 vaccination status with food stamp programs and rent assistance as a possible means of coercing certain populations to take the experimental vaccine.
Borio is hardly Resilience’s only In-Q-Tel connection, as the CEO of In-Q-Tel, Chris Darby, sits on the company’s board of directors. Darby is also on the board of directors of the CIA Officers Memorial Foundation. Darby was also recently a member of the National Security Commission on Artificial Intelligence (NSCAI), where members of the military, intelligence community and Silicon Valley’s top firms argued for the need to reduce the use of “legacy systems” in favor of AI-focused alternatives as a national security imperative. Among those “legacy systems” identified by the NSCAI were in-person doctor visits and even receiving medical care from a human doctor, as opposed to an AI “doctor.” The NSCAI also argued for the removal of “regulatory barriers” that prevent these new technologies from replacing “legacy systems.”

Resilience Board Member Drew Oetting, Source: 8VC
Another notable board member, in discussing Resilience’s intelligence ties, is Drew Oetting. Oetting works for Cerberus Capital Management, the firm headed by Steve Feinberg who previously led the President’s Intelligence Advisory Board under the Trump administration. Cerberus is notably the parent company of DynCorp, a controversial US national security contractor tied to numerous scandals, including scandals related to sex trafficking in conflict zones. Oetting is also part of the CIA-linked Thorn NGO ostensibly focused on tackling child trafficking that was the subject of a previous Unlimited Hangout investigation.
Oetting is also the co-founder of 8VC, a venture capital firm that is one of the main investors in Resilience. 8VC’s other co-founder is Joe Lonsdale and Oetting “started his career” as Lonsdale’s chief of staff. Lonsdale is the co-founder, alongside Peter Thiel and Alex Karp, of Palantir, a CIA front company and intelligence contractor that is the successor to DARPA’s controversial Total Information Awareness (TIA) mass surveillance and data-mining program. In addition, Oetting previously worked for Bill Gates’ investment fund.
Also worth noting is the presence of Joseph Robert Kerrey, former US Senator for Nebraska and a former member of the conflict-of-interest-ridden 9/11 Commission, on Resilience’s board. Kerrey is currently managing director of Allen & Co., a New York investment banking firm which has hosted an annual “summer camp for billionaires” since 1983. Allen & Co. has long been a major player in networks where organized crime and intelligence intersect, and is mentioned repeatedly throughout my upcoming book One Nation Under Blackmail. For instance, Charles and Herbert Allen, who ran the firm for decades, had considerable business dealings with organized crime kingpins and frontmen for notorious gangsters like Meyer Lansky, particularly in the Bahamas. They were also business partners of Leslie Wexner’s mentors A. Alfred Taubman and Max Fisher as well as associates of Earl Brian, one of the architects of the PROMIS software scandal – which saw organized crime and intelligence networks cooperate to steal and then compromise the PROMIS software for blackmail and clandestine intelligence-gathering purposes. Allen & Co. was a major investor in Brian’s business interests in the technology industry that Brian used in attempts to bankrupt the developers of PROMIS, Inslaw Inc. and to market versions of PROMIS that had been compromised first by Israeli intelligence and, later, the CIA.
In addition to these intelligence-linked individuals, the rest of Resilience’s board includes the former CEO of the Bill & Melinda Gates Foundation, Susan Desmond-Hellmann; former FDA Commissioner and Pfizer board member, Scott Gottlieb; two former executives at Johnson & Johnson; former president and CEO of Teva Pharmaceuticals North American branch, George Barrett; CalTech professor and board member of Alphabet (i.e. Google) and Illumina, Frances Arnold; former executive at Genentech and Merck, Patrick Yang; and Resilience CEO Rahul Singhvi.
To Boost or Not to Boost
It is certainly telling that the normally publicity hungry Moderna has said so little about its partnership with Resilience and that Resilience, despite its ambitious plans, has also avoided the media limelight. Considering Moderna’s history and Resilience’s connections, there may be more to this partnership that meets the eye and concerned members of the public would do well to keep a very close eye on Resilience, its partnerships, and the products it is manufacturing.
Given that we now live in a world where government regulatory decisions on the approval of medicines are increasingly influenced by corporate press releases and normal regulatory procedures have fallen by the wayside for being too “slow,” there is likely to be little scrutiny of the genetic material that Resilience produces for the “medicines of tomorrow.” This seems to be already true for Moderna’s recently retooled COVID-19 vaccine, as there has been no independent examination of the new genetic sequence of mRNA used in the Omicron-specific vaccine candidate or its effects on the human body in the short, medium or long term. For those who are skeptical of the outsized role that intelligence-linked companies are playing in the attempted technological “revolution” in the medical field, it is best to consider Resilience’s role in the upcoming fall vaccination campaign and in future pandemic and public health scenarios before trying its “futuristic” products.
Whitney Webb has been a professional writer, researcher and journalist since 2016. She has written for several websites and, from 2017 to 2020, was a staff writer and senior investigative reporter for Mint Press News. She currently writes for The Last American Vagabond.
Do the smallpox vaccines work to prevent monkeypox?
By Meryl Nass, MD | August 16, 2022
181 monkeypox patients (average age 37) were studied in Spain, and their illnesses described in the Lancet.
Mitjà and co-authors noted that 32 individuals in their cohort (18%) acquired monkeypox infection despite a smallpox vaccination history, which “warrants further investigation to better understand the protection provided by vaccination in the context of the current outbreak.”
Smallpox vaccination of infants ended over 50 years ago. Smallpox was declared eradicated 45 years ago. So few people in a cohort whose average age is 37 would be expected to have been vaccinated—and the vaccine they received would have preceded both ACAM-2000 and Jynneos, and been reliable at preventing smallpox. But it apparently did not prevent recent monkeypox.
In 2002 it was suggested that vaccination-induced immunity to smallpox was long-lasting.
We can thank Tony Fauci’s NIAID for sponsoring the original trial (2003) in which 20 plus year old (expired) smallpox vaccine was diluted to see how much you really needed. You didn’t need that much. This study presumably provided the underpinning for the dilution decision regarding Jynneos.
- When will a public health agency tell us whether the vaccines they are indiscriminately providing to MSM actually work?
- When will they tell us the side effects vaccinees are experiencing?
- And when will they tell us the results of the CDC study of 1600 Congolese healthcare workers that CDC jabbed between 2017 and 2020?
Quadruple-vaxxed Pfizer CEO catches COVID, shills Paxlovid
By Mike Campbell | The Counter Signal | August 15, 2022
Pfizer CEO Albert Bourla unironically tweeted that, despite catching COVID, he was grateful for getting jabbed four times and still requiring another one of his products to treat the infection.
“I would like to let you know that I have tested positive for COVID-19,” he tweeted. “I am thankful to have received four doses of the Pfizer-BioNTech vaccine, and I am feeling well while experiencing very mild symptoms. I am isolating and have started a course of Paxlovid.”
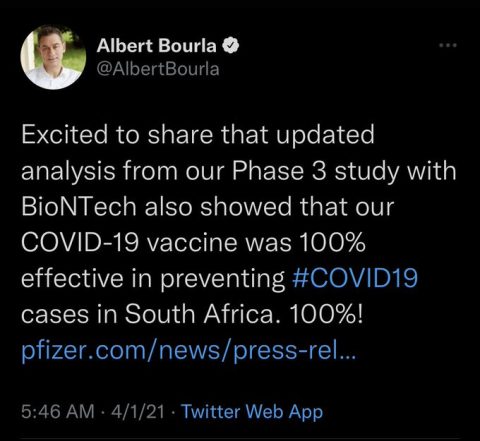
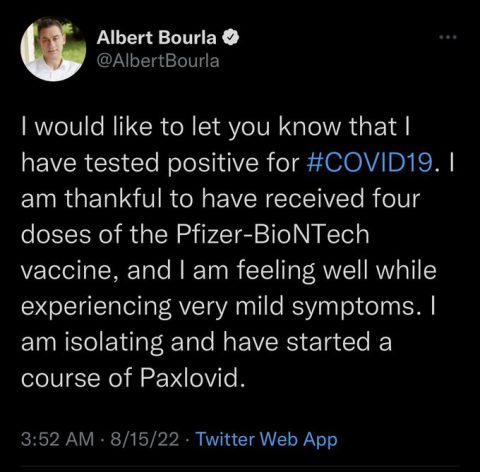
Following his statement, the ridicule via Twitter ratio came on quickly:
Liz Wheeler
Hahahahahahahahahaha remember that time you avoided taking your own vaxx because you knew it was garbage? Until you were found out when Israel refused you entry. I sincerely hope you recover quickly, but you & your 💉 are frauds.
Indeed, it’s harder than ever to take these talking heads seriously.

This is the same company that’s paid millions to settle allegations of bribing doctors and the same company that wanted to keep vaccine data hidden for 75 years, only to be forced by a court order to release nine pages worth of potential vaccine adverse effects.
Now, in this stunning tacit admission, Pfizer’s own CEO has revealed that two boosters can’t even stave off infection. Talk about a product flop.
Of course, Bourla isn’t the only one with a case of the quadruple vaxxed COVID blues. Recently, US President Joe Biden told the world that he’d caught COVID not once but twice despite receiving two boosters.
If there was still any doubt regarding a lack of vaccine efficacy, Pfizer’s CEO has proven that the vaccine can’t stop the spread — which is what everyone was promised when the vaccine was first rolled out.
US oil dynasties fund climate activists

Free West Media | August 15, 2022
According to a media report, the heirs to three US oil dynasties finance climate activists and non-governmental organizations that promote climate protest actions. Descendants of oil barons Getty and Rockefeller allegedly feel responsible for preventing “eradication” on Earth. That may not be the real reason however.
Descendants of the oil billionaires have been paying hundreds of green activists $25 000 a year each for their protests around the world, Britain’s Daily Mail reported August 10. Aileen Getty, Rebecca Rockefeller Lambert and Peter Gil Case fund such salaries through their non-governmental organizations (NGOs).
Aileen Getty, granddaughter of Getty Oil’s founder, now has over $1 million through her Climate Emergency Fund paid to activists. The wealthy heirs to the Rockefeller family, Rebecca Rockefeller Lambert and Peter Gil Case, whose ancestors founded Standard Oil in 1870, have spent over thirty million dollars on the Equation Campaign.
They all pay the activists, who, according to the Daily Mail, have caused disturbances with their actions around the world, especially in recent months, and finance the relevant NGOs. Lambert and Case, for example, put eco-activists from groups like Just Stop Oil on the payroll for $25 000 each and also funded the organization themselves. The descendants of oil baron John D. Rockefeller also established a fund to support anti-fossil fuel protests.
In recent months, thousands of activists have taken to the streets around the world to protest. The environmentalists also rioted and caused destruction, including in the US, Europe, the UK and Australia. Tires of SUVs were punctured in the US, UK and Australia, and famous oil paintings were vandalized in EU countries by the very activists who are on the payrolls of oil heirs’ non-profit organizations.
The Daily Mail questioned this type of funding: “Three American oil scions have been bankrolling mobs of eco-zealots who have terrorized the world by slashing tires, blocking traffic and attacking firms. Aileen Getty, Rebecca Rockefeller Lambert and Peter Gill Case, who are heirs to their families’ huge fortunes, are paying the salaries for thugs through their non-profits in an apparent bid to offset their relatives’ legacies.”
In 2019, Aileen Getty donated $500 000 to Extinction Rebellion climate activists. She herself is convinced that “a comprehensive disruption of everyday life” is necessary for actions. Getty conforms to the stereotype of idle, rich heirs: She contracted HIV from an extramarital affair and has survived numerous drug overdoses.
She told the New York Times that she wanted to support the effectiveness of the activists she sponsored and has so far donated $1 million from her own wealth to the Climate Emergency Fund. In her opinion, the civil disobedience spurned by such grassroots organizations is just a warning signal and the destruction is minimal compared to what is at stake.
She told the newspaper: “Let’s not forget that we’re talking about extinction. Don’t we have a responsibility to do everything we can to protect life on Earth?”
The Daily Mail also pointed out that scaremongering by various scientists are also financed by the oil heirs. In the US, the Climate Emergency Fund of the NGO Scientist Rebellion made $100 000 available for consultant salaries and travel expenses. Eco-warriors need money since they spend their lives protesting. Without funding, we would therefore not see the likes of Greta Thunberg making a fuss.
NASA climate researcher Peter Kalmus, who also belongs to this organization, brought together around 1000 scientists in 25 different countries who blocked traffic and chained themselves to landmark buildings.
‘Wreaking havoc on ordinary people’ to keep oil prices high
According to the Daily Mail, Kalmus justified his involvement in Scientist Rebellion’s concept of disrupting citizens’ everyday lives as follows: “He spent 16 years looking for ways to save the planet and came to the conclusion that the best way to do it is to wreak havoc on ordinary people.”
Last year in June, the Wall Street Journal reported that climate activists were driving up the price of oil: “Some investors are wagering that Wall Street’s preference for green energy will depress spending on oil extraction, setting the stage for supply shortages and higher fuel prices. The bets come as money managers line up trillions of dollars for wind, solar and other renewable programs and expenditures on oil projects tumble. The drop in fossil-fuel spending is becoming so severe that energy companies could struggle to quench the world’s thirst for oil, some analysts say.”
More recently, US sanctions against Russia have also helped to keep oil prices high.
Featured Video

HE SAVED LIVES. NOW HE FACES PRISON.
or go to
Aletho News Archives – Video-Images
From the Archives
NATO Sanctions and the Coming Global Diesel Fuel Disaster
By F. William Engdahl – New Eastern Outlook – 11.04.2022
Amid the ongoing global inflation crisis, NATO heads of state and mainstream media repeat a mantra that high energy prices are a direct result of Putin’s actions in Ukraine since end of February. The reality is that it is the western sanctions that are responsible. Those sanctions including cutting SWIFT interbank access for key Russian banks and some of the most severe sanctions ever imposed, are hardly having an impact on the military actions in Ukraine. What many overlook is the fact that they are increasingly impacting the economies of the West, especially the EU and USA. A closer look at the state of the global supply of diesel fuel is alarming. But Western sanctions planners at the US Treasury and the EU know fully well what they are doing. And it bodes ill for the world economy.
While most of us rarely think about diesel fuel as anything other than a pollutant, in fact it is essential to the entire world economy in a way few energy sources are. The director general of Fuels Europe, part of the European Petroleum Refiners Association, stated recently, “… there is a clear link between diesel and GDP, because almost everything that goes into and out of a factory goes using diesel.” … continue
Blog Roll
 Aletho News
- Trita Parsi: Middle East Unraveling — Are We on the Path to World War?
- Iran FM meets with US envoy on UN meeting’s sidelines at American side’s insistence: Report
- Qatar PM calls for Gulf security framework with Iran, says war must be ‘wake-up call’
- China condemns US extortion of Iranian airlines, rejects Washington’s ‘illegal’ sanctions threats
- Italy to move military personnel from Taif base after missile strike
- Finland’s Stubb tells European leaders to calm down
- Defeating Russia on battlefield impossible – Fico
- Finland’s Gender Clinic Reversal
- Massachusetts Wants Mental Health Visits, Why Does Government Use ‘Health’ to Enter Our Homes & Families?
- US lawmaker admits American people footing bill for Trump’s failed aggression against Iran
- If Americans Knew
- Sanctions are collective punishment: immoral and self-defeating
- Phosphorus Munitions Fired by Israel Burn Groves, Orchards in Southern Lebanon
- Israel Carries Out New Ceasefire Violations Across Gaza
- AI – Emphasis on the ‘I’: Israel Is Funding AI Chatbot Propaganda
- Israel Blocking Hundreds of Wheelchairs for Injured Children From Entering Gaza
- Israel Is Expanding and Upgrading Compounds for Palestinian Militias in Gaza
- The Palestinian-American Residents of This West Bank Town Are Wondering: Where Is Trump?
- Gaza desperately needs tents, wheelchairs, fuel… and everything else (Israel blocks it all) – Daily Update
- Israeli Attacks in Gaza Kill at Least Seven Palestinians Over Three Days, including Woman and Child
- Trump’s militarization of Washington DC as he pursues Israel’s war against Iran
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

