Studies Reveal That Mask Wearing Is Dumbing You Down!

By John O’Sullivan | Principia Scientific | September 12, 2021
A review of peer-reviewed studies suggests regular COVID 19 mask wearing increases risk of mental retardation. Studies affirm what independent medical doctors are increasingly saying – mask wearing mandates are not only unscientific, but contrary to good health and can be deadly!
Below, we show how the scientific literature finds that prolonged mask wearing impedes brain function.
Top medical doctor, Britain’s Dr Vernon Coleman, is Britain’s best-selling medical author for several decades and has repeatedly warned how dangerous mask wearing really is – it can even be deadly to some. He tells us:
“Masks cause hypoxia and hypercapnia – and affect the wearer’s attention and cognitive processes. They make an accident more likely. Anyone driving while wearing a mask should be arrested. Insurance companies should refuse to pay out on claims if a driver was wearing a mask.” [1]
Hypercapnia frequently occurs due to hypoventilation secondary to limited airway pressure and/or tidal volume.
So dangerous is hypoventilation it literally is a matter of life and death to many. Anyone familiar with sleep apnea knows this related condition is well-researched and may be informative in guiding our understanding about impeded breathing, such as from prolonged COVID19 mask wearing.
Dr Coleman, who has built a sterling reputation since the 1980’s as a prominent whistleblower on medical malfeasance, warns:
“Over a dozen scientific papers show clearly that masks are ineffective in preventing the movement of infective organisms. They also reduce oxygen levels and expose wearers to increased levels of carbon dioxide.” [2]
Hypercapnia is the term doctors use to refers to abnormally high levels of carbon dioxide (CO2) in the blood.
As CO2 accumulates in the blood, you’ll see symptoms like difficulty thinking clearly, headaches, and sleepiness. More severe or longer lasting cases of hypercapnia may cause symptoms like dizziness, excessively fast breathing and heart rates, increase in blood pressure, twitching of the muscles, and skin flushing.
Hypoxia
Now keep in mind that when CO2 in the blood is up, as in hypercapnia, then oxygen (O2) must be down. A decrease or less than the normal amount of oxygen in the blood is known as hypoxemia. And if there isn’t enough oxygen in the blood, then there won’t be enough oxygen getting to the organs of the body, which is a condition termed hypoxia.
Hypoxia is, of course, a very serious condition for the body since every organ in the body needs oxygen in order to function. It doesn’t take very long for symptoms to occur as the organs of the body begin to suffer from the lack of necessary oxygen.
See: doi: 10.1016/j.mehy.2008.01.025. Epub 2008 Mar 10.
Chronic hypoxia-hypercapnia influences cognitive function: a possible new model of cognitive dysfunction in chronic obstructive pulmonary disease
“… cognitive impairment is strongly related to combination of chronic hypoxia and hypercapnia, and chronic hypoxia-hypercapnia-induced animal models may mimic the cognitive dysfunction of COPD. “
PubMed (unethically) recently retracted a study titled Facemasks in the COVID-19 era: A health hypothesis
See https://pubmed.ncbi.nlm.nih.gov/33303303/
The above study warned of the lack of science to support mask safety in regard to brain function:
“Many countries across the globe utilized medical and non-medical facemasks as non-pharmaceutical intervention for reducing the transmission and infectivity of coronavirus disease-2019 (COVID-19). Although, scientific evidence supporting facemasks’ efficacy is lacking, adverse physiological, psychological and health effects are established. Is has been hypothesized that facemasks have compromised safety and efficacy profile and should be avoided from use. The current article comprehensively summarizes scientific evidences with respect to wearing facemasks in the COVID-19 era, providing prosper information for public health and decisions making.”
Likewise, in“Exercise with facemask; Are we handling a devil’s sword?” – A physiological hypothesis.
Chandrasekaran B, Fernandes S.Med Hypotheses. 2020 Nov;144:110002. doi: 10.1016/j.mehy.2020.110002. Epub 2020 Jun 22.PMID: 32590322 Free PMC article.
The authors found that:
“Exercising with facemasks may reduce available Oxygen and increase air trapping preventing substantial carbon dioxide exchange. The hypercapnic hypoxia may potentially increase acidic environment, cardiac overload, anaerobic metabolism and renal overload, which may substantially aggravate the underlying pathology of established chronic diseases. Further contrary to the earlier thought, no evidence exists to claim the facemasks during exercise offer additional protection from the droplet transfer of the [COVID] virus.”
We then examined a recent PubMed study on the impacts of walking while wearing masks Jul-Aug 2021;34(4):798-801. doi: 10.3122/jabfm.2021.04.200559.
Effects of Wearing Facemasks During Brisk Walks: A COVID-19 Dilemma
The objective of this study was to evaluate the effects of facemasks on inhaled oxygen and exhaled carbon dioxide. Healthy adults were assessed at rest and during slow and brisk 5-minute walks, with and without masks. What the results showed was that:
“EtCO2 increased; the rise was significantly higher while wearing masks: slow walk, mean EtCO2 (mmHg) change +4.5 ± 2.4 versus +2.9 ± 2.3, P = .004; brisk walk EtCO2 change +8.4 ± 3.0 versus +6.2 ± 4.0, P = .009, with and without masks, respectively. Wearing masks was also associated with higher proportions of participant hypercarbia (EtCO2 range, 46-49 mmHg) compared with walking without masks” and “Sensations of difficulty breathing and shortness of breath were more common while walking with masks.”
Thus, real world studies conducted during the pandemic are signaling a warning that prolonged mask wearing causes a shortage of oxygen to the brain and unhealthy blockage of excretion of carbon dioxide waste from the body.
Both hypoxia and hypercapnia are known dangerous medical conditions, but if you have avidly followed the FAKE NEWS peddled by the mainstream media you will never have heard of such risks from masking up.
While it is proven that in severe cases death may result, the more insidious danger is the unseen, long term effects on our brains. Just spare a thought for the harm being inflicted on children ordered to wear these soiled rags all day in schools.
To clarify the dangers on a strictly objective scientific footing we looked to American Journal of Respiratory and Critical Care Medicine (Volume 186, Issue 12) and looked at The Effect of Hypoxia–Hypercapnia on Neuropsychological Function in Adult Respiratory Distress Syndrome which detailed actual impacts of low oxygen (Hypoxia) on human subjects. https://www.atsjournals.org/doi/full/10.1164/ajrccm.186.12.1307
The study especially addressed the impacts of low oxygen on subjects who already have poor health due to respiratory impairment (Adult Respiratory Distress Syndrome).
A total of 27 patients were included for evaluation of psychiatric morbidities. The study found that:
“Given that the remaining half cohort consists largely of patients with a poor oxygenation index, the majority of the 27 patients should have a less optimal oxygenation index. As it turned out, up to 26 of the 27 additional patients presented with long-lasting psychiatric symptoms. In a way, this phenomenon implies that patients with a poor oxygenation index would end up with long-term psychiatric morbidities, verifying the authors’ inference that hypoxemia predicts long-term neuropsychological impairment among ARDS.”
In effect, this confirmed that anyone who already has compromised respiratory health will be most likely to suffer brain injury from regular mask wearing.
What about the impacts on learning and memory? We looked at ‘Effect of chronic hypoxia and hypercapnia on learning and memory function in mice and the expression of NT and CGRP in brain’ from https://journals.sagepub.com/doi/pdf/10.1177/2058739218818956
The aim of this study was to investigate the effects of hypoxia and hypercapnia on learning and memory function of mice.
Airway blockage, such as impedance from prolonged mask wearing may lead to Chronic obstructive pulmonary disease (COPD), a frequently occurring disease of the respiratory system, with high morbidity and mortality rates. The authors affirming that the most important cause of COPD is hypoxia (low O2) and hypercapnia (elevated CO2). This was previously established by Liu CY, Parikh M, Bluemke DA et al. (2017) Pulmonary artery stiffness in chronic obstructive pulmonary disease (COPD) and emphysema: The Multi-Ethnic Study of Atherosclerosis (MESA) COPD Study. Journal of Cardiovascular Magnetic Resonance 13(1): 1–2.
Disturbingly, the laboratory test results from mice were damning. It showed:
“Our study found that chronic hypoxia and hypercapnia impaired memory function, increased the quantity of brain tissue lipid oxidation products MDA and DNA oxidation products 8-OHdG, decreased SOD activity, destroyed the stability of hippocampal structure, and reduced the number of Nissl bodies and increased apoptotic cells in mice. These indicated that hypoxia and hypercapnia enhanced oxidative stress response, destroyed tissue structure, and increased neuronal apoptosis, thus affecting its neurological function and learning and memory ability.”
https://journals.sagepub.com/doi/pdf/10.1177/2058739218818956
 Brain cell damage shown under the microscope (above)
Pointedly, the authors observed that:
“Chronic hypoxia is usually accompanied by hypercapnia, so we speculate that hypoxia and hypercapnia may cooperate in this process and aggravate the damage caused by hypoxia alone.”
Thus, both these ailments, when triggered from mask wearing, may be inexplicably linked doubling the adverse impacts on brain function.
Personally, I have not worn one of these face diapers at any stage during the fake pandemic. It should be self-evident to anyone with a modicum of critical reasoning skills that exhalation is one of our body’s vital excretion systems, just like urination and defecation. To impede any such function is a recipe for long term ill health, including irreparable cognitive impairment.
At Principia Scientific International we are determined to share with our readers all such valuable science so that we can all make informed choices and not merely unthinkingly do what as we are told by misguided policymakers.
Other references:
[1] https://vernoncoleman.org/articles/passing-observations-35
[2] https://vernoncoleman.org/articles/proof-masks-do-more-harm-good
About John O’Sullivan John is CEO and co-founder (with Dr Tim Ball) of Principia Scientific International (PSI). John is a seasoned science writer and legal analyst who assisted Dr Ball in defeating world leading climate expert, Michael ‘hockey stick’ Mann in the ‘science trial of the century‘. O’Sullivan is credited as the visionary who formed the original ‘Slayers’ group of scientists in 2010 who then collaborated in creating the world’s first full-volume debunk of the greenhouse gas theory plus their new follow-up book.
Deaths From Covid Vaxcine are government mandated genocide
NZ OUTDOORS PARTY | SEPTEMBER 12, 2021
A rush of student deaths and serious heart problems since the government’s decision to roll out the Pfizer vaccine to 12-17 year olds is government mandated genocide says the NZ Outdoors Party. The rollout to teenagers only started a few weeks ago, and already two deaths and two other post Vax admissions to Starship hospital have been reported. Another two serious post vaccine injuries in students are under investigation, including a boy who collapsed in Whangarei and another in the South Island. All are understood to have been healthy until sudden post vaccine heart issues, attributed to blood clots or myocarditis. These are well known adverse effects of this mRNA injection, which is known overseas as the #clotshot.
“The Prime Minister is floundering as the community networks are proving far more efficient at collecting and sharing information than the bureaucrats” says Sue Grey, co-leader of the NZ Outdoors Party. “This highlights one of the problems we have been raising for months. With a novel vaccine that is yet to complete clinical trials, there should be active follow-up of each recipient, to check on their health and to ensure all adverse effects are reported and assessed. The devastating effects on so many families could likely have been avoided if only the government had been more pro-active and transparent about the harm.”
Information obtained under the OIA shows that Medsafe, the government regulator, declined consent for the Pfizer Vaccine in January because it was not satisfied that the benefits exceeded the risks. Since then Medsafe has acknowledged the Pfizer Vax may cause myocarditis, pericarditis and thrombocytopenia ( blood clots).
In February the PfizerVax was given “provisional consent for the restricted treatment of a limited number of patients”, and subject to 58 conditions requiring more research and information.
After the High Court case raised questions about the legality of the Vaccine rollout, the government undertook an emergency law reform within 24 hours to remove the restricted use.
Recently the age limit was reduced to 12 year olds. it is understood the Prime Minister wants to inject everyone in New Zealand.
Despite its own advisors concerns, government advertising has repeatedly claimed the PfizerVax is “safe and effective” and “approved by Medsafe”. The Prime Minister herself claimed this recently in Parliamentary question time.
Many doctors and communities are furious about the ongoing devastation the PfizerVax is causing, and that people are not being told about the risks. A petition calling for an immediate suspension of the Vaccine rollout to teenagers launched today reached over 2000 signatures within hours. http://www.oursay.co.nz
The Outdoors Party says the ongoing rollout must stop immediately, and the government must start to listen both to the people they were elected to represent, and to the many doctors and international experts who have been issuing warnings for months.
“This programme must stop today, without any further excuses, and whoever is responsible must resign immediately” says Outdoors Party President Alan Simmons . End For more information call Alan Simmons alan@outdoorsparty.co.nz 0274 980304 or Sue Grey 22 6910586 suegreylawyer@gmail.com
Why Covid-19 Vaccine Mandates Are Now Pointless
By Nina Pierpont, MD, PhD* | September 9, 2021
Executive Summary:
Covid-19 Vaccine Mandates Are Now Pointless: Covid-19 vaccines do not keep people from catching the prevailing Delta variant and passing it to others
- 1) Excellent scientific research papers published or posted in August 2021 clearly demonstrate that current vaccines do not prevent transmission of SARS-CoV-2.
- 2) Vaccines aim to achieve two ends:
- To protect the vaccinated person against the illness.
- To keep people from carrying the infection and transmitting it to others.
- If enough people are vaccinated or otherwise become immune, it is hoped that the disease will stop circulating. We call this herd immunity.
- On the way to herd immunity, there is an assumption that people who are immunized can form safe clusters or groups within which no one is carrying or transmitting the virus.
- 3) Unfortunately, this last assumption (2.b.ii) is no longer true under the new variant of SARS-CoV- 2, Delta (B.1.617.2), which now accounts for essentially all cases worldwide.
- 4) Delta is more infectious than the Alpha strain (B.1.1.7) that prevailed in the UK from January to May 2021 (and in the US from March to June 2021), meaning that Delta is passed more readily person-to-person than the previous dominant strain. (see section 5, below).
b. From its origin in India, Delta has soared to nearly complete domination of COVID-19 viral strains everywhere in a matter of months, because it spreads so easily and infects both vaccinated and unvaccinated people.
- 5) New research in multiple settings shows that Delta produces very high viral loads (meaning, the density of virus on a nasopharyngeal swab as interpreted from PCR cycle threshold numbers).
- Viral loads are much higher in people infected with Delta than they were in people infected with Alpha.
- Viral loads with Delta are equally high whether the person has been vaccinated or not.
- Viral load is an indicator of infectiousness. [13,14] The more virus one has in the noseand mouth, the more likely it is to be in this individual’s respiratory droplets and secretions, and to spread to others.
- 6) Due to evolution of the virus itself, all the currently licensed vaccines (all based on the originalWuhan strain spike protein sequence) have lost their ability to accomplish vaccine purpose 2(b), above, “To keep people from carrying the infection and transmitting it to others.”
- 7) Vaccine mandates are thus stripped of their justification, since to vaccinate an individual nolonger stops or even slows his ability to acquire and transmit the virus to others.
- 8) Under Delta, natural immunity is much more protective than vaccination. All severities ofCOVID-19 illness produce healthy levels of natural immunity.
The Documentary Evidence:
Here are three studies whose findings and data support the above statements:
(A) The first is by the Massachusetts Department of Health and the CDC, published August 6, 2021 in the CDC’s Morbidity and Mortality Weekly Report. An outbreak of COVID-19 occurred in Provincetown, Massachusetts in July 2021 during two weeks of heavily attended indoor and outdoor public gatherings. The study focuses on the 469 cases among Massachusetts residents who were in attendance. [1] All successfully gene-sequenced isolates (120) were the Delta variant.
346 of the cases in Massachusetts residents (74%) occurred in fully vaccinated people who had received a 2-dose course of the BioNTech/Pfizer or Moderna vaccine, or a single dose of the Johnson & Johnson. Vaccine coverage at this time among all Massachusetts residents was 69%. This suggests that vaccinated people became infected just as frequently as unvaccinated people in this outbreak.
We do not know the vaccination percentage among actual festival attendees who were Massachusetts residents, but we can assume given the demographics of the festival that it was the state average (69%) or higher. We also do not know the total number of Massachusetts residents who attended. Both of these numbers would be needed to determine actual values for vaccine efficacy in this outbreak.
However, we cannot brush the high percentage of vaccinated people in the infected sample under the carpet quite as easily as the authors do, when they say, “As population-level vaccination coverage increases, vaccinated persons are likely to represent a larger proportion of COVID-19 cases” (p. 1061). This is true, but we would still, if vaccine is protective, find vaccinated cases to be underrepresented in an illness sample compared to the number vaccinated in the whole population of attendees. As best we can tell at this festival, vaccination was not protective against infection, because the proportion of vaccinated in the sample (74%) is in the same numeric range as the proportion vaccinated, 69% or above.
Among the 346 cases who were already vaccinated, 79% were symptomatic, reporting cough, headache, sore throat, muscle aches, and fever. Four of these vaccinated, infected individuals (1.2%) were hospitalized. No one died. The remainder of the vaccinated cases did not report symptoms.
Among the 123 cases who were unvaccinated or partially vaccinated, one was hospitalized (0.8%) and no one died. Percentage with symptoms was not reported.
Vaccinated and unvaccinated cases were found to have very similar viral loads (in a sample of 127 and 84 cases, respectively). This means the PCR tests showed that vaccinated and unvaccinated infected people were carrying similar amounts of virus in their upper respiratory tracts at diagnosis and were thus equally infectious.
(B) The next study, released August 10, 2021, examines the Delta viral load phenomenon in far more detail, and shows clearly that vaccinated people can become infected and pass the infection to other vaccinated people. The Hospital for Tropical Diseases in Ho Chi Minh City in southern Vietnam has about 900 staff members, including an Oxford University Clinical Research Unit. The entire hospital staff was vaccinated with the Oxford-AstraZeneca vaccine two-dose series in March and April 2021, and then enrolled in a post-vaccination study. Thus, a great deal of detailed information was available when the outbreak struck. [2]
The entire hospital staff was PCR negative for SARS-CoV-2 in mid-May 2021. The index case (first known case in a cluster) became mildly ill on June 11 and had a positive PCR with a high viral load. The whole staff was then re-tested. 52 additional cases were identified immediately. Ten more had high viral loads, a number being staff who shared an office with the index case. All the additional cases at first had no symptoms.
The hospital was then locked down. Over the next two weeks, 16 additional cases were identified in subsequent PCR surveys. 62 of the 69 PCR-positive cases participated in this study of the outbreak.
Forty-seven (76% of the 62 subjects) developed respiratory symptoms, three with pneumonia on chest x-ray and one requiring three days of nasal cannula oxygen (this is the least intensive form of oxygen therapy). Everyone recovered fully.
Peak viral loads in this fully vaccinated, infected group were, on average, 250 times higher than peak viral loads with older variants early in the pandemic (March-April 2020), when no one was vaccinated. This is a means of comparing the biology of the variants themselves: the Delta virus has gained the ability to replicate itself enormously in the upper respiratory tract, regardless of vaccination, thereby making itself more infectious.
In the current outbreak, viral loads (and thus infectiousness) peaked in the 2-3 days both before and after symptoms began.
All sequenced isolates were the Delta variant. The genetic sequences from hospital staff were more similar to each other than they were to contemporaneous isolates from the city at large or from more distant parts of the country. This means it is likely that the virus spread among the (fully vaccinated) hospital staff from a single infected (and vaccinated) staff member who brought it from the outside. Given the dynamics of symptoms and positivity among the staff, it is clear that asymptomatic or pre-symptomatic staff members, as well as symptomatic, were infecting others.
PCR tests continued to be positive up to 33 days after diagnosis (averaging 21 days). Case- control comparisons showed that staff members with lower titers of neutralizing antibodies after vaccination and at diagnosis were more likely to become infected. However, there was no correlation between vaccine-induced antibody levels at diagnosis and viral loads or the development of respiratory symptoms.
(C) The third study is an analysis of ongoing population-wide SARS-CoV-2 monitoring in the UK, whose primary purpose is following changes in vaccine efficacy. In the UK study, the PCR tests are done on members of randomly selected households across the UK, following a predetermined schedule that ignores symptoms, vaccination, and prior infection. The current analysis was released on August 24, 2021 and summarized in commentary in the British Medical Journal on August 19, 2021. [3, 4]
The study includes measures of viral load or “burden” under Alpha and Delta predominance. While Alpha was the dominant UK strain (January to mid-May 2021), vaccination or prior COVID- 19 disease strongly reduced viral load compared to unvaccinated people who had never had COVID-19.
The sample size was large and random, obtained as described above. 12,287 new PCR-positives were found in the Alpha-dominant period, of which 88% were unvaccinated and had no evidence of prior infection. Only 0.5% of new positive tests were from fully vaccinated people and 0.6% from people with prior COVID-19 infection. Since it was a large, random sample and vaccination percentages increased dramatically in the UK across this time period, we can safely say that vaccination and prior infection were very protective against becoming infected with the Alpha variant. Virtually all the new infections occurred in unvaccinated people.
After mid-June 2021, when greater than 92% of PCR positives in the UK were Delta, the differences in viral load between vaccinated, unvaccinated, and people with past COVID-19 disease nearly vanished. Viral loads in all three groups were much higher than with Alpha, indicating increased infectiousness. More vaccinated people were now showing symptoms when they became positive, also correlated with viral load.
During the Delta-dominant period, the sample was 1939 new positive PCR tests. Of these, 17% (326) were from unvaccinated people without prior COVID-19 disease, 1% (20) were unvaccinated with evidence of prior disease, and 82% (1593) were fully vaccinated. This is approximately the percentage of the UK population who were vaccinated by August 18, 2021— when 75-83% of UK residents were fully vaccinated and 84-89% had received at least one dose. [5]
Like the Massachusetts study reviewed above, this suggests that the new Delta variant infects vaccinated and unvaccinated people with equal probability. To go from 0.5% of randomly sampled new infections in vaccinated people (under Alpha) to 82% (under Delta) in several months, as the population is becoming more and more vaccinated—these are extraordinary numbers.
If vaccination is still effective in preventing infection, we would expect the proportion of infections in a random population sample to be less than the proportion of the population vaccinated. If 82% of randomly obtained positive tests occur in vaccinated people, and about 82% of people are vaccinated, then vaccination is not reducing the likelihood of infection at all. Efficacy at preventing infection has become zero.
The UK study addresses vaccine efficacy in much more complex ways than the straightforward numbers I present here. The authors conclude that both of the earlier UK-approved vaccines (BioNTech/Pfizer and Oxford-AstraZeneca) have lost some efficacy against Delta compared to Alpha. But both vaccines, they maintain, remain substantially effective at keeping people from becoming infected with the Delta strain, in the range of 67 to 80%. If this is the case, why was 82% of their random sample of new positive PCR tests from vaccinated people?
If a vaccine reduces the risk of becoming infected by two-thirds (67%), we would expect the proportion of vaccinated in the positive sample to be less than the proportion of vaccinated in the population. Say we start with 1000 people in the country, of whom we will randomly sample 100. The country is 80% vaccinated. This means that in our sample of 100 we have 80 vaccinated and 20 unvaccinated people. Let’s say that the virus has infected 10% of the people across the sampling period, or 10 total cases. If 8 of the infected are among the vaccinated, and 2 in the unvaccinated (80% and 20% of the positives, matching the ratio of vaccinated and unvaccinated in the population), the vaccine has made no difference in whether one can get infected (0% efficacy). If the vaccine is 67% effective, the cases in the vaccinated group would be reduced by 2/3 to 2.67 cases, and the total cases would be only 4.67 cases (2.67 vaccinated and 2 unvaccinated). This means that only 2.67/4.67 or 57% of the cases would be in the vaccinated group, and 43% in the unvaccinated. (We can go back to 10% overall being positive just using ratios, yielding 5.7 cases among the vaccinated and 4.3 among the unvaccinated.)
This is why the proportion vaccinated in the infected sample, very close to the proportions vaccinated in the total population, are incompatible with the efficacy numbers generated by the authors. It appears to me—as in the Massachusetts study—that the vaccine is not decreasing susceptibility to infection at all, and is in reality somewhere between slightly (insignificantly) decreasing susceptibility and slightly increasing susceptibility to the Delta variant.
The UK study is clear that viral load (and thus infectiousness to others) is much greater with Delta than with Alpha, and that, with Delta, viral load and infectiousness are equal in vaccinated and unvaccinated infected people.
Discussion #1:
These three different studies in three countries with three different population sampling methods produced the same result: with the current, dominant Delta strain, vaccinated people become infected and carry just as much infectious virus in their upper respiratory tracts when infected as unvaccinated people. The reproducibility of this finding makes it a very strong finding.
The study in Vietnam shows clearly that infected, vaccinated people transmit the infection to others.
Under the current dominance of the Delta variant, being vaccinated or not has no influence on a chief determinant of infectiousness: the size of the viral load carried in the nose and mouth of an infected person. In addition, both vaccinated and unvaccinated become infected in significant numbers, approximating the ratios of vaccinated and unvaccinated in the population.
The rationale for mandates—that each individual has a responsibility to be vaccinated to limit spread of the virus to others—is hereby seriously or even fatally undermined. The decision to be vaccinated, under Delta predominance, has become entirely personal, affecting only the future health and well-being of the individual receiving the vaccine.
Blaming the unvaccinated for the rapid spread of the Delta variant has no merit whatsoever, since both vaccinated and unvaccinated infected people are equally infectious to others, and vaccinated and unvaccinated people are represented in illness samples in proportion to their representation in the general population, showing they are equally likely to become infected.
These findings also equalize vaccinated and unvaccinated in terms of quarantine, vaccine- based exclusion, or the wearing of masks.
The Delta variant has entirely changed our expectations of the effects of vaccination on containing the SARS-CoV-2 virus.
What about natural immunity from previous COVID-19 infection?
What about natural immunity from previous COVID-19 infection, with regard to the change in virus strain? An Israeli study posted on August 25, 2021 powerfully shows that “natural immunity [from previous COVID-19 infection] confers longer-lasting and stronger protection against infection, symptomatic disease and hospitalization caused by the Delta variant of SARS- CoV-2 compared to the BNT162b2 [BioNTech/Pfizer] two-dose vaccine-induced immunity.” If a person is both naturally immune and received one vaccine dose, immunity to Delta infection is even stronger. [6]
To demonstrate this, the authors studied the records of a large Israeli Health Maintenance Organization covering 2.5 million people (26% of the population). They compared the numbers of positive PCR tests from June 1 to August 14, 2021, when the Delta variant was dominant, in people who were either immunized in January-February 2021 or had COVID-19 infection in January-February 2021.
Those who were vaccinated but never had COVID-19 disease were 13 times more likely to develop a new SARS-CoV-2 infection than those made naturally immune by COVID-19 disease. The increased risk was also significant for having symptoms or not.
When the prior COVID-19 disease was allowed to happen earlier in the course of the pandemic, from March 2020 through February 2021, vaccinees who had never had COVID-19 disease were still (a) 6 times more likely to have a positive PCR in June-August 2021 than a naturally immune person, (b) 7 times more likely to have symptomatic disease, and (c) at greater risk for COVID- 19-related hospitalization.
By comparison, under Alpha strain dominance during the first half of 2021, over 50,000 staff members of the Cleveland Clinic in Ohio demonstrated that vaccine-induced immunity (from any of the three US-authorized vaccines) and natural immunity were equally protective against COVID-19 disease. [7]
The Israeli study shows at a later time period how the Delta variant has escaped the control of at least one of these vaccines, while natural immunity to earlier forms of SARS-CoV-2 still confers protection.
A Danish study of 203 recovered COVID patients shows that COVID-19 infection/disease provokes robust immune responses in the vast majority of people regardless of disease severity, including mild cases and even true asymptomatic cases (excluding those with false positive tests). [8]
Discussion #2:
It is difficult to tell anything about the virulence or pathogenicity of the Delta variant itself—how sick it makes people—since the available studies are all done in highly vaccinated populations. Vaccination has protected against severe disease and death with all the other variants, and may well do the same with the Delta variant. This remains the most compelling reason individuals may decide to be vaccinated.
What drives people—especially PhD’s, together with certain minorities [9]—to choose not to be vaccinated? There is substantial recorded and written evidence from first-hand observers and vaccine recipients themselves, and in the immunization “adverse effects” registries of both the US and Europe, that we are tolerating with COVID-19 vaccines a level of severe adverse effects, including death, that would have been unthinkable for any earlier vaccine.
So far, convincing evidence that these effects are “not related to vaccine” has not emerged. Convincing evidence would be research-lab-level autopsy studies of people deceased soon after vaccination (or ill soon after vaccination and eventually deceased), including immunofluorescence or other specific staining for the unique proteins, nucleic acids, and lipids of vaccine or SARS-CoV-2 itself in different tissues. (Some excellent examples of this approach are autopsy studies illuminating the pathophysiology of COVID-19 disease by C Magro and others at Weill Cornell Medical Center [e.g. 10].) Biopsy studies of key tissues in living affected people, such as those with persistent neurologic deficits after vaccination for COVID-19, would also provide powerful evidence. It is highly irregular and indeed unacceptable that such autopsy and biopsy studies have not been done.
Some prominent scientists and a significant number of physicians take these allegations of vaccine-caused injury very seriously. Doctors for Covid Ethics, a British/European/worldwide group of physicians, link the known pathophysiology of clots in COVID-19 disease [10] with a possible pathophysiologic mechanism explaining the numerous cases of thrombosis after vaccination, such as those in published literature due to the Oxford-AstraZeneca vaccine. [11,12] This mechanism would not be unique to one vaccine type or brand, nor are the reports of postvaccination thrombosis unique to one type or brand of vaccine.
In the four major papers reviewed above (Massachusetts, Vietnam, UK, and Israel), the biologic facts of the new Delta variant and its relationship to vaccination are clearly and reproducibly established. This is the value of good science.
Conclusion:
Given all the above evidence, mandating others to take a vaccine is a potentially harmful, damaging act.
Since the principal reason for COVID-19 vaccine mandates—protecting others from infection—has evaporated with the ascendance of the Delta variant, those who mandate COVID-19 vaccines may wish to seek legal counsel regarding their culpability and liability (including personal) for potential long-lasting harm to those whom they pressure into vaccination with threat of exclusion from employment or education or other public activity. Remind your attorney that if an unborn or nursing baby is damaged, liability persists until the child is age 23—plenty of time for discovery of the ways whereby vaccine producers and government regulators may have suppressed important information about harmful effects.
References:
- Brown CM, Vostok J, Johnson H, Burns M, Gharpure R, Sami S, Sabo RT, Hall N, Foreman A, Schubert PL, Gallagher GR, Fink T, Madoff LC, MD, Gabriel SB, MacInnis B, Park DJ, Siddle KJ, Harik V, Arvidson, D, Brock-Fisher T, Dunn M, Kearns, Laney AS. 2021. Outbreak of SARS- CoV-2 infections, including COVID-19 vaccine breakthrough infections, associated with large public gatherings –– Barnstable County, Massachusetts, July 2021. MMWR Morb Mortal Wkly Rep 70:1059-1062: https://www.cdc.gov/mmwr/volumes/70/wr/pdfs/mm7031e2-H.pdf; published August 6, 2021.
- Chau NVV, Ngoc NM, Nguyet LA, Quang VM, Ny NTH, Khoa DB, Phong NT, Toan LM, Hong NTT, Tuyen NTK, Phat VV, Nhu LNT, Truc NHT, That BTT, Thao HP, Thao TNP, Vuong VT, Tam TTT, Tai NT, Bao HT, Nhung HTK, Minh NTN, Tien NTM, Huy NC, Choisy M, Man DNH, Ty DTB, Anh NT, Uyen LTT, Tu TNH, Yen LM, Dung NT, Hung LM, Truong NT, Thanh TT, Thwaites G, Tan LV, OUCRU COVID-19 Research Group. 2021. Transmission of SARS-CoV-2 Delta variant among vaccinated healthcare workers, Vietnam. Preprints with The Lancet, available at http://dx.doi.org/10.2139/ssrn.3897733; posted August 10, 2021.
- Pouwels KB, Pritchard E, Matthews PC, Stoesser N, Eyre DW, Vihta KD, House T, Hay J, Bell JI, Newton JN, Farrar J, Crook D, Cook D, Rourke E, Studley R, Peto T, Diamond I, Walker AS, and the COVID-19 Infection Survey Team. 2021. Impact of Delta on viral burden and vaccine effectiveness against new SARS-CoV-2 infections in the UK. medRxiv preprint: https://doi.org/10.1101/2021.08.18.21262237; posted August 24, 2021.
- Griffin S. 2021. Covid-19: Fully vaccinated people can carry as much delta virus as unvaccinated people, data indicate. BMJ 374:2074: http://dx.doi.org/10.1136/bmj.n2074; published 19 August 2021.
6. Gazit S, Shlezinger R, Perez G, Roni Lotan R, Peretz A, Ben-Tov A, Cohen D, Muhsen K, Chodick G, Patalon T. 2021. Comparing SARS-CoV-2 natural immunity to vaccine-induced immunity: reinfections versus breakthrough infections. medRxiv preprint: https://doi.org/10.1101/2021.08.24.21262415; posted August 25, 2021.
5. BBC News: “Covid vaccine: How many people in the UK have been vaccinated so far?” Downloaded on August 23, 2021. Updated article and graph available at https://www.bbc.com/news/health-55274833
- Shrestha NK, Burke PC, Nowacki AS, Terpeluk P, Gordon SM. 2021. Necessity of COVID-19 vaccination in previously infected individuals. 2021. medRxiv preprint: https://doi.org/10.1101/2021.06.01.21258176; posted June 5, 2021.
- Nielsen SSF, Vibholm LK, Monrad I, Olesen R, Frattari GS, Pahus MH, Højen JF, Gunst JD, Erikstrup C, Holleufer A, Hartmann R, Østergaard L, Søgaard OS, Schleimann MH, Tolstrup M. 2021. SARS-CoV-2 elicits robust adaptive immune responses regardless of disease severity. EBioMedicine 68:103410, https://doi.org/10.1016/j.ebiom.2021.103410; published June 4, 2021.
- King WC, Rubinstein M, Reinhart A, Mejia RJ. 2021. Time trends and factors related to COVID-19 vaccine hesitancy from January-May 2021 among US adults: Findings from a large- scale national survey. medRxiv preprint: https://doi.org/10.1101/2021.07.20.21260795; posted July 23, 2021.
- Magro C, Mulvey JJ, Berlin D, Nuovo G, Salvatore S, Harp J, Baxter-Stoltzfus A, Laurence J. 2020. Complement-associated microvascular injury and thrombosis in the pathogenesis of severe COVID-19 infection: A report of five cases. Translational Research 220:1–13: https://doi.org/10.1016/j.trsl.2020.04.007; published online April 15, 2020.
- Bhakdi, S. et al. 2021. Letter to Physicians: Four new scientific discoveries regarding COVID- 19 immunity and vaccines—implications for safety and efficacy.. Doctors for Covid Ethics website, https://doctors4covidethics.org/letter-to-physicians-four-new-scientific- discoveries-crucial-to-the-safety-and-efficacy-of-covid-19-vaccines/; posted July 9, 2021.
- Kantarcioglu B, Iqbal O, Walenga JM, Lewis B, Lewis J, Carter CA, Singh M, Lievano F, Tafur A, Ramacciotti E, Gerotziafas GT, Jeske W, Fareed J. 2021. An update on the pathogenesis of COVID-19 and the reportedly rare thrombotic events following vaccination. Clin Appl Thrombosis/Hemostasis 27:1-14. https://journals.sagepub.com/doi/10.1177/10760296211021498; published June 1, 2021.
- Jones TC, Biele G, Mühlemann B, Veith T, Schneider J, Beheim-Schwarzbach J, Bleicker T, Tesch J, Schmidt ML, Sander LE, Kurth F, Menzel P, Schwarzer R, Zuchowski M, Hofmann J, Krumbholz A, Stein A, Edelmann A, Corman VM, Drosten C. 2021. Estimating infectiousness throughout SARS-CoV-2 infection course. Science 373, 180. https://doi.org/10.1126/science.abi5273; published July 9, 2021.
- van Kampen JJA, van de Vijver DAMC, Fraaij PLA, Haagmans BL, Lamers MM, Okba N, van den Akker JPC, Endeman H, Gommers DAMPJ, Cornelissen JJ, Hoek RAS, van der Eerden MM, Hesselink DA, Metselaar HJ, Verbon A, de Steenwinkel JEM, Aron GI, van Gorp ECM, van Boheemen S, Voermans JC, Boucher CAB, Molenkamp R, Koopmans MPG, Geurtsvankessel C, van der Eijk AA. 2021. Duration and key determinants of infectious virus shedding in hospitalized patients with coronavirus disease-2019 (COVID-19). Nature Communications 12, 267. https://doi.org/10.1038/s41467-020-20568-4; published January 11, 2021.
* Nina Pierpont is a graduate of Yale University (BA in biology), with a MA and PhD from Princeton University in population biology/evolutionary biology/ecology, and the MD degree from the Johns Hopkins University School of Medicine. She has been a Clinical Assistant Professor of Pediatrics at Columbia University’s College of Physicians & Surgeons. She is currently in private practice in upstate New York, specializing in behavioral medicine.
ninapierpont@protonmail.com
Sydney doctor who criticized medical censorship online is suspended from practicing medicine
By Cindy Harper | Reclaim The Net | September 11, 2021
On social media, a Sydney doctor questioned whether vaccines and lockdowns would be effective in ending the pandemic while also scrutinizing how medical authorities were handling treatment. As a result of his postings, New South Wales medical authorities have taken action against Dr. Paul Oosterhuis by suspending him.
Oosterhuis’ social media activities have garnered at least two anonymous complaints to the medical council, the group confirmed on September 2nd.
“Over the last 18 months, I have been increasingly concerned about the misinformation and censorship creeping into science and medicine,” the doctor had stated.
Oosterhuis recommended that medical authorities advise COVID-19 patients to take vitamin D and zinc and to treat them with ivermectin and hydroxychloroquine.
He called the lockdowns “totalitarian” and causing “massive damage to society-wide.”
In a post, he wrote. “The risk of antibody-dependent enhancement of disease… driven by immune escape from the selective evolutionary pressure of vaccinating with a non-sterilizing agent is a real and present danger and needs to be discussed. The danger to millions is distressing me, and discussing that danger is, I believe, unarguably in the public interest.”
According to the Medical Council of New South Wales, Oosterhuis’s social media activity was flagged. He was asked to attend an “immediate action panel” on September 3rd and the anesthetist was questioned by the MCNSW.
“The Council deals with individual doctors whose conduct, performance or health may represent a risk to the public and works with them, where possible, to reduce that risk by for example, placing conditions on their medical registration. Section 150 or immediate action panels are held by the Council when a complaint or notification prompts serious concerns about risk to public safety or the need to otherwise act in the public interest. Panel members include community representatives as well as medical practitioners,” the MCNSW statement read.
The MCNSW provided Reclaim The Net with this full statement here
Ultimately, the MCNSW chose to suspend Dr Oosterhuis’ later that day.
Medical practitioners can be suspended by the medical council under New South Wales’ Health Practitioner Regulation National Law (NSW). The New South Wales Medical Council collaborates with the state Ministry of Health to investigate and resolve complaints about specific doctors and other medical specialists.
According to the council, this law does not give it the power to de-register Oosterhuis or revoke his license and they have no authority to punish him. However, despite his almost 30 years of experience in medicine, his suspension has already barred him from practicing in the medical profession.
Oosterhuis has responded by stating that he will not adjust his behavior to be more compliant. He stated that he intends to challenge the suspension, saying:
“I am very disappointed by the Medical Council’s decision to suspend my registration.
“The material I submitted in support of my evidence-based concerns was not considered. I intend to appeal the decision.
“The council drew upon s150 powers to demand an urgent hearing into some posts I have shared on Facebook on the importance of early treatment, particularly the low hanging fruit of vit D, Zinc, Quercetin, vit C and the repurposed drugs Ivermectin.
“I’m pro choice, pro informed consent… it’s always been a key ethical principle… you need to be able to discuss all the risks, benefits, and alternatives of any medical intervention.”
He later added, “Censorship kills. My responsibility to the Hippocratic oath, and basic ethics compels me to share data that I believe is definitely in the public interest.”
Despite an initial public statement, the MCNSW failed to make any further statements on this issue.
Children are Next in Line for Mandated Coronavirus Vaccine Shots
By Adam Dick | Ron Paul Institute | September 11, 2021
Much attention is focused on President Joe Biden in a Thursday speech announcing that the coronavirus testing alternative United States government employees had been able to use to avoid the mandate to take experimental coronavirus vaccines is being eliminated and that regulations are in the works to require all employees at companies with 100 or more employees to take the “vaccines” or be tested weekly. Less noticed is news that experimental coronavirus vaccines may soon be rolled out for young children. Pfizer-BioNTech is seeking in the next few weeks approval for giving its experimental coronavirus vaccine shots to children ages five through 11, while Moderna is close behind, proceeding with testing of its shots on children 11 and younger. Then come shots for toddlers and babies.
Shots mandates for workers first, shots mandates for children next: That seems to be the situation in America, though it should be noted that some children —especially older children — are workers too.
Of course, as happened Thursday with the testing alternative to shots disappearing for government workers, expect that alternative to go away for people working at private businesses as well. By the time a shots mandate for children comes along, a testing alternative might not be available from the start.
Biden provided in his speech a preview of an argument in favor of mandatory shots for children. First, he asserted that the August 23 expedited Food and Drug Administration (FDA) approval of a Pfizer-BioNTech experimental coronavirus vaccine for people 16 and over means “the time for waiting is over” for people 16 and older who have not taken the shots. Second, Biden suggested that as soon as vaccines are approved for use in an age group of children his conclusion is that the children in that age group should then be given shots:
It comes down to two separate categories: children ages 12 and older who are eligible for a vaccine now, and children ages 11 and under who are not are yet eligible.
The safest thing for your child 12 and older is to get them vaccinated. They get vaccinated for a lot of things. That’s it. Get them vaccinated.
A move to require children to be given the experimental coronavirus vaccine shots should come as no surprise. Children across America have long been mandated to receive many vaccines on a prescribed timeline in accord with the Centers for Disease Control and Prevention (CDC) vaccine schedule or similar state vaccine schedules in order to attend school. And many of the mandates are difficult to avoid. In California, for example, the vaccine mandate applies even to children in private schools and only has a very limited exemption.
The obvious way to introduce the requirement that young children take the experimental coronavirus vaccine shots is to make the shots a prerequisite for attending school. There is plenty of precedent for that from all the other vaccine shots required in the CDC and state vaccine schedules.
Next up, the shots can be required for even homeschooled children, just like the shots requirement for people employed in businesses with a 100 or more employees can be extended to people employed in businesses with under 100 employees, the self-employed, the retired, and the unemployed. Indeed, on Thursday Biden announced he will mandate US government contractors and 17 million healthcare workers take the shots, no matter how many employees their employers have.
There is no constitutional basis for the experimental coronavirus vaccine mandates Biden announced on Thursday. If he can get away with those mandates, what’s to stop him from expanding on those mandates so he can eliminate all the “loopholes,” including the one protecting children from forced shots.
Copyright © 2021 by RonPaul Institute
You’re Next! Roll up your sleeve. Repeat. Repeat. Repeat…
By Meryl Nass, MD | September 10, 2021
What can I say? A demented President and widely disliked Veep are unlikely to be making decisions in Washington. We do not know who or what is making the decisions. The media and public personas all know this to be true, but no one speaks a word of it.
We have vaccines that barely work the way vaccines are supposed to. The media and anyone who chooses to look at the subject know this to be true, but never say so directly.
We have public health officials who contradict themselves and make fools of themselves on a regular basis, but no one in the media points this out.
When the government insisted on secret vaccine contracts, signed deals for purchases of 8 doses per person, chose the military to manage the program, and chose Moncef Slaoui to run the program, surely you had an inkling that something bad was happening?
What does Wikipedia say about Slaoui?
In April 2013, he co-wrote a paper with several other GSK heads that introduced the term “electroceutical” to broadly encompass medical devices that use electrical, mechanical, or light stimulation to affect electrical signaling in relevant tissue types.[18] Over the next several years, he attempted to sell a public audience on GSK’s development of bioelectronic medicine, with appearances on YouTube[19] and at futurist conferences… In 2016 he was named to the inaugural board of directors of Galvani Bioelectronics, the joint venture between GSK and Alphabet Corporation subsidiary Verily Life Sciences.
When cities started encouraging 12-17 year olds to get vaccinated in spite of parental opposition, and provided instructions on how to do so, even in some cases paying cab fare, no one in the media raised an eyebrow.
The US government, and others, are desperate to get us vaccinated, and desperate to get additional doses into us. We don’t know why. We don’t know what exactly is in these vials. We don’t know what their plans are.
But we are blind, deaf, and extremely dumb if we think it is for our health.
At which point do you say enough is enough? The bulldozers are already here.
In setback for Biden’s mandate policy, Florida appeals court allows governor to ban obligatory masks in schools
RT | September 10, 2021
A Florida appeals court has overruled a district judge who sought to block Governor Ron DeSantis from banning mask mandates in public schools, even as President Joe Biden vowed federal support for administrators who do so.
On Friday, the First District Court of Appeals in Tallahassee overruled Leon County Judge John Cooper’s decision to block the enforcement of the mandate ban, meaning schools that try to force children to wear masks can be punished by the governor.
“Upon our review of the trial’s court’s final judgment and the operative pleadings, we have serious doubts about standing, jurisdiction, and other threshold matters,” said the appeals court order, casting doubt on the case the mandate advocates made through a group of parents.
DeSantis is a Republican governor opposed to lockdowns and mask mandates, who has opted for encouraging vaccinations and antibody treatments for Covid-19 instead. He has argued that masking up ought to be voluntary, and that school mask mandates violate the rights of parents and children. Under the rules enacted by DeSantis last month, school administrators who impose mask mandates can be docked pay. Judge Cooper tried to block their enforcement.
Of the 67 school districts in Florida, 13 have adopted strict mask mandates in violation of the state order. So far, DeSantis has withheld the monthly salary of school board members in two counties, Broward and Alachua, while investigating others for non-compliance.
On Thursday, Biden said the federal government would reimburse anyone who defies the mask mandate ban, as part of his push to force some 80 million Americans to get vaccinated or submit to weekly tests under the threat of losing their jobs or paying massive fines. Biden blamed the “unvaccinated” for the surge in Covid-19 cases and said the vaccinated must be protected from them.
“This is not about freedom, or personal choice,” Biden said in a televised speech, later adding, “We’ve been patient, but our patience is wearing thin, and your refusal has cost all of us.”
Biden also said state governors should require vaccinations of all school teachers and staff, imposed a vaccination requirement on 300,000 teachers in the federal Head Start program, and vowed to go after any governors “undermining” his measures.
“If these governors won’t help, I will use my powers as president and get them out of the way,” he said.
Last month, DeSantis vowed to “stand in the way” of Covid-19 mandates, lockdowns, and other restrictions, saying the US can “either have a free society or we can have a biomedical security state.”
Adam Schiff demands more data on Amazon’s policing of “misinformation” in books
By Dan Frieth | Reclaim The Net | September 10, 2021
Rep. Adam Schiff, a Democrat, has written to Amazon and Facebook, requesting more information on their efforts to combat the spread of “misinformation” on their platforms. The Democratic party has intensified its criticism of online platforms for their failure to address what they say is misinformation, which they blame for the stalling of the vaccination program.
“Despite some concrete and positive steps previously taken, these companies owe both the public and the Congress additional answers about the exponential and dangerous proliferation of misinformation,” said Schiff, the chairman of the House Intelligence Committee, in a statement.
In recent weeks more Democrats, including White House officials, have spoken out against online platforms for their failure to address health misinformation, blamed for the increased vaccine hesitancy in the country. Biden singled out Facebook, saying the company was killing people for allowing the spread of vaccine-skeptic content.
In a statement to Reuters, Facebook said that, since the beginning of the pandemic, it had “removed over 20 million pieces of COVID misinformation, labeled more than 190 million pieces of COVID content rated by our fact-checking partners, and connected over 2 billion people with reliable information through tools like our COVID information center.”
It added it had “removed over 3,000 accounts, pages, and groups for repeatedly violating our COVID-19 and vaccine misinformation policies and will continue to enforce our policies and offer tools and reminders for people who use our platform to get vaccinated.”
A spokesperson for Amazon said that it has been “constantly evaluating the books we list to ensure they comply with our content guidelines, and as an additional service to customers, at the top of relevant search results pages we link to the CDC advice on COVID and protection measures.”
The Bots That Are Not
By Mike Hearn | The Daily Sceptic | September 10, 2021
Since 2016 automated Twitter accounts have been blamed for Donald Trump and Brexit (many times), Brazilian politics, Venezuelan politics, skepticism of climatology, cannabis misinformation, anti-immigration sentiment, vaping, and, inevitably, distrust of COVID vaccines. News articles about bots are backed by a surprisingly large amount of academic research. Google Scholar alone indexes nearly 10,000 papers on the topic. Some of these papers received widespread coverage:
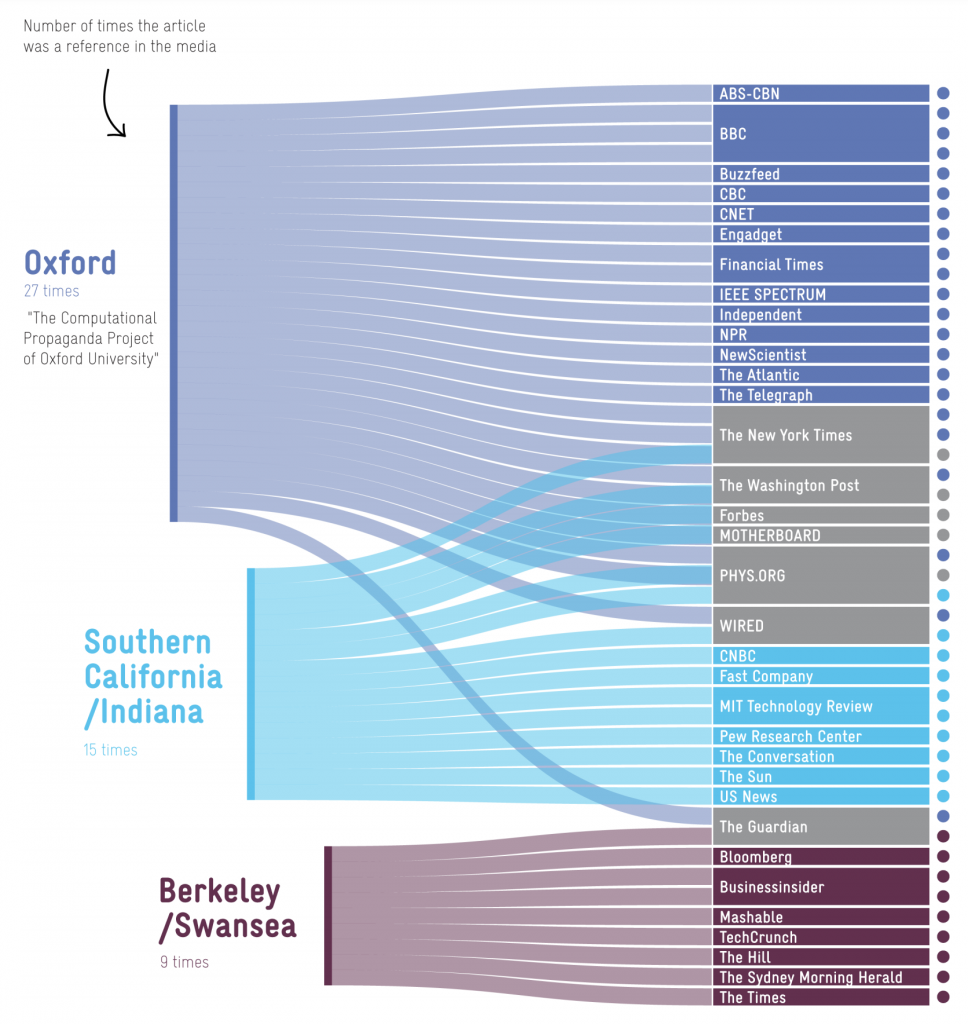
Unfortunately there’s a problem with this narrative: it is itself misinformation. Bizarrely and ironically, universities are propagating an untrue conspiracy theory while simultaneously claiming to be defending the world from the very same.
The visualization above comes from “The Rise and Fall of Social Bot Research” (also available in talk form). It was quietly uploaded to a preprint server in March by Gallwitz & Kreil, two German investigators, and has received little attention since. Yet their work completely destroys the academic field of bot research to such an extreme extent that it’s possible there are no true scientific papers on the topic at all.
The authors identify a simple problem that crops up in every study they looked at. Unable to directly detect bots because they don’t work for Twitter, academics come up with proxy signals that are asserted to imply automation but which actually don’t. For example, Oxford’s Computational Propaganda Project – responsible for the first paper in the diagram above – defined a bot as any account that tweets more than 50 times per day. That’s a lot of tweeting but easily achieved by heavy users, like the famous journalist Glenn Greenwald, the slightly less famous member of German Parliament Johannes Kahrs – who has in the past managed to rack up an astounding 300 tweets per day – or indeed Donald Trump, who exceeded this threshold on six different days during 2020. Bot papers typically don’t provide examples of the bot accounts they claimed to identify, but in this case four were presented. Of those, three were trivially identifiable as (legitimate) bots because they actually said they were bots in their account metadata, and one was an apparently human account claimed to be a bot with no evidence. On this basis the authors generated 27 news stories and 323 citations, although the paper was never peer reviewed.
In 2017 I investigated the Berkley/Swansea paper and found that it was doing something very similar, but using an even laxer definition. Any account that regularly tweeted more than five times after midnight from a smartphone was classed as a bot. Obviously, this is not a valid way to detect automation. Despite being built on nonsensical premises, invalid modelling, mis-characterisations of its own data and once again not being peer reviewed, the authors were able to successfully influence the British Parliament. Damian Collins, the Tory MP who chaired the DCMS Select Committee at the time, said: “This is the most significant evidence yet of interference by Russian-backed social media accounts around the Brexit referendum. The content published and promoted by these accounts is clearly designed to increase tensions throughout the country and undermine our democratic process. I fear that this may well be just the tip of the iceberg.”
But since 2019 the vast majority of papers about social bots rely on a machine learning model called ‘Botometer’. The Botometer is available online and claims to measure the probability of any Twitter account being a bot. Created by a pair of academics in the USA, it has been cited nearly 700 times and generates a continual stream of news stories. The model is frequently described as a “state of the art bot detection method” with “95% accuracy”.
That claim is false. The Botometer’s false positive rate is so high it is practically a random number generator. A simple demonstration of the problem was the distribution of scores given to verified members of U.S. Congress:
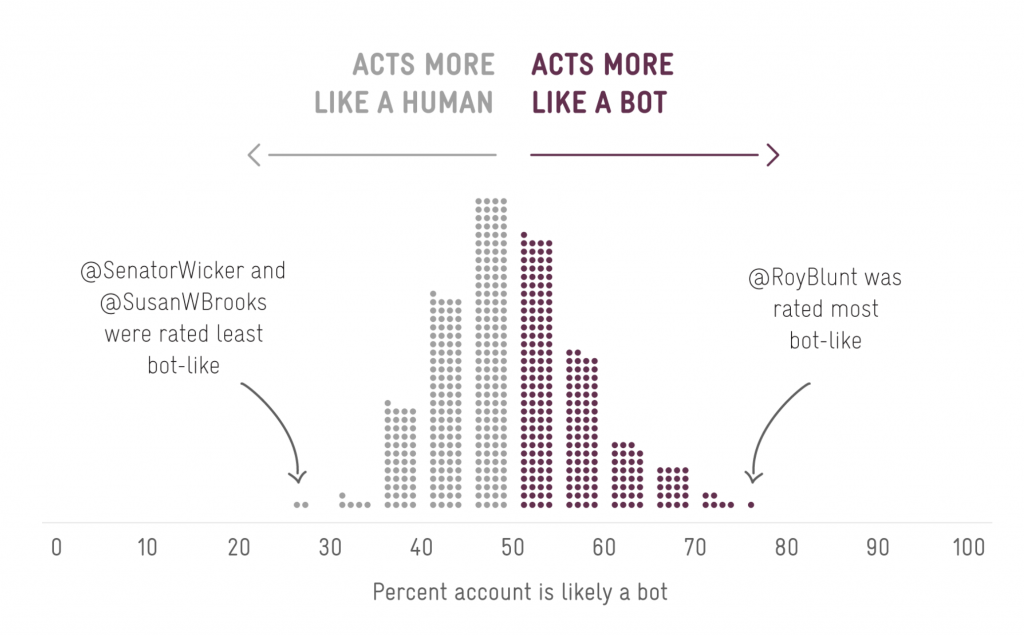
In experiments run by Gallwitz & Kreil, nearly half of Congress were classified as more likely to be bots than human, along with 12% of Nobel Prize laureates, 17% of Reuters journalists, 21.9% of the staff members of UN Women and – inevitably – U.S. President Joe Biden.
But detecting the false positive problem did not require compiling lists of verified humans. One study that claimed to identify around 190,000 bots included the following accounts in its set:
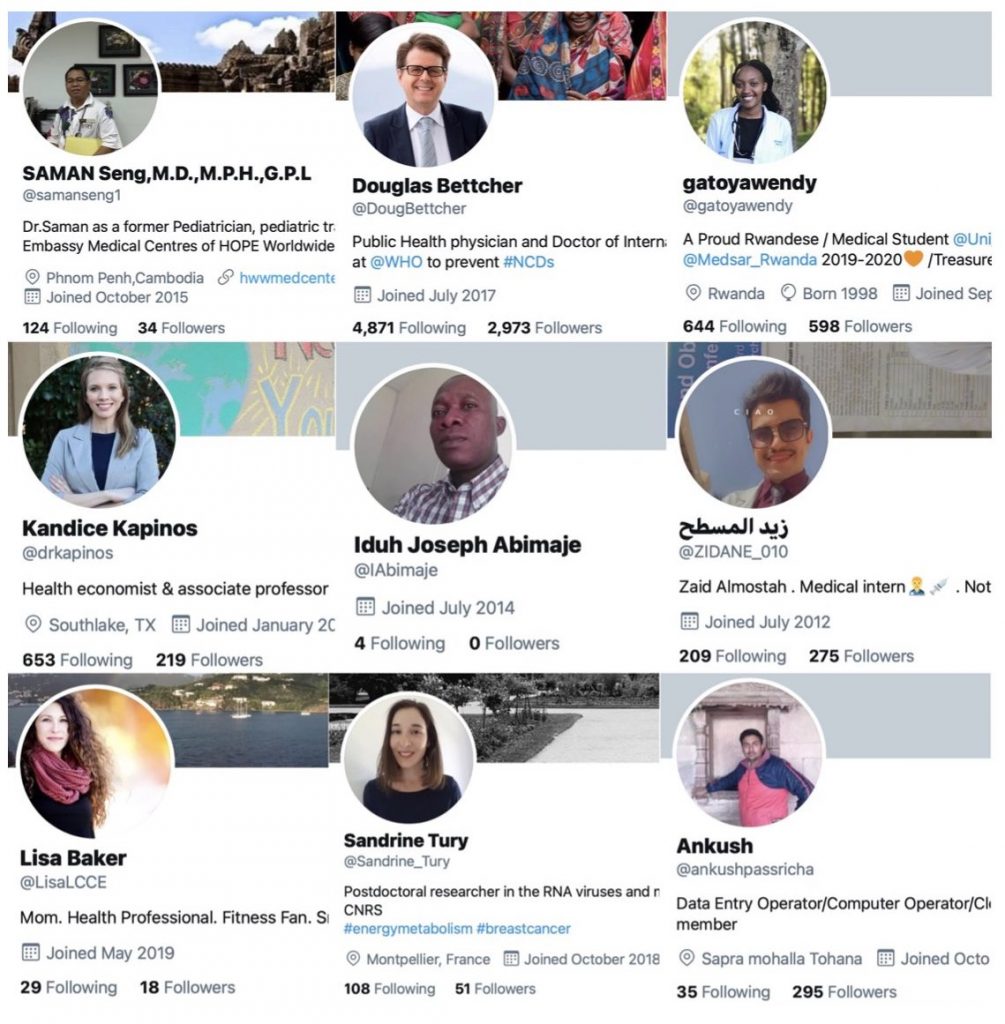
Taken from a dataset shared by Dunn et al.
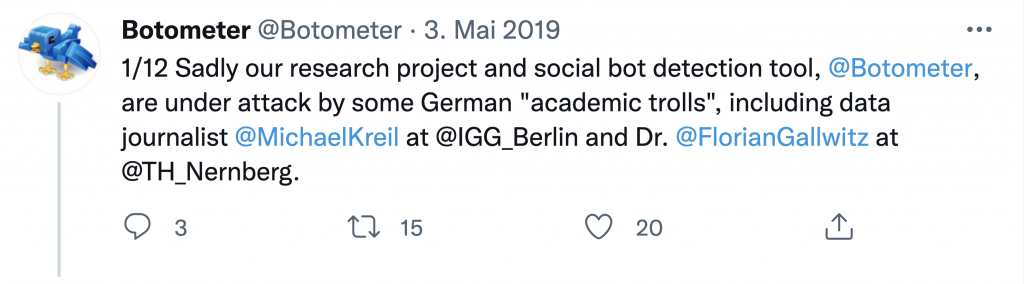
The developers of the Botometer know it doesn’t work. After the embarrassing U.S. Congress data was published, an appropriate response would have been retraction of their paper. But that would have implied that all the papers that relied upon it should also be retracted. Instead they hard-coded the model to know that Congress are human and then went on the attack, describing their critics as “academic trolls”:
Root cause analysis
This story is a specific instance of a general problem that crops up frequently in bad science. Academics decide a question is important and needs to be investigated, but they don’t have sufficiently good data to draw accurate conclusions. Because there are no incentives to recognize that and abandon the line of inquiry, they proceed regardless and make claims that end up being drastically wrong. Anyone from outside the field who points out what’s happening is simply ignored, or attacked as “not an expert” and thus inherently illegitimate.
Although no actual expertise is required to spot the problems in this case, I can nonetheless criticize their work with confidence because I actually am an expert in fighting bots. As a senior software engineer at Google I initiated and designed one of their most successful bot detection platforms. Today it checks over a million actions per second for malicious automation across the Google network. A version of it was eventually made available to all websites for free as part of the ReCAPTCHA system, providing an alternative to the distorted word puzzles you may remember from the earlier days of the internet. Those often frustrating puzzles were slowly replaced in recent years by simply clicking a box that says “I’m not a bot”. The latest versions go even further and can detect bots whilst remaining entirely invisible.
Exactly how this platform works is a Google trade secret, but when spammers discuss ideas for beating it they are well aware that it doesn’t use the sort of techniques academics do. Despite the frequent claim that Botometer is “state of the art”, in reality it is primitive. Genuinely state-of-the-art bot detectors use a correct definition of bot based on how actions are being performed. Spammers are forced to execute polymorphic encrypted programs that detect signs of automation at the protocol and API level. It’s a battle between programmers, and how it works wouldn’t be easily explainable to social scientists.
Spam fighters at Twitter have an equally low opinion of this research. They noted in 2020 that tools like Botometer use “an extremely limited approach” and “do not account for common Twitter use cases”. “Binary judgments of who’s a “bot or not” have real potential to poison our public discourse – particularly when they are pushed out through the media …. the narrative on what’s actually going on is increasingly behind the curve.”
Many fields cannot benefit from academic research because academics cannot obain sufficiently good data with which to draw conclusions. Unfortunately, they sometimes have difficulty accepting that. When I ended my 2017 investigation of the Berkeley/Swansea paper by observing that social scientists can’t usefully contribute to fighting bots, an academic posted a comment calling it “a Trumpian statement” and argued that tech firms should release everyone’s private account data to academics, due to their capacity for “more altruistic” insights. Yet their self-proclaimed insights are usually far from altruistic. The ugly truth is that social bot research is primarily a work of ideological propaganda. Many bot papers use the supposed prevalence of non-existent bots to argue for censorship and control of the internet. Too many people disagree with common academic beliefs. If only social media were edited by the most altruistic and insightful members of society, they reason, nobody would ever disagree with them again.
Featured Video

Death Spikes & Rising Cancer In Our Youth Explained
or go to
Aletho News Archives – Video-Images
From the Archives
Politicians lie
By Mazin Qumsiyeh | Popular Resistance | August 18, 2013
There is no way to say this truth nicely: Politicians lie. That includes Japanese, American, Egyptian, Israeli, and Palestinian politicians! Is there something more common sense than that? Yet, so many citizens around the world believe their own politicians or wistfully acknowledge lies but think it is part of the job needed to run things. They believe even when politicians contradict themselves blatantly. This phenomenon is rather remarkable. It is a dissonance and disconnect from reality that many seem oblivious to. It is very dangerous because it can lead to accepting rationales for going to war. These can be deadly wars that lead to millions of lives lost as happened in what was called World War 1 and WW2. Even when incredible and declassified evidence abound, politicians continue to lie and old mythologies refuse to die. Here are just a few of the countless lies told to us over the past few decades… continue
Blog Roll
 Aletho News
- RSF military group defects, joins Sudanese army: State media
- Ireland goalkeeper refuses to play ‘Israel’ as squad weighs boycott
- China pushes back against US on Cuba, Iran
- Ukrainian Soldiers, Potential Mercenaries: Have Gun, Will Travel!
- Burnham’s UN debut… A masterclass in British disinformation
- Iran flights continue despite US aviation sanctions
- Global Tipping Points Lead the World Into a State of Entropy
- The day-after at the White House: USA and Xi Jinping
- The Geopolitical Balance in the Red Sea: The UAE Being Displaced by New Players
- Iraqi resistance group vows to stage airport sit-ins over Iran aerial blockade
- If Americans Knew
- Deconstructing Netanyahu’s pants-on-fire UN rant – Daily Update
- Trump betrayed voters with his campaign lies and prioritized a foreign country once he took office
- Netanyahu calls Israel’s war in Gaza ‘opposite of genocide’ in UN speech to near-empty hall
- Settler Kidnappings: Torture, Sexual Abuse and Terrorisation of Palestinian Abductees as Israel Deepens Annexation of West Bank
- Gaza winter nears as 162,000 tents become unusable, raising fears of humanitarian crisis
- Netanyahu says, “It’s the opposite of genocide”; UN says Gaza economy is world’s ‘most severe crisis on record’ – Daily Update
- Israel’s US-Backed Assault on Gaza Has Created the ‘World’s Most Severe Economic Crisis on Record’: UN
- ‘Protecting U.S. Citizens’… From Israel
- ‘This is where I live now, the back of a truck’: a day in the life of a grandmother in Gaza
- In UN Speech, Iran’s President Displays Pictures of Children Killed by US, Brings Attention to Israel’s Nuclear Arsenal
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

