Fauci and the Biden Admin are purposely deceiving us about the ‘Delta variant’ threat
By Jordan Schachtel | June 24, 2021
Prominent actors within the U.S. government have been lying to the American people about COVID-19 for 18 months and counting, and their latest behavior shows that the individuals in charge of U.S. Government Science have no intention of stopping the charade anytime soon. Over time, their lies have evolved to become so common and so reckless to the point that someone with even the most rudimentary understanding of viruses can instantly debunk the lies. The latest “Delta variant” paranoia peddling has put their incompetence, deliberate spreading of falsehoods, and perpetual gaslighting of their own citizens on display for the world to see.
The Biden Administration, through lifelong government bureaucrat Anthony Fauci, is making a hard push to fear monger about the supposed dangers posed by the “Delta variant” of the virus that causes COVID-19.
A video posted from the White House account made the rounds Thursday morning, stating:
“Here’s the deal: The Delta variant is more contagious, it’s deadlier, and it’s spreading quickly around the world – leaving young, unvaccinated people more vulnerable than ever. Please, get vaccinated if you haven’t already. Let’s head off this strain before it’s too late.”
Fauci has been on a media tear this week hyping up the threat of the Delta variant.
Sometimes it’s easy to reflexively dismiss these warnings of doom and gloom as total nonsense, especially when they are in fact total, bald-faced nonsense.
(Check out this video from Ivor Cummins breaking down how the Delta variant, previously referred to as the Indian variant, is nothing more than a “political scariant.”)
First of all, it goes against all understanding of 101 concepts for a virus to mutate to become both more contagious and more deadly. If a virus becomes more contagious, it spreads faster but does not kill off its host. If a virus becomes more deadly, it doesn’t spread as fast because it has taken out its host. In fact, the best evidence we have on the Delta variant shows that it is probably less deadly than previous mutations. And it’s always good to remember that we’re talking about a disease that sports an original recovery rate well over 99%.
Second, the idea that human intervention can “head off” a strain is an idea straight out of the “COVID Zero” (the idea that you can eliminate the virus from this earth) pseudoscience playbook. Fauci and the gang are by no means brilliant minds, but they are well aware that they cannot eliminate a virus from circulation. This makes it obvious that there are several ulterior motives in play, none of which have anything to do with our health.
Outside of academic models (we all know how well those held up in the past with lockdowns, masks, etc), there is no hard evidence anywhere in the world that this Delta variant is any more or less dangerous than any other mutation of the virus. In fact, the statistics on this variant shows no particular reason for alarm. Yet the government is — let me know if this sounds familiar — baselessly making stuff up about a virus based on absolutely zero real world data.
Since the beginning of COVID Mania, the government has never been on the side of science, evidence, and data. From the infamous Gates-funded panic models and fraudulent Chinese government “science” that encouraged the world to lock down indefinitely, to the absurd mannequin “studies” about the efficacy of masks, this latest Delta variant scaremongering has once again put their lies on display for the world to see. Given the almost two years of immunity building related to the virus, the threat posed by COVID-19 at this point in time is virtually nonexistent. There never was a legitimate reason for a single restriction on our liberties, and today, the “delta variant” argument to curb our rights and transform our society is more baseless than ever before.
Re-Evaluating Mask Mandates – Part I: Science Gives Way to the “Talisman”
By Masha Krylova | C2C Journal | June 13, 2021
The health of my patient will be my first consideration; I will not use my medical knowledge to violate human rights and civil liberties, even under threat.
—World Medical Association: Declaration of Geneva, 2006
Where all men think alike, no one thinks very much.
—Walter Lippmann, 1937
We all remember when it was natural to strike up a conversation with a stranger on a street, in a mall or in a café. Sharing a smile would often start the enjoyable process from which mutual trust and understanding could flow. Seeing other people’s open faces and hearing them laugh felt contagious and energizing. A spontaneous encounter had a chance to turn into something long-lasting and meaningful.
Those times were pre-Covid-19; the pandemic has brought great upheaval to social norms. Rarely do many of us talk to strangers in public places. Communication is largely transactional – aiming a few words at a clerk behind a plexiglass shield and straining to hear the muffled reply. Laughter has become a rarity. And even if others smile at us, we hardly can tell – or know when to smile back. All we see are faces largely hidden behind masks and staring, shifting or downcast eyes.
Happily, that is beginning to change. Mask mandates are dropping left and right across the United States. As of June 8, 35 U.S. states had removed these requirements in indoor or outdoor public settings. A few U.S. governors have even prohibited local governments and school boards from countermanding such state policy. At the same time, the exposure of Anthony Fauci’s serial contradictions has loosened his grip on the American psyche – weakening the entire pro-mask side. Gathering limits are disappearing as well; the recent Indy 500 was packed with mostly unmasked auto race enthusiasts and fans are once again jamming stadiums for pro sports.
In Canada, a number of provinces are also reopening – led in speed by Alberta, where all provincial restrictions will be dropped within two weeks of 70 percent of the population receiving one dose of vaccine. That pointedly includes the mask mandate. If this occurs, and much of the rest of Canada follows suit, the summer of 2021 could end up being, if not exactly the “best summer ever” in the previous hopeful words of Alberta Premier Jason Kenney, then at least one to rekindle normal life and, perhaps, look back upon as the time when the Covid-19 pandemic was put in its grave.
These lovely sentiments – surely shared by millions of Canadians – could be dashed, however. Reopening is threatened by a number of political leaders, urged on by an entrenched medical/scientific faction, who appear almost terrified of normality’s return and whose default position is to lock down, prohibit and prevent. Ontario, for example, only re-authorized camping last Friday and recently extended its state of emergency until December. Premier Doug Ford, wrote Matthew Lau in the Financial Post, “has turned the presumption of liberty completely on its head. In Ontario there is now a presumption of government control.”
Even in Alberta, big-city mayors are suggesting they might defy the province’s mask mandate lifting. They are egged on by vocal medical experts who have formally demanded that masks remain in place until 70 percent of the population has had two vaccine doses. This may amount to something like “forever,” since vaccination curves in other countries to date have gone nearly flat at approximately 55-65 percent with even one dose. Alberta, it was reported last week, is having trouble achieving the last several percentage points leading to 70 percent with one dose.
In short, if some have their way, it could be masks for a long time. Should further new Covid-19 variants or new infectious diseases come along in the meantime, it might be masks forever.
If Canada is to enter a major political struggle over the possibility of long-term masking, then surely it is worth revisiting the basic question of whether masks actually work. And, even if masks are shown to be useful in slowing the transmission of Covid-19, the public has a right to understand whether habitual mask-wearing carries negative health effects, in order to weigh the costs against the benefits of such an intrusive long-term policy.
With those questions in mind, C2C Journal brings you this exclusive, carefully researched two-part analysis. In Part I, we review the recent history of mask requirements and discuss the initial evidence around widespread mask-wearing.
When it Began: The WHO Mask Guidance
On April 6, 2020, the World Health Organization (WHO) issued Interim Guidance on the use of facemasks against Covid-19. The organization advised only health professionals to wear medical masks or respirators and to avoid non-medical masks because the effectiveness of the latter, it stated, was not established.
Significantly for the wider population – or seemingly so – it also cautioned that “the wide use of masks by healthy people in the community setting is not supported by current evidence and carries uncertainties and critical risks.” Among these were potential self-contamination by frequent touching and re-wearing of single-use masks, breathing difficulties and a “false sense of security, leading to potentially less adherence to other preventive measures such as physical distancing and hand hygiene.”
The WHO’s April guidance was consistent with the statements of numerous public health officials worldwide. It was, for example, preceded by the official statement by Canada’s Chief Public Health Officer Theresa Tam who suggested that “putting a mask on an asymptomatic person is not beneficial, obviously if you’re not infected.”
The official advice should have been unsurprising, even though by this time millions of individuals were rushing to scour store shelves for any and all mask varieties, while others rigged up bizarre contraptions out of old diving helmets or even fish bowls, and a few were seen shuffling down aisles in full hazmat suits (real or home-fashioned). But the official advice was consistent with decades of established international guidance for the management of disease outbreaks, in which masks are recommended for those who are sick – to protect the healthy – but not ubiquitously (see, for example, the WHO’s guide of 2018, or Public Health England Principles of 2015, or the Association of Faculties of Medicine of Canada Primer on Population Health).
Physician Margaret Harris, a member of the WHO’s coronavirus response team, was quoted saying that “the mask is almost like a talisman,” making “people feel more secure and protected.” An official scientist appeared to say that mask-wearing was no longer about science, but about sorcery and emotion.
Regardless of how sound these recommendations are, they soon were thrown overboard as fears spread of “asymptomatic spreaders,” many doctors and scientists started asserting benefits to the public wearing almost any sort of mask, and governments and international organizations sought to reassure jittery populations they were taking “crucial steps” to “save lives” – which now included requiring people to wear masks in a variety of settings.
The WHO subsequently updated its mask guidance, with the most recent document issued on December 1, 2020. Citing a number of studies, this one advised the general public to wear either medical or three-layer fabric facemasks in indoor and outdoor settings where ventilation is inadequate and physical distancing is less than 1 metre. It asserted several pandemic control benefits to such practice, including reduced spread of viral respiratory droplets and reduced stigmatization towards mask-wearers (a transient phenomenon early in the pandemic). Further stated benefits included making people feel that “they can play a role in contributing to stopping spread of the virus,” encouraging proper hygiene and, finally, reducing transmission of other respiratory illnesses such as tuberculosis and influenza.

Caution to the wind: The WHO’s explicit list of negative effects from ubiquitous mask wearing was ignored by all.
The WHO’s list of disadvantages, however, had grown significantly and now also included potential headaches, facial skin problems, difficulties communicating, discomfort, improper mask disposal, poor compliance among young children and difficulties for people with developmental challenges, with chronic respiratory problems or those living in hot and humid conditions. Nor should this have been surprising either, for as we shall see it too was consistent with longstanding scientific understanding. None of these mask-associated risks, however, received a thorough airing in news and social media.
On the contrary, many governments imposed even more stringent and often duplicative requirements, like requiring masks and distancing even outdoors where ventilation was good, or masks and plexiglass barriers, or masks, face shields and distancing. Masks, meanwhile, took on novel roles as political statements or articles of faith employed by political leaders, organizations, public health figures and much of the population. People were even seen swimming with paper masks. Physician Margaret Harris, a member of the WHO’s coronavirus response team, was quoted in an NPR column saying that “the mask is almost like a talisman,” making “people feel more secure and protected.” An official scientist appeared to say that mask-wearing was no longer about science, but about sorcery and emotion.
Meanwhile, no one in the public sphere seemed willing to peruse the WHO’s December 2020 guideline in detail. Had they done so, they might have noticed two statements eerie in their juxtaposition. First, the WHO clearly recognized the serious limitations of the studies it cited about the efficacy of masking to reduce viral spread: “[The] studies differed in setting, data sources and statistical methods and have important limitations to consider notably the lack of information about actual exposure risk among individuals, adherence to mask wearing and the enforcement of other preventive measures.” Second, the WHO nonetheless insisted on universal mask usage: “Despite the limited evidence of protective efficacy of mask wearing in community settings, in addition to all other recommended preventive measures, the [guidelines development group] advised mask wearing.”
The WHO’s categorical recommendation, then, rested on admittedly shaky foundations. Over half a year has passed. One would expect there to be an ever-growing number of studies dedicated to Covid-19 and related issues, including masking. And so there has been.
Current Evidence on Mask Effectiveness
More than 300 scientific papers have been published specifically on masking during the pandemic. The best way to evaluate such a vast body of research without losing the forest for the trees is to focus primarily on literature reviews and systematic reviews (special types of scientific analysis that summarize up-to-date knowledge on a particular issue). This narrows the search to some 20 review studies (as of May 2021). Six of these provide support for universal mask wearing using epidemiological data (1, 2, 3, 4, 5 and 6). Six others offer mechanical evidence by describing material and filtration properties of masks. Two reviews are inconclusive (this and this), while the rest are less relevant (comparing medical masks to N95 masks in a healthcare setting, for example, this).
The most recent and comprehensive review is by researchers from the University of Hawaii at Manoa, Honolulu, published in April 2021. This interdisciplinary report outlines the “state-of-the-art understanding of mask usage against Covid-19” by covering the most important epidemiological data, face mask filtration mechanisms and mask recontamination and reuse.
In their epidemiological evidence the researchers cite eight publications that report a positive association between mask wearing and a reduced risk of Covid-19 infection. These studies were conducted in China, Thailand, the U.S., Germany and Canada. The Canadian evidence notably encompassed both provincial data from Ontario and nationwide data analyzing the effect of mask wearing on Covid-19 case numbers over the course of eight months. “In the first few weeks after their introduction, mask mandates are associated with an average reduction of 25 to 31% in the weekly number of newly diagnosed COVID-19 cases in Ontario,” the study concluded. It also speculated that had indoor masking been mandated by early July, there would have been 25-45 percent fewer weekly cases across the country than actually occurred.
The other studies were different in methodology and reported varying strengths of the association between mask wearing and risk reduction, ranging from 15 percent to 80 percent. The University of Hawaii team’s conclusion appears decisive: “All available epidemiologic evidence suggests that community-wide mask-wearing results in reduced rates of COVID-19 infections.”
Not All Science Is Created Equal: RCTs vs. Observational Studies
The take-home message from the above research appears unequivocal: masks work. The factual conclusion provides scientific support for the political decision to impose a public mask mandate. But for one fact: nearly all Covid-19-related epidemiological studies are either observational analyses (such as this or this), simulation studies (such as this), or a combination thereof (like the Canadian study described above). Almost none involved randomized controlled trials (RCTs).
Why does that matter?
The distinction between study types is imperative for it speaks of the quality and not simply the quantity of the available scientific evidence. Setting aside simulation studies that are hypothetical and therefore of lesser empirical value, it is important to understand the differences between RCTs and observational studies (case-control and cohort studies are two types).
The RCT facilitates an objective comparison between various types of intervention, or between treatment and non-treatment. The RCT achieves this by using the process of randomization, assigning participants randomly either to experimental or control groups. The goal of such studies is to prevent manipulation of the results and to draw, as accurately as possible, a causal relationship between an intervention, or a behaviour, and the subsequent outcome.
The link of causality cannot be achieved in observational research, which involves analyzing data gathered in natural conditions without researchers’ intervention. Although observational studies are illuminating and useful in various scenarios, they are inevitably biased. The bias occurs because such studies do not allow for direct control over confounding variables that may have an impact on the study results. For example, for one to say that “A causes B” requires ensuring that the effects of all other important variables on B have been removed or cancelled through randomization.

Through the process of randomization, RCTs are able to establish a causal link between a treatment or behaviour and an outcome. Observational studies are limited to showing correlation, or association – and thereby can be misunderstood.
This is impossible in observational studies, always leaving a chance that the observed outcome B might have been caused by a variable, or variables, other than A. Thus, observational studies, even those employing advanced statistical analyses, cannot reach conclusions stronger than establishing temporal associations between one thing and another. But association, or correlation, does not demonstrate causation. (The Canadian study cited above, for example, notes that mask mandates are “associated” with a reduction in the rate of Covid-19 infection; it does not assert a causal relationship.)
The Odd Reluctance to Conduct RCTs in Regard to Public Health Matters
Which brings us back to the 300-odd mask-related studies conducted in the Covid-19 era. Many, indeed, found associations or correlations between widespread adoption of masks and a reduction in Covid-19 case counts, or a slowing of acceleration in case counts. In an observational study like this one, however, it is reasonable to ask whether the detected reduction in Covid-19 transmission was caused by mask wearing. Could it not have been due to other preventative health measures adopted around the same time, such as improved hand hygiene, limited social interaction, physical distancing in public settings or even individuals’ general health regimen? And what about the impact of other variables such as age or race on the risk of catching the virus? Finally, could there be other, as-yet overlooked confounders that affect virus spread? Randomization is required to negate the effects of the confounding variables, known or unknown.

Correlation does not show causation: Masks may be associated with a reduced rate of Covid-19 infection, as frequently documented in observational studies, but a host of other factors could also be at work.
Because of these known limitations of observational studies, the RCT is recognized as the gold standard of clinical research practice, a rigorous tool of cause-and-effect analysis. One of the world’s leading experts in medical standards and statistics, Dr. Janus Christian Jakobsen, who is frequently cited for her systematic reviews of meta analyses, authoritatively stated:
“Clinical experience or observational studies should never be used as the sole basis for assessment of intervention effects – randomized clinical trials are always needed…Observational studies should primarily be used for quality control after treatments are included in clinical practice.” (Emphasis added.)
It is thus clear that in health-related contexts, researchers should rely on RCTs whenever possible and use observational studies to gather supplementary evidence.
The most common arguments against RCTs are that they are expensive, time-consuming and impractical for population-wide interventions. There are also understandable ethical objections against exposing healthy control groups to contagious and potentially fatal infections, in this instance attempting to determine whether unmasked people are more likely to catch Covid-19. In fact, some have asserted, in reference to the WHO, that “we should not generally expect to be able to find controlled trials” in the context of population health measures.
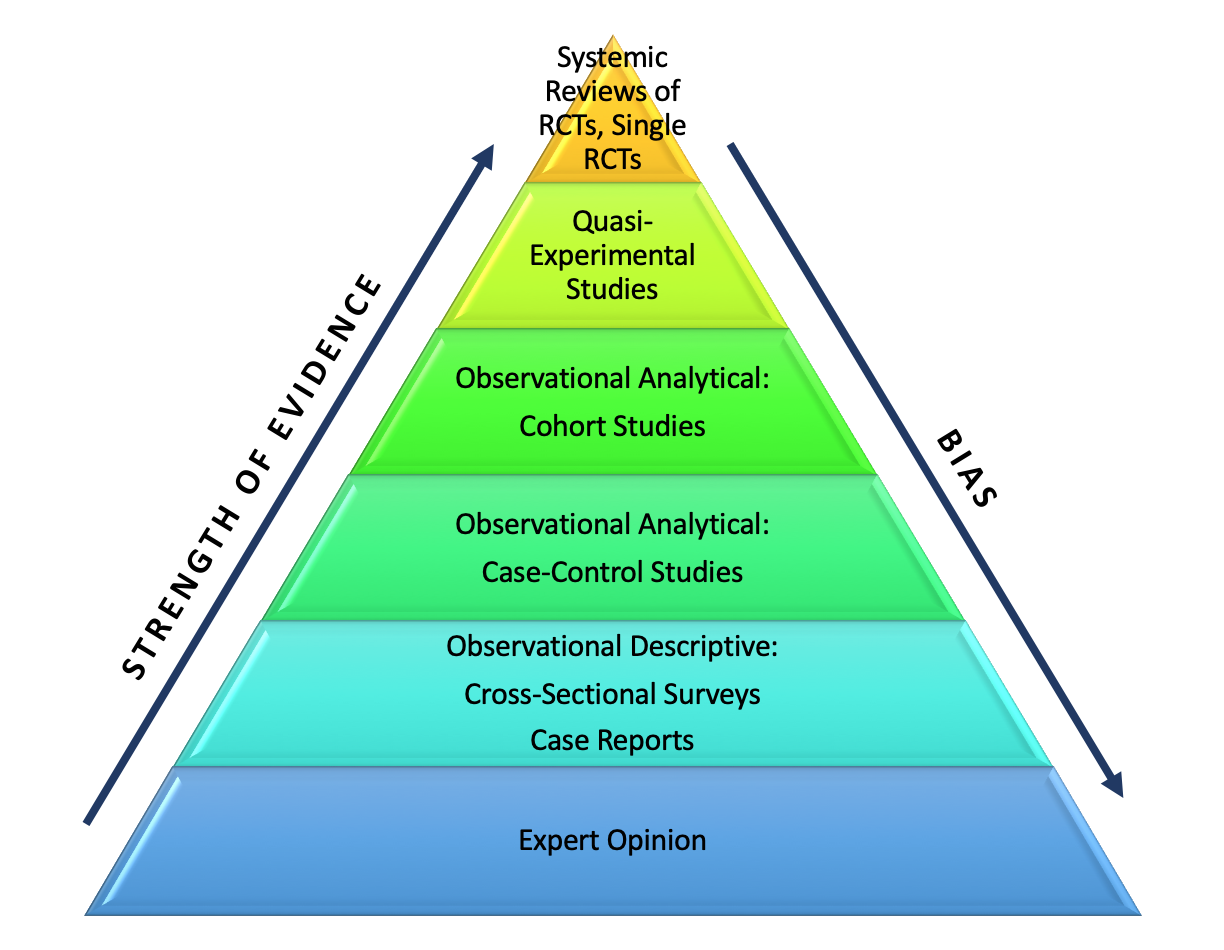
Maximum strength of evidence, minimum degree of bias: Not for nothing is the randomized controlled trial considered the “gold standard” of clinical practice. (Graphic by Masha Krylova/ C2C Journal)
Unethical and impractical? It is claimed that RCTs should not be used to study the effects of health measures on Covid-19 infection – yet numerous RCTs have examined influenza on a community-wide scale.
Still, it has been over a year since mask mandates were first imposed in many countries. Given the prodigious effort poured into seemingly anything to do with Covid-19, this should be ample time for researchers to gather resources and test mask effectiveness in a controlled experimental setting. Nor was it unheard-of prior to the pandemic to perform RCTs in healthcare and wider-population settings to evaluate the effect of mask wearing on the transmission of respiratory illnesses such as influenza (see this review of 2010) and influenza-like illness (also see this scoping review of 2020). These studies clearly overcame objections related to practicality and ethics. Why should Covid-19 be different?
The cited reviews present intriguing details: with respect to influenza, five out of six RCTs conducted in healthcare settings found no significant difference between mask-wearing and control groups. Even more important from the standpoint of the current pandemic, none of four RCTs performed in broader community settings found a significant difference between masking and remaining bare-faced. For influenza-like illnesses, the pooled data from five other RCTs as well showed a non-significant protective effect of mask wearing for avoiding either primary or secondary infection. These results appear substantial and would seem of some relevance to the current pandemic. But there is more.
End of Part I.
Coming next in Part II: Should you care whether masks are more like a sieve or a filter? Is there really no RCT-generated “gold standard” evidence regarding whether wearing masks reduces the spread of Covid-19? And is there any basis to concerns of ill effects from wearing masks?
Maria (Masha) V. Krylova is a Social Psychologist and writer based in Calgary, Alberta who has a particular interest in the role of psychological factors affecting the socio-political climate in Russia and Western countries.
Doctor fired from University of Saskatchewan after posting online statement asking for “informed consent” on vaccines

By Christina Maas | Reclaim the Net | June 25, 2021
Dr. Francis Christian was fired from his position at the University of Saskatchewan and is being investigated by the College of Physicians and Surgeons of Saskatchewan for an online statement calling for informed consent when it comes to vaccines.
Dr. Christian has been a surgeon for over 20 years. In 2018, he was appointed to the position of Director of Surgical Humanities Program and Director of Quality and Patient Safety at the University of Saskatchewan. He also co-founded the Surgical Humanities Program and is an editor of the Journal of The Surgical Humanities.
On June 23, Dr. Christian was suspended from all teaching responsibilities, and will no longer be an employee of the University of Saskatchewan from September 2021. The College of Physicians and Surgeons of Saskatchewan is also investigating him after receiving a complaint about a statement he released last week.
In a statement to over 200 doctors, released on June 17, Dr. Christian recommended informed consent when administering COVID-19 vaccines to children. The statement made it clear that he is pro-vaccine, does not represent any group, the University of Saskatchewan, or the Saskatchewan Health Authority.
“I speak to you directly as a physician, a surgeon, and a fellow human being,” Dr. Christian said in the statement before going on to recommend the principle of informed consent so that the patient is “fully aware of the risks of the medical intervention, the benefits of the intervention, and if any alternatives exist to the intervention.”
“This should apply particularly to a new vaccine that has never before been tried in humans… before the vaccine is rolled out to children, both children and parents must know the risks of m-RNA vaccines,” he added.
The surgeon noted that he was yet to hear of “a single vaccinated child or parent who has been adequately informed” about the risks of COVID vaccines in children.
His statement argued that m-RNA vaccines are experimental. Dr. Christian further argues that the vaccines do not qualify for “emergency use authorization” in kids because “Covid-19 does not pose a threat to our kids. The risk of them dying of Covid is less than 0.003% – this is even less than the risk of them dying of the flu. There is no emergency in children.”
Dr. Christian also noted the vaccines have caused “serious medical problems for kids” around the globe, such as “a real and significantly increased risk” of heart inflammation and myocarditis.
The College of Physicians and Surgeons sent him a letter stating that it has “received information that you are engaging in activities designed to discourage and prevent children and adolescents from receiving Covid-19 vaccination contrary to the recommendations and pandemic-response efforts of Saskatchewan and Canadian public health authorities.”
The Litigation Director of The Justice Center for Constitutional Freedoms, the organization representing Dr. Chrisitian in the complaint made against him, expressed his concerns over medical professionals getting censored and punished for expressing views contradicting the government’s narrative.
“We are seeing a clear pattern of highly competent and skilled medical doctors in very esteemed positions being taken down and censored or even fired, for practicing proper science and medicine,” said Cameron.
“Censoring and punishing scientists and doctors for freely voicing their concerns is arrogant, oppressive and profoundly unscientific,” he added.
“Both the western world and the idea of scientific inquiry itself is built to a large extent on the principles of freedom of thought and speech. Medicine and patient safety can only regress when dogma and an elitist orthodoxy, such as that imposed by the Saskatchewan College of Medicine, punishes doctors for voicing concerns,” Cameron concluded.
There is no Covid third wave in Africa
Alarmist reporting is getting basic facts wrong
By Toby Green | Unherd | June 24, 2021
The last few days have seen an avalanche of reports that a third wave of Covid-19 is underway in Africa. Seasoned coronavirus watchers will not be surprised that the alarm was raised in Geneva. WHO Central issued alarming press releases on June 7th and 17th, with the Regional Director for Africa, Dr Matshidiso Moeti, stating in the latter that “Africa is in the midst of a full-blown third wave”. So what’s happening?
Since the June 7th press release, there have been 1,651 new deaths reported from Covid-19 across the entire continent in 17 days, less than 100 per day. In a continent where 9 million people die annually (roughly 25,000 per day), reported Covid deaths in this “full-blown” third wave thus currently account for roughly 0.4% of daily mortality in Africa. Certainly, there are mortality increases from Covid reported in some countries such as Cape Verde and the Democratic Republic of Congo, but they are not anything like on the scale of what has happened elsewhere.
Moreover, the vast majority of these fatalities have occurred in temperate zones: South Africa, Morocco, Egypt, Algeria, Libya and Tunisia account for 105,000 of the 139,500 deaths reported from Covid-19 across the continent.
Many of the reports on this “third wave” point to the failure to count deaths accurately, and suggest that these figures mask the true problem. Reports from the BBC and the New York Times have pointed to a continent-wide lack of systemic mortality figures. But running at 0.4% of current mortality, and touching a small area of the continent as a whole, even if this was an underestimate by 1000%, Covid would still only be a minor concern to most Africans. In fact, a recent paper disputes these accusations of undercounting: the authors note that “while only 34.6% of countries [in Africa] have complete death registration data… all countries have a system in place, and there is no evidence that COVID-19 mortality data is less accurately reported in Africa than elsewhere”.
What certainly does go under-reported are cases. This is good news, as it indicates that much of the continent’s population has already developed antibodies to Covid-19 through mild infections. In a study from July to October 2020 of mineworkers tested in Ivory Coast, 25.1% had Covid antibodies; meanwhile, a February study in South Africa based on blood donors found antibody levels of 63% in Eastern Cape, 46% in Free State, and 52% in KwaZulu Natal, while a study from Cameroon just published found antibody levels of 32%. These figures far outstrip recorded cases, suggesting that many Africans already have protection from Covid.
However the WHO redefined herd immunity last year as only achievable through vaccination, so it may not want to publicise this. The Guardian last week added to the clamour, reporting on research that had not been peer-reviewed and which claimed that Covid infection did not provide immunity. Ironically, a series of studies published in Nature the week before had found that “the evidence thus far predicts that infection with SARS-CoV-2 induces long-term immunity in most individuals”.
The evidence from Africa is quite clear, in fact. Large sections of the population have now developed Covid antibodies, and death rates are low compared to other chronic illnesses. Herd immunity does not have to be achieved through vaccination, either in Africa or elsewhere. But none of these conclusions fit with the catastrophic decisions taken by global policy elites over the past year, so they won’t be coming to a television news channel near you any time soon.
Toby Green is the author of The Covid Consensus: The New Politics of Global Inequality (Hurst).
Why Hasn’t the Government Published a Cost-Benefit Analysis of Lockdown?
By Noah Carl • Lockdown Sceptics • June 24, 2021
When considering a policy as unprecedented and far-reaching as a nationwide lockdown, you’d assume the Government would carry out a cost-benefit analysis. After all, such analyses are routine in policy-making.
For example, the Treasury maintains a document called ‘The Green Book’, which gives detailed guidance on how to compute the costs and benefits of particular actions. It refers to concepts such as opportunity cost, discount factors and adjusting for inflation.
You might say there wasn’t much time to carry out a detailed cost-benefit analysis before the first lockdown last March. (Though the Government could have provided a few rough numbers for the public to scrutinise.) However, it’s now more than a year later, and there still hasn’t been any attempt to weigh the costs and benefits.
In a report for the Institute of Economic Affairs published last December, the economist Paul Ormerod argued that the Government’s refusal to crunch the numbers reflects a general overreliance on epidemiological expertise, at the expense of economic expertise.
As Russ Roberts, another economist, has observed, “Knowing a lot about the human body does not make you an expert in risk analysis, tradeoffs, or unintended consequences.” Note: this is not to imply that all or even most economists are opposed to lockdowns, but simply that key insights from that discipline have been overlooked during the course of the pandemic.
Several cost-benefit analyses of the UK lockdowns have been published by persons outside the Government, and each one has concluded that the costs almost certainly outweighed the benefits.
Since the NHS typically pays up to £30,000 to extend a patient’s life by one quality-adjusted life-year, a reasonable estimate of the benefits of lockdown can be obtained by multiplying the expected number of life-years saved by 30,000.
For example, if we assume (generously) that lockdowns saved 50,000 lives and prevented 500,000 people from getting long COVID, then the total benefits would be about £16.5 billion. This figure then has to be weighed against some measure of the costs (including effects on the economy, health, education and civil liberties). Given that the fall in GDP alone last year was over £220 billion, it seems very unlikely that lockdowns would pass a cost-benefit test.
The Government’s lack of interest in cost-benefit analysis was highlighted in a recent LinkedIn post by Daniel Fujiwara – an expert in policy evaluation. Fujiwara was apparently invited to “meet with senior Government officials to discuss the pros and cons of lockdown”. However, despite offering his advice and input pro-bono, he “never heard back from them”.
In the post, Fujiwara goes on to say, “Lockdowns should have stopped at the point where an additional day of #lockdown causes more damage to our society than it benefits us… My analysis of the impacts of lockdown last year suggests that we have gone well beyond this threshold.”
One can only assume that the Government’s failure to publish even basic estimates of the costs and benefits of lockdown is due to fear of what those estimates might show…
So Matt Hancock groped his assistant…. who cares?
By Catte Black | OffGuardian | June 25, 2021
Oh gosh, Matt Hancock is being outed as a sleazebag.
Who knew, right?
The Sun published pics purporting to be of him and his girlfriend kissing in an elevator and even the BBC thinks this is newsworthy.
So this is serious now. You can sign off on mass murder all you like, Matt, but when you start breaking social distancing rules by groping married ladies in elevators that’s a step too far.
His lies and hypocrisy are puke-inducing of course. Some people who actually thought the ruling elite really believed in their social distancing, triple masking, hand-sanitizing rules may well be deeply shocked. Many of the more clued in are cheering the humiliation fest. Fair enough I guess. It’s certainly gratifying to see some psychopathic creep suddenly shamed or called to account.
And it’s probably harmless. Isn’t it?

Or then again maybe not.
What actually are these periodic ‘outings’ we witness?
What does it actually mean when an establishment billionaire-owned media outlet somewhere on the permitted and phony spectrum of Left/Right ‘leaks’ some grainy footage, or a clumsily revealing email, that ends up shaming some erstwhile pillar of the prevailing narrative?
Is the system finally getting a conscience? Are things gonna be ok, now [insert hate figure here] is gone?
Of course not. No one seriously thinks that, do they?
The establishment is essentially amoral. A psychopathic hive mind entity without conscience or ethics. It doesn’t expose or reject one of its own unless it sees advantage to itself in doing so. When one of them is publicly humiliated and cast out it’s because he/she has failed in a power play, or been ousted in a palace coup, or is earmarked as a good sacrifice to appease the restless mob.
You see, to the 1%, the 99% are caged dogs. Our masters need to gauge the frustration and make sure it doesn’t spill over. Being thrown a ‘victim’ to rend every now and again is a nice way of venting tension while also giving us the impression the system self-regulates.
It keeps us distracted occupied and works off our aggression and represents NO THREAT to vested interests.
Even the supposed ‘victim’ will likely just ride out the storm or, if fired from his job, get a fat fee and ‘retire’ happily, only to be readmitted to the fold after a short exile.
Ok, maybe in very extreme cases, they’ll occasionally get ‘suicided’, though that’s usually reserved for genuine outsiders with an inconvenient conscience.
Whatever way it plays out, it’s a show. We are groundlings gawping at the painted actors on the stage. Our reaction is anticipated, manipulated, catered for and ultimately despised.
And anyhow we know, don’t we, that rending one of these Ringwraiths is missing the point. They are all replaceable servants of the Machine. Well paid, cosily ensconced – but ultimately expendable.
While we’re tearing the latest ‘victim’ with our teeth we’re forgetting all that and forgetting the real enemy.
And the real enemy is laughing at us.
I hope to see us become more sophisticated. Ignore these staged witch hunts, these hate sessions, these deliberately seeded water-cooler controversies about what Fauci knew or whether Hancock should go…yada y yada y pues yada.
If we are falling for this every time we need to get to know our enemy and its tricks a lot better, or we don’t have much chance of winning in this latest and most important struggle.
Johnson’s govt taken to court by theatre bosses to force release of Covid-19 trial data
RT | June 24, 2021
A group of concert and theatre bosses led by Andrew Lloyd Webber has launched legal action against the British government in a bid to force it to publish data from a trial assessing the safety of indoor events during the pandemic.
The concert managers and theatre producers are demanding that the government provide data from its Events Research Programme – a trial assessing the safety of indoor events – so that they can plan to finally reopen their institutions.
In a statement on Thursday, they said the government had “refused to publish the results from the first phase of the Events Research Programme, despite saying that it would do so on numerous occasions.”
The statement adds that, in addition to not publishing the data from the trial, the government has not provided any form of insurance scheme to safeguard the industry against any further delays following 15 months of closures due to Covid curbs.
The entertainment bosses claim that, according to the government, the trial has been a huge success, which in turn has contributed to the increasing frustration within the entertainment sector concerning the industry’s continuing dormant state.
Pilot events under the programme, which the industry participated in, included the BRIT Awards at the O2 Arena, an outdoor festival event in Liverpool for 5,000 people, a snooker tournament at the Crucible Theatre in Sheffield, and the Download festival for 10,000 people last weekend.
The reopening of the theatre industry in England has been pushed back from its anticipated late June date until July 19, following the spread of the more infectious Delta variant.
Speaking later on Thursday, a spokesman for Prime Minister Boris Johnson said the government had made £2 billion available via a major arts funding package. He added that the government understands “the necessary delay to step four is challenging for live events.”
The impresarios note in their statement that live entertainment and theatre generate £11.25 billion for the UK economy each year, supporting just under one million jobs.
The anti-Covid pill Big Pharma doesn’t want you to have
By John Hollaway | The Conservative Woman | June 22, 2021
From Wikipedia: ‘During the 2020 COVID-19 pandemic, misinformation was widely spread claiming that ivermectin was beneficial for treating and preventing COVID-19. Such claims are not backed by good evidence.’
WHEN encountering an inexplicable anomaly in human behaviour, common rules of thumb can often give an insight. Oddly, though, these differ from country to country. For Americans it is ‘follow the money’. For Italians it is ‘cui bono?’ – who benefits? The nearest French rule is perhaps ‘cherchez la femme’.
Sometimes none of these help. Sometimes a perverse piece of human nature cannot be explained in terms of money, perquisites or feminine influence. The ivermectin mystery is one such.
Ivermectin is a generic prescription drug, discovered in 1975, developed by Merck and released in 1981. It is used to treat many types of parasite infestations in humans and animals. The researchers who created it were awarded the Nobel Prize for medicine in 2015. It is on the World Health Organisation’s List of Essential Medicines and is approved by the Federal Drug Administration (FDA) as an antiparasitic agent.
It can have very rare serious side effects. By 2020 four billion doses had been administered and 16 deaths are believed to have occurred as a consequence, or one in 250million doses. Although the figures are not directly comparable, the annual increased risk of death for a middle-aged man taking a standard (325 mg) aspirin every day to prevent heart disease and stroke is about one in ten thousand. This is about as risky as driving a car.
Ivermectin is therefore a very safe drug. However, the drug oversight establishment does not think so.
On March 22 this year the European Medicines Agency issued this statement:
‘EMA has reviewed the latest evidence on the use of ivermectin for the prevention and treatment of COVID-19 and concluded that the available data do not support its use for COVID-19 outside well-designed clinical trials.
‘In the EU, ivermectin tablets are approved for treating some parasitic worm infestations while ivermectin skin preparations are approved for treating skin conditions such as rosacea. Ivermectin is also authorised for veterinary use for a wide range of animal species for internal and external parasites.
‘Ivermectin medicines are not authorised for use in COVID-19 in the EU, and EMA has not received any application for such use.’
On May 3 the US Food and Drug Administration (FDA) issued this warning under the heading ‘Why You Should Not Use Ivermectin to Treat or Prevent COVID-19’:
‘There seems to be a growing interest in a drug called ivermectin to treat humans with COVID-19. Ivermectin is often used in the U.S. to treat or prevent parasites in animals. The FDA has received multiple reports of patients who have required medical support and beenhospitalized after self-medicating with ivermectin intended for horses.
‘FDA has not approved ivermectin for use in treating or preventing COVID-19 in humans. Ivermectin tablets are approved at very specific doses for some parasitic worms, and there are topical (on the skin) formulations for head lice and skin conditions like rosacea. Ivermectin is not an anti-viral (a drug for treating viruses).
‘The FDA has not reviewed data to support use of ivermectin in COVID-19 patients to treat or to prevent COVID-19; however, some initial research is underway. Taking a drug for an unapproved use can be very dangerous. This is true of ivermectin, too.’
The lack of official support for trials of the efficacy of ivermectin has meant that the typical number of subjects being tested (the ‘cohort’) is fairly small, usually about a hundred. To overcome this a meta-analysis can be undertaken, when the results of many trials are combined and assessed to determine if a trend can be seen. This has been done, most notably by @CovidAnalysis. A paper most recently updated yesterday surveyed 60 properly conducted studies, most with double-blind testing against placebos, with neither the participants nor the researcher knowing who had been given the drug until the trial was over. This report is a preprint, so it has not been peer-reviewed, but the results are conclusive: 93 per cent of the studies show a positive outcome from the administration of ivermectin, with deaths reduced by over 80 per cent.
So why have what might be called ‘Drug Central’ refused to acknowledge this mammoth body of evidence arising from without their bailiwicks? Perhaps because of human nature again. Here they are obeying another rule of thumb commonly seen when institutions encounter new external factors – ‘not invented here’. Perhaps this business school aphorism is also appropriate: ‘Hell hath no fury like a head-office scorned’.
In any event the virucidal properties of ivermectin and its safety have now been established beyond doubt, and we can expect it to be valuable in this role from henceforth. But unfortunately not, perhaps, against Covid-19.
Featured Video

False Flags and the Dawn of Bioterrorism
or go to
Aletho News Archives – Video-Images
From the Archives
How 1960’s French Nuclear Tests Are Still Claiming Lives in Algeria
Sputnik – 15.02.2018
On February 13, 1960, France carried out its first nuclear test in Algeria’s southern Reggane region. According to official statistics, 17 nuclear tests were carried out in total over the next 6 years. The area remains affected, and local scientists say that radioactive contamination has caused genetic mutations and irreversibly changed the region.
There are no official statistics on the number of victims. The only figures can be found in the records kept by the French representative of the local church, which lists 42,000 victims of nuclear tests. Three years ago, the French Ministry of Defense issued a statement, putting the number at 27,000 people. The victims include French soldiers as well as local Algerians who lived in the surrounding areas. … continue
Blog Roll
 Aletho News
- Using nuclear weapons, the US-Israeli alliance still can’t beat Iran
- Sunset on the Quality of Western Propaganda: Arrival of the Dr Strangelove Moment
- Ukrainian general accused of protecting crime bosses
- US-‘Israel’ alliance faces growing rupture after midterms
- GOP’s Crushing Midterm Loss Could Reshape US Political Landscape – Analyst
- Midterm loss gives Congress power to rein in US war on Iran
- Midterms Were ‘Vote of No Confidence’ in GOP, But Iran Has No Illusions About Democrats – Marandi
- Israeli Soldiers Inadvertently Prove Their Own Genocidal Guilt
- Ukraine arrests woman who exposed Azov battalion’s ‘torture chamber’
- Did Israel lose the midterms?
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago

