
Al Seib / Contributor via Getty Images
A leaked Whitehall document seen by Politico suggests that perspex screens installed to stop the transmission of COVID-19 may actually have increased its spread.
Businesses and schools were told by the government to install the screens as a condition of re-opening after the first lockdown and they were widely used by ‘essential’ shops throughout the entire period.
Politico’s Alex Wickham writes that the perspex screens could be about to be scrapped given new information the government has received on their efficacy.
“Ministers are also being advised that those perspex screens that have appeared in some offices and restaurants are unlikely to have any benefit in terms of preventing transmission,” states the report.
“Problems include them not being positioned correctly, with the possibility that they actually increase the risk of transmission by blocking airflow. Therefore there is clear guidance to ministers that these perspex screens should be scrapped.”
Despite the report, government ministers say there is no plan to change advice on installing the screens in businesses.
What other COVID-19 measures put in place to fight the spread of the virus have been utterly useless or actually made it worse?
A study on the effectiveness of face masks involving 6,000 participants in Denmark found “there was no statistically significant difference between those who wore masks and those who did not when it came to being infected by Covid-19.”
June 16, 2021
Posted by aletho |
Science and Pseudo-Science | Covid-19, UK |
Leave a comment
‘HIV’ and ‘AIDS’ are just as bogus as the ‘novel coronavirus’ and ‘Covid.’ Yet they’re now setting the pace in the vaxx-development race.
This month marks the 40th anniversary of the first report of what was subsequently dubbed ‘acquired immunodeficiency syndrome’ or ‘AIDS.’
Officials like Anthony Fauci are using the occasion to spread the message that vaccines for HIV, which is the virus said to cause AIDS, will soon be rolling out. Forty years of fruitless effort supposedly are suddenly successful thanks to the precedent of the lightening-speed and ‘successful’ development of Covid vaccines.
Fauci said June 4 in an MSNBC interview by Rachel Maddow that because of “the technologies that have now been perfected, particularly the mRNA technology and other vaccine platforms that were perfected and used in Covid-19, I believe strongly we’ll go back and be able to really forward and advance the HIV [vaccine] effort.”
A June 6 Guardian article says that Fauci “holds out hope that the three HIV vaccines in advanced clinical trials will prove at least 50% efficacious, justifying a global roll out. But he now hopes mRNA or other advanced technologies could yield even more powerful HIV vaccines.”
Note that under Fauci, in July 2020 as part of Operation Warp Speed, four major NIAID-funded HIV global clinical-trials networks were retooled into the Covid-19 Prevention Network (COVPN). People in the network help create vaxxes and other ‘treatments’ for both HIV and Covid.
And already by April 14, 2020, mRNA ‘vaccine’ maker Moderna had announced that soon they’ll be conducting small human trials on their experimental jabs against HIV and the flu.
So far, at least 26 different mRNA shots are on the way from Moderna, in addition to their three types of Covid jabs. The shots in development range from two for HIV to one ‘personalized cancer vaccine.’
Among the main funders of Moderna’s mRNA HIV-vaxx development is the Bill & Melinda Gates Foundation. AIDS is a special focus of Gates’s, including through the Global Fund and especially for people in sub-Saharan Africa.
Vaccines are immensely profitable: the new, Covid jabs are topping the all-time charts for medical money-making. Plus vaccine makers have no liability for the illnesses and deaths they cause. Therefore using the name ‘vaccine’ for all ‘treatments,’ no matter what they contain, is a formula for making huge amounts of money with very little downside.
And the potential market for HIV ‘vaccines’ alone is very large. For example, an October 2020 paper in the journal Lancet HIV — on the use of two experimental HIV vaxxes made by Janssen in healthy, HIV-negative people, and funded by among others the Gates Foundation — starts with the sentence, “Current estimates of 37.9 million people living with HIV worldwide and 1.7 million new infections annually, with no cure on the horizon, make development of an effective prophylactic vaccine a global priority.” (The paper’s authors reported very high rates of adverse events to the vaccines, but still assessed the shots as being “generally safe and well-tolerated.”)
All of this is despite the fact that HIV has not been detected by anything other than indirect methods such as antibody, T-cell and polymerase chain reaction (PCR) testing. HIV also has not been clearly shown to cause disease. Nor has it been isolated or rigorously imaged via electron microscopy. Isolation is a necessary step before sequencing – because otherwise the resulting sequences reflect a heterogeneous mix of material rather than pure virus. Details on this are below.
This also holds true for the novel coronavirus.
Phalanxes of officials such as Fauci censor these inconvenient facts. And they keep the public captive, overloaded and off-balance with an avalanche of complex and contradictory jargon, modelling and scientific studies.
The Myth of HIV and of AIDS
Kary Mullis won the Nobel Prize in 1993 for inventing PCR. He died in August 2019. There are many videos of him demolishing Fauci and/or the HIV-AIDS hypothesis. He also discusses this in his autobiography Dancing Naked in the Mind Field.
For example, Mullis said the following in one of his video interviews: “He [Fauci] doesn’t know anything really about anything, and I’d say that to his face. Nothing! … He doesn’t understand electron microscopy, and he doesn’t understand medicine, and he should not be in a position like he’s in…. Tony Fauci does not mind going on television in front of the people [taxpayers] who pay his salary and lie directly into the camera.”
Indeed, falsely claiming to have isolated HIV and imaged it with electron microscopy are key parts of the artifice used by Luc Montagnier and Robert Gallo to assert in 1984 that they’d discovered HIV and that it causes AIDS.
The same applies to the novel coronavirus. For example, one of today’s top electron microscopy experts – Duke University pathology professor Sara Miller — herself failed in an April 2021 paper to prove that an electron-microscopy image shows the novel coronavirus. She simply asserted it’s the virus without giving information on, or even references to, the techniques used to show that it is. (If she had given information, it certainly would have relied on the use of antibodies, because they are the main tool for identification purposes. But as I document in my article The Antibody Deception, antibodies cross-react with many other things and therefore cannot accurately pick out the novel coronavirus.)
Mullis wrote the foreword to the very long but very important book Inventing the AIDS Virus. The book was published in 1996 and is by Peter Duesberg, a University of California, Berkeley, professor of biochemistry, biophysics and structural biology. It details the genesis of the HIV-AIDS myth and is still highly relevant today. (Note that Duesberg believes the virus exists but is harmless because it doesn’t multiply in the body, while Mullis believed the virus doesn’t exist at all.)[Note added June 14 after article posted: Mullis apparently did believe the virus exists. See for example this video, which a friend just emailed me. However, I stand by my assertion that HIV has never been conclusively isolated or imaged. Even Mullis’s statements in that video can be seen as indicating HIV is virtually impossible to conclusively isolate or image.]
Mullis writes this in the forward:
“We [he and Duesberg] have not been able to discover any good reasons why most of the people on earth believe that AIDS is a disease caused by a virus called HIV. There is simply no scientific evidence demonstrating that it is true,” wrote Mullis in that foreword. “… We know that to err is human, but the HIV/AIDS hypothesis is one hell of a mistake.”
In the book, Duesberg documents that one main part of the trajectory toward the creation of the myth started in 1912, with the reorganization of the U.S.’s Public Health Service. Another key part was the creation in 1946 of the predecessor of the current CDC — with its predilection for deeming ‘outbreaks’ to be due to infectious diseases, and then testing, tracking and quarantining people under the premise of stopping the spread.
(Two of many valuable insights by Duesberg are on page 137-138: “The CDC has … continued to exploit public trust by transforming seasonal flus and other minor epidemics into monstrous crises and by manufacturing contagious plagues out of noninfectious medical conditions.” And, “[E]pidemiologists have classically studied clusters of sick people as clues to subtle environmental hazards, not infectious agents. But when public health officials issue ominous warnings about mysterious disease outbreaks, they terrify the public with visions of deadly pandemics.”)
Duesberg also details, on pages 174 to188, the failure of HIV to fulfill Koch’s postulates. And on page 202 he concludes that, “AIDS fails all epidemiological criteria of an infectious disease.”
(I believe the same is true for Covid.)
Duesberg points, in addition, to the reasons ‘experts’ give for why it’s virtually impossible to directly detect the virus. For example, he writes on page 206 that:
“[I]f little or no HIV can be found in the body, scientists propose hidden reservoirs and special routes of infection. If only antibodies against HIV [rather than HIV itself] can be found, researchers call them ‘nonneutralizing’ (or ineffective) antibodies and assert that the virus mutates too fast for the antibodies to keep up…. All these hypotheses are constantly being disproved or shown to be irrelevant, but the reservoir of new evasions is inexhaustible.”
That of course parallels the pranks ‘experts’ are playing on the public with respect to the novel coronavirus and Covid.
There are many other prominent people who have spent decades exposing the HIV-AIDS hoax. They include: activist and journalist John Lauritsen in his many articles and his books including The AIDS War: Propaganda, Profiteering and Genocide from the Medical-Industrial Complex; microbiologist Eleni Papadopulos in, among others, a 2004 paper detailing the fatal flaws in the HIV-AIDS hypothesis, a 1997 interview and an October 2020 interview; journalist Jon Rappoport in dozens of blog posts including his March 8, 2021 one, and in his 1988 book AIDS Inc.; and Duesberg’s colleague David Rasnick in many formats such as a 2009 article they co-authored, and his blog, including this May 2021 post. (Rappoport and Rasnick, among others, also have pointed out the striking parallels in the politics and deception surrounding HIV and AIDS and the novel coronavirus and COVID.)
What Are the Real Causes of ‘AIDS’?
Duesberg makes the strong case that ‘AIDS’ is actually 30 conditions inappropriately lumped into the single category. And he demonstrates that the main causes are: toxicity from AZT and other meds given to people who test positive for HIV (more on this below); toxicity from recreational drugs like nitrite inhalants — AKA ‘poppers’; and overuse of antibiotics.
In countries such as Africa, the causes also include poverty, malnutrition, lack of indoor plumbing and tropical infections.
Lauritsen also details this in his 1993 book The AIDS War.
“‘AIDS’ … is defined entirely in terms of other, old diseases, in conjunction with dubious test results and even more dubious assumptions. Although people are undeniably sick, ‘AIDS’ itself does not really exist; it is a phoney construct,” Lauritsen states on page 180 of the book.
Yet virtually all the funding for the vast HIV/AIDS research-administrative-medical-industrial complex assumes HIV is the cause of ‘AIDS.’
In 1984, just three years after the first report of what later would be dubbed AIDS, Fauci became the head of NIAID.
AIDS made him a star: he’s good at grabbing the spotlight with his gift of glib gab, and under his tenure NIAID ballooned thanks to a huge inflow of AIDS-related funding.
Just three years later, in 1987, the first medication for HIV went on the market: AZT, which is highly toxic.
AZT has killed huge numbers of people, thanks in large part to Fauci pushing the message that it is ‘safe and effective.’
“I would say there were hundreds of thousands of people killed by AZT. And many — perhaps most — of them were perfectly healthy before they were put on the drugs,” Lauritsen told me in a telephone interview from his home in Boston. “They got a positive result on the worthless HIV tests, and then they were told to put time on their side and take AZT. And of course it killed them.”
AZT made a mint for its first manufacturer, Burroughs-Wellcome, and then for its second and current maker, GlaxoSmithKline (which bought Burroughs Wellcome in 1995).
Fauci and other powerful officials have also pushed other deadly drugs, such as Bristol-Myers Squibb’s didanosine (ddI).
Duesberg and Lauritsen detail how the U.S. Food and Drug Administration was pressured into giving ddI fast-track approval in 1991 — despite clear evidence that it is toxic, and that there were no placebo-controlled safety or efficacy studies conducted on it.
Even Wikipedia, which usually censors information that criticizes big pharma, states that about one-quarter of people taking ddI develop peripheral neuropathy. And in 2010 the FDA issued a warning that a serious liver disease can occur in people taking ddI.
Today there are at least 46 FDA-approved drugs for people who have tested positive for HIV, according to this list. (The list includes AZT — but for some reason not ddI, even though it’s apparently still on the market).
The most popular of these meds are for ‘pre-exposure prophylaxis’ (PrEP)(also known as ‘treatment as prevention’ or TasP).
Sound familiar? It’s like the billions of perfectly healthy people who are taking the Covid shots.
Most PrEP is combinations of several drugs, many of which are repurposed, older, HIV meds.
The latter include drugs as tenofovir, lamivudine and emtricitabine. These are a type of drug known as nucleoside analogues (AKA nucleoside inhibitors or nucleoside reverse transcriptase inhibitors). And they have the same, and potentially very dangerous, mechanism of action as AZT and ddI: that is, they stop DNA synthesis from taking place in cells throughout the body.
[Full disclosure: in the mid- to late 1990s as a freelance medical writer I co-wrote marketing materials for HIV drugs such as lamivudine and tenofovir through a Toronto, Ontario, marketing agency called Jeffrey Simbrow Associates. Then later, until the mid-2000s, as a medical journalist I wrote many stories for trade publications about HIV drugs. I somehow was completely unaware of the controversy surrounding these drugs and HIV and AIDS.]
Today tens of millions of healthy people are taking PrEP because they’ve been led to believe this will either prevent infection, or lower their HIV levels to undetectable (the latter goes by the slogan ‘U=U’ for ‘undetectable = untransmissible’). And information is suppressed that many people who have tested positive for HIV but haven’t taken any medication remain healthy for decades.
Over the last year, PreP sales have been sliding somewhat, as has HIV testing. ‘Experts’ are blaming this on the curtailment of usual accessible care during the pandemic. (And they’re also telling scary tales of untreated ‘HIV/AIDS’ potentially interfering with efforts to quash Covid.)
Enter the news about HIV vaxxes being on the horizon — and their potentially huge market.
There are tens of millions of people who have tested positive, and many many more being tested every day.
Plus, most people would prefer an HIV vaxx instead of a daily pill; pills are expensive and inconvenient.
Central Players in the HIV and Novel Coronavirus Capers
Not surprisingly, there are major overlaps between the key figures in the HIV-AIDS and novel coronavirus-COVID agendas. And they’re not just the usual suspects such as Bill Gates.
They include names such as Larry Corey, Myron Cohen and Lindsey Baden.
Corey leads the HIV Vaccine Trials Network, a position he’s held since 1999, and which now is the operational center for the COVID-19 Prevention Network (COVPN – mentioned earlier). He also is co-leading vaccine testing at the COVPN – which started, last summer, with a Phase 3 study of one of Moderna’s mRNA Covid jabs.
Cohen is director of the Institute for Global Health and Infections Diseases, and a prof of medical microbiology, immunology and epidemiology at University of North Carolina in Chapel Hill.
Cohen also is co-principal investigator of the another of the four networks that form COVPN, the HIV Prevention Trials Network (HPTN). (The other two are the Infectious Diseases Clinical Research Consortium and the AIDS Clinical Trials Group.)
They’re testing PrEP drugs and antibodies. The latter includes the AbCellera/Eli Lilly antibody bamlanivumab.
The results of one of those studies, on bamlanivumab for workers and residents in care homes, were announced on Jan. 21 by Lilly via a press release. They were published in the prominent Journal of the American Medical Association on June 3, 2021, with Cohen as the lead author. (In my The Antibody Deception article I described how it’s virtually impossible for bamlanivumab to be an effective treatment for anything.)
Baden is the deputy editor of the New England Journal of Medicine (NEJM), a position he’s had since 2005. And he’s also a long-time associate prof at the Harvard Medical School.
He has been working toward HIV vaxxes since at least 2007
Baden’s pushing both the HIV and Covid agendas forward at warp speed. For example, he’s the first author on the Dec. 30, 2020, NEJM paper that concluded that one of Moderna Covid vaccines has “94.1% efficacy at preventing Covid-19 illness.”
Baden is funded by, among many others, Moderna, the Gates Foundation, Wellcome Trust, Janssen, the Military HIV Research Program and NIAID (see pages 2 and 3 of the disclosure forms for the paper’s authors).
There also are many other ways that the money pipers call Baden’s tune.
For example, since February 2020 Baden has been giving once-weekly audio interviews for NEJM, together with the journal’s editor-in-chief Eric Rubin. The pair use this prominent pulpit to, among other things, endorse mass vaccination for Covid including in minorities, pregnant women and children.
And Baden, Corey and Cohen were among the co-authors of a March 2021 NEJM paper titled, ‘Two randomized trials of neutralizing antibodies to prevent HIV-1 acquisition.’ In other, using antibodies for PrEP.
There are hundreds of other key players in the parallel HIV-COVID play. You can use PubMed to look up the papers and conflicts of interest of prominent scientists in your area who have been among those pushing the Covid agenda.
They include everyone from the infamous Neil Ferguson to one of the two co-chairs of the Canadian COVID-19 Immunity Task Force, Catherine Hankins.
They’re all engaged in the gold rush for bogus ‘vaccines’ and other ‘treatments’ for an array of non-existent or benign conditions.
After obtaining an MSc in molecular biology from the Faculty of Medicine at the University of Calgary, Rosemary Frei became a freelance writer. For the next 22 years she was a medical writer and journalist. She pivoted again in early 2016 to full-time, independent activism and investigative journalism. Her website is RosemaryFrei.ca.
June 16, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular | AIDS, Covid-19, HIV |
Leave a comment
New climate change indicators on the U.S. EPA (Environmental Protection Agency) website are intended to inform science-based decision-making by presenting climate science transparently. But many of the indicators are misleading or deceptive, being based on incomplete evidence or selective data.
A typical example is the indicator for heat waves. This is illustrated in the top panel of the figure below, depicting the EPA’s representation of heat wave frequency in the U.S. from 1961 to 2019. The figure purports to show a steady increase in the occurrence of heat waves, which supposedly tripled from an average of two per year during the 1960s to six per year during the 2010s.
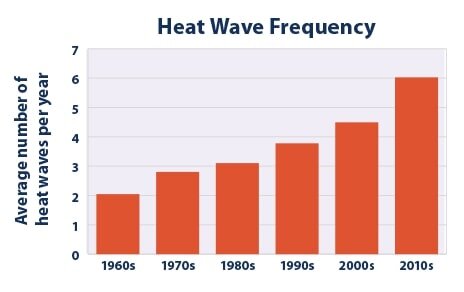
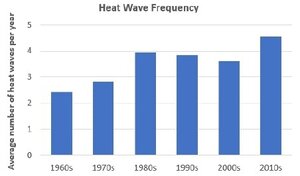
Unfortunately, the chart on the top is highly deceptive in several ways. First, the data is derived from minimum, not maximum, temperatures averaged across 50 American cities. The corresponding chart for maximum temperatures, shown in the bottom panel above, paints a rather different picture – one in which the heat wave frequency less than doubled from 2.5 per year in the 1960s to 4.5 per year in the 2010s, and actually declined from the 1980s to the 2000s.
This maximum-temperature graph revealing a much smaller increase in heat waves than the minimum-temperature graph displayed so boldly on the EPA website is dishonestly hidden away in its technical documentation.
A second deception is that the starting date of 1961 for both graphs is conveniently cherry-picked during a 30-year period of global cooling from 1940 to 1970. That in itself exaggerates the warming effect since then. Starting instead in 1980, after the current bout of global warming had begun, it can be seen that the heat wave frequency based on maximum temperatures (bottom panel) barely increased at all from 1981 to 2019. Similar exaggeration and sleight of hand can be seen in the EPA indicators for heat wave duration, season length and intensity.
A third deception is that the 1961 start date ignores the record U.S. heat of the 1930s, a decade characterized by persistent, searing heat waves across North America, especially in 1934 and 1936. The next figure shows the frequency and magnitude of U.S. heatwaves from 1900 to 2018.
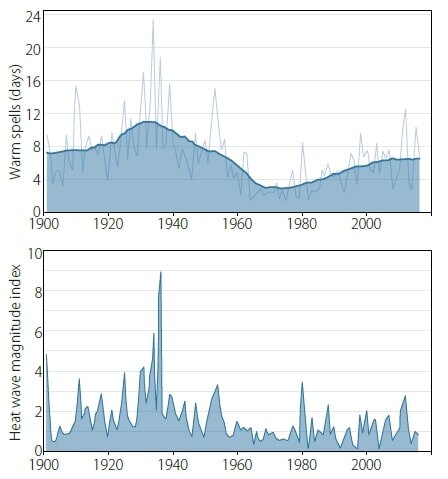
The frequency (top panel) is the annual number of calendar days the maximum temperature exceeded the 90th percentile for 1961–1990 for at least six consecutive days. The EPA’s data is calculated for a period of at least four days, while the heat wave index (lower panel) measures the annual magnitude of all heat waves of at least three days in that year combined.
Despite the differences in definition, it’s abundantly clear that heat waves over the last few decades – the ones publicized by the EPA – pale in comparison to those of the 1930s, and even those of other decades such as the 1910s and 1950s. The peak heat wave index in 1936 is a full three times higher than it was in 2012 and up to nine times higher than in many other years.
The heat wave index shown above actually appears on the same EPA website page as the mimimum-temperature chart. But it’s presented as a tiny Figure 3 that is only 20% as large as the much more prominent Figure 1 showing minimum temperatures. As pointed out recently by another writer, a full-size version of the index chart, from 1895 to 2015, was once featured on the website, before the site was updated this year with the new climate change indicators.
The EPA points out that the 1930s heat waves in North America, which were concentrated in the Great Plains states of the U.S. and southern Canada, were exacerbated by Dust Bowl drought that depleted soil moisture and reduced the moderating effects of evaporation. While this is undoubtedly true, it has been suggested by climate scientists that future droughts in a warming world could result in further record-breaking U.S. heat waves. The EPA has no justification for omitting 1930s heat waves from their data record, or for suppressing the heat wave index chart.
Although the Dust Bowl was unique to the U.S. and Canada, there are locations in other parts of North America and in other countries where substantial heat waves occurred before 1961 as well. In the summer of 1930 two record-setting, back-to-back scorchers, each lasting eight days, afflicted Washington, D.C.; while in 1936, the province of Ontario – also well removed from the Great Plains – experienced 43 degrees Celsius (109 degrees Fahrenheit) heat during the longest, deadliest Canadian heat wave on record. In Europe, France was baked during heat waves in both 1930 and 1947, and many eastern European countries suffered prolonged heat waves in 1946.
What all this means is that the EPA’s heat-wave indicator grossly misrepresents the actual science and defeats its stated goal for the indicators of “informing our understanding of climate change.”
June 15, 2021
Posted by aletho |
Deception, Science and Pseudo-Science | EPA |
Leave a comment
It’s very discouraging to find, with some frequency, people with training in science who are willing to subscribe to rather unscientific statements, proposals, and predictions.
The Smithsonian, for instance.
This article notes with approval that “the World Meteorological Organization released its decadal survey, which included dire predictions: there is a 90 percent chance that one of the next five years will be the hottest on record, and a 40 percent chance that we will experience a year with a global average temperature 2.7 degrees Fahrenheit above pre-industrial levels.”
There is no explanation of what might be the basis for these alarming predictions, nor how the probabilities were arrived at. In poker, you know how many cards are in the deck and how many cards are being dealt. In craps, you know how many spots are on the faces of the die.
The article quotes without comment Arizona State University climate scientist Randall Cerveny who expresses disappointment that “We had had some hopes that, with last year’s COVID scenario, perhaps the lack of travel [and] the lack of industry might act as a little bit of a brake. But what we’re seeing is, frankly, it has not.”
It does not note that during the depression years 1929-1931, when human CO2 production declined 30%, CO2 continued its languid rise, with temperatures continuing to rise till 1941 when they began a slight decline to 1972, again with no change in CO2 rise despite WWII and post-war reconstruction. Thus the “Oncoming Ice Age!” scares in the early 70s (see Time, Newsweek and ScienceNews in the early ’70s). Nor that CO2 change has never preceded any temperature reversal for the last 550 million years. Nor does it note, to supplement the WMO scare text, that humans produce less than 5% of the annual contribution to CO2 in the atmosphere.
It quotes without comment the absurd Paris Accord decision that no temperature increase beyond 2.7F over pre-industrial could be tolerated… ”Otherwise, the planet will face a climate catastrophe.” It does not note that the world has spent half the last 550 million years within a few degrees, plus and minus, of 22C – that’s 72F average vs the current 59F (15C). The dinosaurs basked at 18C, in a wet world.
The choice of 2.7F over preindustrial is imaginatively arbitrary, in light of previous global temperatures in our absence. There has never been a tipping point in the last 550 million years: not at the P-T extinction warming (to at least 28°C), nor, more surprisingly, at the “snowball earth” events when glaciers reached almost to the equator and albedo increased dramatically.
In addition to history, there is theory. The exponential decline in the GHG effect of CO2 has been known since Arrhenius, and the numbers are now correct. The next doubling of CO2 to 800 ppm will increase its GHG effect by less than 2%, in theory.
So there is no justification to propose that CO2 at this time, at these levels, is in control of climate change, nor any justification to assume that we are in charge of CO2.
Climate change is a given, not a problem. Problems have solutions. The fact that “we have to do something about it” doesn’t mean that we can.
CO2 mitigation is a problem, not a solution.
These are not controversial facts. Everyone with scientific interests should know and use them.
June 15, 2021
Posted by aletho |
Fake News, Mainstream Media, Warmongering, Science and Pseudo-Science, Timeless or most popular |
Leave a comment
Since the crisis began in March 2020, there has been a distinct air of medical fascism which has gradually permeated Irish political rhetoric and policy – which has left many conscientious residents shocked.
This dark state of affairs appears to be coming to a head now, as technocrats in Dublin push the totalitarian envelope even further.
Suddenly, after 15 months of running an open-ended crisis narrative, the great and good are now saying, “Now is certainly not the time to be taking risks on travel,” as the government and media operatives begin ramping-up Project Fear once again.
As usual, the state has singled-out the most vulnerable target demographic upon which to leverage its power, and to mete out some of the most outlandish policies ever seen in the western world over the last 150 years, including policies that would even have been beyond the pale for Stalin’s Soviet Union.
Incredibly, after the Irish government pushed some 400,000 of its older citizens to inject the highly controversial, unlicensed experimental gene-based AstraZeneca jab, the government is now banning them from leaving the country – until they have received their second dose.
Irish Independent reports…
More than 400,000 people who are waiting for a second dose of the AstraZeneca Covid-19 vaccine have been told they cannot travel abroad.
he “vaccine bonus” for those who are a month on from their first AstraZeneca jab does not involve foreign travel, the updated advice from the HSE has warned.
People in their 60s, and a significant number of those with underlying conditions, have been left waiting for a second dose of the vaccine, which will take at least eight weeks, but may be even longer for many.
They can avail of the vaccine “bonus”, with one dose after 28 days, allowing certain limited meeting up with others indoors, but “this does not include foreign travel”.
By definition, this can be classed medical fascism – where state and corporations have codified policy in order to coerce and effectively enforce an experimental medical procedure. On paper, this is in direct violation of the Nuremberg Codes which have been recognised for decades as de facto international law. Moreover, citizens are being denied informed consent, which is also a violation of both Irish and European law and contravenes the human rights charter.
This is an incredibly dangerous move by the state, and while it may be done under the now acceptable auspices of fear and general hysteria – it has still been done with no actual scientific evidence to justify it – only often repeated conjecture and increasingly vague claims used to further underpin the ever-evolving self-licking ice cream cone which is the seemingly never-ending “variant” scare.
Intelligent, sober people can now see that the variant scare has been contrived to justify the government’s omnipresent threat of more lockdowns, restrictions and border closures, and above all: to force vaccine compliance.
Meanwhile, technocrats in Brussels are using these artificial travel obstacles created by member states in order to create an artificial demand for a new Vaccine Passport (or ‘COVID credentials’) regime, which they have recently rebranded as a “Digital Wallet” due to pushback against its previous vaccine “Green Pass”:
The EU Digital Certificate, paving the way for travel within the bloc, is due to be operational here from July 19.
The HSE does not specify the same travel restriction for people who received one dose of the other vaccines.
Moreover, government ministers continue to make assertive claims about the alleged “effectiveness” of these unlicensed experimental injections against the newly branded “variants” which are now being deceptively sold to the public as ‘deadly mutations’ of the previously touted ‘novel’ coronavirus:
Public Health England has previously found that one dose of vaccine gives just 33pc protection against the more infectious Delta variant that originated in India.
It said yesterday that two doses of the Pfizer vaccine give 96pc protection while the AstraZeneca gives 92pc.
It comes amid concern at the inevitable rise in the Delta variant, with around 140 cases detected here so far. Another 242 cases of coronavirus were diagnosed yesterday.
How the UK government could make any such claims about the level of “protection” any COVID vaccine actually provides against the alleged ‘variants’ may be more a feat of political science and propaganda than actual clinical science, because the source of these sweeping claims emanates from the pharmaceutical manufacturers themselves. Does anyone seriously doubt by now that these private interests have captured European governments’ regulatory and political institutions?
Still, Irish ‘science’ experts appear to be confused as to how to play the new variant-vaccine narrative. Luke O’Neill, professor of biochemistry at Trinity College, spoke with the Irish Independent, claims to know how the rebranded ‘Delta variant’ virus behaves, while at the same time admitting that, ‘there doesn’t seem to be a huge amount it around’. He then defers to the UK experts and their own spurious Delta claims, whilst advising hapless Irish citizens who have had one dose of the experimental AstraZeneca injection to ‘take care’. By now, this contortionist feat of ‘public health’ gymnastics has become commonplace:
“We know from the UK that one shot of AstraZeneca is not giving the same level of protection from the Delta variant as two shots, so I would think those who have had one shot of AstraZeneca will have to take some precautions until they’ve had their second shot,” he said.
“We’re lucky in that there doesn’t seem to be a huge amount of the Delta variant around, at least currently. The goal has to be to get the second shot into the vulnerable people – including the over-60s – as quickly as possible.”
Of course there is no mention by any government officials about the fact that this problematic AstraZeneca jab has already been halted in multiple countries (and it hasn’t been allowed to be released in the United States either) due to confirmed risks of maiming or death due to fatal blood clotting – a fact now accepted by experts worldwide. This is now accepted as a clear and present danger for any members of the public taking part in this unprecedented human experiment.
In Europe, health officials have stated that countries should also avoid giving the AstraZeneca vaccines to people over 60, as said by the head of the EU drug regulator’s COVID-19 task force on Sunday. But for some strange reason, no Irish politician or mainstream media outlets want to talk about this serious problem.
All of this comes amid the backdrop of British PM Boris Johnson announcing the delaying of an end to the UK government’s indefinite ‘state of emergency’ and lingering lockdown policies. The government claims this is because of fears of the alleged Indian Variant (recently rebranded to ‘Delta Variant’), while claiming that somehow COVID-19 “cases” (not actual clinical cases, but PCR and lateral flow ‘positive’ tests) are now at a three-month high. Britain was scheduled to lift all remaining restrictions on June 21st, but now says that it needs more time to vaccinate more of its population – as extremist voices in political and media circles continue to blame these alleged new ‘outbreaks’ of COVID-19 on ‘the unvaccinated.’
Based purely on its words and polices, Ireland’s ruling Fine Gael-Fianna Fail regime (from the onset, ‘opposition’ party Sinn Fein has also supported these same draconian policies) now finds itself as the vanguard of a new European Soviet.
Needless to say, this level of medical tyranny and mass-hysteria is unprecedented.
The real question remains: will the public at large and conscientious members of the press and government, come to their senses and wake up before the damage to democracy and freedom becomes irreparable?
June 15, 2021
Posted by aletho |
Civil Liberties, Science and Pseudo-Science | European Union |
Leave a comment
Among its top results today under the search term “climate change,” Google News is highlighting articles claiming new research shows global warming will cause stronger Indian and South Asian monsoons and rainfall, which will wreak climate havoc in future decades. Yet, just a few years ago climate alarmists and their media allies claimed global warming will cause weakening monsoons and weakening rainfall, which will wreak climate havoc. The alarmists’ embarrassing self-contradiction begs the question – precisely what among the contradictory alarmist climate narratives is the “settled science”?
On Monday, India Today published an article titled, “Climate change to worsen Indian monsoon, global warming sets stage for dangerous rains: Study.” The article claims, “The Indian monsoon is likely to get much more dangerous and wetter as global warming alters the system, new research says.”
Reporting on the same study, The Indian Express published an article today titled, “A million years of data confirms: Monsoons are likely to get worse.” The article claims, “Global warming is likely to make India’s monsoon season wetter and more dangerous, new research suggests.”
Both articles are prominently highlighted today by Google News.
Just last year, however, the Hindustan Times reported that a newly published peer-reviewed study showed that global warming will weaken monsoons and reduce monsoon rainfall.
Ominously, the Times asserted, “Monsoon rains is the main water source for agriculture in half of India with irrigation facilities being limited.”
“There is clear evidence that warming of sea surface temperatures have reduced intensity of monsoon rains in several places in India, especially the north-east, where the dip in average annual rainfall is 6-8% since 1980s,” the Times quoted K.J. Ramesh, a former director of the India Meteorological Department.
The Hindustan Times article is merely one of many articles and studies that have claimed global warming will weaken monsoons and regional rainfall. For example, in a 2015 article, the climate activist group India Climate Dialogue asserted researchers found in a peer-reviewed study that “the monsoon is weakening, at least since 1990, as researchers have now proved.”
According to India Climate Dialogue, the researchers “found that there was a 10-20% decrease in the mean rainfall in the Indian subcontinent. The monsoon was decreasing over central South Asia – from south of Pakistan through India to Bangladesh.”
“The decline is crucial because in these regions agriculture is still largely rain-fed. The South Asian monsoon brings sustenance to around two billion people,” India Climate Dialogue warned.
So, which is it? Does global warming strengthen monsoons and cause more rainfall, which we are told is bad? Or does global warming weaken monsoons and cause less rainfall, which we are told is bad? Or, just maybe – and as concluded by scientists in a recent peer-reviewed study, modest warming has little impact on monsoons, though that would be quite inconvenient for climate alarmists.
Alarmists, get your propaganda – er, stories – straight and then get back to us with your “settled science.”
June 14, 2021
Posted by aletho |
Science and Pseudo-Science |
Leave a comment
There was no credibility to asymptomatic spread in COVID-19 as a key driver of the pandemic nor even as a driver of minimal infection. We knew early on that this was rare, if at all an issue, in the transmission of COVID virus. Yet this falsehood was propagated by the medical media cartel and Task Forces globally despite having no evidence that it was credible. The US Pandemic Task Force propagated this falsehood to the extent that it was a major driver of the pandemic and used it to shutter the economy and lives. We have looked at the evidence gathered across the last 15 to 16 months and can safely say this was a false narrative that hurt the US immensely. This was such a significant aspect of the pandemic policy decisions, that it could not be based on supposition, speculation, or assumptions. It could not be based on whimsy. I am afraid however, that it was, and this had catastrophic consequences. There was no strong data or any evidence to underpin this and even if this was assumed for several weeks, and even if we took a more cautious approach, we used this false narrative in place to keep draconian and punitive lockdown restrictions in place for too long that had no basis. Lives were lost as a result! For me to buy this, I need to see the evidence and data and there is none! The reality is that there is no verifiable evidence that persons have developed COVID-19 based on asymptomatic spread, evidence that is credible. You must torture the data or infections to find one and still, it is plagued with the very questionable RT-PCR results.
You just cannot discuss this asymptomatic issue without factoring in the very flawed RT-PCR test with its 97% false positives at cycle counts of 35 and above. This RT-PCR disastrous test cannot be omitted for it was part of the ‘asymptomatic’ deception. I cannot be generous in my language anymore. This was not a falsehood; it was meant to deceive!
As such, we are about to debunk ‘asymptomatic spread’ fully on the heels of the catastrophic masking, lockdowns, and school closure polices that visited crushing harms on society. That the US Pandemic Task Force and these absurd, illogical, irrational, unscientific medical experts could use this falsehood and shut the society down and cost so much destruction is a scandal, shameful, and unforgiveable. There was no basis to the ‘asymptomatic spread’ and the falsehood should have been stopped soon after it became clear that this was misleading and had no basis. It cost thousands of lives! More lives lost and instead of protecting the vulnerable, they allowed them to die! Our precious elderly.
They did not try to and failed to protect public health, all these crazy lockdown insane lunatics! That’s what they are, lunatics! These bureaucrats and technocrats, this ruling elite. Flat wrong on everything COVID, yet run around extolling each other, patting each other on the back. For what? The destruction they caused? We begged them to secure the elderly and high-risk strongly but they did not and did not stop the lockdowns. They pretended there were no harms to their lockdowns. It was deliberate, a perverse cruelty on populations. Just look at the declining health due to the isolation from the lockdowns (the mental health costs, the dementia), the inactivity, the loss of education due to school closures, lost medical care, loss of jobs/employment, and income. “Some of these costs, sadly, remain ahead of us, including deaths from delays in cancer screening and treatment, rising opioid overdose, and harms to the life expectancy of today’s children due to lost schooling” (Collateral Global). Alarmingly, we see how COVID wreaks havoc differentially due to baseline risks that are often exaggerated in the underprivileged, but also in the underprivileged in terms of the harms and effects of the lockdowns. For example, “while breast cancer screening in Washington state fell by 50% for women overall, the drop was even more precipitous among minorities”.
Before we lay bare this ‘asymptomatic’ fraud, let us show just how duplicitous these public health agencies can be and how many lies they (and their leaders) spew in an attempt to deceive and confuse the public. In this case to drive fear in parents so as to push them to vaccinate their children. On Friday, the CDC put out a statement (based on their June 11th 2021 MMWR report) that there is a troubling rise in teens being hospitalized for COVID-19. The first fact that jumps out at us is that there were 0 (zero) deaths. CDC stated that adolescent hospitalization rates increased during March and April 2021 after decreases in January and February 2021. This message went viral in the media 24/7. This misinformation and clear effort to lie to the public was couched as ‘troubling rise’. But the lie was that there was a rise in March and April but then a decrease in May back to the level it was at the close of February 2021.
The CDC and its Director Walensky had clear knowledge that the hospitalization rate had decreased but they cherry picked a portion of the graph and data (the upside of the graph) and presented that without the downside portion that shows the decline. What hubris and deceit by Walensky! For she knew she was cherry-picking the data because across all age-groups, hospitalizations had declined during the prior 6 to 8 weeks. She knew this. “Allen says the latest data from May showed that hospitalization rates declined to 0.6 on May 29”. The real atrocity in this reporting by the CDC is that they did not include the data from May 2021. This was a pure effort to mislead the public because the same data used in the report showed a significant decline in the month following the slight increase”. So, the CDC took data that showed an increase in April 2021 and now reports it in June as if the May data of the clear decline does not exist. Just the April data and also, why is it now being reported? How incredibly duplicitous and such arrogance to think the American people are that stupid that they cannot see the decline in May?
Dr. Walensky was actually mis-reporting (deliberately) CDC’s own data. Why? Is this the first time a CDC MMWR report was basically junk pseudo-science? Based on falsehoods? This MMWR report was based on a population-based surveillance system of laboratory-confirmed COVID-19–associated hospitalizations in 99 counties across 14 states, covering approximately 10% of the U.S. population. Horowitz of Blazemedia was beside himself as he discussed this duplicity by the CDC and rightly so. Dr. Walensky stated she was para ‘deeply concerned by the rise’. Yet she knew she was being deceitful, in plain view, understanding that the media cartel would gobble the erroneous tripe up and the public would be too lazy to do the reading just a bit further down in the MMWR to understand the mis-information. “It turns out they picked arbitrary start and end points-an old trick they’ve used with mask studies”. Or is it that Dr. Walensky cannot read the science or understand the data or graphs? Or those reporting to her? They (Dr. Walensky) made this type of deceitful error and omission when they reported and misled on the risk of outdoors transmission (< 1% but claiming it is more like 10%), among many others. Same issues with the summer camp rules and spread after vaccination, with flips and flops between Walensky and Fauci. Someone was or is lying, who?
Makary of Johns Hopkins stated para “that the CDC did not report the key issues in that report. No child died, and the CDC should have said this. This is the great news! The hospitalization rate was lower for COVID than it was for influenza. The CDC should have said this also as the headline. What about the heart swelling complications on teens due to the vaccine… one of the failures of the CDC is their ignoring of natural immunity and this insane rush to mass vaccinate people already immune… we are seeing another set of talking points on the Delta variant scare”.
CDC knew the number was coming down for months but misled in their report when they knew it was 20 hospitalizations per day of about 25 million teens, so a rate of approximately 0.00008%. This was to drive panic about a troubling rise in teen hospitalizations and the very small number was going down, and not up. They pick only one piece of data and this was terrible so as to exploit the fears of parents. This was to drive vaccinations. How low has the CDC fallen and how come they have absolutely no common sense! We set the table for this op-ed with that falsehood by the CDC on rising teen hospitalizations. This is how the last 16 months has been with CDC’s reporting. Late and false! Always one year behind the science. Always misleading. Politicized.
Back to the ‘asymptomatic spread’. This duplicitous ‘asymptomatic’ assertion hobbled and basically doomed the pandemic response from the start, for all of the societal shutdowns and school closures revolved around this falsehood. Dr. Anthony Fauci can be credited with perhaps the greatest falsehood to the American population and the then President Trump. He even has still carried this misleading and duplicitous narrative on asymptomatic spread into current [proclaimed] President Biden’s administration.
Fauci stated the following as he advocated and moved to shut society down: “historically people need to realize that even if there is some asymptomatic transmission, in all history of respiratory viruses of any type, asymptomatic transmission has never been the driver of outbreaks. The driver of outbreaks is always a symptomatic person. Even if there is a rare asymptomatic person that might transmit, an epidemic is not driven by asymptomatic carriers”. This clear statement by Fauci is really the [last] nail devastating his handling of this pandemic. What a disaster he has been and how many thousands of lives he has cost with his statements that have all turned out to be wrong. Recently uncovered e-mails show that Fauci stated that “most transmissions” of virus “occur from someone who is symptomatic” and “not asymptomatic”. But Fauci publicly stated at the Task Force podium that asymptomatic spread is “not rare” but is in fact common and why the nation had to be shut down.
I am so ashamed to be a scientist today and really do not wish to belong in this perverse group of ‘fallen’ nonsensical, illogical, irrational, and specious academics. They are (have been) absurd and actually very harmful by the policy positions they advocated. I have bolded and underlined the critical words by Fauci for the reader as these stand out. Fauci was not supposing here as to asymptomatic spread, he was not speculating, he was declarative and definitive. He was firm! Does this make any sense though given what Fauci then did to society, after making this type of declaration? They did the opposite. They repeatedly came to the podium and misled the nation for they repeatedly told us that due to asymptomatic spread, we would have to wear masks, and socially distance, and close schools, and shut everything down.
These US Task Force experts and the so called ‘medical experts’ in the media knew it. They knew this was false, as there was no science to back this up. None. They knew they were misleading the public and were openly lying, while holding opposing positions behind the scenes. Dr. Fauci’s recent e-mail on asymptomatic spread being no issue and his public Task Force discussions on this early in the pandemic underscore how much deceit and duplicity were in his language to the American people. These people conspired and sold the nation(s) a lie, and in fact, many lies around COVID-19. Lies that cost lives of business owners who lost businesses, workers who lost jobs, and adults and children who lost hope and killed themselves. Not from COVID, but from the lockdowns and the crushing harms from them.
What also hobbled and irreparably damaged the US’s response out of the gate was the devastating lie that we were all at equal risk of severe illness and death if infected. This was a flat lie that has Johnny still today at 20 years old, and in perfect health cowering under his bed thinking he is at the same risk as granny at 85 who has 3 serious grave underlying medical conditions. These medical experts would come to the podium daily and make statements and demands and had no data or evidence to back it up. No credible data, and no media, no one asked them for any. We grew to know that they were empty suits, especially Fauci, just baseless statements but they cost many, many lives, tragically. They caused much suffering and the blame rests with them, the Task Force, for the President implemented their policies, not his policies. He got guidance and recommendations from them. It was their lockdowns, it was their school closures, it was their social distancing, it was their mask mandates.
We knew very early on that COVID was amenable to risk stratification and that your baseline risk was most prognostic for mortality, age and obesity being the principle ones along with renal disease and diabetes as well as heart disease. We knew this. We knew early on that a more focused ‘targeted’ approach was needed and not a ‘one-size-fits-all’ approach that was devastating. Like how we knew that recurrent infection (re-infection) was not real and also a lie. Are we sure that recurrent or re-infection is not credible? Well, you judge for yourself. We have looked at the published evidence and can conclude based on the existing body of evidence, that reinfections are very rare, if at all, and based on typically one or two instances with questionable confirmation of an actual case of re-infection e.g. often easily explained by flawed PCR testing etc. (references 1, 2, 3, 4, 5, 6, 7, 8, 9, 10, 11, 12, 13, 14, 15, 16, 17, 18, 19, 20, 21, 22, 23). Dr. Marty Makary of Johns Hopkins wrote “reinfection is extremely rare and even when it does happen, the symptoms are very rare or [those individuals] are asymptomatic”. Importantly, the World Health Organization (WHO) has recently (May 10th 2021 Scientific brief, WHO/2019-nCoV/Sci_Brief/Natural_immunity/2021.1) alluded to what has been clear for many months (one year now), which is that people are very rarely re-infected. The WHO was very late but better late than never.
Like how we knew that the RT-PCR test was near 100% false positive and a flawed test as a diagnostic test and was damaging lives with the erroneous quarantines and closures when a positive test emerged. We knew that what mattered most was the number of hospitalizations, ICU bed use, and deaths, not the infections. An infection did not mean one was a ‘case’ of disease. And likely a false positive. We knew that a cycle count threshold (Ct) of 24 was the limit and everything above this was a PCR test that was likely false positive, picking up viral dust, fragments, old coronavirus, old recovered infection etc. We knew the CDC had set the Ct at 40 which contributed to the hundreds of thousands and millions of positive cases that were not positive and schools were closed and people quarantined for no reason. We knew that children were at near zero risk of acquiring the infection, spreading it, or getting ill from it, yet continued on frightening parents. The CDC, the teachers’ unions, and the television medical experts have spent the last 15 to 16 months lying and scaring parents needlessly and have been lying openly on risk to children. How else do I state it? They were delivering falsehoods and misleading facts to the public and these are flat lies.
Like how we knew that you do not vaccinate someone who has recovered from COVID-19 as they now have robust, durable, life-long immunity that is far more long-lasting, durable, robust, and complete (sterilizing) than any conferred by a vaccine immunity that confers only narrow ‘spike-specific’ immunity with only the spike epitopes for the immune system to look at, and not the surface of the virus and all the viral epitopes that our natural immunity will consider.
Like how we knew you never ever vaccinate during a pandemic for this drives the emergence of variants yet they did it anyway.
Like we knew that the variants will blow past the narrow vaccine induced immunity and principally the spike that you are injecting with today is long gone. What exists out there now is way different than the initial strain due to mutations on the spike.
Like how we knew that T-cell immunity was out there and represented a large portion of persons who were not candidates for vaccine and were already strongly immune to COVID e.g. had prior infection with other coronaviruses and common cold coronaviruses that confer ‘cross-protection’ cellular immunity via T-cell immunity etc. (Weiskopf , Grifoni, Le Bert, Mateus, Tavukcuoglu, Cassaniti, Dykema, Echeverría, Bonifacius, Nelde, Ansari, Ma, Lineburg, Borena) (references 1, 2, 3, 4, 5, 6, 7, 8, 9, 10, 11, 12, 13, 14). You judge for yourself if this makes sense.
Like how we knew that early outpatient treatment (references 1, 2, 3, 4) was very successful in reducing the risk of hospitalization and death (McCullough, Risch, Zelenko, Tenenbaum, Kory, Smith, Bernstein, Fareed, Ladapo etc.) and that you do not give successful anti-virals late in the disease course for they will not work.
Like how we knew the research community was conducting studies ‘designed to fail’ to show that the anti-virals did not work. They were deceiving the public.
Like how we know that using a vaccine that has not undergone the right and proper safety testing and duration of testing, will result in adverse effects and deaths, as we are now seeing (CDC’s very own VAERS database). Anyone who says, no matter their position in government or any medical expert, that it is safe, is lying to you for they did not do the requisite long-term safety assessment in their studies. They are flat lying and this is dangerous and reckless for it is costing lives. And now they are coming for our children! We pray that the FDA staves them off, as the principle regulator. Our hope rests there.
Like how we knew that the ‘ZERO COVID’ view was ridiculous and impossible and not attainable, and was devastating to our societies. There is no way we could eliminate every infection/case as COVID is now endemic and all around us. ZERO was never possible and we knew it and an absurd intention and all it does is destroy the society by locking down to attain ZERO, you force the pathogen to mutate more infectiously and you will forever be going in circles. And you will have a destroyed society to emerge to. We knew this and particularly that we would likely have to learn to live with it as we do with seasonable influenza and common cold coronaviruses. We have never been able to get rid of every infection/case and the same here. But somehow the Task Force experts did not know this.
Like how we knew all that was needed in this pandemic was calm, some sensible leadership, no politicization, and simple enhanced hand-washing and isolation of only the symptomatic ill/sick persons. No isolation of asymptomatic persons, none. None in their homes or at the borders. We knew this. We knew all we needed to do was give early drug treatment and protect the elderly strongly and allow society to move on unfettered. We knew that population immunity would emerge, as we had no reason to think COVID operated any differently than other viruses etc. as to population immunity.
We also knew early on that the blue and cloth face masks were ineffective and utterly dangerous as used, with no clear benefit, and that mask mandates were a failure, all of them! We knew this. We also knew masks were actually dangerous and, for children, so much so as to impact their social and emotional health and well-being. But we pretended and now masks are part of the daily wardrobe while we knew the medical harms that were accruing and being reported from mask use. We knew the social distance rule of 6 feet was made up, not based on credible science. Same as the 3 feet in school, courtesy of CDC. We know that mass testing of asymptomatic persons was nonsensical and dangerous, adding no benefit. Same as contact tracing etc. once the pathogen breached your shores. We knew this. We knew all of the lockdown measures would hollow out our societies and all of the steps taken, and that handwashing and isolation of ill persons were all that was needed. We knew that we had early outpatient therapeutics that were very effective in reducing hospitalization and death, but failed to use them.
What did we know about lockdowns and school closures and masks? What evidence accumulated and very early? Well, you judge for yourself. We found out clearly about the catastrophic harms (consequences) and failures of lockdowns (references 1, 2, 3, 4, 5, 6, 7, 8, 9, 10, 11, 12, 13, 14, 15, 16, 17, 18, 19, 20, 21, 22, 23, 24, 25, 26, 27, 28, 29, 30, 31, 32, 33, 34, 35, 36, 37, 38, 39, 40, 41, 42, 43, 44, 45, 46, 47, 48, 49, 50, 51, 52, 53, 54, 55, 56, 57, 58) and school closures (references 1, 2, 3, 4, 5, 6, 7, 8, 9, 10, 11, 12, 13, 14, 15, 16, 17, 18, 19, 20, 21, 22, 23, 24, 25, 26, 27, 28, 29, 30, 31, 32, 33, 34, 35, 36, 37, 38, 39, 40, 41, 42, 43, 44, 45, 46, 47, 48, 49, 50, 51, 52, 53, 54, 55, 56).
We even knew of the catastrophic harms due to mask use (references 1, 2, 3, 4, 5, 6, 7, 8, 9, 10, 11, 12, 13, 14, 15, 16, 17, 18, 19, 20, 21, 22, 23, 24).
We also knew of the ineffectiveness of masks (references 1, 2, 3, 4, 5, 6, 7, 8, 9, 10, 11, 12, 13, 14, 15, 16, 17, 18, 19, 20, 21, 22, 23, 24, 25, 26, 27, 28, 29, 30, 31, 32, 33, 34, 35) and knew of the failure of mask mandates (references 1, 2, 3, 4, 5, 6,7, 8). All of this we knew early on and evidence kept accumulating. But the inept medical experts kept hardening the lockdowns and punishing the population needlessly. And lives were lost!
We quickly grew to know that every single mitigation step like lockdowns and school closures was a catastrophic failure and was harming the people, especially crushing harms on women and children, and particularly the poorer women and children (children of color). We knew! We knew that none, not one of the bureaucrats and technocrats and ‘caffe latte’ drinking ‘lap-top’ class elitist academics and scientists and Task Force advisors who called for and pushed the lockdowns and school closures would not suffer the burden like the poorer in society. Not one day did they miss a salary or mortgage or rent payment. They were ‘safe’ and it is quite easy for you to extoll and exact a burden on others once you are not subject to it. It became like a game, these lockdowns, indeed, it becomes a game. We knew we shifted the burden onto the poorer in society. But we did not care, we had uber, lap-tops, gardens to tend to, walks to take, naps to catch up on, Amazon to order from, and secured jobs that allowed us to ‘remote’ exist. The poorer had no such facility. But we did not care. We had pods, tutors, internet, lap-tops and the like for our kids. We did not care!
Yes, we knew all of this but were bamboozled and confused by the idiotic and absurd, specious statements by medical experts who for the life of me have been flat wrong on most everything COVID. Case in point, Dr. Fauci. Flat wrong. Makes no sense. But put a pin in that for a moment. Let me focus on asymptomatic spread of COVID virus, this being the core thesis of this op-ed.
What do we know as of today and knew in the spring of 2020 and certainly in the fall of 2020? What does the science say, the same science that these television medical experts and nonsensical, illogical, irrational, and uninformed Task Force and medical advisors failed to take into account due to their academic sloppiness and sheer politicization. They exhibited a depth of cognitive dissonance to anything that disagreed with their absurdities that they spewed at us daily, to a public who yearned for just honesty and the facts for their informed decision-making. They seem unable to read the science, or to understand the science, or ‘get’ the science, and are clearly blinded to the science.
The fact is that if you are having no symptoms, or if they are very mild, then this significantly reduces spread and actually, with no symptoms, there is no spread. This is where the media and the inept medical experts have confused the public. No one is arguing that you cannot be asymptomatic. Of course you can. We are arguing if you are asymptomatic, the mere fact you have no symptoms means you are not spreading the virus. This works for all pathogens so why is it different for SARS-CoV-2? “Searching for people who are asymptomatic yet infectious is like searching for needles that appear and reappear transiently in haystacks, particularly when rates are falling”. We knew very early on that asymptomatic transmission was not a driver of COVID. This is not only my contention.
We are being emphatic in saying there is no evidence of asymptomatic spread. If there is, please provide us the evidence. Yet we had these incompetent medical experts on television talking and speculating about asymptomatic spread, supposing about it, yet giving us no evidence about it. We also recognize that one must be careful not to claim ‘zero’ as the evidence changes daily and rapidly and absence of documented evidence is also not a reason. It may just have not been studied yet or documented optimally. But we are confident enough based on the existing literature to also agree that ‘it is a dangerous assumption to believe that there is persuasive, scientific evidence of asymptomatic transmission’.
The basis for the societal lockdowns was that 40% to 50% of persons infected with SARS-CoV-2 could potentially spread it due to being asymptomatic. “But fears that the virus may be spread to a significant degree by asymptomatic carriers soon led government leaders to issue broad and lengthy stay-at-home orders and mask mandates out of concerns that anyone could be a silent spreader”. However, the evidence in support of common asymptomatic spread remains largely non-existent and we argue, was overstated and potentially was made with no basis. We actually say that these Task Force members lied to the nation! We argue it was made to drive fear and compliance but was never credible. And just consider the harms from nearly one and a half years of testing and closures for a phenomenon that is not credible. Look at the financial costs and lives lost.
We want to focus on evidence to make our case, that we think validates our hypothesis that asymptomatic spread was a falsehood. We want to debunk it here and we argue that the study findings we share here can be extrapolated fully to examples of no asymptomatic (or very limited/rare) transmission. You judge for yourself.
A high-quality review study by Madewell published in JAMA sought to estimate the secondary attack rate of SARS-CoV-2 in households and determine factors that modify this parameter. In addition, researchers sought to estimate the proportion of households with index cases that had any secondary transmission, and also compared the SARS-CoV-2 household secondary attack rate with that of other severe viruses and with that to close contacts for studies that reported the secondary attack rate for both close and household contacts. The study was a meta-analysis of 54 studies with 77 758 participants. Secondary attack rates represented the spread to additional persons and researchers found a 25-fold increased risk within households between symptomatic positive infected index persons versus asymptomatic infected index persons. “Household secondary attack rates were increased from symptomatic index cases (18.0%; 95% CI, 14.2%-22.1%) than from asymptomatic index cases (0.7%; 95% CI, 0%-4.9%)”. This study showed just how rare asymptomatic spread was within a confined household environment. “The real impact of asymptomatic transmission is likely to be even smaller than this figure because the study combines asymptomatic and pre-symptomatic individuals”.
A study published in Nature found no instances of asymptomatic spread from positive asymptomatic cases among all 1,174 close contacts of the cases, based on a base sample of 10 million persons. AIER’s Zucker responded this way “The conclusion is not that asymptomatic spread is rare or that the science is uncertain. The study revealed something that hardly ever happens in these kinds of studies. There was not one documented case. Forget rare. Forget even Fauci’s previous suggestion that asymptomatic transmission exists but not does drive the spread. Replace all that with: never. At least not in this study for 10,000,000”.
One study in May 2020 examined the 455 contacts of one asymptomatic person. Researchers found that “all CT images showed no sign of COVID-19 infection. No severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) infections was detected in 455 contacts by nucleic acid test”.
The World Health Organization (WHO) also made this claim that asymptomatic spread/transmission is rare. This issue of asymptomatic spread is the key issue being used to force vaccination in children. The science, however, remains contrary to this proposed policy mandate.
Additionally, a high-quality robust study in the French Alps examined the spread of Covid-19 virus via a cluster of Covid-19. They followed one infected child who visited three different schools and interacted with other children, teachers, and various adults. They reported no instance of secondary transmission despite close interactions. These data have been available to the CDC and other health experts for over a year, and while one has to tease out the concept of no asymptomatic spread though I argue it is an easy argument to make, it clearly shows that children do not spread the virus.
Ludvigsson published a seminal paper in the New England Journal of Medicine on Covid-19 among children 1 to 16 years of age and their teachers in Sweden. From the nearly 2 million children that were followed in school in Sweden, it was reported that with no mask mandates, there were zero deaths from Covid and a few instances of transmission and minimal hospitalization. We include this study for it is seminal in showing that masks were never needed and children do not spread the virus or get sick or die from it. But importantly, if asymptomatic spread was so vast, and there were 2 million children, would there not be much more elevated numbers of infection reported?
A recent June 10th 2021 op-ed sheds more confirmatory light that asymptomatic spread was more a myth that a reality. Ballan and Tindall wrote “People presenting with symptoms of Covid-19 are almost exclusively responsible for transmitting SARS-CoV-2… serious infection usually results from frequent exposure to high doses of SARS-CoV-2, such as health care workers caring for sick Covid-19 patients in hospitals or nursing homes and people living in the same household.
A person showing no symptoms of Covid-19 may test positive for SARS-CoV-2 on a PCR test, which doesn’t necessarily mean that they are infectious. They explain further that the myth was driven by a single case report of an asymptomatic woman from China who had spread the virus to approximately 16 contacts in Germany. “Later reports showed that, at the time of contact, this woman was taking medication for flu-like symptoms, invalidating the evidence provided for the theory of asymptomatic transmission”.
Ballan and Tindall further explain that “a person showing no symptoms of Covid-19 may test positive for SARS-CoV-2 on a PCR test, which doesn’t necessarily mean that they are infectious. There are four ways in which this can happen: i) the test may give a false positive result due to several faults in the testing process or in the test itself (the person is not infected), ii) the person may have recovered from Covid-19 in the last three months (the person is not currently infected but dead debris of the virus are being picked up by the test), the person may be pre-symptomatic, i.e, the person is infected but still in the early stages of the disease and has not yet developed symptoms, and iv) the person may be asymptomatic, i.e. the person is infected but has pre-existing immunity and will never develop symptoms”.
In asymptomatic individuals, the viral load is typically very low and the infectious period is also short in duration. They may still exhale virus particles, which another person may encounter. However, the overall likelihood of transmitting the disease to others is negligible. Thus, asymptomatic cases are not the major drivers of epidemics.
Perhaps the clearest statement and we argue the most definitive one came from Dr Anthony Fauci of the US National Institute of Allergy and Infectious Diseases who stated in March 2020 (we outlined in more detail above): ‘In all the history of respiratory-borne viruses of any type, asymptomatic transmission has never been the driver of outbreaks. The driver of outbreaks is always a symptomatic person”. Fauci says clearly the driver of transmission is ‘always’ a symptomatic person. Fauci went on to dispute his own declaration by his admonitions on subsequent Task Force podium speech that asymptomatic spread was very serious and a key driver, and thus why we must close schools, wear masks, and lock down the society. We found out how devastatingly wrong that was as we lost businesses and lives, including of our children due to the lockdowns/closures.
Dr Clare Craig, a pathologist, and her colleague Dr Jonathan Engler have examined the research evidence behind the claim that Covid-19 can be transmitted by asymptomatic individuals. They wrote “harmful lockdown policies and mass testing have been justified on the assumption that asymptomatic transmission is a genuine risk. Given the harmful collateral effects of such policies, the precautionary principle should result in a very high evidential bar for asymptomatic transmission being set. However, the only word which can be used to describe the quality of evidence for this is woeful. A handful of questionable instances of spread have been massively amplified in the medical literature by repeatedly including them in meta-analyses that continue to be published, recycling the same evidence base.”
It is important to carefully distinguish purely asymptomatic (individuals who never develop any symptoms) from pre-symptomatic transmission (where individuals do eventually develop symptoms). To the extent that the latter phenomenon, which has in fact happened only very rarely, is deemed worthy of public health action, appropriate strategies to manage it (in the absence of significant asymptomatic transmission) would be entirely different and much less disruptive than those actually adopted.
We state emphatically that the concept of ‘asymptomatic spread’ of COVID virus was devised to frighten the population into compliance and that it was not central to this pandemic as we were told. Evidence to support its existence remains lacking and absent. We close by offering our continued beliefs and thus opinion on how this pandemic should have been handled from the start. We would have as a basic, the strong double and triple down protection of the elderly high-risk populations. If this is not done properly and first, then there will be no success. We should have fostered improved hand-washing hygiene and isolation of only the ill/sick/symptomatic persons. No asymptomatic person is/was to be quarantined and there is only to be testing of symptomatic persons or when there is strong clinical suspicion. We would promote improved support for the immune system such as public service messages about vitamin D supplements (especially in societies with limited sunlight), and allow the rest of the low-risk society to live largely unfettered daily lives, taking sensible reasonable safety precautions. This would allow them to mingle and be exposed to each other harmlessly and naturally, so that this would drive population level immunity. At the same time, we would offer early outpatient treatment to high-risk positive persons (in nursing homes or their private homes). This includes the elderly, younger persons with underlying medical conditions, and obese persons.
We feel that had this approach been enacted from the very beginning, the devastating losses incurred by businesses and the economy, as well as the deaths of despair to the business owners, employees, and our school children would have been avoided. There were crushing harms to our societies and especially our children and this is unforgivable for the data was always available and we have been screaming loudly from March 2020 on the pending tragedy if our governments continued in that manner. The narrative and falsehood of ‘asymptomatic spread’ helped severely hobble and damage the pandemic response as it caused devastating personal and economic loses to accrue needlessly, and especially for our children. Especially for the poorer among us who could least afford!
June 14, 2021
Posted by aletho |
Civil Liberties, Deception, Science and Pseudo-Science, Timeless or most popular | Covid-19, Human rights |
Leave a comment
Ivermectin, a common anti-parasite drug, has shown great efficacy in the fight against covid-19. For the first time, medical researchers have documented how ivermectin docks to the SARS-CoV-2 spike receptor-binding domain that is attached to the ACE2 receptor. In this way, ivermectin effectively inhibits viral attachment and replication, assisting a precise antiviral response that can target the SARS-CoV-2 spike protein at its most advantageous cleavage site. The researchers showed how ivermectin interferes with the attachment of the spike protein to the human cell membrane. Ivermectin is a simple medicine derived from the bacterium Streptomyces avermitilis. It weakens and kills parasites by interfering with their nervous system and muscle function. Ivermectin targets the glutamate-gated chloride channels in the parasite’s nerve and muscle cells, bolstering inhibitory effects in the parasite’s own neurotransmission. As the chloride ions permeate, the parasite’s cells are hyper-polarized and then paralyzed, resulting in their demise. In this study, ivermectin docked in region of leucine 91 of the spike protein and at the histidine 378 of the ACE2 receptor. The binding energy and constancy of ivermectin was also measured and found to be sufficient at the ACE2 receptor, proving the anti-parasitic molecule a powerful force for blocking viral attachment of SARS-CoV-2.
Ivermectin blocks SARS CoV-2 at the ACE2 receptor in humans
The 17 randomized controlled trials that use ivermectin for early treatment and prophylaxis report positive effects, with an estimated improvement of 73 percent and 83 percent, respectively. Out of 37 early treatment and prophylaxis studies for ivermectin, 97 percent report positive effects. One of the studies documents how ivermectin inhibits the replication of SARS-CoV-2 in vitro and displays broad-spectrum anti-viral activity against the causative virus (SARS-CoV-2). This study showed a 5,000-fold reduction in viral RNA after just 48 hours. The study also proves that effective treatments and prophylactics can mitigate the replication and spread of a virus thousands of times faster than the paranoid, isolationist approach of social distancing and lockdowns. If antivirals were encouraged early and often, then the spread of actual infectious virus would have been mitigated at rates thousands of times faster than the insane method of treating everyone as if they are infectious. By treating actual infections where symptoms are present, the spread is reduced at magnitudes thousands of times greater, while conveying immunity instead of terror. The SARS-CoV-2 spike protein is designed to attach to angiotensin-converting enzyme 2 (ACE2) in humans. To see whether ivermectin could dock at this receptor site and block viral attachment, the researchers used a program called AutoDock Vina Extended. This docking study showed the crystal structure of the SARS-CoV-2 spike receptor binding domain. The researchers looked specifically at the human ACE2 receptor and calculated the root-mean-square deviation (RMSD) of its atomic positions. A lower RMSD value indicates a more accurate docking capacity. When the RMSD value is three or greater, no docking has occurred at the receptor site. Ivermectin did not dock at nine of the locations; however, it did dock at the leucine 91 region of the spike and histidine 378 at the intersection of proteins between SARS CoV-2 and the ACE2 receptor complex. Previous studies proved ivermectin’s efficacy, but had to use high concentrations of the drug because the study relied on African green monkey kidney epithelial cells, which do not express the human ACE2 receptor. SARS-CoV-2 is specifically equipped to infect human ACE2 receptors, so this study could prove ivermectin to be effective in much smaller dosages. Clinical trials are now underway to determine if ivermectin is an effective treatment for covid-19.
The global conspiracy to suppress effective anti-viral medicines
The World Health Organization, the FDA, and the NIH have repeatedly suggested that no antiviral treatments exist for covid-19, even though multiple antiviral herbs and drugs have been studied during previous SARS and MERS epidemics and found to be effective. This time around, many of these antivirals were used with great effectiveness by doctors who were willing to go out on a limb and save lives. Chinese hospitals used various antiviral herbs to treat covid-19 patients. These hospitals studied the effects of the herbs for impeding virus-cell receptor binding, for stimulation of the host’s immunity, for blocking virus entry into host cells through action on the host’s enzymes, and for prevention of SARS-CoV-2 RNA synthesis and replication. The research found numerous phytochemicals to be effective, including: quercetin, ursolic acid, kaempferol, isorhamnetin, luteolin, glycerrhizin, and apigenin. The top three most effective plants for treating covid-19 included licorice root, (Glycyrrhiza glabra) chicory root, (Cichorium intybus) and hibiscus flowers (Hibiscus sabdariffa). A number of antiviral plants contain compounds that target all three antiviral targets, including olive leaf (Olea europaea), white horehound (Marrubium vulgare), black cumin seed (Nigella sativa), garden cress (Lepidium sativum), Judean wormwood (Artemisia Judaica), guava (Psidium guajava), chrysanthemum (Glebionis coronaria), and Maryam’s flower (Anastatica). Medical systems around the world are not properly equipped to strengthen the human immune response or understand what individuals need to overcome an infection. When it comes to fighting infections, the US FDA and European drug regulators parrot the same narrative of ignorance and apathy, withholding viable antivirals from the public. By the way, this is the only legal way to bring experimental vaccines to the global marketplace, by proving that no effective treatments exist. This suppression of science on antiviral treatments has paved the way for emergency use authorization of experimental vaccines and forced countless patients to suffer (and die) on ventilators, without treatment.
Learn more about this new ivermectin study:
https://www.brighteon.com/a9b743b6-3309-48fd-b8eb-9e79f02f9795
June 14, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular, Video | Covid-19, Ivermectin |
Leave a comment
1. Mix together some natural pathogens and government science to develop highly infectious coronasauce. Reduce coronasauce until it’s as thick as thieves.
2. Take one patent system which facilitates rent-seeking. Add coronasauce testing kits and coronasauce ‘antidote’.
3. Indemnify coronasauce ‘antidote’ manufacturers from liability, creating toxic brew of moral hazard.
4. Apply coronasauce to the public and baste with hysteria. (Side recipe: create hysteria from fraudulent PCR test data).
5. Exploit monopolistic licensing system to coerce medical doctors into compliance against their better judgment and pricked consciences. And Hippocratic oath.
6. Vigorously suppress mitigating treatment options to justify emergency consumption of coronasauce ‘antidote’.
7. Isolate and discard voices of reason using the Trusted News Initiative.
8. Inject coronasauce ‘antidote’ into every human on the planet initially twice, but aim for ad infinitum*.
9. Profit**
* If a bitter aftertaste of depopulation is experienced, see Build Back Better recipe for soothing utopianism.
**Enjoy your wages of sin while you can. A banquet of consequences may follow.
June 13, 2021
Posted by aletho |
Civil Liberties, Deception, Science and Pseudo-Science | Covid-19 |
Leave a comment
Rick Bright
Immediately after Rick Bright was transferred out of his position as head of BARDA and sent to the NIH, he started making a huge fuss. The April 22, 2020 NYT discribed his statements:
“While I am prepared to look at all options and to think ‘outside the box’ for effective treatments, I rightly resisted efforts to provide an unproven drug on demand to the American public,” Dr. Bright said. He went on to describe what he said ultimately happened: “I insisted that these drugs be provided only to hospitalized patients with confirmed Covid-19 while under the supervision of a physician.”
By May 14, 2020 Bright was already before Congress, supposedly as the good guy whistleblower who was trying to get things right for the pandemic against huge odds:
Bright told lawmakers Thursday he and other federal health officials had “worked hard” to resist pressure to allow a significant increase in access to hydroxychloroquine, and instead scaled that back to allowing an emergency use authorization but only “with strict guidelines.”
But he said his “concerns were escalated when I learned that officials were pushing to make that drug available outside that emergency authorization.”
“When I spoke outside of the government and shared my concern with the American public, that I believe was the straw that broke the camels back and escalated my removal,” Bright said.
He later said, “The highest priority we have is safety.”
… Bright’s lawyers said last week that the OSC had told them the investigation already had found evidence that Bright was ousted as head of a health agency for pushing back against increasing use of hydroxychloroquine…
HHS, in an emailed statement, said, “Rick Bright was transferred from his role as BARDA director to lead a bold new $1 billion testing program at NIH, critical to saving lives and reopening America.”
“Mr. Bright has not yet shown up for work, but continues to collect his $285,010 salary, while using his taxpayer-funded medical leave to work with partisan attorneys who are politicizing the response to COVID-19,” the statement said.
“His whistleblower complaint is filled with one-sided arguments and misinformation. HHS is reviewing the complaint and strongly disagrees with the allegations and characterizations made by Rick Bright.”
HHS also said that it was under Bright’s leadership that BARDA identified chloroquine and hydroxychloroquine as potential Covid-19 treatments.
“Rick Bright was the sponsor of getting hydroxychloroquine and praised his team for acquiring the drugs,” HHS said.
Bright’s reward? He was made a senior vice president of the Rockefeller Foundation, after refusing to show up for work at NIH. And who raved about him on the Rockefeller Foundation website? None other than Jeremy Farrar and Michael Ryan. I have not written about Ryan so far, but he is another co-conspirator in the efforts to suppress appropriate treatments, poison patients with excess doses of HCQ and prolong the pandemic, as Executive Director of the World Health Organization’s Health Emergencies Programme.
From the Rockefeller Foundation:
“If there is something we have learned throughout the COVID-19 pandemic and other high impact epidemics, it is that pandemic preparedness and response cannot be advanced with a siloed approach,” said Dr. Mike Ryan, Executive Director of the WHO’s Health Emergencies Programme. “Few people bring the full package to the table: profound scientific and public health expertise, years of outbreak response experience, a private and public sector background and a collaborative, innovative, and out-of-the-box mindset. Rick Bright combines all these qualities. His leadership will be an enormous asset to The Rockefeller Foundation and to the global health community.”Dr. Bright resigned from government service in protest over the Trump administration’s approach to handling the Covid-19 pandemic, specifically over the level of political interference in science and the spread of inaccurate information that he said was ‘dangerous, reckless and causing lives to be lost.’
“I’m delighted that Dr. Rick Bright has been appointed as Senior Vice President of Pandemic Prevention and Response at The Rockefeller Foundation,” said Dr. Jeremy Farrar, Director of Wellcome. “The Covid-19 pandemic has highlighted the human and economic costs of epidemics and the fact that we need to be better prepared to identify and respond to emerging infections. Dr. Bright is a leading figure in global health with a wealth of experience, and we look forward to working with him over the coming years.”
Bright’s job at Rockefeller is to work on future pandemic planning. Need I say more?
June 13, 2021
Posted by aletho |
Corruption, Deception, Science and Pseudo-Science | Covid-19, HCQ, NIH, Rockefeller Foundation, United States |
Leave a comment
In recent months a crisis situation in the USA food supply has been growing and is about to assume alarming dimensions that could become catastrophic. Atop the existing corona pandemic lockdowns and unemployment, a looming agriculture crisis as well could tip inflation measures to cause a financial crisis as interest rates rise. The ingredients are many, but central is a severe drought in key growing states of the Dakotas and Southwest, including agriculture-intensive California. So far Washington has done disturbingly little to address the crisis and California Water Board officials have been making the crisis far worse by draining the state water reservoirs…into the ocean.
So far the worst hit farm state is North Dakota which grows most of the nation’s Red Spring Wheat. In the Upper Midwest, the Northern Plains states and the Prairie provinces of Canada winter brought far too little snow following a 2020 exceedingly dry summer. The result is drought from Manitoba Canada to the Northern USA Plains States. This hits farmers in the region just four years after a flash drought in 2017 arrived without early warning and devastated the US Northern Great Plains region comprising Montana, North Dakota, South Dakota, and the adjacent Canadian Prairies.
As of May 27, according to Adnan Akyuz, State Climatologist, ninety-three percent of the North Dakota state is in at least a Severe Drought category, and 77% of the state is in an Extreme Drought category. Farm organizations predict unless the rainfall changes dramatically in the coming weeks, the harvest of wheat widely used for pasta and flour will be a disaster. The extreme dry conditions extend north of the Dakota border into Manitoba, Canada, another major grain and farming region, especially for wheat and corn. There, the lack of rainfall and warmer-than-normal temperatures threaten harvests, though it is still early for those crops. North Dakota and the plains region depend on snow and rainfall for its agriculture water.
Southwest States in Severe Drought
While not as severe, farm states Iowa and Illinois are suffering “abnormally dry” conditions in 64% for Iowa and 27% for Illinois. About 55% of Minnesota is abnormally dry as of end May. Drought is measured in a scale from D1 “abnormally dry,” D3 “severe drought” to D4, “exceptional drought.”
The severe dry conditions are not limited, unfortunately, to North Dakota or other Midwest farm states. A second region of very severe drought extends from western Texas across New Mexico, Colorado, Arizona, Nevada and deep into California. In Texas 20% of the state is in “severe drought,” and 12% “extreme drought.” Nearly 6% of the state is experiencing “exceptional drought,” the worst. New Mexico is undergoing 96% “severe drought,” and of that, 47% “exceptional drought.”
California Agriculture is Vital
The situation in California is by far the most serious in its potential impact on the supply of agriculture products to the nation. There, irrigation and a sophisticated water storage system provide water for irrigation and urban use to the state for their periodic dry seasons. Here a far larger catastrophe is in the making. A cyclical drought season is combining with literally criminal state environmental politics, to devastate agriculture in the nation’s most important farm producing state. It is part of a radical Green Agenda being advocated by Gov. Gavin Newsom and fellow Democrats to dismantle traditional agriculture, as insane as it may sound.
Few outside California realize that the state most known for Silicon Valley and beautiful beaches is such a vital source of agriculture production. California’s agricultural sector is the most important in the United States, leading the nation’s production in over 77 different products including dairy and a number of fruit and vegetable “specialty” crops. The state is the only producer of crops such as almonds, artichokes, persimmons, raisins, and walnuts. California grows a third of the country’s vegetables and two thirds of the country’s fruits and nuts. It leads all other states in farm income with 77,500 farms and ranches. It also is second in production of livestock behind Texas, and its dairy industry is California’s leading commodity in cash receipts. In total, 43 million acres of the state’s 100 million acres are devoted to agriculture. In short what happens here is vital to the nation’s food supply.
California Crisis Manmade: Where has the water gone?
The water crisis in California is far the most serious in terms of consequences for the food supply, in a period when the US faces major supply chain disruptions owing to absurd corona lockdowns combined with highly suspicious hacks of key infrastructure. On May 31, the infrastructure of the world’s largest meat processor, JBS SA, was hacked, forcing the shutdown of all its US beef plants that supply almost a quarter of American beef.
The Green lobby is asserting, while presenting no factual evidence, that Global Warming, i.e. increased CO2 manmade emission, is causing the drought. The NOAA examined the case and found no evidence. But the media repeats the narrative to advance the Green New Deal agenda with frightening statements such as claiming the drought is, “comparable to the worst mega-droughts since 800 CE.”
After 2011, California underwent a severe seven year drought. The drought ended in 2019 as major rains filled the California reservoir system to capacity. According to state water experts the reservoirs held enough water to easily endure at least a five-year drought. Yet two years later, the administration of Governor Newsom is declaring a new drought and threatening emergency measures. What his Administration is not saying is that the State Water Board and relevant state water authorities have been deliberately letting water flow into the Pacific Ocean. Why? They say to save two endangered fish species that are all but extinct—one, a rare type of Salmon, the second a Delta Smelt, a tiny minnow-size fish of some 2” size which has all but disappeared.
In June 2019 Shasta Dam, holding the state’s largest reservoir as a keystone of the huge Central Valley Project, was full to 98% of capacity. Just two years later in May 2021 Shasta Lake reservoir held a mere 42% of capacity, almost 60% down. Similarly, in June 2019 Oroville Dam reservoir, the second largest, held water at 98% of capacity and by May 2021 was down to just 37%. Other smaller reservoirs saw similar drops. Where has all the water gone?
Allegedly to “save” these fish varieties, during just 14 days in May, according to Kristi Diener, a California water expert and farmer, “90% of (Bay Area) Delta inflow went to sea. It’s equal to a year’s supply of water for 1 million people.” Diener has been warning repeatedly in recent years that water is unnecessarily being let out to sea as the state faces a normal dry year. She asks, “Should we be having water shortages in the start of our second dry year? No. Our reservoirs were designed to provide a steady five year supply for all users, and were filled to the top in June 2019.”
In 2008, at the demand of environmental groups such as the NRDC, a California judge ordered that the Central Valley Water project send 50% of water reservoirs to the Pacific Ocean to “save” an endangered salmon variety, even though the NGO admitted that no more than 1,000 salmon would likely be saved by the extreme measure. In the years 1998-2005 an estimated average of 49% of California managed water supply went to what is termed the “environment,” including feeding into streams and rivers, to feed estuaries and the Bay Area Delta. Only 28% went directly to maintain agriculture water supplies.
This past January Felicia Marcus, the chair of the California State Water Resources Control Board, who oversaw the controversial water policies since 2018, left at the end of her term to become an attorney for the Natural Resources Defense Council (NRDC) one of the most powerful green NGO’s, with a reported $400 million in resources to wage legal battles to defend “endangered species” such as the California salmon and the Delta Smelt.
Appointed by green Gov. Jerry Brown as chair of the State Water Board in 2018, Marcus is directly responsible for the draining of the reservoirs into the ocean after they filled in 2019, using the claim of protecting endangered species. In March 2021 with Marcus as attorney, the NRDC requested that the State Water Resources Control Board Marcus headed until recently, take “immediate action” to address perceived threats to listed salmon in the Sacramento River watershed from Central Valley Project (“CVP”) operations. This as the state is facing a new drought emergency?
In 2020 Gov. Gavin Newsom, a protégé of Jerry Brown, signed Senate Bill 1, the California Environmental, Public Health and Workers Defense Act, which would send billions of gallons of water out to the Pacific Ocean, ostensibly to save more fish. It was a cover for manufacturing the present water crisis and specifically attacking farming, as incredible as it may seem.
Target Agriculture
The true agenda of the Newsom and previous Brown administrations is to radically undermine the highly productive California agriculture sector. Gov. Newsom has now introduced an impressive-sounding $5.1 billion Drought Relief bill. Despite its title, nothing will go to improve the state reservoir water availability for cities and farms. Of the total, $500 million will be spent on incentives for farmers to “re-purpose” their land, that is to stop farming. Suggestions include wildlife habitat, recreation, or solar panels! Another $230 million will be used for “wildlife corridors and fish passage projects to improve the ability of wildlife to migrate safely.” “Fish passage projects” is a clever phrase for dam removal, destroying the nation’s most effective network of reservoirs.
Then the Newson bill allocates $300 million for the Sustainable Groundwater Management Act implementation, a 2014 law from Jerry Brown amid the previous severe drought to prevent farmers in effect from securing water from drilling wells. The effect will be to drive more farmers off the land. And another $200 million will go to “habitat restoration,” supporting tidal wetland, floodplains, and multi-benefit flood-risk reduction projects—a drought package with funding for floods? This is about recreating flood plains so when they demolish the dams, the water has someplace to go. The vast bulk of the $500 billion is slated to reimburse water customers from the previous 2011-2019 drought from higher water bills, a move no doubt in hopes voters will look positively on Newsom as he faces likely voter recall in November.
The systematic dismantling of one of the world’s most productive agriculture regions, using the seductive mantra of “environmental protection,” fits into the larger agenda of the Davos Great Reset and its plans to radically transform world agriculture into what the UN Agenda 2030 calls “sustainable” agriculture—no more meat protein. The green argument is that cows are a major source of methane gas emissions via burps. How that affects global climate no one has seriously proven. Instead we should eat laboratory-made fake meat like the genetically-manipulated Impossible Burger of Bill Gates and Google, or even worms. Yes. In January the EU European Food Safety Agency (EFSA), approved mealworms, or larvae of the darkling beetle, as the first “novel food” cleared for sale across the EU.
F. William Engdahl is strategic risk consultant and lecturer, he holds a degree in politics from Princeton University.
June 12, 2021
Posted by aletho |
Malthusian Ideology, Phony Scarcity, Science and Pseudo-Science | Agenda 2030, California, United States |
Leave a comment

 Aletho News

