6 Double Standards Public Health Officials Used to Justify COVID Vaccines
Madhava Setty, M.D. | The Defender | April 13, 2022
We are not only in an epidemiological crisis, we also are in an epistemological crisis. How do we know what we know? What differentiates opinion from a justified belief?
For nearly two years, the public has been inundated by a sophisticated messaging campaign that urges us to “trust the science.”
But how can a non-scientist know what the science is really saying?
Legacy media sources offer us an easy solution: “Trust us.”
Legions of so-called “independent” fact-checking sites that serve to eliminate any wayward thinking keep those with a modicum of skepticism in line.
“Research” has been redefined to mean browsing Wikipedia citations.
Rather than being considered for their merit, dissenting opinions are more easily dismissed as misinformation by labeling their source as untrustworthy.
How do we know these sources are untrustworthy? They must be if they offer a dissenting opinion!
This form of circular reasoning is the central axiom of all dogmatic systems of thought. Breaking the spell of dogmatic thinking is not easy, but it is possible.
In this article I describe six examples of double standards medical authorities have used to create the illusion their COVID-19 narrative is logical and sensible.
This illusion has been used with devastating effect to raise vaccine compliance.
Rather than citing scientific publications or expert opinions that conflict with our medical authorities’ narrative — information that will be categorically dismissed because it appears on The Defender — I will instead demonstrate how, from the beginning, the official narrative has been inconsistent, hypocritical and/or contradictory.
1. COVID deaths are ‘presumed,’ but vaccine deaths must be ‘proven’
As of April 8, VAERS included 26,699 reports of deaths following COVID vaccines.
The Centers for Disease Control and Prevention (CDC) officially acknowledges only nine of these.
In order to establish causality, the CDC requires autopsies to rule out any possible etiology of death before the agency will place culpability on the vaccine.
But the CDC uses a very different standard when it comes to identifying people who died from COVID.
The 986,000 COVID deaths reported by the CDC here are, as footnote [1] indicates, “Deaths with confirmed or presumed [emphasis added] COVID-19.”
If a person dies with a positive PCR test or is presumed to have COVID, the CDC will count that as COVID-19 death.
Note that in the CDC’s definition, a COVID fatality does not mean the person died from the disease, only with the disease.
Why is an autopsy required to establish a COVID vaccine death but not to establish a COVID death?
Conversely, why is recent exposure to SARS-CoV-2 prior to a death sufficient to establish causality — but recent exposure to a vaccine considered coincidental?
2. CDC uses VAERS data to investigate myocarditis yet claims VAERS data on vaccine deaths is unreliable
On June 23, 2021, the CDC’s Advisory Committee on Immunization Practices met to assess the risk of peri/myocarditis following COVID vaccination, especially in young males.
This was the key slide in this presentation:
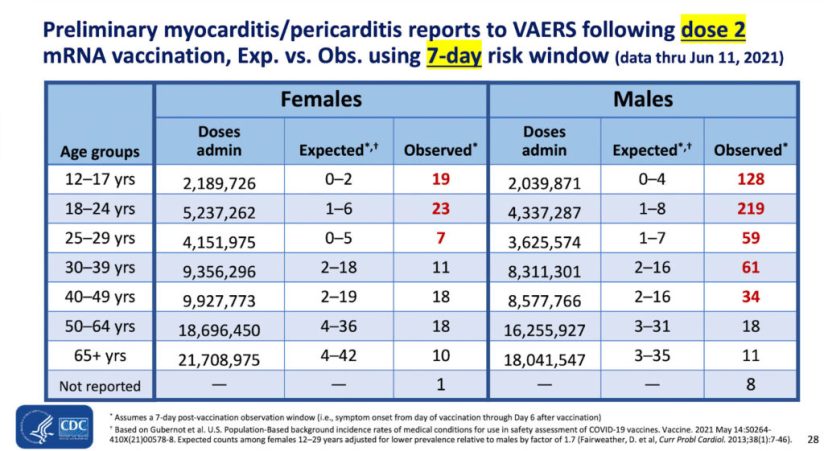
The observed risk of myocarditis is 219 in about 4.3 million second doses of COVID vaccine in males 18 to 24 years old.
The CDC is fine with using VAERS data to assess risk of myocarditis following vaccination — yet the agency rejects all but nine of the 26,699 reports of deaths following the vaccines.
Why does the CDC trust the peri/myocarditis data in VAERS but not the data on deaths?
One reason may be because the onset of myocarditis symptoms is closely tied to the time of vaccination.
In other words, because this condition closely follows inoculation the two events are highly correlated and suggestive of causation.
For example, here is another slide from the same presentation:
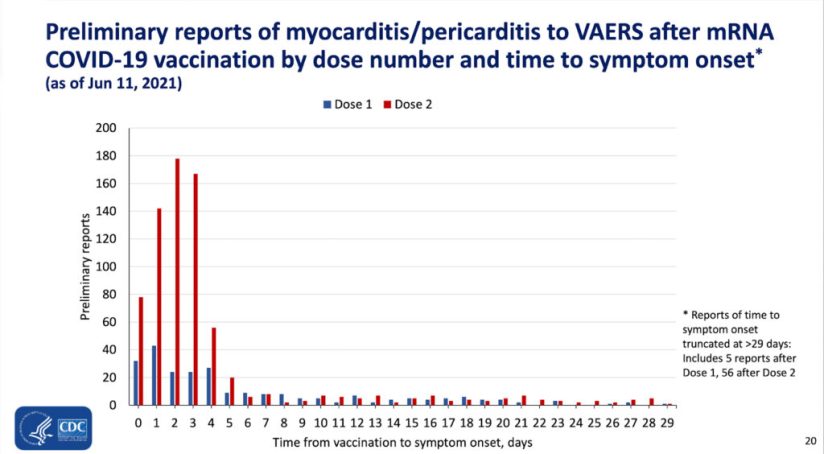
The majority of cases of vaccine-induced peri/myocarditis suffered symptoms within the first few days after injection. As explained above, this is highly suggestive of a causative effect of the vaccine.
A recent study in The Lancet included a similar graph, taken directly from VAERS, on deaths following vaccination:
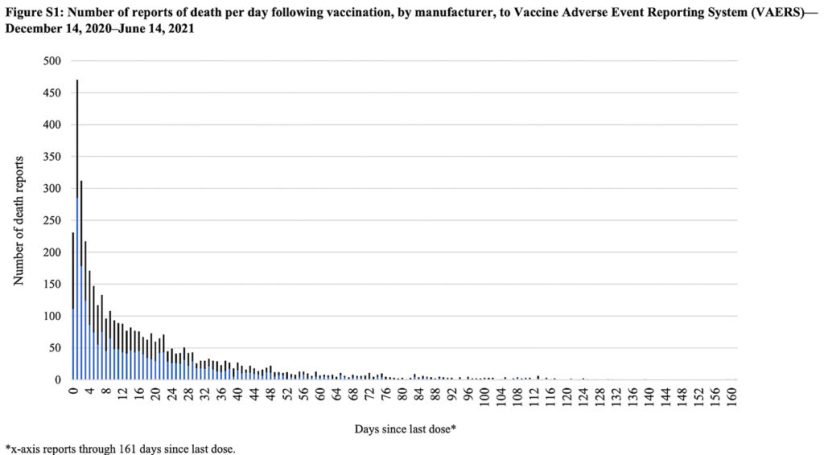
Once again, the event (death) closely follows vaccination in the majority of cases.
As we regard the two graphs above we should acknowledge that the temporal relationship between the injection and the adverse event is suggestive of causation but does not stand as proof of such.
However, it is also important to note that if the vaccination caused the deaths, that is exactly what the plot would look like.
It should be clear that the CDC has no justification for dismissing VAERS deaths if the agency is willing to accept reports of myo/pericarditis from the very same reporting system.
3. CDC pushes ‘relative risk’ for determining vaccine efficacy, but uses ‘absolute risk’ to downplay risk of adverse events
In Pfizer’s Phase 3 trial, nine times more placebo recipients developed severe COVID than those vaccinated during the short period of observation. This constitutes a relative risk reduction of 90%.
This seemed an encouraging finding and was used as a major talking point to compel the public to accept this experimental therapy despite the absence of any long-term data.
However, the risk of a trial participant contracting severe COVID (Table S5) was 1 in 21,314 (0.0047%) if they were vaccinated.
If they received the placebo, the risk was still only 9 in 21,259 (0.0423%).
The vaccine reduced the absolute risk of contracting severe disease by 0.038%.
Mainstream media and the CDC never mentioned the minuscule reduction in absolute risk of contracting severe COVID by getting inoculated.
Moreover, with 0.6% of vaccine recipients in the trial suffering a serious vaccine injury (one that results in death, medical or surgical intervention, hospitalization or an impending threat to life), approximately 16 serious adverse events will result for every serious case of COVID prevented by vaccination.
However, when it comes to risk of myo/pericarditis, the CDC states, “Myocarditis and pericarditis have rarely been reported, especially in adolescents and young adult males within several days after COVID-19 vaccination.”
The CDC further states, “While absolute risk remains small, the risk for myocarditis is higher for males ages 12 to 39 years…”
In other words, the risk of adverse events is being considered in absolute terms, not relative.
The CDC presentation slide above (Table 1) indicates the relative risk of contracting myo/pericarditis in males 18 to 24 is 27 to more than 200 times higher than expected in (unvaccinated) young men that age.
When assuaging the public’s fear around vaccine-induced myocarditis, the CDC finds it useful to cite absolute risk — yet when promoting the efficacy of the vaccine, the CDC emphasizes relative risks.
This double standard has been quietly and masterfully employed to reduce vaccine hesitancy and encourage compliance.
4. FDA requires randomized control studies for early treatment medications — but not for boosters
The CDC reports that as of April 8, 98.3 million Americans had received a COVID booster.
On March 29, the U.S. Food and Drug Administration (FDA) authorized a second booster for the immunocompromised and adults over age 50.
These authorizations were made not because of solid evidence the boosters are effective but rather to remedy the fact that the primary vaccine series has been widely shown to have waning efficacy within a few months.
As reported by The Defender, Dr. Peter Marks, director of the FDA’s vaccine division, Center for Biologics Evaluation and Research, admitted the fourth booster dose approved last week was a “stopgap measure” — in other words, a temporary measure to be implemented until a proper solution may be found in the future.
Despite the lack of solid evidence, the FDA continues to recommend and authorize boosters.
Yet when it comes to early treatment options, the agency holds medicines — including those the agency has already licensed and approved for other uses — to a different standard.
In this CNN interview from August 2021, Dr. Anthony Fauci, head of the National Institute of Allergy and Infectious Diseases, warns people not to take ivermectin for COVID because “there is no clinical evidence that this works.”
With regard to hydroxychloroquine, Fauci said, “We know that every single good study — and by good study, I mean randomized control study in which the data are firm and believable — has s shown that hydroxychloroquine is not effective in the treatment of Covid-19”, as reported by the BBC on July 29, 2020.
Where, then, are the randomized control studies in which the data are firm and believable that show boosters are effective at preventing COVID?
There aren’t any. None have been done.
As of today, the FDA still refuses to authorize the use of ivermectin and hydroxychloroquine to treat COVID despite hundreds of studies that demonstrate significant benefits (ivermectin, hydroxychloroquine) in prevention as well as early and late treatment.
The double standard here is blatant. There are no randomized control studies that show boosters are effective in preventing COVID.
Nevertheless, these experimental therapies have the FDA’s blessing while inexpensive, highly effective safe and proven medicines are ignored despite the enormous evidence that supports their use.
5. FDA uses immunobridging to justify Pfizer shots for young kids, but rejects antibodies as indicative of immune protection from COVID
Immunobridging is a method of inferring a vaccine’s effectiveness in preventing disease by assessing its ability to elicit an immune response through the measurement of biochemical markers, typically antibody levels.
The FDA asserts the presence of SARS-COV-2 antibodies is not necessarily indicative of immune protection from COVID.
Moreover, the FDA’s Vaccine and Related Biologics Product Advisory Committee reached a consensus last week that antibody levels cannot be used as a correlate for vaccine effectiveness.
Their decision is consistent with the CDC’s executive summary of a science brief released on October 29, 2021:
“Data are presently insufficient to determine an antibody titer threshold that indicates when an individual is protected from infection.”
Nevertheless, the FDA used immunobridging as a means to justify authorization of the Pfizer vaccine to children ages 5 to 11, as explained in The Defender here and here.
Because there were no deaths or serious cases of COVID in the pediatric trial, the FDA chose to reject its own position (and that of its advisory committee) regarding antibody titers as a correlate for vaccine efficacy.
6. Causation must be proven for vaccine injuries, but correlation suffices for proving vaccine efficacy
When it comes to vaccine injuries the public is often reminded that correlation does not equal causation.
In other words, just because an injury was preceded by inoculation doesn’t mean the vaccine caused the injury.
But what constitutes causation in medicine? A mechanism of action needs to be identified and pathological studies must confirm this mechanism while eliminating other potential causative factors. Causation can be proven only on a case-by-case basis.
Proving causation requires an enormous burden of proof in medicine.
For example, does smoking cause lung cancer? The answer is yes, it can. That doesn’t mean that it will.
However, when it comes to the benefit of medical intervention, such as a vaccine, causation does not have to be established. Correlation suffices.
In the COVID vaccine trials, fewer vaccinated people contracted COVID than unvaccinated ones. Yet there were those who received the vaccine who contracted the disease anyway.
To be fair, this is how all new medical interventions are evaluated. The benefit doesn’t have to be caused by the vaccine in the strictest sense, there just has to be a correlation between vaccination and a relative protective effect.
The more often this happens, the more confident we can be that the outcome wasn’t simply a coincidence.
Likewise, when it comes to assessing the harm of medical intervention, the most sensible outcome to consider is mortality. After all, what would be the point of introducing a vaccine that prevented some deaths while causing more?
Nevertheless, this is, in fact, what we have done with the Pfizer product. The interim results from the Phase 3 trial demonstrated that all-cause mortality in the vaccinated cohort was higher than in the placebo.
This glaring problem gets brushed aside because there were two deaths from COVID in the placebo arm versus just one in the vaccinated cohort, allowing the vaccine manufacturer to claim a 50% efficacy in preventing this outcome.
However, if we attribute a protective benefit to the vaccine in preventing this one fatality, we must also conclude that the vaccine was responsible for the extra death when considering mortality from all causes.
Doing otherwise would be applying yet another double standard.
How the pandemic could have played out differently
To summarize how devastating the use of these double standards in crafting the “safe and effective” narrative was, let’s look at how different the situation would be if we had adopted the opposite standard:
- There would have been an extremely low number of deaths from COVID. Very few, if any, autopsies have definitively confirmed that a fatality was caused by SARS-CoV-2. If confirmation by autopsy is the standard, there have been essentially zero deaths from COVID during the pandemic.
On the other hand, if we presume the deaths registered in VAERS are in fact vaccine-induced fatalities — similar to how the CDC presumed many deaths from COVID — we can affirm there have been more than 26,000 vaccine deaths. - Using absolute risk reduction as a measure of efficacy, vaccines would have been widely rejected as ineffective, providing only a 0.038% risk reduction for contracting severe COVID.
- Ivermectin and hydroxychloroquine would have been readily available for people who got COVID. And for those who got the vaccine but got COVID anyway, these medicines would have been a great alternative to boosters, which wouldn’t have been approved due to the lack of a single randomized control study proving they work.
- No children between the ages of 5 and 11 would have received this risky, experimental vaccine as it wouldn’t have been authorized for this age group — because Pfizer’s pediatric trials did not demonstrate any meaningful outcomes in children ages 5 to 11.
- The Pfizer vaccine would no longer be in use because interim data demonstrated that all-cause mortality is higher in the vaccinated.
Madhava Setty, M.D. is senior science editor for The Defender.
Report on the FDA’s 4/6/22 Advisory Committee (VRBPAC) meeting on the selection of future boosters
While the committee got nowhere on the choice of next boosters, there were a few very important reveals
By Meryl Nass, MD | April 10, 2022
Authorizing vaccine for the 6 months to 5 year old group was never mentioned. Can it be that FDA is finally grappling with the awful data, the longterm risks of vaccination, and will turn away from unleashing these vaccines on our youngest kids? Or is there simply too much money at stake, too many promised school mandates, too many done deals behind closed doors?
Important takeaways
1. Many members and presenters agreed that antibody levels (aka titers) are not a valid measure of immunity (they are not a correlate of protection, and there is currently NOTHING measurable in the blood that is considered a valid reflection of immunity). This admission is HUGE, as it reveals that neutralizing antibody titers can no longer be used to authorize or approve COVID vaccines.
2. Therefore the only way to determine vaccine effectiveness is a clinical trial.
3. No one at the meeting (nearly 30 people) ventured a guess as to what strain might cause the next COVID wave. All seemed to agree there would be another wave, but this was just a guess. However, without a variant you can’t make a vaccine and you can’t conduct a clinical trial to see if the vaccine works. And you can’t possibly do this by June, to make vaccine available for the fall, when FDA and the VRBPAC expect it will be needed.
4. Dr. Peter Marks, the director of the FDA’s vaccine division, CBER, admitted that the 4th booster dose authorized last week was a “stopgap measure”– in other words, he claims it was to kick the waning vaccine efficacy can down the road.
5. Claims were repeatedly made that vaccine still protects against severe outcomes and death, but FDA’s lead scientist for this presentation, Doran Fink, admitted that efficacy is also waning for severe outcomes. I’ll say it is.
6. NO data was presented at all regarding strain choice/prediction of what to use as the antigen(s) for a newer vaccine. It was as if everyone just got the idea to begin thinking about this yesterday.
7. It appeared that neither CDC, FDA nor the VRBPAC advisors wanted to take any initiative or responsibility in figuring out what kind of a vaccine comes next (with the exception of Dr. Kim, who did show initiative about prescribing a way forward). I am not sure any of them wanted to find a way forward.
8. Was everyone dancing around the strain/variant choice because in fact no one really wants a newer vaccine, or because no one wanted to be responsible for picking a loser? I could not tell whether this was a deliberate slow-roll as a means of squeezing out of the COVID vaccine disaster, or whether we were watching an agency and advisors who are highly risk-averse but have no problems with the vaccines.
9. The Public Comments from about 1:30 pm to 2:30 pm (about 5 hours into the meeting) were evidence of outstanding work by independent scientists and heart-rending testimonies by the vaccine injured. There were only 2 people who favored vaccines in the group, one a top Moderna scientist (Dr. Rita Das) who did not actually belong there… had FDA begged Moderna to find someone to speak in favor of boosters?
10. The word transparency was used a lot. Which was peculiar since FDA’s COVID vaccine data, deliberations and decisions have been anything but transparent. Even the reason for today’s meeting is murky.
The link below is to my live blog of the all day meeting.
https://live.childrenshealthdefense.org/admin/fda-advisory-committee/fullscreen-chat
———————-
Of course, what the FDA needs to say, no doubt in some slowly unrolling, self-serving fashion, is that:
- The mRNA platform was the best we could do under the circumstances, but it didn’t actually work out that well.
- Coronaviruses are mutating or lab-tating too quickly to be able to vaccinate effectively against them.
- While we still have contracts for 5 or 10 doses per person, we are going to cancel them and try early treatments.
What they won’t way is that these vaccines sickened many thousands, or millions, and the US will now establish clinics to evaluate and treat the injured Americans who did what their government asked of them, cover their medical expenses and pay them disability.
PS. When the Japanese found that the HPV vaccines caused similar severe injuries, about 8 or 10 years ago, clinics were established to take care of the injured.
Putting Big Pharma on Trial in the COVID-19 Era, Part 3
Backing the Big Four: Big Pharma and the FDA, WHO, NIH, CDC
By Rebecca Strong | February 16, 2022
I know what you’re thinking. Big pharma is amoral and the FDA’s devastating slips are a dime a dozen — old news. But what about agencies and organizations like the National Institutes of Health (NIH), World Health Organization (WHO), and Centers for Disease Control & Prevention (CDC)? Don’t they have an obligation to provide unbiased guidance to protect citizens? Don’t worry, I’m getting there.
The WHO’s guidance is undeniably influential across the globe. For most of this organization’s history, dating back to 1948, it could not receive donations from pharmaceutical companies — only member states. But that changed in 2005 when the WHO updated its financial policy to permit private money into its system. Since then, the WHO has accepted many financial contributions from big pharma. In fact, it’s only 20% financed by member states today, with a whopping 80% of financing coming from private donors. For instance, The Bill and Melinda Gates Foundation (BMGF) is now one of its main contributors, providing up to 13% of its funds — about $250–300 million a year. Nowadays, the BMGF provides more donations to the WHO than the entire United States.
Dr. Arata Kochi, former head of WHO’s malaria program, expressed concerns to director-general Dr. Margaret Chan in 2007 that taking the BMGF’s money could have “far-reaching, largely unintended consequences” including “stifling a diversity of views among scientists.”
“The big concerns are that the Gates Foundation isn’t fully transparent and accountable,” Lawrence Gostin, director of WHO’s Collaborating Center on National and Global Health Law, told Devex in an interview. “By wielding such influence, it could steer WHO priorities … It would enable a single rich philanthropist to set the global health agenda.”

Bill Gates, Francis Collins, Anthony Fauci. Photo credit: National Institutes of Health
Take a peek at the WHO’s list of donors and you’ll find a few other familiar names like AstraZeneca, Bayer, Pfizer, Johnson & Johnson, and Merck.
The NIH has the same problem, it seems. Science journalist Paul Thacker, who previously examined financial links between physicians and pharma companies as a lead investigator of the United States Senate Committee, wrote in The Washington Post that this agency “often ignored” very “obvious” conflicts of interest. He also claimed that “its industry ties go back decades.” In 2018, it was discovered that a $100 million alcohol consumption study run by NIH scientists was funded mostly by beer and liquor companies. Emails proved that NIH researchers were in frequent contact with those companies while designing the study — which, here’s a shocker — were aimed at highlighting the benefits and not the risks of moderate drinking. So, the NIH ultimately had to squash the trial.
And then there’s the CDC. It used to be that this agency couldn’t take contributions from pharmaceutical companies, but in 1992 they found a loophole: new legislation passed by Congress allowed them to accept private funding through a nonprofit called the CDC Foundation. From 2014 through 2018 alone, the CDC Foundation received $79.6 million from corporations like Pfizer, Biogen, and Merck.
Of course, if a pharmaceutical company wants to get a drug, vaccine, or other product approved, they really need to cozy up to the FDA. That explains why in 2017, pharma companies paid for a whopping 75% of the FDA’s scientific review budgets, up from 27% in 1993. It wasn’t always like this. But in 1992, an act of Congress changed the FDA’s funding stream, enlisting pharma companies to pay “user fees,” which help the FDA speed up the approval process for their drugs.
A 2018 Science investigation found that 40 out of 107 physician advisors on the FDA’s committees received more than $10,000 from big pharma companies trying to get their drugs approved, with some banking up to $1 million or more. The FDA claims it has a well-functioning system to identify and prevent these possible conflicts of interest. Unfortunately, their system only works for spotting payments before advisory panels meet, and the Science investigation showed many FDA panel members get their payments after the fact. It’s a little like “you scratch my back now, and I’ll scratch your back once I get what I want” — drug companies promise FDA employees a future bonus contingent on whether things go their way.
Here’s why this dynamic proves problematic: a 2000 investigation revealed that when the FDA approved the rotavirus vaccine in 1998, it didn’t exactly do its due diligence. That probably had something to do with the fact that committee members had financial ties to the manufacturer, Merck — many owned tens of thousands of dollars of stock in the company, or even held patents on the vaccine itself. Later, the Adverse Event Reporting System revealed that the vaccine was causing serious bowel obstructions in some children, and it was finally pulled from the U.S. market in October 1999.
Then, in June of 2021, the FDA overruled concerns raised by its very own scientific advisory committee to approve Biogen’s Alzheimer’s drug Aduhelm — a move widely criticized by physicians. The drug not only showed very little efficacy but also potentially serious side effects like brain bleeding and swelling, in clinical trials. Dr. Aaron Kesselheim, a Harvard Medical School professor who was on the FDA’s scientific advisory committee, called it the “worst drug approval” in recent history, and noted that meetings between the FDA and Biogen had a “strange dynamic” suggesting an unusually close relationship. Dr. Michael Carome, director of Public Citizen’s Health Research Group, told CNN that he believes the FDA started working in “inappropriately close collaboration with Biogen” back in 2019. “They were not objective, unbiased regulators,” he added in the CNN interview. “It seems as if the decision was preordained.”
That brings me to perhaps the biggest conflict of interest yet: Dr. Anthony Fauci’s NIAID is just one of many institutes that comprises the NIH — and the NIH owns half the patent for the Moderna vaccine — as well as thousands more pharma patents to boot. The NIAID is poised to earn millions of dollars from Moderna’s vaccine revenue, with individual officials also receiving up to $150,000 annually.
Operation Warp Speed
In December of 2020, Pfizer became the first company to receive an emergency use authorization (EUA) from the FDA for a COVID-19 vaccine. EUAs — which allow the distribution of an unapproved drug or other product during a declared public health emergency — are actually a pretty new thing: the first one was issued in 2005 so military personnel could get an anthrax vaccine. To get a full FDA approval, there needs to be substantial evidence that the product is safe and effective. But for an EUA, the FDA just needs to determine that it may be effective. Since EUAs are granted so quickly, the FDA doesn’t have enough time to gather all the information they’d usually need to approve a drug or vaccine.
Pfizer CEO and chairman Albert Bourla has said his company was “operating at the speed of science” to bring a vaccine to market. However, a 2021 report in The BMJ revealed that this speed might have come at the expense of “data integrity and patient safety.” Brook Jackson, regional director for the Ventavia Research Group, which carried out these trials, told The BMJ that her former company “falsified data, unblinded patients, and employed inadequately trained vaccinators” in Pfizer’s pivotal phase 3 trial. Just some of the other concerning events witnessed included: adverse events not being reported correctly or at all, lack of reporting on protocol deviations, informed consent errors, and mislabeling of lab specimens. An audio recording of Ventavia employees from September 2020 revealed that they were so overwhelmed by issues arising during the study that they became unable to “quantify the types and number of errors” when assessing quality control. One Ventavia employee told The BMJ she’d never once seen a research environment as disorderly as Ventavia’s Pfizer vaccine trial, while another called it a “crazy mess.”
Over the course of her two-decades-long career, Jackson has worked on hundreds of clinical trials, and two of her areas of expertise happen to be immunology and infectious diseases. She told me that from her first day on the Pfizer trial in September of 2020, she discovered “such egregious misconduct” that she recommended they stop enrolling participants into the study to do an internal audit.
“To my complete shock and horror, Ventavia agreed to pause enrollment but then devised a plan to conceal what I found and to keep ICON and Pfizer in the dark,” Jackson said during our interview. “The site was in full clean-up mode. When missing data points were discovered the information was fabricated, including forged signatures on the informed consent forms.”
A screenshot Jackson shared with me shows she was invited to a meeting titled “COVID 1001 Clean up Call” on Sept. 21, 2020. She refused to participate in the call.
Jackson repeatedly warned her superiors about patient safety concerns and data integrity issues.
“I knew that the entire world was counting on clinical researchers to develop a safe and effective vaccine and I did not want to be a part of that failure by not reporting what I saw,” she told me.
When her employer failed to act, Jackson filed a complaint with the FDA on Sept. 25, and Ventavia fired her hours later that same day under the pretense that she was “not a good fit.” After reviewing her concerns over the phone, she claims the FDA never followed up or inspected the Ventavia site. Ten weeks later, the FDA authorized the EUA for the vaccine. Meanwhile, Pfizer hired Ventavia to handle the research for four more vaccine clinical trials, including one involving children and young adults, one for pregnant women, and another for the booster. Not only that, but Ventavia handled the clinical trials for Moderna, Johnson & Johnson, and Novavax. Jackson is currently pursuing a False Claims Act lawsuitagainst Pfizer and Ventavia Research Group.
Last year, Pfizer banked nearly $37 billion from its COVID vaccine, making it one of the most lucrative products in global history. Its overall revenues doubled in 2021 to reach $81.3 billion, and it’s slated to reach a record-breaking $98-$102 billion this year.
“Corporations like Pfizer should never have been put in charge of a global vaccination rollout, because it was inevitable they would make life-and-death decisions based on what’s in the short-term interest of their shareholders,” writes Nick Dearden, director of Global Justice Now.
As previously mentioned, it’s super common for pharmaceutical companies to fund the research on their own products. Here’s why that’s scary. One 1999 meta-analysis showed that industry-funded research is eight times less likely to achieve unfavorable results compared to independent trials. In other words, if a pharmaceutical company wants to prove that a medication, supplement, vaccine, or device is safe and effective, they’ll find a way.
With that in mind, I recently examined the 2020 study on Pfizer’s COVID vaccine to see if there were any conflicts of interest. Lo and behold, the lengthy attached disclosure form shows that of the 29 authors, 18 are employees of Pfizer and hold stock in the company, one received a research grant from Pfizer during the study, and two reported being paid “personal fees” by Pfizer. In another 2021 study on the Pfizer vaccine, seven of the 15 authors are employees of and hold stock in Pfizer. The other eight authors received financial support from Pfizer during the study.
As of the day I’m writing this, about 64% of Americans are fully vaccinated, and 76% have gotten at least one dose. The FDA has repeatedly promised “full transparency” when it comes to these vaccines. Yet in December of 2021, the FDA asked for permission to wait 75 years before releasing information pertaining to Pfizer’s COVID-19 vaccine, including safety data, effectiveness data, and adverse reaction reports. That means no one would see this information until the year 2096 — conveniently, after many of us have departed this crazy world. To recap: the FDA only needed 10 weeks to review the 329,000 pages worth of data before approving the EUA for the vaccine — but apparently, they need three-quarters of a century to publicize it.
In response to the FDA’s ludicrous request, PHMPT — a group of over 200 medical and public health experts from Harvard, Yale, Brown, UCLA, and other institutions — filed a lawsuit under the Freedom of Information Act demanding that the FDA produce this data sooner. And their efforts paid off: U.S. District Judge Mark T. Pittman issued an order for the FDA to produce 12,000 pages by Jan. 31, and then at least 55,000 pages per month thereafter. In his statement to the FDA, Pittman quoted the late John F. Kennedy: “A nation that is afraid to let its people judge the truth and falsehood in an open market is a nation that is afraid of its people.”
As for why the FDA wanted to keep this data hidden, the first batch of documentation revealed that there were more than 1,200 vaccine-related deaths in just the first 90 days after the Pfizer vaccine was introduced. Of 32 pregnancies with a known outcome, 28 resulted in fetal death. The CDC also recently unveiled data showing a total of 1,088,560 reports of adverse events from COVID vaccines were submitted between Dec. 14, 2020, and Jan. 28, 2022. That data included 23,149 reports of deaths and 183,311 reports of serious injuries. There were 4,993 reported adverse events in pregnant women after getting vaccinated, including 1,597 reports of miscarriage or premature birth. A 2022 study published in JAMA, meanwhile, revealed that there have been more than 1,900 reported cases of myocarditis — or inflammation of the heart muscle — mostly in people 30 and under, within 7 days of getting the vaccine. In those cases, 96% of people were hospitalized.
“It is understandable that the FDA does not want independent scientists to review the documents it relied upon to license Pfizer’s vaccine given that it is not as effective as the FDA originally claimed, does not prevent transmission, does not prevent against certain emerging variants, can cause serious heart inflammation in younger individuals, and has numerous other undisputed safety issues,” writes Aaron Siri, the attorney representing PHMPT in its lawsuit against the FDA.
Siri told me in an email that his office phone has been ringing off the hook in recent months.
“We are overwhelmed by inquiries from individuals calling about an injury from a COVID-19 vaccine,” he said.
By the way — it’s worth noting that adverse effects caused by COVID-19 vaccinations are still not covered by the National Vaccine Injury Compensation Program. Companies like Pfizer, Moderna, and Johnson & Johnson are protected under the Public Readiness and Emergency Preparedness (PREP) Act, which grants them total immunity from liability with their vaccines. And no matter what happens to you, you can’t sue the FDA for authorizing the EUA, or your employer for requiring you to get it, either. Billions of taxpayer dollars went to fund the research and development of these vaccines, and in Moderna’s case, licensing its vaccine was made possible entirely by public funds. But apparently, that still warrants citizens no insurance. Should something go wrong, you’re basically on your own.
To be continued…
Pfizer Hired 600+ People to Process Vaccine Injury Reports, Documents Reveal
By Michael Nevradakis, Ph.D. | The Defender | April 5, 2022
Pfizer hired about 600 additional full-time employees to process adverse event reports during the three months following the Emergency Use Authorization (EUA) of its COVID-19 vaccine, newly released documents reveal.
According to the documents, Pfizer said, “More are joining each month with an expected total of more than 1,800 additional resources by the end of June 2021.”
The information was contained in a 10,000-page document cache released April 1 by the U.S. Food and Drug Administration (FDA) and made public as part of a court-ordered disclosure schedule stemming from an expedited Freedom of Information Act (FOIA) request.
The latest revelations appeared in a document, “Cumulative analysis of post-authorization adverse event reports” of the Pfizer-BioNTech vaccine, highlighting such adverse events identified through Feb. 28, 2021.
The document was previously released in November 2021, but was partially redacted. The redactions included the number of employees Pfizer hired and/or was planning to hire.
According to the unredacted document released April 1:
“Pfizer has also taken a multiple actions [sic] to help alleviate the large increase of adverse event reports. This includes significant technology enhancements, and process and workflow solutions, as well as increasing the number of data entry and case processing colleagues.
“To date, Pfizer has onboarded approximately 600 additional full-time employees (FTEs).
“More are joining each month with an expected total of more than 1,800 additional resources by the end of June 2021.”
The unredacted version also revealed the number of Pfizer-BioNTech vaccine doses shipped worldwide between December 2020 and February 2021:
“It is estimated that approximately 126,212,580 doses of BNT162b2 [the Pfizer EUA vaccine] were shipped worldwide from the receipt of the first temporary authorisation for emergency supply on 01 December 2020 through 28 February 2021.”
The number of shipped doses previously was redacted.
Remarking upon this newly revealed information, Brian Hooker, chief scientific officer of Children’s Health Defense, told The Defender :
“The rollout of the Pfizer vaccine has led to an unprecedented number of adverse events reported — 158,000 adverse events in the first two-plus months of the rollout means that the rate of reported AE [adverse events] was approximately 1:1000, with many of the AEs graded as serious. This is based on a denominator of 125,000,000 vaccines distributed.
“It is no wonder that an army of 1,800 individuals was needed to process all of the information.”
Hooker noted the total number (1,205,755) of COVID vaccine adverse events reported to the Vaccine Adverse Event Reporting System between Dec. 14, 2020 and March 25, 2022, now eclipses the total number (930,952) of adverse events reported in the 32-year history of the database.
Dr. Madhava Setty, a board-certified anesthesiologist and senior science editor for The Defender, previously reported on the same Pfizer document, before the unredacted version was released.
“In that piece, I alluded to Pfizer’s admission that they needed more staff to process all of the adverse events being reported to them,” Setty said.
“It seems this document has now been updated. 600 FTEs [full-time employees]! … I wonder how many extra people the CDC [U.S. Centers for Disease Control and Protection] has hired? Given how they are operating, I would say zero.”
Pfizer downplayed adverse reactions in request for full FDA license
The April 1 document release also included “request for priority review” — the documentation Pfizer in May 2021 submitted to the FDA for full licensure of its Comirnaty COVID vaccine.
In this document, Pfizer described its vaccine as fulfilling an “unmet medical need,” claiming:
“Mass immunization with a safe and effective vaccine against COVID-19 can dramatically alter the trajectory of the pandemic.
“According to policy briefing by the Institute for Health Metrics and Evaluation published on 31 March 2021, COVID-19 remains a leading cause of death in the US with up to 100,000 additional deaths projected in the US between March and July 2021, many of which can likely be prevented with COVID-19 vaccination.”
Pfizer expressed “concerns” about lifting COVID-related measures, such as lockdowns, on the basis that the lifting of such restrictions would “counteract the impacts of this vaccination effort.”
The document states:
“Vaccination against COVID-19 began with EUA/conditional approvals in December 2020, in a phased rollout defined by national/regional guidance.
- “However, there continue to be concerning trends that may counteract the impacts of this vaccination effort, including:
- “[L]imitations in access to obtaining a vaccine due to infrastructure challenges (ie, clinic and appointment capacity and systems)
- “[I]ncreasing viral transmission fueled by relaxed compliance with mitigations as the pandemic surpasses the 1-year mark (ie, masks, physical distancing, limiting travel)
- “[I]ncreasing circulation of emerging variants of concern (which are currently driving continued spread of viral infection in Europe despite extensive mitigation mandates).”
Pfizer justified its request for full licensure of its COVID vaccine on the following basis:
“A vaccine program must be implemented expediently and rapidly expanded to have a significant impact on the pandemic course.
“Licensure of BNT162b2 is likely to enhance vaccine uptake by facilitating supply of vaccine from Pfizer/BioNTech directly to pharmacies and healthcare providers/facilities.
“The greatest impact of BNT162b2 licensure may be direct supply to healthcare providers who serve vulnerable populations such as elderly patients and those who live in rural and underserved communities (ie, individuals who might be unable to navigate the challenges of securing vaccine access using the systems in place for EUA).
“Expansion of vaccine via licensure would ultimately improve the prospect of achieving population herd immunity to bring the pandemic under control.”
The same document glossed over the adverse effects for which the company previously admitted it hired a significant number of new employees to process, claiming:
“Based on Phase 1 data from the FIH Study BNT162-01, BNT162b1 and BNT162b2 [various vaccines tested during the trial period] were safe and well-tolerated in healthy adults 18 to 55 years of age, with no unanticipated safety findings.
“Phase 2/3 safety data were generally concordant with safety data in Phase 1 of the study, both overall and with regard to younger and older participants.”
This is despite hard figures regarding adverse reactions provided later in the document:
“Through 28 February 2021 (data lock point aligned with Pharmacovigilance Plan), there were a total of 42,086 case reports (25,379 medically confirmed and 16,707 non-medically confirmed) containing 158,893 events. Cases were received from 63 countries.
“Consistent with what was seen in Phase 2/3 of Study C4591001, most reported AEs were in System Organ Classes (SOCs) with reactogenicity events: general disorders and administration site conditions (51,335), nervous system disorders (25,957), musculoskeletal and connective tissue disorders (17,283), and gastrointestinal disorders (14,096).
“Post-authorization data have also informed the addition of adverse drug reactions (ADRs) related to the experience of reactogenicity to the product labeling.”
Release of Pfizer vaccine documents still in progress
Many of the documents released as part of the April 1 tranche appear to include more mundane information and data related to the Pfizer COVID vaccine trials.
These documents include:
- Peer-reviewed scientific articles funded by Pfizer-BioNTech, titled “Phase 1/2 Study of COVID-19 RNA Vaccine” (August 2020) and “Safety and Immunogenicity of Two RANA-Based Covid-19 Vaccine Candidates,” published in the New England Journal of Medicine in October 2020.These studies supported “further evaluation of this mRNA vaccine candidate” despite the apparent appearance of serious adverse effects in one of the 12 participants receiving 30 μg and 100 μg doses of the BNT162b1 candidate vaccine during the trial phase. This, however, does not appear to have been the final vaccine formulation that ultimately received an EUA.
- A questionnaire that vaccine trial participants were required to complete, along with a study book displaying the information to be collected from those participating.
- Documents outlining the randomization scheme used for identifying vaccine trial participants and those who received doses of the vaccine or a placebo.
- Documents listing anonymized demographic characteristics of vaccine trial participants.
- An anonymized listing of important protocol deviations.
- Consent forms that vaccine trial participants were asked to complete, as well as other related documents submitted by Pfizer for Institutional Review Board (IRB) approval, and information regarding institutions participating in the IRB process.
- Clinical study approval forms.
- Audit certificates for vaccine trial locations.
The next set of documents — an expected 80,000 pages — is scheduled to be released on or before May 1.
Michael Nevradakis, Ph.D., is an independent journalist and researcher based in Athens, Greece.
Vaccine Myocarditis: Mystery Solved?

Covid vaccine myocarditis: the catecholamine hypothesis (Cadegiani)
Swiss Policy Research | April 3, 2022
A Brazilian investigator may have identified the mechanism driving mRNA vaccine myocarditis. And the US CDC finally acknowledges the strongly increased risk in young males.
What is causing vaccine myocarditis?
What is causing post-vaccination myocarditis, and why does it affect primarily young adults, especially young males and athletes? It has been speculated that in young males, muscle blood flow may be higher, which may cause higher biodistribution of vaccine mRNA or spike protein. The mRNA or spike protein may then be absorbed by the heart muscle and cause inflammation.
But Brazilian investigator Flavio Cadegiani, who previously looked into the role of androgens (male sexual hormones) in covid, recently proposed a new and highly intriguing theory: Based on autopsy findings, Cadegiani noted that post-vaccination myocarditis appears to be very similar not to typical myocarditis (e.g. viral myocarditis), but rather to adrenergic myocarditis or catecholamine-mediated stress cardiomyopathy (i.e. heart muscle injury caused by catecholamines).
Catecholamines are a group of hormones that include, most notably, dopamine, adrenaline and noradrenaline. These hormones drive the “fight-or-flight response”, and their concentration is highest in young adults, especially in young males and athletes. Cadegiani notes that the adrenal glands (located on top of the kidneys) are amongst the tissues with highest production of spike protein from mRNA covid vaccines, which can cause local inflammation and may lead to a “catecholamine storm”, which is known to have a toxic stress effect on heart muscle cells.
Prior to covid mRNA vaccinations, this type of heart injury was seen almost exclusively in patients with a rare tumor of the adrenal gland (called pheo-chromo-cytoma). Cadegiani suspects that mRNA vaccination is more likely to affect adrenal glands than a mild coronavirus infection, especially in young and healthy adults.
Cadegiani (February 2022): Catecholamines are the key trigger of mRNA SARS-CoV-2 and mRNA COVID-19 vaccine-induced myocarditis and sudden deaths. (ResearchGate)
New CDC study on myocarditis
In a newly published study covering data from 40 US health care systems and about 15 million people, the US CDC purports to show that “the risk for cardiac complications was significantly higher after SARS-CoV-2 infection than after mRNA COVID-19 vaccination for both males and females in all age groups”, which “supports the continued use of recommended mRNA COVID-19 vaccines among all eligible persons aged ≥5 years.”
But the actual data provided by the CDC tells a very different story.
First, the US CDC confirms that among males aged 12 to 17, the rate of diagnosed myocarditis or pericarditis after the second vaccine dose is 1 in 4,500 to 1 in 2,700, and in males aged 18 to 29, the rate is 1 in 15,000 to 1 in 6,600.
These values are significantly higher than anything previously acknowledged by the CDC, but they still only include cases diagnosed by a doctor or in a hospital. If undiagnosed and unrecognized (subclinical) cases of myocarditis and pericarditis are taken into acccount, the rate will likely reach about 1 in 1,000 in young males. Even an undiagnosed case of myocarditis can turn out to be fatal, as the many recent cases of athletes with sudden cardiac arrest have shown.
However, the CDC argues that the risk of diagnosed myocarditis and pericarditis is still higher after SARS-CoV-2 infection, viz. 1 in 2,000 to 1 in 1,500 in males aged 12 to 17, and 1 in 1,800 to 1 in 1,000 in males aged 18 to 29. But previous studies, both in the US and in Europe, have already shown that the incidence of myocarditis remained normal or even below average during major covid waves in 2020 and early 2021 and only increased during vaccination campaigns in 2021 (see chart below).
So what did the CDC get wrong? It’s a classic mistake (or trick): while the CDC speaks of “SARS-CoV-2 infections”, they in fact only captured positive tests and only within the health care system (i.e. at a doctor’s office or in a hospital). SARS-CoV-2 infections were not captured “if testing occurred in homes, schools, community sites, or pharmacies”, or, one may add, if no testing at all occurred. Thus, the CDC captured only a fraction of actual infections (perhaps 10% or even less), and they likely captured only the most severe infections (i.e. young adults who visited a doctor or a hospital).
(In a somewhat related development, the CDC recently reduced US child covid deaths by 25%, as these deaths, while testing positive, had nothing at all to do with covid.)
But the CDC made another basic mistake: not only is the risk of myocarditis/pericarditis after vaccination in young males higher than after infection (as already shown by several other studies), but vaccination doesn’t prevent infection, either, and there is still no evidence that vaccination reduces the risk of post-infection myocarditis in young adults. In other words, the risk after vaccination simply increases the already existing risk after infection.
To make matters even worse, the CDC study considered only the first two doses of covid vaccination, whereas some US colleges and universities have already mandated a third dose for their students, adding even more risk. In fact, a booster dose may well increase the total risk of myocarditis and pericarditis to more than 1 in 1,000 in otherwise perfectly healthy young males. And as a recently published cardiac MRI study has shown, heart abnormalities in adolescents with mRNA vaccine myopericarditis may persist for at least several months.
In conclusion, the forced covid vaccination of young and healthy adults and children may constitute the largest medical scandal, or medical crime, in modern history. Based on the currently available evidence, covid vaccination is only appropriate in people at significant risk of severe acute covid.
CDC (April 2022): Cardiac Complications After SARS-CoV-2 Infection and mRNA COVID-19 Vaccination (CDC/MMWR)
Figure: Myocarditis and Covid Vaccination in the Western US

Myocarditis and Covid Vaccination in the Western US (JAMA )
CDC massages its data in order to terrify parents into vaccinating their babies and preschoolers
By Meryl Nass, MD | March 19, 2022
This story is about a particularly vile piece of disinformation CDC issued today to push vaccines on the most vulnerable, those humans who are too tiny to say no.
As I have noted periodically for twenty years, and it was roundly confirmed 4 weeks ago in the NY Times, CDC cherry-picks the data it presents to the public, hiding most of what it has. Then it blames its ‘outdated’ IT systems for the problems. As the NYT noted,
The CDC has received more than $1 billion to modernize its systems, which may help pick up the pace, [CDC spokesperson] Ms. Nordlund said. “We’re working on that,” she said.
CDC is not a public health agency. It is a public propaganda agency that collects a massive amount of data. CDC marshals its massive data library to create presentations to support the current administration’s desired public health policies. CDC also has state of the art PR staff, as well as TV studios, and produces videos, radio spots and a massive number of press releases which are distributed to the media. CDC pays for getting its messages out. As we learned last year, it paid Facebook for messaging, while Facebook donated $millions in advertising back to CDC. Last March, Mark Zuckerberg stated,
We’ve already connected over 2 billion people to authoritative COVID-19 information, and today as access to COVID-19 vaccines expands, we’re going even further and aiming to help bring 50 million people one step closer to getting vaccinated.
While CDC collects data from a much larger sample size, it often, as in this case, only presents part of its dataset, and/or (as in this case) CDC chooses a specific, limited timeframe from which to select its data.
The story that CDC is crafting today is that tiny children, under the age of 5, have been recently hospitalized at extremely high rates due to COVID, and therefore need to be vaccinated as soon as the vaccine is authorized for them.
- Whereas, the true story is that most children have now been exposed to COVID and are therefore already immunized. Multiple studies have revealed that you are at higher risk of a vaccine-induced adverse reaction if you are already immune–but CDC cleverly never mentions that to parents.
- Many other studies show the immunity derived from exposure is much stronger and long-lasting than from vaccination.
- While a new theory gaining ground is that vaccination after infection may actually narrow and weaken the protection derived from COVID immunity.
Pediatric hospitalizations are now CDC’s golden metric, because, since it has been shown the vaccines do not prevent infection or viral transmission, CDC had to stop saying getting vaccinated protects granny, because it doesn’t. But CDC didn’t let that slow them down. They immediately pivoted to creating stories about preschooler hospitalizations, even though they are rare. Let’s see how this is done.
This current issue of the CDC’s in-house journal, the MMWR, not only discusses hospitalization rates, but provides a downloadable poster that it hopes will be placed in pediatric clinics throughout the country. Here it is:

Hospitalizations five times as high! That’s terrible! Omicron must be much more severe for preschoolers than we were led to believe!
But wait a sec. Let’s compare the pediatric Delta wave with the Omicron wave using the data CDC provides.
The Delta wave lasted longer than Omicron but had fewer cases at any one time. Delta’s wave looked those old graphs of ‘flattening the curve,’ while Omicron, being much more contagious, had a much taller peak while its wave ended much more quickly (what you would supposedly see if you didn’t flatten the curve). Actually, Omicron proved that all the gibberish about vaccines and masks and distancing couldn’t flatten Omicron’s curve at all. But I digress. The Delta wave led to about a third more pediatric hospitalizations overall than Omicron in CDC’s dataset (790 vs 572), but they occurred over a longer time frame.
CDC selected their best data for the age group that they hope to immunize soon, as soon as possible after an EUA is issued for them. Here is how CDC attempts to explain its cherrypicking in its article. While all hospitalizations were reviewed up until December 2021, for December and January 2022:
“some sites examined clinical data on a representative sample of hospitalized infants and children.”
Oh, really? You mean CDC pays hospitals to send all their data to COVID-Net, then CDC lets them choose only a ‘representative sample’ during Omicron’s peak to send? I don’t think so. If CDC contracted and paid for a full dataset, believe me it is getting a full dataset. No self-respecting journal editor would let CDC get away with this.
In fact, the CDC had already planned the baby-toddler vaccine campaign for February, but had to postpone it when FDA delayed the authorization process on February 10. It turned out the Pfizer trial supported neither a reduction in cases nor sufficiently high antibody levels in the 2 through 4 year olds to meet the pre-specified titer required.
FDA was probably hoping to issue an EUA anyway. It had an advisory committee meeting scheduled for February 15 to vote on the proposal–until data from vaccinated 5-11 year olds in NY state (about 365,000 of them) showed the vaccine didn’t work, after only a few weeks. Somehow, some way, the lid was kept on this information after it had been presented to FDA and CDC in early February. But the story got out in a preprint and in the NY Times on February 28, which wrote:
The coronavirus vaccine made by Pfizer-BioNTech is much less effective in preventing infection in children ages 5 to 11 years than in older adolescents or adults, according to a large new set of data collected by health officials in New York State — a finding that has deep ramifications for these children and their parents.
After about 6 weeks, protection against hospitalization dropped from a purported 100% to 48% in the 5-11 year olds, and protection against infection had dropped to a miserable 12%.
I don’t think FDA could then deal with pushing vaccine on preschoolers when it wasn’t working in the elementary school kids, whose dose was over 3 times higher. FDA decided to wait until Pfizer waved its magic wand and produced better data. Brook Jackson can explain how that happens.
I’m guessing that in response to the abominable data, CDC spun up its spin doctors, resulting in this March 18, 2022 publication and poster.
Below is Table 1 from CDC’s March 18 paper, published in its very own, non-peer-reviewed journal, the MMWR. Publishing in its own journal lets CDC get its messages out quickly, and protects CDC’s “science” from external reviewers’ criticisms and comments.
Since the beginning of the pandemic, there were a total of 2,562 children aged under 5 years who were hospitalized with COVID in CDC’s COVID-Net catchment groups in 14 states. They comprised CDC’s data collection. Nearly half (44%) of the hospitalized children were under 6 months of age, and would be too young to be vaccinated under the proposed EUA anyway.
The average length of their hospitalizations was 2 days during the Delta wave and 1.5 days during the Omicron wave. Sounds like most kids were not that sick. The deaths were the same for both Delta and Omicron: 0.5% of the children who required hospitalization died during each wave, although CDC carefully fails to tell us about comorbidities in the children who died or required ICU care. While it is true that there were more hospitalizations per week during the omicron peak than during the delta peak, this happened because cases were compressed into a smaller time period for Omicron, since the virus whizzed rapidly through the population. It took longer for Delta to reach its peak and trough, though there were, in total, more pediatric hospitalizations due to Delta than to Omicron.
CDC managed to spin these data into an appearance of terrible danger for little kids: 5 times as many hospitalizations for Omicron than Delta–but only if you parse the data by week rather than by wave. And if you parse the data by total number of cases (the area under the curve for each wave) there were many fewer hospitalizations per the number of cases for Omicron than for Delta. (I have posted a NY Times graph, which uses CDC data for cases, at the bottom of this article.)
Now that the Omicron wave is over, hospitalizations are way way down. CDC isn’t making that part of its message, even though its article came out today and the data have been available for several weeks. Telling us the current risk for kids is close to zero would ruin the narrative.
I have to vent about one more thing. I am really angry about a lie that CDC placed in its blue poster above. It says, “Get vaccinated to help protect yourself and those too young to be vaccinated.” Except, since the vaccine does not prevent you catching the disease nor spreading it, how could vaccination protect those too young to be vaccinated? It doesn’t, and we have known that since at least last October, when Boris Johnson and Rochelle Walensky started to admit it.
Grasping for talking points, despite being able to spin the data however it pleased, I guess CDC just could not shake itself loose from all its lies…
The bottom line is that the vaccine, designed for the original Wuhan virus, doesn’t do the job—and does it even less well in children. Although the safety data in children are very limited due to the tiny numbers enrolled in Pfizer’s trials, we know from older children and adults, using the Vaccine Adverse Event Reporting System, managed by CDC and FDA, that COVID vaccines are the most dangerous vaccines ever used on a mass scale.
By giving manufacturers a vast liability shield, the federal government has incentivized them to rush out their products and provide only the most minimal safety testing—because the way the law is writtten, they can only be charged with willful misconduct if they knew in advance of their products’ flaws.
Parents whose children are injured by experimental COVID vaccines will never forgive themselves. Please don’t be one of them.


Featured Video

Iran & Its Allies Are Threatening Every Route for Saudi Oil
or go to
Aletho News Archives – Video-Images
From the Archives
A short history of British torture
ICC | December 2005
When the House of Commons was debating how much to increase the time limit for detention without trial the question of torture came up. Officially this was limited to the nice considerations of whether it was all right to send people to places where torture is used and whether Britain can use information collected by the use of torture in other countries. This discussion gave an impression of democratic Britain as the home of civilised behaviour where the very idea of torture is repugnant to our legislators – unlike, say, the US with its secret CIA jails… In reality, the British state has a long history of using and developing a whole range of torture techniques. … continue
Blog Roll
 Aletho News
- House Votes to End Iran War for Third Time
- North Korea Slams US Plan for ‘AUKUS 2.0’ with South Korea and Japan
- Prolonging US-Iran Conflict Not Meeting Interests of Int’l Community – China’s Wang Yi
- EU bans former Zelensky aide from parliament
- NATO-backed Kosovo separatist ‘responsible for war crimes’
- US destroying international space law
- SCO Calls for Binding Global Deal to Prevent Arms Race in Space
- Iran & Its Allies Are Threatening Every Route for Saudi Oil
- ‘40,000 tons of bombs’: Report shows Trump planning ‘largest bomb transfer in modern US history’ to Israel
- Amazon says cloud infrastructure in Bahrain, UAE ‘beyond saving’
- If Americans Knew
- Groups urge Americans to support Van Hollen legislation on Israel’s killing of Americans & Palestinians
- Trump administration plans to send 40,000 tons of bombs to Israel: report
- Sanctions Target Iran’s Government, But Kill Hospitalized 23-Year-Old Woman
- An alternative view on the book “Israel’s Lobby: America in the Grip of a Foreign Power”
- Ed Sheeran’s band Beoga, other opening acts quit tour after Macklemore was dropped over his pro-Palestinian comments
- The assassination attempt on President Trump in Butler and the various Israeli connections to it
- “We Want That the Whole Land Be Jewish”
- BREAKING: Building collapse in Gaza kills at least 20 as they sleep – Daily Update
- ‘School is Life’: 1.5 Million Palestinian Children Face Fourth Year of Shattered Education
- Pentagon admits Iran war caused ammunition shortages, cost US $33.4bn
- No Tricks Zone
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
- Fear Of Debate: Alarmist German Climate Scientist Calls On Mainstream Media To Discredit Skeptic Voices
- End-Of-August Arctic Sea Ice Extent Hasn’t Fallen In 20 Years, Official Data Show!
- News-Making Nepal Region Has Had As-Warm Or Warmer Periods Than The 2000s In The 1600s, 1700s, 1800s
 Aletho News
