Carrying our baggage into the apocalypse
By Richard Hugus | December 23, 2021
Almost two years in, the “Great Reset” has reached a certain stage of maturity. Years of planning, infiltration, manipulation, and social engineering have come to fruition. The many simulations are now being tested in the real world. The actors who trained and rehearsed for their parts as presidents, prime ministers, health officials, trusted doctors, and media personalities have taken their place on stage, miraculously prepared to save humanity from a catastrophe never experienced by mankind. The operation was always too big to go on covertly, so eventually the perpetrators had to announce their plans, the war had to be declared, and troops assembled on the field of battle.
We know more or less who the perpetrators are — the globalists, the central bankers, a certain megalomaniac software developer, eugenicists, pharmaceutical companies, Vanguard, Blackrock, the CIA, the Rothschilds, the Rockefellers, the Illuminati, the Freemasons, Satanists, aliens working on other wavelengths, and so on.
But what about the other side? Here we see people across the spectrum, very few wealthy or holding power, often oriented toward nation, home, family, personal responsibility, and religion — in other words, conservatives. Conspicuously absent from any resistance to the Reset are liberals and leftists, the anti-war and anti-imperialist left, so-called “progressives”, socialists, anarchists, and union leaders — the very people one thought would be the first to stand up against corporate tyranny and totalitarian control. Leftists opposing the Reset quickly became former leftists. This group spent the past two years dealing with what seemed the betrayal of a lifetime, as they watched their ideals of liberation from oppression carried to the point of absurdity. They watched anti-racism turn into racism, sexual liberation into gender chaos, anti-fascism into fascism. Opposition to all forms of discrimination gave way to support for discrimination . . . against the “unvaccinated.” Belief in “my body, my choice” somehow turned into support for no-choice medical mandates. The new radicals came like puppets of the state to disrupt medical freedom rallies, wearing face masks and calling people “Nazis” for not wearing them.

November 7, 2021, Boston Common.”Anarchists” protesting against a rally for medical freedom.
But then the disillusioned leftist realized that all this was actually consistent with socialism, in which the needs of the collective come before individual rights, and that the left actually has more in common with the utopian leaders of the World Economic Forum than it does with the virus-spreading working class who, afterall, were always too thick to understand the higher goals of socialism. In the surprise ending of the Great Reset, Act I the left revealed its true identity — they were the real authoritarians all along! But even with this revelation, the left lost none of its insufferable self-righteousness.
As devastating as the Great Reset operation could be for the future of humanity, it’s a wonder that we still carry our old grievances and prejudices with us. Millions of people have already been killed or injured by mRNA injections, yet different sides in the freedom movement can’t seem to get over their differences. The left has to come to terms with its delusions, but so does the right.
First of all, let’s acknowledge that with all the power the globalists have, it is inconceivable that both sides would not already be heavily infiltrated. The oligarchs would no doubt agree with their former client Vladimir Lenin when he said, “the best way to control the opposition is to lead it ourselves.” We can assume that many in the ranks of Antifa, for example, are undercover cops, FBI agents, informants, and temp work thugs. From Charlottesville in 2017 to the Black Lives Matter riots in 2020 to Boston Common in 2021, we saw them all in action, working in silent agreement with their supposed sworn enemy, the police.
We can also assume that people who look and talk just like Trump-supporting MAGA conservatives are also on the job, as witnessed in the obvious manipulation by agents working with police to entrap protesters in Washington D.C. on January 6, 2021. The left has been familiar with FBI infiltration since the COINTELPRO days of the ’60s. Conservatives becoming active in politics today may not have this experience. They could maybe learn a few things about agents provocateurs and, for that matter, be cautious about “backing the blue”, until they find out just which side “the blue” are actually on. Cops are generally known to serve the powerful. But conservatives don’t consult the left about their experience with the police. Nor is the left talking to conservatives about why wokeness isn’t providing any solutions. The two sides are not talking.
Anti-imperialists have been opposing US foreign wars since the Mexican War in 1846. The list of wars initiated by the US from then to now — criminal wars that had nothing to do with self-defense — is too long to list. Conservatives have generally supported US warmaking and, because of their patriotism, they honor and support the soldiers who fight the wars. But where was the honor in decimating Afghanistan and Iraq, to mention just two? Love of one’s country does not justify starving and bombing people in another country who never harmed the US. Anti-imperialists would not be surprised that the American empire may be about to pay a moral debt for its wars of aggression. They opposed the wars while patriots supported them, and there are some hard feelings there. The reckoning that seems to be coming to America will be hard for the patriots. But it will also be hard for the left when they realize that all along they have been the shameless dupes of the ruling class, who seduced them with high-sounding goals only to put them and everyone else into a prison where they the guards will have control of not only our bodies but our minds. If there was ever a time to fight fascism, this is it. But the left has been AWOL in this struggle, and that is a shame they may never live down.
The control of most of humanity by machines projected by the Great Reset will, if it comes true, make the disputes between left and right seem quaint. We’re going to have much worse problems if we don’t end this soon.
Shameless BBC hosts Big Pharma’s drive to get Africa hooked on Covid vaccine
By Rusere Shoniwa | TCW Defending Freedom | December 23, 2021
AT the end of November, a piece of BBC agitprop to stoke up fervour for vaccinating Africa went viral. As a British citizen of African descent living in London, I was disgusted by it.
I am concerned that people in Africa may ‘get it’ even less than the average Westerner and I really want to try to reach a few Africans who might be wondering what Covid could mean for them.
So let’s start by imagining if Big Pharma were to run a modestly honest advertisement to recruit dealers for pushing Covid ‘vaccines’ in Africa.
It might read something like this: ‘International drug cartel requires Western-educated Black face to front our public campaign to push experimental and unnecessary Covid vaccines on the impoverished African continent.
‘This is a tough market, highly suspicious of the product and not without good reason. Smile and dial merchants need not apply, as you must bypass the consumer to target the decision-maker.
‘Successful applicants must display the ability to rail melodramatically at the “racist vaccine-hoarding” injustices perpetrated by the West against Africa, appealing to the woke sensibilities of those in positions of power within key Western institutions. African leaders will then be expected to do as they’re told.’
I must confess that I reverse-engineered that ad after watching the successful applicant going through the motions like a performing seal on a BBC World News slot set aside for just such agitprop.
Following the latest Covid variant hype, the co-chair of the African Union’s Vaccine Delivery Alliance, Dr Ayoade Alakija, announced on the UK’s flagship propaganda organ: ‘What is going on right now (the emergence of the Omicron Variant) is inevitable.
‘It’s a result of the world’s failure to vaccinate in an equitable, urgent and speedy manner. It is a result of hoarding by high-income countries of the world and quite frankly it is unacceptable. These travel bans are based in politics and not science. It is wrong.’
Abandoning any pretence at journalism, the BBC presenter, Philippa Thomas, played the role of therapist by responding: ‘I hear your anger about the immediate reaction and the lack of action beforehand.’
The stage direction becomes even more obvious and cringeworthy as Thomas then pauses, providing a cue for the good doctor to glance at her script and resume the televised amateur dramatics: ‘So this is hopefully a dress rehearsal because until everyone is vaccinated no-one is safe … why are the Africans unvaccinated? It’s an outrage because we knew we were going to get here.
‘We knew this is where the hoarding, the lack of IP (intellectual property rights) waivers, the lack of co-operation on sharing tech and sharing know-how, we knew this was the crossroads it was going to bring us to. To a more dangerous variant.’
The only valid question she raises concerns the swift travel bans placed on Southern African countries: ‘Why are we locking away Africa when this virus is already on three continents? Nobody is locking away Belgium, nobody is locking away Israel.’
This is an emotional ploy to gain the trust of the small handful of privileged Africans watching this drivel. She is saying to them: ‘I am right-on, woke, one of you.’ She quickly jumps back on board the Covid cult train with a policy ‘nudge’ that must have African leaders reaching for their sickbags.
‘Something needs to be done to everywhere. My recommendation is to have a co-ordinated global shutdown of travel, for the next month if you want, but don’t single out Africa.’
And then back to the greedy, vaccine-hoarding West: ‘The Botswana government ordered 500,000 doses of vaccines at 29 dollars per dose, much higher than the rest of the world paid. They did not get those vaccines because other people jumped ahead in the queue. Moderna supplied to other countries … and so now we have a variant.’
Not a single grain of this guerrilla marketing campaign was challenged by the BBC journalist.
The obvious starting point for a presenter with half an ounce of journalistic integrity would be to explore whether the ‘vaccines’ are working and whether they would indeed have prevented a variant. After all, the fact that they do not halt transmission and infection is no longer controversial.
No sales pitch involving an illness would be complete without recourse to fear-based marketing tactics. Enter the Omicron narrative.
Despite Dr Alakija’s claim that we now have ‘a more dangerous variant’, there was no evidence that this variant would make any difference to disease severity at the time she was invited by the BBC to make her vaccine sales pitch for Africa. (Nor is there proof that vaccination prevents variants from arising in the first place).
Since then, the evidence emerging is that Omicron is less severe than previous variants and more contagious – the ideal combination for hastening herd immunity with minimal population health impact.
Telling medium-sized lies and half-truths with a straight face has always been the minimum qualification for political office, but Covid has raised the bar to a new height – the ability to swim in a pool of one’s own metaphorical vomit without flinching.
The BBC ‘discussion’ might have turned to safety, to tease out how much personal risk Africans will be expected to bear in submitting to a vaccine that doesn’t perform the primary function of a vaccine.
The word ‘safety’, however, was not permitted to impinge in any way on the protestations of the injustice of depriving Africans of the wondrous medical treatments emanating from the hallowed laboratories of Western science.
The reticence about safety is understandable from a marketing perspective since, by any objective measure, these ‘vaccines’ are the most dangerous mass medications rolled out in modern history.
Perhaps Dr Alakija should have been quizzed about how Africans might react to the drug manufacturers’ lack of confidence in the safety of their own products in light of their refusal to distribute it to countries who refuse to provide blanket immunity from liability for injury.
Not a single word of safety information was explored, even in the vaguest terms, in the BBC report. Nothing. Juxtapose studies highlighting the risk of dangerous heart inflammation for young males following Covid vaccination against Africa’s far younger population, with a median age of around 20.
You’d think this safety risk might get a passing mention. Yet neither of the two stooges saw fit to broach the prospect that many young Africans – whose risk of dying from Covid is so small that it is hard to measure – may die following vaccination.
The callousness of this omission is standard operating procedure in Western liberal discourse, a key function of which is to drape a ‘humanitarian’ cloak over policies that enrich corporate interests in the West while harming and exploiting the poor.
Unveiling the farce of the BBC plug for Africa’s vaccination allows us to consider a game in which we imagine what other doctors might say if the BBC were to air credible dissenting voices – a practice that was once regarded as the bread and butter of journalism, but which would now be a radical act of rebellion.
It’s not a difficult game to play. In fact, no imagination is required, because the actual statements of credible dissenting doctors are available on other independent media news channels, as reported in TCW Defending Freedom on December 8.
A new channel based in Austria, AUF1, gives a platform to those medical professionals who refuse to go along with the official narrative.
Typical is Dr Heiko Schöning, who says: ‘The corona panic is a stage-managed production. It’s a confidence trick. It is now urgent that we understand we are now in the grip of a worldwide Mafioso-style criminal enterprise. We can see we are dealing here with organised crime. So what do we do? We don’t play along any longer. Here and now we have to draw the red line.’
Had Dr Schöning just finished watching the two stooges on BBC World News when he described ‘the corona panic’ as ‘a stage-managed production’?
Whether these doctors are right or wrong is irrelevant to the journalistic duty to present credible dissenting voices to the public. The failure to do so goes a long way to meeting the criteria for propaganda.
The question in relation to Dr Alakija’s BBC guerrilla marketing campaign is: Do enough Africans know that there are alternative credible narratives to challenge the mainstream BBC vaccine narrative and how would they respond if these competing narratives were presented?
Does Africa, or anywhere else for that matter, need mass vaccination? Almost two years into this global nightmare, with evidence showing that up to 80% of South Africans (how similar for other African nations?) may have already been exposed to the virus, less than 6% of Africa vaccinated, and a death toll a fraction of that in the ageing populations of the West (Africa’s Covid deaths are 3% of the global total), it is clear that Africa has already learnt to live with the virus.
Had Africans succeeded in applying the same level of rigorous lockdown stupidity that was achieved in the West, it would not have made the slightest difference, as real science is conclusively demonstrating not just the futility of lockdowns but their positive destructiveness.
Despite looser lockdowns (perhaps partly because of this) Africa fared much better than the illiberal West in health outcomes.
No doubt there are other variables at play, but cheap, effective early treatments in some parts of Africa were used to good effect and should continue to be the focus of attention.
Africa and the entire planet would get far more bang for their buck from policies addressing human health holistically rather than with expensive experimental ‘vaccines’ which will continue for as long as human beings are prepared to, or more likely forced to, surrender their bodies to Big Pharma and authoritarian governments.
It must be patently obvious to African leaders that the Covid crisis is a manufactured one, but that does not make it any less of a crisis.
Western liberal democracy is being dismantled at breakneck speed under the cover of Covid containment policies.
The criminality, coercion, censorship, propaganda and blatant negligence all signal the logical conclusion to a brutal colonial mindset – the attempted colonisation of the entire globe to serve the interests of a global elite which has successfully captured Western governments and supranational organisations.
The psychopaths whose aim is to introduce a technocratic global system of human control understand only too well that shutting off travel for economies that rely on tourism is a far bigger killer of economies, and therefore lives, than this virus has ever been.
The message being sent by the sadistic controllers to Africa’s leaders is a simple one: Get serious about imposing vaccines and the technocratic population control measures for which which vaccines are the delivery system … or else.
Covid containment policies represent a desperate authoritarian response to permanent decline. This cannot end well for the West and if the West is a sinking ship, then Africa must not blindly tether itself to this Titanic disaster.
Pfizer, FDA Dodge Media Questions About Pfizer Comirnaty Vaccine
By Seth Hancock | The Defender | December 22, 2021
Two media outlets last week requested, but failed to obtain, clarity from Pfizer on whether its fully licensed Comirnaty COVID vaccine is available in the U.S.
Reporting by The Ohio Star and National File highlighted the ongoing debate over whether the vaccine can legally be mandated, and whether Pfizer can be held liable for injuries related to the vaccine.
The Star reported that despite asking multiple times whether the Comirnaty vaccine is in use, Pfizer would not answer the question.
The U.S. Food and Drug Administration (FDA) in August granted full approval, or Biological License Application Approval (BLA) — for the Comirnaty vaccine for individuals age 16 and older.
The approval, granted without a formal advisory committee meeting or public comments, prompted a number of questions including:
- What, if any, differences exist between the formulations used in the fully licensed Comirnaty vaccine and the Pfizer-BioNTech vaccine being distributed under Emergency Use Authorization (EUA).
- If/when the fully licensed vaccine would be available in the U.S.
Seeking an answer to the latter question, The Star reached out to Pfizer, the FDA and to Ohio’s largest health system, OhioHealth.
A spokeswoman for OhioHealth confirmed the system’s 12 hospitals “are currently distributing the Pfizer vaccine that does not have the Comirnaty branding label.”
In response to whether the Comirnaty vaccine is being used elsewhere in the U.S., Pfizer told The Star in an email:
“The Pfizer-BioNTech COVID-19 Vaccine (EUA labeled product) is currently being shipped; however, please be advised that the COMIRNATY and the Pfizer-BioNTech COVID-19 Vaccine have the same formulation and can be used interchangeably. They are made using the same processes, and there are no differences between them in safety or effectiveness.”
Pfizer’s claim that the two vaccines can “be used interchangeably” is inconsistent with FDA statements, The Star said, citing an FDA Q&A page that states the two vaccines are “legally distinct.”
The FDA reaffirmed that distinction, telling The Star the “statutory authorities governing BLAs and EUAs are distinct and provide different legal requirements.”
The FDA “did not directly address” The Star’s initial question about the specific difference between Comirnaty and the EUA vaccine, or why Pfizer is not shipping Comirnaty if the formulas are “interchangeable.”
However, in a Dec. 9 notice of reissuance of the EUA for the original Pfizer vaccine to give booster shots to 16 and 17-year-olds, the FDA said:
“[a]lthough COMIRNATY (COVID-19 Vaccine, mRNA) is approved to prevent COVID-19 in individuals 16 years of age and older, there is not sufficient approved vaccine available for distribution to this population in its entirety at the time of reissuance of this EUA.”
The Star also reached out to Ohio Attorney General Dave Yost, asking if Ohio’s public universities are following the state’s law, HB 244, which prohibits public institutions from mandating a vaccine that is not fully approved.
Bethany McCorkle, Yost’s communications director, responded that HB 244 does not apply because “the FDA fully approved the vaccines.”
National File, following up on The Star’s reporting, also contacted Pfizer to ask if Comirnaty is in use. Pfizer told National File the “EUA-labeled product will still be shipped and usable until its expiry date.”
Pfizer did not respond to National File’s follow-up requests for additional clarification.
Comirnaty ‘not available at this time’
According to the Centers for Disease Control and Prevention (CDC), a chart showing the current procedural terminology description for the Comirnaty BLA-licensed vaccine states Comirnaty is “not orderable at this time.”
The current procedural terminology description includes a statement from Pfizer:
“At present, Pfizer does not plan to produce any product with these new NDCs (National Drug Code) and labels over the next few months while EUA authorized product is still available and being made available for U.S. distribution. As such, the CDC, AMA (American Medical Association), and drug compendia may not publish these new codes until Pfizer has determined when the product will be produced with the BLA labels.”
According to a Dec.16 letter from the FDA’s acting chief scientist, Jacqueline A. O’Shaughnessy, Pfizer-BioNTech vaccines exported from the U.S. are allowed only if “the regulatory authorities of the country in which the vaccine will be used are fully informed that this vaccine is subject to an EUA and is not approved or licensed by FDA.”
O’Shaughnessy’s letter states there is “a significant amount of Pfizer-BioNTech COVID-19 Vaccine that was manufactured and labeled in accordance with this emergency use authorization. The authorization remains in place with respect to the Pfizer-BioNTech COVID-19 Vaccine for this population.”
In a Twitter exchange last weekend, Rep. Thomas Massie (R-Ky.) cited O’Shaughessy’s letter to refute a tweet by Joe Gerth, a columnist for the Louisville Courier-Journal, who claimed Comirnaty is available.
Can vaccines be ‘interchangeable’ and ‘legally distinct’ at the same time?
Misrepresentations by media and public officials — like those of the Louisville Courier-Journal and Ohio attorney general claiming the Pfizer vaccines in use in the U.S. are FDA-approved — coupled with the FDA’s own ambiguous documents and public statements have given rise to public confusion and legal questions.
Pfizer’s refusal to directly address questions posed by The Ohio Star and National File only adds to the lack of clarity. As political commentator and attorney Robert Barnes told The Star :
“It is an illicit bait and switch. There is no FDA-approved COVID-19 vaccine available in the U.S. The unavailable FDA biologic license approved drug is not medically identical and has to abide different manufacturing standards. As important, you have fewer legal rights and fewer legal remedies when you take an EUA drug than a biologic licensed drug. This directly impacts the legal rights of all Americans.”
The FDA’s assertion that the Comirnaty and Pfizer vaccines are “legally distinct” yet “interchangeable” is at the center of legal arguments around whether one, both — or neither — of the two vaccines can be mandated.
A lawsuit brought by members of the military against the U.S. Department of Justice (DOJ) challenging the DOJ’s COVID vaccine mandate for all service members highlights some of the arguments.
A federal judge on Nov. 12 denied plaintiffs’ request for a preliminary injunction against the DOJ mandates.
However, in his ruling, the judge stated — contrary to claims by Pfizer and the FDA — that the FDA-licensed Comirnaty vaccine is not interchangeable with Pfizer-BioNTech’s EUA-labeled vaccine.
Judge Allen Winsor of the U.S. District Court for the Northern District of Florida said the service members showed the U.S. Department of Defense (DOD) is requiring them to submit to EUA-labeled vaccines, yet “defense counsel could not even say whether vaccines labeled ‘Comirnaty’ exist at all.”
Judge Winsor wrote:
“In the DOD’s view, this is fine because the contents of EUA-labeled vials are chemically identical to the contents of vials labeled ‘Comirnaty’ (if there are any such vials). According to the DOD’s argument, this means servicemembers are not required to accept ‘a product authorized for emergency use.’ …
“Rather, the DOD argues that once the FDA licensed Comirnaty, all EUA-labeled vials essentially became Comirnaty, even if not so labeled. Thus, the DOD argues, the ‘product’ injected is a chemical formulation that has received full FDA licensure — not merely an EUA.”
Judge Winsor called that argument “unconvincing.”
The distinction between an EUA product and one that is fully licensed raises other legal questions. For instance, the FDA fact sheet on the Comirnaty vaccine states:
“This EUA for the Pfizer-BioNTech COVID-19 Vaccine and COMIRNATY will end when the Secretary of HHS determines that the circumstances justifying the EUA no longer exist or when there is a change in the approval status of the product such that an EUA is no longer needed.”
The statement appears to suggest the Pfizer-BioNTech and Comirnaty vaccines are EUA, and that both EUAs will end under the conditions noted.
Another key difference between fully licensed and EUA vaccines relates to the issue of liability. Under the 2005 Public Readiness and Preparedness Act (PREP Act), EUA vaccines are accompanied by a far-reaching liability shield that protects all parties involved with the product from lawsuits.
Specifically, if one is injured by an EUA vaccine, the only way to claim damages and receive compensation is to apply to the Countermeasures Injury Compensation Program, an administrative process under the U.S. Department of Health and Human Services (HHS), which authorized the vaccines.
At this time, the Pfizer Comirnaty vaccine may have no liability shield, making it subject to product liability laws that allow those injured by it to potentially sue for damages, although Pfizer asserts the vaccine is protected under the PREP Act as well.
Children’s Health Defense, following the Comirnaty approval, sued the FDA arguing the approval was a “bait in switch” to provide cover for vaccine mandates.
Seth Hancock is a freelance reporter for The Defender.
© 2021 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Pfizer Vaccine Clinical Trials Poorly Designed From the Start, Analysis Shows
By Madhava Setty, M.D. | The Defender | December 22, 2021
The disagreements around whether COVID-19 vaccinations are “safe and effective” stem not only from the subjective nature of such descriptors but also from the lack of consensus around the data used to substantiate or refute such a claim.
The Centers for Disease Control and Prevention’s (CDC) Morbidity and Mortality Weekly Reports (MMWR) often draw from limited observations, and their assessment of vaccine effectiveness is based on relatively small subsets of our population.
Their conclusions are sometimes reflective of outdated data and conflict with their own recommendations.
For example, here the CDC’s latest estimation of vaccine effectiveness is upwards of 80% in preventing COVID-19 (i.e. the risk of becoming infected is 5 times less if vaccinated). Why then the recommendation for boosters?
Note that this latest metric is based on the CDC’s most recent data from more than one month ago and represents data drawn only from 27 jurisdictions.
Eric Topol, a professor of molecular medicine at Scripps Research, is a former advisory board member of the Covid Tracking Project, a team that worked to collect and synthesize local COVID-19 during the peak of the pandemic.
Politico recently quoted Topol:
“I think we’ve done a horrible job from day one in data tracking for the pandemic. We’re not tracking all the things that we need to to get a handle on what’s going on. It is embarrassing.”
Meanwhile, vaccine injuries continue to accumulate in the Vaccine Adverse Event Reporting System (VAERS) and go unacknowledged, making any constructive discussion around risk impossible.
In order to find common ground, it is perhaps most appropriate to focus on published data from the vaccine trials themselves.
Was Emergency Use Authorization justified? Was the current confusion around vaccine effectiveness and safety predictable from the beginning?
A presentation by the Canadian COVID Care Alliance
Canadian COVID Care Alliance (CCCA) is a group of “Independent Canadian doctors, scientists and healthcare professionals committed to providing top quality and balanced evidence-based information to the Canadian public about COVID-19 so that hospitalizations can be reduced, lives saved and our country restored as safely as possible.”
CCCA assembled a presentation that comprehensively demonstrates how Pfizer’s purported randomized placebo-controlled, double-blinded study veered away from methodologies that would have answered the safety and efficacy questions definitively.
In this concise slide deck with an explanatory video, CCCA powerfully summarized why Pfizer’s trial was not designed to adequately demonstrate its product’s safety and efficacy.
Here are a few key points from the CCCA presentation:
- Initial data demonstrated a high relative risk reduction of infection yet this amounted to an absolute risk reduction of only 0.84%. It is the absolute risk reduction that determines the risk-benefit ratio required to make informed decisions around inoculation.
- Early unblinding: Several months before publishing six-month observational results Pfizer opted to offer its product to those participants who received the placebo. By eliminating nearly all participants in the placebo wing Pfizer effectively closed the curtain on its experiment because long-term comparisons can no longer be made.
- All-cause mortality and morbidity, the only sensible outcomes to use in determining efficacy and risk, were not considered. Indeed, all-cause mortality was higher in the vaccinated group after six months.
- Severe adverse events outnumbered cases of severe COVID prevented after six months of observation.
- Trial participants were not reflective of the most vulnerable members of our population — more than 50% of people dying from COVID are 75 years of age or older. This age group made up only 4.4% of trial participants. Also, 95% of those who have died from COVID had one or more comorbidities. Nearly 80% of trial participants had none.
- Not every trial participant was tested for COVID. Asymptomatic or paucisymptomatic (presenting few symptoms) cases were missed.
Questions regarding unblinding and data integrity
The CCCA presentation also resurrects a puzzling observation mentioned in a briefing document Pfizer submitted only to the FDA’s Vaccine and Related Biologic Products Advisory Committee (VRBPAC) of the FDA, but nowhere else — including the widely cited summary of the trial reported in New England Journal of Medicine.
According to the document, 3,410 participants were suspected from their clinical presentation of having COVID but they were excluded from efficacy calculations because a diagnosis could not be confirmed through PCR testing.
The CCCA presentation presumes this large group of participants was never tested. The wording in the VRBPAC briefing document is indeed vague, stating the participants were “not PCR-confirmed” in one sentence and “unconfirmed” in another.
Assuming Pfizer’s investigators followed their study protocol, these participants were in fact tested. Yet that forces us to accept that more than 3,400 participants who had symptoms of COVID were suffering from other illnesses, not COVID.
In other words, there were 3,580 participants who clinically presented with COVID (3,410 suspected and 170 confirmed). Of these, more than 95% tested negative. This is difficult to accept in a group where clinical suspicion is high.
However, with no further testing by the investigators, we are left to accept these numbers as reported.
Peter Doshi, Ph.D., senior editor at The BMJ, explained the implications of this result in detail, in an opinion piece published nearly one year ago.
In his widely discussed commentary, Doshi noted another baffling finding in the Pfizer data. Within 7 days of administration of the second of two doses, 371 (310 in the vaccinated group and 61 in the placebo group) trial participants were withdrawn from the study due to “important protocol deviations.”
Of course, protocol deviations occur, but why were five times more vaccine recipients excluded than placebo recipients at that point in the study?
Although there were nearly 40,000 participants in the evaluable population, only 170 contributed to the efficacy calculation with regard to protection from infection, and only 10 with regard to protection from severe infection.
In other words, just a handful of incorrectly diagnosed and categorized participants could easily result in a substantially different estimation of the vaccine’s efficacy and safety.
Statistician and educator Mathew Crawford pointed out the likelihood of such a disparity between groups is exceedingly unlikely. However, because the investigators should have been blinded, we must accept this as an extraordinary coincidence.
Incredibly, the very same disparity occurred in the pediatric trials (ages 5 to 11). Table 12 from the corresponding summary to the FDA’s VRBPAC indicated 3.1% of children were removed from the trial if they received the vaccine compared to 0.5% if they received the placebo.
Once again, there is a factor of 5 difference at exactly the same point in the trial (within 7 days of dose 2). It is true that the vaccine formulation requires steps prior to administration that are not required with the placebo, but why didn’t these protocol deviations happen with the first dose as well? What happened to these vaccine recipients soon after they received their second dose?
These remarkable “coincidences” can be best explained if we are willing to consider the possibility that the investigators were not, in fact, blinded. This is precisely the most damning allegation by whistleblower Brook Jackson, formerly a regional director at Ventavia, one of several clinical research organizations conducting Pfizer’s vaccine trials in 2020.
In addition to the unblinding of investigators, Jackson also accused Ventavia of falsifying data.
These are weighty accusations. Why should we believe her? Because her story is corroborated by the trial data themselves.
She was fired within a day of reporting her concerns directly to the FDA. Her story was covered in The BMJ Nov. 2. Mainstream media has yet to report on it.
Conclusion
Though public health authorities continue to proclaim these products are safe and effective, every week brings more and more evidence to the contrary.
A thorough analysis of data from Pfizer’s vaccine trials reveals more questions than answers. Claims the vaccine maker’s product is performing “as expected” may not be so far from the truth.
© 2021 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
How RFK Jr. went from “a good guy” to an “anti-vaxxer”
By Steve Kirsch | December 22, 2021
Here’s the quick summary of the story of how science convinced RFK Jr to become a truthteller about vaccines:
- Back in the 1990’s, RFK was trying to get public attention about the presence of mercury in fish due to pollution from coal plants. This is well known. He was respected as an environmentalist. Everyone (except the coal companies) loved him.
- When he gave lectures, he noticed that a half dozen women would always arrive early and get seats at the front. After each lecture, they would try to get him interested in vaccines causing autism due to the mercury in the vaccines. They sought him out because he was a force and knew about mercury. They thought it would be a perfect fit.
- But every time, Kennedy rejected their efforts. He wanted to stay focused on his environmental mission.
- Finally, one of the women showed up on his doorstep with an 18” high stack of technical papers printed from medical journals. She said, “I’m not leaving until you read these.” That got his attention. He read all the papers. He was alarmed by what he had read.
- He then contacted his friends (they were still his friends at that time) in the CDC and FDA asking them about why they were recommending pregnant women avoid fish, while at the same time recommending these same women get vaccines containing lots of mercury. None of the people at the agencies could answer his questions. They all said, “Talk to Paul Offit.”
- In 2005, RFK called Offit. Offit said the reason why it was OK was that the mercury in thimerosal only lasted a week in the bloodstream; it was quickly eliminated per Pichichero (see this reference for a discussion).
- But RFK had read all the papers. He knew he was being lied to. He immediately cited the pivotal study (by Burbacher in April 2005) that looked at where the mercury “disappeared to.” It went out of the bloodstream and accumulated in the brain where it permanently remained. Offit was speechless. Offit didn’t think anyone knew about the Burbacher study. Offit then acknowledged he knew about the Burbacher study, but said that other papers had overturned that study and offered to send RFK the references. Those references never arrived. That sealed the deal for RFK and led to his famous “Deadly Immunity” article in July 2005.
- Shortly thereafter, Lyn Redwood, one of RFK’s friends, pointed him to the Simpsonwood transcripts showing the CDC knew about the dangers of thimerosal in July1999 and discussed it in a meeting on June 7 and 8, 2000 where the transcripts remained secret until finally released via FOIA request. It turns out, there were several versions of the Verstraeten paper (see “A “SIGNAL” DISAPPEARS ACROSS FIVE GENERATIONS OF STUDY”) each version making the effect on autism smaller (7.62, 2.48, 1.69 was the effect size on autism where 2 or more is very concerning) but there was an admission in an email on December 17, 1999 that Verstraeten sent to colleagues Robert Davis and Frank DeStefano under the subject line “It just won’t go away,” by which one presumes he meant the association between thimerosal and NDDs. At the Simpsonwood meeting, the scientists admitted that they couldn’t rule out that the mercury could be causing a whole host of diseases. They also pointed out that the meeting transcript might be disclosed via FOIA requests, so people were quite guarded in their comments. It was clearly serious because they gathered experts from all over the country for an urgent meeting that lasted nearly two days. They wouldn’t have done that if there wasn’t a serious problem.
In short, RFK Jr. was persuaded the vaccines were unsafe based on science and how people acted to deliberately cover it up. It’s no more complicated than that.
Postscript
The original Verstraten VSD data sets on thimerasol were turned over to a third party to keep them out of reach of FOIA. VSD data is more heavily guarded than the gold in Ft. Knox. Its all there; the vaccine damage to children’s health since 1986.
Here we are today, over twenty years after thimerosal was known to cause problems. We know for sure it causes mercury accumulation in the brain. Here’s the most recent review showing RFK was right: 22 studies showing ethyl- and methylmercury cross the blood-brain barrier using the same LAT system: “In total, these studies indicate that ethylmercury-containing compounds and Thimerosal readily cross the BBB, convert, for the most part, to highly toxic inorganic mercury-containing compounds, which significantly and persistently bind to tissues in the brain, even in the absence of concurrent detectable blood mercury levels.” In short, it goes from the blood to your brain where it stays for the rest of your life.
Of course, the CDC is still lying about it today on their website:

This is why the CDC doesn’t want to debate Kennedy, me, or anyone else on vaccine safety. They would be exposed as deliberately lying to the public. They can’t have that happen. This is why they are relentless in attacking RFK Jr.
If the truth ever got out to the public, say in a Joe Rogan interview, they’d be toast. Remember, you heard it here first :).
Fast forward to today
Clearly, the CDC can completely get away with lies about the safety of thimerosal even 20 years later.
So they are going to use similar techniques to convince everyone the current vaccines are safe, even in light of all the evidence that it isn’t. And they’ll get away with it for decades even after killing over 150,000 Americans in 2021 without anyone noticing.
Silencing critics through censorship, de-platforming, ad hominem attacks, and refusing to debate are all techniques they engage in today to hide the truth and keep it hidden for decades.
Any doctor or pharmacist or other medical professional who speaks against the narrative will be punished through loss of ability to earn a living, loss of medical licensing, or in some cases, loss of life. I can’t tell you how many calls I get a day of medical boards going after people who speak out when they discover that the vaccines are killing and/or injuring people.
The censorship and intimidation grows stronger and stronger every day because more and more people are waking up to the truth.
34,337 Deaths 3,120,439 Injuries Following COVID Shots in European Database
UK Public Data Show 35 Deaths 213 Hospitalizations Among Booster Triple Vaccinated

By Brian Shilhavy | Health Impact News | December 22, 2021
The European (EEA and non-EEA countries) database of suspected drug reaction reports is EudraVigilance, verified by European Medicines Agency (EMA), and they are now reporting 32,649 fatalities, and 3,003,296 injuries following injections of four experimental COVID-19 shots:
- COVID-19 MRNA VACCINE MODERNA (CX-024414)
- COVID-19 MRNA VACCINE PFIZER-BIONTECH
- COVID-19 VACCINE ASTRAZENECA (CHADOX1 NCOV-19)
- COVID-19 VACCINE JANSSEN (AD26.COV2.S)
From the total of injuries recorded, almost half of them (1,470,537) are serious injuries.
“Seriousness provides information on the suspected undesirable effect; it can be classified as ‘serious’ if it corresponds to a medical occurrence that results in death, is life-threatening, requires inpatient hospitalisation, results in another medically important condition, or prolongation of existing hospitalisation, results in persistent or significant disability or incapacity, or is a congenital anomaly/birth defect.”
A Health Impact News subscriber in Europe ran the reports for each of the four COVID-19 shots we are including here. It is a lot of work to tabulate each reaction with injuries and fatalities, since there is no place on the EudraVigilance system we have found that tabulates all the results.
Since we have started publishing this, others from Europe have also calculated the numbers and confirmed the totals.*
Here is the summary data through December 18, 2021.
Total reactions for the mRNA vaccine Tozinameran (code BNT162b2,Comirnaty) from BioNTech/ Pfizer: 15,788 deaths and 1,476,269 injuries to 18/12/2021
- 40,271 Blood and lymphatic system disorders incl. 226 deaths
- 47,256 Cardiac disorders incl. 2,310 deaths
- 433 Congenital, familial and genetic disorders incl. 41 deaths
- 19,912 Ear and labyrinth disorders incl. 11 deaths
- 1,504 Endocrine disorders incl. 5 deaths
- 22,804 Eye disorders incl. 35 deaths
- 120,263 Gastrointestinal disorders incl. 637 deaths
- 370,545 General disorders and administration site conditions incl. 4,452 deaths
- 1,691 Hepatobiliary disorders incl. 82 deaths
- 16,314 Immune system disorders incl. 84 deaths
- 61,494 Infections and infestations incl. 1,649 deaths
- 25,540 Injury, poisoning and procedural complications incl. 279 deaths
- 36,772 Investigations incl. 476 deaths
- 10,065 Metabolism and nutrition disorders incl. 264 deaths
- 179,558 Musculoskeletal and connective tissue disorders incl. 196 deaths
- 1,362 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 128 deaths
- 246,596 Nervous system disorders incl. 1,694 deaths
- 2,127 Pregnancy, puerperium and perinatal conditions incl. 64 deaths
- 223 Product issues incl. 3 deaths
- 26,890 Psychiatric disorders incl. 191 deaths
- 5,314 Renal and urinary disorders incl. 249 deaths
- 55,551 Reproductive system and breast disorders incl. 5 deaths
- 63,512 Respiratory, thoracic and mediastinal disorders incl. 1,742 deaths
- 68,837 Skin and subcutaneous tissue disorders incl. 134 deaths
- 3,257 Social circumstances incl. 21 deaths
- 10,192 Surgical and medical procedures incl. 122 deaths
- 37,986 Vascular disorders incl. 688 deaths
Total reactions for the mRNA vaccine mRNA-1273(CX-024414) from Moderna: 9,612 deaths and 431,805 injuries to 18/12/2021
- 9,176 Blood and lymphatic system disorders incl. 106 deaths
- 14,538 Cardiac disorders incl. 1,000 deaths
- 174 Congenital, familial and genetic disorders incl. 8 deaths
- 5,244 Ear and labyrinth disorders incl. 4 deaths
- 409 Endocrine disorders incl. 4 deaths
- 6,337 Eye disorders incl. 33 deaths
- 35,162 Gastrointestinal disorders incl. 359 deaths
- 114,485 General disorders and administration site conditions incl. 3,239 deaths
- 693 Hepatobiliary disorders incl. 47 deaths
- 4,314 Immune system disorders incl. 17 deaths
- 16,686 Infections and infestations incl. 907 deaths
- 8,851 Injury, poisoning and procedural complications incl. 180 deaths
- 8,917 Investigations incl. 263 deaths
- 4,138 Metabolism and nutrition disorders incl. 231 deaths
- 51,645 Musculoskeletal and connective tissue disorders incl. 193 deaths
- 595 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 76 deaths
- 72,360 Nervous system disorders incl. 919 deaths
- 785 Pregnancy, puerperium and perinatal conditions incl. 6 deaths
- 91 Product issues incl. 4 deaths
- 7,887 Psychiatric disorders incl. 158 deaths
- 2,553 Renal and urinary disorders incl. 183 deaths
- 9,972 Reproductive system and breast disorders incl. 8 deaths
- 19,269 Respiratory, thoracic and mediastinal disorders incl. 1,032 deaths
- 23,101 Skin and subcutaneous tissue disorders incl. 84 deaths
- 1,956 Social circumstances incl. 40 deaths
- 1,946 Surgical and medical procedures incl. 150 deaths
- 10,521 Vascular disorders incl. 361 deaths
Total reactions for the vaccine AZD1222/VAXZEVRIA (CHADOX1 NCOV-19) from Oxford/ AstraZeneca: 6,862 deaths and 1,103,016 injuries to 18/12/2021
- 13,469 Blood and lymphatic system disorders incl. 255 deaths
- 19,919 Cardiac disorders incl. 753 deaths
- 208 Congenital familial and genetic disorders incl. 7 deaths
- 13,018 Ear and labyrinth disorders incl. 5 deaths
- 642 Endocrine disorders incl. 4 deaths
- 19,414 Eye disorders incl. 30 deaths
- 104,504 Gastrointestinal disorders incl. 370 deaths
- 289,568 General disorders and administration site conditions incl. 1,614 deaths
- 985 Hepatobiliary disorders incl. 63 deaths
- 5,105 Immune system disorders incl. 31 deaths
- 34,377 Infections and infestations incl. 471 deaths
- 12,816 Injury poisoning and procedural complications incl. 184 deaths
- 24,316 Investigations incl. 178 deaths
- 12,629 Metabolism and nutrition disorders incl. 101 deaths
- 163,096 Musculoskeletal and connective tissue disorders incl. 125 deaths
- 684 Neoplasms benign malignant and unspecified (incl cysts and polyps) incl. 29 deaths
- 226,199 Nervous system disorders incl. 1,047 deaths
- 558 Pregnancy puerperium and perinatal conditions incl. 17 deaths
- 193 Product issues incl. 1 death
- 20,437 Psychiatric disorders incl. 62 deaths
- 4,164 Renal and urinary disorders incl. 66 deaths
- 15,992 Reproductive system and breast disorders incl. 2 deaths
- 39,444 Respiratory thoracic and mediastinal disorders incl. 880 deaths
- 50,458 Skin and subcutaneous tissue disorders incl. 54 deaths
- 1,563 Social circumstances incl. 6 deaths
- 1,611 Surgical and medical procedures incl. 29 deaths
- 27,647 Vascular disorders incl. 478 deaths
Total reactions for the COVID-19 vaccine JANSSEN (AD26.COV2.S) from Johnson & Johnson: 2,075 deaths and 109,349 injuries to 18/12/2021
- 1,068 Blood and lymphatic system disorders incl. 44 deaths
- 2,052 Cardiac disorders incl. 173 deaths
- 41 Congenital, familial and genetic disorders incl. 1 death
- 1,146 Ear and labyrinth disorders incl. 2 deaths
- 87 Endocrine disorders incl. 1 deaths
- 1,475 Eye disorders incl. 7 deaths
- 8,932 Gastrointestinal disorders incl. 84 deaths
- 28,855 General disorders and administration site conditions incl. 559 deaths
- 138 Hepatobiliary disorders incl. 13 deaths
- 489 Immune system disorders incl. 10 deaths
- 5,092 Infections and infestations incl. 165 deaths
- 1,011 Injury, poisoning and procedural complications incl. 21 deaths
- 5,043 Investigations incl. 115 deaths
- 687 Metabolism and nutrition disorders incl. 51 deaths
- 15,638 Musculoskeletal and connective tissue disorders incl. 47 deaths
- 68 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 6 deaths
- 21,175 Nervous system disorders incl. 224 deaths
- 46 Pregnancy, puerperium and perinatal conditions incl. 1 death
- 29 Product issues
- 1,551 Psychiatric disorders incl. 20 deaths
- 462 Renal and urinary disorders incl. 27 deaths
- 2,485 Reproductive system and breast disorders incl. 6 deaths
- 3,937 Respiratory, thoracic and mediastinal disorders incl. 268 deaths
- 3,370 Skin and subcutaneous tissue disorders incl. 9 deaths
- 358 Social circumstances incl. 4 deaths
- 745 Surgical and medical procedures incl. 61 deaths
- 3,369 Vascular disorders incl. 156 deaths
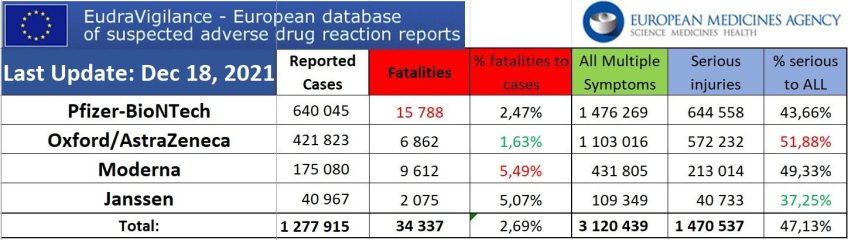
*These totals are estimates based on reports submitted to EudraVigilance. Totals may be much higher based on percentage of adverse reactions that are reported. Some of these reports may also be reported to the individual country’s adverse reaction databases, such as the U.S. VAERS database and the UK Yellow Card system. The fatalities are grouped by symptoms, and some fatalities may have resulted from multiple symptoms.
Meanwhile, The Exposé is reporting that public health data in the UK shows that the vast majority of deaths and hospitalizations in the UK are among those vaccinated, and now there are 35 deaths and 213 hospitalizations being reported among those who have received booster shots and are triple-vaccinated.
“Do Not Discriminate” Against the Unvaccinated, Japanese Government Tells Citizens
By Noah Carl | The Daily Sceptic | December 21, 2021
At this point, almost all Western countries have introduced some form of vaccine passport or vaccine mandate. Despite repeated assurances from the Vaccines Minister that this wouldn’t happen here, Britain is no exception.
Things may go further in some European countries. Austria is set to make vaccination mandatory from 1st February next year. And beginning in January, Greece will impose a monthly fine of €100 on all over 60s who remain unvaccinated.
Even the United States – supposedly the ‘land of the free’ – has not bucked the trend toward use of passports and mandates. Several states have introduced them, including some of the biggest like New York, California and Virginia. Healthcare workers with natural immunity have already been fired for refusing to comply.
You might conclude that introducing passports and mandates is just something that all advanced countries do. But that isn’t true, as there’s one major exception: Japan.
Nobody can doubt Japan’s credentials as an advanced country. It’s a member of the ‘Group of Seven’, along with the U.K., U.S., Canada, France, Italy and Germany. And it boasts the world’s third largest economy overall. Japan is known for its technologically advanced society, where the high-speed trains never run more than a few minutes late.
So what is the country’s stance on passports and mandates? So far, it’s completely eschewed them. Not only that, but the Government and Prime Minister have explicitly told citizens not to discriminate against the unvaccinated.
The following notice appears on the website for the Ministry of Health, Labour and Welfare:
Although we encourage all citizens to receive the COVID-19 vaccination, it is not compulsory or mandatory. Vaccination will be given only with the consent of the person to be vaccinated after the information provided. Please get vaccinated of your own decision, understanding both the effectiveness in preventing infectious diseases and the risk of side effects. No vaccination will be given without consent. Please do not force anyone in your workplace or those who around you to be vaccinated, and do not discriminate against those who have not been vaccinated.
And a similar notice appears on the website for the Prime Minister:
Vaccines will never be administered without the recipient’s consent. We urge the public never to coerce vaccinations at the workplace or upon others around them, and never to treat those who have not received the vaccine in a discriminatory manner.
Western countries still claim to be the foremost defenders of civil liberties. But in the era of Covid safetyism, it seems that mantle has passed to Japan. Perhaps the country will send a delegation of human rights experts to teach the West about individual freedom.
Omicron: The Lockdowners’ Last Stand
By Ron Paul | December 20, 2021
Just as President Biden’s unconstitutional vaccination mandates were being ripped up by the courts, authoritarian politicians, public health bureaucrats, and the mainstream media, announced a new Covid variant to justify another round of lockdowns and restrictions. The things that didn’t work last time would be a good idea to do again this time, they claim.
For these authoritarians, the timing of omicron’s emergence was perfect.
The variant was first discovered in South Africa, with the US and European media running endless scare stories. Authoritarian politicians used the manufactured fear to justify another attack on liberty. Europe shut down and became a virtual prison camp. In Austria, Germany, and elsewhere, citizens became non-persons without a vaccine passport.
South African health officials reported that the variant seemed to be more contagious but far milder than previous variants, as usually happens with such viruses. But the lockdowners would not hear of it. From Boris Johnson in the UK to DeBlasio in New York City, the variant was perfect cover for them to put their boots back on the necks of terrorized citizens.
As to be expected, Fauci reveled in the emergence of the new variant, warning of “record deaths” for the unvaccinated. Similarly, President Biden warned that this would be a “winter of death” for the unvaccinated.
But here’s something the media isn’t reporting about the omicron outbreaks: they are taking place among the fully vaccinated. Cornell University, with 97 percent of the campus fully vaccinated and a mask mandate, has announced that it would return to online only instruction after a massive Covid outbreak. Likewise, the National Football League has postponed several games this weekend due to Covid outbreaks, even though the League is virtually 100 percent vaccinated. And the National Basketball Association, which is above 95 percent fully vaccinated, has just announced that due to a surge in Covid cases it too will postpone games.
The vaccine is not working to prevent infection or transmission of the virus: cases are raging in states with the highest vaccine levels. Yet the “experts” continue to maintain that the only thing that can stop the spread of omicron is vaccines! More people are catching on that this makes no sense. If vaccines don’t stop the spread, how can vaccines stop the spread?
Meanwhile, South Africa, with one of the lowest rates of vaccination, has just announced that they are only seeing a tiny fraction of hospitalizations with omicron compared to previous variants. South Africa’s Covid response authority has written to the health minister recommending an end to containment efforts, contact tracing, and quarantines.
Unvaccinated South Africa is ending Covid restrictions while the hyper-vaccinated North is locking down. Something doesn’t add up.
Fauci loves to say that to question him is to question science, but this has nothing to do with science. It’s about power. Fauci, the political authoritarians, and the corrupt Big Pharma billionaires are trying to make a last stand, desperate to push omicron as a justification for further tyranny and profits. But actual science is not cooperating.
Omicron is spreading and vaccines are not stopping it. Thus far nearly half of omicron infections are asymptomatic. Some experts are predicting that omicron will spell the end of Covid-19. But we know that as long as people like Fauci are around, Covid-19 will never end. Unless, of course, we repudiate the charlatans and profiteers and reclaim our liberty!
Copyright © 2021 by RonPaul Institute
FDA Should Need Only ‘12 Weeks’ to Release Pfizer Data, Not 75 Years, Plaintiff Calculates
By Seth Hancock | The Defender | December 17, 2021
U.S. Food and Drug Administration (FDA) officials skipped the start of oral arguments Tuesday as a federal district court weighed whether the agency can take 75 years to fully release documents on Pfizer’s Comirnaty COVID vaccine, according to a lawyer representing plaintiffs who sued the FDA for the documents.
A U.S. Department of Justice lawyer representing the FDA told the U.S. District Court for the Northern District of Texas the agency will produce more than 329,000 related documents as fast as it can, while safeguarding personally identifiable information and Pfizer trade secrets.
Public Health and Medical Professionals for Transparency (PHMPT), the group behind the Freedom of Information Act (FOIA) request and subsequent lawsuit, is seeking safety and effectiveness data, adverse reaction reports and a list of active and inactive vaccine ingredients.
PHMPT is a group of more than 30 scientists, medical professionals, international public health professionals and journalists. The group’s lawsuit argues the FDA is overestimating the time needed and understaffing the job.
“Assuming a low average of 50 pages per hour per person, even to review the hundreds of thousands of pages the FDA estimates, the agency would need just 19 reviewers to work full-time for 12 weeks to review and produce these documents — which is a tiny fraction of its approximately 18,000 employees,” said PHMPT in a legal brief filed Monday.
The day before oral arguments, the FDA released 14 document files, the largest file including 2,030 pages. PHMPT posted an updated list which shows documents released since Nov. 17.
FOIA does not mandate any particular processing schedule, only that the agency process requests “as soon as practicable,” the FDA said in a legal brief filed Monday.
“The bottom-line issue still remains what processing schedule is ‘practicable’ for the agency,” the FDA said.
At the agency’s proposed rate of 500 documents per month, the last documents would be released in 2096.
A quote from Business Intelligence Associates, an e-discovery company, estimated 400,000 pages could be produced within six to eight weeks at a cost of $132,000, according to PHMPT.
PHMPT wants the FDA documents released within 108 days. That’s the same amount of time the FDA spent reviewing the responsive documents for “the far more intricate task” of licensing Pfizer’s vaccine, the group said in its lawsuit.
Attorney Aaron Siri, who represents PHMPT, said:
“Americans must routinely produce documents, pay fines, and otherwise expend resources to comply with the law. Courts don’t inquire as to the ability or financial resources to comply with the law — they must comply.
“In fact, it would be laughable if a billionaire defendant came before a court and claimed poverty to escape making a document production, but that is the FDA’s position.”
The FDA budget for fiscal year 2019 was $6.1 billion.
In the FDA’s 64-page briefing, the agency argued it needed the full 75 years to redact and release the documents out of “fairness” to other FOIA requesters.
PHMPT defined fairness differently in its responding brief:
“Fairness would be giving millions of Americans who are mandated to receive this liability-free vaccine today assurance regarding the FDA’s review by allowing independent scientists access to the same data the FDA reviewed, without making them wait decades.
“Fairness would be allowing Americans injured by the vaccine today, who cannot sue Pfizer or anyone else for the harm, hope that independent scientists with access to that data can more readily develop treatments for their ailments.
“Fairness would be our federal health authorities allocating more than one person spending a few hours each month to review Pfizer’s documents for public disclosure after having given Pfizer over $17 billion of taxpayer money to develop and market the product.
“That would be fair to the American people.”
Siri noted that no decision has been made by the court and that a transcript of this week’s hearing should be released soon.
U.S. Rep. Ralph Norman (R-S.C.) earlier this month introduced a bill that would force the FDA to release them in 100 days.
© 2021 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Featured Video

The Failed Air War Over Vietnam
or go to
Aletho News Archives – Video-Images
From the Archives
USS Liberty Massacre: A Pivotal Moment in the Hostile Takeover of America
By Kevin Barrett | Crescent | Dhu al-Qa’dah 24, 1445
In corporate America, hostile takeovers are commonplace. They occur when an aggressor—a larger corporation or rich individuals—seizes control of a smaller corporation without asking permission.
What few recognize is that the United States itself has been subjected to a hostile takeover. Since the aggressor, the illegitimate settler colony known as “Israel,” is much smaller than the US, the takeover has necessarily been surreptitious.
As of June, 2024, Israel’s gradual takeover of the US has become obvious and undeniable—a proverbial “elephant in the living room.” … continue
Blog Roll
 Aletho News
- Leaders Condemn Ansarallah Attack on Saudi Arabia While Ignoring Illegal War Against Yemen
- Leaked: Britain’s Covert Iraqi Psyops Network
- Yemeni Armed Forces Warn Airlines Against Using Saudi Airports, Exempt Mecca and Medina
- Iran security chief says powers greater than US tried to conquer Iran but ended in ‘dustbin of history’
- Europe’s mounting social chaos… chickens coming home to roost for proxy war against Russia
- US-Russia Diesel Deal Becomes Massive Defeat for Ukraine
- Hormuz and the Looming Economic Catastrophe
- Dhubab offensive, media blitz and the rapid unraveling of Saudi-backed coalition’s new gambit
- Putin Conveys to Trump Iran’s Vision on Possible Conflict Resolution – Kremlin
- The Search for Truth: Charlie Kirk’s Assassination One Year Later
- If Americans Knew
- For three years, Israel has killed a child in Gaza every 71 minutes – Daily Update
- Israeli forces kill another child in Gaza – Daily Update
- Gaza ceasefire exists in name only, say more than 100 organizations
- Nearly 2 Million in Gaza Need Urgent Shelter Assistance as Winter Looms: IOM Chief Warns
- Suppressing Palestinian resistance: US charity under fire for AI monitoring of Gaza classrooms
- Thousands Are Held in Israeli Torture Camps. This Is What Happens Inside
- Israel puts Gaza’s sick, injured, newborn in peril – Daily Update
- Report claimed Mark Levin used by Israeli government to influence Trump
- Over 2,000 Gazans have died awaiting medical evacuation amid Israel’s continued siege
- How a U.S. Diplomat Suppressed and Altered Reports Critical of Israel
- No Tricks Zone
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI

