Not worried about the jab? You should be
By Harry Dougherty | Conservative Woman | May 19, 2021
THE problem with the Covid-19 vaccines is that we simply do not have enough information about their side-effects, and no one should be shamed (especially not by the President of the United States) or have their lives restricted for having this reasonable, wholly unselfish concern.
Such information does not exist at all for under-18s. The small-scale trials were designed only to test the vaccine on adults. Yet, largely because of media hysteria which has been recently accompanied by outright incitement, local officials have taken it upon themselves to start vaccinating 17-year-olds, citing the bogeyman ‘Indian variant’ in our midst.
The vaccine nudgers in government and the media, aided this week by a multi-million-pound YouTube ad campaign to persuade young people to get vaccinated, deliberately miss the point about the supposedly ‘extremely rare’ side-effects of these experimental vaccines, which include fatal blood clots in some cases.
The trouble is that if our ‘brilliant’ scientists knew nothing about the blood clots when the vaccine was first administered to citizens in December, what else don’t they know about?
Last week, the British regulator MHRA reported 41 new cases and nine more deaths as a result of one of these side-effects, a particular kind of clot known as cerebral venous sinus thrombosis alongside low platelets or thrombocytopenia. To date, there have been 209 cases and 41 deaths reported in the UK for the AstraZeneca vaccine alone. The first were reported in January.
According to an analysis of published MHRA data by Dr Hamid Merchant, a total of 532 ‘blood system events’, including 20 deaths, came through the UK’s Yellow Card system relating to the AstraZeneca jab between January 4 and March 14. There were thousands of non-blood-related reports besides.
Let’s recap on the public guidance regarding the AstraZeneca vaccine. First we were told ‘this vaccine is safe, get vaccinated.’ Then they said, ‘the benefits of this vaccine outweigh the risks, get vaccinated.’ Then the goalposts were moved further: ‘The benefits of that vaccine outweigh the risks if you are over the age of 30, but get vaccinated.’ And now, ‘the benefits of this vaccine outweigh the risks if you are over 40, but get vaccinated, or else!’
If this is how much ‘the science’ has changed in a few months, what will ‘the science’ be a year or two from now? What will we know in the future that cannot be established now? Scientists have not begun to discuss other fatal adverse reactions to have emerged, most significantly the neurological ones for which the AstraZeneca trials were paused.
If countries such as Denmark and Slovakia can suspend the rollout of a vaccine as a precaution, why are individual citizens stupid or callous if they decline the vaccine as a precaution?
In the United States, the government has recorded more deaths after Covid vaccinations than from all other vaccines administered in the country between mid-1997 and the end of 2013, as was reported by Tucker Carlson on Fox News earlier this month. Nothing to see here, of course.
Any reasonable government would have at the very least stopped blackmailing people into getting vaccinated by now. Instead, they have the brass neck to demand that we put our lives in their hands as if we owe it to them. Coerced vaccination is not merely mandatory vaccination, it is mandatory trust, both in government and in ‘the science’, whatever that is.
It is worth reminding those with short memories that tobacco was ‘safe’ for decades. The scientific community promoted smoking not only as safe, but healthy. They were, of course, assisted by celebrities, some of whom would later become senior politicians. And for some 50 years, the overwhelming majority of people were dumb enough to believe it. Who could have guessed that inhaling tar into your lungs twenty times a day, every day, for years, might be bad for your health? We see grim warnings about heart disease, lung cancer and infertility on cigarette packaging today only because scientific outliers of yesterday eventually overwhelmed the consensus with evidence.
More recently and more relevant to the present fiasco, the swine flu vaccine, Pandemrix, was declared safe by regulators in 2009. It was safe, for most. But for some 1,000 people, most of whom were not at any significant risk from swine flu, the vaccine triggered narcolepsy, a crippling chronic sleep disorder that leaves sufferers unable to stay awake. It was only after it was too late for them that the authorities conceded there was a link between Pandemrix and narcolepsy.
One of the victims of Pandemrix, 23-year-old Katie Clack from Peterborough, committed suicide in 2014 because her narcolepsy left her with ‘no quality of life’.
In 2018, the progressive news website Buzzfeed published a powerful feature about NHS workers who had their lives and careers ruined by the side-effects of the swine flu vaccine. Nurse Meleney Gallagher, who now has narcolepsy, told Buzzfeed: ‘I was pressured into it.’
That was in a different era. Earlier this month the same website published a slavish article with the headline: ‘15 anti Vaxxers who were roasted on the internet.’
If history is anything to go by, the idiots out there who think it’s acceptable to bully their vaccine-hesitant friends, colleagues, strangers and even close family are going to look very silly ten years from now.
How the CDC is manipulating data to prop-up “vaccine effectiveness”
New policies artificially deflate “breakthrough infections” in the vaccinated, while old rules continue inflating case numbers in the unvaccinated.
By Kit Knightly | OffGuardian | May 18, 2021
The US Center for Disease Control (CDC) is altering its practices of data logging and testing for “Covid19” in order to make it seem the experimental gene-therapy “vaccines” are effective at preventing the alleged disease.
They made no secret of this, announcing the policy changes on their website in late April/early May, (though naturally without admitting the fairly obvious motivation behind the change).
The trick is in their reporting of what they call “breakthrough infections” – that is people who are fully “vaccinated” against Sars-Cov-2 infection, but get infected anyway.
Essentially, Covid19 has long been shown – to those willing to pay attention – to be an entirely created pandemic narrative built on two key factors:
- False-postive tests. The unreliable PCR test can be manipulated into reporting a high number of false-positives by altering the cycle threshold (CT value)
- Inflated Case-count. The incredibly broad definition of “Covid case”, used all over the world, lists anyone who receives a positive test as a “Covid19 case”, even if they never experienced any symptoms.
Without these two policies, there would never have been an appreciable pandemic at all, and now the CDC has enacted two policy changes which means they no longer apply to vaccinated people.
Firstly, they are lowering their CT value when testing samples from suspected “breakthrough infections”.
From the CDC’s instructions for state health authorities on handling “possible breakthrough infections” (uploaded to their website in late April):
For cases with a known RT-PCR cycle threshold (Ct) value, submit only specimens with Ct value ≤28 to CDC for sequencing. (Sequencing is not feasible with higher Ct values.)
Throughout the pandemic, CT values in excess of 35 have been the norm, with labs around the world going into the 40s.
Essentially labs were running as many cycles as necessary to achieve a positive result, despite experts warning that this was pointless (even Fauci himself said anything over 35 cycles is meaningless).
But NOW, and only for fully vaccinated people, the CDC will only accept samples achieved from 28 cycles or fewer. That can only be a deliberate decision in order to decrease the number of “breakthrough infections” being officially recorded.
Secondly, asymptomatic or mild infections will no longer be recorded as “covid cases”.
That’s right. Even if a sample collected at the low CT value of 28 can be sequenced into the virus alleged to cause Covid19, the CDC will no longer be keeping records of breakthrough infections that don’t result in hospitalisation or death.
From their website:
As of May 1, 2021, CDC transitioned from monitoring all reported vaccine breakthrough cases to focus on identifying and investigating only hospitalized or fatal cases due to any cause. This shift will help maximize the quality of the data collected on cases of greatest clinical and public health importance. Previous case counts, which were last updated on April 26, 2021, are available for reference only and will not be updated moving forward.
Just like that, being asymptomatic – or having only minor symptoms – will no longer count as a “Covid case” but only if you’ve been vaccinated.
The CDC has put new policies in place which effectively created a tiered system of diagnosis. Meaning, from now on, unvaccinated people will find it much easier to be diagnosed with Covid19 than vaccinated people.
Consider…
Person A has not been vaccinated. They test positive for Covid using a PCR test at 40 cycles and, despite having no symptoms, they are officially a “covid case”.
Person B has been vaccinated. They test positive at 28 cycles, and spend six weeks bedridden with a high fever. Because they never went into a hospital and didn’t die they are NOT a Covid case.
Person C, who was also vaccinated, did die. After weeks in hospital with a high fever and respiratory problems. Only their positive PCR test was 29 cycles, so they’re not officially a Covid case either.
The CDC is demonstrating the beauty of having a “disease” that can appear or disappear depending on how you measure it.
To be clear: If these new policies had been the global approach to “Covid” since December 2019, there would never have been a pandemic at all.
If you apply them only to the vaccinated, but keep the old rules for the unvaccinated, the only possible result can be that the official records show “Covid” is much more prevalent among the latter than the former.
This is a policy designed to continuously inflate one number, and systematically minimise the other.
What is that if not an obvious and deliberate act of deception?
Report: COVID vaccine adverse effects, huge numbers
By Jon Rappoport | No More Fake News | May 17, 2021
A long-standing private organization, the National Vaccine Information Center, has analyzed the US government’s database, the Vaccine Adverse Event Reporting System (VAERS).
As of May 7, 2021, VAERS lists 192,954 adverse-event reports associated with COVID vaccines. [1]
These events cover the spectrum from mild transient effects to death.
VAERS has always has multiple problems.
One: Doctors aren’t required by law to report adverse effects. Many of them wouldn’t risk blowback by doing so.
Two: There is no comprehensive effort to determine whether an adverse effect is actually caused by a vaccine.
Three: Patients can make adverse-effect reports—but are often hesitant to do so.
Four: By far the biggest problem is: most Americans aren’t even aware that VAERS exists.
Therefore, on balance, UNDER-REPORTING adverse effects is the primary defect of VAERS.
Many efforts have been made to estimate the degree of under-reporting. These estimates state the VAERS numbers should be multiplied by 10, all the way to 100, to obtain an accurate picture of adverse effects.
Ten times the current number of COVID vaccine adverse effects would equal 1,929,540. A hundred times the current number=19,295,400. Either way, the number is staggering.
The death reports are escalating by the day. As of May 7—4,057.
Here are other very troubling categories of VAERS adverse effects, as of May 7. Permanent Disability=2,475. Doctor’s Office Visit=32,801. Emergency Doctor/Room=25,566. Hospitalized=11,538. Birth Defect=112. Life-Threatening=3,548.
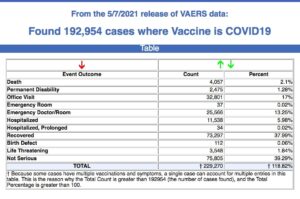
Yet, public officials and news outlets continue to repeat the mantra, “safe and effective,” and urge everyone to take the shot.
Every person who receives the vaccine is supposed to be informed of the risks beforehand. I assure you NO ONE is being given these adverse effect numbers, plus the advice to multiply the numbers by 10 or 100.
Lack of informed consent runs contrary to every medical code.
I can also assure you the FDA, which is considering whether to give full approval to the current COVID vaccines, isn’t multiplying the adverse-effect numbers by 10 or 100.
Here is something else to consider. Even multiplying the VAERS numbers by 100 may not be sufficient, because the RNA COVID shots are employing a new technology which a) has never been used on the public before and b) isn’t a vaccine at all; it’s a genetic treatment.
As I’ve shown in recent articles, the entire field of genetic research is riddled with lies, pretense, and unpredictable ripple-effect consequences. The notion of inserting a single genetic change into a person and limiting its effects to an announced goal is a fiction. Unexpected changes occur. And their negative disruptive effects, long-term, are unknown.
Those effects will never be listed in any database.
SOURCE:
[1] https://www.medalerts.org/vaersdb/findfield.php?TABLE=ON&GROUP1=CAT&EVENTS=ON&VAX=COVID19
THE NEW ABNORMAL AND THE CONFLICTED MIND OF JOE NORMIE
Computing Forever | May 13, 2021
Reality Bites Sort Of… | Thomas Sheridan | https://www.youtube.com/watch?v=qFUsPz2b3jo
Watch: Reality Bites Sort Of… | Thomas Sheridan | https://www.youtube.com/watch?v=qFUsPz2b3jo
Support my work here: https://computingforever.com/donate/
Support my work on Subscribe Star: https://www.subscribestar.com/dave-cullen
Follow me on Bitchute: https://www.bitchute.com/channel/hybM74uIHJKf/
Buy How is This a Thing Mugs here: https://teespring.com/stores/computing-forever-store
http://www.computingforever.com
KEEP UP ON SOCIAL MEDIA:
Gab: https://gab.ai/DaveCullen
Subscribe on Gab TV: https://tv.gab.com/channel/DaveCullen
Minds.com: https://www.minds.com/davecullen
Subscribe on Odysee: https://odysee.com/@ComputingForever
Government insider says UK Gov. plans to continue Lockdown and the Mainstream Media are in on it
THE DAILY EXPOSE • MAY 15, 2021
A Whitehall source directly linked to the Covid Response has said that the UK Government have already structured a detailed plan designed to neutralise each stage of lockdown easing, including the compliance of media outlets to help spread fear.
The Whitehall source has said that he has been “increasingly concerned” with how the Government are behaving, and that their “relationship with the truth” is now not even on nodding terms. The latest plan will involve a series of ‘crisis’ around drug supply; mutant strains; and third waves, specifically choreographed to condition the public for further lockdowns and vaccine passports.
The plan, that according to the source is designed to take us to September 27th 2021 is to be released in stages over the summer months and, according to the Whitehall source, is already ‘well underway’.
On March the 8th, the first milestone of the roadmap was implemented, with school children finally returning to class. The following day Chris Whitty gave a pre-written speech to the Commons that said schools reopening would cause another surge in the virus and ended it with “Let me be clear, many, many more people will die before this is over” the soundbite obligingly repeated on every news outlet, with BBC news having it on-loop all day.
On March the 29th, the second milestone of the roadmap was implemented. The Government said – “The evidence shows that it is safer for people to meet outdoors rather than indoors,”. This is why from the 29th March, when most schools start to break up for the Easter holidays, outdoor gatherings (including in private gardens) of either 6 people (the Rule of 6) or 2 households will also be allowed, making it easier for friends and families to meet outside.
The next day (March 30th) the AstraZeneca Vaccine was again stopped due to blood clots fears, despite the medicine’s regulator clearing it only the previous week. Whilst Boris Johnson repeated what he’d said the previous week that the mutated virus on the continent would inevitably “wash up on our shores”.
On April 19th, the third milestone saw pub gardens, and non-essential shops reopen. Followed immediately by news of a second vaccine being halted for fear it was causing blood clots and the discovery of the South African mutation said to be able to avoid them anyway.
The next milestone is due on May 17th with the Government relaxing social contact rules further and the opening of indoor venues. This will be followed by a story that the mutation is ‘more deadly than first thought’ and that young people are now also vulnerable to it, accompanied by the result of the vaccine passport trials have shown that they have a ‘positive effect on virus reduction’.
The final milestone is due on June 21st where ALL restrictions were promised to be lifted. This will not be allowed to happen. Vaccine passports / Track and Trace will be mandatory, as will masks and social distancing. The entire week of the 21st will be taken up by a third wave, which will suddenly be ‘rampant’, and this will be attributed to a new variant which they will declare is more deadly than the previous strains of Covid allegedly doing the rounds. This will be accompanied with yet more issues with vaccine supplies. Authorities will declare that one of the vaccines is effective against the deadlier strain, but a ‘problem’ with its manufacture will emerge.
The Whitehall source went on to say –
“All the measures are aimed at two things, vaccine passports and lockdowns starting next winter,
“The ultimate goal is to have the public, back in their box.
“Note that Boris is now talking down vaccine’s and bigging-up lockdowns, that wasn’t a mistake, that was all part of the plan”.
The plan also includes an ad campaign like the one seen at Christmas, the message this time will be that the pandemic isn’t over and vaccine passports are the ‘solution’.
Seeing Through the COVID-19 Spin

By Barbara Loe Fisher | The National Vaccine Information Center | April 26, 2021
Seeing through the COVID-19 spin is a challenge even for those who have been writing and talking for years about the need to limit Big Pharma’s influence on health policy and law. Perhaps the greatest change I have seen in vaccine regulation, policymaking and law over the past four decades has been the development of public-private business partnerships between Big Pharma and the government.1 2 3 4 5 That seismic change has affected how new vaccines are developed, licensed and regulated and is influencing what we see happening today.6 7
Since the coronavirus pandemic was declared by government officials in early 2020, lawmakers have been persuaded to build the entire global pandemic response around a single experimental biological product.8 9 10 That single product is generating billions of dollars in profits for liability free drug companies and their partners.11 12 The COVID-19 spin is reaching dizzying new heights every day,13 14 with fundamental facts about the experimental product’s risks and failures getting lost in the hard sell.
At dinner time, if you turn on any major television network in the U.S., you will see that the evening news has turned into one long COVID vaccine commercial infused with a heavy dose of fear mongering. Before the pandemic declaration, we had learned to ignore prescription drug advertising in-between getting news of the day. Now newscasters and TV docs are Pharma’s new COVID “vaccine” sales reps and the only way to get away from the 24/7 sales pitch is to turn off the TV.
Billions of Dollars Paid to TV Networks for DTC Pharma Ads
We should not be surprised. The U.S. and New Zealand are the only two countries in the world that allow direct to consumer pharmaceutical product advertising.15 16 17 In this country. Big Pharma pays US television networks five billion dollars per year to push use of drugs and vaccines.18
Taking a page out of Big Tobacco’s old book and upping the ante, Big Pharma has become a business partner of government.19 The COVID business deal is perhaps the single biggest one in the history of public health programs.20 21 22
Already wealthy drug companies were given at least nine billion dollars from the. government to develop experimental COVID vaccines in record breaking time,23 shaving five to 10 years off the normal vaccine development, testing and licensing process.24 25 But that wasn’t enough. Congress also handed companies a liability shield from lawsuits whenever the product government paid them to produce fails to work as advertised or a person is hurt by using it.26
If you or a loved one dies or is permanently injured by an experimental or soon-to-be FDA licensed COVID vaccine, you cannot sue the drug company who made it, even if there is evidence the company could have made it less reactive or more effective.
Big Pharma Pays Big Tech Billions of Dollars for Ads, Censorship Campaigns
If you are searching for relief from the hype by turning off the TV and turning on your computer, you will be disappointed. The COVID vaccine ad campaign is in high gear online, especially on social media platforms. The Thought Police hired by Big Tech to censor information that does not conform with pre-approved pandemic narratives are making sure you do not have an opportunity to carefully weigh the vaccine’s benefits and risks.27 28 29
Rational thinking on the World Wide Web is no longer tolerated and neither is freedom of speech. The Internet has become a drug company stockholder’s dream and a consumer’s worst nightmare.
Big Pharma and its business partners have paid a lot of money to Big Tech to eliminate freedom of thought and speech online. Right now the weapon of choice is a social media censorship campaign to de-platform dissenters, including reputable charitable organizations like the National Vaccine Information Center publishing well referenced information.30 31 32 The Internet Thought Police are especially upset when anyone talks about reports of serious vaccine complications and deaths, but reports about COVID-19 disease complications and deaths are allowed without restrictions.33
As COVID social distancing regulations have kept more people at home and on their electronic devices, the healthcare and pharma industry has poured more money into direct to consumer digital ads.34 In 2020, drug and vaccine manufacturers funneled about 10 billion dollars into digital advertising that we view on our computers, tablets and cell phones.35 36
How much of Big Tech’s decision to ghost dissenters from search engine results and de-platform social media accounts is influenced by an infusion of direct to consumer advertising dollars from Big Pharma?37
American Taxpayer Pays for COVID-19 Vaccine Ads
This year, the American taxpayer is also paying for TV and digital advertising to promote the use of the COVID-19 vaccine.38 On April 1, 2021, the government announced a three billion dollar COVID vaccine ad campaign39 to get make sure that every American gets vaccinated, a national ad campaign that is using community and religious leaders, as well as celebrities,40 41 to reach into every community to boost vaccine uptake in stores,42 sports arenas,43 schools44 and churches.45
Right now, Pfizer and Moderna, the two U.S. corporations manufacturing experimental messenger RNA (mRNA) COVID-19 vaccines are leading beneficiaries of the free advertising paid for by tax dollars. The first to secure an Emergency Use Authorization (EUA) from the FDA, Moderna counts the federal National Institutes for Health as a business partner,46 while Pfizer partnered with the German company BioNTech.47 Together, Moderna and Pfizer have captured market share and, by the end of 2020, Pfizer had achieved a 180 percent increase in revenue48 49 and Moderna had scored an eye watering 3,900 percent increase. 50 51
So what has the COVID vaccine advertising blitz done so far, other than convincing half of all adults to get at least one dose of the vaccine by mid-April 2021?52
The most notable achievement of the COVID vaccine campaign has been to keep everyone in a constant state of fear and confusion about what is true and what is false.53 There are so many misunderstandings and false impressions out there about the biological product manufactured by Moderna and Pfizer, a product that most people call a vaccine and other call a therapeutic drug but I call a cell disrupter biological.
No Long Term Safety Studies of Experimental mRNA Vaccines
Whatever you want to call it, the experimental mRNA technology that Moderna and Pfizer employed to create the product has not yet been licensed by the FDA to prevent infections in humans. 54 It is a genetic engineering technology that radically departs from the production methods used for two centuries to make live attenuated and inactivated viral and bacterial vaccines.55 It is an experimental technology that injects synthetic RNA directly into cells and, in effect, attempts to turn the human body into a vaccine manufacturing machine.56 57
There are no long-term studies58 evaluating the range of effects at the cellular and molecular level on the biological and genetic integrity of humans who receive the product. Nobody knows if it will, over time, negatively affect normal immune function and cause autoimmune and other chronic inflammatory conditions in the body,59 60 61 or provoke enhanced disease in vaccinated persons encountering mutated versions of the coronavirus in the future.62
Myth: Pfizer and Moderna mRNA Vaccines Have Been Proven to Prevent Infection and Transmission of SARS-CoV-2
What are the two biggest myths that have been generated by the advertising campaign being conducted with Pharma and taxpayer dollars?
The first big myth is that if you get two doses of the mRNA COVID vaccine, you will get artificial immunity and cannot be asymptomatically or symptomatically infected with the SARS-CoV-2 virus and you will not be able to infect others who come in physical contact with you: you dutifully got vaccinated and now you are immune.63 That is a normal assumption because that is what vaccines are supposed to do, but it is a false assumption.
The Emergency Use Authorization the FDA gave to Pfizer and Moderna was not granted based on scientific evidence that the product prevented infection and transmission of SARS-Cov-2.64 65 In fact, the FDA directed manufacturers in the summer of 2020 to make a product that had at least a 50 percent efficacy rate in either preventing or reducing severity of COVID-19 disease.66
The companies chose to apply for an EUA based on nine months of clinical trial data that the product prevents people from developing severe symptoms of COVID-19 disease 67 and reduces the likelihood they will have serious complications leading to hospitalization and death – not that it prevents infection and transmission. There is a difference.
TAKE HOME FACT: COVID-19 vaccines were not designed and have not yet been proven to prevent infection and transmission of the new coronavirus in the majority of recipients. Apparently, that is why public health officials are telling vaccinated people they have to continue wearing masks and social distancing just like unvaccinated people.68 69
Myth: It is “Good” to Feel Bad After mRNA Covid-19 Shots Because It Means the Vaccine is “Working”
The second big myth being perpetuated by COVID spin is that when you have strong reactions to a COVID-19 shot, it is “good” because it means the vaccine is “working.”70 71
The companies and public health officials admit that the mRNA vaccines are reactive and that the majority of people, especially younger people, who get vaccinated will experience reactions strong enough to require a day or two of recovery and even time off work.72 73 But there is not one credible scientific study published in the medical literature demonstrating that high fevers, chills, headache, joint and muscle aching, disabling fatigue and other symptoms are “good” for the body and indicate the body is successfully producing artificial immunity.
In fact, strong reactions to pharmaceutical products like drugs and vaccines are usually something to be concerned about and a reason to exercise caution, especially with repeat doses. 74 75 76
More concerning are the 68,000 adverse event reports following COVID-19 vaccinations, including over 2600 deaths, 77 that have been reported as of April 8, 2021 to the federal Vaccine Adverse Event Reporting System (VAERS) created under the 1986 National Childhood Vaccine Injury Act.78 79 80 81 More than 70 percent of the reaction reports occurred in people between 17 and 65 years old. And that may be just the tip of the iceberg because one government funded study found that less than one percent of vaccine reactions are ever reported to the vaccine reaction reporting system82 created under the 1986 National Childhood Vaccine Injury Act.
Although Pfizer, Moderna and the government admit that messenger RNA COVID vaccines can cause a lot of reaction symptoms like fever, body pain and disabling fatigue,83 84 85 they adamantly deny that the shots cause sudden death86 87 88 or blood clots89 90 91 92 and bleeding disorders like immune thrombocytopenic purpura,93 cardiac and respiratory arrest,94 95 and other very serious health problems.96
Where is the biological mechanism science that proves it is only a coincidence when people suddenly die within minutes, 97 days or weeks of being given a COVID shot98 and that none of the tens of thousands of bad health outcomes being reported to the Vaccine Adverse Event Reporting System are causally related?99
Where is science backing up the claim that feeling so bad you can’t get out of bed or go to work after getting vaccinated is “good” because being in pain is evidence that the product is effective?
TAKE HOME FACT: COVID-19 shots cause reactions in the majority of people.100 101 There is no scientific evidence that having strong reactions to a drug or biological means that the product is effective.102
Government health officials have said that COVID-19 vaccines will be approved for use in children of any age by early 2022.103 With the majority of adults suffering very strong COVID vaccine reactions, especially younger adults,104 105 why are there plans to give the messenger RNA cell disrupter biological to infants and young children when the CDC says the majority of chilren with COVID-19 disease either have mild symptoms or no symptoms at all? 106
The enormous sums of money that Big Pharma and government is spending on television and digital ad campaigns to make sure that every child and adult in America gets a COVID-19 vaccine is creating false impressions and assumptions. When public policy precedes the science and aggressive advertising campaign blur the lines between facts and myths, truth gets lost in the spin and nobody is safe.
Go to NVIC.org and learn more about SARS-Cov-2 and the biological product being referred to as the COVID-19 vaccine on our new coronavirus information pages.
Go to NVICAdvocacy.org, where you can learn how to help defend informed consent rights in your state so you can make voluntary decisions about vaccination for yourself and your minor children.
References
1 Fisher BL. Here Comes the 21st Century Cures Act: Say Goodbye to Vaccine Safety Science. NVIC Newsletter July 21, 2015.
2 Ramsey L, Friedman LF. The government agency in charge of approving drugs gets a surprising amount of money from the companies that make them. Business Insider Aug. 17, 2016.
3 Fisher BL. End Pharma Liability Shield Endangering Public Health and Human Rights. NVIC Newsletter Nov. 8, 2016.
4 The Vaccine Reaction. Drug Companies Pay FDA and NIH to Fast Track and Market Vaccines. Sept 28, 2018.
5 Fisher BL. WHO, Government, Gates & Government: Who’s Calling the Shots? NVIC Newsletter Jan. 27, 2019.
6 National Academies of Sciences, Engineering, and Medicine. Public–private partnership responses to COVID-19 and future pandemics: Proceedings of a workshop—in brief. Washington, DC: The National Academies Press 2020.
7 U.S. Government Accountability Office (GAO). COVID-19: Federal Efforts to Accelerate Vaccine and Therapeutic Development But More Transparency Needed on Emergency Use Authorization. Nov. 17, 2020.
8 National Institutes of Health. NIH clinical trial of investigational vaccine for COVID-19 begins. NIH Press Release Mar. 16, 2020.
9 Lurie N, Saville M et al. Developing Covid-19 Vaccines at Pandemic Speed. NEJM Mar. 31, 2020
10 Fisher BL. COVID-19 Meltdown and Pharma’s Big Money Win. NVIC Newsletter Apr. 1, 2020.
11 Kollewe J. From Pfizer to Moderna: Who’s making billions from Covid-19 vaccines? The Guardian Mar. 6, 2021.
12 Egan M. Pfizer and Moderna could score $32 billion in Covid-19 vaccine sales – in 2021 alone. CNN Dec. 11, 2020.
13 Megan Garnett Coyle. Ad Tech Leaders Unite to Measure the Ad Council & COVID Collaborative’s COVID-19 Vaccine Education Initiative – the Largest PSA Campaign in US History. Businesswire Mar. 30. 2021.
History
14 Medical Xpress. US launches major COVI vaccination ad campaign. Apr. 1, 2021.
15 Lee B. How is Consumer Drug Advertising Regulated in the United States? June 17, 2019.
16 Harvard Health Publishing. Do not get sold on drug advertising. February 2017.
17 Rapaport L. U.S. health care industry spends $30 billion a year on marketing. Reuters Jan. 8, 2019.
18 Kanski A. Nielsen: Pfizer tops list of biggest pharma advertisers in 2018. Medical Marketing & Media Apr. 2, 2019.
19 Johnson B. Up in Smoke: Documents from the Annals of Tobacco Marketing. Ad Age Mar. 29, 2010.
20 Meyer R. Profiteering off a Covid vaccine. World of DTC Marketing Mar. 25, 2021.
21 Kollewe J. From Pfizer to Moderna: Who’s making billions from Covid-19 vaccines? The Guardian Mar. 6, 2021.
22 Dunleavy BP. Pfizer CEO says need for third dose of COVID-19 vaccine ‘likely.’ UPI Apr. 16, 2021.
23 Weintraub EW. Federal spending on COVID-19 vaccine candidates tops $9 billion, spread among 7 companies. USA Today Aug. 10, 2020.
24 The College of Physicians of Philadelphia. Vaccine Development, Testing and Regulation. The History of Vaccines Jan. 17, 2018.
25 Broom D. 5 charts that tell the story of vaccines today. World Economic Forum June 2, 2020.
26 Fisher BL, Parpia R. 2005 PREP Act and 1986 Act Shield Vaccine Manufacturer’s from Liability. The Vaccine Reaction Aug. 10, 2020.
27 Fisher BL. The New Internet Police Protecting You from Freedom of Thought and Speech. NVIC Newsletter Dec. 3, 2018.
28 Caceres M. When Even the New York Times Doesn’t Pass Facebook Muster. The Vaccine Reaction Dec. 28, 2020.
29 Mercola J. New Thought Police NewsGuard Is Owned by Big Pharma. Jan. 24, 2020.
30 Fisher BL. Vaccination and Censorship: The Truth Will Set Us Free. NVIC Newsletter Jan. 26, 2021.
31 O’Neill J. White House working with social media giants to silence anti-vaxxers. New York Post Feb. 19, 2021.
32 Attkisson S. CENSORED: The National Vaccine Information Center. Mar. 8, 2021.
33 Presson J. Questions linger about COVID-19 vaccine. The Mountaineer Feb. 12, 2021.
34 Droesch B. US Healthcare and Pharma Is Among the Fastest-Growing Digital Ad Spenders. EMarketer Oct. 9, 2020.
35 Droesch B. US Healthcare and Pharma Is Among the Fastest-Growing Digital Ad Spenders. EMarketer Oct. 9, 2020.
36 Silk B. Why Digital Is the Future for Pharma Advertising. Ethoseo Oct. 15, 2019.
37 Robbins R. Get ready for more drug ads: Facebook is making a bid for pharma dollars. STAT News Nov. 1, 2016.
38 Holmes K, Kaufman E. HHS begins national vaccine ad campaign with You Tube ads. CNN Dec. 4, 2020.
39 DHHS. U.S. Department of Health and Human Services Launches Nationwide Network of Trusted Voices to Encourage Vaccination in Next Phase of Public Education Campaign. HHS Press Office Apr. 1, 2021.
40 Facher L. The White House is set to unveil a wide-reaching billion-dollar campaign aimed at convincing every American to get vaccinated. STAT News Mar. 15, 2021.
41 Associated Press. Celebrities Make a Stand for COVID-19 Vaccines on TV Special. Voice of America Apr. 16, 2021.
42 Walmart. Administering COVID-19 Vaccines. Apr. 21, 2021.
43 Hoffman DC. Mass COVID-19 Vaccination Site Set to Open at PPG Paints Arena. KDKA2 Mar. 15, 2021.
44 Archie A. This Indiana school district is helping high schoolers get a COBID-19 vaccine before prom. Louisville Courier Journal Apr. 13, 2021.
45 AdventHealth News. AdventHealth Partners with Churches to Provide COVID-19 Vaccines. Apr. 20, 2021.
46 Collins FS. Statement from NIH and BARDA on the FDA Emergency Use Authorization of the Moderna COVID-19 Vaccine. NIAID Dec. 18, 2020.
47 Pfizer Inc. Pfizer and BioNTech Announce Further Details on Collaboration to Accelerate Global GOVIC-19 Vaccine Development. Businesswire Apr. 9, 2020.
48 Macrotrends. Pfizer Revenue 2006-2020. January 2021.
49 NASDAQ. Pfizer sees about $15 billion in 2021 sales from COVID-19 vaccine. Feb. 2, 2021.
50 NASDAQ. Moderna Earnings Date, Estimates & History. MarketBeat Apr. 16, 2021.
51 CBS News. Moderna forecasts $18.4 billion in COVID-19 vaccine sales. Feb. 28, 2021.
52 Yen H, Mattise J. Half of US adults have received at least one COVID-19 shot. Associated Press Apr. 18, 2021.
53 Syal A. Is It Safe to Visit Grandparents After Getting COVID Vaccine? NBC Feb. 14, 2021.
54 Pfizer Inc. The Facts About Pfizer and BioNTech’s COVID-19 Vaccine. Jan 6, 2021.
55 Banks MA. What Are mRNA Vaccines, and Could They Work Against COVID-19? Smithsonian Magazine Nov. 16, 2020.
56 Trafton A. Explained: Why RNA vaccines for Covid-19 raced to the front of the pack. MIT News Office Dec. 11, 2020.
57 Langreth R, Krege N. Moderna Wants to Transform the Body Into a Vaccine-Making Machine. Bloomberg News Aug. 11, 2020.
58 Harris R. Long-Term Studies of COVID-19 Vaccines Hurt by Placebo Recipients Getting Immunized. NPR Feb. 19, 2021.
59 Pardi N, Hogan MJ et al. mRNA vaccines – a new era in vaccinology. Nature Reviews Drug Discovery 2018; 17: 261-279.
60 Jaffe-Hoffman M. Could mRNA COVID-19 vaccines be dangerous in the long- term? Jerusalem Post Nov. 17, 2020.
61 Odell J. Messenger RNA (nRNA) SARS Coronavirus ‘Vaccines’ and their Potential Autoimmunity Part 2. Bioregulatory Medicine Institute Feb. 24, 2021.
62 Arvin AM, Fink K et al. A perspective on potent antibody-dependent enhancement of SARA-Cov-2. Nature 2020; 584: 352-363.
63 Healthline. How Long Does Immunity Last After COVID-19?: How vaccine-induced immunity after receiving immunization works. Feb. 24, 2021.
64 FDA. Pfizer-BioNTech COVID-19 Vaccine. Dec. 11, 2020.
65 FDA. Moderna COVID-19 Vaccine. Dec. 18, 2020.
66 Heidt A. FDA to Require 50 Percent Efficacy for COVID-19 Vaccines. The Scientist July 1, 2020.
67 Crist C. Early Vaccines Will Prevent Symptoms, Not Virus. WebMD Oct. 28, 2020.
68 Syal A. Is It Safe to Visit Grandparents After Getting COVID Vaccine? NBC Feb. 14, 2021.
69 Rouan R. Fact Check: CDC recommends masks in most cases even after COVID-19 vaccines. USA Today Apr. 22, 2021.
70 Crow S. The CDC Says These 3 Side Effects Mean Your Vaccine Is Working. Yahoo Feb. 15, 2021.
71 Finberg R. No, vaccine side effects don’t tell you how well your immune system will protect you from COVID-19. Yahoo News Apr. 19, 2021.
72 Hendler C. Severe Reactions to COVID-19 Vaccine Close Schools in Michigan, Ohio and New York. The Vaccine Reaction Mar. 8, 2021.
73 Farber M. Is the COVID-19 vaccine effective if you don’t have a reaction to it? Fox News Feb. 9, 2021.
74 Bircher AJ. Symptoms and danger signs in acute drug hypersensitivity. Toxicology 2005; 209(2): 201-207.
75 Davidovici BB, Wolf R. The challenge of drug-rechallenge: Facts and controversies. Clin Dermatol 2010; 281(3): 249-253.
76 GlaxoSmithKline Biologicals. Highlights of Prescribing Information for INFANRIX – diphtheria and tetanus toxoids and acellular pertussis vaccine adsorbed suspension: Contraindications, Warnings and Precautions. Nov. 20, 2019.
77 MedAlerts. Search the VAERS Database.
78 FDA. VAERS Overview. Mar. 29, 2019.
79 CDC. Vaccine Safety: Vaccine Adverse Event Reporting System (VAERS).
80 LaVigne P. The Story Behind MedAlerts. NVIC Newsletter Aug. 20, 2013.
81 The College of Physicians of Philadelphia. Vaccine Injury Compensation Programs: National Childhood Vaccine Injury Act (NCVIA)/National Childhood Vaccine Injury Program (NCVIP). The History of Vaccines Jan. 17, 2018.
82 Harvard Pilgrim Health Care, Inc. Electronic System for Public Health Vaccine Adverse Event Reporting System. AHRQ 2011.
83 The Vaccine Reaction. Moderna’s COVID-19 Vaccine Provokes COVID-Like Symptoms in Phase 3 Trial. Oct. 19, 2020.
84 Fisher BL. Over 3,000 “Health Impact Events” After COVID-19 mRNA Vaccinations. The Vaccine Reaction Dec. 22, 2020.
85 Gale J. COVID-19 vaccine side effects hit some recipients hard; that’s not all bad. Here’s what to do about them. Seattle Times Mar. 11, 2021.
86 Sforza T. Health care worker dies after second dose of COVID vaccine, investigation underway. Orange County Register Feb. 4, 2021.
87 Percy N. Kaiser says Pfizer vaccine likely not cause of Calfornia woman’s death. Mercury News Feb. 15, 2021
88 Brown E. Fact Check: Have 966 People Died After Receiving the COVID vaccine? Newsweek Mar. 8, 2021.
89 Goldstein S. Blood clots prevalent with Pfizer and Moderna Vaccine as with Astra Zeneca’s study. Dow Jones/Market Watch Apr. 16, 2021.
90 Ma A. Schuster-Bruce C. Johnson & Johnson asked other drugmakers to help it study blood-clot risks, and Moderna and Pfizer decline, report says. Business Insider Apr. 16, 2021.
91 Scribner H. Recent vaccine news should improve further confidence, doctor says. Deseret News Apr. 15, 2021.
92 Beusekom MV. Study: COVID much more likely than vaccines to cause blood clot. CIDRAP Apr. 15, 2021.
93 Fisher BL. Miami Obstetrician Develops Bleeding Disorder, Dies After Getting COVID-19 Vaccine. The Vaccine Reaction Jan. 11, 2021.
94 Israel National News. Mexican doctor hospitalized after receiving COVID-19 vaccine. Jan. 2, 2021.
95 Microsoft News. 72-year old man sent to ICU following COVID-19 vaccination; MOH confirms cardiac arrest wasn’t caused by vaccine. Feb. 19, 2021.
96 Fisher BL. Healthy Mom, 39, in Utah Dies of Organ Failure Days After Moderna COVID Vaccination. The Vaccine Reaction Mar. 15. 2021.
97 The Vaccine Reaction. Woman Dies Immediately After Getting COVID-9 Vaccine in Virginia. Feb. 21, 2021.
98 Haglage A. No evidence COVID-19 vaccines cause death epidemiologists say: ‘Coincidences are going to happen.’ Yahoo Feb. 4, 2021.
99 Rouan R. Fact check: CDC data on adverse effects of vaccine cannot determine cause. USA Today Apr. 8, 2021.
100 CDC. Local Reactions, Systemic Reactions, Adverse Events and Serious Adverse Events: Pfizer COVID-19 Vaccine. Dec. 13, 2020.
101 FDA. Moderna COVID-19 Vaccine. Dec. 18, 2020.
102 Finberg R. No, vaccine side effects don’t tell you how well your immune system will protect you from COVID-19. Yahoo News Apr. 19, 2021.
103 Thomas N. Fauci expects almost all children to be eligible for Covid-19 vaccines by first quarter 2022 at the latest. CNN Apr 18, 2021.
104 Koweek M. Younger adults are having harsher Covid vaccine side effects. WHIO TV Mar. 5, 2021.
105 Bendix A. Why you can expect more severe vaccine side effects if you’re younger or a woman. Business Insider Apr. 6, 2021.
106 CDC. COVID-19 in Children and Teens: What You Need to Know. Mar. 17, 2021.
Facebook deletes “I trust my immune system” profile photo frames under “misinformation” policy

By Christina Maas | Reclaim the Net | May 16, 2021
Facebook has a lengthy policy on what people are allowed to talk about in relation to COVID vaccines. However, as of the end of last week, the platform continued to host “pro-immune system” profile picture frames until it was contacted by CNBC News.
An analysis by CNBC News found out that there are dozens of profile picture frames promoting pro-immune system opinions. Some are using statements such as “I TRUST MY IMMUNE SYSTEM! #NOTASHOT.” Others didn’t mention the word vaccine, such as “I HAVE AN IMMUNE SYSTEM! #MedicalFreedom.”
Facebook has now deleted all of these frames.
A spokesperson for Facebook told CNBC that such frames did actually violate its policies, adding that the platform would remove frames with vaccine skeptic messages. In its policy on anti-vaccine misinformation, the platform prohibits, “promoting alternative treatments or natural immunity, celebrating those who refuse vaccination, and encouraging vaccine refusals without citing medical rationales or guidance,” and “claims that something other than COVID-19 vaccine can vaccinate you against “COVID-19.”
The spokesperson also noted that pro-vaccine frames are allowed and are trending on the platform.
“In countries where vaccines are available to most of the population, like the US and the UK, we ramped up our efforts to show people when their friends and neighbors share their support for vaccines through profile frames and stickers,” Facebook wrote in a blog post earlier this week.
REVIEW: COVID-19 Vaccines May Lead To Prion-Linked Brain Degeneration Similar To Mad Cow Disease
Researchers published a review that sounds the alarm about potential unintended COVID-19 vaccine side effects
By Tom Pappert | National File | May 12, 2021
A new review of possible unintended consequences of COVID-19 vaccines suggests that the controversial mRNA vaccines – Moderna and Pfizer – may lead to unexpected neurological conditions similar to Mad Cow Disease.
The review by Stephanie Seneff, who works at the Computer Science and Artificial Intelligence Laboratory at MIT, and Dr. Nigh, who specializes in Naturopathic Oncologogy at Immerson Health in Portland, Oregon, was released this week in the International Journal of Vaccine Theory, Practice, and Research, and devotes a considerable space to discussing the research of Dr. J. Bart Classen, who first published a research paper on the possibility of prion-linked brain degeneration caused by the COVID-19 vaccine last month, and expands on his research.
The researchers explain that “researchers have identified a signature motif linked to susceptibility to misfolding into toxic oligomers, called the glycine zipper motif. It is characterized by a pattern of two glycine residues spaced by three intervening amino acids, represented as GxxxG. The bovine prion linked to MADCOW has a spectacular sequence of ten GxxxGs in a row,” and notes that “the SARS-CoV-2 spike protein is a transmembrane protein, and that it contains five GxxxG motifs in its sequence” and, thus, “it becomes extremely plausible that it could behave as a prion”.
“Recall that the mRNA vaccines are designed with an altered sequence that replaces two adjacent amino acids in the fusion domain with a pair of prolines,” the authors continue. “This is done intentionally in order to force the protein to remain in its open state and make it harder for it to fuse with the membrane. This seems to us like a dangerous step towards misfolding potentially leading to prion disease.”
Prions were first described as the method by which Mad Cow Disease causes brain degeneration due to misfolding proteins in the body. The CDC notes that “prion diseases are usually rapidly progressive and always fatal.” Mad Cow Disease “progressively attacks the brain but can remain dormant for decades,” per the BBC.
“Pfizer claims the RNA fragments ‘likely… will not result in expressed proteins’ due to their assumed rapid degradation in the cell,” the researchers note. They add, “While we are not asserting that non-spike proteins generated from fragmented RNA would be misfolded or otherwise pathological, we believe they would at least contribute to cellular stress that promotes prion-associated conformational changes in the spike protein that is present.”
When Classen previously published his research, fact checkers were quick to point to public statements from Pfizer that dismissed concerns of brain prions as a result of their vaccine. It may be worth noting that “the most expensive settlement that Pfizer has paid was over $2.3 billion paid as a fine to resolve civil and criminal penalties for illegal marketing of four medications including Bextra, Geodon, Zyvox, and Lyrics.”
Oregon Governor Using New CDC Mask Guidelines to Impose Vaccine Passports and a Caste System
By Adam Dick | Ron Paul Institute | May 14, 2021
Some people have celebrated as a signal of the collapse of coronavirus crackdowns the Thursday announcement of the Centers for Disease Control and Prevention (CDC) that it is changing its guidance to indicate that people ”fully vaccinated” with experimental coronavirus vaccines need not wear masks indoors or outdoors or engage in so-called social distancing in many circumstances. Hopefully, the celebrating people are right. But, there are politicians out there, including Oregon Governor Kate Brown, who look at the new guidance differently — as a means to exert new types of control over people, including through mandating vaccine passports and a vaccine caste system.
Notably, United States President Joe Biden, who posted Thursday at Twitter that “The rule is now simple: get vaccinated or wear a mask until you do,” seems to have a similar take as does Brown.
In a Thursday statement, Brown noted that the Oregon state government will continue requiring all people, whether they have taken experimental coronavirus vaccines or not, to wear masks in public transportation situations and places including hospitals, health care clinics, correctional facilities, long-term care facilities, and schools, before describing the vaccine passport mandate and vaccine caste system the state will be imposing in light of the new CDC guidance.
Brown makes clear her determination that in Oregon only “fully-vaccinated” people may now legally be “in most public places” without wearing a mask and engaging in so-called social distancing. If you do not fit in that special category, Brown condemns you to a lower caste in Oregon where you must continue complying with such mandates.
Brown’s plan includes requiring “businesses, employers, and others” to either implement vaccine passports and a vaccine caste system or continue requiring mask wearing and social distancing compliance from everyone. Whether a business or other entity chooses Option A or Option B, it will be acting as an enforcer of the state’s abusive dictates. Brown explains in her Thursday statement:
In the coming days, the Oregon Health Authority will be providing updated guidance for businesses, employers, and others to allow the option of lifting mask and physical distancing requirements after verifying vaccination status. Some businesses may prefer to simply continue operating under the current guidance for now, rather than worrying about verifying vaccination status, and that’s fine.
Brown is doing her best to ensure freedom advocates have nothing to celebrate in her state. She likes her coronavirus crackdown, and she is working to keep the crackdown going as long as she can.
Copyright © 2021 by RonPaul Institute
Featured Video

Get ready for the big Israeli false flag cyber-attack
or go to
Aletho News Archives – Video-Images
From the Archives
Some Call It Conspiracy Theory – Part 1
BY IAIN DAVIS | SEPTEMBER 25, 2023
There are certain assumptions that are applied to anyone labelled a “conspiracy theorist”—and all of them are fallacies. Indeed, the term “conspiracy theory” is nothing more than a propaganda construct designed to silence debate and censor opinion on a range of subjects. Most particularly, it is used as a pejorative to marginalise and discredit whoever challenge the pronouncements and edicts of the State and of the Establishment—that is, the public and private entities that control the State and that profit from the State.
Those of us who have legitimate criticisms of government and its institutions and representatives, who are therefore labelled “conspiracy theorists,” face a dilemma. We can embrace the term and attempt to redefine it or we can reject it outright. Either way, it is evident that the people who weaponise the “conspiracy theory” label will continue to use it as long as it serves their propaganda purposes.
One of the most insidious aspects of the “conspiracy theory” fabrication is that the falsehoods associated with the term have been successfully seeded into the public’s consciousness. Often, propagandists need do no more than slap this label on the targeted opinion and the audience will immediately dismiss that viewpoint as a “lunatic conspiracy theory.” Sadly, this knee-jerk reaction is usually made absent any consideration or even familiarity with the evidence presented by that so-called “lunatic conspiracy theorist.”
This was the reason why “conspiracy theorist” label was created. The State and its propagandists do not want the public to even be aware of inconvenient evidence, let alone to examine it. The challenging evidence is buried under the “wild conspiracy theory” label, thereby signalling to the unsuspecting public that they should automatically reject all of the offered facts and evidence.
There are a number of components that collectively form the conspiracy theory canard. Let’s break them down. … continue
Blog Roll
 Aletho News
- ‘Stop Putting Drugs in Our Food’: Scientists Link Folic Acid in Food to Rising Rates of Colorectal Cancer
- The 14 Things That Happen to Your Newborn in the First 48 Hours
- JFK’s Forgotten Confrontation with Israel
- Trump’s Cyber Director Pick Has Deep Ties To Israeli Intelligence
- Get ready for the big Israeli false flag cyber-attack
- The Ukrainian Reset experiment: A war and surveillance state blueprint for the EU
- Pentagon fails ninth financial audit in a row, unable to account for trillions in assets
- Russia rejects Danish plot claims, vows response to expulsion
- Study of 14,000 Children Links Vaccination to Higher Rates of Chronic Illness
- Strike Iran Again, Open Pandora’s Box | Brian McGlinchey
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- New Study: Modern Temps Are Among The Coldest Of The Last 10,000 Years In East Central Europe
- Germany’s Renewable Energies Lead to 1.4 Billion Euro Electric Power Trade Deficit
- Argentina’s Perito Moreno Glacier Joins Antarctica and Arctic In Defying Doomsday Melt Claims
- New Study: Barents Sea Temperatures Were Warmer And Sea Ice Less Extensive In The 1700s Than Today
- German Authorities Start Initiative To Evaluate Public Register For Climate “Disinformation” Spreaders!
- Zonal Asymmetry of Temperature Change in the Antarctic Circumpolar Current
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean

