Unvaccinated German care home worker, accused of sparking a November 2021 outbreak that left three elderly women dead, faces criminal trial
eugyppius: a plague chronicle | January 18, 2023
From the Deutsche Presse-Agentur :
After a Corona outbreak that left three dead in a Hildesheim care home, a former employee will face trial in February…. She stands accused of one count of negligent homicide and two counts of negligent bodily injury, as well as forgery. The 45-year-old allegedly faked double vaccination against Corona by presenting a fake vaccine certificate …
Despite the infection of her son, the woman was at first allowed to continue working in late November 2021. … She is alleged to have been infected without noticing, and initially transmitted the virus to a colleague during a coffee break. Thus, a “chain of infection is alleged to have been set in motion.” Three female residents aged 80, 85 and 93 died in the outbreak.
According to the indictment, forensic medical examination revealed that Corona was the cause of death in the case of the 80-year-old. Other causes could not be ruled out for the other two victims … The woman has admitted to falsifying her vaccine certificate, but denies responsibility for the outbreak.
There were three other infections among home staff, and 11 among residents … Because the woman was known to oppose vaccination, her employer obtained information about the the date and batch numbers [listed on her certificate]. These … made it clear it was a forgery.
I’ve followed this case for a while, but I’ve avoided writing about it, because it just makes me depressed.
There’s the little things that irritate me, like the contact-tracing hocus-pocus and the ridiculous assumption that moments of transmission can be located as precisely as a coffee break. Or the awkward fact, that of the three Covid deaths this incident achieved for our un-unpluggable mortality ticker, medical examiners could assign only one to the virus with any confidence. The main thing, though, is just the incredible injustice of blaming fellow humans for infections with pervasive seasonal respiratory pathogens. This poor woman only faked vaccination to keep her job, and the outbreak at her home occurred well after the myth of vaccine efficacy against infection had collapsed. There’s just no reason to bring charges here.
If anything killed those old women, it was the care home and their decision to keep employees with positive close contacts at work. They almost certainly had no choice: These places suffer chronic staffing shortages, vastly exacerbated by pandemic-era mismanagement. And indeed, why should anyone work in a care home now? The pay is poor, you endure unusual levels of harassment over personal medical choices, and you can even face prosecution for passing on viruses your kids pick up at school.
‘Science Fiction Medicine’: Moderna Developing mRNA Injection to Treat Heart Failure
By Michael Nevradakis, Ph.D. | The Defender | January 17, 2023
Moderna raked in significant earnings in 2022, based on $18.4 billion in sales of its mRNA COVID-19 vaccine — the company’s one and only product on the market.
But in a Jan. 9 update on the company’s “industry-leading mRNA pipeline,” Moderna told investors it is developing multiple new mRNA products — including a treatment designed to be injected directly into the hearts of patients who have sustained heart attacks or heart failure.
Moderna said it launched a phase 1B clinical trial of its mRNA-0184 injection, which it said: “encodes for relaxin, a naturally occurring hormone that is known to cause hemodynamic changes that are potentially beneficial for heart failure patients.”
The company stated:
“The mRNA sequence of mRNA-0184 is engineered to instruct the body to produce relaxin with an extended half-life, with the goal of producing a sustained clinical benefit in heart failure patients — this longer half-life may result in more durable effects compared to previous approaches.”
According to the Daily Mail, mRNA-0184 “uses the same technology as the company’s flagship COVID jab and is designed for people weeks or months after a heart attack to help them recover,” by “instructing human heart cells to generate a hormone that is known to improve blood flow, helping restore damaged heart muscles.”
Patients in the trial “have stable heart failure and the trial will determine how safe the shot is and how well patients can tolerate it, as well as perfecting the dosage amount and frequency.”
In a Nov. 4, 2021, presentation introducing the novel mRNA-0184 therapy, Moderna claimed its “relaxin program … is being developed to treat decompensated heart failure.”
Relaxin is “a naturally occurring hormone that is known to cause” changes to blood flow that are “potentially beneficial for heart failure patients,” according to the company.
A federal disclosure filed by Moderna on Dec. 21, 2022, regarding its phase 1B clinical study indicates that 98 participants are expected to be enrolled and that the study is expected to be completed by May 7, 2024.
The clinical trials are taking place at six locations in Poland and the U.K.
In an October 2022 interview with Sky News Australia, Moderna CEO Stéphane Bancel said:
“We are now in a super exciting program where we inject mRNA in people’s hearts after a heart attack to grow back new blood vessels and re-vascularize the heart.
“It’s a bit like science fiction medicine but that’s what is really exciting to me.”
Prior to jumping into the race to develop a COVID-19 vaccine, Moderna had a long history of failure, as persistent safety concerns and other doubts about its mRNA delivery system threatened its entire product pipeline, according to investigative journalist Whitney Webb.
‘No safety track record’ for this type of genetic therapy, expert says
Cardiologist Dr. Peter McCullough, an outspoken critic of COVID-19 vaccines, was less enthusiastic than Bancel about Moderna’s mRNA injection targeting heart disease.
McCullough told The Defender :
“There is no safety track record for genetic therapies that introduce functional code for production of a protein for an uncontrolled quantity and uncontrolled duration of time. There are no assurances on long-term safety of mRNA technology.”
Previous similar efforts have failed, McCullough said, casting doubt on the possibility of success for the mRNA-0184 injection.
“In a large trials program, Novartis failed to show benefit with a similar hormone, serelaxin, thus the Moderna product looks unattractive as a heart failure therapeutic,” he said.
The Gateway Pundit, reporting on Moderna’s announcement, remarked, “In short, Moderna will fix the problem it created,” in a thinly veiled reference to the increased prevalence of heart disease and heart failure among individuals who received COVID-19 vaccines.
Moderna announces several more mRNA vaccines and therapeutics that are in its pipeline
Moderna stated that it has 48 programs in development, including 36 in ongoing clinical studies.
“Moderna continues to scale, now with 48 programs in development, including 36 programs in clinical trials encompassing mRNA infectious disease vaccines and mRNA therapeutics spanning seven different modalities,” the statement read.
Bancel said:
“We enter 2023 in a great position, with significant momentum across our clinical pipeline, a highly energized team and a strong balance sheet of over $18 billion of cash and cash equivalents.
“With our infectious disease franchise continuing to accelerate with exciting near-term catalysts for RSV [respiratory syncytial virus] Phase 3 data and Flu Phase 3 data, and recent breakthroughs in the development of individualized cancer treatments, as well as our rapid advancement in rare diseases and promising cardiology programs, the Moderna platform is delivering across several modalities.
“Our progress is meeting the high expectations we set out a few years ago, and with encouraging clinical data across the entire Moderna platform, we are accelerating our investments to deliver the greatest possible impact to people through mRNA medicines … 2023 is going to be a very exciting year for Moderna, and most importantly, for patients.”
These “exciting” developments, according to the company, include candidate vaccines and therapeutics for flu, RSV, cytomegalovirus and cystic fibrosis, as well as a “personalized cancer vaccine.”
As previously reported by The Defender, several Big Pharma companies, including Moderna, are vying to develop an RSV vaccine, despite repeated failed attempts to develop a vaccine for this illness in the past. These efforts have been ramped up just as many regions in the U.S. and worldwide are reporting outbreaks of RSV.
Moderna’s RSV candidate vaccine, which utilizes mRNA technology and is known under the identifier mRNA-1345, is currently in a phase 3 clinical study, according to the company’s announcement.
Moderna is also conducting two studies, with participants in the Northern and Southern hemispheres, of its candidate mRNA-1010 seasonal influenza vaccine, which also utilizes mRNA technology.
In conjunction with Merck, Moderna announced its mRNA-4157/V940 candidate vaccine — specifically, a “personalized” cancer vaccine that has been trialed on melanoma patients and which, according to Moderna, is the first treatment to have demonstrated “efficacy for an investigational mRNA cancer treatment in a randomized clinical trial.”
In addition to injectables, Moderna also announced the ongoing development of an inhalable mRNA therapy, VX-522, “mRNA targeted at treating the underlying cause of cystic fibrosis” that is “delivered to the lung.”
The company said it expects continued sales of its COVID-19 mRNA vaccine in 2023, stating “expected minimum COVID-19 vaccines sales of approximately $5.0 billion” and “potential additional contracts in the United States, Europe, Japan, and other key markets.”
Moderna’s announcement also referenced several recent acquisitions and new partnerships the company has entered into.
This includes the acquisition of OriCiro Genomics, “a Japanese company with a novel development approach for cell-free synthesis and amplification of plasmid DNA, a key building block of mRNA manufacturing.”
A “strategic research collaboration” with CytomX Therapeutics was also announced, “for [the] development of mRNA-based conditionally activated therapeutics for oncology and non-oncology conditions.”
Moderna’s ongoing partnership with Metagenomi, “to accelerate the development of in vivo gene editing therapeutics,” was also highlighted in its announcement. Metagenomi is funded by Bayer, which acquired Monsanto, producer of the widely used weedkiller Roundup, in 2018.
As previously reported by The Defender, thousands of lawsuits are currently pending in the U.S., claiming that Roundup causes cancer.
Michael Nevradakis, Ph.D., based in Athens, Greece, is a senior reporter for The Defender and part of the rotation of hosts for CHD.TV’s “Good Morning CHD.”
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Pregnant Women Reject COVID-19 Vaccination
Post-Partum Hemorrhage Among Many Reasons to Decline Experimental Injection
By Peter A. McCullough, MD, MPH | Courageous Discourse | January 18, 2023
Early in 2021 the American College of Obstetrics and Gynecology accepted an undisclosed amount of money from the US government (HHS WH) as part of the COVID-19 Community Corps Program. From that point forward, ACOG broke with traditional practice on experimental and and novel therapies being contraindicated, and with federal dollars in hand, moved to a wholesale endorsement of COVID-19 vaccination with no assurances on short or long-term safety. Throughout the campaign, enthusiasm for vaccination was tepid among gravid women with <20% at any time having accepted a vaccine. However, the sharpest decline in rates of uptake occurred in the gravid and by summer of 2022, fewer than 2% were getting vaccinated.

There were no large scale randomized, placebo-controlled double blind clinical trials demonstrating safety in pregnant women. The non-randomized literature was prone to financial conflict-of-interest bias since the doctors and editors were likely affiliated with ACOG, and influenced by the government money and aspiration to promote mass vaccination. Thus, as a clinical scientist, my concern is only the neutral papers on safety were being written and published. A paper by Dick et al, caught my attention by reporting a nearly fourfold post-partum hemorrhage rate among those triple compared to double vaccinated. One could imagine how large the magnitude would have been compared to unvaccinated where hemostasis is not impaired.

Dick A, Rosenbloom JI, Karavani G, Gutman-Ido E, Lessans N, Chill HH. Safety of third SARS-CoV-2 vaccine (booster dose) during pregnancy. Am J Obstet Gynecol MFM. 2022 Jul;4(4):100637. doi: 10.1016/j.ajogmf.2022.100637. Epub 2022 Apr 7. PMID: 35398583; PMCID: PMC8988438.
In 2021, McCullough and Stricker published that because of the known dangerous mechanism of action of COVID-19 vaccination and the lack of any assurances on maternal-fetal safety, that all of the products are considered pregnancy category X which means they should not be used. This message got out to the community and rates of vaccination have progressively winnowed. As we sit here today, we should understand that ACOG and the OB/GYN community is compromised and thereby putting the maternal-fetal health of women at risk by promoting COVID-19 vaccination. Under no circumstances should a woman of childbearing potential or gravid should receive a COVID-19 vaccine. It is absolutely contraindicated.
McCullough PA Lack of Compelling Safety data for mRNA COVID Vaccines in Pregnant Women, 2021
I just put the FAA in a “no win” situation. If there is not a PROPER investigation, heads should roll.

Susan Northrup is the current US Federal Air Surgeon, the first woman to hold this position.
By Steve Kirsch | January 21, 2023
I just had a nice chat with Federal Air Surgeon Dr. Susan E. Northrup. By the end, she no longer can say, “I didn’t know.” If she doesn’t act now, she should be prosecuted for jeopardizing pilot lives.
Executive summary
At 10:15am on Saturday Jan 21, 2023, I made a call to the private cell phone of the Federal Air Surgeon of the FAA Dr. Susan Northrup. The call lasted 2 minutes.
In the call, I referred to the news article where she basically said that she had seen no evidence that the COVID vaccines have incapacitated pilots.
At first I thought she was lying, but it turns out she was telling the truth. She’s seen no evidence because even though she admitted on the call that she knew about Bob Snow, nobody at the FAA ever bothered to call him. Ever!!! So they’ve never seen the evidence because they deliberately refused to look at the evidence!! Get it? That’s how science works.
So I asked Dr. Northrup if she was interested in speaking with pilots who have been disabled by the COVID vaccine. She indicated she was. After all, what could she say at that point? She had to say “yes.”
It’s troubling she hasn’t talked to Bob Snow. I have talked to Bob Snow. I interviewed him for my Rumble channel even though it isn’t my job to investigate these incidents. Check out my interview with Josh Yoder and my interview with Bob Snow.
In other words, I’ve done more to investigate this incident than the FAA.
Captain Snow narrowly averted crashing the plane, but she never talked to him to assess whether the vax might have been involved. Seriously?!?! I offered to put her in touch with Captain Snow and she accepted.
So I emailed her (using her official work email at the FAA) a list of pilots, their phone numbers. She now has the contact info for these pilots:
- Josh Yoder (head of US Freedom Flyers who is in touch with dozens of vaccine injured pilots)
- Bob Snow (American Airlines)
- Kevin Stillwagon (Delta Airlines)
- Cody Flint (4 doctors have determined he was incapacitated in flight due to the COVID vaccine)
- John C. Lamb (66 yr old commercial aviator with no previous heart problems. On Jan 6, his first class medical was deferred, due to 2nd AB block, Mobitz type 2. His wife had a heart attack 8 days after her Moderna shot. See this story for more details).
More importantly, in that email, I also invited her to host a public roundtable at the FAA inviting people on both sides of the “safe and effective” narrative so that the FAA could learn the truth. I just talked to Senator Ron Johnson and I can assure you that he’d be DELIGHTED to help her assemble a roundtable of doctors on both sides of the narrative to brief top FAA officials on the risks of these vaccines.
And I offered to publish her revised statement to the public so we can get the truth out that the vaccines are NOT safe and are disabling pilots.
Here’s the kicker. The corruption at the FAA runs deep. Did you know that nobody at the FAA has ever called Bob Snow? How can the FAA investigate this incident without ever even talking to the pilot?
Susan is going to have to reveal to the American public what exactly the FAA did to investigate the Bob Snow incident which happened on April 9, 2022. How is it that in 9 months nobody at the FAA (or from any other government organization) has reached out to Captain Snow? WTF? We need some transparency here on how these vaccine incidents are being investigated!
But Susan knew about Snow and she must have known that nobody reached out to call him. In other words, everyone knew they had a vaccine injured pilot and deliberately chose to NOT investigate. I have asked Susan for an explanation. If I don’t receive an explanation in 24 hours, I will call for her to resign.
I am calling for this since nobody in Congress is (other than Senator Johnson). None of them want to know. Heck, when I call members of Congress, they ignore me. Neither does the mainstream media. It appears that the responsibility for investigating these incidents falls on Steve Kirsch’s Substack (which has a full-time staff of just me) to hold these people accountable.
Susan is also going to have to talk about why there was a 300% increase in long-term disability claims filed at American Airlines (Jan – July 2022) and what investigation the FAA made into what was disabling those pilots.
We have a pilot shortage in America. What did Susan find when the FAA investigated why the disability claims skyrocketed? Or did they do nothing to investigate? If they didn’t do anything, why didn’t they? I’d like to know. The New York Times and CNN …. well, not so much.
Finally, did you know that Susan’s husband, John Hyle, is a pilot. John refused to take the COVID vaccine due to safety concerns. So it’s not just a few “anti-vaxxers” spreading “misinformation.” Susan clearly realizes that intelligent people she clearly respects have legitimate concerns that cause them to refuse to take the shot.
The narrative is falling apart.
We need public transparency on all of the things above. And we need it now before lives are lost.
We’ve had a couple of close calls. The FAA needs to be proactive about this, not REACTIVE after a crash happens.
Fired Workers Sue New York City, Seek $250 Million and End to COVID Vaccine Mandate
The Defender | January 20, 2023
New York City public-sector workers who lost their jobs for refusing to comply with the city’s COVID-19 vaccine mandate on Thursday filed a $250 million lawsuit against the city and Mayor Eric Adams seeking to end the mandate.
The 72 fired workers are demanding the city overturn the mandate, reinstate their jobs and compensate them with punitive damages.
The workers argue the mandate should be found “arbitrary and capricious” given that “President Joe Biden, Governor Kathy Hochul and Senator Chuck Schumer have all declared that the pandemic is over,” and that it was already rescinded for private sector employees and students, according to the lawsuit.
The lawsuit, filed in the Bronx County Supreme Court of the State of New York, also alleges the plaintiffs were discriminated against with “willful or wanton negligence, or recklessness” and were mocked and ridiculed by their colleagues.
Many of the plaintiffs — formerly with the New York Police Department (NYPD), the New York Fire Department, the Department of Education, the Department of Health and other agencies — worked for the city for more than 20 years but now are unemployed, have lost their homes and their ability to support their families, the lawsuit states.
Attorney James Mermigis, who represents the plaintiffs, told The Defender :
“Anybody that goes into the city does not have to be vaccinated except for NYC public sector workers, including firemen, policemen, teachers.
“I just think it is absurd, especially once Mayor Adams lifted the mandate for private employees, that these people, who were heroes during COVID-19, still have the mandate.”
According to the lawsuit, Adams admitted, “I don’t think anything dealing with COVID is makes sense [sic], and there’s no logical pathway of what one can do[sic].”
The lawsuit also alleges the COVID-19 vaccines don’t prevent disease transmission and that it is well-established that the risks of vaccination outweigh the benefits.
It also argues the plaintiffs have immunity from prior infection that should exempt them from any mandate, because “the scientific community has conclusively established that natural immunity provides strong and durable protection.”
According to the lawsuit, the city used, “a discriminatory practice to coerce, intimidate, threaten, or interfere with Petitioners in their exercise or enjoyment of their closely held religious beliefs,” by failing to engage in “cooperative dialogue” with them regarding their petitions for religious exemption, which were denied.
The plaintiffs seek $250 million in punitive damages.
“[Punitive damages] punish the city for its behavior towards its employees in the hopes that they will establish policies in the future that will prevent this from happening again,” Mermigis said.
Landmark win for New York healthcare workers may help city workers
Alleging New York City lacked the authority to institute COVID-19 vaccine mandates, city workers cited the landmark ruling earlier this month by the New York Supreme court, which struck down the state’s COVID-19 vaccine mandate for healthcare workers.
In that case, which Children’s Health Defense (CHD) financed, the court held that the state’s health department lacked the authority to impose the mandate.
In the ruling, Judge Gerard Neri declared the mandate “null, void, and of no effect.”
The court also ruled that the state’s mandate was “arbitrary and capricious” on the basis that COVID-19 vaccines do not stop transmission of the virus, thereby eliminating any rational basis for such a policy.
That lawsuit was filed Oct. 20, 2022, by Medical Professionals for Informed Consent and additional plaintiffs against NYSDOH, New York Gov. Kathleen C. Hochul and Mary T. Bassett, the state’s health commissioner.
Commenting on the Supreme Court ruling in favor of healthcare workers, Mermigis said he believes the decision will help the workers’ case against the city.
“It puts less pressure on the judge reading our lawsuit knowing that another judge in New York also eliminated a healthcare vaccine mandate,” Mermigis said.
Michael Kane, CHD’s national grassroots organizer and founder of Teachers for Choice, said:
“It’s historic what Sujata Gibson and CHD were able to do and it’s part of the cascading falling dominoes. It really feels like it’s just a matter of time.
“They will delay as much as they can, but public opinion has shifted. The courts are no longer afraid. Judges are no longer afraid to rule lawfully, and we are starting to see that.”
Court of public opinion is shifting
More than 1,750 city workers were fired for refusing vaccination, including 36 members of the NYPD and 950 Department of Education employees, The New York Post reported.
Many of them brought — and won — lawsuits against the city. But the city appealed all of the rulings challenging its vaccine mandate for public employees, The Defender reported.
On Sept. 13, 2022, a Manhattan Supreme Court ruled that unvaccinated NYPD officer Alexander Deletto could keep his job. The city appealed that ruling.
In a Sept. 23, 2022, ruling, Manhattan Supreme Court Justice Lyle Frank reinstated the jobs of several unvaccinated members of the NYPD’s union, the Police Benevolent Association of the City of New York. The city also appealed that decision.
On Oct. 5, 2022, Staten Island Supreme Court Justice Ralph Porzio ruled New York City must reinstate a Staten Island firefighter. The city appealed that decision as well.
Later in October 2022, Justice Porzio struck down New York City’s COVID-19 vaccine mandate for public workers, ruling in favor of 16 unvaccinated city workers who sued following their termination. That decision is currently being appealed.
According to Kane, however, the tides are turning — and that could be significant for the lawsuit filed Thursday.
Kane said:
“We are now seven days into the [CHD] victory and there has been no appeal. This is the first case for New York employees that have been fired that has stood for even seven days …
“The most important thing now is that the court of public opinion is different. I really feel that we are winning the majority in the court of public opinion, and that influences what happens in all of these courts …
“We are definitely rooting for him [Attorney Mermigis] and hoping he is very successful with the case.”
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Meta gave the CDC de facto power to police Covid “misinfo”
By Didi Rankovic | Reclaim The Net | January 20, 2023
The mask is slipping (pun fully intended), all over the place – regarding the Big Tech/Big Government collusion. Now it’s time to pay close attention to the role played by the Centers for Disease Control and Prevention (CDC).
We’ve already been awed – just by the magnitude of the whole thing – if not exactly “shocked” by the Twitter Files.
After all, while it was happening, a whole lot of observers surmised that something of the sort had to be behind the unprecedented and, seemingly inexplicable levels of censorship on the platform.
But – what in the world was happening at Facebook, around the same time? After all, Facebook is an almost orders of magnitude bigger and more influential social network than Twitter.
For the time being, we don’t have the same “direct line” to internal documents as is the case with Twitter, which was made possible by the dedication to transparency by the new owner himself.
However, what could be dubbed as the “Facebook Files” are based on credible sources, too – Reason is coming out with a story based on confidential emails that emerged thanks to a court case – the state of Missouri suing the Biden administration.
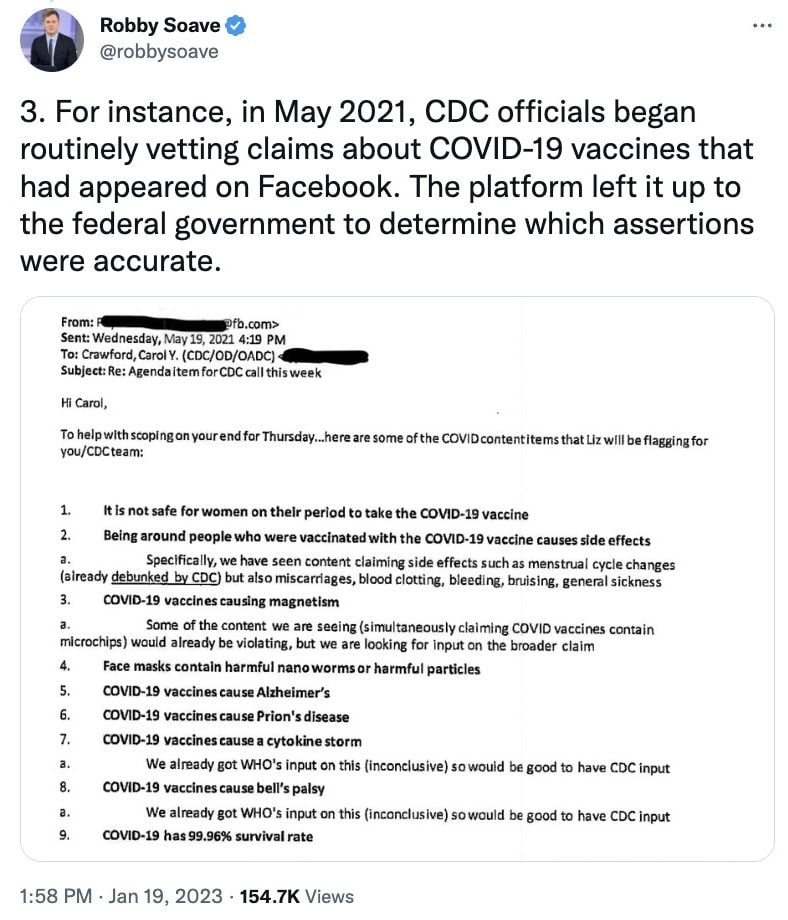
The emails show that Facebook (and by extension Instagram) representatives and the CDC not only kept in touch at all times, but that the tech giant also “routinely asked government health officials to vet claims relating to the virus, mitigation efforts such as masks, and vaccines.”
In turn, the CDC kept a watchful eye on what speech was allowed on Facebook, what policies toward censorship of “inconvenient” Covid topics applied, and this government agency had no problem instructing the social network behemoth how to behave in these instances.
Robbie Soave, a senior editor for Reason, revealed some examples of what was happening in a series of tweets citing the emails and providing screenshots. One shows that in May 2021, CDC started to get involved in “vetting” content on Facebook that concerns Covid vaccines. And CDC had the last word on what was allowed to remain online as “accurate.”
Other emails show that Facebook (Meta) made sure the CDC was given de facto power to police Covid “misinformation,” while at the same time flagging content for the CDC, consulting with it on claims that could “contribute to vaccine refusals.”

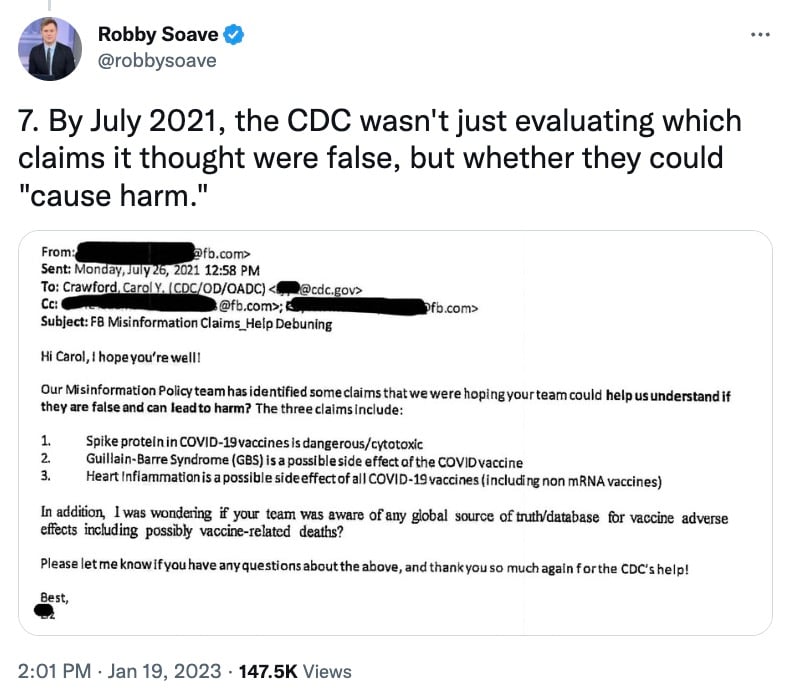


At the same time, Reason is acknowledging that this was by no means the only federal agency to engage in similar activities, all aimed at pressuring some of the world’s biggest social platforms to allow only a certain narrative, and discredit any skepticism, even that coming from medical professionals and scientists.
Even President Biden made sure to “contribute” to this effort, when he in June 2021 bizarrely accused Facebook of “killing people.”
This was really meant to say that the giant had better not dare allow any Covid content the White House failed to “vet” behind the scenes – one way or another.
And the giant obliged, sometimes probably even exceeding the level of compliance expected from the administration. An internal email now reveals that Facebook went as far as to “snitch” on its own users making fun of Anthony Fauci, apparently in a bid to defend his reputation – again, at the expense of free speech.
“One email warned the CDC that Facebook users were mocking Fauci for changing his mind about masking and double-masking. The CDC replied that this information was ‘very helpful’,” Soave, the magazine’s senior editor and host on The Hill TV channel, tweeted.
The upcoming, March issue of Reason delves into how the CDC turned into the speech police when it came to pressuring social media to block content that the government agency decided was Covid “misinformation.”
And this was online speech that this, and other government agencies, have no constitutional way of directly suppressing without breaking the law.
“There is a word for government officials using the threat of punishment to extort desired behaviors from private actors. That word is: jawboning,” Soave remarked in one of the tweets.
And one can imagine – and the emails now show – just how gun-shy and ready to please those in power Facebook had become, after years of public vilification, and who knows what kind of pressure behind the scenes in the wake of the 2016 US election.
GMC Blinks First: Regulator Declines to Investigate Dr Aseem Malhotra Over Vaccine Warnings in BBC Interview

BY NIALL MCCRAE | THE DAILY SCEPTIC | JANUARY 21, 2023
To paraphrase the Sound of Music song, “How do we solve a problem like Malhotra?” After receiving several complaints, the General Medical Council has decided not to investigate cardiologist Dr. Aseem Malhotra, who has become a thorn in the side of the medical profession.
Professional regulators have been at the forefront of pandemic discipline, contributing to a culture of fear among practitioners. Severe action has been taken against registrants who criticise or do not comply with the official narrative. I know this from my experience as an officer of the Workers of England Union, representing members brought before the Nursing and Midwifery Council on charges of bringing the profession into disrepute. Apparently the public must be protected against nurses who don’t believe that masks stop airborne respiratory viruses, or who believe in informed consent for novel mRNA vaccines.
A significant strike against this censorial tyranny was by general practitioner Sam White last year. Dr. White was ordered, as a condition of maintaining his clinical licence, to delete his social media posts about COVID-19 and to refrain from making similar comments. Dr. White took the GMC to the High Court and won. The condition was overturned as a breach of his rights to freedom of expression under the Human Rights Act 1998.
Whereas White was an early critic of COVID-19 policy, Malhotra is a relatively recent convert. Initially he promoted the vaccine, but when his fit and healthy father died shortly after receiving the injections, Malhotra changed his mind and began speaking out against the mass vaccination programme. His personal loss came alongside his observation in clinical practice of a marked increase in myocarditis cases (as well as blood clots and other cardiac complications). Malhotra had a review paper published on this phenomenon, and his findings of iatrogenic harm are corroborated by other medical scientists.
Malhotra has repeatedly urged suspension of the vaccination programme until the risks are better understood. He became a darling of vaccine sceptics, with his charismatic and compassionate voice doing the rounds of alt media channels and independent-minded broadcasters working for more mainstream channels (such as Tucker Carlson’s show on Fox News, and Neil Oliver on GB News ). However, he was ignored by the legacy media, and it was not until two weeks ago, when he took the opportunity of a BBC interview on statins, that his call was more widely heard.
The context for Malhotra’s BBC appearance was a claim by Chief Medical Officer Chris Whitty that cardiac morbidity had increased as a result of limited access to statins during lockdown. Malhotra disagreed, explaining that myocarditis is unrelated to cholesterol level, which statins are meant to control. He instead blamed the vaccines, telling the BBC presenter that this radical medical intervention should be halted. Cue outrage.
The Guardian did a particularly nasty report on Malhotra, smearing him as a peddler of an ‘anti-vax’ conspiracy theory. Numerous doctors expressed their outrage on social media, angered by the BBC giving a platform to this known sceptic, who they accused of hijacking an interview on a different topic. Some reported Malhotra to the GMC.
The GMC’s decision not to act against Malhotra is a victory for science, ethics and common sense, but we should not get ahead of ourselves. This was a reluctant decision by the regulator, as the wording of their response to the referrals shows:
We recognise that Dr Malhotra has views on the COVID-19 mRNA vaccines that are at odds with the national and international scientific and medical communities. We also recognise that his words are strong and there is a question around the accuracy of his statements. There is currently no evidence that Dr. Malhotra has engaged in the type of Covid conspiracy related conduct that has to date justified regulatory action.
Note here the emphasis on consensus, as if that amounts to truth. It seems that if Malhotra had followed the likes of James Delingpole or Maajid Nawaz down the rabbit hole of globalist conspiracy, he would have been in big trouble. The GMC continued:
We also feel it is relevant that Dr. Malhotra started expressing his concerns about the vaccines in late 2021 and by this time the vaccine programme was well underway with the vast majority of vaccines delivered before this time. We would suggest that Dr. Malhotra’s impact on the COVID-19 vaccination programme in the U.K. could only have been negligible.
This is the most worrying line in the GMC response. If Malhotra is right about the risks of these vaccines, the GMC should be concerned that doctors were inhibited from speaking out earlier, thereby potentially saving lives. Instead, the GMC assumes that Malhotra is wrong, and that his remarks have not stopped the biggest vaccination drive in history.
The GMC acknowledged that Malhotra has a right to freedom of expression under Article 10 of the Human Rights Act, although that is not an absolute right for a medical practitioner. His outspoken opinions on the vaccines, according to the GMC, are “not so egregious as to justify a public hearing and a forum for further scepticism to be aired as to aspects of the COVID-19 pandemic and response”.
This, I believe, is the real reason why the GMC has decided not to take any further action. Any proceedings would inevitably attract publicity and give Dr. Malhotra a platform to air his sceptical views. Ultimately, the truth will get out, and those who tried to hide it will be judged by history.
Dr. Niall McCrae is a former university lecturer who now works for the Workers of England Union.
The Re-education of Dr Sally Price
A culture of fear and censorship in the Australian medical profession
By Rebekah Barnett | Dystopian Down Under | January 14, 2023
On a Friday in August 2021, Dr Sally Price received a phone call from the Australian Health Practitioner Regulation Agency (AHPRA). There had been an anonymous complaint against her, and AHPRA was to follow up with an investigation.
“So of course, I was checking my email all afternoon,” says Dr Price, who describes the ensuing investigation as, “destructive” and “very stressful.”
At the time, Dr Price was a practicing GP in Perth, with additional qualifications in nutritional medicine and Ayurveda. In over 30 years of practice, Dr Price had never received a complaint, and she was mystified as to which of her patients could possibly have complained to AHPRA.
When the email from AHPRA finally arrived in her inbox, Dr Price was surprised to find that the complaint was not from a patient, but from a social media follower who, to the best of her knowledge, she has never met or had any contact with.
The complaint centred around five Facebook story posts, four of which were reposted content from a non-partisan, pro-choice activist group called Reignite Democracy Australia (RDA). Two of the posts referenced efforts of politicians (in Australia and Italy) to resist vaccination mandates. Another story was a repost offering insight into the physiological effects of the fear response.
The complainant characterised the reposts as “anti-vaccination,” though none of the posts gave advice on vaccination or stated any opinion on the Covid vaccines. This was all that was required for AHPRA to launch an official investigation into Dr Price’s conduct.
AHPRA’s position statement on the Covid vaccination rollout (March 2021) set the bar for such vague complaints to trigger investigations, when they specifically barred doctors from expressing messages that could be construed as anti-vaccination on their social media:
”There is no place for anti-vaccination messages in professional health practice, and any promotion of anti-vaccination claims including on social media, and advertising may be subject to regulatory action.”
Dr Price was given two weeks to respond, during which time she engaged with her indemnity organisation in a highly stressful back-and-forth, knowing that her reputation, and maybe even her licence were on the line. Dr Price was strongly advised to offer to undergo ‘re-education’ at her own cost, so as to avoid more serious consequences, such as suspension, or having conditions imposed.
AHPRA agreed that Dr Price should undergo 10 hours of re-education and submit a letter of reflection detailing what she had learned from the process. “What you have to do is pull your forelock and tell AHPRA that you’ve been a very naughty girl,” says Dr Price.
As part of her re-education, Dr Price was required to study the Australian Medical Association’s (AMA) Code of Ethics (2017). Ironically, this firmly established in Dr Price’s mind that the AMA’s Code of tehics and AHPRA’s position statement on the Covid vaccination rollout were at odds with each other. “As I studied the AMA Code of Ethics, I was struck by how AHPRA’s position statement overrode our professional ethics, and that had me more deeply concerned,” says Dr Price. “It highlighted to me that none of this was ok.”
The AMA’s Code of Ethics states that doctors must, “consider first the well-being of the patient,” (Article 2.1.1) and that they must provide full informed consent before undertaking any tests, treatments or procedures (Article 2.1.4). Dr Price says that AHPRA’s position statement and hawkish regulatory behaviour put the public health agenda before the patient and made it “impossible” for doctors to provide valid informed consent to patients.
AHPRA’s unilateral decision that all doctors must fall in line with the vaccination rollout was also in conflict with the AMA Code’s provision that doctors may conscientiously object to providing certain treatments or procedures (Article 2.1.13), and that they may publicly state opinions contrary to the status quo (Article 4.3.3). Further, the Code requires that doctors “practise effective stewardship, the avoidance or elimination of wasteful expenditure in health care…” (Article 4.4.1), and that they use their “knowledge and skills to assist those responsible for allocating health care resources, advocating for their transparent and equitable allocation.” (Article 4.4.3) These articles imply a responsibility for doctors to speak out and take action when they believe that public health policy could be improved upon.
Feeling conflicted about how to practice good medicine under these conditions, Dr Price decided to take some leave to reflect and regroup. She lodged a complaint with Ahpra and the Ombudsman, requesting either a waiver to excuse her from the requirements of AHPRA’s position statement, or that AHPRA explain how she might be able to practice under their conditions whilst also keeping to the AMA’s Code of Ethics. No waiver or explanation was provided, and so Dr Price determined that continuing to practice as a GP was untenable. Her registration has since lapsed.
Dr Price says that, as it stands, the system has strayed from its primary purpose of letting doctors be doctors, and putting patients first. She speaks to a culture of fear within the medical profession. “The thing to understand is that doctors feel like someone is always behind them waiting to stab them in the back or put a bag over their head. That’s how it feels being under AHPRA,” she says.
The censorial nature of AHPRA’s regulatory practices was brought into the national spotlight several weeks ago by former AMA president Dr Kerryn Phelps, who recently revealed that she is Covid vaccine injured. In a submission to the federal government’s Long Covid Inquiry (Submission #510), Phelps wrote, in reference to the aforementioned AHPRA position statement,
“Regulators of the medical profession have censored public discussion about adverse events following immunisation, with threats to doctors not to make any public statements about anything that ‘might undermine the government’s vaccine rollout’ or risk suspension or loss of their registration.”
This is a view also held by cardiologist and Australian Medical Professionals’ Society (AMPS) founder, Dr Chris Neil, who warned in a recent article for Spectator Australia, that many medical professionals believe that not only is the AHPRA position statement unlawful, but that “it is at the root of a dangerous shift in Australian Medicine.” Neil points to the changes to the National Law for Health Practitioner Regulation introduced last October in the Queensland Parliament.
The changes, which the AMA strongly opposed, will further compel doctors to fall in line with public policy decided by bureaucrats, and will create a culture of ‘guilty until proven innocent’ by way of publicly naming and shaming medical professionals who are under investigation. AMPS has gone on the defensive with a Stop Medical Censorship national tour, on which medical, legal and other professionals gather to speak to audiences about the implications of censorship in medicine.
Dr Price says she feels damaged by the experience of being investigated by AHPRA, and she may not return to the profession. “I’m not sure that I want to come back. If medicine were to return to its ethical code, I will reconsider.”
Florida Governor Ron DeSantis’ “Prescribe Freedom” plan bans vaccine passports, supports doctors’ free speech

By Cindy Harper | Reclaim The Net | January 19, 2023
Florida’s Republican Gov. Ron DeSantis plans to introduce legislation that will, among other things, stop Florida from being a “biomedical security state.” The legislation will ban all vaccine passport mandates.
DeSantis said the purpose of the legislation is to “prescribe freedom.”
“When the world lost its mind, Florida was a refuge of sanity, serving strongly as freedom’s linchpin,” the Republican governor said on Tuesday. “These measures will ensure Florida remains this way and will provide landmark protections for free speech for medical practitioners.”
“It required us over the past few years to stand against major institutions in our society: The bureaucracy, the medical establishment, legacy media, and even the President of the United States who, together, were working to impose a biomedical security state on society,” he added.
DeSantis’ surgeon general Dr. Joseph Ladapo said he supports the bill because it would protect the free exchange of ideas between medical professionals.
“As a health sciences researcher and physician, I have personally witnessed accomplished scientists receive threats due to their unorthodox positions,” Ladapo said. “However, many of these positions have proven to be correct, as we’ve all seen over the past few years. All medical professionals should be encouraged to engage in scientific discourse without fearing for their livelihoods or their careers.”
The legislation would protect medical professionals’ freedom of speech by protecting their religious views and their right to disagree with the preferred narrative. The bill would also protect medical freedom of choice by banning discrimination based on vaccination status, testing, and mask-wearing.

Related:
California’s chilling medical misinformation law is an affront to the US constitution
MHRA Passes the Buck: “All the Covid Vaccine Authorisation Decisions Were Taken by the Government Minister”
The Blame Game Begins
BY NICK DENIM | THE DAILY SCEPTIC | JANUARY 19, 2023
I have just received a very interesting MHRA reply to an FOI request about whether the Healthy Secretary delegated Covid vaccine decisions to the MHRA.
MHRA said “All the Covid vaccines and therapeutics authorisation decisions were taken by the Licensing Minister and were not delegated.”
What makes this so interesting is the wider context. Under the Human Medicines Regulations, the Licensing Authority is the Secretary of State for Health. He or she delegates to MHRA all the work associated with that – licensing of medicines, pharmacovigilance, inspection of manufacturers, enforcement and so on.
But for the Covid vaccines, MHRA is saying that the Secretary of State personally took all the decisions.
I read that as the blame game having started. I’ll explain why.
Back in 2020, MHRA would have known only too well that the clinical trials had been rushed (10 months compared with typical time to market of 5-10 years), had not been comprehensive (e.g. limited pharmacokinetics/pharmacodynamics) and wouldn’t finish until 2024. There were many warnings from experts around the world. MHRA’s line about ‘rolling review’ was, and remains, bunkum.
MHRA scientists and officials would have known about the problems (with all medicines) of scaling up production from small-scale, laboratory-based production for trials purposes to full-scale production. For example, larger quantities of ingredients can be more difficult to mix. They wouldn’t therefore have been surprised to have seen batch problems with the Covid vaccines around the world. One batch resulted in the hospitalisation of 120 children in Vietnam. One batch caused ocular injury to nurses when a vial was broken. In Japan, 1.63 million doses were recalled due to metallic contamination. Probably just the tip of the iceberg.
MHRA then saw adverse event reporting starting to reveal serious safety issues in the U.K. and around the world. First, myocarditis and blood clots, in March 2021, a few weeks after approval of the AstraZeneca vaccine (now effectively withdrawn) and later other heart issues, neurological problems and immunosuppression with Pfizer and Moderna.
MHRA knew in 2020 that the risk to younger age groups from Covid was very low and after rollout it would have seen assessments of vaccine effectiveness falling month on month. It wriggled hard against the evidence in the UKHSA weekly surveillance reports that vaccine effectiveness was even negative for younger age groups.
Since then the Covid vaccine narrative has continued to take a pounding as more clinicians around the world speak up, the research evidence about cardiac, neurological and immunosuppression problems continues to pile up, and the 1,000 per week excess deaths have still not been explained.
MHRA might have been criticised by Baroness Cumberlege for being “unresponsive and defensive”, but its staff aren’t all deaf, blind or stupid. They knew.
So my inference is that the blame game has started.
Mind you, MHRA is on a sticky wicket in any blame game. There are serious shortfalls in its own safety management:
- It doesn’t have a process for investigating individual Yellow Card reports. It says it tries to investigate individual fatal and serious Yellow Card reports but it doesn’t have a process so it doesn’t know how many it has investigated (FOI 21/1109);
- It’s never had a safety audit (FOI 22/562);
- It doesn’t actively seek out real-world data – for example, real-world population-level data such as hospitalisation for ‘adverse events of special interest’ segmented by vaccination status and age. In January 2022, MHRA did not hold such data (CSC 88243) and in August 2022, UKHSA (FOI 22/472) only held population level info on thrombosis with thrombocytopenia syndrome (TTS). Instead, it waits for signal detection from Yellow Card reports of adverse events, which are massively under-reported;
- It doesn’t (or can’t) define the quantitative level of risk which is ‘acceptable’ as the basis of “acceptably safe” (FOI 22/390);
- It lost 20% of posts in 2021 due to funding cuts and has 20% vacancies below that new baseline (FOI 22/1007);
- It doesn’t have a process for delegating the authority to approve medicines for public use (FOI 22/1002) or governance of individuals competence (qualification, experience and training) (FOI 22/1007) to MHRA officers;
- It has hidden safety data (FOI 22/1083), redacting numbers in tables on the pretext of maintaining patient confidentiality;
- It appears quietly to have dropped a key strand of its Covid vaccine surveillance: Targeted Active Monitoring. FOI 22/1083 asked for a copy of the latest report but it was 15 months old (August 2021).
But back to “All the Covid vaccines and therapeutics authorisation decisions were taken by the Licensing Minister and were not delegated.” I’m left wondering what safety advice MHRA gave to Chris Whitty and ministers about the Covid vaccines back in late 2020 and early 2021 and subsequently as the serious safety issues started to emerge. And I wonder what briefings MHRA gave to the Commission on Human Medicines Expert Working Group on Covid Vaccine Benefits and Risks and to the COVID-19 Vaccines Safety Surveillance Methodologies Expert Working Group – neither publishes minutes.
It’s high time MPs and the Covid Inquiry started to ask some searching questions.
Until Nick retired a few years ago, he was a Senior Civil Servant in a Government Department.
Featured Video

or go to
Aletho News Archives – Video-Images
From the Archives
A Lesser “Grade” of Human
By Michael Hoffman | Revelation of the Method | January 3, 2024
Will the more than 100 Iranians killed by terrorist bombs today be mourned in the West as victims of terrorism? Certainly not. Allied doctrine has it that the killing of Israeli or American civilians is a crime of cosmic proportions, while shedding the blood of “enemy” women and children is perfectly acceptable; indeed commendable.
The West does not memorialize the hundreds of thousands of civilians bombed by the U.S. in Serbia, Iraq, Afghanistan and every major German city 1943-1945. America’s fire-bombing of the city of Tokyo by General Curtis LeMay in March 1945 was followed by Harry Truman’s atomic incineration of Hiroshima and Nagasaki in August of that year. Truman never had a moment of doubt or regret over the murder of more than a 100,000 Asian children, mothers and non-combatant boys and men. It was business as usual for the “noble” Allies during the “Good War.”
In the West human rights signifies passionate concern only for civilians designated as truly human: Israelis first, then Americans and British, followed by their satraps.
This inhumanity is the legacy of Talmudic ideology, beginning with tractate Sanhedrin 57a from 400 A.D., concerning liability for capital punishment: “If a Jew murders a gentile, he is exempt.”
This teaching of contempt was reiterated in the dogma of Chabad Lubavitch founder Rabbi Shneur Zalman in the 18th century. … continue
Blog Roll
 Aletho News
- MOE: Nearly 22,000 Students and Education Workers Killed
- Guterres in Islamabad: Genocide, cowardice, and the cage of Imran Khan
- Johnson, Marandi say Yemen holds upper hand over Saudi Arabia
- False flags won’t save aggressors, Iran FM spokesman says
- The Makkah Pact Enters Into Force: The End of American Dominance or Its New Form?
- NATO’s top generals gather in Kiev
- EU’s continuing expansion – greater threat to Russia
- US Senator Murphy says Pentagon denied him entry to US base in Qatar
- Israel expands “incitement” charge to target Palestinian education and memory
- How Israel seeks to reshape Arab classrooms
- If Americans Knew
- Three Years of Genocide: How America’s Israel-First Media Filtered Out the Truth
- Israeli war chief briefs ministers on potential war against Palestinian Authority
- New Report: Israel Killed nearly 21,000 Palestinian Students and Education Workers in Past Three Years
- Israel’s flailing chatbot army
- Five Palestinians Killed, Others Injured by Israeli Fire in Gaza
- Israel is rewriting the Palestinian curriculum in East Jerusalem to erase Palestinian identity
- Three years of genocide: Israel turned prisons into killing grounds and torture sites
- Three years of genocide. Words fail. Daily Update
- ‘I’d rather die than go back’: A Palestinian teen’s 10-month nightmare in Israeli jail
- How Jared Kushner’s firm’s investment in an Israeli company could be a major conflict of interest
- No Tricks Zone
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels

