False and Misleading Efficacy Claims — What is the Motivation?
Dr. Rochelle Walensky Tweeting Counterfactuals with Intent
By Peter A. McCullough, MD, MPH | Courageous Discourse | November 10, 2022
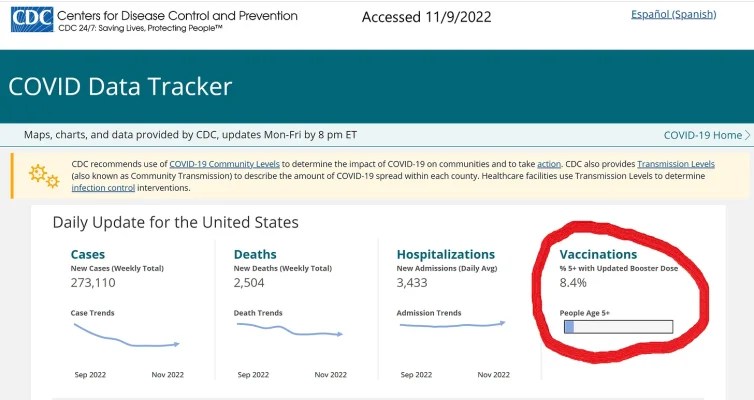
CDC Director, Rochelle Walensky, MD, MPH, for the record, continues to make false claims about the COVID-19 vaccine boosters with the apparent motivation of getting more Americans “fully vaccinated.” This is in the backdrop of an 8.4% rate of Americans over age 5 taking one of them.[i]
No matter how hard the internal pressure is at the CDC to get a “needle in every arm,” what would be such a strong motivation for Walensky to blatantly deceive Americans with such obvious counterfactual information?
She states “COVID-19 vaccines may not prevent every infection (as apparent in her personal case), but they do provide us important protection against severe illness, hospitalization, and death…”

In order for that claim to be valid by US regulations, a COVID-19 vaccine would need to reduce the risk of adjudicated COVID-19 hospitalization and death as a primary endpoint in a prospective, double blind, randomized, placebo-controlled trial. The benefit would need to be meaningful, e.g., ~20% relative risk reduction, and statistically significant, e.g., p<0.05. The conclusive study should have no significant threats to validity such as loss to follow-up. There has been no pivotal randomized trial, and no one can claim COVID-19 vaccines reduce hospitalization and death. The shortest section on the FDA Pfizer Fact Sheet is the “Benefits” section! This is given with the consent form and makes no claims about severity, hospitalization, and death.[ii]

She goes on to promote a two-month period between the last injection (presumably legacy mRNA) and the new bivalent vaccine. This schedule has never been tested and demonstrated to be safe in human beings. Even more shocking, the bivalent boosters which failed in animal studies to stop Omicron, have never been tested for safety or efficacy in human RCTs with clinical outcomes. In academic medicine and the pharmaceutical regulatory community, the question is WHY does Walensky cross the line into making false claims, an illegal act for fully FDA approved and marketed drugs/vaccines? Only senate or congressional hearings with direct questions will get the truth out of her.
Here are some possibilities: 1) she is following orders from higher governmental authorities, 2) she knows the claims are false but truly believes the only way for vaccination to work is to keep everyone vaccinated on a continuous basis no matter what the costs, 3) she is in a form of a trance or psychological state driven by fear in herself and for humanity where COVID-19 vaccination has become like a talisman with special powers and cannot be challenged. Indeed, Walensky has never comprehensively discussed safety of COVID-19 vaccination, and she has not disclosed who should NOT take a COVID-19 vaccine. So, the next time someone in your circles claims you or your loved one should take a COVID-19 vaccine to be “safe” or “protected” from serious outcomes, ask them to take a look at the consent fact sheet and read the tiny benefit section.
[i] CDC COVID Tracker, Accessed November 9, 2022
[ii] VACCINE INFORMATION FACT SHEET FOR RECIPIENTS AND CAREGIVERS ABOUT COMIRNATY (COVID-19 VACCINE, mRNA), THE PFIZER-BIONTECH COVID-19 VACCINE, AND THE PFIZER-BIONTECH COVID-19 VACCINE, BIVALENT (ORIGINAL AND OMICRON BA.4/BA.5) TO PREVENT CORONAVIRUS DISEASE 2019 (COVID-19) FOR USE IN INDIVIDUALS 12 YEARS OF AGE AND OLDER, August 22, 2022
DR MIKE YEADON COVID DEATH SHOTS IS MEDICAL MURDER
Dr Mike Yeadon – Let’s not put a Gloss on It. The COVID death shots Is Medical Murder
First RSV Emergency Declared as Pfizer and GSK Race to Get Vaccines Approved

By Michael Nevradakis, Ph.D. | The Defender | November 8, 2022
Southern California’s Orange County Health Department this month declared a local health emergency over concerns around the rising number of pediatric cases of Respiratory Syncytial Virus (RSV).
County officials also declared a Proclamation of Local Emergency, allowing them to access state and federal resources in response to the spread of RSV.
The news came amid media warnings of a looming “tripledemic” of RSV, influenza and COVID-19 and news that Pfizer and GlaxoSmithKline (GSK) are close to securing regulatory approval for their RSV vaccine candidates — including Pfizer’s RSV vaccine for pregnant women.
RSV was first identified in 1956, and frequently affects children, with a majority of childhood cases occurring before age 2. For most children, symptoms are similar to those of the common cold, according to the Centers for Disease Control and Prevention (CDC).
It can, however, cause serious symptoms in the very young and the elderly, although childhood deaths are infrequent, according to CDC data.
According to California attorney Rita Barnett-Rose, there’s no evidence to support claims that Orange County hospitals are overextended, or to justify a state of emergency.
In an interview with The Defender, Barnett-Rose drew parallels between Orange County’s emergency declaration for RSV and other state, local and federal emergency declarations for COVID-19:
“One of the other alarming things that happened with COVID is when [Gov. Gavin] Newsom declared the state of emergency in COVID. He also waived the 30 and 60-day review periods for all local governing boards.
“So, yeah, so that’s what everyone is concerned about, this perpetual state of emergency.
“And the other thing that it triggers is it asks, once they declare a state of emergency, aside from getting the funding, it also triggers a request to Governor Newsom to declare a statewide state of emergency and then also to have Newsom ask President Biden to declare a national state of emergency.”
That could lead to Emergency Use Authorization (EUA) of RSV vaccines, according to Barnett-Rose, who told The Defender there may be an avenue to challenge the legality of the latest Orange County emergency declaration.
Is pharma using the COVID playbook to push RSV vaccines?
Dr. Regina Chinsio-Kwong, Orange County’s health officer, said in a press release county officials issued the declaration due to “rapidly spreading virus infections causing record numbers of pediatric hospitalizations and daily emergency room visits.”
The declaration will allow the county to access state and federal resources and to allow non-pediatric hospitals to offer beds to sick children, Chinsio-Kwong said.
Children’s Health Defense (CHD) California Chapter notes that this declaration was unanimously ratified “over the objections by members of the public who showed up to speak against the declarations.”
Dr. Melaine Patterson, chief nursing officer for Children’s Health Orange County, said area hospitals are seeing an “unprecedented” volume of children visiting their emergency rooms — approximately 400 per day, with wait times of “four to 12 hours.”
She also said that, as of Nov. 1, there were 285 patients in her hospital, compared to 188 on that date last year, adding that 11 of those current patients were placed in ICU as a result of RSV infections. RSV cases also are on the rise nationally.
Chinsio-Kwong advised the public to remain “up to date with other vaccinations such as flu and COVID-19” to “reduce the burden on hospitals this fall and winter.”
“Our best shot at protecting ourselves and our children from respiratory illnesses continues to be the same things we practiced throughout the pandemic including the use of masks when indoors around others and staying home when you are sick,” Chinsio-Kwong said.
However, Barnett-Rose said hospitals in Orange County may be overextended not due to an unusually high number of admissions, but due to unvaccinated staff having been let go.
She told The Defender :
“I do think that has a big role in it, and a lot of people pointed that out during the hearings and public comments were made about that.
“They were trying to claim … there were not enough pediatric experts or pediatric-trained doctors and medical professionals, so they needed to go outside of the county. And I do think a big part of that is that they did let go of many pediatric nurses and pediatric physicians that refused to take the vaccines. So I do think that this is a crisis of their own making … if there is even a crisis.”
San Diego County also issued a warning to its residents Nov. 4 over rising RSV cases but stopped short of declaring an emergency.
CHD California questioned why Orange County would declare a “Local Health Emergency” now — even though local COVID-19 states of emergency haven’t been lifted.
Despite claims that the purpose of these new declarations is exclusively meant to help county hospitals, CHD California said, “the language of the emergency Resolutions says something else entirely”:
“Both the Resolution to ratify the Local Health Emergency under Health & Safety Code section 101080 and the Proclamation of a Local Emergency under Government Code section 8630 declare the need for these local emergencies not only based on the asserted need to handle allegedly rising cases of RSV — but also because of other unnamed ‘other respiratory illnesses’ that were not discussed during the special meeting or otherwise disclosed to the public.”
Barnett-Rose provided insights into the legal meaning underlying these declarations. She told The Defender :
“There’s a local health emergency, which is declared by the public health officer as opposed to the [county] board … and that is when the health officer says … ‘I’ve been talking to the hospitals and we’ve done some assessments and there’s an increasing rate of respiratory illnesses and the children’s hospitals, and so, because of this, I am asking to declare a local health emergency.’ …
“But her authority to declare a local health emergency only lasts for seven days unless it’s ratified by our board of supervisors. And so, on Nov. 2, our board ratified that, which means now it’s in place and it needs to be renewed or looked at every 30 days, unless Governor Newsom waives that condition.”
CHD California argued that the “overly broad language used in these emergency declarations should be deeply concerning to anyone wary of a repeat of the “public health” measures ordered under COVID-19,” noting that adding the vague statement referring to “other respiratory viruses” creates “plenty of room for further abuse.”
Barnett-Rose told The Defender that, during the Nov. 2 meeting, Chinsio-Kwong said, “No restrictions are currently [emphasis added] in place,” a statement that “caused … a little bit of an uproar during the hearing because of her wording, which suggests that indeed they may end up rolling out mask mandates or some other mandates.”
Under this type of “slippery language,” argued CHD California, even the common cold could be used to issue an emergency declaration.
Barnett-Rose agreed:
“How do you measure that? How do you dispute it? How do you examine it? How do you end it?
“If you’re going by one infectious disease, at least you can try to find some data on hospitalizations or cases or deaths or ICU beds. But when it’s everything, it can still include COVID, flu, cold, COPD, a whole bunch of things that would qualify as respiratory illnesses.”
Barnett-Rose said that attempts will be made to legally challenge these declarations as “overbroad,” noting, however, that while case law precedent exists to challenge overbroad legislation, there is no such precedent in place for states of emergency.
Barnett-Rose she’s looking into whether there’s some way to litigate against these broad states of emergency.
When statutes are overbroad, she said, sometimes you can challenge them for being overley broad or too vague, but she’s not sure if there’s a similar precedent for challenging an overly broad state of emergency.
Declaring a local state of emergency at the county level could trigger a chain of events leading all the way to a national declaration of emergency, according to CHD California:
“By ratifying and/or declaring these local emergencies, the Board has now triggered an official request to Governor Newsom that he also declare a state-wide state of emergency on the same overly broad basis — and to ask the President of the United States to declare a national state of emergency.”
“A nationally declared state of emergency may trigger all of the same measures that have already deeply divided our country: masks on airplanes, business and school closures, and coercive school and employee mandates for experimental ‘vaccines’ offered as the ‘only solution’ back to Freedom,” CHD California argued.
Barnett-Rose said the emergency declaration in Orange County may be tied to the fact that there are multiple RSV vaccines already in the pipeline:
“The reason this is becoming really huge news is because this is what happened with the COVID state of emergency, too, it kind of went like that in dominoes.
“Once Biden declares a national state of emergency, then that triggers all of the emergency use authorizations that allowed the so-called vaccines for COVID. And I’m sure you already know that there’s vaccines in the works now for RSV that they’re floating out there in the news as well.”
Recounting events that occurred in relation to COVID-19, Barnett-Rose told The Defender that Orange County and some other counties in California declared a state of emergency, “then it went to the state, then it went national, and then, of course, once there’s a national emergency, you can go into Iowa.”
“So I do think that this is very suspicious timing, the articles that we are seeing in the news about being close to this RSV vaccine,” Barnett-Rose said. “And so, I do think that they’re trying to repeat the same playbook.”
Up to 30 RSV vaccine candidates already in pipeline
Pharmaceutical industry publication FiercePharma reported that Pfizer and GSK “moved closer to regulatory approvals” in the past week, and “could each see the first-ever approvals for an RSV vaccine in 2023.”
GSK’s candidate will be reviewed May 3, 2023, while Pfizer is “eyeing an approval filing by year-end.”
In all, up to 30 RSV candidate vaccines have been identified by the National Institutes of Health (NIH).
GSK has secured priority review status for its RSV vaccine following the submission of data from its AReSVi-006 phase 3 trial. The candidate vaccine exclusively targets adults 60 and older, and the data reportedly “showed high overall vaccine efficacy against RSV lower respiratory disease” at a rate of 82.6%, Fierce Biotech reported.
GSK initially intended to develop an RSV vaccine for older adults and for infants, but plans for the latter were shelved due to a “safety concern.” Nevertheless, GSK CEO Emma Walmsley in a call last week with investors described GSK’s new vaccine as “a very significant scientific achievement.”
Previous efforts to develop an RSV vaccine have failed because they “had a persistent tendency to cause worse disease,” due to “a phenomenon known as antibody-dependent enhancement (ADE).”
Dr. Ruth Karron, a pediatrician and professor of international health at the Johns Hopkins Bloomberg School of Public Health, said, “The difference this year is the general public for the first time is probably eagerly awaiting an RSV vaccine, because they’re seeing firsthand just how much of a problem RSV can be,” in a statement drawing a clear connection with the reported increase in RSV cases this year.
Pfizer announced Nov. 1 that its own candidate RSV vaccine wrapped up its phase 3 trial for efficacy early. Unlike GSK’s candidate vaccine, Pfizer’s vaccine targets pregnant women. The vaccine is designed to be administered early in the third trimester with the intent that the vaccine-induced antibodies be passed from the mother to her newborn.
Pfizer, in its Nov. 1 announcement, claimed that its bivalent RSV prefusion vaccine candidate RSVpreF, also known as PF-06928316, delivered “broadly positive” results — namely, a significant reduction in the rate of respiratory illness in newborns and their mothers.
Pfizer claimed 81.8% efficacy against severe cases of RSV for babies up to three months, and 69.4% efficacy after six months.
Pfizer’s MATISSE (MATernal Immunization Study for Safety and Efficacy) trial involved 7,400 pregnant women and their newborns, tracking the infants for one year following birth, and some for two years. It was conducted in 18 countries beginning in June 2020.
Pfizer’s vaccine trial did not deliver statistically significant results regarding the prevention of infant medical visits caused by RSV, including for non-severe cases.
Nevertheless, Pfizer said there are “no major safety concerns” with its product, adding:
“At the recommendation of the DMC [Data Monitoring Committee], and in consultation with the U.S. Food and Drug Administration (FDA), Pfizer has stopped enrollment in the study.
“Based on these positive results Pfizer plans to submit a Biologics License Application (BLA) to the FDA by the end of 2022 for the vaccine candidate followed by other regulatory authorities in the coming months.”
Pfizer’s phase 3 trial data has not yet been vetted by independent experts, and has not been peer-reviewed or published.
On March 2, 2022, Pfizer’s candidate vaccine received a Breakthrough Therapy Designation from the FDA, while previously, in November 2018, the FDA granted it Fast-Track status, according to the Pfizer release.
“Pfizer’s investigational RSV vaccine candidate builds on foundational basic science discoveries including those made at the National Institutes of Health (NIH),” the vaccine maker said in its press release.
The NIH research in question also was “key to the hugely successful COVID-19 vaccines,” according to ABC 7 Los Angeles.
Others looking to develop an RSV vaccine include Moderna and AstraZeneca and Sanofi, in a joint initiative. Moderna received fast-track designation from the FDA on Aug. 3, 2021, for its mRNA-1345 RSV vaccine for older adults, while AstraZeneca and Sanofi are developing a viral vector RSV vaccine by the name of “nirsevimab.”
An August 2021 article in The Defender predicted that RSV would represent the “new frontier for vaccine development,” as pharmaceutical companies would be “lured by the prospect of a large untapped global RSV vaccine market,” leading to a vaccine development “gold rush.”
Media tout benefits, ignore safety concerns
Online news portal Vox described the development of new RSV vaccines as “very, very good news” in a recent article.
Coupled with media coverage about “rising” RSV cases nationwide, it appears the stage is being set to create an emergency in the public consciousness, which could lead to EUAs being granted to the new vaccines and a rush to get the public vaccinated.
Blogger James Roguski, however, called into question the results of the Pfizer phase 3 trial, raising many safety concerns that are indicated in the company’s own data but were downplayed by Pfizer in its public proclamations. In a recent post, he wrote:
“In the Phase II study, researchers found that women who received RSVpreF vaccine containing aluminum hydroxide had a higher incidence of local reactions than those who received RSVpreF vaccine without aluminum hydroxide.
“It seems like 1 of the 117 infants in the placebo group suffered fetal death and 6 infants in the ‘vaccinated’ group are unaccounted for.”
Roguski also highlighted the many adverse events that were recorded for both infants and pregnant mothers who participated in the study, none of which were recorded for the placebo group.
For infants, some of these adverse events included acute respiratory failure, bronchiolitis, cardiac murmur, chordee (bent penis), conjunctival hemorrhage, hypoglycemia, jaundice, low birth weight, neonatal hypoxia, neonatal respiratory failure, seizure, sepsis, upper respiratory tract infection and vascular malformation.
Pregnant women, in turn, experienced adverse events including fetal growth restriction, fetal tachycardia, gestational diabetes, nonreassuring fetal heart rate pattern, premature labor, premature separation of placenta, vaginal hemorrhage and thrombocytopenia.
For some, these safety concerns are conjuring up memories of previously failed attempts to develop an RSV vaccine.
A vaccine tested in 1966 led to the deaths of two toddlers as a result of “enhanced disease symptoms,” while many infants “suffered worse symptoms than usual, and needed to be hospitalized.”
As previously reported by The Defender, RSV itself originated in monkeys housed in a Maryland facility where they were used to conduct polio vaccine research. Remarking on this and the connection to RSV vaccine development today, Brian Hooker, CHD’s chief scientific officer, told The Defender, “It is incredible that the vaccine industry can create a disease — RSV from the polio vaccine — and then create another vaccine to ‘prevent’ that disease. Talk about a business proposition!”
Michael Nevradakis, Ph.D., based in Athens, Greece, is a senior reporter for The Defender and part of the rotation of hosts for CHD.TV’s “Good Morning CHD.”
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Much Ado About Nothing
By Todd Hayen | OffGuardian | November 12, 2022
Do any of you think we are over-reacting? I don’t think so, but the sheep-folk certainly do. They claim they are willing to let bygones be bygones and just put it all in the past and get on with life.
I am sure everyone reading this is aware of the bombshell editorial The Atlantic dropped recently with their amnesty nonsense. I don’t think I have been more livid reading an article since the days of seeing piece after piece about how effective masks are against viral transmission.
I won’t comment on The Atlantic blather directly here, as there have been many fine responses to it, but wow, what a piece. So typical of a bully trying to pretend he loved his victims all along when he knows he is cornered and about to be punished. One last punch disguised as a kiss.
I just got back from a little cruise. Major ports were Barcelona, Rome, Florence, Monaco, and a smattering of little French and Italian hideaways. I had mixed feelings about going, but realized that if this tsunami we all see coming a few miles off the shore has the potential of wiping out most travel in the foreseeable future, I figured I might as well get something in before the onslaught.
It was nice in a lot of ways, as would be expected, but in other ways unusually disconcerting. For one thing, very, very few people had masks, and thus there was a palatable scent in the air of “Covid is a thing of the past.”
One would think this was a good thing, but instead it exuded a very clear vibe of denial.
Oddly enough, not wearing masks, and believing Covid to be over, to me is just another example of compliance to authority.
I know that seems a stretch, but if Covid were real, coupled with the truth that the vaccines do not work, and we were told again and again that there would be no natural herd immunity without a working vaccine, and we still hear of infections rising, variants being created, and hospitals becoming over crowded, why would people think the disease just died and disappeared? The reason is because we were told it was over.
We were told we suddenly didn’t need masks, that we could party with friends, vaxxed or unvaxxed, that we could gather in huge crowds, get on cruise ships (no one even cared that I was unvaccinated.) We were told what was true, what was real and what to worry or not worry about. And like sheep, most people blindly followed.
So shouldn’t I be happy? If I were, it would be for all of the wrong reasons. It is true we are all happy when the slave owner puts down the whip. Whip or not, however, we are still slaves.
I, too, bask in the sun of my controlled freedom—I went on a cruise didn’t I? After two years of not being “allowed to” — so I am just as guilty of this sort of compliance. I am one step closer to truth though; I know this offer of freedom is a tactic, a ploy, and a ruse.
I’ll take a scrap of bread when it is offered, but I will not succumb to complacency and forgive my master for his cruelty when he behaves, albeit for just a moment, as my friend. Most everyone else seems fine to let bygones be bygones.
I am not, and I suspect most of you reading this are not as well.
The great danger I see here in the masses just carrying on in complacent forgiveness is that they are encouraged to stay blind. Surely if they speak out against the atrocities that the world has experienced over the past three years they would quickly be categorized as a trouble maker, a pariah, and a misfit.
“Just get over it, man, it’s all over.”
Is it? No, of course not, you and I know that, and it is all still going on in various ways under the covers now, in the dark recesses of the culture: persecutions, continued efforts to vaccinate, and particularly vaccinate children, warnings of an “upcoming dark winter” where restrictions will come back into the mainstream. On and on, you know what I am speaking of.
However, the mass attitude now, as per The Atlantic piece, is “nothing all that much really happened.”
No one died unnecessarily due to the Covid response, no one got sick, no one lost their job or their livelihood, no one suffered socially (particularly children wearing masks in school), no one suffered educationally, nothing bad really happened.
If you are still pissed about all that DID happen, then you are overreacting… much ado about nothing.
So get over it, forget and forgive.
Not everyone in the world has read that article, but what I saw in Europe, it seems that most people, at least on physical observation, are basically taking on that attitude.
It breaks my heart.
I think about the countless mothers sitting by their children in countless hospitals nurturing them through a totally unprecedented heart incident.
I think of the countless families standing together at the funeral of a loved one, dead prematurely from a heart attack, blood clotting, or cancer—cause unknown, unless you want to apply the newly created diagnoses, “Sudden Adult Death Syndrome.” What the hell is that?
A novel disease and now a common cause of death? Easy peasy explanation, eh? I think of the countless numbers of people suffering from a myriad of strange afflictions, which suddenly appeared out of nowhere.
I think again of countless people having suffered unconscionably, and pointlessly, after losing their jobs, their businesses, their life savings, and their livelihood—the countless children with lower IQs, and those who have suffered social retardation due to the mask mandates, social distancing, and mandatory online teaching at home with no socialization at all.
I could write 100 pages describing all of this—but most people don’t know, and if they do, don’t care, or just attribute all of this horror to the “cost of living—some are lucky in life, some are not.”
During my recent cruise not a word was uttered about any of this, thousands of people were encountered walking the streets of Rome, Florence, Barcelona, all laughing, eating, drinking, playing. While just beneath their feet, hidden a foot underground, there are skulls and bones of the fallen—all forgotten, and the perpetrators all forgiven.
When I was occasionally shaken from my self-induced and compliant vacation reverie, my heart ached talking to all of the young vibrant crewmembers on our ship.
I would hear of their plans to be married, create families, further their careers and live fully their vibrant lives—followed with the admission that they all had to be vaccinated to get their current jobs on the ship.
What really lies ahead for these beautiful children of God so innocent and full of life? I would shake my head, “maybe none of this is true, and maybe I am making more of it than it really is. Maybe they are right, and it really wasn’t that bad, just a mistake made here and there that we really could get over. It is all fine… let’s move on.”
Then a bone cracks under my foot—just a few inches from the surface of awareness—the truth. And I slip back into reality.
Dr. Clare Craig On The Three Key Factors Of The Pandemic
The Fat Emperor – Ivor Cummins | November 9, 2022
Dr. Clare Craig is one of the best pathologists out there, and deeply understands the scientific details of the pandemic – and I caught her in person at the International health congress in Portugal – all scientific talks are here or will be uploaded shortly https://odysee.com/@MartaGB:2
Good News on Omicron Outcomes from Prison
Captive Environment Allows Real Look at Risk for Hospitalization and Death
By Peter A. McCullough, MD, MPH | Courageous Discourse | November 8, 2022
Prisoners and staff are a prototypical congregate group amenable to epidemiologic study and in the setting of the SARS-CoV-2 outbreak, ideal for study of the patterns of spread and risk for serious outcomes.
Throughout the pandemic, review and interpretation of peer-reviewed manuscripts in widely read journals has required careful review of data in supplementary tables. The conclusions by the authors in many papers must be ignored given the heavy bias for all journals to “promote” mass vaccination. For example, thus far, there has not been a single paper in the New England Journal of Medicine that has concluded COVID-19 vaccines are unsafe, or not indicated, or do not have a favorable risk to benefit ratio.
Prior to COVID-19 for any new therapy or surgery, there are always divergent views where some papers conclude an intervention is beneficial and others do not. Disagreement is normal in medicine. The pervasive heavy-handed government intelligence community and public health agency operations have biased the medical journals to publish a one-sided story on COVID-19 vaccination. The paper by Chin et al, in the New England Journal of Medicine is a perfect example.[i] They studied 59,794 residents and 16,572 staff, using data collected from December 24, 2021, through April 14, 2022. Buried in the supplemental tables are important data on the real risk of hospitalization and death with the Omicron variant in prisoners characterized by whether they had prior COVID-19 and how many doses of a vaccine they had received.
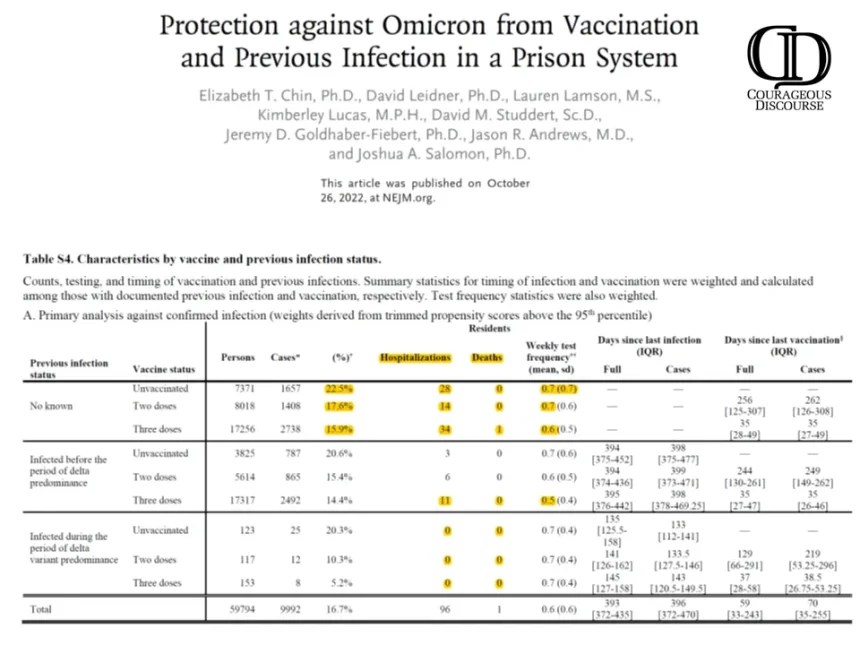
Chin ET, Leidner D, Lamson L, Lucas K, Studdert DM, Goldhaber-Fiebert JD, Andrews JR, Salomon JA. Protection against Omicron from Vaccination and Previous Infection in a Prison System. N Engl J Med. 2022 Oct 26. doi: 10.1056/NEJMoa2207082. Epub ahead of print. PMID: 36286260. Supplemental Tables.
As shown, there is a negligible risk of hospitalization and death with Omicron infection. Specifically, there were zero deaths in the unvaccinated. To demonstrate how far off-base authors and editors are on interpretation, take a look at the paper’s conclusions:
“Our findings in two high-risk populations suggest that mRNA vaccination and previous infection were effective against omicron infection, with lower estimates among those infected before the period of delta predominance. Three vaccine doses offered significantly more protection than two doses, including among previously infected persons.”
My conclusions are considering natural immunity status, COVID-19 vaccination provided no meaningful protection against hospitalization and death with Omicron. Based on these data, a rational prison physician or health administrator would conclude that bivalent boosters for Omicron are not clinically indicated nor medically necessary. So next time you see headlines regarding a journal article, look for a second opinion from “Courageous Discourse” or other reliable stacks and sources of analysis.
[i] Chin ET, Leidner D, Lamson L, Lucas K, Studdert DM, Goldhaber-Fiebert JD, Andrews JR, Salomon JA. Protection against Omicron from Vaccination and Previous Infection in a Prison System. N Engl J Med. 2022 Oct 26. doi: 10.1056/NEJMoa2207082. Epub ahead of print. PMID: 36286260.
Why Are People Losing Confidence in Vaccines?
BY DR DAVID PATON | THE DAILY SCEPTIC | NOVEMBER 8, 2022
A new peer reviewed article in the journal Vaccine has been published comparing surveys data on attitudes to vaccination from before the pandemic with attitudes now.
The authors report that “paradoxically, despite the success of COVID-19 vaccination campaigns, vaccine confidence has significantly declined since the onset of the pandemic”.
I am not quite sure why the authors appear so surprised at their result but a clue can be found in their use of the word “despite”. In many countries the “success” of the COVID-19 vaccination campaign relied in large part in pressuring, bullying and sometimes coercing people to get vaccinated.
Now if governments tell you that getting vaccinated is in your best interests, but that nonetheless those who choose not to get vaccinated will be pilloried in the press and on social media, barred from participating in normal everyday activities and, in some cases, sacked from their employment, perhaps we should not be surprised that people start to doubt whether those governments really do have their best interests at heart.
And those doubts have substance behind them. From a very early stage, it was clear that for many people, the known risks from vaccination probably outweighed any likely benefit. This was most obvious for those who had already had Covid (and for whom the marginal impact of vaccination in preventing a further infection was small), for groups who faced very low risks of serious illness if they contracted Covid and especially for young males for whom vaccination seems to be bring additional risks of heart problems.
But instead of acknowledging that Covid-19 vaccines may make sense for some people and not everyone, too many public health officials, scientists and politicians have systematically downplayed immunity from previous infection, brushed aside concerns over side effects and dismissed concerns that the roll out to the whole population was rushed given uncertainty over long term effects.
The latter was a particularly serious error. Right from the start of the roll out the public was assured that the vaccines had been thoroughly tested. Yet in May 2021, the Government decided to stop providing the AstraZeneca vaccine to under 40s due to the relatively high rate of blood clots. That decision would have been little consolation to the families of the 73 people whose deaths the MHRA report as being linked to that vaccine.
Rather than taking that as a lesson, authorities around the world doubled down and rolled out vaccine mandates, passports and travel restrictions as a way of twisting more arms into receiving the jab. Ironically, these measures were aimed primarily at young people for whom the benefits of vaccination were lowest and (particularly for males) the risks seem highest.
The official rationale for these policies was that vaccination would help protect others from being infected. We now know that there was never any evidence to back this up. And when official data started to suggest that the vaccinated may be getting infected at similar if not greater rates than the unvaccinated, the response of some journalists was not to probe further and investigate but to encourage the authorities to suppress the data. Truly, you could not make it up.
Researchers such as Alex de Figueiredo from the London School of Hygiene and Tropical Medicine warned at the time that coercion was likely to lead to a loss of trust in vaccination more generally. With the latest research paper, we have firm evidence that this is indeed the case.
It is not unreasonable to conclude that the most dangerous ‘anti-vaxxers’ over the past two years have not been fringe conspiracy theorists but governments and the public health establishment itself.
It’s a sorry state of affairs, but where do we go from here? Well public health leaders could start by switching tack. Rather than setting out to persuade everyone to get vaccinated, they could concentrate on providing good information about benefits and risks to help people decide whether vaccination is right for them. If, at the same time, they start to engage honestly with those who have suffered side effects and acknowledge the high level of uncertainty that still exists in the evidence, perhaps they can begin to regain some of the trust they have so negligently lost.
David Paton is Professor of Industrial Economics at Nottingham University Business School.
Featured Video

Houthis Don’t Have to Conquer Saudi Arabia to Make It Pay
or go to
Aletho News Archives – Video-Images
From the Archives
A Lesser “Grade” of Human
By Michael Hoffman | Revelation of the Method | January 3, 2024
Will the more than 100 Iranians killed by terrorist bombs today be mourned in the West as victims of terrorism? Certainly not. Allied doctrine has it that the killing of Israeli or American civilians is a crime of cosmic proportions, while shedding the blood of “enemy” women and children is perfectly acceptable; indeed commendable.
The West does not memorialize the hundreds of thousands of civilians bombed by the U.S. in Serbia, Iraq, Afghanistan and every major German city 1943-1945. America’s fire-bombing of the city of Tokyo by General Curtis LeMay in March 1945 was followed by Harry Truman’s atomic incineration of Hiroshima and Nagasaki in August of that year. Truman never had a moment of doubt or regret over the murder of more than a 100,000 Asian children, mothers and non-combatant boys and men. It was business as usual for the “noble” Allies during the “Good War.”
In the West human rights signifies passionate concern only for civilians designated as truly human: Israelis first, then Americans and British, followed by their satraps.
This inhumanity is the legacy of Talmudic ideology, beginning with tractate Sanhedrin 57a from 400 A.D., concerning liability for capital punishment: “If a Jew murders a gentile, he is exempt.”
This teaching of contempt was reiterated in the dogma of Chabad Lubavitch founder Rabbi Shneur Zalman in the 18th century. … continue
Blog Roll
 Aletho News
- Houthis Don’t Have to Conquer Saudi Arabia to Make It Pay
- MOE: Nearly 22,000 Students and Education Workers Killed
- Guterres in Islamabad: Genocide, cowardice, and the cage of Imran Khan
- Johnson, Marandi say Yemen holds upper hand over Saudi Arabia
- False flags won’t save aggressors, Iran FM spokesman says
- The Makkah Pact Enters Into Force: The End of American Dominance or Its New Form?
- NATO’s top generals gather in Kiev
- EU’s continuing expansion – greater threat to Russia
- US Senator Murphy says Pentagon denied him entry to US base in Qatar
- Israel expands “incitement” charge to target Palestinian education and memory
- If Americans Knew
- Three Years of Genocide: How America’s Israel-First Media Filtered Out the Truth
- Israeli war chief briefs ministers on potential war against Palestinian Authority
- New Report: Israel Killed nearly 21,000 Palestinian Students and Education Workers in Past Three Years
- Israel’s flailing chatbot army
- Five Palestinians Killed, Others Injured by Israeli Fire in Gaza
- Israel is rewriting the Palestinian curriculum in East Jerusalem to erase Palestinian identity
- Three years of genocide: Israel turned prisons into killing grounds and torture sites
- Three years of genocide. Words fail. Daily Update
- ‘I’d rather die than go back’: A Palestinian teen’s 10-month nightmare in Israeli jail
- How Jared Kushner’s firm’s investment in an Israeli company could be a major conflict of interest
- No Tricks Zone
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative

