2 Minutes of “Experts” Being WRONG About the COVID Vaccine
To those who still repeat the Big Pharma lie that “Nobody Ever Said The Vaccine Would Stop The Transmission Of Covid Virus”
Here are many people saying it!
By Brenda Baletti, Ph.D. | The Defender | August 29, 2023
Kaiser Permanente and Lionsgate Studios in California reversed mask mandate policies last week, just a few days after imposing them.
Kaiser Permanente, the largest healthcare provider in California, on Aug. 22 announced it had “reintroduced a mask mandate for physicians, staff, patients, members, and visitors in the hospital and medical offices in the Santa Rosa Service Area,” in a statement obtained by The Press Democrat.
Kaiser said the mandate was in response to an increase in the number of patients testing positive for COVID-19.
But just two days later, on Aug. 24, Kaiser officials told The Press Democrat the mask reinstatement applied only to physicians and staff, not to patients and visitors.
“Our intent was to communicate that as of Tuesday, we have expanded the masking requirement for our employees and physicians to medical offices and clinic settings; we apologize for any confusion among Press Democrat readers,” Kaiser said in its latest statement.
It also said, “We have not changed our masking requirements in the hospital, which have been in effect since April: employees and physicians are required to wear masks and we ask visitors to wear masks when in the hospital.”
But Kaiser also confirmed to Becker’s Hospital Review on Aug. 23 that it had reintroduced the mask mandate.
The Press Democrat reported the reversal happened after people noticed many visitors to the hospital were not masking.
Local media reported that some Northern California residents supported the mask mandate policy when it was first announced, but others were skeptical and frustrated in response to the mandate announcement.
“I think it’s more political than anything, just think they’re trying to do what they did in 2020,” said Carmichael resident Craig Roberts.
Lionsgate also reverses mandate
Lionsgate on Friday also notified employees that the mask mandate it had imposed about a week prior for employees on the third and fifth floors of the studio’s five-story office building in Santa Monica was over, Deadline reported.
Lionsgate imposed the mandate after multiple people in its Santa Monica headquarters came down with COVID-19. The company told Deadline it imposed the mandate in compliance with rules set by the Los Angeles County Department of Public Health.
Lionsgate told The Wrap the health department informed the company it could lift the mask requirement after several days of no new infections.
The company also distanced itself from responsibility for the mandate, stating that:
“Lionsgate never changed its own mask policy. The LA County Department of Health ordered us to institute the temporary masking requirement after we reported a cluster of COVID cases to them and we have an obligation to comply with their orders.”
In addition to mandating “a medical grade face covering (surgical mask, KN95 or N95),” every Lionsgate employee was required to perform a daily self-screening before coming to the office and was told to stay home if they exhibited any symptoms or had traveled internationally in the last 10 days.
Lionsgate was conducting contact tracing and providing at home COVID-19 test kits. It is unclear if those practices are still required.
Reversals come amid pushback and more evidence of mask failures
The mask policy reversals come amid pushback from critics after a growing number of businesses and hospitals in recent weeks reinstituted mask mandates and social distancing requirements, and a new report warned that broader mandates may be coming this fall.
Many doctors have also called for mask mandates to return to healthcare settings.
Meanwhile, documents recently released from the National Institutes of Health (NIH) revealed that public health officials privately questioned the effectiveness of masks and the guidance issued by the Centers for Disease Control and Prevention (CDC) promoting their use.
And an NIH study suggested surgical N95 masks, held up as the gold standard for COVID-19 protection, may expose users to dangerous levels of toxic chemicals, the Daily Mail reported.
The study found the chemicals released by these masks had 8 times the recommended safety limit of toxic volatile organic compounds, which can cause symptoms ranging from headaches and nausea to organ damage and cancer, with prolonged use.
Since the original mandates ended, several studies concluded the mandate policies failed to achieve their promised results.
The Wall Street Journal on Monday published an op-ed criticizing mask mandates.
And dissenters have taken to X (formerly Twitter), calling on people not to comply with mandates.
“This is what can be done when people stand together against tyrannical, unscientific and dangerous so-called public health policies,” author and health freedom activist Meryl Dorey wrote in a Substack post reporting on the policy reversals.
Brenda Baletti Ph.D. is a reporter for The Defender. She wrote and taught about capitalism and politics for 10 years in the writing program at Duke University. She holds a Ph.D. in human geography from the University of North Carolina at Chapel Hill and a master’s from the University of Texas at Austin.
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
By Ron Paul | August 28, 2023
Just four and a half months since President Biden declared an end to the Covid “emergency,” the media is suddenly full of stories about the return of Covid. This time a new “variant” is being rolled out and the media, in collusion with big Pharma and the fear-industrial complex, are churning out stories about how forced masking is making a comeback.
Also, the “unvaccinated” are again to be denied basic human rights in the name of fighting a virus that the vaccine demonstrably does not protect against.
In short, they are desperately trying to revive the tyranny, insanity, and utter irrationality of the two-year Covid scare. And they are pretending none of us remembers how they destroyed society with their lockdowns, mask mandates, and vaccine mandates. They are hoping that none of us will remember the suicides, lost jobs, broken marriages, increased alcoholism and drug abuse, and the rest of what went along with the world’s experiment with global lockdown.
Even Fauci himself is back – like a moth drawn to the light of publicity. Despite all the scientific evidence that the lockdowns were a disaster, that they did far more harm than good, Fauci has re-emerged with his trademark arrogance and claimed that they were the right thing to do and should be done again if that’s what it takes to force people to take the vaccine. A vaccine that does not work.
They won’t even allow us to mention the spike in all-around mortality or the millions who may have been vaccine-injured the first time around. They want us to think that 20-year-old world-class athletes have always just dropped dead of heart attacks out of the blue. It’s all normal! Don’t question it! What are you, some kind of conspiracy theorist? Are you a science-denier?
Yes, look for a renewal of all those old hollow phrases used to attack those of us who can see with our own eyes and hear with our own ears. Their slogans are meant to silence any debate. The same “experts” like Fauci who claimed “I am the science” are back and they shamelessly demand to silence us again.
The big question is… why? Why are they doing this and how do they think they can get away with it a second time? One reason they believe they can get away with it again is that no one has ever been punished for what they did the first time. The Federal Government made sure that the pharmaceutical companies would not be liable for vaccine damages.
The public figures who openly became monsters, demanding the unvaccinated be drummed out of society and maybe even off the face of the earth have not been shamed or shunned. Politicians who displayed cowardice and worse have not been voted out of office for their treachery.
Why are they coming back around for another round of Covid tyranny? Fear is a weapon to gain control. Last time around they generated fear to radically change how America voted. Suddenly everyone was mailed ballots. How closely were they checked? No one knew and no one dared ask. The people who did ask about the election are now facing jail terms.
They want us to shut up while they do it again. Will we?
Publication of Baseline Protocol for Those Suffering from Long-COVID and Post-Acute Sequelae after COVID-19 Vaccination
By Peter A. McCullough | Courageous Discourse | August 27, 2023
For several weeks I have been messaging the scientific community and the public about an approach addressing the burden of SARS-CoV-2 Spike protein in tissues and organs in the human body that is largely responsible for post-COVID and vaccine injury syndromes.
No therapeutic claims can be made since large, prospective, double-blind randomized, placebo-controlled trials have not been completed on any of the compounds mentioned in this paper. I checked clinicaltrials.gov and no such trials have been planned. The Biden HHS US Action Plan for Long-COVID Research has pumped a billion dollars into long-COVID research and no new therapies have emerged. HHS, NIH, CDC, FDA have not recognized the larger issue of vaccine damage to the body.
At three and one half years into the pandemic and two and a half years into the COVID-19 vaccine debacle, myself and my clinic partners formulated a baseline regimen upon which additional drugs or agents can be added. We believe the Spike protein and the inflammation caused by it and its proteolytic fragments are at the heart of the pathophysiology we are observing.
We searched the literature for all available sources of evidence for products that can aid the human body in breaking down and catabolizing the Spike protein. We found two compounds, nattokinase and bromelain. Both of which additionally have fibrinolytic properties which are advantageous in the prothrombotic milieu induced by the persistent Spike protein. Curcumin was added for its anti-inflammatory properties in the setting of post-COVID and vaccine patients. The main safety caveats are bleeding and allergic reactions, both of which are manageable. It is our experience that both nattokinase and bromelain can be used in addition to antiplatelet and anticoagulant drugs with physician monitoring.
The empiric regimen can be continued for 3-12 months or more and be guided by clinical observation:
-Nattokinase 2000 FU (100) mg orally twice a day without food
-Bromelain 500 mg orally once a day without food
-Curcumin 500 mg orally twice a day (nano, liposomal, or with piperine additive suggested)
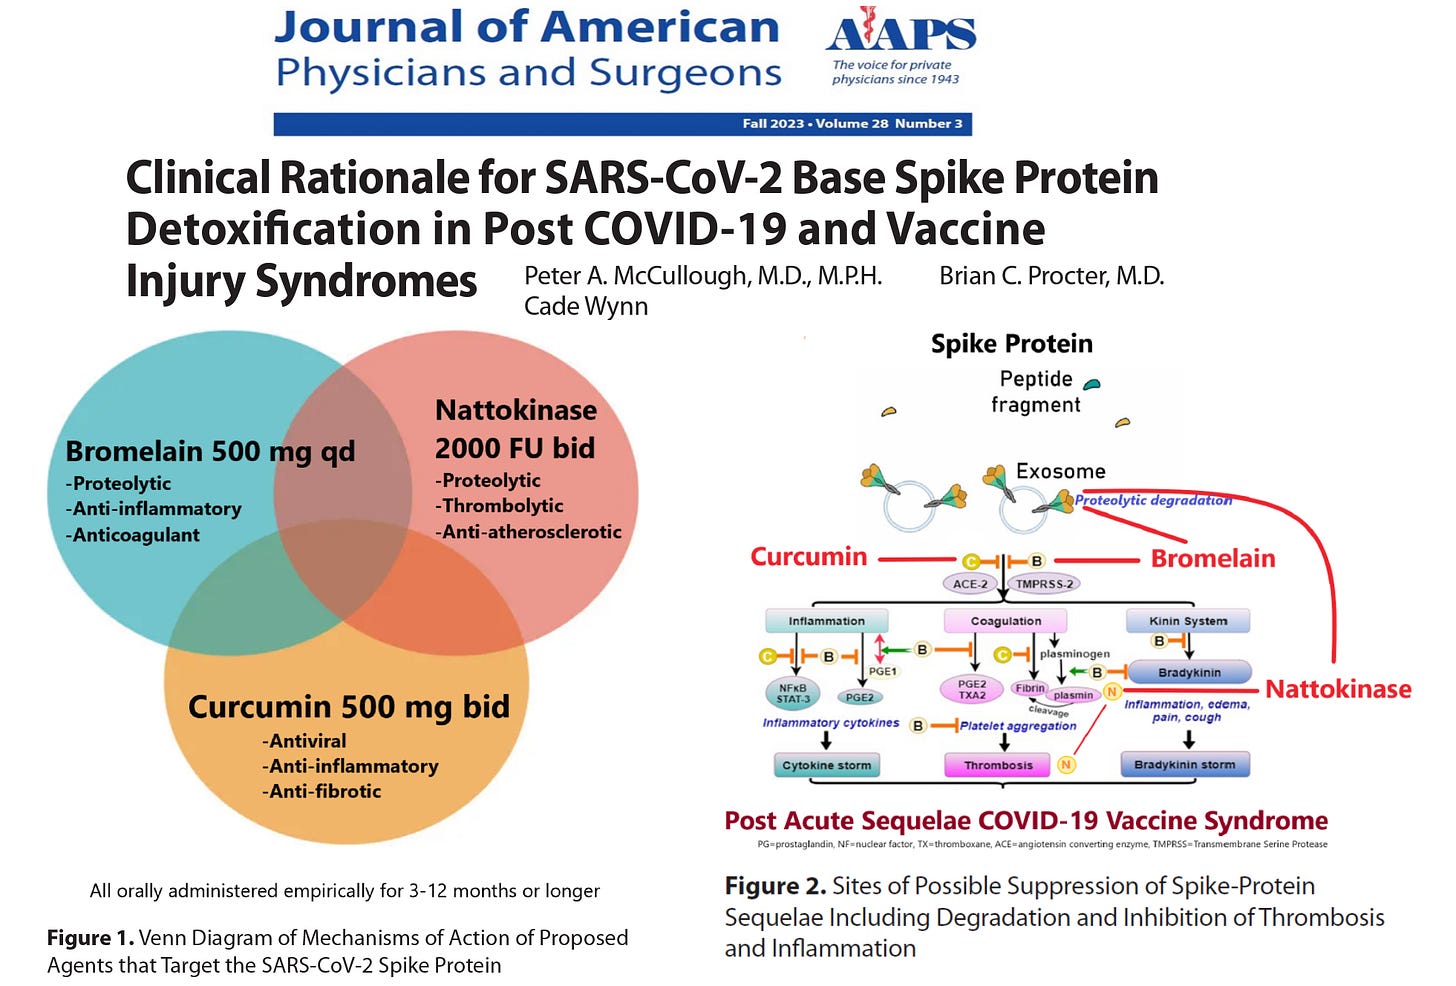
The full manuscript is linked and serves as your reference. While we are seeing case examples of improvement, we aim to collaborate with others as we did with the McCullough Protocol, to demonstrate clinical effectiveness of Base Spike Detoxification as a fundamental strategy for a large number of individuals who have suffered long-term consequences from SARS-CoV-2 infection and COVID-19 vaccination.
Brownstone Institute | August 26, 2023
Last year, it seemed that masks were gone for good. US District Judge Kathryn Kimball held that Biden’s national mask mandate on airplanes was “illegal.” Airlines and airports immediately revoked their mask requirements. Flight attendants sang in celebration, passengers cheered, and companies welcomed the change in policy.
While Americans rejoiced, the Biden Administration worked behind the scenes to ensure that it could reimplement mask mandates at any time, in any place, for any reason.
The humiliation exercise never had a scientific basis. Existing air filtration systems made the threat of viral transmission on aircraft negligible. Studies found that there was “no direct evidence” of Covid-19 being transmitted aboard aircraft.
Despite the data, President Biden issued nationwide mask mandates in his first hours in office. His administration appealed Judge Kimball’s decision last April. “Our focus here was seeing what power we had to preserve,” explained White House Press Secretary Jen Psaki.
The case was dismissed as moot because the court found, “there is not a grain of evidence that the CDC has any plans to promulgate an identical mandate.”
Recent news suggests that prediction may have been wrong. The Covid regime appears to be revamping for a resurgence of mandates and potential lockdowns. CNN ran a headline Wednesday urging readers to “break out the masks against Covid.” The federal government has entered into Covid-related contracts with consultants and medical equipment providers to enforce “safety protocols” beginning in the next two months.
The return of Covid hysteria begs the question: what “power” did Jen Psaki and the White House want to preserve? Their legal briefs appealing Judge Kimball’s decision offer clues.
In court, the Biden Administration argued that mask mandates should be permissible even if there is no evidence to support them. Further, government lawyers wrote that these mandates should be permissible to any extent that bureaucrats deem necessary, even if the risk of Covid is nonexistent.
That is not hyperbole. Opponents of the mandates argued that the government should have “controlled trials” to provide evidence of efficacy and potential negative side effects before implementing universal masking.
The Biden Administration responded that the government did not need to provide any evidence or rational basis for its orders. Instead, “the CDC’s determination that there was good cause” should be sufficient. Government edicts should not be subject to judicial scrutiny, according to the government’s brief.
Further, there should be no limit to that authority, according to the Biden Administration. “It was equally permissible for the CDC,” the brief argued, “to make the masking requirement applicable to all passengers… regardless of whether there is any indication that the plane is diseased or dirtied.”
It’s not difficult to discern what we might call the Biden Doctrine of administrative rule-making. It means that the agencies can order whatever they want, whether or not there is any plausible basis in law or whether or not there is any rational basis for it at all. It is a doctrine of bureaucratic supremacy.

BY DR GARY SIDLEY | THE DAILY SCEPTIC | AUGUST 24, 2023
It is a long-established conclusion from the scientific world that face masks achieve no appreciable reduction in viral transmission. We knew this in 2015-16 with regard to surgeons and their patients (here and here). We knew this in 2020 from a gold-standard Cochrane review, an analysis of 14 studies on influenza and a healthcare investigation that concluded that masks “may paradoxically lead to more transmissions”. We knew this in 2021 based on the Danish mask study and two comprehensive evidence reviews (here and here). We knew this in 2022 in relation to primary schools and universities, and a debunking of premature pro-mask conclusions drawn from the Bangladesh study. And – as if more evidence was needed – at the start of 2023 we had the latest Cochrane review, yet again concluding that covering our faces with cloth and plastic does not significantly reduce the likelihood of contracting respiratory viral infections. Yet, despite this collective scream from the scientific community that the ‘MASKS DON’T WORK’, it seems that nothing will muzzle the strident protestations of the mask disciples, such as those at Independent SAGE.
A recent article in the Daily Mail led with the scary headline: ‘Scientists raise alarm over new Covid variant and call for return of face masks.’ Two of the scientists raising concerns were Professors Trish Greenhalgh and Stephen Griffin, the former announcing, “It’s, once again, time to mask up”, while the latter concurs – albeit more cryptically – with his recommendation of the re-imposition of a “mitigation-based approach”. Both Greenhalgh and Griffin are members of Independent SAGE.
When Independent SAGE was formed in May 2020, as an alternative to official SAGE, it claimed to be a group of multi-disciplinary experts whose mission was to offer the Government scientific advice on how to minimise deaths during the Covid crisis. In reality, it constituted a group of zero-Covid fanatics pushing extreme counter-pandemic measures: whatever non-evidenced, human-rights-infringing restrictions the Government proposed, Independent SAGE typically called for them to be longer and harsher.
A cursory inspection of the group’s membership explains a lot. The previously-mentioned Trish Greenhalgh is, undoubtedly, the most extreme spokesperson for the pro-mask cult, previously asserting that the search for rigorous scientific evidence was the “enemy of good policy“. The founding Chairman of the group, Professor David King, was the senior scientific advisor to the Government of Tony Blair, currently an influential advocate of globalist agendas promoting top-down control of the population. Another core participant is the lifelong member of the Communist party – Professor Susan ‘let’s-wear-a-mask-forever‘ Michie. Also, the current co-Chair of Independent SAGE is Anthony Costello, a Professor of Global Health and Sustainable Development at University College London and a former director at the World Health Organisation. Given the histories and affiliations of these group participants it was predictable that they would grasp the next available opportunity to call for the return of community masking.
Clearly, the use of the term ‘independent’ in relation to this group was a misnomer. In stark contrast, Dr. Ashley Croft – the independent expert commissioned by the Scottish Covid Inquiry – appears to be a much better fit for the role of supplier of impartial information, free from the shackles of groupthink and mainstream ideology. Dr. Croft is a Consultant Public Health Physician and Medical Epidemiologist. In his report he lists his conclusions about the physical measures taken against COVID-19 as follows (emphasis mine):
In 2020 there was scientific evidence to support the use of some of the physical measures (e.g. frequent handwashing, the use of PPE in hospital settings) adopted against COVID-19. For other measures (e.g. face mask mandates outside of healthcare settings, lockdowns, social distancing, test, trace and isolate measures) there was either insufficient evidence in 2020 to support their use – or alternatively, no evidence; the evidence base has not changed materially in the intervening three years.
It has been argued that the restrictive measures introduced during the COVID-19 pandemic resulted in individual, societal and economic harm that was avoidable and that should not have occurred.
This genuinely independent voice was not well-received in some quarters. Unused to the expression of viewpoints that deviate from the dominant Covid narrative, the mainstream media predictably squealed disapproval about Croft’s perspective and resorted to attempts to smear him for his “vaccine scepticism”. And no doubt those ideologues at Independent SAGE will – as I write – be doing likewise.
As the year advances, the evidence against mass masking continues to accumulate. In April, researchers at London’s St. George’s Hospital reported that a mask mandate in 2020-21 in their healthcare settings “made no discernible difference to reducing hospital-acquired SARS-CoV-2 infections”. And – lest we forget – we purportedly live in a free and open society where coercive restrictions should only be imposed where there is unequivocal proof of a pronounced and widespread benefit from adoption of the behaviour targeted; we are a million miles away from that scenario, and that is even before we consider the harms of community masking.
But will this quieten the pro-mask cult? It seems these perpetual advocates of face coverings are driven by some supra cognitive construct that trumps the empirical evidence. Mass concealment of human faces appears to signify something sacred to groups like Independent SAGE: is it equality, egalitarianism, altruism? Or could their persistent pushing of masks be simply due to cognitive dissonance: they have stridently trumpeted the practice for so long that it would now be too psychologically painful, and damaging to their status and self-image, to admit their previous energies have been woefully misplaced? Whatever the underlying reason, we can expect escalating appeals from the muzzle mafia over the coming months.
Dr. Gary Sidley is a retired NHS Consultant Clinical Psychologist and co-founder of the Smile Free campaign.
The Highwire with Del Bigtree | August 24, 2023
Mass media is calling for the reinstitution of COVID restrictions due to new variants, with no conversation about the efficacy or the harm they’ve caused. Jefferey Jaxen connects all the dots, which appears to be pointing to a Pandemic 2.0.
BY DR CARL HENEGHAN AND DR TOM JEFFERSON | THE DAILY SCEPTIC | AUGUST 25, 2023
This week saw the publication of a suite of systematic reviews by the Royal Society (RS) on the effect of non-pharmaceutical interventions in the pandemic.
Politico headlined with ‘Top review says Covid lockdowns and masks worked, period’. The Guardian led with ‘Lockdowns and face masks “unequivocally” cut the spread of Covid, report finds’, and the i newspaper stated: ‘Masks and social distancing did reduce Covid infections, new report shows, proving lockdown sceptics wrong.’
So there you have it, a slam dunk, sceptics, you were all wrong. You should have masked up and stayed in lockdown.
Even more so when you listen to the Chair of the report’s group, Mark Walport, who said: “There is sufficient evidence to conclude that early, stringent implementation of packages of complementary NPIs was unequivocally effective in limiting SARS-CoV-2 infections.”
Four systematic reviews informed the effectiveness of non-pharmaceutical interventions in the Covid pandemic. However, here is some of what these reviews report.
A systematic review on environmental control measures:
Many of these studies were assessed to have critical risk of bias in at least one domain, largely due to confounding factors that could have affected the measured outcomes. As a result, there is low confidence in the findings.
One study, an RCT, showed that daily testing of contacts could be a viable strategy to replace lengthy quarantine of contacts. Based on the scarcity of robust empirical evidence, we were not able to draw any firm quantitative conclusions about the quantitative impact of TTI interventions in different epidemic contexts.
Effectiveness of face masks for reducing transmission of SARS-CoV-2:
We analysed 35 studies in community settings (three RCTs and 32 observational) and 40 in healthcare settings (one RCT and 39 observational). Ninety-one percent of observational studies were at ‘critical’ risk of bias (ROB) in at least one domain, often failing to separate the effects of masks from concurrent interventions.
Effectiveness of international border control measures during the COVID-19 pandemic:
There is little evidence that most travel restrictions, including border closure and those implemented to stop the introduction of new variants of concern, were particularly effective.
The report makes the same errors that the UKHSA and Public Health England did. They ignored the critical biases and the confounders when drawing conclusions. Some of the comments misunderstand the evidence required for making healthcare decisions.
Chris Dye, Professor of Epidemiology at the University of Oxford, who led the review on masks for the Royal Society, said if they had only looked at randomised controlled trials, they would have come to the same conclusion as the Cochrane review. However, the researchers behind the paper released Thursday chose to analyse a larger body of studies and found strong evidence that masks work.
So, if we ignore high-quality evidence, we arrive at the conclusion we want – they fully understand the politics. Low-quality evidence means the estimated effect will differ substantially from the actual effect – we’ve known this for quite some time, and it is fundamental to the delivery of evidence-based interventions. An approach that uses low-quality evidence shouldn’t inform healthcare, and it doesn’t. That’s why we have NICE, which uses the best available evidence to develop recommendations that guide health, public health and social care decisions.
Did the reviewers, for instance, ask if there was a protocol for any of these studies – something we have previously pointed out. There were none, despite protocols being essential for robust research.
There is something we do agree with in the report, that the “future assessments should also consider the costs as well as the benefits of NPIs, in terms of their impacts on livelihoods, economies, education, social cohesion, physical and mental wellbeing, and potentially other aspects”. However this report looked at none of that. The single focus on one outcome, ignoring harms, further hinders informed decision-making.
The RS report wants us to believe that RCTs are impossible during a pandemic: “While RCTs should not be discounted, it is highly likely that most information in a future pandemic will continue to be observational.”
Yet the pandemic has re-emphasised the importance of high-quality randomised clinical trials and highlighted the need for preparation, coordination and collaboration.
The Royal Society review shows that some academics are losing their ability to think critically. Instead of retrofitting evidence to preconceived conclusions, it would be much better to report the uncertainties and set out those questions that need addressing. Refusal to acknowledge uncertainties does a disservice to society and undermines public trust in research.
Staying at home decreases your risk of all sorts of hazards – in the short term, you won’t get run over and you’ll reduce the risk of an infection or an accident. But what matters is the costs of what happens when you reemerge.
Poll Statistics Reveal America Waking Up to Immunization Debacle
By Peter A. McCullough, MD, MPH | Courageous Discourse | August 23, 2023
The Kaiser Family Foundation is a pro-vaccine organization that has an biased polling system aimed at showing satisfaction and benefit of mass vaccination among other family issues. The May 23 through June 12, 2023 poll reveals some shocking new data. A substantial minority of Americans believe the COVID-19 vaccines have caused great harm. Here are the results.

As you can see it is roughly a third of Americans are awake and understand the COVID-19 vaccines have failed, cause great harm, and pose a giant safety risk to Americans. It is also interesting to note a quarter of respondents have been awakened to the link between childhood hyper vaccination and autism spectrum disorder. I wonder what the actual sentiment is on vaccines if Kaiser had asked the questions in a more unbiased manner and did not load up their survey with charged words such as “false” and “misinformation”.

or go to
Aletho News Archives – Video-Images
By Donald Neff | Washington Report On Middle East Affairs | January 1996
On January 4, 1948, Jewish terrorists drove a truck loaded with explosives into the center of the all Arab city of Jaffa and detonated it, killing 26 and wounding around 100 Palestinian men, women and children.[1] The attack was the work of the Irgun Zvai Leumi – the “National Military Organization,” also known by the Hebrew letters Etzel – the largest Jewish terrorist group in Palestine. The Irgun was headed by Revisionist Zionist Menachem Begin and had been killing and maiming Arabs, Britons and even Jews for the previous ten years in its efforts to establish a Jewish state.
This terror campaign meant that at the core of Revisionist Zionism there existed a philosophical embrace of violence. … continue
 Aletho News If Americans Knew No Tricks Zone

