Those Doctors Calling for Spreaders of Covid Misinformation to be Punished Should be Careful What they Wish For
Many of their Claims – that the Vaccinated Couldn’t Infect Others, For Instance – Turned Out to be False
BY NIGEL WILSON | THE DAILY SCEPTIC | AUGUST 24, 2023
The Journal of the American Medical Association recently published a review of alleged ‘misinformation’ about COVID-19 that physicians were responsible for, either on social media and in other news sources.
In the paper, the corresponding author, Dr. Sarah L. Goff, MD PhD, defined misinformation. She surveyed social media platforms and news sources for anything written by other physicians that fits her selected examples of both. She then proposes that physicians guilty of writing what she judges to be misinformation should be “regulated and disciplined”.
Dr. Goff and her co-authors define misinformation as “false, inaccurate or misleading information according to the best evidence available at the time” and disinformation as “having an intentionally malicious purpose”.
Dr. Goff states: “We conservatively classified inaccurate information as misinformation rather than disinformation because the intent of the propagator cannot be objectively assessed.”
Dr. Goff identified four major themes of alleged misinformation. These included: (1) vaccines were unsafe and/or ineffective; (2) masks and/or social distancing did not decrease risk for contracting COVID-19; (3) other medications for prevention or treatment were effective despite not having completed clinical trials or having been FDA approved, and (4) other misinformation.
Dr. Goff includes a brief discussion of vaccine safety and effectiveness and mask effectiveness, but does not attempt to undertake a full review of the published evidence in these areas. Instead, she seems to assume that her readers will agree that any suggestion that vaccines or masks were ineffective or unsafe are self-evidently false.
Dr. Goff states that the American Medical Association has called for disciplinary action for physicians propagating COVID-19 misinformation. She laments the fact that “few physicians appear to have faced disciplinary action” for alleged sins against Covid orthodoxy.
I am not an expert in analysis of published medical research. I don’t work in a School of Public Health like Dr. Goff. I have worked as a licensed physician in England for over 40 years as a family doctor and an occupational physician and I have over 40 years’ experience reading the medical peer review literature. I retired from full time medical practice in 2017. I have a reasonable understanding of English, maths, logic and critical thinking. I don’t pretend to have read all the published research on masks or vaccinations. However, I continue to read leading medical journals on a regular basis.
I understand the concept of truth and how hard it is to establish an absolute truth in science. I understand the enlightenment principles that any ideas can be discussed, that nobody has a veto on ideas and that it is important to doubt and test all of our ideas continually. There is no indication from her writing that Dr. Goff understands how important it is to doubt, question and test the effectiveness and safety of interventions such as vaccines and masks.
From my reading of the peer review literature, for illustration purposes, I identified the following four publications as examples of publications which should raise concerns and questions about COVID-19 vaccines and masks.
In 2019, the World Health Organisation (WHO) published a report entitled ‘Non-pharmaceutical public health measures for mitigating the risk and impact of epidemic and pandemic influenza’. The WHO concluded: “There are a number of high-quality randomised controlled trials demonstrating that personal measures (e.g. hand hygiene and face masks) have at best a small effect on transmission.”
In February 2023 a Cochrane review into the effectiveness of masks concluded: “Compared with wearing no mask in the community studies only, wearing a mask may make little to no difference in how many people caught a flu-like illness/Covid-like illness.”
A study from the Department of Infectious Diseases in Cleveland, Ohio, in December 2022 found that “the bivalent COVID-19 vaccine only offered modest effectiveness”.
A study from the University of Queensland in September 2022 concluded: “Never in vaccine history have 57 leading scientists and policy experts released a report questioning the safety and efficacy of a vaccine. They not only questioned the safety of the current COVID-19 injections but were calling for an immediate end to all vaccination. Many doctors and scientists around the world have voiced similar misgivings and warned of consequences due to long-term side effects.”
These four publications are examples which give us a legitimate reason to question the use of masks and the Covid vaccines and to look further for evidence. Are we not allowed to raise questions about these issues without being threatened with disciplinary procedures? Not to ask any questions would be lacking in curiosity in the extreme, especially for practising physicians concerned about the safety of their patients and the integrity of their advice. These publications do not prove anything conclusively, but they should not be ignored. Expressing doubt and asking questions about the safety and effectiveness of vaccines and masks is not false, inaccurate or misleading, to use the definition adopted by Dr. Goff. If questions arise in my mind, why don’t similar questions arise in the minds of Dr. Goff and her co-authors? How did Dr. Goff reach such a degree of certainty about the effectiveness of masks and vaccines against COVID-19 that she can classify any statement to the contrary as misinformation worthy of disciplining a colleague? Why does she conclude that a colleague who disagrees with her does not have the right to be heard? Why would she seek to silence those who disagree with her?
Inaccurate information which is not deliberately intended to deceive is simply inaccurate. In science and medicine there are many inaccurate statements made in good faith by researchers who are presenting their data or their theories as accurately and honestly as possible. It is important that all theories and all research data can be published, even when the data or the theory are wrong. Disciplinary action for any statement which turns out to be inaccurate or false would surely suppress a large proportion of all scientific and medical discourse. Is this what Dr. Goff wants?
It could be argued that the examples of misinformation used by Dr. Goff are themselves misinformation. To suggest that anyone who states that the Covid vaccines were unsafe and/or ineffective is guilty of misinformation is to ignore significant evidence which raises questions about the vaccines. To suggest that anyone who states that masks did not decrease risk for contracting COVID-19 is guilty of misinformation is also to ignore evidence to support this view. It could be argued that Dr. Goff is using false, inaccurate or misleading examples of misinformation in her study in order to suppress dissenting views.
Dr. Goff appears to have very little humility. She does not appear to be in any doubt that she and her co-authors are infallible in relation to masks and vaccines. She seems to think she is the ultimate arbiter of truth, and that she is immune from being regulated or disciplined for her views in the way she promotes for others. I would not propose disciplining or applying regulatory sanctions to Dr. Goff or her colleagues if her publication includes false, inaccurate or misleading statements. Instead, I would propose respectful dialogue with her to debate her proposal, offering arguments to the contrary with a view to educating her and myself.
In England, medical doctors are obliged to respect colleagues’ skills and contributions, and to treat colleagues fairly. We must create a working environment in which it is safe to ask questions and raise concerns. I believe in these principles. Failure to adhere to these standards can lead to disciplinary action against medical doctors. I understand that similar professional obligations apply to medical doctors in the United States. Dr. Goff does not appear to respect the skills and contributions of colleagues who disagree with her. She seems to be promoting a working environment in which it is not safe for those who disagree with whatever the orthodoxy within the medical profession is at any one time to ask questions and raise concerns. Does she not realise that this may make it unsafe for her to raise concerns and ask questions in due course?
Dr. Goff acknowledges in her final sentence that “a coordinated response by federal and state governments and the profession that takes free speech carefully into account is needed”. This tiny nod towards free speech is somewhat undermined by her attempts to censor her colleagues’ right to disagree with her. Free speech is nothing if it is not accorded to those with whom we disagree.
Frederick Douglass, the American social reformer said: “To suppress free speech is a double wrong. It violates the rights of the hearer as well as those of the speaker.” If Dr. Goff persuades those in power to regulate or discipline those who disagree with her, then their right to free speech is violated and our right to hear them is violated. Does Dr. Goff not have a glimmer of doubt about her omniscience? Does she not think there is even a faint possibility that physicians who disagree with her might have something useful to say?
Why do some physicians think that the best response when another physician disagrees with them is to censor their colleague? How could any physicians achieve such unshakeable certainty in their own omniscience? When did they forget the fundamental principles of the enlightenment, that all ideas can be discussed and that nobody has a veto on any ideas? How did the principles of treating colleagues with respect and upholding the free speech of those with whom we disagree become so degraded?
Dr. Goff and her co-authors should be careful what they wish for. They seek to discipline colleagues for daring to disagree with their orthodoxy. If they succeed, the cancel police may be coming for them next.
Dr. Nigel Wilson MRCGP FFOM is a retired consultant occupational physician.
German Judge Gets Probation Sentence For Allowing Kids to go Maskless
After his house was raided in 2021

NAKED EMPEROR | AUGUST 23, 2023
Christiaan Dettmar, a family judge from the Weimar District Court in Germany recently faced the Erfurt Regional Court for his stance against the unnecessary imposition of mask mandates on children. In April 2021, going against the grain, he ruled that children at two Weimar schools should not be burdened with wearing Covid masks in class, defying the restrictive guidelines set by the Thuringian Ministry of Education.
However, in a move reflective of the bureaucratic stranglehold on such decisions, higher courts dismissed his ruling, claiming it unauthorised. The Thuringian Higher Regional Court stated that the family judge did not possess the jurisdiction on this matter, a viewpoint also echoed by the Federal Court of Justice. They insisted that only administrative courts should handle state orders regarding corona protection measures.
At the time (in April 2021), Dettmar had his office, private residence and car searched after he ruled that children should not be wearing masks. He also had his phone confiscated after his decision which embarrassed the government.
His decision to end mask mandates was made after hearing evidence from Professor Kappstein on the lack of benefit of wearing masks and observing distance rules for the children and third parties. Kappstein said that after evaluating all the international data on the subject of masks, the effectiveness of masks for healthy people in public is not supported by scientific evidence.
Dettmar concluded that not only are masks useless but they are also dangerous.
The compulsion imposed on school children to wear masks and to keep their distance from each other and from third persons harms the children physically, psychologically, educationally and in their psychosocial development, without being counterbalanced by more than at best marginal benefit to the children themselves or to third persons. Schools do not play a significant role in the “pandemic”.
The PCR tests and rapid tests used are in principle not suitable on their own to detect an “infection” with the SARS-CoV-2 virus. This is already clear from the Robert Koch Institute’s own calculations, as explained in the expert reports. According to RKI calculations, as expert Prof. Dr. Kuhbandner explains, the probability of actually being infected when receiving a positive result in mass testing with rapid tests, regardless of symptoms, is only two per cent at an incidence of 50 (test specificity 80%, test sensitivity 98%). This would mean that for every two true-positive rapid test results, there would be 98 false-positive rapid test results, all of which would then have to be retested with a PCR test.
A (regular) compulsion to mass-test asymptomatic people, i.e. healthy people, for which there is no medical indication, cannot be imposed because it is disproportionate to the effect that can be achieved. At the same time, the regular compulsion to take the test puts the children under psychological pressure, because in this way their ability to attend school is constantly put to the test.
In the recent trial against Judge Dettmar, although the prosecution demanded a hefty three-year prison term, the defence, representing the concerns and wishes of countless parents and citizens, argued for acquittal. The presiding judge at the Erfurt Regional Court noted that the Weimar judge’s decision emanated from his personal views.
After originally being sentenced to two years in prison, the court has now suspended the sentence on probation.
However, it is still possible that Dettmar may lose his office and pension as a result of the conviction.
Throughout the proceedings, the courtroom was electric with tension and support. Spectators broke into spontaneous applause in favour of Dettmar. This would have continued except the judge threatened to throw them out. The prosecution’s attempt to paint the judge’s intentions as malicious was met with scepticism. They claimed that he intentionally set up a child protection procedure against the mask mandate, misrepresenting it as a statement against government measures. Their evidence, mainly based on emails and chat messages, was tenuous at best.
The defence, however, passionately highlighted the judge’s genuine concern for the well-being of children. They asserted that the case was merely an attempt to suppress and penalise differing opinions in a society where free thought should be celebrated.
Reiterating his unwavering stand, Dettmar confirmed he would make the same decision again. The subsequent lifting of school mask mandates by German states in April 2022 only reinforces the argument that such restrictions should never have been in force in the first place.
The American Board of Internal Medicine’s Longstanding War On Doctors Is Escalating
The ABIM’s history proves their present actions are political/financial and not scientific. They are making examples of us “dissenters” to scare the rest of the country’s docs to keep quiet.
BY PIERRE KORY, MD, MPA | AUGUST 23, 2023
The unholy alliance of industry captured high-impact medical journals, federal public health agencies, professional societies (ABIM, AMA, APHa etc), and most importantly, the state medical licensing boards directed by the Federation of State Medical Boards (FSMB) are still going hard after us “dissenting” doctors. You know, those of us that very publicly called out the unscientific policies implemented by corrupted policymakers in a directed pursuit of profits and power. Their actions trying to silence us (and to scare other doctors from speaking out) are escalating.
Recently, what I call the “misinformation committee” of the American Board of Internal Medicine (ABIM) voted to strip Professor Paul Marik and myself of our Board certifications. To best understand why they would do this, I think it is important to review what the ABIM is, how it operates, and then detail their absurd attempt to paint us as misinformationists by using disinformation.
Let’s trace my current relationship with the ABIM to today:
At the end of my training, I became Board Certified by the ABIM in three specialties (Internal Medicine, Pulmonary Diseases, and Critical Care Medicine).
What is the ABIM? Well, from this devastating article by Kurt Eichenwald, an accomplished corporate investigative journalist who did a devastating takedown of the ABIM and its officers in a Newsweek piece in 2015:
The ABIM is a purported nonprofit that certifies new physicians as meeting standards of practice. Beginning in the early 1990s, the ABIM ordered certified doctors to be recertified, again and again. Without the ABIM seal of approval, lots of internists and subspecialists can’t get jobs and can’t admit patients to hospitals. So by taking advantage of that monopolistic power, the ABIM has forced hundreds of thousands of physicians to follow recertification processes that doctors complain cost them tons of money (paid to the ABIM), require tons of time (taken from families and medical practices) and accomplish nothing.
In many doctor’s opinion, this cash grab of the ABIM by selling “certifications” is a corrupt farce. There is no evidence that certifying doctors in this highly costly way does anything to improve the quality of care delivered. The ABIM has not only refused to produce data showing the program improves patient care but also hasn’t conducted any studies on that matter. In fact, the ABIM and its related organizations are:
harming American medicine and diminishing the quality of scientific research, pushing physicians to close practices rather than wasting time on expensive and frustrating busywork, and forcing specialists to play a game of medical trivial pursuit. (Even Baron has admitted that he was tested for recertification on topics he never used in his practice.)
But it sure does generate cash for ABIM executives. Note that Board Certification used to simply be a sort of “honor” denoting that the member passed a more rigorous examination in their specialty. That “honor” comes at a price though:
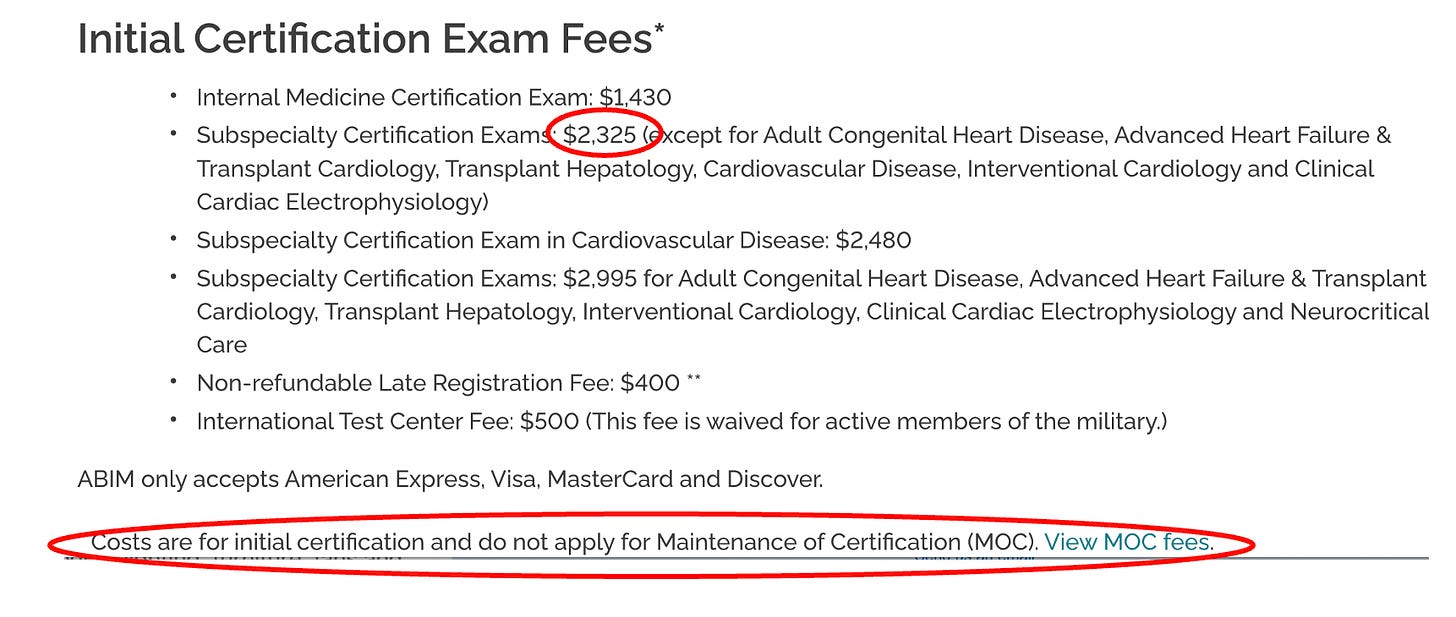
Since I am (was?) Board certified in 3 specialties, lets do some math as this is what it costs me to re-certify every ten years:
$1,430 for Internal Medicine
$2,325 for Pulmonary Diseases
$2,325 for Critical Care Medicine
But wait, we are not done yet. These bastards were not making enough money with once-every-ten-year recertification exam fees, so they invented a new program of annual busywork education requirements which they called Maintenance of Certification (MOC) which costs you $220 every year for every certification (plus late fees if you forget). To wit, I went into my patient portal and discovered. I owe them $480 for each of my certifications!
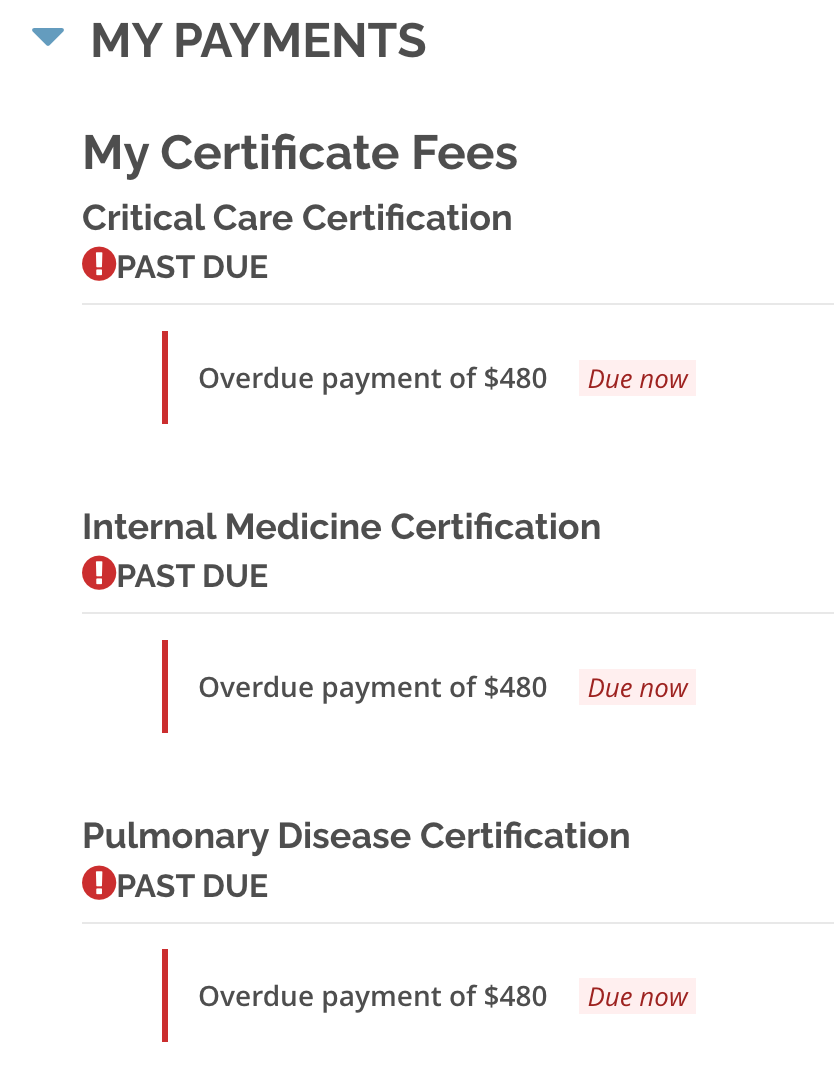
And get this – that money essentially goes to ABIM executive salaries and pensions and other dubious private investments as described by Eichenwald where he details the insane lengths the ABIM goes to “hide” the compensation and pension data on its executives. What is worse is that ABIM certification has now been made a requirement of employment as a faculty member of academic medical centers and hospitals and is also a requirement to be on many insurance company panels (these actions further strengthen the control of doctor behavior).
Doctors have started publicly slamming the group in industry publications. “ABIM is imposing on us an onerous and ill-conceived tool, one that most physicians agree is irrelevant,” Dr. Karmela Chan wrote in Internal Medicine News. “I am glad this conversation is happening, because, frankly, the process was enough to make me want to quit being a doctor.” Further, in a recent poll of 2,211 physicians conducted on a doctors-only website called Sermo, 97 percent of the respondents criticized recertification.
Richard J. Baron, the ABIM CEO that sent letters threatening decertification to me and Paul, makes close to a million dollars a year, however that data is almost impossible to find due to the ABIM’s multiple attempts to obscure it as well as its spokespeople avoiding answering any inquiries on the topic. Here is a summary of Eichenwalds findings on the ABIM:
- In 2015, they were 5 months late in filing their publicly available financial report with the IRS (that several journalists were very interested in).
- The report is full of obfuscations and anomalies of reporting of not only the actual money earned by the executives, and particularly Baron, but his financial conflicts of interest are even better hidden.
- A big percentage of the ABIM’s millions was in the form of cash to one former employee.
- The ABIM in 2013 had 57 million against liabilities of 105 million – while Baron was going around saying that its assets are three times its liabilities (this was a 100% lie. When I get to the ABIM’s response to our defense letter, remember that what liars do is.. lie).
- It lost $4.8 million on $55.5 million in revenues, no small feat and almost entirely due to a bloated payroll.
- It also claims it spends no money on lobbying while it spent between 100K to 160K annually to lobby Congress on Medicare and Medicaid (another lie).
- The data on top officers compensation is so obscured and fragmented, Eichenwald reported that he had found it much easier to discover executive compensation at Enron, Worldcom and Adelphia – all famous for lying on tax filings. Again no small feat (to be one of the top corporate liars in the U.S).
- Officers “double dip” – former CEO Christine Cassel got $741K from ABIM and $247K from the ABIM “Foundation” (slush fund for ABIM officials) and also got $219K in “other compensation” – totaling $1.2 million for one year. (Nice gig if you can get it).
- But wait, we are not done. Cassel also got $504K in “deferred compensation” for a total of $1.71 million more that year (six times the median compensation for similar sized non-profits). Six times.
Then there is this doozy of an article which came out this week in The Defender by Children’s Health Defense, detailing the ABIM CEO Richard Baron’s conflicts of interest:

Some of the most disturbing reveals:
“The head of a national medical organization who publicly called for doctors to lose their licenses unless they supported government narratives on COVID-19 treatments and vaccines concealed his relationship with a public relations firm whose client list also included Pfizer, Moderna and the Centers for Disease Control and Prevention (CDC).
Dr. Richard Baron, president and CEO of the American Board of Internal Medicine (ABIM) is a client of Weber Shandwick, investigative journalist Paul D. Thacker reported on Wednesday.
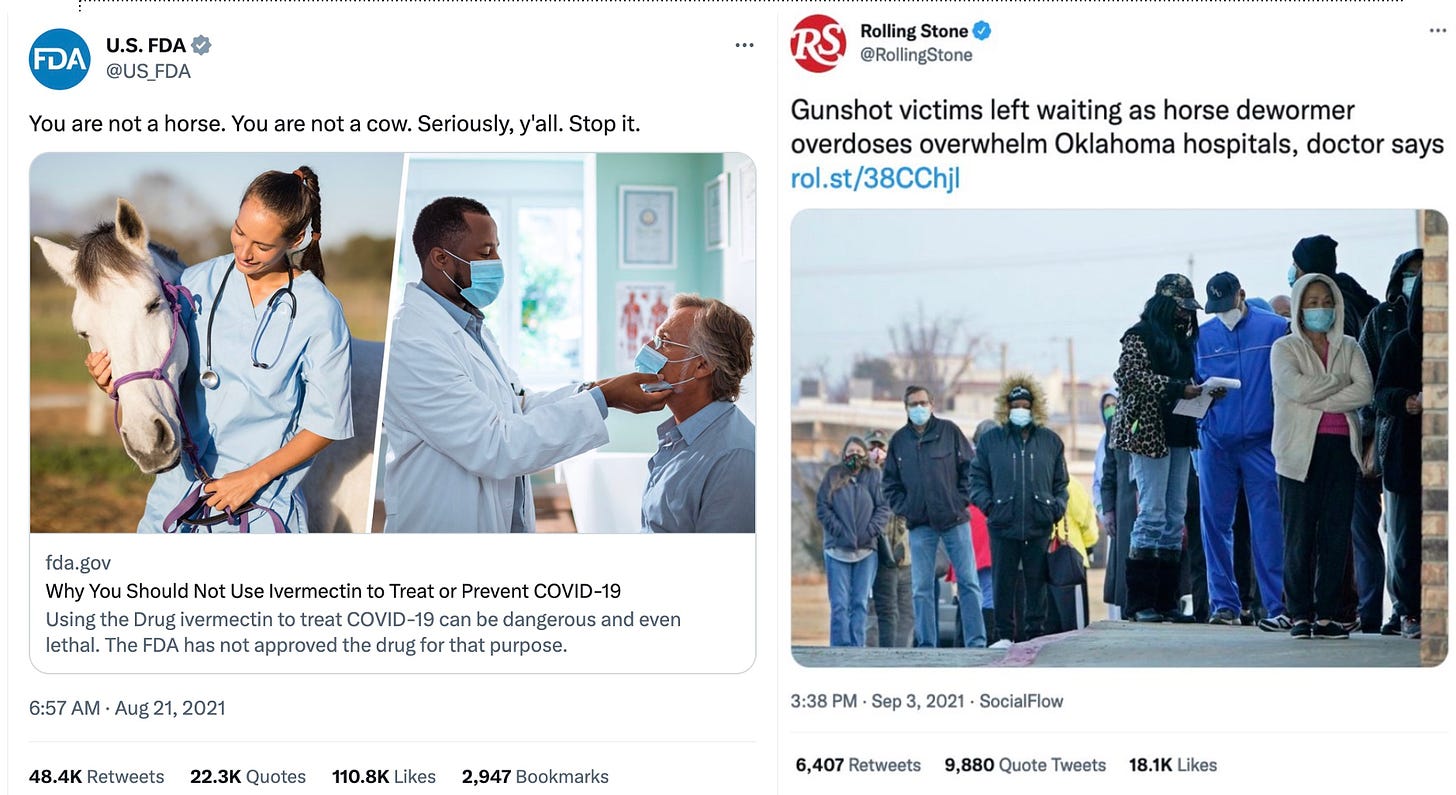
Note that I went after Weber Shandwick in my book, “The War on Ivermectin” where I argue (without proof, although I believe that is coming because I know of a subpoena coming their way) that they created and launched the “Horse Dewormer PR campaign,” highlights of which was the famous FDA tweet and absurd Rolling Stone article:
In late 2021, Baron publicly pushed for doctors who spread “misinformation” about COVID-19 and the vaccines to lose their license and certification.
Last year, Baron partnered with Weber Shandwick to propose a South by Southwest (SXSW) panel titled “When Doctors Prescribe Misinformation.” The proposal was subsequently accepted and the panel took place at SXSW in Austin, Texas, on March 13.
According to Thacker, “Weber Shandwick’s panel featuring Dr. Baron has been widely promoted by the PR firm’s employees,” including Sarah Mahoney, executive vice president, Healthcare Communications, Strategy & Planning for Weber Shandwick, who in a LinkedIn post, wrote she “can’t think of a more important topic right now.”
Although to the unawake the following may seem normal public health practice, but to those of us fighting agency capture by Big Pharma, it is absurd:
The CDC’s National Center for Immunization and Respiratory Diseases (NCIRD) in September 2020 awarded Weber a $50 million contract “to promote the vaccination of children, pregnant women and those at risk for flu and increase the general acceptance and use of vaccines,” according to the PR firm’s website.
Thacker said he believes much of what is labeled “misinformation” in medicine and academic research “is really just corporate PR,” and that “Congress needs to take a harder look at funding for ‘misinformation research.’“
Speaking of taking a harder look at where the funding is coming from for “misinformation research” and the ABIM, it turns out that.. we can’t. Why? Check out this tweet showing a clause inserted into the ABIM’s by-laws in 1998:
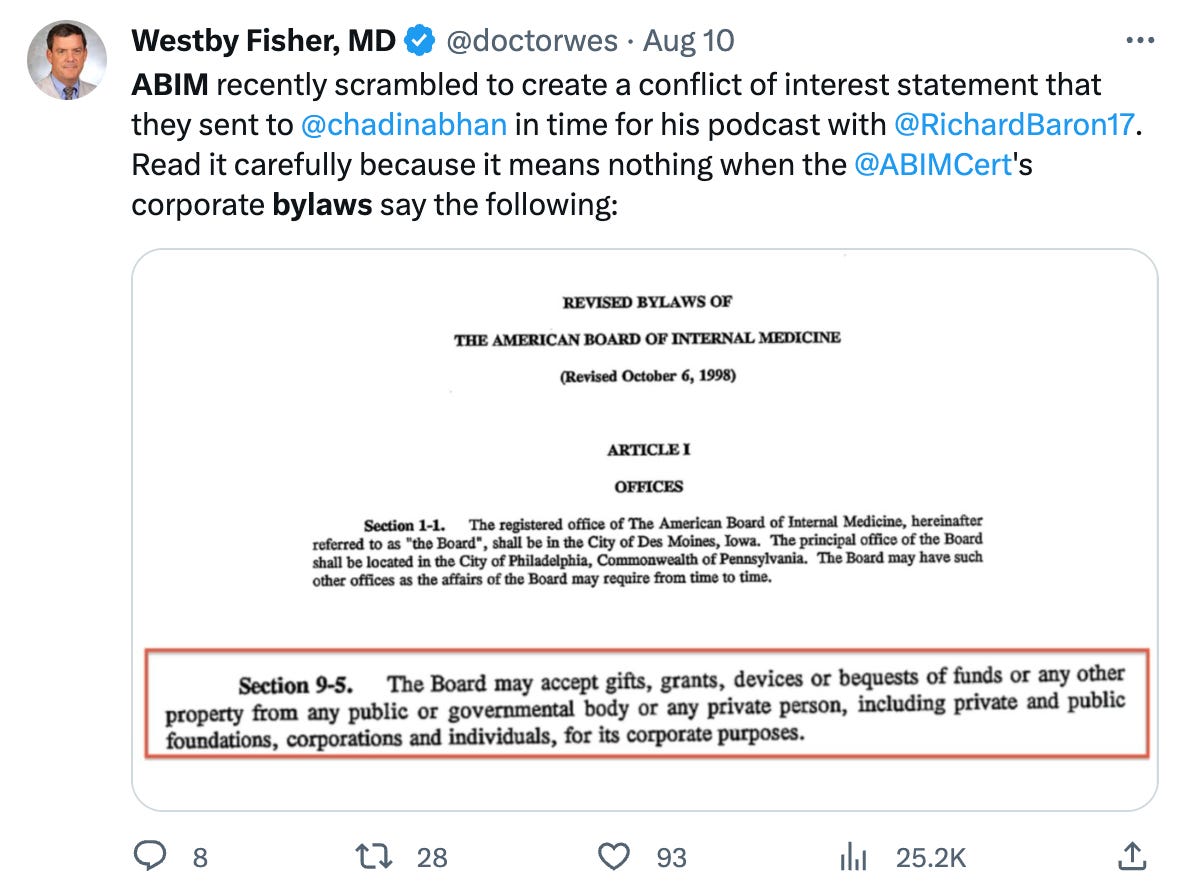
But wait, it gets better, like way better. Also in their by-laws:
Information that is disclosed will be kept confidential except to the:
-
- President and Chair of the Board;
- The chairs of the relevant Subspecialty Boards, Test-Writing Committees, and other Committees of the Board, members who serve on the relevant Boards and Committees, and staff working with the respective committees;
- The Conflict of Interest Committee members and Conflict of Interest Committee staff,
except as required for the purposes of continuing medical education.
So, basically, they can take money from any corporate entity and do not have to disclose it to anyone. Again, nice gig if you can get it.
Back to the ABIM’s history: One of Eichenwalds more disturbing observations about the behavior of the ABIM:
I can attest to the ABIM’s pomposity. Starting with my first story about the ABIM, the organization usually has refused to acknowledge I even asked a question. The only other group to do that in my 30-year journalism career was a company that processed payments for child pornography websites. Plus, when I reported on the uprising by doctors, the ABIM ignored the facts and instead investigated me.
Now lets fast forward to Covid. On July 29, 2021, the FSMB (this entity controls the state medical licensing boards, not the ABIM – at least on paper) issued a policy statement that “Physicians who generate and spread COVID-19 vaccine misinformation or disinformation are risking disciplinary action by state medical boards, including the suspension or revocation of their medical license.”
What is interesting is how fast and how rigidly the ABIM followed the FSMB’s lead and enacted their own misinformation policy despite the fact that, as my colleague Meryl Nass has pointed out:
“suddenly claiming that using licensed drugs for COVID, criticizing federal policies for COVID or criticizing the value of COVID vaccines is unprofessional” gives the specialty board the right to revoke a certification—well, that was never part of its contract with me. So pulling my certification for issues that were never specified in the original contract is breach of contract.
I think it would only be a breach if contracts, like our Constitution and the practice of medical ethics, were still “a thing.”
The ABIM apparently liked the FSMB’s “misinformation policy” idea to attack dissenting doctors so much (or were told to like it) that 2 months later, they, along with their colleagues at the American Board of Pediatrics and the American Board of Family Medicine, issued a statement supporting the FSMB’s position, saying, “We all look to board certified physicians to provide outstanding care and guidance; providing misinformation about a lethal disease is unethical, unprofessional and dangerous.” (note that they seem particularly focused on Covid misinformation and not any other disease model or therapeutics. Do you think it could be because Covid vaccines and therapeutics opened immensely profitable markets to Pharma overnight?).
Again from Meryl Nass (please subscribe to her Substack):
Furthermore, the processes the ABIM is using, as described by CEO Richard Baron, MD in his podcast with the New England Journal of Medicine are procedurally unfair. Dr. Baron earns $1 million/year to threaten doctors for a crime that does not exist. Baron, notably, refused to specify where the line was between misinformation and genuine disagreement in that podcast, though he seems to have no difficulty at all drawing the line when it comes to licensees who speak publicly about how to manage COVID. In a truly Orwellian effort, the ABIM and the ABIM Foundation have dedicated the year to ‘building trust’ in medicine.”
In what I suspect was the ABIM’s first enforcement of their shiny new policy, they go after Peter McCullough, Paul Marik, and myself on the same day (May 26, 2022) with a letter quoting numerous public statements we made, implying that we needed to defend the substance of such statements with supporting data or risk losing our certifications.
“Game on” I thought, looking forward to the exercise of “debating” scientific data with the ABIM. However, our FLCCC lawyer, Alan Dumoff pointed out that the ABIM’s policy and procedures state that the process of accusing a member of misinformation requires that they first provide evidence to us that what we said was inaccurate. So, we wrote back, pointing out to the ABIM their brazen “error” (yeah right) in not complying with their own policy and procedures.
“Nonsense” they wrote back (in short). Their logic was truly shocking – they say that the fact they provided the substance and references to my public statements means they did their duty (rather than their providing references that would refute my statements which is what their policy states they need to do).
You can read their brazen, illegitimate, dismissive response here:

This letter above demonstrates the unchecked power they have – they alone determine whether they are following their own policy which they so clearly were not. What did I say about liars before?
Anyway, rebut them we did. We wrote a 76 page treatise with 175 references, 11 exhibits, and 22,000 words, marshaling and weaving numerous data sources to support all our public statements that they had a problem with. May it enter the historical record here (I think you Covid vaccine and ivermectin data geeks will find the letter impressive).
We sent that letter over 6 months ago… and finally got an answer a few weeks ago. To understand the misinformation committee’s response, note this statement from an editorial written by Baron where he tries to give examples of misinformation:
A whole range of statements with which many — or even most —physicians might disagree would therefore not trigger our disciplinary process. On the other hand, when someone certified by the ABIM says something like “the origin of all coronary heart disease is a clearly reversible arterial scurvy” or “children can’t spread Covid” or “vaccines don’t prevent Covid deaths or hospitalizations,” we are not dealing with valid professional disagreement; we are dealing with wrong answers.
That last sentence is critical as Baron literally is saying that the ABIM gets to determine what is a valid professional disagreement versus a “wrong answer.” Good to know, especially in regards to the fact that the narrative that “vaccines prevent Covid deaths or hospitalizations” was strongly refuted in our initial response letter.
This issue about drawing a line between misinformation and genuine disagreement is a critical one. From our letter of appeal written by our lawyer Alan Dumoff:
Threshold Issue: What Standard Distinguishes Legitimate Differences of Professional Opinion and Misinformation
We disagree with the Committee’ s interpretation of the data, which we address below, but the initial question is by what standard the American Board of Internal Medicine (“ABIM” or “Board”) evaluates evidence to determine that disagreement with consensus generally, and regarding controversial matters around COVID-19 policy specifically, rise to the level of actionable misinformation. The Board’s policy recognizes the right to legitimate debate, which requires it not merely show evidence supporting a consensus view but that it demonstrate that these professional disagreements are not legitimate but outright misinformation.
If not grounded in an articulated standard, at the very least, the Board must demonstrate that the views at issue are false by citing the fallacies in the actual substance of the evidence provided, not simply by critiquing a few isolated studies divorced from the totality of evidence. Resting solely upon citations to mainstream publications while substantially avoiding the evidence in our Submission, and our detailed critiques of these publications does not provide a basis for the Board to take action against my clients.
A diplomate’s medical positions must be plainly erroneous to merit sanction. Departure from consensus is hardly unusual and by itself insufficient. While the Sanctions Notice gives the appearance of having done so, the Committee did not directly engage the numerous imperfections in the mainstream approach Drs. Kory and Marik’s have pointed to in substantial detail. The Committee has not engaged the evidence submitted and demonstrated it is illegitimate, only that it departs from the consensus, that is insufficient to support a sanction.
The point is that the ABIM appears absurdly obsessed with getting doctors to spout only consensus opinions. This is literally unprecedented in science. From Michael Chrichton the author:
I want to pause here and talk about this notion of consensus, and the rise of what has been called consensus science. I regard consensus science as an extremely pernicious development that ought to be stopped cold in its tracks. Historically, the claim of consensus has been the first refuge of scoundrels; it is a way to avoid debate by claiming that the matter is already settled. Whenever you hear the consensus of scientists agrees on something or other, reach for your wallet, because you’re being had. Let’s be clear: the work of science has nothing whatever to do with consensus. Consensus is the business of politics. Science, on the contrary, requires only one investigator who happens to be right, which means that he or she has results that are verifiable by reference to the real world. In science consensus is irrelevant. What is relevant is reproducible results. The greatest scientists in history are great precisely because they broke with the consensus. There is no such thing as consensus science. If it’s consensus, it isn’t science. If it’s science, it isn’t consensus. Period.
I love that last line so much it bears repeating, “If it’s consensus, it isn’t science. If it’s science, it isn’t consensus. Period.”
Now, let’s look at their response to our 76 page letter teeming with supportive data for our statements. Can read their letter in its entirety here but I thought I would just pull the most illustrative sections:
… the CCC (i.e. misinformation committee) concluded that your statements about the purported dangers of, or lack of justification for, COVID-19 vaccines are false and inaccurate because they, too, are not supported by factual, scientifically grounded, and consensus driven scientific evidence. In fact, the overwhelming body of factual, scientifically grounded, and consensus-driven evidence – at and since the time you made those statements – shows that the COVID-19 vaccines are safe and effective for children and for adults
I have heard of the term “evidence-based medicine (EBM)” which is what I practice, but not “consensus driven science” (completely new invention – pernicious indeed. I Actually adhere to the original definition and conceptual framework envisioned by the founders of evidence based medicine which was incredibly well detailed in a by my friend “A Midwestern Doctor” in his brilliant recent post “What Happens To Doctors Who Innovate”.
Anyway, they then listed a few published, peer-reviewed papers supporting their point, blissfully un-acknowledging of the fact that the high-impact journals have been systematically censoring pretty much all negative analyses of the vaccine campaign’s impacts while publishing nothing but positive reports with cherry-picked and/or fraudulent data – so there is no way for the truth about vaccines to win in scientific debates my friends.
The high-impact journal censoring of adverse vaccine data is identical to their censoring of dozens of positive trials of ivermectin, something I extensively detail in the chapter called “The Journal Rejections of Positive Ivermectin Studies” in my book.
It gets even better – they next argue against my claims of lack of safety of the vaccines by, get this, referencing proclamations by the WHO and CDC. They ignore all the immense data to the contrary that I submitted while of course being willfully oblivious to the fact that the CDC and WHO are fully Pharma captured agencies:
Moreover, the vaccine safety data overwhelmingly (overwhelmingly?) contradicts your statements about vaccine risks. See, e.g., Centers for Disease Control and Prevention, “Safety of COVID-19 Vaccines,” https://www.cdc.gov/coronavirus/2019-ncov/vaccines/safety/safety-of-vaccines.html (updated March 7, 2023) (reporting that “Adverse Events (Serious Safety Problems) Are Rare,” and that “[t]he benefits of COVID-19 vaccination outweigh the known and potential risks”); World Health Organization, “Safety of COVID-19 Vaccines,” https://www.who.int/news-room/feature-stories/detail/safety-of-covid-19-vaccines (March 31, 2021) (stating that “[b]illions of people have been safely vaccinated against COVID-19,” that “mRNA vaccines [for COVID-19] have been rigorously assessed for safety, and clinical trials have shown that they provide a long-lasting immune response”).
The paragraph above should enter the historical record… somewhere. That will NOT age well. The only thing more absurd to contemplate is whether they know they are lying in their letter or if they are simply referencing propaganda that they themselves swallowed whole? In a way, the former might be more acceptable to me at this point.
Their opinion on how I got ivermectin wrong was similarly brazen – they ignored all the meta-analyses (historically considered the strongest form of data, a fact they seem to have willfully avoided) in favor of listing a handful of trials where ivermectin was supposedly found ineffective, relying mostly on citing “the Big 6” (what I named the chapter describing the fraud behind the 6 largest, Pharma-conflicted and most publicized trials on ivermectin). This was 100% unsurprising.
Check it out:
First, the CCC concluded that your statements about the safety and efficacy of ivermectin and hydroxychloroquine as treatments for COVID-19 are false and inaccurate because they are not supported by factual, scientifically grounded, and consensus driven scientific evidence (there it is again).
Susanna Naggie, M.D., M.H.S., et al., “Effect of Ivermectin vs Placebo on Time to Sustained Recovery in Outpatients With Mild to Moderate COVID-19,” 328 JAMA 1721 (2022), https://www.nejm.org/doi/full/10.1056/nejmoa2115869 (finding in a double-blind, randomized, placebo-controlled study with 1,800 participants that “[a]mong outpatients with mild to moderate COVID-19, treatment with ivermectin, compared with placebo, did not significantly improve time to recovery,” and that “[t]hese findings do not support the use of ivermectin in patients with mild to moderate COVID-19”);
I laughed out loud when they led their argument with the Naggie trial funded by the NIH as it contained the most brazen fraud of the Big 6 Pharma Ivermectin trials. All you need to know about the trial is that they moved the primary comparison endpoint of the trial.. in the middle of the trial. They moved the main comparison from symptoms at Day 14 to Day 28. Note that changing endpoints in the middle of a trial is a supposed never event. Except the same trick was pulled in the Remdesivir trial.
Anyway, in a presentation by Naggie, in this secondary endpoint, you can see that ivermectin was superior at Day 14 to a high degree of Bayesian “statistical significance” but the “statistical significance” was not reached at Day 28 (I use quotes around statistical significance because it is an erroneous concept when doing Bayesian statistics but that is what they did anyway when they pre-specified a threshold of above 0.95 as “significant”). Can anyone tell me why they moved the endpoint to Day 28 in the middle of the trial:
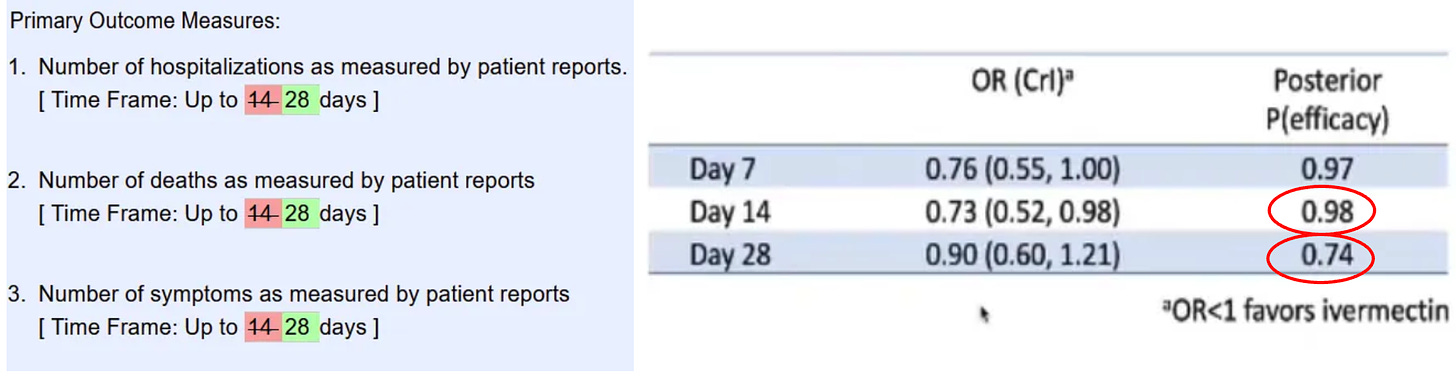
With this brazen maneuver (and many others) it allowed Naggie et al to publish this conclusion: “these findings do not support the use of ivermectin in patients with mild to moderate COVID-19.” Not-so-fun fact: Naggie also sat on the NIH covid treatment guidelines committee where she voted to not recommend ivermectin right before she and her University received tens of millions.. to study ivermectin in Covid. You want more? She also owns stock in a competitor to ivermectin (monoclonal antibodies for Omicron) and has received money from numerous other Big Pharma companies including Gilead. Lets get back to the letter…
Rather, the CCC seeks to accomplish precisely what you assert ABIM should be doing: seeking to “further the professional integrity of medicine by encouraging evidence-based debate” (emphasis added).
Indeed, as set forth in ABIM’s False or Inaccurate Medical Information policy, physicians have an ethical and professional responsibility to provide factual, scientifically grounded, and consensus driven scientific evidence (there it is again). As discussed above, by touting the effectiveness of ivermectin and hydroxychloroquine as COVID-19 treatments and casting doubt on the efficacy and safety of COVID-19 vaccines with such seemingly authoritative statements, you have made statements that are inimical to ABIM’s ethics and professionalism standards for board certification.
In light of all the evidence and circumstances, the CCC determined to recommend that your board certification be revoked.
There is only one silver lining here. One – the impending loss of my certifications does not affect me materially because I have a private fee-based practice due to my need for complete autonomy and lack of restrictions in empirically treating the vaccine injured with various repurposed and alternative therapeutics. I thus cannot and will not accept insurance, and secondly, my academic career is over – no longer will I ever enter back into the system of medicine.
About the only opportunity this whole attack has created is one where I get to defend myself on appeal in a debate with three academic white coats of their choosing. Bring. It. On.
Although the outcome of the debate is assuredly pre-determined, I know it will satisfy a deep yearning many of us dissidents have had for going on 3 years now – to debate someone, anyone, anywhere. Crush them with data. Make ‘em look silly although I will be the only one who knows it happened. It will let me vent my disgust at how they have widely disseminated corrupted scientific evidence and policies while simultaneously ignoring the clinical observations and expertise of frontline doctors who have treated thousands of actual Covid patients.
I will then toss in a little lecture about how RCT’s have long ceased to be a credible means of proving anything in science given that in modern medicine only “Big RCT’s” count and that all “Big RCT’s” require such massive funding that the bias of the funders outweighs any objectivity such trials can profess to attain. I will also remind them that throughout modern medical history, the findings of RCT’s and retrospective observational trials are identical, yet academia has been taught to systematically ignore observational trials. Reason: only massively funded entities can conduct a “Big RCT” while any committed clinician willing to give up nights and weekends can conduct an observational trial. Pharma cannot allow research to be conducted that they have no control over – so they took over the journals and medical school curriculums which now literally teach that observational controlled trials can only be considered “hypothesis generating” and thus their results should not be acted on. Nonsense.
I will also remind them that they are violating international law and human, civil, and political rights as argued by Meryl Nass in another of her excellent posts regarding her own persecution by her state licensing Board:
International law is on our side. A total of 172 countries are parties to the International Covenant on Civil and Political Rights:
According to the 1948 Universal Declaration of Human Rights, Article 19,
“Everyone has the right to freedom of opinion and expression; this right includes freedom to hold opinions without interference and to seek, receive and impart information and ideas through any media and regardless of frontiers.”
According to the 1966 International Covenant on Civil and Political Rights,
“Everyone shall have the right to freedom of expression; this right shall include freedom to seek, receive and impart information and ideas of all kinds, regardless of frontiers, either orally, in writing or in print, in the form of art, or through any other media of his choice.”
And the Nebraska Attorney General protected doctors and pharmacists in Nebraska from their Boards, explicitly allowing them to prescribe HCQ and IVM. His opinion is a tour de force, which goes into detail about why the CDC, FDA and NIH guidelines are contradictory, unscientific and should not be followed. It should be cited in every case.
I also plan on reminding them that the FDA got its ass handed to them in court last week during a hearing of Paul Marik, Mary Tally Bowden and Robert Apter’s suit against the FDA. From an Epoch Times article on the hearing:
“FDA explicitly recognizes that doctors do have the authority to prescribe ivermectin to treat COVID,” Ashley Cheung Honold, a Department of Justice lawyer representing the FDA, said during oral arguments on Aug. 8 in the U.S. Court of Appeals for the 5th Circuit.
The statements “don’t prohibit doctors from prescribing ivermectin to treat COVID or for any other purpose” Ms. Honold said.
“FDA is clearly acknowledging that doctors have the authority to prescribe human ivermectin to treat COVID. So they are not interfering with the authority of doctors to prescribe drugs or to practice medicine,” she said.
So, if the FDA recognizes we have the authority to prescribe ivermectin, then assuredly we are allowed to have the opinion that it is a valid therapy. However, the ABIM will not allow an ABIM certified physician to publicly express this opinion or recommend this practice. Maybe the ABIM should have a little chat with the FDA?
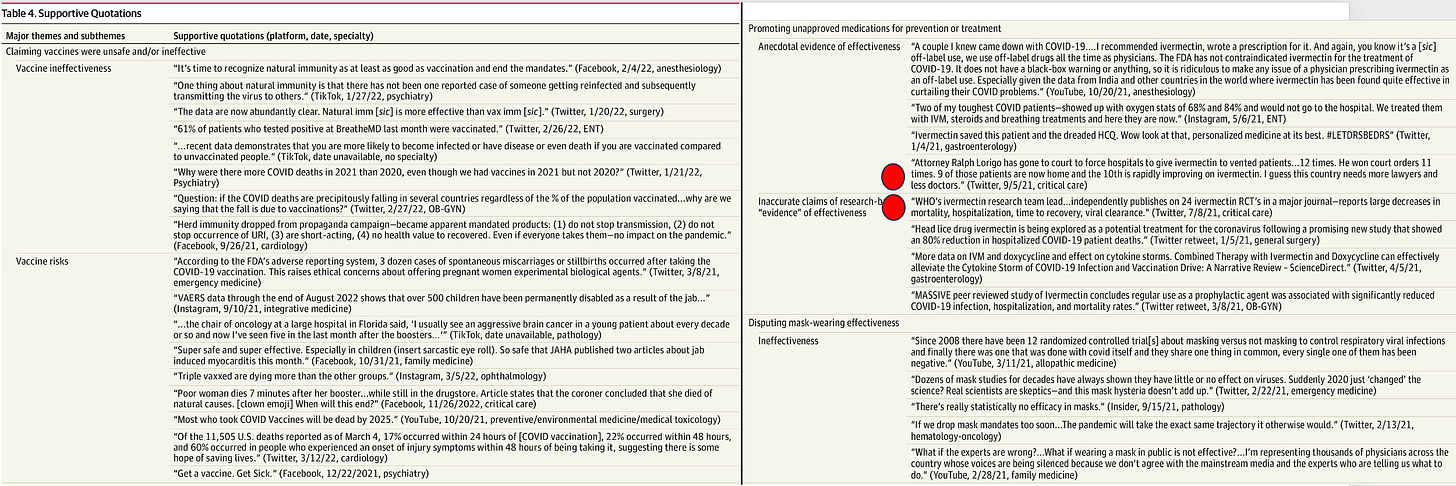
The nonsense doesn’t end with the ABIM, as they are only one prong of this campaign. How is this for some comic relief, published last week in one of the top journals in the world where they found that almost all the Covid misinformation in the U.S on social media can be traced to 52 doctors.

I was honored to discover that yours truly made the list! In their quoted examples of misinformation in Table 4, I have taken the liberty of owning up to the posts attributed to me, all of which I stand by to this day:

I think I will finish with this excerpt from a recent Wall Street Journal op-ed touching on the Missouri vs. Biden case where the administration is being sued for its systematic censoring of U.S citizens on social media by every intelligence and health agency in our Federal government :
This is where the decision of U.S. District Judge Terry Doughty sheds light. His detailed recounting shows a Washington energetic in protecting Americans from Covid opinions, expertise and claims that conflicted with its own, at a time when it served politicians to show they were trying to save Americans from encountering a virus that couldn’t be avoided. When government has a message to deliver, especially when the political stakes are high, it won’t be content just to push its own message, it will try to silence others. Fighting back will always be necessary. The only surprise in our age is how thoroughly the “liberal” position has become the pro-censorship position (that last line is a doozy).
Son Alleges Texas Hospital’s COVID Treatment Plan Killed Unvaccinated Father
By Michael Nevradakis, Ph.D. | The Defender | August 21, 2023
For decades, Constantine “Gus” Kotsanis was a respected otolaryngologist in Grapevine, Texas. Having emigrated from Greece at age 15, Constantine became a University of Texas-Southwestern medical professor, a cancer and autism researcher and founder of the Kotsanis Institute of Functional Medicine.
In an interview with The Defender, Constantine’s son, Andy Kotsanis, said that in the 1980s, his father helped transform what was previously the Grapevine Medical Center into the Baylor Scott & White Medical Center — Grapevine, affiliated with Baylor University. It is now the largest not-for-profit health system in Texas.
It was in that same hospital, that on March 14, 2021, Constantine “violently lost his life,” his son said — days after being admitted with respiratory problems and a subsequent COVID-19 diagnosis.
Andy said he believes his father’s death resulted from the treatment he received, including remdesivir, fentanyl and other drugs Constantine and his family had not authorized.
Andy also alleges he was “threatened and assaulted by the police and the hospital administrator” as his father was dying, and barred from the room as his father passed away.
Today, Andy is raising awareness about his father’s death — and the stories of others who endured similar treatment — through his own activism and as a social media outreach coordinator for the FormerFedsGroup Freedom Foundation.
Andy discussed his family’s experience around his father’s hospitalization and subsequent death at Baylor Scott & White, and the activism he is now involved in as a result. He shared extensive documentation and photos with The Defender to corroborate his story.
Hospital president to victim’s family: ‘I’m not letting you see him’
Andy told The Defender that he was the very first baby born at Baylor Scott & White’s then-new outpatient operating room. Just days earlier, his father “was the first physician to do a procedure in that operating room,” he said. “So, there’s a very long history with my father and Baylor.”
“This is a story of tragedy, but also betrayal, because he helped build that place,” Andy said.
According to Andy, his father was not vaccinated for COVID-19. “He was not a fan of it,” he said. He said he now believes his father’s vaccination status may have played a crucial role in the treatment he received in the hospital.
After hearing about Gail Seiler’s story, Andy said, “Maybe they played that same game with him and did not tell the truth completely to us,” he said.
Andy said his father spent “a little over six days” in the hospital. He was admitted when “he had a hard time breathing. … He was really struggling, [in] a great state of hypoxia, almost to the point where he was exhausted with breathing.”
At the hospital, his father tested positive for COVID-19 and was admitted. According to Andy, the pulmonologist assigned to his father, Dr. Jagadeshwar Gummi Reddy, administered four rounds of remdesivir daily.
“At first, my father was calling me, saying ‘I feel a little bit better, everything’s fine,’” Andy said. “Then things started to go downhill very quickly. … I didn’t understand at the time what remdesivir was, how powerful it was and what it did to people or how deadly it was.”
A few days later, another phone call came from the hospital, this time from nurse Sarah Grice, who told Andy’s mother, “I had to put your husband in restraints, because he was confused about why he had tubes in his lungs.”
After his father’s death, Andy discovered that hospital medical records claimed no restraints were used.
“At the time, I didn’t know that there’s a formula that they follow: They sedate you and they’ll put you in restraints if they have to put remdesivir in you,” Andy said. “We requested to speak to the hospital administrator, Chris York, president of Baylor Grapevine at the time.”
According to Andy, York “arrogantly” told them, “‘I don’t care who your dad was or who your husband was, I’m not letting you see him.’ I said, ‘I think this is criminal. You’re not letting me see my dad. I don’t know what’s going on. Please let me see my father.’”
But York told them, “If you think it’s a crime, call the police,” according to Andy, who said, “I’ll never forget that sentence for the rest of my life.”
Nurse ‘started performing the most violent chest compressions I’ve ever seen’
Grice called the family again, telling Andy’s mother, “Your husband said he wants to die and be put on a ventilator.” This sounded nothing like my dad, Andy said, “because all over his chart, it says he didn’t want to be intubated. No ventilator, no remdesivir.”
“So how do you go from ‘No, I don’t want to be on a ventilator’ to ‘I want to die, put me on the ventilator’ in a matter of less than six days?” Andy asked.
On what turned out to be the day before his father’s death, Andy, his mother and their attorney “barged in the front door … demanding to see my father,” Andy said. “We were ready to press charges if they didn’t let us in.”
Subsequently, York “made the decision to only let my mother in,” Andy said, while Reddy spoke to him in person. According to Andy, this discussion was peculiar.
“He came downstairs with his mask off, with his hands shaking like he was scared, like someone was after him,” Andy said. “He introduced himself [and said] ‘My hands are tied. There’s nothing I can do.’ I said, ‘That’s not a good answer, sir,’ and he just walked away. It was almost like he was being bullied.”
Reluctantly, Andy’s mother approved the use of the ventilator that day, Andy said. But at 5 a.m. the next morning, the hospital called to say his dad was coding.
Again, only one family member was allowed into Andy’s father’s hospital room, so the family decided to let Katerina, his sister, be that person.
Expecting “some humane treatment,” Andy said they were instead met at the front door by Donna, an older nurse, and Demorrius Jones, a policeman, who “arrogantly greeted us in a very rude way.”
According to Andy, they got York on the phone, who said, “No one can go into the room. You have to watch him die through the glass.”
Andy told The Defender that, through the glass, they saw nurse practitioner Rommel Villas Lantajo handing a syringe to Grice, who then injected Constantine.
“Before she injected him, I saw the heart monitor,” Andy said. “He had a pulse of 122. So, I’m thinking to myself ‘Why is he coding? He has a heartbeat.’”
After the injection, “his pulse started to drop rapidly, and she [the nurse] started to do the most violent chest compressions I’ve ever seen,” Andy said.
“His body was bouncing 10 inches off the table. It was like watching someone get chainsawed in half. It was very violent and brutal, and looked more like she was trying to kill him, not save his life,” Andy said.
Andy said his father’s health was “already compromised with all those drugs they gave him” in the preceding day, which included fentanyl, adding that “he was still on the ventilator when she [Grice] was doing what she was doing.”
Grice subsequently stopped administering chest compressions and, according to Andy’s mother, “turned off all the machines.” Immediately following this, “My dad lifted his chest off the table, and then he had a seizure and died in front of my mother” while she was screaming “Stop, stop, stop!”
Andy was not present as his father died, though, because the police officer had “forced me out of the ICU. He threatened to arrest me if I didn’t leave the hospital immediately.”
Father’s death ‘malicious and arbitrary’
“They did this to a very kind, gentle soul,” Andy said, adding that his father’s death was “malicious and arbitrary, on behalf of Chris York, the administrator.”
“I’m still in shock,” Andy said, telling The Defender :
“The aftermath was so bad. I’m still in therapy over it. I’m very sad. I can’t put into words what a panic attack is like. I didn’t have irritable bowel syndrome until my dad died. You only get that when you experience something traumatic. Some people consider that a form of PTSD [post-traumatic stress disorder].”
“I’ve had several panic attacks,” Andy added. “I’ve lost count.” He said he’s “almost had to institutionalize” his mom. “I put my whole life on hold and I’m still, to this day, at her aid, trying to help her. She’s still not the same,” he said.
Andy also noted the anomaly of an extraordinary number of pages — many of them duplicates — in his father’s medical charts. “You’re in the hospital for six days but the chart is 948 pages long?” he asked. Another anomalous document dealt with “permission to be filmed,” he said, calling it “a very suspicious document.”
‘This is a huge cover-up’
His father’s experience led Andy to become an activist, he said.
“I’m trying to promote my story on my website and to inform everyone, the whole planet, that we’re witnessing the collapse of the healthcare system. … They’re using drugs in hospitals that are clearly not working,” he said. “I’m trying to show people that this is what they did to me. This is what they probably plan to do to you if you’re in there.”
“If that’s how you want to say goodbye to a loved one, go to Baylor Scott & White,” Andy said. “They’ll be more than happy to accommodate you if that’s your desire. That’s how I feel about this organization.”
“Hopefully, in the future, this can be a reference point for people to go, ‘We don’t want to be like Baylor, don’t pull a Baylor, don’t be like Baylor.’ That’s where I’m going with this,” Andy said. “This was so vicious and atrocious. I’ll never forget it.”
Aside from his website, Andy’s activism has included “putting road signs out, [placing] cards on doors,” he said, adding that such acts are “perfectly legal in the state of Texas” due to the Texas Citizens’ Participation Act.
However, just weeks after Andy began these activities, he was warned by local police and a local detective to “be careful” where he placed his signs and cards because his “First Amendment rights are limited.”
Andy said he experienced more difficulty with police when he attempted to press manslaughter charges against Baylor Scott & White. Local police referred him to Baylor Police and the Texas Rangers. When Andy contacted the Rangers, they advised him to “start a paper trail” by calling Baylor Police.
Yet, Baylor Police refused to take a report, telling him to “call our legal department.”
“So, this is a huge cover-up,” Andy told The Defender. “The police are covering up, in my opinion, what I would consider a homicide.”
Andy said his efforts, though, have managed to secure a degree of professional difficulty for York. According to Andy, “He orchestrated this, and now he’s no longer in the state of Texas. For a small while, he was an administrator in Arkansas, but thanks to my efforts informing his new employer, he’s no longer [there].”
In addition to his individual activism, Andy joined the FormerFedsGroup Freedom Foundation, which advocates on behalf of victims of COVID-19 hospital protocols and others with similar experiences. He described them as “the best group you can find if you’re a victim.”
“We’re on a mission,” Andy said. “We’re here to help as many people get as many stories out there and turn the narrative around.”
Many people have reached out to him through the FormerFeds Group but also through his own website, said Andy, describing similar treatment that they or loved ones experienced at hospitals, including at Baylor Scott & White.
Referring to the COVID-19-related hospital protocol prescribed by the Centers for Disease Control and Prevention, Andy said he is not certain if it was followed by Baylor Scott & White in his father’s case. But he noted that his and other victims’ experience make it sound like “there’s a formula they’re following.”
Andy said these efforts are important to everyone, even if they haven’t been victims of COVID-19 hospital protocols or similar treatment.
“We all get old and will need a little extra attention,” he said. “The question is, what kind of attention is that going to be? I’m hoping it’s going to be a real standard of care.”
Andy shared some words of advice for individuals who have had similar experiences or who may end up in the hospital for similar reasons.
“If you can get the chart, get the chart, print the chart. Read it before you do any reporting. Do your own homework,” he said.
He also recommends seeking professional help to grieve. “It’s okay to ask for help.”
“Also, understand that there are people like me out there, a lot of us that are going to, for as long as we’re alive, try to turn this thing around,” he added. “Don’t give up because you feel like you’re going nowhere. I have felt that way many times. … Believe in yourself. Don’t give up. Be persistent.”
Michael Nevradakis, Ph.D., based in Athens, Greece, is a senior reporter for The Defender and part of the rotation of hosts for CHD.TV’s “Good Morning CHD.”
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Hurricane Katrina and the “Angels of Mercy”
Ethical boundaries in medical decision-making
By Jonathan Engler and Jessica Hockett | HART | August 21, 2023
The debate as to how much “pandemic” harm was caused not by a virus, but rather by the dystopian response to the perceived threat of a virus, has been raging for some time now.
Jonathan tweeted about this last year in relation to Lombardy and that thread was turned into this Panda article.
An analysis of the spatial characteristics of deaths during the spring 2020 wave in Northern Italy was carried out by him along with a Panda colleague; this suggested that it looked nothing like a spreading virus, and more like the sudden imposition of a policy response.
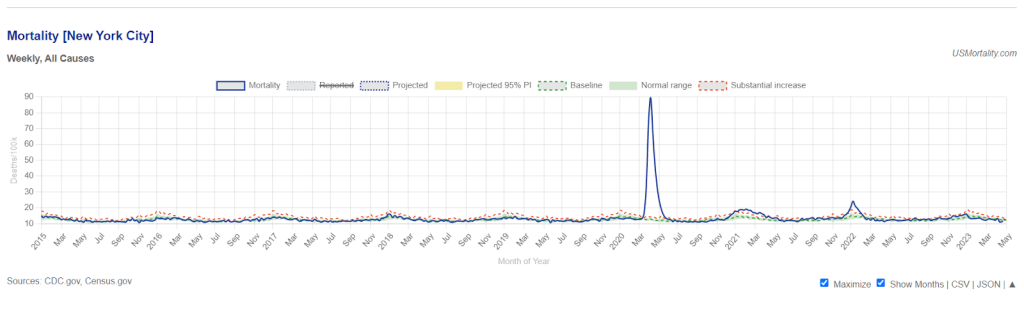
More recently, Jessica has essentially come to the same conclusions about New York: that something terrifyingly unnatural appears to have happened, which cannot be explained by the sudden spread of a deadly virus.
It surely does not require any scientific understanding whatsoever to glance at the below graph of total mortality rate in NYC going back to 2015 and see that what happened in a few weeks during spring 2020 suggests an abrupt episode of ferocious lethality which was at odds not only with anything observed anywhere at the time or thereafter, but also with even the highest estimates of the infection fatality rate alleged to have caused “the pandemic”.
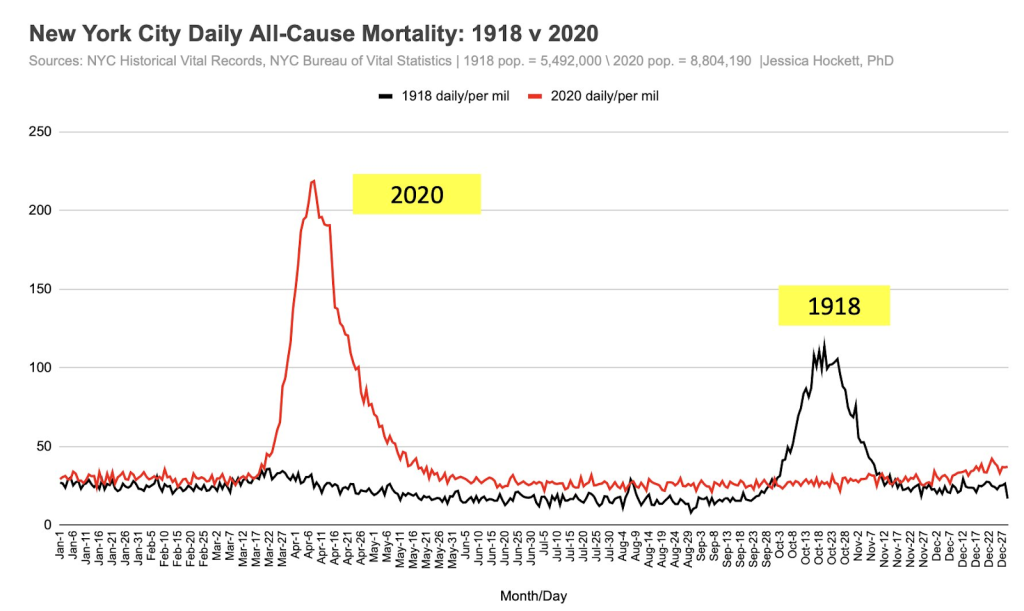
If we look back even further, it can be seen that the reported spring 2020 mortality spike in New York is actually around double that observed in the autumn of the 1918 pandemic. But other places in 2020 did not see waves of deaths anywhere near those observed during the 1918 pandemic.
Moreover, unlike elsewhere, the increase in deaths was seen across a younger demographic, not exclusively in the elderly.
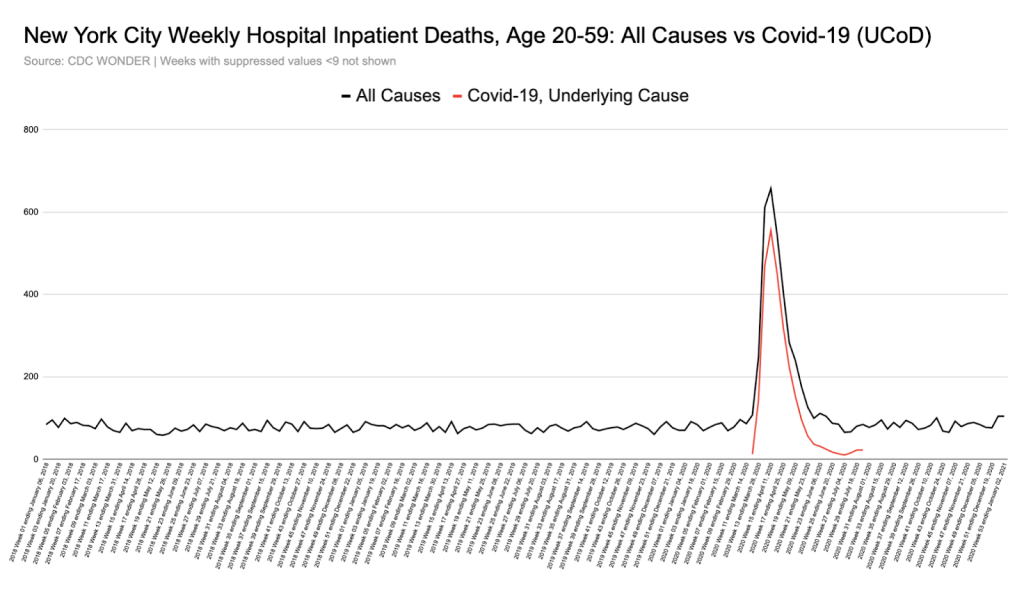
As shown in the graph below, all-cause hospital inpatient weekly death counts in the 20-59 age group were dramatically elevated for a short period, by a shocking 6-fold at their peak, with nearly all these deaths being coded as ‘covid’.
In fact, in New York, the % increase in all-cause deaths during the spring “1st wave” period was the same in the 20-69 year old age group as in the 70s and over:
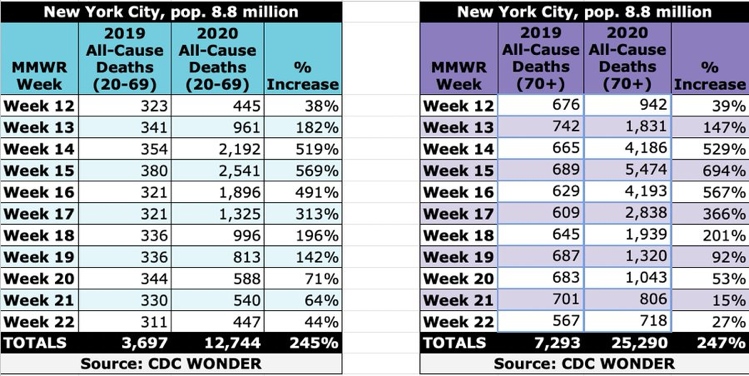
In other places, however, what we were told was the same disease caused by the same virus left the younger age groups largely untouched, with nearly all deaths being in the elderly.
This discrepancy remains completely unexplained. It seems unarguable that certain difficult questions certainly need asking about what happened in New York in 2020 if we are to unravel the truth about what happened there.
Of course, the narratives emerging from Northern Italy and New York in 2020 were instrumental in driving fear and hysteria worldwide. Moreover, the number of deaths in both places informed early estimates of the IFR. These inciting incidents directly sparked much of the worldwide exaggerated, fear-driven response to what we now know was (if anything) a virus mainly affecting the frail and elderly, to which most people already had sufficient immunity to prevent severe illness.
For these reasons, it is essential that particular attention is paid to try to ascertain precisely what happened in these specific places.
It’s worth detailing – as evidence for the deeply dystopian mindset operating at the time – just some of the many deviations from normality that adversely affected human health and immunity, or which constituted sudden changes to healthcare practice.
These included (but were not limited to):
- Stress and anxiety from confinement (being told to stay home) and fear propaganda
- Discouragement to attend hospitals if ill
- Reduced community prescribing of broad-spectrum antibiotics
- Low staff levels in healthcare settings due to self-isolation of those “testing positive,” even with no symptoms
- Isolating the elderly
- Barring loved ones from hospital and care homes
- Fear (on the part of HCWs) of tending to covid positive patients, compromising basic medical and care needs.
- Early and inappropriate invasive ventilation
- Overuse of midazolam and opiates
Inevitably, and rightly, some researchers have started to perform post-pandemic autopsies analysing the motives and reasoning used to justify policies and other changes in behaviour and to examine their real world consequences.
Some medical practitioners have taken umbrage at any suggestion that the stressful environment and sudden expectations and pressures laid upon them may have resulted in well-meaning medical staff crossing ethical lines, or violating the Hippocratic Oath.
Those who wish to point out that there is historical precedent for medical staff behaving diabolically while thinking they are doing good often invoke atrocities during the 1930s and 1940s (and receive opprobrium as a result).
However, there is a much more recent example, and one which we were oblivious to until recently, despite this incident being totally “out in the open”, the subject of a lengthy investigative article, book, and a TV mini-series: the post Hurricane Katrina incident at Memorial Hospital Center in New Orleans in 2006.
Wikipedia provides the basic facts:
In the hurricane aftermath, the basement of Memorial Hospital Center flooded, power failed, and battery power for essential equipment started to run out. Most, but not all, patients were successfully evacuated.
The hurricane occurred on 29th August. A shocking finding was made in the aftermath, as described in the Wikipedia article:
On September 11, mortuary workers recovered 45 bodies from the hospital. Toxicology tests were performed on 41 bodies, and 23 tested positive for one or both of morphine and the fast-acting sedative midazolam [branded as Versed in the US], although few of these patients had been prescribed morphine for pain.
In the following weeks, it was reported that staff had discussed euthanizing patients. Some reports went further; Bryant King, an internist at Memorial, told CNN that he believed “the discussion of euthanasia was more than talk.”
LifeCare told the state Attorney General’s office that nine of their patients might “have been given lethal doses of medicines by a Memorial doctor and nurses.”
King publicly charged that one or more healthcare workers had killed patients, based on conversations with other health care workers. King told CNN that when he believed a doctor was about to kill patients, he boarded a boat and left the hospital. King explained his actions in terms of his opposition to Pou’s alleged actions, arguing “I’d rather be considered a person who abandoned patients than someone who aided in eliminating patients.”
Following an investigation into the deaths described above, the local DA (“District Attorney”) decided there was sufficient evidence to charge three medical staff with four counts of second-degree murder. Charges against two were later dropped in exchange for testimony.
The prosecution was deeply unpopular. Despite substantial evidence of deliberate actions taken to terminate lives – indeed, enough to satisfy the legal definition for homicide – many members of the public felt medical staff were simply “doing their best” under very trying circumstances. According to a local reporter the incident “ignited a furious debate in New Orleans and elsewhere about whether sharp ethical boundaries can be drawn around decisions on patient comfort made in a crisis.”
The DA failed to win re-election, and when the new DA convened a Grand Jury* at an undisclosed location, much of the previously amassed evidence was not presented and some of the key witnesses not called. The Grand Jury decided that charges should be dropped.
Unsurprisingly, several commentators (e.g., Loyola University Law Professor Dane Ciolono) opined that the Grand Jury was convened and run in such a way as to ensure charges would be dropped while providing “cover” for such an outcome.
Whatever actually occurred at Memorial Hospital, or whatever the staff’s motives, the incident speaks to an unsettling, yet undeniable truth: during a crisis, “ethical red lines” – however deeply held and valued – may be easily crossed. Society may judge those decisions acceptable or understandable, as appears to have happened with the Memorial Hospital case.
In summary, it would appear that the legal process was manipulated to assure an outcome which accorded with public opinion – that is to say to extinguish the possibility of prosecution while maintaining the pretence of due legal process. In this way, facing up to the stark reality – that as a society we mete out justice arbitrarily when we wish to – was avoided. Perhaps the well-ordered rules-based system suggested by statutory definitions of what actions constitute crimes, is to some extent just “for show”.
The Memorial Hospital case obliterates – with a relatively recent example – the notion that doctors and nurses all have the same ethical boundaries which they simply will not cross under any circumstances.
Could such boundaries have been crossed during the recent covid event?
A number of commentators are considering the possibility that changes in the policies and practices around the use of certain drugs (midazolam and opiates), and procedures (invasive ventilation) – sometimes in combination – may have contributed to the high mortality reported, at least in some specific places.
In relation to drugs, in an article published on his Substack last year, the blogger known as Bartram’s Folly explored the possibility that (in the UK) sheer fear and panic may well have driven medical staff to use midazolam and opiates more liberally in patients with covid, which may have encompassed anyone with a positive covid test.
In the UK one such mechanism which may have encouraged this measure is the NICE Guideline NG163 (no longer on their website but available here or as PDF download here), about which others have also written in detail. This guideline effectively transposed the advice for treating end-stage cancer patients with midazolam and opiates into that for covid patients. More detail on this here.
Of the guideline, Bartram said,
“… the NICE guidelines appear to have introduced a pathway for doctors which allowed for (perhaps even encouraged) more than a gentle nudge for those who were ill with Covid towards death, some of whom might well have survived given the chance. This iatrogenesis hypothesis would mean that at least some of the deaths recorded as with Covid might well have been a direct result of the care guidelines as set out by NICE.“
Later, Bartram makes the point that the pretext of a crisis situation or emergency may establish the grounds for ethical boundaries to be crossed or disregarded, at least temporarily, under the auspices of ignorance or ‘doing one’s best’ with the information said to be known or available at the time:
It is important to note that in the iatrogenesis hypothesis it isn’t necessary for some people to have had an evil intent – it is entirely possible that individuals promoted and exercised a policy that resulted in needless deaths while believing that they were ‘doing the right thing’ (e.g., see Hannah Arendt’s concept of the banality of evil).
In particular, ‘petty bureaucrats’ appear to be readily able to think up policies without seeing the need to consider the full consequences, and when these consequences are eventually revealed will usually point to the minutes from endless meetings with other petty bureaucrats to show that they weren’t personally responsible for the policy and they were simply following process.
Of course, once a framework had been decided front-line staff might have been grateful for the guidance offered given the challenging times, at least until the negative consequences of the guidance became painfully clear.
It should also be remembered that – in the US at least – certain extraordinary policy measures may have been important factors. For example, during the emergency NYC Governor Cuomo issued executive orders and suspended laws which gave doctors and nurses immunity and absolved hospitals of the responsibility to keep close patient records. (The order itself can be found here, and some legal commentary on it here.) Articles in JAMA can be interpreted as giving ethical permission for physicians to issue unilateral DNR orders, avoid CPR, and ration ventilators and critical care beds.
Moreover there are numerous examples of doctors, nurses and others in the US who later said they were following guidance, learning as they went. (See this interesting essay by Dr Kory, for example.) Under these circumstances it is easy to see how they could assume that something which ordinarily might have been questionable would become acceptable as “everyone else was doing it”.
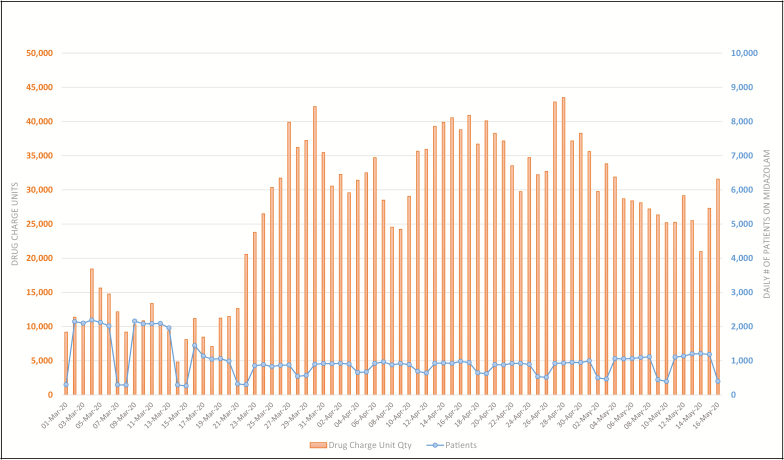
Evidence of increased midazolam use can be seen in the US as well as in the UK. This graph from a study describing the use of 7 specific drugs in 47 hospitals in NY shows the daily count of patients (blue) who received midazolam and the disproportionate quantities used (orange) between March 1 and May 16, 2020.
Moreover, midazolam is currently listed by the FDA to have been in short supply since 2 April 2020:

This Guardian article from 13 April 2020 reports on a letter sent by “a group of prominent medical practitioners and experts” to capital punishment states imploring them to:
“release their stocks of essential sedatives and paralytics that they hoard for executions” so that they can be “used for intubations and mechanical ventilation of the most severely ill coronavirus patients who cannot breathe for themselves”.
The tone of this letter can be taken to illustrate the sense of sheer panic prevailing at the time – certainly not conducive to rational decision-making – combined with the assumption that invasive ventilation was going to be extensively required and used.
This takes us to the question of invasive ventilation, whether it might have been used too often, inappropriately, and why.
As well as panic, the role of fear on the part of healthcare workers cannot be underestimated. Here is Dr Vinay Prasad stating that:
“It is a unique situation in medicine. In our whole medical career, doctors have never been personally afraid the way they were [with covid].”
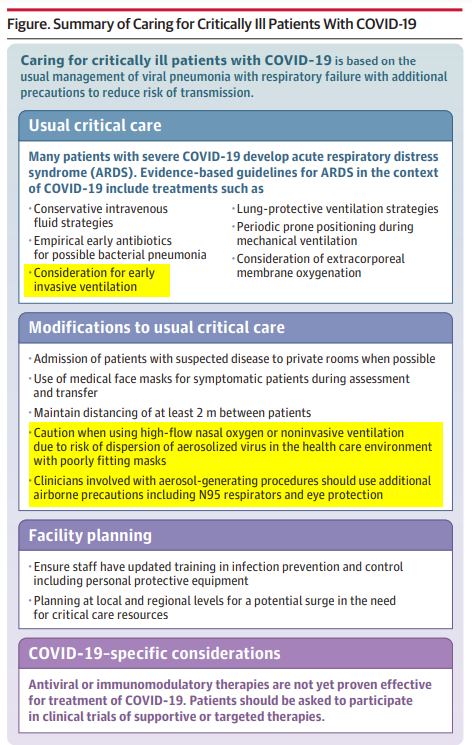
Official guidance (see for example this from a British anaesthetists’ professional association) certainly reinforced the idea that one of the benefits of early intubation was to reduce the aerosolization of virus, such that it would be safer for those caring for the patients, compared to when non-invasive forms of ventilation were used.
This JAMA Clinical Update “Care for Critically Ill Patients With COVID-19” published on 11 March 2020 strongly supports the idea that the thinking was very much that non-invasive oxygen augmentation could be dangerous for healthcare workers:
The journalist Alex Berenson was early to point out that ventilator shortage may have more to do with overuse “to protect staff” than to being overwhelmed by patients in respiratory failure.
It seems like fear may well have been augmented by official guidance to result in significant overuse of this measure.
It is important to understand the differences between the Memorial Hospital incident and what may have happened in the early stages of the covid crisis. In New Orleans, it may indeed have been reasonable to assume that it was going to be impossible to evacuate the patients (who were given midazolam and opiates to ease suffering) in time, and that they were indeed unsaveable due to the extraordinary circumstances. (Whether or not this was actually the case will probably never be known, because of the legal shenanigans described above.)
However, whether that applies to all, some, or just a few of those who died in spring 2020 after being administered the same or other drugs (or placed on mechanical ventilators or issued a unilateral DNR, etc.) is still a matter of debate whereas for sure, Hurricane Katrina was self-evidently an extreme weather event that created devastation and emergency conditions in its fury and wake.
Certainly, it seems clear that personal fear and a belief in the lethality of this infection drove much medical decision-making in the early days. It is not hard to imagine actions being taken which were then rationalised by imagining the suffering that had been prevented, limited resources preserved, and many lives saved. The deaths witnessed could easily have acted as positive reinforcement in the minds of healthcare workers as to how serious the illness was. These protocols could lead to the deaths of patients who were not particularly old and frail and thus reinforce the message that the virus was potentially fatal even in such people
The decisions that healthcare workers made, and the influences on and factors involved in those decisions, will be discussed and dissected for decades to come. When humanity is ready to confront what occurred – and admit that ethical inversions in hospitals and care homes contributed to unintentional iatrogenic death, we can move toward keeping it from happening again.
* (A Grand Jury in the US is a specific type of court empowered by law to determine whether probable cause exists to support criminal charges for a suspect in a crime. Louisiana – in which New Orleans is situated – is one of 23 US states that use grand juries for indictments in serious crimes.)
Eris vaccine marketing hits Germany, complete with panic about a nonexistent August “Covid wave”
eugyppius: a plague chronicle | August 20, 2023
We will not be free of the virus until we are free of the vaccinators.
The leftist taz newspaper on 17 August: New German Wave: The new Covid variant Eris has arrived in Germany. Concerns about a new wave are growing – but the country is not well prepared.
The pandemic is over, but the virus is still dangerous: Reports of the new variant EG.5.1. seem to confirm this analysis. EG.5.1. (Eris) has been considered a “variant of interest” since 9 August. According to the WHO, the phenotype does not differ fundamentally from other Omicron lineages and does not require special public health measures …
With the announced end of the pandemic, virtually all mandated protective measures have been lifted in Germany. The most important instrument in the fight against Covid-19 is thus the immunisation of the population through infection or vaccination.
Das Erste, state media, on 19 August: Covid Variant “Eris”: How Dangerous is the New Mutation EG.5?
The World Health Organisation WHO has upgraded the new Covid mutationEG.5. This variant, called “Eris,” now belongs to the “variants of interest.” …
As WHO Covid expert Maria Van Kerkhove explained in Geneva on Wednesday, more severe outcomes have not been observed with Eris, but vaccination confers less protection than with other virus variants. …
Even though the new variant is unlikely to cause severe disease, the [German vaccine regulatory authority] STIKO still recommends getting vaccinated – above all to avoid possible long-term consequences of SARS-CoV-2 infection and to protect employees in medical and nursing care.
n-tv, a subsidiary broadcaster of RTL, on 18 August: The Number of Coivd-19-Cases Continues to Rise.
The pharmaceutical company Moderna has announced that its updated Covid vaccine according to an initial study is effective against the Eris sub-variant. The company now expects to launch the new vaccine in time for the autumn vaccination season. Approval from vaccine regulators however is still pending.
Moderna, like vaccine manufacturers Novavax and Pfizer, has developed versions of its vaccines with Biontech SE that target Eris subvariants. Shortly before, the pharmaceutical company Pfizer had reported that its revised vaccine had been effective against Eris in a study with mice. …
Most recently, it was suspected that the cinema hype surrounding the feel-good film “Barbie” and the gloomy biopic “Oppenheimer” may have caused many infections. At the same time, the Robert Koch Institute (RKI) recorded an increase in the number of reported Covid infections. Experts, however, see no reason for concern so far.
Frankfurter Rundschau, a regional Frankfurt paper, on 17 August: Covid comeback with “Eris”: First experts demand return to masking.
Is Covid on the attack again? There are indications that the virus is once on the rise once more. …
British doctors are already calling for a return to masking. [Relentless virus charlatan and deranged hypermasker] Trisha Greenhalgh suggests that, “in view of the spread of new variants,” masking in high-risk situations should be considered.
The [virus surveillance] of the Federal Ministry of Health shows that the numbers are also on the rise in Germany. … “Eris” is already responsible for every fourth corona infection, according to new figures from the RKI. “The number of Covid-19 cases reported to the RKI .. seems to be related to the increasing circulation of this ‘variant of interest’,” the Robert Koch Institute says.
The increase in the case numbers – at least in Great Britain – coincides with the opening of the blockbusters “Barbie” and “Oppenheimer” in British cinemas, which has given rise to talk of the “Barbenheimer” phenomenon. It is well known that larger crowds in enclosed indoor spaces are associated with an increased risk of corona infection. So is it time for a mask renaissance?
In the USA, more and more voices calling for one. [Relentless virus pest] Eric Feigl-Ding … used the hashtag #MaskUp on Twitter to call once again for protecting oneself from Covid infections with masks. Health Minister Karl Lauterbach shared the post, warning that the latest Covid data from New York is “worrying.” …
“There is still a risk that a more dangerous variant will emerge, which could lead to a sudden increase in cases and deaths,” emphasises WHO Director-General Tedros Adhanom Ghebreyesus. Not only adapted vaccines that take the new variants into account, but also wearing a mask would then help to protect oneself and others, Frankfurt virologist Martin Stürmer told Spiegel.
tagesschau, state media, on 17 August: Covid Case Numbers are Rising Again.
The number of laboratory-confirmed Corona cases in Germany is rising again – but at a relatively low level. This development has been ongoing for around a month, reports the Influenza Working Group at the Robert Koch Institute (RKI) … According to the report, about 2,400 confirmed cases of Covid-19 were reported nationwide last week. This is more than double the number reported in the week ending 9 July, when there were about 1,000. …
According to the RKI report, the activity of acute respiratory diseases in general in the population was “at a low summer level.” … “Anyone with symptoms of an acute respiratory infection should stay at home for three to five days and until the symptoms have clearly improved,” advises the RKI. …
Despite all of this obnoxious verbiage, absolutely nothing of virological note is happening in Germany. Official Covid testing has been all but abolished here, forcing our journaloids to unearth statistics from RKI influenza surveillance – something they refused to do during the pandemic itself, because the flu people routinely posted data that undermined their panic narrative. Here, I’ve circled in red the scary rise in infections from the latest RKI report that we’re meant to be worried about:
This microscopic uptick is dwarfed by the February/March wave that peaked between weeks 8 and 13. Our media luminaries took next to no notice of this frightening late-winter surge, and as I type this, Covid diagnoses have not even re-achieved their June levels. The difference between the state of things now and the state of things in February is not the unremarkable Eris variant. XBB was also debuting across Europe early this year, driving the post-February case peak, and nobody cared. The only thing that is different now, is the proximity of the autumnal vaccination liturgy and the prospect of new, updated vaccines from Pfizer/BioNTech, Moderna and Novavax. That is why we are hearing about variants and masks and Long Covid all over again. It is also why many of these articles contain buried within them somewhere the advice to line up for the shiny new anti-Covid juice this Fall. This whole thing is, very plainly, a psy-op, if a very low-effort one.
There are several patterns in the German reporting that are worth noting. First of all, the latest hysteria was unleashed on 17 August, prompted by a report on Eris from the German news agency Deutsche Presse-Agentur. Particularly in the realm of routine reporting, the news agencies are a powerful coordinating force, and their influence here means that the full media panic machine is not engaged. We’re looking instead at pieces thrown together by low-level staff desperate to fill column inches. Second, all the German stories are firmly downstream from Anglophone sources, going so far as to recycle from British tabloids the improbable theory of a “Barbenheimer” wave (it is painful even to type this stupid word). Third, at least German health authorities – Karl Lauterbach excepted – resolutely refuse to provide virus doom quotes. Thus the Frankfurter Rundschau had to appropriate the tweets of Anglosphere mask hysterics like Greenhalgh and Feigl-Ding to make Eris sound scary.
I know there are rumours that American authorities are planning to bring back mask mandates and other restrictions in the coming months, and I’ll be honest: We should be so lucky. If the pandemicists try to kick up another round of non-pharmaceutical interventions this fall, they’ll be flirting with self destruction. There are important prerequisites for virus panic: You need a plausibly novel pathogen, the risk of which can be exaggerated. You need a prevailing sense of stability, with nothing else much going on, because the public health interventions themselves have to seem new. Risk, excitement and the prospect of a break from routine are important enticements. That’s all gone now. Covid is not a new scary virus anymore; nearly everyone has had personal experience with it. Solid majorities everywhere have learned to hate lockdowns, despise masking and avoid the mRNA vaccines. The pandemicists need a plausibly new virus to reopen the circus, and they need a lot of people to forget about what a misery the last pandemic response was. They’ll have another chance in ten or fifteen years, I’d guess. Then, it’ll be time to worry.
Critics Slam JAMA Study Claiming 52 U.S. Doctors Spread COVID ‘Misinformation’
By Monica Dutcher | The Defender | August 18, 2023
Critics of a study published this week in JAMA concluding 52 doctors from across the U.S., propagated “COVID-19 misinformation about vaccines, treatments, and masks on large social media and other online platforms” called the study nothing more than “propaganda.”
“Ultimately, misinformation is just a weaponized term meaning nothing,” said Vinay Prasad, M.D., MPH. “People who use it are often completely ignorant of science and truth.
Prasad and others pointed to several flaws in the study, including the researchers’ definition of “misinformation,” the reported percentage of those with post-COVID-19 condition, or “long COVID” and the false claim that the Johnson & Johnson vaccine alone led to deaths — as deaths also have been linked to the Pfizer and Moderna mRNA vaccines.
The CDC as the arbiter of COVID truths
The University of Massachusetts researchers who produced the study defined misinformation as “assertions unsupported by or contradicting U.S. Centers for Disease Control and Prevention [CDC] guidance on COVID-19 prevention and treatment during the period assessed or contradicting the existing state of scientific evidence for any topics not covered by the CDC.”
But in an Aug. 16 Substack article, Prasad — a hematologist-oncologist and professor in the Department of Epidemiology and Biostatistics at the University of California, San Francisco — challenged the notion of using the CDC as the litmus test for pandemic-related information.
CDC “made many errors,” Prasad wrote, citing a paper he published in March, documenting 25 statistical or numerical errors made by the CDC that he said raised questions about the agency’s “real or perceived systematic bias.”
It’s also well documented that the agency constantly changed its mask guidance and published conflicting information about vaccine effectiveness.
Dominique Brossard, professor and chair of Life Sciences Communication at the University of Wisconsin-Madison, who studies medical misinformation, told USA Today, “The guidance kept on changing … Communication around the vaccine was horrible.”
Dr. Jeff Barke, an Orange County, California, primary care physician and founding member of America’s Frontline Doctors, called the CDC “a captured agency,” saying “it makes no sense whatsoever to recommend this toxic product [COVID-19 vaccines] to children.”
The CDC never came out with early treatment guidelines, Barke said. It was always about vaccines and masks. Barke recalled prescribing ivermectin to his patients and the pharmacists not filling it, asking him for the “diagnostic code” in order to proceed.
Barke told The Defender :
“The pharmacy never asks for a diagnostic code if you prescribe OxyContin for a patient. So it’s OK for a doctor to prescribe a Schedule II narcotic — no questions asked — but I can’t prescribe a product that has a proven safety record of 50 or 60 years.”
Barke is a co-plaintiff in a lawsuit to stop a California law that subjects the state’s doctors to discipline, including the suspension of their medical licenses, for sharing “misinformation” or “disinformation” about COVID-19 with their patients.
What exactly is ‘misinformation’?
The study’s authors identified four categories of “misinformation”:
- Claiming vaccines were unsafe and/or ineffective.
- Promoting unapproved medications for prevention or treatment.
- Disputing mask-wearing effectiveness.
- “Other misinformation,” to include conspiracy theories and the virus’s origins.
The authors reviewed COVID-19-related posts from doctors on the social media platforms Twitter (now X), Facebook, Instagram, Parler and YouTube between January 2021 and December 2022.
The researchers initially focused their Twitter review on America’s Frontline Doctors’ profile because of the organization’s “volume of COVID-19 misinformation in its tweets” and “large following.”
Physicians who followed America’s Frontline Doctors’ Twitter page were targeted on Twitter and other platforms.
Using the search terms “COVID,” “vaccine,” “doctor,” “physician,” “ineffective,” “pharmaceutical,” “ivermectin,” “hydroxychloroquine” and others, the authors of the study identified 52 doctors — 50 licensed and two unlicensed — who used social media to spread COVID-19 “misinformation.”
Results showed most of the 52 physicians (76.9%) who posted “misinformation” did so in more than one of the four categories identified. The majority posted vaccine “misinformation.”
Dr. Meryl Nass — who on Thursday sued the Maine Board of Licensure in Medicine and its individual members, alleging the board violated her First Amendment rights and her rights under the Maine Constitution — called the JAMA study “a piece of propaganda.”
Nass said:
“There is no science. They [the authors] are trying to make it look like they’re doing something quantitative when they’re not. There was a lot known about the ineffectiveness of the vaccines at the time they were working on this paper.”
Unpacking the misinformation in the misinformation study
The University of Massachusetts researchers said doctors’ claims that myocarditis was common in children who received the vaccine and that the risks of myocarditis outweighed the risk of vaccination were “unfounded.”
But myocarditis “does outweigh the benefits of vaccinations for some ages — in men — and some doses,” said Prasad, citing an article published in the Journal of Medical Ethics.
The paper, which focused on booster mandates at American universities, concluded the mandates were unethical because they could result in greater health risks, like booster-associated myocarditis, than benefits to healthy young adults.
Several other studies have shown either myocarditis deaths across all age groups, or elevated myocardial injury after vaccination.
The researchers also flagged any posts discussing pre-pandemic studies that definitively concluded masks do not prevent the spread of respiratory viral infections. And they deemed as misinformation any post that undermined the role of masks in slowing the spread of the infection and that pointed to rising cases in areas with mask mandates.
But a plethora of studies on mask ineffectiveness emerged during the time the Massachusetts team was conducting its research on physicians and “misinformation.”
There were also reports on “The Foegen effect” — the idea that deep re-inhalation of droplets and virions caught on facemasks might make COVID-19 infection more likely or more severe. German physician Dr. Zacharias Fögen introduced the concept in a study that concluded: “mask use might pose a yet unknown threat to the user instead of protecting them, making mask mandates a debatable epidemiologic intervention.”
“The totality of the evidence to date shows no benefit from community mask wearing,” said Prasad, who pointed to Cochrane’s multiple analyses.
According to the JAMA study, doctors who said the COVID-19 vaccines were ineffective at preventing COVID-19 spread or that the virus originated in a lab in China were propagators of misinformation.
Yet plenty of data show the vaccines did not prevent transmission, and scientists even testified to evidence that COVID-19 could have resulted from controversial gain-of-function research at the Wuhan Institute of Virology.
In the wake of the pandemic, multiple organizations have published guidelines on “medical misinformation” — including YouTube and the American Medical Association (AMA).
Last June, the AMA adopted a new policy to limit medical disinformation, including ensuring that medical licensing boards can take disciplinary action against health professionals who spread health-related disinformation.
In California, however, a judge ruled in January that the state does not have the power to penalize doctors who spread “misinformation” or “disinformation.”
“COVID-19 is a quickly evolving area of science that in many aspects eludes consensus,” the judge decided.
Monica Dutcher is a Maryland-based senior reporter for The Defender.
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Can You Overdose on Ivermectin? Dr. Pierre Kory’s Answer Will Shock You
The Vigilant Fox | Vigilant News | August 17, 2023
“Of all the harmful misinformation spread over the past couple of years, one of the most disturbing false narratives was targeted at the Nobel-Prize-winning, human medicine ivermectin,” expressed filmmaker Mikki Willis in his ground-breaking documentary titled, Ivermectin: The Truth.
Ivermectin is “one of the safest and most effective medicines of this era. A medicine that, according to the numerous top scientists I’ve interviewed … could have ended the pandemic before it began.”
But Ivermectin is “horse dewormer,” the media said. “It could put you in a coma.” “It can kill you,” pundits warned.

But is this actually true?
Popular podcaster Greg Hunter, AKA USA Watchdog, asked Dr. Pierre Kory, one of the world’s leading experts on Ivermectin, straight-up, “Can I OD (overdose) on Ivermectin if I get two or three times the [standard] dose. Can I kill myself?”
“Let me answer scientifically. So there is a world-famous toxicologist named Jacques Descotes, and he’s French. And two years ago, he was commissioned to do a scoping review of the entire data on the safety of Ivermectin in its history. And his conclusion after doing this comprehensive review is that he does not believe that there has been one single case of anyone dying from an Ivermectin overdose.”

Prof. Jacques Descotes: Image – Academica.edu
“Oh, Lord,” reacted Greg Hunter. “How many pills have been given worldwide? I heard 4 billion, but it must be more than that.”
“Over 4 billion,” Dr. Kory confirmed. “Now, people have died where the deaths were reported as caused by Ivermectin. But when he [Prof. Jacques Descotes] reviewed those cases, he didn’t think those arguments [were] credible.”
Let’s dive deeper into Prof. Descotes’ analysis.
But first, a quick look at his impressive credentials. “Pr. Jacques Descotes, MD, PharmD, PhD, Professor Emeritus, Claude Bernard University of Lyon (France), [is] a world-known toxicologist with a 40-year track [record] as an independent consultant for the pharmaceutical industry as well as an advisor to regulatory bodies worldwide,” BusinessWire wrote.
In March 2021, he conducted a review of Ivermectin’s safety profile based on over 350 articles – plus accessible web sources. Here are his conclusions:
“Ivermectin has been administered orally to hundreds of millions of people throughout the world in the past three decades. The assessment of reported adverse events temporally associated with Ivermectin exposure shows that Ivermectin-induced adverse effects have so far been infrequent and usually mild to moderate.
“It is noteworthy that no deaths have seemingly ever been reported after an accidental or suicidal overdose of Ivermectin. No greater toxicity of Ivermectin has been substantiated in elderly people despite repeated assertions that an ageing blood-brain barrier might lead to increased Ivermectin toxicity level. The positive clinical experience accumulated with Ivermectin administration led many medical experts to break away from early adamant contra-indications in pregnant women. Finally, several national pharmacovigilance networks around the world released information and opinions to ascertain Ivermectin safety in human subjects. So far, there are no critical safety limitations to Ivermectin prescription in current indications.
I also want to point out that no severe adverse event has been reported in dozens of completed or ongoing studies involving thousands of participants worldwide to evaluate the efficacy of Ivermectin against COVID-19.”
“In order to overdose from Ivermectin, you have to take either a hundred or a thousand times the standard dose,” declared Dr. Kory.
“And there have been accidental poisonings where people have taken large amounts. But you know what happens every time? When they take these massive amounts of Ivermectin, it tends to affect them neurologically. They’ll get confused. They might be stumbling — uncoordinated. They go to the hospital, and there’s no treatment required. But within days, the patients return to normal. So, there’s been no life-ending injuries. No deaths reported with Ivermectin. So, that shows you why it’s one of the safest drugs in history, even at massive overdoses.
Greg Hunter’s full interview with Dr. Pierre Kory is available to watch.
Featured Video

Trita Parsi: Israel Set a Trap for Total War in the Region
or go to
Aletho News Archives – Video-Images
From the Archive
Zionism’s Violent Legacy
By Donald Neff | Washington Report On Middle East Affairs | January 1996
On January 4, 1948, Jewish terrorists drove a truck loaded with explosives into the center of the all Arab city of Jaffa and detonated it, killing 26 and wounding around 100 Palestinian men, women and children.[1] The attack was the work of the Irgun Zvai Leumi – the “National Military Organization,” also known by the Hebrew letters Etzel – the largest Jewish terrorist group in Palestine. The Irgun was headed by Revisionist Zionist Menachem Begin and had been killing and maiming Arabs, Britons and even Jews for the previous ten years in its efforts to establish a Jewish state.
This terror campaign meant that at the core of Revisionist Zionism there existed a philosophical embrace of violence. … continue
Blog Roll
 Aletho News
- Trita Parsi: Israel Set a Trap for Total War in the Region
- Trump’s Iran war is on an Israeli leash
- Saudi oil boss issues global supply warning
- Riyadh Says Its Oil System Is Intact. The Numbers Say Otherwise.
- Trump and Netanyahu Want to “Finish the Job” on Iran
- US ‘one-sided dictation’ not Iran’s beliefs makes rational talks impossible: Baghaei
- Iran’s Next Strike May Not Explode. It Could Shut You Down /Col Doug Macgregor
- Iran: US political targets legitimate if assassinations return
- Iraq shuts key border crossing with Iran under US pressure: Report
- Undersea Internet cables could be targeted in retaliation for attacks on Iran: IRGC deputy chief
- If Americans Knew
- The Israel Lobby’s Changing Fortunes
- AIPAC has become such a political liability that it’s shifting to a more “nimble” approach to buying politicians
- At least 160 Israeli settler attacks in 2 weeks
- Will Gaza’s Ancient Christian Community Disappear Forever?
- Israel’s vision of regional security rests on keeping Arab states weak
- Heidi Levine recounts how Palestinian youths helped save her in settler attack
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- Trump’s Intensifying Sabotage of the ICC, for Israel’s Sake
- Israeli military detain US and UK volunteers in West Bank including Democratic NY politician Brad Lander
- Americans at National Conservatism Conference held in Israel this year criticize Israel
- No Tricks Zone
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation


