Medical Board Chief who wanted Doctors delicensed for ‘misinformation’ in bed with PR firm tied to CDC, Pfizer, Moderna
By Michael Nevradakis, Ph.D. | The Defender | August 18, 2023
The head of a national medical organization who publicly called for doctors to lose their licenses unless they supported government narratives on COVID-19 treatments and vaccines concealed his relationship with a public relations firm whose client list also included Pfizer, Moderna and the Centers for Disease Control and Prevention (CDC).
Dr. Richard Baron, president and CEO of the American Board of Internal Medicine (ABIM) is a client of Weber Shandwick, investigative journalist Paul D. Thacker reported on Wednesday.
In late 2021, Baron publicly pushed for doctors who spread “misinformation” about COVID-19 and the vaccines to lose their license and certification. Baron said then that “putting out flagrant misinformation is unethical and dangerous during a pandemic.”
Weber, the world’s second-largest PR firm, has branded its team as “misinformation and disinformation” experts and says it provides clients with services to help manage any perceived threats posed by spreaders of such information.
The firm has organized conference panels on “medical misinformation” in which Baron participated.
Last year, Baron partnered with Weber Shandwick to propose a South by Southwest (SXSW) panel titled “When Doctors Prescribe Misinformation.” The proposal was subsequently accepted and the panel took place at SXSW in Austin, Texas, on March 13.
According to Thacker, “Weber Shandwick’s panel featuring Dr. Baron has been widely promoted by the PR firm’s employees,” including Sarah Mahoney, executive vice president, Healthcare Communications, Strategy & Planning for Weber Shandwick, who in a LinkedIn post, wrote she “can’t think of a more important topic right now.”
The CDC’s National Center for Immunization and Respiratory Diseases (NCIRD) in September 2020 awarded Weber a $50 million contract “to promote the vaccination of children, pregnant women and those at risk for flu and increase the general acceptance and use of vaccines,” according to the PR firm’s website.
Under the contract, Weber employees were embedded in the NCIRD to “communicate the risks and recommended actions for outbreaks and convey vaccine recommendations to healthcare providers,” according to Thacker.
Medicine has always been ‘in bed with Big Pharma’
Several doctors have faced disciplinary action by state medical boards for allegedly spreading “misinformation.” One of them is internist and biological warfare epidemiologist Dr. Meryl Nass, a member of Children Health Defense’s scientific advisory committee.
Nass on Thursday sued the Maine Board of Licensure, which suspended her license in January 2022.
The board’s suspension arose from its adoption of a position statement promulgated by the Federation of State Medical Boards (FSMB) threatening physicians “who generate and spread COVID-19 vaccine misinformation” with suspension or revocation of their medical license.
In 2021, ABIM and FSMB collaborated to create the statement used to discipline Nass.
Nass told The Defender that in order to get certified by organizations like ABIM, there are several requirements, primarily related to demonstrating competence in one’s field of specialization, including completing a residency, being certified by the residency director, and paying for and passing the board examinations.
Nass told The Defender that in order to get certified by organizations like ABIM, there are several requirements. She explained:
“You complete a medical residency in your field of specialization. Your residency director certifies your competence and moral character, and you must pay for and pass your board examination to demonstrate your command of your specialty.
“When you’ve paid them for board certification and successfully completed all the requirements, how can they change the rules 20 or 50 years later and say, ‘we’re going to decertify you now because we don’t like your viewpoint?’
“There was nothing in any documentation from the Board of Internal Medicine about misinformation, or any other standards that the board can impose apart from competency to practice when it issued certifications.”
Dr. Richard Eggleston, a retired ophthalmologist in Clarkston, Washington, also faces disciplinary action — by the Washington Medical Commission — arising from articles he published in a local newspaper in 2021, questioning the official narrative and medical advice related to COVID-19.
Doctors aren’t being targeted exclusively for spreading “misinformation” — some, like Dr. Mary Kelly Sutton, an integrative physician, were targeted for their less-than-100% support for COVID-19 vaccines.
Last month, the Massachusetts medical board revoked Sutton’s medical license, claiming she improperly exempted eight children from required school vaccinations. This came a year after California also revoked Sutton’s medical license.
Sutton told The Defender, “The voice of medicine today is determined by the marketing wisdom of Madison Avenue, not by what is sound information from scientific research.”
Sutton said the whole practice of medicine rests on sharing and providing information necessary for informed decisions and consent. When specialty boards issue vague accusations, they engage in “harassment,” and an “egregious overreach of power” and are obstructing the practice of medicine.
A California law aimed at punishing doctors for providing “misinformation” to their patients is now in “legal limbo” following conflicting rulings in state courts earlier this year, which could affect Sutton’s and other California doctors’ cases going through the courts.
This trail of evidence demonstrates medical boards are not simply acting on their own authority but in collusion with state governments, federal agencies and private companies.
“There’s no one who is a ‘misinformation’ or ‘disinformation’ expert whose opinion does not align with the government and with the corporations,” Thacker told The Defender. “That’s what makes them an ‘expert.’”
“What’s always been true is that medicine has been in bed with Big Pharma,” he added. “It’s now becoming a lot more transparent. These relationships are much more transparent.”
‘A very political attempt to shut down people from having alternative viewpoints’
According to Thacker, Baron began his “crusade for the biopharmaceutical industry” in September 2021. In a post for ABIM’s blog, Baron said, “I want to state unequivocally that ABIM can and does take action, independent of state licensing boards, to remove certification from physicians for unprofessional and unethical behavior.”
For Thacker, Baron’s concern about “misinformation” was first triggered when physicians spoke out against COVID-19 vaccine safety, efficacy and side effects. “These are the same concerns held by Weber Shandwick, who Pfizer and Moderna are paying big buck[s] to promote their vaccines,” he said.
“Baron’s relationship with Weber Shandwick was not disclosed” by JAMA, Thacker said, “nor in an accompanying viewpoint Baron wrote for JAMA.”
After an inquiry by Thacker, JAMA’s editor-in-chief, Kirsten Bibbins-Domingo, said, “We initiated our internal investigation earlier this week, in accordance with our standard processes for allegations of non-disclosure of conflicts.”
“It is notable that Baron has done his best to mislead the public and other physicians about what he is doing,” Nass said. “He claims the ABIM is trying to ‘protect the legitimacy of medical expertise’ rather than censoring viewpoints it does not like.”
Nass said Baron “conjures up examples of what the board might censure.” She pointed to a Feb. 23, 2023, New England Journal of Medicine (NEJM) article Baron co-authored with attorney Carl J. Coleman, which stated:
“When a licensed physician insists that viruses don’t cause disease or that COVID-19 vaccines magnetize people or connect them to cell towers, professional bodies must be able to take action in support of fact and evidence based practice.”
“Yet this is a fabrication,” Nass said, adding:
“Instead, Dr. Baron, who earns about $1.2 million yearly from the ABIM and the ABIM Foundation, has decertified Drs. Peter McCullough, Paul Marik and Pierre Kory — all highly celebrated, published and esteemed doctors in their fields.
“None of them have uttered any mumbo-jumbo about cell towers, magnetism or a non-viral etiology for COVID-19. All have had their board certifications revoked for the viewpoints they expressed — viewpoints that are supported by a preponderance of the medical literature.”
In a January 2022 article for Health Affairs, Coleman wrote, “Licensing boards are state agencies subject to the First Amendment, and as such they are limited in their ability to penalize physicians based on the content of their speech.”
Yet, a 2022 NEJM article co-authored by Baron argued that while “Differences of opinion in medicine are necessary for progress … there are some opinions that have been so thoroughly repudiated by existing evidence as to be considered definitively wrong.”
‘All this money is sloshing around now for misinformation research’
According to Thacker, “PR firms are now moving into the ‘disinformation’ space after decades of deceit on behalf of multiple industries,” with Weber Shandwick having “expanded into the disinformation space in late 2021,” promoting tactics that help “brands combat misinformation and disinformation that may implicate them.”
Speaking to Thacker, Dr. Aaron Kheriaty, director of bioethics at the Ethics and Public Policy Center, said, “The ABIM is clearly part of this ‘medical misinformation’ push, which is orchestrated by pharmaceutical companies and their PR allies” and which serves “the interests of Big Pharma.”
Remarking on the presence of a “medical misinformation” panel at SXSW, long known as a music, film and technology festival, Thacker told The Defender, “Anyone and everyone is getting involved in ‘misinformation’ and ‘disinformation.’”
“Baron has given a TED Talk, for instance. Why is TED Talks involved in this?” he asked.
In 2019 Baron delivered a talk at TEDx Chicago titled, “Please Don’t Confuse Your Google Search with My Medical Degree.”
For Thacker, the answer relates to financial interests. “All this money is sloshing around now for ‘misinformation’ research. Anyone can hop up and down saying ‘I’m an expert on misinformation and disinformation, get me a grant, get me on a panel,’” he said.
Weber embedded staffers within the CDC while representing Pfizer, Moderna
Thacker wrote that prior to discovering Baron’s ties to Weber Shandwick, he had confirmed the PR firm’s ties to COVID-19 vaccine manufacturers Pfizer and Moderna.
These ties did not prevent the CDC from awarding the $50 million contract to Weber Shandwick in September 2020 to push vaccines. The Daily Mail subsequently reported Thacker’s findings.
Medical Marketing and Media reported “Weber’s duties include providing 10 on-site health communications staffers, seven health comms specialists, two health research specialists and one social media specialist” to NCIRD, as well as “generating story ideas, distributing articles and conducting outreach to news, media and entertainment organizations.”
In October 2020, a blog post by Stacy Montejo, senior vice president at Weber Shandwick, disclosed that Pfizer is one of the firm’s clients. A month later, with Moderna’s COVID-19 vaccine awaiting Emergency Use Authorization, the company hired Weber Shandwick to handle the vaccine’s publicity, according to PR Week.
Such relationships have continued to the present. In June, Moderna announced a new communications strategy “to further educate the world about Moderna’s mRNA technology and its promise to transform the future of human health.”
The effort is led by Laura Schoen, “who is sometimes titled president of global healthcare at Weber Shandwick, and other times chief healthcare officer at IPG DXTRA, Weber Shandwick’s parent company,” Thacker wrote.
Lucy Rieck, a Weber Shandwick employee, previously publicly tweeted support for a panel Moderna proposed for this year’s SXSW, titled “COVID, Monkeypox, Disease X, What’s Next?” That proposal does not appear to have been accepted for presentation.
Conflicts of interest between Weber Shandwick, the CDC and NCIRD, and Pfizer and Moderna do not appear to have been disclosed.
In October 2022, Sen. Rand Paul (R-Ky.) sent a letter to the CDC inquiring about its relationship with Weber Shandwick and requesting “information regarding the nature of Weber’s work for the NCIRD.” It’s unclear whether the CDC complied with the request.
Todd S. Richardson, one of the attorneys representing Eggleston, told The Defender “While it is certainly understandable that governmental agencies will hire PR firms to help them get their message out … it becomes of real concern to me when those agencies, or people working within the agencies, try to silence those who disagree.”
According to Thacker, the web of relationships between Weber Shandwick doesn’t just extend to Big Pharma companies, the CDC and its agencies, or to doctors such as Baron. Academics such as Brown University’s Claire Wardle, Ph.D., a key figure in the “misinformation research” space, have participated in some of the firm’s events.
Wardle, a professor of the practice of Health Services, Policy and Practice at Brown University who has no scientific or medical credentials, participated in an online meeting organized by Weber Shandwick in October 2020 to discuss “election misinformation.”
Subsequently, Wardle played a key advisory role in the Biden administration, federal agencies, social media platforms and Ivy League institutions as they sought to censor content that ran counter to the government’s COVID-19 narrative.
According to Thacker, she “helped organize many of today’s campus disinformation groups … with funding from Google” and later sent Twitter a report aimed at countering the “growing threat of disinformation to trust in COVID-19 vaccines.”
Thacker said the biopharmaceutical industry is “the smartest at putting out disinformation. What other industry has bought off the medical community and the science community?” he asked. “They bought off the researchers, the government, the academic journals.”
Thacker said he believes much of what is labeled “misinformation” in medicine and academic research “is really just corporate PR,” and that “Congress needs to take a harder look at funding for ‘misinformation research.’“
Michael Nevradakis, Ph.D., based in Athens, Greece, is a senior reporter for The Defender and part of the rotation of hosts for CHD.TV’s “Good Morning CHD.”
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Dr. Meryl Nass sues Maine Medical Board over suspension, alleges Board violated her first amendment rights
By Brenda Baletti, Ph.D. | The Defender | August 17, 2023
Dr. Meryl Nass today filed suit against the Maine Board of Licensure in Medicine and its individual members, alleging the board violated her First Amendment rights and her rights under the Maine Constitution.
The complaint alleges the board engaged in retaliatory conduct against Nass, a practicing internal medicine physician and member of the Children’s Health Defense (CHD) scientific advisory board, when the board suspended her medical license for publicly expressing her dissenting views on official COVID-19 policies, the COVID-19 vaccine and alternative treatments.
“Because she was outspoken, the board targeted Dr. Nass as someone to silence,” her attorney, Gene Libby told The Defender.
In fall 2021, the board issued a position statement, quoted in the complaint, stating that licensees could face disciplinary action if they “generate and spread COVID-19 vaccine misinformation or disinformation.”
In October 2021, soon after the statement was issued, the board received a complaint alleging Nass was spreading misinformation online and soon after launched an investigation.
The board suspended Nass’ medical license on Jan. 12, 2022, without a hearing, accusing her of engaging in “unprofessional conduct” by spreading “misinformation about COVID-19.”
It also accused her of improperly prescribing hydroxychloroquine and ivermectin for three patients for off-label uses of those drugs.
The board suspended Nass’ license and ordered a neuropsychological evaluation, implying she was mentally impaired or a substance abuser and incompetent to practice medicine.
“There were no grounds to order a mental health examination,” Libby said. “That was simply a means to communicate to the public that there was something wrong with Dr. Nass, to discredit her and tarnish her reputation.”
After Nass moved to have the board dismiss its complaint against her, alleging First Amendment violations, the board on Sept. 26, 2022, withdrew its accusations of “misinformation”, just prior to her first hearing date, Oct. 11, 2022.
The board’s case now rests on Nass’ alleged non-adherence to the medical “standard of care” as it pertained to ivermectin and hydroxychloroquine for treating COVID-19 and on the alleged “record-keeping” issues.
Nass told The Defender :
“The two primary complaints against me were that my statements were misleading and that I was prescribing drugs off-label. My speech — which I should note, was not simply opinion, it was an educated opinion developed after consulting the medical literature — is protected by the First Amendment.
“And prescribing drugs off-label is a perfectly legal thing to do, as explicitly stated on the FDA [U.S. Food and Drug Administration] website. Somewhere between 20-50% of drugs are prescribed off-label. The lawyers on the board staff know all of this. It’s their job to know the law with respect to medicine.
“They didn’t do this because they thought I had committed some kind of violation. They did it because they thought I’m older and I wouldn’t have the money to challenge them and so they could get away with it — they thought they could turn me into a poster child to scare all the doctors in the country.
“It is part of this broader attempt by the U.S. government and governments across the world to criminalize dissent by criminalizing so-called ‘misinformation.’”
Libby said the remaining allegations against Dr. Nass “are simply a pretext to discipline her. Because now, from an institutional standpoint, the board has to do something. She’s been under suspension for 19 months, which is the longest suspension that I’m aware of for any physician in the state.”
The board refused to schedule hearings on Nass’ suspension on consecutive days. Instead, it has held one day of hearings every other month. There have been six days of hearings so far over 10 months — and Nass’ license has been suspended the entire time.
“This is fundamentally unfair to Dr. Nass, but she’s within the grip of an institution that doesn’t want her speaking out,” Libby said.
In her lawsuit, Nass alleges the board and its members used their power to “crush dissenting views and chill disfavored speech.”
Nass is asking the court for declaratory relief, for an injunction to stop the board from continuing to retaliate against her and for monetary damages and legal fees.
CHD is providing financial and legal resources to Nass’ Maine-based legal team.
CHD President Mary Holland told The Defender :
“CHD is proud to support Dr. Nass’ lawsuit against the Maine medical board and its individual members.
“The board and its members have deprived Dr. Nass of her license and livelihood for over a year with no basis whatsoever. This kind of censorship, intimidation and punishment of doctors of conscience must stop.
“People need independent, thoughtful, caring physicians like Dr. Nass to be honored, not hounded as the board has done.
“I am pleased to see this case move forward in the courts in the interests of justice, for Dr. Nass, her patients and the broader society.”
Board provided resources to ‘combat spread of vaccine misinformation’
The Maine board’s Fall 2021 position statement expressed its support for a statement by the Federation of State Medical Boards (FSMB) — a private organization with no regulatory authority — which threatened physicians “who generate and spread COVID-19 vaccine misinformation” with suspension or revocation of their medical license.
According to the statement, physicians have a high degree of public trust and therefore a responsibility to “share information that is factual, scientifically grounded and consensus-driven for the betterment of public health.”
The Maine board’s statement endorsed the FSMB statement, encouraged physicians to address misinformation when encountered, directed physicians to use circulated materials from the American Medical Association (AMA) and said that questioning the COVID-19 vaccine qualifies as “misinformation,” according to the complaint.
The AMA materials provide scripts, talking points and strategies for “combating the spread of vaccine misinformation.”
The Maine board’s chair, Dr. Maroulla Gleaton, is also an FSMB director.
Nass is a widely recognized expert on the anthrax vaccine and biological warfare. She testified before Congress six times and was quoted in major media outlets including The New York Times, The Washington Post, the Los Angeles Times and the Chicago Tribune.
She has also been a prominent critic of governmental handling of the COVID-19 pandemic, the suppression of effective treatments such as ivermectin and hydroxychloroquine and the safety and risks of the vaccine — all topics she has discussed in her Substack, on the radio, in interviews and elsewhere.
But, the complaint notes, her positions have been in conflict with those asserted in the position statement and the resources it highlights as “supporting the fight against COVID-19 misinformation.”
This was merely an attempt by the board to justify its decision to immediately suspend Nass and to intimidate her, the complaint alleges.
Board’s only concern was ‘silencing’ Nass and ‘branding her as crazy’
When Nass questioned the board’s authority to investigate a complaint unrelated to the practice of medicine and instead “focused entirely on a statement made in her private life,” the board responded, on Oct. 14, 2021, that she was engaged in “alleged unprofessional conduct” by provisioning “misleading and/or inaccurate” information.
In the January board meeting where the board decided to suspend her license, the conversation focused on Nass’ “unprofessional conduct due to the spreading of misinformation about COVID-19.”
The board also cited three matters related to treating patients, alleging Nass improperly diagnosed a patient “over the phone,” that she had provided misinformation to a pharmacist about why she was prescribing ivermectin for a patient, and that she had improperly issued another prescription.
On Sept. 7, 2022, Nass moved to dismiss the complaint, alleging the board was violating her First Amendment rights.
The board responded by withdrawing all charges based on her speech, retaining only the charges related to the treatment of three patients.
Libby told The Defender that through the entire investigation and hearings, the board never even spoke to the three patients. It did not inform them their medical records had been subpoenaed, or ask them about their treatment by Dr. Nass.
“Yet the remaining disciplinary charges are all predicated on Dr. Nass’ consultation with and advice to these patients.”
Libby called the patients to testify in Nass’ hearings. They all made “glowing comments” about her availability, her medical advice and her handling of their cases and expressed anger that Nass was being targeted by the board for their cases.
Libby said he interpreted this to indicate the board’s singular focus was not to ensure patient well-being, but rather “silencing Dr. Nass and attempting to brand her as crazy.”
According to the complaint, the board’s animus against Nass is also demonstrated by the fact that it is flouting its own rules for selecting and paying expert witnesses.
Board guidelines stipulate that witnesses can be paid a maximum of $125/hour for preparation and $175/hour for testimony and that the witnesses should have the same specialty as the practitioner in question and be licensed to practice in Maine.
But the board is paying Dr. Jeremy Faust, an emergency room physician from Brigham & Women’s Hospital in Boston, $500/hour to testify.
And board member Gleaton, who has conflicts of interest because of her position as FSMB director and has acted in openly mocking ways, has refused to recuse herself.
The next medical board hearing is set for mid-September.
But in the meantime, Libby said “The actions of the board are so outrageous, they need to be acted on legally.”
Brenda Baletti Ph.D. is a reporter for The Defender. She wrote and taught about capitalism and politics for 10 years in the writing program at Duke University. She holds a Ph.D. in human geography from the University of North Carolina at Chapel Hill and a master’s from the University of Texas at Austin.
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
The WHO’s Proposed Amendments Will Increase Man-Made Pandemics
By Meryl Nass | Brownstone Institute | August 17, 2023
This report is designed to help readers think about some big topics: how to really prevent pandemics and biological warfare, how to assess proposals by the WHO and its members for preventing and responding to pandemics, and whether we can rely on our health officials to navigate these areas in ways that make sense and will help their populations. We start with a history of biological arms control and rapidly move to the COVID pandemic, eventually arriving at plans to protect the future.
Weapons of Mass Destruction: Chem/Bio
Traditionally, the Weapons of Mass Destruction (WMD) have been labelled Chemical, Biological, Radiologic, and Nuclear (CBRN).
The people of the world don’t want them used on us—for they are cheap ways to kill and maim large numbers of people quickly. And so international treaties were created to try to prevent their development (only in the later treaties) and use (in all the biological arms control treaties). First was the Geneva Protocol of 1925, following the use of poison gases and limited biological weapons in World War I, banning the use of biological and chemical weapons in war. The US and many nations signed it, but it took 50 years for the US to ratify it, and during those 50 years the US asserted it was not bound by the treaty.
The US used both biological and chemical weapons during those 50 years. The US almost certainly used biological weapons in the Korean War (see this, this, this and this) and perhaps used both in Vietnam, which experienced an odd outbreak of plague during the war. The use of napalm, white phosphorus, agent orange (with its dioxin excipient causing massive numbers of birth defects and other tragedies) and probably other chemical weapons like BZ (a hallucinogen/incapacitant) led to much pushback, especially since we had signed the Geneva Protocol and we were supposed to be a civilized nation.
In 1968 and 1969, two important books were published that had a great influence on the American psyche regarding our massive stockpiling and use of these agents. The first book, written by a young Seymour Hersh about the US chemical and biological warfare program, was titled Chemical and Biological Warfare; America’s Hidden Arsenal. In 1969 Congressman Richard D. McCarthy, a former newspaperman from Buffalo, NY wrote the book The Ultimate Folly: War by Pestilence, Asphyxiation and Defoliation about the US production and use of chemical and biological weapons. Prof. Matthew Meselson’s review of the book noted,
Our operation, “Flying Ranch Hand,” has sprayed anti-plant chemicals over an area almost the size of the state of Massachusetts, over 10 per cent of its cropland. “Ranch Hand” no longer has much to do with the official justification of preventing ambush. Rather, it has become a kind of environmental warfare, devastating vast tracts of forest in order to facilitate our aerial reconnaissance. Our use of “super tear gas” (it is also a powerful lung irritant) has escalated from the originally announced purpose of saving lives in “riot control-like situations” to the full-scale combat use of gas artillery shells, gas rockets and gas bombs to enhance the killing power of conventional high explosive and flame weapons. Fourteen million pounds have been used thus far, enough to cover all of Vietnam with a field effective concentration. Many nations, including some of our own allies have expressed the opinion that this kind of gas warfare violates the Geneva Protocol, a view shared by McCarthy.
A Biological Weapons Convention
Amid great pushback over US conduct in Vietnam, and seeking to burnish his presidency, President Nixon announced to the world in November 1969 that the US was going to end its biowarfare program (but not the chemical program). Following pointed reminders that Nixon had not eschewed the use of toxins, in February 1970 Nixon announced we would also get rid of our toxin weapons, which included snake, snail, frog, fish, bacterial, and fungal toxins that could be used for assassinations and other purposes.
It has been claimed that these declarations resulted from careful calculations that the US was far ahead technically of most other nations in its chemical and nuclear weapons. But biological weapons were considered the “poor man’s atomic bomb” and required much less sophistication to produce. Therefore, the US was not far ahead in the biological weapons arena. By banning this class of weapon, the US would gain strategically.
Nixon told the world that the US would initiate an international treaty to prevent the use of these weapons ever again. And we did so: the 1972 Convention on the Prohibition of the Development, Production and Stockpiling of Bacteriological (Biological) and Toxin Weapons and on their Destruction, or Biological Weapons Convention (BWC) for short, which entered into force in 1975.
But in 1973 genetic engineering (recombinant DNA) was discovered by Americans Herbert Boyer and Stanley Cohen, which changed the biological warfare calculus. Now the US had regained a technological advantage for this type of endeavor.
The Biological Weapons Convention established conferences to be held every 5 years to strengthen the treaty. The expectation was that these would add a method to call for ‘challenge inspections’ to prevent nations from cheating and would add sanctions (punishments) if nations failed to comply with the treaty. However, since 1991 the US has consistently blocked the addition of protocols that would have an impact on cheating. By now, everyone accepts that cheating occurs and is likely widespread.
A leak in an anthrax production facility in Sverdlovsk, USSR in 1979 caused the deaths of about 60 people. While the USSR tried a sloppy cover-up, blaming contaminated black market meat, this was a clear BWC violation to all those knowledgeable about anthrax.
US experiments with anthrax production during the Clinton administration, detailed by Judith Miller et al. in the 2001 book Germs, were also thought by experts to have transgressed the BWC.
It has taken over 40 years, but in 2022 all declared stocks of chemical weapons had been destroyed by the USA, by Russia, and the other 193 member nation signatories. The chemical weapons convention does include provisions for surprise inspections and sanctions.
Pandemics and Biological Warfare Receive Funding from Same Stream
It is now 2023, and during the 48 years the Biological Weapons Convention has been in force the wall it was supposed to build against the development, production, and use of biological weapons has been steadily eroded. Meanwhile, especially since the 2001 anthrax letters, nations (with the US at the forefront) have been building up their “biodefense” and “pandemic preparedness” capacities.
Under the guise of preparing their defenses against biowarfare and pandemics, nations have conducted “dual-use” (both offensive and defensive) research and development, which has led to the creation of more deadly and more transmissible microorganisms. And employing new verbiage to shield this effort from scrutiny, biological warfare research was renamed as “gain-of-function” research.
Gain-of-function is a euphemism for biological warfare research aka germ warfare research. It is so risky that funding it was banned by the US government (but only for SARS coronaviruses and avian flu viruses) in 2014 after a public outcry from hundreds of scientists. Then in 2017 Drs. Tony Fauci and Francis Collins lifted the moratorium, with no real safeguards in place. Fauci and Collins even had the temerity to publish their opinion that the risk from this gain-of-function research was ‘worth it.’
What does gain-of-function actually mean? It means that scientists are able to use a variety of techniques to turn ordinary or pathogenic viruses and bacteria into biological weapons. The research is justified by the claim that scientists can get out ahead of nature and predict what might be a future pandemic threat, or what another nation might use as a bioweapon. The functions gained by the viruses or other microorganisms to turn them into biological warfare agents consist of two categories: enhanced transmission or enhanced pathogenicity (illness severity).
1) improved transmissibility may result from:
a) needing fewer viral or bacterial copies to cause infection,
b) causing the generation of higher viral or bacterial titers,
c) a new mode of spread, such as adding airborne transmission to a virus that previously only spread through bodily fluids,
d) expanded range of susceptible organs (aka tissue tropism); for example, not only respiratory secretions but also urine or stool might transmit the virus, which was found in SARS-CoV-2,
e) expanded host range; for example, instead of infecting bats, the virus is passaged through humanized mice and thus acclimated to the human ACE-2 receptor, which was found in SARS-CoV-2,
f) improved cellular entry; for example, by adding a furin cleavage site, which was found in SARS-CoV-2,
2) increased pathogenicity, so instead of causing a milder illness, the pathogen would be made to cause severe illness or death, using various methods. SARS-CoV-2 had unusual homologies (identical short segments) to human tissues and the HIV virus, which may have caused or contributed to the late autoimmune stage of illness, impaired immune response and ‘long COVID.’
Funding for (Natural) Pandemics, Including Yearly Influenza, was Lumped Together with Biological Defense Funding
Perhaps the comingling of funding was designed to make it harder for Congress and the public to understand what was being funded, and how much taxpayer funding was going to gain-of-function work, which might lead them to question why it was being done at all, given its prohibition in the Biological Weapons Convention, and additional questions about its value. Former CDC Director Robert Redfield, a physician and virologist, told Congress in March of 2023 that gain-of-function research had not resulted in a single beneficial drug, vaccine, or therapeutic to his knowledge.
Nonprofits and universities like EcoHealth Alliance and its affiliated University of California, Davis veterinary school were used as intermediaries to obscure the fact that US taxpayers were supporting scientists in dozens of foreign countries, including China, for research that included gain-of-function work on coronaviruses.
Perhaps to keep the lucrative funding going, fears about pandemics have been deliberately amplified over the past several decades. The federal government has been spending huge sums on pandemic preparedness over the past 20 years, routing it through many federal and state agencies. President Biden’s proposed 2024 budget requested “$20 billion in mandatory funding across DHHS for pandemic preparedness” while the DHS, DOD, and the State Department have additional budgets for pandemic preparedness for both domestic and international spending.
Although the 20th century experienced only 3 significant pandemics (the Spanish flu of 1918-19 and 2 influenza pandemics in 1957 and 1968) the mass media have presented us with almost non-stop pandemics during the 21st century: SARS-1 (2002-3), avian flu (2004-on), swine flu (2009-10), Ebola (2014, 2018-19), Zika (2016), COVID (2020-2023), and monkeypox (2022-23). And we are incessantly told that more are coming, and that they are likely to be worse.
We have been assaulted with warnings and threats for over 2 decades to induce a deep fear of infectious diseases. It seems to have worked.
The genomes of both SARS-CoV-2 and the 2022 monkeypox (MPOX) virus lead to suspicion that both were bioengineered pathogens originating in laboratories. The group of virologists assembled by Drs. Fauci and Farrar identified 6 unusual (probably lab-derived) parts of the SARS-CoV-2 genome as early as February 1, 2020 and more have been suggested subsequently.
I do not know if these viruses leaked accidentally or were deliberately released, but I am leaning toward the conclusion that both were deliberately released, based on the locations where they first appeared, the well-orchestrated but faked videos rolled out by the mass media for COVID, and the illogical and harmful official responses to each. In neither case was the public given accurate information about the infections’ severity or treatments, and the responses by Western governments never made scientific sense. Why wouldn’t you treat cases early, the way doctors treat everything else? It seemed that our governments were trading on the fact that few people knew enough about viruses and therapeutics to make independent assessments about the information they were being fed.
Yet by August 2021, there was no corresponding course correction. Instead, the federal government doubled down, imposing vaccine mandates on 100 million Americans in September 2021 in spite of ‘the science.’ There has been no accurate statement yet from any federal agency about the lack of utility of masking for an airborne virus (which is probably why the US government and WHO delayed acknowledging airborne spread by COVID for 18 months), the lack of efficacy of social distancing for an airborne virus, and the risks and poor efficacy of 2 dangerous oral drugs (paxlovid and molnupiravir) purchased by the US government for COVID treatment, even without a doctor’s prescription.
Never have any federal agencies acknowledged the truth about the COVID vaccines’ safety and efficacy. Instead, the CDC turns definitional and statistical cartwheels so it can continue to claim they are “safe and effective.” Even worse, with all that we know, a third generation COVID vaccine is to be rolled out for this fall and the FDA has announced that yearly boosters are planned.
All this goes on, even a year after we learned (with continuing corroborations) that children and working age adults are dying at rates 25 percent or more above the expected averages, and the vascular side effects of vaccination are the only reasonable explanation.
Maiming with Myocarditis
Both of the two US monkeypox/smallpox vaccines (Jynneos and ACAM2000) are known to cause myocarditis, as do all 3 COVID vaccines currently available in the US: the Pfizer and Moderna COVID-19 mRNA vaccines and the Novavax vaccine. The Novavax vaccine was first associated with myocarditis during its clinical trial, but this was downplayed and it was authorized and rolled out anyway, intended for those who refused the mRNA vaccines due to the use of fetal tissue in their manufacture.
Here is what the FDA’s reviewers wrote about the cardiac side effects noted in the Jynneos clinical trials:
Up to 18.4% of subjects in 2 studies developed post-vaccination elevation of troponin [a cardiac muscle enzyme signifying cardiac damage]. However, all of these troponin elevations were asymptomatic and without a clinically associated event or other sign of myopericarditis. p. 198
The applicant has committed to conduct an observational, post-marketing study as part of their routine PVP. The sponsor will collect data on cardiac events that occur and are assessed as a routine part of medical care. p. 200
In other words, while the only way to cause an elevated troponin level is to break down cardiac muscle cells, the FDA did not require a specific study to evaluate the extent of cardiac damage that might be caused by Jynneos when it issued its 2019 license. How frequently does myocarditis occur after these vaccines? If you use elevated cardiac enzymes as your marker, ACAM2000 caused this in one in thirty people receiving it for the first time. If you use other measures like abnormal cardiac MRI or echo, according to the CDC it occurs in one in 175 vaccinees. I have not seen a study with rates of myocarditis for Jynneos, but there was an unspecified elevation of cardiac enzymes in 10 percent and 18 percent of Jynneos recipients in two unpublished prelicensure studies available on the FDA website. My guess for the mRNA COVID vaccines is that they cause myocarditis in this general range, the vast majority of which remain undiagnosed and probably asymptomatic.
Why would our governments push 5 separate vaccines all known to cause myocarditis on young males who have been at extremely low risk from COVID, and who simply get a few pimples for 1-4 weeks from monkeypox unless they are immunocompromised? It’s an important question. It does not make medical sense. Especially when the vaccine probably does not work—Jynneos didn’t prevent infection in the monkeys in whom it was tested nor did it do well in people. And the CDC has failed to publish its trial of Jynneos vaccine in the ~1,600 Congolese healthcare workers on whom the CDC tested it for efficacy and safety in 2017. The CDC made the mistake of announcing the trial, and posting it to clinicaltrials.gov as required, but has not informed its advisory committee that reviewed the vaccine, nor the public, of the trial’s results.
There can be no question about it: our health agencies are guilty of malfeasance, misrepresentation, and deliberate infliction of harm on their own populations. The health agencies first incited terror with apocalyptic predictions, then demanded patients be medically neglected, and finally enforced vaccinations and treatments that were tantamount to malpractice.
COVID Vaccines: The Chicken or the Egg?
The health authorities could have just been ignorant — that could possibly explain the first few months of the COVID vaccines’ rollout. But once they figured out, and even announced in August 2021 that the vaccines did not prevent catching COVID or transmitting it, why did our health authorities still push COVID vaccines on low-risk populations who were clearly at greater risk from a vaccine side effect than from COVID? Particularly as time went on and newer variants were less and less virulent?
Once you acknowledge these basic facts, you realize that maybe the vaccines were not made for the pandemic, and instead the pandemic was made to roll out the vaccines. While we cannot be certain, we should at least be suspicious. And the fact that the US contracted for 10 doses per person (review purchases here, here, here, here and here) and so did the European Union (here and here) and Canada should make us even more suspicious – there is no justification for agreeing to purchase so many doses for vaccines at a time when the vaccines’ ability to prevent infection and transmission was questionable, and its safety suspect or worrying.
Why would governments want ten doses per person? Three maybe. But ten? Even if yearly boosters were expected, there was no reason to sign contracts for enough vaccine for the next nine years for a rapidly mutating virus. Australia bought 8 doses per person. By December 20, 2020 New Zealand had secured triple the vaccines it needed, and offered to share some with nearby nations. No one has come forward to explain the reason for these excessive purchases.
Furthermore, you don’t need a vaccine passport (aka digital ID, aka a phone app that in Europe included a mechanism for an electronic payments system) unless you are giving out regular boosters. Were the vaccines conceived of as the means for putting our vaccinations, health records, official documents–and most importantly, shifting our financial transactions online, all managed on a phone app? This would be an attack on privacy as well as the enabling step to a social credit system in the West. Interestingly, vaccine passports were already being planned for the European Union by 2018.
A Pandemic Treaty and Amendments: Brought to You by the Same People who Mismanaged the Past 3 Years, to Save us from Themselves?
The same US and other governments and the WHO that imposed draconian measures on citizens to force us to be vaccinated and take dangerous, expensive, experimental drugs, withheld effective treatments, and refused to tell us that most people who required ICU care for COVID were vitamin D-deficient and that taking vitamin D would lessen COVID’s severity–decided in 2021 we suddenly needed an international pandemic treaty. Why? To prevent and ameliorate future pandemics or biological warfare events… so we would not suffer again as we did with the COVID pandemic, they insisted. The WHO would manage it.
To paraphrase Ronald Reagan, the words, “I’m from the WHO, and I’m here to help” should be the most terrifying words in the English language after the COVID fiasco.
What the WHO and our governments conveniently failed to mention is that we suffered so badly because of their medical mismanagement and our governments’ merciless economic shutdowns and mismanagement. According to the World Bank, an additional 70 million people were forced into extreme poverty in 2020 alone. This was due to policies issued by our nations’ rulers, their elite advisers and the World Health Organization, which came out with guidance to shut down economic activity that most nations adopted without question. The WHO is acutely aware of the consequences of economic lockdowns, having published the following:
Malnutrition persisted in all its forms, with children paying a high price: in 2020, over 149 million under-fives are estimated to have been stunted, or too short for their age; more than 45 million – wasted, or too thin for their height…
Starvation may have killed more people than COVID, and they were disproportionately the youngest, rather than the oldest. Yet the WHO prattles on about equity, diversity, and solidarity—having itself caused the worst food crisis in our lifetime, which was not due to nature but was man-made.
How can anyone take seriously claims by the same officials who mishandled COVID that they want to spare us from another medical and economic disaster–by using the same strategies they applied to COVID, after they masterminded the last disaster? And the fact that no governments or health officials have admitted their errors should convince us never to let them manage anything ever again. Why would we let them draw up an international treaty and new amendments to the existing International Health Regulations (IHR) that will bind our governments to obey the WHO’s dictates forever?
Those dictates, by the way, include vaccine development at breakneck speed, the power to enforce which drugs we will be directed to use, and which drugs will be prohibited, and the requirement to monitor media for “misinformation” and impose censorship so that only the WHO’s public health narrative will be conveyed to the public.
The WHO’s Pandemic Treaty Draft Requires the Sharing of Potential Pandemic Pathogens. This is a Euphemism for Bioweapons Proliferation.
Obviously, the best way to spare us from another pandemic is to immediately stop funding gain-of-function (GOF) research and get rid of all existing GOF organisms. Let all nations build huge bonfires and burn up their evil creations at the same time, while allowing other nations to inspect their biological facilities and records.
But the WHO in its June 2023 Bureau Text of the Draft Pandemic Treaty has a plan that is the exact opposite of this. In the WHO’s draft treaty, which most nations’ rulers appear to have bought into, all governments will share all viruses and bacteria they come up with that are determined to have “pandemic potential” — share them with the WHO and other governments, putting their genomic sequences online. No, I am not making this up. (See screenshots from the draft treaty below.) Then the WHO and all the Fauci’s of the world would gain access to all the newly identified dangerous viruses. Would hackers also gain access to the sequences? This pandemic plan should make you feel anything but secure.
Fauci, Tedros, and their ilk at the WHO, and those managing biodefense and biomedical research for nation states are on one side, the side that gains access to ever more potential biological weapons, and the rest of us are on the other, at their mercy.
This poorly conceptualized plan used to be called proliferation of weapons of mass destruction—and it is almost certainly illegal. (For example, see Security Council resolution 1540 adopted in 2004.) But this is the plan of the WHO and of many of our leaders. Governments will all share the weapons.
The Genomic Sequencing Conundrum
And governments are to commit to building biolabs that must include genomic sequencing. No explanation has been forthcoming about why each nation needs to install its own genome sequencing laboratories. Of course, they would sequence the many viruses that will be detected as a result of the pathogen surveillance activities nations must perform, according to the WHO treaty draft. But the same techniques can be used to sequence human genomes. The fact that the EU, UK, and US are currently engaged in projects to sequence about 2 million of their citizens’ genomes provides a hint they may want to collect additional genomes of Africans, Asians, and others.
This might fly as simply sharing state-of-the-art science with our less-developed neighbors. But it is curious that there is so much emphasis on genomics, compared to an absence of discussion about developing repurposed drugs for pandemics in the draft treaty or IHR amendments.
But we can’t forget that virtually all developed nations, in lockstep, restricted the use of safe generic hydroxychloroquine, ivermectin, and related drugs during the pandemic. In retrospect, the only logical explanation for this unprecedented action was to preserve the market for expensive patentable drugs and vaccines, and possibly to prolong the pandemic.
Genomes offer great potential profits, as well as providing the substrate for transhumanist experiments that could include designer babies.
The latest version (aka the WHO Bureau draft) of the pandemic treaty can be accessed here. I provide screenshots to illustrate additional points.

Draft pages 10 and 11:




The WHO Treaty Draft Incentivizes Gain-of-Function Research
What else is in the Treaty? Gain-of-Function research (designed to make microorganisms more transmissible or more pathogenic) is explicitly incentivized by the treaty. The treaty demands that administrative hurdles to such research must be minimized, while unintended consequences (aka pandemics) should be prevented. But of course, when you perform this type of research, leaks and losses of agents can’t always be prevented. The joint CDC-USDA Federal Select Agent Program (FSAP) which keeps track of research on potential pandemic pathogens collects reports of about 200 accidents or escapes yearly from labs situated in the US. The FSAP annual report for 2021 notes:
“In 2021, FSAP received 8 reports of losses, 177 reports of releases, and no reports of thefts.”
Research on deadly pathogens cannot be performed without risks both to the researchers and the outside world.
Draft page 14:

Vaccines Will be Rolled Out Speedily Under Abbreviated Future Testing Protocols
Vaccines normally take 10-15 years to be developed. In case you thought the COVID vaccines took too long to be rolled out (326 days from availability of the viral sequence to authorization of the first US COVID vaccine) the WHO treaty draft has plans to shorten testing. There will be new clinical trial platforms. Nations must increase clinical trial capacity. (Might that mean mandating people to be human subjects in out-of-the-way places like Africa, for example?) And there will be new “mechanisms to facilitate the rapid interpretation of data from clinical trials” as well as “strategies for managing liability risks.”
Draft page 14:


Manufacturer and Government Liability for Vaccine Injuries Must be “Managed”
Nations are supposed to use “existing relevant models” as a reference for compensation of injuries due to pandemic vaccines. Of course, most countries do not have vaccine injury compensation schemes, and when they do the benefits are usually minimal.
Is the US government’s program to be a model of what gets implemented internationally?
The US government scheme for injuries due to COVID pandemic products (the Countermeasures Injury Compensation Program or CICP) has compensated exactly 4 (yes, four) of the 12,000 claimants for COVID product-related injuries as of August 1, 2023. All pandemic EUA drugs and vaccines convey a liability shield to the government and manufacturers (this includes monoclonal antibodies, pre-licensure remdesivir, paxlovid, molnupiravir, some ventilators and all COVID vaccines) and the only avenue for injury compensation is through this program.
Slightly over 1,000 of the 12,000 claims have been adjudicated while 10,887 are pending review. Twenty claims were deemed eligible and await a benefits review. Benefits are only paid for uncovered medical expenses or lost income. A total of 983 people, or 98 percent of those whose claims have been adjudicated had their claims denied, many because they missed the brief one-year statute of limitations. Below are the latest data from this program:
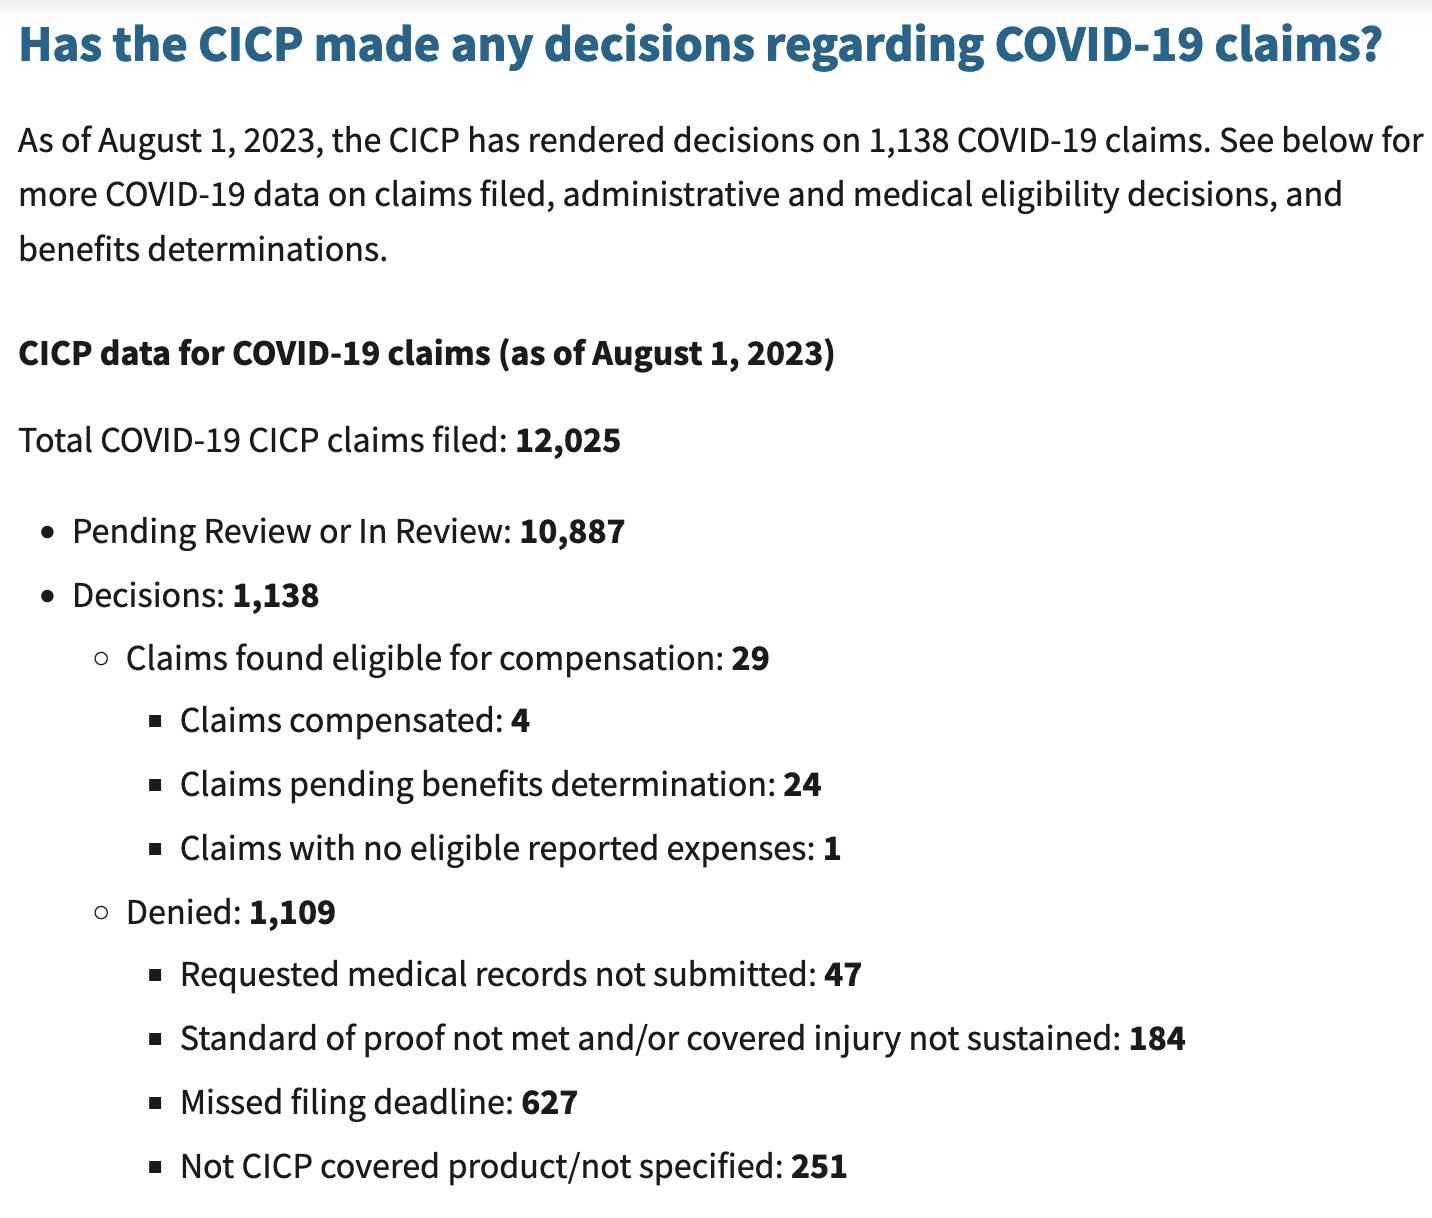
The treaty draft also demands weakening the strict regulation of medical drugs and vaccines during emergencies, under the rubric of “Regulatory Strengthening.” As announced in the UK last week, where ‘trusted partner’ approvals will be used to speed licensure, this is moving toward a single regulatory agency approval or authorization, to be immediately adopted by other nations (p 25).

Next Up: Vaccines Developed in 100 Days
A plan to develop vaccines in 100 days and have them manufactured in 30 additional days has been widely publicized by the vaccine nonprofit CEPI, founded in 2017 by Sir Dr. Jeremy Farrar, who is now the WHO’s Chief Scientist. The plan has been echoed by the US and UK governments and received some buy-in from the G7 in 2021. This timeframe would only allow for very brief testing in humans, or would, more likely, limit testing to animals. Why would any country sign up for this? Is this what we the people want?
The plan furthermore depends on the vaccines only being tested for their ability to induce antibodies, which is termed immunogenicity, rather than being shown to actually prevent disease, at least for the initial rollout. My understanding of FDA regulation was that antibody levels were not an acceptable surrogate for immunity unless they had been demonstrated to actually correlate with protection. However, the FDA’s recent vaccine decisions have scrapped all that and vaccines are now being approved based on antibody titers alone. The FDA’s vaccine advisory committee has asked it for better indicators of efficacy than this, but the advisers have also voted to approve or authorize vaccines in the absence of any real measures showing that they work. I learned this because I watch the FDA vaccine advisory meetings and provide a live blog of them.
We all know how long it took for the public to become aware that the COVID vaccines failed to prevent transmission and only prevented cases for a period of weeks to months. The US government has still not officially admitted this, even though CDC Director Rochelle Walensky told CNN’s Wolf Blitzer the truth about transmission on August 6, 2021.
It is critical for the public to understand that safety testing can only be accomplished in human beings, as animals react differently to drugs and vaccines than humans do. Therefore, limited testing in animals would mean there was no actual safety testing. But testing vaccines in humans for only short periods is also unacceptable.
Testing vaccines during brief trials in humans (the Pfizer trials only followed a “safety subset” of trial subjects for a median of two months for safety) allowed COVID vaccines to be rolled out without the public being aware they could cause myocarditis and sudden deaths, most commonly in athletic young males in their teens and twenties, or a myriad of other conditions.
Finally, following this rapid manufacturing plan, thorough testing for potential failures in the manufacturing process could not be performed. With the current plan for far-flung, decentralized manufacturing facilities that are said to be necessary to achieve vaccine equity for all, there are nowhere near enough regulators who could inspect and approve them.
Will the WHO Respect Human Rights?
The need to respect “human rights, dignity, and freedom of persons” is embedded in the current International Health Regulations (IHR), as well as other UN treaties. However, the language guaranteeing human rights, dignity, and freedom of persons was peremptorily removed from the proposed IHR Amendments, without explanation. The removal of human rights protections did not go unnoticed, and the WHO has been widely criticized for it.
The WHO apparently is responding to these criticisms, and so the language guaranteeing human rights that was removed from the drafts of the International Health Regulations has been inserted into the newest version of the pandemic treaty.
Conclusions
As long predicted by science fiction, our bio- and cyber-scientific achievements have finally gotten away from us. We can produce vaccines in 100 days and manufacture them in 130 days–but there will be no guarantees that the products will be safe, effective, or adequately manufactured. And we can expect large profits but no consequences for the manufacturers.
Our genes can be decoded, and the fruits of personalized medicine made available to us. Or perhaps our genes will be patented and sold to the highest bidder. We might be able to select for special characteristics in our children, but at the same time, a human underclass could be created.
Our electronic communications can be completely monitored and censored, and uniform messaging can be imposed on everyone. But for whom would this be good?
New biological weapons can be engineered. They can be shared. Maybe that will speed up the development of vaccines and therapeutics. But who really benefits from this scheme? Who pays the price of accidents or deliberate use? Wouldn’t it be better to end so-called gain-of-function research entirely through restrictions on funding and other regulations, rather than encouraging its proliferation?
These are important issues for humanity, and I encourage everyone to become part of the conversation.
Dr. Meryl Nass, MD is an internal medicine specialist in Ellsworth, ME, and has over 42 years of experience in the medical field. She graduated from University of Mississippi School of Medicine in 1980.
‘A Fauci Clone’: New NIAID Director Oversaw Remdesivir Trials, Has Ties to Biosafety Lab Research

By Michael Nevradakis, Ph.D. | The Defender | August 15, 2023
When he retired in December 2022, Dr. Anthony Fauci, then-director of the National Institute of Allergy and Infectious Diseases (NIAID) was the highest-paid federal employee and the recipient of the largest federal retirement package in history.
Fauci’s successor, Dr. Jeanne M. Marrazzo, will soon take over leadership of the agency — and its $6.3 billion budget.
Fauci praised Marrazzo, telling CNN, “She’s very well-liked. She’s a really good person. I think she’s going to do a really good job.”
But some of her critics, including medical and public health experts interviewed by The Defender, questioned Marrazzo’s suitability for leading NIAID, citing her limited experience as a medical practitioner and her role in supervising clinical trials of remdesivir, a controversial drug used to treat hospitalized COVID-19 patients.
Critics also called out her steadfast support for strict restrictions and countermeasures during the pandemic, and her receipt, since 1997, of more than $20 million in grants from the National Institutes of Health (NIH) and payments from Big Pharma — including from Gilead, the manufacturer of remdesivir.
And lastly, some pointed to Marrazzo’s key administrative role in a University of Alabama (UAB) institution which houses a BSL3 (biosafety level 3) laboratory that conducts gain-of-function research.
Before being named director of the NIAID, Marrazzo was director of the Division of Infectious Diseases at the UAB at Birmingham. She will replace Dr. Hugh Auchincloss, who has served as NIAID’s acting director following Fauci’s departure.
Commenting on the appointment, Brian Hooker, Ph.D., senior director of science and research for Children’s Health Defense (CHD), said:
“It looks like Dr. Marrazzo will give us more of the same, unfortunately. Her flip-flopping, penchant for Big Pharma, and support of draconian public health (control) measures mean that she’ll take a reactionary posture to any ‘pandemic threat’ and may be as gleeful as Fauci at the prospect of new pandemics.
“I have dim hopes that she may learn some lessons while the investigations into Fauci lying to Congress play out. However, these bureaucrats don’t really believe that the law applies to them.”
The NIAID is the second largest center at the NIH. According to CNN, it “supports research to advance the understanding, diagnosis and treatment of infectious, immunologic and allergic diseases,” as well as “research at universities and research organizations around the United States and across NIAID’s 21 laboratories.”
“Marrazzo fits the mold of every public health leader so far that has led the charge during the pandemic,” Dr. Kat Lindley, president of the Global Health Project and director of the Global COVID Summit, told The Defender.
Lindley added:
“My concern with Marrazzo is actually her Big Pharma ties, her lack of clinical experience with COVID-19 in particular, and her blatant ignorance on early treatment and support for unproven, scientifically debunked measures, in particular masking.
“Any scientist or physician should understand that masking has never proven to be effective and, in the case of children, even detrimental.”
Touted remdesivir as ‘silver bullet’ for treating COVID
During her tenure at UAB, the university served as one of the clinical trial sites for remdesivir, an antiviral originally developed by Gilead Sciences as a treatment for Hepatitis C and respiratory syncytial virus (RSV).
According to the NIH, the trial was intended “to evaluate the safety and efficacy of the investigational antiviral remdesivir in hospitalized adults diagnosed with coronavirus disease 2019.” Marrazzo supervised the UAB trial site.
UAB has long served as a research site for remdesivir. A February 2021 UAB report states, “Gilead entered into collaboration with the UAB-led Antiviral Drug Development and Discovery Center … to study remdesivir against coronaviruses” in 2014.
“These earlier studies enabled remdesivir to more quickly be tested and approved for human use as a treatment for COVID-19 when the 2020 pandemic struck,” UAB stated.
The trial results, published in the New England Journal of Medicine (NEJM) in November 2020, found remdesivir shortened “the time to recovery in adults who were hospitalized with COVID-19 and had evidence of lower respiratory tract infection.”
Fauci later praised remdesivir as the “standard of care” for treating COVID-19.
However, according to investigative journalist Jordan Schachtel, studies “show that there are zero clinical benefits to injecting patients with remdesivir. Many studies show that remdesivir can severely injure vital organs such as the heart and kidneys.”
Yet, Marrazzo never disclosed a conflict of interest when publicly commenting on remdesivir, Schachtel said. She described it as a “silver bullet” in remarks shared with The Washington Post in July 2020, and in tweets praising the drug.
“Given the UAB-Gilead partnership, one would think that Dr. Marrazzo would refrain from commenting on issues through which she maintained a clear conflict of interest,” Schachtel wrote. “She did no such thing.”
According to the U.S. government’s Open Payments database, Marrazzo received seven payments from Gilead, totaling $2,474.93.
But as Marrazzo repeatedly praised remdesivir — and, according to Schachtel, has “never shown remorse” for this despite mounting evidence of the harm it has caused — she has repeatedly spoken out against hydroxychloroquine for treating COVID-19.
In June 2020, in reference to a study published in the NEJM claiming hydroxychloroquine is ineffective in protecting people from COVID-19, Marrazzo said these findings “should provide a very big nail in the coffin” for the use of this treatment.
The following month, Marrazzo called a video that went viral on social media describing hydroxychloroquine as a cure for COVID-19 “very irresponsible and despicable,” adding that she was “glad that video is hopefully not being shared very much.”
In October 2021, she said hydroxychloroquine and ivermectin hold “special appeal” to the unvaccinated.
Yet, in April 2020, prior to the conclusion of the remdesivir clinical trial, Marrazzo said, “We are using it [hydroxychloroquine] in our hospital … for a range of patients including when patients are beginning to deteriorate,” adding:
“And lots of media folks are asking what we think about hydroxychloroquine. And the reality is that we live and die by the evidence. And one issue is the argument about whether it’s even ethical to use these treatments when we don’t have the evidence.
“But I would get back to the compassionate use argument. When you have a patient who’s dying, you have to use what you can, what’s available.”
Cheerleader for COVID vaccines and Merck’s molnupiravir
Marrazzo has also praised COVID-19 vaccines and therapeutics. In May 2020, she was “hopeful” about the Moderna COVID-19 vaccine clinical trial — despite its enrollment of only eight volunteers, saying “We don’t have the luxury of time here in this case.”
In August 2021, she called the U.S. Food and Drug Administration’s approval of the Pfizer Comirnaty COVID-19 vaccine “great news,” saying, “Vaccines are our best weapon against this disease” and are “working incredibly well to prevent severe disease” and reduce hospitalizations.
In January 2022, Marrazzo said “Vaccination makes the biggest difference” in fighting COVID-19, adding that “boosters, of course, are going to augment that protection.”
And in October 2021, Marrazzo praised molnupiravir, Merck’s antiviral pill for COVID-19, stating it had “extraordinary potential.” Results of a preprint study later showed the drug may fuel the development of new and potentially deadly variants of COVID-19.
Marrazzo has received five payments from Merck, totaling $8,820.
Cardiologist Dr. Peter McCullough told The Defender Marrazzo “has been willfully blind to the failure of COVID-19 vaccines” and “appears incapable of mastering the four pillars of pandemic response to lead America through the next pandemic: 1) contagion control, 2) early treatment, 3) late treatment and 4) vaccination.”
A ‘slap in the face’ to vaccine, hospital protocol victims
During the COVID-19 pandemic, Marrazzo made frequent television appearances in which, according to a UAB statement, she “helped inform the world … sharing critical information and perspectives.” UAB touted Marrazzo as a COVID-19 expert during this period.
According to AL.com, Marrazzo was on Alabama Gov. Kay Ivey’s COVID-19 task force, supporting “emergency public health measures that closed business and mandated mask wearing.”
In March 2020, Marrazzo supported “flattening the curve,” calling on the public “to make personal sacrifices for the greater good.” In similar statements made on May 8, 2020, Marrazzo warned of a “backslide” if measures like social distancing were loosened.
In June 2020, she said masks can “change the trajectory of this epidemic.”
In a June 2020 YouTube video, “Why you should wear a mask,” Marrazzo said, “Masks have contributed to the control of this pandemic in other communities.” She called for masks for schoolchildren over age 6 and included mask-wearing in a list of “Three basic rules” along with hand washing and social distancing.
In an article she co-authored and in which she highlighted “the intersection of the COVID-19, HIV, and STI pandemics,” Marrazzo drew parallels between wearing masks and wearing condoms, writing:
“Condoms reduce transmission of HIV and bacterial STIs effectively, if used adequately and consistently, but lack of access to condoms or perhaps even personal preference limits their utility.
“As a correlate to barrier protection, masking has proven effective to reduce the expulsion of SARS-CoV-2 and other respiratory virus droplets.”
The paper also repeated claims regarding the “lack of benefit” of hydroxychloroquine, zinc and vitamins C and D in treating COVID-19. Conversely, referring to the COVID-19 vaccines, the authors stated, “There were few serious adverse events in either arm, and there were no deaths related to the vaccine.”
Blaming the unvaccinated
In May 2021, she criticized loosened Centers for Disease Control and Prevention (CDC) recommendations that the vaccinated do not need to wear masks, stating that because less than 50% were vaccinated in her community, she would still wear a mask indoors despite being fully vaccinated herself.
In July 2021 she warned of a “summer surge” that would be fueled by the unvaccinated.
In December 2021 Marrazzo again scolded the unvaccinated. “Your decision to get infected is unfortunately not just going to be affecting you,” she said. “It’s going to be serving a source of incredible infectiousness going forward.”
Dr. Scott Atlas, a member of the White House Coronavirus Task Force during the Trump administration, told KUSI News San Diego that Marrazzo “was completely wrong about COVID … Pushing pseudoscience, pushing … her belief that vaccines stopped the spread of the infection, that children have high risk, and that masks were efficacious.”
“Marrazzo represents everything that was done wrong in the handling of COVID,” said Gail Seiler, Texas chairperson, Projects and Content, for the FormerFedsGroup Freedom Foundation and a survivor of the CDC’s COVID-19 hospital protocols, including administration of remdesivir.
Seiler told The Defender that Marrazzo advocated for no early treatment until the patient “worsened to the point of hospitalization,” and at that point to give remdesivir, “a drug that she profits from.”
Seiler added:
“Because of people like Marrazzo, patients in the hospital were given no hope of survival. Because of her ignoring the evidence, over a million people died who shouldn’t have.
“Her selection to the NIAID is a slap in the face to every family whose loved ones were killed by the protocols she profited from. And it exemplifies why the general public has lost trust in agencies such as the NIAID.”
Financial ties to Big Pharma
Marrazzo received a total of $20,405,337 in NIH grants for 67 studies between 1997 and 2023, according to NIH data. These grants ranged between $6,000 and $2.82 million and averaged over $304,000 per grant.
Open Payments data show Marrazzo has received $28,761,36 across 37 “general payments” and $152,208.42 across seven payments for “associated research funding,” including $18,636.59 in consulting fees, $4,500 in honorariums, and payments from companies such as Merck, GlaxoSmithKline, Gilead, Janssen and Abbott Laboratories.
In December 2018, Marrazzo participated in a panel titled “Role of the Genital Tract Microbiome in Sexual and Reproductive Health,” during the Keystone Symposia Conference in South Africa, which was “made possible with funding from the Bill & Melinda Gates Foundation.”
Her employer, UAB, received at least two Gates Foundation grants pertaining to health-related research in recent years. This includes a June 2021 grant, “Modeling Impact of Service Delivery Redesign” totaling over $1.5 million, and a $124,921 grant in April 2020 for a project titled “COVID-19 CTA: HTS Core for screening compounds.”
UAB’s Division of Infectious Diseases boasts “an active research portfolio with approximately $39 million in external research funding.” Research specialties include “Pathogenesis of viral infections,” “Antiviral therapy,” “Travel medicine and international health” and “Host defenses and infectious diseases in immunocompromised patients.”
Big supporter of gain-of-function research
UAB also houses a BSL3 research laboratory, the Southeastern Biosafety Laboratory Alabama Birmingham (SEBLAB), funded in part by NIH. According to UAB, it is “one of a limited number of institutions,” adding that the university ranks “among the top 25 in funding from the National Institutes of Health.”
The university states that SEBLAB researchers are “able to bring their skills to bear on the SARS-CoV-2 pandemic, and other issues directly relevant to biodefense and emerging infectious disease,” with a focus on NIAID “priority pathogens” and discovery of “new treatments to prevent or combat” diseases caused by infectious agents.
These projects have also included “Testing drugs on SARS-CoV-2,” a process involving growing the virus in SEBLAB. According to UAB researcher Kevin Harrod, Ph.D.,“We grow the viruses, measure them and provide them to the BARDA [the U.S. government’s Biomedical Advanced Research and Development Authority] contractor.”
BSL3 and BSL4 laboratories across the U.S. and the world have been associated with controversial gain-of-function research, which some have said is responsible for the development and subsequent alleged leak from one such facility, the Wuhan Institute of Virology in China, leading to prominent calls to end such research.
According to Independent Institute, “Marrazzo’s views on the origin of COVID-19 are hard to find,” as are her views on gain-of-function research.
Francis Boyle, J.D., Ph.D., a professor of international law at the University of Illinois who drafted the Biological Weapons Anti-Terrorism Act of 1989, told The Defender that Marrazzo’s selection signals that the NIH and NIAID have no intention of stopping gain-of-function research at BSL3 and BSL4 facilities.
Boyle said:
“They will have her in place to deal with the next pandemic that they know is coming out of their own BSL3 and BSL4 labs, just as Fauci dealt with the COVID-19 pandemic that came out of the Wuhan BSL4 and the University of North Carolina BSL3 and that Fauci and [former NIH Director] Francis Collins funded.
“Under her auspices NIAID will continue to research, develop, manufacture and stockpile every hideous type of Nazi biological warfare weapon known to humanity … There will be no end to it and to these death scientists like her … unless and until we stop them by criminal prosecutions.”
Boyle called Marrazzo a “Fauci clone, not an original and independent thinker,” adding, “The Bidenites and the globalists and Big Pharma behind them picked her to continue the Fauci/NIAID policies and programs across the board.”
Michael Nevradakis, Ph.D., based in Athens, Greece, is a senior reporter for The Defender and part of the rotation of hosts for CHD.TV’s “Good Morning CHD.”
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
YouTube Greatly Expands Its Medical “Misinformation” Policies
New rules, largely determined by the WHO
By Christina Maas | Reclaim The Net | August 16, 2023
YouTube, the titan of online video content, has expanded its Covid misinformation policy to cover what it calls all forms of medical misinformation.
YouTube has also declared its plan to delist videos promoting “cancer treatments proven to be harmful or ineffective,” effectively disallowing content creators from encouraging natural cures.
The platform pledges to implement its medical misinformation policies when a topic exhibits high public health risks, is supposedly prone to misinformation, and when official guidance from health authorities is accessible to the public.
The changes also see YouTube recommitting to groups such as the WHO and other health bodies on what information is deemed to be acceptable for people to talk about on the platform – despite these institutions having recently received major blows to their credibility.
According to the policy update, YouTube will no longer host content that:
- Misinforms about prevention techniques or contradicts current health authority guidelines, including inaccuracies regarding the safety or efficacy of approved vaccines.
- Promotes treatments that local health bodies or the WHO have neither approved nor recognized as safe and effective. Moreover, it bans content that advocates for harmful substances or practices that have been scientifically proven to be detrimental.
- Denies the existence of specific health conditions.
As stated in its blog post, YouTube intends to punish content promoting not only what it believes to be overtly harmful treatments but also unproven ones that are audaciously offered as replacements for recognized alternatives.
For instance, influencers suggesting vitamin C supplements or garlic for cancer may have their content removed, the post states.
This marks a substantial escalation in the Google-owned platform’s ongoing crusade against what it believes to be the dissemination of medical misinformation, heavily catalyzed by the controversial experience of battling narratives about themes such as COVID-19 and vaccines, something YouTube was heavily criticized for as truthful content ended up being censored on the platform.
YouTube had targeted vaccine “misinformation,” such as demonetizing and deleting vaccine skepticism, thereby refining their approach in response to the global pandemic situation.
New Book by Doctors for COVID Ethics Details Dangers of mRNA Vaccines
By Margot DesBois | The Defender | August 15, 2023
The Doctors for COVID Ethics (D4CE), an international group of physicians and scientists, last month released a new book, “mRNA Vaccine Toxicity,” an extensive assessment of the mechanisms and manifestations of mRNA vaccine technology harm, through the perspectives of immunology, pathology, pharmacokinetics, epidemiology and medical history.
The book is available to download free of charge or order in print.
D4CE, led by microbiologist and immunologist Dr. Sucharit Bhakdi, consists of more than 100 medical practitioners and researchers from 30 countries who “oppose the ongoing abuse of science and medicine for the destruction of peoples’ health, livelihoods, and even lives,” and believe “this abuse includes but is not limited to the ‘public health’ measures taken in the contrived COVID ‘pandemic.’”
In the months following the European Medicines Agency’s (EMA) issuance of emergency approval for the COVID-19 vaccines, D4CE wrote a series of open letters to the EMA warning of short-term and long-term health dangers from these experimental products and calling for their immediate withdrawal.
During the past two years, the group has conducted five online symposia and published numerous articles, letters, video presentations and other resources on current threats to health and freedom posed by the COVID-19 public health mandates.
Written and edited by D4CE founding signatory and biochemist Dr. Michael Palmer, “mRNA Vaccine Toxicity ” includes chapter contributions by Bhakdi; Brian Hooker, Ph.D., Children’s Health Defense (CHD) senior director of science and research; Margot DesBois, CHD science fellow; and biochemist David Rasnick, Ph.D.
In the book’s afterword, Catherine Austin Fitts, president of Solari, Inc., publisher of the Solari Report, provides insight into the broader implications of this scientific information and encourages readers to pass on this knowledge and resist the future deployment of harmful medical technologies.
The foreword by CHD President Mary Holland, reproduced in full below, previews the book’s contents:
Anyone alive today may be forgiven for experiencing PTSD (Post-Traumatic Stress Disorder) about all things COVID—the lockdowns, the fear-mongering, the masking, the testing, the censorship, the suppression of effective treatments, the coerced experimental gene-based shots, and the pervasive injuries and deaths. After three years of horror, it is only human to want to put this behind us and to forget.
Yet this book makes abundantly clear that we would do so at our own peril. This undeclared war against humanity is not over, and we must arm ourselves with knowledge.
The book’s purpose is to explain what the COVID-19 mRNA vaccine toxicity means for future mRNA vaccines. It outlines three potential mechanisms that likely account for what’s happened: (1) the toxicity of the lipid nanoparticles; (2) the toxicity of the vaccine-induced spike proteins; and (3) the immune system’s response to them.
It concludes that the immune system’s response to the spike proteins is the most significant toxic factor because it both corresponds to the autopsy findings of inflammation and immune system damage and jibes with the theoretical mechanisms of harm.
The book’s conclusion is bleak: “Every future mRNA vaccine will induce our cells to produce its own specific antigen, related to the particular microbe it targets. We must therefore expect each such vaccine to induce immunological damage on a similar scale as we have witnessed with those directed against COVID-19.”
Recognizing that myriad mRNA vaccines are in the pipeline or already on the market—against flu, RSV, HIV, malaria, cancer, allergies, heart disease, to name a few—this knowledge is as chilling as it is critical.
The book warns: “First and foremost, we must accept that we are indeed in our governments’ crosshairs. Instead of relying on their treacherous and malevolent guidance, we must therefore watch out for ourselves and our loved ones—do our own research and seek out honest health advice wherever it may be found, be it inside or outside the established venues of science and of medicine.”
You hold in your hands an indispensable primer. The book is comprehensive, drawing on a wide array of published scientific literature, reasonably short and highly readable—156 pages of text and 20 pages of citations—providing required reading on virology, immunology and toxicology. It has excellent citations, illustrations of viral and immune mechanisms, and stained tissue photographs of those who died from COVID-19 shots.
The chapter on the epidemiology of COVID-19 mRNA vaccine adverse events is illuminating—looking at the vast harms to date. Here we learn that 13 billion COVID vaccine doses have been administered worldwide—almost two doses for each person on the planet. And the US dispensed 650 million doses, causing millions of adverse events.
The types of injuries are remarkable for their breadth—including myocarditis, blood clotting throughout the body and neurological, immunological and reproductive harms. Still, the CDC has the audacity to call the vaccines “safe” and to recommend them for all people 6 months and up on at least an annual basis.
The final chapter by David Rasnick chronicles how AIDS and HIV became the “blueprint for the perversion of medical science” that we continue to live through today. In the 1980s, Dr. Tony Fauci initiated “science by press release,” proclaiming and enforcing an entirely unproven AIDS narrative.
Rasnick cogently explains that the AIDS orthodoxy is false, having never been proven despite 40 years and billions of dollars invested. He writes:
“[A]s incredible as this may sound, there has not been a single scientific study designed or conducted to determine whether or not AIDS—or even HIV—is sexually transmitted. . . .
“Since WWII—but especially in recent decades—the stifling of debate and the persecution of dissenters has become entrenched in virtually every major field of science in the US. It is particularly virulent in the so-called biomedical sciences. . . .
“The conjoining of government, big business and academe which President Eisenhower warned about in 1961 now rules the world. . . . The COVID-19 fraud is the AIDS scam writ large. . . . We are in the middle of a global totalitarian takeover and things are going to get much worse in the months ahead.”
The book’s overall conclusion echoes Rasnick:
“It is not possible to interpret the actions of the authorities as ‘honest mistakes.’ Too much has occurred that points unequivocally to a sinister agenda behind the gene-based COVID-19 vaccines. The rushed approval without necessity, the outright threats and the coercion, the systematic censorship of honest science and the suppression of the truth about the numerous killed or severely injured vaccine victims have all gone on for far too long to permit of any doubts as to intent and purpose.
“Our governments and the national and international administrative bodies are waging an undeclared war on all of us . . . [T]his war has been going on for decades, and we must expect it to continue and to escalate.”
While this well-founded information is both alarming and depressing, knowledge is power. If we come to grips with the reality that past and future harm from mRNA vaccines is both intentional and inevitable, we can protect ourselves and our loved ones.
Forewarned is forearmed. Read this book and keep it close as a reference until we’ve turned the page on this dark chapter in global history.
Margot DesBois is a science and research fellow with Children’s Health Defense.
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
U.S. Lawyers Reiterate Claim Ivermectin was never prohibited for treating COVID-19
Attorneys restate claim that FDA merely advised doctors against IVM for dying patients, but did NOT prohibit it.
BY JOHN LEAKE | COURAGEOUS DISCOURSE | AUGUST 14, 2023
Last November, I wrote the following post:
The Epoch Times recently reported an astonishing statement by a U.S. government lawyer in a federal court in Texas, where the FDA is being sued by Dr. Paul Marik of Virginia, Dr. Mary Bowden of Texas, and Dr. Robert Apter of Arizona. The three plaintiffs claim the FDA illegally prohibited them from prescribing the drug to their patients. At a November 1 hearing, U.S. lawyer Isaac Belfer argued for the defendant:
The cited statements were not directives. They were not mandatory. They were recommendations. They said what parties should do. They said, for example, why you should not take ivermectin to treat COVID-19. They did not say you may not do it, you must not do it. They did not say it’s prohibited or it’s unlawful. They also did not say that doctors may not prescribe ivermectin.”
If Belfer’s assertion is true, it raises a very urgent question: On what legal grounds did hospitals all over the United States refuse to administer ivermectin to severely ill COVID-19 patients, even when patients and their family members begged for the drug to be administered?
If ivermectin was not prohibited by the FDA or any other U.S. medical authority for treating COVID-19, why did Dr. Paul Marik’s hospital prohibit him from administering the drug to his dying patients? Why was Dr. Mary Bowden reported to the Texas Medical Board for disciplinary action when she prescribed it? Why did many pharmacists fear losing their licenses if they filled ivermectin prescriptions for treating COVID-19?
In our book, The Courage to Face COVID-19: Preventing Hospitalization and Death While Battling the Bio-Pharmaceutical Complex, Dr. McCullough and I document numerous instances of hospitals flatly refusing to grant the wishes of dying patients and their family members for ivermectin.
All these patients asked for was to be allowed to try the drug (FDA-approved for River Blindness, Elephantiasis, and Scabies) for COVID-19. The patients and their kin gladly indemnified the hospitals and arranged to have their independent primary care doctors deliver and administer the drug. Nevertheless:
- Hospital administrators absolutely refused to grant this wish.
- Hospital attorneys fought tooth and nail against using ivermectin to treat COVID-19 patients, doing everything in their power to challenge patient lawsuits and appeal court orders to administer the drug.
- Even when hospital doctors acknowledged that the patients were dying, they insisted it was better to let the disease take its natural course rather than allow patients to try ivermectin.
- Even when patients’ families succeeded in getting a court orders to administer the drug, many hospitals still refused, even at the risk of being held in contempt of court.
Several readers have told us that our chapters covering this shameful scandal— Chapters 38: Begging for the Wonder Drug and Chapter 40: Graduating into Eternity—are horrifying beyond belief.
Now we hear U.S. government lawyers arguing in court that the FDA never prohibited using ivermectin to treat COVID-19 patients, but merely recommended not using it. This indicates that hospitals had no legal grounds for denying sick patients a drug that could have helped them. How is withholding medicine from a sick man any different from withholding a life ring from a man who has fallen overboard in high seas?
For families who watched their loved ones slip away after being denied the right to try ivermectin, U.S. attorney Isaac Belfer’s statement may be interpreted as declaring open season for lawsuits against hospital administrators and doctors.
After I wrote the above post, I exchanged an e-mail with Dr. Marik in which he expressed profound discouragement about U.S. Judge Jeffrey Vincent Brown’s granting of the government’s Motion to Dismiss the case on the grounds of sovereign immunity.
Nevertheless, Dr. Marik and his co-plaintiffs, Robert L. Apter and Mary Talley Bowden, appealed the dismissal and are now being heard before a three-judge panel of the 5th U.S. Circuit Court of Appeals.
Once again, attorneys for the U.S. government are in the hot seat about their mendacious claims about the FDA’s directive to doctors and hospitals against prescribing or administering Ivermectin, either to outpatients or to patients dying in hospital.
Instead of acknowledging the obvious reality that the FDA did indeed DIRECT doctors and hospitals against administering Ivermectin, U.S. attorneys continue to insist that the FDA’s communiques were mere advice.
This preposterous argument not only overlooks the plain language of the FDA’s communiques, it also overlooks the salient fact that numerous doctors (like Paul Marik) were fired from their jobs for administering ivermectin to their dying patients, and the fact that many State Medical Boards revoked doctors’ licenses for doing the same. If these punitive actions taken against doctors were NOT based on the FDA’s directives, on what grounds were they taken?
As was just reported by Just the News columnist Greg Piper:
The 5th Circuit panel seemed skeptical of Civil Division Appellate Attorney Ashley Honold’s argument that the FDA’s “informational statements” against ivermectin, including its conflation of human and animal dosages, were “merely quips” about reported problems after “self-medicating” rather than “prohibit[ing] anyone” from using ivermectin.
Judge Jennifer Walker Elrod cited the phrase “Stop it” in the agency’s viral “You are not a horse” post on X, then known as Twitter. “If you were in English class, they would say that was a command. … That is different than ‘we’re providing helpful information,'” she told Honold.
Readers of this Substack will probably agree with my sentiment that enough is enough of lying and obfuscating U.S. government agency officials and their mercenary lawyers. It’s time for the grown-up, reasonable citizenry of this country to join Marik, Bowden, et al. in suing the pants off the FDA and other U.S. agencies against whom there is a preponderance of evidence that they have unlawfully interfered with the doctor-patient relationship and committed negligent homicide, fraud, and concealment.
Cry havoc and let slip the plaintiffs’ attorneys! Sue the FDA; sue doctors and hospital administrators; and sue the medical boards. Let them pay for the damages they have inflicted on the families of patients who were denied ivermectin until their last breaths. Let them pay for the massive damage and distress they have caused for courageous doctors like Paul Marik and his colleagues who tried to help their patients.
First ‘confirmed’ cases in America were on U.S. aircraft carrier …
Or this should have been the obvious conclusion from a strangely-ignored antibody study

The USS Theodore Roosevelt left San Diego on January 17, 2020. Some sailors had shore leave at a port of call in Vietnam March 5-9. There seems to have been little interest in the question of how crew members were first infected or when “case zero” on the ship experienced symptoms. In a future article, I’ll point out that an “outbreak of norovirus” occurred on the ship Feb. 2-22. Only 382 of the ship’s 4,800 crew members “voluntarily” participated in the antibody study. At one time, officials said at least 1,000 crew members would participate in the antibody study.
BY BILL RICE, JR. | AUGUST 14, 2023
For a few weeks in early spring 2020, the drama of an outbreak of COVID-19 on the aircraft carrier USS Theodore Roosevelt was world news.
Inexplicably, however, journalists and Covid researchers missed or ignored several blockbuster findings that could re-write key (and, I believe, false) narratives about this novel virus. In this author’s opinion, this possibly represents an intentional disinformation campaign perpetrated by “trusted” Naval and public health officials.
A later antibody study of a sample of the ship’s crew members produced several eye-opening findings. In my view, two findings qualify as particularly significant:
Information contained in the study strongly suggests that at least two crew members (and most likely several other crew members) had already been infected with the novel coronavirus when the ship sailed from San Diego on January 17, 2020.
The date is significant as this would be three days before the CDC reported the first “confirmed” Covid case in America. (This case was “confirmed” on January 20, 2020 but the PCR sample was taken on January 18.)
Language in the Roosevelt study definitely “confirms” that at least two sailors, both of whom later tested positive for antibodies, experienced Covid symptoms between Jan. 12-17, 2020.
For more than three years, “official” Covid histories state the first “confirmed” case in America was a man from Washington who’d recently returned from Wuhan, China. As developed below, crew members of the USS Roosevelt could, in fact, be listed as “confirmed” cases and by themselves debunk the narrative that America’s first cases came from travelers returning from Wuhan.
The same antibody results suggest that at least 59.7 percent of the ship’s approximately 4,800 crew members had already been infected by mid to late April 2020. This means approximately 3,000 crew members had contracted the virus by this date.

Sadly, Aviation Ordnanceman Chief Petty Officer Charles Robert Thacker Jr., 41, passed away on April 13, 2020 reportedly from complications of Covid. Officer Thacker tested positive for Covid March 30th and was in isolation in housing on Guam when he was found unresponsive April 9th. According to published reports, Thacker was receiving twice-a-day medical evaluations. He had gone to the Naval hospital in Guam on April 4th, but had been discharged back to his isolation quarters. It’s unclear how his medical condition deteriorated so rapidly without anyone knowing. It’s also unclear if he was staying by himself or with other sailors in isolation. I hope CDC and Navy officials can provide more details in a future interview, which I’ve requested. According to antibody and PCR test results, approximately 3,000 Roosevelt crew members were infected by Covid and Thacker was the only death. As of April 16, six of 4,800 crew members were hospitalized. Many sailors who were hospitalized seemed to have been hospitalized as a precaution, according to various press reports.
According to news reports, only one crew member, age 41, died from “complications of Covid.” (A future article will provide details that make me think the public hasn’t learned the full story of the death of Chief Petty Officer Charles Robert Thacker Jr.).
As the vast majority of Roosevelt crew members were under the age of 40, this one death reveals that the Infection Fatality Rate (IFR) for crew members under age 41 was 0.0000 percent.
In my opinion, the second big headline from this antibody study should have been: “Covid poses virtually no mortality risk to anyone middle age or younger … even in the worst and most intense spread environments.”
Instead, the prevailing narrative remained that Covid was a serious threat to “everyone” in the world, even though lessons from the Roosevelt proved this was not the case.
Two other naval vessels had ‘outbreaks’ where antibody tests
The above finding was further reinforced by two other “outbreaks” on military vessels from approximately the same time period.
Sixty percent of crew members on the French air craft carrier The Charles De Gaulle tested positive for antibodies after an outbreak said to have begun in March 2020.
According to this chart, 74.75 percent of crew members of this French aircraft carrier either had “confirmed” or “suspected” cases of Covid (60 percent of de Gaulle crew members tested positive for antibodies, the same percentage as the Roosevelt study)
None of the 1,739 sailors on the de Gaulle died. Also, an outbreak that infected at least 41 percent of the 333 crew members on the guided missile destroyer USS Kidd resulted in no deaths.
This means that Covid outbreaks that spread through three military ships between January – April 2020 – potentially affecting almost 7,000 Navy personnel – resulted in only one (presumed) Covid death.
According to results of antibody and PCR tests administered to crew members of these three Naval vessels, a total of 4,408 sailors were either “confirmed” or “probable/suspect” Covid cases.
As only one crew member died from Covid, the Infection Fatality Rate was 0.022 percent – which is significantly lower than the infection fatality rate for influenza (which is often reported as 0.1 percent).
Most news reports in the early months of the official pandemic said the IFR from Covid was between 1 and 4 percent, meaning that at least 1 in 100 people infected with this virus would later die from complications caused by this new and contagious virus.
However, among Naval personnel believed to have contracted this virus while serving on these three vessels, only 1 of 4,408 likely-infected sailors died from Covid.
Expressed as a fraction, the IFR for flu (0.1 percent) corresponds to 1 death in 1,000 flu cases. From this statistic, one could state that influenza is at least four times more deadly than Covid … at least among healthy young and middle-aged sailors.
It should also be emphasized that sailors on all three vessels lived with the virus in extremely-cramped quarters with the virus circulating for weeks or months. In other words, it’s hard to produce a more virulent environment for virus spread.
In the opinion of this journalist, neither of these two findings have received the attention they warrant. Study findings which should have been Page-1 news around the world have barely been cited by researchers, with most members of the public probably unaware of these two narrative-shifting findings.

See top graph … Figure 3 from the Roosevelt antibody study presents information on the number of sailors who tested positive for antibodies between April 20-24. The two cases on the far right would pre-date the fist confirmed Covid case in America. At least six antibody-positive crew members had symptoms before the ship’s port-of-call in Vietnam (March 5-9, 2020). The study does not address how these sailors – isolated and confined to the ship for many weeks – contracted the virus. Note also that most of the antibody positive sailors either did not test positive with a PCR test or had yet to receive a PCR test, which begs the questions of how and when these crew members contracted the virus their positive antibody tests say they’d definitely contracted. None of the positive sailors were interviewed by CDC or Navy officials.
Roosevelt Antibody Study key findings …
On April 20-24, 382 Roosevelt crew members “voluntarily” donated blood for antibody tests. (Positive results on an antibody tests show/suggest “prior infection.”)
Quick Comments:
- 382 crew members is only 7.9 percent of the crew of approximately 4,800.
- Earlier reports said the Navy and CDC were going to test at least 1,000 crew members for antibodies. I’ve never learned why the study was down-sized dramatically or wasn’t made mandatory, which one thinks might have been the case in time of an alleged medical crisis and world-wide pandemic.
– As I will show in a future article, 98.1 percent of the crew of the Charles de Gaulle were tested for antibodies.
60, 62 or “nearly” 66 percent infected …
All three figures are used in the Roosevelt study, with 60 percent being the most common percentage. From the study:
N = 382 – Survey respondents/participants
N = 228 positive (antibody) ELISA result (59.7 percent)
N = 238 had “previous or current Covid infection (62 percent)
One sentence in the study reads:
“Nearly two thirds of persons in this sample had positive ELISA test results, which indicate previous exposure to SARS-CoV-2.”
In my opinion, these could be labelled as ‘confirmed’ cases …
In several places in the study, authors define a “current or previous infection.” For example:
- “Current or previous SARS-CoV-2 infection is defined as a positive RT-PCR test result or a reactive antibody result determined by testing performed at CDC laboratories on specimens collected during April 20–24, 2020.”
“… (4) Previous or current SARS-CoV-2 infection was defined as a positive real-time RT-PCR result or positive ELISA (antibody) result.”
Quick comments:
Although different semantic interpretations might be offered, in my opinion, the above language says at least two Roosevelt cases should be “confirmed” as “early cases” that happened before the first “confirmed” case in America.
That is, all 228 sailors who tested positive via ELISA antibody tests satisfied the definition of individuals who had “current or previous” Covid infections. This figure would include the two sailors who tested positive and experienced Covid symptoms 98 and 99 days before receiving their antibody tests.
As far as I’m aware, this might be the only CDC study that defines a Covid case as someone who tested positive on an ELISA antibody test.
This language is extremely significant as hundreds of other early cases in the world could/might be “confirmed” if the same definitions used in the Roosevelt study also applied to these likely early cases.
Move the birthday of Covid spread up several months …
If this criteria applied to other likely/possible cases, the timeline of the “start date” of virus spread would be moved up at least three months. The first “confirmed cases” would be November 2019, or October 2019 if not September 2019 … but certainly not January 20, 2020.
For example, I’ve identified many Americans – as well as citizens from France, Italy and the UK – who tested positive via antibody tests (including several/many who tested positive with ELISA antibody tests). These possible/likely cases include many citizens who experienced Covid symptoms in late 2019. None of these citizens have been “confirmed” as Covid cases.
Almost all other studies define or confirm Covid cases as individuals who tested positive via a PCR test. As almost no PCR tests were administered to Americans prior to March 2020, it is literally impossible to “confirm” an early case via the “PCR-positive” confirmation protocol.
Again, modifying the definition of “previously-infected” individuals to include those who tested positive via an antibody test should be viewed as very significant and represents a stark departure from other CDC statements.
Symptoms and symptom onset dates matter …
Significantly, Roosevelt study participants filled out questionnaires, providing information on when sailors experienced Covid/ILI symptoms. Participants reported what symptoms they experienced, how many symptoms and, most significantly, self-reported dates where they first experienced these symptoms. (Most antibody-positive sailors experienced at least four symptoms; many experienced six or more symptoms).
The data that immediately jumped out to me (but apparently no one else) was the two crew members who self-reported symptoms 99 and 98 days before donating blood for this serology test (donation dates were April 20-24, 2020).
Working backward from April 20-24, 2020, the crew member who experienced symptoms 99 days before donating blood would have been symptomatic January 12-16, 2020. The sailor who experienced symptoms 98 days earlier would have been symptomatic January 13-17.
Comments:
Inexplicably, Navy and CDC medical personnel did not interview either of these sailors, both of whom could/would have qualified as “case zero” in America. In fact, no sailor in the survey was questioned about their symptoms.
From study: “… although the date of any symptom onset was collected, information on timing, duration, and severity of individual symptoms was not collected.”
“Symptom onset” typically occurs two to 14 days after infection. This means these two sailors, if they had Covid, were infected even earlier in January. For the sailor who experienced symptoms 99 days earlier, the infection date could have been between December 29, 2019 and January 15, 2020.
While the ship left San Diego January 17, 2020, I’ve yet to learn when sailors began to board the ship. My assumption is sailors boarded the ship at least several days before the ship got underway to prepare for its deployment, which lasted approximately 70 days.
If any crew members were symptomatic or infected with Covid on or before January 17, these crew members would almost certainly have begun to infect any “close contacts” who didn’t already have natural immunity.
(The possibility some crew members might have already been infected as early as November 2019, or perhaps even earlier, does not seem to have been considered by any public health official or journalist. At least to me, The Red Cross antibody study proves that residents of California had been infected by November 2019. If this was the case with some Roosevelt crew members, these crew members would likely have come on board the ship with natural immunity.)
In my opinion, if the CDC and Navy had tested the vast majority of the crew for antibodies, and these crew members had also filled out symptom questionnaires, the number of possible cases pre-dating the first confirmed case in America would have been much larger than two possible American “case zeroes.”
That is, by severely limiting the size of this antibody study, CDC and Navy authors limited the number of other possible early cases the study might have identified.
At least four other crew members who tested positive for antibodies (six in total) self-reported symptoms before the ship arrived at port in Vietnam Mach 5-9.
Twelve crew members who later tested positive for antibodies self-reported symptoms 41 or more days before giving blood for their antibody tests. Again, if the study size was much larger, many more sailors would have likely reported “symptom onset” dates before the ship’s port of call in Vietnam, as well as other crew members who were perhaps infected prior to January 20, 2020.
MORE DISCUSSION …
I can’t say the Navy/CDC “concealed evidence” of early spread because the information that made me suspect this is included in the study. Indeed, the key information is depicted on a graph (“Figure 3”) of the study. Also, text in the study makes this conclusion almost impossible to miss. For example:
“Among 12 participants with positive ELISA results >40 days after symptom onset, eight maintained positive microneutralization test results, including two participants who were tested >3 months after symptom onset.”
The Roosevelt antibody study, which was published online on June 8, was covered by prominent news organizations, including The New York Times and Reuters. The NY Times actually put the key information in its sub-headline:
Headline: “After Outbreak on Carrier Roosevelt, Many Have Antibodies”
Sub-headline: “A C.D.C. study found that some sailors showed protection against the coronavirus three months after the onset of symptoms”
FWIW, the sub-headline is not entirely accurate as 99 and 98 days would be “more than three months” after onset of symptoms. I mention the Times’ headline only to point out that no Times’ journalist or editor seems to have figured out that the first known case in America could have been a member of this ship (although the newspaper’s own headline should have told them this).
The story also quotes the study’s corresponding author Daniel Payne, who highlighted the fact some crew members had apparently had Covid antibodies for several months. (I have requested an interview with Dr. Payne).
“This is a promising indicator of immunity,” said Daniel C. Payne, an epidemiologist and one of the lead authors of the study … “We don’t know how long-lasting, for sure, but it is promising.”
Previous stories mentioned the growing number of “positive cases” on the ship, but none reported anywhere close to 60 percent of the crew being infected. For example, by April 21 (one day after the antibody tests had begun), 678 sailors had tested positive via a PCR test (14.1 percent of the crew).
Reuters’ journalist correctly highlighted the fact the study’s “results could indicate a far higher presence of the coronavirus.”
However, the journalist seems to de-amplify the significance of such a large percentage of positives with this latter text:
“… one of the Navy officials said that may not be the case because of the way the study was carried out … The outbreak investigation did not encompass the entire crew, and the results of this study cannot be generalized to the entire crew,” the official said.
The article later includes this disclaimer: “Medical groups, such as the American Medical Association, have warned that serology tests can lead to false positives.”
Like all journalists who wrote articles about this study, the Reuters reporter never asked why the project didn’t encompass the entire crew nor does this journalist question the assumed predicate (that a larger sample might have produced lower antibody-positive percentages than the study/sample that was performed. As noted, a sample of almost 100 percent of French sailors produced the identical percentage of antibody positives – 60 percent).
Nor do the journalists challenge the AMA’s statement that antibody tests “can” produce “false positives.” The author and the AMA could have noted, accurately, that serology tests “can” also lead to false negatives.
That is, if antibody tests are producing more “false negatives” than “false positives,” serology “prevalence” percentages in many/most antibody studies might be even higher than reported.
Such (requisite?) sentences support my belief that any antibody test that suggests much higher percentages of “early” cases will be routinely maligned or spun as being somehow insignificant.
One of the most disturbing take-aways from my “early spread” research is that, as far as I can tell, 100 percent of mainstream or corporate journalists, are not going to investigate credible evidence of early spread.
I understand why government and public health officials might want to cover-up evidence their “virus-origins” narrative was wrong all along, but I don’t understand why the “skeptical, watchdog” press would participate in what must be a massive conspiracy to conceal the truth.
I’ve harvested too much previously-unreported information from my research into Navy ship antibody studies to include in one article. Future articles will highlight other findings which have received little or no scrutiny to date – findings I believe deserve scrutiny, even if belated.
***
AUTHOR’S NOTE: Anyone with relevant information about the outbreak on the Roosevelt or any Naval vessel can email the author at: wjricejunior@gmail.com.
I would be very interested to hear from any Roosevelt crew members. Confidentiality will be protected.
The “Wellness-to-Fascism Pipeline” Baffles Experts as Truth Marches On
Congregating and Caring about Your Health is Dangerous to our Democracy
BY IGOR CHUDOV | AUGUST 13, 2023
Be careful with your workouts! An article from the Guardian alerts us to a “wellness-to-fascism pipeline.”

“People who study conspiracy theories” are worried that joining gyms and trying to get healthy makes people descend into what these experts describe as fascism, explains author James Ball.

James has a peculiar idea of what fascism is, however:

According to James, only fascists question masks, lockdowns, or the BBC. Good people mysteriously become “fascists” when they join gyms or look after their wellness.
Some of the most dangerous people, believe it or not, are personal trainers!
Some people’s problems escalated when their personal trainer learned about their work. “I had three successive personal trainers who were anti-vax. One Belgian, two Swiss,” I was told by a British man who has spent most of the past decade working in Europe for the World Economic Forum, which organises the annual summit at Davos for politicians and the world’s elite.
The poor WEF chap above was even dropped by his personal trainer when his employment at the WEF was revealed:
When the trainer found out the man worked for the World Economic Forum, he was immediately cut off.
Most worryingly for the “conspiracy expert” Peter Knight, people of all political persuasions, right or left, end up in the same place when they realize that “everything is a lie”:

Peter Knight has the strangest explanation, by gender, as to why people “get sucked into conspiracy theories.”
He explains that men are drawn into conspiracies because of the “involuntary celibacy” movement.
It is not that difficult to imagine why young men hitting the gym might be susceptible to QAnon and its ilk. This group spends a lot of time online, there is a supposed crisis of masculinity manifesting in the “incel” (involuntary celibacy) movement and similar, and numerous rightwing influencers have been targeting this group.
Mind you, at the beginning of the article, James Ball discussed how personal trainers are the superspreaders of conspiracies. Have you ever seen an involuntarily celibate gym personal trainer?
His explanation of why women believe the same theories could not be more different! Women, it turns out, believe the same conspiracies as men because of the “female data gap”!
“Far too often, we blame women for turning to alternative medicine, painting them as credulous and even dangerous,” she says. “But the blame does not lie with the women – it lies with the gender data gap. Thanks to hundreds of years of treating the male body as the default in medicine, we simply do not know enough about how disease manifests in the female body.”
There is a much simpler explanation as to why people believe the “Covid was lab-made” conspiracy theory, “Covid vaccine does not work” conspiracy theory, or “15-minute cities are promoted by the World Economic Forum” theory.
The explanation is that these theories are true. Both genders are capable of critical thinking, seeing the truth, and sharing it.
This simple explanation does not insult millions of thinking men by portraying them as “incels,” nor does it portray women as stupid creatures confused by the imaginary “gender data gap.”
Trying to find explanations for complicated but important events affecting us and not believing dishonest press is not fascism. God gave us brains for a reason – to think for ourselves! Critical thinking is the opposite of fascism, which requires uncritical obedience to the state ideology.
Despite its stupidity, the Guardian’s article exposes the most important social network that the press, fact-checkers, and the powers-to-be cannot control.
This social network is people physically and directly interacting with each other and sharing news and opinions.
It cannot be suppressed by means other than drastic lockdowns, which kept people at home in 2020. The gyms, far from being uniquely instrumental in developing critical thinking, are simply places where people congregate and share stuff while doing something pleasant. Thus, not surprisingly, gym-goers share explanations of current events with their peers without any censorship or any algorithmic intermediary.
The Guardian recognizes this:
Society’s discussion of QAnon, anti-vaxxers and other fringe conspiracies is heavily focused on what happens in digital spaces – perhaps too much so, to the exclusion of all else. The solution, though, is unlikely to be microphones in every gym and treatment room, monitoring what gets said to clients.
The conspiracy experts are baffled by this development and ironically blame “isolation,” even though the phenomenon they observe is rooted in physical interaction between people:
Jane has her own theory as to why her wellness group got radicalised and she did not – and it’s one that aligns with concerns from conspiracy experts, too. “I think it’s the isolation,” she concludes, citing lockdown as the catalyst, before noting the irony that conspiracies then kick off a cycle of increasing isolation by forcing believers to reject the wider world.
“It becomes very isolating because then their attitude is all: ‘Mainstream media … they lie about everything.’”
I do not think of myself and my dear subscribers as isolated: we congregate here, we read newspapers, although critically, and we interact with friends or relatives. Anyone can say anything they want in the comments. Am I wrong?
The Jab Or Not The Jab
Tactics and strategy in our irregular war
By Emanuel E. Garcia, M.D. | August 11, 2023
Those of us in the ‘resistance’ or ‘opposition’ — we skeptics who question and have questioned the covidian debacle and all of its accoutrements — seem inevitably to fall into discussions about the Jab. Deaths, adverse events, excess mortality, turbo cancers, immune dysregulation — you name it — but it is almost as if the Jab is some kind of black hole with a gravitational pull that sucks us all in and, in the end, directs our tactics and strategy rather monomaniacally for dealing with the Covidian Onslaught.
Let me be clear about my own position. From the beginning, when Covid Mania swept across the world, I felt that there was never a need for a vaccine of any kind.
Why?
First, because the illness or conglomeration of symptoms that appeared to be the result of a contagious pathogen was never as lethal as the Corporate Media led us to believe. It was, in fact, no more lethal than a bad flu, as eminent epidemiologist John Ioannidis demonstrated relatively early. Second, because treatments for the illness had also been developed and appeared to have been quite successful. Third, because I had faith in sound preventive measures such as sunlight, exercise, nutrition, the vitamins C and D, among others, as well as the wisdom and strength of our natural immune response.
During one interview I said, in fact, that the only way I would receive the Covid Jab would be if I were shot dead first.
As events unfolded in 2020 and beyond, the push for the Jab as the only way out of the pandemic that never really was, became quite intense. Big Pharma could certainly smell the massive profits, profits guaranteed by agreements that absolved these manufacturers from any harms associated with their product, and governments around the world colluded by seducing, cajoling and then, ultimately, coercing people into receiving the one-size-fits-all solution.
At first they told us the Jab was our only way out, and that it prevented us from getting, transmitting and dying from Covid. The Jabs of course did nothing of the sort. Their mechanisms of action, which included tampering with our genome and manufacturing a spike protein in numbers far exceeding what could occur with a natural infection, bespoke disaster. And, indeed, disaster has befallen and disaster will, I am certain, only worsen, for those who were either naive, terrified, gullible, stupid or indifferent enough to queue up for inoculations, and for those who were coerced into receiving them upon pain of loss of income and loss of inclusion in society.
The Jab, however, disastrous as it is, is but one of a number of instruments employed to do us harm.
Let’s not forget the effects of the lockdowns, masking, ‘social’ distancing; let’s not forget the active suppression of early treatment; let’s not forget the demolition of small businesses and the upwards transfer of trillions to the already super-rich; let’s not forget the ceaseless and unremitting drumbeat of fear; let’s not forget how our medical and governmental institutions betrayed our trust; let’s not forget the intrusions upon our privacy and our bank accounts, and the stalwart push for universal health passes and digital identification.
We are, and have been, buffeted on many fronts, with a single end in sight for those in the Globalist Mafia Cartel who have been doing the buffeting: murder and enslavement.
How may we, who can see the agenda, best combat the onslaught? Is it by showing over and over the many instances of Jab-related adverse events and sudden deaths? Or is it by planting our stake in the ground in defense of basic human rights and freedoms?
I have argued and continue to argue that there will always be another Jab — in fact, there will be a plethora of Jabs in our future. The more fundamental and abiding issue is preservation of our unalienable rights to physical and mental sovereignty and freedom of expression.
We must understand that this massive and unique Covid psyops, global in scope and relentless in pressure, has been deviously constructed to be impervious to logical rebuttal. For example, a neighbour of mine who nearly died from a blood clot, was told by her doctors not that the Covid Jab may have been a causative factor, but that Covid itself was. In the face of our rightful assertions that the Covid Jab is dangerous, a Jab recipient who is healthy will think we’re crazy, thanks to fate, human individuality and resilience, and/or variable Jab batches.
It is now time for us to draw the larger picture for those who are sitting on the fence or wandering the pastures on its other side. The larger picture of how the Few are oppressing the Many, of how the rights we are born with — rights not conferred or bequeathed by governments — are being trampled, and how censoring dissident and questioning voices is never and has never been the work of democratically-oriented societies.
At the Parliament Protest of 2022 here in Wellington, New Zealand, people from all walks and echelons of the citizenry came together, in unity, against the unlawful and unjustifiable imposition of mandates, against the usurpation of our most cherished, fundamental and precious human inheritance: autonomy and freedom.
Directing our energies to this transcendent matter, the matter of preserving autonomy and freedom and choice, is paramount — and positive — and far more likely to breach the resistance of sleepwalkers than a focus on the perils of the Jab which they themselves have taken so readily, given their unshakable and unquestioning belief in the wondrous benevolence of vaccine medicine.
Let’s get started, let’s emphasize freedom and social connections and a new way of healing and let us, in so doing, lead by example.
Sen. Ron Johnson Says Pandemic “Preplanned By An Elite Group Of People” Who Conducted “Event 201”
By Tyler Durden | Zero Hedge | August 13, 2023
And now, better late than never, a US politician recognizes that all may not have been what it seemed with the pandemic – and its tyrannical response.
Senator Ron Johnson on Friday told Fox Business’ Maria Bartiromo that Covid-19, and its response, were “preplanned by an elite group of people” who conducted “Event 201” – a joint exercise conducted by John Hopkins, the Bill and Melinda Gates Foundation and the World Economic Forum – which envisioned the spread of a coronavirus pandemic in South America which included over 65 million deaths worldwide.
The simulation concluded that national governments are nowhere near ready for a pandemic.
“We are going down a very dangerous path, but it is a path that is being laid out and planned by an elite group of people that want to take total control over our lives, and that’s what they are doing, bit by bit,” said Johnson, who sits on the Senate Homeland Security Committee and is a ranking member of the Senate Permanent Subcommittee on Investigations.
To which Bartiromo responded: “It is just extraordinary to me that the government was working with social media to amplify lies and suppress truth and has been doing so repeatedly. We just saw the Facebook story, the Twitter files, all of the all the way, government officials from the CDC, FBI, you know CIA, a thousand people according to the reporters working on the Twitter files, worked with social media to amplify lies and suppress truth.
Why couldn’t the American people know that, you know, there were other alternatives to treat Covid why can’t American people know there were side effects with the vaccine?
Johnson then said: “This is all preplanned by an elite group of people, that is what I am talking about, Event 201 occurred in late 2019, prior to the rest of us knowing about the pandemic. Again — this is very concerning in terms of what is happening, what continues to be planned for our loss of freedom,” adding “ It needs to be exposed but unfortunately, very few people even in Congress are willing to take a look at this. They all pushed the vaccine, they don’t want to be made aware of the fact that vaccines might have caused injuries or death, so many people simply just don’t want to admit they were wrong and they’re going to do everything they can to make sure they’re not proven wrong.”
“We are up against a very powerful group of people here, Maria.”
Watch:
Featured Video

“Historic Russia”: The Land Putin Will Not Give Back
or go to
Aletho News Archives – Video-Images
Book Review
Why the War on Conspiracy Theories Is Bad Public Policy
By Kevin Barrett • Unz Review • February 1, 2019
 A Review of Conspiracy Theories and Other Dangerous Ideas by Cass Sunstein (based on an earlier paper co-authored with Adrian Vermeule); In Defense of Troublemakers: The Power of Dissent in Life and Business by Charlan Nemeth; and Conspiracy Theories and the People Who Believe Them, edited by Joseph E. Uscinski
On January 25 2018 YouTube unleashed the latest salvo in the war on conspiracy theories, saying “we’ll begin reducing recommendations of borderline content and content that could misinform users in harmful ways—such as videos promoting a phony miracle cure for a serious illness, claiming the earth is flat, or making blatantly false claims about historic events like 9/11.”
At first glance that sounds reasonable. Nobody wants YouTube or anyone else to recommend bad information. And almost everyone agrees that phony miracle cures, flat earthism, and blatantly false claims about 9/11 and other historical events are undesirable.
But if we stop and seriously consider those words, we notice a couple of problems. First, the word “recommend” is not just misleading but mendacious. YouTube obviously doesn’t really recommend anything. When it says it does, it is lying. … continue
Blog Roll
 Aletho News
- “Historic Russia”: The Land Putin Will Not Give Back
- How the Cambridge Analytica scandal still haunts Mark Zuckerberg
- The Ongoing Cancellation Campaign Against a Dissenting Academic in Norway
- Yemen and ‘the Houthis’: Challenging Sami Hamdi’s Narrative
- No, Christians did not invent Zionism
- AIPAC-led lobbying network opens branches in Cypriot, Greek parliaments
- Araghchi blasts ‘parasitic’ alliance as US taxpayers pay for Israel’s war on Iran
- Easy fix for Europe’s chaos? Stop fueling war against Russia
- Putin’s key remarks on peace talks and Europe’s ‘schizophrenia’
- Trita Parsi: Israel Set a Trap for Total War in the Region
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago

