Her Father Got COVID and Died — But She Believes the CDC, NIH and Hospital Protocols Are What Really Killed Him

By Michael Nevradakis, Ph.D. | The Defender | May 16, 2023
Ralph Marxen Jr. had just turned 70 and was enjoying life with his wife of 49 years, Lynda, and his adult children and grandchildren. The Minnetonka, Minnesota, native was in good health and, according to his daughter, Nicole Riggs, walked long distances daily and wasn’t on any medications.
In August 2021, several members of Riggs’ household contracted COVID-19, including, presumably, her parents. A week later, while most family members were recovering, Marxen’s condition deteriorated leading him to be admitted to Abbott Northwestern Hospital in Minneapolis on Aug. 23, 2021.
Marxen would never leave the hospital — he died there on Sept. 7, 2021.
During his stay, Marxen, who had not received a COVID-19 vaccine, was administered more than 50 medications, including remdesivir, vancomycin, fentanyl and midazolam, and in the days prior to his death, he was placed on a ventilator.
At the time of his death, Marxen had “multiple organ system failure including renal failure, endocarditis, hyperkalemia, MRSA [methicillin-resistant Staphylococcus aureus] pneumonia, MRSA bacteremia and sepsis,” Riggs said.
Riggs told The Defender the treatments she and her family requested for Marxen, including ivermectin, monoclonal antibodies and vitamins, were refused.
She said she did not believe her father’s refusal of the COVID-19 vaccines played a role in his illness — in fact, she argued that her father’s non-vaccinated status — and the COVID-19 protocols prescribed by the Centers for Disease Control and Prevention (CDC) and the National Institutes of Health (NIH) — were factors in the treatment he received from the hospital and its medical staff.
‘Is this a hospital or a prison?’
“My dad went to the ER seeking help for dizziness and nausea,” Riggs said. “He was 70 years old and took no daily meds. He was unvaccinated and refused to take their unreliable PCR tests.”
In a separate interview with Minnesota’s Alpha News, Riggs said that two of her father’s friends had gotten vaccinated “and they both got vax-injured.” As a result, “He was adamant that he was not going to get the vaccine.”
“I think this played a part in him not getting good care,” Riggs told The Defender.
Riggs recounted the chain of events that led her father to end up in the hospital.
“In the middle of August 2021, my household of four, plus my parents, became ill with fever and fatigue, and a few of us had chest congestion,” Riggs said. “Myself, my husband and my two boys were spit-tested for COVID and were all told we were positive for COVID. We assumed my parents had the same.”
But after a week of being sick, she said they noticed that her father “didn’t seem to be bouncing back like the rest of us. He was having trouble walking to the bathroom because he was so weak and dehydrated.”
Due to his older age, his family “decided to call the ambulance and get him checked out,” Riggs said. Paramedics recommended Marxen go to the hospital for further evaluation, so he was admitted on Aug. 23, 2021, after an ER visit.
“From the beginning, the medical records indicate they wanted to get him on remdesivir even though they couldn’t get him to PCR test,” Riggs said.
“Within a day, a friend of the family who had been working with COVID patients for the past year told us to call the hospital and request that my dad be given monoclonal antibodies (a.k.a. Regeneron),” Riggs said. However, the nurse treating her father said he “had never heard of that before, and that was the end of that discussion.”
“That seemed strange to me, but I still trusted them at that time,” Riggs said.
The day after her father was admitted to the hospital, her mother also was admitted, after her oxygen levels dropped to the low 90s.
“My parents were soon hospital room neighbors,” Riggs said. “COVID medications were started, which we later learned was hospital protocol with remdesivir and dexamethasone.”
Despite being in neighboring rooms though, Riggs’ parents could not visit each other. “My mom wanted to go see my dad since he was in the room right next door, but she realized that her bed had an alarm that sounded when she tried to get up. She also learned that both of them were locked in their rooms as well,” Riggs said.
She added:
“My mom’s nurse thought ‘it wasn’t appropriate,’ and refused to let her go see my dad. They had to wait until that nurse was off her shift before the doctor would OK my mom to go into my dad’s room for a short visit.
“Is this a hospital or a prison?”
It wasn’t long before Riggs began to receive more disturbing updates about the treatment her parents were receiving in the hospital.
She told The Defender :
“My brother started a CaringBridge site to keep our whole family updated. It wasn’t long before I started to receive unsettling messages from people I knew and trust. One was from my dad’s old neurological chiropractor, saying ‘no remdesivir and no ventilator, that’s asking to die.’ He also sent me information on how to get a lawyer involved.
“It was then that I started to research and realize the dangers of the deadly hospital protocols put in place by the NIH and CDC, especially for those on Medicare, as the hospital is given a 20% bonus payment if certain steps are followed with those patients, starting with a positive COVID PCR test.”
According to Riggs, this was evident in her father’s medical records.
“One of the doctors actually wrote this in the medical records: ‘I don’t think it’s impossible to use remdesivir without a PCR positive,’” Riggs said, adding, “My dad initially refused a nasal PCR test because he knew they could be inaccurate and wanted to be treated by symptoms, not a PCR positive COVID test result.”
However, the hospital told Marxen and his family this was not possible. According to Riggs, the doctor said, “Certain treatments may not be available without PCR-proven COVID, and that if his condition worsened such that he required intubation, we would run the nasopharyngeal swab.”
“Basically, my dad was told he wouldn’t get access to ‘certain treatments’ until he submitted to their request to be PCR tested,” Riggs said. “And if he got bad enough, they would test him anyway.”
The hospital also told them if Marxen’s condition deteriorated enough that they needed to put him on a ventilator, they would do the test without his permission.
Her father finally “relented” and tested positive for COVID-19. That’s when the hospital administered remdesivir “and many other harmful drugs,” Riggs said, and denied their request for safer alternatives.
‘It all happened so fast’
From this point forward, “It all happened so fast,” Riggs said. Her father was transferred to progressive care on Aug. 26, 2021, and to the ICU the next day.
“My dad was denied visitation by anyone under the guise of ‘COVID isolation,’” Riggs said. “Even my mom, who was in the same hospital with COVID.”
Marxen’s condition quickly deteriorated. “My dad was told he needed to get on the ventilator so he could get relief and a feeding tube,” Riggs said. “By this time, my dad hadn’t slept in two days and hadn’t eaten in five days.”
“After two days in the ICU, he was freaking out, pulling off his mask and pulling out his IV,” Riggs said. “They got him ‘reoriented’ and brought in the doctor. If you knew my dad, you would know that this was totally out of character for him. He was the kindest, most loving man and father. He was one of my best friends.”
“Soon, he felt he had no other option but to be put on a ventilator,” Riggs said. “A decision he had to make scared and alone because we were kept from him … They had finally got him desperate enough to submit to getting on a ventilator.”
Marxen was intubated on Aug. 29, 2021, and placed on fentanyl and propofol, Riggs said, “even though, reading the records, they knew that wasn’t the solution, but they did it anyway.”
Riggs said she and her family again requested monoclonal antibodies be administered, “but were denied because it was too late in the progression of the disease to be a benefit.”
They also requested “vitamin C, vitamin D, zinc, hydroxychloroquine, ivermectin,” but were denied “and told they refused to go off of protocol, ‘because the one time we did that, the patient died,’” Riggs added.
“My dad’s medical records indicate vitamin D was ‘deemed not appropriate during this admission,’” Riggs noted. “We asked them to take him off vancomycin because that can make you retain fluid and he was already doing that. They told us no, and that the drug was ‘the gold standard.’”
‘He was kept from everyone that truly loved him’
According to Riggs, she would call the hospital every day at 6 p.m. for updates, and her brother would do so daily at 6 a.m. This continued until Sept. 7, 2021, the day her father would be placed “off quarantine” and allowed to see family members again.
However, “on Sept. 7, we were told that the ‘infectious disease team’ said he needed another seven days of quarantine,” Riggs said. “This decision was not even made by his ICU doctor.”
Instead, Riggs and her family were told “the nurses would set up a Facetime for us for the evening of Sept. 7,” Riggs said. “After that call, I was crying and pacing in my house. My thoughts were, ‘Are we going to just leave him in there to die alone?’ I needed to actually do something.”
Riggs said she decided to request her father’s medical records from the hospital, “so I could see exactly what was going on there.” However, she was told the records could not be released “unless he signed the release form” — even though her father was sedated and on a ventilator “and it wasn’t possible for him to sign anything.”
In response, the hospital told Riggs that she “would need to provide his death certificate for the records if we hadn’t already set up power of attorney.”
“So, he had to die before I could access his records?” Riggs asked. “How did this nightmare become our reality?”
Within a few hours of this exchange, Riggs received a call that her father was “actively dying” and if they wanted to see him, they needed to do it soon, because he would pass away during that night.
“Now that he was dying, we were able to come see him — but hours before we couldn’t? This made zero sense to me,” Riggs said.
On arriving at the hospital, she and other family members “were required to wear space-like soft helmets, which made it impossible to even kiss my dad goodbye.”
According to Riggs, she and her family “gave the OK to remove him from the ventilator so we could pray scripture over him through his transition.”
“I thought removing him from the ventilator would cause him to pass away because he couldn’t live without it,” Riggs said. “But I can’t help but wonder if that’s really how it went down. His records show that he was given fentanyl at 5:10 p.m. and midazolam at 5:32 p.m. He passed away at 6:22 p.m.”
Riggs said the “official” cause of death was determined to be “respiratory failure with underlying COVID-19.”
When her father died, he had multi-system organ failure. Riggs said she did not believe her father died of COVID-19, but instead due to the CDC- and NIH-approved protocols.
“He was isolated and kept from everyone that truly loved him for 16 days,” Riggs said. “Then, under the guise of ‘palliative care,’ he was finished off with fentanyl and midazolam.”
According to Alpha News, the price tag from the hospital for the treatment her father received during those 16 days was $1.2 million.
A statement provided by Abbott Northwestern to Alpha News said the following:
“Allina Health respects the privacy of its patients and is unable to comment on specific patient care.
“We have great confidence in the exceptional care our medical teams provide to our patients, which is administered according to evidence-based practices by our talented and compassionate care teams.”
‘To honor my dad, I have put my grief into action’
Riggs said her father’s death had knock-on effects on her and her family.
“Now my mom, who survived remdesivir, can’t afford to keep their home,” Riggs said. “She had to sell almost all of their possessions accumulated over 50 years to move into one of the bedrooms of my two-bedroom home. Two of my boys … now share a bedroom in our living room.”
“She can hardly make the bed without being out of breath and she struggles mentally with what they endured and getting a grasp on her new life without my dad in it,” Riggs added.
Despite these challenges, Riggs said that “to honor my dad, I have put my grief into action,” getting involved in activism for victims of hospital protocol deaths.
Riggs is now the Minnesota chair of the FormerFedsGroup Freedom Foundation, a national coalition that has documented cases involving COVID-19 care protocols at hospitals.
“I don’t want the families … to be isolated and alone in their pain of losing their loved one,” Riggs said, adding that she has launched weekly Zoom calls for Minnesota families and survivors of hospital protocols, and is also launching in-person meetups.
Riggs also recently attended the Halt Hospital Homicide rally, which she described as the “first national rally for hospital protocol deaths.”
She drew parallels with those who died of COVID-19 vaccine injuries. “The vax-injured are ignored and not believed, just like those of us who have had a family member die or get injured by the hospital protocols,” she said.
“My dad, Ralph, will go on in our memories as a wonderful husband of 50 years, dad, grandpa and great-grandpa, as well as a fun fisherman and the best homemade French fry maker around.”
Michael Nevradakis, Ph.D., based in Athens, Greece, is a senior reporter for The Defender and part of the rotation of hosts for CHD.TV’s “Good Morning CHD.”
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
COVID Was Not Dangerous to Unvaccinated Pregnant Women
BY IGOR CHUDOV | MAY 11, 2023
Remember the endless media hysterics about COVID being “dangerous to unvaccinated pregnant women”?

A recent report MBRRACE-UK throws doubt on such statements. It covers 2018-2020, so the year of 2020 was a part of the COVID pandemic.
In the UK, in 2020 (before COVID vaccines), only NINE women died from (or with) COVID-19 during pregnancy or up to six weeks after giving birth.

Remember that in 2020, all pregnant women in the UK were unvaccinated. COVID was at its worst in 2020.
COVID was quite rampant in the UK at the time. According to Our World in Data, the UK had 94,194 COVID deaths in 2020. However, only nine deaths out of those involved pregnant women.
ONS reports that England and Wales had 613,936 live births in 2020.

So,
- Pregnant women’s COVID deaths (9 total) were less than one in ten thousand overall COVID deaths.
- Pregnant women’s deaths (9 total) were less than one in 68,000 (sixty-eight thousand) births.
- In other words, for every pregnant woman who died of COVID in 2020, over 68,000 did NOT die.
Every death is a tragedy, especially those of future mothers. Those nine deaths were tragic for the families involved. I am very sorry for each of the nine women who died with COVID in the UK in 2020. I am relieved, however, that the number of deaths among pregnant women was far less than what the media intimated.
Was COVID a great danger to pregnant women? The numbers above suggest that the chance of dying from COVID for unvaccinated women in 2020 was very remote, as there was less than one COVID death per 68,000 births.
To me, this cannot be considered “particularly dangerous.” Pregnant women are young (most are under 40), and Covid is not particularly deadly to that age category.
So, those who believed that COVID-19 puts future mothers’ lives at tremendous risk were lied to. Pregnant women were given false information to nudge them to get vaccinated.
We finally have the proof.
‘Absolutely Reckless’: NIH Allows EcoHealth Alliance to Resume Coronavirus Research
By Brenda Baletti, Ph.D. | The Defender | May 10, 2023
The National Institutes of Health (NIH) this week reinstated a controversial federal grant to EcoHealth Alliance to study the risk of bat coronavirus spillover.
EcoHealth is a New York-based nonprofit whose stated mission is to develop “science-based solutions to prevent pandemics and promote conservation.”
In 2014, EcoHealth received $3.7 million from the National Institute of Allergy and Infectious Diseases (NIAID) to study the risk of bat coronavirus emergence and the potential for outbreaks in human populations — research that included genetically manipulating coronaviruses to make them more infectious to humans.
At the time, Dr. Anthony Fauci was the director of the NIAID, which operates under the NIH.
Nearly $600,000 of the $3.7 million went to EcoHealth’s collaborator, the Wuhan Institute of Virology in China.
However, in April 2020, under the Trump administration, the NIH terminated EcoHealth’s grant over concerns the organization had violated the grant terms, using U.S. taxpayer money to fund gain-of-function research at the Wuhan lab.
EcoHealth on Monday announced that the NIH reinstated the grant, but with new terms, and that EcoHealth will collaborate with the Duke-National University of Singapore Medical School to study zoonotic coronaviruses “with the aim of being transparent about the study’s goals.”
Peter Daszak, Ph.D. — who secretly collaborated with Ralph Baric, Ph.D., and Fauci to steer the media and scientific community away from questions about whether COVID-19 could have originated in a lab — is EcoHealth’s executive director and principal investigator on the grant.
Rep. Morgan Griffith (R-Va.), who sits on the House Energy and Commerce Committee that found multiple serious violations by EcoHealth of the contractual terms and conditions of the 2014 NIH grant, said the decision to reinstate the grant was “absolutely reckless,” given the organization’s “negligence and breach of their contract with the NIH on the coronavirus research done at the Wuhan Institute of Virology (WIV).”
Francis Boyle, J.D., Ph.D., bioweapons expert and professor of international law at the University of Illinois, told The Defender he wasn’t surprised to see the grant reinstated.
“People involved in this, like EcoHealth Alliance, Fauci, the Biden administration, et cetera, know they have crossed the Rubicon and there is no turning back. And they don’t intend to turn back unless and until we stop them. It’s as simple as that,” he added.
Boyle, who authored the Biological Weapons Convention known as the Biological Weapons Anti-Terrorism Act of 1989 that was approved unanimously by both houses of the U.S. Congress and signed to law by President George Bush Sr., also added:
“Clearly, all this gain-of-function work is offensive biological warfare weapons work in violation of the convention and my biological weapons anti-terrorism act, the penalty for which is life imprisonment.”
In January, the Office of Inspector General in the U.S. Department of Health and Human Services (HHS) released a report outlining missed deadlines, confusing protocols and misspent funds in EcoHealth Alliance’s grant management, particularly as it related to the Wuhan lab.
In response, HHS set new terms for the four-year, now-$2.9 million NIAID grant, under which EcoHealth will receive $576,290 this year.
Under the new terms, EcoHealth is barred from conducting any research in China or collecting any new samples from vertebrates and must implement additional oversight of its finances and accounting practices.
The conditions also prevent EcoHealth from doing any work “involving enhanced potential pandemic pathogens,” although the organization can continue to work with “highly pathogenic agents” or “infectious agent[s] or toxin[s]” that may warrant a biocontainment safety level (BSL) of 3 or higher. The Wuhan lab was a BSL-4 lab.
EcoHealth is the recipient of 17 active U.S. government grants totaling more than $50 million, The Epoch Times reported.
Publications like Nature and Science celebrated the reinstatement of the grant. Nature said the research was “essential for preventing the next pandemic.”
Science wrote that the Trump administration called for the cancellation of the grant, “amid unsupported allegations that a lab leak at WIV started the COVID-19 pandemic.”
The origins of the COVID-19 virus continue to be debated, but evidence has emerged over the past several years that the “lab-leak theory” is a plausible hypothesis despite attempts to dismiss it.
Several U.S. agencies, former agency officials and independent scientists have concluded that a Wuhan lab leak most likely caused the COVID-19 pandemic. A U.S. Department of Energy report released in February and a Senate report released in April both arrived at the conclusion that COVID-19 likely stemmed from a lab leak.
Brenda Baletti Ph.D. is a reporter for The Defender. She wrote and taught about capitalism and politics for 10 years in the writing program at Duke University. She holds a Ph.D. in human geography from the University of North Carolina at Chapel Hill and a master’s from the University of Texas at Austin.
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Andrew Bridgen and Fraser Myers clash in fiery debate on Covid vaccine harms
GBNews | May 8, 2023
Andrew Bridgen, a Member of Parliament in the UK, has been vocal about vaccine harms and the origins of Covid.
Fraser Myers, deputy editor of Spiked online, published an article called “The delusions of Andrew Bridgen – Conspiratorial thinking corrodes reason, democracy and humanism”.
The pair joined Andrew Doyle on GB News in a fiery debate.
One Health: A Plan to ‘Surveil and Control Every Aspect of Life on Earth’?
This is part two of a two-part series on the One Health initiative. Read part one here.
By Michael Nevradakis, Ph.D. | The Defender | May 8, 2023
The World Health Organization (WHO) defines “One Health,” as “an integrated, unifying approach that aims to sustainably balance and optimize the health of people, animals and ecosystems,” as they are “closely linked and interdependent” — a concept that on the surface appears to promote noble goals interlinking human and environmental health.
However, some scientists and medical experts are concerned about One Health’s vague goals. Arguing that the concept has been “hijacked,” they question the intent of those involved with the development and global rollout of the concept — including the WHO, the Centers for Disease Control and Prevention (CDC) and the World Bank.
Experts who spoke with The Defender also raised questions about other aspects of the One Health concept, including a biosecurity agenda, a global surveillance system, vaccine passports and restrictions on human behavior.
While these goals are underpinned by a vaguely defined “Theory of Change,” experts told The Defender that major financial interests are at the heart of the One Health agenda, which appears to be closely linked to climate change and sustainable development initiatives promoted by the same global organizations.
One Health objectives include a ‘global takeover of everything’
In a May 1 article, Dr. Joseph Mercola connected the One Health concept, as promoted by global organizations, to the policies and restrictions pursued in response to COVID-19, describing it as an attempted “global takeover of everything.”
Mercola tied the One Health concept to key entities that have supported gain-of-function research. According to Mercola:
“Interestingly, the term ‘One Health,’ which was formally adopted by the WHO and the G20 health ministers in 2017, was first coined by the executive vice president of the EcoHealth Alliance, the same firm that appears to have had a hand in the creation of SARS-CoV-2.”
During the 2019 lecture “Can One Health Help Prevent the Next Pandemic?” EcoHealth Alliance President Peter Daszak, Ph.D., commissioner in The Lancet’s One Health Commission, said “emerging infectious diseases” are “a growing global threat.”
He also argued that many of these emerging diseases are “zoonotic — spread from animals to humans.”
Francis Boyle, J.D., Ph.D., professor of international law at the University of Illinois and a bioweapons expert who drafted the Biological Weapons Anti-Terrorism Act of 1989, questioned this narrative, telling The Defender :
“All these ‘emerging infectious diseases’ are emerging out of their offensive biological warfare weapons programs conducted in their BSL4 [biosecurity level 4] and BSL3 laboratories.
“If you look at the people on the WHO advisory committee dealing with ‘emerging infectious diseases,’ that’s exactly what they are doing — ‘emerging’ them from their labs.”
One example is that of Marion Koopmans, DVM, Ph.D., director of the WHO Collaborating Centre for emerging infectious diseases at Erasmus Medical Centre in the Netherlands and member of the WHO’s One Health High-Level Expert Panel (OHHLEP).
According to Boyle, “Erasmus is where this offensive Nazi biowarfare gain-of-function death science dirty work first became notorious under Fouchier, [who] started the entire controversy over his gain-of-function work there.”
Boyle was referring to Ron Fouchier, Ph.D., who also is deputy head of Erasmus’ Viroscience Department and who, according to Science, “alarmed the world” in 2011, after he and other researchers “separately modified the deadly avian H5N1 influenza virus so that it spread between ferrets” — an early example of gain-of-function research.
Dr. Meryl Nass, an internist and biological warfare epidemiologist who is a member of the Children’s Health Defense scientific advisory committee, said such objectives are kept deliberately vague. She referred to a CDC document that stated:
“Successful public health interventions require the cooperation of human, animal, and environmental health partners … Other relevant players in a One Health approach could include law enforcement, policymakers, agriculture, communities, and even pet owners.
“By promoting collaboration across all sectors, a One Health approach can achieve the best health outcomes for people, animals, and plants in a shared environment.”
Nass wrote on her blog, “I anticipate that One Health will be used to impose changes in the way humans and animals interact … most likely based on the needs of the WEF [World Economic Forum]/elites and not the needs of the people or the animals that will be affected.”
Reggie Littlejohn, founder and president of Women’s Rights Without Frontiers and co-chair of the Stop Vaccine Passports Task Force, told The Defender, “It’s not clear that One Health is prioritizing human health.”
Highlighting the “vague” language employed by the global organizations promoting One Health, Littlejohn said that one goal may be to “govern farm animal health in addition to human health,” through which “they could do things like forcing vaccines on livestock.”
One Health means ‘surveilling everything’
The experts who spoke with The Defender expressed concerns over the biosecurity agenda that is associated with the stated objectives of One Health.
According to Nass, this reflects how the WHO “has been changing into a biosecurity agency,” adding that “the justification, apparently, for the WHO’s director-general to take over jurisdiction of healthcare during pandemics, but also potentially ecosystems, animals and plants, is through One Health.”
Nass noted that One Health “is mentioned several times in the National Defense [Authorization] Act for Fiscal Year 2023” (NDAA), which includes 18 pages on “pandemic preparedness” and a formal definition of the “One Health approach” on page 952 of the act.
Independent journalist and researcher James Roguski also highlighted the prominent placement of One Health in the NDAA and noted that, by formally defining the concept within the act, it is now part of the Code of Federal Regulations.
However, Roguski said the NDAA goes even further:
“The U.S. has pledged a billion dollars a year to the World Bank Pandemic Fund in support of the global health security agenda. The WHO is one of 14 intermediaries who will receive and redistribute some of that billion dollars.
“Basically, it’s capitalism, it’s corruption, it’s an abomination from a health perspective. Let’s just throw money at pharmaceutical companies, build out the infrastructure in these nations and, if you’re making tons of products locally, you’re going to be able to convince the local government to stick them in people’s arms or shove it down their throat.
“And none of it really has shown to be of any health benefit. It’s damage to people’s health.”
Associated with the promotion of a global biosecurity agenda is the development of a global surveillance infrastructure that would purportedly protect human and animal health and the environment. An Oct. 3, 2022, WHO document states:
“The emergence of the SARS-CoV-2 virus that caused COVID-19 has underlined the need to strengthen the One Health approach, with a greater emphasis on connections to animal health and the environment …
“… It uses the close, interdependent links among these fields to create new surveillance and disease control methods. …
“We now have an unprecedented opportunity to strengthen collaboration and policies across these many areas and reduce the risk of future pandemics and epidemics while also addressing the ongoing burden of endemic and non-communicable diseases
“Surveillance that monitors risks and helps identify patterns across these many areas is needed.”
Remarking on this, Littlejohn said One Health’s proponents talk about “interoperable, integrated surveillance systems.” She told The Defender :
“I believe … these surveillance systems of people, animals, plants, and the environment are going to be coordinated by some kind of a global surveillance system that is interoperable globally and integrated.
“Whoever’s running this show, the WHO, the Chinese Communist Party … the Bill and Melinda Gates Foundation, who are the people who really appear to be running the show at the WHO, are going to be able to tap into and see all of our private information. Not just us, but animals and plants.”
Dr. David Bell, a public health physician and biotech consultant and former director of global health technologies at Intellectual Ventures Global Good Fund, told The Defender that what global organizations intend is “surveilling everything.” He said:
“It means surveilling everything, surveilling the climate for possible threats, surveilling animal population, surveilling wildlife, surveilling the soil to see if there’s new traces of virus or bacteria in river systems, et cetera.
“This allows you to ‘discover’ what we already know is nature, and then turn nature into a potential threat or into a threat. The more surveillance you have and the wider it is, the more inevitable ‘threats’ you’ll find … because you can make an argument that almost any new variant virus is a ‘threat.’
“It will allow them to keep a constant kind of fear which then allows you to introduce authoritarian controls such as central bank digital currencies and digital passports … that allow them to monetize the human population more effectively.”
Nass noted that global actors such as the WHO “talk about sharing of specimens during a pandemic … so they can try to make vaccines too. However, they don’t talk about performing surveillance on human beings. But what they did say, which let the cat out of the bag, is that they would want to get informed consent from countries for sharing of genomic data, rather than from individuals.”
Part of this surveillance infrastructure also would include vaccine passports, which figure prominently in the pandemic treaty and amendments to the International Health Regulations (IHR) currently under negotiation at the WHO.
According to Littlejohn:
“I believe that they laid the infrastructure during the COVID-19 crisis, and we’re having a little bit of a ‘break’ here between pandemics, but that structure, that infrastructure is going to snap shut with the next pandemic if we don’t stop it. That structure has to do with vaccine passports.
“It could be called a ‘smart health card’ or ‘digital health ID,’ or even a mandatory digital driver’s license can serve as the platform for a China-style social credit system. And there’s a new bill in front of the Senate right now … the Improving Digital Identity Act of 2023 … It’s a mandatory national ID that’s going to be interoperable, coordinated, integrated and can serve as the same platform as China’s social credit system … to surveil us.”
Restrictions on human behavior could lower humans to the level of animals
The WHO’s Oct. 3, 2022, document also claimed that “Some 60% of emerging infectious diseases that are reported globally come from animals, both wild and domestic,” adding that “human activities and stressed ecosystems have created new opportunities for diseases to emerge and spread.”
Such stressors “include animal trade, agriculture, livestock farming, urbanization, extractive industries, climate change, habitat fragmentation and encroachment into wild areas,” according to the WHO.
“To the extent that carbon emissions due to transportation within cities would contribute to climate change, then the ‘15-minute city’ would be a way of addressing that,” Littlejohn said. “The danger is that they will enforce it by having surveillance cameras everywhere to make sure you don’t go outside of your district without permission.”
In a March 30 article, “Your Daughter for a Rat,” Bell cited a One Health editorial published in The Lancet stating that “all life is equal, and of equal concern.” In response, Bell suggested that One Health aims to lower humans to the level of animals.
The same Lancet article described One Health as “a call for ecological, not merely health, equity” and called for a “subtle but quite revolutionary shift of perspective” away from “anthropocentrism”: “All life is equal, and of equal concern.”
“It looks like this is going to be the justification for moving people down to the value of animals,” Nass said in response; a sentiment shared by Boyle, who said, “One Health relates the healthcare of human beings to the healthcare of animals and thus reduces healthcare for human beings to the level of healthcare for animals.”
According to Bell, “suggesting that we have a duty as a species on this planet to look after every species equally and treat them more equally [is] becoming sort of a religion or dogma. It defies what any rational society in the history of humanity” has practiced and is “a very unusual approach and potentially very scary.”
One Health: Follow the money
The WHO has attempted to give theoretical credence to the One Health concept by developing a so-called “Theory of Change” (ToC).
Although the WHO says the ToC is designed to provide “a conceptual framework” for “organisations, agencies and initiatives working towards similar One Health goals” and a “common narrative of coherence,” the theory itself does not appear to have a clear definition.
“They want to be able to do whatever they want,” Littlejohn said. “If you define it, then you can hold them to the definition … one of the tactics is just to be really obscure and incomprehensible.”
“This is a term that is used in these circles,” Bell added. “It’s stating the obvious, that if you do a certain act, you’ll have a certain outcome. It’s a fancy way of saying that.”
Bell also referred to the “fallacy that is being pushed that humans are having increasing contact with wildlife,” supposedly leading to “this threat of viruses jumping from wildlife to humans.”
Calling it a “ludicrous claim,” Bell said that “when humans move into wildlife habitats, the wildlife don’t start living with humans. They die out.”
Noting that “it used to be very common” for people to live with farm animals, Bell added that the claim that pandemics are becoming more common due to increased contact with animals is itself “not true,” but is “used to instill fear and to try to get people to buy into this One Health, constant health emergency agenda.”
Nass said One Health proponents “don’t actually have any evidence” to support their claims, offering the example of antimicrobial resistance in bacteria found in meat consumed by humans, as a result of antibiotics administered to livestock. “That’s been the hook that One Health has been hung on,” Nass said.
However, Nass said this problem “could be solved in a heartbeat if the U.S. Food and Drug Administration or the U.S. Department of Agriculture just told farmers they can’t put antibiotics into animal feed anymore, they can only use them when an animal gets sick.”
In his recent article, Mercola suggested following the money. “Private interests wield immense power over the WHO, and a majority of the funding is ‘specified,’ meaning it’s earmarked for particular programs. The WHO cannot allocate those funds wherever they’re needed most.”
As a result, this “massively influences what the WHO does and how it does it. So, the WHO is an organization that does whatever its funders tell it to do,” naming organizations such as the Gates Foundation as prime funders of the WHO.
Bell said that supporters of One Health include “those who have been pushing the COVID agenda … and enriching themselves from it,” including “private foundations who are on the bandwagon” and “corporations who stand to gain from controlling the food chain and controlling agriculture and pharmaceuticals, et cetera.”
“It’s corporate authoritarians that have benefited themselves from public health through COVID and the certainly inappropriate COVID response,” Bell added. “And it’s the same and it’s not disconnected with the climate emergency agenda.”
One prominent financial actor closely involved with the development of the One Health agenda is the World Bank, as WHO documents indicate.
At a November 2022 OHHLEP meeting, Franck Berthe, the World Bank’s senior livestock specialist, introduced the World Bank’s Financial Intermediary Fund, which would “allow countries to borrow funds to strengthen their health system and promote the OH [One Health] approach.”
According to Nass, “the WHO and the World Bank have helped form this financing operation for the biosecurity agenda,” while Boyle told The Defender, “There is nothing humanitarian about these backers and the WHO promoting the One Health agenda.”
Both Nass and Bell said the One Health agenda is closely tied to the UN’s Sustainable Development Goals and Agenda 2030. Bell said that the One Health agenda attempts to deal with a supposed “existential threat to human health” that “must be dealt with in a centralized way, rather than giving people a choice.”
One Health closely tied to WHO pandemic treaty, IHR amendments
Experts who spoke with The Defender also emphasized the connections between the One Health concept and the pandemic treaty and IHR amendments under negotiation.
Mercola wrote that through the One Health agenda, which recognizes “a very broad range of aspects of life and the environment [that] can impact health and therefore fall under the ‘potential’ to cause harm,” the WHO “will be able to declare climate change as a health emergency and subsequently require climate lockdowns.”
Roguski, who has extensively researched the pandemic treaty and IHR amendments, said that in amendments the EU recently proposed for the pandemic treaty, the term “One Health” appears 29 times, including calling upon countries to develop and regularly update pandemic prevention plans via the One Health approach.
Referring to the need to prevent potential “pandemic situations,” the proposals also call for strengthening global public health surveillance “using a One Health approach,” which will also “address the drivers of the emergence and re-emergence of disease at the human-animal-environment interface, including but not limited to climate change, land use change, wildlife trade, desertification and antimicrobial resistance.”
The proposals also suggest the One Health approach could be used “to produce science-based evidence, and support, facilitate and/or oversee the correct, evidence-based and risk-informed implementation of infection prevention and control,” and go as far as to suggest targets on “antimicrobial consumption/use.”
Roguski told The Defender that the latest draft of the pandemic treaty refers to One Health 13 times. Such language would “be used to take over complete control of our lives,” Roguski added.
For example, one proposal states, “Each Party shall, in accordance with national law, adopt policies and strategies, supported by implementation plans, across the public and private sectors and relevant agencies, consistent with relevant tools, including, but not limited to, the International Health Regulations, and strengthen and reinforce public health functions for: (c) surveillance (including using a One Health approach).”
Other proposals include:
“The Parties commit to strengthen multi-sectoral, coordinated, interoperable and integrated One Health surveillance systems … to identify and assess the risks and emergence of pathogens and variants with pandemic potential, in order to minimize spill-over events, mutations and the risks associated with zoonotic neglected tropical and vector-borne diseases, with a view to preventing small-scale outbreaks in wildlife or domesticated animals from becoming a pandemic.
“Each Party shall … develop and implement a national One Health action plan on antimicrobial resistance that strengthens antimicrobial stewardship in the human and animal sectors, optimizes antimicrobial consumption, increases investment in, and promotes equitable and affordable access to, new medicines, diagnostic tools, vaccines and other interventions, strengthens infection prevention and control in health care settings and sanitation and biosecurity in livestock farms, and provides technical support to developing countries.”
Roguski said the phrase “One Health” doesn’t directly appear in documents related to the proposed IHR amendments, but he added the WHO “is going to try to get them both to prevail,” referring to both the treaty and IHR amendments.
Littlejohn said, the One Health approach and the proposed language in the treaty “gives them the right to surveil and potentially control every aspect of life on earth.”
Noting that the proposed treaty also calls for a “commitment to counteract ‘misinformation,’ ‘disinformation,’ and ‘false news,’” Littlejohn added, “they’re going to surveil our social media … and if any of us steps out of line by contradicting what the WHO says, then we could be censored.”
“That’s what I think is in mind with this commitment to ‘coordinated, interoperable and integrated’ One Health surveillance systems,” Littlejohn added. “I think that’s how it could end up being deployed. Ultimately, globalist entities, such as the World Economic Forum and the UN are using the WHO as their way of establishing global control.”
“The reason that health is such a good pretext is that people can become terrified,” Littlejohn added. “To the extent that their minds are paralyzed if they think they could die or get really sick, they’re willing to give up freedoms that they would not be willing to give up in other contexts.”
Roguski told The Defender :
“They made a lot of bad decisions. They gave a lot of bad advice [and] they caused a lot of harm to a lot of people. You can’t just give those people more power, authority and control without looking at what they did and going, ‘no, you should not be in charge of any of this.’”
In turn, Mercola wrote that “The globalist takeover hinges on the successful creation of a feedback loop of surveillance for virus variants, declaration of potential risk followed by lockdowns and restrictions, followed by mass vaccinating populations to ‘end’ the pandemic restrictions, followed by more surveillance and so on.”
And according to Bell, One Health “is part of a much bigger picture of finding ways to pull apart the intrinsic ideas that most societies have been built on.”
“I think that this is part of a move to undo these sorts of ideas and to replace them with a sort of religion of fear of our surroundings and denigration of other humans that can then be used by very greedy people to increase their wealth and power,” Bell said. “It’s taken over public health to a large extent.”
Michael Nevradakis, Ph.D., based in Athens, Greece, is a senior reporter for The Defender and part of the rotation of hosts for CHD.TV’s “Good Morning CHD.”
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Biden regime & WHO finally realise nobody cares anymore, fold up last vestiges of the Covid circus
Polish health minister denounces Pfizer vax profiteering, amazingly asks if it is “only about money”
eugyppius: a plague chronicle | May 7, 2023
The Biden Administration have announced that their insane vaccine requirements for government employees and international travellers will finally end on 11 May, when the American pandemic state of emergency expires. The WHO have likewise declared that Covid-19 “no longer constitutes a public health emergency of international concern.” Three years and two months after it all started, the last remaining participants in the Covid circus are finally folding up their tables and going home.
It’s worth asking why now, because by any objective measure, there has been no virus activity worthy of the words ‘pandemic’ or ‘emergency’ for a very long time. The answer seems to be the failure of Corona to return in the winter, as long-absent influenza succeeded in suppressing Corona infections (in accordance with my prediction), and the increasing disinterest of the public in obtaining official test results has put all virus statistics in the toilet. They’re ending it now, in other words, not because anything on the ground has changed, but because they no longer have any hope of the scary headlines necessary to keep the machine up and running.
As in the beginning, so in the end: The pandemicists will give you always and forever the maximum virus suppression and the maximum vaccination that is politically possible. Not what is prudent, or what has any hope of achieving anything, or what has evidence in its favour, but simply the maximum that they can give you, for as long as they can give it to you. That is a reason in itself, never to let the pandemicists anywhere near the levers of power ever again.
The pandemic may be over, but there is no stopping the vaccines. Thanks to the incredibly stupid contracts that the EU concluded with Pfizer/BioNTech, we are drowning in them, and some of our less prosperous neighbours to the east have had enough:
With the Covid vaccination campaigns concluded, the European Union is sitting on an enormous vaccine surplus – and hundreds of millions more doses are expected to arrive this year and next… Because they are not needed, EU member states have been trying for months to retroactively adjust the contracts, without much success.
One country has now lost patience in the face of the tough negotiations, and is venting its anger. The Polish Health Minister Adam Niedzielski on Tuesday sent a letter to the “shareholders of Pfizer” [which] says that the delivery of hundreds of millions of doses planned by Pfizer despite a “stable epidemic situation” is “completely pointless.”
The excess doses can no longer even be given away; there is no government “interested” in Covid vaccines, said the minister …
Niedzielski also breaks prior agreements on the confidentiality of talks between governments, pharmaceutical companies and the mediating EU Commission … [and] reveals what Pfizer is offering the states: They’ll reduce the total quantity of the outstanding orders, in exchange for half the price of each dose that is not produced: “That’s a charge for literally non-existent doses that were never produced and will never be produced and that don’t cost Pfizer a penny.”
No wonder there has been such urgency to keep these negotiations secret.
Niedzielski writes that he is “extremely” sorry, but he is forced to conclude that the company is not prepared to show “a satisfactory level of flexibility and make any realistic proposals.” … The health minister called on Pfizer to “live up to its responsibility towards EU citizens and member states and work in good faith towards a solution that is fair for everyone.” Poland wants to continue to believe that the pharmaceutical industry is not only about money.
Hahhhahahahahahhhahahhhahahahahhahhahahhahhaha.
Video source
WHO Denies Pandemic Treaty Will Reduce Sovereignty of States – But it’s Pure Propaganda
BY DR DAVID BELL | THE DAILY SCEPTIC | MAY 6, 2023
The Director General of the World Health Organisation (WHO) reassures us that the WHO’s ‘pandemic accord’ (or ‘treaty’) won’t reduce the sovereignty of Member States. The WHO trusts that these words will serve as a distraction from reality. Those driving the perpetual health emergency agenda are planning to give WHO more power, and states less. This will happen whenever WHO designates a ‘Public Health Emergency of International Concern’ (PHEIC), or considers we may be at risk of one.
The WHO’s proposed treaty, taken together with its ‘synergistic’ amendments to the International Health Regulations (IHR), aim to undo centuries of democratic reform that based sovereignty with individuals, and by extension their state. The discomfort of facing this truth and the complexities it raises is providing the cover needed to push these changes through. This is how democracy, and freedom, wither and die.
Why it’s hard to acknowledge reality
Our society in the West is built on trust and a feeling of superiority – we built the institutions that run the world and they, and we, are good. We consider ourselves humanitarians, the public health advocates, the unifiers, and anti-fascist freedom-lovers. We consider our system is better than the alternatives – we are ‘progressive’.
It takes quite a step for comfortable, middle-income, Left-leaning professionals to believe that the institutions and philanthropic organisations we have admired all our lives might now be pillaging us. Our society relies on having ‘trusted sources’, the WHO being one of them. Among others are our major media organisations. If our trusted sources told us we were being misled and pillaged, we would accept this. But they are telling us these claims are false, and that all is well. The WHO’s Director General himself assures us of this. Anyone who thinks rich corporate and private sponsors of WHO and other health institutions are self-interested, that they might mislead and exploit others for their own benefit, is a conspiracy theorist.
We are all capable of believing the rich and powerful of past ages would exploit the masses, but somehow this is hard to believe in the present. For proof of their benevolence, we rely on the word of their own publicity departments and the media they support. Somehow, malfeasance on a grand scale is always a figment of history, and now we are smarter and enlightened.
Over recent decades we have watched individuals accumulate wealth equivalent to medium-sized countries. They meet our elected leaders behind closed doors at Davos. We then applaud the largesse they bestow on the less fortunate, and pretend all this is fine. We watch as corporations expand across national borders, seemingly above the laws that apply to ordinary citizens. We allowed their ‘public-private partnerships’ to turn international institutions into purveyors of their commodities. We ignored this descent because their publicity departments told us to, becoming apologists for obvious authoritarians because we want to believe they are somehow doing a ‘greater good’.
Whilst a schoolchild might see through this facade to the conflicted greed beyond, it is much harder for those with years of political baggage, a peer network, reputation and career to admit they have been duped. The behavioural psychologists that our governments and institutions now employ understand this. Their job is to keep us believing the trusted sources they sponsor. Our challenge is to put reality above right-think.
The remaking of WHO
When the WHO was set up in 1946 to help coordinate responses to major health issues, the world was emerging from the last great bout of fascism and colonialism. Both these societal models were sold on the basis of centralising power for a greater good. Those who considered themselves superior would run the world for those less worthy. The WHO once claimed to follow a different line.
Since the early 2000s WHO’s activities have been increasingly dictated by ‘specified funding’. Its funders, increasingly including private and corporate interest, tell it how to use the money they give. Private direction is fine for private organisations promoting their investors’ wares, but it is obviously a non-starter for an organisation seeking to mandate medicines, close borders and confine people. Anyone with a basic understanding of history and human nature will recognise this. But these powers are exactly what the amendments to the International Health Regulations and the new treaty intend.
Rather than consider alternate approaches, WHO is seeking censorship of opinions not fitting its narrative, publicly denigrating and demeaning those who question its policies. These are not the actions of an organisation representing ‘we the people’, or confident in its ability to justify its actions. They are the trappings we have always associated with intellectual weakness and fascism.
WHO’s impact on population health
In its 2019 pandemic influenza recommendations, WHO stated that “not in any circumstances” should contact tracing, border closures, entry or exit screening or quarantine of exposed individuals be undertaken in an established pandemic. It wrote this because such measures would cause more harm than good, and disproportionately harm poorer people. In 2020, in conjunction with private and national sponsors, it supported the largest wealth shift in history from low to high income by promoting these same measures.
In abandoning its principles, WHO abandoned millions of girls to nightly rape through child marriage, increased teenage pregnancies and child mortality, reduced childhood education, and grew poverty and malnutrition. Despite most of these people being too young to be troubled by Covid and already having immunity, they promoted billions of dollars of mass vaccination whilst traditional priorities such as malaria, tuberculosis and HIV/AIDS deteriorate. Western media have met this with silence or empty rhetoric. Saving lives does not turn a profit, but selling commodities does. The WHO’s sponsors are doing what they need for their investors, whilst WHO is doing what it needs to keep their money flowing.
The new powers of WHO
The IHR amendments will reduce the sovereignty of any WHO Member State that fails to actively reject them, giving a single person (the Director General) direct influence over health policy and the freedom of its citizens is indisputable. It is what the document says. Countries are required to “undertake” to follow the WHO’s “recommendations”, which are no longer simply suggestions or advice. Whilst the WHO does not have a police force, the World Bank and IMF are on board, and control much of your money supply. The U.S. Congress passed a bill last year recognising that the U.S. Government should address countries that do not comply with the IHR. We are not witnessing toothless threats; most countries, and their people, will have little choice.
The real power of the WHO’s proposals is in their application for any health-related matter they proclaim to be a threat. The proposed amendments state this explicitly, whilst the ‘Treaty’ expands the scope to ‘One-Health‘, a hijacked public health concept that can mean anything perceived to be affecting human physical, mental or social well-being. Inclement weather, crop failures or the promulgation of ideas that cause people stress – everyday things that humans have always coped with, now become reasons to confine people and impose solutions dictated by others.
In essence, those sponsoring WHO are manufacturing crises of their own desiring, and are set to get wealthier from other’s misery, as they did during Covid. This under the guise of ‘keeping us safe’. As WHO implausibly insists, “no one is safe until all are safe”, so removal of human rights must be broad and prolonged. Behavioural psychology is there to ensure that we comply.
Facing the future
We are building a future in which compliance with authoritarian dictates will win the return of stolen freedoms, whilst censorship will suppress dissent. People who wish to see evidence, who remember history or insist on informed consent will be designated, in WHO parlance, far-Right mass killers. We have already entered this world. Public figures who claim otherwise are presumably not paying attention, or have other motivations.
We can meekly accept this new disease-obsessed world, some may even embrace the salaries and careers it bestows. Or we can join those fighting for the simple right of individuals to determine their own future. At the very least, we can acknowledge the reality around us.
Dr. David Bell is a clinical and public health physician with a PhD in population health and background in internal medicine, modelling and epidemiology of infectious disease. Previously, he was Programme Head for Malaria and Acute Febrile Disease at FIND in Geneva, and coordinating malaria diagnostics strategy with the World Health Organisation. He is a member of the Executive Committee of PANDA.
Unrepentant Corona arch-villain Christian Drosten re-emerges to give the vaccines credit for ending the pandemic
Insists that lockdowns and school closures remain policy options in the future

Virus-understander-in-chief Christian Drosten posing as a scrappy compassionate avatar of The Science, rather than the conniving and perpetually wrong loser that he is.
eugyppius: a plague chronicle | May 6, 2023
That eternal turd who will not flush, Christian Drosten, has resurfaced with an odious media interview, demanding that the vaccines receive credit for ending the pandemic and that oppressive non-pharmaceutical interventions like lockdowns and school closures remain on the table for future pandemics.
From Tagesspiegel :
The measures taken by the federal and state governments in the Corona pandemic proved highly controversial and triggered fierce debates. The Berlin Charité virologist Christian Drosten, among the advocates of harsh restrictions, has now warned against drawing the wrong conclusions. The “fundamental, ideological exclusion of lockdowns and school closures” is foolhardy, Drosten told the newspapers of the Funke Mediengruppe.
“Not all pathogens have the same characteristics. A virus could surface that is especially dangerous for children, for example, or that triggers insidious sequelae despite a harmless initial infection.”
“The school closures in 2020 and 2021 were a mistake, but please don’t take away our power to close schools again in the future! The next virus might really be dangerous to children! We don’t always cry wolf, except when we do!”
Infections such like mumps and measles have caused brain inflammation, diabetes or infertility, the director of the Institute of Virology added. “If such a virus developed into a highly transmissible pandemic pathogen, politicians would inevitably have to take measures. You can’t categorically rule out things like lockdowns and school closures, that’s neither realistic nor responsible.”
Yes, you can categorically rule out lockdowns and school closures. We literally never did any of this before at this scale or for this duration in response to any virus, nor were lockdowns or other invasive measures ever even contemplated until the Chinese gave you guys a bunch of evil ideas three years ago. What’s more, all of your interventions were utter, abject failures; they did nothing.
Drosten also criticised the public debate on Covid vaccinations, which “is often still destructive.” The fact that further Covid vaccinations for children and many adults are now no longer recommended “does not prove that vaccines have always been unnecessary,” the Charité professor emphasised.
“Rather, with the help of vaccinations, we have mitigated the impact of infections and developed a high level of immunity in the population. This is the only reason that the vaccine recommendations could now be changed.”
Had we vaccinated not a single soul, we’d have identical levels of immunity in the population right now from Omicron. We also wouldn’t have all those awkward vaccine injury headlines.
In case you’re not yet angry enough, though, it gets worse:
The director of the Institute for International Health at Charité, Beate Kampmann, warned against vaccine scepticism. “Vaccination is not only about the well-being of the individual, but also about the health of society as a whole, that is public health, and that also means solidarity,” she told the newspapers.
“Sometimes people forget that they contribute to the protection of everyone with their personal decision. That was true for Corona, but it’s also true for measles, for example.”
Why are these assholes always lying, I want to know. The vaccines were not intended to stop transmission, the trials weren’t designed to show whether they would stop transmission, and we’ve known beyond all doubt since the summer of 2021 that they don’t stop transmission. Nobody who was vaccinated against Corona contributed to anybody else’s health at all, this is all just a straight-up untruth.
The pandemicists aren’t going away. They have amassed a great toolkit of new powers, and they will be slinking around for decades waiting for the next opportunity to try them out all over again. Now that the virus hysteria has boiled off and some minimal standards of rationality have returned to the discussion, it should be a priority to discredit every last one of these virus pests, Corona astrologers, modellers, and panic mongerers, now and for all time. Otherwise we’re at great risk for getting the same thing all over again.
When the trading gets rough, the pros go insider
The farm to table vertical integration of the gates foundation investing racket
by el gato malo – bad cattitude – may 6, 2023
in the aftermath of great events, “who knew what and when did they know it?” is always an interesting question.
the US intelligence community (michael spenger substack ) was suspected to have caught wind of covid back in november 2019.

astonishingly, the IC itself denies this and claims they were in the dark until later
Every official interviewed by the Committee—from working level analysts at NCMI to an official with relevant knowledge at the NSC—said that their first indication of a novel virus came with the publication of the ProMED notice published at 11:59 p.m. on December 30, 2019 that reported the announcement of a novel virus by the Wuhan Municipal Health Committee.
In sum, the first warnings of COVID-19 came from the non-IC based public health track—in this case disease surveillance conducted by local public health authorities in Wuhan.
but this invites some pretty pointy questions about their competence, no?
because it sure looks like pretty much everyone on the super special inside track of business and finance CLEARLY knew by then.
bill gates knew. the WEF and team davos knew. and they were making big plays to make big money months before the intelligence community is even claimed, much less claims to have known what was going on.
it does make one wonder…

bill gates bought $55 million (with an option for $100mm) of bioNtech stock in september of 2019 right before they suddenly had the intellectual property for the most profitable vaccine in history.
they were not working on vaccines previously.
i wonder where they got the tech?
no one seems to know.
but it sure looks like billy g knew.
so, here’s a fun little nugget from the bill and melinda gates foundation investment into bioNtech, from whom pfizer licensed the IP for the covid vaccine.
pretty prescient for september 2019.

source
does this seem like “boilerplate?”
because it seems oddly specific (but deniable) as a “partnership” on something unrelated that could suddenly be “covid.”
and the timing is awfully provocative especially in light of some other events.
he did well getting out as well.
gates sold in 2021, banking $260 million, pretty much right at the top and has since changed his tune on mRNA vaccines, but this is hardly uncommon for “investors talking their book.”
the rest of this fact pattern looks a bit nastier though, more like the 3.0 sand hill road model of “buy up companies in a space and then mandate the adoption of their products.”
this has been the great game out there since even before kleiner perkins hired al gore to shill and lobby for their greentech portfolio. they are currently playing a similar (and more subtle) game playing hungry hungry hippos with HVAC companies and then pushing through new “air handling mandates” for new buildings, schools, offices, etc. cuz “public health.”
but the gates foundation makes them look like pikers.
if you’re going to make a big push into selling vaccines and drugs, why buy mere lobbyists when you can buy the WHO? gates is by far their largest private donor, 25X the size of the next biggest and was their number 2 donor overall.

$531 million buys A LOT of access and control. it’s perfect. the WHO is not only on the ground all over, but they also give advice and set policy/terms for assistance. so gates gets all the info instantly about what’s happening in diseases and then gets to tell the WHO what to tell everyone to do about it. play the hero and add a zero (to your bank balances).
it’s a truly great grift and few dare call it out as the nasty, hard-knuckle lobbying and advocacy it is because it looks like philanthropy.
weaponized philanthropy to be sure, but “philanthropy” and tax free to boot.
not only did bill get early word on wuhan and reach out and place big money on the one subtle square that was going to pay out huge by suddenly having the answer to the most asked question on earth and coming out of obscure nowhere to partner with pharma titan pfizer, but he went a full step further and actually held a pandemic war game under the auspices of john’s hopkins that gathered top policy makers and thought leaders to assess a global outbreak of an “imaginary” disease that happened to look exactly like SARS-cov2. this was the now infamous “event 201.”
and look who threw the party: the WEF and the gates foundation.
it’s obvious that they knew exactly what was coming. this was the overt planning plenary for covid. it was not pretend. and many/most those attending must have known that. this is the same time gates was buying bioNtech.
the bioNtech investment was 9/4/19. event 201 was 10/18, five weeks later.
who knows how much earlier the due diligence and planning must have begun, especially for the investment.
there’s getting lucky, and there’s putting the fix in because you know what others do not.
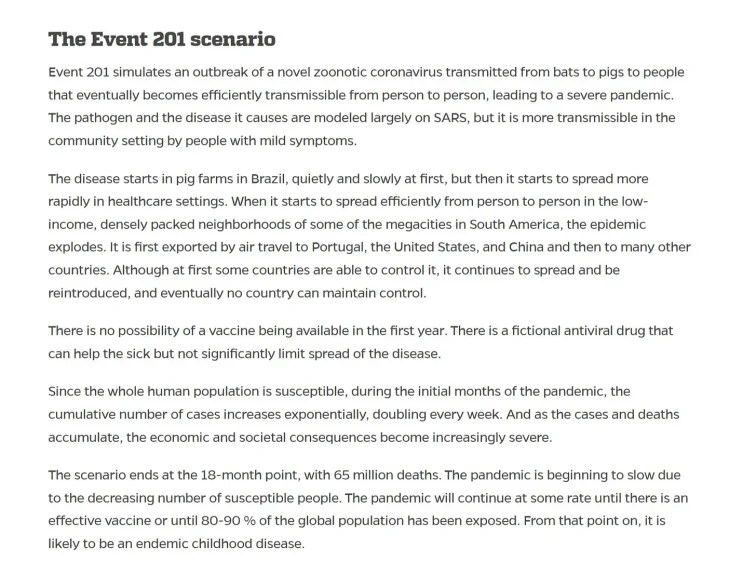
tell me that this “imaginary scenario” 2-3 months before the whole world knew what was happening was just a lucky guess.
the “players” were a high powered gang including big business, healthcare companies, the UN, the head of china’s CDC, a number of academics, the head of US CDC preparedness and response, monetary authorities, and media firms.
Featured Video

Houthis Keep Advancing as the Red Sea Crisis Deepens
or go to
Aletho News Archives – Video-Images
From the Archives
15 Saudi ‘hijackers’ were CIA agents working for US: Scholar
Press TV – April 13, 2016
Fifteen of the 9/11 “hijackers” from Saudi Arabia were CIA agents working for the United States government, which was seeking to destroy the Middle East for Israel and to double the American military budget, says Dr. Kevin Barrett, an American academic who has been studying the events of 9/11 since late 2003…. continue
Blog Roll
 Aletho News
- Russia Just Struck the Eyes of NATO’s War Machine in Ukraine
- Russia summons UK charge d’affaires over Kiev drone support
- NATO member warns bloc seeking pretext for war with Russia
- Macgregor: We Haven’t Seen the Worst of the Iran War Yet
- ‘We are not like everyone else’ laws that bind other nations do not apply to Israel, says Likud lawmaker
- Report: Saudi Arabia seeks allies’ assistance as missiles deplete amid war on Yemen
- Fuel Crisis Deepens: Pakistan Warns Tanker Attack in Red Sea Would Be an ‘Act of War’
- ‘Bucha massacre’ a false flag orchestrated by UK – Moscow
- China Rejects Outside Pressure on Trade Ties After New US Russia Sanctions Bill
- Houthis Keep Advancing as the Red Sea Crisis Deepens
- If Americans Knew
- Deportation Case of Palestinian Activist Salah Sarsour Tests First Amendment
- ‘We Will Not Forget’: Palestinians Mark 44 Years since Sabra and Shatila
- Why do we let Zionists decide what we can and can’t say?
- US welcomes Israeli, Iranian delegations to UN, but not Palestinians – Daily Update
- Biden’s Genocide Accomplices Targeted by New Accountability Campaign
- AIPAC’s Network Has Already Spent $67.2 Million to Shape the Midterm Elections
- Jewish Supremacist Manufacturing a Civilizational Threat to License Bigotry
- US bans Palestinian president from speaking at the UN
- Israeli Forces Detain Journalist Alaa al-Rimawi amid Widespread West Bank Raids
- Even a pro-Israel Congress member has put a hold on 40,000 one-ton bombs to Israel
- No Tricks Zone
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
- Fear Of Debate: Alarmist German Climate Scientist Calls On Mainstream Media To Discredit Skeptic Voices
- End-Of-August Arctic Sea Ice Extent Hasn’t Fallen In 20 Years, Official Data Show!
 Aletho News
