The Game Is Over and They Have Lost
By Robert Blumen | Brownstone Institute | January 23, 2023
The Guardian on Jan 15, 2023 published the most perfect piece of new normal nostalgia that ever was or could be: Coronavirus: ‘People aren’t taking this seriously’: experts say US Covid surge is big risk by Melody Schreiber.

This piece may be studied as a Platonic Form. Nothing could more perfectly demonstrate the inability of the covid fear porn publishers to let go of the narrative. If the author didn’t have her own website, I would have attributed the piece to an instance of ChatGPT trained on every Guardian and New York Times article from the past three years.
The writer employs every single discredited covid trope at least once. I will list a few of the best, here. To cover them all I would have to quote the entire article and that would violate the Fair Use Doctrine. I have chosen a tabular form with a quote alongside the trope that it is derived from:
| Quote | Trope |
| “In the fourth year of the pandemic.” | We are still in a pandemic. It will never end. |
| “This is one of the greatest surges of Covid cases in the entire pandemic, according to wastewater analyses of the virus.” | The current wave is the worst wave ever. |
| “Covid-19 is once again spreading across America and being driven by the recent holidays.” | Super-spreader events and family gatherings. |
| “The Omicron subvariants BQ.1.1 and BQ.1 as well as the quickly expanding XBB.1.5 make up the majority of cases.” | Just when you thought we were over it, a new variant has emerged. |
| “With XBB, there’s such a significant transmission advantage that exposure is really risky – it’s riskier now than it’s ever been” in terms of transmissibility, Sehgal said.” | The new variant is more dangerous than previous variants. |
| “And the more the virus spreads, the more opportunities it has to evolve, potentially picking up mutations that make it easier to overcome immunity.” | The variants only get worse over time, never more mild. |
| “the winter surge, which is once again putting pressure on health systems.”“Williams is worried that hospitals are reaching maximum capacity.”“Health workers have experienced three years of burnout, disability and death, and some have needed to exit the workforce.” | The health care system is under pressure. It will probably collapse. People will be dying in the streets, unable to obtain care. |
| “Despite the high rates of Covid spread, hospitalizations have not yet reached previous peaks seen earlier in the pandemic, probably due to immunity … but that protection should not be taken for granted, he said, particularly because immunity wanes.” | Natural immunity does not protect you. Even if you are immune, you should still get all the vaccines and boosters. |
| “The severe cases we are seeing are probably at least somewhat avoidable, if folks make sure that they stay updated on vaccination, because that’s still the safest way to gain immunity.” | Vaccination stops the spread. |
| “You’re just fighting a lot of misinformation.” | Everything that you have read contrary to this narrative consists of lies by malevolent misinformation spreaders. |
| When Joe Biden declared the pandemic was “over” in September, he said, it probably stalled public enthusiasm for the new booster. | Happy talk about the end of covid is dangerous. |
| “While vaccines are very important…” | All roads lead to vaccination. |
| “In New Hampshire, nursing homes will not admit those that they feel that they cannot staff to care for, which I think is admirable, but the consequence of that is that the hospitals are jammed up,” he said. Hospitals that might release patients to care facilities for transitional or long-term care will see beds filled for longer.” | The elderly in care homes are at risk. |
| “The share for children under four roughly doubled in 2022.” | Children are at risk. |
| “As Ray put it: ‘When we could be wearing a mask, why aren’t we?’” | Masks work to prevent respiratory viral transmission. |
My favorite part of the piece is, “Yet because of poor messaging from officials, many people may not even realize the US is experiencing a surge.” I am one of those many people who did not know this. A surge of what? A normal seasonal flu that makes people feel a bit under the weather for a week? A bad cold-vid?
We can celebrate our return to the old normal when an outbreak of a seasonal virus is of concern to those who are infected or who care for a family member. All of society need not be thrust into a panic over such things. The more normal the world is, the more resources of those who are impacted will have to deal with their troubles. And the better will those who are not directly affected be able to support them.
As a software engineer I note with some amusement that the variant (or as I like to call them “scariant”) names now have two periods. In a software release version a version with double dot is used for a minor bug fix release, (e.g. 3.0.1). “Minor” means that the release is not important enough for users to upgrade immediately. Perhaps the same thinking should be applied to the way we handle the emergence of new viral variants.
When Biden said that the pandemic is over, followed by “If you notice, no one’s wearing masks. Everybody seems to be in pretty good shape,” that may have been his dementia inhibiting the filter that was supposed to kick in before he said something truthful. Biden only said the quiet part out loud: the public has put the panic phase in the rearview. Even Anthony Fauci made the incomprehensible statement that the pandemic isn’t over but we are out of the “pandemic phase.” Every statement like this is more toothpaste for the pandemic dead-enders to put back in the tube.
The article bemoans the low acceptance rate of the booster vaccinations. We are told that cases are avoidable if patients had sought additional injections. First thing: do we care about cases? Second thing: it is not true that the covid vaccines prevent infection. That could only be so if the failed claim of sterilizing immunity were valid.
Vaccine advocates have walked back the earlier claims that one or any number of shots would prevent the recipient from getting infected. It was let out late in 2022 that the clinical trials did not even test for the ability of the drugs to stop transmission. It’s hard to believe that anyone can still say that after so many multiply-vaccinated-and-boosted public figures have gotten covid.
My friend Kevin Duffy, a professional investor, after seeing the Guardian article, sent me this image. The graph shows the market psychology of a financial bubble and subsequent market crash. I have added the red oval highlighting where Kevin thinks we are now: in the denial phase, after the bubble has burst.
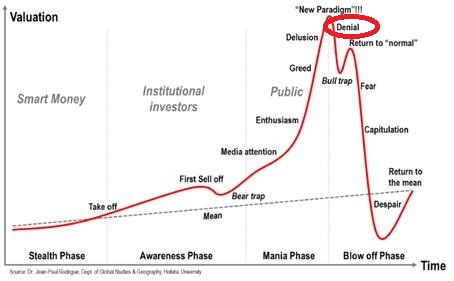
I am also reminded of the Kubler-Ross stages of grief that a patient or a loved one goes through when receiving a terminal diagnosis. The stage in her sequence is denial. The subsequent stages are anger, bargaining, depression and acceptance.
The same could be said of all of these tropes: Does anyone believe them anymore? This is not news. It is a last-gasp attempt to squeeze more juice out of a dehydrated lemon. These messages were potent fear generators two years ago. But with each use, the charge becomes weaker.
The script has worn itself out. These tropes are now tired and ineffective. The fear-pushers seem unaware that the message has lost its effect, but do not have anything else to offer. The tell is not that they publish articles like this. It is how much these pieces show that they don’t know that the game is over and they have lost.
Meta gave the CDC de facto power to police Covid “misinfo”
By Didi Rankovic | Reclaim The Net | January 20, 2023
The mask is slipping (pun fully intended), all over the place – regarding the Big Tech/Big Government collusion. Now it’s time to pay close attention to the role played by the Centers for Disease Control and Prevention (CDC).
We’ve already been awed – just by the magnitude of the whole thing – if not exactly “shocked” by the Twitter Files.
After all, while it was happening, a whole lot of observers surmised that something of the sort had to be behind the unprecedented and, seemingly inexplicable levels of censorship on the platform.
But – what in the world was happening at Facebook, around the same time? After all, Facebook is an almost orders of magnitude bigger and more influential social network than Twitter.
For the time being, we don’t have the same “direct line” to internal documents as is the case with Twitter, which was made possible by the dedication to transparency by the new owner himself.
However, what could be dubbed as the “Facebook Files” are based on credible sources, too – Reason is coming out with a story based on confidential emails that emerged thanks to a court case – the state of Missouri suing the Biden administration.
The emails show that Facebook (and by extension Instagram) representatives and the CDC not only kept in touch at all times, but that the tech giant also “routinely asked government health officials to vet claims relating to the virus, mitigation efforts such as masks, and vaccines.”
In turn, the CDC kept a watchful eye on what speech was allowed on Facebook, what policies toward censorship of “inconvenient” Covid topics applied, and this government agency had no problem instructing the social network behemoth how to behave in these instances.
Robbie Soave, a senior editor for Reason, revealed some examples of what was happening in a series of tweets citing the emails and providing screenshots. One shows that in May 2021, CDC started to get involved in “vetting” content on Facebook that concerns Covid vaccines. And CDC had the last word on what was allowed to remain online as “accurate.”
Other emails show that Facebook (Meta) made sure the CDC was given de facto power to police Covid “misinformation,” while at the same time flagging content for the CDC, consulting with it on claims that could “contribute to vaccine refusals.”
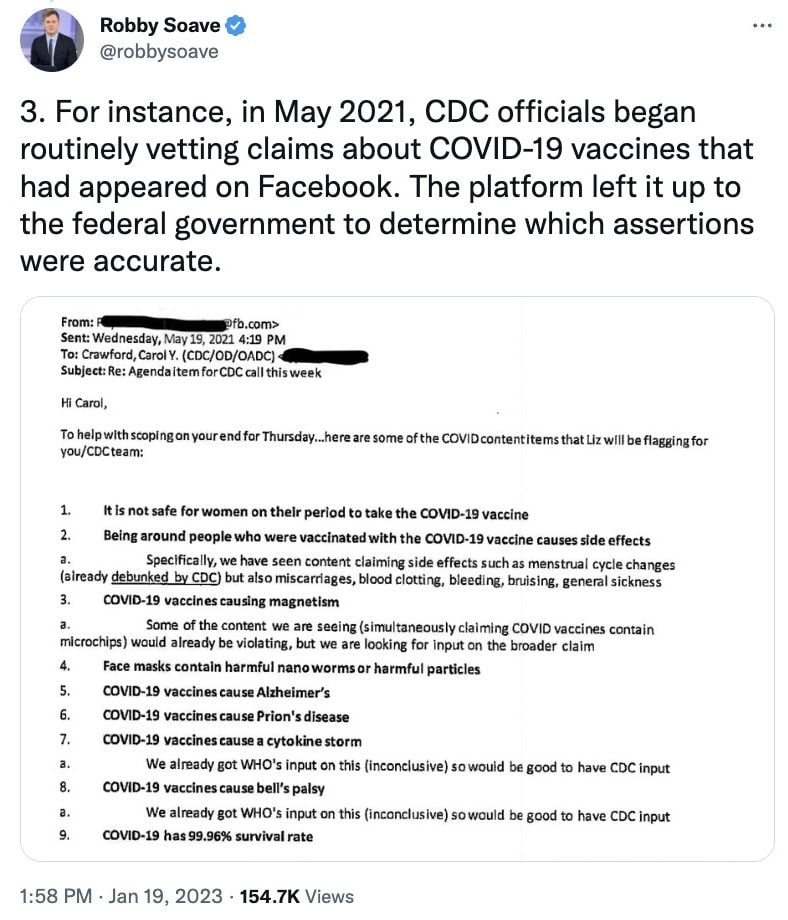

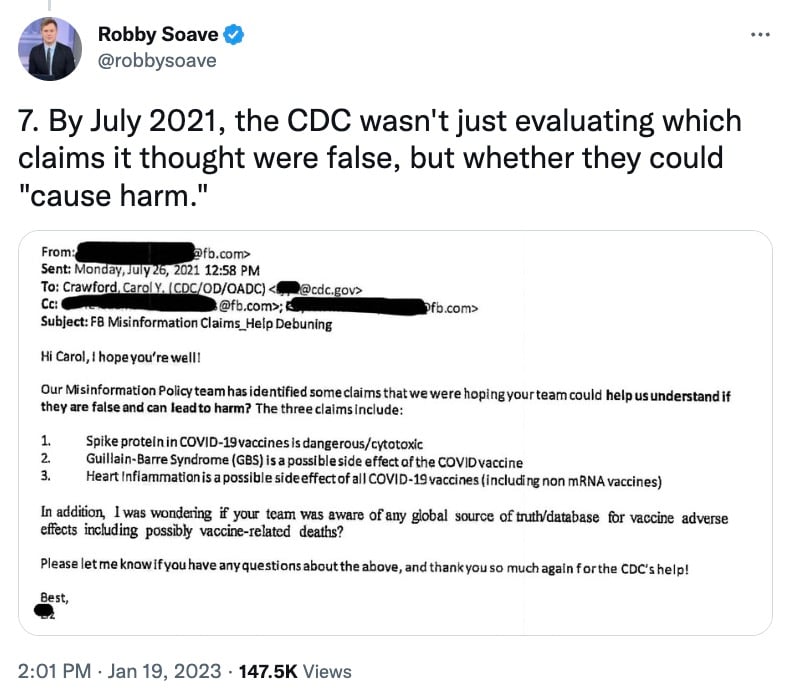


At the same time, Reason is acknowledging that this was by no means the only federal agency to engage in similar activities, all aimed at pressuring some of the world’s biggest social platforms to allow only a certain narrative, and discredit any skepticism, even that coming from medical professionals and scientists.
Even President Biden made sure to “contribute” to this effort, when he in June 2021 bizarrely accused Facebook of “killing people.”
This was really meant to say that the giant had better not dare allow any Covid content the White House failed to “vet” behind the scenes – one way or another.
And the giant obliged, sometimes probably even exceeding the level of compliance expected from the administration. An internal email now reveals that Facebook went as far as to “snitch” on its own users making fun of Anthony Fauci, apparently in a bid to defend his reputation – again, at the expense of free speech.
“One email warned the CDC that Facebook users were mocking Fauci for changing his mind about masking and double-masking. The CDC replied that this information was ‘very helpful’,” Soave, the magazine’s senior editor and host on The Hill TV channel, tweeted.
The upcoming, March issue of Reason delves into how the CDC turned into the speech police when it came to pressuring social media to block content that the government agency decided was Covid “misinformation.”
And this was online speech that this, and other government agencies, have no constitutional way of directly suppressing without breaking the law.
“There is a word for government officials using the threat of punishment to extort desired behaviors from private actors. That word is: jawboning,” Soave remarked in one of the tweets.
And one can imagine – and the emails now show – just how gun-shy and ready to please those in power Facebook had become, after years of public vilification, and who knows what kind of pressure behind the scenes in the wake of the 2016 US election.
COUNTDOWN 2030 – PART 1
December 6, 2022
By 2030, you will OWN NOTHING and be HAPPY.
This is not just a slogan or a conspiracy theory.
This is 1 of the 8 World Economic Forum (WEF) predictions. Watch their video https://www.weforum.org/agenda/2016/11/8-predictions-for-the-world-in-2030/
WEF was born out of a CIA-funded Harvard program headed by Klaus Schwab’s mentor, Henry Kissinger. Sulzer AG, in Schwab’s earlier years, where he was director, would go on to break international law by aiding the South African apartheid regime in its illegal thermonuclear bomb program.
Klaus Schwab, founder & executive Chairman of the WEF, in his book, “COVID-19: The Great Reset” published a few months after the start of Covid 19 outlines his plans for the world. Quoting Schwab, WEF’s Young Global Leaders have penetrated numerous Countries’ Cabinets and become Presidents, Prime Ministers, or CEOs. During the coronavirus pandemic, several WEF Young Global Leaders played prominent roles, promoting zero-covid strategies, lockdowns, mask mandates, and digital ‘vaccine’ passports. In contrast, there was a totally opposite approach from those who are not affiliated with the WEF.
Unfortunately, it is very difficult to get the truth, with the censorship of independent professors, doctors, journalists & politicians and the fact that mainstream media, Google & ‘fact checkers’ are funded & controlled by the same people behind this diabolical plan.
This might be the most important 1 hour 40 min you spend, unless you don’t mind ending up ‘owning nothing’, being tracked & 24/7 surveilled (under your skin, as per WEF Agenda Contributor, Yuval Noah Harari) and ending up with CBDC (Central Bank Digital Currency), UBI (Universal Basic Income) and eventually Social Credit System.
The “Great Reset” echoes the real, unspoken of plans behind UN Agenda 21, now known as Agenda 2030. (more of this in Part 2) Lastly, to understand why they say “you will be happy” when you own nothing, is where the METAVERSE comes in (more of this in Part 2),
Call to action: Please share this film. Knowledge is power. Lets work together to co-create a future independent from the WEF, WHO & UN
Be critical thinkers and do your own research. Here are links to the excerpts used in this video, curated in South Africa:
https://www.corbettreport.com/wef/
https://rumble.com/v1dxzgh-episode-278-radical-truths.html
https://rumble.com/v11p0vo-the-megadeath-intellectuals-of-the-great-reset.html
https://www.youtube.com/watch?v=fI16ylFLLz8
https://www.jrepodcast.com/episode/joe-rogan-experience-1780-maajid-nawaz/
https://odysee.com/@MaajidNawaz:d/EP8-Radical:9
https://senatormastriano.com/2022/03/01/expert-panel-discussion-on-covid-19-and-medical-freedom/
https://odysee.com/@OracleFilms:1/New-Normal—Happen-Network:3
https://www.youtube.com/watch?v=CA_Phpz4woY
https://www.corbettreport.com/how-green-finance-is-monopolizing-the-planet-with-whitney-webb/
https://odysee.com/@QuantumRhino:9/Maajid-Nawaz-with-Joe-Rogan—The-Joe-Rogan-Experience–1780:f
https://edition.cnn.com/videos/world/2019/11/26/yuval-noah-harari-interview-anderson-vpx.cnn
https://www.youtube.com/watch?v=hL9uk4hKyg4
https://www.youtube.com/watch?v=jTfW-cchpYA
https://www.bmj.com/content/371/bmj.m4425/rr-31
https://www.youtube.com/watch?v=JfyIW9wRvB4
https://www.youtube.com/watch?v=-3aPT8MuH_E
https://www.youtube.com/watch?v=JDM1CIwa5Bw
Florida Governor Ron DeSantis’ “Prescribe Freedom” plan bans vaccine passports, supports doctors’ free speech

By Cindy Harper | Reclaim The Net | January 19, 2023
Florida’s Republican Gov. Ron DeSantis plans to introduce legislation that will, among other things, stop Florida from being a “biomedical security state.” The legislation will ban all vaccine passport mandates.
DeSantis said the purpose of the legislation is to “prescribe freedom.”
“When the world lost its mind, Florida was a refuge of sanity, serving strongly as freedom’s linchpin,” the Republican governor said on Tuesday. “These measures will ensure Florida remains this way and will provide landmark protections for free speech for medical practitioners.”
“It required us over the past few years to stand against major institutions in our society: The bureaucracy, the medical establishment, legacy media, and even the President of the United States who, together, were working to impose a biomedical security state on society,” he added.
DeSantis’ surgeon general Dr. Joseph Ladapo said he supports the bill because it would protect the free exchange of ideas between medical professionals.
“As a health sciences researcher and physician, I have personally witnessed accomplished scientists receive threats due to their unorthodox positions,” Ladapo said. “However, many of these positions have proven to be correct, as we’ve all seen over the past few years. All medical professionals should be encouraged to engage in scientific discourse without fearing for their livelihoods or their careers.”
The legislation would protect medical professionals’ freedom of speech by protecting their religious views and their right to disagree with the preferred narrative. The bill would also protect medical freedom of choice by banning discrimination based on vaccination status, testing, and mask-wearing.

Related:
California’s chilling medical misinformation law is an affront to the US constitution
Germany, “standing atop a billion-dollar mountain of masks,” begins to incinerate the rapidly expiring surplus
eugyppius: a plague chronicle | January 20, 2023
From Welt :
Authorities have come up with a term that sounds at least halfway sane. They’re calling it “thermal reprocessing.” Four federal states now claim to have thermally reprocessed – or, in plain language, to have incinerated – a total of 17.25 million expired Corona masks.
Baden-Württemberg has destroyed 6.1 million masks, Saxony 5.5 million, North Rhine-Westphalia 5 million, and Mecklenburg-Vorpommern 656,000 …
The Federal Ministry of Health (BMG) in Berlin has also “thermally recycled” masks in recent months. The number so far is “less than one million units,” a spokesperson said … The destroyed masks were purchased during the peak of the pandemic, and have exceeded their expiration date …
The federal and state governments are currently standing atop a billion-dollar mountain of masks. According to information provided by the Ministry of Health in September, there are a total of 3.7 billion masks in the federal inventory … The federal states have have an additional 180 million Corona masks at their disposal …
The states want to burn even more masks, but for the moment they’re not allowed, because much of the surplus in their possession is technically federal property. Thus they’ve begun begging the government to take the masks back:
“The Interior ministry of Hesse, together with many ministries of other states, have turned to the federal government with an urgent request to either take back their unusable masks … or grant permission for their destruction…” says a spokesperson. Unfortunately, the federal government has not yet agreed. “The Federal Ministry of Health has referenced uncertainties in customs law that the government has not yet been able to clarify.”
I’m going to go out on a limb here, and say the Scholz government is reluctant to write off the masks purely because of the negative publicity it’ll generate. I can’t imagine how customs regulations would prevent the Health Ministry from destroying its own expiring property.
Karsten Klein, chairman of the FDP faction in the Bundestag Budget Committee, has criticised the previous government’s over-procurement: “The coalition has inherited a hugely expensive mask mountain [Merkel health minister] Jens Spahn. As important as federal support for procuring masks was in 2020, under Spahn it led to literal frenzied buying that completely lost sight of actual demand” …
But we haven’t even gotten to the best part. The idiot pandemicists are still hoarding masks, even as they’re burning them:
… Additionally, the “National Health Protection Reserve is still stockpiling masks. The Reserve was established in mid-2020 by the Merkel government to prevent future shortages. According to the Ministry of Health, there are currently 245 million masks in the reserve, part of which will expire at the end of 2023.
Doubts about the usefulness of the Reserve are growing. In November, the Budget Committee called on the government to … examine “whether a federal physical stockpile for the health system is at all necessary or economical” …
For the taxpayer, mask procurement is very expensive. The costs at the federal level alone have totalled 5.8 billion Euros since the beginning of the pandemic.
It’s just so astounding, this entirely pointless and still ongoing mass delusion. Masks do nothing to stop infection, we have spent three years learning in excruciating detail that they do nothing to stop infection, we are now setting fire to millions of masks heedlessly purchased at the height of pandemic hysteria when there was every reason to expect that masks would do nothing to stop infection, and still we’re pouring millions of Euros into some kind of retarded national strategic mask reserve that will also surely be incinerated in the coming years because masks do nothing to stop infection. Even more unfathomable is this ridiculous fiction that useless products which do nothing can ever “expire.” What is the fear, that expired masks will do even more of nothing than new masks?
Everything about Corona is such a multifaceted ridiculous farce.
What’s behind Jacinda Ardern’s resignation?

By Guy Hatchard | TCW Defending Freedom | January 19, 2023
New Zealand’s Prime Minister Jacinda Ardern resigned last night after months of rumours. Ardern, whose popularity has plummeted during the last six months, told us she ‘had nothing left in the tank’.
The backstory to this resignation is a tale of woe. Ardern said she wants to be remembered as someone who tried to be kind. The subtext is: the country is in an unprecedented mess but don’t blame me. School attendance is running at just 67 per cent on any given day. Machete-wielding teenagers are ram-raiding liquor, tobacco and luxury stores daily in an unprecedented crime wave. The health system is overwhelmed. Ardern’s government promised to build 100,000 new homes over three years. It has delivered 1,500.
Our tourist, farming and hospitality industries have never recovered from lockdowns and border closures. It takes months to get a visa to visit NZ and the government says it only wants rich people to come. Ardern insisted on universal Covid vaccination mandates. There is a suspicion that our 90 per cent vaccination rate has left most people in a lethargic fog. Excess all-cause deaths are still running 15 per cent above the long-term trends, and it is not Covid.
History will judge Ardern harshly, but don’t blame her alone. This was a Parliament who woke up on all sides of the house to the weakness of our constitutional arrangements (there are none). The Bill of Rights was tossed aside and no one in Parliament cared.
The leader of the National opposition Chris Luxon said if he was in power, he would withdraw benefits from unvaccinated single mothers. David Seymour, leader of the ACT party, said those losing their jobs through vaccine mandates only had themselves to blame. Labour’s coalition partner, the Greens, led by example. They encouraged mothers in labour to ride to hospital on a bicycle.
Revelations this week (here and here) that Ardern personally overruled her scientific advisers who were expressing doubts about the safety of Covid vaccines for young people and the wisdom of mandates have circulated very widely and no doubt this further undermined confidence in the government.
Political insider and right-wing commentator Cameron Slater published an article ten days ago saying that out of all the politicians he has known (and he has known most since Muldoon in the 70s) Ardern is the only one he rates as truly evil.
Ardern introduced ‘rule by regulation’. Adopting the enabling model favoured by fascists in the 1930s, her government has empowered authorities to tell us all what to do, when to stay at home, and where not to go. The courts, the Human Rights Commission and the broadcast regulators have all followed the government line meticulously which has had a devastating effect on business, families, communities and professions. To cement her policies, Ardern introduced massive government funding of our media and broadcasters.
Ardern’s government, in an absurd overreach, funded a nationwide effort to discredit critics of policy, labelling them terrorists. This has divided a formerly egalitarian society, instituting a Stasi-like snitch culture that encourages us to report a neighbour. Government Disinformation Project employees appeared on funded films aired on television labelling knitting, blond hair, braids, vaccine hesitancy, love of natural foods, yoga and motherhood as signs of terrorism that should be reported to the intelligence services (view it here if you can stand watching this nasty piece of propaganda and hate).
Why did Ardern suddenly change overnight in August 2021 from being a kindly figure saying she would never mandate vaccines, to being one of the world’s most draconian proponents? We can only speculate. NZ is a member of the Five Eyes intelligence network. Given the Pentagon’s recently revealed massive involvement in US Covid policy and gain of function research funding, was she fed information that a bioweapon was in play?
For a couple of weeks now government announcements and advertisements encouraging vaccination and boosters have been conspicuously absent. Has the penny finally dropped? We doubt it. It will take an honest, intelligent politician (are there any?) to roll back Ardern’s dictatorial powers and kickstart New Zealand. Why would any aspiring newby give up that much power? The prospect will be too intoxicating.
Ardern was a protege of Tony Blair and Klaus Schwab of WEF. They must bear some blame too. What fantasies of global power did they offer to a young person who was given to idealistic dreaming that segued into fanaticism?
Our final verdict: It is not Ardern but the whole NZ Parliament elected in 2020 that will be judged as the worst in our short history as an independent island nation, formerly famous for championing the underdog and offering opportunity to all. Ardern’s resignation has lit the bonfire of modern democracy.
Are vaccine deaths being disguised as virus deaths?
By Professor Roger Watson and Dr Niall McCrae | TCW Defending Freedom | January 18, 2023
A new Covid-19 variant has appeared: XBB.1.5 (or ‘Kraken’, for the fear factor). This could explain why deaths are surging again, with Japan recording about 400 daily, and Australia (despite being in the height of summer) in the dozens. But are people really dying from the latest strain of coronavirus?
Excess mortality is highest in countries with the highest rates of Covid-19 vaccination. Correlation is not causation, but only the wilfully blind are describing this human toll as ‘baffling’. Ordinary people do not need scientific expertise to join the dots. At the very least, the authorities should be investigating this unprecedented rise in mortality as a possible iatrogenic disaster (ie caused by medical treatment, like thalidomide).
While there is growing public awareness of the lethality of the mRNA injections, the scientific orthodoxy is continuing to suppress the truth. In reports showing an increased incidence of cardiovascular disease after vaccination, researchers always moderate the message by stating that the benefits overwhelmingly outweigh the risks. However, many publications do not even consider the vaccines as a cause of illness or death.
Our editor alerted us to the article Covid Leading Cause of Death Among Law Enforcement for Third Year in Medscape. The data for this study of police officers across the US were taken from an annual report issued by the National Law Enforcement Officers Memorial Fund, titled 2022 End-Of-Year Preliminary Law Enforcement Officers Fatalities Report.
The report claims that in the past year 70 officers died in the line of duty of causes related to Covid-19. The good news is that this is ‘down dramatically from 2021, when 405 officer deaths were attributed to Covid’, but this was still a significant loss of front-line personnel, surpassing the number of deaths from firearms-related incidents.
The authors of the original report attribute the decline in deaths to ‘reduced infection rates and the broad availability and use of vaccinations’. However, this putative triumph of the Covid-19 vaccine needs more scrutiny than afforded by Medscape writer Lisa O’Mary.
In the original report we were keen to know how many law enforcement officers had died of other deadly infections. We anticipated influenza, meningitis, gastroenteritis and septicaemia among other potential killers, but none of these are mentioned in the report despite exposure on duty. We also wondered what the ‘background noise’ was in terms of how many law enforcement officers had died in total during the preceding years whether in the line of duty or not. Sadly, this figure was not reported either.
Covid-19, uniquely amongst infectious diseases, is being recorded as a cause of death in the line of duty but it is not clear why. We do not have any doubts about the bona fides of the National Law Enforcement Officers Memorial Fund and we do not, at face value, question their use of the numbers with which they have been provided. What is clear is that, like most of the public sector in the US (and the UK) they have fallen for the Covid-19 narrative and been willing participants in the ‘fear porn’ that has gripped so many otherwise well-meaning organisations.
We see several problems with the researchers’ claim that low Covid-19 mortality in officers was due to the vaccine. The first problem is the distinction between the definition of deaths ‘with’ as opposed to ‘of’ Covid-19 and the possible attenuation of the Covid-19 virus over time. Then, we are not informed in the report, and data seem unavailable, about the extent to which Covid-19 testing was or is still being carried out. If there was a significant reduction in Covid-19 testing between 2021 and 2022 that would be a significant confounding factor.
A bold claim about the success of the vaccine rollout would need, at least, to show how many law enforcement officers were vaccinated. Even then the outcome would not provide much insight into cause (vaccination) and effect (death from Covid-19).
It is not clear how many US law enforcement officers are vaccinated. There were indications that compulsory vaccination was going to be introduced for law enforcement officers. But there was also evidence that the law enforcement unions ‘pushed back’ against the idea. In fact, uptake of Covid-19 vaccines was so low amongst law enforcement officers that hundreds were reported to be dying and that, according to the Washington Post, they were a danger to the public. Therefore, it seems incongruous that, on the one hand, law enforcement officers are a public hazard due to their low Covid-19 vaccination status, and on the other hand have their own lives saved ‘dramatically’ as a result of the Covid-19 vaccines.
There is a more serious question that the researchers failed to ask themselves. Is it possible that some of the 70 officers dying in 2022, and some of the 405 in the year of the initial vaccine rollout, were victims of the Covid-19 vaccine? Consider, for example, an officer who is hospitalised for breathlessness, and is discovered to have dangerous blood clots. On admission he tests positively on a PCR test, which is notoriously prone to false positives. If this officer were to die, he would be added to the Covid-19 mortality figures. This is not fantasy, but the reality of how the pandemic has been perpetuated over the last three years – with the collusion of the scientific community.
Insider reveals truth about Covid-19 pandemic from within the National Health Service
How the misdiagnosis of deaths occurred and was due to changes from 2016
The Naked Emperor’s Newsletter | January 15, 2023
An ex-director at one of the largest hospital trusts in the UK decided they wanted to reveal what really happened during the pandemic. They have kindly allow me to reproduce their thoughts. The catalyst for this revelation, according to the insider, was Dr. Malhotra speaking out about cardiac problems post vaccination.
This is an interesting take on what happened inside the National Health Service (NHS) and confirms, with more details, what we already knew and suspected.
Introduction (Long but important to understand the rest)
In 2016, the British Government proposed & piloted a change to the process of how deaths were certified across all hospitals in the UK. I have attached a link to this Department of Health (DoH) document.
The DoH document proposed a switch to the “Medical Examiner” (ME) System and was sent to a number of different audiences for feedback and consultation. The ME system was already being piloted at two hospitals up north. The results of the consultation are here.
Prior to the Covid-19 Pandemic, the death certification process involved treating doctors of a patient to attend Bereavement Services/Patient Affairs to discuss the death and either:
a) refer the death to the Coroner or
b) write a Medical Certificate of Cause of Death (MCCD).
The MCCD states the cause of death. Whereby a direct cause (1a) or contributing causes (1b) (1c) (1d) are stated along with co-morbidities (not directly causing the death) being written in (2) on the MCCD. The MCCD is only ever a probable cause of death, it is not definitive.
The only definitive way of determining an accurate and plausible cause of death is to refer the deceased patient to HM Coroner (if certain criteria is met), for HM Coroner to accept and take on the case, resulting in a Post Mortem (PM) being conducted by a Histopathologist. When a death is seen as natural and there is nothing untoward, the MCCD is written by the treating doctor of a deceased patient. Usually this is an F1, F2, SHO or Registrar that attends. It is rare for a treating Consultant to attend, but they will finalise the cause of death.
A strict hospital hierarchy exists within the NHS for doctors. It is as follows – from lowest to highest rank: Foundation Year 1 (FY1), Foundation Year 2 (FY2), Senior House Officer (SHO), Registrar (Reg), Consultant, Clinical Lead, Medical Director. Junior doctors will very rarely speak up or challenge their seniors. A senior decision is seen as final and it will be carried out and executed without any hesitance or questioning. In my 5.5 years of experience in End of Life Care, I have only ever seen one junior doctor disagree with a proposed cause of death and challenge their consultant.
With the number of deaths that occur in a hospital, as you can imagine, there is a great deal of variation with regards to causes of death, as we have numerous different doctors writing an MCCD and coming up with various different potential diseases in different orders.
The proposed ME system would change this, as the government would now hire and pay one Medical Examiner, to sit in every hospital and write all MCCD’s for all deceased patients. This would effectively eliminate any variation in causes of death.
In 2016, when I heard of this proposal, I worked as a Bereavement Officer at a hospital in Central London. My mentor/line manager at the time was a former Chief Nurse who managed Bereavement Services and all hospital deaths would be controlled by her and the department.
We essentially carried a huge amount of power with regards to decision making, as we would go through all patient notes following the death of a patient, and essentially guide and advise doctors on what would need to be written with regards to an MCCD or Coroners Referral.
In my personal opinion, our role was to sit on the fence and act in the best interests of a deceased patient (and their families), but also protect the hospital and our doctors from any potential negligence. As you can imagine many battles were fought over decisions about a cause of death of a patient or a referral to the coroner with a vast amount of doctors over the years.
F2’s and SHO’s were particularly the worst with regards to carrying an arrogance of knowing what should be written on an MCCD or stating that a patient didn’t need to be referred to the Coroner (often stating that their Consultant had given them instructions). It is worth noting that Consultants are also only human and can be incorrect at times too. We have to remember that they are succeeded in hierarchy by a Clinical Lead and beyond that a Medical Director. Who have far more experience and knowledge.
When I asked my mentor in 2016, how the ME system would change things, I was told that Bereavement Services/Patient Affairs would become purely administrative and that the clinical judgement would fall to the Medical Examiner.
The power and decision making with regards to MCCD/Coroners Referrals was being taken away not only from treating doctors but also from Bereavement Services/Patient Affairs/Bereavement Officers/Bereavement Service Managers/Directors of End of Life Care.
This decision making power was being handed solely to the Medical Examiner, who has not been involved in the treatment of a patient during an admission. I took all this information in at the time and acquired as much knowledge as I could from my mentor/line manager.
In 2016, I also happened to make a move and take up an opportunity to manage my own Bereavement Services at one of the largest hospital trusts in the whole of the UK. On average, I would oversee MCCD/Coroner Referrals for approx 1750 deaths on an annual basis. I developed a very close working relationship and friendship with one of the Medical Directors (a doctor with the highest ranking in a hospital). This was especially helpful when having to challenge doctors with regards to MCCDs/Coroners Referrals.
Progressing to Director of End of Life Care, I became involved with the reporting of mortality rates, conducting mortality reviews and writing hospital policies. I had also developed an excellent working relationship with the HM Coroner who oversaw our Trust. HM Coroner holds the power to investigate any hospital or trust with regards to a death or a number of deaths. A slight problem may arise, in that HM Coroner has an allegiance to the Crown and the Government.
When a death is reported to the Coroner. This was previously reported via telephone call by the treating doctor. A discussion was had with the Coroners Office and a direct outcome and instruction would come from the Coroner’s Office, by way of HM Coroner (via a phone call).
There is a fundamental flaw to this system, as there is no documentation of the decision and instruction from the Coroner’s. It comes via word of mouth. There is always room for error without any electronic documentation. Every Hospital/Trust & HM Coroner will have a different system of reporting deaths. I personally made a decision to safeguard my hospital and the trust, by developing an electronic coroners referral form, which I proposed to our Coroner and developed after their agreement. We now had documentation of every death being reported and every outcome.
When reporting a death, the Coroner will look at a proposed cause of death and accept it, or reject the cause of death and take on the case (death of the patient), leading to an Inquest or a PM.
In 2019, our Medical Director, came into my office one morning and stated that the Board of Directors at the Hospital had made a decision to switch to the Medical Examiner System. Hearing the words ME system was a massive case of Déjà vu (conversation with my mentor in 2016). I knew exactly what the ME system was, but I chose instead, to play the fool and enquire what exactly the ME system was and what it meant for our service, my staff and our roles. Everything the Medical Director mentioned to me that day was a carbon copy of what I already knew
I knew that my time in End of Life Care had come to an end. I’d reached the top and there was no more progress for me. Losing all power and decision making to any ME coming into the hospital did not appeal to me. I’d already made up my mind that I needed to leave. Seeking a new challenge and experience, I made a move in 2019 to another major hospital in Central London, this time side tracking into operational management. I was in charge of the operational management of Nephrology, Rheumatology, Dermatology and Diabetes & Endocrinology.
2020 – Covid Arrives
In Jan 2020, I remember hearing about the first case of Covid-19 at our hospital, with a patient arriving from China and walking into our A&E. A&E was shutdown and steam cleaned that day, I recollect the moment I heard about this. In my mind, I saw the reporting of Covid-19 in the media as nothing more than Bird Flu or Ebola, which had caused panic but yet passed. I wasn’t worried in the slightest bit.
Things began to escalate around in Feb 2020, around the time I was going on holiday. Due to the reporting by the media, I bought N95 masks as a precaution for my trip and to give to my parents and younger sister. I was blessed to have had an opportunity to spend a few days in Sri Lanka for a wedding and then nearly a whole month in Australia (March 2020). I watched as the narrative of a deadly infectious disease continued to grow with every day that passed. I made a decision to cut my holiday short by a couple of days so that I could make sure I got back to my family and not end up being stranded in Australia.
Upon returning to the UK in late March 2020. One of the immediate things that struck me was the lack of any temperature monitoring or questioning at Heathrow Airport. This seemed odd for a potentially deadly infectious disease that was spreading around the world. This was especially odd, as Sri Lanka & Australia had questioned me/checked temperatures upon arrival, with even Singapore monitoring temperatures during transit.
My mother had just recovered from Cancer, my father was over 70 and my younger sister was born with Down’s Syndrome alongside having multiple other conditions. I had three high risk individuals to Covid-19 in my family and I was scared/fearful of giving them Covid-19. I asked my hospital to allow me to work from home. They refused. I wasn’t deemed high risk, although I lived with my parents at the time. I needed to help my mum and my sister. The hospital held no regard for the safety of it’s employees. They forced me to come into work. I spent two months isolating in my bedroom, I barely came out of my room, for fear of spreading an infectious disease. Never once did I think about the situation or my prior experience or knowledge, I was just reacting to the media frenzy. I was full of panic and stress.
The first irregularity I noticed, was the government and media stating that Covid-19 was an infectious disease. However just before the first lockdown was implemented, I noted that the government had downgraded the status of Covid-19 stating it was no longer infectious. This made no sense to me. Why would we need to isolate if they downgraded the status? My circle of friends contained many medics and dentists. They were all panicking at the time, saying they had inadequate surgical masks and that they needed N95 masks.
N95 masks were seen as the only way to prevent medical professionals from becoming infected with Covid-19. The public being asked to wear surgical masks made no sense to me. The virus would be able to go straight through. Something didn’t seem right.
I ended up meeting and dating an FY1 doctor (my ex gf) around October 2020. We clicked because she was different from every other doctor, I had previously spoken to about Covid-19. She also had her suspicions and believed it wasn’t as infectious as it was made out to be. We both started to slowly realise that Covid-19 was a real disease (as it was showing up on X-rays in patients) but that it wasn’t infectious at all [NE – I have since confirmed with them that they mean not as infectious as was being made out], despite all the reporting in the media.
I needed to experience working in a Covid-19 hotspot and see all the action for myself. In March 2021, I quit my job at the hospital in Central London and took up an opportunity to manage A&E and AMU (Acute Medical Unit) at a hospital in South London. The 6 months that I spent working in A&E/AMU confirmed all my suspicions and culminated in my decision to end my career in the NHS.
The entire 6 months, I was not tested once with a PCR Test, despite walking into wards full of Covid-19 Positive patients on a daily basis. Yet we were required to test multiple times when visiting another country.
The PCR Test that the NHS was using to test patients, is known to have false-positive results. This is shown in numerous studies which can be found online, an example of which is:
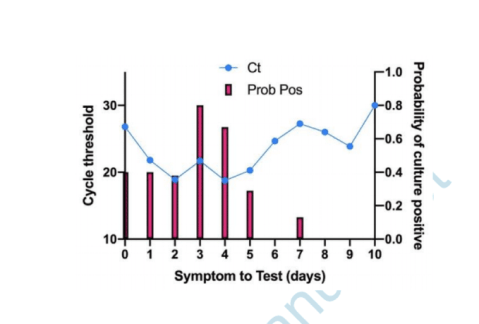
Are you infectious if you have a positive PCR test result for COVID-19? – The Centre for Evidence-Based Medicine.
If a patient tests positive for Covid-19 with a PCR Test, this doesn’t mean they are infected. If tested again, they may well turn out with a negative test. However in the NHS, patients are only tested once and this stays on their record throughout their admission. Hospital policies were changed alongside the implementation of the Medical Examiner System, to ensure that any patient who died within 30 days of positive test, would have to have Covid-19 as their primary cause of death. This was regulated by the Medical Examiner.
The highest cause of death at every hospital per annum pre Covid-19 is Pneumonia. Pneumonia is a Respiratory Disease like Covid-19. Pneumonia can be broken down into 4 different causes of death: Bronchopneumonia, Aspiration Pneumonia, Community Acquired Pneumonia & Hospital Acquired Pneumonia.
These four causes when added together kill the largest number of people on an annual basis prior to the pandemic.
The Medical Examiner (one individual in each hospital), was certifying all these Pneumonia deaths as Covid-19 deaths. When 4 different diseases being grouped and now being called Covid-19, you will inevitably see Covid-19 with a huge death rate.
The mainstream media was reporting on this huge increase in Covid-19 deaths due to the Medical Examiner system being in place. Patients being admitted and dying with very common conditions such as Old Age, Myocardial Infarctions, End Stage Kidney Failure, Haemorrhages, Strokes, COPD & Cancer etc were all now being certified as Covid-19 via the Medical Examiner System.
Hospitals were switching to and from the Medical Examiner system and the Pre Pandemic System as when they pleased. When Covid-19 deaths needed to be increased, the hospital would switch to the Medical Examiner System. Doctors were one week being told they needed to complete an MCCD, to then be told the following week that they weren’t required to fill out an MCCD, as the Medical Examiner was handling this.
Hospitals were incentivised to report Covid-19 deaths over normal deaths, as the government was paying hospitals additional money for every Covid-19 death that was being reported. The Medical Examiner system ensured that Covid-19 was being put down as the cause of death. The government sends out the annual NHS budget to Primary Care Trusts. This is split to fund Hospitals and GP Surgeries. A clinical coding team at each hospital will assign codes to each treatment or death, so that money is paid out to the hospitals.
Any doctor who argued against Covid-19 as a cause of death was bullied and vilified. The General Medical Council maintains a register of all doctors within the UK. This ensures that there is a fear of being struck off for speaking out against an agenda. The GMC effectively controls all doctors in the UK. Even if a doctor realises what is going on and wants to speak out. They will think twice about talking, as they would be risking their entire career and everything that they’ve worked so hard for.
Doctors essentially have their hands tied, many have families, kids, mortgages and mouths to feed. If I was in their situation, I would think twice about speaking out, for fear of being struck off by the GMC and losing everything.
The NHS Track & Trace App, which was introduced to try and control the spread of the virus, did not apply to medical professionals. We were all asked to turn this off, as Doctors and staff isolating for 14 days disrupted patient flow, beds and the discharge of patients.
Any doctor that I spoke to regarding taking the Covid-19 vaccine, were insistent that they were going to wait for a period of time, before taking it themselves, to ensure that it was safe. How is it ethical to give a vaccine to your patients, but not want to take it yourself? In my 12 years of NHS service, never has a doctor pushed or influenced the public to take a vaccine. Yet on social media, I was seeing close friends who were doctors, starting to post on social media that they have taken the vaccine and that the public should. I wouldn’t be surprised if doctors were being forced to promote the vaccine by their superiors or if they were receiving monetary gain in doing so.
I have no doubt in my mind, that the Government has planned the entire pandemic since 2016, when they first proposed the change to medical death certification. Stress leads to disease and illness. Panic leads to people following whatever orders and instructions that are given to them by authority, such as prolonged mask use, which leads to an increase in admissions in to the NHS system due to hypoxia and bacterial pneumonia.
The NHS treatment pathway involved patients being placed onto ventilators. There is a 50% chance of death from this clinical decision alone. How many innocent people have died from the clinical decision to place them onto a ventilator.
During boardrounds (where every admitted patient is discussed), we were seeing patients on a daily basis being admitted due to suffering from adverse affects of taking the vaccine. Patients were blacking out after taking the vaccine or suffering from clots or strokes.
The NHS is all about money and making money. The safety of a patient didn’t seem like the most important thing. It was more about how do we make more beds available so that another patient can be treated. Patients with no next of kin are discharged to nursing homes with care packages. I can’t comment on what happened to these patients in nursing homes, during the pandemic, as I have no experience of their inner workings.
Patients are seen as money, even upon death, hospitals receive money for each death. Is there an actual concern for patient health and safety? I know numerous doctors who are driven primarily by money and monetary gain.
THE REASON WHY I LEFT THE NHS in 2021
56 yr old male, admitted into A&E with end stage kidney failure, has a previous history of regular dialysis treatment for this. No respiratory symptoms on admission and no temperature. However when tested with a PCR Test he unfortunately tests positive. This stays on his record throughout his admission. Our hospital is relatively small in comparison to others I have worked at, we have no dialysis machine as a result. We urgently need to transfer this patient to another hospital otherwise this patient will die. Our treating doctor calls up larger hospitals with a dialysis machine to organise his transfer. All doctors pick up the phone and request the Covid-19 status of the patient. A transfer is declined due to a Covid-19 infection protocol. Our doctors again reiterate the point that this patient will die without dialysis. We are told there is nothing that can be done and that the patient cannot be accepted for transfer.
This gentleman ended up dying without dialysis. Now please tell me what goes on the MCCD….
1a) Covid-19
2) End Stage Kidney Failure
Not written by the treating doctor who disagreed with this cause of death, but by a medical examiner, put in place by the government and the hospital.
When innocent people are being killed by a corrupt organisation and system, for pure monetary gain, I can’t stand by and be part of this anymore. My conscience was clear and I no longer wanted to be a part of this anymore. I am very blessed and lucky that I was in a position to walk away. I’ve been able to speak out, because my hands are not tied and I am not regulated by any organisation or governing body. I believe in speaking the truth and in doing so, I am only just an instrument for God.
I joined the NHS, 12 years ago because I had a desire to help those in need, but the moment I realised that I was not doing this anymore was the time for me to walk away. I apologise to you all if the above thread is confusing with regards to terminology or you cannot understand it’s contents. I’m hoping that at the very least, it can be understood by my fellow medical professionals or by journalists who would like to report the truth.
Pro-mask propaganda cranks up a couple of notches
By Gary Sidley | Coronababble | January 11, 2023
It’s happening again. After a period of welcome sanity – where those covering their faces in community settings could accurately be described as a deviant minority – the pro-mask propaganda machine has gone into overdrive. In what seems to be a co-ordinated enterprise, in the last couple of weeks our mainstream media has spread a variety of news stories pushing for more of us to hide our faces behinds strips of cloth and plastic. These include:
1. The announcement, at the end of 2022, that Northampton and Kettering General Hospitals have decided to re-impose mask requirements on all patients and visitors. This policy change provides further evidence of the mask postcode lottery operating within our healthcare system, where the decisions are left to the whims of local bureaucrats.
2. The pro-mask baton was taken up in the new year when Professor Susan Hopkins (chief medical advisor at the UK Health Security Agency) urged people who feel ill to wear a mask should they venture outside. In the grand scheme of masking zealotry, this was a modest recommendation, but – ominously – it does perpetuate the dubious assertion that wearing face coverings in the community reduces viral transmission, as well as preparing the ground for further incremental restrictions.
3. Throughout 2020/21, fear porn was highly effective in leveraging compliance with Covid restrictions, so no wear-a-mask propaganda drive would be complete without some scary stories and images from China. Our mainstream media were only too keen to oblige, with headlines about Covid deaths soaring, funeral homes overwhelmed and bodies being burnt in the streets in the aftermath of China’s relaxing of restrictions.
4. And then – predictably – the arch ‘nudgers’ (aka behavioural scientists) put their heads above the parapet, pushing their collectivist agenda. In a Guardian article, Professor Stephen Reicher repeated the tired trope that those opposed to mass masking were right-wing activists engaged in a culture war. He then urges the psychological manipulation of the masses by equating mask wearing with virtue (otherwise known as the ‘ego’ nudge) when he recommends, ‘reframing mask wearing as a community issue: less about individuals exercising personal responsibility; more about a collective exercising social responsibility, looking after each other, making sure we all come through this well’.
Meanwhile, Professor David Halpern (chief executive of the Behavioural Insights Team, the UK’s ‘Nudge Unit’) was promoting a similar narrative. In an interview for the Daily Telegraph (funded by the Reckitt Global Hygiene Institute), Halpern celebrates the use of ‘informal social pressure’ to get people to wear masks throughout the Covid era, and champions the concept of a ‘collectivist mindset’.
In effect, these two high-profile behavioural scientists are urging more covert shaming and peer pressure to get people to do the ‘right’ thing.
5. Reinforcements for the pro-mask push then arrived in the form of spokespeople for the World Health Organisation (WHO) – a prominent mouthpiece for the global pandemic industry – who have been doing the rounds again, regurgitating the messages we heard throughout the Covid era. For instance, Dr Maria Van Kerkove (an epidemiologist at the WHO’s ‘Health Emergencies Program’) has been popping up on social media sharing scary stories about variants and urging us all to mask up when ‘around other people’. While Dr Abdirahman Mahamud (an ‘Incident Manager’ at the WHO) stridently proclaims that ‘masking saves lives’, a preposterous assertion that would – in a rational world – send the official fact-checkers into overdrive.
6. If – God forbid – mask mandates were to return, public transport is likely to be the first target. So a story highlighting the risks associated with air travel would be gold dust for the propagandists. And, hey presto, we have one. Evidently, some researchers have been rummaging in the waste-water systems of 29 aeroplanes and found that, in 28 of them, they contained the virus responsible for Covid-19. (I wonder how many millions of other bugs they would have found among the excrement?).
7. And to cap it all, Nicola Sturgeon – the mask matriarch from north of the border – appears again at a press conference to urge us all to wear masks on public transport.
If our public health specialists had been following the science, the requirement to wear masks in community settings would never have been imposed; the bulk of the more robust, real-world evidence concludes that community masking has no appreciable impact on viral transmission. Also, it is apparent that the mask U-turn in 2020 – when our experts shifted from a ‘masks don’t work’ narrative to an authoritarian one involving mandates – was driven by ideology rather than empirical research. Taking these two observations into account, it is now morally appropriate to resist this latest push by the pro-mask lobby for the re-imposition of this ineffectual and dehumanising restriction.
And what would be the most effective way to counter further mask mandates? DO NOT COMPLY.
Featured Video

“Historic Russia”: The Land Putin Will Not Give Back
or go to
Aletho News Archives – Video-Images
From the Archive
How Ukraine Tortured and Slaughtered Donbass
By Kit Klarenberg | Al Mayadeen | July 11, 2024
Almost immediately after the proxy war erupted, ISIS-tier footage of the torture and murder of Russians in Ukrainian custody emerged.
On July 6th, the New York Times published an astonishing investigation: In Ukraine, Killings of Surrendering Russians Divide an American-Led Unit. The article documents in grim detail how Chosen Company, an international volunteer battalion for Kiev, routinely executes Russian prisoners of war. It is the very first mainstream admission that this practice – a brazen breach of the Geneva Conventions, and a grave war crime – is widespread among Ukraine’s fighters, both foreign and homegrown. … continue
Blog Roll
 Aletho News
- Record Oil, Empty Tanks: The UAE’s Miracle Recovery
- Burnham tackles Britain’s poverty with aggression in Yemen
- Peace in Ukraine: the easy way – or the hard way
- Trump & the Rrrrussians
- US taxpayer money laundered back through Ukraine – Musk
- Before COVID, an NIH lab chief proposed making a SARS-like bat virus more infectious
- Gates, Bourla on Trial in Netherlands Accused of ‘Great Reset’ Scheme at Vaccine Injury Hearing
- BRITAIN’S WARNING: PREPARE FOR WAR
- “Historic Russia”: The Land Putin Will Not Give Back
- How the Cambridge Analytica scandal still haunts Mark Zuckerberg
- If Americans Knew
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- Damning report shows the media must confront its failures on Gaza
- BBC senior broadcaster speaks out on Gaza coverage
- Netanyahu vows vast West Bank invasion in response to 20-minute skirmish that left 2 Israeli soldiers and 2 Palestinian fighters dead
- Tied up and tortured: Israel using US-made electroshock weapons on Palestinian detainees
- The outsourced risk: how newsrooms rely on Gaza’s freelancers without protecting them
- Gaza bakeries forced to shut as Israel blocks flour shipments
- Gaza’s breast cancer patients face a deadly wait for treatment amid Israel’s genocide
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- The Israel Lobby’s Changing Fortunes
- No Tricks Zone
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago

