COVID SHOTS FLAGGED FOR PARALYTIC SYNDROME
The Highwire with Del Bigtree | June 2, 2022
It wasn’t true

The Naked Emperor’s Newsletter | June 2, 2022
“In the current large population study of subjects, who were not vaccinated against SARS-CoV-2, we observed no increase in the incidence of myocarditis or pericarditis from day 10 after positive SARS-CoV-2.”
Remember when you were told to get vaccinated but you had concerns about myocarditis? Remember when the scientists, doctors and people we are meant to trust said not to worry because you were more likely to get myocarditis from Covid? Well, it wasn’t true.
A study published last month in the Journal of Clinical Medicine on MDPI took a look at the incidence of myocarditis and pericarditis in post COVID-19 unvaccinated patients. It was undertaken by the University of Jerusalem and Tel Aviv University and looked at 213,624 adult patients who had a documented positive COVID-19 test.
16,632 patients with a first vaccination received before COVID-19 infection were excluded, leaving 196,992 patients versus 590,976 in the control group, to study. The control group consisted of patients with one or more negative COVID-19 tests and no vaccination.
When the authors looked at the results of their study, they concluded that there was “no statistical difference in the incidence rate of both myocarditis and pericarditis… between the COVID-19 cohort and the control cohort” I.e. COVID-19 did not increase the risk of myocarditis and pericarditis when compared with those who did not get Covid.
These results tie in with a previous study in Nature, which I wrote about in April. This found a greater than 25% Increase in Cardiovascular events in under 40s during Vaccine rollout but NOT during Covid waves.
Numerous other studies have found that the vaccines increase the chances of myocarditis and pericarditis and this is openly acknowledged on government websites and vaccine reference material.
However, up until now, one of the excuses for continuing to give these vaccines was that you were more likely to get myocarditis or pericarditis with a Covid infection. This study shows this to be false.
Once again, a conspiracy theory has come true again.
BY JEFFREY A. TUCKER | BROWNSTONE INSTITUTE | JUNE 2, 2022
From the very outset of this pandemic, the topic of natural infection has been a taboo. To suggest that anyone might have been better off risking infection and thereby gaining immunity from a respiratorial virus rather than hiding under the sofa for two years was seen as outrageous and irresponsible.
My theory is that the reason has always been political. And that’s tragic.
Generations have gone by that have understood it. A life strategy to flee all pathogens is deeply dangerous. The immune system, in order to be trained to protect against severe disease, needs exposure. Not to all things, of course, but to many pathogens that are not finally debilitating or fatal. We’ve evolved with pathogens in what Sunetra Gupta calls a “dangerous dance.” This dance is unavoidable, especially for fast-mutating viruses like SARS-CoV-2.
And yet from the beginning, this knowledge seemed to be lost. This is gravely embarrassing since it’s been known for 2,500 years. It was worse than just lost. As a person who wrote almost daily during the pandemic, I too was careful not to discuss this topic with too much bluntness. We all felt the political pressure to stay silent or at least cloud our prose with euphemisms.
The single most controversial sentence of the Great Barrington Declaration was this one: “The most compassionate approach that balances the risks and benefits of reaching herd immunity, is to allow those who are at minimal risk of death to live their lives normally to build up immunity to the virus through natural infection, while better protecting those who are at highest risk.”
That talk about building up immunity is what drove people bonkers, as if no one was somehow allowed to utter a settled scientific truth. And yet long before Fauci began to speak as if getting infected was the worst possible fate, he was more honest.
Even I knew (from what I learned in 9th grade and what my mother taught) that the pandemic would only end with endemicity naturally earned. That is precisely what is happening. The CDC’s publication MMWR printed a seroprevalence study showing that from December 2021 to February 2022 – that period during which it seemed like everyone in the country got covid – went from 33.5% to 57.7%. In children, it went from 44.2% to 75.2%. It’s higher in both groups now.That the study got no real attention to it shows that we are fast moving toward the end, and how? Not through vaccination, which protects against neither infection nor transmission. It ends with everyone meeting the virus. There is of course some threshold of herd immunity with this virus, though it keeps rising with each mutation, requiring ever more rounds of infection to achieve it. It is surely higher than 70% but probably less than 90% depending on population mobility and other factors.We can look at that data today and wonder. What if we had never locked down? What if we had gone on with life as normally while urging those in risk categories to wait it out a bit while we achieved endemicity? How long would it have taken to get there?
Might it have been over by the summer of 2020? It is possible. It’s hard to know such counterfactuals with precision, but it does seem highly likely that the lockdowns achieved nothing good, caused tremendous damage, and also unnecessarily prolonged the pandemic. In addition, they degraded everyone’s immune system: we didn’t just avoid covid but everything else too.
And the main reason was due to the unwillingness of public health authorities to talk about actual science. When Fauci was asked about natural immunity in September 2021, he said “I don’t have a really firm answer for you on that. That’s something that we’re going to have to discuss regarding the durability of the response…I think that is something that we need to sit down and discuss seriously.”
The WHO even changed its definition of herd immunity to exclude natural infection as a factor! The whole institution gave itself over to vaccine sales based on wild exaggerations of their effectiveness while all-but-denying robust and broad immunity through exposure.
A key political factor to natural immunity is that it does not call on government to assume totalitarian controls to stop a virus. It presumes the operations of a normal society. The government wanted all power and deployed it to stop the virus. Therefore, science was out of the question, replaced by political propaganda from start to finish.
It’s not well understood that the US policy from the very outset accepted and adopted a zero covid approach. That gradually unraveled over time as unworkable. Trump’s own advisors tricked him into believing that he could achieve that just like Xi Jinping did. He fell for it, and pushed the two weeks to flatten the curve under the belief that this would make the virus go away. His rhetoric that day set the stage for more than two years of utter nonsense.
And here we are all this time later and top headlines are finally admitting what should have been obvious from the beginning. For a virus this prevalent, it ends with widespread natural immunity. Here’s the Bloomberg headline:

The rest of the article is designed to walk back that core claim. We are still not ready to face the terrible realities that the lockdowns achieved nothing and that the vaccines did not end the pandemic. The taboo subject of meeting the virus is still today what it was 30 months ago, nearly unsayable.
My theory is that this is entirely for political reasons. They hatched a wild plan to control a virus that would come and go like all such viruses in history, and so therefore they had to pretend their efforts were essential to the great task. They never were. That’s the bitter reality.
Reflecting on this topic of exposure and immunity eventually leads a person to realize that we don’t need centralized control, coercion, and dictatorial power to manage a pandemic. Pandemics are unavoidable but they largely manage themselves while the best-possible outcomes rest with the intelligence of individuals informing choices based on their own risk assessment. (I feel like I’ve been writing some version of that sentence for 33 months.)
And this speaks to the big problem we have today. The people who did this to us have not admitted error and probably won’t. Despite all the failures, these same people are gearing up for another round of lockdowns based once again on the ideology that the worst-possible fate for anyone is to face a virus naturally and bravely.
Think about this: our lords and masters are saying that our only choice in the face of any prevalent pathogen is to hunker down, don’t hold parties, don’t send kids to school, don’t go to church, don’t go work, don’t travel, and instead just wait for them to make a fancy serum to inject in our arms, which we must accept whether we like it or not.
In short, a government that seeks to control all pathogenic spread is one with totalitarian powers that knows not human rights or freedoms.
The Counter Signal | June 2, 2022
While countries around the world continue to drop their COVID mandates, Trudeau says Canada’s are here to stay due to the risk from new variants that don’t even exist yet.
“The reality is, as much as people would like to pretend that we’re not, we’re still in a pandemic,” he said.
“There are Canadians who die every single day because of COVID-19 in our hospitals.”
Trudeau adds that vaccine mandates are needed to protect against variants that do not (yet) exist.
“We are still at risk, particularly at risk, as Fall approaches, of new variants.”
“. . . What will also further damage our tourism industry is if we get another wave. If we get more serious impacts from COVID.”
This announcement comes a day after Canadian airline Westjet’s CEO, Alexis von Hoensbroech, spoke out against the mandates.
“As vaccines are not preventing the spreading of the virus since Omicron, there is no more logic to maintain it,” he said.
Indeed, most countries dropped their COVID mandates weeks, if not months ago. The latest country to do so was Italy.
Additionally, even big Pharma and Bill Gates have acknowledged the futility of the current vaccines and their mandates.
In January, Pfizer CEO Albert Bourla admitted that two doses of the vaccine “Offer very limited protection if any.” He further claimed his team was working on a new vaccine, “Version 1.1,” to effectively tackle the Omricron variant. However, to date, nothing has been produced.
And last week at the WEF conference in DAVOS, Gates admitted the vaccine wears off fast and doesn’t block transmission.
Earlier this week, Liberals, NDP, and Bloq Quebecois members of Parliament rejected a motion to lift the travel restrictions that conservative members had put to a vote.
The next day, the Trudeau government extended the current requirements until at least June 30.
But, given that future variants are always possible, Trudeauian logic implies there’s no end in sight.
By Steve Kirsch | June 1, 2022
Executive Summary
They are adopting authoritarian medicine in Ontario, Canada by requiring physicians to either follow authoritarian guidelines which are not science based, or have their license to practice medicine revoked.
If you live in Canada, please contact the members of the College of Physicians and Surgeons of OntarioCollege of Physicians and Surgeons of Ontario and let them know what you think of their actions.
If you live in California, which is about to go the same way, please donate NOW to the campaigns of Michael Huang and Brian Tyson.
Introduction
Dr. Ira Bernstein who practices medicine in Ontario, Canada is about to have his license to practice medicine revoked soon. Currently he is required by the authorities to operate under the following restrictions:
Furthermore, Dr. Bernstein is now required to post a sign in his waiting room that says this:
Dr. Bernstein must not provide medical exemptions in relation to vaccines, mask requirements or diagnostic testing for COVID-19. Dr. Bernstein must not prescribe ivermectin or hydroxychloroquine. Further information may be found on the College of Physicians and Surgeons of Ontario website at www.cpso.on.ca
What was his crime?
None of his patients complained. None of his patients were hospitalized or died from COVID. Nobody was harmed.
What was his crime? He didn’t toe the line and treat COVID patients like the College thinks they should be treated.
The message to physicians in Canada is clear: you either treat COVID patients using methods approved by the medical authorities or they’ll take away your livelihood for the rest of your life.
If this type of authoritarian medicine can happen in Canada, it can happen everywhere else in the world. No Canadian physicians are coming to Dr. Bernstein’s defense publicly because doing so would jeopardize their license.
Who is behind this? The College of Physicians and Surgeons of Ontario. They are listed here. I’m sure they are all proud of their actions because the President wrote this (emphasis mine):
The CPSO is here to help support physicians, and in doing so, fulfill our mandate to serve the public trust in Ontario’s health care. I am proud of the CPSO’s clear messaging to its membership regarding vaccine and mask exemptions. Our role is to protect the public and that includes protection from misinformation and risk of ignoring public health policies.
These people are incompetent. Their recommendations are based on politics, not science. They are the ones that should have their licenses revoked.
For example, they think masks work even though masks have never worked to slow or stop any virus in history and the best controlled large-scale study (in Finland) showed that wearing masks resulted in higher infection rates (as UCSF Professor Vinay Prasad pointed out). That’s what the best science says.
In Ontario, a doctor faces NO professional discipline for giving hundreds of children under 5, some as young as 6 months old, the COVID jab. No matter how many die, they will not be sanctioned.
I’ve reached out to the College to see if any members will appear on our weekly VSRF calls. Don’t hold your breath on that one.
Welcome to the new world of authoritarian medicine!
California is going to be implementing similar policies. Your state is next.
We’re basically on our way to implementing the same thing in California. Check out this article:

I received this message:
I hate to tell you but there is already a bill in the California legislature that is proposing just that: either a doctor does as he/she is told or his/her license could be revoked and/or disciplinary action could be taken. My father who was a practicing physician and surgeon for the better part of 40 years told me when I worked for him told me that the insurance industry would capture the medical industry within 25 years after the institution of Medicare. That was in 1975. That has now taken place. If the proposed California legislation goes through, we can kiss traditional medicine and the conscientious practice of medicine by unfettered medical practitioners goodbye. We have to oppose the legislation in California or it will spread like wildfire throughout this country and, yes, the US will be just like Canada.
And this message:
The same criminal and idiotic medical regulations are in place in Australia, and have been since the start of the Covid 19 “pandemic”. The Canadians must be singing from the same song-sheet as AHPRA (Australian Health Practitioners Regulation Authority). I wonder who wrote the lyrics?
It’s important to memorialize statements like this in the public record to show that there were millions of critical thinkers who were being ignored.
What you can do
If you live in Ontario, Canada, you can reach out and contact the members of the College and let them know what you think of their actions. Please don’t just sit back and let this happen.
If you live in California, please make a generous contribution to red-pilled doctors running for public office such as Michael Huang and Brian Tyson.
Please donate immediately as these doctors could really use the funds and the election is days away. It is now or never. Thank you.

By Paul Joseph Watson | Summit News | May 30, 2022
Billionaire Bill Gates says there’s a 50 per cent chance the next pandemic will be caused by man-made climate change or be deliberately released by a bio-terrorist.
The Microsoft founder made the comments during an interview with Spanish news outlet El Diario.
Asserting that the next major pandemic is likely to occur within 20 years, Gates said, “It could be a virus made by man, by a bioterrorist who designed it and intentionally circulated it. That is a very scary scenario because they could try to spread it in different places at once.”
“Or it could be something that makes the leap from the natural world. The human population is growing and we are invading more and more ecosystems. That is why I calculate that there is a 50% chance that we will have a pandemic of natural origin in the next 20 years, as a consequence of climate change,” he added.
The prediction that climate change will cause a virus which will then require another global vaccine rollout is somewhat convenient for Gates given that he is heavily invested in both areas.
Gates reiterated the call made in his recent book to pump billions of dollars into researching future pathogens by creating a 3,000-strong team of specialists under the control of the World Health Organization, which would require a 25% budgetary increase.
Commenting on the recent outbreak of monkeypox, Gates said “there is very little chance” it will have an impact anything like coronavirus, although he cautioned that it could mutate into something significantly nastier.
Gates infamously warned of a coming super-virus five years before the emergence of COVID-19 during a 2015 TED talk.
As we highlighted earlier this month, Gates warned that COVID was not over and that there is likely to be an “even more fatal” variant of the virus coming.
During an event at the Munich Security Conference back in February, Gates said that “sadly” Omicron is a “type of vaccine” and has “done a better job getting out to the world population than we have with vaccines” by providing natural immunity.
eugyppius – May 29, 2022
Last year, the CDC published a paper comparing Pediatric COVID-19 Cases in Counties With and Without School Mask Requirements. The authors looked at data from 520 United States counties, concluding that “Counties without school mask requirements experienced larger increases in … case rates … compared with counties that had school mask requirements.” Corona astrologers and face diaper fetishists everywhere have used the findings to argue for forcing healthy children who are at no risk to wear fasks masks for multiple hours each school day.
More county-level data on American infection rates and mask mandates has since become available, and two Toronto scientists have taken the opportunity to replicate the study, looking now at 1,832 counties. In a turn of events that will surprise nobody, they find that the larger dataset shows that mask mandates actually do zero, and that prior findings were almost surely an illusion.
Here are masked vs. unmasked case rates, using a smaller data pool similar to that from the CDC study:
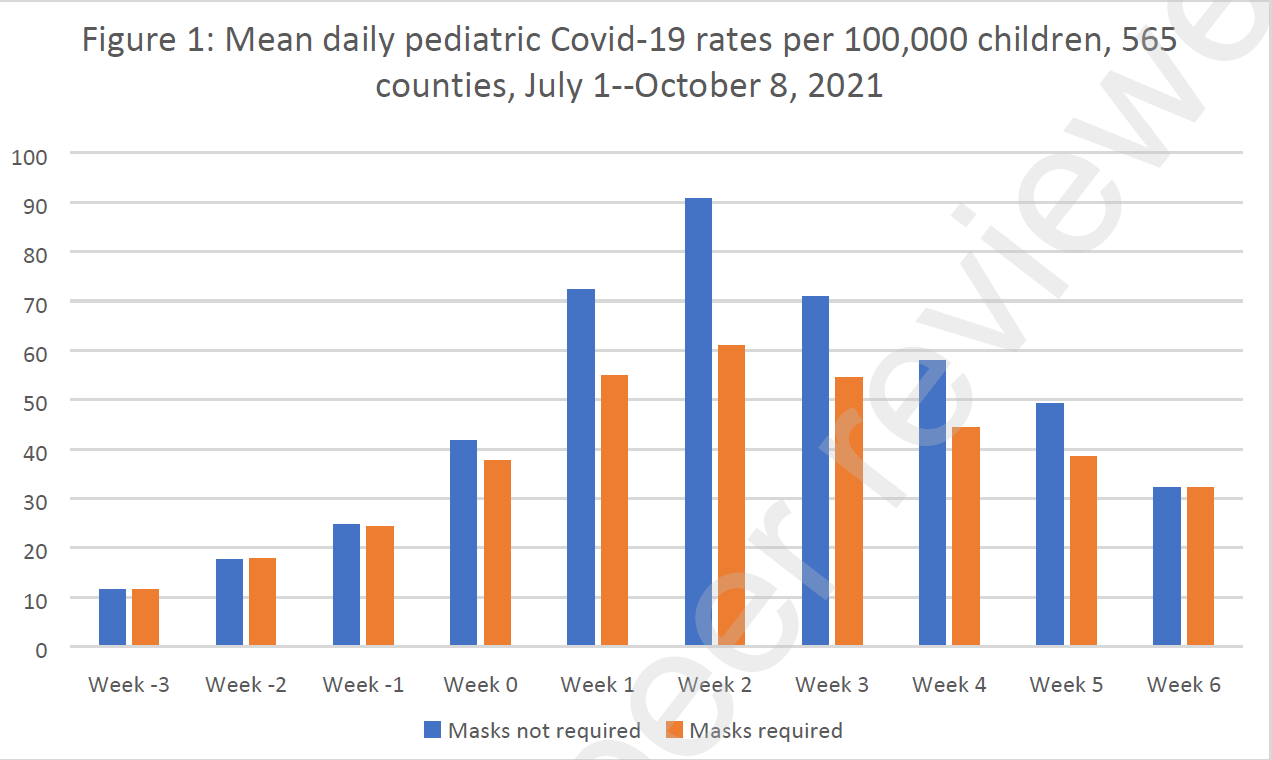
Yes, the maskless counties seem to do worse! Yet the Toronto authors point out that the original CDC study only considered infection rates through the second week after schools reopened, which turned out to be “exactly the peak of school case numbers for [their] sample of counties.” This obscured the fact “that cases quickly declined in later weeks and did so faster in counties without mask mandates.” Even the smaller sample used by the CDC study, in other words, showed no difference in masked vs. unmasked counties by the six-week mark.
The replication, with a much bigger dataset, meanwhile, showed that maskless counties never led infections at all:
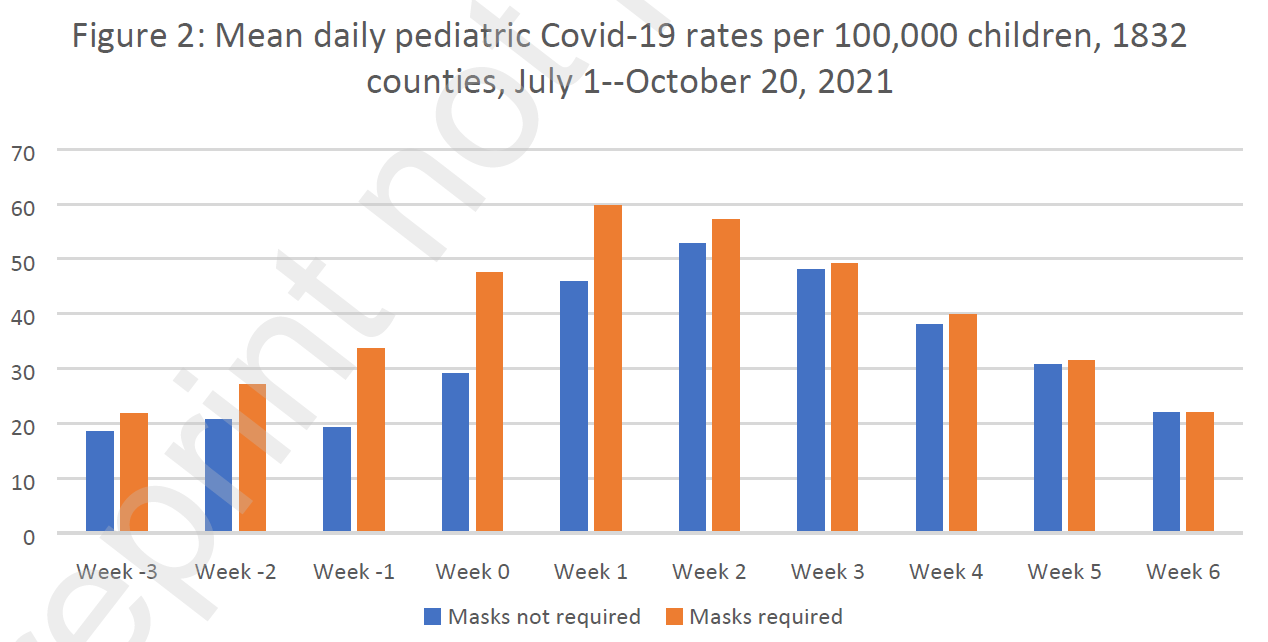
The authors note that the CDC study, by ending their analysis on 4 September 2021, effectively excluded counties with a school-start date after 14 August, which entailed an oversampling of southern states. I’ll fill in the blanks here: Counties in the American south tend to have fewer school mask requirements, and also to experience late summer infection spikes related to high temperatures and extensive reliance on climatisation.
Although masks have become the most clearly discredited measure deployed against SARS-2 (which is saying something), they just won’t go away. Even in places that have lifted all Corona restrictions, a great many people continue to mask in public, and it seems likely that many countries – Germany among them – will retain vestigial mask requirements indefinitely, probably for years. Masking is a totally unsupported superstitious practice that does nothing against viral infection, and yet for precisely this reason, no amount of evidence will ever convince the maskers to stop.
By Justin Hart | Rational Ground | May 26, 2022
Every year humans endures a “flu season” – a period denoting the high-water mark of that year’s wave of respiratory viral pathogens. Believe it or not we still have strains of the 1889 Russian flu, the 1918 Spanish flu, the 1957 Asian flu, the 1968 Hong Kong Flu, the 2009 H1N1 virus – all these various strains of nasty bugs rear their head every single year.
In late 2019, a new “novel” pathogen appeared on the scene – a bug from the “Coronavirus” family (“corona” describing the spike-like structure of the particles.) The official title was SARS-CoV-2. SARS = “severe acute respiratory syndrome”; CoV-2 = “Coronavirus 2.” This particular virus can cause a disease called COVID-19 (“Coronavirus Disease 2019”). The disease is thought to have originated in China and found significant human-to-human transmission. It is thought to be “novel” because prior infections of other pathogens do not seem to create anti-bodies to tackle this newfound disease within the human body.
Officials raised alarms about the potential mortality witnessed from COVID-19. Governments across the world scrambled to address and protect their populations from what quickly became a pandemic. Efforts ranged from stringent to downright authoritarian. Results were mixed to say the least. In early 2022, it was thought that SARS-Cov-2 and COVID-19 would join the panoply of viruses and diseases we experience during the annual ebb and flow of life.
That’s the short sterile version of what transpired.
Here’s what actually happened:
All of this was designed to latch onto a virus that many assert has unnatural origins. The ramifications of a man-made virus set loose upon the world by accident or on purpose should frighten us more than the virus itself. Someone was playing god and it appears they are just getting started.
My book, Gone Viral: How Covid Drove the World Insane comes out in September.

The Highwire with Del Bigtree | May 26, 2022
As the monkeypox outbreak saturates the news cycle, we check in with Epidemiologist and Cardiologist Dr. Peter McCullough to look into the danger the virus poses to the public.
By Dr. Joseph Mercola | May 26, 2022
Well, the COVID jab pushers have had to resort to all sorts of obfuscation to hide the fact that the injections don’t work, and now they’re really scraping the bottom of the barrel of excuses. According to a recent Reuters report,1 “Increased contact among vaccinated people can give the false impression that COVID-19 vaccines are not working.”
This irrational explanation has been levied in response to studies showing COVID-jabbed individuals are getting infected at higher rates than the unjabbed, and there are many such studies.
“These studies are likely to involve statistical errors, particularly if they did not account for different contact patterns among vaccinated versus unvaccinated people,” Korryn Bodner, a research associate in infectious disease modeling in Toronto, told Reuters. Bodner is the first author of a preprint study2 posted on medRxiv at the end of April 2022.
Are the Jabbed More Carefree Than the Unvaxxed?
Bodner’s claim is that those who got the jab may be more likely to throw caution to the wind and mingle with others, hence getting infected more frequently, while the unjabbed may be more cautious because they know they’re vulnerable. This rationale is dubious at best, considering:
a)The unvaccinated have continuously been accused of not taking COVID seriously and going about their lives as normal
b)Those who have taken the jab are, by and large, a far more fearful lot; they tend to listen to the “authorities” and take all of their advice to heart, which would include avoiding large gatherings and close one-on-one interactions without wearing a face mask
Check out the following story, reported by Anchorage Daily News :3
“Arianne Bennett recalled her husband, Scott Bennett, saying, ‘But I’m vaxxed. But I’m vaxxed,’ from the Washington hospital bed where he struggled to fight off COVID-19 this winter … Bennett went to get his booster in early December after returning to Washington from a lodge he owned in the Poconos, where he and his wife hunkered down for fall.
Just a few days after his shot, Bennett began experiencing COVID-19 symptoms, meaning he was probably exposed before the extra dose of immunity could kick in. His wife suspects he was infected at a dinner where he and his server were unmasked at times …
‘He was absolutely shocked. He did not expect to be sick. He really thought he was safe,’ Arianne Bennett recalled. ‘And I’m like, ‘But baby, you’ve got to wear the mask all the time. All the time. Up over your nose.'”
Within days of his third dose, he got a serious case of COVID. Yet they blame it on hypothetical exposure to an apparently healthy food server. This kind of irrational reasoning is prevalent among those who got the jabs and who keep going back for more as they are part of the 30% of the population that have been completely brainwashed.
To reiterate what I’ve explained since 2020, asymptomatic spread is likely to be so rare as to be nonexistent.4 It was a lie perpetuated to drive up fear and prop up rising “case” rates that didn’t really exist. It’s basic virology that you cannot transmit a virus unless you have a “hot” infection, and if you have an active, transmissible infection, you have symptoms. The symptoms are a sign that your body’s defenses are kicking in to rid itself of the live virus.
No symptoms, no transmission. So, unless the server was feeling sick and went to work anyway, the simplest explanation for Bennett’s demise was the shot itself. And if the server was sick, the fact that Bennett got so ill suggests the shot is ineffective, even at two doses.
The pro-pharma shills want you to believe there are so many confounding variables, we can’t possibly draw any conclusions from data showing the shots don’t work. Yet looking at data from a wide spectrum of sources, all show the same alarming trends. What “confounding factor” could possibly account for ALL of them being misinterpreted?
An Unproven Hypothesis
Reuters 5 does note that Bodner’s simulations “do not prove that this type of bias affected studies of vaccine effectiveness versus the Omicron variant.” What it does show, according to Bodner, is that “even if vaccines work, increased contact among vaccinated persons can lead to the appearance of the vaccine not working.”
In other words, this is a hypothesis that has yet to be proven. Her modeling suggests it COULD make the jabs appear ineffective IF those who got the jab actually behave very differently from the unjabbed.
But again, it’s highly unlikely that the unvaccinated are avoiding exposure by steering clear of close contacts and crowds to a greater degree than those who got the jab. It’s far more reasonable to suspect that the shots don’t work.
On a side note, Bodner’s study was funded by the Canada COVID-19 Immunity Task Force.6 This task force is housed at McGill University in Montreal, Canada, and McGill University is a long-term recipient of grants from the Bill & Melinda Gates Foundation.7,8,9,10
What Do the Data Say About COVID Jab Effectiveness?
Based on data from around the world, it seems clear that the COVID gene transfer injections are not working. In fact, they’re having the opposite effect of what you’d expect from a real vaccine. According to a Washington Post analysis of state and federal data,11 in September 2021, when Delta was most prominent, 23% of those who died from COVID in the U.S. had received the jab.
In January and February 2022, when Omicron started dominating, that percentage jumped to 42%. In December 2021 and January 2022, just under half of all the COVID patients in intensive care at Kaiser Permanente’s hospital system in Northern California had also received one or more shots.12
Many argue that Omicron was more contagious than Delta, hence the higher death toll. But Omicron was also far milder than Delta, so why would the jabbed die at a higher rate from a less lethal variant than a more lethal one?
One attempt at an explanation is that the fatalities are now occurring primarily among the elderly. Nearly two-thirds of those who died from COVID during the Omicron wave were 75 and older. During the Delta wave, 75-year-olds and older accounted for just one-third of the deaths.13
But that was the case from the beginning, and it still doesn’t answer the question: Why would old people be more likely to die from a milder virus than a more serious one? To answer that question, the injection pushers revert back to the argument of waning potency. Two-thirds of those who died in January and February 2022 did not have a booster shot. According to Anchorage Daily News :14
“Experts say the rising number of vaccinated people dying should not cause panic in those who got shots, the vast majority of whom will survive infections. Instead, they say, these deaths serve as a reminder that vaccines are not foolproof and that those in high-risk groups should consider getting boosted and taking extra precautions during surges.”
So, in other words, the jab only works for a handful of months, and then you have to take another. And another. And another. According to the U.S. Centers for Disease Control and Prevention,15 the first two doses wear off after five months, necessitating a third dose, and the third dose wears off in just four months, at which time you’re supposed to get dose No. 4.
Israeli data16 show the effectiveness of shot No. 4 in preventing severe disease declines by 56% in just seven weeks. So, it appears the protection you get from the shots keeps getting shorter with each dose. Meanwhile, data show the shots can render you increasingly susceptible to all manner of infection and disease, through a wide variety of mechanisms.
Moderna Trial Data Reveal Repeated Infections Are Likely
Among such data is a preprint study17 posted on medRxiv April 19, 2022, which found adult participants in Moderna’s COVID jab trial who got the real injection, and later got a breakthrough infection, did not generate antibodies against the nucleocapsid — a key component of the virus — as frequently as did those in the placebo arm.
Curiously, placebo recipients produced anti-nucleocapsid antibodies twice as often as those who got the Moderna shot, and their anti-nucleocapsid response was larger regardless of the viral load. As a result of this reduced antibody response, those who got the jab may be more prone to repeated COVID infections. As reported by The Defender :18
“[T]he authors found that using the presence of anti-nucleocapsid (anti-N) antibodies to determine whether a person was exposed to SARS-CoV-2 will miss some infections. Thus, the sensitivity of this kind of test, when applied to vaccinated individuals, is not ideal.
However, there are more important implications19,20 of these findings … Specifically, the study implies that the reduced ability of a vaccinated individual to produce antibodies to other portions of the virus may lead to a greater risk of future infections in the vaccinated compared to the unvaccinated.
It is important to note that this is not just another argument for the superiority of natural immunity. Rather, this is evidence suggesting that even after a vaccinated person has a breakthrough infection, that individual still does not acquire the same level of protection against subsequent exposures that an unvaccinated person acquires.
This is a troubling finding, and something investigators conducting the Moderna vaccine trial likely knew in 2020.”
UK Data Confirm Results
These findings are corroborated by data from the U.K. Health Security Agency. It publishes weekly COVID-19 vaccine surveillance data, including anti-nucleocapsid antibody levels. The report21 for Week 13, issued March 31, 2022, shows that COVID-jabbed individuals with breakthrough infections have lower levels of these antibodies — a finding they attributed to the protective benefit of the shot:
“These lower anti N responses in individuals with breakthrough infections (post-vaccination) compared to primary infections likely reflect the shorter and milder infections in these patients.”
However, this interpretation is likely flawed, because less severe infection is associated with lower viral load, and as the study above demonstrated, the “vaccinated” have lower anti-nucleocapsid antibody levels than the unvaccinated at all viral load levels, but especially so at the lowest viral loads. As noted by The Defender :22
“This is one of the most significant findings of the study because it overturns the heretofore unchallenged idea that decreased seroconversion in the vaccinated is due to less severe infection in this population — which is a benefit provided by the vaccine.
However, this new study shows that even at low viral loads, the unvaccinated are more likely to seroconvert than those who are vaccinated. In fact, the difference in seroconversion rates is the greatest at lowest viral loads. The decrease in conversion rates is not a result of a benefit from the vaccine. It is a consequence of it.”
Boosted Now Have Three to Four Times Higher Case Rates
The Defender also reviews other U.K. data showing the COVID case rate is three to four times higher among those who have received a booster shot, compared to the unvaccinated. This is true for all age groups with the exception of children under 18:23
“What could explain such a large increase in infection rates among the boosted? Interestingly, the authors … warn that the unvaccinated may have contracted COVID-19 prior to the observation period — in other words, they may have acquired natural immunity previously, giving them added protection …
But their own data tells the opposite story. The boosted are more likely to contract the disease — by a factor of 3 to 4. How do we know whether the larger infection rates in the boosted are due to more robust immunity in the unvaccinated because of prior infection or due to an immune deficiency in the boosted?
The question can be definitively answered by examining the trend of infection rates [using] … the equivalent table from two months earlier. There is still a greater infection rate among the boosted, but it is only two to three times higher. If the authors’ hypothesis was correct, the more recent data should have shown less of a difference, not more.
If anything, their data support the finding that the decreased seroconversion rates in the vaccinated may be causing a greater risk of repeated infections.”
Walgreens’ Data
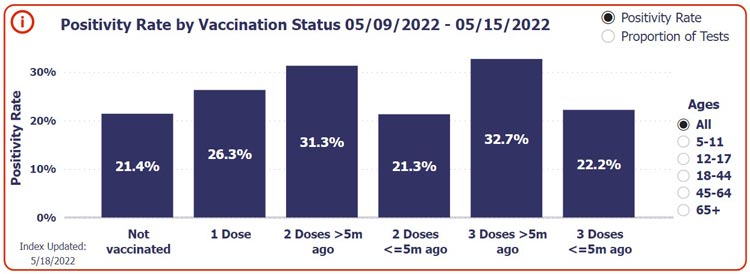
Data from the pharmacy chain Walgreens in the U.S. also reveal the same trend — COVID-jabbed individuals are testing positive for COVID at higher rates than the unjabbed, and those who got their last shot five months or more ago have the highest risk.
As you can see in the screenshot from Walgreens’ COVID-19 tracker24 below, during the week of May 9 through 15, 2022, 21.4% of unvaccinated individuals who got tested for COVID got a positive result. Of those who had gotten just one COVID shot, the positivity rate was 26.3%.
Of those who received two doses five months or more ago, 31.3% tested positive, and of those who received a third dose five months or more ago, the positive rate was 32.7%. So, after the first booster shot (the third dose), people are at greatest risk of testing positive for COVID.
Risk-Benefit Analyses
We also have the benefit of more than one risk-benefit analysis, and all show that, with very few exceptions, the COVID jabs do more harm than good. A risk-benefit analysis27 by Stephanie Seneff, Ph.D., and independent researcher Kathy Dopp, published in mid-February 2022, concluded that the COVID jab is deadlier than COVID-19 itself for anyone under the age of 80.
Another analysis,28 which relied on data in the U.S. Vaccine Adverse Events Reporting System (VAERS), concluded that in those under age 18, the shots only increase the risk of death from COVID, and there’s no point at which the shot can prevent a single COVID death, no matter how many are vaccinated.
If you’re under 18, you’re a shocking 51 times more likely to die from the jab than you are to die from COVID if not vaccinated. In the 18 to 29 age range, the shot will kill 16 for every person it saves from dying from COVID, and in the 30 to 39 age range, the expected number of vaccine fatalities to prevent a single COVID death is 15. Only when you get into the 60 and older categories do the risks between the jab and COVID infection even out.
A third risk-benefit analysis by researchers in Germany and The Netherlands was published in June 2021, in the journal Vaccines.29 The paper caused such an uproar, part of the editorial board resigned in protest.30 The journal retracted the paper, but after a thorough re-review, it was republished in the August 2021 issue of Science, Public Health Policy and the Law.31
These researchers concluded that, “as we vaccinate 100 000 persons, we might save five lives but risk two to four deaths.”32 A fourth, still preliminary, analysis — based on more than 1,700 death reports collected by Steve Kirsch — shows the shots do more harm than good in anyone under age 60. Kirsch writes:33
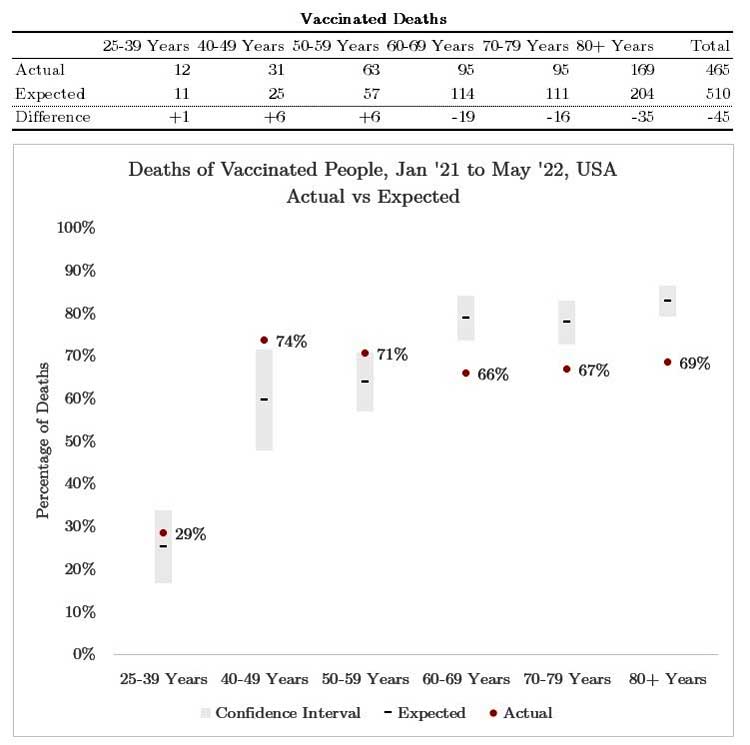
“Figure 1 below is an analysis of survey data I collected. The analysis shows that the vaccines are harmful to those under 60. The red dots higher than the error bar means more vaccinated people observed dead than expected based on the population of vaccinated to all people.
In other words, if we vaccinated 60% of people (middle of the grey bar) and 70% (red dot) of the deaths are vaccinated, we have a serious problem. The precautionary principle of medicine suggests if you are under 60 and thinking of taking a vaccine, you shouldn’t. These preliminary results are both statistically significant …
The conclusion is very clear: nobody under 60 years old should get the vaccine because there is no evidence of a benefit. In fact, if you are between 40-60, it’s clear that vaccination makes it more likely you’ll die, not less likely.”
While some analyses present a direr picture than others, taken together, it’s clear that there appears to be no long term benefits to the COVID jabs. We’re consistently ending up with a higher cost than can conceivably be considered reasonable. The pro-pharma side will likely continue to lob flimsy excuses at the data, but at some point, the truth will be so clear that even the blind will see it. Until that day, continue to inform yourself and share what you find.
Sources and References

or go to
Aletho News Archives – Video-Images
A new Unbekoming paperback
Peter Gøtzsche reviewed every randomised mammography screening trial ever conducted for the Cochrane Collaboration. Cochrane’s headline is that, assuming a 15% mortality reduction, one woman in 2000 avoids dying of breast cancer over ten years. Ten are overdiagnosed and treated. Two hundred experience false alarms.
But that headline assumes the reduction. When Gøtzsche looked only at the trials with adequate randomisation — the higher-quality ones — the reduction disappeared. No effect on breast cancer mortality. No effect on all-cause mortality.
This is the Cochrane finding, published in the establishment’s own database of systematic reviews.
No woman being asked to consent to a mammogram this week knows it.
That is why the new Unbekoming paperback exists. … continue
 Aletho News If Americans Knew No Tricks Zone
 Aletho News
