Much has been said about the Biden Administration’s re-joining international institutions, after former U.S. President Donald Trump broke away from the standardised participation in international agreements and consensus. Notably, the international community singled out the U.S. under Trump for the so-called “deal of the century”, which veered away from the two-state paradigm that has steered international diplomacy on Palestine and Israel for decades.
Trump’s decision to quit the UN Human Rights Council in 2008 was described by former U.S. envoy to the UN Nikki Haley as determined by the body’s “unending hostility towards Israel.” Echoing Haley, the former U.S. Secretary of State Mike Pompeo called the council “a protector of human rights abusers.” Perhaps Pompeo had conveniently forgotten the U.S.’s own track record of backing military coups which disappeared tens of thousands of political opponents. The same goes for the correlation between U.S. financial aid and human rights abuses – the countries which benefit from U.S. aid uphold similar political trajectories to the U.S.
Not much difference has been articulated in terms of U.S. President Joe Biden deciding to re-join the UNHRC in 2022. U.S. Secretary of State Ned Price stated his “concerns” about the organisation. “We will vigorously oppose the council’s disproportionate attention on Israel, which includes the council’s only standing agenda item targeting a single country.” The Trump administration’s departure from the international community was based on the same alleged premise.
Agenda Item 7, which focuses upon Israel’s violations, is a permanent fixture at the UNHRC and the source of much criticism and allegations of “anti-Israel bias” – a term popularised during the Trump era and extended now through the Biden administration. At the UN General Assembly, Israeli Prime Minister Naftali Bennett also accused the body of being anti-Israel and the U.S.’s return to the international fold as working in Israel’s benefit.
The UNHRC is just as farcical as the UN. Whether the U.S. re-joins or decides to boycott, nothing changes in terms of human rights violations. A U.S. seat on the UNHRC will not alter Biden’s foreign policy, nor will it impede the U.S. from warfare and violence. In 2020, the U.S. military spending increased by 4.4 percent from 2019, according to the Stockholm International Peace Research Institute. The U.S. is the largest military spender globally, making up 39 percent of the global expenditure in 2020. Anyone rejoicing at the U.S. decision to re-join the UNHRC might do well to consider the political violence it is applauding.
Neither Trump nor Biden have portrayed a stance based on human rights values. The same can be said for previous administrations. However, much has been lost in terms of the significance with which Trump exposed and applied U.S. foreign policy.
As long as international institutions exist, and human rights rhetoric remains the only threshold in terms of purported accountability, the mainstream narrative will not take stock of the fact that the U.S., like international organisations, operates from within a manipulation of the human rights and democratic framework. The result is a cycle of violations which are then isolated in terms of the oppressed and the oppressor, to forge a collective concern about human rights. Having a few permanent scapegoats, such as Cuba, for example, which has faced decades of dead-end international support against the U.S. illegal blockade, allows the U.S. to preside over the democratic debacle, even as it annihilates democratic expression throughout the world.
With or without the U.S., the human rights debacle will continue unabated. If, according to the U.S., Cuba does not deserve a seat at the UNHRC, what has the U.S. done to deserve it? In the same vein, given the U.S. inclusion, what values is the UNHRC seeking to impart?
October 20, 2021
Posted by aletho |
Progressive Hypocrite | Human rights, Joe Biden, United Nations, United States |
Leave a comment

Sally Rooney during the Edinburgh International Book Festival on 22 August 2017 in Edinburgh, Scotland. [Simone Padovani/Awakening/Getty Images]
The pro-Israel crowd on social media was quick to pounce on award-winning Irish novelist, Sally Rooney, as soon as she declared that she had “chosen not to sell … translation rights of her best-selling novel, ‘Beautiful World, Where Are You’ to an Israeli-based publishing house”.
Expectedly, the accusations centered on the standard smearing used by Israel and its supporters against anyone who dares criticise Israel and exhibits solidarity with the oppressed Palestinian people.
Rooney’s laudable action was not in the least ‘racist’ or ‘anti-Semitic’. On the contrary, it was taken as a show of support for the Palestine Boycott, Divestment and Sanctions Movement (BDS), whose advocacy is situated within anti-colonial and anti-racist political discourses.
Rooney, herself, has made it clear that her decision not to publish with Modan Publishing House, which works closely with the Israeli government, is motivated by ethical values.
“I simply do not feel it would be right for me, under the present circumstances, to accept a new contract with an Israeli company that does not publicly distance itself from apartheid and support the U.N-stipulated rights of the Palestinian people,” she said in a statement on 12 October.
In fact, Rooney’s contention is not with the language itself, as she stated that “the Hebrew-language translation rights to my new novel are still available, and if I can find a way to sell these rights that is compliant with the BDS movement’s institutional boycott guidelines, I will be very pleased and proud to do so.”
Rooney is not the first intellectual to take an ethical position against any form of cultural normalisation with Israeli institutions, especially those that directly support and benefit from the Israeli military occupation of Palestine. Her position is consistent with similar stances taken by other intellectuals, musicians, artists, authors and scientists. The ever-expanding list includes Roger Waters, Alice Walker and the late Stephen Hawking.
The BDS movement has made it abundantly clear that, in the words of the movement’s co-founder, Omar Barghouti, “the Palestinian boycott targets institutions only, due to their entrenched complicity in planning, justifying, whitewashing or otherwise perpetuating Israel’s violations of international law and Palestinian rights.”
Of course, some are still not convinced. Those critics of the BDS movement intentionally conflate between anti-Semitism and a legitimate form of political expression, which aims at weakening and isolating the very economic, political and cultural infrastructures of racism and apartheid. The fact that numerous anti-Zionist Jews are supporters and advocates of the movement is not enough to make them reconsider their fallacious logic.
One of the ‘politest’ denunciations of Rooney, appearing in the Jewish Forward magazine, was penned by Gitit Levy-Paz. The author’s logic is puzzling, to say the least. Levy-Paz accused Rooney that, by refusing to allow her novel to be translated into Hebrew, she has excluded “a group of readers because of their national identity.”
While the Forward writer is guilty of confusing political ethics and nationality, she is not the only one. Israeli Zionists do this as a matter of course, where the Zionist ideology and the Jewish religion – and, in this case, language – are quite often interchangeable. As a result, the definition of ‘anti-Semitism’ has been stretched to include anti-Zionism – though Zionism is a modern ideological construct. Since Israel defines itself as a Jewish and Zionist state, it follows that any form of criticism of Israeli policies are often depicted as if a form of anti-Semitism.
One of the most interesting aspects of this conversation on language is that the Hebrew language has been used by the State of Israel since its establishment in 1948 as the language of oppression. In the minds of Palestinians, anywhere in Palestine, Hebrew is rarely the language used to communicate culture, literature, social coexistence and such. Instead, every military ordinance issued by the Israeli army, including closures and home demolitions, let alone the proceedings of military court hearings, and even the racist anti-Palestinian chants in football stadiums, are communicated in Hebrew. Palestinians are then excused if they do not view the modern Hebrew language as a language of inclusion, or even innocuous, everyday communication.
These realisations are not the outcome of daily experiences only. Successive Israeli governments have passed numerous legislations over the years to elevate Hebrew at the expense of Arabic. For over seven decades, the ethnic cleansing of the Palestinian people has been coupled with the erasure of their culture and their language, from the Hebraicisation of historic Arabic names of towns, villages and streets, to the demolition of ancient Palestinian graveyards, olive groves, mosques and churches, the Israeli ethnocide is a top item on the Israeli political agenda.
The Israeli Nation State Law of 2018, which elevated Hebrew as Israel’s official language and downgraded Arabic to a “special status”, was the culmination of many years of a relentless, centralised Israeli campaign, whose sole purpose is to dominate the Palestinians, not only politically but culturally as well.
All that in mind, the hypocrisy of Israel’s mouthpieces is unmistakable. They welcome, or at least remain silent, when Israel tries to demolish and bury Palestinian culture and language, but cry foul when a respected author or a well-regarded artist tries, though symbolically, to show solidarity with the oppressed and occupied Palestinian people.
The Palestinian boycott movement is conscious of its morally-driven mission, thus can never duplicate the tactics of the Israeli government and official institutions. BDS aims at pressuring Israel by reminding peoples all over the world of their moral responsibility towards the Palestinians.
BDS does not target Israelis as individuals and, under no circumstances, does it target Jewish individuals because they are Jews, or the Hebrew language, as such. Israel, on the other hand, continues to target Palestinians as a people, downgrades their language, dismantles their institutions and systematically destroys their culture. This is rightly referred to as cultural genocide, and it is our moral responsibility to stop it.
October 20, 2021
Posted by aletho |
Ethnic Cleansing, Racism, Zionism, Solidarity and Activism | Human rights, Israel, Palestine, Zionism |
Leave a comment
IN A recent lecture titled ‘Covid-19 Vaccine Safety and Pivot to Early Treatment: Risks of Scientific Censorship and Reprisal’, and a veritable tour de force, Dr Peter McCullough described his emerging understanding of the ‘catastrophe’ of Covid-19 ‘gene-transfer’ vaccines, the ‘loaded weapon’ of the spike protein they produce, and the high effectiveness of early Covid treatments, tragically denied by governments.
The video of the lecture can be seen here, with a summary provided by Cracknewz.
Today we publish the first section of our edited transcript (subsequent parts will follow over the rest of the week) in which Dr McCullough expresses his deep sense of unease at the stripping of his academic titles and at the inexplicable and unprecedented absence of any safety precautions or monitoring of the novel emergency authorised vaccines.
***
Part 1: Cancelled for telling the truth
I think the reason why everybody is here is we have a sense that something very bad is going on in the world. And I’m here to tell you, I think it is. And . . . it’s influencing all of us, each and every one of us. And it may have started a long time ago. I’m not an expert on this at all, and I know people are working on this. But somehow we’ve all been drawn into this and it’s affecting us. And I think we all have a sense of urgency that now’s the time, now’s the time when things look relatively normal around us in terms of the bricks and mortar and our social structures and our employment, it’s relatively normal now. And I think all of us have a sense it’s not going to be normal soon with the pace that things are moving. So now’s the time, everyone’s asking what can they do? If you feel tension right now and you feel some emotional distress, and if you feel as if things aren’t going right . . . right now, I think your perceptions are correct. And if your perceptions are correct, now’s the time for action.
I’ve recently taken a position as a chief medical adviser for the Truth for Health Foundation, which is a foundation centred out of Tucson, Arizona, which is dedicated to exactly what we’re doing right now. I am the president of the Cardiorenal Society of America, and I’ve been the president for five years. I helped form that organisation. I donated to it. I think I’m going to be stripped of that title with . . . within a week. I’m the editor-in-chief of Reviews in Cardiovascular Medicine. I think I will be stripped of that within a month. Today, I was stripped of the editorship of Cardiorenal Medicine, a Swiss-based journal. And in the last year, I have lost my job at a major health system with no explanation and no due process. I’ve been stripped of every title that I’ve ever had in that institution. I’ve received a threat letter from the American College of Physicians . . .
So whatever’s happening is happening [is] because of our efforts to have some scientific interchange. We are participating in a topic of public importance – that’s the reason why every table [here] is full. What we are doing is lawful. What’s not lawful and what’s not right is what’s happening with respect to censorship and the threat of reprisal.
I’m the senior associate editor of American Journal of Cardiology and if Bill Roberts can keep me in there, I’ll hang in there. My tagline is America Out Loud, talk radio. . . . I am from Texas originally, I went to Baylor University undergraduate, then UT Southwestern. I went on to the University of Washington in Seattle. I came to Michigan. I did three years of general internal medicine actually in Grayling area to pay back my student loans . . . And then I went to University of Michigan School of Public Health and got my Master’s degree in epidemiology. I was kind of trained to do this public health work. I joined Beaumont Hospital under Dr Joel Kahn and Bill O’Neill, and I trained in cardiology. I took my first job at Henry Ford, was the programme director at Henry Ford, became the Chief of Cardiology at the University of Missouri in Kansas City. Returned to Beaumont, was a division chief for a long time. Was the chief academic scientific officer for St John Providence Health System and then moved on. I wanted to finish up down in Texas and I held wonderful positions in Texas.
But I’m not new to the national scene. Even early on when I was at Henry Ford, I was on President Clinton’s advisory panel to health care. When I was at Beaumont, I testified in front of the Congressional Oversight Panel regarding a product label expansion of drugs, and I was on C-SPAN for seven hours getting fried by the senators. So I wasn’t new to this. But what’s new to me now is to be in a position of – and I’ll take it – of authority. OK, I’ll take it because somebody has to. [applause from audience]
I had a window last year when this whole thing started, I had a window to America through a Republican journal, The Hill. And I’m kind of a middle of the road person. I’m not a really hardcore right winger, but The Hill took me and I was a regular contributor to The Hill. And then I changed over and actually started my own radio programme on America Out Loud talk radio, The McCullough Report, because I needed the window. In our medical field, we publish in journals to each other, doctors and scientists. We talk to each other. But the public is largely excluded from that big conversation.
And our journal publications are slow. We’re talking two to five years to get something in print. You know, this thing hit us. We needed to get now. We needed to get things published now. We needed speed because it’s a mass casualty situation. So that’s what this is all about. These letters behind my name, I predict, will be progressively erased. I took one off there this week. It’s going to happen. It’s going to happen because there’s powerful forces at work, far more powerful than we can possibly think of, that are influencing anybody who is in a position of authority. And I already told you, I’m going to take authority.
So the first authoritative position I’m going to take is this: as an American and as a consumer, for new biologic products, demand safety, safety, safety . . . safety . . . We have a situation where there has been an injection of a substance into half of Americans’ bodies. And there’s yet to be a report to America on (its) safety. Astonishing.
Well, it wasn’t the case back in 1976, there’s Gerald Ford getting his swine flu vaccine, right, swine flu in 1976. We got to 25 deaths, 550 cases of Guillain-Barré syndrome, which is ascending paralysis. There were 55million Americans vaccinated, 220million people in the country at that time. [They] shut it down. Not safe. It was very transparent. Americans were watching. Sure, there was some controversy: were the deaths related, not related? It didn’t matter. Unexplained deaths didn’t matter. Shut down the programme. [It was] not safe. It was considered a debacle . . . and it went down as a debacle . . .
In my view, we’ve been gambling. We’ve watched a gamble go on in our country. And the gamble has gone like this: this virus came in and we’re going to test out some new tech, and we’re going to gamble with, not just America, we’re going to gamble with the world. This is a gamble of extraordinary, extraordinary implications. We didn’t have to and we don’t have to, but we did. And this is the gamble. The gamble is genetic gene transfer technology. The FDA considers the current American vaccines Pfizer, Moderna, Johnson & Johnson as gene transfer tech. That’s what it is, it’s gene transfer tech.
There were 24 of these platforms that have been around for decades. They were all designed to transfer genetic information. Most of the time, just to transfer in the RNA to produce a missing protein. For instance, a deficiency disease called Fabry disease, a deficiency of α-galactosidase. I ran the programme in Dallas on this, an interesting medical problem. But it was just simply a way of producing their deficient enzyme. Seems pretty harmless, right? Give the cells an injection of messenger RNA about once a month, maybe once every three months, and then the body could make this needed protein. Okay? There’s been other ones. There’s been attempts in heart failure, in cancer. The only messenger RNA gene transfer technology drug that’s on the market is called Patisiran, and that is a drug that produces a small interfering messenger RNA that interferes with the production of what’s called transthyretin, which is a protein that causes amyloidosis, which is a medical condition.
So we actually do have one of these on the market, but there’s 24 others that have largely been losers, and they’ve been losers in many ways because they couldn’t produce enough of the deficient protein, or they couldn’t actually be reverse transcribed and produced the gene that’s needed to install on the genome.
But these were ready to go, and the adenoviral DNA shown on the left of the screen here. That’s Johnson & Johnson. So that’s an adenoviral vector where these replication incompetent virions come in and they inject DNA into the cytoplasm. The DNA is taken up into the nucleus. From the nucleus, the messenger RNA for the Wuhan spike protein is produced. That messenger RNA then produces the spike protein. But because it’s not a synthetic RNA, it actually is digested within RNA [unclear]. But the issue is, there’s so much of the DNA that goes into the nucleus, there is so much of its persistent effect that Johnson & Johnson can basically get by with one shot, which is amazing. So it is a ton, I can tell you right now, from a genetic perspective, it’s a ton of material that’s going into the human body.
With the messenger RNA vaccines, Pfizer and Moderna are different. These are synthetic messenger RNAs. They have what’s called a nucleoside analogue cap at the three prime and five prime end. And those caps are sturdy. Normally, a messenger RNA is used once it’s disposed of – used, once disposed of. This one is used over and over and over again and stays in the cells for a long time. We don’t know how long, but it looks long. It looks very long.
And we are working with scientists all over the world. And there is a belief now that the messenger RNA can survive cell division so a parent cell can give it to daughter cells. And it looks like the messenger RNA can actually be transferred in little packets called microsomes to other cells. So it’s not just a mosaic of cells that gets the messenger RNA. It may be much more proliferative than that. And the messenger RNA itself is used over and over again to produce the spike protein. The spike protein is the little red characters there. And when they’re expressed on the cell surface, that’s an abnormal protein.
For the first time in human history, we have a biologic product that’s telling our body to produce an abnormal protein. You know, the design of this was to produce a normal protein, but this is to produce an abnormal protein. It’s not just an abnormal protein, it’s the [unclear] or the spine on the surface of the virus. The virus is the ball. The little spines, you’ve seen a million cartoons of it, that’s the spike protein. 1,200 amino acids, probably about eight to 12 glycosylation sites and two major segments to it, S1 in S2 and what connects them is what’s called the furin cleavage joint.
The furin cleavage joint is what was manipulated, we believe, with gain of function research in the lab in China. So in this little red character here, which looks pretty benign, it is kind of a loaded weapon, if you will. And what I mean by weapon, it’s now known that the spike protein itself is independently pathogenic. It causes damage itself, okay? And I think everyone accepts this. When I mean damage, it damages the cells in which it’s produced. When it’s on the cell surface, the body immediately recognises it’s not supposed to be there and attacks. When the spike protein breaks free, which it does, it circulates in the human body for about two weeks. In a paper by Ogata and colleagues – this is being filmed and this is going to be fact-checked, so I want the fact-checkers to see that – Ogata et al, Harvard circulates in measurable and plasma for two weeks after a messenger RNA vaccination. After the second shot, it’s no longer measurable, probably because the antibodies produced dampen it down. It doesn’t mean the spike protein is gone. We don’t know how long the cells produce the abnormal spike protein.
It would have been wonderful if the spike protein just stayed in the arm. If the deposit, the 1cc injection in the arm, and if the production of the spike protein would have just stayed in the arm and the immune reaction stay in the arm, that would have been, I think, the best possible scenario for these vaccines. Not the case. When the Ogata paper broke, everyone said, ‘Oh boy, now the spike protein is circulating.’ Okay? Then, when the first man who took the vaccine, he took shot one, shot two, when he died in Germany and had an autopsy, the question was: where is the spike protein being produced in the body? And that’s when that autopsy hit and it was in the brain. It was in the heart. It was in all the essential organs. We knew we were in trouble. We knew we were in trouble.
Never once did we have a vaccine or any injection in the human body that got distributed via lipid nanoparticles throughout the body within a matter of weeks and then set up shop to produce a damaging protein. This protein circulates. It damages organs. It damages endothelial cells. Blood cells. It causes blood clotting. There is a wealth of scientific papers on this. There’s nothing about the spike protein that’s good. These little red characters here on the slide are lethal. They’re lethal.
They play a part in the fatal nature of the natural infection. And the Chinese have published a ton of studies on this. Everything we learn about the spike protein is bad. There’s a paper now showing the spike protein interacts strongly with the p53 and the BRCA genes, which are the cancer genes in the human body.
Now, if you’re going to have spike protein for a day or two, a week or two, probably not a big deal, but if you’re going to have a spike protein on shot one and shot two and shot three and shot four, in year one, in year two, in year three, who can imagine what’s going to happen to the human body? How many runs can a human body take with a potentially lethal pathogenic spike protein that was manipulated in a lab in Wuhan, China, and now available for human consumption by injection across the world?
That’s what we know about these vaccines. Everything we know about it, you would agree, is a dangerous mechanism of action. We’re late on this, we’re late, but we got this in press, Bruno and colleagues, 57 authors, 17 countries, where the title of the paper is ‘SARS-CoV-2 Mass Vaccination: Urgent Questions On Safety’. Highlighted parts there: if we don’t have safety boards, data safety monitoring boards, critical event committees, human ethics committees assigned to these programmes, we have no hope of shutting this down or even evaluating for safety.
I’ve chaired over 24 data safety monitoring boards. I chair two for the National Institutes of Health right now. I know what I’m talking about. I know about data. I have over 650 publications in the National Library of Medicine, 45 on Covid. I’ve reviewed more reports and made more inferences on scientific data, I think, than anybody in the world right now and certainly in my field – in heart and kidney disease – in history. I’m not fooling around when I say our governments owed it to us from the beginning to have a data safety monitoring board. Where’s the DSMB? The data safety monitoring board is an independent group of experts without a stake in the outcome. The sponsors of the US programme are the FDA, the CDC and then, behind them, Pfizer, Moderna and J&J. None of those entities are qualified or capable or even ethically charged to evaluate mortality or outcomes. They personally have a stake in the outcome of this. We never let the company decide on causality of a problem. We never let a company tell us if a product is safe. We always have external bodies.
And by the way, when these came through the clinical trials, there were data safety monitoring boards. And over two months, when they select relatively healthy populations, they did look okay after two months. The problem is, once they got broadly used in the population, we realised, holy smokes, we not only don’t have a data safety monitoring board – you know everyone’s asked to sign the consent form, saying they’re in a clinical investigation, it does say that – we actually didn’t have any guard-rails on this to . . . if a problem was there, to be able to tell America and tell the world, ‘Listen, we’ve got a problem. We’ve got to do something about it.’ Okay? We didn’t have the fundamental safety mechanism.
Historians will write about this. Okay? This is kind of like Tuskegee. There was a terrible experiment, there’s been terrible historical things. Not having a data safety monitoring board will go down in history as a colossal mis-step in public health. How in the world can we take the sponsors of the programme – the FDA, the CDC, Pfizer, Moderna – and let them be in charge of safety? And even worse, how can we let them not ever produce a safety report, never do a safety press briefing? Nothing.
The messenger RNA or adenoviral DNA, the production of the spike protein is a dangerous mechanism of action. It injures cells, tissues and organ and endothelial damage, and we have papers to support that all the way. The spike protein circulates at least for two weeks. Body fluid, donated blood, that explains the shedding events that . . . you know so well. No genotoxicity, teratogenicity or oncogenicity studies. They wouldn’t be needed for vaccines from a regulatory perspective, but they would for gene transfer technologies.
There’s a concerning reduced fertility study by Moderna submitted to the European Medical Association. Fertility did go down in animals. It wasn’t a huge drop, but it was real. There was a concerning biodistribution study, Pfizer in Japan, where the lipid nanoparticles hyper-concentrated in the ovaries. As the Chinese had shown us a couple of years earlier with a paper by Ning and colleagues. As I mentioned, there are no safety committees. No restriction of properly excluded patients from the trials.
When the trials were done, they properly excluded the FDA, Pfizer, Moderna and J&J, for a reason. Exclusions must be justified with all the regulatory authorities and the Office for Human Research Protections for a reason. Pregnant women, women of childbearing potential who cannot not guarantee contraception, Covid-recovered, suspected Covid-recovered, those with severe allergies. Why are they excluded? You have to justify it. The two reasons to exclude patients from clinical trials is: no opportunity for benefit and excess opportunity for harm. And these groups were excluded.
When we finish a study and a drug is on the market, we never just let the excluded groups get the drug on a whim. Or, ‘Why don’t we just try it out now?’ There’s never been a drug where we say, ‘You know, we kept pregnant women out of it. It could be dangerous. Let’s just go ahead and give it to them.’ Never. That should be an alarm bell. The behaviour of doctors and the American College of Obstetrics and Gynaecology that says to vaccinate women with no randomised trials safety data ought to be a giant alarm bell going off.
Alarming. That’s a bellwether. Pregnant women and the foetus are the special situation in medicine. We have pregnancy categories for this. We bend over backwards. We only use drugs where we have lots of years of experience. We know they’re safe in pregnant women. We only allow inactivated flu, tetanus and pertussis, all inactivated. That’s it. That’s it. And I published an opinion editorial . . . where I said, ‘Listen, this is pregnancy Category X. Any new seizure drug, any new diabetes drug – no different, no different. This should be alarming.’
I have a lot of interaction with doctors. I don’t have a single doctor who can look me in the eye and support what’s being done to pregnant women. What I see in their eyes is fear, shame, guilt. They know they’re wrong, but they’re confused, and they can’t seem to understand why they’re wrong. Doctors and those with them – and there’s a lot with them – are in a trance right now. They’re in a trance. They’re in a mass psychosis. And it’s worldwide.
***
Part 2: The vaccines are killing people
YESTERDAY we published the first part of an edited transcript of a recent lecture delivered by Dr Peter McCullough in which he highlighted the astonishing absence of safety precautions and safety monitoring in relation to the experimental Covid vaccines. Today he explains there is no system – nothing – to protect the American people from vaccine damage.
What’s going on in the minds of these doctors and health care providers is the same. It’s what I call lockstep. They’re in lockstep. They’re thinking the same way. They’re frightened. They’re confused. They’re kind of scrambled. They can’t really explain or justify what they’re doing. Even awful things like in Scandinavia, like euthanasia for the seniors is going on. They can’t explain it. And they’re fearful.
And I ask them, ‘Do you know who Tony Fauci is? Do you know who Bill G [is] ?’ They don’t even know this. I say, ‘Are you on Twitter?’, ‘No, we’re not on Twitter here.’ So it’s not going through social media, you guys, it’s not going through Twitter, it’s not going through the Gates Foundation, it’s not going through Pfizer . . . something’s in the minds of people and it’s global. And they’re in lockstep. And there’s a tiny fraction of people whose eyes are clear, their ears hear and they understand what’s going on.
The most, most egregious thing is there have been no attempts to present or mitigate risks.
All of you in pharmaceutical companies, as soon as there’s one or two deaths, there’s an immediate investigation. ‘What happened?’ We figure out maybe it interacts with other drugs, maybe there’s some background conditions. Maybe if somebody already had Covid, maybe that’s really the problem and we tried to vaccinate on top of that, which we shouldn’t. [There’s] no attempts to mitigate risks.
If anybody asks your opinion on the vaccines, I suggest you start with this: say, ‘Listen, I’m concerned there’s been no report card. The CDC and FDA hold all the data’ . . . Demand a report card. Until we get transparency of data, this thing is not going to be corrected.
January 22nd, we had a problem, at 27.1million Americans [vaccinated] we hit 182 deaths. This is VAERS system – Vaccine Adverse Events Reporting system – this is the weekly update. These are the permanent VAERS number, remember, a form gets filled out, 80 per cent of the time it’s filled out by a doctor or nurse who thinks the vaccine caused the injury. It gets assigned a temporary VAERS number. The CDC calls, and the CDC verifies that it happened. Okay? These are permanent: 182 deaths.
We normally get 158 deaths a year, every year, in the system. That’s kind of the average, about 158 deaths across 70 vaccines. I just had one two days ago, I had a flu shot. We give 278million vaccines in the United States per year, 70 different vaccines. I’m not anti-vaccine. I’ve taken all the vaccines. I’ve been in India. I’ve taken even more vaccines. I’m telling you, 182 – if I was chairing a data safety monitoring board – and I probably should have, honestly – I would have shut down the programme with my committee. I’d say, ‘Listen, there’s too many deaths, we’ve got a mortality signal.’ Any one of you in pharmaceuticals know this, there’s been many drugs that never made it to market because of unexplained deaths. Okay? It didn’t stop there . . .
And so here we are, as of . . . a week ago: 14,506 deaths – and look at the numbers – over 200,000 hospitalisations, office visits or other urgent visits. You’ve heard of people scornfully talk about the unvaccinated in a hospital. But what about the vaccinated contributing to health care costs? Look at the vaccinated. Unfortunately, sadly, 18,439 permanently disabled people. That cost them. That costs society. That costs all of us.
When the CDC and FDA reviewed myocarditis in June, I was on both of those calls. And I can tell you they were only looking at 200 cases. They now have 5,371 cases. The FDA has official warnings on this. The FDA is trying to tell mothers and fathers, ‘Don’t vaccinate your children. Warning, warning myocarditis can occur.’ 200 cases in June. 5,307 verified cases. I had one in my practice. Young guy going to college, he’s just trying to do the right thing. He wasn’t sure; he took the vaccine. Now he’s got SD segment elevation, sky high troponins, early left ventricular dysfunction, chest pain. He has to go on heart failure medications and colchicine and steroids and has three months of care and more EKGs and more echoes and this and that. And his parents are distraught and the tension is going up and up. The CDC officer called me to verify that that’s real. And I said, ‘Yeah’. We went through it. He goes, ‘Okay.’ So, my patient is part of that 5,371. How many more do we need to convince people?
There is a paper published by Jennifer Hogue that’s an analysis that has concluded that the chances of, with a young person under 30 getting the vaccine, the chances of being hospitalised with myocarditis – which my patient had happen – is greater than that child being hospitalised with Covid-19. You can’t make this thing up. It’s not a proposition that anyone would take, it wouldn’t. The temporal relationship – and this is shot one and shot two aggregated over time – the temporal relationship to getting the shot and death is exquisite . . . is exquisite. We now know from multiple independent analysis, people got frustrated because the CDC and FDA is not giving us the data. People got it and analysed [it]. 50 per cent of the deaths occur within 48 hours. 80 per cent of deaths occur within a week. They are tightly temporally related. McLachlan, from Queen Mary University in London, has concluded, by having independent reviewers review a representative sample of the deaths, 86 per cent of the deaths have no other explanation. Now on two occasions, in March and in June, the CDC, with no fanfare, put out on their website that CDC and FDA doctors, quote, ‘reviewed all the deaths and none were related to the vaccine’ unquote.
I can tell you, I do this [type of] work for Big Pharma, for biotech and the NIH. Reviewing deaths takes a lot of time. All the hospital charts, all the labs, all the EKGs, the paramedics [unclear], what have you. It takes for ever. Two separate reviewers, then you have to have an adjudication process. For them to whip this up, with thousands and thousands of deaths, is not believable. And in March was the first time where I developed a conclusion of what’s going on is malfeasance, wrongdoing by those in positions of authority. And I think historians, historians will go back and look at this. This includes the deaths that occur in the vaccine centre. You know, people are on their phones and they’re doing CPR in the vaccine centre. Even those weren’t related to the vaccine?
Now there have been some nursing home studies, one by [?] I believe in Denmark, and another one done, a similar type of analysis where in a nursing home setting, the conclusion was by independent reviewers where they actually had the charts, maybe 40 per cent of the deaths were really directly attributable to the vaccine and that there were other processes that played a role. Whether it’s 4 per cent, 40 per cent or 86 per cent, it’s way too high. And unfortunately, our seniors are bearing the brunt of this. The seniors are the ones we are trying to protect. They’re the ones who are dying after the vaccine. It’s pretty clear. It’s a steep, age-related phenomenon. Now, this paper, recently out by [?] and colleagues, have pitted the Covid-19 respiratory deaths and the seven-day Covid-19 vaccine deaths on these two figures. And even though the y axis is much different, the age relationship is the same, meaning the spike protein is probably the lethal nature of it. And it’s a matter of dose and duration and all the complications.
The is: why are we vaccinating children? And in this analysis, it’s interesting, the paper actually goes through the entire age ranges. The conclusion of the paper you could draw is, if someone actually takes the Covid-19 vaccine for death as an outcome, one is actually more likely to die of the vaccine death than actually taking their chances of acquiring Covid-19 and dying of Covid-19. It is astonishing, because when you take the vaccine, it’s completely deterministic, right? It’s a 100 per cent chance it’s in your body. But people at this point in time, people who are contemplating taking the vaccine, they’ve lived a year and a half without getting Covid-19. Do you know what that means? That means that they’ve been dodging it pretty good . . .
But the point is, 15 per cent they actually can’t get Covid. They can’t get Covid. And a leading theory is maybe they have cross-immunity from other coronaviruses. But leading work by Dr Sabine Hazan in Ventura Hills, California, has shown that people who don’t get Covid, even they get exposed – and all of you clinically know this – if you have a household of six people in a house, it’s not six for six with Covid, never. It’s always one or two people don’t get it. And the reason is probably the microbiome. Believe it or not, those of you with a healthy microbiome, it can be scored according to grades of microbiome, and one of the leading good-guy bacteria is called Bifidobacterium, it is amazing that those with high Bifidobacterium, high microbiome scores can’t get Covid-19. And even the CDC agrees – 15 per cent of people, they estimate, cannot get Covid-19. Because when you take it in the nose and mouth, you’re always constantly swallowing, it gets in the GI tract right away.
I personally had Covid in October of 2020, and I was in a research study that was actually doing sequencing, and I was in an FDA-approved protocol. So I know I had the British variant, the Alpha variant, and I know they sequenced it from what came out. So it’s interesting.
So what’s happened over time is this vaccine has become weaponised, just like the kids can get myocarditis. It’s not right and it’s not rare. The other thing I think is malfeasance is to call anything ‘rare’. We never do that in clinical research. Never. The correct term in safety, pharmacovigilance, is ‘tip of the iceberg’. Whatever we’re seeing now in sporadic reporting is ‘tip of the iceberg’. VAERS could be an under-representation by a hundred-fold or even more. We think – we’ve done some analysis on this using CMS – we think on mortality, maybe it’s a multiplier of five. But the point is we never would say ‘rare’. And what the CDC has done, I think very, very disingenuously, is when they had 200 cases in June, they divided it by everybody who took the vaccine and said, ‘It’s rare.’ Well, you can’t do that unless you check everybody for myocarditis, unless you do an EKG and troponin.
You can’t declare that they don’t have myocarditis unless you check for it. But Jessica Rose, in her first paper, showed that it’s cardiovascular, neurological and immunological [that] are the main non-fatal syndromes, and as shown here, they skew towards younger people, probably because the genetic material is more avidly taken up in younger cells. And so those cells, it depends on where the mosaic is, where they can express the spike protein in damage. And it’s very possible that those who have a greater uptake in the brain are going to express the neurologic complications, those that have uptake in the heart express cardiovascular, et cetera.
So without pharmaceutical protection from the pharmaceutical laws, about deaths and about data safety monitoring boards and about pharmacovigilance, the vaccines will do more harm, right? So we don’t have anything to protect the American people. That’s the reason why everybody’s so on edge. Where’s the protection of our people? That’s what our agencies are supposed to do. And right now, that is being completely abrogated.
So the vaccines have been considered not safe on either side of the Atlantic. This is not just an American problem. So the evidence-based consulting group in the UK – and Tess Lawrie is one of the leaders – but they are the principal consulting group to the World Health Organisation. I’m telling you they’re legit. They are very legit. They have analysed the [UK] Yellow Card system. And the Yellow Card system is just like our VAERS system. So it’s a good external validation of, is what (I am) saying, you know, tractable. Her conclusion: an immediate halt to the vaccination programme is required, whilst a full and independent safety analysis is undertaken to investigate the full extent of harms – Dr Tess Lawrie in May of 2021.
So in medicine, we have what’s called Hill Bradford tenets of causality. When we see something bad going on and we’re using a drug or biologic product, we have to ask the question: is it actually causing the problem? And so the tenets of causality say, is there a temporal relationship? I showed you that: it’s really strongly related in time. This doesn’t happen any old time, it happens pretty much right when you get the shots. Is it internally consistent? Yeah. Death, all the other nonfatal events. Is it externally consistent? Sure: US, UK, EU. Okay. Is there a tractable, biologically plausible mechanism of action of how the vaccines could actually kill a human being? You betcha. If we get a vigorous uptake of the material and a vigorous run with the spike protein in a susceptible body, can it be lethal? Of course it can. Just like the virus can be lethal, and just like the same people who are dying with the virus are dying with the vaccine, it makes sense. It satisfies Bradford Hill tenets of causality. There’s no question about it. The vaccines are causally related to some, if not the majority, of everything you’re seeing here. I can tell you as a scientist, as a doctor, as an epidemiologist trained at University of Michigan School of Public Health, I can tell you with every fibre of my body, these vaccines are doing this. They are doing this. And anybody who tries to brush this off, ‘Oh, they’re not related’, what have you, I’m telling you, you have layer after layer of tractability in your analysis.
***
Part 3: How they cooked the books
This the third part of an edited transcript of a recent lecture delivered by Dr Peter McCullough. You can read Part 1 here and Part 2 here. Today’s section starts with his explanation of the sleight of hand by which the Pfizer vaccine won FDA approval before going on to discuss the implications of vaccine’s limited efficacy.
PFIZER was not approved. And this meeting that happened on August 23rd, it was Pfizer, it was the FDA [but] there was no academic advisory board and no independent presenters – [it was] a closed meeting. And they looked at the data. And what happened . . . probably will go down as one of the greatest regulatory sleights of hand, regulatory malfeasance of all time. Pfizer got a continuation of the Emergency Use Authorisation, not approval. BioNTech – it was a shared intellectual property product – BioNTech got split off and said, ‘Oh, they have a separate product that’s a legally distinct product. It may be medicinally distinct.’ BioNTech gets conditional approval, but it doesn’t exist yet in the United States, it gets a draft package insert, which is very scant, with a lot of post-marketing obligations for myocarditis information that basically says, ‘We don’t know if this is safe in pregnancy at all.’ And what came out of that meeting was a talking point that Pfizer was approved. That went all the way up to the President of the United States. Pfizer was approved.
That triggered an entire wave of vaccine mandates for a product that was thought to be approved when it really wasn’t. And the person who signed the letter to BioNTech Comirnaty – the product that doesn’t exist yet, that got conditional approval – Dr Gruber, within a week resigns from the FDA.
I’m telling you, anybody can tell that something is deeply wrong in the regulatory environment in the United States . . . These sequences of events will go down in history as American lives were lost. There’s been a failure of these vaccines to do what they’re supposed to do. When they came out of clinical trials, I was testifying in the US Senate on November 19th and I’ll never forget, I was a lead witness, and our final question was, ‘Doctors, do you have any question regarding the Covid-19 vaccines?’ All I knew on November 19th of 2020 was that the vaccines [was] by press release – and I think it was Pfizer first – that they had 90 per cent vaccine efficacy. But the rates of Covid-19 in both placebo and vaccine groups were less than 1 per cent.
How could that be? I mean, November, we were stoking, we had, you know, I think our laboratory rates went 5 per cent, 10 per cent, 15 per cent, you know, there was a lot of Covid in November and there was a ton in December. How could they have done trials where people’s rates of Covid-19 were less than 1 per cent? That’s what we knew from the press release. So I will never forget, I was recovering from Covid myself. I had this smothering N95 mask, I was on the Senate floor and I literally just sat there and I said nothing. And Harvey Risch next to me and George Fareed next to me – nothing, not a statement. I’m so glad I didn’t say anything because things, as they played out, what we saw in the clinical trials was the following: that there [were] very few hospitalisations and deaths, but there was no benefit at all. There were a few cases of Bell’s palsy, but there weren’t any of these horrific vaccine deaths or these horrific strokes or myocarditis, what have you. They looked pretty clean out of clinical trials.
So people would ask me, ‘What do you think about the vaccines?’ I’d say, ‘Well, I don’t have a choice. The patients can take them if they want to.’ So I didn’t recommend them or not recommend them. And 70 per cent of my practice – I practise non-invasive cardiology and internal medicine, I maintain my boards in both, as long as I can maintain my board in both – took the vaccine. 70 per cent took the vaccine. People in my family took the vaccine. They did it patriotically. Some of them – remember, there were no mandates back then. No mandates. And people were actually waiting for the vaccine. What’s happened? Well, it turns out that with the legacy data in this recent paper by MMWR, that the vaccine efficacy held up. Moderna turns out to be at 120 days post vaccine, 92 per cent vaccine efficacy. Pfizer 77 per cent. And Janssen 68 per cent – that’s Johnson & Johnson. Now these aren’t randomised data, but they try to calculate using fair statistics in a population. This is the first data, by the way, that the CDC has released with respect to differential vaccine efficacy. Right? So is one better?
Remember, they keep telling you, ‘Just take a shot.’ You say, ‘Well, which one should I take?’ ‘Well, just take any one.’ Oh, come on, we’re Americans. We like to make choices, right? So this is your first official . . . so you see, you’d think they’d come out on the news at least and tell you this, right? But this . . . so it looks pretty good. But there’s no safety data in this manuscript, and I can tell you, look at the numbers 15, 17, 14. Look at the denominators. Wait a minute. You’ve had 168million people take the vaccines. You know, these are pretty scant data. And in the text of it, there are six major limitations.
Number four, take a look at it. ‘The vaccine efficacy estimates were adjusted for relative potential confounders.’ And by the way, the outcome on the previous side was hospitalisations, but ‘residual confounding is possible’. Let me tell you a residual confounder. You know what determines who gets hospitalised or who doesn’t get hospitalised in United States? If they got early treatment. That’s what makes a difference. Not, not a vaccine. [applause] So take a look at these papers. Every single paper that makes a claim on a vaccine prevents hospitalisation and death. Your next question is, ‘Who received early treatment and who didn’t?’ ‘Oh, we didn’t think of that. Sorry.’ Give me the next paper, because it’s not legit. And look at fifth, ‘Product specific vaccine efficacy by variant, including the Delta variant, was not evaluated.’
Well, let me tell you what, the Delta is brand new. We have what’s called legacy data, and then we have Delta. And right now we’re 99 per cent Delta and everything, everything you saw in that slide is obsolete. And the failure of the vaccines, and truth revealed, happened a few months ago in July. This was a British naval vessel. 3,700 fully vaccinated sailors go out, they go in the Mediterranean, they stop at, I think the island of Crete, sailors had a little fun, before you know it, there’s a breakout on the boat – note sailors, no girls – on the boat, breakout, Delta, and they’re passing it to each other. Right in line with this, there was a Houston wedding, a fully vaccinated wedding – you guys have been involved in these family things, right, where you can’t go to a wedding unless you’re vaccinated? – well terrific, they all went to the wedding vaccinated and sure enough, there was an outbreak of Delta. There was a private flight, Democratic lawmakers fly from Texas to Washington. They get Delta, and Kamala Harris has to scramble to the Walter Reed to get tested and what have you.
In fact, Farinholt at Baylor College of Medicine, Houston, studied the Houston wedding, and he proved that the fully vaccinated can actually acquire and carry and pass to other people Delta. Farinholt proved that. Our CDC director came on TV and told Americans that towards the end of July, saying, ‘Listen, the vaccines can’t stop Delta,’ she said it herself. And in fact, the CDC has told us this. Barnstable County in Massachusetts, here’s an outbreak, people in congregate settings. The light blue is the fully vaccinated? What’s the problem here? The fully vaccinated are more of the Covid contagion than the unvaccinated? This is the CDC telling us this. This isn’t me. This isn’t my opinion. This is the CDC telling us this. Mayo Clinic in Boston, a company [unclear], they have over a million sequenced samples. They had great data from Rochester County, Minnesota, 25,000 individuals. They calculate vaccine efficacy. But look at July as Delta shades in, Moderna is holding up at 76 per cent vaccine efficacy, Pfizer’s at 42 per cent vaccine efficacy. OK?
Pfizer is 30 micrograms of messenger RNA, Moderna is 100 micrograms of messenger RNA. They’re very different products. Our CDC and FDA has not presented that to America, that they’re very different products. We don’t know about Johnson & Johnson, but the differential choice of the products has also been something that has been whitewashed by our agency. ‘Just take a vaccine, take any vaccine. Just get vaxed.’ ‘Well, no. Wait a minute. They are different products.’ Israel, which is probably giving us the best forecast of what we’re going to be like, is telling the story. And you don’t have to be a University of Michigan epidemiologist to figure this out, you guys. Fully vaccinated patients with Covid-19: 86 per cent. Population fully vaccinated, 84.4 per cent. It’s superimposable. The vaccine, Pfizer, 30 micrograms, has completely and totally failed. [applause] We’ve just got to call it. Just call it. You can’t sugar-coat it. You can’t sugar-coat this. This is complete and total failure. Israel’s post-vaccination curve in their country is bigger than their pre-vaccination curve. If you had asked the question, would Israel have been better off not to vaccinate a single person? Answer: yes, from an epidemiology perspective, yes. It is a complete and total failure. What are they doing in Israel? Doubling down. Boosters. They’ve got 11million people in the country. They’ve already boosterised two million people. Guess what? They already have papers published – there’s one from Haifa, Israel – published, already showing booster failures.
I’ve already had one in my clinic. I didn’t realise this until two weekends ago. Two of my Webexing, smart engineer-type people who work on the computer at home have avoided Covid-19, faithfully got Pfizer number one, faithfully Pfizer number two – do you know that earlier this year you could just show up at CVS and Walgreens and get another one and they’d give it to you? What, wait a minute. This is strict regulatory approval. This is Emergency Use Authorisation. You just don’t get a booster for the hell of it. Yeah, you do. Believe it or not, you didn’t need to wait for approvals of boosters on September 17th. People can just do it on their own and CVS and Walgreens and these vaccine centres don’t care. It’s like, the more the merrier. I’ve never seen anything like this in my life. These are supposed to be regulated products. How in the world . . . they’re supposed to be keeping track of lot numbers and there’s vaccine cards that are going to dictate the rest of your life and they’re just, for the hell of it, they’re going to give you another shot if you want it? This is unbelievable.
So, they announced to me when I saw them in the office, they go, ‘We already got our boosters.’ I said, ‘Boy, that’s pretty prompt.’ I didn’t say anything, you know, people have their own choice. And sure enough about two weeks later, ‘Oh, I’ve got Covid and my husband’s got Covid.’ And she got Covid, and she’s fully boosterised, so she would have fit that the boosters are not holding because it’s Delta and the vaccines have not been adjusted to cover Delta, which is the most mutated form of the variant.
But the CDC knew about vaccine failures even back on May 25th, where at that time, through community departments of public health, they didn’t have all the cases, but they reported 10,262 cases to the CDC as fully vaccinated Americans who had broken through. 10 per cent were known to be hospitalised and 2 per cent died. I’ll tell you, that’s not good. That’s May 25th. What did the CDC do in response to that? The CDC said, ‘We’re not tracking these failures any more.’ They went on to say, in their website, ‘If you’ve been vaccinated, don’t get any more testing.’ Hospitals followed and said, ‘You know what, if you’ve been vaccinated, we’re not going to test you before your heart cath or your . . . but if you’re unvaccinated, we’re going to test you.’ Some of you are shaking your heads, right?
Then the CDC went even further and said, ‘You know what, the cycle thresholds on the PCR test, if you’ve been vaccinated, we’re only going to count ones where cycle thresholds are low, less than 25, because, you know, we don’t want to get false positive from the vaccine. However, if you’ve been unvaccinated, we’ll take it, anything you want to give us.’ Yeah. So the CDC made some decisions on May 25th of what’s called biased asymmetric reporting. This fabricated the books. It cooked the books to make the vaccine failures look small and make the problem starting May 25th forward look like it was going to be a crisis of the unvaccinated. And we started to hear talking points like, ‘Oh my gosh, the hospitals are filling up and they’re all unvaccinated,’ and people would kind of say ‘unvaccinated’ with kind of a snarl. I’d see that, you know, and if people would hear the reports.
I took a drive from Dallas down to Austin, and I was actually on Alex Jones, anybody watch Alex Jones? [applause] I am not a hardcore right wing guy. My wife says, ‘Don’t go on with him. Don’t go on’, because, you know, Alex Jones, he’s like, ‘Get your guns, get your ammo. They’re coming for us.’ And so I went down there with fear and trepidation. I said, ‘Alex, you know, I’m just a doctor. I just, you know, I’m happy to go on.’ I said, ‘but I don’t have any guns or ammo and . . . and I’m just, you know, I don’t have a red cap or anything.’ And his producers say, ‘Alex, Alex, no stunts, no stunts for Dr McCullough, just . . .’ And so Alex was really good. If you’ve ever seen the video, he was just . . . and it turns out he’s a really smart guy. He had . . . he has, like, 20 stacks of paper in front of him. He keeps that studio at like 58 degrees, I said, ‘You’ve got to be kidding me?’ But apparently, he burns off all this energy as he gets wired up. And I said, ‘Alex, do you read all this stuff?’ He goes, ‘Yeah, I read all of it.’ I said, ‘You got to be kidding me.’ He’s a smart guy. And he, basically, he does what he calls stunts. I don’t know if you saw him when he ate a whole packet of ivermectin, you know, he does stunts. [laughter from audience] Alex does stunts to kind of, I guess that’s what they do in media. But for me, it was no stunts. We went over the data and I told him, I said, ‘Listen, this is all set up to be a crisis of the unvaccinated by intentional asymmetric reporting.’ https://freeworldnews.tv/watch?id=6136a2193b76170da9351b95
And everybody bought off on this. But the CDC continues to tell us it’s not. The CDC on July 26 had again, you know, sporadically reported – this isn’t the universe of cases – they had 6,587 fatal or hospitalised cases. And look at this, 19 per cent of them died. These basically came in through hospitals who voluntarily reported to the CDC. A 19 per cent mortality rate in those hospitalised fully-vaccinated is a problem. And anybody who tries to tell you, ‘Oh if you get . . . at least a consolation prize of being vaccinated, is that you have a little easier ride with Covid’, so, wait a minute, this doesn’t look like it’s an easier ride, okay? The CDC, as of August 23rd, told us who’s dying and who’s dying and who’s being hospitalised is people over 65. So we’re back to the seniors. Covid-19 has always been about the seniors, so why in the world has the dialogue for the last nine months been on the children? This is a crisis of the seniors and our seniors have paid the price. Some of them, the ultimate price . . .
***
Part 4: Malfeasance and abusing Mother Nature
This the fourth part of an edited transcript of a recent lecture delivered by Dr Peter McCullough. You can read Part 1 here, Part 2 here and Part 3 here. This latest section of Dr McCullough’s tour de force moves on to vaccine damage, deaths and the tragic denial by governments of early treatment.
I NEVER thought I’d say the words malfeasance and propaganda as a US citizen talking about our public servants.
These people serve us, including the President. Okay? They serve us. And the CDC (Centres for Disease Control and Prevention) and the FDA (Food and Drug Administration) and the NIH (National Institutes of Health) serve us.
They’re supposed to make sure our drugs are safe, they’re supposed to analyse the data and help us. The doctor and the patient sit above the CDC, NIH and FDA, and they sit in this circle of what’s called a fiduciary relationship, what we call shared medical decision-making.
And in no way, shape or form should that medical circle ever be broken. And malfeasance and propaganda are the tools to break that circle that should not be broken.
These two studies show 23 per cent of Americans hospitalised with Covid-19 have been vaccinated. Full stop. This is June. We’re not even fully into Delta, Okay? All these hospitals, all these vitriolic intensive care unit staff and other people telling you that it’s all unvaccinated.
There’s a billboard on the way up from Dallas down to Austin saying over 90 per cent of people are unvaccinated. It’s not supported by the peer-reviewed published data.
So, by pushing mass vaccination, governments have created evolutionary pressures on the virus. The vaccine is not sufficiently safe in everyone and it doesn’t work well enough in everyone. And to make matters worse, it’s making it worse for everybody, because we’re fooling with Mother Nature.
Once we got to October of 2020, the diversity of the viral lineages started to go down in every country once we started vaccination. We always had half a dozen to a dozen different strains. We always had alpha, beta, gamma Delta. They had different names back then, but we always had them. Okay?
So it’s not like the vaccines cause mutation, but the vaccines produce what’s called a nonlethal evolutionary pressure. And that nonlethal evolutionary pressure is shown by this paper of Venkatakrishnan, showing that, here’s the spike protein and the target is what’s in green, light green there.
The antibody is the big dark blob. The antibody is way bigger than the spike protein. The spike protein is only 1,200 amino acids, the antibodies are huge. And you can see there you got to have that target to hit.
As there is antigenic change – and with Delta originally, it was seven mutations, then it was Delta Plus, now the British think there’s about 20 more different mutations – and Delta, it’s funny because the mutations are peppering around the gain of function research that was done into furin cleavage joint.
So it’s almost like Mother Nature knows it’s wrong and says, ‘Listen, I’m going to take the starch out of this thing by mutating.’ It’s really interesting, but you can see now the antibodies no longer hit Delta. That’s the reason why. The vaccines actually probably did work with Alpha and Beta, but they no longer work with Delta.
The Israeli ministry thinks the vaccine effectiveness of Pfizer is about 39 per cent. If a vaccine cannot last a year and have at least 50 per cent protection, it’s not viable as a vaccine. So Delta is making waves.
Look at these diversity curves. We went from the British variant, that’s what I had back in October, we have actually started to have the pressure and look how Delta has gone from a few per cent back in May. Delta now is 99 per cent of what we’ve had.
We’ve never had a super-dominant, hyper-dominant strain, period. This is a product of vaccination. More than 25 per cent of people vaccinated, you start messing around with Mother Nature. This is really a problem.
So, in the messaging before I was completely banned from Twitter, which is actually a sign of high-quality scientific citation. (laughter and applause from audience) In fact, I was never on social media until my daughter convinced me to go on it. And that was like about a year ago, and it was probably the worst mistake I ever made.
But I can tell you there’s no podcaster I can’t bring down off YouTube. I told of most of them, ‘You’re going to go on with me, be prepared to win every censorship award you can win. Because all we’re going to do is cite the data and you’re gone. We just pinpoint and they just go down.’
I just brought down Tommy Kerrigan, a great young podcaster, he’s gone. And I told him, ‘That’s really a badge of courage.’
But you don’t fool with Mother Nature. When I had been tweeting before I was off, I said, ‘Listen, I’m not against the vaccines, but let’s limit it maybe to nursing home workers, where there were outbreaks.’
There were never any school outbreaks, never, Okay? There was never any credible student-to-teacher transmission – didn’t happen. The Chinese and a paper from New York showed 85 per cent of the transmission occurs in the home, Okay?
So this idea that people were out here, that we were all transmitting it to each other just wasn’t tractable. It happened in the home.
And so what we needed from the very beginning was early treatment for Covid-19, and I testified in the US Senate. I told America, ‘Stopping the spread of the virus is great to the best we can, but we can’t just focus on this. The masks are not treatment, Okay? We need to have an early home treatment programme. We can do it by telemedicine, reduce hospitalisations and deaths.’
There’s only two bad outcomes with this illness: Hospitalisation and death. I think if everybody knew they were going to get a cold and they could ride it out at home, but you weren’t going to be destroyed by this in the hospital, I think you’d say, ‘Okay, I’ll get through it.’ Okay?
Early in March of 2020, I said there are two bad outcomes for this – hospitalisation and death, and I was on these task force calls and I waited.
And I think it was about April I asked some people, ‘Are we going to do start doing something? Are we going to open up a Covid clinic and start treating this problem?’ And the doctors were terrified.
One doctor said, ‘You’re kidding. We’re closing down our clinics. We just got an executive order to do telemedicine. We’re not going to contaminate our clinics. We’re not going to contaminate yours.’
And then, after another couple of weeks, I said, ‘If we don’t start treating this, our hospitals are going to fill up.’ And when I watched the fear, the sheer, unadulterated, unbridled, terrifying fear in the eyes and the voices of doctors and health care providers and administrators, I knew what was going to go on.
I said, ‘They’re not going to treat a single person. They are terrified for the first time, of getting it themselves.’
And you know what terrified us was the Italians. The Italians ran out of masks and ran out of Personal Protective Equipment in a few places, and they posted a list of dead Italian doctors and they hit a thousand. They put it on the internet.
There was a young male nurse in New York who had asthma, you probably remember him. He died. They had him on CNN. And I think that scared the bejesus out of people. And then I realised: Listen, nobody’s going to treat this illness.
And we had the President, White House Task Force, Senate, House, NIH, FDA and CDC. Not a single leader at any time said, ‘Death and hospitalisation are the two bad outcomes. Let’s get a team of doctors in here who know how to treat this. And let’s stop this from happening.’ No one framed the problem. And if you don’t frame a problem, you can never solve it. Never solve it. (applause)
And I became incredibly agitated, and I was really, really hard on Trump. I know some of you guys are Trump supporters. He’s the only one that had enough power and authority to make that statement and make it happen. And if he didn’t do it, no one was going to do it and he let us down.
And to make matters worse, he got Covid himself. And he actually got first-class treatment. The one doctor I liked was that kind of cocky doctor that Trump had. Remember that guy? He was a DO, got out there, handsome guy. He goes, ‘We’re going to give him some monoclonal antibodies. We’re going to sequence the other drugs, and we’re just going to get through it just fine.’
I said, ‘That’s the type of doctor America needs.’ That’s the type of doctor that every single senior citizen needed – a confident doctor who’s going to get the drugs rolling fast and get our seniors through the illness.
So President Trump got first-class treatment that was available and should be available and should have been delivered to every single American. And what happened? He didn’t say a word. He goes, ‘Listen, it saved my skin,’ and then everybody else got … went on to get slaughtered by the virus. It was awful. Early home treatment is our only chance to reduce these outcomes.
A hospitalisation is a safety net for survival, but contemporary mortality in the Covid network – and I’m part of that network out of the Brigham Hospital – was still 38 per cent of people getting in the ICU.
Vaccination or herd immunity is terrific, but you know natural immunity is I think ultimately what we’re after. I testified in the Texas Senate in March of 2021 and I told Texans, ‘Listen, we’re at herd immunity.’ I used the CDC equation. I said, ‘That doesn’t mean it’s over with. Herd immunity means it’s just not going to spread very far in a congregate setting, because there are enough people to be a buffer.’
And one of the public health officials in Texas backed me up a few weeks later, and they opened up the baseball season, Rangers baseball game and the Department of Health were, like, ‘I’m going to fry McCullough on this.’
And you know what? There weren’t any outbreaks. They looked for them. There weren’t because we had herd immunity.
We actually do have herd immunity, but it doesn’t mean you’re not going to have some more cases. But it’s not going to be devastating. So, vaccinated or not, the acute Covid-19 high-risk patients demand early treatment.
I told you the vaccines don’t work and I refuse to discriminate against a vaccinated or unvaccinated person. It’s wrong, it’s wrong. (applause) And we cannot do that. We cannot do that. As horrible as it is to be discriminated against, whether you’ve chosen or not chosen the vaccine, don’t turn around and do it to somebody else.
Don’t do it. Because that’s the slippery slope, that’s the slippery slope of division and derision. In meanness and unkindness, an injury that’s going to happen.
And you can see it right now. You can see it right now, right? Who’s marked? Who isn’t marked? Who did this? Who did that? You can see the snarl.
I heard some awful narrative the other day that there was a person in the hospital, a senior, and she was struggling with Covid-19 and they, of course, asked her, ‘Did you take the vaccine?’ And she goes, ‘I didn’t take the vaccine.’
And the family member says, Well, how can I get, you know, some of these things that I want my loved one to have?’ And the nurse said, ‘Well, it’d be a lot easier if she was vaccinated. You’d probably get what you want.’ Yeah, so there’s these stories are already rolling. And, you know what, there’s perverse discrimination going on.
So I’ll give you an example, a patient of mine got really sick with Covid-19. This Delta has been tough to treat. Anybody who’s tried to treat it, believe me, I underestimated it – it’s tough to treat, he got really sick, we got to the point where he needed a monoclonal antibody infusion.
I sent him to the place in Dallas, which I know has it, and I know we can get it. He shows up there. And then the first thing the doctor leans over him and says, ‘Have you been vaccinated or not?’
And I coached the patient. He goes, ‘I decline to answer.’ And the ER doctor said, ‘What do you mean?’ He goes, ‘I decline to answer.’ And then he said, ‘Okay, so what do you want?’ He said, ‘I came here for an antibody infusion.’
The ER doctor said fine. He got the antibody infusion. So, on the way out the door he goes, ‘Hey, doc, what if I would have answered that question one way or the other? What would you have said?’
He goes, ‘Oh, if you would have told me you are vaccinated, I would have given you remdesivir.’ Yeah! Yeah – so the discrimination goes both ways in this idiotic treatment protocol that we have for Covid-19. You can’t make this stuff up.
So I’ve always said that early therapy has got the greatest chance of reducing hospitalisation and death. And then when you do these other things, it makes sense that low-risk things like lockdowns and wearing masks, if you have two people wearing masks and neither one has the virus, the mask can’t obviously … can’t possibly do anything right.
So what I’ve said from the very beginning, I’ve been on the Laura Ingram TV show a bunch of times and of course, they always want to talk about masking. And I think it’s just distracting from the really important stuff that we’re talking about tonight.
***
Part 5: We’ll beat this via natural immunity
This the fifth and final part of an edited transcript of a recent lecture delivered by Dr Peter McCullough. You can read Part 1 here, Part 2 here, Part 3 here and Part 4 here. In this section, Dr McCullough focuses on natural immunity, and why we have to fight for our medical freedom.
WHO here has had Covid-19? That is awesome. That is awesome. (cheers and applause) Let me just say one thing: natural immunity is the way out of this.
Listen, if we don’t recognise natural immunity, when is this going to end? This is really important. My natural immunity card, you know, your Senate Majority Leader, Mike Shirkey, met up with me in Berrien Springs and he gave me a little yellow band, where it says ‘naturally immunised’.
Guys, order them. Let’s have a million yellow bands and let’s wear them. He’s a good guy, let’s do it, because the bottom line is we have to demonstrate natural immunity. That’s our only way out of this. It’s the only way out of it.
You know, there are legal letter to the CDC (Centres for Disease Control and Prevention) demanding natural immunity to be recognised. Demand it. Okay, we have to demand it. And be relentless on this.
Listen, natural immunity, you can’t give it, you can’t receive it. There’s no credible evidence that you can get Covid-19 over and over again.
Blaylock reviews this, and lots of cohorts have natural immunity strongly protective to date that we honestly shouldn’t have to worry about this.
The bottom line is that when we vaccinate people, we actually cause harm. Now another large paper in the British Medical Journal shows that if we vaccinate people who are naturally immune who don’t need it, all we do is cause harm. Harm – three to four times as many safety events, including hospitalisation.
Probably the people who are really being damaged on those red boxes I showed you are people who don’t need the vaccine. Okay? So that’s the reason why, as a Covid-recovered person, that’s the reason why I worry most about the vaccine. I worry about the fact that I’ve already had my run in with the spike protein.
A recent paper presented by Bruce Patterson in the Rome summit showed how in people who had natural Covid 19, he found 15 months later spike protein in the monocytes.
There must be a spike protein party in the body, and you must spend months scavenging the stuff out of here. The last thing I want in me is another run of the spike protein. I don’t need it. It’s going to cause harm.
While we’re here, because freedom is at risk; we’re at the beginning of, I think, a dark time, it’s very dark for me personally right now, it’s just things are really going bad in the last 18 months and I can’t tell you, my wife every day asked me, ‘What’s going to be the next shoe to drop?’ You know, we are really at the end of this needle.
Now’s the time to talk about it and to get activated in talking to as many people, and you have to try to clear their eyes – have to. Conversation by conversation.
Medical freedom is related to social freedom, is related to economic freedom. I’ll give credit to this to Eric Clapton, he’s my new friend. He came over to my house because my wife’s a great cook.
My wife’s from the Middle East. He came over and she made some great Arabic food and he said he was injured by the vax. He goes, ‘I’m 76. I was kind of worried. I wanted to tour.’
He hadn’t toured in two years. That’s how he makes his money. And he said, ‘Listen, there’s a circle of medical freedom, and if this is broken, then it’s going to break social freedom and then economic freedom.’
So right now, we’ve got to shore up that medical circle, no matter what. I mean medical freedom to get the treatment that people need; medical freedom to demand good care in the hospital and get it and medical freedom to decide what goes in your body. Okay? (applause)
It’s very, very important. No one, no one under any circumstances at all – approved, unapproved, I don’t care – no one can receive any pressure, coercion or threat of reprisal for something injected into your body that you can’t take out, period. That is the line.
And I got so many people in the military reaching out to me right now, and they’re just absolutely in agony, I said, ‘Hold the line.’ I said, ‘If our military can’t hold the line, who can?’
People are going nuts. If you think it’s bad now, there are rallies in England begging for ivermectin and for hydroxychloroquine.
This just came up yesterday. Woman sues Aventis Health to force ivermectin treatment of husband. Since when do we actually have to sue hospitals to use simple, affordable, generic medicines that may help patients, of which we have some randomised trials to support?
Do you know there have been court orders and there have been hospitals that are denying court orders. Since when? Historians will record.
You know, the last patient I had with a big heart attack in the ICU and the family was there, we were negotiating drugs all day long. ‘Maybe we’ll use a little fentanyl, maybe we’ll use this? We’re going to use this drug or that drug.’
I mean, we negotiate all the time. Suddenly in Covid, there’s no negotiation. None. ‘No, sorry. We’re not going to do it.’ Therapeutic nihilism. It’s in the minds of doctors, hospital administrators, nurses and others to actually cause harm.
And this is, that thought pattern, is something you need to smell out, recognise, call and we got to extinguish. Should we take a genetic vaccine? And people ask me all the time, ‘Doctor, which ones are best? Can I just, can I just get it? Can I just get through?’
I said, ‘How much is this going to buy you? Three months of work? Six? It doesn’t end, it’s not like one shot. If they’re going to guarantee you ten years of employment, maybe you’d take the risk, but there’s no guarantees here. You’re not guaranteed anything for taking the vaccine, right?
Public outrage over these ineffective, unsafe forced vaccinations, we’re at a point, the vaccines don’t work well enough in everyone and they’re not safe in everyone.
I’ve always said, ‘Listen, 168 million took the vaccines, for the vast majority of people, including my family members, nothing happened – terrific. We hope there’s some benefit.
It is my clinical observation – just my observation, I can’t prove it – but those who took the vaccine, I think they are a little easier to treat. But that’s a consolation prize. That’s not a reason to get a vaccine.
So there’s been censorship in scientific discourse. What we’re having right now is a public discourse of a topic of public importance. We are, by law, allowed to do this. There’s nothing unlawful about what we’re doing. And Senator Johnson, who’s one of our heroes, has been pounding mainstream media. It is lawful.
Someone can take a manuscript demonstrating vaccine failure and post it on Twitter. It’s lawful to do that. It is unlawful, in my view, and wrong in my view, to have that censored as a point of information for people to consider.
We’re crushing the lifeblood of medical science and it’s all in the open. December 10, Trusted News Initiative – BBC, CNN, MSNBC, Twitter, all social media said, ‘We are going to do everything to promote the vaccine, and we’re going to do everything to crush any vaccine hesitancy, including crushing early treatment and crushing anything on vaccine safety.’
That’s the reason why we haven’t heard anything of vaccine safety. It’s in the open. Everything is wide open. There’s no trickery here.
Rick Bright, the guy who blocked hydroxychloroquine inside the White House and starved America of hydroxychloroquine, he has joined the Rockefeller Foundation. Okay?
Stephen Hahn, the FDA (Food and Drug Administration) commissioner who put all these negative blankets on hydroxychloroquine and the other drugs, he has joined the venture capital firm, who basically is the funder of Moderna.
The National Institutes of Health, which Francis Collins, former University of Michigan and Tony Fauci worked for, they co-own the patent for the Moderna vaccine. It’s in the wide open.
Scott Gottlieb, former chairman of the FDA, kind of my media foe when I go on TV, is on the board of Pfizer. This is in the open, you guys.
The conflict of interest is not the driver of this, but it is a happy by-product for those who are profiting. A blockbuster drug is considered a billion dollars a year and the pharmaceutical reps, they have to fight for these sales and they talk to doctors, what have you.
You know, Pfizer in less than a year with the vaccine, with no reps, with no sales force, with no costs, is at £33billion for the vaccine, prepaid. You can’t beat this.
The conflict of interest is absolutely unavoidable and it’s crushing the lifeblood of medicine, and it’s everywhere. Look, there’s so much money in this. Look at these statements. ‘Dear Dr McCullough, Federation of State Medical Boards has recently issued a statement that physician disciplinary actions, including suspension or revoking of licence.’
I’m being filmed right now. This is my licence revocation presentation, you can see that I’ve been pinpoint with respect to the data. ‘We are particularly concerned about physicians who use their authority,’ and I have it and I won’t deny it, ‘to denigrate vaccination’.
I’m not denigrating it, I gave you the data. I told you my family members took it. I took a vaccine two days ago. I’m not denigrating the vaccine. But, ‘at a time when the vaccines continue to demonstrate excellent effectiveness’ – which is, they don’t – ‘against severe illness, hospitalisation and death’. There’s no data for that.
Who’s going to decide information or misinformation?’ I don’t think there’s any fairness in the courts. I tell you, I’m an expert in a lot of it … the medical literature is corrupt. The courts are corrupt. All the major aspects of government are corrupt.
I made a presentation for the Heritage Foundation in Washington, an open meeting. Heritage Foundation gives a lot of advice to the House and Senate, NIH (National Institutes of Health) and others, and I gave basically a lot of this. And you could hear a pin drop afterwards.
And finally, one of the former AMA (American Medical Association) presidents came out and said, ‘Dr McCullough, we have the largest biological product catastrophe in human history going on right now.
‘We’ve had two administrations buy into it, the House and the Senate, the major media, the entire medical establishment, and no one knows how to stop it.’
To me, that was a stunning admission from leaders in Washington. Some people know. People know. It’s not just us. In the last two weeks, I’ve been called privately by the Federal Reserve. I’ve been called privately by two people, pretty high up in the Vatican.
I’ve been called and I’ve had conferences with some official leaders of other countries, like the leader of the other country, and they want to talk to me.
Okay, I’m telling you, we are not the only ones who realise that we’re in the middle of a major biological catastrophe. And these boards, though, are going to hunt us. And the question is, how far are they going to go and how much are we going to lose? I can tell you personally, I’m willing to lose it all. (applause)
And I told it, I think I was on Alex Jones, I was on Alex Jones, I was on Tucker Carlson and they go, ‘Dr McCullough, aren’t you afraid someone’s going to come after you?’ I said, ‘Bring it on, bring it on.’ (cheers and applause) And I did. And I did.
And there are other heroes, there are other people who do understand what’s going on. We’re not alone. These people in the media are good people. They are walking a line. You don’t understand, they’re walking a line.
They, to some degree, they do feel their lives are threatened. I’m not playing around. They’re very visible. These people are on our team. They do partially or fully understand what’s going on. Our goal is to stay alive in the media. That’s the goal.
People say, ‘Dr McCullough, what are you trying to do?’ I said, ‘Listen, I haven’t spent a dime doing this. In fact, I’ve lost a tremendous amount of money so far. I’m doing this because I don’t know anything else I can do.
I can’t save every person who calls me. But if I can actually help you and help others and help everybody who comes into my circle, we can get some awareness and awakening. We are going into a really bad time right now. We have very little time left to get active, I mean, really active.
There are things going on that you can’t make up. ‘Baylor (a Texas health system) gets a restraining order against Covid-19 vaccine sceptic doc’ – ie, me. September 16. There was no hearing. There’s no order that I had to sign.
There’s a case – but we’re not there yet, there still has to be discovery, depositions, there has to be a hearing. I’m telling you, this didn’t happen. This didn’t happen, but this was sent out and all the major media, the medical media what have you. And do you know why it was sent out? Somebody paid money or influence or power to Medscape to do this in order to signal to the media and let them think that I’m in trouble.
So the media doesn’t have me do this. That’s what this was about. This is about the lawsuit that does exist. In fact, I filed a motion, it’s called a slap lawsuit, a strategic lawsuit against public participation. They are trying to silence me just like other dark times in history where there were people trying to shout out that something was going wrong.
If we don’t act now, our future is this. I really believe this. Take a look at Australia. They have hardly any Covid. On some days, they’ll have one Covid death and 300 vaccine deaths.
They’ve already rounded up a large number of 12 year-old and 13 year-old boys and girls into an auditorium. They vaccinated them, they killed two on the spot. Okay, I’m telling you this is going on.
I’ve been to Melbourne, I’ve been to Sydney, they’re great places – they’re not great places right now. They’re shooting rubber bullets at each other.
Now is the time that we have to get activated. This is unbelievable. Melbourne’s like San Diego. It’s a beautiful place. There’s absolutely no reason why this should be happening. If they would stop now, just stop everything. Stop the vaccine, stop the lockdowns, stop everything and just treat the one or two Covid patients they have, we’d all be back to normal, but they’re not.
There are powerful forces in place that want this to happen. Very powerful forces. The challenge is to break it. And the only way to break these powerful forces is to just say no, you’ve got to break it. That’s how we break. It’s very, very important. (applause)
So people have asked me, ‘Dr McCullough, what’s behind this?’ When I got to Tucker Carlson, at one point in time, he just started, he started raising his hands, he goes, ‘Who’s behind this, who’s behind this?’ I said, ‘Tucker, I’m just a doctor. I’m just trying to explain to you, I’m just a doctor. I’m just reporting the news here.’
But I referred him to Peter Breggin or Nicholas Wade or Whitney Webb. There are a bunch of investigative reporters that will get behind it. This book is out. It’s 15 dollars, probably the best thing you could buy. It has a thousand references. It’s meticulous.
It’s largely going to tell you who’s profiting for this and the web of stakeholders here and what’s driving it. I don’t think it’s the root cause. But I think it’s who’s behind a lot of what’s going on. I can tell you,everything we’re living through right now was planned. The book is called Covid-19 and the Global Predators: We are the Prey.
So to conclude, the Covid-19 pandemic is obviously a global disaster. Its pathophysiology is complex, it’s not amenable to a single drug. Don’t bake it on a single drug. The pre-hospital phase, the time of therapeutic opportunity, we’ve got a lot more treatment we need to give.
Hospitalisation and late treatment is inadequate. Early therapy, sequenced multi-drug approach is the way to go. Use these monoclonal antibodies until they take them away, and then you can even use hydroxychloroquine, ivermectin until they take it away and then still use the other drugs and you’ll still win.
Covid-19 genetic vaccines: Unfavourable safety profile, not sufficiently effective, cannot be generally supportive. Do I think they’re absolutely horrible? No. Maybe somebody could benefit. I’m not completely against it.
The Novavax is a protein vaccine that could be good in the future. There’s 27 different vaccines. It’s just that these genetic vaccines, just like the first of anything, are not working out.
Censorship and reprisal are working to crush the freedom of speech and scientific discourse and medical progress. And I am out of gas. Thank you.
October 20, 2021
Posted by aletho |
Full Spectrum Dominance, Science and Pseudo-Science, Timeless or most popular, Video, War Crimes | Covid-19, COVID-19 Vaccine, Human rights, United States |
Leave a comment

Earlier this morning, the Israeli Interior Minister Ayelet Shaked officially notified 36-year-old Palestinian-French human rights defender Salah Hammouri of the revocation of his permanent residency status in Jerusalem based on a “breach of allegiance to the State of Israel.” This decision comes after being approved by the Israeli Attorney General Avichai Mendelblit and Minister of Justice Gideon Sa’ar. The initiation of his residency revocation and forced deportation, pursuant to Amendment No. 30 to the Entry into Israel Law of 1952, comes on the heels of the Israeli apartheid regime’s targeted harassment campaign against Salah Hammouri, a vocal Palestinian human rights advocate, long-time employee at Addameer Prisoner Support and Human Rights Association, and former prisoner.
In communicating the decision to move forward with residency revocation on the basis of “breach of allegiance,” the Minister of Interior cites intentionally vague and broad allegations of “terroristic activities” and/or affiliation with “terrorist entities,” based on withheld “secret information” withheld. The withholding of “secret information” mirrors the Israeli occupation’s administrative detention practices, in stark violation of fair trial standards, which place Palestinians under indefinite detention based on secret material that cannot be disclosed to the detainees or their lawyers. To this end, she further cites recommendations based on his past history of arrests—most of which were under administrative detention, without charge or trial. Notably, the Ministry explicitly alludes to the notable escalation of permanent residency revocation of Palestinian Jerusalemites for “breach of allegiance,” as exemplified by the case of Salah Hammouri, by stating that the decision was necessary “to deter others from breaching allegiance to the State of Israel.”
As a Palestinian human rights defender who challenges Israel’s widespread and systematic human rights violations and voices legitimate calls for justice and accountability, Salah has endured constant Israeli attempts to intimidate him and his family, including previous arbitrary arrests, banning from entering the West Bank for almost 16 months, and the deportation of his wife, Elsa Lefort, a French national, separating him from his wife and son in 2016.
Previously, on 3 September 2020, the Israeli occupying authorities notified Salah Hammouri of the Ministry’s intention to revoke his permanent residency status for so-called “breach of allegiance” to the State of Israel. Notably, Salah and his legal counsel, HaMoked Center for the Defence of the Individual and Advocate Lea Tsemeel, submitted written and oral claims challenging the decision.
Salah is alarmed by the imminent threat of having his residency revoked, which denies Salah’s basic human rights to family life, freedom of movement and residence, including the right to leave and to return to his country, freedom of expression, as enshrined in Article 19 of the ICCPR and freedom of peaceful assembly and association, in line with Articles 21 and 22 of the ICCPR.[1] Residency policies embedded in Israel’s regime of racial domination and oppression are designed to maintain a perilous legal status for Palestinians in East Jerusalem and uphold an Israeli-Jewish demographic majority in the city.
Israel’s policy of revoking Palestinian residency rights in East Jerusalem further violates Article 43 of the Hague Regulations and Article 64 of the Fourth Geneva Convention, which stipulates that the Occupying Power may not act as a sovereign legislator or extend its own legislation over the occupied territory.[2] Moreover, the criterion of allegiance to Israel is illegal. In fact, international humanitarian law explicitly forbids the Occupying Power from demanding allegiance from the occupied population, as stated in Article 45 Hague Regulations and Article 68(3) of the Fourth Geneva Convention.[3] Furthermore, the transfer of Palestinians from occupied East Jerusalem is considered a war crime under Article 8 of the Rome Statute of the International Criminal Court.[4] The revocation of residency policy forms part of a widespread and systematic transfer policy directed against a civilian population, which may also amount to a crime against humanity under Article 7 of the Rome Statute.[5]
[1] Articles 19, 21, and 22, ICCPR.
[2] Hague Convention (IV) Respecting the Laws and Customs of War on Land and Its Annex: Regulations Concerning the Laws and Customs of War on Land (adopted 18 October 1907, entry into force 26 January 1910) (henceforth the “Hague Regulations”) Article 43, Hague Regulations, and Article 64, Fourth Geneva Convention.
[3] Article 45, Hague Regulations, and Article 68(3), Fourth Geneva Convention.
[4] Rome Statute of the International Criminal Court (adopted 17 July 1998, entry into force 1 July 2002) 2187 UNTS 3. (henceforth “Rome Statute”)
[5] Article 7, Rome Statute
Israeli Minister of Interior to Officially Revoke Permanent Residency of Lawyer Salah Hammouri_0.pdf
October 19, 2021
Posted by aletho |
Ethnic Cleansing, Racism, Zionism, Full Spectrum Dominance, War Crimes | Human rights, Israel, Zionism |
Leave a comment
In 2019, 97% of countries in Western Europe were not adding fluoride to their water.1 While a handful use fluoridated salt, the majority do not. Yet, despite the lack of fluoridated water or salt in their diets, the rates of tooth decay have declined significantly in all the countries.2
In September 2021, Great Britain’s health secretary Sajid Javid announced he would be adding fluoride to all public water supplies,3 forcing citizens to consume the neurotoxin. The statement came in conjunction with approval by the United Kingdom’s chief medical officers from England, Northern Ireland, Wales and Scotland.4
Paradoxically, his announcement comes one year after a consumers’ group in the U.S. filed a federal lawsuit challenging water fluoridation that supplies 200 million U.S. citizens. The suit was brought against the Environmental Protection Agency and would require water utilities to stop fluoridation.5
Fluoride is a naturally-occurring mineral in water and soil that scientists in the 1940s found might help prevent tooth decay.6 Water fluoridation began in the U.S. in Grand Rapids, Michigan, in 1945 and other Michigan communities and then states adopted the practice in the years that followed.
Ninety-six percent of the fluoride7 used in U.S. water systems comes from apatite ore, the source of phosphate fertilizers. While the mineral’s composition also includes “high concentrations” of hydroxide, fluoride and chloride, the CDC calls the addition of this neurotoxic chemical “one of public health’s greatest success stories.”8 Yet, this “great success story” originates with highly toxic by-products in the production of fertilizer.9
The production process involves mixing the apatite with sulfuric acid derived from molten sulfur, which the American Water Works Association describes as “a waste product from cleaning petroleum feedstock.”10
Once the toxic vapors are converted to a dangerous liquid waste, it is transported from fertilizer factories to water reservoirs where it is added to drinking water.11 However, unlike pharmaceutical grade fluoride in toothpaste, this is “an untreated industrial waste product, one that contains trace elements of arsenic and lead.”12
Unfortunately, not many are aware of the effects fluoride has as a cradle-to-grave neurotoxin or the origin of the waste product added to the water supply. Although there has been some pushback against the proposal in the U.K.,13 Javid “is understood to be keen to press ahead with adding the mineral to the water supply and will gain powers to do so across England under laws going through parliament.”14
Despite Evidence of Danger, UK to Force Fluoridation
In a concerted effort to convince the public to accept the proposal, the U.K.’s chief medical officers came out together endorsing water fluoridation across the U.K. countries.15 In an effort to make it look like adding fluoride to the water is a benefit to U.K. citizens’ health, they added the proposal to legislation called “The Health and Care bill,”16 which is set to go before the MPs, which will then give Javid the authority needed to order fluoridation.17
In response to this, three British scientists sent a public letter to Great Britain’s prime minister, Boris Johnson. In the press release published from the U.K Freedom from Fluoride Alliance they write,18 “This is not a good time for the British government to mislead the public on the dangers posed by the practice of water fluoridation.”
The scientists believe that the statements from the chief medical officers from the four U.K. countries extol the weak benefits of fluoridation, but ignore stronger evidence that fluoride is a developmental neurotoxin. According to the scientists,19
“The dental lobby has controlled this debate for far too long. You can repair a damaged tooth but early damage to the brain (especially during fetal development and infancy) cannot be repaired or reversed.
This is so serious for the future of our country that the matter should not be resolved by the kind of ‘sleight of hand’ used by those who wrote the script for the CMOs’ statement.”
In their statement20 there are two short paragraphs that deal with the risk of fluoridation, which the scientists refer to as “sleight of hand.” Within the paragraphs, the CMOs do not mention the numerous studies demonstrating neurotoxicity and do not mention the lawsuit against the U.S. EPA. These points were made in their open letter to the prime minister in which they said they:21
“… sincerely hope that your health advisers will acknowledge the strong scientific evidence of fluoride’s neurotoxicity (and other ill health effects) and put the health of our people above promoting what appears to be a well-intended but clearly outdated practice of water fluoridation.
This would not be the first time that a well-entrenched medical or dental practice has had to give way to advances in scientific understanding of unexpected side effects.”
However, as reported in The Times,22 “Chris Whitty, the chief medical officer for England, has dismissed safety concerns over the compounds, saying there is no evidence that it causes cancer and that claims about health risks are ‘exaggerated and unevidenced’.”
Strong Evidence Fluoride Is Neurotoxic
One of the first studies demonstrating fluoride has an adverse effect on children’s IQ was originally published in 1989 in the Chinese Journal of Control of Endemic Diseases. Since then, the Fluoride Action Network23 has recorded dozens of studies that have analyzed the relationship between IQ and fluoride.
Of these, 70 human studies and 60 animal studies have demonstrated an association between exposure and a reduction in learning or memory capacity. The human studies had children and adult participants that provide compelling evidence of damage. The Fluoride Action Network also published an analysis of the challenges associated with the studies that did not find an association.24
Some of the strongest studies demonstrating an association were published in 2019 and 2020. The claims made by proponents of fluoridation that there is only “one or two studies” finding harm, or that they are only from areas with naturally high fluoride levels, are no longer relevant. The scientific evidence can now be considered overwhelming and undeniable. The studies include:
Green 2019 — published in the Journal of the American Medical Association’s journal on Pediatrics.25 It reported substantial IQ loss in Canadian children from prenatal exposure to fluoride from water fluoridation.26
Riddell 2019 — published in Environment International.27 It found a shocking 284% increase in the prevalence of ADHD among children in fluoridated communities in Canada compared to nonfluoridated ones.28
Till 2020 — published in Environment International.29 It reported that children who were bottle-fed in Canadian fluoridated communities lost up to 8.8 IQ points compared to those in nonfluoridated communities.30
Uyghurturk 2020 — published in Environmental Health,31 It found that pregnant women in fluoridated communities in California had significantly higher levels of fluoride in their urine than those in nonfluoridated communities. The levels found in their urine were the same as those found to lower children’s IQ in past studies.32,33
Malin 2019 — published in Environmental Health.34 It linked a doubling of symptoms indicative of sleep apnea in adolescents in the U.S. to levels of fluoride in the drinking water. The link between fluoride and sleep disturbances may be through fluoride’s effect on the pineal gland.35
Malin 2019 — published in Environment International.36 It reported that exposure to fluoridated water led to a reduction in kidney and liver function among adolescents in the U.S. and suggested those with poorer kidney or liver function may absorb more fluoride bodies. The National Institutes of Health funded this study.37
The level of evidence that fluoride is neurotoxic now far exceeds the evidence that was in place when lead was banned from gasoline. A recent review by Danish scientist, Harvard professor and neurotoxicity expert Dr. Philippe Grandjean also concluded that:38
“… there is little doubt that developmental neurotoxicity is a serious risk associated with elevated fluoride exposure, whether due to community water fluoridation, natural fluoride release from soil minerals, or tea consumption, especially when the exposure occurs during early development.
Given that developmental neurotoxicity is considered to cause permanent adverse effects, the next generation’s brain health presents a crucial issue in the risk-benefit assessment for fluoride exposure.”
Fluoride Is an Endocrine Disrupter That Affects the Brain
Evidence shows that fluoride as an endocrine disrupter affects both sleep and the brain. It contributes to the rising rate of children and adults with attention deficit hyperactive disorder (ADHD). One study39 published in 2015 demonstrated that children with higher rates of medically diagnosed ADHD resided in states where there was a greater proportion of people consuming fluoridated water.
In 2006, the National Resource Council of the National Academies labeled fluoride an endocrine disruptor.40 According to the National Institutes of Health in 2014,41 “Research shows that endocrine disruptors may pose the greatest risk during prenatal and early postnatal development when organ and neural systems are forming.” The NIH has since removed that statement from their website.42
Exposure to fluoride is also linked to thyroid disease,43 which in turn contributes to heart disease, obesity, depression and other health problems. Fluoride has an adverse effect on sleep patterns. One study44 found chronic low-level exposure altered sleep patterns in adolescents aged 16 to 19.
They found fluoride levels of .52 mg per liter was associated with a 1.97 times higher likelihood of sleep apnea at least once per week. This level is lower than the current recommendation of 0.7 mg/L.45
The researchers theorized46 that the accumulation of fluoride in the pineal gland may affect sleep patterns. Additionally, the researchers wrote that in adults, fluoride concentrations in the pineal gland correlate with calcification, which in turn is associated with a decrease in melatonin production, lower sleep time and lower REM sleep percentage.
Health and Human Services Lowers Level of Fluoride in 2015
In 2010, a study47 published in the Journal of the American Dental Association concluded that there was an association between fluorosis and children’s teeth and intake from infant formula and other dietary sources. They wrote:
“Results suggest that prevalence of mild dental fluorosis could be reduced by avoiding ingestion of large quantities of fluoride from reconstituted powdered concentrate infant formula and fluoridated dentifrice.”
The CDC also followed suit in 2010, warning that mixing powdered or liquid infant formula with fluoridated water could increase the chance of a child developing enamel fluorosis.48 These recommendations have since been deleted.49
However, your teeth are the window to your bones, and when you see damage to your teeth you must ask the question: What kind of damage to your bones is occurring?
In April 2015, the U.S. Department of Health and Human Services admitted the fluoride levels they had been promoting damaged children’s teeth.50 Major dental fluorosis was apparent in 41% of teenagers,51 which includes white spots, yellow coloring or pitted enamel.
Despite levels of fluoride that were high enough to cause fluorosis, the CDC52 also reported that 42% of children and adolescents ages 6 to 19 years and 90% of adults had cavities in their permanent teeth. Although some health experts continue to promote fluoride as protection against cavities, it’s apparently not doing the job.
Instead of completely removing fluoride from the water to protect bone health in 2015, the HHS announced they would simply reduce the level of fluoride in the water to minimize “the risk of cosmetic fluorosis in the general population.”53 To stress the idea that fluorosis is solely a cosmetic issue negates the potential risk to bone health.
By 2020, the American Dental Association was fully on board with fluoridating water in the U.S. In a letter54 to the National Academies of Sciences, Engineering, and Medicine, they noted their members agreed that the 2018 edition of Fluoridation Facts, the ADA’s resource on community water fluoridation, answered questions on the relationship between consumption and lowered intelligence or behavioral disorders.
Choosing to blatantly ignore all the studies showing fluoride is a dangerous neurotoxin, they stated, “The evidence from individual studies and systematic reviews does not support claims of a causal relationship.”55 Additionally, they urged that the National Toxicology Program Monograph on Fluoride Exposure and Neurodevelopmental and Cognitive Health should move its classification of fluoride from a “presumed” neurotoxin to an “unknown” neurotoxin.
Their justification for this was to claim:56 “There is not a wide body of literature examining fluoride as a potential neurotoxin.” In other words, 70 human and 60 animal studies were not enough to “support claims of a causal relationship” and is not a “wide body of literature examining fluoride as a potential neurotoxin.”
Help End the Practice of Water Fluoridation
What might be assumed from statements made by politicians and experts, is there is a greater concern over tooth decay than there is over loss of intelligence, brain health in adults and children and damage done through endocrine disruption.
For citizens in the U.K., a petition has been initiated in Parliament recommending that instead of adding fluoride to compel the entire nation to ingest a neurotoxin, “it would be better if people brush their teeth with toothpaste daily and monitor intake of sugar.”57
U.K. citizens can sign the petition at this link. If it reaches 100,000 signatures, Parliament must consider it for debate. For those who live in an area with fluoridated water, you can protect your health by filtering the water supply.
Because fluoride is a very small molecule, it’s difficult to filter once added, but reverse osmosis filtration can be effective.58 Clean pure water is a prerequisite for optimal health; thus, the only real solution is to stop the practice of artificial water fluoridation.
Sources and References
October 19, 2021
Posted by aletho |
War Crimes | Human rights, UK |
Leave a comment
In a previous post, I looked at where ‘The Science’ of community masking came from. Here I’ll do the same thing for lockdowns.
As many lockdown sceptics (including myself) have noted, lockdowns represent a radical departure from conventional forms of pandemic management. There is no evidence that, before 2020, they were considered an effective way to deal with influenza pandemics.
In a 2006 paper, four leading scientists (including Donald Henderson, who led the effort to eradicate smallpox) examined measures for controlling pandemic influenza. Regarding “large-scale quarantine”, they wrote, “The negative consequences… are so extreme” that this measure “should be eliminated from serious consideration”.
Likewise, a WHO report published mere months before the COVID-19 pandemic classified “quarantine of exposed individuals” as “not recommended under any circumstances”. The report noted that “there is no obvious rationale for this measure”.
And we all know what the U.K.’s own ‘Pandemic Preparedness Strategy’ said, namely: “It will not be possible to halt the spread of a new pandemic influenza virus, and it would be a waste of public health resources and capacity to attempt to do so.”
As an additional exercise, I searched the pandemic preparedness plans of all the English-speaking Western countries (U.K., Ireland, U.S., Canada, Australia and New Zealand) for mentions of ‘lockdown’, ‘lock-down’ ‘lock down’ or ‘curfew’.
Only ‘curfew’ was mentioned, and only once – in Ireland’s plan. The relevant sentence was: “Mandatory quarantine and curfews are not considered necessary.” None of the lockdown strings were mentioned in any of the countries’ plans.
So where did ‘The Science’ of controlling Covid using lockdowns come from? As everyone knows, China implemented the first lockdown (of Hubei province) in January of 2020. Yet it wasn’t until March that lockdowns became part of ‘The Science’.
As this chart taken from the paper by David Rozado shows, major Western media outlets did not start mentioning ‘lockdown’ frequently until March:
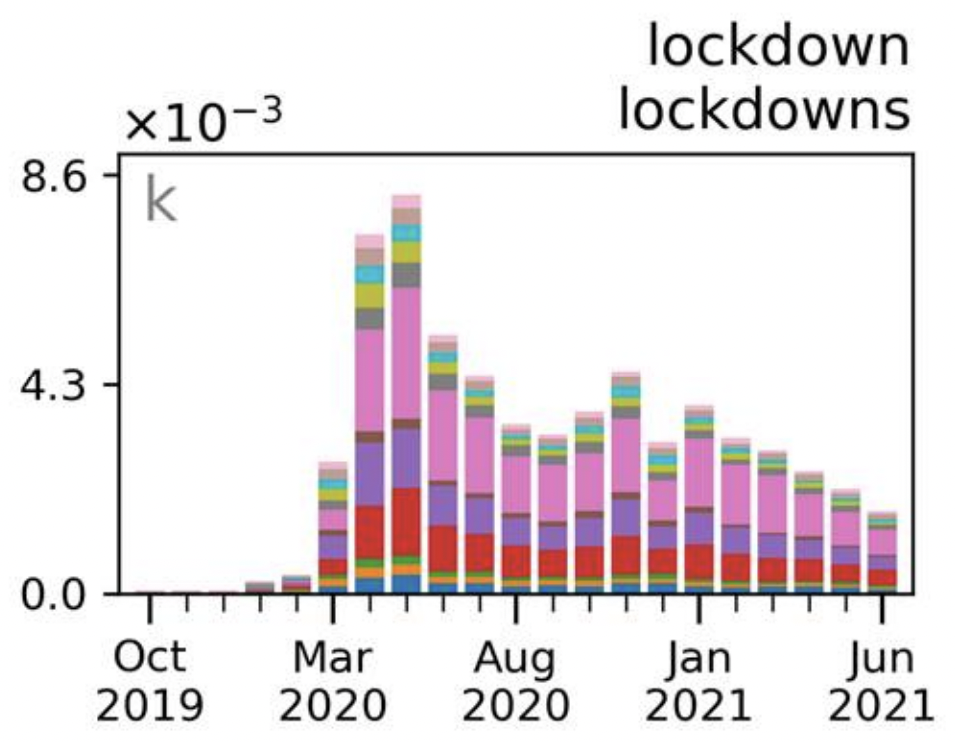
And this chart confirms that worldwide Google search interest for ‘lockdown’ was essentially nil until 8th March 2020:
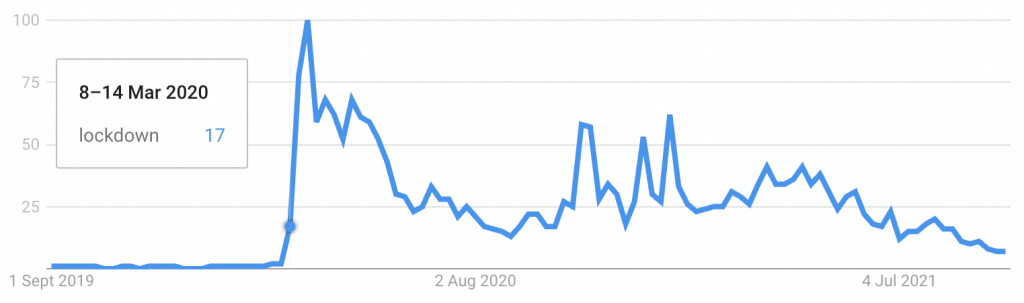
So what happened in early March? Well, Italy was the first Western country to lock down – on 9th March last year. And as Michael Senger argues, its decision appears to have been prompted by the WHO’s report of 24th February, which gave a glowing evaluation of China’s lockdown. (Senger’s piece is well worth reading.)
Other Western countries then followed suit. The next most important event, following Italy’s decision to lock down, was the publication of a report by Neil Ferguson’s team on 16th March.
This report has been described as the “catalyst for policy reversal”. Up until then, the U.K. had been more or less following its pandemic preparedness plan. As late as March 5th, Chris Whitty told the Health and Social Care Committee that “what we’re very keen to do is minimise social and economic disruption”.
Although other, similar reports had already been published, the analysis by Neil Ferguson’s team was seen as particularly authoritative. According to the New York Times, the report “also influenced the White House to strengthen its measures”.
On March 17th, Neil Ferguson and his colleagues held a press conference after returning from Downing Street. They confirmed that Britain would be adopting a new strategy. “The aim is not to slow the rate of growth of cases but actually pull the epidemic into reverse,” Ferguson said.
As to why the U.K. was changing tack, Ferguson noted, “We have had bad news from Italy and from early experience in UK hospitals”. However, subsequent revelations suggest that “bad news” was less important than the shifting of the Overton window.
In an interview with the Times published in December last year, Ferguson noted that “people’s sense of what is possible in terms of control changed quite dramatically between January and March”. Referring to China’s lockdown, he elaborated, “We couldn’t get away with it in Europe, we thought… And then Italy did it. And we realised we could”.
After China’s initial response in Hubei, it took two months for lockdowns to go from ‘unprecedented’ to ‘unavoidable’. They received two major doses of intellectual credibility: first from the WHO, and then from Neil Ferguson’s team. Italy set the all-important precedent for Western countries.
As to whether one should trust ‘The Science’ on lockdowns, a reasonable answer would be, ‘Do you mean the pre or the post-Covid science?’
October 19, 2021
Posted by aletho |
Civil Liberties, Science and Pseudo-Science | China, Covid-19, Human rights, UK |
Leave a comment
Joining me today is Ben Swann, here to discuss how he has been fighting back against the COVID-19 tyranny, and the actions he is taking to create a space where the truth can be heard. And no discussion with Ben would be complete without a back and forth about the many different ways in which COVID-19 itself is a deception.
Podcast: Play in new window | Download | Embed
Subscribe: Apple Podcasts | Email |
(https://www.rokfin.com/TLAVagabond)
(https://odysee.com/@TLAVagabond:5)
(https://www.bitchute.com/channel/24yVcta8zEjY/)
October 19, 2021
Posted by aletho |
Civil Liberties, Deception, Mainstream Media, Warmongering, Science and Pseudo-Science, Timeless or most popular, Video | Covid-19, COVID-19 Vaccine, Human rights |
Leave a comment
Few subjects have been more controversial than ivermectin and hydroxychloroquine — two long-established, inexpensive medications widely and successfully used in many parts of the world for the prevention and treatment of COVID.
By contrast, the use of both medications against COVID has been largely suppressed in the U.S, where doctors have been threatened and punished for prescribing them.
On Oct. 15, Nebraska Attorney General (AG) Doug Peterson issued a legal opinion that Nebraska healthcare providers can legally prescribe off-label medications like ivermectin and hydroxychloroquine for the treatment of COVID, so long as they obtain informed consent from the patient.
However, if they did neglect to obtain consent, deceive, prescribe excessively high doses or other misconduct, they could be subject to discipline, Peterson wrote.
The AG’s office emphasized it was not recommending any specific treatment for COVID. “That is not our role,” Peterson wrote. “Rather, we address only the off-label early treatment options discussed in this opinion and conclude that the available evidence suggests they might work for some people.”
Peterson said allowing physicians to consider early treatments will free them to evaluate additional tools that could save lives, keep patients out of the hospital and provide relief for our already strained healthcare system.
The opinion, based on an assessment of relevant scientific literature, was rendered in response to a request by Dannette Smith, CEO of the Nebraska Department of Health and Human Services.
Smith asked the AG’s office to look into whether doctors could face discipline or legal action under Nebraska’s Uniform Credential Act (UCA) — meant to protect public health, safety and welfare — if they prescribed ivermectin or hydroxychloroquine.
“After receiving your question and conducting our investigation, we have found significant controversy and suspect information about potential COVID-19 treatments,” Peterson wrote.
For example, a paper published in the Lancet — one of the most prestigious medical journals in the world — denounced hydroxychloroquine as dangerous, yet the statistics were flawed and the authors refused to provide analyzed data.
The paper was retracted, but not before countries stopped using the drug and trials were cancelled or interrupted.
“The Lancet’s own editor-in-chief admitted that the paper was a ‘fabrication,’ a ‘monumental fraud’ and a ‘shocking example of research misconduct’ in the middle of a global health emergency,” Peterson wrote in the opinion.
A recently published paper on COVID recognized that “for reasons that are yet to be clarified,” early treatment has not been emphasized despite numerous U.S. healthcare providers advocating for early treatment and “scores of treating and academic physicians” — who have published papers in well respected journals — urging early interventions.
Peterson cited numerous studies showing ivermectin and hydroxychloroquine reduced mortality by up to 75% or more when used as a preventative or prophylaxis for COVID, suggesting hundreds of thousands of lives could have been saved had the drugs been widely used in America.
“Every citizen — Democrat or Republican — should be grateful for Doug Peterson’s thoughtful and courageous counteroffensive against the efforts of Big Pharma, its captive federal regulators, and its media and social media allies to silence doctors and deny Americans life-saving treatments,” Robert F. Kennedy Jr., chairman of Children’s Health Defense, told The Defender via email.
“We finally have a leader who puts constitutional rights, peer-reviewed science and human health above industry profits. Doug Peterson is uncowed and unbowed — a genuine hero on horseback for all Americans.” Kennedy said.
Children’s Health Defense President Mary Holland agreed. “This Nebraska AG opinion lets doctors get back to being doctors — without being second-guessed by government, pharmacists and others interfering in the crucial doctor-patient relationship,” Holland said.
Although the AG’s office did not rule out the possibility that other off-label drugs might show promise — either now or in the future — as a prophylaxis or treatment against COVID, it confined its opinion to ivermectin and hydroxychloroquine for the sake of brevity.
Nebraska AG highlights science on ivermectin
In his legal opinion, Peterson concluded evidence showed ivermectin demonstrated striking effectiveness in preventing and treating COVID, and any side effects were primarily minor and transient. “Thus, the UCA does not preclude physicians from considering ivermectin for the prevention or treatment of COVID,” Peterson wrote.
In the decade leading up to the COVID pandemic, Peterson found numerous studies showing ivermectin’s antiviral activity against several RNA viruses by blocking the nuclear trafficking of viral proteins, adding to 50 years of research confirming ivermectin’s antiviral effects.
In addition, safety data for ivermectin showed side effects were “vanishingly small.” The latest statistics available through VigiAccess reported only 5,674 adverse drug reactions to ivermectin between 1992 and October 13, 2021, an “incredibly low” number given that 3.7 billion doses have been administered since the 1980s, Peterson wrote.
Peterson cited several studies showing ivermectin led to improvement of COVID outcomes when used in early treatment or as a prophylaxis, while noting many studies with negative findings about ivermectin “excluded most available evidence,” cherry picked data within studies, misreported data, made unsupported assertions of adverse reactions to ivermectin and had “conclusions that did follow from evidence.”
Peterson also found that epidemiological evidence for ivermectin’s effectiveness, derived by analyzing COVID-related data from various states, countries or regions is instructive in the context of a global pandemic.
In one instance, a group of scholars analyzed data comparing COVID rates of countries that routinely administer ivermectin as a prophylaxis and countries that did not. The research showed “countries with routine mass drug administration of prophylactic … ivermectin have a significantly lower incidence of COVID-19.”
“This ‘highly significant’ correlation manifests itself not only ‘in a worldwide context’ but also when comparing African countries that regularly administer prophylactic ‘ivermectin against parasitic infections’ and African countries that do not,” Peterson wrote. “Based on these results, the researchers surmised that these results may be connected to ivermectin’s ability to inhibit SARS-CoV-2 replication, which likely leads to lower infection rates.”
Nebraska AG calls out FDA, Fauci on hypocrisy on ivermectin
Many U.S. health agencies have now addressed the use of ivermectin for COVID. The National Institutes of Health (NIH) has adopted a neutral position, choosing not to recommend for or against the use of ivermectin — a change from its position in January 2021 where it discouraged use of the drug for treatment of COVID.
Peterson wrote:
“The reason for the change is the NIH recognized several randomized trials and retrospective cohort studies of ivermectin use in patients with COVID-19 have been published in peer-reviewed journals. And some of those studies reported positive outcomes, including shorter time to resolution of disease manifestations that were attributed to COVID-19, greater reduction in inflammatory marker levels, shorter time to viral clearance, [and] lower mortality rates in patients who received ivermectin than in patients who received comparator drugs or placebo.”
Yet, on Aug. 29, Dr. Anthony Fauci, director of the National Institute of Allergy and Infectious Diseases within the NIH, went on CNN and announced “there is no clinical evidence” that ivermectin works for the prevention or treatment of COVID. Fauci went on to reiterate that “there is no evidence whatsoever” that it works.
“This definitive claim directly contradicts the NIH’s recognition that ‘several randomized trials … published in peer-reviewed journals’ have reported data indicating that ivermectin is effective as a COVI D-19 treatment,” Peterson wrote.
In March 2021, the FDA posted a webpage, “Why You Should Not Use lvermectin to Treat or Prevent COVID-19.”
“Although the FDA’s concern was stories of some people using the animal form of ivermectin or excessive doses of the human form, the title broadly condemned any use of ivermectin in connection with COVID-19,” Peterson wrote. “Yet, there was no basis for its sweeping condemnation.”
Peterson wrote:
“Indeed, the FDA itself acknowledged on that very webpage (and continued to do so until the page changed on September 3, 2021) that the agency had not even ‘reviewed data to support use of ivermectin in COVID-19 patients to treat or to prevent COVID-19.’ But without reviewing the available data, which had long since been available and accumulating, it is unclear what basis the FDA had for denouncing ivermectin as a treatment or prophylaxis for COVID-19.
“On that same webpage, the FDA also declared that ‘[i]vermectin is not an anti-viral (a drug for treating viruses).’ It did so while another one of its webpages simultaneously cited a study in Antiviral Research that identified ivermectin as a medicine ‘previously shown to have broad-spectrum anti-viral activity.’”
“It is telling that the FDA deleted the line about ivermectin not being ‘anti-viral’ when it amended the first webpage on September 3, 2021,” Peterson noted.
Peterson said the FDA’s most controversial statement on ivermectin was made on Aug. 21, when it posted a link on Twitter to its “Why You Should Not Use lvermectin” webpage with this statement: “You are not a horse. You are not a cow. Seriously, y’all. Stop it.”
“This message is troubling not only because it makes light of a serious matter but also because it inaccurately implies that ivermectin is only for horses or cows,” Peterson wrote.
Peterson said the FDA has assailed ivermectin’s safety while ignoring the fact that physicians routinely prescribe medications for off-label use and that ivermectin is a “particularly well-tolerated medicine with an established safety record.”
Peterson added the FDA is ignoring several randomized controlled trials and at least one metaanalysis suggesting ivermectin is effective against COVID. He pointed out the Centers of Disease Control and Prevention has adopted a similar stance — unsupported by scientific evidence — and the media has fueled confusion and misinformation on the drug.
Peterson questions professional associations’ stance on ivermectin
Professional associations in the U.S. and internationally have adopted conflicting positions on ivermectin and COVID. The American Medical Association (AMA), American Pharmacists Association (APhA) and American Society of Health-System Pharmacists (ASHP) issued a statement in September strongly opposing the ordering, prescribing or dispensing of ivermectin to prevent or treat COVID outside of a clinical trial.
But their statement relied solely on the FDA’s and CDC’s suspect positions.
The AMA, APhA and ASHP also mentioned a statement by Merck — the original patent-holder — opposing the use of ivermectin for COVID because of a “concerning lack of safety data in the majority of studies.”
“But Merck, of all sources, knows that ivermectin is exceedingly safe, so the absence of safety data in recent studies should not be concerning to the company,” Peterson wrote.
Peterson called into question the objectivity of Merck in providing an opinion on ivermectin that U.S. health agencies are relying upon. “Why would ivermectin’s original patent holder go out of its way to question this medicine by creating the impression that it might not be safe?” Peterson asked. “There are at least two plausible reasons.”
Peterson explained:
“First, ivermectin is no longer under patent, so Merck does not profit from it anymore. That likely explains why Merck declined to ‘conduct clinical trials’ on ivermectin and COVID-19 when given the chance.
“Second, Merck has a significant financial interest in the medical profession rejecting ivermectin as an early treatment for COVID-19. [T]he U.S. government has agreed to pay [Merck] about $1.2 billion for 1.7 million courses of its experimental COVID-19 treatment, if it is proven to work in an ongoing large trial and authorized by U.S. regulators.”
Merck’s treatment is known as “molnupiravir,” and aims to stop COVID from progressing when given early in the course of disease. When Merck announced Oct. 1, that preliminary studies indicated molnupiravir reduced hospitalizations and deaths by half, the drug maker’s stock price immediately jumped to 12.3%.
“Thus, if low-cost ivermectin works better than, or even the same as molnupiravir, that could cost Merck billions of dollars,” Peterson wrote.
Peterson takes on science of hydroxychloroquine
Peterson said based on his review of the evidence, his office did not find clear and convincing evidence that would warrant disciplining physicians who prescribe hydroxychloroquine for the prevention or early treatment of COVID after first obtaining informed patient consent.
Peterson pointed to similar findings with hydroxychloroquine — a less toxic derivative of a medicine named chloroquine — widely used since it was approved by the FDA in 1955 for treatment of malaria.
Peterson noted that as early as 2004, a lab study revealed chloroquine was “an effective inhibitor of the replication of the severe acute respiratory syndrome coronavirus (SARS-CoV) in vitro” and should “be considered for immediate use in the prevention and treatment of SARS-CoV infections.”
In 2005, another study showed chloroquine had strong antiviral effects on SARS-CoV infection and was effective in preventing the spread of SARS-CoV in cell cultures.
Other studies showed hydroxychloroquine exhibited antiviral properties that can inhibit SARS-CoV-2 virus entry, transmission and replication, and contains anti-inflammatory properties that help regulate pro-inflammatory cytokines.
Peterson wrote, “many large observational studies suggest that hydroxychloroquine significantly reduces the risk of hospitalization and death when administered to particularly high-risk outpatients as part of early COVID-19 treatment.”
Peterson said the drug is considered to be so safe it can be prescribed for pregnant women, yet during the pandemic, the FDA raised questions about hydroxychloroquine and adverse cardiac events.
These concerns prompted one group of researchers to conduct a systematic review of the hydroxychloroquine safety literature pre-COVID. Their review indicated people taking hydroxychloroquine in appropriate doses “are at very low risk of experiencing cardiac [adverse events], particularly with short-term administration” of the drug.
Researchers noted COVID itself can cause cardiac problems, and there was no reason “to think the medication itself had changed after 70 years of widespread use,” Peterson wrote.
Peterson said one piece of key flawed data had substantially contributed to safety concerns surrounding the drug — the admittedly fraudulent Lancet study that falsely claimed hydroxychloroquine increased frequency of ventricular arrhythmias when used for treatment of COVID.
The findings were so startling that major drug trials involving hydroxychloroquine “were immediately halted” and the World Health Organization pressured countries like Indonesia that were widely using hydroxychloroquine to ban it. Some countries, including France, Italy and Belgium, stopped using it for COVID altogether.
Peterson wrote:
“The problem, however, is that the study was based on false data from a company named Surgisphere, whose founder and CEO Sapan Desai was a co-author on the published paper.
“The data were so obviously flawed that journalists and outside researchers began raising concerns within days of the paper’s publication. Even the Lancet’s editor in chief, Dr. Richard Horton, admitted that the paper was a fabrication, a monumental fraud and a shocking example of research misconduct in the middle of a global health emergency.”
Despite calls for the Lancet to provide a full expansion of what happened, the publication declined to provide details for the retraction.
As with ivermectin, the FDA and NIH adopted positions against the use of hydroxychloroquine for COVID — making assertions that were unsupported by data. The AMA, APhA and ASHP, which opposed ivermectin, also resisted hydroxychloroquine for the treatment of COVID.
By contrast, the Association of American Physicians and Surgeons, and other physician groups, support the use of both ivermectin and hydroxychloroquine as an early treatment option for COVID. Peterson cited an article co-authored by more than 50 doctors in Reviews in Cardiovascular Medicine who advocated an early treatment protocol that includes hydroxychloroquine as a key component.
Governing law allows physicians to prescribe ivermectin and hydroxychloroquine, AG says
Neb. Rev. Stat. § 38-179 generally defines unprofessional conduct as a “departure from or failure to conform to the standards of acceptable and prevailing practice of a profession or the ethics of the profession, regardless of whether a person, consumer or entity is injured, or conduct that is likely to deceive or defraud the public or is detrimental to the public interest.”
The regulation governing physicians states that unprofessional conduct includes:
“[c]onduct or practice outside the normal standard of care in the State of Nebraska which is or might be harmful or dangerous to the health of the patient or the public, not to include a single act of ordinary negligence.”
Peterson said healthcare providers do not violate the standard of care when they choose between two reasonable approaches to medicine.
“Regulations also indicate that physicians may utilize reasonable investigative or unproven therapies that reflect a reasonable approach to medicine so long as physicians obtain written informed patient consent,” Peterson wrote.
“Informed consent concerns a doctor’s duty to inform his or her patient, and it includes telling patients about the nature of the pertinent ailment or condition, the risks of the proposed treatment or procedure and the risks of any alternative methods of treatment, including the risks of failing to undergo any treatment at all.”
Peterson said this applies to prescribing medicine for purposes other than uses approved by the FDA, and that doing so falls within the standard of care repeatedly recognized by the courts.
Peterson said the U.S. Supreme Court has also affirmed that “off-label usage of medical devices” is an “accepted and necessary” practice, and the FDA has held the position for decades that “a physician may prescribe [a drug] for uses or in treatment regimens or patient populations that are not included in approved labeling.”
Peterson said the FDA has stated “healthcare providers generally may prescribe [a] drug for an unapproved use when they judge that it is medically appropriate for their patient, and nothing in the federal Food, Drug and Cosmetic Act (“FDCA”) limit[s] the manner in which a physician may use an approved drug.”
In a statement to KETV NewsWatch 7, Nebraska’s Department of Health and Human Services said:
“The Department of Health and Human Services appreciates the AG’s office delivering an opinion on this matter. The document is posted and available to medical providers as they determine appropriate course of treatment for their patients.”
© 2021 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
October 18, 2021
Posted by aletho |
Science and Pseudo-Science | Covid-19, FDA, HCQ, Human rights, Ivermectin, United States |
Leave a comment
At long last, thanks to the testimony of a Palestinian held at Guantanamo Bay, someone might finally be held accountable for the gross human rights violations the agency inflicted on so many with such impunity for years.
In a landmark move, the Biden administration has advised the US Supreme Court that Abu Zubaydah, a Palestinian man who has been in US custody for nearly 20 years, can provide limited testimony for use in a Polish criminal investigation into his torture at a CIA “black site” in that country.
Acting Solicitor General Brian Fletcher has stated that Zubaydah’s testimony will be subject to US national security review, and while he would be permitted to describe his treatment while in CIA custody, “information that could prejudice the security interests” of Washington could be redacted.
Nonetheless, even such truncated scope for disclosure is a seismic development, for Zubaydah has been held incommunicado since his March 2002 capture in Pakistan. Indeed, his CIA torturers specifically sought “reasonable assurances that [Zubaydah] will remain in isolation and incommunicado for the remainder of his life,” in order that their criminal maltreatment remained secret, and they were insulated from prosecution. Such assurances were eagerly granted by Washington.
“There is a fairly unanimous sentiment within [headquarters] that [Zubaydah] will never be placed in a situation where [he] has any significant contact with others and/or has the opportunity to be released,” a classified memo declared. “While it is difficult to discuss specifics at this point, all major players are in concurrence that [Zubaydah] should remain incommunicado for the remainder of his life.”
So it was that Zubaydah was moved around an assortment of CIA black sites for four years, and was viciously tortured every step of the way. Among other gruesome acts, he was repeatedly waterboarded, locked in a tiny coffin-like box for hundreds of hours, hung from hooks, denied sleep, and forced to remain in ‘stress positions’ for extended periods – resulting in permanent brain damage and the loss of his left eye – in an attempt to extract information that he didn’t actually possess.
Zubaydah’s arrest was hailed as a major coup at the time, with US officials branding him a major Al-Qaeda financier, a key link between the group’s leader Osama bin Laden and its overseas operational cells, the manager of the camp in Afghanistan where the 9/11 hijackers were purportedly trained, a central figure in every major Al-Qaeda terrorist operation, and “engaged in ongoing terrorism planning against US interests.”
None of this was true. The basis for these lurid, false claims was a CIA psychological assessment of Zubaydah, which was primarily concerned with justifying his vicious abuse – it falsely stated, for example, that he had written Al-Qaeda’s manual on resisting interrogation, arguing that, due to his “incredibly strong resolve, expertise in civilian warfare [and] resistance to interrogation techniques,” torture was the only means by which information could be extracted from him.
Before this abuse commenced, Zubaydah was interviewed by FBI operative Ali Soufan. While he was recovering from life-threatening injuries incurred during his capture by Pakistani intelligence – he had been shot in the thigh, testicles, and stomach with an assault rifle – Soufan treated him well, building rapport and trust. This light-handed approach prompted Zubaydah to open up – he named Khalid Sheikh Mohammed as the “mastermind” of the 9/11 attacks, and described rumors of a “dirty bomb” plot being planned by a US citizen.
This information may not even have been accurate, however. The FBI’s top Al-Qaeda analyst, Dan Coleman, describes Zubaydah as a mere “safehouse keeper” with severe mental problems, who “claimed to know more about Al-Qaeda and its inner workings than he really did.” The torture he suffered no doubt played a pivotal role in prompting him to make such claims.Khalid Sheikh Mohammed was subsequently waterboarded 183 times, and admitted to all manner of grave crimes – including planning to blow up a building that didn’t even exist at the time of his capture.
In any event, Soufan was confident Zubaydah had no more secrets to tell, but the CIA claimed to be unconvinced – after all, Langley paid its Pakistani counterparts $10 million for him, and needed a greater return on that investment. When the torture finally stopped, with no further intelligence gathered, the agency was forced to conclude Soufan had been right all along.
As the Senate Select Committee report later found, the CIA still considered its tactics a success, to be “used as a template for future interrogation of high-value captives,” on the basis that such hideous treatment had “confirmed Zubaydah did not possess the intelligence” it erroneously assessed him to have.
That report is classified today, although Zabuydah’s name appears a total of 1,343 times in a publicly released executive summary and accompanying documents. It notes that the CIA frequently had trouble distinguishing “detainees who had information but were successfully resisting interrogation from those who did not actually have the information,” and at least 26 individuals had been wrongfully held by the agency.
This included an “intellectually challenged” man whose detention was used as leverage to force a family member to provide information, two former CIA sources, and two individuals whom the CIA had assessed to be connected to Al-Qaeda based solely on information fabricated by another detainee who’d been subjected to ‘enhanced interrogation’ techniques. Detainees often remained in custody at black sites for months after the agency determined there was no reason to keep them.
Other shocking excerpts reveal that a number of CIA personnel attached to the detention and interrogation program had on their personal files “notable derogatory information” that called into question “their eligibility for employment, their access to classified information, and their participation in CIA interrogation activities.” Among them were officers who, “among other issues, had engaged in inappropriate detainee interrogations, had workplace anger management issues, and had reportedly admitted to sexual assault.”
The agency seemed assured of its immunity from prosecution for its crimes, with several detainees having been informed they would never get out of CIA custody alive. One was told they’d be leaving only “in a coffin-shaped box,” while another was warned “we can never let the world know what I have done to you.” CIA officers also threatened several detainees with harm to their families should any details of their maltreatment be made public – this included telling one that their children’s lives would be at risk, a second that his mother would be sexually abused, and a third that his mother’s throat would be cut.
Since September 2006, Zubaydah has been held at Guantanamo Bay, despite the CIA having acknowledged that he wasn’t even a member of Al-Qaeda, let alone a significant figure within the group. The scars from his time in “black site” detention remain writ large today, with virtually perpetual headaches, an “excruciating sensitivity to sounds,” frequent seizures, and an inability to recall his own father’s name.
Still, the Supreme Court permitting him to make limited disclosures about his experiences is an encouraging sign that the invocation of “state secrecy privilege” to block disclosure of key evidence related to the CIA’s global post-9/11 torture program may no longer be a viable get-out for officials. This, in turn, raises the prospect that, at long last, someone might finally be held accountable for the gross human rights violations the agency and its assorted contractors inflicted on so many with such impunity for so long.
Kit Klarenberg is an investigative journalist exploring the role of intelligence services in shaping politics and perceptions.
October 18, 2021
Posted by aletho |
Deception, False Flag Terrorism, Subjugation - Torture | CIA, Human rights, United States |
Leave a comment
“It is now apparent that these products in the blood stream are toxic to humans. An immediate halt to the vaccination programme is required while an independent safety analysis is undertaken to investigate the full extent of the harms, which the UK Yellow Card data suggest includes thromboembolism, multi-system inflammatory disease, immune suppression, autoimmunity and anaphylaxis, as well as Antibody Dependent Enhancement (ADE).” Tess Lawrie, Evidence-Based Medicine Consultancy
“For we wrestle not against flesh and blood, but against the rulers of the darkness of this world, against spiritual wickedness in high places.” Ephesians 6:12
Question – Have the mRNA vaccines been tested on animals?
Answer – Yes, they have.
Question – Were the animal trials successful?
Answer – Yes and no.
Yes, the experiments on mice showed that a low dose of the vaccine induces a robust antibody response to the infection.
But, no, the antibodies were not able to attack the spike protein from a different strain of the virus.
Question – I’m not sure what that means? Do you mean that the vaccine DOES provide some limited protection from the original (Wuhan) virus, but does not necessarily provide protection from the variants?
Answer – That’s right, but it’s a bit more complicated than that because– as the virus changes — the antibodies that helped to fight the original virus can actually enhance the “infectivity” of the variant. In other words, vaccine-generated antibodies can switch-sides and increase the severity of the illness. Simply put, they can make you sicker or kill you. Scientists have known this for a long time. Check out this clip from a 2005 research paper:
“A jab against one strain might worsen infection with others….
In the.. study, Gary Nabel of the National Institute of Allergy and Infectious Diseases.. injected mice with spike protein from a SARS virus taken from a human patient infected in early 2003. They then collected the antibodies the animals produced.
In lab experiments, they showed that these antibodies were unable to attack spike protein from a different strain of SARS, isolated from a patient infected in late 2003…. The team next tested whether the antibodies would attack spike proteins from two SARS strains isolated from civets, from which the virus is thought to have originally jumped into humans. In this case, they found hints that the antibodies actually boosted the ability of the virus to infect cells. …
The results show that the virus changes over time, so that a strain that crops up in one outbreak might be quite different from that in a later outbreak. “This virus is not standing still and we need to take this into account,” Nabel says.
This raises the prospect that a vaccine against one strain of SARS virus could prove ineffective against others. Worse, a jab against one strain might even aggravate an infection with SARS virus from civets or another species. “It’s obviously a concern,” Nabel says..
This would not be the first case where exposure to one strain of a virus can worsen infection with another.” (“Caution raised over SARS vaccine”, Nature )
Question – I’m still confused. Can you summarize what they’re saying?
Answer – Sure. They’re saying that scientists have known for nearly two decades that vaccines narrowly aimed at just one protein are bound to fail. They’re saying that the spike protein is highly-adaptable and capable of changing its shape to survive. They’re saying that vaccines aimed at the spike protein will inevitably produce variants that evade vaccine-generated antibodies. They’re saying that by narrowing the vaccine’s focus to the spike protein alone, the drug companies have ensured that previously helpful antibodies will do an about-face, allow the virus to enter healthy cells, replicate at will, and cause sickness or death. They are saying that the current crop of vaccines is in fact perpetuating the pandemic. And–since the science has been clear for the last 16 years– we can add one more observation to the list, that is, that the current approach to mass vaccination is neither haphazard, slapdash or random. It is intentional. The vaccination campaign managers are deliberately ignoring the science in order to sustain a permanent state of crisis. Science is being manipulated to achieve a political objective.
Question – I think you’re exaggerating, but I’d like to get back to the animal trials instead of arguing politics. As you probably know, the reports in the media do not square with your analysis, in fact, all of the articles in the MSM say the animal trials were a rousing success. Here’s a short blurb that I found today that confirms what I’ve been saying:
“… vaccination of nonhuman primates with the mRNA vaccine induced robust SARS-CoV-2 neutralizing activity and notably, rapid protection in the upper and lower airways….” (Covid-19, NIH.gov)
Question – Are you suggesting the authors are lying?
Answer – No, they are not lying. They’re just not telling you the whole truth, and you need to know the whole truth so you can make an informed decision. The vaccines DO provide some (temporary) protection. We don’t dispute that. They also trigger a strong immune response. We don’t dispute that either. But what difference does it make? Let me explain: Let’s say, you have a really bad head cold so you take a new medication that you think will relieve the pain. And–sure enough– an hour after taking the pills– Presto — your congestion and headache are completely gone. That’s fantastic, right? Wrong, because what you fail to realize is that the medication is laced with slow-acting strychnine that kills you three days later. Do you still think it was a good idea to take the medication?
Of course, not. And the same rule applies to these vaccines which do, in fact, boost your antibodies and provide some fleeting “immunity”. But they can also kill you. Don’t you think that should be factored in to your decision? Keep in mind, people have died 3, 4, 5 weeks after inoculation without any prior warning. Many of them might have even been bursting with antibodies, but they’re still dead. Can you see the problem?
Question – Okay, but there’s still this matter about the animal trials. The media says that the drug companies performed the animal trials and they were successful. Do you disagree with that?
Answer – They were not successful and the “fact checkers” that were hired to discredit vaccine critics like me, have deliberately mischaracterized what happened in the trials. For example, here’s a typical “fact checker” article titled “COVID-19 vaccines did not skip animal trials because of animal deaths” by Reuters. Here’s an excerpt:
“Posts claiming that COVID-19 vaccine producers skipped animal trials due to the animals in those trials dying are false. Pfizer-BioNTech, Moderna and Johnson & Johnson, which have been granted emergency authorization use by the Food and Drug Administration (FDA) in the United States, all conducted animal trials and had no significant safety concerns to report.”
Sounds reassuring, right? But then they say:
“Due to time constraints and the urgency to find a vaccine for COVID-19, Moderna and Pfizer did receive approval to run animal testing and early trials on humans at the same time, as opposed to fully completing animal trials before moving on to human trials. This, however, does not mean animal trials were skipped or that the safety of the vaccines were compromised.”
Let me see if I got this straight: The drug companies were in such a hurry that they conducted their minimalist animal trials at the same time as their human trials (which is unprecedented) and then rushed the results to the FDA so they could be rubber stamped and waved through under the Emergency Use Authority?
Is that how it went down?
Yes, it is.
But if they were rushed through in a couple months, then the “fact checkers” are tacitly admitting that there is no long-term safety data. And there IS no long-term safety data, nor is there any attempt to disprove the research from the earlier trials where the ferrets, mice and other animals died following injection of mRNA vaccines. They don’t deny it, they just ignore it as if sweeping it under the rug will make it all go away. Here’s a clip from the research paper that Reuters refers to in its article:
“We demonstrate that the candidate vaccines… respectively—induce strong antigen-specific immune responses in mice and macaques….Both (vaccines) protected 2–4-year-old macaques from challenge with infectious SARS-CoV-2, and there was reduced detection of viral RNA in immunized macaques as compared to those that received saline.” (Note–We’ve already acknowledged that the vaccines do produce a strong immune response. Here’s more:)
“Neutralizing GMTs declined by day 56 (35 days after dose 2), consistent with the contraction phase; however, they remained well above the GMT of the human sera panel. The duration of the study was not long enough to assess the rate of decline during the plateau phase of the antibody response.” (“BNT162b vaccines protect rhesus macaques from SARS-CoV-2”, Nature )
Can you see what’s going on? The trial was only 56 days-long, in fact, none of the animal trials exceeded 56 days. Think about that for a minute. The reason the animals died in prior trials is because they were exposed to a mutated version of the (wild) virus that eventually killed them. That’s how ADE (antibody-dependent enhancement) works. It doesn’t happen overnight and it doesn’t happen in 56 days. It takes much longer than that for a mutated version of the virus to emerge and reinfect the host. The drug companies know that. They’re not stupid. So the fact that the animals mounted a strong immune response is completely irrelevant. We KNOW they mounted a strong immune response. We also know they died some months later when a different strain of the virus emerged. Bottom line: The production of antibodies does not mean a drug is safe.
The obvious purpose of the trials was to get the vaccines over the finish-line before anyone figured out what was going on. It’s the same reason why the drug companies “unblinded” their human trials after the vaccines got the green light from the FDA. Shortly after the trials were concluded, the people in the placebo arm were allowed to get vaccinated.
Why would they do that? Why would they vaccinate the people who willingly allowed themselves to be guinea pigs for the sake of public health, only to vaccinate them shortly after, thus, eliminating any chance of finding out what the long-term safety issues might be? It makes no sense, does it?
Take a look at this short clip from the British Medical Journal whose scientists are equally bewildered:
“The (drug) companies say they have an ethical obligation to unblind volunteers so they can receive the vaccine. But some experts are concerned about a “disastrous” loss of critical information if volunteers on a trial’s placebo arm are unblinded…
Although the FDA has granted the vaccines emergency use authorization, to get full license approval two years of follow-up data are needed. The data are now likely to be scanty and less reliable given that the trials are effectively being unblinded.
Consumer representative Sheldon Toubman, a lawyer and FDA advisory panel member, said that Pfizer and BioNTech had not proved that their vaccine prevents severe covid-19. “The FDA says all we can do is suggest protection from severe covid disease; we need to know that it does that,” he said.
He countered claims, based on experience with other vaccines, six weeks of follow-up was long enough to detect safety signals. Six weeks may not be long enough for this entirely new type of “untested” [mRNA] vaccine, Toubman said.
Goodman wants all companies to be held to the same standard and says they should not be allowed to make up their own rules about unblinding. He told The BMJ that, while he was “very optimistic” about the vaccines, “blowing up the trials” by allowing unblinding “will set a de facto standard for all vaccine trials to come.” And that, he said, “is dangerous.”
(“Covid-19: Should vaccine trials be unblinded?” The British Medical Journal )
Do you like his choice of words: “blowing up the trials”? Do you think it is a fair description of what the drug companies did?
Yes, it is.
And what possible motive would the drug companies have to blow up the trials? I can see only two possibilities:
- They think their vaccine is so terrific, it will save the lives of many of the people in the placebo group.
- They expect a high percentage of the people in the vaccine group to get either severely sick or die, so they want to hide the evidence of vaccine-linked injury.
Which is it?
You know the answer. Everyone watching this farce knows the answer.
Question – Okay, so let’s cut to the chase: Are the vaccines are safe or not?
No, they are not safe. The way we decide whether a drug is safe or not is by putting it through a rigorous process of testing and clinical trials. After the testing, the data is passed on to physicians, statisticians, chemists, pharmacologists, and other scientists who review the data and make their recommendations or criticisms. That didn’t happen with the Covid vaccines, in fact, all the normal standards and protocols were suspended in the name of “urgency”. But many believe that the “urgency” was manufactured to push through vaccines that would never have been approved on their own merits. All you have to do is look through the vaccine injury data (VAERS) and you’ll see this is the most lethal medical intervention of all time and, yet, the public health experts, the media and the government keep crowing that they’re “safe and effective”. It’s nonsense and the drug companies know it’s nonsense which is why they reject all liability for the people that are going to be killed by these “poison-death shots.”
Do you know what goes on inside your body after you are injected with one of these “gene based” vaccines?
Once the vaccine enters the bloodstream it penetrates the cells that line the blood vessels forcing them to produce spike proteins that protrude into the bloodstream like millions of microscopic thorns. These thorns activate blood platelets which trigger blood clotting followed shortly after by an immune response that destroys the infected cells thus weakening the vascular system while draining the supply of killer lymphocytes. In this way, the vaccine launches a dual attack on the body’s critical infrastructure causing widespread tissue damage throughout the circulatory system while leaving the immune system less able to fend off future infection.
Now if you think you can have a long-and-happy without a functioning circulatory system, then none of this matters. But if you’re bright enough to realize that wreaking havoc on your vascular system is the fast-track to the graveyard, then you’ll probably understand that injecting these “poison-death shots” is a particularly bad idea.
By the way, it’s a real stretch to call these hybrid injections, “vaccines”. They have about as much in common with a traditional vaccine as a python does with a coffee table. Nothing. The “vaccine” moniker was chosen in order to shore-up public confidence, that’s all. It’s part of a marketing strategy. There is no real similarity. The majority of people trust vaccines and see them as a shining example of medical achievement. The drug companies wanted to tap into that trust and use it for their own purposes. That’s why they called it a “vaccine” instead of “gene therapy” which more accurately describes ‘what it does.’ But–like we said– it’s just a marketing strategy.
Have you ever wondered how the drug companies were able to roll out their own-individual vaccines just weeks apart from each other? That’s a pretty good trick, don’t you think; especially since vaccine development typically takes from 10 to 15 years. How do you think they managed that? Here’s an excerpt from an article which provides a little background on the topic:
“The virus behind the outbreak that began in Wuhan, China, was identified on Jan. 7. Less than a week later — on Jan. 13 — researchers at Moderna and the NIH had a proposed sequence for an mRNA vaccine against it, and, as the company wrote in government documents, “we mobilized toward clinical manufacture.” By Feb. 24, the team was shipping vials from a plant in Norwood, Mass., to the National Institute of Allergy and Infectious Diseases, in Bethesda, Md., for a planned clinical trial to test its safety.” (“Researchers rush to test coronavirus vaccine in people without knowing how well it works in animals”, Stat )
Got that? “The virus broke out in Wuhan… on Jan. 7, and less than a week later Moderna had a proposed sequence for an mRNA vaccine against it???
Really? Is that the same Moderna that had been playing-around with mRNA for over a decade but was never able to successfully bring a vaccine to market?
Yep, the very same company. Here’s more:
“And by Feb. 24, the team was shipping vials from a plant in Norwood, Mass??”
Wow! Another Covid miracle! You almost get whiplash watching these companies crank out their “wonder drugs” at record-breaking speed.
Keep in mind, there’s a very high probability that the virus was man-made, (In other words, it’s a bioweapon.) and the people who have been implicated in the funding and creation of that bioweapon are also closely aligned with the big drug companies that have produced the antidote in record time that has already netted tens of billions of dollars in profits for a drug for which there was no reliable animal testing, no long-term safety data, and no formal regulatory approval.
So I’ll ask you again: Doesn’t that all sound a bit suspicious?
Is it really that hard to see the outline of a political agenda here? After all, aren’t the drug companies working with the regulatory agencies that are working with the public health officials that are working with the media that are working with the corrupted politicians that are working with the Intel agencies that are working with the meddling globalist billionaires that are working with the giant private equity firms that oversee the entire operation pulling the appropriate strings whenever needed?
It sure looks like it.
And, don’t the tectonic social changes we’ve seen in the last year have more to do with a broader scorched-earth campaign launched by the “parasite class” against the rest of humanity than they do with a fairly-mild virus that kills mainly old and frail people with multiple underlying health conditions?
Right, again. In fact, many have noticed the cracks in the pandemic artifice from the very beginning, just as many have pointed out that the virus-meme is just the mask behind which parasites continue to conduct their global restructuring project. In short, it’s all about politics; bare-knuckle, take-no-prisoners NWO politics.
Answer – You’ve asked a number of questions about the animal trials, but none about the biodistribution and the pharmacokinetics studies that were done at the same time. Why is that? (Note--Pharmacokinetics; “the branch of pharmacology concerned with the movement of drugs within the body.”)
Question– I didn’t know there were any. Did the media report on them?
Answer – No, they didn’t. They completely ignored them, even though they were produced by Pfizer and provide essential information about where the substance in the vaccine goes in the body, in what amounts, and for how long. By knowing how the drug is distributed, it is possible to make educated assumptions about its effect on the organs and other tissue. In other words, these studies are invaluable. The Doctors for Covid Ethics have done extensive research on the studies and written a report titled “The Pfizer mRNA vaccine: pharmacokinetics and toxicity”. Here’s a few excerpts that help to illustrate the dangers of the vaccines:
“As with any drug, a key consideration for the toxicity of the COVID mRNA vaccines is where exactly in the body they end up, and for how long they will stay there. Such questions, which are the subject of pharmacokinetics, are usually thoroughly investigated during drug development. Initial studies on pharmacokinetics and also on toxicity are carried out in animals… this document has rather far-reaching implications: it shows that Pfizer—as well as the authorities that were apprised of these data— must have recognized the grave risks of adverse events after vaccination even before the onset of clinical trials. Nevertheless, Pfizer’s own clinical trials failed to monitor any of the clinical risks that were clearly evident from these data, and the regulatory authorities failed to enforce proper standards of oversight. This dual failure has caused the most grievous harm to the public….
What do Pfizer’s animal data presage for biological effects in humans?
- Rapid appearance of spike protein in the circulation.
- Toxicity to organs with expected high rates of uptake, in particular placenta and
lactating breast glands
- Penetration of some organs might be higher with the real vaccine than with this
luciferase model… The rapid entry of the model vaccine into the circulation means that we must expect the spike protein to be expressed within the circulation, particularly by endothelial cells. ( Endothelial – The thin layer of cells lining the blood vessels) We have seen before that this will lead to activation of blood clotting through direct activation of platelets and also, probably more importantly, through immune attack on the endothelial cells…
Summary
Pfizer’s animal data clearly presaged the following risks and dangers:
- blood clotting shortly after vaccination, potentially leading to heart attacks, stroke, and venous thrombosis
- grave harm to female fertility
- grave harm to breastfed infants
- cumulative toxicity after multiple injections
With the exception of female fertility, which can simply not be evaluated within the short period of time for which the vaccines have been in use, all of the above risks have been substantiated since the vaccines have been rolled out—all are manifest in the reports to the various adverse event registries. Those registries also contain a very considerable number of reports on abortions and stillbirths shortly after vaccination, which should have prompted urgent investigation. […]
Of particularly grave concern is the very slow elimination of the toxic cationic lipids. In persons repeatedly injected with mRNA vaccines containing these lipids… this would result in cumulative toxicity. There is a real possibility that cationic lipids will accumulate in the ovaries. The implied grave risk to female fertility demands the most urgent attention of the public and of the health authorities.
Since the so-called clinical trials were carried out with such negligence, the real trials are occurring only now—on a massive scale, and with devastating results. … Calling off this failed experiment is long overdue. Continuing or even mandating the use of this poisonous vaccine, and the apparently imminent issuance of full approval for it are crimes against humanity.” (“The Pfizer mRNA vaccine: pharmacokinetics and toxicity”, Doctors for Covid Ethics )
Don’t you think people are entitled to know what the government wants to inject into their bodies? Don’t you think they have a right to know how it will effect their immune systems, their vital organs and their overall health? Don’t you think they have the right to decide for themselves which drugs they will take and which they will refuse to take?
Forcing someone to take a drug he does not want, is not just wrong. It’s un-American. Which is why people should reject vaccine mandates as a matter of principle. They are an attack on personal liberty, the foundation of our constitutional system. It’s a principle worth dying for.
As for the mass vaccination campaign, it is the most maniacally-genocidal project ever concocted by man. There’s simply no way to calculate the amount of suffering and death we are about to face for trusting people whose policies were obviously shaped by their undiluted hatred of humanity. As German microbiologist Dr. Sucharit Bhakdi said:
“In the end, we’re going to see mass illness and deaths among people who normally would have had wonderful lives ahead of them.”
It is a great tragedy.
October 18, 2021
Posted by aletho |
Civil Liberties, Deception, Science and Pseudo-Science, Timeless or most popular, War Crimes | COVID-19 Vaccine, Human rights, Moderna |
Leave a comment
As children across the country are forced to cover their faces for hours at a time to attend school, President Joe Biden and First Lady Jill were caught on camera flouting DC’s mask mandates at an upscale Georgetown restaurant, Fiola Mare (whose mask policy they were also violating).

In a video posted Sunday night, the Bidens can be seen leaving the restaurant as employees in the background are dutifully masked up – a ‘fuck you, plebs’ not seen since the Met Gala event last month.
Wearing masks indoors was made mandatory in DC after Democratic Mayor Muriel Bowser reinstated the policy in July after the delta variant began to surge.
“Per CDC guidance and DC Mayor Muriel Bowser’s executive order, all individuals over age 2 are required to wear a mask indoors, regardless of vaccination status. Masks must be always worn while in our restaurants, except while eating and drinking. Thank you for understanding,” reads Fiola Mare’s website.
Meanwhile…

Full article
October 18, 2021
Posted by aletho |
Civil Liberties, Progressive Hypocrite, Supremacism, Social Darwinism | Covid-19, Human rights, United States |
Leave a comment
When a population is placed in a state of sufficiently grave fear and anger regarding a perceived threat, concerns about the constitutionality, legality and morality of measures adopted in the name of punishing the enemy typically disappear. The first priority, indeed the sole priority, is to crush the threat. Questions about the legality of actions ostensibly undertaken against the guilty parties are brushed aside as trivial annoyances at best, or, worse, castigated as efforts to sympathize with and protect those responsible for the danger. When a population is subsumed with pulsating fear and rage, there is little patience for seemingly abstract quibbles about legality or ethics. The craving for punishment, for vengeance, for protection, is visceral and thus easily drowns out cerebral or rational impediments to satiating those primal impulses.
The aftermath of the 9/11 attack provided a vivid illustration of that dynamic. The consensus view, which formed immediately, was that anything and everything possible should be done to crush the terrorists who — directly or indirectly — were responsible for that traumatic attack. The few dissenters who attempted to raise doubts about the legality or morality of proposed responses were easily dismissed and marginalized, when not ignored entirely. Typically, they were vilified with the accusation that their constitutional and legal objections were frauds: mere pretexts to conceal their sympathy and even support for the terrorists. It took at least a year or two after that attack for there to be any space for questions about the legality, constitutionality, and morality of the U.S. response to 9/11 to be entertained at all.
For many liberals and Democrats in the U.S., 1/6 is the equivalent of 9/11. One need not speculate about that. Many have said this explicitly. Some prominent Democrats in politics and media have even insisted that 1/6 was worse than 9/11.
Joe Biden’s speechwriters, when preparing his script for his April address to the Joint Session of Congress, called the three-hour riot “the worst attack on our democracy since the Civil War.” Liberal icon Rep. Liz Cheney (R-WY), whose father’s legacy was cemented by years of casting 9/11 as the most barbaric attack ever seen, now serves as Vice Chair of the 1/6 Committee; in that role, she proclaimed that the forces behind 1/6 represent “a threat America has never seen before.” The enabling resolution that created the Select Committee calls 1/6 “one of the darkest days of our democracy.” USA Today’s editor David Mastio published an op-ed whose sole point was a defense of the hysterical thesis from MSNBC analysts that 1/6 is at least as bad as 9/11 if not worse. S.V. Date, the White House correspondent for America’s most nakedly partisan “news” outlet, The Huffington Post, published a series of tweets arguing that 1/6 was worse than 9/11 and that those behind it are more dangerous than Osama bin Laden and Al Qaeda ever were.
And ever since the pro-Trump crowd was dispersed at the Capitol after a few hours of protests and riots, the same repressive climate that arose after 9/11 has prevailed. Mainstream political and media sectors instantly consecrated the narrative, fully endorsed by the U.S. security state, that the United States was attacked on 1/6 by domestic terrorists bent on insurrection and a coup. They also claimed in unison that the ideology driving those right-wing domestic terrorists now poses the single most dangerous threat to the American homeland, a claim which the intelligence community was making even before 1/6 to argue for a new War on Terror (just as neocons wanted to invade and engineer regime change in Iraq prior to 9/11 and then exploited 9/11 to achieve that long-held goal).
With those extremist and alarming premises fully implanted, there has been little tolerance for questions about whether proposed responses for dealing with the 1/6 “domestic terrorists” and their incomparably dangerous ideology are excessive, illegal, unethical, or unconstitutional. Even before Joe Biden was inaugurated, his senior advisers made clear that one of their top priorities was to enact a bill from Rep. Adam Schiff (D-CA) — now a member of the Select Committee on 1/6 — to import the first War on Terror onto domestic soil. Even without enactment of a new law, there is no doubt that a second War on Terror, this one domestic, has begun and is growing, all in the name of the 1/6 “Insurrection” and with little dissent or even public debate.
Following the post-9/11 script, anyone voicing such concerns about responses to 1/6 is reflexively accused of minimizing the gravity of the Capitol riot and, worse, of harboring sympathy for the plotters and their insurrectionary cause. Questions or doubts about the proportionality or legality of government actions in the name of 1/6 are depicted as insincere, proof that those voicing such doubts are acting not in defense of constitutional or legal principles but out of clandestine camaraderie with the right-wing domestic terrorists and their evil cause.
When it comes to 1/6 and those who were at the Capitol, there is no middle ground. That playbook is not new. “Either you are with us, or you are with the terrorists” was the rigidly binary choice which President George W. Bush presented to Americans and the world when addressing Congress shortly after the 9/11 attack. With that framework in place, anything short of unquestioning support for the Bush/Cheney administration and all of its policies was, by definition, tantamount to providing aid and comfort to the terrorists and their allies. There was no middle ground, no third option, no such thing as ambivalence or reluctance: all of that uncertainty or doubt, insisted the new war president, was to be understood as standing with the terrorists.
The coercive and dissent-squashing power of that binary equation has proven irresistible ever since, spanning myriad political positions and cultural issues. Dr. Ibram X. Kendi’s insistence that one either fully embrace what he regards as the program of “anti-racism” or be guilty by definition of supporting racism — that there is no middle ground, no space for neutrality, no room for ambivalence about any of the dogmatic planks — perfectly tracks this manipulative formula. As Dr. Kendi described the binary he seeks to impose: “what I’m trying to do with my work is to really get Americans to eliminate the concept of ‘not racist’ from their vocabulary, and realize we’re either being racist or anti-racist.” Eight months after the 1/6 riot — despite the fact that the only people who died that day were Trump supporters and not anyone they killed — that same binary framework shapes our discourse, with a clear message delivered by those purporting to crush an insurrection and confront domestic terrorism. You’re either with us, or with the 1/6 terrorists.
What makes this ongoing prohibition of dissent or even doubt so remarkable is that so many of the responses to 1/6 are precisely the legal and judicial policies that liberals have spent decades denouncing. Indeed, many of the defining post-1/6 policies are identical to those now retrospectively viewed as abusive and excessive, if not unconstitutional, when invoked as part of the first War on Terror. We are thus confronted with the surreal dynamic that policies long castigated in American liberalism — whether used generally in the criminal justice system or specifically in the name of avenging 9/11 and defeating Islamic extremism — are now off-limits from scrutiny or critique when employed in the name of avenging 1/6 and crushing the dangerous domestic ideology that fostered it.
Almost immediately after the Capitol riot, some of the most influential Democratic lawmakers — Senate Majority Leader Chuck Schumer (D-NY) and House Homeland Security Committee Chair Bennie Thompson (D-MS), who also now chairs the Select 1/6 Committee — demanded that any participants in the protest be placed on the no-fly list, long regarded as one of the most extreme civil liberties assaults from the first War on Terror. And at least some of the 1/6 protesters have been placed on that list: American citizens, convicted of no crime, prohibited from boarding commercial airplanes based on a vague and unproven assessment, from unseen and unaccountable security state bureaucrats, that they are too dangerous to fly. I reported extensively on the horrors and abuses of the no-fly list as part of the first War on Terror and do not recall a single liberal speaking in defense of that tactic. Yet now that this same brute instrument is being used against Trump supporters, there has not, to my knowledge, been a single prominent liberal raising objections to the resurrection of the no-fly list for American citizens who have been convicted of no crime.
Axios, Jan. 12, 2021
With more than 600 people now charged in connection with the events of 1/6, not one person has been charged with conspiracy to overthrow the government, incite insurrection, conspiracy to commit murder or kidnapping of public officials, or any of the other fantastical claims that rained down on them from media narratives. No one has been charged with treason or sedition. Perhaps that is because, as Reuters reported in August, “the FBI has found scant evidence that the Jan. 6 attack on the U.S. Capitol was the result of an organized plot to overturn the presidential election result.” Yet these defendants are being treated as if they were guilty of these grave crimes of which nobody has been formally accused, with the exact type of prosecutorial and judicial overreach that criminal defense lawyers and justice reform advocates have long railed against.
Dozens of the 1/6 defendants have been denied bail, thus being imprisoned for months without having been found guilty of anything. Many are being held in unusually harsh and bizarrely cruel conditions, causing a federal judge on Wednesday to hold “the warden of the D.C. jail and director of the D.C. Department of Corrections in contempt of court,” and then calling on the Justice Department “to investigate whether the jail is violating the civil rights of dozens of detained Jan. 6 defendants.” Some of the pre-trial prison protocols have been so punitive that even Sen. Elizabeth Warren (D-MA) — who calls the 1/6 protesters “domestic terrorists” — denounced their treatment as abusive: “Solitary confinement is a form of punishment that is cruel and psychologically damaging,” Warren said, adding: “And we’re talking about people who haven’t been convicted of anything yet.” Warren also said she is “worried that law enforcement officials are deploying it to ‘punish’ the Jan. 6 defendants or to ‘break them so that they will cooperate.”
The few 1/6 defendants who have thus far been sentenced after pleading guilty have been subjected to exceptionally punitive sentences, the kind liberal criminal justice reform advocates have been rightly denouncing for years. Several convicted of nothing more than trivial misdemeanors are being sentenced to real prison time; last week, Michigan’s Robert Reeder pled guilty to “one count of parading, demonstrating or picketing in a Capitol building” yet received a jail term of 3 months, with the judge admitting that the motive was to “send a signal to the other participants in that riot… that they can expect to receive jail time.”
Meanwhile, long-controversial SWAT teams are being routinely deployed to arrest 1/6 suspects in their homes, and long-time liberal activists denouncing these tactics have suddenly decided they are appropriate for these Trump supporters. That prosecutors are notoriously overzealous in their demands for harsh prison time is a staple of liberal discourse, but now, an Obama-appointed judge has repeatedly doled out sentences to 1/6 defendants that are harsher and longer than those requested by DOJ prosecutors, to the applause of liberals. In sum, these defendants are subjected to one of the grossest violations of due process: they are being treated as if they are guilty of crimes — treason, sedition, insurrection, attempted murder, and kidnapping — which not even the DOJ has accused them of committing. And the fundamental precept of any healthy justice system — namely, punishment for citizens is merited only once they have been found guilty of crimes in a court of law — has been completely discarded.
Serious questions about FBI involvement in the 1/6 events linger. For months, Americans were subjected to a frightening media narrative that far-right groups had plotted to kidnap Michigan Gov. Gretchen Whitmer, only for proof to emerge that at least half of the conspirators, including its leaders, were working for or at the behest of the FBI. Regarding 1/6, the evidence has been clear for months, though largely confined to right-wing outlets, that the FBI had its tentacles in the three groups it claims were most responsible for the 1/6 protest: the Proud Boys, Oath Keepers, and the Three Percenters. Yet last month, The New York Times acknowledged that the FBI was directly communicating with one of its informants present at the Capitol, a member of the Proud Boys, while the riot unfolded, meaning “federal law enforcement had a far greater visibility into the assault on the Capitol, even as it was taking place, than was previously known.” All of this suggests that to the extent 1/6 had any advanced centralized planning, it was far closer to an FBI-induced plot than a centrally organized right-wing insurrection.
Despite this mountain of abuses, it is exceedingly rare to find anyone outside of conservative media and MAGA politics raising objections to any of this (which is what made Sen. Warren’s denunciation of their pre-trial prison conditions so notable). The reason is obvious: just as was true in the aftermath of 9/11, people are petrified to express any dissent or even question what is being done to the alleged domestic terrorists for fear of standing accused of sympathizing with them and their ideology, an accusation that can be career-ending for many.
Many of the 1/6 defendants are impoverished and cannot afford lawyers, yet private-sector law firms who have active pro bono programs will not touch anyone or anything having to do with 1/6, while the ACLU is now little more than an arm of the Democratic Party and thus displays almost no interest in these systemic civil liberties assaults. And for many liberals — the ones who are barely able to contain their glee at watching people lose their jobs in the middle of a pandemic due to vaccine-hesitancy or who do not hide their joy that the unarmed Ashli Babbitt got what she deserved — their political adversaries these days are not just political adversaries but criminals and even terrorists, rendering no punishment too harsh or severe. For them, cruelty is not just acceptable; the cruelty is the point.
The Unconstitutionality of the 1/6 Committee
Civil liberties abuses of this type are common when the U.S. security state scares enough people into believing that the threat they face is so acute that normal constitutional safeguards must be disregarded. What is most definitely not common, and is arguably the greatest 1/6-related civil liberties abuse of them all, is the House of Representatives Select Committee to Investigate the January 6th Attack on the United States Capitol.
To say that the investigative acts of the 1/6 Committee are radical is a wild understatement. Along with serving subpoenas on four former Trump officials, they have also served subpoenas on eleven private citizens: people selected for interrogation precisely because they exercised their Constitutional right of free assembly by applying for and receiving a permit to hold a protest on January 6 opposing certification of the 2020 election.
When the Select 1/6 Committee recently boasted of these subpoenas in its press release, it made clear what methodology it used for selecting who it was targeting: “The committee used permit paperwork for the Jan. 6 rally to identify other individuals involved in organizing.” In other words, any citizen whose name appeared on permit applications to protest was targeted for that reason alone. The committee’s stated goal is “to collect information from them and their associated entities on the planning, organization, and funding of those events”: to haul citizens before Congress to interrogate them on their constitutionally protected right to assemble and protest and probe their political beliefs and associations:


List of 11 private citizens who received subpoenas from the 1/6 Congressional Committee for deposition testimony and records
Even worse are the so-called “preservation notices” which the committee secretly issued to dozens if not hundreds of telecoms, email and cell phone providers, and other social media platforms (including Twitter and Parler), ordering those companies to retain extremely invasive data regarding the communications and physical activities of more than 100 citizens, with the obvious intent to allow the committee to subpoena those documents. The communications and physical movement data sought by the committee begins in April, 2020 — nine months before the 1/6 riot. The committee refuses to make public the list of individuals it is targeting with these sweeping third-party subpoenas, but on the list are what CNN calls “many members of Congress,” along with dozens of private citizens involved in obtaining the permit to protest and then promoting and planning the gathering on social media.
What makes these secret notices especially pernicious is that the committee requested that these companies not notify their customers that the committee has demanded the preservation of their data. The committee knows it lacks the power to impose a “gag order” on these companies to prevent them from notifying their users that they received the precursor to a subpoena: a power the FBI in conjunction with courts does have. So they are relying instead on “voluntary compliance” with the gag order request, accompanied by the thuggish threat that any companies refusing to voluntarily comply risk the public relations harm of appearing to be obstructing the committee’s investigation and, worse, protecting the 1/6 “insurrectionists.”
Worse still, the committee in its preservation notices to these communications companies requested that “you do not disable, suspend, lock, cancel, or interrupt service to these subscribers or accounts solely due to this request,” and that they should first contact the committee “if you are not able or willing to respond to this request without alerting the subscribers.” The motive here is obvious: if any of these companies risk the PR hit by refusing to conceal from their customers the fact that Congress is seeking to obtain their private data, they are instructed to contact the committee instead, so that the committee can withdraw the request. That way, none of the customers will ever be aware that the committee targeted their private data and will thus never be able to challenge the legality of the committee’s acts in a court of law.
In other words, even the committee knows that its power to seek this information about private citizens lacks any convincing legal justification and, for that reason, wants to ensure that nobody has the ability to seek a judicial ruling on the legality of their actions. All of these behaviors raise serious civil liberties concerns, so much so that even left-liberal legal scholars and at least one civil liberties group (obviously not the ACLU) — petrified until now of creating any appearance that they are defending 1/6 protesters by objecting to civil liberties abuses — have begun very delicately to raise doubts and concerns about the committee’s actions.
But the most serious constitutional problem is not the specific investigative acts of the committee but the very existence of the committee itself. There is ample reason to doubt the constitutionality of this committee’s existence.
When crimes are committed in the United States, there are two branches of government — and only two — vested by the Constitution with the power to investigate criminal suspects and adjudicate guilt: the executive branch (through the FBI and DOJ) and the judiciary. Congress has no role to play in any of that, and for good and important reasons. The Constitution places limits on what the executive branch and judiciary can do when investigating suspects . . . . .
Full Article $
October 17, 2021
Posted by aletho |
Civil Liberties, Progressive Hypocrite | FBI, Human rights, United States |
Leave a comment

 Aletho News

