Biden administration sought control over TikTok
RT | August 26, 2023
The Biden administration sought to gain control over nearly every aspect of the inner workings of social media behemoth TikTok as part of negotiations allowing its continued operation in the US, according to a draft agreement obtained by Forbes last week.
The agreement, which runs to nearly 100 pages, would reportedly give the White House a level of control over the Chinese-owned platform even greater than that which it was found last year to be exercising over US-based competitors like Facebook and Twitter, allowing government officials to not only monitor and influence the conversation on the platform but also to interfere in the day-to-day operations of TikTok in the US.
Government agencies like the Department of Justice and Department of Defense would have full authority to examine TikTok’s servers, equipment, records, facilities, and other properties, according to the draft. They could also block changes to the app’s US terms of service, privacy policy, and moderation policies and veto the hiring of any individual involved in data security for the US.
The agreement would also force TikTok and its parent company ByteDance to submit to outside audits, assessments, code inspections, and cybersecurity checks by supposedly independent entities chosen by the US government. The company would be required to foot the bill for these intrusions.
The platform’s US staff could even have been required to exclude ByteDance’s executives from security-related decisions, instead deferring to an executive security committee whose actions would also be concealed from ByteDance. This committee’s primary responsibility would be maintaining US national security first and TikTok’s profitability second.
The draft seen by Forbes, dated last summer, is the product of months of exchanges between ByteDance and the Committee on Foreign Investment in the United States (CFIUS), which oversees foreign involvement in business deals that could potentially impact national security and has been investigating ByteDance for four years.
TikTok has repeatedly been threatened with a blanket ban or forced sale of its US assets to an American competitor as both President Joe Biden and his predecessor Donald Trump claimed the platform is used by Beijing for information warfare.
CFIUS renewed the call for a ban or sale in March after the DOJ launched an investigation into ByteDance employees using TikTok to spy on American journalists. A spokesperson for ByteDance confirmed the surveillance but attributed it to rogue employees who have since been fired.
TikTok has over 150 million American users spending 90 minutes or more on the platform. While the company pledged in 2021 to isolate US user data on servers owned by tech giant Oracle to assuage spying concerns, Biden prohibited its use by federal employees in December and dozens of state and city governments have followed suit.
California Church Fined For Defying Covid Lockdowns Sues County For Tracking Worshipers Without Their Knowledge
By Cindy Harper | Reclaim The Net | August 26, 2023
A church in California punished during Covid lockdowns with a fine of $1.2 million is now suing over geofencing-based surveillance of its members.
The church, Calvary Chapel San Jose, along with Pastor Mike McClure, allege in the federal lawsuit filed this week that Santa Clara County engaged in warrantless and invasive surveillance, using the geofencing method and thus abusing location data harvested from the worshipers’ phones.
The filing is based on claims that both First Amendment related to free speech, and the Fourth Amendment, meant to protect against unlawful searches, were violated by the county as it resorted to spying via geofencing.
We obtained a copy of the complaint for you here.
Advocates for Faith & Freedom, a group that filed the lawsuit, specified that the county turned to SafeGraph data company in order to carry out this activity, and accuses the officials behind the scheme as engaging in tracking of residents not only without appropriate warrants and in an invasive manner, but also keeping this activity a secret from the public.
“This type of expansive geofencing operation is not only an invasion of privacy but represents a terrifying precedent if allowed to go unaddressed,” the complaint states. “As it stands, Defendants assert that, as long as they call it research, any level of government can target and spy on any individual or group at any time for any duration.”
It is further alleged that the operation lasted more than a year, “with seemingly no oversight, boundaries, or limitations.” The implication of this is that those targeted by this controversial, dragnet-style surveillance weren’t safe from it anywhere – be it the prayer room or the bathroom.
Those behind the lawsuit also reject the arguments that the defendants have apparently chosen to go with, namely, that the whole operation was done for the sake of “research,” and is therefore justified.
But, argues Advocates for Faith & Freedom, accepting such logic would mean that there would be no real limits to how government entities at any level could use geofencing to track either groups or individuals. This lack of boundaries means that the spying could go on against anyone and for any amount of time – and potentially be used against opponents.
“This is not just un-American; it is downright Orwellian,” stated Advocates for Faith & Freedom.
Santa Clara County, meanwhile, had nothing to add to its previous comments on the matter, well before the lawsuit was filed. Back in March, the county reacted to a report about tracking of worshipers written by journalist David Zweig.
The Royal Society Lockdown Report Authors Understand That by Ignoring the High Quality Evidence they Reach the Politically Acceptable Conclusion
BY DR CARL HENEGHAN AND DR TOM JEFFERSON | THE DAILY SCEPTIC | AUGUST 25, 2023
This week saw the publication of a suite of systematic reviews by the Royal Society (RS) on the effect of non-pharmaceutical interventions in the pandemic.
Politico headlined with ‘Top review says Covid lockdowns and masks worked, period’. The Guardian led with ‘Lockdowns and face masks “unequivocally” cut the spread of Covid, report finds’, and the i newspaper stated: ‘Masks and social distancing did reduce Covid infections, new report shows, proving lockdown sceptics wrong.’
So there you have it, a slam dunk, sceptics, you were all wrong. You should have masked up and stayed in lockdown.
Even more so when you listen to the Chair of the report’s group, Mark Walport, who said: “There is sufficient evidence to conclude that early, stringent implementation of packages of complementary NPIs was unequivocally effective in limiting SARS-CoV-2 infections.”
Four systematic reviews informed the effectiveness of non-pharmaceutical interventions in the Covid pandemic. However, here is some of what these reviews report.
A systematic review on environmental control measures:
Many of these studies were assessed to have critical risk of bias in at least one domain, largely due to confounding factors that could have affected the measured outcomes. As a result, there is low confidence in the findings.
One study, an RCT, showed that daily testing of contacts could be a viable strategy to replace lengthy quarantine of contacts. Based on the scarcity of robust empirical evidence, we were not able to draw any firm quantitative conclusions about the quantitative impact of TTI interventions in different epidemic contexts.
Effectiveness of face masks for reducing transmission of SARS-CoV-2:
We analysed 35 studies in community settings (three RCTs and 32 observational) and 40 in healthcare settings (one RCT and 39 observational). Ninety-one percent of observational studies were at ‘critical’ risk of bias (ROB) in at least one domain, often failing to separate the effects of masks from concurrent interventions.
Effectiveness of international border control measures during the COVID-19 pandemic:
There is little evidence that most travel restrictions, including border closure and those implemented to stop the introduction of new variants of concern, were particularly effective.
The report makes the same errors that the UKHSA and Public Health England did. They ignored the critical biases and the confounders when drawing conclusions. Some of the comments misunderstand the evidence required for making healthcare decisions.
Chris Dye, Professor of Epidemiology at the University of Oxford, who led the review on masks for the Royal Society, said if they had only looked at randomised controlled trials, they would have come to the same conclusion as the Cochrane review. However, the researchers behind the paper released Thursday chose to analyse a larger body of studies and found strong evidence that masks work.
So, if we ignore high-quality evidence, we arrive at the conclusion we want – they fully understand the politics. Low-quality evidence means the estimated effect will differ substantially from the actual effect – we’ve known this for quite some time, and it is fundamental to the delivery of evidence-based interventions. An approach that uses low-quality evidence shouldn’t inform healthcare, and it doesn’t. That’s why we have NICE, which uses the best available evidence to develop recommendations that guide health, public health and social care decisions.
Did the reviewers, for instance, ask if there was a protocol for any of these studies – something we have previously pointed out. There were none, despite protocols being essential for robust research.
There is something we do agree with in the report, that the “future assessments should also consider the costs as well as the benefits of NPIs, in terms of their impacts on livelihoods, economies, education, social cohesion, physical and mental wellbeing, and potentially other aspects”. However this report looked at none of that. The single focus on one outcome, ignoring harms, further hinders informed decision-making.
The RS report wants us to believe that RCTs are impossible during a pandemic: “While RCTs should not be discounted, it is highly likely that most information in a future pandemic will continue to be observational.”
Yet the pandemic has re-emphasised the importance of high-quality randomised clinical trials and highlighted the need for preparation, coordination and collaboration.
The Royal Society review shows that some academics are losing their ability to think critically. Instead of retrofitting evidence to preconceived conclusions, it would be much better to report the uncertainties and set out those questions that need addressing. Refusal to acknowledge uncertainties does a disservice to society and undermines public trust in research.
Staying at home decreases your risk of all sorts of hazards – in the short term, you won’t get run over and you’ll reduce the risk of an infection or an accident. But what matters is the costs of what happens when you reemerge.
CDC Now Refusing New COVID Vaccine Adverse Event Reports in Its V-Safe Program
By David Gortler | Brownstone Institute | August 24, 2023
The Centers for Disease Control and Prevention (CDC) V-safe website quietly stopped collecting adverse event reports with no reason or explanation. The V-safe website simply states: “Thank you for your participation. Data collection for COVID-19 vaccines concluded on June 30, 2023.” If you go there today, V-safe directs users to the FDA’s VAERS website for adverse event reporting, even though officials continually derided VAERS as “passive” and “unverified.”

VAERS and V-safe are mutually exclusive safety collection databases operated by the FDA and CDC, respectively. VAERS is an older way of collecting safety data where one can fill out a form online, or manually, or by calling a toll-free number, whereas V-safe is a device “app” which requires online registration. Both VAERS and V-safe collect personal information, lot numbers, dates and associated information, but V-safe was an active collection system geared towards a younger app-using demographic.
Does this mean that the CDC believes that the mRNA Covid-19 injections are so safe, there is no need to monitor adverse event reports any longer? What is the argument against continued monitoring, especially since the V-safe website was already up and paid for?
While CDC’s V-safe was stealthily and abruptly turned off, refusing to accept new safety reports, to this very day the CDC continues to urge everyone ages 6 months and older to stay up to date with COVID-19 vaccines and boosters.
As a drug safety expert, I personally can’t cite another example of any agency or manufacturer halting collection of safety data. It seems even worse because mRNA technology is relatively new with long-term manifestations unknown. On top of this, both manufacturers and the FDA refuse to share the list of ingredients, such as lipid nanoparticles, which could affect individuals differently and take a long time to manifest clinically.
Safety Data Collection Should Never Stop:
Now, contrast that with the fact that the National Highway Traffic and Safety Administration (NHTSA) will still accept a safety report for a 30-year-old Ford Bronco II. Indeed, this is an oddly specific example, but only because I drove this exact vehicle as a family hand-me-down as a student, through my residency, fellowship, for my tenure as a Yale professor on the mean streets of New Haven and even during my years at the FDA as a medical officer /senior medical analyst.
Like mRNA shots, Bronco IIs are still available on the market and people are still using them up to this very day. My Bronco became an intermittent topic of conversation with friends and FDA colleagues. One day, I was informed by a patrolling security guard at the FDA that it was the oldest car on campus.
I didn’t know much about cars (or mRNA technology) back then, but when a fellow FDA-er informed me that my Bronco II had noteworthy safety problems and that the NHTSA still had their eye on this vehicle (rollover accidents were more common and more fatal) I addressed the problem: I got rid of the reliable relic, even though I really liked it. NHTSA Is still accepting safety reports three decades later.
CDC No longer accepting safety reports despite rapidly increasing safety findings:
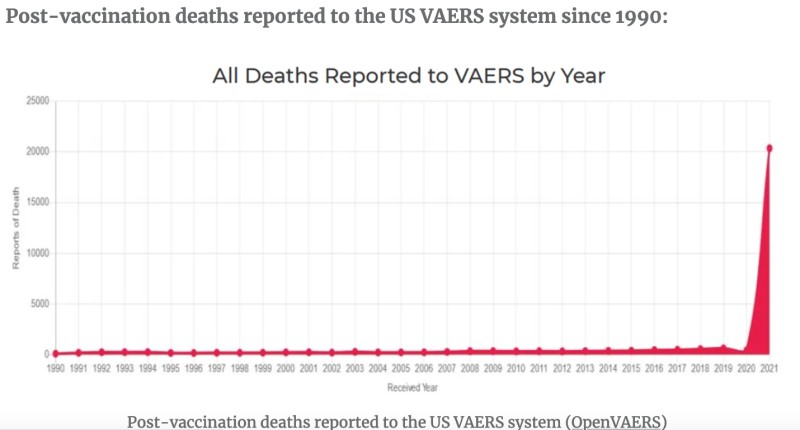
Unlike my old Bronco, mRNA injections have only been on the market for about two years, and according to the FDA Vaccine Adverse Event Reporting System (VAERS) database, mRNA “vaccines” have been named the primary suspect in over 1.5 million adverse event reports, of which there are >20,000 heart attacks and >27,000 cases of myocarditis and pericarditis just in the USA alone. Worldwide numbers would be greater. According to many references, including an FDA-funded study out of Harvard, VAERS reports represent fewer than 1 percent of vaccine adverse events that actually occur.
Interestingly, the NHTSA link above on my Ford Bronco II only shows: one parts recall, one investigation and 23 complaints, and still features a button in the upper right hand corner for submitting new complaints.
Wikipedia defines an humanitarian crisis or humanitarian disaster as a: “singular event or a series of events that are threatening in terms of health, safety or well-being of a community or large group of people.” Based on VAERS and previous V-safe findings, adverse events from mRNA shots in the USA alone could be considered a humanitarian crisis.
Despite those alarming clinical findings, the CDC has concluded that collecting new safety reports is somehow no longer in the interest of America’s public health. Existing data from the V-safe site showed around 6.5 million adverse events/health impacts out of 10.1 million users, with around 2 million of those people unable to conduct normal activities of daily living or needing medical care, according to a third-party rendering of its findings. In other words, despite mRNA shots still being widely available and the CDC promoting its continued use, it’s “case closed” with regards to collecting new safety reports, under today’s federal public health administration.
Will the CDC opine on the existing data or justify its halting of collecting new safety data? To the best of my knowledge, stopping the collection of public health information doesn’t have a clinical justification or scientific precedence — especially when it comes to an actively marketed product.
In George Orwell’s 1984, characters were told by The Party to “reject the evidence of your eyes and [your] ears.” Now, the CDC isn’t even allowing that evidence to be collected for viewing (and prospective rejecting). It’s a terrible idea for any product, let alone novel mRNA technologies.
Dr. David Gortler, a 2023 Brownstone Fellow, is a pharmacologist, pharmacist, research scientist and a former member of the FDA Senior Executive Leadership Team who served as senior advisor to the FDA Commissioner on matters of: FDA regulatory affairs, drug safety and FDA science policy. He is a former Yale University and Georgetown University didactic professor of pharmacology and biotechnology, with over a decade of academic pedagogy and bench research, as part of his nearly two decades of experience in drug development. He also serves as a scholar at the Ethics and Public Policy Center.
Passing the Talmud Torch: New CDC Director
By Karl Haemers | Taboo Truth | August 21, 2023
The previous Director of the Centers for Disease Control and Prevention, Rochelle Walensky, submitted a letter of resignation to the Biden administration on May 5. On June 16, the Biden White House announced its “Intent to Appoint Dr. Mandy Cohen as Director of the Centers for Disease Control and Prevention.” Walensky’s term officially ended on June 30. At this moment of writing, the date is August 20. Mandy Cohen has been the official Director of the CDC for seven weeks.

Out With the Old Boss
Walensky’s term from January 2021 to the end of June 2023 was a period of devastating ineptitude combined with profiteering and reckless power projection by herself and the agency she led. This was the period of the vaccine roll-out, and Walensky pushed vaccines as the only treatment for an over-hyped threat of a SARS-CoV-2 virus. AP said Walensky “was brought in to raise morale at the CDC, to rebuild public trust in the agency and to improve its sometimes-bumbling response to the pandemic.”
Instead Walensky claimed vaccination was necessary for everyone to prevent the spread, then later after the virus panic was diminished, the CDC declared that the vaccines never had the ability to prevent spread, only reduce symptoms. Walensky declared that it was “urgent” for pregnant “persons” (she would not say “mothers” or “women”) to get the vaccine to protect their babies and themselves. A careful reading of the CDC study Walensky referenced as a source for her recommendation stated no such thing, but declared that some safety concerns had arisen for pregnant “people” including over 20% pre-birth death of the fetus. Especially in the first and second trimester, insufficient data was available to make any recommendation. More data was needed. Walensky urged pregnant “persons” to get vaccinated anyway, making the nation’s pregnant mothers test subjects in the vaccine trial.
It was Walensky who spouted the slogan “a pandemic of the unvaccinated,” to describe her claim that hospital beds were filled overwhelmingly with unvaccinated people, and that the great percentage of deaths were among the unvaccinated. See the official Press Briefing by White House COVID-19 Response Team and Public Health Officials, timestamp 37:00. “There is a clear message that is coming through: This is a pandemic of the unvaccinated.”
The CDC’s own study showed the exact opposite, with 74% of cases in the fully vaccinated. Studies out of Israel, one of the most heavily vaccinated nations in the world at the time, also showed the great majority of people allegedly sick and dead from covid were vaccinated. Walensky was also a strong promoter of mask-wearing, even for vaccinated children attending school, when data showed children were at almost no low risk of death from the dreaded covid disease.
In a move of chutzpah, Walensky announced in August 2022 that she would “shake up” the CDC with extensive changes referred to as a “reset,” because the $12 billion agency “needs to become more nimble.” Walensky said it was her “responsibility to lead this agency to a better place.”
‘It’s not lost on me that we fell short in many ways’ responding to the coronavirus, Walensky said. ‘We had some pretty public mistakes…’
Some had hope at the time Walensky would acknowledge the CDC’s large over-reach and over-reaction to an over-hyped pandemic, doing more public health harm than good with its extreme lockdown measures — but that was false hope. Instead Walensky implemented “Increasing use of preprint scientific reports to get out actionable data, instead of waiting for research to go through peer review and publication by the CDC journal Morbidity and Mortality Weekly Report.” Walensky said she would “get rid of some of the reporting layers that exist, and I’d like to work to break down some of the silos.” Both of these measures sound like lowering the scientific standards upon which the CDC reacts, not raising them. “Altering the agency’s organization chart to undo some changes made during the Trump administration,” and establishing a new “health equity” department hardly sound like improvements either.
One critic of Walensky’s “reset,” James Lyons-Weiler, Ph.D., “research scientist and author, said the changes are just an escalation of the deeper problem of governmental agencies colluding with pharmaceutical companies to lower scientific testing standards.”
Robert F Kennedy Jr.’s Children’s Health Defense called Walensky’s time as Director of the CDC a “contentious reign” in its “CDC Director Walensky Resigns, Ending Contentious Reign Over COVID Vaccine Policies.” This provides an accurate summary of the damage Walensky’s covid policies inflicted on American school children, businesses, families and lives.
Under Walensky, the CDC also gave false information on vaccine safety monitoring, added the COVID-19 vaccines to the childhood vaccine schedule despite known harms, withheld data on boosters from the agency’s own advisers and told pregnant women the vaccine was safe — just days after Pfizer reportedly finalized a report demonstrating it wasn’t, among other things that have outraged critics.
In her letter of resignation, Walensky said “I have never been prouder of anything I have done in my professional career.”
The White House issued its brief “Statement from President Biden on Dr. Rochelle Walensky” on the same day it received Walensky’s resignation letter, which must be seen to be believed.
“Dr. Walensky has saved lives with her steadfast and unwavering focus on the health of every American. As Director of the CDC, she led a complex organization on the frontlines (sic) of a once-in-a-generation pandemic with honesty and integrity. She marshalled (sic) our finest scientists and public health experts to turn the tide on the urgent crises we’ve faced.
“Dr. Walensky leaves CDC a stronger institution, better positioned to confront health threats and protect Americans. We have all benefited from her service and dedication to public health, and I wish her the best in her next chapter.”
Walensky’s next chapter should be spent in prison for betraying the trust of the American people. She gave no clear reason for her resignation, except to note the “waning of the covid-19 pandemic” and “the nation is at a moment of transition as emergency declarations come to an end.” On the same day of Walensky’s announced resignation, May 5, the WHO officially ended the covid “global emergency.” The U.S. ended its covid “public health emergency” on May 11.
Two days after the director transfer, on July 2, Walensky had the further chutzpah to give an interview with the Wall Street Journal, “Departing CDC Director Rochelle Walensky Warns of Politicized Science,” in which “she says public needs to be wary of misinformation.” Once again Children’s Health Defense details why this is another act of astounding hypocrisy showing how Walensky’s CDC itself highly politicized the “science” and spread dangerous misinformation.
Rochelle Walensky is Jewish, as chronicled in an essay on substack Taboo Truth. It examines previous Jewish CDC Directors Jeffrey Koplan, Tom Frieden and Anne Schuchat and their various scandals, and other Jews within the agency’s historic infrastructure, including massive funding lobbied by Jewish Home Depot owner Bernard Marcus which expanded the CDC to the bureaucratic leviathan it is today.

Our new director of the CDC is also Jewish. Her name is Mandy Cohen, and in its June 16 “Intent to Appoint Dr. Mandy Cohen as Director of the Centers for Disease Control and Prevention,” the Biden White House presents her credentials (most recent listed first).
- Secretary of North Carolina’s Department of Health and Human Services
- transformation of North Carolina’s Medicaid program and Medicaid expansion.
- Chief Operating Officer and Chief of Staff of the Centers for Medicare and Medicaid Services
- Acting-Director of the Center for Consumer Information and Insurance Oversight
- Affordable Care Act policy development and implementation
- medical degree from Yale School of Medicine and a Master’s (sic) in Public Health from the Harvard School of Public Health
Walensky was also a graduate of Harvard School of Public Health. Just as Walensky, Jewish Mandy Cohen is married to a Jewish man, Samuel Cohen, a health care regulatory attorney. He is:
“Managing Director of Health Policy at Curi Advisory, which is a full-service advisory firm that serves physicians and medical practices. Equal parts fierce physician advocates, smart business leaders, and thoughtful partners, Curi’s advisory, capital, and insurance offerings deliver valued advice…”
Mandy’s maiden name is Krauthamer, spelled differently and not likely a relation except by tribe to the Jewish Neo-Con war-monger journalist Charles Krauthammer. Mandy’s Jewish mother Susan was a nurse practitioner in an emergency room on Long Island, who inspired Mandy onto a public health path. Her Jewish father was a high school guidance counselor.
An extensive and detailed profile of Mandy Cohen emerged in the first year of the covid pandemic when she was Secretary of the North Carolina Department of Health and Human Services (NCDHHS). Titled “She’s the face of NC’s fight against COVID-19. Meet Dr. Mandy Cohen, Tar Heel of the Year,” it announces “Cohen is The News & Observer’s 2020 Tar Heel of the Year, an honor that recognizes a North Carolina resident who has made lasting and significant contributions in the state and beyond.” This humanizing puff piece states, “Cohen has become the figurative and literal face of North Carolina’s ongoing fight against COVID-19.”
“It is a fight in which she’s relied most upon data and science and something less easily quantified: the sense of empathy and compassion that some closest to her say make her a perfect fit for her position. It is a fight that’s challenged her to balance competing interests — one that at times has brought fierce criticism from skeptics who dismiss science or downplay the virus — while maintaining the goal of preserving the health and lives of North Carolinians.”
According to North Carolina Dept. of Health and Human Services, using my own simple calculation, over the past year the case fatality rate from Covid-19 amounts to .4%. This means 3,903 people in North Carolina died with covid over the past year (not necessarily from covid, and according to flawed PCR test diagnostics acknowledged by the CDC itself). Open VAERS shows that 179 people in North Carolina have been reported slain by the vaccine since its roll-out in early 2021 until June 16 of this year (the same date the White House announced intention to appoint Cohen CDC director).
Recall that the Vaccine Adverse Reporting System (VAERS) was shown by the CDC’s own funded study in 2010 to report less than 1% of actual adverse vaccine events. The number of people slain in North Carolina by the vaccine could be more honestly at least 18,000. To compare these numbers—covid-killed vs. vaccine-killed—we should divide 18,000 by 2.5, since the covid-killed number is only for one year (the mildest year), and the vaccine-killed for 2.5 years. Answer: at least 7,200 vaccine-killed per year compared to under 4,000 per year covid-killed. The cure may have been at least almost twice as lethal as the disease.
As the Pfizer and Moderna vaccines were scheduled to arrive in North Carolina, Cohen addressed her staff. “So that tells me a couple things… One, no one else is talking about vaccines and sort of setting the stage and being transparent. So, A-plus, team. … We’re setting expectations. We’re sharing what we know. We’re being concrete. We’re talking about all our plans, so I’m really pleased.”
Yes, A-plus, team. Mandy is really pleased you were talking about vaccines and being transparent. Unfortunately for the thousands slaughtered by the vaccines in North Carolina and their families, you were not transparent about the carnage the vaccines could cause in the state. Cohen’s “sense of empathy and compassion” made her a perfect fit for that job.
Cohen’s Jewish identity is featured:
“She spent most of the next hour listening to her staff members detail their work. By the time the meeting was ending, Cohen had changed her virtual background to that of a picture of her family for some Throwback Thursday show-and-tell. The picture was from her oldest daughter’s baby-naming ceremony, a Jewish ritual, and the family was standing in front of a menorah.
“‘Throwback Thursday and Hanukkah,’ Cohen said with some excitement, introducing her family.
“Like her family, her faith has played an important role in helping her navigate the pandemic. She wears a necklace with the chai (pronounced like “high”) symbol around her neck. The symbol represents the Hebrew word for life and health.
“When Cohen and her husband moved to North Carolina, they did not know anyone. The synagogue they chose became a second home. “And I also joke with the rabbi that I think Jews were public health people before they knew what public health was,” Cohen said, referencing Jewish dietary restrictions, and how even before the pandemic there was “a lot of washing your hands in Jewish ritual practices.
“Back on the work call, Cohen wished a Happy Hanukkah to those celebrating. It was the first night of the festival, and she needed to hurry home.”
If Cohen’s “faith” is even remotely Talmudic-influenced, the chai symbol represents the Hebrew word for life and health to Jews, and death and sickness for Goyim. Washing hands in Jewish rituals may sometimes be a necessity to cleanse away the blood from the male genital mutilation ceremony of circumcision, cruel animal sacrifices, and Jewish Ritual Murder that includes drinking the blood of raped, tortured and slaughtered children. Cohen of course does not allude specifically to these Talmudic blood rituals, but the hand-washing associated with them could hardly have made such extreme Talmudic fundamentalist Jews “public health people.”

Cohen cannot be accused of these Judaic horrors, but just as with Walensky, nor can she be trusted with a “sense of empathy and compassion” while wearing a Hebrew symbol of life and health. Chai means “to live and walk in the Jewish cultural lifestyle,” and also “the lowest (closest to the physical plane) emanation of God.” She may be worshiping a Hebrew god who seems more like a demon, demanding blood, insanely jealous, viciously punitive to a genocidal extent, and intolerably racist.

The ever-alert Children’s Health Defense, in commenting on Cohen’s appointment to CDC director, did not take its criticism so far, but it is indicative that CHD called Cohen “fanatic.” In “‘Fanatic?’: Biden’s New CDC Director Was Strong Proponent of Pandemic Mandates, Masks and Lockdowns,” author Michael Nevradakis, Ph.D. quotes critics who have emerged throughout the covid years 2020-21 as voices of medical scientific reason.
“Cohen appears to be fully entrenched in the ‘bio-pharmaceutical complex.’ She was on the wrong side of every pandemic public health intervention, failed to recognize early therapeutics and natural immunity, and to date has not acknowledged the safety disaster unfolding with the COVID-19 mass, indiscriminate, vaccination program.”
-Dr. Peter McCullough, author The Courage to Face COVID-19: Preventing Hospitalization and Death While Battling the Bio-Pharmaceutical Complex
“(Cohen is) a public health COVID authoritarian and the worst possible person to become the next CDC head.”
-Alex Berenson, commentator and former New York Times journalist
Berenson is Jewish, and in his own article, “URGENT: Joe Biden is about to pick the worst possible person to become the next CDC head,” said something Nevradakis did not include:
“Apparently diversity mandates haven’t hit the CDC yet. Cohen is a lot like Walensky, a nice Jewish* doctor** from the Northeastern suburbs with all the right degrees.
“(*I can say it, I’m Jewish)
“(**The actual expression is “nice Jewish girl” but I don’t want to get in trouble)”
Berenson is suing Andy Slavitt, Jewish (not found in “early life and education,” but at the end in Categories, “American Jews”), over censorship infringements. Slavitt started out at Goldman-Sachs investment bank, and ended up senior adviser on President Joe Biden’s coronavirus response team.
Returning to quotes in the CHD article:
“Going through [Cohen’s] timeline is a strange blast from the past of heartbreaking fear-mongering, pseudo-science, and propaganda. She passed with flying colors all three tests of compliance: closures, masking, and vaccine mandates.”
– Jeffrey A. Tucker, founder and president of the Brownstone Institute
In his essay, “New CDC Director Is Another Lockdowner,” Tucker starts by telling us that in order to have power and influence in the Soviet Union, one needed to be a member of the Communist party.
“We are headed this way in the US today. The party in question is the lockdown party. … That’s my best read on why Mandy Cohen is being pulled away from her perch in North Carolina, where she led a catastrophic pandemic response, to be the replacement for Rochelle Walensky as head of the Centers for Disease Control and Prevention. She is a faithful member of the lockdown party and thus demonstrates her willingness to do it again should the occasion arise.”
My best read is that both Walensky and Cohen are members of the Jewish party, with lockdowns as their strategy to advance Jewish profit and control objectives. Their willingness to do it again is rooted in their faithfulness to Jews and Judaic indoctrination. The occasion will arise because they will engineer one again. For a wider analysis of the Jewish role in covid, see the TOO book review “New Covid Book Tackles Taboo Truths.”
CHD/Nevradakis: “Cohen was ‘the top choice of Jeffrey D. Zients,’ the Biden administration’s former COVID-19 response coordinator.”

Zients is of course Jewish as well, suggesting the well-known phenomenon of Jewish tribal nepotism in appointing Cohen. Zients went from COVID-19 response coordinator, “charged with rolling out a massive vaccine program nationwide in early 2021,” to the current White House Chief of Staff, “like the chief operating officer for the government.”
Zients replaces Ron Klain, also Jewish.
“Jewish Ron Klain has been Joe Biden’s political alter ego for many of the last 40 years, regardless of his position or Biden’s interaction with Jews and Israel,” Democratic Party strategist Steve Rabinowitz said, adding: “Along the way, Klain has proven himself as friendly to our community and to Israel as we are with his old/new boss.”
Closely similar to Zients, and generally similar to Walensky and Cohen, Klain formerly took charge of a “pandemic response” to another disease scare in 2014, as Obama’s “Ebola Czar,” according to the Jewish Forward. Given the general Jewish hatred of the Russian Czars, I struggle to understand why these Jews apply this term to themselves when they lead “pandemic response” efforts. Perhaps to further defame the long-dead Czars, but doesn’t this also defame themselves?
CHD/Nevradakis quotes:
“Dr. Mandy Cohen during her tenure as North Carolina’s HHS secretary pushed through the most draconian COVID-19 measures imaginable.
“With her at the helm of the CDC, I expect we will just get more lying and hiding regarding the agency’s abysmal response to the pandemic and horrific track record in general.”
-Brian Hooker, Ph.D., P.E., senior director of science and research for Children’s Health DefenseCohen was particularly harsh on children in North Carolina, imposing mask mandates in school regardless of vaccination status, extending school closures longer than most other states, and threatening to sue a county school board if it did not “rescind a new policy that eliminates COVID-19 quarantine measures for most students and staff.” All this after it was known that children were at almost zero risk from covid. In “studies of children (that) are the most comprehensive yet anywhere in the world,” 2 in a million children died of covid, and most of those had “co-morbidities.”
Combine Walensky’s damage to unborn babies in the womb with Cohen’s damage to school-age children, and these two Jewish lockdown/vaccine “fanatics” covered the entire childhood age range with trauma and death, for no valid reason.
Adolescent suicides spiked during the pandemic. In North Carolina under Cohen’s lockdown reign, “youth” suicides spiked, attempts up 46% among 10-14 year old girls in 2021. Cohen continued to impose among the harshest school lockdown measures in the nation, motivated no doubt by her Jewish “sense of empathy and compassion.”
When they heard rumors that the Biden Administration—itself overwhelmingly Jewish—was planning to propose Cohen as CDC director, a group of 28 Congresspeople (24 men including a Senator and a Representative from North Carolina, and 4 women including Marjorie Taylor Greene) issued a joint letter to the President dated June 13 2023. They state:
“Dr. Cohen is unfit for the position. Throughout her career, Dr. Cohen has politicized science, disregarded civil liberties, and spread misinformation about the efficacy and necessity of COVID vaccinations … and the necessity of masks.
“… Dr. Cohen was a proponent of unnecessary, unscientific COVID restrictions on school children… After a North Carolina school district followed the science by declining to institute unscientific mask mandates and voted with an overwhelming majority to end “contact tracing” and curtail other unproven and largely hysterical quarantine policies, Dr. Cohen threatened to bring legal action against the district. Dr. Cohen’s willingness to threaten the school district put politics over the well-being of children and is just another example of the litany of public health abuses the American people endured at the hands of bureaucrats throughout the COVID-19 pandemic.”
The letter continues:
“Dr. Cohen has an extensive history of publicly… supporting radical, left-wing policies … (She) endorsed an unconstitutional ban on semi-automatic rifles and lobbied to classify climate change as a ‘public health crisis.’”
“Given her strong affiliation with… the COVID-19 lockdowns, it will be difficult for the American people to trust Dr. Cohen to run the CDC as a nonpartisan actor who makes objective decisions rooted in scientific data, and not in political expediency.”
Or Jewish Talmudic “science tikkun” as espoused by militant Jewish vaccine promoter Peter Hotez. In 2020 as secretary of NCDHHS, Cohen said in an interview with Religious News Service : “There’s so much of what I do in the health and human services space that’s so aligned with Jewish values of healing the world.” Healing the world is dangerously close to the Judaic concept of tikkun olam: fixing the world. The article further states: “It (wearing the Hebrew Chai necklace) is a testament to her faith — she is Jewish — and, in this strange pandemic moment, to her religious values.”
And: “As the Jewish High Holidays approach, Cohen said she looks forward to the time of reflection and introspection — the themes of Rosh Hashana and Yom Kippur — especially as they relate to her public work.” This ten day period between Judaic holy days includes a day of judgment where the fate of the wicked is decided. It is a time of reflection and repentance. As the wicked witch of North Carolina health and death, Cohen had much upon which to reflect and repent.
Dale Folwell is running for North Carolina governor. He tweeted:
“… the actions of Dr. Mandy Cohen during Covid resulted in more disease, death, poverty and illiteracy. As NC Governor, I would be hard pressed to ever follow her lead at CDC if chosen by the POTUS.”
The tweet was on June 2, two days after Cohen officially became Director of the CDC.
Private Sector, Monied Interests
In the short time between her resignation from NCDHHS in November 2021 and her appointment to CDC Director on July 1, 2023, Cohen was the Executive Vice President of Aledade, “the nation’s largest network of independent primary care practices.” She was also the Chief Executive Officer of Aledade Care Solutions, “the company’s new health services unit.” Aledade’s Executive Team’s webpage still lists Cohen as EVP and CEO of the Care Solutions new unit.

The Department of Justice lists under Government Ethics, Conflicts of Interest:
“An employee is prohibited from participating personally and substantially in a matter in which he, his spouse, minor child, or a general partner, or an organization of which he is an officer, director, trustee, partner or employee has a financial interest.”
Or she, in Cohen’s case. We must watch her closely for conflicts of interest, since her Jewish predecessor Walensky was identified in just such a conflict in 2021 soon before and after her appointment to CDC director. In “CDC Director Walensky’s Husband Received $5 Million in HHS Grants – and That’s Just the Start of It,” we see the insider connections, including Fauci, and another NIAID official who was on the oversight committee that approved the grant, both of whom worked with Rochelle in her time at CDC before she became director. They funneled a large research grant to Rochelle’s husband Loren’s private biotech firm Lytica Therapeutics. He is shown on the Team webpage as “Scientific Cofounder” and his bio states he is “Professor Pediatrics at Harvard Medical School, and Director of the Harvard/MIT MD-PhD Program.”
Also on the team is a Daniel Cohen, PhD, Associate Principal Scientist, Protein Chemistry. Mandy’s Wikipedia entry shows in its Early Life section, she “has two younger siblings.” The “Tar Heel of the Year” article says, “Her brother’s family just had a baby in May…” Certainly we see many Cohens throughout the Jewish power structure, and cannot verify that Daniel has any direct relation to Mandy except by tribe.


Hebrew name Cohen means Priest, descended from Aaron.
Cohen’s CDC Promotes “Chest Milk”
Such speculation is unnecessary. Cohen’s depravity emerged within a week of taking office when numerous news reports quoted the CDC stating: “transgender and nonbinary-gendered individuals may give birth and breastfeed or feed at the chest (chestfeed).” This ignited outrage from the nation’s mothers, Republican party candidates, Fox News and many others.
Not surprisingly, links to the CDC statement in these reports go nowhere or in circles now, but one prominent mention found on the CDC official website says under “Priority Breastfeeding Strategy: Continuity of Care” – “Review (of) Continuity of Care in Breastfeeding Support; a Blueprint for Communities” document: “Create community environments that proactively promote, protect, and support chest/breastfeeding.”
It is under “Health Equity Considerations” where we find the horrifying statement under “Pronoun Use – Remember That:” There is more. “An individual does not need to have given birth to breastfeed or chestfeed. Some families may have other preferred terminology for how they feed their babies, such as nursing, chestfeeding, or bodyfeeding.”
In an established pattern of recklessness endangering the nation’s children and mothers, Cohen failed to warn of the dangers to babies from synthetic hormone-induced “chest milk.” The synthetic hormone no longer recommended for increasing natural female lactation but recommended (not by name) for transsexual “chest feeding” Domperidone is a known risk to babies.
Cohen’s tribal colleagues the Jewish Pritzker family rules the transsexual transition industry with billions of dollars in grants, investments, donations and profits to impose the unholy inhuman agenda. Family oligarch Tom Pritzker was only one of two names listed in Jewish Epstein’s notorious black book with a special hand-written note: “Numero Uno.”

Caution: Another Jew Leads CDC
We have seen excessive evidence that the new CDC director Mandy Cohen will inflict whatever catastrophic lockdown measures and vaccine mandates the next contrived disease panic offers to further Jewish objectives, just as previous CDC director Rochelle Walensky.
May we all take caution. Not viruses, but certain Jews acting in coordination have infected the governmental power structure with the capability of inducing sickness and death by unelected, arbitrary and capricious decree. The cure is truly worse than the disease. The new CDC director Mandy Cohen, driven by her Judaic faith, now leads the most powerful Federal agency imposing public health/death measures.
May we turn to a more natural, holistic health model to survive her impending reign of terror at CDC.
The American Board of Internal Medicine’s Longstanding War On Doctors Is Escalating
The ABIM’s history proves their present actions are political/financial and not scientific. They are making examples of us “dissenters” to scare the rest of the country’s docs to keep quiet.
BY PIERRE KORY, MD, MPA | AUGUST 23, 2023
The unholy alliance of industry captured high-impact medical journals, federal public health agencies, professional societies (ABIM, AMA, APHa etc), and most importantly, the state medical licensing boards directed by the Federation of State Medical Boards (FSMB) are still going hard after us “dissenting” doctors. You know, those of us that very publicly called out the unscientific policies implemented by corrupted policymakers in a directed pursuit of profits and power. Their actions trying to silence us (and to scare other doctors from speaking out) are escalating.
Recently, what I call the “misinformation committee” of the American Board of Internal Medicine (ABIM) voted to strip Professor Paul Marik and myself of our Board certifications. To best understand why they would do this, I think it is important to review what the ABIM is, how it operates, and then detail their absurd attempt to paint us as misinformationists by using disinformation.
Let’s trace my current relationship with the ABIM to today:
At the end of my training, I became Board Certified by the ABIM in three specialties (Internal Medicine, Pulmonary Diseases, and Critical Care Medicine).
What is the ABIM? Well, from this devastating article by Kurt Eichenwald, an accomplished corporate investigative journalist who did a devastating takedown of the ABIM and its officers in a Newsweek piece in 2015:
The ABIM is a purported nonprofit that certifies new physicians as meeting standards of practice. Beginning in the early 1990s, the ABIM ordered certified doctors to be recertified, again and again. Without the ABIM seal of approval, lots of internists and subspecialists can’t get jobs and can’t admit patients to hospitals. So by taking advantage of that monopolistic power, the ABIM has forced hundreds of thousands of physicians to follow recertification processes that doctors complain cost them tons of money (paid to the ABIM), require tons of time (taken from families and medical practices) and accomplish nothing.
In many doctor’s opinion, this cash grab of the ABIM by selling “certifications” is a corrupt farce. There is no evidence that certifying doctors in this highly costly way does anything to improve the quality of care delivered. The ABIM has not only refused to produce data showing the program improves patient care but also hasn’t conducted any studies on that matter. In fact, the ABIM and its related organizations are:
harming American medicine and diminishing the quality of scientific research, pushing physicians to close practices rather than wasting time on expensive and frustrating busywork, and forcing specialists to play a game of medical trivial pursuit. (Even Baron has admitted that he was tested for recertification on topics he never used in his practice.)
But it sure does generate cash for ABIM executives. Note that Board Certification used to simply be a sort of “honor” denoting that the member passed a more rigorous examination in their specialty. That “honor” comes at a price though:
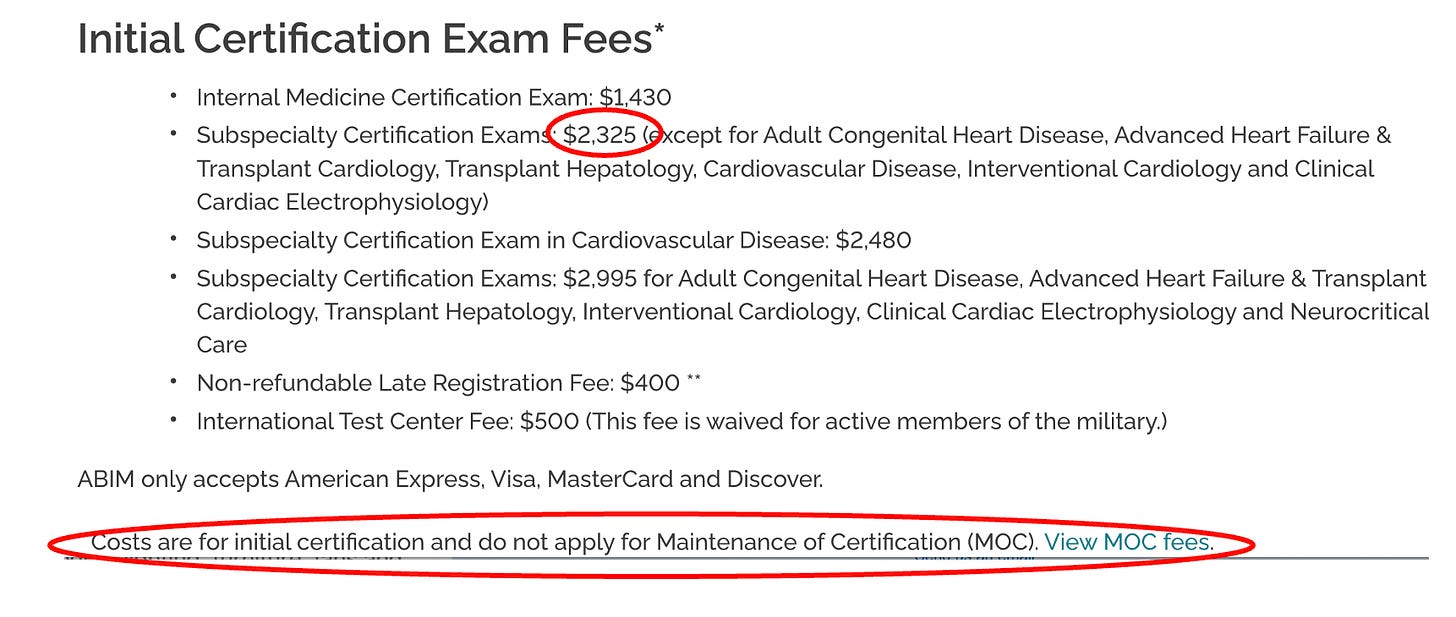
Since I am (was?) Board certified in 3 specialties, lets do some math as this is what it costs me to re-certify every ten years:
$1,430 for Internal Medicine
$2,325 for Pulmonary Diseases
$2,325 for Critical Care Medicine
But wait, we are not done yet. These bastards were not making enough money with once-every-ten-year recertification exam fees, so they invented a new program of annual busywork education requirements which they called Maintenance of Certification (MOC) which costs you $220 every year for every certification (plus late fees if you forget). To wit, I went into my patient portal and discovered. I owe them $480 for each of my certifications!
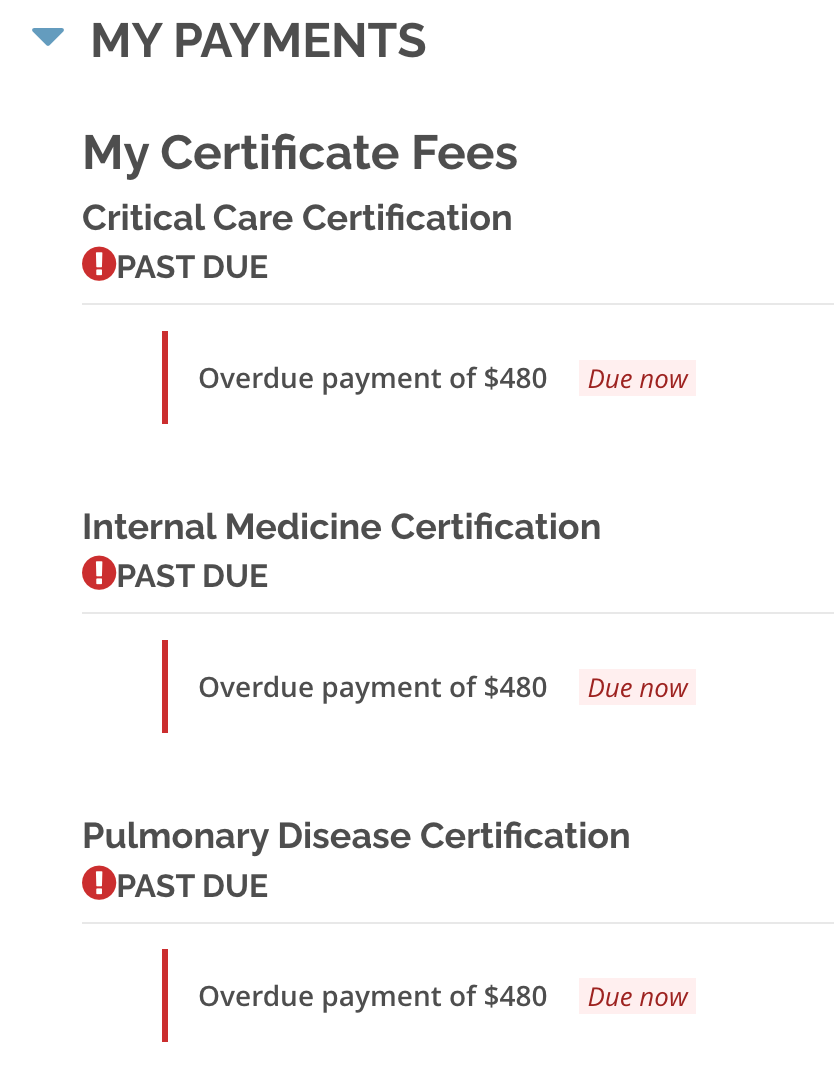
And get this – that money essentially goes to ABIM executive salaries and pensions and other dubious private investments as described by Eichenwald where he details the insane lengths the ABIM goes to “hide” the compensation and pension data on its executives. What is worse is that ABIM certification has now been made a requirement of employment as a faculty member of academic medical centers and hospitals and is also a requirement to be on many insurance company panels (these actions further strengthen the control of doctor behavior).
Doctors have started publicly slamming the group in industry publications. “ABIM is imposing on us an onerous and ill-conceived tool, one that most physicians agree is irrelevant,” Dr. Karmela Chan wrote in Internal Medicine News. “I am glad this conversation is happening, because, frankly, the process was enough to make me want to quit being a doctor.” Further, in a recent poll of 2,211 physicians conducted on a doctors-only website called Sermo, 97 percent of the respondents criticized recertification.
Richard J. Baron, the ABIM CEO that sent letters threatening decertification to me and Paul, makes close to a million dollars a year, however that data is almost impossible to find due to the ABIM’s multiple attempts to obscure it as well as its spokespeople avoiding answering any inquiries on the topic. Here is a summary of Eichenwalds findings on the ABIM:
- In 2015, they were 5 months late in filing their publicly available financial report with the IRS (that several journalists were very interested in).
- The report is full of obfuscations and anomalies of reporting of not only the actual money earned by the executives, and particularly Baron, but his financial conflicts of interest are even better hidden.
- A big percentage of the ABIM’s millions was in the form of cash to one former employee.
- The ABIM in 2013 had 57 million against liabilities of 105 million – while Baron was going around saying that its assets are three times its liabilities (this was a 100% lie. When I get to the ABIM’s response to our defense letter, remember that what liars do is.. lie).
- It lost $4.8 million on $55.5 million in revenues, no small feat and almost entirely due to a bloated payroll.
- It also claims it spends no money on lobbying while it spent between 100K to 160K annually to lobby Congress on Medicare and Medicaid (another lie).
- The data on top officers compensation is so obscured and fragmented, Eichenwald reported that he had found it much easier to discover executive compensation at Enron, Worldcom and Adelphia – all famous for lying on tax filings. Again no small feat (to be one of the top corporate liars in the U.S).
- Officers “double dip” – former CEO Christine Cassel got $741K from ABIM and $247K from the ABIM “Foundation” (slush fund for ABIM officials) and also got $219K in “other compensation” – totaling $1.2 million for one year. (Nice gig if you can get it).
- But wait, we are not done. Cassel also got $504K in “deferred compensation” for a total of $1.71 million more that year (six times the median compensation for similar sized non-profits). Six times.
Then there is this doozy of an article which came out this week in The Defender by Children’s Health Defense, detailing the ABIM CEO Richard Baron’s conflicts of interest:

Some of the most disturbing reveals:
“The head of a national medical organization who publicly called for doctors to lose their licenses unless they supported government narratives on COVID-19 treatments and vaccines concealed his relationship with a public relations firm whose client list also included Pfizer, Moderna and the Centers for Disease Control and Prevention (CDC).
Dr. Richard Baron, president and CEO of the American Board of Internal Medicine (ABIM) is a client of Weber Shandwick, investigative journalist Paul D. Thacker reported on Wednesday.
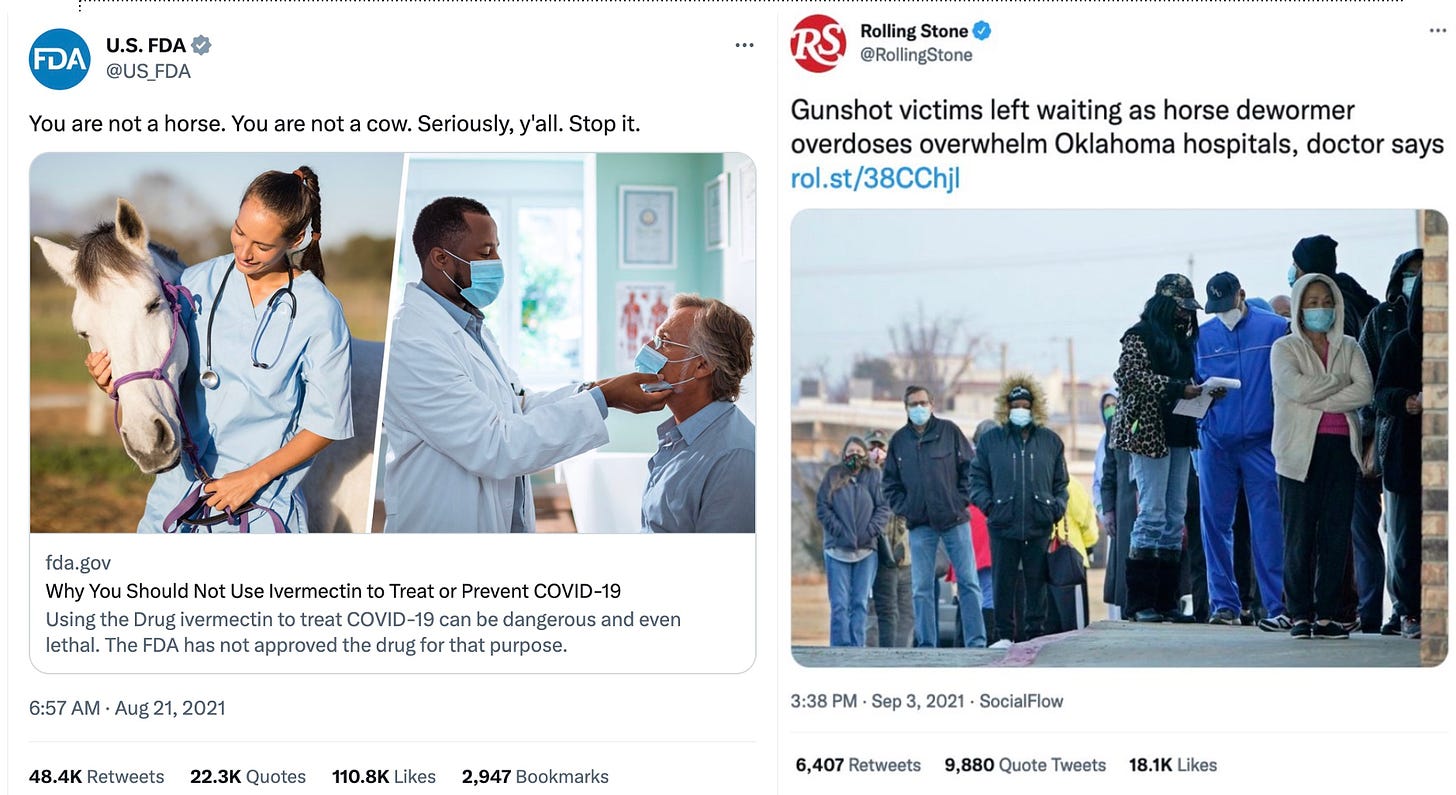
Note that I went after Weber Shandwick in my book, “The War on Ivermectin” where I argue (without proof, although I believe that is coming because I know of a subpoena coming their way) that they created and launched the “Horse Dewormer PR campaign,” highlights of which was the famous FDA tweet and absurd Rolling Stone article:
In late 2021, Baron publicly pushed for doctors who spread “misinformation” about COVID-19 and the vaccines to lose their license and certification.
Last year, Baron partnered with Weber Shandwick to propose a South by Southwest (SXSW) panel titled “When Doctors Prescribe Misinformation.” The proposal was subsequently accepted and the panel took place at SXSW in Austin, Texas, on March 13.
According to Thacker, “Weber Shandwick’s panel featuring Dr. Baron has been widely promoted by the PR firm’s employees,” including Sarah Mahoney, executive vice president, Healthcare Communications, Strategy & Planning for Weber Shandwick, who in a LinkedIn post, wrote she “can’t think of a more important topic right now.”
Although to the unawake the following may seem normal public health practice, but to those of us fighting agency capture by Big Pharma, it is absurd:
The CDC’s National Center for Immunization and Respiratory Diseases (NCIRD) in September 2020 awarded Weber a $50 million contract “to promote the vaccination of children, pregnant women and those at risk for flu and increase the general acceptance and use of vaccines,” according to the PR firm’s website.
Thacker said he believes much of what is labeled “misinformation” in medicine and academic research “is really just corporate PR,” and that “Congress needs to take a harder look at funding for ‘misinformation research.’“
Speaking of taking a harder look at where the funding is coming from for “misinformation research” and the ABIM, it turns out that.. we can’t. Why? Check out this tweet showing a clause inserted into the ABIM’s by-laws in 1998:
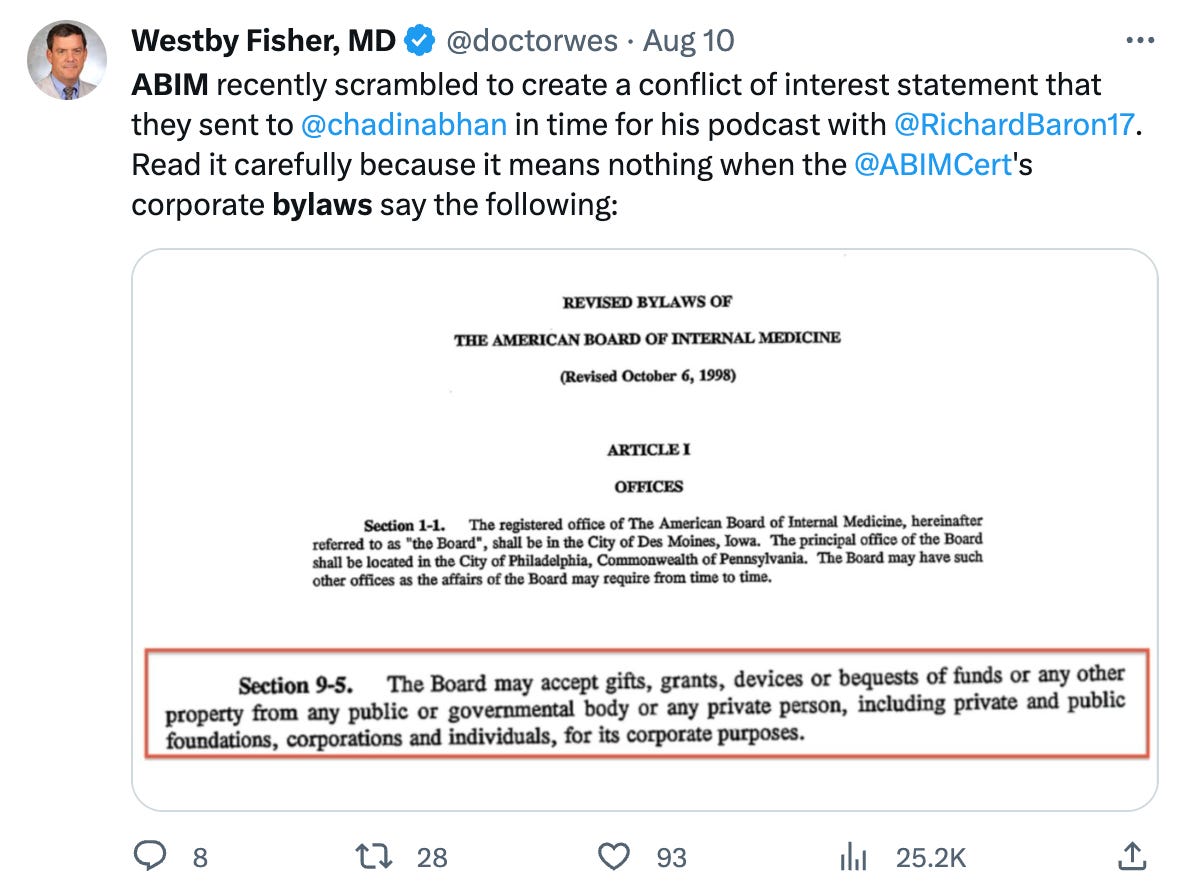
But wait, it gets better, like way better. Also in their by-laws:
Information that is disclosed will be kept confidential except to the:
-
- President and Chair of the Board;
- The chairs of the relevant Subspecialty Boards, Test-Writing Committees, and other Committees of the Board, members who serve on the relevant Boards and Committees, and staff working with the respective committees;
- The Conflict of Interest Committee members and Conflict of Interest Committee staff,
except as required for the purposes of continuing medical education.
So, basically, they can take money from any corporate entity and do not have to disclose it to anyone. Again, nice gig if you can get it.
Back to the ABIM’s history: One of Eichenwalds more disturbing observations about the behavior of the ABIM:
I can attest to the ABIM’s pomposity. Starting with my first story about the ABIM, the organization usually has refused to acknowledge I even asked a question. The only other group to do that in my 30-year journalism career was a company that processed payments for child pornography websites. Plus, when I reported on the uprising by doctors, the ABIM ignored the facts and instead investigated me.
Now lets fast forward to Covid. On July 29, 2021, the FSMB (this entity controls the state medical licensing boards, not the ABIM – at least on paper) issued a policy statement that “Physicians who generate and spread COVID-19 vaccine misinformation or disinformation are risking disciplinary action by state medical boards, including the suspension or revocation of their medical license.”
What is interesting is how fast and how rigidly the ABIM followed the FSMB’s lead and enacted their own misinformation policy despite the fact that, as my colleague Meryl Nass has pointed out:
“suddenly claiming that using licensed drugs for COVID, criticizing federal policies for COVID or criticizing the value of COVID vaccines is unprofessional” gives the specialty board the right to revoke a certification—well, that was never part of its contract with me. So pulling my certification for issues that were never specified in the original contract is breach of contract.
I think it would only be a breach if contracts, like our Constitution and the practice of medical ethics, were still “a thing.”
The ABIM apparently liked the FSMB’s “misinformation policy” idea to attack dissenting doctors so much (or were told to like it) that 2 months later, they, along with their colleagues at the American Board of Pediatrics and the American Board of Family Medicine, issued a statement supporting the FSMB’s position, saying, “We all look to board certified physicians to provide outstanding care and guidance; providing misinformation about a lethal disease is unethical, unprofessional and dangerous.” (note that they seem particularly focused on Covid misinformation and not any other disease model or therapeutics. Do you think it could be because Covid vaccines and therapeutics opened immensely profitable markets to Pharma overnight?).
Again from Meryl Nass (please subscribe to her Substack):
Furthermore, the processes the ABIM is using, as described by CEO Richard Baron, MD in his podcast with the New England Journal of Medicine are procedurally unfair. Dr. Baron earns $1 million/year to threaten doctors for a crime that does not exist. Baron, notably, refused to specify where the line was between misinformation and genuine disagreement in that podcast, though he seems to have no difficulty at all drawing the line when it comes to licensees who speak publicly about how to manage COVID. In a truly Orwellian effort, the ABIM and the ABIM Foundation have dedicated the year to ‘building trust’ in medicine.”
In what I suspect was the ABIM’s first enforcement of their shiny new policy, they go after Peter McCullough, Paul Marik, and myself on the same day (May 26, 2022) with a letter quoting numerous public statements we made, implying that we needed to defend the substance of such statements with supporting data or risk losing our certifications.
“Game on” I thought, looking forward to the exercise of “debating” scientific data with the ABIM. However, our FLCCC lawyer, Alan Dumoff pointed out that the ABIM’s policy and procedures state that the process of accusing a member of misinformation requires that they first provide evidence to us that what we said was inaccurate. So, we wrote back, pointing out to the ABIM their brazen “error” (yeah right) in not complying with their own policy and procedures.
“Nonsense” they wrote back (in short). Their logic was truly shocking – they say that the fact they provided the substance and references to my public statements means they did their duty (rather than their providing references that would refute my statements which is what their policy states they need to do).
You can read their brazen, illegitimate, dismissive response here:

This letter above demonstrates the unchecked power they have – they alone determine whether they are following their own policy which they so clearly were not. What did I say about liars before?
Anyway, rebut them we did. We wrote a 76 page treatise with 175 references, 11 exhibits, and 22,000 words, marshaling and weaving numerous data sources to support all our public statements that they had a problem with. May it enter the historical record here (I think you Covid vaccine and ivermectin data geeks will find the letter impressive).
We sent that letter over 6 months ago… and finally got an answer a few weeks ago. To understand the misinformation committee’s response, note this statement from an editorial written by Baron where he tries to give examples of misinformation:
A whole range of statements with which many — or even most —physicians might disagree would therefore not trigger our disciplinary process. On the other hand, when someone certified by the ABIM says something like “the origin of all coronary heart disease is a clearly reversible arterial scurvy” or “children can’t spread Covid” or “vaccines don’t prevent Covid deaths or hospitalizations,” we are not dealing with valid professional disagreement; we are dealing with wrong answers.
That last sentence is critical as Baron literally is saying that the ABIM gets to determine what is a valid professional disagreement versus a “wrong answer.” Good to know, especially in regards to the fact that the narrative that “vaccines prevent Covid deaths or hospitalizations” was strongly refuted in our initial response letter.
This issue about drawing a line between misinformation and genuine disagreement is a critical one. From our letter of appeal written by our lawyer Alan Dumoff:
Threshold Issue: What Standard Distinguishes Legitimate Differences of Professional Opinion and Misinformation
We disagree with the Committee’ s interpretation of the data, which we address below, but the initial question is by what standard the American Board of Internal Medicine (“ABIM” or “Board”) evaluates evidence to determine that disagreement with consensus generally, and regarding controversial matters around COVID-19 policy specifically, rise to the level of actionable misinformation. The Board’s policy recognizes the right to legitimate debate, which requires it not merely show evidence supporting a consensus view but that it demonstrate that these professional disagreements are not legitimate but outright misinformation.
If not grounded in an articulated standard, at the very least, the Board must demonstrate that the views at issue are false by citing the fallacies in the actual substance of the evidence provided, not simply by critiquing a few isolated studies divorced from the totality of evidence. Resting solely upon citations to mainstream publications while substantially avoiding the evidence in our Submission, and our detailed critiques of these publications does not provide a basis for the Board to take action against my clients.
A diplomate’s medical positions must be plainly erroneous to merit sanction. Departure from consensus is hardly unusual and by itself insufficient. While the Sanctions Notice gives the appearance of having done so, the Committee did not directly engage the numerous imperfections in the mainstream approach Drs. Kory and Marik’s have pointed to in substantial detail. The Committee has not engaged the evidence submitted and demonstrated it is illegitimate, only that it departs from the consensus, that is insufficient to support a sanction.
The point is that the ABIM appears absurdly obsessed with getting doctors to spout only consensus opinions. This is literally unprecedented in science. From Michael Chrichton the author:
I want to pause here and talk about this notion of consensus, and the rise of what has been called consensus science. I regard consensus science as an extremely pernicious development that ought to be stopped cold in its tracks. Historically, the claim of consensus has been the first refuge of scoundrels; it is a way to avoid debate by claiming that the matter is already settled. Whenever you hear the consensus of scientists agrees on something or other, reach for your wallet, because you’re being had. Let’s be clear: the work of science has nothing whatever to do with consensus. Consensus is the business of politics. Science, on the contrary, requires only one investigator who happens to be right, which means that he or she has results that are verifiable by reference to the real world. In science consensus is irrelevant. What is relevant is reproducible results. The greatest scientists in history are great precisely because they broke with the consensus. There is no such thing as consensus science. If it’s consensus, it isn’t science. If it’s science, it isn’t consensus. Period.
I love that last line so much it bears repeating, “If it’s consensus, it isn’t science. If it’s science, it isn’t consensus. Period.”
Now, let’s look at their response to our 76 page letter teeming with supportive data for our statements. Can read their letter in its entirety here but I thought I would just pull the most illustrative sections:
… the CCC (i.e. misinformation committee) concluded that your statements about the purported dangers of, or lack of justification for, COVID-19 vaccines are false and inaccurate because they, too, are not supported by factual, scientifically grounded, and consensus driven scientific evidence. In fact, the overwhelming body of factual, scientifically grounded, and consensus-driven evidence – at and since the time you made those statements – shows that the COVID-19 vaccines are safe and effective for children and for adults
I have heard of the term “evidence-based medicine (EBM)” which is what I practice, but not “consensus driven science” (completely new invention – pernicious indeed. I Actually adhere to the original definition and conceptual framework envisioned by the founders of evidence based medicine which was incredibly well detailed in a by my friend “A Midwestern Doctor” in his brilliant recent post “What Happens To Doctors Who Innovate”.
Anyway, they then listed a few published, peer-reviewed papers supporting their point, blissfully un-acknowledging of the fact that the high-impact journals have been systematically censoring pretty much all negative analyses of the vaccine campaign’s impacts while publishing nothing but positive reports with cherry-picked and/or fraudulent data – so there is no way for the truth about vaccines to win in scientific debates my friends.
The high-impact journal censoring of adverse vaccine data is identical to their censoring of dozens of positive trials of ivermectin, something I extensively detail in the chapter called “The Journal Rejections of Positive Ivermectin Studies” in my book.
It gets even better – they next argue against my claims of lack of safety of the vaccines by, get this, referencing proclamations by the WHO and CDC. They ignore all the immense data to the contrary that I submitted while of course being willfully oblivious to the fact that the CDC and WHO are fully Pharma captured agencies:
Moreover, the vaccine safety data overwhelmingly (overwhelmingly?) contradicts your statements about vaccine risks. See, e.g., Centers for Disease Control and Prevention, “Safety of COVID-19 Vaccines,” https://www.cdc.gov/coronavirus/2019-ncov/vaccines/safety/safety-of-vaccines.html (updated March 7, 2023) (reporting that “Adverse Events (Serious Safety Problems) Are Rare,” and that “[t]he benefits of COVID-19 vaccination outweigh the known and potential risks”); World Health Organization, “Safety of COVID-19 Vaccines,” https://www.who.int/news-room/feature-stories/detail/safety-of-covid-19-vaccines (March 31, 2021) (stating that “[b]illions of people have been safely vaccinated against COVID-19,” that “mRNA vaccines [for COVID-19] have been rigorously assessed for safety, and clinical trials have shown that they provide a long-lasting immune response”).
The paragraph above should enter the historical record… somewhere. That will NOT age well. The only thing more absurd to contemplate is whether they know they are lying in their letter or if they are simply referencing propaganda that they themselves swallowed whole? In a way, the former might be more acceptable to me at this point.
Their opinion on how I got ivermectin wrong was similarly brazen – they ignored all the meta-analyses (historically considered the strongest form of data, a fact they seem to have willfully avoided) in favor of listing a handful of trials where ivermectin was supposedly found ineffective, relying mostly on citing “the Big 6” (what I named the chapter describing the fraud behind the 6 largest, Pharma-conflicted and most publicized trials on ivermectin). This was 100% unsurprising.
Check it out:
First, the CCC concluded that your statements about the safety and efficacy of ivermectin and hydroxychloroquine as treatments for COVID-19 are false and inaccurate because they are not supported by factual, scientifically grounded, and consensus driven scientific evidence (there it is again).
Susanna Naggie, M.D., M.H.S., et al., “Effect of Ivermectin vs Placebo on Time to Sustained Recovery in Outpatients With Mild to Moderate COVID-19,” 328 JAMA 1721 (2022), https://www.nejm.org/doi/full/10.1056/nejmoa2115869 (finding in a double-blind, randomized, placebo-controlled study with 1,800 participants that “[a]mong outpatients with mild to moderate COVID-19, treatment with ivermectin, compared with placebo, did not significantly improve time to recovery,” and that “[t]hese findings do not support the use of ivermectin in patients with mild to moderate COVID-19”);
I laughed out loud when they led their argument with the Naggie trial funded by the NIH as it contained the most brazen fraud of the Big 6 Pharma Ivermectin trials. All you need to know about the trial is that they moved the primary comparison endpoint of the trial.. in the middle of the trial. They moved the main comparison from symptoms at Day 14 to Day 28. Note that changing endpoints in the middle of a trial is a supposed never event. Except the same trick was pulled in the Remdesivir trial.
Anyway, in a presentation by Naggie, in this secondary endpoint, you can see that ivermectin was superior at Day 14 to a high degree of Bayesian “statistical significance” but the “statistical significance” was not reached at Day 28 (I use quotes around statistical significance because it is an erroneous concept when doing Bayesian statistics but that is what they did anyway when they pre-specified a threshold of above 0.95 as “significant”). Can anyone tell me why they moved the endpoint to Day 28 in the middle of the trial:
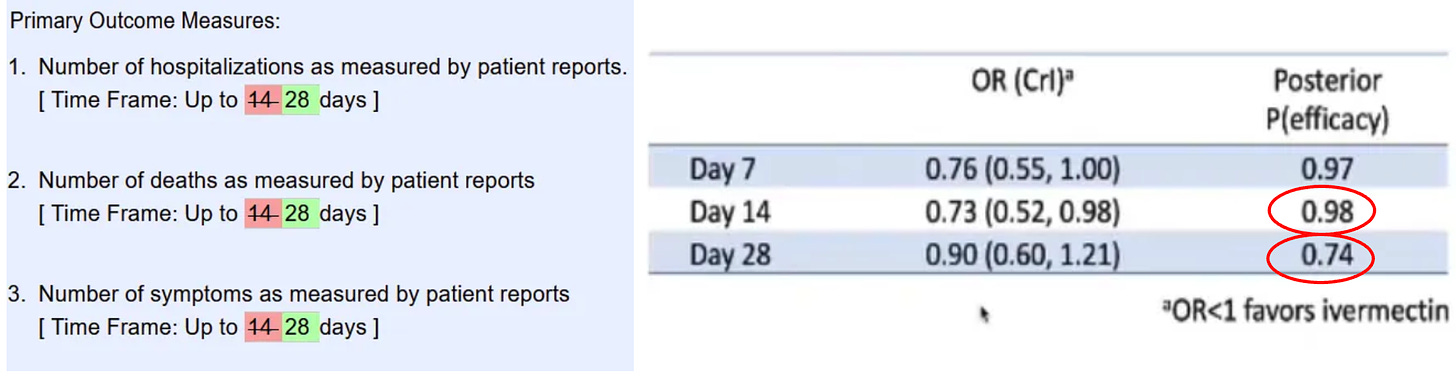
With this brazen maneuver (and many others) it allowed Naggie et al to publish this conclusion: “these findings do not support the use of ivermectin in patients with mild to moderate COVID-19.” Not-so-fun fact: Naggie also sat on the NIH covid treatment guidelines committee where she voted to not recommend ivermectin right before she and her University received tens of millions.. to study ivermectin in Covid. You want more? She also owns stock in a competitor to ivermectin (monoclonal antibodies for Omicron) and has received money from numerous other Big Pharma companies including Gilead. Lets get back to the letter…
Rather, the CCC seeks to accomplish precisely what you assert ABIM should be doing: seeking to “further the professional integrity of medicine by encouraging evidence-based debate” (emphasis added).
Indeed, as set forth in ABIM’s False or Inaccurate Medical Information policy, physicians have an ethical and professional responsibility to provide factual, scientifically grounded, and consensus driven scientific evidence (there it is again). As discussed above, by touting the effectiveness of ivermectin and hydroxychloroquine as COVID-19 treatments and casting doubt on the efficacy and safety of COVID-19 vaccines with such seemingly authoritative statements, you have made statements that are inimical to ABIM’s ethics and professionalism standards for board certification.
In light of all the evidence and circumstances, the CCC determined to recommend that your board certification be revoked.
There is only one silver lining here. One – the impending loss of my certifications does not affect me materially because I have a private fee-based practice due to my need for complete autonomy and lack of restrictions in empirically treating the vaccine injured with various repurposed and alternative therapeutics. I thus cannot and will not accept insurance, and secondly, my academic career is over – no longer will I ever enter back into the system of medicine.
About the only opportunity this whole attack has created is one where I get to defend myself on appeal in a debate with three academic white coats of their choosing. Bring. It. On.
Although the outcome of the debate is assuredly pre-determined, I know it will satisfy a deep yearning many of us dissidents have had for going on 3 years now – to debate someone, anyone, anywhere. Crush them with data. Make ‘em look silly although I will be the only one who knows it happened. It will let me vent my disgust at how they have widely disseminated corrupted scientific evidence and policies while simultaneously ignoring the clinical observations and expertise of frontline doctors who have treated thousands of actual Covid patients.
I will then toss in a little lecture about how RCT’s have long ceased to be a credible means of proving anything in science given that in modern medicine only “Big RCT’s” count and that all “Big RCT’s” require such massive funding that the bias of the funders outweighs any objectivity such trials can profess to attain. I will also remind them that throughout modern medical history, the findings of RCT’s and retrospective observational trials are identical, yet academia has been taught to systematically ignore observational trials. Reason: only massively funded entities can conduct a “Big RCT” while any committed clinician willing to give up nights and weekends can conduct an observational trial. Pharma cannot allow research to be conducted that they have no control over – so they took over the journals and medical school curriculums which now literally teach that observational controlled trials can only be considered “hypothesis generating” and thus their results should not be acted on. Nonsense.
I will also remind them that they are violating international law and human, civil, and political rights as argued by Meryl Nass in another of her excellent posts regarding her own persecution by her state licensing Board:
International law is on our side. A total of 172 countries are parties to the International Covenant on Civil and Political Rights:
According to the 1948 Universal Declaration of Human Rights, Article 19,
“Everyone has the right to freedom of opinion and expression; this right includes freedom to hold opinions without interference and to seek, receive and impart information and ideas through any media and regardless of frontiers.”
According to the 1966 International Covenant on Civil and Political Rights,
“Everyone shall have the right to freedom of expression; this right shall include freedom to seek, receive and impart information and ideas of all kinds, regardless of frontiers, either orally, in writing or in print, in the form of art, or through any other media of his choice.”
And the Nebraska Attorney General protected doctors and pharmacists in Nebraska from their Boards, explicitly allowing them to prescribe HCQ and IVM. His opinion is a tour de force, which goes into detail about why the CDC, FDA and NIH guidelines are contradictory, unscientific and should not be followed. It should be cited in every case.
I also plan on reminding them that the FDA got its ass handed to them in court last week during a hearing of Paul Marik, Mary Tally Bowden and Robert Apter’s suit against the FDA. From an Epoch Times article on the hearing:
“FDA explicitly recognizes that doctors do have the authority to prescribe ivermectin to treat COVID,” Ashley Cheung Honold, a Department of Justice lawyer representing the FDA, said during oral arguments on Aug. 8 in the U.S. Court of Appeals for the 5th Circuit.
The statements “don’t prohibit doctors from prescribing ivermectin to treat COVID or for any other purpose” Ms. Honold said.
“FDA is clearly acknowledging that doctors have the authority to prescribe human ivermectin to treat COVID. So they are not interfering with the authority of doctors to prescribe drugs or to practice medicine,” she said.
So, if the FDA recognizes we have the authority to prescribe ivermectin, then assuredly we are allowed to have the opinion that it is a valid therapy. However, the ABIM will not allow an ABIM certified physician to publicly express this opinion or recommend this practice. Maybe the ABIM should have a little chat with the FDA?
The nonsense doesn’t end with the ABIM, as they are only one prong of this campaign. How is this for some comic relief, published last week in one of the top journals in the world where they found that almost all the Covid misinformation in the U.S on social media can be traced to 52 doctors.

I was honored to discover that yours truly made the list! In their quoted examples of misinformation in Table 4, I have taken the liberty of owning up to the posts attributed to me, all of which I stand by to this day:
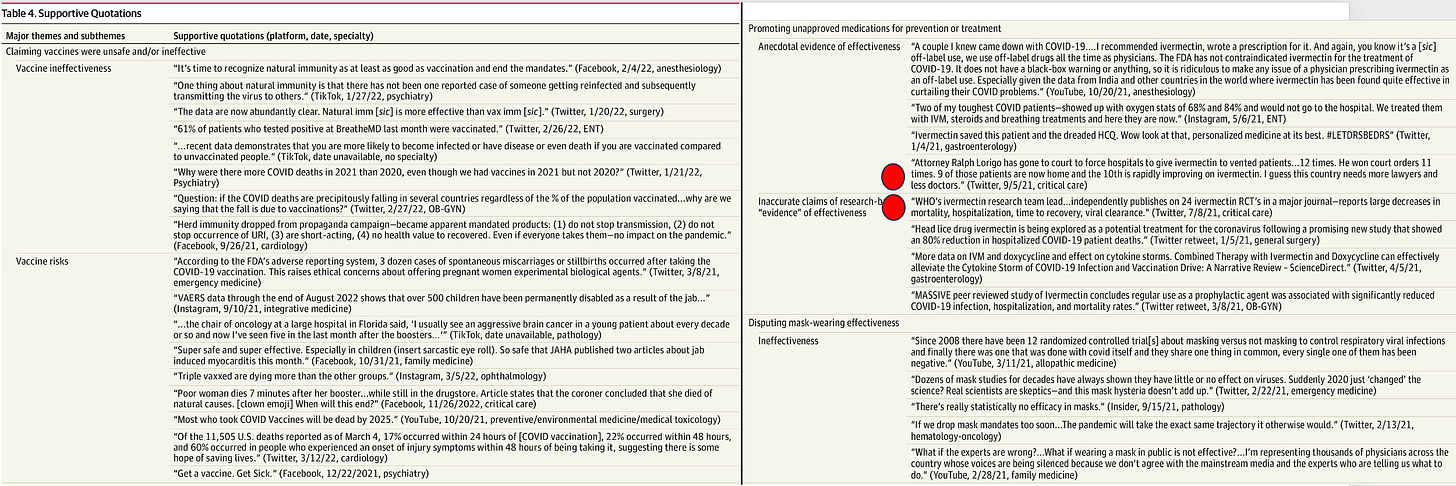

I think I will finish with this excerpt from a recent Wall Street Journal op-ed touching on the Missouri vs. Biden case where the administration is being sued for its systematic censoring of U.S citizens on social media by every intelligence and health agency in our Federal government :
This is where the decision of U.S. District Judge Terry Doughty sheds light. His detailed recounting shows a Washington energetic in protecting Americans from Covid opinions, expertise and claims that conflicted with its own, at a time when it served politicians to show they were trying to save Americans from encountering a virus that couldn’t be avoided. When government has a message to deliver, especially when the political stakes are high, it won’t be content just to push its own message, it will try to silence others. Fighting back will always be necessary. The only surprise in our age is how thoroughly the “liberal” position has become the pro-censorship position (that last line is a doozy).
New Memos Hint at Biden’s Personal Interest in Firing Ukraine Prosecutor Targeting Burisma
By Ekaterina Blinova – Sputnik – 22.08.2023
New memos indicate that then-Vice President Joe Biden did not act in concert with the US government when he threatened to withhold $1 billion in Ukraine aid unless the Poroshenko government fired the prosecutor general who targeted Hunter Biden’s Ukrainian employer at that time.
Joe Biden and Democrats have repeatedly stressed that his insistence on firing Ukrainian then-Prosecutor General Viktor Shokhin back in December 2015 was consistent with the US policy of stamping out corruption in Ukraine.
At the time, then-Vice President Joe Biden even went so far as to threaten then-Ukrainian President Petro Poroshenko that Washington would deprive Ukraine of a much-needed $1 billion loan guarantee in case the latter did not fire Shokhin. The conversation reportedly occurred in December 2015. Biden openly bragged about the incident to the Council on Foreign Relations gathering in January 2018:
“I said, ‘You’re not getting the billion.’ I’m going to be leaving here in, I think it was about six hours. I looked at them and said: ‘I’m leaving in six hours. If the prosecutor is not fired, you’re not getting the money.’ Well, son of a bitch, he got fired. And they put in place someone who was solid at the time.”
However, memos by Treasury and Justice Department officials obtained by Just the News, an independent US media outlet founded by award-winning investigative journalist John Solomon, indicate that the US government held Shokhin in high regard at the time and concluded that Ukraine had made progress in fighting endemic corruption, thus deserving the loan guarantee.
“Ukraine has made sufficient progress on its reform agenda to justify a third guarantee,” read an October 1, 2015, memo by the Interagency Policy Committee (IPC), a Barack Obama task force.
Moreover, Senior State Department officials sent Shokhin a personal note saying they were “impressed” with his office’s work and invited him and his staff to Washington for a January 2016 strategy session prior to his sacking.
Remarkably, an audio tape from March 2016 which appeared to record Biden and Poroshenko’s conversation showed that the Ukrainian president pointed out that there was no evidence that Shokhin and his office were anyhow mired in corruption:
“Despite the fact that we didn’t have any corruption charges, we don’t have any information about him doing something wrong, I especially asked him … No, it was the day before yesterday. I especially asked him to resign,” Poroshenko allegedly told Biden in a tape released in 2020 by then-parliamentarian Andrii Derkach.”
Per Solomon, Biden’s political maneuver stemmed from the fact that the latter had been aggressively investigating Burisma Holdings, a Ukrainian gas firm that hired Joe’s son Hunter in 2014 and paid him a hefty salary of $83,333 a month despite Hunter having no expertise or experience in the energy sphere.
What’s more, Hunter’s business associate Devon Archer, who was also employed by Burisma at the time, testified to the House Oversight Committee on July 31 that Shokhin’s investigation was rattling the Ukrainian gas firm and that the Burisma leadership was putting pressure on Hunter to deal with it.
Joe Biden’s role in firing Shokhin created much controversy in 2019, when House Democrats pushed ahead with the impeachment of then-President Donald Trump who asked Poroshenko’s successor, Volodymyr Zelensky, to look into the Bidens’ conduct in a phone conversation.
Democratic lawmakers and officials testified during Trump’s first impeachment that Joe’s actions in withholding the $1 billion in aid had nothing to do with Hunter and were thoroughly consistent with the US government’s Ukraine policy. Per Solomon, this narrative appears to be false.
The US investigative journalist specifically quoted lawyers who worked on Trump’s impeachment defense. They said that they didn’t have access to the memos unearthed by Just the News, showing that the Obama government was satisfied with Shokhin’s work. As per Trump’s former legal team, the documents in question would have made a significant difference to the Trump impeachment case.
The Democratic Party’s apparent attempts to shield Biden, who announced his presidential bid on April 25, 2019, seemingly fit into a broader set of actions by US officials, Biden campaign aides, intelligence operatives, Big Tech and Big Media to suppress any narrative which could cast a shadow on the Bidens’ conduct.
In October 2020, a concerted action by the former top brass of US intelligence agencies, Silicon Valley giants and the US mainstream press smeared a legitimate story by the New York Post stemming from files of a so-called “laptop from hell”, belonging to Hunter Biden, as “Russian disinformation”. It turned out later that the damning materials on the infamous laptop were genuine.
Eris vaccine marketing hits Germany, complete with panic about a nonexistent August “Covid wave”
eugyppius: a plague chronicle | August 20, 2023
We will not be free of the virus until we are free of the vaccinators.
The leftist taz newspaper on 17 August: New German Wave: The new Covid variant Eris has arrived in Germany. Concerns about a new wave are growing – but the country is not well prepared.
The pandemic is over, but the virus is still dangerous: Reports of the new variant EG.5.1. seem to confirm this analysis. EG.5.1. (Eris) has been considered a “variant of interest” since 9 August. According to the WHO, the phenotype does not differ fundamentally from other Omicron lineages and does not require special public health measures …
With the announced end of the pandemic, virtually all mandated protective measures have been lifted in Germany. The most important instrument in the fight against Covid-19 is thus the immunisation of the population through infection or vaccination.
Das Erste, state media, on 19 August: Covid Variant “Eris”: How Dangerous is the New Mutation EG.5?
The World Health Organisation WHO has upgraded the new Covid mutationEG.5. This variant, called “Eris,” now belongs to the “variants of interest.” …
As WHO Covid expert Maria Van Kerkhove explained in Geneva on Wednesday, more severe outcomes have not been observed with Eris, but vaccination confers less protection than with other virus variants. …
Even though the new variant is unlikely to cause severe disease, the [German vaccine regulatory authority] STIKO still recommends getting vaccinated – above all to avoid possible long-term consequences of SARS-CoV-2 infection and to protect employees in medical and nursing care.
n-tv, a subsidiary broadcaster of RTL, on 18 August: The Number of Coivd-19-Cases Continues to Rise.
The pharmaceutical company Moderna has announced that its updated Covid vaccine according to an initial study is effective against the Eris sub-variant. The company now expects to launch the new vaccine in time for the autumn vaccination season. Approval from vaccine regulators however is still pending.
Moderna, like vaccine manufacturers Novavax and Pfizer, has developed versions of its vaccines with Biontech SE that target Eris subvariants. Shortly before, the pharmaceutical company Pfizer had reported that its revised vaccine had been effective against Eris in a study with mice. …
Most recently, it was suspected that the cinema hype surrounding the feel-good film “Barbie” and the gloomy biopic “Oppenheimer” may have caused many infections. At the same time, the Robert Koch Institute (RKI) recorded an increase in the number of reported Covid infections. Experts, however, see no reason for concern so far.
Frankfurter Rundschau, a regional Frankfurt paper, on 17 August: Covid comeback with “Eris”: First experts demand return to masking.
Is Covid on the attack again? There are indications that the virus is once on the rise once more. …
British doctors are already calling for a return to masking. [Relentless virus charlatan and deranged hypermasker] Trisha Greenhalgh suggests that, “in view of the spread of new variants,” masking in high-risk situations should be considered.
The [virus surveillance] of the Federal Ministry of Health shows that the numbers are also on the rise in Germany. … “Eris” is already responsible for every fourth corona infection, according to new figures from the RKI. “The number of Covid-19 cases reported to the RKI .. seems to be related to the increasing circulation of this ‘variant of interest’,” the Robert Koch Institute says.
The increase in the case numbers – at least in Great Britain – coincides with the opening of the blockbusters “Barbie” and “Oppenheimer” in British cinemas, which has given rise to talk of the “Barbenheimer” phenomenon. It is well known that larger crowds in enclosed indoor spaces are associated with an increased risk of corona infection. So is it time for a mask renaissance?
In the USA, more and more voices calling for one. [Relentless virus pest] Eric Feigl-Ding … used the hashtag #MaskUp on Twitter to call once again for protecting oneself from Covid infections with masks. Health Minister Karl Lauterbach shared the post, warning that the latest Covid data from New York is “worrying.” …
“There is still a risk that a more dangerous variant will emerge, which could lead to a sudden increase in cases and deaths,” emphasises WHO Director-General Tedros Adhanom Ghebreyesus. Not only adapted vaccines that take the new variants into account, but also wearing a mask would then help to protect oneself and others, Frankfurt virologist Martin Stürmer told Spiegel.
tagesschau, state media, on 17 August: Covid Case Numbers are Rising Again.
The number of laboratory-confirmed Corona cases in Germany is rising again – but at a relatively low level. This development has been ongoing for around a month, reports the Influenza Working Group at the Robert Koch Institute (RKI) … According to the report, about 2,400 confirmed cases of Covid-19 were reported nationwide last week. This is more than double the number reported in the week ending 9 July, when there were about 1,000. …
According to the RKI report, the activity of acute respiratory diseases in general in the population was “at a low summer level.” … “Anyone with symptoms of an acute respiratory infection should stay at home for three to five days and until the symptoms have clearly improved,” advises the RKI. …
Despite all of this obnoxious verbiage, absolutely nothing of virological note is happening in Germany. Official Covid testing has been all but abolished here, forcing our journaloids to unearth statistics from RKI influenza surveillance – something they refused to do during the pandemic itself, because the flu people routinely posted data that undermined their panic narrative. Here, I’ve circled in red the scary rise in infections from the latest RKI report that we’re meant to be worried about:
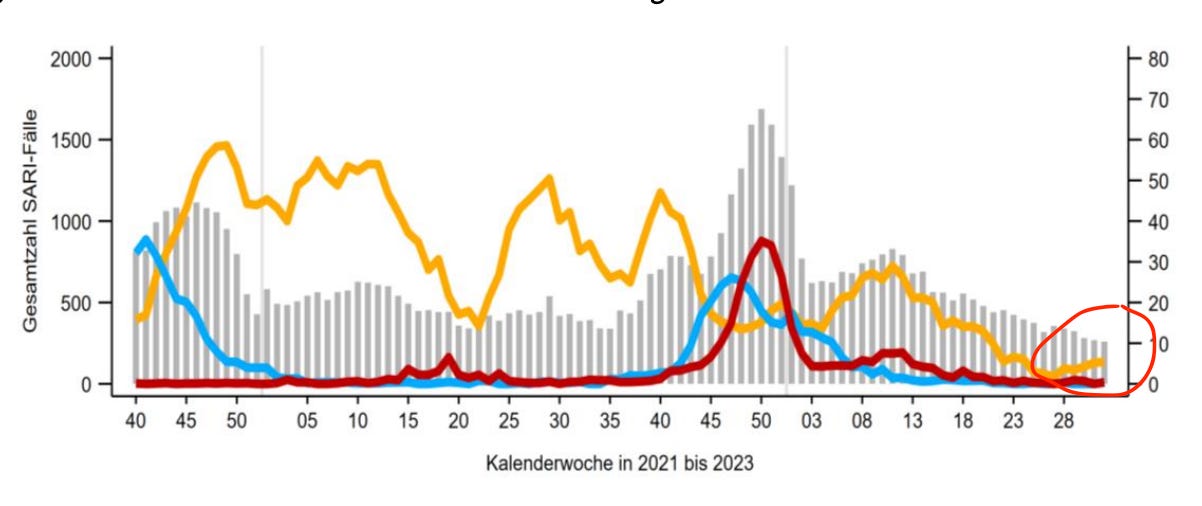
This microscopic uptick is dwarfed by the February/March wave that peaked between weeks 8 and 13. Our media luminaries took next to no notice of this frightening late-winter surge, and as I type this, Covid diagnoses have not even re-achieved their June levels. The difference between the state of things now and the state of things in February is not the unremarkable Eris variant. XBB was also debuting across Europe early this year, driving the post-February case peak, and nobody cared. The only thing that is different now, is the proximity of the autumnal vaccination liturgy and the prospect of new, updated vaccines from Pfizer/BioNTech, Moderna and Novavax. That is why we are hearing about variants and masks and Long Covid all over again. It is also why many of these articles contain buried within them somewhere the advice to line up for the shiny new anti-Covid juice this Fall. This whole thing is, very plainly, a psy-op, if a very low-effort one.
There are several patterns in the German reporting that are worth noting. First of all, the latest hysteria was unleashed on 17 August, prompted by a report on Eris from the German news agency Deutsche Presse-Agentur. Particularly in the realm of routine reporting, the news agencies are a powerful coordinating force, and their influence here means that the full media panic machine is not engaged. We’re looking instead at pieces thrown together by low-level staff desperate to fill column inches. Second, all the German stories are firmly downstream from Anglophone sources, going so far as to recycle from British tabloids the improbable theory of a “Barbenheimer” wave (it is painful even to type this stupid word). Third, at least German health authorities – Karl Lauterbach excepted – resolutely refuse to provide virus doom quotes. Thus the Frankfurter Rundschau had to appropriate the tweets of Anglosphere mask hysterics like Greenhalgh and Feigl-Ding to make Eris sound scary.
I know there are rumours that American authorities are planning to bring back mask mandates and other restrictions in the coming months, and I’ll be honest: We should be so lucky. If the pandemicists try to kick up another round of non-pharmaceutical interventions this fall, they’ll be flirting with self destruction. There are important prerequisites for virus panic: You need a plausibly novel pathogen, the risk of which can be exaggerated. You need a prevailing sense of stability, with nothing else much going on, because the public health interventions themselves have to seem new. Risk, excitement and the prospect of a break from routine are important enticements. That’s all gone now. Covid is not a new scary virus anymore; nearly everyone has had personal experience with it. Solid majorities everywhere have learned to hate lockdowns, despise masking and avoid the mRNA vaccines. The pandemicists need a plausibly new virus to reopen the circus, and they need a lot of people to forget about what a misery the last pandemic response was. They’ll have another chance in ten or fifteen years, I’d guess. Then, it’ll be time to worry.
Featured Video

Thomas Fazi: NATO’s Hybrid Warfare – Deception & Permanent War
or go to
Aletho News Archives – Video-Images
Book Review
The Zeolite Book — First Edition, 2026, Paperback
The volcanic mineral medicine will not patent — for the toxic burden medicine will not name
Lies are Unbekoming – October 30, 2026
 Zeolite is old. It is in Roman concrete that has held for two thousand years. It’s in the water filters of ancient cisterns. It’s in the stomachs of Pacific livestock whose keepers knew, somehow, that this grey crumbling rock made the animals healthier. It’s in Soviet clinical protocols from the 1960s. It’s in the standard emergency response to the Chernobyl explosion.
In 1986, after the Chernobyl reactor failure, the Soviet Union manufactured and distributed natural zeolite at industrial scale — for soil remediation, for livestock feed, for human consumption, for the cleanup itself. Karl Hecht, who had been director of the Institute for Experimental and Clinical Pathophysiology at the Charité of Humboldt University Berlin, spent the six decades after that building the clinical research base — on silicon’s role in human health, on zeolite’s clinical safety, on its applications in ageing. In 2018, Pavelić and colleagues published a comprehensive clinical safety review of natural clinoptilolite in Frontiers in Pharmacology. In 2019, Mastinu analysed its binding affinities. In the Western medical literature, these works sit largely uncited.
What has not been treated at book length, until now, is how a volcanic mineral with six decades of Soviet clinical work behind it, two major peer-reviewed Western reviews, and ongoing clinical use across the former Eastern Bloc, remains almost entirely absent from Western medical practice — and what the toxic burden it’s meant to address actually is.
The Zeolite Book gathers the Soviet clinical record, the Western peer-reviewed studies, three contemporary practitioner voices, and three serious counterviews into one honest treatment. That’s why the book runs to seven appendices. 288 pages, four parts, three practitioner voices, three counterviews, seven appendices. The honest treatment is the argument.
Blog Roll
 Aletho News
- They Compared the Spice to the Drug. The Spice Won — Again. (Part 2)
- Thomas Fazi: NATO’s Hybrid Warfare – Deception & Permanent War
- Wrong, AP and NPR: Europe’s 50,000 Heat Deaths Are a Computer-Model Estimate, Not a Real Body Count
- Questioning Your Doctor Is Now Considered A Psychological Problem (Seriously)
- London tourism expo promotes Israeli agency linked to theft of Palestinian land
- Dockworkers launch global strike against Israeli and US military shipments
- Europe facing gas price shock – Gazprom chief
- Ukraine continues recruiting people with disabilities
- Weaponized Journalism: 2021 Sayer Ji Interview with NPR
- Beyond Netanyahu: what Israel’s election means for Palestinians
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!

