The Nudge: Ethically Dubious and Ineffective
BY GARY SIDLEY | BROWNSTONE INSTITUTE | MARCH 1, 2022
More and more people in the US will be wising up to their government’s use of behavioural science – or ‘nudging’ – as a means of increasing compliance with Covid-19 restrictions. These psychological techniques exploit the fact that human beings are almost always on ‘automatic pilot,’ habitually making moment-by-moment decisions without rational thought or conscious reflection.
The use of behavioural science in this way represents a radical departure from the traditional methods – legislation, information provision, rational argument – used by governments to influence the behaviour of their citizens. But why expend all that time and energy when, by contrast, many of the ‘nudges’ delivered are – to various degrees – acting upon the public automatically, below the level of conscious thought and reason?
By going with the grain of how we think and act, the state-employed ‘nudgers’ can covertly shape our behaviour in a direction deemed desirable by the regime of the day – an appealing prospect for any government. The ubiquitous deployment of these behavioural strategies – which frequently rely on inflating emotional distress to change behaviour – raises profound moral questions.
The UK has been an innovator in these methods, but they are now raising widespread disquiet here. In fact serious concerns about our Government’s use of behavioural science were previously raised in relation to other spheres of government activity. In 2019, a Parliamentary report found that the distress evoked in people targeted by behavioural insights in relation to tax collection may, in some instances, have led to victims taking their own lives.
In the Covid-19 era, it appears the behavioural scientists have been given free reign. As a retired consultant clinical psychologist, I – and 39 professionals from the psychology/therapy/mental health sphere – have become so concerned we are calling on the UK Parliament to formally investigate the government’s use of behavioural science. People across the world can glean from the UK experience what may also have been done to them, and what may be next.
The Behavioural Insights Team
The appetite for using covert psychological strategies as a means of changing people’s behaviour was boosted by the emergence of the ‘Behavioural Insights Team’ (BIT) in 2010 as ‘the world’s first government institution dedicated to the application of behavioural science to policy.’ The membership of BIT rapidly expanded from a seven-person unit embedded in the UK Government to a ‘social purpose company’ operating in many countries across the world. A comprehensive account of the psychological techniques recommended by the BIT is provided in the document, MINDSPACE: Influencing behaviour through public policy, where the authors claim that their strategies can achieve ‘low cost, low pain ways of nudging citizens … into new ways of acting by going with the grain of how we think and act.’
Since its inception in 2010, the BIT has been led by Professor David Halpern who is currently the team’s chief executive. Professor Halpern and two other members of the BIT also currently sit on the Scientific Pandemic Insights Group on Behaviours (SPI-B), which advises the Government on its Covid-19 communications strategy. Most of the other members of the SPI-B are prominent UK psychologists who have expertise in the deployment of behavioural-science ‘nudge’ techniques.
‘Nudges’ of concern: fear inflation, shaming, peer pressure
The BIT and the SPI-B have encouraged the deployment of many techniques from behavioural science within the UK Government’s Covid-19 communications. However, there are three ‘nudges’ which have evoked most alarm: the exploitation of fear (inflating perceived threat levels), shame (conflating compliance with virtue) and peer pressure (portraying non-compliers as a deviant minority) – or “affect,” “ego” and “norms,” to use the language of the MINDSPACE document.
Affect and Fear
Aware that a frightened population is a compliant one, a strategic decision was made to inflate the fear levels of all the UK people. The minutes of the SPI-B meeting dated the 22nd of March 2020 stated, ‘The perceived level of personal threat needs to be increased among those who are complacent’ by ‘using hard-hitting emotional messaging.’ Subsequently, in tandem with the UK’s subservient mainstream media, the collective efforts of the BIT and the SPI-B have inflicted a prolonged and concerted scare campaign upon the UK public. The methods used have included:
– Daily statistics displayed without context: the macabre mono focus on showing the number of Covid-19 deaths without mention of mortality from other causes or the fact that, under normal circumstances, around 1,600 people die each day in the UK.
– Recurrent footage of dying patients: images of the acutely unwell in Intensive Care Units.
– Scary slogans: for example, ‘IF YOU GO OUT YOU CAN SPREAD IT, PEOPLE WILL DIE,’ typically accompanied by frightening images of emergency personnel in masks and visors.
Ego and Shame
We all strive to maintain a positive view of ourselves. Utilising this human tendency, behavioural scientists have recommended messaging that equates virtue with adherence to the Covid-19 restrictions and subsequent vaccination campaign. Consequently, following the rules preserves the integrity of our egos while any deviation evokes shame. Examples of these nudges in action include:
– Slogans that shame the non-compliant: for example, ‘STAY HOME, PROTECT THE NHS, SAVE LIVES.’
– TV advertisements: actors tell us, ‘I wear a face covering to protect my mates’ and ‘I make space to protect you.’
– Clap for Careers: the pre-orchestrated weekly ritual, purportedly to show appreciation for NHS staff.
– Ministers telling students not to ‘kill your gran.’
– Shame-evoking adverts: close-up images of acutely unwell hospital patients with the voice-over, ‘Can you look them in the eyes and tell them you’re doing all you can to stop the spread of coronavirus?’
Norms and Peer Pressure
Awareness of the prevalent views and behaviour of our fellow citizens can pressurise us to conform, and knowledge of being in a deviant minority is a source of discomfort. The UK Government repeatedly encouraged peer pressure throughout the Covid-19 crisis to gain the public’s compliance with their escalating restrictions, an approach that – at higher levels of intensity – can morph into scapegoating.
The most straightforward example is how, during interviews with the media, Government ministers often resorted to telling us that the vast majority of people were ‘obeying the rules’ or that almost all of us were conforming.
However, in order to enhance and sustain normative pressure, people need to be able to instantly distinguish the rule breakers from the rule followers; the visibility of face coverings provides this immediate differentiation. The switch to the mandating of masks in community settings in summer 2020, without the emergence of new and robust evidence that they reduce viral transmission, strongly suggests that the mask requirement was introduced primarily as a compliance device to harness normative pressure.
Ethical questions
Compared to a government’s typical tools of persuasion, the covert psychological strategies outlined above differ in both their nature and subconscious mode of action. Consequently, there are three main areas of ethical concern associated with their use: problems with the methods per se; problems with the lack of consent; and problems with the goals to which they are applied.
First, it is highly questionable whether a civilised society should knowingly increase the emotional discomfort of its citizens as a means of gaining their compliance. Government scientists deploying fear, shame, and scapegoating to change minds is an ethically dubious practice that in some respects resembles the tactics used by totalitarian regimes such as China, where the state inflicts pain on a subset of its population in an attempt to eliminate beliefs and behavior they perceive to be deviant.
Another ethical issue associated with these covert psychological techniques relates to their unintended consequences. Shaming and scapegoating have emboldened some people to harass those unable or unwilling to wear a face covering. More disturbingly, the inflated fear levels will have significantly contributed to the many thousands of excess non-Covid deaths that have occurred in people’s homes, the strategically-increased anxieties discouraging many from seeking help for other illnesses.
Furthermore, a lot of older people, rendered housebound by fear, may have died prematurely from loneliness. Those already suffering with obsessive-compulsive problems about contamination, and patients with severe health anxieties, will have had their anguish exacerbated by the campaign of fear. Even now, after all the vulnerable groups in the UK have been offered vaccination, many of our citizens remain tormented by ‘COVID-19 Anxiety Syndrome’), characterised by a disabling combination of fear and maladaptive coping strategies.
Second, a recipient’s consent prior to the delivery of a medical or psychological intervention is a fundamental requirement of a civilised society. Professor David Halpern explicitly recognised the significant ethical dilemmas arising from the use of influencing strategies that impact subconsciously on the country’s citizens. The MINDSPACE document – of which Professor Halpern is a co-author – states that, ‘Policymakers wishing to use these tools … need the approval of the public to do so’ (p74).
More recently, in Professor Halpern’s book, Inside the Nudge Unit, he is even more emphatic about the importance of consent: ‘If Governments … wish to use behavioural insights, they must seek and maintain the permission of the public. Ultimately, you – the public, the citizen – need to decide what the objectives, and limits, of nudging and empirical testing should be’ (p375).
As far as we are aware, no attempt has ever been made to obtain the UK public’s permission to use covert psychological strategies.
Third, the perceived legitimacy of using subconscious ‘nudges’ to influence people may also depend upon the behavioural goals that are being pursued. It may be that a higher proportion of the general public would be comfortable with the government resorting to subconscious nudges to reduce violent crime as compared to the purpose of imposing unprecedented and non-evidenced public-health restrictions. Would UK citizens have agreed to the furtive deployment of fear, shame and peer pressure as a way of levering compliance with lockdowns, mask mandates and vaccination? Maybe they should be asked before the government considers any future imposition of these techniques.
A truly independent and comprehensive evaluation of the ethics of deploying psychological ‘nudges’ – during public health campaigns and in other areas of government – is now urgently required, not only in Britain, but in all countries where these interventions have been used.
Dr Gary Sidley is a retired consultant clinical psychologist who worked in the UK’s National Health Service for over 30 years, a member of HART Group and a founder member of the Smile Free campaign against forced masking.
Backed by Big Pharma, NewsGuard Brings ‘Fact Checking’ to Tens of Millions of Kids in Schools
By Michael Nevradakis, Ph.D. | The Defender | February 28, 2022
The American Federation of Teachers (AFT) is partnering with NewsGuard — a for-profit “fact-checking” company with deep ties to Big Pharma — to help students in U.S. classrooms “navigate a sea of online disinformation.”
AFT is the second-largest teachers’ union in the U.S. It’s also a staunch advocate of mandatory COVID vaccination and masks for schoolchildren.
Under a deal announced last month, AFT agreed to purchase NewsGuard licenses for its entire membership of teachers — 1.7 million in total — making the NewsGuard tool available to tens of millions of public school students and their families.
Teachers will receive licensed copies of NewsGuard’s internet browser extension, providing access to its “traffic light” ratings and “nutrition label” reviews evaluating the purported reliability of news and information websites when those sites are visited.
Announced during “News Literacy Week,” AFT touted the agreement as an opportunity for its member teachers to play a bigger role in helping their students “navigate a sea of online disinformation.”
AFT stated:
“For years, educators have fought battles against suspect sourcing, with their students often misled by dubious outlets and spam sites posing as ‘news’. NewsGuard offers a practical solution, alerting students and educators to those sites while also providing a valuable lesson in media literacy.
“Students and their teachers will be able to see how NewsGuard applies nine criteria of journalistic practice to thousands of websites and will get an immediate read on the truthfulness and rigor of the information they encounter when searching online.”
Randi Weingarten, president of AFT, added:
“We are constantly trying to help our students, particularly our middle, high school and post-secondary students, separate fact from fiction, as we help them develop their critical-thinking and analytical skills.
“NewsGuard is a great tool in this regard. It is a beacon of clarity to expose the dark depths of the internet and uplift those outlets committed to truth and honesty rather than falsehoods and fabrications. This historic deal will not only help us steer clear of increasingly fetid waters—it will provide a valuable lesson in media literacy and a discussion point for teachers in class on what can, and can’t, be trusted.
“The hallmark of good journalism is fair, richly sourced reporting that gives citizens an insight into how the world works. Sadly, the foundational role of the fourth estate is in danger of being poisoned by torrents of trash. NewsGuard reminds us of the importance of an independent press that students can rely on to form their own views and opinions so they can participate as active citizens in our democracy.”
Axios described the deal as one in which American schoolchildren are getting “an internet librarian,” adding that “[t]he hope is that students with the skills to spot disinformation will grow into more thoughtful and better-informed citizens and voters.”
Drawing on the library analogy, NewsGuard stated:
“Imagine you walked into a library, and there were a trillion pieces of paper flying around in the air, and you grabbed one, and you didn’t know anything about it, or where it came from or who’s financing it.
“That’s the internet, that’s your Facebook feed, that’s your Google search.”
Helping children become more media literate and better able to spot misinformation online appears, at face value, to be a noble goal.
However, a closer look at NewsGuard’s advisers, partners and investors reveals a web of interests closely linked to the military, intelligence, media and political establishments, as well as to the world of corporate marketing — including an advertising agency sued for illegally marketing opioids.
How does NewsGuard work?
Launched in March 2018 as an effort to “fight fake news,” NewsGuard maintains a database of news and information outlets, which are ranked for their supposed “trustworthiness.”
These rankings then become available to the public via extensions that are available for mainstream browsers such as Google Chrome, Firefox and Microsoft Edge.
Once installed, the browser extension displays green or red warning labels next to a ranked website’s address, indicating whether the site is considered to be “trustworthy” or not.
As of January 2022, NewsGuard had evaluated and ranked 7,466 domains which it claims covers 95% of online news engagement.
Algorithms alone are insufficient for identifying “fake news,” according to NewsGuard:
“Our goal isn’t necessarily to stop [fake news] but to arm people with some basic information when they’re about to read or share stuff,” Brill said. “We’re not trying to block anything.
“Our goal is to help solve this problem now by using human beings—trained, experienced journalists—who will operate under a transparent, accountable process to apply basic common sense to a growing scourge that clearly cannot be solved by algorithms.”
How does this evaluation process take place?
NewsGuard uses nine weighted criteria to rate and analyze news websites along two broad categories: credibility and transparency.
The following five criteria are incorporated into the “credibility” category, listed alongside their respective “weights”:
- Does not repeatedly publish false content (22 points).
- Gathers and presents information responsibly (18 points).
- Regularly corrects or clarifies errors (12.5 points).
- Handles the difference between news and opinion responsibly (12.5 points).
- Avoids deceptive headlines (10 points).
Under the “transparency” category are these four criteria:
- Discloses ownership and financing (7.5 points).
- Clearly labels advertising (7.5 points).
- Reveals who’s in charge, including possible conflicts of interest (5 points).
- Provides the names of content creators, along with either contact or biographical information (5 points).
It is unclear how the respective “weights” were determined and set, or how they are measured.
Connected to these nine criteria, NewsGuard implemented a “Nutrition Label” system, which it uses to rate news sites according to one of four categories: “Green,” “Red,” “Satire” or “Platform.” The corresponding icon then appears in browsers when a rated website is visited.
These categories are connected to the previously mentioned point system, such that sites with a “score” of 60 points or higher earn a “Green” label, while those below 60 points are given a “Red” label.
Specifically:
- A “Green” label indicates the website “generally adheres to basic standards of credibility and transparency.”
- A “Red” label indicates the website “generally fails to meet basic standards of credibility and transparency.”
- Α “Satire” (yellow) label indicates the website is “not a real news website.”
- A “Platform” (gray) label indicates the website “primarily hosts user-generated content that it does not vet” and the information on this site “may or may not be reliable.”
The “Nutrition Labels,” aside from the color-coded system indicated above, also include a more detailed analysis about each news site. As explained by NewsGuard:
“The labels will explain the history of the site, what it attempts to cover, who owns it, who edits it, and make transparent other relevant factors, such as financing, notable awards or missteps, whether the publisher participates in programs such as the Trust Project, which holds publishers to transparency standards, or has repeatedly been found at fault by one of the established programs that check individual articles.”
In other words, there is a direct connection between NewsGuard’s website-level rating system and the various “fact-checking” entities that evaluate the content of individual news stories.
Each website is initially “independently reviewed” by a NewsGuard analyst against the nine criteria. The analyst prepares the “Nutrition Label,” the website is contacted for comment, and then “at least one senior editor and NewsGuard’s co-CEOs review every Nutrition Label prior to publication to ensure that the rating is as fair and accurate as possible.”
In addition to its formal ratings process, a separate NewsGuard “SWAT Team” is “on call on a 24/7 basis to receive and act on alerts about sites that are suddenly trending, but that have not yet been rated — including because the site was just launched to promote a fictitious, sensational story.”
The “SWAT Team” then rates these websites in real time.
NewsGuard also works on social media platforms — specifically, on links to news articles on other websites that are posted on social media.
Additionally, NewsGuard maintains what it calls “advertiser inclusion lists.” As of January, these lists contained 4,247 so-called “quality news sites.” The lists are used to help online advertisers direct their advertising expenditures toward websites NewsGuard deems reliable.
NewsGuard, which received $6 million in seed funding from various investors and venture capitalists, is subscription-based.
A NewsGuard subscription costs $2.95 per month, which includes the browser extension and a mobile app for Android and iOS devices. (The browser extension is available for free on the Microsoft Edge browser, thanks to a licensing agreement with Microsoft).
AFT deal not first time NewsGuard has ventured into education arena
For some, fighting “fake news” on websites and social media isn’t enough — they believe the “battle” needs to reach educational institutions.
As stated in 2019 by Jonathan Anzalone, assistant director and lecturer at Stony Brook University’s Center for News Literacy:
“Our problems are much larger than identifying a bogus website or a piece of propaganda. It’s like we just invented fire, and we’re trying to learn how to deal with it. It will take more than a few tools, as valuable as they may be.”
As a solution, Anzalone recommended “large-scale educational intervention” and “constant reinforcement in class and at home that we have to be critical of the news.”
These calls for “educational intervention” in 2019 perhaps foreshadowed NewsGuard’s later turn toward educational institutions.
NewsGuard’s past educational collaborations may also provide more than a few hints as to the types of learning materials it will provide as part of its new agreement with AFT.
Prior to NewsGuard’s new agreement with AFT, it had maintained a collaboration with Turnitin, a tool commonly used in secondary and higher education to evaluate students’ written assignments and identify possible cases of plagiarism.
NewsGuard’s partnership with TurnItIn, announced May 4, 2020, was touted as an initiative “that will help many million students and teachers spot and avoid misinformation, improve their research abilities and develop critical media literacy skills.”
On its end, Turnitin promoted its collaboration with NewsGuard as a marriage between “academic integrity” and “digital literacy” that would enable students to “navigate 21st-century news with 21st-century skills” and to “imbue [their] work with integrity right from the source.”
Offering NewsGuard through the Turnitin service would allow “students and instructors, writers and researchers [to] confidently discern the legitimacy of digital news and information, using only the sources best suited for their needs.”
Commenting on this partnership in 2020, Crovitz described it as a “perfect match,” and stated:
“From the start, our mission has been to help people tell the difference between trustworthy sources and the many online sources that have hidden agendas, publish misinformation, or exist to promote hoaxes.
“We have heard from many teachers how valuable NewsGuard has been to help students in their research and writing find sources that publish with accuracy and integrity and to stay away from the others. To be able to provide that information to Turnitin’s millions of students and teachers is a tremendously important milestone in advancing that mission.”
Free access to NewsGuard via Turnitin appears to have ended with the conclusion of the 2020-2021 academic year. However, a series of NewsGuard learning materials developed as part of the partnership with Turnitin remain online, and provide a likely indication as to the nature and content of the resources NewsGuard will now make available to schools and teachers as part of its new collaboration with AFT.
These resources, which offer an eye-opening look at how students are instructed to identify so-called “misinformation,” include:
- A NewsGuard lesson plan on the COVID-19 “Infodemic.”
- A guide to Turnitin source credibility and how it can be aligned with NewsGuard lesson plans.
- An implementation guide for school administrators.
- A set of “best practices” for educators about using NewsGuard.
- A student guide for using NewsGuard.
- A complete collection of NewsGuard resources.
The lesson materials for the so-called COVID-19 “Infodemic,” which are targeted primarily to high school students, but also, middle school and university students, include the following statement:
“As misinformation about COVID-19 proliferates online, and as remote learning and social distancing cause students to spend even more of their time on social media and other platforms, media literacy skills have taken on greater importance.
“To address this need, NewsGuard has created a suite of plug-and-play resources for educators to teach a media literacy lesson through the lens of COVID-19 misinformation.”
A set of PowerPoint slides on “Coronavirus Conspiracies & Other Health Hoaxes,” includes a quiz wherein one of the questions asks students to identify which sources they would trust, out of the following list: Medicine-Today.net, MedicineNet.com, Vaccination.co.uk, Patient.info, HealthyChildren.org, and ChildrensHealthDefense.org (the ‘correct’ answers, we are told, are MedicineNet.com, Patient.Info, and HealthyChildren.org).
An accompanying “tip sheet” unironically advises students, educators, and parents to “be suspicious of requests for secrecy or pressure to take action quickly,” and to “teach yourself and your kids to ask the tough questions.”
In turn, the “best practices” recommended by NewsGuard and Turnitin include a suggestion that “students should reference NewsGuard throughout the semester/year,” whenever “they need to do research for a project or paper or any time they need to consult current events.”
As part of this, educators are advised to “have students annotate their bibliographies with explanations for why they selected each source, drawing from NewsGuard’s Nutrition Label reviews to provide evidence for why they deemed certain sources reliable.”
NewsGuard partnerships extend to businesses, ad agencies and the WHO
NewsGuard’s line of products extends beyond its browser extension, “Nutrition Labels,” and educational materials.
For example, it offers a product called “Misinformation Fingerprints,” a “catalog of all the top current hoaxes on the internet.”
According to NewsGuard, the product is “purpose-built for use by both human analysts and AI tools” which “provide a continuously updated view of the digital information environment — and a powerful way to track narratives that are emerging and spreading online,” specifically, the “top misinformation narratives spreading online.”
The users of “Misinformation FIngerprints” include the Pentagon’s Cyber Command and the U.S. State Department’s Global Engagement Center.
For businesses, an “Insights Dashboard” helps clients access NewsGuard’s news reliability ratings and misinformation fingerprints “through a powerful, searchable web interface purpose-built for use by businesses seeking to identify and mitigate risks from misinformation and disinformation.”
“BrandGuard” targets advertisers and advertising agencies. It is touted as “the only humanly generated, constantly updated solution” to help such companies “avoid advertising on misinformation sites while finding valuable new inventory on trustworthy news sites.”
Similarly, NewsGuard’s “HealthGuard” product targets the healthcare industry and global public health authorities.
Described as “a vaccine against medical information,” HealthGuard, we are told, “helps patients, healthcare workers and anyone involved in the medical field identify trustworthy sources of health information — and avoid dangerous misinformation.”
How does HealthGuard purport to accomplish this?
It maintains a set of ratings for more than 3,000 online health information sources, as well as a catalog of “false health narratives — from bogus cancer cures to COVID vaccine myths,” through which it “provides a solution to the “infodemic” of rampant online health misinformation.”
The WHO said it relies on NewsGuard “to fight health hoaxes. Andy Pattison, head of the WHO’s Digital Channels Team, said:
“Though health misinformation circulates online, it causes real life consequences. We must put tools in the hands of people everywhere so they can better assess the credibility of health information online in order to make informed health choices in their life.
“NewsGuard has been instrumental in helping WHO and partners keep people safe by identifying and combating online COVID-19 and vaccine misinformation.”
NewsGuard on Aug. 24, 2020, announced a partnership agreement, “to provide the WHO and the technology platforms that WHO advises on healthcare-related online safety with a variety of reports and data aimed at fighting online COVID-19 misinformation online.”
Dr. Sylvie Brand, director of the WHO’s infectious hazards management department, described the partnership with NewsGuard:
“WHO has been fighting an infodemic of misinformation on multiple fronts, working hand in hand with governments, the private sector and civil society.
“It is vital that people everywhere get the right information at the right time to protect themselves and their loved ones. That’s why we are looking forward to working with NewsGuard and other platforms to fight misinformation and disinformation.”
In turn, NewsGuard claims that, through the provisions of this agreement where it will provide information about health “hoaxes” to social media and search platforms, “digital platforms will finally be able to act before these new myths — whether it’s about a vaccine or another supposed source of the virus—spread on their platforms.”
As it turns out, NewsGuard since 2020 has filed at least 29 such reports with the WHO As described by NewsGuard, these reports have highlighted:
“… trending health hoaxes and conspiracies across Facebook, Instagram, and YouTube, which the WHO has been able to share with digital platforms to alert them to misinformation and hoaxes on their platforms.
“These reports identify large social media pages, accounts, and public and private groups that encourage the spread of false and often dangerous narratives about the virus and vaccines.”
One such report, dated Oct. 28, 2021, is titled “Despite NewsGuard’s prior warnings in reports to the WHO, Facebook and Instagram have allowed known anti-vaccine misinformation superspreaders to flourish on their platforms.
A June 22, 2021 report, “COVID-19 and Vaccine Misinformation Groups and Pages on Facebook” prominently features Children’s Health Defense (CHD), among other pages and groups.
NewsGuard included CHD on its list of websites that spread “vaccine myths,” lamenting that “[s]ome of the websites NewsGuard identified have become more popular online than trustworthy sources of information about COVID-19,” while specifically stating that CHD’s website “has received more engagement … than the CDC and the National Institutes of Health.”
A February 2021 NewsGuard interview with Robert F. Kennedy, Jr. was “annotated in italics in footnote form with fact checks debunking the dozens of arguments Kennedy employed to bolster his false claim that Pfizer and Moderna’s COVID-19 vaccines are dangerous.”
NewsGuard’s involvement in health-related matters also extends to the creation of a “COVID-19 Misinformation Tracking Center,” which “reports on fake news, rumors and bad actors related to the Coronavirus Pandemic.”
What constitutes a “bad actor” does not appear to be defined.
Via this “tracking center,” NewsGuard compiled a list of 53 supposed COVID myths. The list appears in a September 2021 NewsGuard “special report” on “Top COVID-19 vaccine myths.”
In addition to partnering with the WHO, NewsGuard’s HealthGuard partners with the Center for Countering Digital Hate (CCDH).
Described by Mercola as “a progressive cancel-culture leader,” CCDH has “extensive ties to government and global think tanks that has labeled questioning the COVID-19 injection as ‘threats to national security.’”
Who are the people behind NewsGuard?
NewsGuard was founded by two veterans of mainstream journalism: Steven Brill (who previously founded Court TV, the Yale Journalism Initiative and The American Lawyer), and Gordon Crovitz, former publisher of the Wall Street Journal.
When it launched, NewsGuard had a team of 25 professional journalists, purportedly to evaluate the reliability of news sources.
Two other key founding members of NewsGuard, who are still with the company, include James Warren and Eric Effron.
Brill and Crovitz are members of the U.S. Council on Foreign Relations, a highly influential U.S. foreign policy establishment think tank.
This stance is further reflected in the makeup of NewsGuard’s advisory board, which includes a who’s who of individuals from the political, intelligence, Big Tech and media establishments, including:
- Don Baer, who served as White House communications director during the administration of Bill Clinton
- Arne Duncan, who served as Secretary of Education during the administration of Barack Obama.
- (Ret.) General Michael Hayden, former director of the CIA, former director of the NSA, and former Principal Deputy Director of National Intelligence.
- Leo Hindery, Jr., the former chairman of the National Cable Television Association.
- Elise Jordan, a political analyst for NBC News and a former speechwriter for Secretary of State Condoleezza Rice, under the administration of George W. Bus.
- Kate O’Sullivan, general manager for digital diplomacy of Microsoft.
- Anders Fogh Rasmussen, former general secretary of NATO, former prime minister of Denmark, and founder of the Alliance of Democracies Foundation.
- Tom Ridge, the first Secretary of Homeland Security, under the administration of George W. Bush.
- Richard Stengel, former editor of Time Magazine and former Undersecretary of State for Public Diplomacy under the administration of Barack Obama. He is the author of “Information Wars: How We Lost the Global Battle Against Disinformation and What We Can Do About It.”
- Jimmy Wales, co-founder of Wikipedia.
NewsGuard says members of the advisory board play “no role in the determination of ratings or the Nutrition Label[s] … unless otherwise noted” and “have no role in the governance or management of the organization.”
However, members’ association with the military and intelligence community and their connections to major technology companies and media outlets that support COVID measures and mandatory vaccination cannot be overlooked.
Looking at NewsGuard’s team members, similar connections can be made to the media, political and intelligence establishments.
Two team members, Alex Cadier and Amy Westfeldt, have previous “fact-checking” experience. Cadier worked with Agence France-Presse’s AFP Fact Check Service since 2020, with a focus on “COVID-19 vaccine misinformation, 5G conspiracy theories and other myths.”
Westfeldt produced The Associated Press’ first fact checks, soon after the 2016 U.S. presidential election, in conjunction with Facebook. She also founded the “Not Real News” fixture.
Two other team members, Nerissa Beekharry and Cynthia Brill, were previously associated with Verified Identity Pass, operator of the Clear Pass for airport security checkpoints.
And at least two team members, Sam Howard and Sruthi Palaniappan, were involved in presidential campaigns: Howard with the Obama 2012 campaign and Palaniappan with Hillary Clinton’s campaign in 2016, the same year he was a delegate at the Democratic National Convention .
NewsGuard’s partnerships also reflect an affinity for entities associated with Big Tech, the military and intelligence establishments and government more broadly — even as a private initiative.
For example, NewsGuard partners include:
- Microsoft (including Microsoft Bing, Microsoft Edge, Microsoft Education and MSN).
- The WHO.
- The U.S. Department of Defense and the U.S. State Department.
- The U.S. National Security Innovation Network.
- The UK’s Department for Digital, Culture, Media and Sport.
- The News Media Alliance (a U.S.-Canada newspaper trade association).
- The German Marshall Fund of the United States.
- GumGum (a “contextual intelligence” company).
- Dartmouth University, Northeastern University and the University of Michigan.
- Advertising and marketing firms such as IPG, Peer39, TripleLift and the Publicis Groupe.
Backed by Big Pharma?
As mentioned above, NewsGuard received approximately $6 million in venture funds for its launch.
One of its major early investors was the Publicis Groupe, a multinational advertising agency and communications conglomerate.
Publicis, the third largest communications group in the world, divides its businesses into four “solutions hubs”: Publicis Communications, Publicis Media, Publicis Sapient and Publicis Health.
It is Publicis’ health division that has generated significant controversy. The company names “40 clients in the life sciences industry,” including “being a preferred partner with 13 of the top 20 global pharmaceutical companies.”
These clients include Pfizer, AstraZeneca, Merck, Bayer, Abbot, Allergan, Biogen, Eli Lilly, Genentech, Gilead, Sanofi and Purdue Pharma.
In October 2018, GlaxoSmithKline sent its $1.5 billion media account to the Publicis Group, then added an additional $400 million account — for its new portfolio of Pfizer Consumer Healthcare brands such as Advil, Caltrate, and Centrum, as part of a joint venture with Pfizer.
In August 2019, Publicis secured the account of another pharmaceutical giant, Novartis, worth $600 million.
However, it was its partnership with Purdue Pharma that directly generated controversy and legal trouble for the Publicis Groupe.
In May 2021, the Massachusetts attorney general’s office filed a lawsuit against Publicis Health, accusing it of helping Purdue Pharma develop deceptive marketing materials and advertising campaigns, used to mislead doctors into prescribing OxyContin, a widely-abused opioid.
According to the lawsuit:
“From 2010 until 2019, Publicis worked with opioid companies, particularly Purdue Pharma, to increase sales of dangerous opioids like OxyContin, including in Massachusetts, in ways that increased the risk to patients and the public of opioid use disorder, overdose, and death.
“Publicis devised and deployed unfair and deceptive marketing campaigns designed to push doctors to prescribe opioids to more patients, in higher doses, and for longer periods of time.”
So while NewsGuard purports to be fighting against online misinformation and deception pertaining to public health — it has no problem taking money from a major advertising and communications conglomerate that has itself been accused of deceptive practices relating to health care.
Maurice Lévy, chairman of the Publicis Group, made the following remarks on the occasion of NewsGuard’s launch:
“Advertisers are increasingly concerned about their brand safety and do not want to help finance and appear alongside fake news.
“NewsGuard will be able to publish and license ‘white lists’ of news sites our clients can use to support legitimate publishers while still protecting their brand reputations.”
As noted by Dr. Joseph Mercola:
“Seeing how Publicis represents most of the major pharmaceutical companies in the world and funded the creation of NewsGuard, it’s not far-fetched to assume Publicis might influence NewsGuard’s ratings of drug industry competitors, such as alternative health sites.
“Being a Google partner, Publicis also has the ability to bury undesirable views that might hurt its clientele.”
Publicis is a partner of the World Economic Forum (WEF) and, indeed, appears as a partner of the WEF’s “Great Reset” (as are pharmaceutical companies and COVID-19 vaccine manufacturers such as AstraZeneca, Johnson & Johnson, Moderna, and Pfizer).
What appears to be a common thread connecting NewsGuard employees, investors and partners is connections to organizations that have a vested interest in promoting COVID vaccination and pandemic countermeasures;
And now NewsGuard is coming to children’s schools.
Michael Nevradakis, Ph.D., is an independent journalist and researcher based in Athens, Greece.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
The great debate: PolitiFact vs. “the world’s top misinformation spreaders”
The request from PolitiFact to remove the fact check recording
By Steve Kirsch | February 25, 2022
Recently, I got an email from PolitiFact’s Editor-in-Chief, Angie Holan, requesting I remove the recording of my conversation with their so-called “fact checker,” Gabrielle Settles who was doing a fact check on VAERS.
I refused her request.
Gabrielle asked if she could record the call and I consented, so that entitles all parties to record the call. PolitiFact did not deny that we both consented. She wrote,
I am not in the least embarrassed by how she conducted the interview. I’m asking that you remove the video as a professional courtesy because the reporter did not consent to be recorded.
First of all, she should be embarrassed by the interview. The interviewer was clearly focused on proving an agenda and showed no interest in exploring evidence that was counter her agenda. I gave her the story of the century if she would just follow up on what I suggested she do.
Secondly with respect to permission, by asking me if it was OK to record the call, she is giving implied consent for the call to be recorded since she is doing the asking. All parties on the call consented to being recorded meaning the conversation is no longer private and all parties can record the call.
The debate challenge
I then raised the stakes: I challenged PolitiFact to a debate to settle the matter once and for all in front of a live Internet audience as to who are the liars and who are the truth tellers. Here is the email I sent on Feb 25, 2022 at 2:58pm PST:
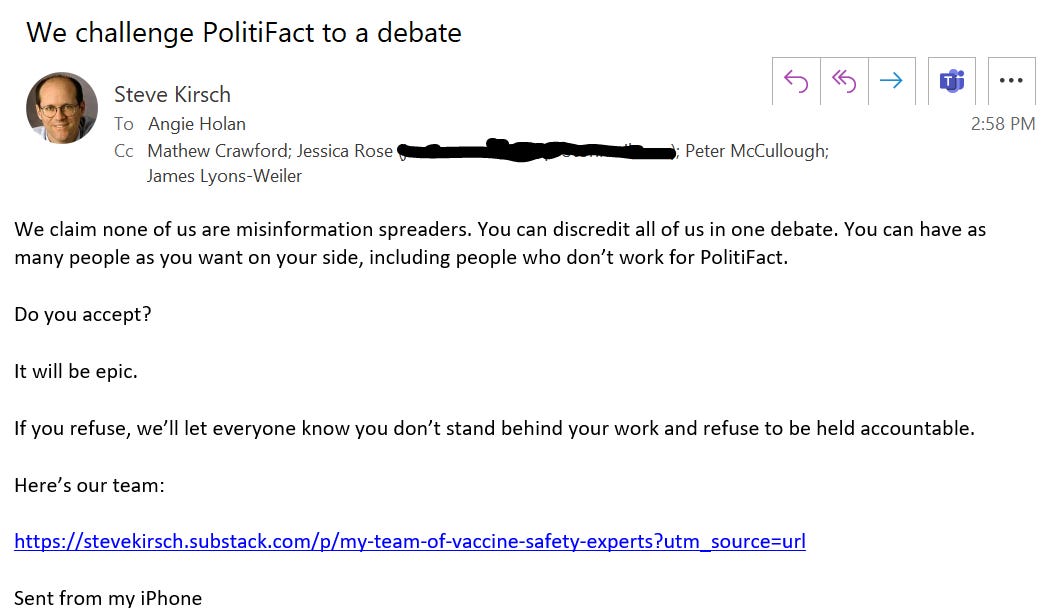
A good, old-fashioned debate.
They can have as many people as they want on their side, the more the better since it will remove all excuses when they lose.
We can use the debate rules suggested here, or anything else they are comfortable with.
The purpose is simple: to ascertain who is really spreading misinformation.
After all, the US Surgeon General has said how dangerous COVID-19 misinformation is. So has the California State Legislature: In House Resolution No. 74 of the 2021–22 Regular Session, the California State Assembly declared health misinformation to be a public health crisis, and urged the State of California to commit to appropriately combating health misinformation and curbing the spread of falsehoods that threaten the health and safety of Californians.
The fastest way to stop all COVID misinformation is to challenge the spreaders of the misinformation and discredit them in a debate
Of course, the problem with a debate is that usually one side wins. If it is the misinformation spreaders, the narrative is crushed. This is why nobody wants a debate: they can’t take the risk.
PolitiFact can’t win a fair debate. There is way too much information out now on how dangerous the vaccines are that is impossible for them to explain.
This is why I don’t think that there is a snowball’s chance in hell they will accept.
I sent the email to Angie earlier today and have not heard back. I will update this article if I do. Don’t hold your breath.
Watch the video that they don’t want you to see
The video they wanted me to remove exposes how the fact checker had absolutely no interest in exploring any of the evidence that proved that the VAERS data was correct.
In short, the video proves that these so-called fact checkers aren’t interested in the facts; they are interested in defending the false narrative.
Be sure to check out the original story (it’s point #5 in this article), and be sure to watch the video if you haven’t already. It shows just how biased these fact checkers are.
Be sure to check out the comments at Rumble on the video:
Other points about VAERS:
- The CDC warns in boldface lettering on its website, “[k]nowingly filing a false VAERS report is a violation of Federal law (18 U.S. Code Section 1001) punishable by fine and imprisonment.”
- Not only are there criminal penalties for filing false VAERS reports, but physicians or medical providers file a majority of them. Dr. McCullough says health care providers file 60 to 80% of VAERS reports. You can verify this by reading the reports.
- Whoever files the report has to have the lot number and batch number of the vaccine and it’s fairly time consuming process. McCullough says that the CDC has analysts call whoever entered the report in order to verify it. McCullough has received those calls.
- Doctors are of course not compensated for filing VAERS reports so they often don’t file them. Most are probably unaware that they are required to file VAERS reports. No one gives them training on filing VAERS reports. Hospital employees have said their hospitals don’t even know about the requirement to report VAERS injuries.
Read more about fact checkers
See this article.
In the meantime, California wants to ensure that no doctor can question whatever the government says
California just introduced a bill that would enable medical boards to take away the license of any doctor who spreads “COVID-19 misinformation.” This is a tacit admission that they can’t win on the facts, so they have to use threats and intimidation to keep the truth from emerging. Their only weapon is censorship.
Here’s the bill: AB-2098.
They define COVID-19 misinformation as anything going against the government narrative.
In short, they want to take away the free speech rights of doctors who would no longer be allowed to question anything the government says. After they do that, citizens will be next.
See this California Globe article, CA Lawmakers Propose Bill to Punish Doctors Who Speak Against COVID Treatment ‘Consensus’, for more info.
Florida is doing the opposite: Protecting the rights of doctors to speak freely
Meanwhile, Florida is doing the opposite by proposing a law that would protect the rights of doctors to speak the truth.
We live in interesting times.
Comments from my good friend Dr. Byram Bridle
Byram tried to debate the authorities in Canada, but they were a no show. He likes courts because the other party is forced to appear.
Here is what he wrote:
Hi Steve, I can’t get any of the narrative-pushers in Canada to debate the science. It would be great if you could have some success with this in the US. But, I agree with you; they almost certainly won’t. Those who don’t stand on the science will never engage in a conversation. People who love the narrative need to start asking their ‘champions’ why they keep refusing to step into the arena with the dissidents. At some point they are going to have to admit that their ‘champions’ are cowards and do nothing more than ‘talk the talk’ from behind their keyboards. A lack of scientific expertise becomes quite apparent when one has to respond off-the-cuff to another scientist in real-time. One place that the ‘experts’ for the narrative cannot hide is in court. So far, I have been seeing them crushed in this venue. This is why many court decisions are being made on technicalities; to avoid ruling on the evidence, the weight of which is not in favor of the narrative.
They are censoring doctors in the UK
From the comments:
GPs have been warned that criticising the Covid vaccine or other pandemic measures via social media could leave them ‘vulnerable’ to GMC* investigation.’1
*GMC = General Medical Council. This is the body that can strike doctors from the medical register so they cannot work as a doctor.
‘Vulnerable to GMC investigation’. What a deliciously creepy phrase that is, dripping with unspoken menace, whilst pretending to be helpful. It sounds like something the Mafia would come up with.
‘I would keep quiet about this, if I were you.’ Baseball bat tapping gently on the floor. ‘No, this is not a threat, think of it as advice from a friend. We don’t like to see anybody making themselves, or their family, vulnerable, and getting seriously injured now, would we?’
It seems that, unless you prostrate yourself before the mighty vaccine, and intone ‘Our vaccine, which art in heaven, hallowed be thy name…’ and suchlike, you will be attacked from all sides … simultaneously. Indeed, to suggest that vaccines are not perfect in every way is the twenty first century’s equivalent of blasphemy.”
See: https://drmalcolmkendrick.org/2022/02/23/a-few-thoughts-on-covid19-vaccination/
They are censoring doctors in Australia
Elizabeth Hart in the comments notes that muzzling doctors from questioning the Covid jabs is the same in Australia.
AHPRA, the regulator of ‘health practitioners’ here, issued a Position Statement dated 9 March 2021, which states: “Vaccination is a crucial part of the public health response to the COVID-19 pandemic. Many registered health practitioners will have a vital role in COVID-19 vaccination programs and in educating the public about the importance and safety of COVID-19 vaccines to ensure high participation rates.”
Health practitioners are also warned: “Any promotion of anti-vaccination statements or health advice which contradicts the best available scientific evidence or seeks to actively undermine the national immunisation campaign (including via social media) is not supported by National Boards and may be in breach of the codes of conduct and subject to investigation and possible regulatory action.” (Search for AHPRA position statement 9 March 2021 to download PDF.)
Who defines what is “the best available scientific advice”? We know what a disastrous quagmire of conflicts of interest is “the best available scientific advice”…
In regards to ‘anti-vaccination’, in practice, any questioning of Covid jabs in Australia is regarded as ‘anti-vaccination’, as tennis star Novak Djokovic discovered when he tried to come here recently to participate in the Australian Open. The Immigration Minister banished Djokovic from Australia because he “has previously stated that he ‘wouldn’t want to be forced by someone to take a vaccine’ to travel or compete in tournaments”. For being an individual wanting to retain his bodily autonomy, Immigration Minister Alex Hawke considered the presence of Djokovic “may be a risk to the health of the Australian community”, presumably as Djokovic might inspire Australians to make their own informed decision about the Covid-19 jabs, counter to government diktats. (See the court judgement here: https://www.judgments.fedcourt.gov.au/judgments/Judgments/fca/full/2022/2022fcafc0003 )
What does the antagonism against Novak Djokovic mean for critical thinking Australians who have similarly made their own informed decision to refuse to consent to Covid jabs that don’t prevent infection nor transmission, injections which purportedly provide questionable ‘protection’ of very limited duration, against a disease it was known from the beginning wasn’t a serious threat to most people?
Now we have a dire situation in Australia where millions of people have been coerced to be jabbed to maintain their livelihoods under state government and business/employer mandates, this directly flouts the obligation for valid voluntary consent to be given before vaccination.
I’ve complained about this matter to medical organisations in Australia, see my email to the Medical Board of Australia, AHPRA, RACGP, RACP, AMA, 8 June 2021: https://vaccinationispolitical.files.wordpress.com/2021/06/coercive-covid-19-injections-in-australia-medical-board-of-australia-ahpra-racgp-racp-ama.pdf
After perseverance, I finally received a response from AHPRA, which confirms: “Practitioners have an obligation to obtain informed consent for treatment, including vaccination. Informed consent is a person’s voluntary decision about health care that is made with knowledge and understanding of the benefits and risks involved.” See: https://vaccinationispolitical.files.wordpress.com/2021/10/response-from-ahpra-re-informed-consent.pdf
But this isn’t happening! With so many people being coerced and manipulated into submitting to the jabs under state government and business/employer mandates, this isn’t authentic voluntary consent. The situation is really bad in Australia, which I suspect is possibly the most mandated jab country in the world.
Summary
We want to make sure people know the truth about PolitiFact. I literally handed Gabrielle Settles the story of the century and she had no interest at all in pursuing any of it.
Everyone should watch the video of how they operate.
If PolitiFact and others want to end misinformation, all they have to do is debate us. Instead, governments are passing laws to censor doctors since they don’t have the facts on their side.
All over the world, governments do not want the people to hear the fully story.
If vaccines work, then why are they bending the curves in the wrong direction?
el gato malo – bad cattitude – february 27, 2022
israel has been a good laboratory for covid intervention assessment. they are a small nation in one climate zone with a small population, good record keeping, a pretty honest set of health agencies, and modern healthcare system. they did lots of testing and they also pursued damn near every mitigation in the book from lockdowns to masking to mandating vaccines and vaccine passports. and unlike many places, they were extremely serious about compliance. they even have an very useful control group in palestine that did almost none of these things.
this provides an interesting opportunity to measure the efficacy of such interventions. at this point, it’s so well established that masking and distancing have no effect that we can more or less drop them from consideration and focus solely on vaccines. (to the extent they worked, they would drive apparent vaccine efficacy in israel anyhow).
and the two states have had remarkably similar overall outcomes and had near identical cumulative deaths per capita through 2021. however, it looks like this might be starting to diverge and this creates a useful comparison.
about three weeks ago, i left THIS POST with some questions:

we now have enough data to start to answer this.
the relative vaxx rates are very different and israel is over 50% boosted vs ~0 in palestine. so, if boosters are working, this is about as good a natural experiment setup as you could ask for.
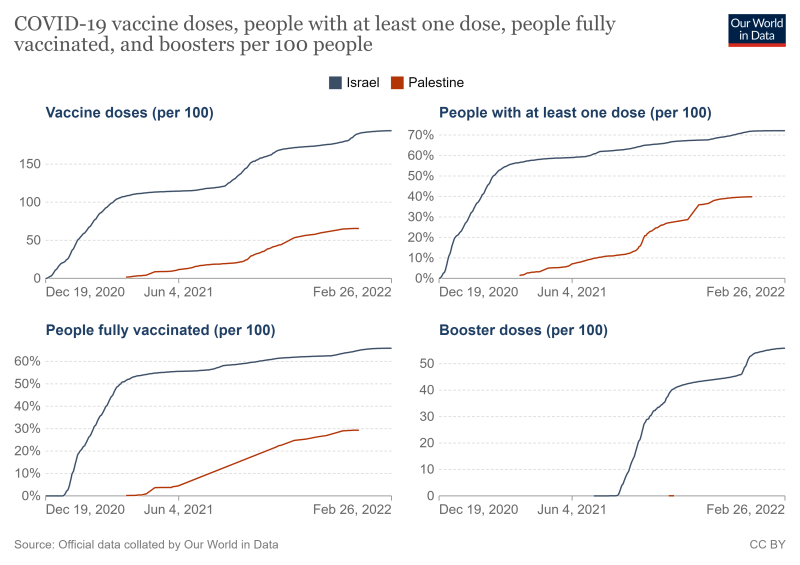
cases are a problematic metric due to variance in testing rates (and we know vaccines do not stop cases) and palestine does not report hospital data. but we can compare deaths, so this is the figure i used.
OWID is the source for all data.
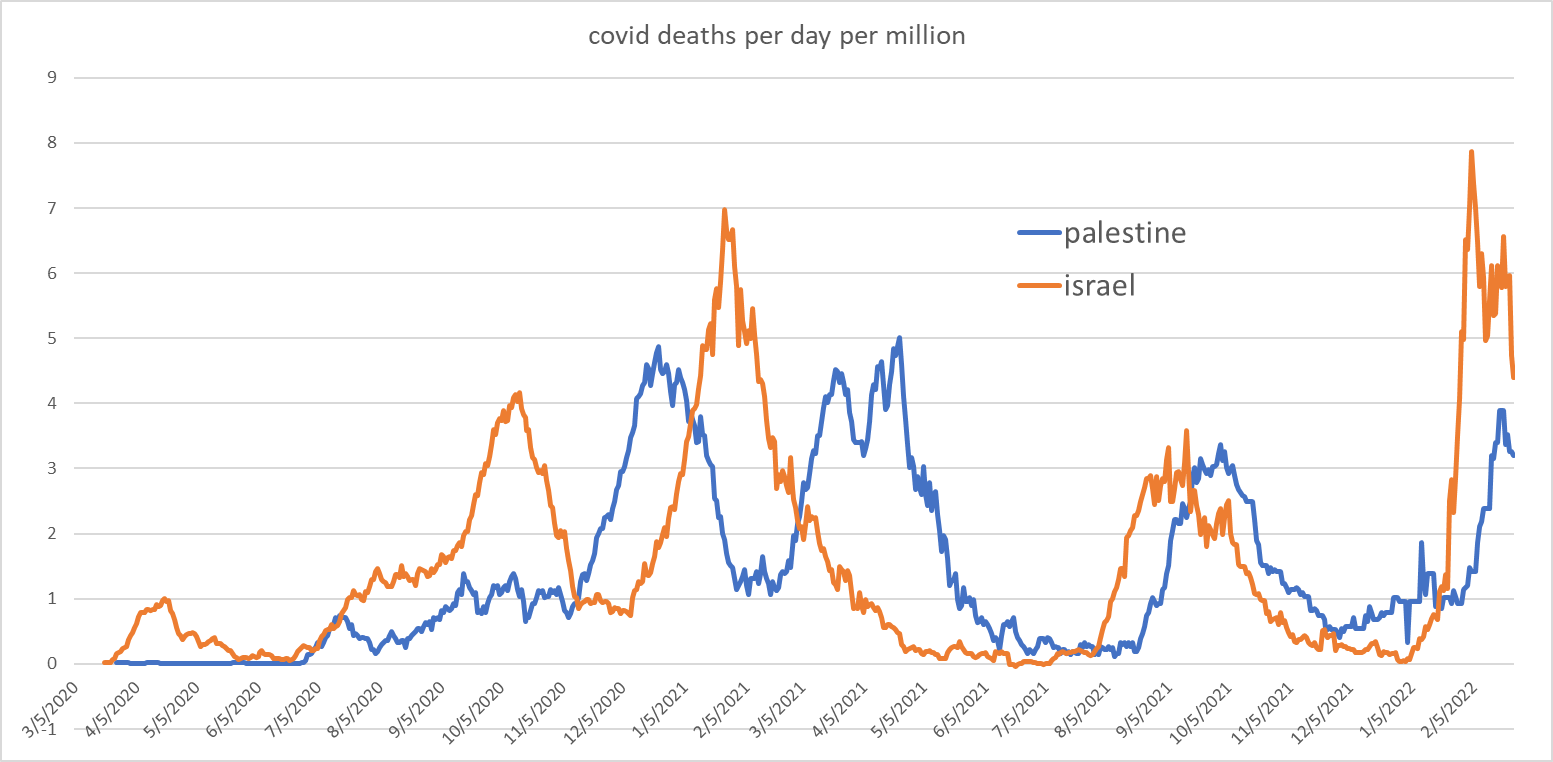
this series is striking. as has commonly been the case, palestine lagged israel by a couple weeks. (i suspect this is reporting lag, this data is day of report, not day of incidence).
assuming this peak holds, the palestine peak was 21% below winter seasonal peak last year. israel was up 13%. that’s a meaningful divergence and the israeli figure is deeply unexpected given a milder variant and 18 months of vulnerable cohort depletion.
this starts to hint at something being quite wrong and also starts to rule out “variant” as the source, because it did not drive that outcome in palestine.
it can be notoriously difficult to eyeball area under curve, so i have plotted cumulative deaths here:
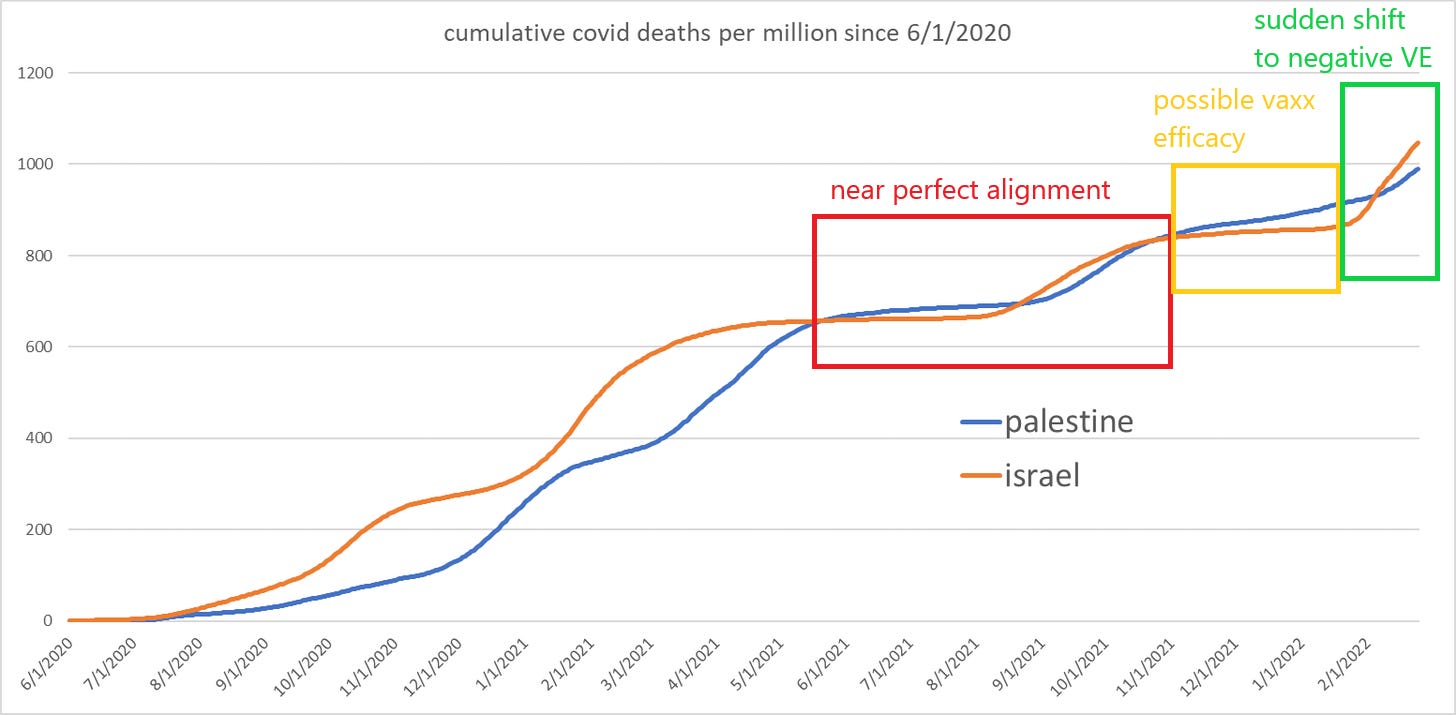
as can be seen, israel had gone pancake flat in november 2021 through jan 2022. then it inflected severely. this is omicron which hit the levant in the second half of december 2021. clinically, you’d expect about a 24 day log to show up in deaths and this tends to jibe with the data i’ve seen all over the world.
it’s possible that boosters were having some effect in bending the curve, but to the extent that they did, it was either fleeting or rapidly inverted in the face of a new variant. (or both)
this becomes extremely easy to see when we zoom into 2022 and start a cumulative count from 1/1/2022.
there is a powerful inflection in israel that does not exist in palestine and israel has seen roughly twice the cumulative per capital death rate of palestine so far this year.
if boosters are effective in preventing deaths from omicron, it sure does not show up here.
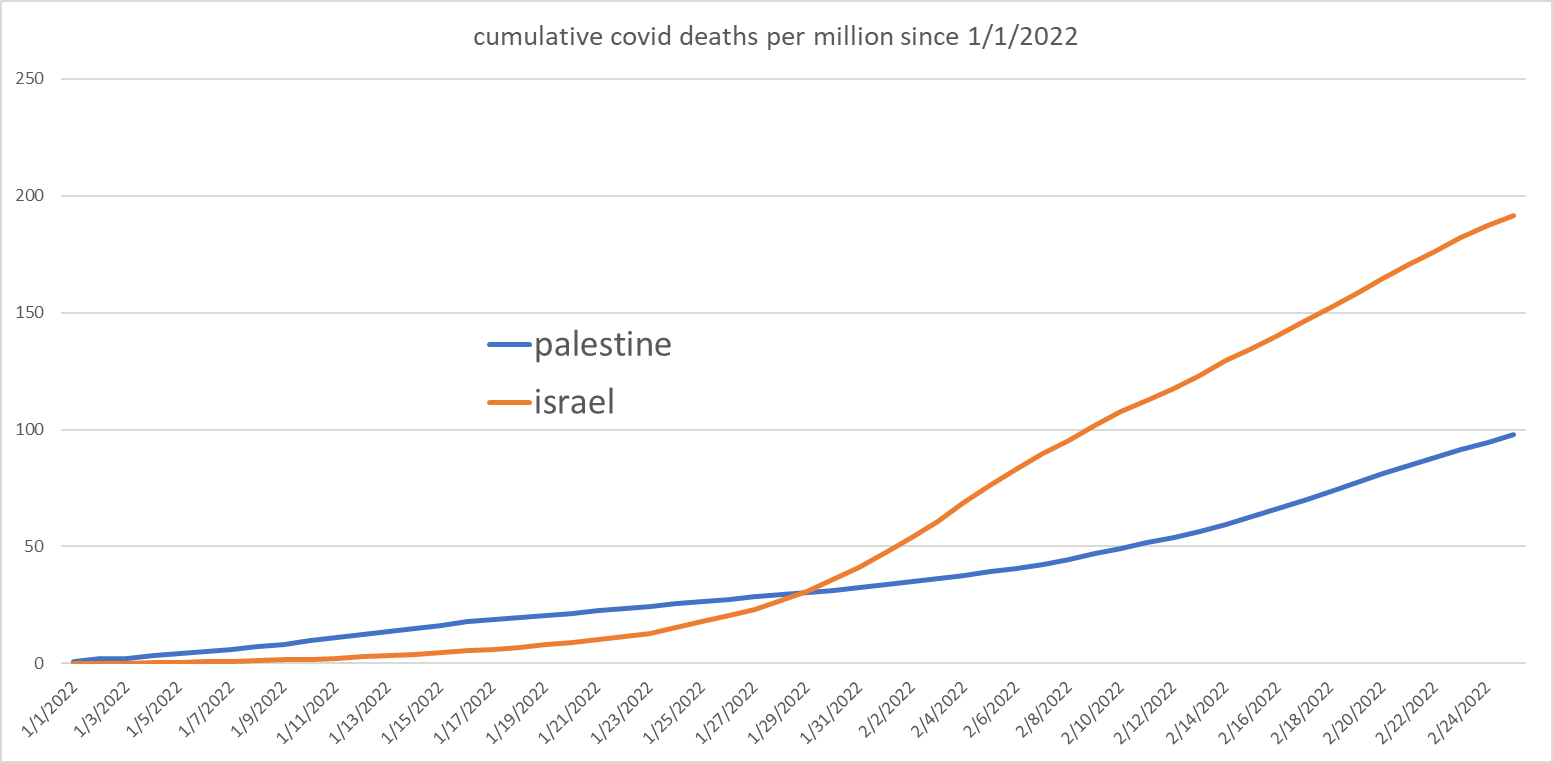
this also lets us rule out “omicron” as a source of greater underlying virulence/fatality. if this were so, it would be manifest in both places. the fact that it is not doing so supports the idea that omicron is an OAS/hoskins effect evolution taking advantage of the narrow antigenic fixation generated by mRNA and adenovirus vaccines. it also seems to show that this advantage is NOT, as many claim, limited to cases. it seems to carry through to deaths as well.
we can also compare israel to itself and see how this highly vaccinated and boosted period compares to the prior year when vaccination was zero. from this data as well, we see strong support for the OAS hypothesis.
israel had been doing better. then omi came and everything changed.
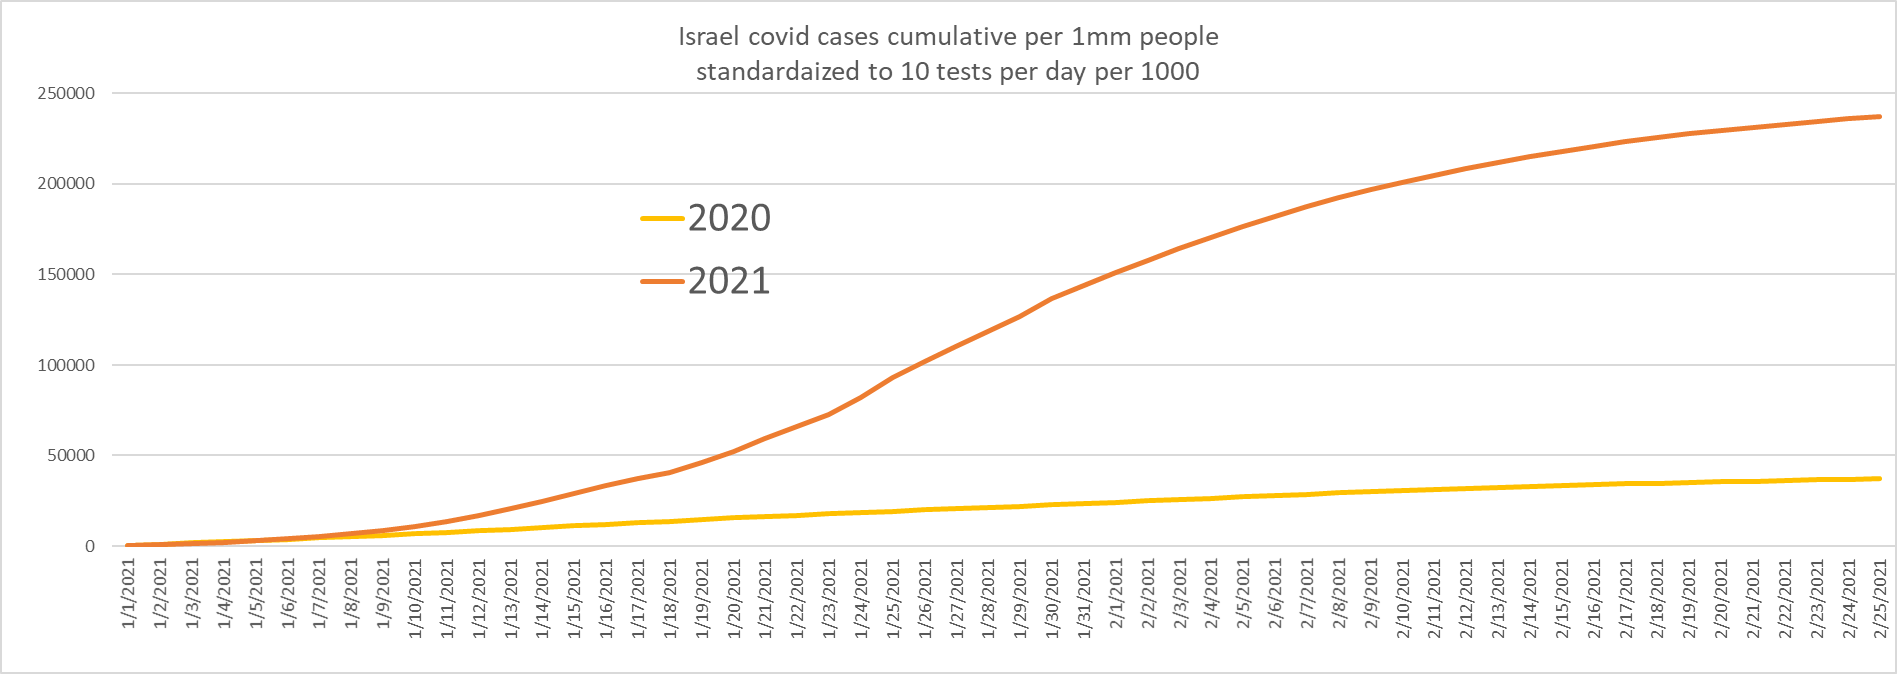
(to remove the skew from widely varying sample rate driven by big shifts in testing levels, i have normalized all cases data to 10 tests per day per 1000 population though given the absurdity of calling a high Ct PCR+ a “case” even lacking symptoms, all case data is troublesome to assess, but we work with what we have, not with what we wish we had)
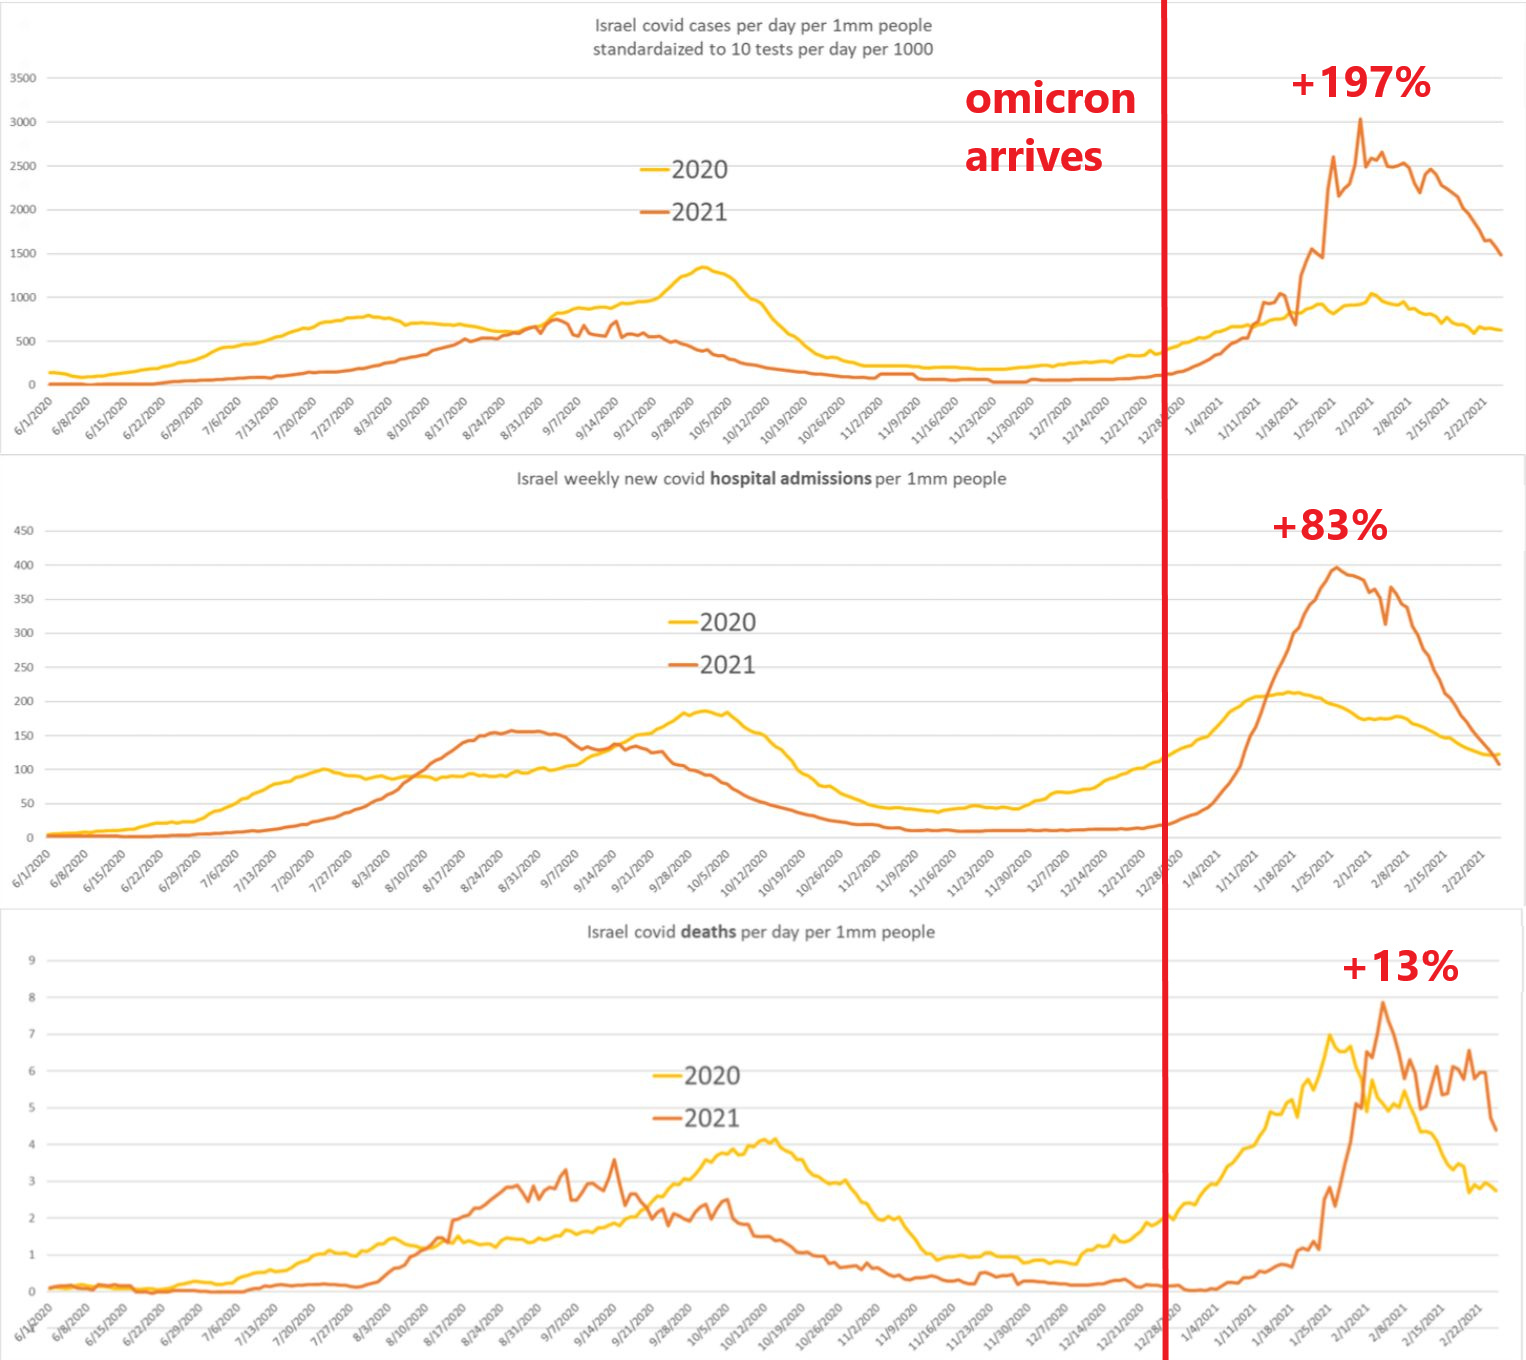
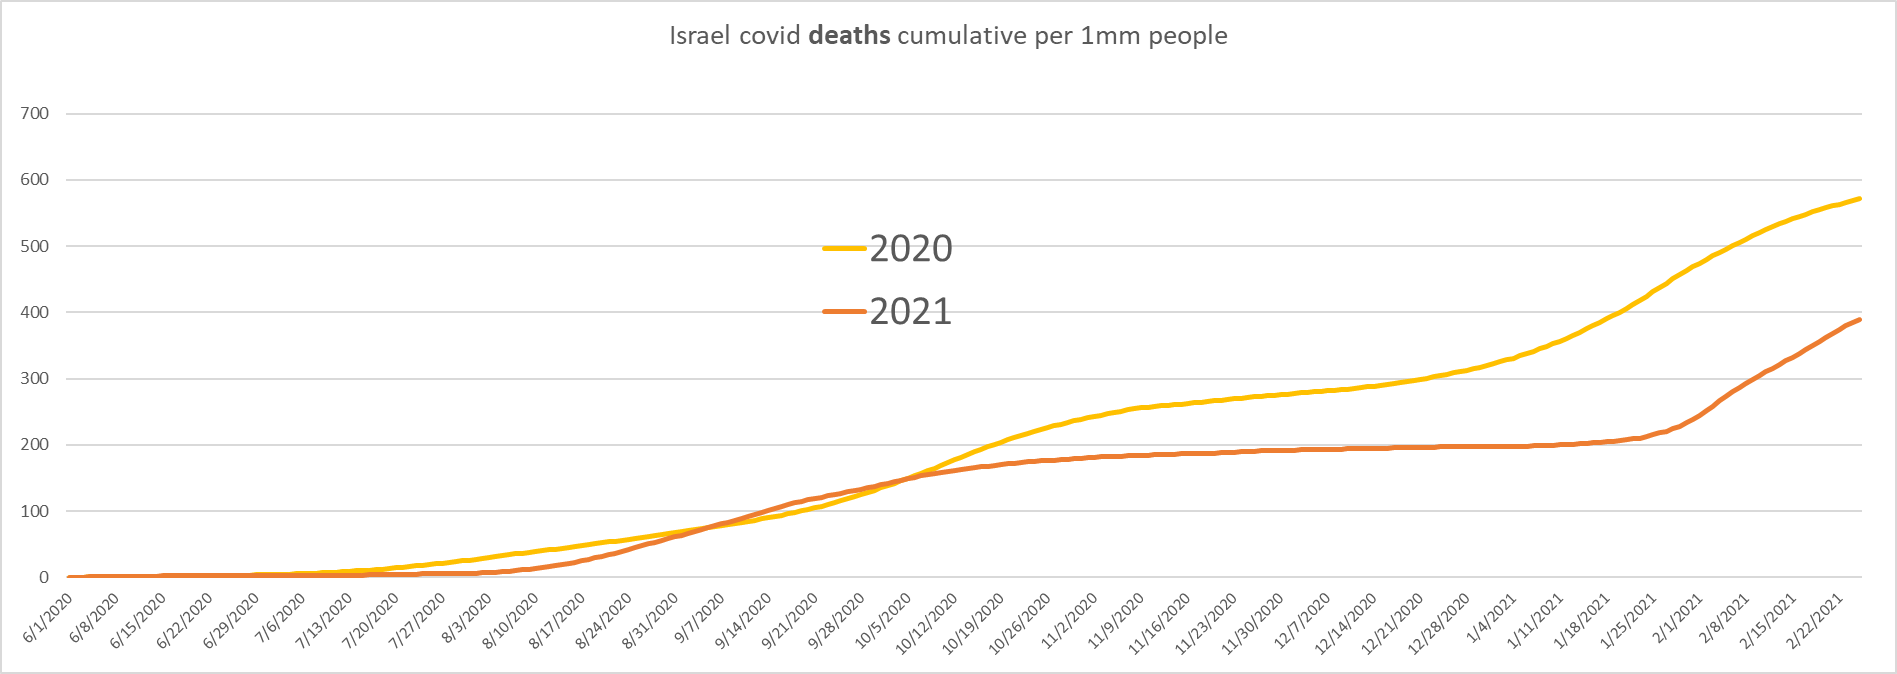
cases nearly tripled and hospitalizations nearly doubled. deaths rose 13%.
according to israeli authorities and hospitals, this was not driven by “the unvaxxed” but rather by the vaccinated. they seem to make up more than their share of severe outcomes though one must we wary of simpson’s paradoxes. (more HERE)
it might be possible to construct an argument whereby vaccine efficacy is claimed on any given infection (once you are sick, better to be vaxxed) but if that is, in aggregate, swamped by a rise in cases (and we know vaccines lead to more cases, not fewer) then this is still not much of an argument. having vaccines reduce risk of hospitalization per case by 50% but tripling case risk is still a 50% rise in overall hospitalization.
the aggregate data is possibly supportive of this claim outcome, but it’s far from certain either way.
but still, if the overall outcomes are worse post vaxx in the active arm but not in control, from a public health perspective do we really care why?
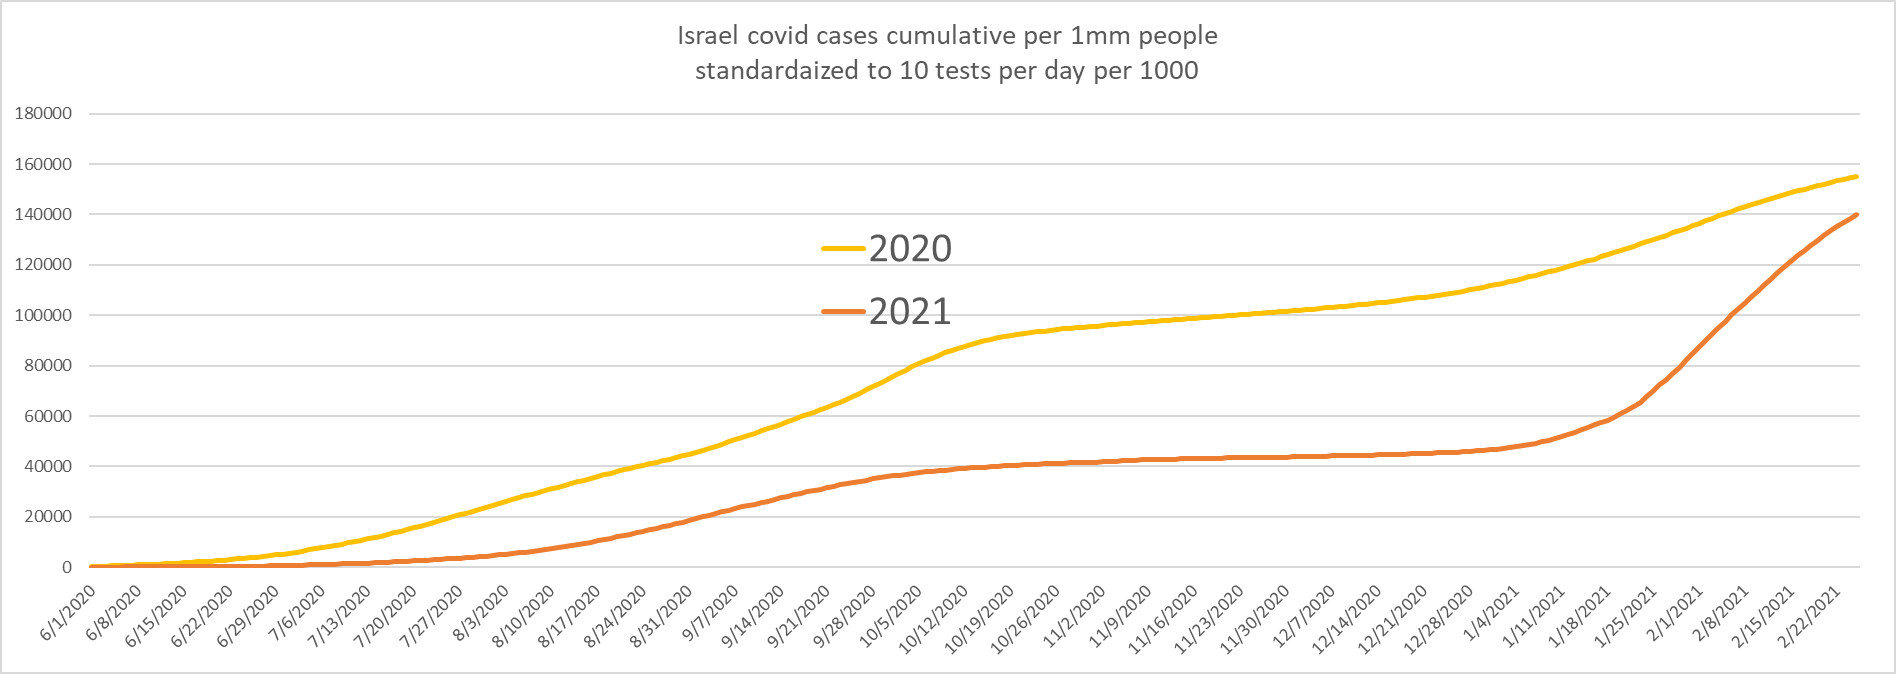
cases were trending MUCH lower. then that changed in a hurry.
zooming in makes it all the more clear.
even adjusted for testing, this is a massive surge in cases.
we see the same in hospitalization.
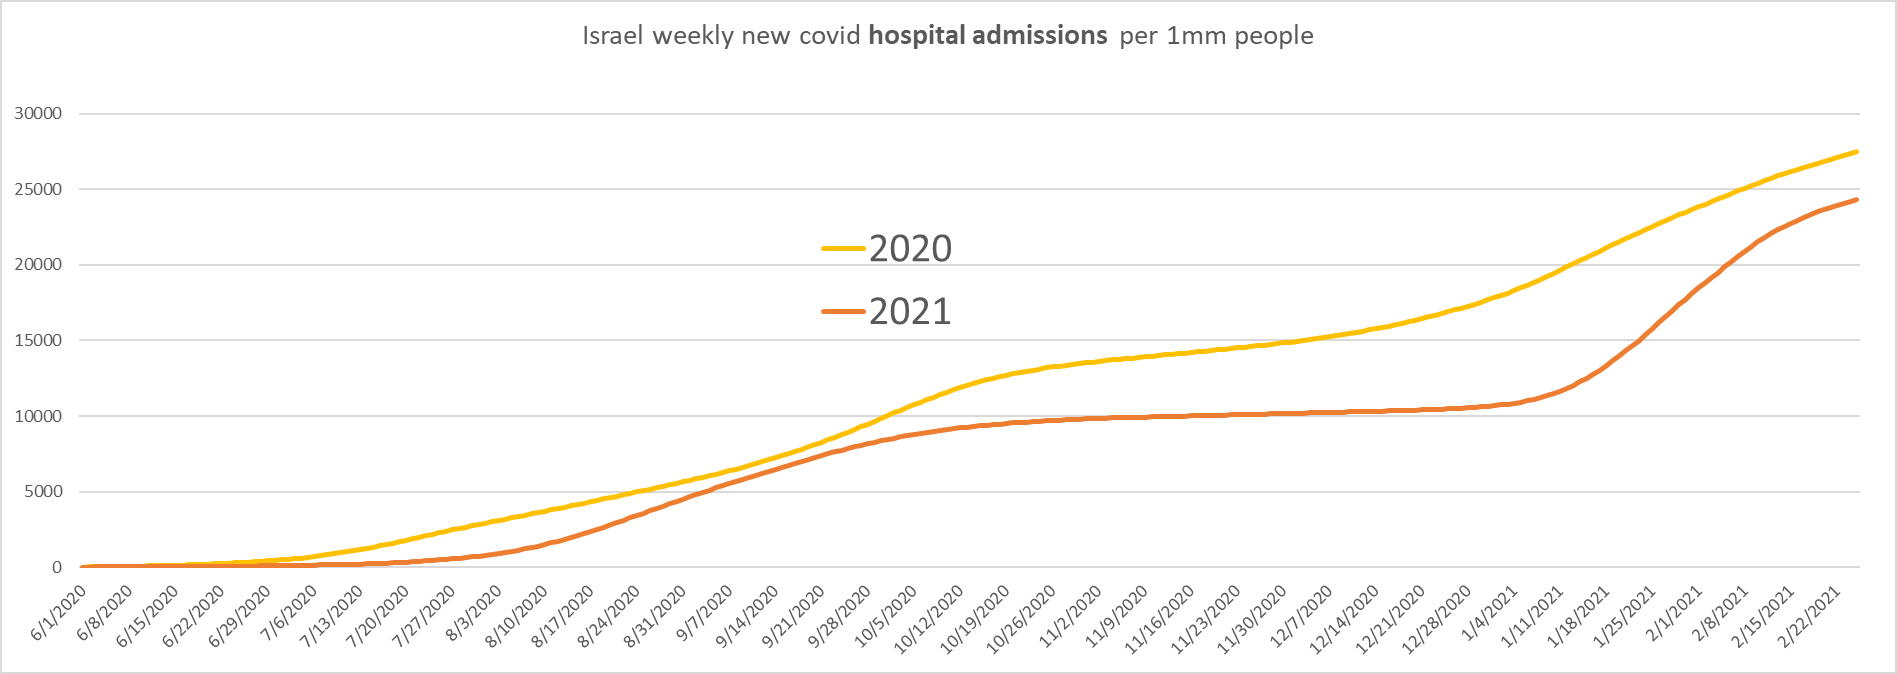
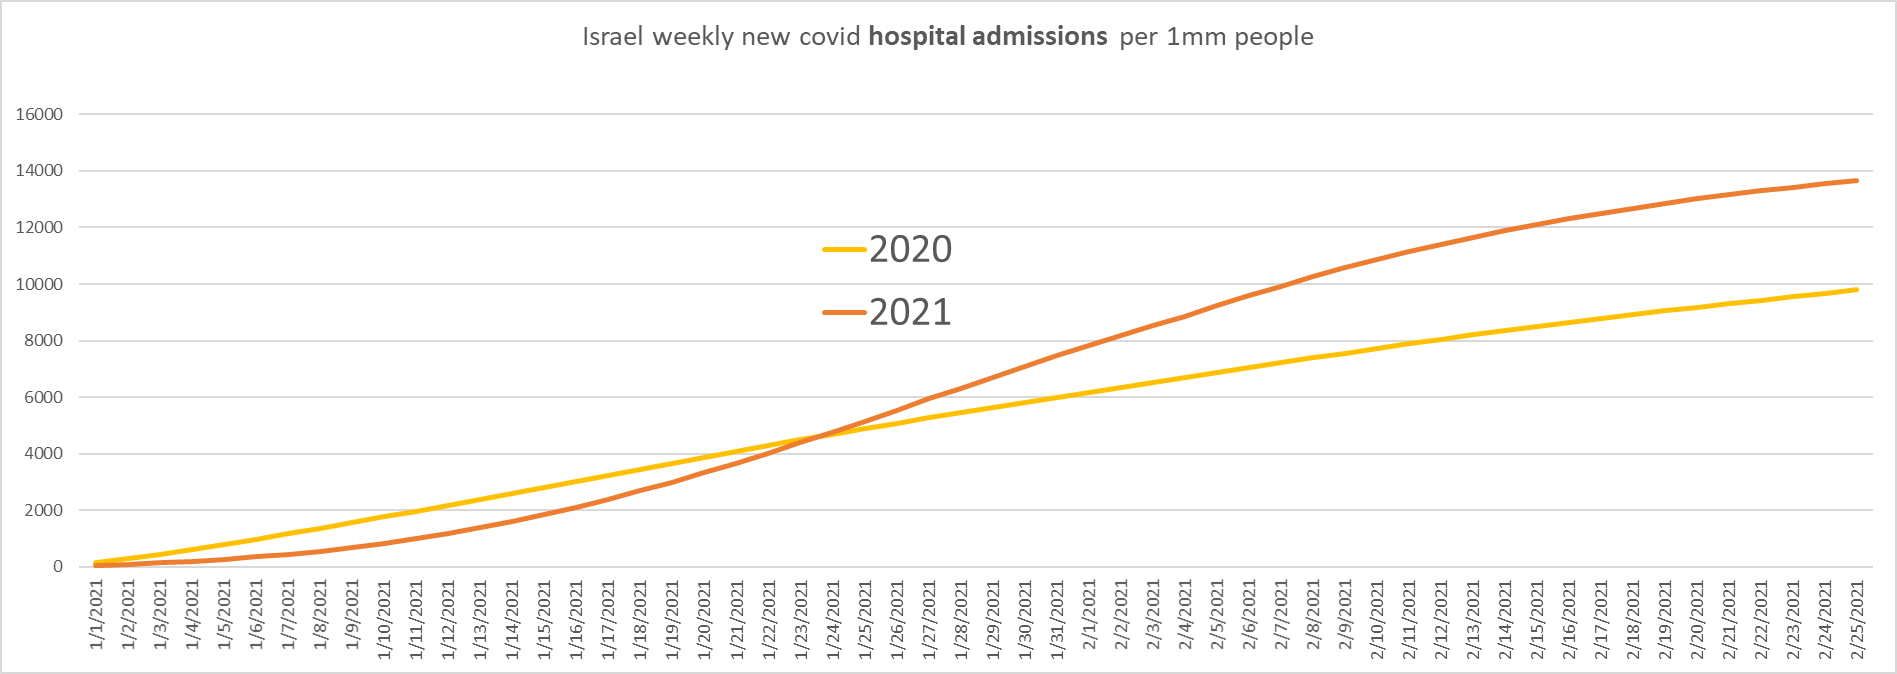
and see the crossover to worse outcomes in 2022 when we zoom in.
overall, they are 39% higher in aggregate YTD vs prior yr.
deaths have not yet caught up, but appear likely to do so.
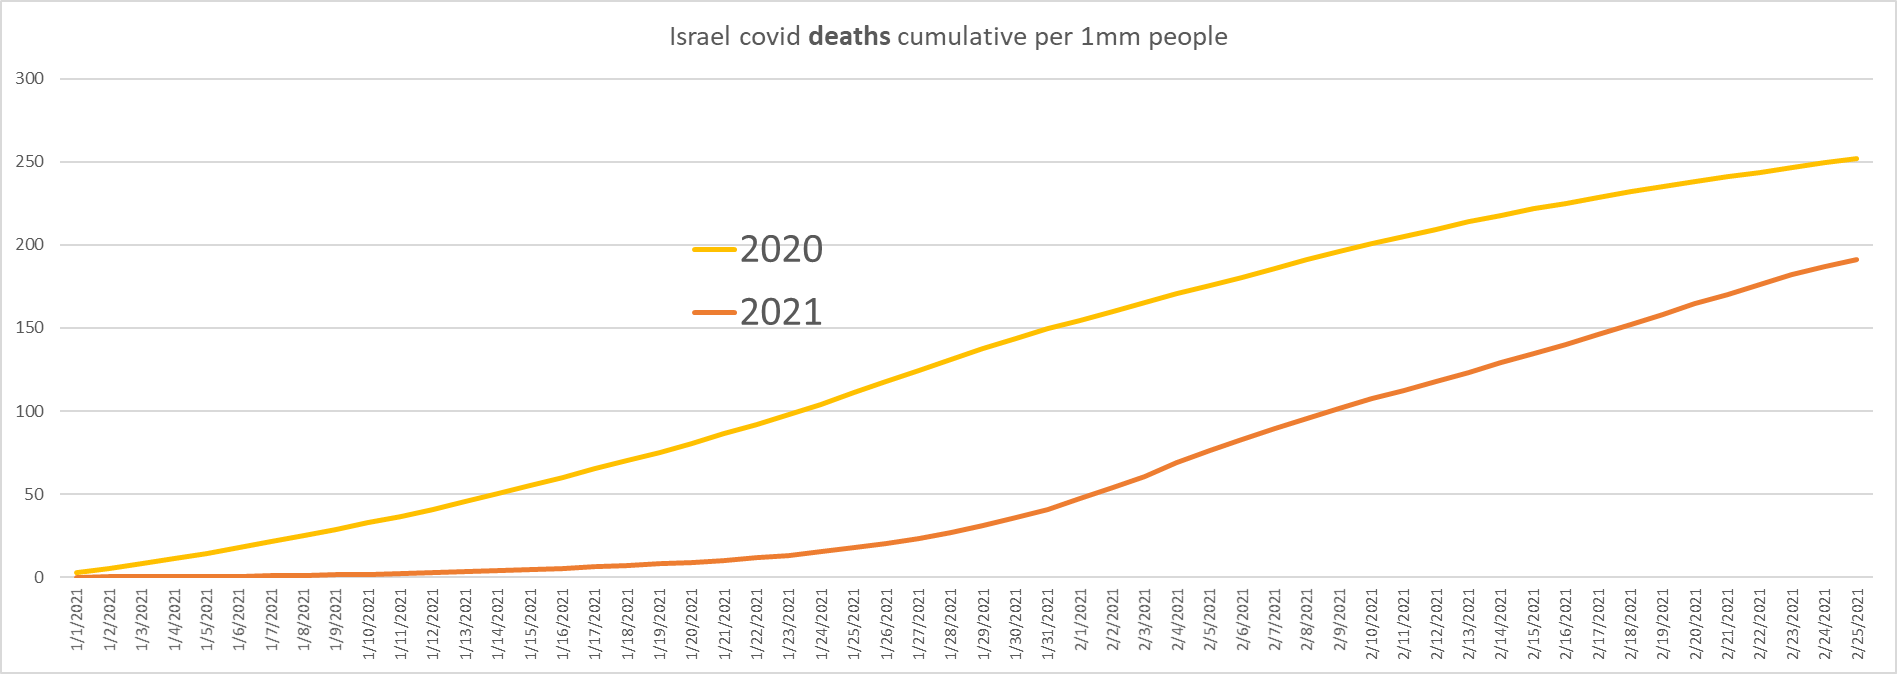
taken as a whole, this is pretty damning of the booster programs.
israel saw a big spike in deaths that was not present in the palestine control group.
it saw a massive jump in cases, a big jump in hospitalizations, and is rapidly converging on deaths (which will lag the others by ~3-4 weeks).
there is just no way to spin this as a win. it looks like an own goal.
this was the known and knowable outcome of widespread inoculation with a leaky vaccine. it is, in fact, WHY we do not use leaky vaccines.
they will rapidly and inevitably select for escape or vaccine enhanced variants. and now it makes you worse and worst of all, locks you into a suboptimal antigenic response pattern that may keep you from EVER generating real sterilizing immunity. the truly nasty part of this may take years to really see.
omicron was not “bad luck” it was invoked consequence of ill conceived intervention. even assuming they ever worked as claimed (dubious) these vaccines were always going to fail because that’s what leaky vaccines do.
this was known and knowable. the drug companies that made them knew it. the regulatory agencies that approved them knew it. and many, many doctors, researchers and public health officials all over the world knew it. they were silenced, threatened, and attacked for it. and this is the bitter fruit of that harvest.
in the US, the data has been manipulated and misused so badly as to render it outright fraud. it becomes obvious when one compares the US data (which calls all “unknown or undetermined” patients “unvaxxed” and used the fact that the EPIC system is awful to create a false sense of VE) with a system that keeps good records as longtime gatopal™ HOLD2, newly on substack, has done here.
like so much of the rest of the covid response, we knew better than to do this, but it was done anyway.
and now, the US is lying about it while others are, at least, coming clean.
but this truth will be too vast to hide much longer, even behind these big lies.
and american health and regulatory agencies are going to have a great deal to answer for.
dr atlas (with whom many at rational ground, including even notorious internet felines, had the pleasure to collaborate) is correct in everything he says here except in his use of the world “almost.”
Moscow and Kiev issue updates on Ukrainian border guards reported killed
RT | February 26, 2022
The Russian military has claimed that Ukrainian border guards, whom Ukraine initially declared entirely slain, survived, while Kiev’s military concurred that it might indeed be the case.
Both countries’ armed forces on Saturday said that a group of Ukrainian border guards stationed on Zmeinyy (Snake) Island, located some 48km off Ukraine’s southern coast in the Black Sea, were captured by Russian forces. Russia says they were taken alive and unharmed to Sevastopol in Crimea.
However, the initial story allegedly went as follows: a group of 13 border guards on the island were confronted by a Russian warship on Thursday. The Russian ship ordered the group by radio to surrender, the Ukrainians replied “go f**k yourself,” and the Russian ship opened fire. After several hours of fighting, all the guards were killed.
The story spread like wildfire on social media and was held up by the Ukrainian government, Western media outlets and journalists as an example of Ukrainian “heroism.” Ukrainian President Volodymyr Zelensky honored the troops he declared slain, saying: “On our [Snake] Island, defending it to the last, all the border guards died heroically,” and promising to award them the posthumous title of “Hero of Ukraine.”
The first signs that something else may have happened came early on Saturday, as Russia’s Black Sea Fleet announced that dozens of Ukrainian border troops were delivered to Sevastopol, Crimea, with videos online purportedly showing their arrival.
Ukraine’s Border Guard Service stated shortly afterwards that the troops on Snake Island “bravely defended themselves,” but were taken prisoner when the island was captured. According to the military branch, reports that all had perished were “preliminary,” and came after the Ukrainian military lost contact with the island. The ministry did not say how many guards were stationed on the island, and did not claim to know whether any died or were injured.
The Russian Ministry of Defense likewise confirmed the capture of the island. Spokesman Major General Igor Konashenkov said that 82 Ukrainian servicemen had been stationed on the island, that all surrendered, and that none were injured. Konashenkov said that as prisoners were being transported off the island, 16 Ukrainian Navy boats disguised as civilian vessels launched an attack on Russia’s Black Sea fleet.
Konashenkov said that Russians destroyed six of the Ukrainian vessels, and claimed that US drones were seen operating in the area, suggesting that the US “directed” the Ukrainian boats. These reports have not yet been corroborated.
A recording of the Snake Island garrison supposedly telling the Russian ship to “go f**k yourself” is still circulating on social media. There is currently no evidence that the recording is genuine, and Ukraine’s Border Guard Service only said that the troops gave a message indicating “no one will surrender.”
A short history of laboratory leaks and gain-of-function studies
By Professor Paul R. Goddard | GM Watch | February 19, 2022
Two myths have hindered investigations into the origins of the SARS-CoV-2 virus: one, that viruses seldom escape from laboratories; and two, that most pandemics are zoonotic, caused by a natural spillover of a virus from animals to humans.
Promoters of the first myth include the World Health Organization (WHO). At a press conference in Wuhan, China, in February 2021, Peter Ben Embarek, the head of the WHO inspection team tasked with looking into the origins of the virus, said it was “extremely unlikely” that it had leaked from a lab and as a result the lab escape hypothesis would no longer form part of the WHO’s continuing investigations.[1]
Dr Peter Daszak, president of the EcoHealth Alliance, has promoted both myths. As long ago as 2012, Dr Daszak co-authored a paper in The Lancet claiming that “Most pandemics – e.g. HIV/AIDS, severe acute respiratory syndrome, pandemic influenza – originate in animals”.[2] Since the start of the pandemic, he has claimed that “lab accidents are extremely rare”, and that they “have never led to large scale [disease] outbreaks”. He also said that suggestions that SARS-CoV-2 might have come out of a lab are “preposterous”, “baseless”, “crackpot”, “conspiracy theories”, and “pure baloney”.[3]
In September 2020 Dr Anthony Fauci, director of the US National Institutes of Health’s (NIH) National Institute of Allergy and Infectious Diseases (NIAID), and his co-author wrote in a paper about COVID’s origins, “Infectious diseases prevalent in humans and animals are caused by pathogens that once emerged from other animal hosts.”[4] Fauci has tried to quash the notion that SARS-CoV-2 could have come from a lab. In May 2020 he said that the virus “could not have been artificially or deliberately manipulated” and in October 2020 that year that the lab leak theory was “molecularly impossible”.[5]
But emails uncovered this year by a Freedom of Information request in the US reveal a wide gap between what Fauci was being told by experts about the virus’s origins and what he was saying publicly. In January 2020, a group of four virologists led by Kristian G. Andersen of the Scripps Research Institute told Fauci that they all “find the genome inconsistent with expectations from evolutionary theory”[6] – in other words, it likely didn’t come from nature and could have come from a lab.
Fauci hastily convened a teleconference with the virologists on 1 February 2020.[7] As the New York Post reported, “Something remarkable happened at the conference, because within three days, Andersen was singing a different tune. In a Feb. 4, 2020, email, he derided ideas about a lab leak as ‘crackpot theories’ that ‘relate to this virus being somehow engineered with intent and that is demonstrably not the case’.”[8]
Andersen and his colleagues then published an article on 17 March 2020 in the journal Nature Medicine that declared, “Our analyses clearly show that SARS-CoV-2 is not a laboratory construct or a purposefully manipulated virus.”[9] The article was highly influential in persuading the mainstream press not to investigate lab leak theories.[10]
While the emails do not prove a conspiracy to mislead the public, they certainly make it more plausible. Just one day after the teleconference at which his experts explained why they thought the virus seemed manipulated, Francis Collins, then-director of the NIH, complained about the damage such an idea might cause.
“The voices of conspiracy will quickly dominate, doing great potential harm to science and international harmony,” he wrote on 2 February 2020, according to the emails.[11]
But there is another reason why Fauci and Collins might not want the lab leak idea to take hold. Dr Daszak’s EcoHealth Alliance had channelled funding from the NIH’s NIAID to the Wuhan Institute of Virology (WIV) in China, for dangerous gain-of-function (GoF) research on bat coronaviruses. So money from organisations headed by Fauci, Collins, and Daszak funded research that could have led to the lab leak that some believe caused the pandemic.[12]
While it should have been clear from the beginning that Drs Fauci and Daszak have strong vested interests in denying the lab leak theory, until recently their assertions were taken as objective fact by most science writers and media.
But a brief look at the history of lab leaks and the origins of pandemics confirms that their claims are highly misleading. Research shows that the escape of viruses from laboratories and supposedly contained experiments, such as vaccine research and programmes, is a common occurrence. In addition, many pandemics have arisen from lab escapes and almost all have not been directly zoonotic. Even when viruses do ultimately originate in animals and make the jump into humans, they mostly fester in a separated community of human beings for many years – centuries or millennia – before spreading during abnormal movements of people due to wars and famines.
What is GoF research?
In its broadest definition, GoF research provides a virus or other microbe with a new function, such as making it more virulent or transmissible, or widening its host range (the types of hosts that the organism can infect).[13] Through GoF, researchers can create new diseases in the laboratory.
GoF can be achieved by any selection process that results in changes in the genes of the organism and as a result, its characteristics. One example of such a process is passing a virus through different animal cells, which can result in a loss of function (weakening it) or a gain of function (making it more able to replicate in a new host species). The researcher can then select the altered organism, depending on the purpose of the research.
In the last decade, GoF researchers have used genetic engineering to directly intervene in the genome of viruses to enhance a desired function.
But long before GoF studies involving deliberate genetic alteration, researchers had started to experiment with widening the host range of certain viruses, in order to develop vaccines. Often these experiments had unintended outcomes, including causing outbreaks of the disease being targeted.
Smallpox
An example is the development of the smallpox vaccine. Most of us are aware of how Edward Jenner in 1796 put cowpox to work in a new way, to infect humans. This led to the successful vaccination programme that eventually eliminated smallpox from the world.
But what many people do not know is that the experiments of 1796 were not his first attempts at using an animal pox in humans. His first subject was his baby son, who had been born in 1789. He inoculated the lad with swinepox and later tested the inoculation’s effectiveness with smallpox. As Greer Williams pointed out in the book Virus Hunters, “The best we can say for this experiment is that it muddied the water… whether the experimental infections had anything to do with [the son’s] mental retardation it is impossible to say.”[14]
Vaccination does not give immunity from smallpox for life: A booster is required every few years. The last person to die from smallpox was Janet Parker, a photographer who worked on the floor above a lab in Birmingham, UK, where research on the virus was being conducted. She had been vaccinated against smallpox in 1966 but contracted the disease in 1978 when the virus escaped from the lab by an unknown route. She died some days later (see Table 1).
Introducing a virus or other microbe to a new host has historically been associated with problems. Before Jenner, inoculation with variola minor (smallpox from a sufferer with minor disease), had been used as a preventive measure in China as early as the tenth century.[15] Variolation, as it was termed, was introduced to the UK in 1717, but is reported to have killed 1 in 25. So Jenner’s experiments have to be viewed in the light of the contemporary practice, which was killing 4% of those inoculated.
What is more, as Greer Williams noted, variolation was an “excellent way of spreading the disease and starting new epidemics”.[16]
Yellow fever
In 1900 the French had given up on building the Panama Canal due to yellow fever decimating the workers. Eventually the disease was conquered in the region by a mosquito eradication programme based on the experiments of the US Army surgeon Major Walter Reed.[17] This success was crucial to the completion of the project in 1914.
But what is often forgotten is that a series of doctors and laboratory workers died trying to combat yellow fever. In 1900 Dr Jesse W. Lazear was the first researcher to die from yellow fever after he apparently allowed himself to be bitten by an infected mosquito as part of his experiments.[18] Between 1927 and 1930, yellow fever caused 32 laboratory infections, killing five people.[19]
As the research into viruses continued, so did the infection rate amongst the researchers and the death toll of researchers and those inoculated against diseases rose. I do not doubt that the final outcome was to the good of mankind, but occasionally a “vaccine” would go spectacularly wrong.
Polio
In the 1930s, 40s and 50s the infection that seemed to most frighten Western society was poliomyelitis. Perhaps it was because unlike with most infectious diseases, cleanliness did not seem to be a protection and exercising could be positively harmful. In fact polio struck those who were healthy and wealthy and was worse if the person was fit and active. Much effort was put into finding a vaccine and among the first to succeed was Dr Jonas Salk. There had been abortive attempts in the 1930s but the 1935 vaccination programme had actually killed people.
Salk was a meticulous researcher and his technique was excellent. Unfortunately this was not the case with all of the laboratories that prepared the vaccine for public use. In particular, the Cutter Laboratories failed to kill the virus and poliomyelitis was spread by their version of the Salk vaccine, paralysing and killing the recipients. Eventually the proper controls permitted the successful rollout of the killed vaccine. It was later replaced by an attenuated polio virus vaccine, which has nearly eliminated polio from the world. It will not, however, succeed in completely eliminating the disease, as the attenuated virus can revert to a wild form. Thus the final push may require the use, once again, of the killed virus polio vaccine.
The infection of laboratory workers with the microbes they were working on was so common that steps were introduced in the 1940s to prevent escape of the organisms. According to Wikipedia, the first prototype Class III (maximum containment) biosafety cabinet was fashioned in 1943 by Hubert Kaempf Jr., then a US Army soldier.[20] The regulations were enhanced and the escape of dangerous organisms decreased, but has never disappeared. This is clearly demonstrated in Table 1, which lists some, but by no means all, of the known lab leaks since the 1960s.
Escapes from bioweapons facilities
Whilst all of the incidents in the table are of interest, some are more worrying than others. In 1971 and 1979 there were outbreaks of smallpox and anthrax in the Soviet Union, caused by escapes of weaponised smallpox and weaponised anthrax from their own bioweapons facilities. In 1977 it is believed that a laboratory somewhere on the border of China and Russia put the H1N1 virus back together and it escaped and caused at least two pandemics. SARS1, which erupted first in 2003, later escaped from laboratories six times, four of which were in China, plus Singapore and Taiwan.[21]
The more you look at the table, the more you wonder if there is any virus that has not at some time escaped from a laboratory. Laboratory workers have told me that it is common for technicians to become infected with the organisms they are working with and their usual response in the past has been to take multivitamins and hydroxychloroquine.
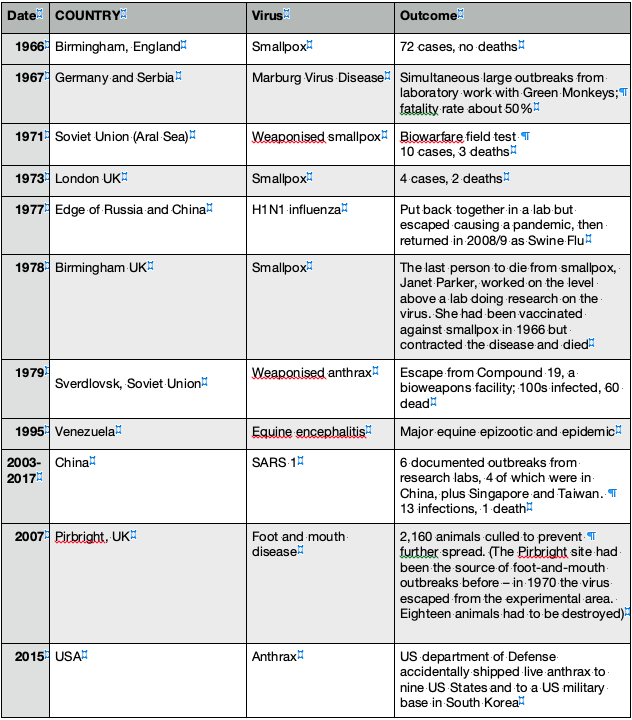
Table 1: Some serious leaks of viruses from laboratories[22]k
The recent history of gain-of-function studies
Since 2010, GoF studies have increasingly focused on finding out whether non-pathogenic strains of viruses could be made infective and harmful to human beings.[23] This was supposedly in order to know whether or not the microbe was likely to be hazardous to human beings and then, if it was, devise vaccines and drugs against it.
In my opinion, such work simply increases the sum total of different pathogens that can affect human beings. When medical doctors are made aware of this type of research, they are usually speechless at the stupidity that anybody would contemplate doing such work. I now call such studies Make Another Disease (MAD) research.
This type of MAD research dramatically increased in laboratories in the USA between 2012 and 2014. The resulting accidents in which small outbreaks of novel viral diseases occurred led to three hundred scientists writing to the Obama administration asking for GoF to be stopped. The US Government responded by announcing a pause on the research in 2014 because of the inherent dangers.[24]
In the same year Dr Fauci, whose recorded belief was that the studies were worth the risk,[25] gave money from the NIH to Dr Daszak of Ecohealth Alliance to continue GoF research on coronaviruses.[26] This was carried out at the Wuhan Institute of Virology using genetically engineered humanized mice, culminating in reports in 2017 and 2018 that the researchers had successfully made harmless coronaviruses pathogenic to humans.[27]
In the autumn of 2019 the Covid-19 pandemic of SARS-2 started in Wuhan and, to date, over five million people across the world have died from the virus.
Are pandemics ever zoonotic?
In addition to stating erroneously that viruses only rarely escape from laboratories and/or that SARS-Cov-2 was unlikely to have done so, Drs Daszak and Fauci hold that most pandemics are zoonotic in origin. They say that pandemics start from a disease spreading from an animal but they do not state the time period involved. I would suggest that pandemics never occur from the immediate spread from an animal. In order for a pandemic to occur, a reservoir of the infection, adapted to human beings, must develop. This usually takes many years. Moreover the spread usually occurs due to the unnaturally large movement of people that occurs due to wars and famines.
I will give just a couple of well known examples.
When the Europeans invaded the Americas, 90% or more of the indigenous people of America died from the introduced diseases, which included measles, smallpox and mumps. In return, syphilis spread to Europe. Yes, the diseases had all arisen from animals initially, but the adaptation to make them pathogenic enough to cause a pandemic must have occurred over a period of the several thousand years during which the populations of Europe and America were separated.
AIDS was discovered in the early 1980s and it was soon clear that the Human Immunodeficiency Virus had arisen from the Simian Immunodeficiency Virus. However, studies have concluded that the first transmission of SIV to HIV in humans took place around 1920 in Kinshasa in the Democratic Republic of Congo (DR Congo),[28] so that it had at least 40–50 years of sporadic infection of human beings before it started to spread round the world as a pandemic. During that time there were many local wars in Africa and, of course, the 2nd World War.
In my book PANDEMIC, I document the world’s worst pandemics and conclude that it is only malaria that seems to be indifferent to wars, killing people whether or not there are hostilities. All other historical pandemics have at least some connection with war and occur when isolated groups with an endemic disease meet another group without the disease.
Conclusion
Thus historically we come to an impasse with SARS-CoV-2. This arose in a city many miles away from an animal population that might have harboured a similar virus, at a time when the supposed original host was dormant (late autumn), near a laboratory known to be working on the viruses. It then spread from person to person at an alarming rate and was seen to be totally adapted to human beings, to the extent that it was unable to even infect the bat it was supposed to have arisen from.
As a person who has studied the history of pandemics and lab leaks, imagine my surprise when authorities, not only in China but also in the USA and UK, stated categorically that the virus was obviously zoonotic and we were conspiracy theorists if we proposed the opposite. I had to conclude that they were misguided or purposely lying.
References
1. Matthews J (2021). WHO investigation descends into farce in rush to rule out a lab leak. GMWatch. 10 Feb. https://www.gmwatch.org/en/news/archive/2021-articles2/19691
2. Morse SS et al (2012). Prediction and prevention of the next pandemic zoonosis. The Lancet 1-7 Dec; 380(9857):1956–1965. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3712877/
3. Matthews J (2020). Why are the lab escape denialists telling such brazen lies? GMWatch. 17 Jun. https://gmwatch.org/en/news/archive/2020-articles/19437
4. Morens DM, Fauci AS (2020). Emerging pandemic diseases: How we got to COVID-19. Cell 182. 3 Dec. https://www.cell.com/cell/pdf/S0092-8674(20)31012-6.pdf
5. Chaffetz J (2022). Fauci, Feds tried to quash COVID lab leak origin theory – protecting Chinese interests over American lives. Fox News. 27 Jan. https://www.foxnews.com/opinion/fauci-covid-lab-leak-origin-theory-china-jason-chaffetz
6. Wade N (2022). Emails reveal scientists suspected COVID leaked from Wuhan lab – then quickly censored themselves. New York Post. 17 Feb. https://nypost.com/2022/01/24/emails-reveal-suspected-covid-leaked-from-a-wuhan-lab-then-censored-themselves/
7. Carlson J, Mahncke H (2021). Behind the scenes of the natural origin narrative. Epoch Times. 30 Sep. https://www.theepochtimes.com/behind-the-scenes-of-the-natural-origin-narrative_4023181.html
8. Wade N (2022). As above.
9. Andersen KG et al (2020). The proximal origin of SARS-CoV-2. Nature Medicine 26:450–452. 17 Mar. https://www.nature.com/articles/s41591-020-0820-9
10. Wade N (2022). As above.
11. Wade N (2022). As above.
12. Lerner S, Hvistendahl M, Hibbett M (2021). NIH documents provide new evidence US funded gain-of-function research in Wuhan. The Intercept. 10 Sep. https://theintercept.com/2021/09/09/covid-origins-gain-of-function-research/
13. Board on Life Sciences et al (2015). Gain-of-function research: Background and alternatives. In: Potential Risks and Benefits of Gain-of-Function Research: Summary of a Workshop. National Academies Press (US). Apr 13. https://www.ncbi.nlm.nih.gov/books/NBK285579/
14. Williams G (1959). Virus Hunters. Knopf.
15. Goddard PR (2020). PANDEMIC: Plagues, Pestilence and War: A Personalised History. Clinical Press. https://www.amazon.co.uk/PANDEMIC-Paul-Goddard-MD-FRCR/dp/1854570994
16. Williams G (1959). Virus Hunters. As above.
17. Feng P (undated). Yellow fever. National Museum of the United States Army. https://armyhistory.org/major-walter-reed-and-the-eradication-of-yellow-fever/
18. College of Physicians of Philadelphia (undated). Jesse Lazear. https://www.historyofvaccines.org/content/jesse-lazear
19. Berry GP and Kitchen SF (1931). Yellow fever accidentally contracted in the laboratory: A study of seven cases. The American Journal of Tropical Medicine and Hygiene s1–11(6):365–434. https://www.ajtmh.org/view/journals/tpmd/s1-11/6/article-p365.xml
20. Wikipedia (undated). Biosafety level. https://en.wikipedia.org/wiki/Biosafety_level#:~:text=The%20first%20prototype%20Class%20III,Laboratories%2C%20Camp%20Detrick%2C%20Maryland.
21. Mihm S (2021). The history of lab leaks has lots of entries. Bloomberg. 27 May. https://www.bloomberg.com/opinion/articles/2021-05-27/covid-19-and-lab-leak-history-smallpox-h1n1-sars
22. Sources:
* 1967 https://www.who.int/news-room/fact-sheets/detail/marburg-virus-disease
* 1966 and 1978 https://en.wikipedia.org/wiki/1978_smallpox_outbreak_in_the_United_Kingdom
* 1971 Aral smallpox incident: https://en.wikipedia.org/wiki/1971_Aral_smallpox_incident; 1973 https://api.parliament.uk/historic-hansard/written-answers/1973/apr/12/smallpox
* 1977, 1979 The history of lab leaks has lots of entries: https://www.bloomberg.com/opinion/articles/2021-05-27/covid-19-and-lab-leak-history-smallpox-h1n1-sars
* 2003-2017 Breaches of safety regulations are probable cause of recent SARS outbreak, WHO says BMJ. 2004 May 22; 328(7450): 1222 and The Origin of the Virus (Clinical Press, Bristol) 2021;
* 2007 https://en.wikipedia.org/wiki/2007_United_Kingdom_foot-and-mouth_outbreak
* 2015 US military accidentally ships live anthrax to labs. https://doi.org/10.1038/nature.2015.17653
23. Herfst S et al (2012). Airborne transmission of influenza A/H5N1 virus between ferrets. Science 336(6088):1534-41. https://pubmed.ncbi.nlm.nih.gov/22723413/
24. The White House (2014). Doing diligence to assess the risks and benefits of life sciences gain-of-function research. 17 Oct. https://obamawhitehouse.archives.gov/blog/2014/10/17/doing-diligence-assess-risks-and-benefits-life-sciences-gain-function-research
25. Fonrouge G (2021). Fauci once argued for risky viral experiments – even if they can lead to pandemic. New York Post. 28 May. https://nypost.com/2021/05/28/fauci-once-argued-viral-experiments-worth-the-risk-of-pandemic/ ; Barnard P, Quay S, Dalgleish A (2021). The Origin of the Virus. Clinical Press.
26. NIH (2014). Understanding the Risk of Bat Coronavirus Emergence. Project Number 1R01AI110964-01. https://reporter.nih.gov/search/-bvPCvB7zkyvb1AjAgW5Yg/project-details/8674931
27. Barnard P, Quay S, Dalgleish A (2021). The Origin of the Virus. Clinical Press.
28. Avert (2019). Origin of HIV and AIDS. https://www.avert.org/professionals/history-hiv-aids/origin
About the author: Professor Paul R Goddard BSc, MBBS, MD, DMRD, FRCR, FBIR, FHEA is Emeritus Professor, University of the West of England, Bristol; retired consultant radiologist; and former president of the Radiology Section of the Royal Society of Medicine. He is the author of PANDEMIC, A Personalised History of Plagues, Pestilence and War, Clinical Press Ltd, August 2020, and PANDEMIC, 2nd Edition 2021, Clinical Press, Bristol, available from Gazelle Book Services Ltd and good bookshops, ISBN 978-1-85-457105-2. On a similar theme, see The Origin of the Virus, Clinical Press 2021.
The above article is adapted from material that was first presented as the Long Fox lecture to The Bristol Medico-Chirurgical Society and Bristol University (2017) and to the British Society for the History of Medicine Biennial Congress (September 2021).
Pfizer Steps Up Advertising for Its ‘Blockbuster’ Drug to Treat Heart Conditions…
… Including Those Caused by COVID Vaccines
By Michael Nevradakis, Ph.D. | The Defender | February 24, 2022
Two major pharmaceutical companies chose February, the month of love — or hearts — to launch an advertising campaign urging people experiencing heart issues for the first time to visit their doctors.
Pfizer and Bristol Myers Squibb (BMS) this month revived the “No Time to Wait” ad campaign, spending $1.28 million on TV ads alone.
The campaign warns anyone experiencing palpitations and shortness of breath that they may be at increased risk of developing atrial fibrillation (AF), deep vein thrombosis (DVT), other types of blood clots and strokes — the same types of cardiovascular ailments found among people who have received COVID-19 vaccines.
The campaign urges viewers to seek early medical attention in order to reduce the risk of these serious complications.
“Early medical attention” could include prescription drugs — including Eliquis, developed and marketed by none other than Pfizer and BMS.
According to industry publication Fierce Pharma :
“The aim is to get patients back into their doctors’ offices — and of course, if needed, be diagnosed with any relevant condition that may require them to take a blood thinner, such as Eliquis.”
Eliquis, described as a “blockbuster blood thinner and atrial fibrillation (AF) drug,” is a major revenue generator for the Pfizer-BMS alliance, delivering more than $9 billion in annual revenue — far more than competing drugs such as Xarelto (produced by Bayer in conjunction with Johnson & Johnson), and Pradaxa, produced by Boehringer Ingelheim.
Pfizer and BMS relaunched the “No Time to Wait” campaign in conjunction with several advocacy organizations and medical societies, including World Thrombosis Day, which expressed support for the Pfizer-BMS initiative as a means of “educating” the public.
Characterized as a “surround-sound campaign,” Pfizer-BMS use television, radio and social media to deliver the “No Time to Wait” message to the public.
As part of the campaign, a DVT and pulmonary embolism (PE) television advertisement debuted on Valentine’s Day, Feb. 14. The ad showed two patients describing how they “didn’t wait” to speak to their doctors about the AF, DVT and PE symptoms they had begun to experience while performing everyday activities.
Speaking to the camera, the two actors describe symptoms, such as shortness of breath and a racing heart, which are potential indicators of AF, DVT and PE.
Official campaign literature urges the public to take action:
“Right now, people may be weighing a decision to visit a healthcare provider. However, symptoms like swelling, pain, tenderness or redness in the leg, thigh or pelvis can possibly be related to a potentially serious condition such as deep vein thrombosis (DVT). It’s critical to not brush off these symptoms.”
BMS, via its spokesperson, described the reasons for relaunching the campaign:
“We received so much positive feedback from patients and advocates on the impact this campaign had on patients, we knew it was our responsibility to continue to evolve the program and further get the message out.
“In the middle of 2021, we decided to evolve the campaign, with new insight that symptomatic people at risk for AFib or DVT/PE can often dismiss their symptoms or misattribute [emphasis added] them to other health and lifestyle factors.”
Could “misattribute,” in this instance, actually refer to cases where those who had recently received a COVID vaccine experienced the onset of heart-related conditions, in some cases leading to their deaths?
Is Pfizer benefitting from vaccine-induced ailments?
Could the relaunching of the “No Time to Wait” campaign represent an effort by Pfizer to engage in damage control from the increase in vaccine-induced heart conditions — while benefiting from the sale of a drug used to address those same ailments?
There are several objectives Pfizer and BMS could accomplish with the campaign.
First, by launching an advertising campaign warning people they may be at risk of certain heart conditions, Pfizer and BMS are in a sense “naturalizing” heart ailments in young and/or healthy individuals.
Second, by “naturalizing” the prevalence and likelihood of such heart conditions, these companies may deflect blame for these conditions from COVID vaccines, including the Pfizer-BioNTech vaccine.
Third, by referring patients to their doctors, the Pfizer-BMS alliance may directly benefit financially from the increased prevalence of heart ailments and conditions in the vaccinated public — as doctors prescribe more Eliquis, the top-selling blood thinner and AF drug, to treat their symptoms.
‘Normalizing’ heart conditions in young and healthy
According to Pfizer and the Centers for Disease Control and Prevention (CDC), even “the healthiest athletes” are now at risk for blood clots, as stated in an urgent warning issued this month.
The media and health authorities in recent months have proffered multiple explanations for why healthy people are developing blood clotting and heart conditions, blaming everything from weather and energy bills to cannabis use — but not COVID vaccines.
Here are some examples:
- September 2021: The Times of India ran a story on a “doctors’ reminder” that “nobody is too young for a heart attack.”
- September 2021: A study indicated that cannabis use doubled the risk of heart attacks in young adults.
- October 2021: The New York Post reported on “[t]he little-known heart attack that’s striking ‘fit and healthy’ women as young as 22.”
- November 2021: British tabloid The Sun reported on “[t]he ways cold weather can affect your body — from winter vagina to blood clots.”
- November 2021: A Times of India report asked why heart attacks are “becoming common in ‘seemingly’ fit people.”
- November 2021: Healthline reported e-cigarettes can raise the risk of heart disease and stroke.
- December 2021: Another British tabloid, Express, warned about the “healthy” diet that “may ‘increase’ your risk of having a heart attack.”
- January 2022: Norton Health informed us that “[p]reventing heart disease in children is becoming more urgent as more kids develop heart disease.”
- January 2022: A report is published warning that “sports can break your heart in more ways than one.”
- January 2022: A report by CT (Connecticut) Insider indicated more people were suffering from heart disease and strokes “after COVID.”
- January 2022: The Daily Mail warned the “[r]isk of heart problems could be increased even if you drink less than NHS weekly units,” referring to recommendations made by the UK’s National Health Service.
- January 2022: The Sun ran a report claiming weather can “harm” one’s health, leading to heart attacks, stroke or gout.
- January 2022: Another report by The Sun warned 300,000 Brits were “living with [a] stealth disease that could kill within 5 years.” The “stealth disease” in question is aortic valve stenosis, a condition where the heart’s aortic valve narrows.
- February 2022: Nature magazine reported the risk of heart disease “soars after COVID — even with a mild case.”
- February 2022: A doctor interviewed on the UK’s ITV warned an increase in energy bill amounts may cause heart attacks and strokes.
Mark Crispin Miller, professor of media, culture and communication at New York University and founder of News from Underground compiled a list of reports like those listed above.
In looking at incidents and reports during the week of Feb. 8-14 alone, Crispin told readers:
“Before we note all those whose ‘sudden deaths’ made news just this past week — ‘unexpected deaths’ with no reported cause, or due to heart attacks, strokes, blood clots, cardiac arrest or swift, aggressive cancers (all known to be ‘adverse events’ post-‘vaccination’) — let’s review how this unprecedented global spike in sudden death has been deliberately obscured by ‘our free press.’”
Miller highlighted an ABC News report, “‘Broken heart’ cases surge during COVID, especially among women.”
In another example, Science magazine reported geneticists found the answer to “sudden unexplained child deaths.”
Downplaying of the connection between the COVID vaccines and serious heart conditions often has involved high-profile athletes.
For instance, 33-year-old soccer star Sergio Aguero of FC Barcelona was forced to announce his retirement in December 2021, after suffering chest pains and dizziness during a match in October 2021. He never played again.
According to Aguero’s cardiologist, the vaccine was not the reason for his ailment and retirement.
However, Aguero himself, in a Twitter question-and-answer session earlier this month, did not reject this possibility, stating: “I don’t know if Covid or [the] vaccine caused my retirement.”
Media, however, continue to promote the narrative that vaccines have nothing to do with the surge in sudden illnesses or deaths among athletes.
For example, Miller cited a Feb. 1 Washington Post article describing stories of athletes dying due to COVID vaccination as a “falsehood.”
Miller then compared what he described as the “disgraceful” Washington Post report with a documented timeline of athletes who suffered from heart failure between March 2021 and January 2022.
This string of incidents is further illustrated and detailed by the Real Science blog, which found 707 such incidents as of this writing and demonstrated in graphical form the sharp increase in heart failure incidents involving athletes over the course of 2021 and into 2022, as COVID vaccination uptake increased.
Nevertheless, Politifact, in December 2021, assured the public “[t]here’s no proof athletes collapsed with heart issues because of COVID-19 vaccination,” while in November 2021, U.S. News & World Report warned “COVID may trigger [a] heart condition in young athletes.”
As reports of vaccine-induced heart ailments rise, studies confirm link
Multiple studies and reports have confirmed a link between COVID vaccines and heart ailments.
These reports include:
- September 2021: A report found adolescent boys are at higher risk of hospitalization from the Pfizer vaccine than from COVID.
- November 2021: Renowned cardiologist Dr. Steven Gundry warned the Pfizer and Moderna COVID vaccines “dramatically increase” the risk of heart attacks.
- January 2022: Data from the Vaccine Adverse Event Reporting System (VAERS) indicates myocarditis tops the list of COVID vaccine injuries for 12- to 17-year olds.
Meanwhile, reports continue to grow of previously healthy people who develop heart conditions following COVID vaccines.
Here are just a few examples:
- June 2021: A 13-year-old Michigan boy died three days after receiving the second dose of the Pfizer COVID-19 vaccine.
- June 2021: An athlete who received the second dose of the Pfizer vaccine developed myocarditis, triggered by the vaccine.
- August 2021: A 14-year-old boy developed myocarditis after receiving the Pfizer vaccine.
- October 2021: A 17-year-old developed multisystem inflammatory syndrome and myocarditis after receiving the Pfizer vaccine.
- December 2021: A 26-year-old’s death from heart inflammation was found to have “probably” been caused by the Pfizer vaccine.
- January 2022: An autopsy found the death of another 26-year-old from myocarditis was the direct result of receiving the Pfizer vaccine.
- February 2022: A six-year-old developed vaccine-induced myocarditis, leaving him unable to walk.
- February 2022: Autopsies showed that the deaths of two teenage boys who died soon after receiving the Pfizer vaccine were directly caused by the vaccine.
Reports and studies like those listed above have led to increasing calls for the vaccination of minors to be reassessed or outright halted, including:
- January 2022: More than 30 experts called on UK regulators to reassess COVID vaccination for 12- to 15-year olds.
- January 2022: Data revealed reports of heart disease following COVID vaccines had increased 15,600% in young people under the age of 30, compared to the previous 31 years of heart injuries reported following receipt of FDA-approved vaccines.
They’ve also triggered calls for further scrutiny on the part of health authorities, which appear to have had some effect, at least in certain instances.
For example:
- October 2021: The U.S. Food and Drug Administration delayed a decision on green-lighting the administration of the Moderna vaccine to adolescents, citing heart problems (however, the Pfizer vaccine was nevertheless approved for the same age group).
- October 2021: Health authorities in Denmark and Sweden paused administration of the COVID vaccine to younger age groups, citing reports of myocarditis.
- December 2021: The CDC was monitoring eight cases of heart inflammation reported in 5- to 11-year-olds who received the Pfizer vaccine.
Nevertheless, in January 2022, the Centers for Disease Control and Prevention (CDC) refused to investigate the case of a 13-year-old who died of myocarditis days after receiving the Pfizer vaccine, while in August 2021, doctors “downplayed” the connection between the onset of myocarditis in a 25-year-old, and receipt of the Moderna vaccine.
‘No Time to Wait’ campaign spending indicative of broader Big Pharma marketing expenditures
Big-dollar ad spending is par for the course for Big Pharma companies such as Pfizer, as previously reported by The Defender.
For instance, a 2019 Forbes article reported Pfizer spent twice as much on marketing/selling as it spent on research.
Pfizer’s heavy advertising is also evident in its most recent quarterly report, for the fourth quarter of 2021. The report indicates a 10% increase — a total of $12.7 billion — in 2021 “SI&A expenses,” which include marketing and advertising, as compared to 2020, when there was no COVID vaccine available.
The report also projects Pfizer’s SI&A expenses will range between $12.5 and $13.5 billion in 2022.
BMS, in turn, spent $990 million in advertising and marketing in both 2020 and 2021 — after spending $633 million in 2019.
In sum, pharmaceutical ad spending totaled $6.58 billion in 2020, and was expected to surpass $11 billion by the end of 2021 — including $3.9 billion in spending on television advertisements alone.
In addition to “traditional” advertising and marketing campaigns, pharmaceutical companies adopted some more creative ways to promote their products — and perhaps purchase further goodwill on the part of media outlets.
In an October 2021 article, The Defender highlighted several examples of Pfizer sponsoring television news programs and segments, ranging from “Good Morning America” to “Anderson Cooper 360°” to “CBS HealthWatch.”
For example, an Oct. 4, 2021 tweet posted on CNBC’s official Twitter account portrayed Pfizer in glowing terms, accompanied by the text: “paid post for Pfizer.”
And a March 15, 2021 tweet by Pfizer expressed pride in the release of a National Geographic documentary, “Mission Possible: The Race for a Vaccine.”
Michael Nevradakis, Ph.D., is an independent journalist and researcher based in Athens, Greece.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Financial conflicts within government advisory groups
JCVI – don’t bite the hand…
Health Advisory & Recovery Team | February 25, 2022
There’s a well known expression “Don’t bite the hand that feeds you.” It can be taken literally – if an animal bites the hand that feeds it, it won’t get fed. In the business or academic world, it means don’t upset your funder. It’s obvious really – if you do, they won’t fund you anymore. The bigger the amount received, the less of a good idea it is to upset the funder.
The Joint Committee on Vaccination and Immunisation (JCVI) “advises UK health departments on immunisation.”[i] The JCVI has a sub-committee specifically to advise on COVID-19 vaccines. The chair of the JCVI, Professor Andrew Pollard, recused himself from all JCVI COVID-19 meetings because he is involved in the development of a SARS-CoV-2 vaccine at Oxford University – where he works. This was done to avoid any “perceived conflict of interest.”
Professor Lim Wei Shen was appointed chair of the JCVI sub-committee on COVID-19 vaccines. In August 2021, he stated categorically that 12-15 year olds would not be offered COVID-19 vaccines.[ii] Barely 6 weeks after that statement, 12-15 year olds were offered jabs.[iii] Barely 6 months later, on February 16th, 2022, the sub-committee issued a statement saying that, although 5-11 year olds are “generally at very low risk of serious illness from the virus”, they would be offered 2 doses of the Pfizer mRNA jab.[iv] This recommendation occurred despite the trials in children not being due for completion until May 2026.[v] We have previously noted that Professor Lim has a substantial conflict of interest: he has direct responsibility for material levels of funding received by his department from Pfizer.
At the time of writing, the most recent minutes for the sub-committee meetings are from May 2021. The sub-committee and main JCVI minutes report “Declarations of Interest” for the committee members. The Code of Practice describes the JCVI as “an independent Departmental Expert Committee and a statutory body.”[vi] Independent being the word of interest. One would expect this to mean “free from conflicts of interest”, but a closer look revealed that this was not the case.
The COVID-19 sub-committee of the JCVI has 15 core members (1 lay member). None of the members of this sub-committee declared conflicts of interests. Five of the 14 non-lay members provided additional information in their ‘non-declaration’ that revealed conflicts of interest. One, for example, declared funding from “the National Institute for Health Research, the Medical Research Council, the Wellcome Trust and Gavi, The Vaccine Alliance, and the Bill & Melinda Gates Foundation”, but didn’t consider any of that vaccine funding as a conflict of interest. A cursory search on the remaining nine members revealed that six had conflicts of interest – from running a COVID-19 vaccine trial to being their organisation’s representative for Pfizer. One member failed to declare that he leads the Pfizer Vaccine Centre of Excellence in Bristol.
The members work for organisations, which collectively have received approximately $1,000,000,000 – one billion dollars – from the Bill and Melinda Gates Foundation. The Gates Foundation aims to “accelerate the development and commercialization of novel vaccines and the sustainable manufacture of existing vaccines.”[vii] No doubt the Gates Foundation would have welcomed the sub-committee’s decision.
The majority of the COVID-19 JCVI sub-committee members have conflicts of interest. These members don’t seem to realise that their research or institution receiving huge sums of money from pharmaceutical companies and/or the Gates Foundation is a conflict of interest.
Has this committee truly been able to provide an independent assessment of the risk and reward of the main products of interest of the Gates Foundation? Or has it made a decision to not bite the hand that feeds it?
Read full article here:
- [i] https://www.gov.uk/government/groups/joint-committee-on-vaccination-and-immunisation#conflict-of-interests
- [ii] https://www.youtube.com/watch?v=9RS1v7jN94w
- [iii] https://www.england.nhs.uk/2021/09/nhs-rolls-out-covid-19-jab-to-children-aged-12-to-15/
- [iv] https://www.gov.uk/government/news/jcvi-updates-advice-on-vaccinations-for-5-to-11-age-group
- [v] https://clinicaltrials.gov/ct2/show/NCT04816643
- [vi] https://assets.publishing.service.gov.uk/government/uploads/system/uploads/attachment_data/file/224864/JCVI_Code_of_Practice_revision_2013_-_final.pdf
- [vii] https://www.gatesfoundation.org/our-work/programs/global-health/vaccine-development-and-surveillance
Featured Video

Death Spikes & Rising Cancer In Our Youth Explained
or go to
Aletho News Archives – Video-Images
From the Archives
Politicians lie
By Mazin Qumsiyeh | Popular Resistance | August 18, 2013
There is no way to say this truth nicely: Politicians lie. That includes Japanese, American, Egyptian, Israeli, and Palestinian politicians! Is there something more common sense than that? Yet, so many citizens around the world believe their own politicians or wistfully acknowledge lies but think it is part of the job needed to run things. They believe even when politicians contradict themselves blatantly. This phenomenon is rather remarkable. It is a dissonance and disconnect from reality that many seem oblivious to. It is very dangerous because it can lead to accepting rationales for going to war. These can be deadly wars that lead to millions of lives lost as happened in what was called World War 1 and WW2. Even when incredible and declassified evidence abound, politicians continue to lie and old mythologies refuse to die. Here are just a few of the countless lies told to us over the past few decades… continue
Blog Roll
 Aletho News
- RSF military group defects, joins Sudanese army: State media
- Ireland goalkeeper refuses to play ‘Israel’ as squad weighs boycott
- China pushes back against US on Cuba, Iran
- Ukrainian Soldiers, Potential Mercenaries: Have Gun, Will Travel!
- Burnham’s UN debut… A masterclass in British disinformation
- Iran flights continue despite US aviation sanctions
- Global Tipping Points Lead the World Into a State of Entropy
- The day-after at the White House: USA and Xi Jinping
- The Geopolitical Balance in the Red Sea: The UAE Being Displaced by New Players
- Iraqi resistance group vows to stage airport sit-ins over Iran aerial blockade
- If Americans Knew
- Deconstructing Netanyahu’s pants-on-fire UN rant – Daily Update
- Trump betrayed voters with his campaign lies and prioritized a foreign country once he took office
- Netanyahu calls Israel’s war in Gaza ‘opposite of genocide’ in UN speech to near-empty hall
- Settler Kidnappings: Torture, Sexual Abuse and Terrorisation of Palestinian Abductees as Israel Deepens Annexation of West Bank
- Gaza winter nears as 162,000 tents become unusable, raising fears of humanitarian crisis
- Netanyahu says, “It’s the opposite of genocide”; UN says Gaza economy is world’s ‘most severe crisis on record’ – Daily Update
- Israel’s US-Backed Assault on Gaza Has Created the ‘World’s Most Severe Economic Crisis on Record’: UN
- ‘Protecting U.S. Citizens’… From Israel
- ‘This is where I live now, the back of a truck’: a day in the life of a grandmother in Gaza
- In UN Speech, Iran’s President Displays Pictures of Children Killed by US, Brings Attention to Israel’s Nuclear Arsenal
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years