Viral Tweet Opposing ‘Herd Immunity’ Gets Pretty Much Everything Wrong
By Noah Carl • The Daily Sceptic • October 22, 2021
In a recent viral tweet, the anti-Brexit campaigner Jolyon Maugham criticised the Government’s initial Covid strategy (which, as we know, was later ditched in favour of lockdowns).

I’m no defender of the Government’s response to the pandemic, but it’s hard to imagine a more wrong-headed criticism than this. Indeed, it’s impressive how many fallacies Maugham managed to pack into 280 characters.
First: “Herd immunity”. As the authors of the Great Barrington Declaration have tirelessly pointed out, describing any response to the pandemic as a ‘herd immunity strategy’ is like describing a pilot’s plan to land a plane as a ‘gravity strategy’. Given that Covid cannot be eliminated, herd immunity will eventually be reached, regardless of what we do.
The goal of any plan to address Covid, write Kulldorff and Bhattacharya, “should be to minimise disease mortality and the collateral harms from the plan itself, while managing the build-up of immunity in the population.”
Second, the implication of Maugham’s tweet is that the Government’s initial strategy was motivated by Conservative ideology, and that the alternative – lockdown – is what’s backed by science.
Yet, as I and others have pointed out, it’s actually lockdown that deviates substantially from the pre-Covid consensus. Indeed, the UK’s pandemic preparedness plan does not even mention the term. And in 2019, the WHO classified “quarantine of exposed individuals” as “not recommended under any circumstances”.
Given that the first lockdown was implemented by a communist one-party state, and that subsequent lockdowns were imposed with almost no prior discussion, it would make more sense to say lockdown was motivated by ideology.
Third, the virus does not “target” working class and poorer people, while leaving Etonians and bankers unscathed. It is not some pathogenic agent of class warfare.
If “target” is taken to mean “infect”, then the virus targets people who aren’t immune to it. And if “target” is taken to mean “kill”, then it would be most accurate to say the virus targets the old and the immunocompromised. After all, these groups account for the overwhelming majority of deaths.
Now, it’s true that death rates have been higher in working class occupations, as I noted in a previous post. But this is far more plausibly due to lockdown than to the Government’s initial strategy, which was in any case abandoned in March of 2020.
As the art critic J. J. Charlesworth quipped, “There was never any lockdown. There was just middle-class people hiding while working-class people brought them things.” Middle-class people like Jolyon Maugham, I might add.
Illinois Sheriffs Reject Mayor Lightfoot’s Urgent Plea To Cover Police Shortage In Crime-Hit Chicago
By Tyler Durden | Zero Hedge | October 22, 2021
As hundreds of Chicago police are being put on “no-pay leave” over their refusal to submit their personal Covid vaccination status with the city, Chicago Mayor Lori Lightfoot appears to have fewer and fewer allies as she desperately tries to fill the gap of officer shortages due to the vax order. Area county sheriffs are refusing to send additional manpower that’s she requesting to urgently cover the gaps, telling her that’s it’s a problem of the mayor’s own making.
“Chicago Mayor Lori Lightfoot received a rude awakening after multiple sheriffs in nearby jurisdictions refused her request to fill the gap in police manpower after she threatened to fire 3,000 local officers for not complying with the city’s COVID-19 vaccine mandate,” The Washington Examiner reports on the latest developments. “DuPage County Sheriff James Mendrick and Kane County Sheriff Ron Hain said they’ve helped Lightfoot in the past, but her latest request is a self-inflicted wound that could have been avoided. They said they would only step in and help the Chicago Police Department if city officers were in distress or under duress.”
Sheriff Hain had this to say, echoing recent criticisms of the Chicago police union which has cited terrible communication and heavy-handedness in place of requests for dialogue on the issue: “[The Illinois Law Enforcement Alarm System] typically responds to emergency situations where there is no opportunity for planning,” Hain said. “This situation to me is much different.”
Despite sheriff’s offices shutting the door on the mayor’s request to cover Chicago PD officer shortages, police continue to reportedly be summoned to headquarters where they are given one last on the spot ultimatum: submit to last week’s vaccine status order or be relieved from duty without pay.
So far the city says it’s not yet going after street patrol officers, which is obviously on fears of a coming crime wave that will hit an already understaffed notoriously high-crime city.
BBC has compiled recent statistics as the standoff over the vax mandate continues:
Chicago, a city of nearly three million people, has seen more than 1,600 sexual assaults, nearly 3,000 shootings and 649 murders this year – a 14% increase over last.
Just as violent crimes have risen, though, thousands of the city’s police force may not show up to work.
… Nearly one-third of Chicago’s almost 13,000-member police department have so far refused to register their vaccination status, putting them on track for dismissal. Twenty-one have been officially removed from active duty so far, but some officials have warned that the mandate could leave Chicago’s police force dangerously depleted.
Adding fuel to the fire of the crisis, President Joe Biden during his CNN Town Hall remarks Thursday night continued pushing his view that emergency responders should be fired for defying local vaccine mandates.
The president even appeared to mock those rejecting vaccine mandates on the basis of “freedom”…
“I have the freedom to kill you with my COVID,” Biden said, mocking what he sees as the attitude of mandate opponents. “No, I mean, come on, freedom.”
Meanwhile the head of Chicago’s largest police union, John Catanzara, is still urging officers to hold the line, despite a weekend gag order imposed on him by the city.
“It is the city’s clear attempt to force officers to ‘Chicken Little, the sky is falling’ into compliance,” he’s recently urged the union’s 11,000 members. “Do not fall for it. Hold the line.”
CDC Director: We may need to update our definition of ‘fully vaccinated’
By Kit Knightly | OffGuardian | October 23, 2021
Yesterday, in a press conference, the director of the CDC warned that they may have to “update” the definition of “fully vaccinated”.
At the virtual presser accompanying the approval of “mix-and-match” booster jabs, Dr Rochelle Walensky told reporters that:
We will continue to look at this. We may need to update our definition of ‘fully vaccinated’ in the future,
The “updated” definition would potentially mean only people who have had the third “booster” shot would be considered “fully vaccinated”, while people who have had the two original shots are no longer “fully vaccinated”.
Whilst the warning might just be a ploy to scare people into getting their “booster” without forcing them to, it should be noted a revised definition of “fully vaccinated” has already been adopted in other countries.
For example, it is already policy in Israel where, in early September they “updated what it means to be vaccinated,”. You now need a third shot, or else you are no longer considered vaccinated.
We wrote about it at the time, and predicted it would likely spread to the rest of the world.
In fact, figures in the alternate media have been predicting this for a while. See this clip from YouTuber WhatsHerFace back in August:
As for the potential purpose of any “updated definition”, well it would be twofold.
Firstly, it would allow them to maintain control. Forcing people to jump through hoops just to “get back” rights they once took for granted creates an atmosphere that normalises state tyranny.
Secondly, and more cynically, it would allow them to artificially manipulate statistics to flatter the vaccines’ effectiveness whilst hiding any damage they might do.
We already know that, in the US and others, you’re not considered “vaccinated” if you’re only single-jabbed, or double-jabbed for less than two weeks. So any patient infected with “Covid” in that time is considered “unvaccinated”, NOT a “breakthrough infection”.
By redefining “fully vaccinated”, they can turn millions of double-jabbed people back into “unvaccinated” people and stop them from becoming potential “breakthrough infections” and hurting the vaccine effectiveness stats.
This will, in turn, camouflage any excess mortality in those who have had the vaccine, for example due to antibody-dependent enhancement, because all those who die will officially be “not fully vaccinated”.
They’ll likely push it through soon, before this winter’s flu season hits, so any flu deaths can be “unvaccinated covid deaths”.
And for anybody out there who got double-jabbed thinking they were buying their life back, we’re sorry, but we did warn you this would happen.
As Infection Rates for Vaccinated Aged 40-79 Hit Double the Rates in the Unvaccinated, the U.K. Health Security Agency Suggests that Vaccines May Hobble the Immune Response on Infection

By Will Jones • The Daily Sceptic • October 23, 2021
Another week, another Vaccine Surveillance report (now published by the U.K. Health Security Agency (UKHSA), the successor to Public Health England), and with it more worrying news on the vaccine front.
Infection rates in the double-vaccinated compared to the unvaccinated continue to rise, meaning unadjusted vaccine effectiveness continues to decline. Infection rates are now higher in the double-vaccinated compared to the unvaccinated by 124% in those in their 40s, 103% in those in their 50s and 60s and 101% in those in their 70s, corresponding to unadjusted vaccine effectiveness estimates of minus-124%, minus-103% and minus-101% respectively. For those over 80 the unadjusted vaccine effectiveness is minus-34% while for those in their 30s it is minus-27%. For 18-29 year-olds it is 25%, so still positive but low, while for under-18s it is 90%, the only age group showing high efficacy. Vaccine effectiveness against emergency hospital admission and death continues to hold up, though with some indication of gradual slide, particularly in older age groups (see below). (For definitions and limitations, see here.)

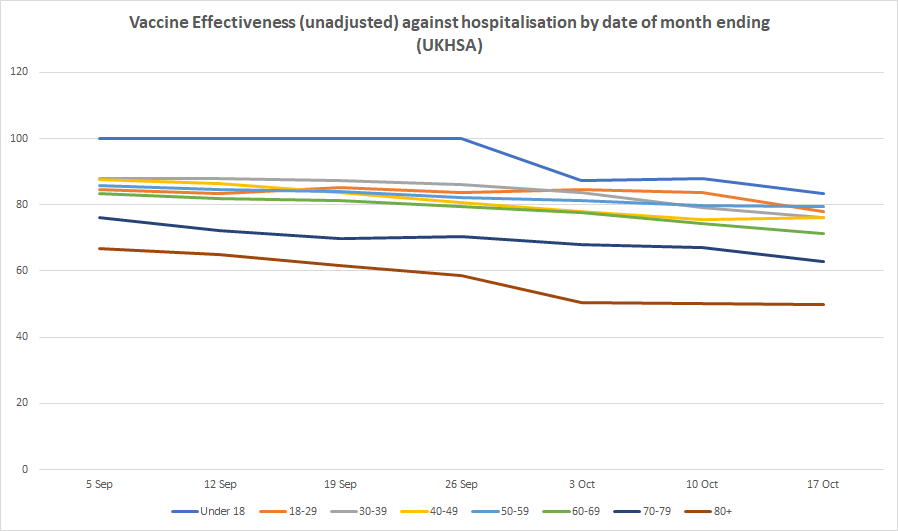

The UKHSA has continued to receive criticism for publishing this data, with claims that the figures used for the unvaccinated population are unreliable and likely too high, artificially suppressing the infection rate and vaccine effectiveness. Cambridge statistician Professor David Spiegelhalter put out a scathing tweet on these lines on Friday, but he didn’t elaborate on his claim or link to an article explaining it further.
Professors Norman Fenton and Martin Neil have argued that in fact the PHE/UKHSA data may underestimate the number of unvaccinated rather than overestimate them, which would have the reverse effect.
Either way though, what wouldn’t change is the fact of the large and fast decline in effectiveness against infection. This is now generally acknowledged among many scientists (likely caused by waning over time or new variants or both), though has not had the logical impact on Government policy one might have expected and hoped for of eliminating the rationale for vaccine passports and mandates.
A further point revealed for the first time in this week’s surveillance report is that the vaccines may actually hobble the body’s ability to develop the strongest immunity once infected. As noted by Alex Berenson, the report mentions (in passing) that “recent observations from U.K. Health Security Agency (UKHSA) surveillance data” show that “N antibody levels appear to be lower in individuals who acquire infection following two doses of vaccination”.
The report does not elaborate on this, but on the face of it it is a startling admission. It is basically saying that a certain kind of antibody which is not produced by the vaccines but is usually produced by infection (and hence is used by PHE/UKHSA to identify those with antibodies-from-infection) is not produced so well by those who are infected post-vaccination. Insofar as this is true it means the vaccines may actually prevent the immune system from developing the strongest form of protection against reinfection. This phenomenon of the immune system being in some way hobbled by the way it first encounters a pathogen is well-known and is referred to as original antigenic sin.
There would be a number of implications of this. It would mean that since the vaccine rollout got going the prevalence of N antibodies in the population has ceased to be a reliable measure of how many people are previously infected (which might explain why it has been rising so slowly during the Delta surge). It would also mean the vaccines may make reinfections and serious illness upon reinfection more likely. Plus likely other things as well.
This is something that should be investigated fully and the results published so that its impact can be properly assessed and understood.
Six Questions to Ask Before Deciding Whether to Comply With Mask Mandates
All the reasons why mask mandates shouldn’t be reimposed
By Dr. Gary Sidley • The Daily Sceptic • October 20, 2021
On the July 19th 2021, England removed almost all its legal mandates that required healthy people to wear face coverings in community settings. Scotland, Wales and Northern Ireland, however, opted to retain their mask mandates, as did London on its public transport system. Ominously, the Government’s Covid strategy for this winter includes the prospect of a ‘Plan B’ that could see the return of compulsory face masks in indoor settings in England. After a few months of bare-faced normality, how will the general public react to future directives to muzzle up?
Smile Free – a campaign group seeking the permanent removal of all mask mandates – urges each person to consider the responses to the following six questions before deciding whether to hide your face again.
Q1. Do masks help reduce viral spread?
Although some studies claim otherwise, the real-world evidence strongly suggests that masking the healthy does not significantly reduce the spread of respiratory viruses for neither the wearer nor others. Key reasons for this lack of efficacy are likely to include the improper use and storage of masks in the real world and the growing recognition that SARS-CoV-2 (the virus responsible for COVID-19) is spread via microscopic aerosol particles that are far too small to be kept at bay by face coverings.
Q2. Will wearing a mask cause me any physical harm?
If worn only for short periods, significant physical harms from wearing a mask are unlikely. However, there is evidence that long term use can lead to a number of negative consequences, including: headaches, skin irritation, fatigue and dehydration, reduced heart and lung efficiency and eye irritation. In addition, face coverings may put elderly people at more risk of injury from falls.
Q3. Do masks cause any social or psychological harms?
The social and psychological consequences of hiding our faces from other people are profound. Humans are social animals. We need to interact with others and communicate to sustain our wellbeing. Face coverings are dehumanising, inhibiting all forms of emotional expression and social interaction. Individuality minimised, identity hidden, the masked population appear broadly the same as they trudge along in their social vacuums. The impact of a masked population on children is even more problematic, denying them access to facial expressions that are so crucial for their emotional development.
Q4. Will wearing a mask help to reassure others who are anxious?
Most definitely not. Acting as a crude, highly visible reminder that danger is all around, face coverings are fueling widespread anxiety. Fear is underpinned by a perception of threat and being masked is a blatant indicator that we are all bio-hazards. Furthermore, continuing to wear masks while we gradually try to return to normality will act to keep fear going, as the wearer may attribute their survival to the mask rather than conclude that it is now safe to return to everyday activities. To recommend face coverings as a source of reassurance is akin to insisting people wear a garlic clove around their necks to reduce their fear of vampires.
Q5. Under the law, do I have a ‘reasonable excuse’ not to wear a mask?
In general terms, if wearing a mask is likely to cause you ‘severe distress’, or put you ‘at risk of harm or injury’, you are legally exempt. Mental health problems (such as anxiety, depression, and paranoia) and physical health problems (such as asthma and other respiratory difficulties) are sufficient and lawful reasons not to wear a face covering. Furthermore, you are not obliged to disclose your specific reason for exemption to anybody other than an official enforcement officer (usually a police officer); any other person who challenges you about not wearing a face covering is likely to be acting unlawfully and thereby risking prosecution. Indeed, a service provider has been fined £7000 under the Discrimination Disability Act for denying access to a woman without a mask.
Q6. Do I risk being fined if I don’t wear a mask?
While it is possible that a fine could be imposed for not complying with a mask mandate, such an event seems rare. Thus, in the four-month period June-to-September 2020, only 89 fines were issued (61 on public transport, 28 in retail settings) across the whole of England and Wales. Furthermore, if you are unfortunate enough to receive a fine and decide to contest it in Court, it is highly likely you will succeed; according to figures produced by the Crown Prosecution Service, all charges under the Coronavirus Act have either been withdrawn in Court or quashed after innocent people were wrongfully indicted.
In conclusion, mandating masks for healthy people in their communities is irrational, counterproductive, unethical and ultimately unenforceable. To help continue the fight against legal requirements to wear face coverings, please consider joining our Smile Free campaign.
Covid Is A Deliberate Three-Pronged Attack On Our Health
By Rhoda Wilson | The Exposé | October 21, 2021
Kevin Galalae has published his research in a document titled: PCR Tests and the Depopulation Program. He concludes “the coronavirus blamed for countless deaths real and imagined is a political fiction. The symptoms attributed to Covid are caused by a deliberate three-pronged attack on our health and lives by our own national and international authorities.”
The deliberate three-pronged attack is summarised as follows:
- damage the epithelium of the nasopharyngeal cavity with PCR test swabs to bring down the immune defences that protect our brain
- create a closed loop between the mouth and the nose, thus between outgoing and incoming air, by forcing us to wear face masks throughout the day
- increase damage to the brain by subjecting us to chemicals and neurotoxins that could never reach the brain had they not destroyed the blood-brain barrier
Kevin Galalae is a Canadian human rights activist, author, journalist and historian. He has authored numerous books including Killing Us Softly: The Global Depopulation Policy. As an activist, Galalae has many notable accomplishments including matters in the United Kingdom, European Union and United Nations and is an ardent defender of a free World Wide Web.
Galalae is also an expert on the topic of the global depopulation policy – also known as Agenda 21, Agenda 2030 or population control. His biography makes interesting reading and, as downloaded from The EveryDay Concerned Citizen, is attached below.
The creator of the PCR test, Dr. Kary Mullis, has stated clearly and on many occasions that the results of the PCR tests can be easily misinterpreted to mean anything. The PCR testing methodology does not distinguish if positive results are infectious.
Given their invasive nature and the fact that they were never meant for diagnostic but for research purposes, why are they being used as often as possible on the same individuals and on as many people as possible? “Well, now I know how the system is misusing them!” Galalae exclaims and gives his explanation, with links to scientific research, in his twelve-page document: PCR Tests and the Depopulation Program (see attached below).
PCR Tests
“The long swab inserted into the nasopharyngeal cavity all the way to the roof of the nose … damages the fascicles of the olfactory nerve, which, as it turns out, has dire consequences for human health and lifespan because the olfactory nerve is one of only two windows in the cranium through which viruses and bacteria can move from nose to brain, thus can cross the blood-brain barrier, the other one being the trigeminal nerve.” – PCR Tests and the Depopulation Program

The olfactory nerve contains sensory nerve fibres relating to the sense of smell. It is the only cranial nerve that has stem cells – called olfactory ensheathing cells – which enable it to continually regenerate throughout life. They are the cells that protect the olfactory nerve and aid its regeneration in case of damage through age or injury. These cells are so unique that doctors have recently begun using them to successfully repair spinal cord injuries and to treat brain diseases.
Additionally, the olfactory ensheathing cells assist in innate immunity because they are phagocytic and, as such, ingest bacteria. The innate immune system includes all our body’s first line defences such as the physical barriers lining the nose, throat, lungs and gut, as well as the skin. Innate immunity provides broad protection and is quick to react to any threat. The olfactory ensheathing cells are thus a crucial part of the protection provided to the brain.
For adults aged between 57 and 85 years, once the olfactory ensheathing cells lose their ability to regenerate the chance of dying within five years is four times higher.
The PCR tests serve two important roles for the depopulation program.
In the short-term, by repeatedly damaging the olfactory nerve with nasal swabs the incidence of viral and bacterial infections is rapidly raised. This helps governments create and sustain the impression of a pandemic. The more people are tested the more people are damaged and left defenceless against various infections that are then mislabelled en masse as Covid infections. And, by simply raising the number of cycles in the thermal cycler the authorities get the percentage of positive results they want.
Juliet Morrison, a virologist at the University of California-Riverside, said she believes any test with a cycle threshold over 35 is too sensitive. “I’m shocked that people would think that 40 could represent a positive.”
“And in the long-term, by periodically damaging the olfactory nerve it will lose its ability to regenerate and this helps governments prematurely kill countless people ages 57 to 85, the very age groups governments of the developed world want dead to ease the old-age burden and prevent economic collapse.” – PCR Tests and the Depopulation Program
The trigeminal nerve is a nerve responsible for sensation in the face and motor functions. If the test swab is inserted at the wrong angle and it touches this nerve it can affect the sense of taste and even sight.
“But even inserted at the correct angle, the mucosa of the nasopharyngeal cavity is damaged irrespective of the angle at which the swab is inserted at so long as it is inserted as deeply and rotated as vigorously as required by the PCR testing procedure, especially when the swabs are designed to do as much damage as possible by having serrated tips capable of scratching and damaging as much epithelium as possible” – PCR Tests and the Depopulation Program
After examining various PCR test swabs under a microscope, Professor Antonietta Gatti found that the fibres the swabs contain are as dangerous for human beings as inhaling asbestos.
Ethylene oxide, a well-known cancer-causing substance, is used to sterilize the PCR test swabs. “And since the swabs smear this mutagenic chemical on the mucosa of the nose, which is hypersensitive, it damages our health in unknown ways.” – PCR Tests and the Depopulation Program
Face Masks
“By mandating mask wearing indoors and outdoors, knowing that exhaled air contains numerous bacteria and viruses, the planners are subjecting billions of people to inhale pathogens that the body exhaled from the respiratory tract … Hundreds of studies show that the inside of surgical masks contain greatly increased loads of bacteria and fungi after prolonged wearing and are a source of contamination not only for those wearing them but also for those around them.” – PCR Tests and the Depopulation Program
The latest and most comprehensive study has found that mask wearing by the general population leads to: a drop in oxygen; fatigue; rise in carbon dioxide; respiratory impairment; headache; and, temperature rise and moisture under the mask.
How do the test swabs and masks work together towards the same aim?
Galalae surmises that the test swabs damage the immune defences of the brain leaving it exposed to pathogens. And then, the masks subject the brain to asphyxiation by depriving it of oxygen and bombarding it with carbon dioxide. The respiratory center of the brain – which controls minute-to-minute breathing – begins to malfunction and as a result, people have trouble breathing. “The breathlessness (dyspnoea) associated with Covid is therefore not due to lung lesions but to damage to neural processing, thus due to brain damage.” – PCR Tests and the Depopulation Program
Chemicals And Toxins
“The general population has been subjected to an onslaught of dangerous chemicals through hand sanitisers, whose use medical authorities have mandated for the most mundane activities ever since the plandemic has been started. Methanol is probably the most dangerous and most often found chemical in hand sanitisers … It is known to cause metabolic acidosis, visual disturbances and neurological deficit.” – PCR Tests and the Depopulation Program
Galalae then goes on to explain how the adult population is subjected to neurotoxins – most likely isodecanes and mycotoxins – hidden in body care products, food and drinks (especially beer).
Summary
Galalae ends with “this explains, among other things,” and he lists a number of points the below being a few of them, why:
- incidences of illness increase as PCR testing increases;
- the pathology attributed to Covid is so wide-ranging and so far removed from any other viral infection of the respiratory tract;
- the pandemic disappears and reappears;
- vaccine passports are only given to people who are either vaccinated or have had positive PCR tests, but never to those who show that they have naturally acquired antibodies; there is no pharmacological treatment for Covid; and,
- governments continue to insist on subjecting as many people as possible as often as possible to an intrusive medical test that can be easily done by analysing saliva.
Italian Senator suspended for not showing vaccine passport
By Didi Rankovic | Reclaim The Net | October 21, 2021
Protesters who have been gathering across Italy to support a campaign against introduction of vaccination certificates, known as “the green pass” in that country have some supporters in high places like senators and members of parliament (MPs).
One of them, Senator Laura Granato, has experienced first-hand what the new rules around Covid passes mean for gainfully employed persons who oppose them: she was suspended and left without her daily allowance for ten days for refusing to show the pass once inside the Senate building.
Granato first managed to get in, but was “reported” for deciding not to show the document. The senator was in this way prevented from taking part in a meeting that was discussing precisely the green passes, which became mandatory both for public and private sector workers on Friday.
These new, more restrictive measures have been described as “some of the toughest in the world,” while Granato echoed the sentiment of Italians opposed to them blasting the passes as “certificates of obedience.”
In Italy, the green pass is designed to show that a person has either been vaccinated, has tested negative (these tests are valid only for several days) or that they recently recovered from Covid. The government believes that mandating green passes for the workplace will boost the vaccine drive and avoid a repeat of lockdowns that have ravaged Italy’s economy over the past nearly two years of the pandemic.
But although many Italians are “obeying the certificates of obedience” – no doubt seeing no way out other than ultimately losing their livelihoods – many others remain defiant and indignant at the prospect, with thousands of dock workers in Trieste protesting over the weekend, along with others elsewhere in Italy.
And while over one million green passes were downloaded on the first working day that the new, tougher Covid restrictions came into force, they have so far failed to significantly increase the number of vaccinations.
Featured Video

Death Spikes & Rising Cancer In Our Youth Explained
or go to
Aletho News Archives – Video-Images
From the Archives
Politicians lie
By Mazin Qumsiyeh | Popular Resistance | August 18, 2013
There is no way to say this truth nicely: Politicians lie. That includes Japanese, American, Egyptian, Israeli, and Palestinian politicians! Is there something more common sense than that? Yet, so many citizens around the world believe their own politicians or wistfully acknowledge lies but think it is part of the job needed to run things. They believe even when politicians contradict themselves blatantly. This phenomenon is rather remarkable. It is a dissonance and disconnect from reality that many seem oblivious to. It is very dangerous because it can lead to accepting rationales for going to war. These can be deadly wars that lead to millions of lives lost as happened in what was called World War 1 and WW2. Even when incredible and declassified evidence abound, politicians continue to lie and old mythologies refuse to die. Here are just a few of the countless lies told to us over the past few decades… continue
Blog Roll
 Aletho News
- Burnham’s UN debut… A masterclass in British disinformation
- Iran flights continue despite US aviation sanctions
- Global Tipping Points Lead the World Into a State of Entropy
- The day-after at the White House: USA and Xi Jinping
- The Geopolitical Balance in the Red Sea: The UAE Being Displaced by New Players
- Iraqi resistance group vows to stage airport sit-ins over Iran aerial blockade
- Turkish parliament to review Saudi-Pakistan defense pact next month
- DEATH SPIKES & RISING CANCER IN OUR YOUTH EXPLAINED
- Iran offers Trump deal before US election
- Merz regime wants ‘secret police’ – opposition
- If Americans Knew
- Deconstructing Netanyahu’s pants-on-fire UN rant – Daily Update
- Trump betrayed voters with his campaign lies and prioritized a foreign country once he took office
- Netanyahu calls Israel’s war in Gaza ‘opposite of genocide’ in UN speech to near-empty hall
- Settler Kidnappings: Torture, Sexual Abuse and Terrorisation of Palestinian Abductees as Israel Deepens Annexation of West Bank
- Gaza winter nears as 162,000 tents become unusable, raising fears of humanitarian crisis
- Netanyahu says, “It’s the opposite of genocide”; UN says Gaza economy is world’s ‘most severe crisis on record’ – Daily Update
- Israel’s US-Backed Assault on Gaza Has Created the ‘World’s Most Severe Economic Crisis on Record’: UN
- ‘Protecting U.S. Citizens’… From Israel
- ‘This is where I live now, the back of a truck’: a day in the life of a grandmother in Gaza
- In UN Speech, Iran’s President Displays Pictures of Children Killed by US, Brings Attention to Israel’s Nuclear Arsenal
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

