Why all the fuss about Ivermectin?
By Brian C. Joondeph | American Thinker | September 3, 2021
First hydroxychloroquine, now ivermectin, is the hated deadly drug de jour, castigated by the medical establishment and regulatory authorities. Both drugs have been around for a long time as FDA-approved prescription medications. Yet now we are told they are as deadly as arsenic.
As a physician, I am certainly aware of ivermectin but don’t recall ever writing a prescription for it in my 30+ years’ medical career. Ivermectin is an anthelmintic, meaning it cures parasitic infections. In my world of ophthalmology, it is used on occasion for rare parasitic or worm infections in the eye.
Ivermectin was FDA approved in 1998 under the brand name Stromectol, produced by pharmaceutical giant Merck, approved for several parasitic infections. The product label described it as having a “unique mode of action,” which “leads to an increase in the permeability of the cell membrane to chloride ions.” This suggests that ivermectin acts as an ionophore, making cell membranes permeable to ions that enter the cell for therapeutic effect.
Ivermectin is one of several ionophores, others including hydroxychloroquine, quercetin, and resveratrol, the latter two available over the counter. These ionophores simply open a cellular door, allowing zinc to enter the cell, where it then interferes with viral replication, providing potential therapeutic benefit in viral and other infections.
This scientific paper reviews and references other studies demonstrating antibacterial, antiviral, and anticancer properties of ivermectin. This explains the interest in this drug as having potential use in treating COVID.
Does ivermectin work in COVID? I am not attempting to answer that question, instead looking at readily available information because this drug has been the focus of much recent media attention. For the benefit of any reader eager to report this article and author to the medical licensing boards for pushing misleading information, I am not offering medical advice or prescribing anything. Rather, I am only offering commentary on this newsworthy and controversial drug.
What’s newsworthy about ivermectin? A simple Google search of most medications describes uses and side effects. A similar search of ivermectin provides headlines of why it shouldn’t be taken and how dangerous it is.

YouTube screen grab
The Guardian describes ivermectin as horse medicine reminding readers considering taking the drug, “You are not a horse. You are not a cow”, saying it’s a medicine meant for farm animals. The FDA echoed that sentiment in a recent tweet, adding “Seriously, y’all. Stop it,” their word choice making it obvious who the tweet was directed to.
Perhaps the FDA didn’t realize that Barack and Michelle Obama often used the term “y’all” and that some might construe the FDA tweet as racist.
The FDA says ivermectin “can be dangerous and even lethal,” yet they approved it in 1998 and have not pulled it from the market despite it being “dangerous and lethal.” Any medication can be “dangerous and lethal” if misused. People have even overdosed on water.
It is true that ivermectin is also used in animals, as are many drugs approved for human use. This is a list of veterinary drugs with many familiar names of antibiotics, antihypertensives, and anesthetics commonly used by humans. Since these drugs are used in farm animals, should humans stop taking them? That seems a rather unscientific argument against ivermectin, especially coming from the FDA.
And healthcare professionals are not recommending or prescribing animal versions of ivermectin as there is an FDA-approved human formulation.
Does ivermectin work against COVID? That is the bigger question and worthy of investigation, rather than reminding people that they are not cows.
A study published several months ago in the American Journal of Therapeutics concluded,
Meta-analyses based on 18 randomized controlled treatment trials of ivermectin in COVID-19 have found large, statistically significant reductions in mortality, time to clinical recovery, and time to viral clearance. Furthermore, results from numerous controlled prophylaxis trials report significantly reduced risks of contracting COVID-19 with the regular use of ivermectin. Finally, the many examples of ivermectin distribution campaigns leading to rapid population-wide decreases in morbidity and mortality indicate that an oral agent effective in all phases of COVID-19 has been identified.
To my knowledge, these 18 studies have not been retracted, unlike previous studies critical of hydroxychloroquine which were ignominiously retracted by prestigious medical journals like The Lancet and the New England Journal of Medicine.
Yet the medical establishment refuses to even entertain the possibility of some benefit from ivermectin, castigating physicians who want to try it in their patients. 18 studies found benefit. Are they all wrong?
Podcaster Joe Rogan recently contracted COVID and recovered within days of taking a drug cocktail including ivermectin. Was it his drug cocktail, his fitness, or just good luck? Impossible to know but his experience will keep ivermectin in the news.
Highly unvaccinated India had a surge in COVID cases earlier this year which abruptly ended following the widespread use of ivermectin, over the objections and criticism of the WHO. In the one state, Tamil Nadu, that did not use ivermectin, cases tripled instead of dropping by 97 percent as in the rest of the country.
This is anecdotal and could have other explanations but the discovery of penicillin was also anecdotal and observational. Good science should investigate rather than ignore such observations.
The Japanese Medical Association recently endorsed ivermectin for COVID. The US CDC cautioned against it.
There is legal pushback as an Ohio judge ordered a hospital to treat a ventilated COVID patient with ivermectin. After a month on the ventilator, this patient is likely COVID free and ivermectin now will have no benefit, allowing the medical establishment to say “see I told you so” that it wouldn’t help.
By this point, active COVID infection is not the issue; instead, it is weaning off and recovery from long-term life support. The early hydroxychloroquine studies had the same flaw, treating patients too late in the disease course to provide or demonstrate benefit.
These drugs have been proposed for early outpatient treatment, not when patients are seriously ill and near death. Looking for treatment benefits in the wrong patient population will yield expected negative results.
Given how devastating COVID can be and how, despite high levels of vaccination in countries like the US, UK, and Israel, we are seeing surging cases and hospitalizations among the vaccinated, we should be pulling out all the stops in treating this virus.
Medical treatment involves balancing risks and benefits. When FDA-approved medications are used in appropriate doses for appropriate patients, prescribed by competent physicians, the risks tend to be low, and any benefit should be celebrated. Instead, the medical establishment, media, and regulatory authorities are taking the opposite approach. One has to wonder why.
The State That Doesn’t Care If You Live Or Die

By Tom Woods | Principia Scientific | September 3, 2021
Ask the average person in whatever country you choose what his chances of hospitalization with or death from COVID are and the answers will shock you. Nearly everyone you speak to is completely uninformed.
Naturally it is impossible to make rational decisions amidst this degree of ignorance.
Now is as good a time as any for some perspective.
The survival rate for people in the 0-19 age group is 99.997 percent. For 20-29 it’s 99.986 percent. You can find all the figures in the graphic below.
The data come from a recent paper by Stanford’s Cathrine Axfors and John Ioannidis, “Infection fatality rate of COVID-19 in community-dwelling populations with emphasis on the elderly: An overview.” Here’s how it breaks down:

A person under 50 is therefore at greater risk of death from drowning, choking on food, sunstroke, or from a sharp object.
This is not to say that we’re not dealing with a nasty virus for some people who contract it. But do you think the average person has any idea that the numbers for survival are this high?
In the UK, the Daily Mail just published an article called, “Is it time to stop obsessing over Covid figures? Statistics reveal virus is NOT the biggest killer — with heart disease, dementia and cancer each claiming four times as many lives in an average week last month.”
“Even before the rollout of the vaccine,” the article notes, “fewer than one per cent of people who caught Covid died. Now, scientists say that figure is ten times smaller.”
They included this graphic, for perspective:

Much as I welcome this, it’s pretty rich for the British press (or indeed any press) to publish an article and a chart like that, though, scratching their heads as to why people are obsessed about COVID, when they themselves are directly responsible for the misinformation that brought about that obsession.
Remember when the Washington Post called Iowa the “state that doesn’t care if you live or die” when that state removed its COVID restrictions? That was seven months ago.
Here’s the chart. Think we’re going to hear any apologies, or any “gee, I guess I don’t understand this virus as well as I thought,” or…?

That’s enough perspective for one day.
No Animal Studies for the Vaccines
By Martin Armstrong | ArmstrongEconomics | September 2, 2021
I find it extremely unbelievable that nobody will investigate this entire scam for what it is. The people behind the vaccines should be dragged in to testify what is going on. Moderna has admitted it took them only 2 days to create the vaccine. In Texas, they are trying to launch a criminal investigation. The FDA is no longer trustworthy, for the normal time to get anything approved is 12 years. What has been released in less than one year with no animal studies? There has been NO TESTING to determine side effects on pregnancy, fertility, or lactation.
It is just stunning that we have politicians REFUSING to look at anything, probably because they are too busy counting their bribes. The White House said under NO condition would they ever fire Fauci, meaning under NO condition will they investigate anyone.
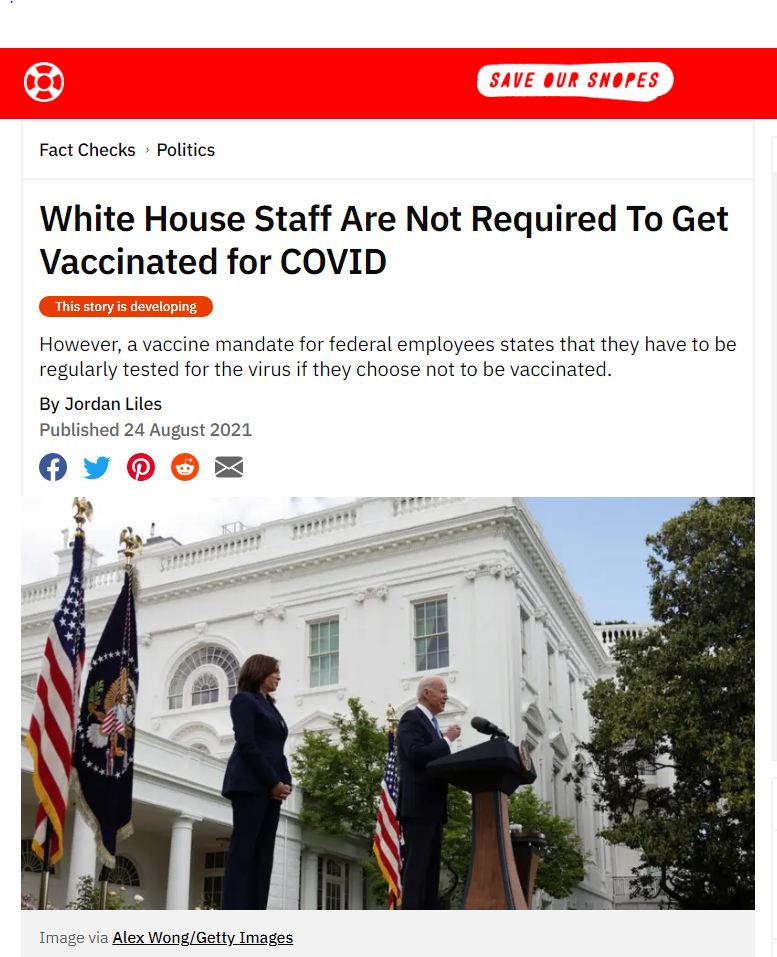
Meanwhile, even the notorious corrupt Snopes had to admit this is TRUE. Despite demanding everyone gets vaccinated, the White House said its own staff DOES NOT need to be vaccinated provided they are routinely checked. So why is the White House the entire exception? Even the military is demanding 100% compliance. Meanwhile, the White House has demanded everyone else receive vaccinations or lose their job.

The fact that they have skipped animal trials is very disturbing. When the government is part of the conspiracy against the public, we will NEVER know the truth about anything. Jack Dorsey has been especially protective of the narrative. Nobody is allowed to question the government no matter what.
Then there are studies revealing that natural immunity to COVID is 13 times better than the vaccines. They try to bury such studies, and they also try to ensure that they are not peer-reviewed in order to discredit them. The Science journalist Alex Berenson was permanently suspended from Twitter one day after his tweets that reported an Israeli study that making this finding that natural immunity from a prior Covid-19 infection is 13 times more effective than vaccines against the delta variant. Twitter is now acting against the very basis of free speech, which is threatening people’s lives. I would love to see Twitter taken down, for they are clearly now responsible for the deaths of many people from vaccine injuries.

To show that this is one giant cover-up, OSHA has instructed employers NOT TO REPORT vaccine injuries suffered by employees if they only “recommend” the shots. Many employers with more than 10 employees are required to keep a record of serious work-related injuries and illnesses. Nobody should volunteer to be vaccinated to satisfy an employer, for you will not be covered for any injury or loss of pay, and you could be fired for not showing up to work for a period of time. However, if employers mandate vaccines to work, then the vaccine injuries should become subject to reporting, lawsuits, and workman’s comp claims.
Why Testing Your Immunity to COVID-19 Is Important
By Dr. Joseph Mercola | September 4, 2021
Antibody testing is the gold standard for determining immunity, says immunologist and physician Dr. Hooman Noorchashm. Yet, the CDC and FDA are actively deterring people from testing their immunity. Why?
In May 2021 the FDA issued an advisory discouraging Americans from testing the status of their antibody immunity to COVID-19, Noorchashm wrote in an editorial on his blog. “Those who are adequately immune to COVID-19 are rarely, if ever, getting reinfected — regardless of whether this immunity comes from vaccination or from a natural infection,” Noorchashm said.
Meanwhile, “those who are NOT immune to SARS-CoV-2 are susceptible to being infected,” he said. He surmises that to end the pandemic upward of 90% of the population need to become immune.
As far as testing for immunity, according to Noorchashm, the FDA advisory prevents people from obtaining critical information necessary to protect themselves during the pandemic. “ … by not encouraging liberal COVID-19 antibody testing, especially in fully vaccinated Americans, the FDA and CDC are preventing vaccinated, but inadequately immune, persons from finding out that they remain susceptible to infection,” he wrote.
Citing his own experience as a physician, he said “patients who hesitate to undergo vaccination are far more likely to do so when they are confronted with a negative antibody test demonstrating they are susceptible.”
SOURCES:
Ivermectin Metaanalysis
By Meryl Nass, MD | September 3, 2021
Tess Lawrie’s group’s metaanalysis of ivermectin research papers, published in June, has received a great deal of positive attention. It was, as expected, carefully done. The authors graded the quality of the papers they reviewed.
The abstract noted:
“Therapeutic Advances: Meta-analysis of 15 trials found that ivermectin reduced risk of death compared with no ivermectin (average risk ratio 0.38, 95% confidence interval 0.19–0.73; n 5 2438; I2 5 49%; moderate-certainty evidence)…” This means that using only evidence of moderately good quality (high quality is often hard to come by, especially using observational data), if 100 people sick enough with Covid to die are given ivermectin, only 38 will die, and 62% will be saved.
“Low-certainty evidence found that ivermectin prophylaxis reduced COVID-19 infection by an average 86% (95% confidence interval 79%–91%).”
More doctors are using the drug. More patients are hearing about it. I have been getting more calls from patients who want to know about it. The NY Times said pharmacists are filling 88,000 scripts a week now.
Covid death rates, compared to the number of cases diagnosed, are way down compared to 2020 and last winter. While the NYT says there are 100,000 Covid patients in hospital now, only 1,500 are dying daily, or 1.5%, a much lower percentage than previous waves.
This is probably due to lower virulence of current variants, some benefit from vaccination, less use of ventilators and more use fo effective therapeutics.
And so now the CDC is coming down hard and many pharmacist have decided to stop filling the scripts in the past week. More on this in my next post.
Top Misinformation Article Attributed to Chicago Tribune
By Dr. Joseph Mercola | September 2, 2021
According to Facebook’s content transparency report for the first quarter of 2021, released in mid-August 2021, the most popular article shared on the platform between January 2021 and March 2021 was about a 56-year-old Miami, Florida, obstetrician who died two weeks after his first Pfizer injection.1
The story initially ran in the South Florida Sun Sentinel 2 April 8, 2021, and was republished by the Chicago Tribune that same day.3 The doctor, Dr. Gregory Michael, received his first dose December 18, 2020.
Three days later, he developed small spots on his hands and feet, which prompted him to go to the emergency room, where they found he had an abnormally low blood count. Platelets stop bleeding by clotting, and when platelets drop too low, internal bleeding can occur, resulting in what looks like blood blisters on the skin.
Michael remained in intensive care for two weeks, but no matter what they did, his platelet count refused to budge. During the night of January 3, 2021, he died of a massive stroke. According to the coroner, the COVID injection could not be ruled out as a contributing or causative factor.
In a Facebook post, Michael’s widow stated he’d been “very healthy” and that he’d been a COVID-19 vaccine advocate. His death caused her to question the safety of the shot, however.
“I believe that people should be aware that side effects can happen, that the vaccine is not good for everyone and in this case destroyed a beautiful life, a perfect family and has affected so many people in this community.” she wrote. “Please do not let his death be in vain please save more lives my making this information news.”4
Even Viral Content Has Minor Reach
According to The New York Times,5 Facebook held off on publishing the first-quarter report for fear the findings might “look bad for the company.” Executives decided they wanted to make some “key fixes to the system” before releasing it. That’s why it wasn’t published until August.
Interestingly, the report reveals that even when something goes viral, the total number of views is still a tiny fraction of the overall content. Even the biggest accounts make up but a small portion of overall content views. Combined, the top 20 accounts with the most views during the first quarter — which included UNICEF, The Dodo and LADbible — accounted for only 1.18% of all U.S. content views.
As noted in the report, this “shows that, even though it may seem like a page or post has extensive reach on the platform, that isn’t the case when measured against the total amount of content available on the platform.”
Facebook Calls Out CCDH for Manufacturing ‘Faulty Narrative’
As you may know, an obscure one-man organization funded by dark money called the Center for Countering Digital Hate (CCDH) has published several reports, including “The Anti-Vaxx Playbook,”6 “The Disinformation Dozen”7 and “Disinformation Dozen: The Sequel,”8 in which the founder, Imran Ahmed — an unregistered foreign agent — claims to have identified the top most influential “anti-vaxxers” in the U.S.
In a completely unexpected turn of events, Facebook is now calling out the CCDH for having manufactured a faulty narrative without evidence against the 12 individuals targeted in its reports (myself included).9
This is important, seeing how the CCDH reports have been the primary “reference” source of authority used by media and government officials to smear, threaten and infringe on American citizens’ right to free speech.
The U.S. Department of Homeland Security even lists promulgating “false narratives” around COVID-19 as a top national security threat, which basically puts a “domestic terrorist” target on the backs of those of us who have been identified by the CCDH as the most prolific “superspreaders” of COVID misinformation.
As reported by GreenMed Info :10
“Google now shows an astounding 84,700 search results for CCDH’s defamatory phrase ‘disinformation dozen. ’Amazingly, this includes 16,000 news stories within the international press, approximately 100% of which are word-for-word amplifications of CCDH’s claims/defamatory statements and reported uncritically as fact.
In addition, the Surgeon General Vivek Murthy, the White House Press Secretary Jen Psaki, and president Biden all used CCDH’s report as the sole source for their own defamatory accusations, reaching a dangerous rhetorical climax on July 20th when Biden stated that these 12 individuals are literally “killing people” [by spreading misinformation].”
No Evidence to Support ‘Misinfo Superspreader’ Claim
In an August 18, 2021, Facebook report, Monika Bickert, vice president of Facebook content policy, sets the record straight, and in the process, demolishes the CCDH’s claims:11
“In recent weeks, there has been a debate about whether the global problem of COVID-19 vaccine misinformation can be solved simply by removing 12 people from social media platforms. People who have advanced this narrative contend that these 12 people are responsible for 73% of online vaccine misinformation on Facebook. There isn’t any evidence to support this claim …
That said, any amount of COVID-19 vaccine misinformation that violates our policies is too much by our standards — and we have removed over three dozen Pages, groups and Facebook or Instagram accounts linked to these 12 people, including at least one linked to each of the 12 people, for violating our policies.
We have also imposed penalties on nearly two dozen additional Pages, groups or accounts linked to these 12 people, like moving their posts lower in News Feed so fewer people see them or not recommending them to others. We’ve applied penalties to some of their website domains as well so any posts including their website content are moved lower in News Feed.
The remaining accounts associated with these individuals are not posting content that breaks our rules, have only posted a small amount of violating content, which we’ve removed, or are simply inactive.
In fact, these 12 people are responsible for about just 0.05% of all views of vaccine-related content on Facebook. This includes all vaccine-related posts they’ve shared, whether true or false, as well as URLs associated with these people.”
It’s worth restating the key point in this quote: Combined, the top 12 individuals and organizations identified by the CCDH as being responsible for a whopping 73% of vaccine misinformation on Facebook, are in fact only responsible for 0.05% of vaccine-related content — 1,460 times lower than the CCDH’s outrageous claim. That’s no small discrepancy.
CCDH Claims Blasted as Unjustified and Biased
Bickert goes on to refer directly to the CCDH report “The Disinformation Dozen,”12 stating:
“The report13 upon which the faulty narrative is based analyzed only a narrow set of 483 pieces of content over six weeks from only 30 groups, some of which are as small as 2,500 users.
They are in no way representative of the hundreds of millions of posts that people have shared about COVID-19 vaccines in the past months on Facebook.
Further, there is no explanation for how the organization behind the report identified the content they describe as ‘anti-vax’ or how they chose the 30 groups they included in their analysis. There is no justification for their claim that their data constitute a ‘representative sample’ of the content shared across our apps.”
CCDH Meets Definition of ‘Hateful Extremists’
Ironically, while the CCDH claims to “counter hate” online, and Ahmed sits on the Steering Committee of the U.K. Commission on Countering Extremism, CCDH itself actually meets the Commission’s definition of hateful extremists.14 In the 2019 Commission document, “Challenging Hateful Extremism,” the term is defined as:15
“Behaviours that can incite and amplify hate, or engage in persistent hatred, or equivocate about and make the moral case for violence; And that draw on hateful, hostile or supremacist beliefs directed at an out-group who are perceived as a threat to the wellbeing, survival or success of an in-group; And that cause, or are likely to cause, harm to individuals, communities or wider society.”
In addition, in the forward of the report, lead commissioner Sara Khan notes that “Hateful extremists seek to restrict individual liberties and curtail the fundamental freedoms that define our country.”
All of these definitions and clarifications of what hateful extremism is fit the CCDH to a T. Ahmed manufactured data to create a false narrative that 12 individuals pose a threat to the well-being and survival of the whole world, and then used that narrative to incite hate against us and curtail our freedom of speech.
Who Fact Checks the Fact Checkers?
In related news, the self-appointed arbiter of factual truths, NewsGuard, has had to backpedal in recent months and issue dozens of corrections to “fact checks” in which they’ve labeled the Wuhan lab leak theory as a debunked conspiracy theory with no basis in fact.
Since the beginning of the COVID pandemic, NewsGuard has wrongly down-rated 225 websites for articles mentioning the lab leak theory.16 In reality, there’s far more evidence to support the lab leak theory than any other theory, but it took over a year before the weight of this evidence became too obvious for the media to ignore.
NewsGuard’s erroneous fact checks were recently highlighted in an August 11, 2021, report by the American Institute for Economic Research (AIER).17
AIER decided to take a closer look at NewsGuard after receiving a request for comments on a NewsGuard fact check article regarding AIER and the Great Barrington Declaration — a statement written by public health experts from Harvard, Stanford and Oxford that calls on government to implement focused protection rather than lockdowns and self-isolation. AIERS investigation found that:18
“… NewsGuard falls far short of the very same criteria for accuracy and transparency that it claims to apply to other websites. Most of the company’s fact checkers lack basic qualifications in the scientific and social-scientific fields that they purport to arbitrate.
NewsGuard’s own track record of commentary — particularly on the Covid-19 pandemic — reveals a pattern of unreliable and misleading claims that required subsequent corrections, and analysis that regularly conflates fact with opinion journalism in rendering a judgement on a website’s content.
Furthermore, the company’s own practices fall far short of the transparency and disclosure standards it regularly applies to other websites … NewsGuard’s staff primarily evaluates scientific claims by appealing to the authority of public figures who they designate as ‘experts’ on the subject in question.
Their approach generally avoids direct examination of the evidence surrounding contested claims, and instead cherry-picks a figure to treat as an authoritative final word … many of their preferred authorities are political officeholders rather than persons trained in scientific or social-scientific methods.
By selectively curating cherry-picked political authorities rather than evaluating evidence directly, NewsGuard’s approach to fact-checking effectively sidesteps the scientific method. This strategy is rendered even more problematic by the general lack of scientific expertise within NewsGuard’s team of writers.
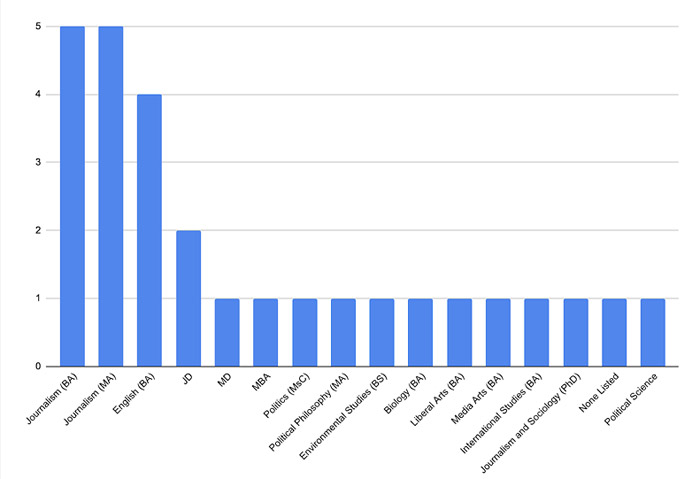
We examined the educational credentials, including the highest degree listed, for 28 publicly identified staff members on NewsGuard’s website. The company’s staff page reveals shockingly little expertise in either the hard sciences such as medicine or social sciences such as public policy, economics, and related fields …
Most NewsGuard articles on Covid-19 topics and policies are written by [NewsGuard Deputy Editor for Health, John] Gregory, whose only identified qualification is a bachelor’s degree in Media Arts … Gregory would not qualify as an expert in most of the fields he is responsible for fact-checking …
Of course, non-experts have every right to offer opinions on scientific and social-scientific matters. Whether or not they should be taken seriously as fact checkers or act as arbiters of scientific disputes is another question entirely.”
NewsGuard Staff by Field and Highest Degree Attained
NewsGuard Apologizes for Erroneous Fact Checks
After being confronted about its erroneous fact checks on the lab leak theory, NewsGuard offered the following apology in a statement sent to AIER:19
“NewsGuard either mischaracterized the sites’ claims about the lab leak theory, referred to the lab leak as a ‘conspiracy theory,’ or wrongly grouped together unproven claims about the lab leak with the separate, false claim that the COVID-19 virus was man-made without explaining that one claim was unsubstantiated, and the other was false.
NewsGuard apologizes for these errors. We have made the appropriate correction on each of the 21 labels.”
AIER commented on the apology:20
“Gregory and his colleagues appear to have simply decided that their own premature dismissal of the lab leak hypothesis equated to ‘fact’ and proceeded to penalize other sites not for factual errors, but rather for diverging from NewsGuard’s own editorial position on the same subject.
When this position turned out to be mistaken, NewsGuard pivoted to remove the errors — albeit in non-transparent ways that downplay the significance or pervasiveness of their mistake.”
NewsGuard Fails to Fulfill Its Own Credibility Criteria
In their report, AIER goes on to apply the criteria NewsGuard uses to evaluate a website’s credibility to NewsGuard itself. It’s ranking? A paltry 36.25 out of 100. According to AIER:21
“This website fails to adhere to several basic journalistic standards, and should be used with extreme caution as a source for verifying the reliability of the websites it purports to rate …
When we see fact checkers like NewsGuard, who not only fail to uphold their high-sounding principles but even publicly encourage working with the government to suppress speech, we should raise red flags.”
The NewsGuard ratings are meant to influence the reader, instructing them to disregard content with cautionary colors and cautions. That it would serve as the thought police of the technocratic establishment that seeks to silence dissent and bury information that doesn’t help move the Great Reset agenda forward is no surprise.
Especially considering its primary startup capital came from Publicis Groupe,22 a PR group that represents most of Big Pharma, including vaccine makers, and Big Tech. NewsGuard is also backed by Microsoft23 and Google.
The Publicis Groupe has been manipulating what people think about commercial products for nearly a century. Over that century, this advertising and communications firm bought or partnered with targeted advertising avenues, beginning with newspapers, followed by radio, TV, cinema and the internet.
With revenue avenues secured, Publicis’ clients and partners built a global presence that dominated the advertising world. Be it tobacco or sugar, Publicis Groupe found a way to promote and strengthen big industries. Publicis was recently sued24 for its deadly and illegal marketing of Purdue Pharma’s opioid products.
When you consider that Publicis describes its business model approach as putting clients and their needs and objectives at the center of all they do so their clients can “win and grow,” it’s easy to see what’s driving NewsGuard.
Overall, NewsGuard is just another big business aimed at keeping the chemical, drug and food industries, as well as mainstream media, intact by discrediting and eliminating unwanted competitors and analysts who empower you with information that runs counter to any given industry’s agenda.
If you’re as disturbed by censorship as I am, be sure to contact your local library today to find out if they’re one of the more than 700 libraries using NewsGuard. If they are, then ask them if they’re aware of NewsGuard’s censorship of truthful news that is now encroaching on scientific freedom and threatening the very roots of our democracy.
If your local library is using NewsGuard, it would be helpful to start a campaign to get it removed. Contact your neighbors and let them know what is happening so they can kick out this public health threat. Likewise, whenever you see someone referencing reports by the CCDH, call them out on it.
Sources and References
- 1 USA Today August 23, 2021
- 2 Sun Sentinel April 8, 2021
- 3 Facebook Heidi Neckelmann
- 4 Chicago Tribune April 8, 2021
- 5 New York Times August 20, 2021 (Archived)
- 6 The Anti-Vaxx Playbook (PDF)
- 7, 12, 13 CCDH, The Disinformation Dozen
- 8 Misinformation Dozen: The Sequel
- 9, 11 Facebook August 18, 2021
- 10 GreenMed Info August 19, 2021
- 14 Greenmed Info March 25, 2021
- 15 Challenging Hateful Extremism 2019
- 16, 17, 18, 19, 20, 21 AIER August 11, 2021
- 22 Washington Post March 3, 2018
- 23 axios.com August 23, 2018, NewsGuard Launches First Product With Help From Microsoft
- 24 Reuters May 6, 2021
UK Schoolchildren To Be Covid Vaxxed With Or Without Parental Consent
ALERT: ALL PARENTS IN U.K. WITH CHILDREN AGED 12 – 15 years
By Dr. Mike Yeadon | Health Impact News | August 26, 2021
I’ve just been informed via someone senior in the vaccination authorities that they will begin VACCINATING ALL SCHOOL CHILDREN AGED 12 – 15 years old STARTING SEPTEMBER 6th 2021.
WITH OR WITHOUT YOUR CONSENT.
Children are at no measurable risk from SARS-CoV-2 & no previously healthy child has died in U.K. after infection. Not one.
The vaccines are NOT SAFE. The USA reporting system VAERS is showing around 13,000 deaths in days to a few weeks after administration. A high % occur in the first 3 days. Around 70% of serious adverse events are thromboembolic in nature (blood clotting- or bleeding-related).
We know why this is: all of the gene-based vaccines cause our bodies to manufacture the virus spike protein & that spike protein triggers blood coagulation.
The next most common type of adverse events are neurological.
Death rates per million vaccinations are running everywhere at around 60X more than any previous vaccine.
Worse, thromboembolic events such as pulmonary embolisms, appear at over 400X the typical low rate after vaccination.
These events are serious, occur at a hideously elevated level & are at least as common in young people as in elderly people. The tendency is that younger people are having MORE SEVERE adverse events than older people.
There is literally no benefit whatsoever from this intervention. As stated, the children are unquestionably NOT AT RISK & vaccinating them WILL ONLY RESULT IN PAIN, SUFFERING, LASTING INJURIES AND DEATH.
Children rarely even become symptomatic & are very poor transmitters of the virus. This isn’t theory. It’s been studied & it pretty much doesn’t happen that children bring the virus into the home. In a large study, on not one occasion was a child the ‘index case’ – the first infected person in a household.
So if you’re told “it’s to protect vulnerable family members”, THAT IS A LIE.
The information emerging over time from U.K. & Israel is now showing clearly that the vaccines DO NOT EVEN WORK WELL. If there’s any benefit, it wanes.
Finally, the vaccines ARE NOT EVEN NECESSARY. There are good, safe & effective treatments.
IF YOU PERMIT THIS TO GO AHEAD I GUARANTEE THIS: THERE WILL BE AVOIDABLE DEATHS OF PERFECTLY HEALTHY CHILDREN, and severe illnesses in ten times as many.
And for no possible benefit.
KNOWING WHAT I KNOW FROM 40 years TRAINING & PRACTISE IN TOXICOLOGY, BIOCHEMISTRY & PHARMACOLOGY, to participate in this extraordinary abuse of innocent children in our care can be classified in no other way than MURDER.
It’s up to you. If I had a secondary school age child in U.K., I would not be returning them to school next month, no matter what.
The state is going to vaccinate everyone. The gloves are off. This has never been about a virus or public health. It’s wholly about control, totalitarian & irreversible control at that, and they’re nearly there.
PLEASE SHARE THIS INFORMATION WIDELY.
With somber best wishes,
Mike
ACIP vote yesterday, after deceitful CDC briefings, removes liability from Comirnaty and opens door to mandates
By Meryl Nass, MD | August 31, 2021
In a nutshell: Yesterday CDC asked its advisory committee to “recommend” the Comirnaty vaccine for 16 and 17 year olds. And it agreed, unanimously. Or pusillanimously.
The vote may seem silly or superfluous, because it had already been recommended for this age group as an EUA.
But this vote was anything but superfluous. This seemingly minor recommendation, which did not get headlines, moves the licensed Comirnaty vaccine from a place where the manufacturer is legally liable for injuries, to a berth within the Childhood Vaccine Injury Compensation Program, for which there is no manufacturer liability. Instead a $0.75 excise tax is charged per dose, which goes into a fund administered by DHHS to pay for injuries, if one is lucky enough to convince the special masters (judges) in the program that a vaccine caused your injury. Once a vaccine is recommended for children, its liability is waived no matter who receives it.
But the important part is that once this process is complete (which I expect to be only a very few weeks), Pfizer can roll out stocks of the licensed vaccine while still having its liability waived. That means that the loophole I told you about last week is being backfilled by the USG, with the help of the supine and spineless ACIP committee members, and will soon disappear.
I say spineless with true conviction, because the briefings they received yesterday were a load of fraud and hogwash. Yet no one challenged the data nor the conclusions. It is hard to believe that the lot of them are really that stupid that they believed what they heard. It is also hard to believe that none of them had a conflict of interest, which they all asserted along with their vote.
Furthermore, no one ever actually said why the vote was held: which was for liability purposes, nor that the vote would lead to mandates, which could not be implemented under the EUA.
So, it is disappointing.
Children’s Health Defense went to court today in Tennessee to challenge the FDA on issuing both a license and EUA for the same product. AFLDS also went to court today in Colorado challenging the mandate. More on these cases later.
Featured Video

Death Spikes & Rising Cancer In Our Youth Explained
or go to
Aletho News Archives – Video-Images
From the Archives
Politicians lie
By Mazin Qumsiyeh | Popular Resistance | August 18, 2013
There is no way to say this truth nicely: Politicians lie. That includes Japanese, American, Egyptian, Israeli, and Palestinian politicians! Is there something more common sense than that? Yet, so many citizens around the world believe their own politicians or wistfully acknowledge lies but think it is part of the job needed to run things. They believe even when politicians contradict themselves blatantly. This phenomenon is rather remarkable. It is a dissonance and disconnect from reality that many seem oblivious to. It is very dangerous because it can lead to accepting rationales for going to war. These can be deadly wars that lead to millions of lives lost as happened in what was called World War 1 and WW2. Even when incredible and declassified evidence abound, politicians continue to lie and old mythologies refuse to die. Here are just a few of the countless lies told to us over the past few decades… continue
Blog Roll
 Aletho News
- RSF military group defects, joins Sudanese army: State media
- Ireland goalkeeper refuses to play ‘Israel’ as squad weighs boycott
- China pushes back against US on Cuba, Iran
- Ukrainian Soldiers, Potential Mercenaries: Have Gun, Will Travel!
- Burnham’s UN debut… A masterclass in British disinformation
- Iran flights continue despite US aviation sanctions
- Global Tipping Points Lead the World Into a State of Entropy
- The day-after at the White House: USA and Xi Jinping
- The Geopolitical Balance in the Red Sea: The UAE Being Displaced by New Players
- Iraqi resistance group vows to stage airport sit-ins over Iran aerial blockade
- If Americans Knew
- Deconstructing Netanyahu’s pants-on-fire UN rant – Daily Update
- Trump betrayed voters with his campaign lies and prioritized a foreign country once he took office
- Netanyahu calls Israel’s war in Gaza ‘opposite of genocide’ in UN speech to near-empty hall
- Settler Kidnappings: Torture, Sexual Abuse and Terrorisation of Palestinian Abductees as Israel Deepens Annexation of West Bank
- Gaza winter nears as 162,000 tents become unusable, raising fears of humanitarian crisis
- Netanyahu says, “It’s the opposite of genocide”; UN says Gaza economy is world’s ‘most severe crisis on record’ – Daily Update
- Israel’s US-Backed Assault on Gaza Has Created the ‘World’s Most Severe Economic Crisis on Record’: UN
- ‘Protecting U.S. Citizens’… From Israel
- ‘This is where I live now, the back of a truck’: a day in the life of a grandmother in Gaza
- In UN Speech, Iran’s President Displays Pictures of Children Killed by US, Brings Attention to Israel’s Nuclear Arsenal
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

