Should people who have recovered from COVID take a vaccine?
By Marc Girardot | Trial Site News | July 6, 2021
Epidemiology1 , immunology2 and the clinical data3 all say a clear “No!”.
There is no good reason to vaccinate the recovered.
________________________________________________________________________
A British friend, recovered from COVID, decided to get vaccinated despite being naturally immune. This is the email he recently sent me:
“Marc I suffered a mild stroke on Wednesday 8 days after taking the Astrazeneca 2nd dose. Since I am a marathon runner I am a very ‘rare case’. I don’t smoke, have high blood pressure, high cholesterol, family history or come into any of the risk categories for blood clots…
You did warn me against taking the second dose and I wished I’d heeded your advice. I’ve taken a totally unnecessary risk with my life and I bitterly regret doing it.”
Contrary to most, Tony was informed; he had been told about the power of natural immunity, about the long—if not lifelong—duration of immunity, of the risk inherent to any medical procedure (Yes, vaccination is a medical procedure!), as well as of the rising levels of adverse events. He admitted he hadn’t imagined it could happen to him…
Though it is hard to assess precisely the actual severity and breadth of vaccine-related adverse events, it is very clear that vaccination against COVID-19 isn’t as harmless4 as pharmaceutical companies, mainstream media, academia, health authorities and the medical community have been saying. And, in contrast to high risk individuals who are still susceptible, recovered people have no real benefit to balance the additional risks of vaccination.
2021 Adverse Events Reporting
| VAERS US | EUROVIGILANCE EUROPE | YELLOW CARDS UK | |
| Date | 18/06/2021 | 04/06/2021 | 16/06/2021 |
| Fully Vaccinated (Mn) | 148.46 | 137.44 | 30.68 |
| Deaths | 6,136 | 4,572 | 1,356 |
| Incidents | 387,288 | 316,925 | 73,944 |
| Death per 100,000 | 4.1 | 3.3 | 4.4 |
For over a year, mainstream media, health authorities as well as many “experts” have been downplaying the power of the immune system, dismissing natural immunity5 and proclaiming that immunity to COVID-19 was short-lived6. Simultaneously, vaccines have been portrayed as the silver bullet to this crisis, an incidental procedure with no risk whatsoever. The data shows a different picture and many are coming forward7 8, to challenge the official narrative. We will demonstrate that the official narrative is a dangerous fallacy.
The human immune system is one of the most sophisticated achievements of evolution. The survival of our species has depended on it for millenia. Today, we still very much rely on it. For the record, 99% of people infected with SARS-CoV-2 recover without treatment. Only 1% of SARS-CoV-2 patients, who did not receive early home-based treatment, end up hospitalized9. In other words, the immune system overwhelmingly protects. Even vaccines are entirely dependent on the immune system: vaccines essentially teach our immune systems what viral markers to be prepared for, they are not cures per se. Without a functional immune system, there can be no effective vaccine10.
On the waning immunity fallacy
Once recovered, the immune response recedes, notably via a decrease in antibodies. It is not only natural; it is indispensable to restore the body to a normal, balanced state. Just as a permanent state of fever is harmful, a high number of targetless antibodies or T-cells constantly circulating throughout the body could create serious complications, such as autoimmune diseases11. Taking an evolutionary perspective, only those whose antibody and T-cell count waned post-infection survived. So, a decreasing number of antibodies and T-cells is reassuring, even healthy.
Antibody Levels during infection and post infection

Redline= antibodies – Blue-line= Memory B cells | Credit: Nature
But this decrease in T-cells and antibodies doesn’t mean that immunity is lost . It means the immune system has adapted to the new situation, and is now just on sentinel mode: Memory B- and T-cells, circulating in the blood and resident12 in tissues, act as vigilant13 and effective sentinels for decades:
- survivors of the Spanish Flu epidemic were tested for their immunity to the 1918 influenza virus 90 years later –14,15 and still demonstrated immunity;
- people who had recovered from the 2003 SARS infection demonstrated robust T-Cell responses seventeen years later16.
- the wide-spread prevalence of high cross-immunity17,18,19— gained from past common cold infections—further demonstrates the resilience of natural immunity for coronaviruses.
Indeed, all recent studies show that specific anti-SARS-CoV-2 immunity remains effective20,21,22,23, possibly for a lifetime24. Our immune system is a modular platform, it can combine in an infinite number of ways to address a multitude of threats in a variety of contexts. As such it is neutral to the viral threats it faces. In other words, there is absolutely no reason to believe that those recovered from Covid-19 would lose their immunity over the years, or even the decades25 to come.
On the reinfection fallacy
You might have also heard of people becoming reinfected by SARS-CoV-2. Indeed, immunity, natural or vaccine-induced, isn’t the impenetrable shield described by many. Essentially harmless and asymptomatic reinfections do take place. That is, in fact, the very mechanism by which adaptive immunity is triggered.
However, symptomatic reinfections are very rare26,27. Like an army that adapts its response to the size and the progression of its enemy forces, adaptive immunity provides a specific, rapid and resource-optimized response. As such reinfections are mostly asymptomatic28 and recovered patients are protected from severe disease.
In fact, innocuous reinfections can play a positive public health role by acting as continuous immune updates29 for the population. They can help form a seamless and progressive adaptation to emerging variants and strains. And indeed a recent study showed that couples with children were more frequently asymptomatic than couples without, most likely because children act as natural and harmless immunisation vehicles. The most likely reason why high density countries mostly have very low death tolls is that they have asymptomatic reinfections that regularly and widely update the population’s immunity.
On the variant fallacy
As demonstrated by the low numbers of symptomatic reinfections mentioned above, and also by multiple studies31,32, variants have thus far not escaped acquired immunity. Just as Americans can speak and interact seamlessly in England, unhindered by a few word variants33, natural immunity is unhindered by variants, possibly more so than vaccine-induced immunity. There is ample evidence of the sophistication and breadth of the human immune system, and it is clear that a few minor gene changes in the virus cannot evade its arsenal .
Across the world34, multiple studies demonstrate high levels of pre-existing cross-reactive T-cells35 and antibodies to SARS-CoV-2. In other words, many were already largely immune via other coronaviruses. This is the most likely explanation for the unexpectedly high level of asymptomatic infections during the pandemic. More importantly, this demonstrates that even with large genetic differences, prior immunity to related coronaviruses is sufficient to avoid severe COVID-19. Therefore, it is quite evident that variants are of no concern to the recovered population.
On the vaccine better-than-natural-immunity fallacy
You might have heard people stating that vaccines provide better protection than natural immunity. That is an interesting way of bending reality. How can a vaccine be more effective at immunisation than the disease it is trying to mimic?
Theoretically, there are several reasons explaining why natural immunity is better than vaccine-induced immunity:
- Fewer immune targets: mRNA/DNA vaccines present only a fraction of the virus genetic code (5-10%). For example, they don’t utilize the ORF1 highly immunogenic epitopes36. Therefore, the immune system recruits a smaller number of T-cells by tapping into a narrower repertoire and consequently mounts a less effective response37. The logic: Imagine you lose a number of key players for a football tournament, you might still win, but it will be harder.
- Longer immune trigger time: The smaller number of epitope targets also means that the alarm to the immune system will be delayed. This is a key driver of success in the COVID-19 battle. The wider the target repertoire, the faster the encounter between dendritic cells and identifiable antigens.
The logic: Like a party you go to, you can start partying much faster when you have ten friends there than when you have only one. They are just easier to find. - Inappropriate delivery location: The intramuscular delivery of current vaccines unfortunately doesn’t mimic viral penetration and propagation at all. Coronaviruses don’t enter the body via muscles. They do so via the respiratory tract, often infecting cell-to-cell. Contrary to muscle-delivered vaccines, natural immunity places a strong sentinel force of memory resident cells at the portals of entry38 and shuts the body entrance to the virus preemptively. From an evolutionary standpoint, this makes perfect sense.
The logic: it’s much easier to stop an army coming through a narrow gorge than on the beaches of Normandy.
Recent research confirms this logic. One comparative study39 in Israel found the protection from severe disease to be 96·4% for Covid-19 recovered individuals but 94.4% for vaccinated ones, and concluded “Our results question the need to vaccinate previously-infected individuals.” Another reference comparative study40 by a team at New York University highlighted a faster, wider and more impactful humoral and cytotoxic reaction in recovered immunity versus vaccine-induced.
There is ample evidence that vaccinating people recovered from COVID-19 doesn’t bring any benefit. It quite possibly does the opposite, because of the risk of building tolerance to elements of the virus43 translating into reduced immune potency.
On the vaccine innocuity fallacy
Without denigrating the incredible contribution of vaccines to modern medicine and public health, one needs to acknowledge that vaccines are a medical procedure. As such, vaccines should never be considered lightly. They are neither neutral, nor trivial, all the more so when they are injected into billions of people.
By their very nature, vaccines tinker with the sophisticated balance of one’s immune system. That in itself demands respecting rigid safety protocols. Though we have made considerable progress in our understanding of immunology, we are still very far from understanding its intricacies and subtleties, especially when it comes to novel mRNA and DNA technologies. Because of the risk of anaphylactic44 shock, auto-immune diseases, unforeseen interactions, design flaws, deficient quality protocols, over-dosage, and so on, vaccines have traditionally been strictly regulated.
History teaches us to be watchful45 with vaccines, from the botched inactivation of polio vaccines that ended infecting 40,000 kids46 with polio in 1955, to the 1976 swine flu vaccine47 which caused 450 to develop Guillain-Barré syndrome, to the more recent vaccine-induced outbreak of polio in Sudan48. The recent rejection49 by Brazilian health authorities of the Bharat’s Covaxin is a clear reminder of how rigorous and independent our health authorities need to be if vaccines are to promote, not hinder, public health.
Map of Vaccine Symptoms
316,925 reports (date: 06/20/21)
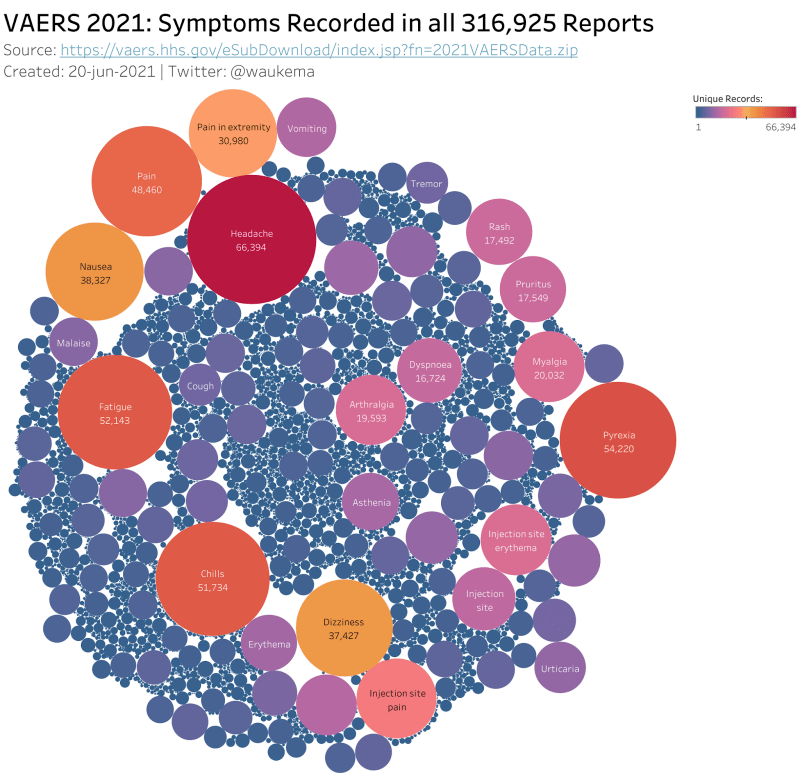
credit: Wouter Aukema – source: CDC
After 6 months of vaccination and a year of research, a number of red flags should be alerting the would-be vaccinated and health authorities:
- Wandering nanoparticles: The lipid nanoparticles, the carriers of the mRNA, were supposed to remain in the muscle, but ended up broadly distributed throughout the body50, notably in the ovaries51, the liver52 and possibly the bone marrow.
- Anaphylactic PEG: A number of concerns had been raised regarding the novel use of PEG adjuvant53. Notably, prior research had raised the risk of cardiac anaphylaxis at second injection54.
- Sensitive locations: ACE-2 receptors susceptible to binding to the spike protein are highly expressed in blood vessel lining cells of highly sensitive areas, such as the brain, the heart, the lungs, the liver and both male and female reproductive systems.
- Toxic circulating spikes: The spike proteins induced by mRNA/DNA vaccines have been shown to be pathogenic55,56,57,58 and highly inflammatory59, notably because of the similarity of a spike sequence to that of Staphylococcal Enterotoxin B60. It has also been found to be directly causing blood clots through platelet activation61,62. One researcher said, “Our findings show that the SARS-CoV-2 spike protein causes lung injury even without the presence of an intact virus”.
- BBB disruption – A recent study highlights the risk of disruption of the blood-brain barrier63, a fundamental filter mechanism to protect the brain64,65. The spike protein has also been found to cross the BBB and create inflammation in the brain,.
- High adverse events: Even though most likely under-reported66, the overall number of serious adverse events versus other traditional vaccines remains very high. The 6,000+ deaths67 seen [in the US] in six months exceed all the vaccine-related deaths in 30 years. This is quite disquieting, and tends to confirm the aforementioned red flags..
- Children more at risk: The Covid-19 vaccines seem to be more harmful to children and teens, notably with a growing number of myocarditis68,69 events. The fact that vaccine doses are not adjusted for body weight is notably a cause for concern given the discovery of circulating nanoparticles and spike toxicity.
These are essentially just the short-term effects of these novel vaccines. There is no long-term clinical data regarding the implications of these vaccines, notably regarding autoreactive antibodies (antibodies that target one’s own body creating autoimmune diseases).
To conclude, we question why anyone healthy and recovered from COVID-19 would want or be advised to take any risk—even the most remote—in getting vaccinated given that:
- those who have recovered from COVID-19 enjoy robust immunity,
- natural immunity duration is decades-long, probably lifelong,
- natural immunity effectiveness is better than vaccine-induced,
- variants are not an immunological concern, presenting no risk of immune escape,
- vaccines are medical interventions which should never be taken lightly, especially when still experimental,
- there is no benefit for COVID-19 recovered and
- COVID-19 vaccines are obviously not as safe as stated initially by the manufacturers.
- The 2021 seasonal peak in Europe started down on January 22 when only 0.13% of the population was fully vaccinated.
- “Comprehensive analysis of T cell immunodominance and immunoprevalence of SARS-CoV-2 epitopes in COVID-19 cases” by Alessandro Sette et al, Cell, February 2021
- “No point vaccinating those who’ve had COVID-19: Findings of Cleveland Clinic study” by Dr. Sanchari Sinha Dutta, June 2021
- “Pfizer-BioNTech vaccine is “likely” responsible for deaths of some elderly patients, Norwegian review finds” by Ingrid Torjesen, British Medical Journal, May 2021
- “Why COVID-19 Vaccines Offer Better Protection Than Infection” by Brian W. Simpson, John Hopkins School Of Public Health Expert Insights, May 2021
- “Study Finds People Have Short-Lived Immunity to Seasonal Coronaviruses” by Dr. Francis Collins, CDC’s Director Blog, September 2020
- “Are Covid Vaccines Riskier Than Advertised? There are concerning trends on blood clots and low platelets, not that the authorities will tell you” by Joseph A. Ladapo and Harvey A. Risch, The Wall Street Journal, June 2021
- “Why we petitioned the FDA to refrain from fully approving any covid-19 vaccine this year” by Peter Doshi et al, The British Medical Journal Opinion, June 2021
- “Phase 3 trial shows REGEN-COV™ (casirivimab with imdevimab) …” show 4.1% of at risk Placebo (non treated) patients are hospitalized, or 1% of the general population
- “Coronavirus vaccines may not work in some people. It’s because of their underlying conditions.” by Ariana E. Cha, The Washington Post, May 2021
- “Determinants and outcomes of accelerated arteriosclerosis: Major impact of circulating antibodies” by Alexandre Loupy, Circulation Research, June 2015
- “Peripheral and lung resident memory T cell responses against SARS-CoV-2” by Meritxell Genescà et al, Nature, May 2021
- “Tissue-Resident Memory T Cells and Fixed Immune Surveillance in Nonlymphoid Organs” by Francis R. Carbone, Journal of Immunology, July 2015
- “Flu survivors still immune after 90 years” by Ed Yong, National Geographic
- “Neutralizing antibodies derived from the B cells of 1918 influenza pandemic survivors” by James E. Crowe Jr., Nature
- “SARS-CoV-2-specific T cell immunity in cases of COVID-19 and SARS, and uninfected controls” by Le Bert et al, Nature, July 2020
- “Targets of T Cell Responses to SARS-CoV-2 Coronavirus in Humans with COVID-19 Disease and Unexposed Individuals” by A.Sette et al, Cell, June 2020
- “A majority of uninfected adults show pre-existing antibody reactivity against SARS-CoV-2” by Pascal M. Lavoie et al, JCI Insight, March 2021
- “Cross-reactive antibody immunity against SARS-CoV-2 in children and adults” by Todd Bradley et al, Nature, May 2021
- “Robust SARS-CoV-2-specific T cell immunity is maintained at 6 months following primary infection” by Paul Moss, Nature Immunology, May 2021
- “Naturally enhanced neutralizing breadth against SARS-CoV-2 one year after infection” by Michel C. Nussenzweig, Nature, June 2021
- “A long-term perspective on immunity to COVID” by ” by A.Radbruch & H-D.Chang
- “SARS-CoV-2 natural antibody response persists up to 12 months in a nationwide study from the Faroe Islands” by Peter Garred et al, 2021
- “SARS-CoV-2 infection induces long-lived bone marrow plasma cells in humans” by Ali H. Ellebedy et al, Nature, May 2021
- “Immunity to the Coronavirus May Last Years, New Data Hint” by Apoorva Mandavilli, New York Times, November 2020
- “Prior SARS-CoV-2 infection is associated with protection against symptomatic reinfection” by Christopher J.A. Duncan, Journal of Infection, December 2020
- “What we know about covid-19 reinfection so far” by Chris Stokel-Walker, British Medical Journal, January 2021
- “Antibody Status and Incidence of SARS-CoV-2 Infection in Health Care Workers” by Thomas G. Ritter, et al, New England Journal of Medicine, December 2020
- “Development of potency, breadth and resilience to viral escape mutations in SARS-CoV-2 neutralizing antibodies” by Paul D. Bieniasz et al, March 2021
- Get article on
- “Comprehensive analysis of T cell immunodominance and immunoprevalence of SARS-CoV-2 epitopes in COVID-19 cases” by A.Tarke et al… – Cell – 16-02-2021
- “Landscape of epitopes targeted by T cells in 852 individuals recovered from COVID-19: Meta-analysis, immunoprevalence, and web platform” by Matthew R. McKay et al, Cell, May 2021
- “How Broad is Covid Immunity?” by M.Yeadon/M.Girardot, Panda, March 2021
- Countries: Canada, Ecuador, Gabon, Germany, India, Singapore, Sweden, UK, USA, Tanzania, Zambia
- “Cross-reactive CD4+ T cells enhance SARS-CoV-2 immune responses upon infection and vaccination” by Claudia Giesecke-Thiel, April 2021
- “Profiling SARS-CoV-2 HLA-I peptidome reveals T cell epitopes from out-of-frame ORFs” by Pardis C. Sabeti, Cell, June 2021
- “The landscape of antibody binding in SARS-CoV-2 infection” by Irene M. Ong et al, PLOS biology, June 2021
- “Adaptive immunity to SARS-CoV-2 and COVID-19” by Alessandro Sette & Shane Crotty, Cell, January 2021 – page 866
- “Protection of previous SARS-CoV-2 infection is similar to that of BNT162b2 vaccine protection: A three-month nationwide experience from Israel” by Amit Hupper et al, April 2021
- “Discrete Immune Response Signature to SARS-CoV-2 mRNA Vaccination Versus Infection” by Sergei Koralov, Cell, May 2021
- “We observe striking expansion of circulating plasmablasts in COVID-19 patients relative to healthy volunteers”
- “In COVID-19 (recovered) patients, we observed an expansion of cytotoxic populations and a dramatically elevated cytotoxic signature in NK cells, CD4 and CD8 T cells, and γδ T cells.”
- “Differential Effects of the Second SARS-CoV-2 mRNA Vaccine Dose on T Cell Immunity in Naïve and COVID-19 Recovered Individuals” by Jordi Ochando et al, Cell, March 2021
- “Suspicions grow that nanoparticles in Pfizer’s COVID-19 vaccine trigger rare allergic reactions” by Jop de Vrieze, Science, December 2020
- “Historical Vaccine Safety Concerns”, CDC
- “The Cutter Incident: How America’s First Polio Vaccine Led to a Growing Vaccine Crisis” by Michael Fitzpatrick, Journal of the Royal Society of Medicine, 2006
- “The Public Health Legacy of the 1976 Swine Flu Outbreak” by Rebecca Kreston, 2013
- “UN says new polio outbreak in Sudan caused by oral vaccine” by Maria Cheng, Associated Press, September 2020
- “Anvisa denies certificate of good practice to Bharat Biotech, which produces Covaxin” by Enzô Machida and Murillo Ferrari, CNN, March 2021
- “Organ bio distribution study undertaken by the Japanese regulator”
- “Potential adverse effects of nanoparticles on the reproductive system”by Shao LQ, DovePress, September 2018
- “Synthetic Lipid Nanoparticles Targeting Steroid Organs” by Bertrand Tavitian, The Journal of Nuclear Medicine, 2013
- “PEGylated liposomes: immunological responses” by Tatsuhiro Ishida et al, Science and Technology of Advanced Materials Vol 20, 20219
- “Pseudo-anaphylaxis to Polyethylene Glycol (PEG)-Coated Liposomes: Roles of Anti-PEG IgM and Complement Activation in a Porcine Model of Human Infusion Reactions” by János Szebeni et al, ACS Nano, 2019
- “Superantigenic character of an insert unique to SARS-CoV-2 spike supported by skewed TCR repertoire in patients with hyperinflammation” by Ivet Bahar et al, PNAS, October 2020
- “SARS-CoV-2 spike protein induces inflammation via TLR2-dependent activation of the NF-κB pathway” by Hasan Zaki et al, March 2021
- “SARS-CoV-2 Spike Protein Impairs Endothelial Function via Downregulation of ACE 2” by John Y-J. Shyy, Circulation Reseacrh, MArch 2021
- “Single intratracheal exposure to SARS-CoV-2 S1 spike protein induces acute lung injury in K18-hACE2 transgenic mice” by Pavel Solopov et al, The FASEB Journal, May 2021
- “SARS-CoV-2 spike protein interacts with and activates TLR4” by Fuping You et al, December 2020
- “Bacterial Toxins—Staphylococcal Enterotoxin” by Bettina C. Fries & Avanish K. Varshney
- “A prothrombotic thrombocytopenic disorder resembling heparin-induced thrombocytopenia following coronavirus-19 vaccination” by Sabine Eichinger et al, The New England Journal of Medicine, April 2020
- “Acquired Thrombotic Thrombocytopenic Purpura: a rare disease associated Acquired with BNT162b2 vaccine” by Dorit Blickstein et al, Journal of Thrombosis and Haemostatis, June 2021
- “The SARS-CoV-2 spike protein alters barrier function in 2D static and 3D microfluidic in-vitro models of the human blood–brain barrier” by Sergio H. Ramirez, Neurobiology of Disease, December 2020
- “The S1 protein of SARS-CoV-2 crosses the blood–brain barrier in mice” by William A. Banks et al, NAture Neuroscience, December 2020
- “Guillain-Barré syndrome following ChAdOx1-S/nCoV-19 vaccine” by Boby Varkey Maramattom et al, June 2021
- “Underreporting of Side Effects to VAERS” by Vincent Iannelli, Vaxopedia, September 2017
- Open VAERS data
- “The C.D.C. is investigating nearly 800 cases of rare heart problems following immunization.” by Apoorva Mandavilli, New York Times, June 11, 2021
- “Israel reports link between rare cases of heart inflammation and COVID-19 vaccination in young men” by Gretchen Vogel & Jennifer Couzin-Frankel, Science, June 2021
Stringency Index Is Not Associated With COVID-19 Death Rate Across US States, but IS Associated With Higher Unemployment
By Noah Carl • Lockdown Sceptics • July 5, 2021
Some people oppose lockdown on principle, arguing that the government should never infringe on fundamental liberties like the freedom to leave our home or open our business, regardless of the impact this may have on disease transmission.
It’s a reasonable position, but I’m more drawn to the consequentialist case against lockdowns. This can be summed up as “benefits small, costs large”. In other words, even if lockdowns do reduce mortality from COVID-19 (under some circumstances), they don’t do so by anywhere near enough to justify their costs.
As I noted recently, several cost-benefit analyses of the UK’s lockdowns have been published, and each one concluded that the costs almost certainly outweighed the benefits. (Which may explain why the Government has thus far refrained from publishing any estimates itself.)
A rather elegant demonstration of the consequentialist case against lockdown was provided back in May, in the form of a Twitter thread by the data scientist Youyang Gu.
Comparing the 50 US states, Gu obtained data on the COVID-19 death rate, the change in unemployment rate, and the average Government Stringency Index. The latter is a measure of the number and severity of restrictions imposed during the course of the pandemic (school closures, stay-at-home orders, etc.). Gu’s two main charts are shown below:

He found that the Stringency Index was not associated with the COVID-19 death rate (left-hand chart), but was strongly associated with an increase in unemployment (right-hand chart). In other words, US states with longer and more stringent lockdowns haven’t had fewer COVID-19 deaths, but they have seen higher unemployment.
In the replies to Gu’s thread, some critics argued that restrictions were often imposed in response to large outbreaks, so you can’t assume that causation only goes from restrictions to deaths and unemployment. However, Gu points out that the relative ordering of restriction levels is fairly constant over time, so this is unlikely to be a major issue.
His analysis adds to a large body of evidence indicating that – for the vast majority of Western states – the benefits of lockdown were small, but the costs were very large. Gu’s thread is worth reading in full.
Vaccine Billionaires and Human Guinea Pigs
By Colin Todhunter | OffGuardian | July 3, 2021
How do you make a potentially dangerous and ineffective drug appear like a miracle of modern science? You could, for instance, enrol only certain people in clinical trials and exclude others or bring the study to a close as soon as you see a spike in the data that implies evidence of effectiveness.
There are many ways to do it.
According to health practitioner and writer Craig Stellpflug in his article ‘Big Pharma: Getting away with murder’(2012), the strategy is to get in quick, design the study to get the result you want, get out fast and make lots of money.
Stellpflug says:
If a study comes up negative for your favorite drug, just don’t publish it! 68 per cent of all drug studies are swept under the carpet to keep those pesky side effects from being reported. Only 32 per cent of studies come up positive and a lot of those studies are ‘shortened’ to limit the long-term findings. Studies cut short were found to overestimate the study drug’s effectiveness and miss dangerous side effects and complications by an average of 30 per cent. This would explain the amazing 85 per cent drug study success rate in the hands of Big Pharma according to the Annals of Internal Medicine.”
Of course, it helps to get the regulatory agencies on board and to convince the media and health officials of the need for your wonder product and its efficacy and safety. In the process, well-paid career scientists and ‘science’ effectively become shaped and led by corporate profit margins and political processes.
And what better way to make a financial killing than by making a mountain out of a molehill and calling it a ‘pandemic’?
COVID-19 VACCINE CONCERNS
The Wall Street Journal recently published an article by two health professors who said politics — not science — is behind the failure of health officials and the media to fully inform the public about the potential risks associated with COVID vaccines.
Although the article is available in full to subscribers only, the Children’s Health Defense (CHD) website provides an informative summary.
The CHD notes that Dr Joseph A Ladapo, associate professor of medicine at the David Geffen School of Medicine, and Dr Harvey A Risch, professor of epidemiology at Yale School of Public Health, wrote that while prominent scientists have raised concerns that the safety risks of Covid-19 vaccines have been underestimated, the politics of vaccination has relegated their concerns to the outskirts of scientific thinking.
The two professors noted that clinical studies do not always tell the full story about the safety of medications and that the health effects often remain unknown until the medicine is rolled out to the general public. Examples include Vioxx, a pain reliever that increased the risk of heart attack and stroke; antidepressants that appeared to increase suicide attempts among young adults; and an influenza vaccine used in the 2009-10 swine flu epidemic that was suspected of causing febrile convulsions and narcolepsy in children.
The authors added that clinical trials often enrol patients who are not representative of the general population and more is learnt about drug safety from real-world evidence. With this in mind, they said the large clustering of side effects following COVID vaccines is concerning as is the silence around these potential signals of harm.
Serious adverse events reported by the Vaccine Adverse Event Reporting System include low platelets, heart inflammation, deep-vein thrombosis and death. However, the two scientists argue this is likely to be a fraction of the total number of adverse events.
They criticise the Centers for Disease Control and Prevention (CDC) and the US Food and Drug Administration (FDA) for ignoring the reported serious COVID vaccine side effects.
The authors acknowledge the risks of COVID vaccines in certain populations, not least children, may outweigh the benefits. They also state that not a single published study has demonstrated that patients with a prior infection benefit from COVID-19 vaccination. Something which is not readily acknowledged by the CDC or Anthony Fauci, an indication, according to the authors, of how deeply entangled pandemic politics is in science.
They conclude that public health authorities are making a mistake and risking public erosion of trust by not being forthcoming about the possibility of harm from the vaccines.
MERCK AND VIOXX
It is revealing that the two scientists refer to Vioxx, which was once popular for treating the symptoms of arthritis. It was removed from the market in 2004 after concerns that it may have injured hundreds of thousands of patients, while possibly killing tens of thousands in the US.
Dr David Graham, whistleblower and senior FDA investigator, criticised the FDA’s approval process of Vioxx (rofecoxib), an anti-inflammatory drug administered orally. In various interviews and congressional hearings, he described the outcome of Vioxx as disastrous and unparalleled in the history of the US. He added that the saga surrounding Vioxx had constituted an unprecedented failure of the nation’s system of drug approval and oversight.
In 2004, Graham argued that the painkiller had caused 88,000 to 139,000 heart attacks in the US – 30-40 per cent of which were fatal – over the previous five years. Nevertheless, manufactured by Monsanto (a company with a proven track record of corrupt practices) and co-marketed by Merck, Vioxx became a leading drug in providing pain relief from the symptoms of various forms of arthritis.
Research presented to the FDA in early 2001 showed that patients taking Vioxx had a higher risk of heart attack compared to those taking some of the older alternatives.
However, the real game-changer came in 2004 when Dr Graham released the findings that found Vioxx increased the chance of heart attack and death from cardiac arrest significantly more than its biggest rival on the market. Dosages of Vioxx in excess of the recommended daily dose of 25 milligrams were also found to more than triple a patient’s risk compared to those who had not taken painkillers.
In September 2004, Vioxx was pulled from the market. But in 2006, more damning findings were revealed by a study that showed that some patients had likely suffered from a heart attack much sooner after starting treatment with Vioxx.
Appearing in the Canadian Medical Association Journal, the study showed that 25 per cent of the patients who had heart attacks while taking Vioxx did so within two weeks of starting the drug. This indicated that Vioxx-related cardiovascular risks may occur much earlier than previously thought.
The FDA was criticised for its close relationship with Merck and witnesses at a senate finance committee hearing described how danger signals of Vioxx went ignored. Indeed, a 2007 article published by the National Institutes of Health alleged that even though scientists at Merck knew that the drug might adversely affect the cardiovascular system, none of the intervention studies submitted to the FDA in 1998 were designed to evaluate such risk.
ROBBER BARONS AND GUINEA PIGS
Merck reported over $11 billion in Vioxx sales during the five years the drug was on the market. To date, the company has paid nearly $6 billion in litigation settlements and criminal fines over Vioxx. Still, in hard-nosed commercial terms, it was a massive success, resulting in a $5 billion gain for the company.
In May 2021, it was reported that Covid-19 vaccines had created at least nine new billionaires. According to research by the People’s Vaccine Alliance, the new billionaires included Moderna CEO Stéphane Bancel and Ugur Sahin, the CEO of BioNTech, which has produced a vaccine with Pfizer. Both CEOs were then worth around $4 billion. Senior executives from China’s CanSino Biologics and early investors in Moderna have also become billionaires.
Although the nine new billionaires are worth a combined $19.3 billion, the vaccines were largely funded by public money. For instance, according to a May 2021 report by CNN, BioNTech received €325 million from the German government for the development of the vaccine. The company made a net profit of €1.1 billion in the first three months of the year, largely thanks to its share of sales from the Covid-19 vaccine, compared with a loss of €53.4 million for the same period last year.
Moderna’s Covid-19 vaccine sales reached $1.7 billion in the first three months of this year and it had its first profitable quarter ever. Moderna is expected to make $13.2 billion in Covid-19 vaccine revenue in 2021. The company received billions of dollars in funding from the US government for development of its vaccine.
Big Pharma has every reason to perpetuate the notion of a deadly global pandemic and to inflate the efficacy of and need for its vaccines. And it, along with its associates in government and at the WHO, has every reason to discredit alternative and arguably more effective treatments like Ivermectin (see the online article ‘The Campaign against Ivermectin: WHO’s Chief Scientist Served with Legal Notice for Disinformation and Suppression of Evidence‘).
There is no need to cover ground here that has been covered extensively elsewhere but it is now abundantly clear that many continue to question the overall official COVID-19 narrative, the fear propaganda, the specific data, the PCR testing protocols, the apparent conflicts of interest and vaccine efficacy.
Moreover, A group of 57 leading scientists, doctors and policy experts recently released a report calling into question the safety and efficacy of the current Covid-19 vaccines. They are calling for an immediate end to all vaccine programmes.
There are hundreds of scientists who have questioned governmental and WHO strategy and who have brought attention to the extremely low risks posed by COVID to the bulk of the population as well as the destructive (ineffective) policies and decisions pertaining to lockdowns and other restrictions.
There are many other top scientists who are questioning the need for mass vaccination and who have also pointed out credible and extremely disturbing side effects (real and potential) of such a strategy, not least Dr Robert Malone, credited with developing mRNA vaccine technology, Dr Byram Bridle, a viral immunologist, and Dr Geert Vanden Bossche, a prominent virologist and vaccine expert.
Unlike Merck and Vioxx, it will be governments (the public) that foot any future indemnity costs of these experimental vaccines that have escaped proper (long-term) testing. And given the scale of the rollout, the damage caused could make the adverse effects of Vioxx seem a mere blip.
Vaccines that were brought to market via emergency authorisation use for an ‘emergency’ constructed on the basis of deaths so often wrongly attributed to COVID-19. Brought to market on the basis of flawed PCR test protocols with magnification cycles primed to create a ‘casedemic’.
To borrow from Dr David Graham: are we currently witnessing something more disastrous and unparalleled in the history of the world, let alone the US: an unprecedented failure of gobal drug approval and oversight?
In the meantime, while billions of vaccinated people serve as human guinea pigs, the newly crowned vaccine kings will make hay while the sun shines (and the fear continues).
YouTube censors video of Nobel Prize winner Dr. Satoshi Ōmura discussing ivermectin

By Tom Parker | Reclaim the Net | July 2, 2021
Before the coronavirus pandemic, ivermectin was described as a “wonder” drug by the medical community. And in 2015, Dr. Satoshi Ōmura and Dr. William C. Campbell were awarded half the Nobel prize in Physiology or Medicine for their work that led to the development of ivermectin.
“The importance of Ivermectin for improving the health and wellbeing of millions of individuals with River Blindness and Lymphatic Filariasis, primarily in the poorest regions of the world, is immeasurable,” the Nobel Assembly stated in its press release for the 2015 Nobel Prize in Physiology or Medicine.
But after the pandemic began, the tech giants have gone all out to purge content that recommends ivermectin as a treatment for COVID-19.
And today, these Big Tech policies against ivermectin resulted in one of Ōmura’s speeches where he discussed ivermectin being struck down for “violating YouTube’s community guidelines.”
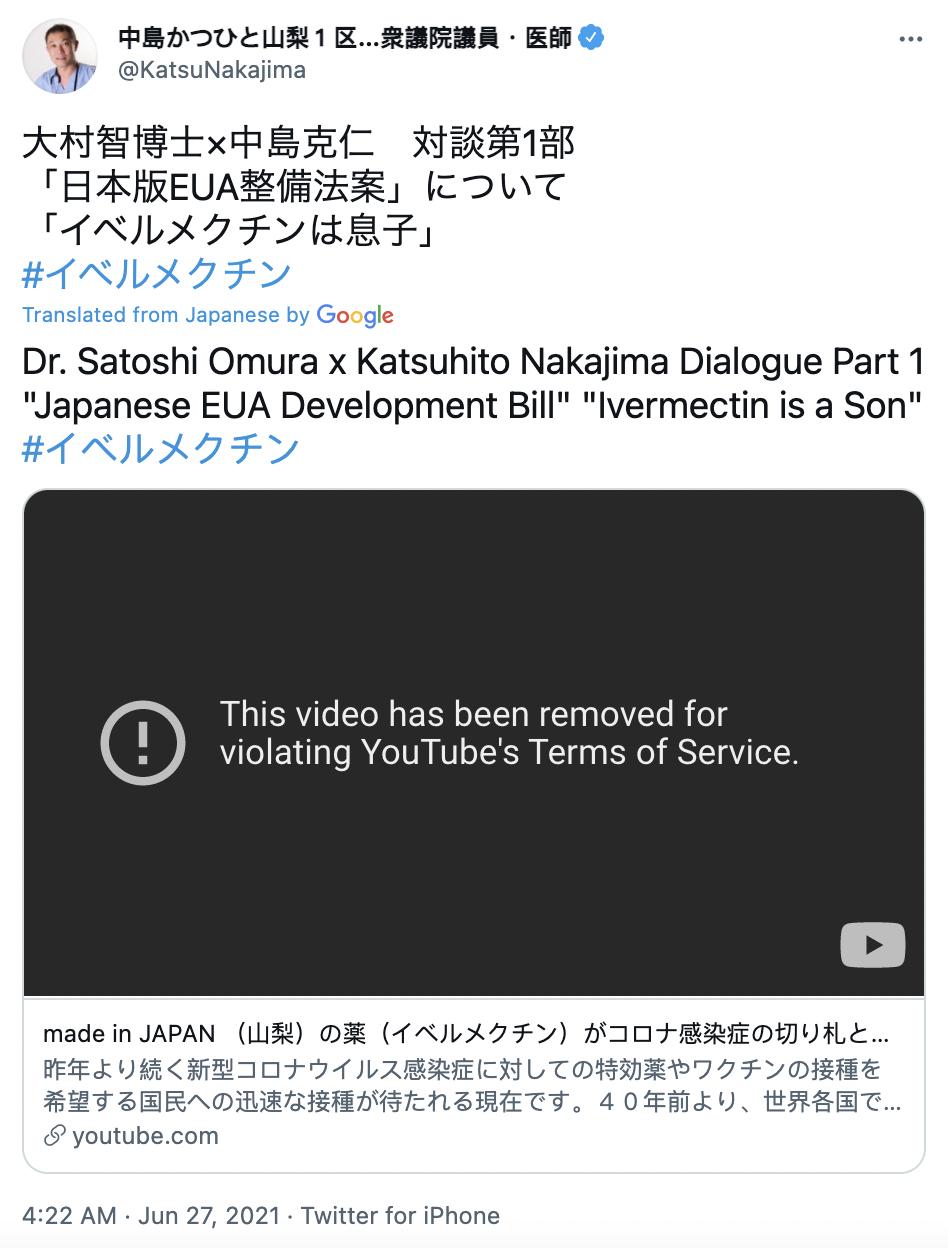
“When the fascists at YouTube censor the Noble Prize winner Dr. Satoshi Omura, a man whose discoveries have saved a hundred million + from blindness, the world has entered a very, very dark place,” Australian Member of Parliament Craig Kelly tweeted. “I cannot express in words how angry & sad this makes me & fearful for the future.”
Frontline Covid-19 Critical Care, an alliance of physicians and scholars that has committed to “research and develop lifesaving protocols for the prevention and treatment of COVID-19 in all stages of illness,” also spoke out against the censorship and warned that “brilliant scientists and lifesaving science are systematically being gagged.”
Ōmura joins the ranks of many other senators, lawmakers, medical journals, biologists, and YouTubers who have been censored by Big Tech for discussing ivermectin.
In many states, minors may consent to receive COVID-19 shot even without parent’s knowledge
By Mordechai Sones | America’s Frontline Doctors | June 30, 2021
A District Administration survey conducted just before the FDA’s authorization for 12-15-year-olds to receive the COVID-19 shot found that only 3 in 10 parents said they would vaccinate their children right away, with most instead wanting to wait and see, or saying they would not get their child vaccinated at all or would do so only if required for school.
However, with the authorization of Pfizer’s shot for 12-15-year-olds, a group that totals almost 17 million, minors can consent to receive the COVID-19 shot even without the parent’s knowledge in many states.
The age at which a minor can consent to receive the experimental biological agent in Alabama is age 14; in San Francisco, 12; Philadelphia, 12; North Carolina, 11; South Carolina, 16. America’s Frontline Doctors (AFLDS) Legal Director Ali Schultz explained: “They can all consent, minors can consent, on their own, even if they live with their mom and dad who are married, they live with their parents, no issues, the child literally can consent at school to receive the vaccine, without the parents even knowing.”
She continued: “We’ve had so many people reach out, and they were just heartbroken, they cannot believe that their child was able to get this without them even knowing, because as parents they were personally against the vaccine, and no-one even ran it by them.
“And what’s even scarier: It’s up to the health care provider, in a multitude of states; Iowa, Idaho, Washington, Arkansas; so if a ‘health care provider’ deems that it is appropriate for a minor to get the vaccine, then they can do so without parental consent.”
According to District Administration, although most states still require parental consent, “the landscape may be shifting slightly as more jurisdictions seek to encourage vaccination of young people.” Their specific findings are as follows:
- Most states (41) require parental consent for vaccination of minors below the age of 18, although one of these states (NE) requires consent below age 19. There are some exceptions to these requirements:
- Many allow for certain minors, such as those who are emancipated, homeless or living apart from their parent or guardian, or married, to self-consent.
- Cities in two states (San Francisco in CA and Philadelphia in PA), have moved to allow minors, ages 12 and older, to self-consent for COVID-19 vaccination.
- In one state (AZ), if a parent refuses to consent for COVID-19 vaccination, but if a child or a doctor requests it, a court order can be obtained to allow for vaccination.
- In 5 states, a minor’s ability to self-consent is based on a specific age as follows:
- Two states where a minor must be at least 16 (RI and SC)
- One state where a minor must be at least 15 (OR)
- One state where a minor must be at least 14 (AL)
- One state where a minor must be at least 11 (DC; in DC, each healthcare provider may institute additional requirements which could include requiring a parent or guardian to be present).
- The remaining 5 states apply the “mature minor doctrine”, meaning that there is no specific age cut-off but providers have discretion to decide if a minor possesses the maturity to consent for themselves (AR, ID, NC, TN, WA).
- This means that parental consent has already been required for 16-17 year-olds in most states (41) since the initial authorization of the Pfizer vaccine on December 11, 2020. Two additional states require consent for some subset of 12-15 year-olds, bringing the count to 43 states where most minors in this age group would need parental consent. Once the next group of children is eligible for vaccination, those below age 12, this number will grow to 45.
National Vaccine Information Center‘s Barbara Loe Fisher commented on the “shifting landscape”: “This past year, we have seen many lawmakers in the U.S. and other countries vote to eliminate or severely restrict civil liberties in the name of the public health. One of the most outrageous legislative actions violating parental and human rights took place in Washington, D.C. in November 2020 when City Council officials gave doctors the power to vaccinate children as young as 11 years old and hide what they did from parents. The D.C. Mayor refused to veto the bill and, in January 2021, the U.S. Congress sat on its hands and gave tacit approval to enactment of the most dangerous child vaccination law in America.”
She continued: “In a breathtaking violation of medical ethics and several federal laws, the new vaccine concealment law in Washington, DC allows doctors to extract “informed consent” from young children too immature to know what informed consent means or what a vaccine reaction looks and feels like. The D.C. City Council majority, with only three members dissenting, cruelly disempowered parents by voting to make it illegal for a doctor, insurance company or school administrator to divulge a child’s vaccination history in records that can be seen by the child’s mother or father.
“An 11-year old child does not know or understand his or her personal health history but most parent do. If a child has experienced previous vaccine reactions, has severe allergies or other health conditions that could increase vaccine risks, parents kept in the dark will not have a way to protect their child from further harm.
“Parents who don’t know which vaccines their children have been given will not be able to monitor them for signs of a potentially life-threatening vaccine reaction that requires immediate medical treatment. If the child is injured or dies after vaccination, parents will not know they must apply to the federal Vaccine Injury Compensation Program (VICP) before the filing deadline expires.
“Parents will not know their insurance company has been billed for vaccines. Parents will not know that a school the child attends is in possession of their child’s secret vaccination records even when there is a vaccine exemption for religious belief reasons on file with the school.
“This blatant violation of a parent’s moral right and legal responsibility to make medical risk decisions on behalf of a minor child was endorsed by the American Academy of Pediatrics22 and pushed through by the DC City Council, while the Mayor and the US Congress looked the other way.”
She concluded: “The Universal Declaration of Bioethics and Human Rights states that:
“The interests and welfare of the individual should have priority over the sole interest of science or society;” and “For persons who are not capable of exercising autonomy, special measures are to be taken to protect their rights and interests;” and “Any preventive, diagnostic and therapeutic medical intervention is only to be carried out with the prior, free and informed consent of the person concerned, based on adequate information.”
“It is a profound betrayal of public trust for any city, state or federal government to strip parents of their God given right to protect their children from harm by allowing a doctor to give a child a pharmaceutical product without getting a parent’s permission. Science is not perfect, doctors are not infallible, and pharmaceutical products like vaccines come with risks that can be greater for some individuals than others, which is why parents must retain the human right to exercise informed consent to medical risk taking on behalf of their minor children.
“Will the vaccine concealment bill that is now law in Washington, DC be exported to your state next?”
Mercury News provided the list of where parental or guardian consent is now generally required for COVID-19 vaccinations among people ages 12 to 15, based on a CNN query to health departments across all 50 states:
- Alabama — Yes for younger than 14
- Alaska — Yes
- Arizona — Yes
- Arkansas — Yes
- California — Yes
- Colorado — Yes
- Connecticut — Yes
- Delaware — Yes
- Florida — Yes
- Georgia — Yes
- Hawaii — Yes
- Idaho — Yes
- Illinois — Yes
- Indiana — Yes
- Iowa — “It is up to each individual health care provider/health system”
- Kansas — Yes
- Kentucky – Yes
- Louisiana — Yes
- Maine — Yes
- Maryland — Yes
- Massachusetts — Yes
- Michigan — Yes
- Minnesota — Yes
- Mississippi — Yes
- Missouri — Yes
- Montana — Yes
- Nebraska — Yes
- Nevada — Yes
- New Hampshire — Yes
- New Jersey — Yes
- New Mexico — Yes
- New York — Yes
- North Carolina — No for teens
- North Dakota — Yes
- Ohio — Yes
- Oklahoma — Yes
- Oregon — Yes for younger than 15
- Pennsylvania — Yes
- Rhode Island — Yes
- South Carolina — Yes
- South Dakota — Yes
- Tennessee — Yes for younger than 14
- Texas — Yes
- Utah — Yes
- Vermont — Yes
- Virginia — Yes
- Washington — Yes
- West Virginia — Yes
- Wisconsin — Yes
- Wyoming — Yes
Additionally, some private businesses or pharmacies have their own rules.
Featured Video

AIDS Inc. by Gary Null (2007)
or go to
Aletho News Archives – Video-Images
From the Archives
Clash of Civilization, Iran Part II
By Jamal Kanj – Intifada-Palestine.com – January 14, 2011
Israel’s survival kit is: perpetuate conflict, insecurity to rationalize collective hate and finally playing victim.
Devoid of conflict, Israel implodes internally; without hate, Zionism loses its justification; and playing eternal victim to continue blackmailing the West. Absence of this holy trinity, Israel ceases to exist.
From its inception, the house of Zion has mastered exploiting adversarial powers to advance Israel’s cause. For instance, their influence over the Democratic Party in the US began with President Truman’s bid for 2nd term election in 1948.
Responding to strong opposition from Secretary of State General George Marshall and Department experts urging against recognition of Israel, President Truman replied: “I’m sorry gentlemen but I have to answer to hundreds of thousands [Jewish voters] who are anxious for the success of Zionism. I do not have hundreds of thousands of [voting] Arabs among my constituents”
Zionists influence over liberal American politics was matched with the doctrinal school of Conservative theoreticians aligning the Republican Party’s platform with Israel’s objectives. The Neoconservative Zionists, coined Zioncons, invented the “Clash of Civilization” concept to fight Israel’s wars. … continue
Blog Roll
 Aletho News
- 12 Things Your Psychiatrist Was Trained Not to Tell You
- From Unipolar Universalism to Multipolar Civilizational Distinctiveness
- RSF military group defects, joins Sudanese army: State media
- Ireland goalkeeper refuses to play ‘Israel’ as squad weighs boycott
- China pushes back against US on Cuba, Iran
- Ukrainian Soldiers, Potential Mercenaries: Have Gun, Will Travel!
- Burnham’s UN debut… A masterclass in British disinformation
- Iran flights continue despite US aviation sanctions
- Global Tipping Points Lead the World Into a State of Entropy
- The day-after at the White House: USA and Xi Jinping
- If Americans Knew
- Israel forces Gazans to live in constant peril – Daily Update
- Deconstructing Netanyahu’s pants-on-fire UN rant – Daily Update
- Trump betrayed voters with his campaign lies and prioritized a foreign country once he took office
- Netanyahu calls Israel’s war in Gaza ‘opposite of genocide’ in UN speech to near-empty hall
- Settler Kidnappings: Torture, Sexual Abuse and Terrorisation of Palestinian Abductees as Israel Deepens Annexation of West Bank
- Gaza winter nears as 162,000 tents become unusable, raising fears of humanitarian crisis
- Netanyahu says, “It’s the opposite of genocide”; UN says Gaza economy is world’s ‘most severe crisis on record’ – Daily Update
- Israel’s US-Backed Assault on Gaza Has Created the ‘World’s Most Severe Economic Crisis on Record’: UN
- ‘Protecting U.S. Citizens’… From Israel
- ‘This is where I live now, the back of a truck’: a day in the life of a grandmother in Gaza
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

