After rollout under emergency authorisation, manufacturers of covid-19 vaccines now have their sights on regulatory approval. But what’s the rush, asks Peter Doshi, and is just six months of data from now unblinded trials acceptable?
In April 2021, Pfizer and Moderna announced efficacy results at the six month mark from the phase III trials of their respective covid-19 vaccines.1 2
Pfizer CEO Albert Bourla said the company’s data “confirm the favourable efficacy and safety profile of our vaccine and position us to submit a Biologics License Application to the US FDA [Food and Drug Administration].”1 And on 7 May it formally initiated that application which, if successful, will earn the Pfizer-BioNTech product, BNT162b2, the distinction of becoming the first covid-19 vaccine approved by the FDA.
Because lest we forget, all covid-19 vaccines currently in use in the US are available under emergency access only.
(The situation is similar in Europe, where four covid-19 vaccines have been granted “conditional marketing authorisations,” a fast track mechanism that can be used in emergencies. These can be converted into standard “marketing authorisations” pending positive data after authorisation, but this has not yet happened for any covid-19 vaccine being administered.)
As hundreds of millions of people around the world get vaccinated, it may seem like wordsmithing to highlight the fact that none of the covid-19 vaccines in use are actually “approved.” Through an emergency access mechanism known as Emergency Use Authorisation (EUA), the products being rolled out still technically remain “investigational.”3 Factsheets distributed to vaccinees are clear: “There is no FDA approved vaccine to prevent covid-19.”4
The approval-authorisation distinction is often misunderstood by the media,5 even in the scientific press. But it was the focus of much discussion back in September 2020. With large phase III trials by Pfizer and Moderna well under way, and the November US presidential election looming, many worried about political pressure resulting in the rollout of an unsafe or ineffective vaccine.6
The FDA had already come under fire, accused of bending to the White House in granting EUAs for two covid-19 treatments, hydroxychloroquine and convalescent plasma. But those fears largely dissipated when the FDA published a guidance document in early October outlining its expectations for the EUA. According to the document, at least half of a trial’s participants would need to be followed for at least two months.7 This alone made it all but certain no vaccine could cross the line before the election.
The FDA also said it would want a vaccine at least 50% effective (with a confidence interval reaching no lower than 30%) against a primary endpoint of preventing SARS-CoV-2 infection or covid-19 disease of any severity8—parameters it had previously defined as necessary for approval. Even for non-clinical parameters, like manufacturing quality, the FDA characterised its expectations for the EUA as “very similar” to those for approval.3
Six months: enough?
One key difference between EUA and approval (also called “licensure,” and which for vaccines is known as a BLA (Biologics License Application)) was the expected length of follow-up of trial participants. Unlike its clear articulation of two months for an EUA, the FDA has not committed to a clear minimum for approval.
Cody Meissner, a professor of paediatrics at Tufts University and member of the FDA’s advisory committee, was curious. “Is it possible to predict or estimate when conditions of safety and efficacy might be satisfied for BLA?” Meissner asked at the agency’s 10 December meeting which had been convened to consider the FDA’s first emergency authorisation for the Pfizer vaccine.
The FDA’s Doran Fink responded: “I couldn’t predict, but I will say that we typically ask for at least six months of follow-up in a substantial number of clinical trial participants to constitute a safety database that would support licensure.”
An approval based on six months of data would represent one of the fastest for a novel vaccine in FDA history. Among the six “first in disease” vaccines approved by the FDA since 2006, pre-licensure pivotal trials were a median of 23 months in duration, according to a recent analysis.9
Six months also seems substantially shorter than previously conceptualised expectations. A World Health Organization expert group on covid-19 vaccines (which included FDA regulators) in August 2020 called for follow-up “until at least month 12, or until an effective vaccine is deployed locally.”10 Another group, composed of industry and academic authors, similarly wrote in October 2020: “we recommend longer term follow-up of all participants … for at least a year after randomisation.”11
On paper, the phase III studies by Pfizer, Moderna, and Janssen are all of two years’ duration. But the FDA’s official position on minimum follow-up before licensure is unclear at best.
In its formal guidance last June, the agency said that for licensure applications, it wanted participants followed for covid-19 outcomes for “as long as feasible, ideally at least one to two years”12 after the first injection. But the same document states that safety assessments for “serious and other medically attended adverse events” should be studied “for at least six months after completion of all study vaccinations. Longer safety monitoring may be warranted for certain vaccine platforms.”
Asked to clarify whether its guidance is asking for follow-up of at least six months or one year, a spokesperson told The BMJ: “We do not have any further information beyond what is in the guidance document.”
Unblinded and without a control group—what about safety?
Duration of protection is not the only question that longer, placebo controlled trials can address. They also address vaccine safety.
“Very often, it’s the fact that we have that placebo controlled follow-up over time, that gives us the ability to say that the vaccine didn’t cause something at a longer period of time after vaccination,” the FDA’s Philip Krause explained last December.13
Yet there is a gap—currently of unknown size but growing—between any expectation of blinded placebo controlled data, and the reality that within weeks of the vaccines receiving an EUA the unblinding of trials commenced as placebo recipients were offered the chance to get vaccinated.
Steven Goodman, associate dean of clinical and translational research at Stanford University, told the FDA in an invited presentation last December, “Once a vaccine is made widely available and encouraged, maintaining a double blinded control group for more than a nominal period is no longer in the investigator’s (or regulator’s) control and undue pressure to do so may undermine the entire vaccine testing enterprise.”14
Goodman’s recommendation was to rapidly convert the trials into crossover studies, enabling those on placebo to get vaccinated (and vice versa), while maintaining the blind. The companies challenged the feasibility, calling it “onerous,” and a crossover never occurred.15
The BMJ asked Moderna, Pfizer, and Janssen (Johnson and Johnson) what proportion of trial participants were now formally unblinded, and how many originally allocated to placebo have now received a vaccine. Pfizer declined to say, but Moderna announced that “as of April 13, all placebo participants have been offered the Moderna covid-19 vaccine and 98% of those have received the vaccine.”2 In other words, the trial is unblinded, and the placebo group no longer exists.
Janssen told The BMJ: “We do not have specific figures on how many of our study participants have received a vaccine at this time.” But the company confirmed it was implementing an amended protocol across all countries to unblind all participants in its two phase III trials, the earlier of which passed the median of two month follow-up mark in January.
How the FDA will weigh the loss of blinding and placebo controlled follow-up is unclear, but just months ago the agency said these trial properties were vital.
“Continuation of placebo controlled follow-up after EUA will be important and may actually be critical to ensure that additional safety and effectiveness data are accrued to support submission of a licensure application as soon as possible following an EUA. … Once a decision is made to unblind an ongoing placebo controlled trial, that decision cannot be walked back. And that controlled follow-up is lost forever,” the FDA said last October.3
At its next advisory committee in December 2020, the FDA reiterated the importance of the placebo group: “Placebo controlled follow-up can be very important in showing that whatever happened in the vaccine group also happened in the placebo group. Because that’s our best way of knowing.”13
What’s the rush?
The US’s “Operation Warp Speed” delivered on its promise to get a novel vaccine into arms in record time (box). Millions of doses of vaccines are being administered daily across the US, making clear that lack of FDA approval is no barrier to access. So just what benefit is there in seeking, and granting, a BLA?
The BMJ asked the manufacturers why they were seeking a BLA. Moderna did not respond and Janssen only confirmed it intended to apply for a BLA “later in 2021.” Pfizer likewise did not answer but instead quoted an FDA webpage on medical devices, which stated: “Sponsors of EUA products are encouraged to follow up the EUA with a pre-market submission so that it can remain on the market once the EUA is no longer in effect.”16 But EUAs have no built-in expiry date—in fact, 14 EUAs for Zika diagnostic tests remain active despite the public health emergency expiring in 2017.17
Cody Meissner told The BMJ he saw some distinct advantages of a BLA over EUA. An approved vaccine, for one, would provide “an element of assurance,” increasing public trust in the vaccines, particularly for those currently sitting on the fence. It would also pave the way for claims of vaccine injury to be routed through a more established compensation programme, and for adding the vaccine to government funded schemes to reach children in financial need.18 Finally, it may affect the potential for vaccine mandates: “It is unlikely these vaccines will be mandated while an EUA is in place. Remember that currently these vaccines are still considered experimental.”
While still under EUA, an increasing number of educational and other institutions have already mandated vaccines, but debates over the legality of these actions has hinged on the distinction between authorisation and approval.19
But approving a vaccine in order to legally support mandates or convince people of its safety arguably puts the cart before the horse. Meissner responded that a BLA would not be issued until the FDA is convinced of the short and long term safety of these vaccines.
No new biodistribution studies for covid-19 vaccines
Officials have consistently emphasised that despite shaving years off traditional timelines for producing vaccines, no compromises in the process were taken.20 However one type of study, tracking the distribution of a vaccine once injected in the body, was not conducted using any of the three vaccines currently authorised in the US.
Such biodistribution studies are a standard element of drug safety testing but “are usually not required for vaccines,” according to European Medicines Agency policy,21 which adds, “However, such studies might be applicable when new delivery systems are employed or when the vaccine contains novel adjuvants or excipients.”
In the case of covid-19 vaccines, regulators accepted biodistribution data from past studies performed with related, mostly unapproved compounds that use the same platform technology.22232425
Janssen told The BMJ its covid-19 vaccine leverages the same technology as its Ebola vaccine, which received licensure last June. “Our confidence in our adenovirus vector Ad26 is based on our experience with this vector.”
Pfizer and Moderna did not respond to The BMJ’s questions regarding why no biodistribution studies were conducted on their novel mRNA products, and none of the companies, nor the FDA, would say whether new biodistribution studies will be required prior to licensure.
Footnotes
Competing interests PD gave a public statement at the October and December FDA advisory committee meetings mentioned in this article (transcripts here: https://faculty.rx.umaryland.edu/pdoshi/#publications), and may continue to engage in public input towards regulatory decision making around covid-19 vaccines. PD is also employed by a university that has mandated covid-19 vaccines for all faculty, staff, and students. The views and opinions expressed here are those of the author and do not necessarily reflect official policy or position of the University of Maryland.
US Food and Drug Administration. 161st Vaccines and Related Biological Products Advisory Committee (VRBPAC) meeting. 2020. https://www.fda.gov/media/143982/download
US Food and Drug Administration. Development, authorization and licensure of vaccines to prevent COVID-19. October 6, 2020. https://www.fda.gov/media/142723/download
. An overview of vaccine development, approval, and regulation, with implications for covid-19. Health Aff (Millwood)2021;40:25–32.doi:10.1377/hlthaff.2020.01620pmid:33211535
US Food and Drug Administration. 162nd Vaccines and Related Biological Products Advisory Committee (VRBPAC) meeting. 2020. https://www.fda.gov/media/144859/download
Goodman S. Considerations for placebo-controlled trial design if an unlicensed vaccine becomes available. Vaccines and related biological products advisory committee. 2020. https://www.fda.gov/media/144354/download
. Emergency use authorizations (EUAs) versus FDA approval: implications for covid-19 and public health. Am J Public Health2021;111:1065–9.doi:10.2105/AJPH.2021.306273pmid:33950730
THE problem with the Covid-19 vaccines is that we simply do not have enough information about their side-effects, and no one should be shamed (especially not by the President of the United States) or have their lives restricted for having this reasonable, wholly unselfish concern.
Such information does not exist at all for under-18s. The small-scale trials were designed only to test the vaccine on adults. Yet, largely because of media hysteria which has been recently accompanied by outright incitement, local officials have taken it upon themselves to start vaccinating 17-year-olds, citing the bogeyman ‘Indian variant’ in our midst.
The vaccine nudgers in government and the media, aided this week by a multi-million-pound YouTube ad campaign to persuade young people to get vaccinated, deliberately miss the point about the supposedly ‘extremely rare’ side-effects of these experimental vaccines, which include fatal blood clots in some cases.
The trouble is that if our ‘brilliant’ scientists knew nothing about the blood clots when the vaccine was first administered to citizens in December, what else don’t they know about?
Last week, the British regulator MHRA reported 41 new cases and nine more deaths as a result of one of these side-effects, a particular kind of clot known as cerebral venous sinus thrombosis alongside low platelets or thrombocytopenia. To date, there have been 209 cases and 41 deaths reported in the UK for the AstraZeneca vaccine alone. The first were reported in January.
According to an analysis of published MHRA data by Dr Hamid Merchant, a total of 532 ‘blood system events’, including 20 deaths, came through the UK’s Yellow Card system relating to the AstraZeneca jab between January 4 and March 14. There were thousands of non-blood-related reports besides.
Let’s recap on the public guidance regarding the AstraZeneca vaccine. First we were told ‘this vaccine is safe, get vaccinated.’ Then they said, ‘the benefits of this vaccine outweigh the risks, get vaccinated.’ Then the goalposts were moved further: ‘The benefits of that vaccine outweigh the risks if you are over the age of 30, but get vaccinated.’ And now, ‘the benefits of this vaccine outweigh the risks if you are over 40, but get vaccinated, or else!’
If this is how much ‘the science’ has changed in a few months, what will ‘the science’ be a year or two from now? What will we know in the future that cannot be established now? Scientists have not begun to discuss other fatal adverse reactions to have emerged, most significantly the neurological ones for which the AstraZeneca trials were paused.
If countries such as Denmark and Slovakia can suspend the rollout of a vaccine as a precaution, why are individual citizens stupid or callous if they decline the vaccine as a precaution?
In the United States, the government has recorded more deaths after Covid vaccinations than from all other vaccines administered in the country between mid-1997 and the end of 2013, as was reported by Tucker Carlson on Fox News earlier this month. Nothing to see here, of course.
Any reasonable government would have at the very least stopped blackmailing people into getting vaccinated by now. Instead, they have the brass neck to demand that we put our lives in their hands as if we owe it to them. Coerced vaccination is not merely mandatory vaccination, it is mandatory trust, both in government and in ‘the science’, whatever that is.
It is worth reminding those with short memories that tobacco was ‘safe’ for decades. The scientific community promoted smoking not only as safe, but healthy. They were, of course, assisted by celebrities, some of whom would later become senior politicians. And for some 50 years, the overwhelming majority of people were dumb enough to believe it. Who could have guessed that inhaling tar into your lungs twenty times a day, every day, for years, might be bad for your health? We see grim warnings about heart disease, lung cancer and infertility on cigarette packaging today only because scientific outliers of yesterday eventually overwhelmed the consensus with evidence.
More recently and more relevant to the present fiasco, the swine flu vaccine, Pandemrix, was declared safe by regulators in 2009. It was safe, for most. But for some 1,000 people, most of whom were not at any significant risk from swine flu, the vaccine triggered narcolepsy, a crippling chronic sleep disorder that leaves sufferers unable to stay awake. It was only after it was too late for them that the authorities conceded there was a link between Pandemrix and narcolepsy.
One of the victims of Pandemrix, 23-year-old Katie Clack from Peterborough, committed suicide in 2014 because her narcolepsy left her with ‘no quality of life’.
In 2018, the progressive news website Buzzfeedpublished a powerful feature about NHS workers who had their lives and careers ruined by the side-effects of the swine flu vaccine. Nurse Meleney Gallagher, who now has narcolepsy, told Buzzfeed: ‘I was pressured into it.’
If history is anything to go by, the idiots out there who think it’s acceptable to bully their vaccine-hesitant friends, colleagues, strangers and even close family are going to look very silly ten years from now.
MIT did a study on Covid Skeptics and guess what? They found out we’re better at science, data analytics and communication than they are! Unfortunately this means we have to be stopped. I read from the study and give my commentary.
The risk of long Covid – the persistence of Covid symptoms like fatigue and headaches for three months or more – has been used to justify health interventions including with younger people who are not at elevated risk from acute infection. For instance, Health Secretary Matt Hancock suggested in April that young people should get vaccinated to avoid long Covid, saying Covid was a “horrible disease” and long Covid affected people in their 20s “just as much” as any other age group, sometimes with “debilitating side effects that essentially ruin your life”.
New research, however, casts doubt on whether symptoms attributed to long Covid are really associated with COVID-19 at all, at least in adolescents.
The study, which has yet to be peer-reviewed, is the first (as far as the authors are aware) to compare the incidence of long Covid symptoms in those who have and have not had the virus, defined in terms of having detectable antibodies. It involved 1,560 secondary school pupils aged 13 to 18 in Eastern Saxony (median age 15) enrolled in the SchoolCovid19 study since May 2020. All have been tested for antibodies throughout the study and in March and April 2021 completed a 12 question long-Covid survey regarding “the occurrence and frequency of difficulties concentrating, memory loss, listlessness, headache, abdominal pain, myalgia/arthralgia, fatigue, insomnia and mood (sadness, anger, happiness and tenseness)”.
The findings are remarkable. Of 1,560 pupils, 1,365 (88%) were seronegative (no IgG antibodies detected) and 188 (12%) were seropositive. Each of the long Covid symptoms was present in at least 35% of the pupils within the seven days before the survey. Crucially, however, there was no statistically significant difference in reported symptoms between seropositive and seronegative pupils (see chart above).
These findings suggest that, in adolescents at least, the prevalence of long Covid is considerably exaggerated, and that the presumed symptoms of long Covid are common to those who have and have not had the virus. One possibility is that this is a background rate for teenagers. However, the authors are struck by the high incidence of the symptoms and suggest they may be linked to the lockdown conditions, saying they confirm “the negative effects of lockdown measures on mental health and well-being of children and adolescents”.
Because the study was only among adolescents it did not include any who had suffered severe illness or been hospitalised, which is where some earlier research on long Covid has focused.
For adolescents it suggests that the threat from long Covid has been greatly overdone, and that the apparent symptoms of the condition are much more likely to be caused by lockdowns than by a viral infection.
I’ve written about this before, and I’m sure I’ll write about it again.
We’re told that the RNA COVID vaccines force the cells of the body to produce a foreign “spike” protein.
There is a little thing you may have heard of called EVIDENCE.
In other words, show me a well-done study, using a few thousand people who have been vaccinated, which proves that all these people’s cells ARE producing that foreign protein and ONLY that foreign protein.
There isn’t such a study.
But if there were—
“Look, a few hundred people didn’t produce the spike protein at all. Wonder what they DID produce.”
“I see a hundred people out of two thousand who produced a huge excess of the spike protein. Wonder what effect THAT is having.”
“I see two hundred people who produced the spike protein plus a bunch of other foreign proteins. A few of those foreign compounds I’ve never seen before. That’s not good at all.”
In fact, show me a large-scale study in which an injection is designed to force the human body to produce ANY specific protein. Let’s see the results.
Can’t find that study, either?
Believing what genetic researchers tell you is like believing what a grifter tells you about how to win at roulette.
For example, are you aware that, after decades of genetic research and tens of thousands of studies linking genes to diseases, there isn’t a single gene-treatment that can cure a disease across the board?
What there is, is a great deal of money that hustlers have raised for bio-tech firms. And there are many sky-blue promises.
And oh yes, there are many examples of errors, in which experimental gene insertions yield unexpected results. Unintended and dangerous results. Unpredicted alterations in genomes.
So the huge numbers of reported injuries and deaths from the COVID RNA vaccines are surely the result of more than just the production of the spike protein.
Why is nobody talking about this?
Because people assume the problem must be the spike protein and only that protein.
The people of planet Earth are part of a guinea-pig vaccine experiment that is much wider than that. We are being subjected to an open-ended genetic spin of the roulette wheel.
And there are no safeguards and no comprehensive follow-ups.
For this reason alone, the entire effort to develop the RNA injections should have been banned from the beginning—until researchers demonstrated convincingly that the risks would be minimal. Of course, they couldn’t make that guarantee.
But the fatuously named Warp Speed program rocketed ahead. Based on pretentious and speculative “science.”
People tend to think—because they watch sci-fi movies—that scientific evil doers are firing a perfectly destructive single arrow at the heart of humanity. But evil-doers are quite capable of launching a thunderstorm of multiple pyrotechnics beyond their control.
As I pointed out in prior articles on this subject, the analogous area of GMO plant genetics is replete with uncontrolled effects—including gene drift, in which injected Monsanto genes move from plants into soil bacteria and human gut bacteria.
Genetic ripple-effects throughout an organism can force the unnatural production of a number of different proteins while modifying others.
This is NOT good; and some of the ways in which it is not good are unknown.
Based on the current level of knowledge in the field of gene-research, the entire program of manufacturing and injecting RNA into the body is an insane criminal enterprise.
As time passes, I expect investigators to discover new ways in which these RNA shots are harming people. And some of those investigators will say, “THIS turns out to be what the vaccine is doing. THIS one thing.” And they’ll be wrong.
It’s five, ten, 20 different things. Caused by ripple effects throughout the genome.
In this episode, Dr. Pierre Kory, Chief Medical Officer of the FLCCC Alliance, discusses the ways that public health organizations are manipulating scientific data on early COVID-19 therapeutics in order to sow uncertainty; and why they are doing it.
Donate to the Front Line Covid-19 Critical Care Alliance to educate medical professionals and the public in safe and effective ways to prevent and treat COVID-19.
Your donations will help support the FLCCC Alliance with the rising costs of public relations, research, medical education, translation, and advocacy.
A few months ago I wrote about the government’s Covid-related advertising expenditure. In late spring 2020, all Covid-19 media campaigns were centralised into the Cabinet Office, Michael Gove’s sprawling 8,000-plus strong department. By the end of the year, HM Government had become the country’s largest spender for media advertising. My estimate was a total government outlay on advertising for Covid-related purposes in 2020 of approximately £240million.
For media outlets facing a collapse in advertising revenue because of the closure of the economy, the government spending was a lifeline. Whether the Fourth Estate could objectively report on the government’s handling of the virus whilst simultaneously receiving copious funding from that same government was highly debatable.
Since my article in February, more data has come to light. The Cabinet Office has continued spending heavily on Covid media campaigns, mainly through its media buying partner Manning Gottlieb, laying out just over £87million in the first three months of 2021. This brings its Covid advertising spend to more than £280million between April 2020 and March 2021.
Since the beginning of the coronavirus scare, the Cabinet Office’s outlay on Covid media campaigns has increased steadily, with Q1 21’s figure (£87million) being more than double the amount spent in Q2 20 (£42.6million), and up significantly on both Q3 20 (£71.3million) and Q4 20 (£79.7million). (As noted, it was in Q2 20 that the Cabinet Office began centralising Covid-related media programmes.)
Approximately 88 per cent of the Cabinet Office’s advertising spend is done through Manning Gottlieb, with whom the government has had a close working relationship since awarding the company a £800million media buying services contract in October 2018.
At that time Alex Aiken, Executive Director for Government Communications, stated that the government’s communications team sees such media endeavours as an important way to counter ‘disinformation’ and ‘fake news’. As anyone with a decent grasp of history will know, it is of course governments who are the regular purveyors of truth and honesty: the Soviet Union’s Pravda (translating as ‘truth’) being a helpful example of such services rendered to the public by the benevolent state.
However, this is only part of the story. After this large contract, Manning Gottlieb were awarded a further three contracts specifically with the Cabinet Office.
The first of these was in November 2018 at a value of £183million: the primary focus of this appears to have been for media campaigns during the transition period following Britain’s exit from the European Union. Nevertheless, with an end date of 31 May 2022, a proportion of these resources were funnelled into Covid-19 media campaigns.
Subsequently, a £119million contract was signed (effective March 2020) purely for the provision of media buying services for Covid-19 related campaigns. This contract was later extended – until either March or August 2021 (the government’s website is unclear) – by a further £229million, bringing this contract to a total value of £348million.
A third contract, effective 1 April 2021, was signed for the same purpose, Covid-19 media campaigns. This contract is extendable until 21 May 2022 and has a maximum value of £320million. Whether it will be expanded in a similar fashion to the previous contract signed with Manning Gottlieb remains to be seen.
Taken together, the three contracts have a value of £851million. As noted, some of this figure was spent before the pandemic on information campaigns surrounding Brexit. Nevertheless, over the last two quarters Covid advertising spending has outweighed Brexit by a factor of about 4:1. To this sum should be added spending from bodies such as Public Health England before the Cabinet Office’s centralisation efforts, which appears to be in the region of £15million, a figure smaller than I previously estimated.
That said, if the most recent contract with Manning Gottlieb was extended in the same way as the previous one (by an additional £229million), there is no reason why the Cabinet Office’s Covid advertising spend could not hit a total of £1billion over the next year to year-and-a-half.
With a pandemic that appears all but finished – oh, but for an entirely unpredictable ‘Indian variant’ – one wonders what the government will do with hundreds of millions of pounds of advertising through to late May next year. One can only presume that it will be used to browbeat the public into accepting a vaccine for which the majority have no need, or for the increasingly probable reimposition of further lockdowns.
The first of these prompts the question: if you are spending hundreds of millions to persuade people to get a vaccine, perhaps it is not all that necessary in the first place. Were the vaccine of an ordinary type and of indisputable value, I dare say no media campaign at all would be necessary: there is little more than their own health that people care about.
That contracts are projected to last at least another year is indeed worrying. Along with councils advertising positions for ‘Covid marshals’ until 2023, one wonders if the government already has plans for further infringements on our liberties, the timeframe for which has been built into contracts such as those as agreed with Manning Gottlieb. Given the backtracking, twisting and turning that has been displayed to date, it would not appear unlikely.
With a remit to purchase advertising across all media types, companies such as Manning Gottlieb are central to the dissemination of information in the public sphere. It remains an open question whether, while receiving central funds important to their survival, the media will be able or willing to scrutinise government policy, both in the realms of further lockdowns and of the constant bombardment of vaccine propaganda.
The track record so far shows that the vast majority of the media is both unable and unwilling to ask difficult questions surrounding the government’s handling of the pandemic. With hundreds of millions of pounds sloshing around over the next few years, don’t expect that to change any time soon.
FDA managed to find 385 adverse event reports for either HCQ or CQ in its FDA adverse event reporting system database, as justification for withdrawing its EUA for the chloroquine drugs.
But there wa something strange about these reports. Only 102 of the 385 reports, or 26%, came from the United States. Why would foreigners be submitting reports of adverse events associated with a chloroquine drug to the FDA, instead of to their own pharmacovigilance system?
According to FDA, “FAERS is a database that contains information on adverse event and medication error reports submitted to FDA.” It is not an international database.
Might FDA have requested that foreign entities submit reports? Might some of those foreign entities have been sites where the HCQ overdose trials were conducted? The big three multicenter overdose trials were Recovery, Solidarity and REMAP-Covid. Page 8 of the FDA report does indicate that some of those patients, for whom adverse event reports were filed, had received excessive HCQ doses. Of a total of 256 reports for which FDA had dosing data, depending where you place the excessive dose cut-off, between 23 and 95 had received high doses.
FDA did a number of different things to suppress the use of hydroxychloroquine. This just happens to be one thing I had not previously reported on.
What else is interesting is that this report was compiled in May 2020. It is attached to a website dated July 2020, ten months ago.
In the intervening 10 months, well over 100 papers have been published on HCQ’s use in Covid. FDA claims, “The FDA’s job is to carefully evaluate the scientific data on a drug to be sure that it is both safe and effective for a particular use…” Yet FDA has ignored this massive amount of accumulating literature on hydroxychloroquine, during which 400,000 Americans died of/with Covid. Why? Willful misconduct?
It appears that some time last month the EPA provided a major update of what it calls its “climate change indicators.” The EPA’s web page for this is headed “Climate Change Indicators in the United States,” with the sub-heading “Climate Change Is Happening Now.” The update is an initiative of the Biden administration, now eager to invest a few trillion dollars of your money in new “green” infrastructure, after several years in which the Trump EPA paid no attention to keeping these data up to date. The New York Times reports on the big update on today’s front page, under the headline “Climate Change Is getting Worse, E.P.A. Says. Just Look Around.”
The basic technique here is to propagandize you with every sort of essentially irrelevant anecdotal information, while diverting your attention away from the only indicator of “climate change” that actually counts, which is temperature. After all, if temperatures aren’t going up, it isn’t “global warming.” Here, we have some 54 supposed climate “indicators” — everything from rain to drought to ice to sea level — out of which the things relating to actual temperature are only a handful, and then are buried deep in the midst of all the others, probably in the hope that you will miss them. And moreover, the temperature data are then grossly misrepresented in what has to be an intentional effort at deception.
But let’s start with the official line from the new Biden EPA.
The Earth’s climate is changing. Temperatures are rising, snow and rainfall patterns are shifting, and more extreme climate events – like heavy rainstorms and record high temperatures – are already happening. Many of these observed changes are linked to the rising levels of carbon dioxide and other greenhouse gases in our atmosphere, caused by human activities.
The Times then picks up on the theme by its headline calling for you to “just look around” to determine that “climate change” is happening. The idea is that you can determine that there is “climate change” by observing ice on ponds, or something, without having to bother with those complicated thermometers, let alone sophisticated satellite measurements:
Wildfires are bigger, and starting earlier in the year. Heat waves are more frequent. Seas are warmer, and flooding is more common. The air is getting hotter. Even ragweed pollen season is beginning sooner. . . . [EPA’s indicators] map everything from Lyme disease, which is growing more prevalent in some states as a warming climate expands the regions where deer ticks can survive, to the growing drought in the Southwest that threatens the availability of drinking water, increases the likelihood of wildfires but also reduces the ability to generate electricity from hydropower.
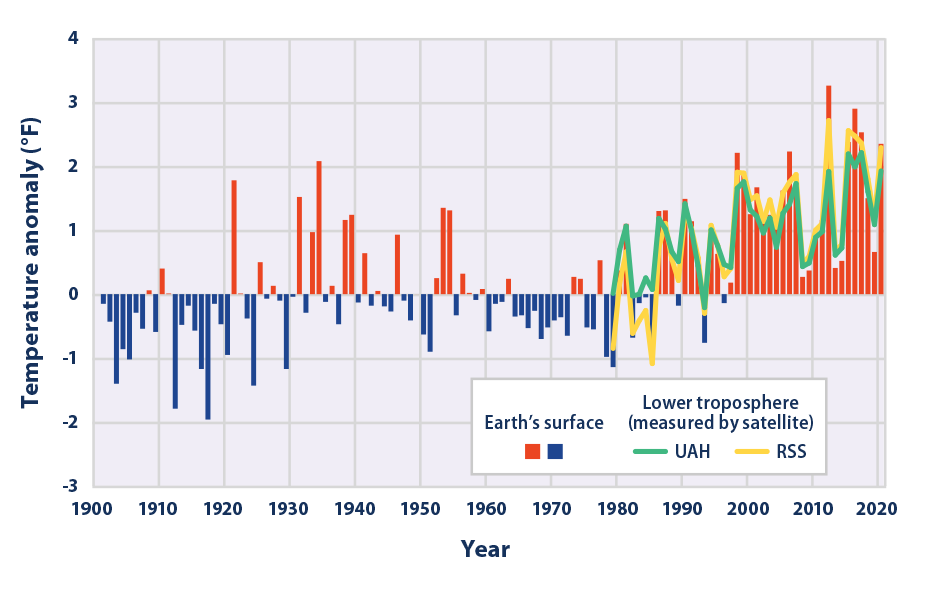
So how about the temperature guys? As you can see, the Times does throw in a couple of references to “heat waves” and “hotter air” in the midst of all the stuff about flooding, ragweed pollen, ticks, and whatever else. What’s missing is any citation or link to any source to support the assertion about actual temperatures. But over at the EPA page, under the heading “U.S. and Global Temperature,” we find the following graph, which is said to have been updated to April 2021:
That appears rather scary! Everything looks like it is going up sharply with passing time. Check out especially the green line, which is identified as the “lower troposphere [temperatures] (measured by satellite) of UAH.” The green line ends with a steep uptick, leaving it with the latest data point just below a record reached in 2016, and a full 2 deg F above the 1901-2000 average.
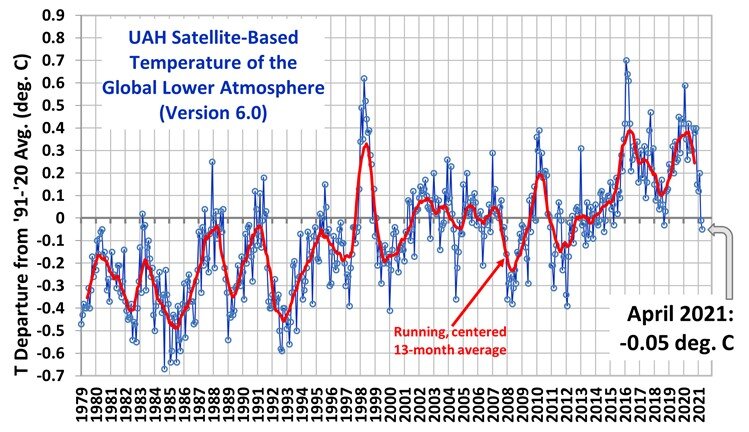
Oh, but here is the actual lower troposphere temperature record from UAH, available at the website of Roy Spencer, who is the guy who compiles the UAH record:
There are a few differences in the presentation that require a little interpretation, like the EPA graph is in deg F and has anomalies from a 1901-2000 mean, while the UAH graph is in deg C and shows anomalies from a 1991-2020 mean. But still, it leaps out that the green line on EPA’s web page, said to be the UAH record, ends with a sharp uptick and with the last point a full 2 deg F above the mean line; while this record, from UAH itself, ends with a sharp downtick and the last point actually below the mean line. Although EPA explicitly says on its web page that it updated the information in April 2021, this downtick in the UAH record began in January 2020 — a year and 4 plus months ago — and reflects a decline in lower troposphere temperatures of some 0.65 deg C, which is almost 1.2 deg F.
In other words, well more than half of the seemingly scary increase in temperature since 1901 shown in the EPA graph has just gone away in the last 16 months. So the Biden EPA, not wanting to complicate the official story of “climate change is happening now,” simply truncated the data in its graph at January 2020 to shut out the last year plus of big temperature declines. There is no way to characterize the EPA graph as other than intentionally deceptive.
I guess it’s OK because it’s in the noble cause of convincing the American people to allow the government to spend a few trillion dollars on windmills and electric car charging stations for the rich.
Awareness of ivermectin’s efficacy and its adoption by physicians worldwide to successfully treat COVID-19 have grown exponentially over the past several months. Oddly, however, even as the clinical trials data and successful ivermectin treatment experiences continue to mount, so too have the criticisms and outright recommendations against the use of ivermectin by the vast majority, though not all, of public health agencies (PHA), concentrated largely in North America and Europe.
The Front Line COVID-19 Critical Care Alliance (FLCCC) and other ivermectin researchers have repeatedly offered expert analyses to respectfully correct and rebut the PHA recommendations, based on our deep study and rapidly accumulated expertise “in the field” on the use of ivermectin to treat COVID-19. These rebuttals were publicized and provided to international media for the education of providers and patients across the world. Our most recent response to the European Medicines Agency (EMA) and others recommendation against use can be found on the FLCCC website here.
In February 2021, the British Ivermectin Recommendation Development (BIRD), an international meeting of physicians, researchers, specialists, and patients, followed a guideline development process consistent with the WHO standard. It reached a consensus recommendation that ivermectin, a verifiably safe and widely available oral medicine, be immediately deployed early and globally. The BIRD group’s recommendation rested in part on numerous, well-documented studies reporting that ivermectin use reduces the risk of contracting COVID-19 by over 90% and mortality by 68% to 91%.
A similar conclusion has also been reached by an increasing number of expert groups from the United Kingdom (UK),Italy, Spain, United States (US), and a group from Japan headed by the Nobel Prize-winning discoverer of Ivermectin, Professor Satoshi Omura. Focused rebuttals that are backed by voluminous research and data have been shared with PHAs over the past months. These include the WHO and many individual members of its guideline development group (GDG), the FDA, and the NIH. However, these PHAs continue to ignore or disingenuously manipulate the data to reach unsupportable recommendations against ivermectin treatment. We are forced to publicly expose what we believe can only be described as a “disinformation” campaign astonishingly waged with full cooperation of those authorities whose mission is to maintain the integrity of scientific research and protect public health.
The following accounting and analysis of the WHO ivermectin panel’s highly irregular and inexplicable analysis of the ivermectin evidence supports but one rational explanation: the GDG Panel had a predetermined, nonscientific objective, which is to recommend against ivermectin. This is despite the overwhelming evidence by respected experts calling for its immediate use to stem the pandemic. Additionally, there appears to be a wider effort to employ what are commonly described as “disinformation tactics” in an attempt to counter or suppress any criticism of the irregular activity of the WHO panel.
The WHO Ivermectin Guideline Conflicts with the NIH Recommendation
The FLCCC Alliance is a nonprofit, humanitarian organization made up of renowned, highly published, world-expert clinician-researchers whose sole mission over the past year has been to develop and disseminate the most effective treatment protocols for COVID-19. In the past six months, much of this effort has been centered on disseminating knowledge of our identification of significant randomized, observational, and epidemiologic studies consistently demonstrating the powerful efficacy of ivermectin in the prevention and treatment of COVID-19. Our manuscript detailing the depth and breadth of this evidence passed a rigorous peer review by senior scientists at the U.S Food and Drug Administration and Defense Threat Reduction Agency. Recently published, our study concludes that, based on the totality of the evidence of efficacy and safety, ivermectin should be immediately deployed to prevent and treat COVID-19 worldwide.
The first “red flag” is the conflict between the March 31, 2021, WHO Ivermectin Panel’s “against” recommendation and the NIH’s earlier recommendation from February 12th of a more supportive neutral recommendation based on a lower amount of supportive evidence of ivermectin’s efficacy at that time.
Two flawed lines of analysis by the WHO appear to account for this inconsistent result:
The WHO arbitrarily and severely limited the extent and diversity of study designs considered (e.g., retrospective observational controlled trials (OCT), prospective OCTs, epidemiological, quasi-randomized, randomized, placebo-controlled, etc.).
The WHO mischaracterized the overall quality of the trial data to undermine the included studies.
The Severely Limited Extent and Diversity of Ivermectin Data Considered by the WHO’s Ivermectin Panel
The WHO Ivermectin Panel arbitrarily included only a narrow selection of the available medical studies that their research team had been instructed to collect when formulating their recommendation, with virtually no explanation why they excluded such a voluminous amount of supportive medical evidence. This was made obvious at the outset due to the following:
No pre-established protocol for data exclusion was published, which is a clear departure from standard practice in guideline development.
The exclusions departed from the WHO’s own original search protocol it required of Unitaid’s ivermectin research, which collected a much wider array of randomized controlled trials (RCT).
Key Ivermectin Trial Data Excluded from Analysis
The WHO excluded all “quasi-randomized” RCTs from consideration (two excluded trials with over 200 patients that reported reductions in mortality).
The WHO excluded all RCTs where ivermectin was compared to or given with other medications. Two such trials with over 750 patients reported reductions in mortality.
The WHO excluded from consideration 7 of the 23 available ivermectin RCT results. Such irregularities skewed the proper assessment of important outcomes in at least the following ways:
Mortality Assessment
WHO Review: Excluded multiple RCTs such that only 31 total trials deaths occurred; despite this artificially meager sample, an estimate of up to a 91% reduction in the risk of death was found.[1]
Compared to the BIRD Review: Included 13 RCTs with 107 deaths observed and found a 2.5% mortality with ivermectin vs. 8.9% in controls; estimated reduction in risk of death=68%; highly statistically significant, (p=.007).
Assessment of Impacts on Viral Clearance
WHO Review: 6 RCTs, 625 patients. The Panel avoided mention of the important finding of a strong dose-response in regard to this outcome.
This action in (i) is indefensible given that their Unitaid research team found that among 13 RCTs, 10 of the 13 reported statistically significant reductions in time to viral clearance, with larger reductions with multiday dosing than single-day, consistent with a profound dose-response relationship.[2]
Adverse Effects
WHO: Only included 3 RCTs studying this outcome. Although no statistical significance was found, the slight imbalance in this limited sample allowed the panel to repeatedly document concerns for “harm” with ivermectin treatment.
Compare (a) to the WHO’s prior safety analysis in their 2018 Application for Inclusion of Ivermectin onto Essential Medicines List for Indication of Scabies:
“Over one billion doses have been given in large-scale prevention programs.”
“Adverse events associated with ivermectin treatment. are primarily minor and transient.”[3]
The WHO excluded all RCTs studying the prevention of COVID-19 with ivermectin, without supporting rationale. Three RCTs including almost 800 patients found an over 90% reduction in the risk of infection when ivermectin is taken preventively.[4]
The WHO excluded observational controlled trials (OCT), with 14 studies of ivermectin. These included thousands of patients, including those employing propensity matching, a technique shown to lead to similar accuracy as RCTs.
One large, propensity-matched OCT from the US found that ivermectin treatment was associated with a large decrease in mortality.
A summary analysis of the combined data from the 14 available ivermectin OCTs found a large and statistically significant decrease in mortality.
The WHO excluded numerous published and posted epidemiologic studies, despite requesting and receiving a presentation of the results from one leading epidemiologic research team. These studies found:
In numerous cities and regions with population-wide ivermectin distribution campaigns, large decreases in both excess deaths and COVID-19 case fatality rates were measured immediately following the campaigns.
Countries with pre-existing ivermectin prophylaxis campaigns against parasites demonstrate significantly lower COVID-19 case counts and deaths compared to neighboring countries without such campaigns.
Assessment of the Quality of the Evidence Base by WHO Guideline Group
The numerous above actions minimizing the extent of the evidence base were then compounded by the below efforts to minimize the quality of the evidence base:
The WHO mischaracterized the overall quality of the included trials as “low” to “very low,” conflicting with numerous independent expert research group findings:
An international expert guideline group independently reviewed the BIRD proceeding and instead found the overall quality of trials to be “moderate.”
The WHO’s own Unitaid systematic review team currently grade the overall quality as “moderate.”
The WHO graded the largest trial it included to support a negative assessment of ivermectin’s mortality impacts as “low risk of bias.” A large number of expert reviewers have graded that same trial as “high risk of bias,” detailed in an open letter signed by over 100 independent physicians.
We must emphasize this critical fact: If the WHO had more accurately assessed the quality of evidence as “moderate certainty,” consistent with the multiple independent research teams above, ivermectin would instead become the standard of care worldwide, similar to what occurred after the dexamethasone evidence finding decreased mortality was graded as moderate quality, which then led to its immediate global adoption in the treatment of moderate to severe COVID-19 in July of 2020.[5]
Further, The WHO’s own guideline protocol stipulates that quality assessments should beupgraded when there is the following:
a large magnitude of effect (despite their data estimating a survival benefit of 81%, the low number of studies and events included allowed them to dismiss this finding as “very low certainty”) or;
evidence of a dose-response relationship. The WHO shockingly omits the well-publicized reports by their Unitaid research team of a powerful dose-response relationship with viral clearance.
In sum, the WHO’s recommendation that “ivermectin not be used outside clinical trials” is based entirely upon:
the dismissal of large amounts of trial data;
the inaccurate downgrading of evidence quality; and
the deliberate omission of a dose-response relationship with viral clearance.
Consequently, these actions formed the basis of their ability to avoid a recommendation for immediate global use.
Even more surprising is that based on their “very low certainty” finding, the panel goes on to “infer” that “most patients would be reluctant to use a medication for which the evidence left high uncertainty regarding effects on outcomes they consider important.”
This statement is insupportable in light of the above actions. No patient could ever rationally consent to a trial in which they were acutely ill and would be subject to the possibility of receiving a placebo, once informed of: the large amount of relevant and positive trials that the WHO removed from consideration, their avoidance of reporting a large dose-response relationship, and their widely contradicted “very low certainty” grading of large mortality benefits. Such a trial would result in a historic ethical research violation, causing both a widespread loss of life and a resultant loss of trust in PHAs and research institutions for decades to come.
The many methods employed by the WHO to distort the evidence base and arrive at a non-recommendation are made even more suspicious and questionable by the following:
The WHO GDG did not hold a vote on the use of ivermectin. This highly irregular decision was purportedly based on the Ivermectin Panel’s “consensus on evidence certainty.”
Unitaid Sponsors allegedly inserted multiple limitations and weakened the conclusions in the preprint, systematic review manuscript by the Unitaid research team, which has recently led to formal charges of scientific misconduct.
BIRD: Approved ivermectin in March, 2021, for the prevention and treatment of COVID-19 based on 21 RCTs and 2,741 patients.
Conclusion
As expert clinician-researchers in society, we are firmly committed to ensuring that public health policy decisions derive from scientific data. Disturbingly, after extensive analysis of the recent WHO ivermectin guideline recommendation, we could not arrive at a credible scientific rationale to explain the numerous irregular, arbitrary, and inconsistent behaviors documented above. Further, after consultation with numerous physicians, guideline reviewers, legal experts, and veteran PHA scientists, we identified two major socio-political-economic forces that serve as the main barrier influences preventing ivermectin’s incorporation into public health policy in major parts of the world. They are:
1) the modern structure and function of what we will describe as “Big Science” and;
2) the presence of an active “Political-Economic Disinformation Campaign.”
“Big Science”
Also known as “Big RCT Fundamentalism,” Big Science reflects a dramatic shift in the practice of modern evidence-based medicine (EBM). Beginning before COVID, it has since rapidly evolved into the current system that more tightly meshes the entities of “Big Pharma,” “Big PHA’s/Academic Health Centers” (AMC), “Big Journals,” “Big Media,” and “Big Social Media” into the public health system’s efforts at guiding patient care, research and policy.
The structure and function of “Big Science” in COVID-19 is most simply represented as follows:
Only arbitrarily defined, “large, well-designed” RCTs (Big RCT), generally conducted on North American or European shores, can “prove” the efficacy of a medicine.
Only Big Pharma/Big PHA/AMCs have the resources/infrastructure to conduct Big-RCTs. (Many equate Big PHA/AMC with Big Pharma, given the funding source of the former.)
Only Big RCTs by Big Pharma or Big PHA/AMC can publish study findings in high-impact, high-income country medical journals (Big Journals).
Only medicines supported by Big Journal publications are deemed to have “sufficient evidence” and “proven efficacy” to then be recommended by Big PHAs.
Only medicines recommended by Big PHAs are covered by “Big Media” or escape censorship on “Big Social Media.”
Conversely, repurposed, off-patient medications such as ivermectin do not attract Big PHA or Big Pharma sponsors to conduct the mandatory Big RCT. Given this structural handicap, many effective medicines including ivermectin are consequently incapable of ever meeting Big PHA standards for approval in such a system. In the case of ivermectin, it is then considered, first by Big PHAs, then throughout Big Media and Big Social media, to be “unproven” given it lacks “sufficient evidence” and is thus heavily censored from public discussion and awareness. Mentions of ivermectin on Big Social Media led to the removal of a popular Facebook group (“Ivermectin MD Team” with over 10,000 followers). Additionally, all YouTube videos mentioning ivermectin in treatment of Covid-19 were removed or demonetized, as well as Twitter pages locked. Further, in Big Media, even the most credentialed independent and expert groups who recommend ivermectin based on a large body of irrefutable evidence are labeled as “controversial” and purveyors of “medical misinformation.”
A health system structured to function in this manner is clearly vulnerable to and overly influenced by entities with financial interests. Further, in Covid, such systems have evolved into rigidly operating via top-down edicts and widespread censoring. This allows little ability for emerging scientific developments not funded by Big Pharma to be disseminated from within the system or through media or social media until years later when, and if, a Big RCT is completed. This barrier has presented as an enduring horror throughout the pandemic given the widespread loss of life caused by the systematic withholding of numerous rapidly identified, safe and effective, repurposed medicines for fear of using “unproven therapies” without “sufficient evidence” for use. Alternatively, and for the first time in many physicians’ careers, those who seek to treat their patients with such therapies, based on their professional interpretation of the existing evidence are restricted by their employers issuing edicts “from above.” They are then forced to follow protocols that rely predominantly on pharmaceutically engineered therapeutics.
It must be recognized that distinct from “regulatory” agencies such as the FDA, whose system often relies upon the primary importance of a “Big RCT,” stronger foundations used by PHAs are available. One of the long-standing tenets of modern evidence-based medicine is that the highest form of medical evidence is a “systematic review and meta-analysis” of RCTs and not a sole Big RCT. Disturbingly, not one of the Big PHAs mention this established principle or their long-standing reliance on such evidence-based practices for issuing recommendations. In the case of ivermectin, they willfully ignore the multiple published expert meta-analyses of ivermectin RCTs, including almost two dozen trials and thousands of patients, reporting consistent reductions in mortality, time to clinical recovery, and time to viral clearance.
These improvements are found consistently and repeatedly, no matter the RCT design, size, or quality, and from varied centers and countries throughout the world. All studies were done without any identified conflict of interest with the vast majority of double-blind, single-blind, quasi-randomized, open-label, standard of care comparison, combination therapy comparisons, etc., reporting benefits. Satoshi Omura, Nobel Prize-winning discoverer of ivermectin, wrote in his team’s recent review paper that “the probability of this judgement on ivermectin’s superior clinical performance being false is estimated to be 1 in 4 trillion.” This supports our public warnings against further “placebo-controlled trials” given the near absolute certainty of harm to research subjects included in a placebo Big RCT.
Conversely, despite sitting atop the highest form of medical evidence, many non-regulatory Big PHAs around the world cry out for a Big RCT. This is while avoiding the issuance of even one of the several “weaker” recommendation options available to them in the setting of a low-cost, widely available medicine with an unparalleled safety profile and a constantly surging humanitarian crisis, even in the interim. Insufficient evidence, unproven — these are comments from WHO, NIH, Europe’s EMA, South Africa’s SAPHRA, France’s ANSM, United Kingdom’s MHRA, and Australia’s TGA.
Most disturbing to contemplate is our estimation that if the use of penicillin in bacterial infection were to have been tested in these same numbers and types of trials in the 1940s, the graphical display of benefits would look nearly identical to those found with ivermectin. Further, the U.S Cures Act of 2016, “specifically designed to accelerate and bring new innovations and advances faster and more efficiently to the patients who need them” emphasized the importance of using various forms of “real-world evidence” data to aid in regulatory decision-making. We can find no evidence of an organized effort to examine the more than 14, often large OCTs that show evidence of the substantial beneficial use of ivermectin. Further, no PHA has cited the numerous convincing epidemiological analyses that find rapidly falling case fatality rates following ivermectin distribution campaigns.
With the lack of a credible explanation for the absence of even a weak recommendation for ivermectin in the setting of widespread increased death rates from COVID-19, numerous citizens have speculated that this can only be explained by the presence of an active disinformation campaign by entities with nonscientific and largely financial objectives dependant on the non-recognition of ivermectin’s efficacy. We explore the near certainty of this occurring below.
Active Political-Economic “Disinformation” Campaign
“Disinformation” campaigns, best described in the article, “The Disinformation Playbook,” are initiated when independent science interferes with or opposes the interests of corporations or policymakers. Although thankfully rare, in certain cases these entities will actively seek to manipulate science and distort the truth about scientific findings that imperil their profit or policy objectives. First developed by the tobacco industry decades ago, these deceptive tactics include the following;
The Fake: Conduct counterfeit science and try to pass it off as legitimate research.
The Blitz: Harass scientists speaking out with results inconvenient for industry.
The Diversion: Manufacture uncertainty about science where little or none exists.
The Screen: Buy credibility through alliances with academia/professional societies.
The Fix: Manipulate government processes to influence policy inappropriately.
Numerous examples of the above disinformation tactics by corporations and policymakers, particularly within the pharmaceutical industry, have been documented:
Georgia Pacific publishing “fake science” on the dangers of asbestos (The Fake)
Most worrisome is that ivermectin appears to be up against one of the largest financial and global policy oppositions in modern history, including but not limited to:
Numerous Big Pharma companies and sovereign nations selling billions of vaccine doses.
Scale of market for vaccines now exponentially increasing due to the developing market for “booster shots” against rapidly appearing variants.
Concerns of numerous Big Pharma and Big PHA’s that if ivermectin is approved as effective treatment for COVID-19, EUAs for all vaccines would be revoked.
Disinformation: EMA erroneously claims effective concentrations are unattainable.
Numerous Big Pharma/Big PHA concerns that ivermectin’s potential as an alternative to vaccines may increase vaccine hesitancy and disrupt mass vaccination rollouts.
Opponents include large philanthropic sponsors with global vaccination goals.
Disinformation: WHO Panel does not review ivermectin prevention trials.
Numerous Big Pharma company investments in novel, engineered therapies (i.e., oral antivirals by Merck and Pfizer and Gilead) directly compete with ivermectin.
Disinformation: Merck places a post on their website, without scientific supporting evidence or named scientist authors that: “No evidence of either a mechanism of action, clinical efficacy or safety in COVID-19 exists.”
Big Pharma company’s (Astra-Zeneca) investment into a long-acting antibody product for prevention and treatment of COVID-19, which competes with ivermectin.
Big Pharma’s Remdesivir demand would rapidly decline once hospitalizations were to decrease after ivermectin approval.
Based on the lack of a rational explanation for the above actions by WHO, Merck, FDA, and Unitaid, we conclude that they result from an active disinformation campaign, executed both through the PHA’s, media and the WHO Guideline group recommendations. As highly published researchers, we find the allegations of scientific misconduct in the writing of the WHO/United research team’s meta-analysis manuscript to be deeply disturbing. It clearly represents a disinformation tactic with an intent to distort and diminish the reporting of a large magnitude benefit on mortality among many hundreds of patients. Further, Merck’s demonstrably and blatantly false statements against ivermectin deserve no further discussion. It is yet another entry into the disturbing historical record of actions committed by a Big Pharma entity with the primary intent of protecting profit at the expense of the welfare of global citizens.
For These Compelling and Irrefutable Reasons, The FLCCC Makes a Call to Action
This call to action is no longer just to health authorities, but to citizens everywhere to fight back against these disinformation tactics. We find the advice of the Union of Concerned Scientists (UCS) to be an excellent guide to action in this regard:
Global Citizens
Share the playbook with your social media networks when you see new examples like those outlined above.
Set the record straight. When you see someone spreading disinformation on a topic, counter it. There are millions around the world who either have studied the data or have experience with the potent efficacy of ivermectin in COVID-19. It is important to correct false assertions.
Consider divesting your retirement funds and other investments from companies engaging in disinformation.
If a governmental or NGO scientist, report actions that diminish their role in policymaking.
Media
Avoid false equivalencies that distort scientific consensus.
Correct the record when scientific information is misrepresented, particularly by Big PHA/Big Pharma.
Report abuses of science in government.
As an expert group of ivermectin researchers, we are unsure of what else to offer in order to correct or counteract this misrepresentation of an important drug. Our belief is that, of the above actions, the most effective counter to the disinformation campaign would be that a whistleblower become active from within WHO, the FDA, the NIH, Merck, or Unitaid. This moment in history demands a man or woman with the courage and conviction to step forward. Urgently.
In both the interests of humanity and to motivate and inspire such a citizen of the world, we leave you with the words of Albert Einstein: “The world will not be destroyed by those who do evil, but by those who watch them and do nothing.”
[1]Special emphasis must be placed on this decision; selecting only trials where very few deaths occurred.
(n.b., the number of events observed within trials is a primary criterion for judging the “certainty of evidence”). This action provides almost the entire basis for the panel’s assessment of a “very low certainty of evidence.” It is in effect, a “smoking gun,” one of the many actions above demonstrating that the primary objective of the Panel was to recommend against use of ivermectin. [2]This omission is the second most important action allowing the panel to find a “very low certainty of evidence,” given that, per WHO protocol, if a dose-response relationship is found, the certainty of evidence must be upgraded. [3]Special emphasis must be placed on the harm of excluding trials data supporting ivermectin in the prevention of COVID-19. If the preventive efficacy of ivermectin were to be known or accepted, this would allow deployment in regions without vaccines.
[4]British Ivermectin Recommendation Development (BIRD) panel (2021). The BIRD Recommendation on the Use of Ivermectin for COVID-19. Full report. https://tinyurl.com/u27ea3y
[5]The FLCCC Alliance recommended, as well as gave U.S. Senate testimony in support of, the use of corticosteroids in COVID-19 months before this announcement, during the prolonged period when all PHAs recommended against its use
Sincerely,
The Front Line COVID-19 Critical Care Alliance
Pierre Kory, MD
Keith Berkowitz, MD
Paul E. Marik, MD
Fred Wagshul, MD
Umberto Meduri, MD
Scott Mitchell, MBChB
Joseph Varon, MD
Eivind Vinjevoll, MD
Jose Iglesias, DO
A Whitehall source directly linked to the Covid Response has said that the UK Government have already structured a detailed plan designed to neutralise each stage of lockdown easing, including the compliance of media outlets to help spread fear.
The Whitehall source has said that he has been “increasingly concerned” with how the Government are behaving, and that their “relationship with the truth” is now not even on nodding terms. The latest plan will involve a series of ‘crisis’ around drug supply; mutant strains; and third waves, specifically choreographed to condition the public for further lockdowns and vaccine passports.
The plan, that according to the source is designed to take us to September 27th 2021 is to be released in stages over the summer months and, according to the Whitehall source, is already ‘well underway’.
On March the 8th, the first milestone of the roadmap was implemented, with school children finally returning to class. The following day Chris Whitty gave a pre-written speech to the Commons that said schools reopening would cause another surge in the virus and ended it with “Let me be clear, many, many more people will die before this is over” the soundbite obligingly repeated on every news outlet, with BBC news having it on-loop all day.
On March the 29th, the second milestone of the roadmap was implemented. The Government said – “The evidence shows that it is safer for people to meet outdoors rather than indoors,”. This is why from the 29th March, when most schools start to break up for the Easter holidays, outdoor gatherings (including in private gardens) of either 6 people (the Rule of 6) or 2 households will also be allowed, making it easier for friends and families to meet outside.
The next day (March 30th) the AstraZeneca Vaccine was again stopped due to blood clots fears, despite the medicine’s regulator clearing it only the previous week. Whilst Boris Johnson repeated what he’d said the previous week that the mutated virus on the continent would inevitably “wash up on our shores”.
On April 19th, the third milestone saw pub gardens, and non-essential shops reopen. Followed immediately by news of a second vaccine being halted for fear it was causing blood clots and the discovery of the South African mutation said to be able to avoid them anyway.
The next milestone is due on May 17th with the Government relaxing social contact rules further and the opening of indoor venues. This will be followed by a story that the mutation is ‘more deadly than first thought’ and that young people are now also vulnerable to it, accompanied by the result of the vaccine passport trials have shown that they have a ‘positive effect on virus reduction’.
The final milestone is due on June 21st where ALL restrictions were promised to be lifted. This will not be allowed to happen. Vaccine passports / Track and Trace will be mandatory, as will masks and social distancing. The entire week of the 21st will be taken up by a third wave, which will suddenly be ‘rampant’, and this will be attributed to a new variant which they will declare is more deadly than the previous strains of Covid allegedly doing the rounds. This will be accompanied with yet more issues with vaccine supplies. Authorities will declare that one of the vaccines is effective against the deadlier strain, but a ‘problem’ with its manufacture will emerge.
The Whitehall source went on to say –
“All the measures are aimed at two things, vaccine passports and lockdowns starting next winter,
“The ultimate goal is to have the public, back in their box.
“Note that Boris is now talking down vaccine’s and bigging-up lockdowns, that wasn’t a mistake, that was all part of the plan”.
The plan also includes an ad campaign like the one seen at Christmas, the message this time will be that the pandemic isn’t over and vaccine passports are the ‘solution’.
By Jamal Kanj – Intifada-Palestine.com – January 14, 2011
Israel’s survival kit is: perpetuate conflict, insecurity to rationalize collective hate and finally playing victim.
Devoid of conflict, Israel implodes internally; without hate, Zionism loses its justification; and playing eternal victim to continue blackmailing the West. Absence of this holy trinity, Israel ceases to exist.
From its inception, the house of Zion has mastered exploiting adversarial powers to advance Israel’s cause. For instance, their influence over the Democratic Party in the US began with President Truman’s bid for 2nd term election in 1948.
Responding to strong opposition from Secretary of State General George Marshall and Department experts urging against recognition of Israel, President Truman replied: “I’m sorry gentlemen but I have to answer to hundreds of thousands [Jewish voters] who are anxious for the success of Zionism. I do not have hundreds of thousands of [voting] Arabs among my constituents”
Zionists influence over liberal American politics was matched with the doctrinal school of Conservative theoreticians aligning the Republican Party’s platform with Israel’s objectives. The Neoconservative Zionists, coined Zioncons, invented the “Clash of Civilization” concept to fight Israel’s wars. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.



 Aletho News

