The US Centers for Disease Control and Prevention (CDC) spent hundreds of thousands of dollars to buy people’s data from third party companies – SafeGraph and Cuebiq – who are in the business of tracking physical locations.
The CDC did this in a bid to check how citizens were complying with lockdown and other Covid restrictions, reports The Epoch Times, which has had access to the contracts between the parties.
One of these companies received $420,000, while the other deal was worth $208,000. The CDC was allowed to buy this data thanks to emergency rules enacted because of the pandemic.
They were designed to give the government organization the data it deemed necessary in order to properly react.
This included tracking people for the sake of “evaluating the impact of visits to key points of interest, stay at home orders, closures, re-openings and other public health communications related to mask mandate, and other emerging research areas on community transmission of SARS-CoV-2.”
The data SafeGraph and Cuebiq are able to get hold of and sell on comes from apps installed on phones. In SafeGraph’s case, this information covered points like neighborhood patterns – revealing the frequency at which somebody visited a place “of interest,” as well as where they came to that place from, and where they went from there.
Cuebiq, meanwhile, sold its shelter-in-place index dataset, and that reveals for how long a phone is inside a house, expressed in percentages, as well as the time people would spend in another state. The goal was to assess who was “sheltering in place” as the authorities had mandated.
The contracts were signed only in 2021 but the CDC at first, early into the pandemic, got a taste of the two companies’ location data offer for free.
The organization was not shy about it at the time, either, and in 2020, used the data to produce two studies, covering metropolitan areas in the US. The subject was how often the people tracked were moving around if distancing restrictions were in place – the result was, less often.
The same is true of movement during radical lockdown measures, and US taxpayers also footed the bill that allowed the CDC to come up with this “revolutionary” result: once states started lifting these measures, people started to move around more frequently.
I am frequently asked: why are the government agencies still pushing COVID-19 vaccination after there have been calls in the US Senate and all around the world to pull them off the market for lack of safety and efficacy?
In a March 10, 2023 letter from FDA Commissioner Robert Califf, MD, and CDC Director Rochelle Walensky, MD, MPH, to Florida Surgeon General Joseph Ladapo, MD, PhD, the agencies give their rationale. While Walensky does not have a compelling academic track record, her FDA counterpart Califf has been considered a staunch advocate of randomized trials and a hawk on safety of cardiovascular drugs over his career which was notable for building the Duke Clinical Research Institute, one of the most impressive academic research organizations in the world.
Here are 10 assertions that Califf and Walensky make to Ladapo and Americans on why the COVID-19 vaccines should be “pushed.”
“The claim that the increase of VAERS reports of life-threatening conditions reported from Florida and elsewhere represents an increase of risk caused by the COVID-19 vaccines is incorrect, misleading and could be harmful to the American public.” They are assuming unproven benefit at the start. The Bradford Hill criteria have been applied to VAERS and causality has been met. Autopsy studies have conclusively demonstrated causality for fatal syndromes. Doctors use the VAERS system when they believe COVID-19 vaccines caused the death, NOT when the death is unrelated to the vaccine in practice.
“The FDA-approved and FDA-authorized COVID-19 vaccines have met FDA’s rigorous scientific and regulatory standards for safety and effectiveness and these vaccines continue to be recommended for use by CDC for all people six months of age and older.” The FDA has relied on the false surrogate of antibody elevations after injection eight times. This is neither rigorous nor valid. Large randomized, double blind placebo controlled trials with hospitalization/death as the primary endpoint are required to prove efficacy in all age groups.
“Despite increased reports of these events, when the concern was examined in detail by cardiovascular experts, the risk of stroke and heart attack was actually lower in people who had been vaccinated, not higher.” They cite a nonrandomized study with inadequate control for the known determinants of cardiovascular disease. Both selection bias and confounding eliminate any valid claims of benefit. There is no mechanism by which COVID-19 vaccination would reduce cardiovascular events. There are >200 published manuscripts on COVID-19 vaccines mechanistically causing cardiovascular events including myocarditis, accelerated atherosclerotic cardiovascular disease, aortic dissection, hypertensive crisis, etc.
“FDA and CDC physicians continuously screen and analyze VAERS data for possible safety concerns related to the COVID-19 vaccines. For signals identified in VAERS, physicians from FDA and CDC screen individual reports, inclusive of comprehensive medical record review. Most reports do not represent adverse events caused by the vaccine and instead represent a pre-existing condition that preceded vaccination or an underlying medical condition that precipitated the event.” The agencies have not produced a report giving their analysis of what caused death after vaccination. Since many deaths occur on the day of the shot or in the next few days that follow, the public deserves to see regulatory evidence for cause of death.
“In addition to VAERS, FDA and CDC utilize complementary active surveillance systems to monitor the safety of COVID-19 vaccines.” CDC V-safe is one of the active systems mentioned. The CDC refused to release to the public until ordered by the courts, demonstrated an unacceptable 7-8% rate of hospitalization, emergency care, or urgent office visit caused by vaccine side effects. So agency use of systems demonstrate lack of safety and are not reassuring to the public.
“Based on available information for the COVID-19 vaccines that are authorized or approved in the United States, the known and potential benefits of these vaccines clearly outweigh their known and potential risks. Additionally, not only is there no evidence of increased risk of death following mRNA vaccines, but available data have shown quite the opposite: that being up to date on vaccinations saves lives compared to individuals who did not get vaccinated.” There are no randomized placebo controlled trials demonstrating hospitalization/death are reduced as primary endpoints. Thus the agencies cannot make an efficacy claim from a regulatory perspective. Nonrandomized studies have the following threats to validity: 1) selection bias—healthier more health conscious people take vaccines, 2) vaccinated are more likely to seek early treatment which reduces hospitalization/death, 3) no control over prior COVID-19 infection which greatly influences risk of hospitalization/death, 4) no adjudication of COVID-19 endpoints.
“Another study using mathematical modeling estimated that the vaccines saved an estimated 14 million lives from COVID-19 in 185 countries and territories between December 8, 2020, and December 8, 2021.” Modeling studies start with the unproven assertion that vaccination reduces death which has not been demonstrated in proper randomized trials, hence extrapolations to large populations are invalid.
“The most recent estimate is that those who are up to date on their vaccination status have a 9.8 fold lower risk of dying from COVID-19 than those who are unvaccinated and 2.4 fold lower risk of dying from Covid-19 than those who were vaccinated but had not received the updated, bivalent vaccine. Roughly 90% of deaths from COVID-19, as carefully classified by the CDC, in recent months have occurred among those who were not up to date on their vaccines.” This estimate did not account for the two known determinants of COVID-19 mortality: early treatment and natural immunity.
“Over the course of the pandemic, FDA and CDC have held numerous public meetings to discuss the safety and effectiveness of the COVID-19 vaccines where detailed safety data are shared with outside experts and public comment is encouraged. Further, FDA publishes the full regulatory action package containing hundreds of pages summarizing clinical studies and review for each COVID-19 approval on FDA’s website (see “COVID-19 Vaccines Authorized for Emergency Use or FDA Approved”) and CDC publishes an extensive amount of information on their clinical use in Interim Clinical Considerations. Complete information about both benefits and risks helps health care providers better care for their patients.” The FDA/CDC have never reviewed or commented on the Pfizer 90-day post-marketing data which reported 1223 deaths shortly after the shot. The FDA attempted to block these data to the public for 55 years. The agencies have never conducted a symposium to review the >1000 peer-reviewed published papers on serious adverse events and death after COVID-19 vaccination.
“Unfortunately, the misinformation about COVID-19 vaccine safety has caused some Americans to avoid getting the vaccines they need to be up to date.” The Rasmussen Report indicates 28% of Americans know someone who has died after the vaccine. Nothing in that report suggested “misinformation” was leading to hesitancy, moreover it was word of mouth on the horrifying outcomes Americans are witnessing among their family and friends that is leading to refusal rates of boosters.
There are easily another ten invalid assertions made by the agency that could be handled by experienced clinical investigators. Take a look at the letter yourself. Keep in mind the FDA/CDC deceived America by asserting that SARS-CoV-2 did not come out of the Wuhan Laboratory and just a few days ago the US House of Representatives voted to declassify our documents from the laboratory after multiple agencies and witnesses capitulated on the lab origin. This casts doubts on truthfulness of any agency public health assertions during the crisis.
The important message to Americans is that our agencies have no intention of carefully considering vaccine safety or changing course on their relentless pursuit of frequent, mass, indiscriminate COVID-19 vaccination down to 6-month old babies. It will be up to you to protect yourself and your family.
After ICAN obtained the v-safe data and published to the world that 7.7% of v-safe users sought medical care (and that the CDC hid this number from the public for two years), Reuters reached out to my firm stating it had received comment from the CDC regarding this figure.
Incredibly, CDC told Reuters that the 7.7% figure was grossly inflated because it claimed there were 10 million records in v-safe, not 10 million users. Here is the exact email I received from Reuters:
“CDC says v-safe has 10 million records, not 10 million users, and that one person could submit multiple records of seeking medical care for the same adverse event. Which makes the 7.7% statistic problematic… Is that something ICAN was aware of or able to adjust for?”
Based on the CDC’s claim, the major news outlet asked if ICAN would be modifying its claim of 7.7%. But it was the CDC’s claim that was categorically false!
ICAN was correct: there were 10 million v-safe users, not 10 million records; and the 7.7% also did not double-count because it was the number of unique v-users who submitted one or more reports of seeking medical care.
The CDC was plainly pushing the major news to declare ICAN’s claim false and, hence, characterize it as misinformation.
Had Reuters just accepted the CDC’s claim, as typically occurs, it likely would have published a story declaring ICAN’s 7.7% figure to be false information.
Luckily, to its credit and because one of its reporters proceeded objectively and with integrity, this news outlet did not just take the CDC’s word for its claim. It actually gave us an opportunity to respond to this claim. (Albeit not by asking if ICAN believed it was wrong but by asking if it would adjust the figure it published.)
CDC Proven Wrong
Showing that the CDC was wrong was simple. All we had to do was use the CDC’s own data it provided to ICAN!
The data the CDC provided to ICAN clearly and without any doubt showed that ICAN was using the precise and correct number of v-safe users and the number of unique v-safe users who reported needing medical care. Meaning, the 7.7% was absolutely accurate – without any doubt.
We sent this proof and asked Reuters to please ask that CDC substantiate with actual proof, not just conclusory assertions, how ICAN was supposedly wrong and spreading misinformation. And again, to Reuter’s credit, because it demanded proof from the CDC, the CDC eventually relented!
The CDC finally conceded that v-safe did in fact have approximately 10 million users and, hence, the 7.7% figure of those who reported seeking medical care was accurate.
With that, I expected that interaction would be one heck of a story in and of itself! I foresaw a Reuters story that disclosed this CDC behavior – here was the CDC trying to get a major news outlet to publish false information! It was trying to get it to write that the 7.7% figure was incorrect.
That should have been its own major story. And although Reuters did publish a story about v-safe, thus far, these behind-the-scenes communications have not been published. I expect they never will, other than in this article.
CDC Asks Reuters to Ask ICAN for a Copy of CDC’s V-Safe Data
It gets even worse. Making plain that the CDC officials communicating with Reuters were not concerned about the facts, and instead were focused solely on pushing their “safe and effective” mantra which is typically not questioned, they further revealed the agency’s disfunction: the CDC officials asked Reuters if it could get a copy of the v-safe data from ICAN and send it back to the CDC representatives Reuters were dealing with so they can review that data. If that sounds nutty, it is because it is.
Just so you don’t think you misread the foregoing, let me repeat: CDC asked Reuters to get the v-safe data that CDC had given to ICAN days before, and then send that data back to the CDC to review.
You can’t make this stuff up. Mind you, the data had already all been made public on ICAN’s website.
What this shows is that these CDC officials were driving forward to push a major news outlet to claim to the world that ICAN’s claim of 7.7% was false without actually looking at the data to assure their claim was accurate. It also shows an incredible level of disfunction at the CDC; instead of getting the data internally, they had to ask a news outlet to get its own data produced to ICAN to then send it back to CDC.
And these are the folk that have effectively dictated what level of civil and individual rights most Americans would have over the last three years!
CDC Seeks to Deceive Again
When the foregoing gambit by the CDC did not work, it had a new gambit. It tried to get Reuters to publish that the 7.7% figure was misleading by claiming to Reuters that “[i]n the first week after vaccination, reports of seeking any medical care … range from 1-3% (depending on vaccine, age group and dose).”
But as we explained to Reuters, even this is not true. For example, 3.36% of those younger than 3 years old reported receiving medical care within one week of receiving the Moderna vaccine.
Even if all combinations of vaccine, age group, and dose resulted in between 1% to 3% of infants, children, or adults seeking medical care within one week, that is not necessarily an insignificant figure! Why is this somehow comforting? Especially in the context of vaccinating the entire country.
And why should the reports of medical care on days 14 or 21 or 28 be ignored? Is it because the CDC thought it was not relevant information? And, if so, why in the world ask v-safe users to submit this information on these days? Or is it because the CDC did not like what the numbers showed? I will let you be the judge.
As noted above, and a sad irony, when medical care is sought during the first seven days, the CDC presumably attributes that to expected reactogenicity and tells the public to not be concerned. And if it occurs beyond seven days, it pretends as if that data does not exist – even though harms from COVID-19 vaccines, as the CDC well knows, can occur well after the first seven days, as discussed in depth in part 7 of this v-safe substack series.
Also, here, we are talking about a novel medical product, hence heightening the need for assessing its long-term safety – certainly beyond 7 days post-vaccination.
This shows how the sausage is made in mainstream media. But for the actual tenacity – I would even say courageous – pushback from a Reuters reporter, the story around ICAN’s v-safe claims could have ended very differently.
The real story I can only imagine this reporter would have liked to publish, the one I told above, however, would no doubt be a step too far for Reuters as an organization – at least for now, until brave journalists become the typical journalist.
It can be difficult to keep up with the CDC’s ever-changing COVID-19 booster recommendations, but what is consistent is that the number and frequency of boosters are continually increasing and data supporting these recommendations keeps decreasing. At one point, even mainstream media called out the CDC for the lack of data for these recommendations.
To pin down the CDC on one of its recommendations, in April 2022, ICAN asked the CDC to produce its data that support the efficacy of COVID-19 boosters for 12-49 year olds. The response? Shocking.
The CDC admitted that “A search of our records failed to reveal any documents pertaining to your request.” None. Not one record. Not one study. This means the CDC did not have any data to back up its claims or recommendations for boosters in this age group.
For anyone that has looked at the data regarding boosters, the CDC’s response is unsurprising because study after study shows that repeated boosters increase the chances of contracting COVID-19 disease. For example, as a recent Cleveland Clinic study showed (see Figure 2 in the study), the chances of contracting COVID-19 increase with each additional dose of COVID-19 vaccine.
The above is another piece of evidence in ICAN’s snowballing work to hold our “health” agencies accountable for every unsupported recommendation and false claim made to the public.
See below for more instances where ICAN uncovered “health” agencies making unsupported claims to the public:
Substack All-Star Igor Chudov just published another important article. This article asks if the CDC was lying all along about “vaccine effectiveness?”
My question (and it’s a serious one) is this: Can someone name ONE pronouncement of CDC officials that either wasn’t a lie or of highly-dubious veracity?
Partial List of Lies …
Per my assessment, the CDC and other national public health agencies and their key experts …
Lied about there being no evidence of early cases in America.
Lied when they said there was no possibility this virus leaked from a lab.
Lied about the effectiveness of masks.
Lied when they said the virus could be spread on physical surfaces.
Lied when they said it would take only two weeks to “flatten the curve.”
Lied when they said that virus transmission could easily happen outside.
Lied about the stats of “cases” and “deaths.”
Lied about the mortality risk to children and healthy young adults.
Lied about ivermectin and HCQ being worthless drugs for treatment.
Lied about remdesivir being a safe drug.
Lied about the vaccines being “safe and effective.”
Lied when they labeled these shots as “vaccines.”
Lied about the “vaccines” and boosters preventing “severe” cases and deaths.
Lied about the necessity or importance of testing people (including the asymptomatic) over and over.
Lied when they attacked and sought to censor people who were telling the truth.
Lied when they “adjusted” estimates of ILI in the Flu Season of 2019-2020 … to make it seem this flu season did not produce “widespread” and “severe” ILI (Covid?) outbreaks.
Before Covid, lied about the effectiveness of the flu vaccines.
A few other questions …
Do liars continue to lie? Will liars lie again?
Do liars often try to cover-up their lies?
Do liars in positions of great power often attack people who try to expose their lies?
Is it smart to continue to trust proven or known liars?
How many lies does some person or agency have to tell before people start to realize they are listening to a liar?
Eight leading critics of the United States’s COVID-19 response have called for an investigation of the many failures of policy architects and key decision makers — at institutions ranging from the Centers for Disease Control and Prevention and Food and Drug Administration to universities and hospitals — over their repeated mishandling of the pandemic.
Given the immense harm inflicted on our society by the follies of a ruling class and their expert advisers who never failed to make a wrong decision when presented with the opportunity, as well as the fact that lives are still being destroyed by their lingering policies, we can only hope this blueprint does not go ignored.
Dubbing themselves the “Norfolk Group,” the association of scholars includes such prominent names as Stanford epidemiologist Jay Bhattacharya, Harvard epidemiologist Martin Kulldorff, UCSF physician Tracy Beth Høeg, Johns Hopkins University surgeon Marty Makary, and Indiana University School of Medicine immunologist Steven Templeton.
According to the Norfolk Group’s website, although initially organized by the Brownstone Institute in May 2022, the eight members of the group have since worked free from outside influence to draft the 80-page document they published earlier this year, “Questions for a COVID-19 Commission.”
Presented as a series of summaries and questions pertaining to key elements of U.S. COVID policy, the document, in effect, lays out a thorough indictment of the consistent incompetence of our ruling class while also raising concerns over the possible influence on policy by special interests such as teachers unions and drug companies.
Regarding natural immunity, the authors ask, “Why did the CDC downplay infection-acquired immunity, despite robust evidence for it?”
In respect to school closures, they ask, “Why were schools and universities closed despite early evidence about the enormous age-gradient in COVID-19 mortality … and early evidence that school closures would cause enormous collateral damage to the education and mental health of children and young adults?”
On that matter, they also wonder, “Why did the CDC incorporate policy language proposed by leaders of teachers unions on the scientific and public health aspects of school reopening without soliciting expertise of outside scientists in public health, infectious diseases, or other related fields?”
When discussing lockdowns, they inquire, “Why was so much influence on public health policy accorded to Drs. [Francis] Collins and [Anthony] Fauci? They control the largest source of infectious disease research funding in the world. How many infectious disease scientists, who should have been strong voices during the pandemic, kept quiet for fear of losing the research funding on which their livelihood depends?”
In their section on epidemiologic modeling, they demand, “Why did world leaders overly rely on models that made unverified assumptions about the pandemic’s trajectory rather than trying to verify these assumptions and their implications?”
When addressing COVID-19 vaccines, they raise questions such as, “Why did many organizations continue with mandates through summer and fall of 2021, despite data demonstrating both waning efficacy of symptomatic infection and reduced long term ability to curb viral spread?”
Regarding masks, they state, “Prior to the COVID-19 pandemic, the evidence that masks did little if anything to stop the spread of respiratory viruses was uncontroversial,” before summarizing a few studies demonstrating this and asking the obvious: “[W]hy did public health officials and agencies promote the idea that masks would be effective against SARS-CoV2?”
In its entirety, the Norfolk Group’s “Questions for a COVID-19 Commission” serves as a blueprint for the kind of investigation our country needs. Just don’t expect the Biden administration to do anything about it.
Daniel Nuccio holds master’s degrees in both psychology and biology. Currently, he is pursuing a PhD in biology at Northern Illinois University studying host-microbe relationships. He is also a regular contributor to The College Fix where he writes about COVID, mental health, and other topics.
Pfizer missed a deadline to turn over internal studies on myocarditis, per an FDA order. The deadline came and went. Now, they quietly have a new date in June. Why the delay on such important data? And, why does the FDA set arbitrary deadlines which aren’t enforced?
As Biden announces the coming end of the Covid Public Health Emergency in the US, the new majority in Congress appear to not be letting agencies off the hook. The past three years of remarkably poor public health policy have placed the CDC, WHO, and Social Media companies in the sights of numerous committee investigations, and new legislation seeking answers and medical freedom.
Airline pilot and co-founder of US Freedom Flyers, Josh Yoder, and Clinical Cardiologist, Dr. Thomas Levy, join Del to discuss the recent FAA change to the heart test limits and the coincidental timing of the change coming amid increasing concerns over myocarditis from the COVID-19 vaccine.
The CDC’s information page on Covid-19 vaccines contains the following bullet points on “How mRNA COVID-19 vaccines work:”
First, mRNA COVID-19 vaccines are given in the upper arm muscle or upper thigh, depending on the age of who is getting vaccinated.
After vaccination, the mRNA will enter the muscle cells. Once inside, they use the cells’ machinery to produce a harmless piece of what is called the spike protein…. After the protein piece is made, our cells break down the mRNA and remove it, leaving the body as waste.
Or, in other words, as we have long been told, “it” – the mRNA – “stays in the arm.” And then, after having instructed the muscle cells to produce the spike, is disposed of.
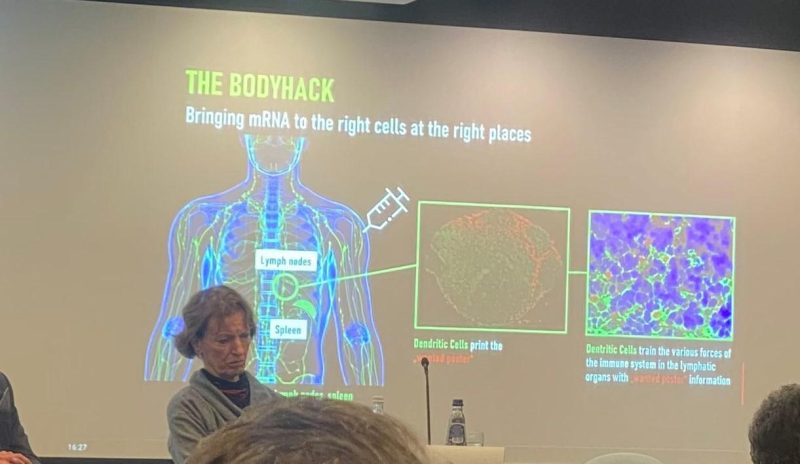
But look at the below picture from a recent presentation on mRNA vaccination at the European Parliament. The picture was posted on Twitter by Virginie Joron, a French member of the parliament. The speaker is no less an authority than Özlem Türeci, the Chief Medical Officer of BioNTech: the German biotech company that developed what has come to be known to most of the world as the “Pfizer” Covid-19 vaccine.
Have a closer look at Türeci’s slide, which tells a very different story than that which the CDC has been telling Americans for the last two years.
Far from “staying in the arm” and entering the muscle cells at the injection site, the injection site is only the point of departure for a journey that is supposed to take the mRNA rather to the lymph nodes. The subtitle of the slide is “Bringing mRNA to the right cells at the right places.” The deltoid is not the right place; the lymph nodes are.
Once in the lymph nodes, a specific sort of cell, the dendritic cells, is supposed to manufacture the spike protein: here colorfully described as the “wanted poster” that will help the immune system to identify the SARS-CoV-2 virus in case of subsequent exposure.
A passage from The Vaccine, the book that Türeci and her husband, BioNTech CEO Ugur Sahin, wrote which journalist Joe Miller, explains why BioNTech’s platform specifically targets the lymph nodes:
What Ugur learnt was that the location to which a vaccine delivers its ‘wanted poster’ really mattered. The reason for this, the couple’s team in Mainz later realised, was that not all dendritic cells … were created equal. The ones that resided in lymph nodes – of which the spleen is the largest – were particularly adept at capturing mRNA and making sure the instructions it carried were acted upon. These kidney-bean shaped organs, found under our armpits, in our groins, and at several other outposts in the body, are the information hubs of the immune system. (p. 98)
Indeed, Sahin and Türeci were so determined to get their mRNA into the lymph nodes that they had an earlier mRNA construct injected directly into the patient’s lymph nodesin the groin (p. 104).
Needless to say, such an approach was not likely to obtain wide acceptance as a vaccine! This is why the couple, as explained in their book, needed to package the mRNA in lipid nanoparticles, in order to ensure that mRNA administered by way of an intramuscular injection would, nonetheless, be widely distributed around the body and thus reach the lymph nodes.
This is to say that the wide biodistribution of the mRNA that came to light after rollout was never a bug. It is a feature of BioNTech’s mRNA technology. Having elicited an immune response by way of injection into the groin, Sahin is even said to have wondered, “How substantial could the immune response be if a vaccine got into all lymphatic tissues around the body, and recruited all the resident DCs [dendritic cells] into action?” (p. 105)
So, why has the CDC been lying about this for the last two years and insisting that the mRNA “stays in the arm?” Well, the obvious answer is that the idea of the mRNA staying at the injection site is reassuring, since otherwise we could fear systemic adverse effects of precisely the sort that have emerged since rollout.
It is worth noting, moreover, that in developing its vaccine, as discussed in my earlier article here, BioNTech simply skipped the so-called safety pharmacology studies whose purpose is precisely to test a candidate vaccine for potential systemic adverse effects – and regulators, including the FDA, let the company do it.
Robert Kogon is a pen name for a widely-published financial journalist, a translator, and researcher working in Europe.Follow him at Twitter here. He writes at edv1694.substack.com.
The Centers for Disease Control and Prevention (CDC) on Thursday added COVID-19 vaccination to its routine immunization schedule for children and adults.
Although the CDC does not have the authority to set requirements itself, the agency’s immunization schedule provides formal guidance for state and local public health officials who set the rules for which vaccines are required to attend school.
The schedule also is the basis for vaccine recommendations made by most physicians.
“Given all that we have learned about the dangers and ineffectiveness of COVID-19 shots over the last two years, it is horrifying to see the CDC now recommend this as a routine shot to children,” Mary Holland, Children’s Health Defense (CHD) president and general counsel told The Defender.
“Although it is unsurprising given the agency capture, it is nonetheless tragic,” she added.
Under the new guidelines, the CDC recommends healthy children 6 months to 11 years old receive a primary series of two doses of the mRNA Moderna or Pfizer-BioNTech monovalent COVID-19 vaccine, followed by a booster of the bivalent shot.
It recommends that healthy people age 12 and older receive two doses of either the Moderna, Pfizer or Novavax vaccine followed by a bivalent booster.
All COVID-19 vaccines being administered in the U.S. to people under 18 are Emergency Use Authorized (EUA) products. The U.S. Food and Drug Administration (FDA) did grant full approval to Pfizer’s Comirnaty COVID-19 vaccine for ages 12 and older, however, the Comirnaty vaccine is not available in the U.S. — which means all children who get the Pfizer vaccine are getting an EUA product.
In Wednesday’s congressional hearing on the Biden administration’s response to COVID-19, Rep. Dan Crenshaw (R-Texas) asked CDC Director Dr. Rochelle Walensky, why the CDC broke with its own norms and put an EUA vaccine on the childhood immunization schedule for a disease that poses very little risk to children and for which the vaccine poses many potential side effects without preventing transmission.
Walensky responded:
“The reason that the ACIP [Advisory Committee on Immunization Practices] recommended the CDC put the COVID-19 vaccine on the pediatric schedule was only because it was the only way it could be covered in our ‘Vaccines for Children’ program.
“It was the only way that our under-uninsured children would be able to have access to the vaccines … That was the reason to put it there.”
Data collected by the CDC through its Vaccine Adverse Event Reporting System (VAERS) and a growing number of other sources indicate serious health risks associated with COVID-19 vaccination for children.
“The COVID vaccines have not been shown to be either effective or safe for children,” CHD argued in an amicus brief filed in Louisiana last year. “The benefits to children are minuscule, while the risks — including the risk of potentially fatal heart damage — are ‘known’ and ‘serious,’ as the FDA itself has acknowledged.”
Other changes to the childhood schedule include adding the PVC15 shot, a pneumococcal conjugate vaccine used to help protect against pneumococcal bacteria and only recently approved for children; updated guidance for the flu and hepatitis B vaccines; and new recommendations for the measles, mumps and rubella (MMR) and polio vaccines.
The CDC now recommends an additional dose of the MMR vaccine in places where there is a mumps outbreak. It also recommends an additional poliovirus vaccine for children and adults if new polio cases emerge.
This would mean the childhood vaccination schedule would increase the number of recommended injections from 54 to 72 over the course of a person’s childhood, between the ages of 6 months and 18 years, The Defender reported last year.
CDC schedule protects pharmaceutical companies from liability for vaccine injuries
Vaccine makers are not liable for injuries or deaths associated with EUA vaccines but can be held liable for injuries caused by a fully licensed vaccine — unless that vaccine is added to the CDC’s childhood vaccination schedule.
Parents of children injured by vaccines listed on the childhood schedule can seek compensation through the taxpayer-funded National Vaccine Injury Compensation Program (NVICP), a no-fault alternative to the traditional legal system for resolving vaccine injury claims.
However, the revisions voted on by the ACIP committee last year explicitly state (slide 24) that the pneumococcal polysaccharide vaccine (PPSV23) and COVID-19 vaccines are not covered under the NVICP.
Instead, the COVID-19 vaccines added to the childhood schedule will remain covered by the Countermeasures Injury Compensation Program (CICP). To date, only 19 claims related to COVID-19 filed with the CICP have been found eligible for compensation, though no compensation has yet been paid.
Since it was established in 2010, the CICP only compensated 30 of the nearly 12,000 claims filed.
Are we seeing ‘the beginning of the end of Big Pharma’s reign’?
The addition of the COVID-19 vaccine to the immunization schedule “helps ‘normalize’ this vaccine and sends a powerful message to both healthcare providers and the general public that everyone ages 6 months and older should stay up to date with recommended COVID-19 vaccines (including a booster, when eligible), just as they would with any other routinely recommended vaccine,” Dr. Neil Murthy and Dr. A. Patricia Wodi said in a statement reported by CNN.
This “normalization” comes at a time when over 85% of the U.S. population hasn’t been boosted, despite the massive government-sponsored media push.
Nationally, only 12% of children ages 6 months to 4 years have received one dose of the vaccine. Only 58% of children ages 12 to 17 and 32% of children ages 5 to 11 have received two doses of the vaccine. Numbers vary widely across states.
Holland commented on the implications of adding this shot to the schedule:
“The childhood schedule is already unscientific and unjustifiable. Adding this shot may well be the straw that breaks the camel’s back. Parents are likely to resist, finally calling the entire childhood vaccine schedule into question.
“That day has been long in coming, but it is now here. I believe we are now watching the beginning of the end of Big Pharma’s reign over the nation’s children.”
At Wednesday’s congressional hearing, lawmakers repeatedly raised concerns about how regulatory agencies’ flawed recommendations led to a lack of confidence in public institutions.
Rep. Cathy McMorris Rodgers (R-Wash.) said, “There’s serious distrust today with our public health agencies. [Polling indicates] 40% of the public does not trust our public health agencies to handle the next public health emergency.”
Walensky indicated that vaccination rates for all vaccines on the childhood schedule among kindergarten children declined last year, dropping from 95% to 93% over the last two years, amounting to hundreds of thousands of parents opting not to comply with the childhood vaccination schedule.
VAERS is the primary government-funded system for reporting adverse vaccine reactions in the U.S. While reports submitted to VAERS require further investigation before a causal relationship can be confirmed, VAERS historically has been shown to report only 1% of actual vaccine adverse events.
According to Retsef Levi, Ph.D., with the Massachusetts Institute of Technology, the vaccines “cause unprecedented levels of harm, including the death of young people and children.”
Multiple studies have determined that the vaccines increase the risk of myocarditis and pericarditis, particularly in young men.
An October 2022 study revealed the CDC was aware of the safety signal for these side effects months before it informed the public.
At the recent FDA vaccine advisory committee meeting, several committee members also raised concerns about recommending annual bivalent boosters for children given the lack of data.
Dr. Archana Chatterjee, Ph.D., committee member and dean of the Chicago Medical School and vice president for medical affairs at Rosalind Franklin University said:
“As we look at this question [simplifying the vaccination schedule] for young children, the data is just too few for us to really make scientifically sound decisions regarding this question. The trial data need to be much more robust than we have seen in the past.”
In light of data like this, vaccination for COVID-19 for children and healthy people is losing public and even governmental support in some places.
Under public pressure and facing a series of lawsuits, last week California dropped its plan to mandate COVID-19 vaccination for school children.
As of Feb. 6, 21 states have legislation or executive orders banning student vaccine mandates, according to the National Academy for State Health Policy, a nonpartisan organization of state health policymakers.
Only the District of Columbia currently has a vaccine mandate for school children, although it is not set to go into effect until the 2023-2024 school year.
Denmark ended its universal COVID-19 vaccination campaign for healthy individuals in February 2022.
Brenda Baletti Ph.D. is a reporter for The Defender. She wrote and taught about capitalism and politics for 10 years in the writing program at Duke University. She holds a Ph.D. in human geography from the University of North Carolina at Chapel Hill and a master’s from the University of Texas at Austin.
The CDC recently codified International Classification of Disease (ICD) codes for Covid-19 vaccine status. ICD codes are extensively used in medical records, medical insurance data and health research to classify precisely disease states as well as injuries from exogenous agents such as accidents, medication and medical device injuries, toxic chemicals, etc. Vaccination status is not a disease or an injury state, yet CDC has rationalized creating ICD codes for it. The coding is set to become effective on April 1, 2023.
As described by Dr. Robert Malone, “The ICD classification system is run by the World Health Organization, not the US government.” The vaccine status ICD codes were developed by the US Centers for Medicare and Medicaid Services (CMS) some nine months ago, and CDC is implementing them.
The coding scheme, Z28.xxx, includes both vaccination status and possible reasons for the status. However, there does not appear to be a code for “fully vaccinated,” only for various states of “not fully vaccinated.”
The code Z28.0 means “immunization not carried out because of contraindication.” Z28.1 means “immunization not carried out because of patient decision for reasons of belief or group pressure.”
Z28.2 means “immunization not carried out because of patient decision for other and unspecified reason.”
Z28.8 means “immunization not carried out for other reason” which because of code Z28.2 must refer to reasons not attributable to patient decisions.
Finally, Z28.39 means “other underimmunization status,” including “Delinquent immunization status” and “Lapsed immunization schedule status.”
However, a potential contradiction arises because code Z28.310 means “unvaccinated for COVID-19.”
In order to reconcile this, the Z28 codes in the previous paragraph must refer to vaccines other than for Covid-19. The only other Covid-19 code is Z28.311 which means “partially vaccinated for COVID-19,” where “partial” refers to the CDC definition for “fully vaccinated” at the time when the patient visits the health-care provider who records the vaccination status in the medical chart.
It is apparent that the details of reasons for patient choices for vaccine status are not specified in codes for Covid-19 vaccines, but the CDC has some two months to fix this. There are no specific codes yet for “refused to divulge COVID-19 vaccination status” or “unknown COVID-19 vaccination status,” but these codes are likely to be added at some point.
What is the usage for which this information is planned? There is certainly a public health rationale for agencies to be able to monitor population vaccination status. Personal health information is routinely analyzed by public health agencies, insurance companies and health researchers, but in anonymized and grouped formats. The identifiable information is recorded in the databases, however HIPAA and other laws strictly protect identifiable health information and regulate how such information may be used for analyses.
In theory, vaccination status could be no different. Medical records already know your age, gender and race, where you reside, about your obesity, diabetes, your smoking and alcohol usage and your HIV status. Some of this information could be stigmatizing if released publicly, but at present there are no politicized or other circumstances to force unwanted choices on members of the public based on this compiled personal information.
Imagine, however, that one day, government agents are pounding on your door at 6am, telling you that you are required to take smoking cessation medications, under penalty of forced residence in a “smoking-cessation hotel” until you submit to the government’s requirement.
The medications have built-in transmitters that are activated when exposed to stomach acid, so taking them is recorded. After all, 500,000 Americans die every year from smoking-related diseases and their end-of-life medical care is an expense for which the government no longer wants to pay. Your smoking is economically hurting the medical care that grandma needs. Or something.
But Covid-19 and its vaccination are different. The Covid vaccines and their boosters were created under emergency-use authorization (EUA) protocols and are not fully licensed. The Biologics License Application (BLA) versions, e.g., Comirnaty, are not generally available in the US. This licensing chicanery has not gone unnoticed by the American public and a substantial fraction of people find the vaccines controversial.
Many people have seen their multiple-vaccinated friends and relatives get Covid, some multiple times. Many have also seen friends and relatives harmed by the vaccines, and most people know of the incessant daily deaths of healthy athletes, deaths discussed as caused by “coincidence.” People have seen the vaccines touted as solutions to the pandemic, yet utterly fail across the population to suppress transmission of the infection.
And, people have been bombarded with daily narratives for two solid years that the vaccines are “safe and effective” and that they must be taken, and that unvaccinated people are “bad,” “selfish,” demonized as doing damage to society, and should be shunned.
That is, personal vaccination status today is the most stigmatizing personal data of modern times, surpassing having AIDS. As such, any government compilation must be “bulletproof” against hacking and misuse. As well, the government must be trusted to maintain the data for use only as other personal medical data have been used.
Given the two-plus years of massive government propaganda about the vaccines, about their adverse effects, about Covid, about early Covid treatment, and the government collusion with social media companies in suppression of valid dissenting medical and scientific opinions and data, there is no empirical reason to support trusting the government with such sensitive, stigmatizing data.
There is no reason to believe that the government will not release the status information to insurance companies or other companies doing large business with the American public. Further, there is no recourse should the government actually release such confidential data. Thus, nothing may stop such companies from restricting activities based on the stigmatized data. For example, public travel could be blocked; bank accounts could be blocked; purchasing could be blocked.
The free pursuit of happiness is enshrined in our Declaration of Independence. The government cannot lawfully interfere with normal transactions of everyday life. But private companies working at the government’s behest, with government-supplied personal status information, could very well do it.
As has been seen from the FOIA documents, hundreds of government employees have spent the pandemic years doing exactly this unconstitutional behavior in getting social media companies to suppress Americans’ freedom of speech.
Furthermore, there is now no rational government interest in compiling vaccination status at all. At a time when vaccination was generally thought (incorrectly) to reduce Covid-19 transmission across the population, there might have been a rationale for doing so.
However, on August 11, 2022, the CDC stated publicly that the Covid-19 vaccines do not work as a public health measure to control virus transmission. They said, “Receipt of a primary series alone, in the absence of being up to date with vaccination* through receipt of all recommended booster doses, provides minimal protection against infection and transmission (3,6).” “Being up to date with vaccination provides a transient period of increased protection against infection and transmission after the most recent dose, although protection can wane over time.”
The fact that such benefit is “transient” and wanes implies that after some short period, boosters fail to reduce risk of transmission and thus that vaccine mandates are invalid.
The only government interest in mandating Covid vaccines, and thus in compiling personal information about vaccination status, is that the vaccines reduce transmission. They don’t.
Secondly, the CDC’s August 11th policy guidance does not distinguish between vaccinated and unvaccinated people in any way for any policy. There is thus no compelling government purpose in defining people as vaccinated or unvaccinated. It would be like the government compiling personal information on hair color, except that hair color is not stigmatizing and vaccination status is extremely stigmatizing.
The government itself—through the CDC—has determined that vaccination status is not of policy importance. There can thus be no compelling interest for the government to forcibly collect this information against the wishes of the population, even were it not stigmatizing. So much more so after the government has spent the last two years publicly demonizing unvaccinated people for their rational and legitimate personal health choices.
Harvey Risch, Senior Scholar at Brownstone Institute, is a physician and a Professor Emeritus of Epidemiology at Yale School of Public Health and Yale School of Medicine. His main research interests are in cancer etiology, prevention and early diagnosis, and in epidemiologic methods.
The mask is slipping (pun fully intended), all over the place – regarding the Big Tech/Big Government collusion. Now it’s time to pay close attention to the role played by the Centers for Disease Control and Prevention (CDC).
We’ve already been awed – just by the magnitude of the whole thing – if not exactly “shocked” by the Twitter Files.
But – what in the world was happening at Facebook, around the same time? After all, Facebook is an almost orders of magnitude bigger and more influential social network than Twitter.
For the time being, we don’t have the same “direct line” to internal documents as is the case with Twitter, which was made possible by the dedication to transparency by the new owner himself.
However, what could be dubbed as the “Facebook Files” are based on credible sources, too – Reason is coming out with a story based on confidential emails that emerged thanks to a court case – the state of Missouri suing the Biden administration.
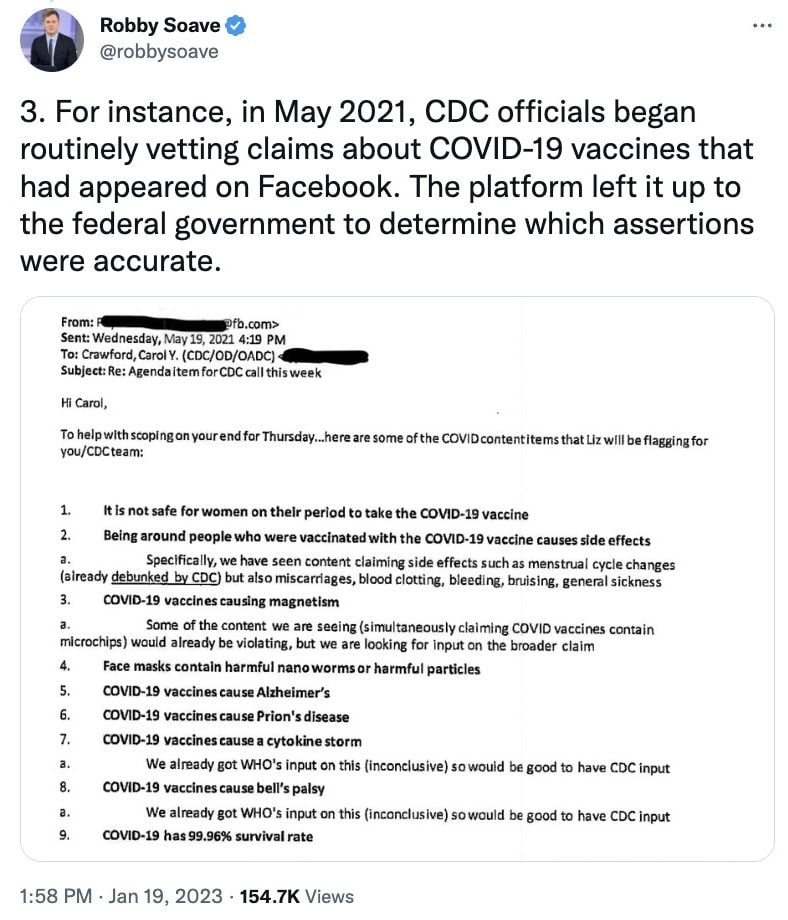
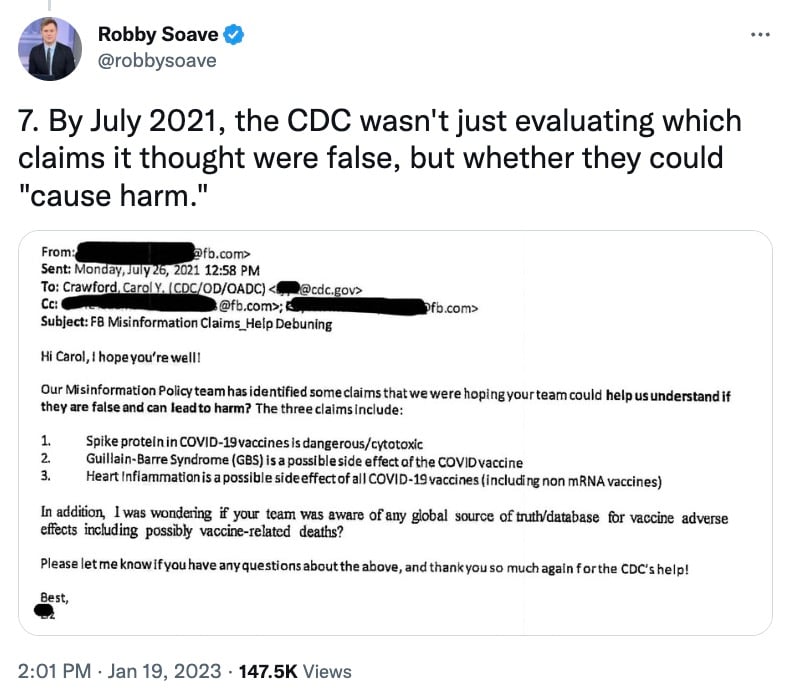
The emails show that Facebook (and by extension Instagram) representatives and the CDC not only kept in touch at all times, but that the tech giant also “routinely asked government health officials to vet claims relating to the virus, mitigation efforts such as masks, and vaccines.”
In turn, the CDC kept a watchful eye on what speech was allowed on Facebook, what policies toward censorship of “inconvenient” Covid topics applied, and this government agency had no problem instructing the social network behemoth how to behave in these instances.
Robbie Soave, a senior editor for Reason, revealed some examples of what was happening in a series of tweets citing the emails and providing screenshots. One shows that in May 2021, CDC started to get involved in “vetting” content on Facebook that concerns Covid vaccines. And CDC had the last word on what was allowed to remain online as “accurate.”
Other emails show that Facebook (Meta) made sure the CDC was given de facto power to police Covid “misinformation,” while at the same time flagging content for the CDC, consulting with it on claims that could “contribute to vaccine refusals.”
At the same time, Reason is acknowledging that this was by no means the only federal agency to engage in similar activities, all aimed at pressuring some of the world’s biggest social platforms to allow only a certain narrative, and discredit any skepticism, even that coming from medical professionals and scientists.
Even President Biden made sure to “contribute” to this effort, when he in June 2021 bizarrely accused Facebook of “killing people.”
This was really meant to say that the giant had better not dare allow any Covid content the White House failed to “vet” behind the scenes – one way or another.
And the giant obliged, sometimes probably even exceeding the level of compliance expected from the administration. An internal email now reveals that Facebook went as far as to “snitch” on its own users making fun of Anthony Fauci, apparently in a bid to defend his reputation – again, at the expense of free speech.
“One email warned the CDC that Facebook users were mocking Fauci for changing his mind about masking and double-masking. The CDC replied that this information was ‘very helpful’,” Soave, the magazine’s senior editor and host on The Hill TV channel, tweeted.
The upcoming, March issue of Reason delves into how the CDC turned into the speech police when it came to pressuring social media to block content that the government agency decided was Covid “misinformation.”
And this was online speech that this, and other government agencies, have no constitutional way of directly suppressing without breaking the law.
“There is a word for government officials using the threat of punishment to extort desired behaviors from private actors. That word is: jawboning,” Soave remarked in one of the tweets.
And one can imagine – and the emails now show – just how gun-shy and ready to please those in power Facebook had become, after years of public vilification, and who knows what kind of pressure behind the scenes in the wake of the 2016 US election.
Newly released emails reveal that leadership within the US Centers for Disease Control and Prevention and National Institute of Health acted to prevent the release of a long-delayed review of fluoride’s toxicity by the National Toxicology Program. The emails specifically claim that Assistant Secretary for Health Rachel Levine intervened to stop the release of the NTP review, also known internally as a monograph.
An email dated June 3rd, 2022, shows Nicole Johnson, Associate Director for Policy, Partnerships and Strategic Communication in CDC’s Oral Health Division contacting Jennifer Greaser, a Senior Public Health Policy Analyst in CDC’s Washington office. Johnson states:
“The latest we heard (yesterday) is that ASH Levine has put the report on hold until further notice.”
ASH Levine refers to the U.S. Assistant Secretary of Health, Rachel Levine.
The emails were released as part of the ongoing legal dispute between the U.S. Environmental Protection Agency (EPA) and plaintiffs Food and Water Watch, the Fluoride Action Network (FAN), and others who are seeking an end to water fluoridation Throughout the historic lawsuit the plaintiffs have argued that the practice violates the EPA’s Toxic Substances Abuse Act.
Hearings for the lawsuit began in June 2020, but were delayed for more than two years after U.S. District Court Judge Edward Chen put the proceedings on hold pending the release of the NTP’s review of all of the available research on fluoride. The NTP had previously claimed the review would be available in May 2022. However, the review has not been made public and hearings have been delayed and rescheduled as the judge awaited the NTP’s conclusions.
In late October 2022, Judge Chen ended the two year stay on the lawsuit when he ruled that the NTP review could be viewed in its unpublished form to better inform his final decision. However, due to concerns from the EPA, Judge Chen ruled that the report could not be made public unless the NTP releases it.
On December 14, 2022, the plaintiff’s filed several exhibits with Judge Chen, including a redacted version of the NTP’s assessment of fluoride’s neurotoxicity and internal emails between the CDC and the NTP which were obtained via Freedom of Information Act requests.
What do the #FluorideEmails reveal?
Michael Connett, attorney for the plaintiffs, outlined the findings of the emails in several exhibits submitted to Judge Chen. “These emails confirm that the NTP considered the May 2022 monograph to be the NTP’s final report,”Connett writes. “They also confirm that the CDC was opposed to the NTP releasing the report, and that leadership at the top levels of the Department of Health Human Services intervened to stop the report from being released.”
As Connett notes, on April 28, 2022, Dr. Mary Wolfe, the Director of NTP’s Office of Policy, Review and Outreach, emailed Casey Hannan, the Director of CDC’s Division of Oral Health, and stated that the NTP’s “analysis and conclusions are set”. Dr. Wolfe also let Hannan know that the NTP had reviewed the CDC’s submitted comments, but still planned to release the review “mid/late May” 2022.
In a May 11, 2022 email, Wolfe again notifies Hannan and the CDC that the NTP has “set May 18, 2022 for publication of the monograph. The monograph will be posted to the NTP website, and we will email a notice of the posting to NTP listserv subscribers.”
However, later that day and the following day, Dr. Karen Hacker, the Director of CDC’s National Center for Chronic Disease Prevention and Health Promotion (NCCDPHP), tells Dr. Wolfe that there is concern within the CDC about publishing the NTP review without an additional review by “NIH leadership”. Hacker also asked about the potential of a “interagency review” by the Department of Health and Human Services (HHS).
Dr. Wolfe subsequently told the CDC that “we (the NTP) believe the current findings, as stated in the monograph, reflect the scope of our evaluation and the available scientific literature and no revision is needed”.
Meanwhile, while Dr. Wolfe was defending the work of the NTP, internal emails among officials at the CDC’s Division of Oral Health reveal that the CDC was already preparing to prevent the release. A May 12, 2022 email from Hannan states:
“The May 18th release date for [the monograph] is almost certainly not going to happen. OASH and NIH OD are pretty clearly going to get more involved.”
OASH is a reference to the Office of the Assistant Secretary of Health, the second highest office in the Department of Health and Human Services, while NIH OD refers to the NIH’s Office of the Director, the highest office within the NIH. The current Director of the NIH is Lawrence A. Tabak.
Jay Sanders, Education & Outreach Director with the Fluoride Action Network, told The Last American Vagabond he believes the emails “reveal a concerted effort at the highest level of the U.S. public health bureaucracy to squash a key report on fluoride neurotoxicity”. Sanders also stated the emails “show the lengths these agencies are willing to go to to protect their pet project, fluoridation, from any scientific scrutiny.”
Together with the June 3rd, 2022 email, these communications point to direct intervention from the head of the NIH and the Assistant Secretary for Health at the Department of Health and Human Services.
The emails confirm what has long been suspected. Namely, that government officials at some level were preventing the release of this important review on the toxicity of fluoride. The CDC interference comes on top of an already unusual process employed by the NTP to evaluate the data on the safety of water fluoridation.
“This report, which has now been reviewed 4 times, is now going to be reviewed a 5th time by the NTP,” Fluoride Action Network attorney Michael Connett stated during the October 2022 hearing. “There will be at least 5 separate peer review processes extending over 4 years. This is, to put it mildly, exceptionally unusual.”
The next hearing in the #FluorideLawsuit takes place on January 12, 2023 at 2:30 PM US Eastern.
When the House of Commons was debating how much to increase the time limit for detention without trial the question of torture came up. Officially this was limited to the nice considerations of whether it was all right to send people to places where torture is used and whether Britain can use information collected by the use of torture in other countries. This discussion gave an impression of democratic Britain as the home of civilised behaviour where the very idea of torture is repugnant to our legislators – unlike, say, the US with its secret CIA jails… In reality, the British state has a long history of using and developing a whole range of torture techniques. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.









 Aletho News

