HOW IS THIS A THING? 27TH OF JUNE 2022
Sources:
Women’s Health and COVID-19: FLCCC Weekly Update (June 15, 2022): https://odysee.com/@FrontlineCovid19CriticalCareAlliance:c/Weekly_Webinar_June15#d
These are third party polls. We don’t control the recipients. The people making the assessments of vaccine deaths are almost all people who took the shot.
By Steve Kirsch | July 3, 2022
Here are the last two external polls we ran:
Both show that the vaccine killed nearly twice as many people as COVID did.
The survey recipients are a broad cross-section of America and were selected by Pollfish.
For the Jun 30 poll, the numbers were 45 killed by the vaccine [Q16] vs. 23 killed by the COVID virus [Q18] and for the Jul 2 poll, the numbers were 38 [Q22] and 18 [Q24], respectively.
If the vaccines are safe and effective, how can they explain these poll results? This is objective poll data of the American people.
These are great polls to run past your blue-pill friends and have them explain it to you since they are the expert and you don’t know anything.
I predict silence from the medical community, the mainstream media, Congress, and the government agencies. Not even 60 Minutes is going to touch this data with a ten foot pole. Nobody will. They will just ignore it just as they have for my earlier polls.
Next step for us: run it against 5,000 people.
“FDA, CDC, NIH, Moderna, & Pfizer secretly told me this”
By Dr. Paul Alexander | June 30, 2022
They said, follow the $CIENCE. Fauci said he is the $CIENCE.
I have been trying to warn. I have written on this here in stack. I try again.
Everything you have been told by government, by CDC, by NIH, by Fauci, by Birx, by Bourla, by Pfizer, by all your government officials, were lies, distortions, exaggerations, meant to mislead you. All pure lies on everything about lockdowns and these failed COVID gene injections. All, every single part was a lie. A deception. This entire COVID pandemic, was a lie! Yes, we had an emergency, but everything done to us the last over 2 years was a fraud hoax, a lie. Every single COVID policy failed. Canada, US, UK, everywhere.
The entire lockdown lunacy failed! All school closures failed, just killed children. Everything was a lie! They knew it would never work but knew one thing, that you as people, as the population, crazily thought, that they as health officials and medical doctors, wanted to do good by them and they could ‘trust’ you. You would do them no harm.
Little did they know. Little did we know the corruptible malfeasants we were dealing with. I include many medical doctors in this.
Trump was right when he early on said it was hoax. He did not mean the virus was a fraud or hoax. He meant the repose. The response was, and he saw what the deepstate and media, and CDC and NIH and Fauci and Birx were doing to him. But he could not stop them. He could, he could have, but he was weak. He then did the unthinkable. He allowed Fauci and Birx to lead a crazy lockdown lunatic policy that harmed and killed thousands of Americans. None of it worked! Not one!
You will come to learn, that 2.5 years of your life was taken away, for a lie! A greed, power drunk lie! By sick malfeasant people. Their motives. That must all be investigated and if it is shown they did this deliberately and caused deaths, we jail them all! Yes, 2.5 years lost to these malfeasants. The COVID injection is a failed ineffective dangerous injection.
I am no anti-vaxxer, but I am against these injections.
I was told by these officials (FDA, CDC, NIH, Moderna, & Pfizer), in confidential secret discussions, that in about 6 to 6.5 years from roll-out, in those who take the injections, they feared mass auto-immune disease and deaths, they feared viral immune escape and very problematic variants, and they anticipated constant deaths from the injections but a major number of deaths to emerge. I could not even understand exactly what they did for it was so haphazard, but these were officials. And they wanted to talk to me. To tell me ‘their truths’.
They said based on all they knew, that the COVID injections could never work, especially the mRNA platform. It never worked in the animal model and was pathological. They told me that in about 6 to 6.5 years, there will be a surge in deaths in persons who take the injections (then about 1 year ago). This was their projection. They advised me they nor their families will never (especially their children) take any of the COVID injections.
The key is the injection works for some people and I argue we do not know how long and what the effects are and this is what I was told. But you understand that too. You cannot take a 15 year process and boil it down to a few months and declare it is safe. They were never safety tested to exclude harms and deaths longer term. We do not know exactly what is coming. But it certainly does not work for a whole bunch of people. Look around, you know people who have been harmed by these injections and died. Do you not? Something is very wrong with these injections. Very wrong and they just will not stop.
I am being open with you to inform you. I am sick and tired, years now, of the lies and fraud and disaster put out by the media, the alphabet health agencies etc. You trusted your public health officials, you think ‘they care about you’, well, they never cared about you, your family, or the truth. It is to them about the $CIENCE.
I think I shared prior that my office was on the 6th floor of the HHS building in DC, Operation warp speed and Moderna were stationed on the 7th floor. FDA, CDC etc. have sub-satellite offices at HHS. At least when I was there and Hahn, Redfield etc. came there daily after congress or White House to see their staff, various persons, persons in various offices.
These people I talked with, came to me out of anger and fear too, they knew who I was and wanted to tell me their stories and how worried they were for the population, and fearful for their lives and own careers as to the COVID injections (and other issues). If they spoke out openly so had to talk secretly.
They were very very dismayed and angered and worried as to why the agencies they worked for e.g. FDA and NIH and CDC etc. and the pharmaceuticals were not properly regulating and conducting the proper safety studies, proper durations of follow-up. They felt the COVID injection program was a pure disaster and should be stopped back then. This is 6 months or so before roll-out. They felt no healthy children should ever be given the very injections they were working on. They were that concerned.
I want to be clear again, based on all I know today, based on what I was told, many many children will die due to these injections. Healthy children will die, not ‘if’, but ‘will die. Healthy children, healthy people, normal people never needed and do not need these injections. I have told you before that (strong research and scholarship by Geert) we will be in a pandemic for 100 years if we continue these injections. It is the COVID injection itself that is driving the variants and these CDC, NIH, Moderna, and Pfizer officials are malfeasants IMO who are continuing this. There is no sound justification. These malfeasants know that they are vaccinating with the Wuhan strain (legacy strain) that has been gone many months now and omicron dominates. The vaccinal antibodies are to the original Wuhan strain and will not hit the omicron spike antigen (original antigenic sin (OAS)).
It is the COVID injection (and consequent non-neutralizing antibodies pressuring the spike antigen) that is causing the vaccinated to become infected, hospitalized, and die. The data is clear. Massive antibody-dependent enhancement, some refer to this as antibody mediated viral enhancement. Some pathogenic priming. All IMO the very same. The recall antibodies are to something that does not exist today. The key is to reduce viral pressure, infectious pressure on the population, so that the sub-optimal injections have less virus to put under pressure. We have effective chemoprophylaxis, we can do this. We have early treatment. This can worked effectively and this can thus help reduce viral transmission. At the same time, the best step is to stop these filed injections.
I want all of these people investigated in proper public and legal inquiries, and if it is shown they did wrong, in proper inquiries, I want them arrested. I want all who made policy decisions that costed lives, to be jailed! All their monies taken!
Dr. Rogers looked at the FDA June 28th meeting and his takeaway is bang on and what we have been saying here for near a year now here:
‘‘Yesterday, the FDA’s Vaccines and Related Biological Products Advisory Committee approved a bivalent Covid-19 shot with the Wuhan strain and the Omicron variant.
The vote was:
19 yes.
2 no.
A few thoughts:
The Wuhan strain is no longer in circulation. So they are vaccinating against a strain that no longer exists.
The Omicron variant that they are going to put into this shot is Omicron BA.4/BA.5:
1. By the time it gets to market in the fall, Omicron BA.4/BA.5 will likely no longer be in circulation.
2. There is no efficacy data whatsoever on vaccines against Omicron BA.4/5.
3. There is no safety data whatsoever on vaccines against Omicron BA.4/5.
4. They do not intend to gather any efficacy or safety data between now and when these shots will be released in the fall:
At the meeting, the manufacturers (Moderna, Pfizer, and Novavax) were asked what their production timelines are… and they said out loud, “So long as we don’t have to provide any clinical data, we’ll have them ready by fall.”
Dr. Rogers is a smart guy.
His work:
DID FORMULATIONS CHANGE OVER TIME?
Team Enigma | June 28, 2022
How Bad is Your Batch?
We have a list of 691 lot numbers for the C-19 injections. The list was leaked from CDC and contains valid lot numbers, NDC codes, manufacture and expiration dates. The adverse events and deaths per lot number show very strange patterns of data over time. It’s as if a “cliff” has occurred in March 2021 – did the manufactures change the formulations or is there some other explanation?
I am using data on removed reports from VAERS provided by Albert Benavidez: https://public.tableau.com/app/profile/alberto.benavidez/viz/WelcomeTheEaglesEntireVAERSDeletedReportsDashboard/Home
The fawning media coverage notwithstanding, uptake has been pitifully low
By Alex Berenson | Unreported Truths | July 2, 2022
Despite a massive media and government pressure campaign, American parents are overwhelmingly rejecting Covid vaccines for their young children.
About one week after the shots became available, barely 1 percent of children under 5 have received mRNA jabs for Covid, data from several states show.
Ohio:
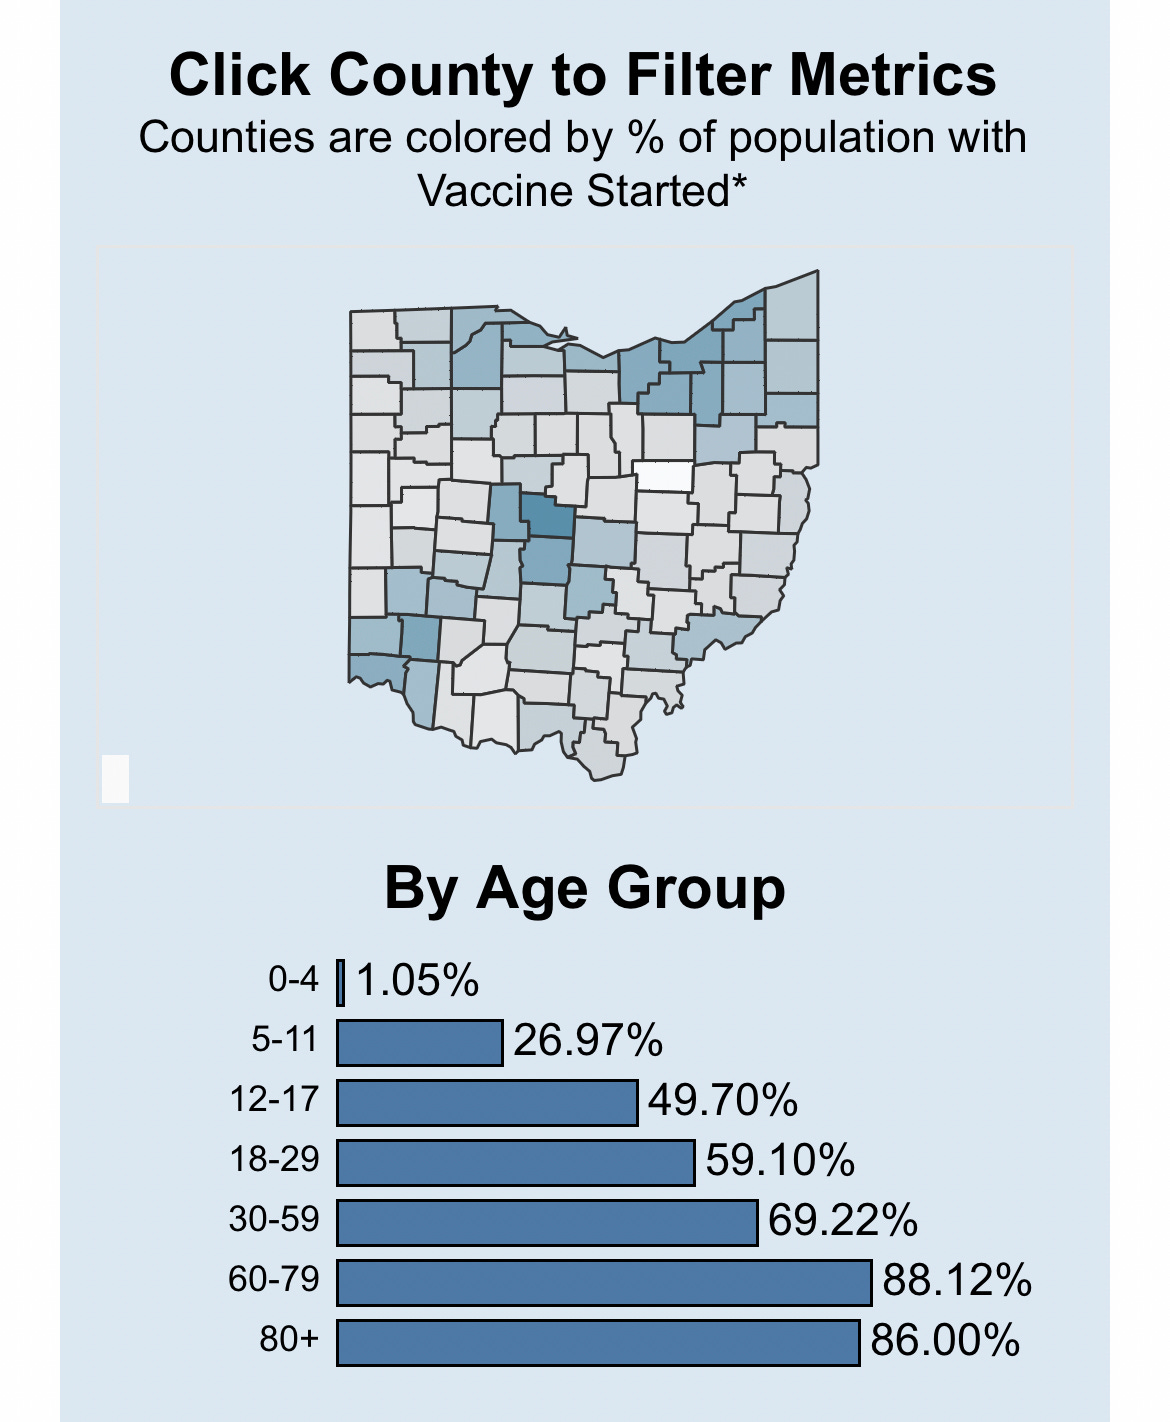
Even in California, among the bluest states, only about 2 percent of kids under 5 have been jabbed.
Demand is likely to be near zero going forward. The recent history of Covid shots shows that the increasingly tiny minority of mRNA fanatics get themselves or their children jabbed or boosted quickly after regulators okay new doses. So pent-up desire for new shots is likely nonexistent.
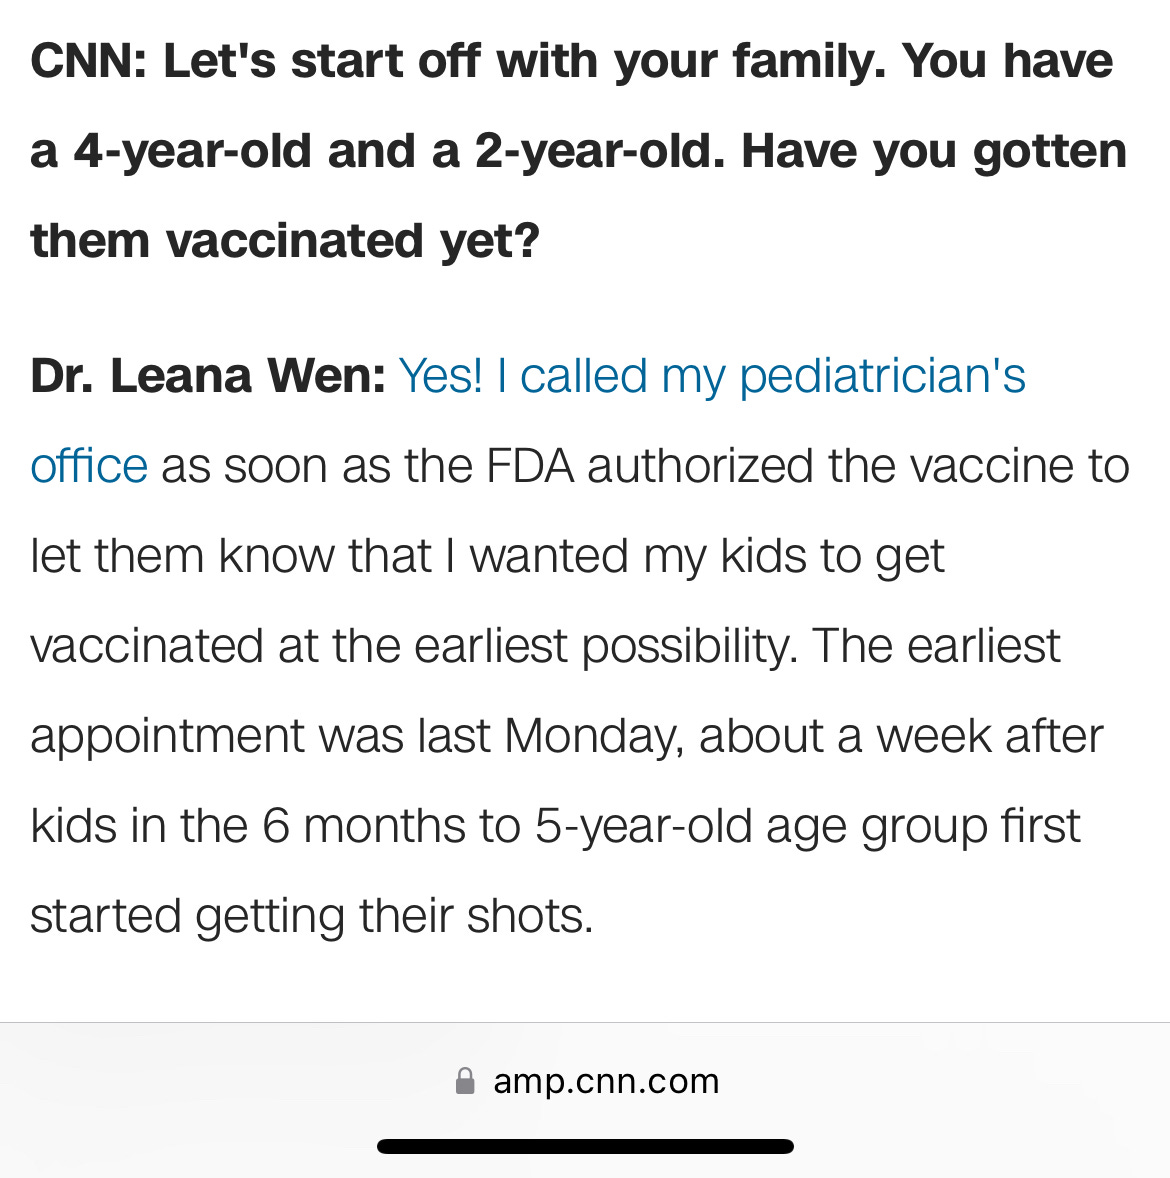
As usual, elite media outlets have largely refused to acknowledge this reality, instead running endless articles that seek to normalize and encourage the shots.
(CNN gonna CNN:)
But at this point many parents have seen and experienced the side effects of the vaccines for themselves. They also know firsthand that the shots do little if anything to stop Omicron infections (though they may not be aware how terrible the data truly are). And they know that Covid is a minuscule risk for children who are not already seriously ill, and that most kids have already been exposed.
(All the Sesame Street ads in the world can’t change reality. Congrats, Elmo. You’re in the 1 percent. Cute Band-Aid, though.)

But as it becomes clear just how few little kids have gotten the shots, any future media and public health pressure campaigns will look embarrassingly out-of-touch.
Someone may want to tell the Biden Administration: the less said about the pathetic decision to make these shots available for kids under 5, the better.
Oh, wait, too late.
Uncle Joe wins again!
BY CLAYTON FOX | BROWNSTONE INSTITUTE | JUNE 30, 2022
The media, and the people who work in and around it, the Blue Checks™ of Twitter, have upped the ante over the past few years regarding how far they are willing to go to enforce various preferred narratives.
Pick any major story of the past three years—e.g. Lab Leak, Jussie Smollett, Russiagate, Ukrainian Biolabs, Ivermectin, Hospitalizations From COVID v. With Covid, January 6th, ‘Transitory’ Inflation, and of course Hunter’s Laptop—and you will find absolutely hysterical narrative pushing up front followed by retractions, corrections, and outright denials as reality became undeniable.
In the meanwhile, our civilization was ripped apart, our citizens were gaslit and impoverished, and in countries across the Western world, innocent people were removed from polite society, branded as lepers, and fired from their jobs.
Why? Because there is one story that just won’t die and for which no corrections have been issued—the shibboleth that vaccination can prevent infection, transmission, and help “end” COVID.
While there is never an excuse for hateful rhetoric towards, and intervention in, the personal medical choices of law-abiding Americans, perhaps one could have, kinda sorta, understood the campaign if the new vaccines had provided long-lasting immunity and prevented community transmission. They do not.
Early on we were told: “Nine out of ten [vaccinated] people won’t get sick” (Columbia University feat. Run-DMC, February 12th, 2021, no this is not a joke); “Vaccinated people do not carry the virus, don`t get sick” (Dr. Rochelle Walensky, March 29th, 2021); “When people are vaccinated, they can feel safe that they are not going to get infected” (Dr. Anthony Fauci, May 17th, 2021).
And by mid-summer, 2021, we were still being told that unequivocally, these vaccines were a resounding success worthy of uncritical support. On July 27th in Scientific American, Dr. Eric Topol wrote, “Vaccination is the closest thing to a sure thing we have in this pandemic.” Not to be outdone, Dr. Anthony Fauci of the NIAID told CBS on August 1st, that the unvaccinated were responsible for “propagating this outbreak.”
But on July 29th, 2021, the Washington Post reported a scoop that the CDC was privately acknowledging that the vaccinated could spread COVID as easily as the unvaccinated. Occasionally, they are forced to report inconvenient facts. And August 5th, CDC Director Walensky told CNN’s Wolf Blitzer that, “They continue to work well for Delta, with regard to severe illness and death — they prevent it. But what they can’t do anymore is prevent transmission.”
While there is a mountain of medical literature available demonstrating quite clearly the failure of these vaccines to prevent infection and transmission, the August 5th declaration from the CDC Director should have made clear that being vaccinated is contributing in no way to the safety of others, nor to the eradication of this virus.
In fact, Israeli Health Minister Nitzan Horowitz was even caught on tape in September of last year explaining that the use of the Israeli Green Pass wasn’t intended to make a difference epidemiologically, but because it would help convince people to get vaccinated. And even vaccine poobah Bill Gates admitted in a late 2021 interview, that, “We got vaccines to help you with your health, but they only slightly reduce the transmissions.”
So there should be no question that continuing to suggest in any way that these shots are a panacea, and that those who refused to get them were plague spreaders, should have been thoroughly trashed by Fall 2021.
Nonetheless, on September 24th President Joe Biden coined his now famous phrase “a pandemic of the unvaccinated.” To our north, Prime Minister Trudeau called the unvaccinated science deniers, misogynists, and racists, and asked rhetorically whether Canadians should “tolerate” them.
And during the first week of January 2022, while kicking the unvaccinated out of French daily life and public spaces, French President Emmanuel Macron said he wanted the measures to “piss off” his unvaccinated citizens. With world leaders speaking this way, it’s no wonder so many Blue Check™ elites took up the banner!
Prominent media figures like Amy Siskind, Pulitzer Prize winner Gene Weingarten, and more have come out of the woodwork in recent months to share with us their enthusiasm for medical discrimination. Noted neurotic Howard Stern is all in on forced vaccination due to what must be his own debilitating fear of his mortality. Bill Kristol says the unvaccinated have “blood on their hands.”
David Frum, heir to Maimonides, writes, “Let the hospitals quietly triage emergency care to serve the unvaccinated last.” Charles M. Blow was “furious” at the unvaccinated. CNN contributor Dr. Leana Wen suggested that the unvaccinated should not be allowed to leave their homes. The Ragin’ Cajun even wants to punch the unvaccinated in the face!
All of the above links/stories were posted after Dr. Walensky’s unequivocal announcement that the vaccines do not prevent transmission.
And all of the self-satisfied segregationists are supported in their vitriol by the Blue Checks™ of the Medical Establishment, like Dr. Paul Klotman, President and Executive Dean of the Baylor School of Medicine, who said on camera back in January that he isn’t polite to friends and family who aren’t vaccinated. “Keep them away. I don’t do it respectfully, I tell them to stay away, and teach them a lesson.” Less vitriolic but equally problematic, the WHO’s COVID-19 “technical lead” Dr. Maria Van Kerkhove continued to push the lie that vaccination can prevent outbreaks as recently as January 26th, 2022. She is, as well, a Blue Check™. And yes, Dr. Anthony Fauci is still at it, even as of April 14th, 2022, telling MSNBC that harsh Chinese lockdowns could be used to get the population vaccinated so that “When you open up, you won’t have a surge of infections.”
The examples are legion. Blue Checks, Medical Blue Checks, Times Columnists, Radio Jocks, Presidents, and Prime Ministers have all espoused misinformation and/or hate speech regarding vaccination status. But they are all given intellectual cover by the official reporting of the fourth estate. Even in the face of all the evidence that there is no epidemiological basis for discrimination, our intellectual betters in the legacy media press onward the canard.
On August 26th, the Toronto Star ran an article entitled, “When it comes to empathy for the unvaccinated, many of us aren’t feeling it.” Then, on December 22nd, published an explainer which stated that two doses won’t stop you from spreading COVID-19. Comme ci, comme ca.
Back in February, MSNBC political contributor Matthew Dowd shared his insight that the unvaccinated do not believe in the United States Constitution, because if they did, they would get vaccinated for “We The People.” For the common good.
An examination of the New York Times reveals three articles written this year which overtly continue supporting the idea that the vaccines prevent transmission. First, on January 29th in a piece entitled, “As Covid Shots For Kids Stall, Appeals Are Aimed At Wary Parents,” the author cites “public health officials” who say that to aid in “containing” the pandemic, kids must also be vaccinated. (It is worth mentioning that the current vaccines and boosters being distributed were designed in February 2020 to provide an immune response to a version of the SARS-CoV-2 spike protein circulating prior to that, not entirely similar to what is circulating now.)
Then February 23rd, in a hit piece on the Surgeon General of Florida Dr. Joe Ladapo, the Times writes, “When public health officials across the country were urging vaccines as a way to end the pandemic, Dr. Ladapo was raising warning flags about possible side effects and cautioning that even vaccinated people could spread the virus.”
So, Dr. Ladapo was correct?
Finally, in a piece about Novak Djokovic published March 3rd, they write, “Djokovic was the only player ranked in the top 100 in Australia who had not received a Covid-19 vaccination, which experts have long said will not eradicate the virus unless most of the population receives one.”
They do not address the question of how a vaccine which does not prevent transmission can eradicate a virus. And they won’t. As Israeli Health Minister Horowitz candidly admitted, none of this is about epidemiology.
And even when mainstream media tacitly acknowledges the failures of the vaccines to prevent transmission, they skillfully elide the significance of this fact in order to allow them to continue to scapegoat the unvaccinated. In a dazzling display of sophistry, Time Magazine moved the Overton window in this January 12th, 2022 piece, “These Charts Show That COVID-19 Is Still A Pandemic of the Unvaccinated.”
The author states that due to the rapidly narrowing gap between cases in the vaccinated and unvaccinated, some readers might think that the phrase “pandemic of the unvaccinated” is no longer justifiable. But with the grace of a ballerina, Time goes on to tell us that because the vaccines are still showing efficacy against severe illness, the phrase is still kosher. If an unvaccinated person gets sicker than his vaccinated neighbor who contracted COVID at a fully vaccinated wedding, that unvaccinated person is still the problem!
New York Magazine isn’t lacking in similar gymnastics. On February 16th of this year, Matt Stieb published a piece entitled, “Is Kyrie Irving Going to Get Away With It?” Irving is the Brooklyn Nets player who famously chose not to be vaccinated, and has become a fetish object for the Covidian Left. Stieb acknowledges that Irving’s vaccinated teammates were getting COVID at such high rates that it forced Nets management to allow Irving back to play in away games but still calls the New York City ban on unvaccinated athletes “a rare public health mandate with real teeth.”
Just seven days later on February 23rd, Will Leitch, in the same publication, sighs, “Unfortunately, It’s Time to Let Kyrie Irving Play in New York.” He outlines all the reasons why epidemiologically it makes no sense to prevent athletes like Irving and Novak Djokovic from participating, but says, “It would feel like they got away with all their bullshit.” And also, they are “annoying.”
And this barely concealed hatred for the unvaccinated from media and government and Big Tech—even in the rare moments when writers such as Leitch acknowledge the failure of the vaccines to prevent transmission—has real consequences. People have lost their jobs. People have been arrested for trying to go to a movie theater.
Families got kicked out of restaurants, and patrons either cheered or remained indifferent, which is worse. A teenage boy at an uber-progressive and expensive Chicago prep school committed suicide after being bullied over an incorrect rumor he was unvaccinated. The stench of bad journalism rots people’s basic decency.
A January Rasmussen poll found that, “Fifty-nine percent (59%) of Democratic voters would favor a government policy requiring that citizens remain confined to their homes at all times, except for emergencies, if they refuse to get a COVID-19 vaccine…Forty-five percent (45%) of Democrats would favor governments requiring citizens to temporarily live in designated facilities or locations if they refuse to get a COVID-19 vaccine…”
As well as, “Twenty-nine percent (29%) of Democratic voters would support temporarily removing parents’ custody of their children if parents refuse to take the COVID-19 vaccine.” Unfortunately, these disturbing results are politically lopsided, but it’s no surprise when you consider who the readers of most legacy media platforms are.
The saddest thing is that these media outlets and their flag bearers really think their readers are all morons. The New York Times believes that, in the midst of the Omicron wave as boosted person after boosted person was getting COVID, they could tell you these particular vaccines are still the way to eradicate this thing, and expect you to deny reality and nod your head.
It calls to mind the quote attributed to Solzhenitsyn (or Elena Gorokhova), “The rules are simple: they lie to us, we know they’re lying, they know we know they’re lying, but they keep lying to us, and we keep pretending to believe them.”
We have ceded the better angels of our common cerebrum to people who may not have our best interests at heart, and a sycophantic laptop class who gleefully endorses their diktats and “fact-checks.” Collectively: Sophistry Inc.
Their behavior, endorsed by every single entity which holds power in our society, is destroying us, and has already poisoned us such that there may be no antidote. Yes, first they came for the unvaccinated, but that doesn’t mean they won’t come for you next.
Computing Forever | July 1, 2022
Sources:
https://www.irishmirror.ie/news/irish-news/fifth-wave-latest-covid-19-27342285
Sources:
Women’s Health and COVID-19: FLCCC Weekly Update (June 15, 2022): https://odysee.com/@FrontlineCovid19CriticalCareAlliance:c/Weekly_Webinar_June15#d
Are those two things related?
By Jordan Schachtel | The Dossier | June 29, 2022
Virtually every single adult in Portugal has taken at least two doses of “miracle cure” COVID vaccine, with the vast majority “boosted” as well. Yet this month, the most vaxxed country in Europe has consistently reported its worst outcomes.
Once thought to be the best positioned nation in Europe to deal with future bouts with the coronavirus, a nuclear bomb of reality has hit Lisbon.
Out of all the countries in Europe, “Portugal has experienced the most dramatic wave,” the Guardian reports. “With infections per million remaining at a seven-day average of 2,043 on Monday – the second highest new case rate in the world.”
It appears the “miracle cure” vaccines have not only not failed to curb the COVID issue, but has potentially made it worse.
That’s why PAXLOVID does not work for them
By Igor Chudov | June 30, 2022
A new study just came out:

It looked at how long “culturable virus” (that is, virus capable of infecting people) is present in Covid patients after the first positive test. The authors literally cultured swabs of patients, on various days past-diagnosis, and counted how many patients, by vaccination status, are still carrying live, replication-competent virus.
The result is shocking:

What this chart shows is that one-third of boosted people still carried live, culturable virus at 10 days after the beginning of the infection. This is contrasted with unvaccinated people, who had only 6% of persons still contagious at Day 10.
This means that the share of boosted people who are still contagious (31%) is over five times greater, than the share of still-contagious unvaccinated people (6%).
In other words: out of 100 boosted persons who catch Covid, fully one-third will be still carrying LIVE VIRUS on Day 10. Out of 100 unvaccinated persons, only one out of 16 would test positive on Day 10 — over five TIMES fewer people.
As a word of warning, the study involved a relatively small amount of people, so statistical significance is probably not quite what we’d like it to be — but it shows what we saw all along in other news.
It also means that boosted people, who might feel better in a few days, would be contagious for a few MORE days after recovery, thus becoming silent superspreaders of Covid. So much for “stopping the spread”!
This is why Paxlovid does Not Work for the Boosted
This study explains why Paxlovid does not work in vaccinated (and boosted) people. For the introduction into my paxlovid series, see the sad story of double-boosted Dr. Fauci, who relapsed on Paxlovid, with links to my Paxlovid articles shown chronologically:
What Paxlovid is, is a biomolecular “snooze button” that suspends viral replication for 5 days. However, as we can see, one-third of the boosted people still carry live virus at 10 days due to delayed, or disabled, immune responses. Those persons would be likely to rebound on Paxlovid.
The numbers also match other calculations: my guesstimate of unvaccinated Paxlovid rebound was 12% — that is not too far from 6% of unvaccinated people in this study who carried live virus on Day 10. 31% of boosted people who still have live virus on Day 10, matches Twitter reports of 40-50% rebound rates in vaccinated people.
In other words, while we had fairly certain evidence that Paxlovid does not work for vaccinated people, and suspected the vaccine, we were missing the most crucial proof: that of live virus not clearing in the boosted. The study I mentioned above, provides this proof.
It also exposes vaccines as merely “increasing tolerance” to Sars-Cov-2, as opposed to generating robust immune response that leads to rapid viral clearance.
Molnupiravir
I personally have not paid close attention to Merck’s Molnupiravir, due to it being a dead-end, mutagenic, cancer-causing, variant-generating, toxic-to-bones drug from hell, which is, fortunately, seeing little use. Our friend Modern Discontent discovered that Molnupiravir is also snake oil and does not work in vaccinated people.
Getting boosted is a great way to become unable to clear a Covid infection in 10 days and become a Covid superspeader.
BY NOAH CARL | THE DAILY SCEPTIC | JUNE 30, 2022
Until recently, South Korea was the poster child for the ‘contain and vaccinate’ strategy, having kept infections to a minimum until completing its vaccine rollout.
In November of last year, former ‘Zero Covid’ proponent Devi Sridhar argued, “It is never too late to learn lessons from countries such as South Korea, which pursued maximum suppression, and succeeded.” And in a super-viral tweet, Vincent Rajkumar (a professor at the Mayo Clinic) proclaimed, “South Korea followed the textbook principles of epidemiology. Kept deaths 40 times lower all the way till 75% of population fully vaccinated. This is success.”
All that was true until February of this year, when the country saw its first major outbreak. This outbreak, as I noted previously, led to a large spike in excess mortality; by March’s end, the number of weekly deaths was almost 70% higher than normal.
Owing to this spike, South Korea now has the same excess mortality as Sweden – which took a famously relaxed approach to dealing with Covid. Note: the chart below is based on weekly deaths, rather than age-standardised mortality rates, so it overstates excess mortality in both countries.
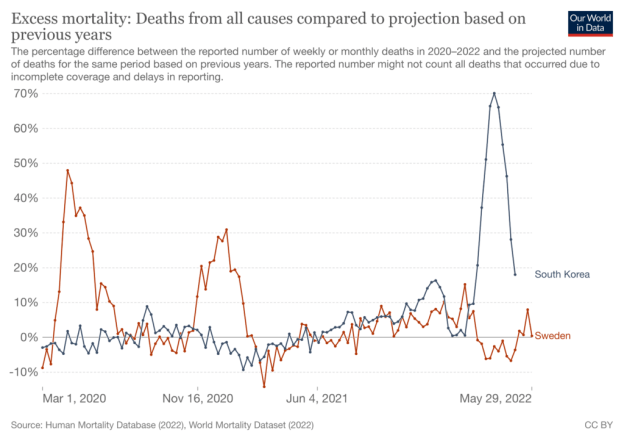
Incidentally, you wouldn’t know this from looking at the official Covid death rates. As the chart below indicates, the number of ‘confirmed’ Covid deaths per million people is much higher in Sweden, presumably due to differences in testing or diagnosis. Which illustrates the importance of tracking excess mortality.
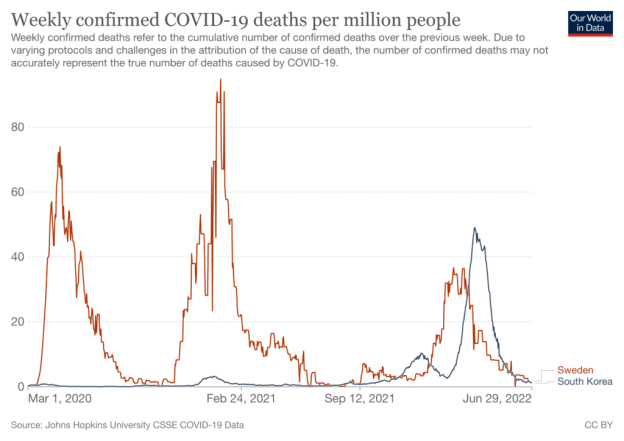
So, the country that did least to contain Covid has ended up with the same death toll as one of the countries that did most. What’s more, the majority of Sweden’s infections occurred before the vaccine rollout, whereas the vast majority of South Korea’s occurred after. Which suggests the benefits of containing the virus until after the vaccine rollout have been overstated.
Of course, South Korea didn’t do terribly. By containing the virus using border controls and contact tracing, they avoided really draconian lockdowns, and saw a comparatively mild downturn. Yet the measures they took still constitute a major infringement on civil liberties. As the Guardian notes, “Koreans’ movements were so finely and publicly tracked that secret love affairs and even hidden sexualities were brought to light.”
Anyone who cares about civil liberties will now have to ask whether South Korea’s strategy was worth it, given that Sweden ended up with the same death toll.
By Megan Redshaw | The Defender | June 29, 2022
The U.S. Food and Drug Administration’s (FDA) vaccine advisory panel on Tuesday voted 19 to 2 to recommend new COVID-19 booster shots that include the Omicron variant this fall.
The FDA’s Vaccines and Related Biological Products Advisory Committee (VRBPAC) did not issue guidance on whether additional data would be needed to recommend an updated composition of the primary-series vaccines authorized for emergency use in the U.S., or whether it would be appropriate to continue to use a primary-series vaccine as a booster.
It is the first time VRBPAC has suggested vaccine makers modify their vaccines to target a different variant, according to CNBC, which also reported the FDA will likely accept the committee’s recommendation.
If so, the FDA would be authorizing a vaccine change without requiring additional data showing a bivalent vaccine — containing both the original 2019 Wuhan variant and one of the Omicron variants — is safe and effective for those age groups that are already authorized to receive a booster dose.
The FDA plans to decide by early July whether vaccines will target the now-dominant BA.4 and BA.5 Omicron subvariants or the BA.1 Omicron variant that led to a surge in infections last winter, Reuters reported.
At the beginning of the meeting, Dr. Peter Marks, director of the FDA’s Center for Biologics Evaluation and Research, suggested a newly designed shot could begin in October, adding that it takes manufacturers around three months to choose a vaccine design and begin producing doses.
Dr. Paul Offit, director of the Vaccine Education Center and professor of pediatrics in the Division of Infectious Diseases at Children’s Hospital of Philadelphia, and Dr. Hank Bernstein, professor of pediatrics at Zucker School of Medicine, were the only two members who broke from the panel to vote against the initiative.
Offit acknowledged there’s a benefit to providing a booster in the fall to some age groups, but questioned whether Omicron was the right strain. He said the move to new-variant vaccines was happening too fast, with too little data.
“I think as a new product it should be handled as a new product,” Offit said. “I think we need a higher standard than what we’ve been given. …“I’m not comfortable enough to support the risk of a new product.”
Bernstein expressed concern over the lack of data used to justify changing the strain, and the potential that by the time a subsequent booster is approved, it will contain outdated strains.
“So, in sum, I think including an Omicron strain in the vaccine seems to have some potential, but data especially for BA.4 and BA.5 are limited at this time, and that’s why I’m struggling to even make a strain change at this time,” Bernstein said.
Bernstein also said he didn’t see a need to change the strain as the current vaccine being used is shown to be effective against severe disease — a claim made just two weeks earlier at a prior VRBPAC meeting.
Bernstein said the strain change would need to be supported by data showing improved vaccine effectiveness and he “didn’t think we really have the data to be able to say that” even though the panel looked at the immune response.
Dr. Ofer Levy, VRBPAC member and an infectious disease physician at Boston Children’s Hospital, voted “yes” to change the computation of COVID-19 boosters, despite Pfizer’s admission there is “no established correlate of protection,” referring to the level of antibodies needed to confer protection.
“You have a lot of data now,” Levy told Pfizer. “What is your relative protection?”
“I would say there is no established correlate of protection,” Kena Swanson, Ph.D., vice president of viral vaccines at Pfizer, told Levy.
Levy circled back during the meeting:
“I would like to hear from FDA what their overall approach will be around improving our understanding of correlate protection. We spend a good amount of time reviewing antibody data. We have no doubt antibody data is important. We don’t have a level of antibody that anybody is comfortable stating is correlated [with] protection.
“So yes, the antibodies are important but so are the T cells. We heard from Dr. Weir, yes, T-cell assays are trickier and they’re more diverse, but it’s not going to happen without federal leadership to have a standardization of the T-cell assay and encourage or in fact require the sponsors to gather that information.”
“So what is the effort to standardize the pre-clinical assays?” Levy asked. “This is an effort that’s critical not just now but for future cycles of vaccine revision. If we aren’t able to define a standard for correlate protection we are fighting with one arm behind our back.”
Marks acknowledged the importance of Levy’s question, but said T-cell-mediated immunity was “difficult to study” initially.
“We have been having conversations with our colleagues at the NIH [National Institutes of Health] and throughout government about how we might move forward here,” Marks said. “It is something that we don’t have an answer to yet.”
Marks said as vaccines are developed in the future, it will “become even more important” to define a standard of correlate protection because “we won’t be able to have a large naive population to vaccinate with newer vaccines.”
“We will need to understand the T-cell response better,” Marks said. “I take your point, it’s just that we haven’t solved the problem yet.“
Dr. Meryl Nass, a member of the Children’s Health Defense scientific advisory committee, told The Defender that in her opinion, Tuesday’s meeting was a “vote to essentially approve a future framework — the future framework being a dearth of evidence required to change the booster, without clinical evidence and without a correlation of protection.”
Nass added:
“They voted on using an Omicron variant in the next booster iteration — which could contain any Omicron variant and could be either mono- or bi-valent.
“But most likely they will keep the current version and add another — which might double the amount of mRNA, or not.”
The new formulation might be for adults alone or adults and children, or only older adults and the immunocompromised, Nass said.
Brian Hooker, Ph.D., Children’s Health Defense chief scientific officer and professor of biology at Simpson University, told The Defender :
“The proposed move by VRBPAC will increase the harm to the U.S. public to unprecedented levels, as this action will further circumvent necessary clinical trials even beyond the slapdash testing of COVID-19 vaccines under Emergency Use Authorization.
“This adds to a foundation of lies used to authorize the original COVID-19 vaccines without anywhere near proper testing.”
Dr. Cody Meissner, VRBPAC panel member and professor of pediatrics at Tufts University, expressed concern about the financial risk pharmaceutical companies “are taking by making these vaccines.”
“If there’s a low likelihood the vaccines will be recommended, then they could incur significant loss,” he said.
Marks responded:
“I guess I would say that I would make recommendations here knowing the vaccine manufacturers will be kept whole by the United States government at least for some vaccines. I could be wrong but I think that’s a reasonable assumption.”
During the meeting, Moderna told the panel it would be ready with a “couple of hundred million” bivalent, or double-targeted, vaccines designed to combat BA.1 by September, but it would be late October or early November if the company needs to design a new vaccine targeting subvariants.
Pfizer said it and partner BioNTech have a significant amount of vaccine doses designed for the BA.1 variant ready and are already preparing to produce a large number of doses targeting BA.4 and BA.5 Omicron subvariants.
Pfizer said either could be ready for an early October rollout.
Multiple concerns raised during the public comment session
During the public comment session of the meeting, experts raised concerns that were largely ignored by the advisory panel.
Dr. Dustin Bryce, with Interest of Justice, said the FDA, Centers for Disease Control and Prevention (CDC) and the World Health Organization are “usurping Congress’ definition of a vaccine — which is any substance designed for the prevention of one or more disease.”
“FDA actually classifies mRNA as gene therapy, which they say is to treat or cure an existing disease by modifying your genes,” Bryce said. “Gene therapies are still being studied and are experimental at this time.”
Citing FDA documents, Bryce said gene therapy, unlike a vaccine, is so inherently unsafe the FDA says it requires 15 years of research to follow up on safety due to known risks of antibody-dependent enhancement, alteration of DNA and delayed adverse effects, such as cancer.
Bryce said:
“FDA says that gene therapy use in the mass population represents an unreasonable risk and they should limit the number of subjects who might be exposed to risk. We require due process and forbid the FDA from authorizing the proposed changes.
“We are demanding that EUA [Emergency Use Authorization] is promptly revoked because unreasonable risks are inherent in gene therapy products, as evidenced by large numbers of reports of adverse serious events linked to or suspected of being caused by an EUA product, product failure and product ineffectiveness.”
Bryce said COVID-19 vaccines fail to meet the requirements of EUA because not a single mRNA vaccine has been found to be effective for the prevention or treatment of an existing disease.
Michael Briskin pointed out in his public comment that the FDA receives approximately 75% of its budget from pharmaceutical companies, which he believes represents a conflict of interest.
Briskin challenged the use of the phrase “safe and effective” to describe COVID-19 vaccines, given the FDA has done no long-term testing to determine whether these products are safe.
Briskin presented data showing a significant rise in reported deaths among working-age Americans following COVID-19 vaccine mandates.
He said:
“In the short-term, 2021 was a very interesting year. We saw a stark increase [in death] among working-age adults from 18 to 64 and specifically in Q3 and into Q4, so something new for the working-age demographic partly through 2021 would be the clear correlation.
“With comparable trends in BLS [Bureau of Labor Statistics] data, children’s health insurance data, Israeli ambulance data, and of course we have the [Vaccine Adverse Event Reporting System (VAERS)] data — which the CDC tried to minimize but a recent FOIA [Freedom of Information Act] request forced them to reveal that they never once did the PRR calcification that was supposed to be their tool for spotting safety signals, according to their posted documents.”
“And what do we do when people get injured from these vaccines?” Briskin asked the panel. “We leave them in the mud.”
Briskin chastised the panel for authorizing boosters for infants two weeks earlier when data showed two doses weren’t effective and only 10 cases were used to assess efficacy.
“Three-quarters of the severe COVID in the trial was in the vaccine arm, as was the only hospitalization case which was accompanied by a seizure,” Briskin said. “And Moderna is so dangerous in young people Nordic countries won’t allow it to be used in anyone under the age of 30.”
Briskin said:
“In fact, the director of health of Denmark just admitted that vaccinating children was a mistake, whereas our officials only ever doubled down. And now we’re about to double down so hard we are about to lose the pretense of holding these pharmaceutical companies to any statistically meaningful regulatory standards for formula modification.
“For people following at home, what this agency is proposing is not just modifying the genetic code in the vaccine and the structure of the proteins produced to chase variants, but even things like doubling the microgram count for Pfizer — all without doing any statistically powered safety studies.”
“And to be clear,” Briskin added, “the companies we’re giving carte blanche to include Pfizer, the world’s largest criminal organization having paid the world’s largest criminal fine, and Moderna, which never made a safe product before we did away with long-term safety testing.”
Dr. Eric Feintuch, a chiropractor, asked the FDA if the agency knows how long mRNA from COVID-19 vaccines and the spike protein stay in the body, whether they know what the rate of protein production is and whether the FDA is aware of the consequences of the methylpseudouridine substitutions at the codon optimization step.
“For anyone on this panel who says it doesn’t go anywhere, tell me what proof you have of that,” Feintuch said, referring to the spike protein.
Feintuch said COVID-19 vaccines are associated with prion disease, noting 26 people have reported experiencing sudden onset of a severe and fatal brain disorder within one month of the second mRNA vaccine dose.
“This information needs to be researched and seen,” Feintuch said.
“A thousand peer-reviewed studies question the safety of COVID-19 vaccines. Doesn’t anyone see the safety signals? Is there anyone here who will stand up?” he asked. “Some of you know this, you need to stand up and you need to help us.”
Dr. David Wiseman, a research scientist with a background in pharmacy, pharmacology and experimental pathology, said VRBPAC is once again being asked to opine on inadequate information.
Wiseman said the FDA recently waived efficacy requirements for COVID-19 vaccines and has ignored its experts, notably Levy, who “has called for federal efforts to validate and standardize a correlate of protection.”
“Recent vaccine decisions were based on irrelevant Wuhan immunobridging,” Wiseman said. “Omicron assays are unvalidated and unverified by FDA.”
Wiseman said safety questions surrounding COVID-19 vaccines remain unanswered:
“We have shown correlations between vaccination and all-cause mortality. FDA says VAERS is under- and misreported. A FOIA disclosure reveals that CDC has not conducted safety signal analyses, which we have provided to FDA. Neurologic adverse events are finally being acknowledged [but there are] still no cancer studies.”
Wiseman further pointed out that FOIA requests show vital studies involving the spike protein have not been done:
“A Stanford study in [the journal] Cell showed vaccine message and antigen persisting for at least eight weeks. Does spike accumulate? Is this why myocarditis rates after boosting match or best primary series rates for some ages?
“Does spike persistence contribute to immune suppression, imprinting and negative efficacy? What is the toxicity of multiple doses? How will sameness of the manufacturing process be defined? Are the guidelines talking about monovalents or bivalents?”
Pfizer has dismissed concerns about the spike protein as “academic,” Wiseman said, “but it is certainly not.”
Booster formulation should be changed to combat waning efficacy, committee said
During the meeting, which occurred two weeks after the panel signed off on the primary COVID-19 vaccine series for the nation’s youngest children, a change in booster composition was deemed necessary due to waning effectiveness.
Dr. Mahesh Shenai, neurosurgeon and data analyst, said in a tweet:
“After many months of extolling benefits of vax and booster, now they are criticizing its efficacy and durability. . . to set the stage for a new updated booster!?”
In a briefing document published ahead of Tuesday’s meeting, FDA officials predicted a major COVID-19 outbreak will occur in the fall “due to the combination of waning immunity, further evolution of variants and increased indoor activity.”
A similar committee that advises the WHO recently suggested COVID-19 vaccines be reformulated to include both the original SARS-CoV-2 Wuhan variant and the first version of Omicron, BA.1 — although this variant has since been replaced by other strains of BA.4 and BA.5.
Moderna and Pfizer studied Omicron-specific vaccines in preparation for fall boosters, but efforts have been complicated by new subvariants.
If the government decides it wants a booster shot that targets BA.4 and BA.5 — two strains derived from the Omicron variant that are becoming dominant — vaccine manufacturers will have to race to produce the doses by fall, The New York Times reported.
Vaccines produced by Pfizer, Moderna, Novavax and Johnson & Johnson were developed against the original Wuhan COVID strain that emerged in 2019, but as the virus has rapidly evolved, these vaccines have become less effective.
COVID-19 vaccines target the spike protein the SARS-CoV-2 virus uses to invade human cells, but as the virus mutates away from the original strain, it has trouble “recognizing and attacking the spike,” CNBC reported. The Omicron variant has more than 30 mutations.
Marks said during the meeting he hopes changing the booster will “convince people to go get that booster,” adding the FDA plans to begin a booster campaign in October.
Megan Redshaw is a staff attorney for Children’s Health Defense and a reporter for The Defender.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.

or go to
Aletho News Archives – Video-Images
By Whitney Webb | MintPress News | May 17, 2019
NEW YORK — For nearly two decades, one of the most overlooked and little known arrests made in the aftermath of the September 11 attacks was that of the so-called “High Fivers,” or the “Dancing Israelis.” However, new information released by the FBI on May 7 has brought fresh scrutiny to the possibility that the “Dancing Israelis,” at least two of whom were known Mossad operatives, had prior knowledge of the attacks on the World Trade Center. … continue
 Aletho News If Americans Knew No Tricks Zone

