ARE BOOSTERS MAKING PEOPLE VULNERABLE TO COVID?
Newly released science is showing that the booster may increase your risk of catching COVID-19. Immune exhaustion and confusion may be to blame.
By Dr. Joseph Mercola | May 26, 2022
Well, the COVID jab pushers have had to resort to all sorts of obfuscation to hide the fact that the injections don’t work, and now they’re really scraping the bottom of the barrel of excuses. According to a recent Reuters report,1 “Increased contact among vaccinated people can give the false impression that COVID-19 vaccines are not working.”
This irrational explanation has been levied in response to studies showing COVID-jabbed individuals are getting infected at higher rates than the unjabbed, and there are many such studies.
“These studies are likely to involve statistical errors, particularly if they did not account for different contact patterns among vaccinated versus unvaccinated people,” Korryn Bodner, a research associate in infectious disease modeling in Toronto, told Reuters. Bodner is the first author of a preprint study2 posted on medRxiv at the end of April 2022.
Are the Jabbed More Carefree Than the Unvaxxed?
Bodner’s claim is that those who got the jab may be more likely to throw caution to the wind and mingle with others, hence getting infected more frequently, while the unjabbed may be more cautious because they know they’re vulnerable. This rationale is dubious at best, considering:
a)The unvaccinated have continuously been accused of not taking COVID seriously and going about their lives as normal
b)Those who have taken the jab are, by and large, a far more fearful lot; they tend to listen to the “authorities” and take all of their advice to heart, which would include avoiding large gatherings and close one-on-one interactions without wearing a face mask
Check out the following story, reported by Anchorage Daily News :3
“Arianne Bennett recalled her husband, Scott Bennett, saying, ‘But I’m vaxxed. But I’m vaxxed,’ from the Washington hospital bed where he struggled to fight off COVID-19 this winter … Bennett went to get his booster in early December after returning to Washington from a lodge he owned in the Poconos, where he and his wife hunkered down for fall.
Just a few days after his shot, Bennett began experiencing COVID-19 symptoms, meaning he was probably exposed before the extra dose of immunity could kick in. His wife suspects he was infected at a dinner where he and his server were unmasked at times …
‘He was absolutely shocked. He did not expect to be sick. He really thought he was safe,’ Arianne Bennett recalled. ‘And I’m like, ‘But baby, you’ve got to wear the mask all the time. All the time. Up over your nose.'”
Within days of his third dose, he got a serious case of COVID. Yet they blame it on hypothetical exposure to an apparently healthy food server. This kind of irrational reasoning is prevalent among those who got the jabs and who keep going back for more as they are part of the 30% of the population that have been completely brainwashed.
To reiterate what I’ve explained since 2020, asymptomatic spread is likely to be so rare as to be nonexistent.4 It was a lie perpetuated to drive up fear and prop up rising “case” rates that didn’t really exist. It’s basic virology that you cannot transmit a virus unless you have a “hot” infection, and if you have an active, transmissible infection, you have symptoms. The symptoms are a sign that your body’s defenses are kicking in to rid itself of the live virus.
No symptoms, no transmission. So, unless the server was feeling sick and went to work anyway, the simplest explanation for Bennett’s demise was the shot itself. And if the server was sick, the fact that Bennett got so ill suggests the shot is ineffective, even at two doses.
The pro-pharma shills want you to believe there are so many confounding variables, we can’t possibly draw any conclusions from data showing the shots don’t work. Yet looking at data from a wide spectrum of sources, all show the same alarming trends. What “confounding factor” could possibly account for ALL of them being misinterpreted?
An Unproven Hypothesis
Reuters 5 does note that Bodner’s simulations “do not prove that this type of bias affected studies of vaccine effectiveness versus the Omicron variant.” What it does show, according to Bodner, is that “even if vaccines work, increased contact among vaccinated persons can lead to the appearance of the vaccine not working.”
In other words, this is a hypothesis that has yet to be proven. Her modeling suggests it COULD make the jabs appear ineffective IF those who got the jab actually behave very differently from the unjabbed.
But again, it’s highly unlikely that the unvaccinated are avoiding exposure by steering clear of close contacts and crowds to a greater degree than those who got the jab. It’s far more reasonable to suspect that the shots don’t work.
On a side note, Bodner’s study was funded by the Canada COVID-19 Immunity Task Force.6 This task force is housed at McGill University in Montreal, Canada, and McGill University is a long-term recipient of grants from the Bill & Melinda Gates Foundation.7,8,9,10
What Do the Data Say About COVID Jab Effectiveness?
Based on data from around the world, it seems clear that the COVID gene transfer injections are not working. In fact, they’re having the opposite effect of what you’d expect from a real vaccine. According to a Washington Post analysis of state and federal data,11 in September 2021, when Delta was most prominent, 23% of those who died from COVID in the U.S. had received the jab.
In January and February 2022, when Omicron started dominating, that percentage jumped to 42%. In December 2021 and January 2022, just under half of all the COVID patients in intensive care at Kaiser Permanente’s hospital system in Northern California had also received one or more shots.12
Many argue that Omicron was more contagious than Delta, hence the higher death toll. But Omicron was also far milder than Delta, so why would the jabbed die at a higher rate from a less lethal variant than a more lethal one?
One attempt at an explanation is that the fatalities are now occurring primarily among the elderly. Nearly two-thirds of those who died from COVID during the Omicron wave were 75 and older. During the Delta wave, 75-year-olds and older accounted for just one-third of the deaths.13
But that was the case from the beginning, and it still doesn’t answer the question: Why would old people be more likely to die from a milder virus than a more serious one? To answer that question, the injection pushers revert back to the argument of waning potency. Two-thirds of those who died in January and February 2022 did not have a booster shot. According to Anchorage Daily News :14
“Experts say the rising number of vaccinated people dying should not cause panic in those who got shots, the vast majority of whom will survive infections. Instead, they say, these deaths serve as a reminder that vaccines are not foolproof and that those in high-risk groups should consider getting boosted and taking extra precautions during surges.”
So, in other words, the jab only works for a handful of months, and then you have to take another. And another. And another. According to the U.S. Centers for Disease Control and Prevention,15 the first two doses wear off after five months, necessitating a third dose, and the third dose wears off in just four months, at which time you’re supposed to get dose No. 4.
Israeli data16 show the effectiveness of shot No. 4 in preventing severe disease declines by 56% in just seven weeks. So, it appears the protection you get from the shots keeps getting shorter with each dose. Meanwhile, data show the shots can render you increasingly susceptible to all manner of infection and disease, through a wide variety of mechanisms.
Moderna Trial Data Reveal Repeated Infections Are Likely
Among such data is a preprint study17 posted on medRxiv April 19, 2022, which found adult participants in Moderna’s COVID jab trial who got the real injection, and later got a breakthrough infection, did not generate antibodies against the nucleocapsid — a key component of the virus — as frequently as did those in the placebo arm.
Curiously, placebo recipients produced anti-nucleocapsid antibodies twice as often as those who got the Moderna shot, and their anti-nucleocapsid response was larger regardless of the viral load. As a result of this reduced antibody response, those who got the jab may be more prone to repeated COVID infections. As reported by The Defender :18
“[T]he authors found that using the presence of anti-nucleocapsid (anti-N) antibodies to determine whether a person was exposed to SARS-CoV-2 will miss some infections. Thus, the sensitivity of this kind of test, when applied to vaccinated individuals, is not ideal.
However, there are more important implications19,20 of these findings … Specifically, the study implies that the reduced ability of a vaccinated individual to produce antibodies to other portions of the virus may lead to a greater risk of future infections in the vaccinated compared to the unvaccinated.
It is important to note that this is not just another argument for the superiority of natural immunity. Rather, this is evidence suggesting that even after a vaccinated person has a breakthrough infection, that individual still does not acquire the same level of protection against subsequent exposures that an unvaccinated person acquires.
This is a troubling finding, and something investigators conducting the Moderna vaccine trial likely knew in 2020.”
UK Data Confirm Results
These findings are corroborated by data from the U.K. Health Security Agency. It publishes weekly COVID-19 vaccine surveillance data, including anti-nucleocapsid antibody levels. The report21 for Week 13, issued March 31, 2022, shows that COVID-jabbed individuals with breakthrough infections have lower levels of these antibodies — a finding they attributed to the protective benefit of the shot:
“These lower anti N responses in individuals with breakthrough infections (post-vaccination) compared to primary infections likely reflect the shorter and milder infections in these patients.”
However, this interpretation is likely flawed, because less severe infection is associated with lower viral load, and as the study above demonstrated, the “vaccinated” have lower anti-nucleocapsid antibody levels than the unvaccinated at all viral load levels, but especially so at the lowest viral loads. As noted by The Defender :22
“This is one of the most significant findings of the study because it overturns the heretofore unchallenged idea that decreased seroconversion in the vaccinated is due to less severe infection in this population — which is a benefit provided by the vaccine.
However, this new study shows that even at low viral loads, the unvaccinated are more likely to seroconvert than those who are vaccinated. In fact, the difference in seroconversion rates is the greatest at lowest viral loads. The decrease in conversion rates is not a result of a benefit from the vaccine. It is a consequence of it.”
Boosted Now Have Three to Four Times Higher Case Rates
The Defender also reviews other U.K. data showing the COVID case rate is three to four times higher among those who have received a booster shot, compared to the unvaccinated. This is true for all age groups with the exception of children under 18:23
“What could explain such a large increase in infection rates among the boosted? Interestingly, the authors … warn that the unvaccinated may have contracted COVID-19 prior to the observation period — in other words, they may have acquired natural immunity previously, giving them added protection …
But their own data tells the opposite story. The boosted are more likely to contract the disease — by a factor of 3 to 4. How do we know whether the larger infection rates in the boosted are due to more robust immunity in the unvaccinated because of prior infection or due to an immune deficiency in the boosted?
The question can be definitively answered by examining the trend of infection rates [using] … the equivalent table from two months earlier. There is still a greater infection rate among the boosted, but it is only two to three times higher. If the authors’ hypothesis was correct, the more recent data should have shown less of a difference, not more.
If anything, their data support the finding that the decreased seroconversion rates in the vaccinated may be causing a greater risk of repeated infections.”
Walgreens’ Data
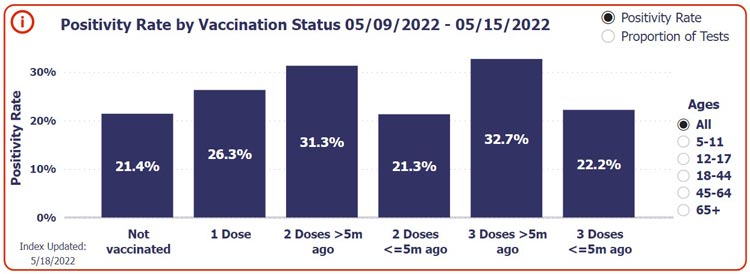
Data from the pharmacy chain Walgreens in the U.S. also reveal the same trend — COVID-jabbed individuals are testing positive for COVID at higher rates than the unjabbed, and those who got their last shot five months or more ago have the highest risk.
As you can see in the screenshot from Walgreens’ COVID-19 tracker24 below, during the week of May 9 through 15, 2022, 21.4% of unvaccinated individuals who got tested for COVID got a positive result. Of those who had gotten just one COVID shot, the positivity rate was 26.3%.
Of those who received two doses five months or more ago, 31.3% tested positive, and of those who received a third dose five months or more ago, the positive rate was 32.7%. So, after the first booster shot (the third dose), people are at greatest risk of testing positive for COVID.
Risk-Benefit Analyses
We also have the benefit of more than one risk-benefit analysis, and all show that, with very few exceptions, the COVID jabs do more harm than good. A risk-benefit analysis27 by Stephanie Seneff, Ph.D., and independent researcher Kathy Dopp, published in mid-February 2022, concluded that the COVID jab is deadlier than COVID-19 itself for anyone under the age of 80.
Another analysis,28 which relied on data in the U.S. Vaccine Adverse Events Reporting System (VAERS), concluded that in those under age 18, the shots only increase the risk of death from COVID, and there’s no point at which the shot can prevent a single COVID death, no matter how many are vaccinated.
If you’re under 18, you’re a shocking 51 times more likely to die from the jab than you are to die from COVID if not vaccinated. In the 18 to 29 age range, the shot will kill 16 for every person it saves from dying from COVID, and in the 30 to 39 age range, the expected number of vaccine fatalities to prevent a single COVID death is 15. Only when you get into the 60 and older categories do the risks between the jab and COVID infection even out.
A third risk-benefit analysis by researchers in Germany and The Netherlands was published in June 2021, in the journal Vaccines.29 The paper caused such an uproar, part of the editorial board resigned in protest.30 The journal retracted the paper, but after a thorough re-review, it was republished in the August 2021 issue of Science, Public Health Policy and the Law.31
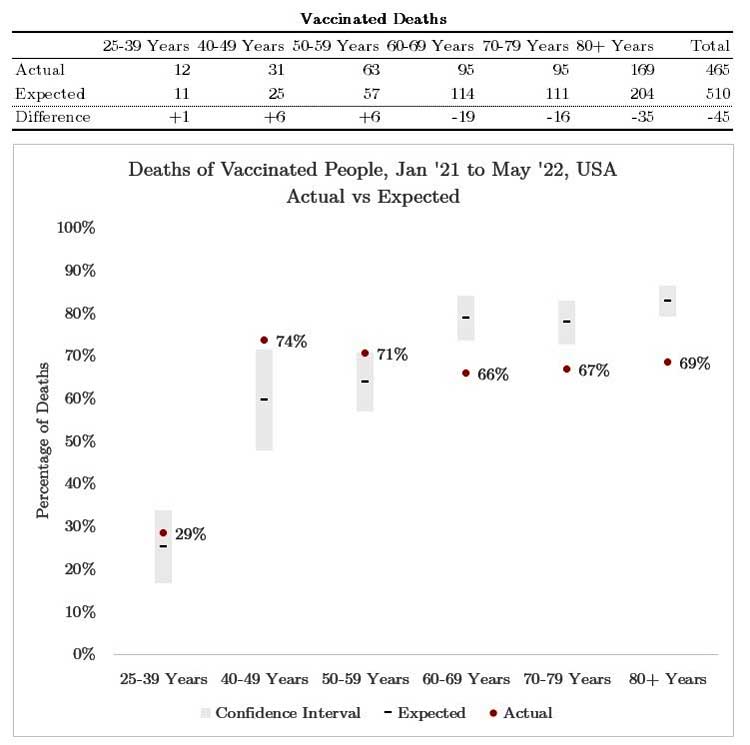
These researchers concluded that, “as we vaccinate 100 000 persons, we might save five lives but risk two to four deaths.”32 A fourth, still preliminary, analysis — based on more than 1,700 death reports collected by Steve Kirsch — shows the shots do more harm than good in anyone under age 60. Kirsch writes:33
“Figure 1 below is an analysis of survey data I collected. The analysis shows that the vaccines are harmful to those under 60. The red dots higher than the error bar means more vaccinated people observed dead than expected based on the population of vaccinated to all people.
In other words, if we vaccinated 60% of people (middle of the grey bar) and 70% (red dot) of the deaths are vaccinated, we have a serious problem. The precautionary principle of medicine suggests if you are under 60 and thinking of taking a vaccine, you shouldn’t. These preliminary results are both statistically significant …
The conclusion is very clear: nobody under 60 years old should get the vaccine because there is no evidence of a benefit. In fact, if you are between 40-60, it’s clear that vaccination makes it more likely you’ll die, not less likely.”
While some analyses present a direr picture than others, taken together, it’s clear that there appears to be no long term benefits to the COVID jabs. We’re consistently ending up with a higher cost than can conceivably be considered reasonable. The pro-pharma side will likely continue to lob flimsy excuses at the data, but at some point, the truth will be so clear that even the blind will see it. Until that day, continue to inform yourself and share what you find.
Sources and References

By Mark Shaw | The Daily Sceptic | May 25, 2022
“Let’s move on please, there are more important things to deal with.” This is what we often hear in relation to ‘partygate’. I don’t think sceptics are in such a hurry. We all want to move on in life but that is not easily achieved when we have been misinformed, taken for a ride and then taken to the cleaners.
The sceptics aren’t just Daily Sceptic readers but a growing number of the public who are seeing that much of the media have not delivered a full, honest account in reporting the last two years of pandemic restrictions and enforced medical interventions. What I find interesting is that, in much of the media’s eagerness to see the downfall of Boris Johnson, everyone is getting to see a little more of the ‘bigger picture’ the media have, up until now, been trying to hide. How could those enforcing all those ridiculous mandates be indulging in so many parties and social mixing if Covid was such a deadly disease? Why were so many coerced into a trial vaccination programme for a disease that evidently poses so little threat to them?
How we have been deceived! Yet much of the media focus on the minor detail of whether a particular event was a party, what certain photos show, whether Boris Johnson actually knew he was attending a party, whether he should have received more fines etc. They want to know if there is enough evidence to show that the PM misled Parliament because convention dictates that, if that were the case, he should resign – the big news story. The news story for me is whether the Government misled the public, not Parliament.
The scandal that lies before us is one demonstrating how those in power, who determined the rules and directed the hardships of the last two years, are more concerned about themselves and whether they have misled their colleagues than us plebs. The deception has severely affected many of us, the younger generation in particular. There are now increased hospital waiting lists, deaths from delayed cancer diagnosis and treatment and rampant economic inflation – true wrongs that deserve more than a token fine. It is this mendacity and betrayal that have consequences and will continue, possibly for decades, to have grave ramifications from which some may never be able to ‘move on’.
Dr. Mark Shaw is a retired dentist.
Especially the 2nd by Yahi et al; shows the non-neutralizing Abs bind to the virus spike, and enhances infectiousness of virus.
Binds but does not neutralize the virus; “Infection-enhancing anti-SARS-CoV-2 antibodies recognize both the original Wuhan/D614G strain and Delta variants. A potential risk for mass vaccination?”
Dr. Paul Alexander | May 10, 2022
Yahi et al.: so it is the binding to the virus by non-neutralizing Abs that do not eliminate the virus but increases infectiousness… it enhances the infection capability and explains why the vaccinated are getting infected; the non-neutralizing Abs bind to the virus in the upper respiratory tract and drive infection yet binds to the lower respiratory tract and prevents severe disease. This study shows original antigenic sin and ADE…
“our data suggest that the balance between neutralizing and facilitating antibodies in vaccinated individuals is in favor of neutralization for the original Wuhan/D614G strain. However, in the case of the Delta variant, neutralizing antibodies have a decreased affinity for the spike protein, whereas facilitating antibodies display a strikingly increased affinity. Thus, ADE may be a concern for people receiving vaccines based on the original Wuhan strain spike sequence (either mRNA or viral vectors).”
1)Van Egeren et al.: “Risk of rapid evolutionary escape from biomedical interventions targeting SARS-CoV-2 spike protein”
3)An infectivity-enhancing site on the SARS-CoV-2 spike protein targeted by antibodies
4)Lectins enhance SARS-CoV-2 infection and influence neutralizing antibodies
5)Structural insight into SARS-CoV-2 neutralizing antibodies and modulation of syncytia
6)The emergence and ongoing convergent evolution of the SARS-CoV-2 N501Y lineages
By Tyler Durden | Zero Hedge | May 24, 2022
Moderna CEO Stéphane Bancel is complaining about having to ‘throw away’ 30 million doses of Covid-19 vaccine because ‘nobody wants them.’
“It’s sad to say, I’m in the process of throwing 30 million doses in the garbage because nobody wants them. We have a big demand problem,” Bancel told an audience at the World Economic Forum, adding that attempts to contact various governments to see if anyone wants to pick up the slack was a total fail.
“We right now have governments – we tried to contact … through the embassies in Washington. Every country, and nobody wants to take them.”
“The issue in many countries is that people don’t want vaccines.”
Bancel’s comments come days after Bloomberg reported that EU health officials want to amend contracts with Pfizer and other vaccine makers in order to reduce supplies.
During a virtual meeting organized by Polish Health Minister Adam Niedzielski, governments shared a joint letter to the EU Commission which reads: “We hope that the discussion with the commission and among member states will allow flexibility in the vaccine agreements,” adding “We are also counting on vaccine producers to show understanding to the exceptional challenges that Poland is facing supporting Ukraine and giving shelter to millions of Ukrainian citizens fleeing the war.”
Some countries are seeking to amend so-called advanced purchase agreements signed with producers, as demand for shots wanes and budgets come under strain from the fallout of the war in Ukraine and the costs of accommodating refugees.
Adjusting deals with suppliers could grant member states the right to “re-phase, suspend or cancel altogether vaccine deliveries with short shelf life,” Estonia, Latvia and Lithuania’s prime ministers wrote in a joint letter to Commission President Ursula Von Der Leyen late last month.
Meanwhile, in a separate letter the health ministry of Bulgaria called for an “open dialog” with the commission and pharmaceutical companies, arguing that the current arrangement forces member states to “purchase quantities of vaccines they don’t need.”
Amazing Polly | May 23, 2022
I cover the US’s leading Orthopox Virus researcher who conducted at least 2 rounds of gain of function research on viruses related to smallpox. Other revelations about bio-terror ‘research’ in here too. Support my work: https://amazingpolly.net/contact-support.php THANKS! References below.
NYT Mousepox Gain of Function: https://www.nytimes.com/2003/11/01/us/bioterror-researchers-build-a-more-lethal-mousepox.html
Buller Says Vaccine for Monkeypox (using smallpox vax) NOT recommended: https://pubmed.ncbi.nlm.nih.gov/17661673
Buller paper on Monkeypox Outbreaks up to 2012: https://pubmed.ncbi.nlm.nih.gov/23626656/
Judicial Watch re James Leduc / Wuhan: https://www.judicialwatch.org/wuhan-lab-fauci-grants/
National Biocontainment Training Center report by Leduc: https://apps.dtic.mil/sti/pdfs/AD1022067.pdf
By Carla Peeters | Brownstone Institute | May 23, 2022
The number of previously healthy children younger than 16 years of age with mysterious hepatitis cases have doubled in two weeks to 450 cases worldwide, including 11 deaths. Most cases have been reported in the UK (160) and the US (currently, 180). In Europe most cases are found in Italy (35) and Spain (22). Over 8-14% of the patients needed liver transplantation. These children will be on lifelong medication. Until now the real cause of a sudden spark in hepatitis is not clear.
Although 50-72% of the cases tested positive with a PCR test for Adenovirus, tissue and liver samples taken in the UK do not show any typical features that might be expected with a liver inflammation due to this virus.
In the UK, 18% of the reported cases tested positive for SARS-CoV-2 virus and three cases had tested positive 8 weeks prior to admission. The most plausible cause of hepatitis traces to a viral origin. Brodin and Aditi hypothesize a SARS-CoV-2 superantigen mediated immune activation in an Adenovirus-sensitized host.
At this point many of the children with hepatitis are too young to be eligible for COVID-19 vaccination. So far, no common environmental exposure has been found.
Jaundice is characteristic for all children with hepatitis, which could have many reasons including toxins and malnutrition. A search into the peer-reviewed scientific literature on the toxicology of nanoparticles, microplastics, disinfectants and hypercapnia/hypoxia, children have been extensively exposed to during the pandemic makes bio corona formation and accumulation of toxic substances a reasonable explanation for disruption of the liver homeostasis.
The capacity for excessive activation of liver inflammatory pathways has been described for these materials prior to the pandemic. Effects of the complex mixture of these materials and associated chemical pollutants presented have not yet been assessed. Understanding how these materials interact with its biological surroundings during long-term and frequent exposure is of utmost importance.
Pandemic Measures and Liver Toxicity
Early in the pandemic several researchers warned of the unsafe use of facemasks, tests, and disinfectants and their weakening effect on the immune system. Many institutions are starting research on harmful chemicals due to air pollution as they pose a known threat to public health and the economy, representing 10% of global GDP in health costs and 3.75 billion lost working days at the global level in 2060.
Unfortunately, almost no funded research has been started in the area of the safe, cost/benefit use of the mandates. Instead, during the pandemic large amounts of money were spent on less urgent research on non-pandemic related issues.
While Covid-19 was originally thought to be a respiratory infection, various research papers have indicated myocardial inflammation, hepatitis, or neurological experiences independent of severity of Covid-19 and sometimes without evidence of a viral infection. Other researchers found that cardiac damage was more related to clotting and microthrombi were frequent. Almost 25% of people hospitalized develop myocardial injury and many develop arrhythmias or thromboembolic disease.
Lockdowns, with many people experiencing an ongoing state of fear and anxiety and frequent exposure to nanoparticles, microplastics, high CO2 exposure and toxic substances impaired the innate immune system even more.
Furthermore, several studies have indicated a remarkable suppression of the innate immune system after injections with PEGylated lipid nanoparticle (LNP) modified mRNA vaccines. In vivo studies for cytotoxicity and genotoxicity of these vaccines, prior to their release under EUA and being mandated for many people and children, have been neglected.
Unfortunately, more than two years into the pandemic an alarming stage of mysterious rises in infectious and noncommunicable diseases and sudden non-Covid deaths have been reported, even neonatal deaths. The Observer reported one in three people in the UK are experiencing long-term illness.
The Liver Is an Immune Surveillance System
The liver is an important organ responsible for the storage, synthesis, metabolism and redistribution of carbohydrates, fats and vitamins and numerous essential proteins. It is the main detoxification center of the body. A most important organ for generating an effective innate immune response and covering a robust and long-lasting immunity, it works to keep virus, bacteria and excessive inflammations in check.
About 30% of the total blood passes through the liver every minute and is scanned by the mononuclear phagocytic system (MPS) in the liver. The microenvironment in the liver shapes and functions the antigen specific CD4+ T cell population with the capacity for longevity/self-renewal for more than a decade.
High amounts of CD8, Natural Killer T cells, dendritic cells and macrophages (Kupfer cells) in the liver play an important role in the protective innate immune system during injury and infection deciding for tolerance or excessive inflammation. Specific liver cells, hepatocytes, produce 80-90% of the circulating innate immunity proteins in the body including acute phase proteins, complement, bactericidal proteins and more.
Neutrophils, the most abundant leukocytes in the blood, present in the liver perform important functions in inflammation and act as a functional bridge between the innate and adaptive immunity (B cells and T cells) activating antigen specific immune responses.
Homeostatic inflammation is a normal part of a healthy liver. In the complex microenvironment of the liver, the hepatic immune system tolerates harmless molecules while at the same time remaining alert to possible infectious agents, malignant cells or tissue damage. Inflammatory processes are required to rid itself of pathogens, cancer cells or toxic products of metabolic activity. The inflammatory processes are intimately linked to mechanisms that resolve inflammation and promote tissue regeneration.
Excessive and dysregulated inflammatory activity are key drivers of liver pathology, associated with systemic inflammation: chronic infection, autoimmunity and cancer. Mechanisms to resolve liver inflammation are essential to maintain local organ and systemic homeostasis. It is the balance between activation and tolerance that characterizes the liver as a frontline immunological organ. Disrupting this precious surveillance system increases the risk for severe disease and death.
Immune-Liver Disruptors
A possible role of the pandemic measures in excessive inflammation in the human body by immune-liver disruptors is realistic. Independently they may each cause problems of the liver. Serious drawbacks of the measures have become most visible in children, the obese and immunocompromised and the poor.
Nanoparticles (i.e. inhaled graphene oxide, titanium dioxide, Ag from facemasks or swabs) present in the body are cleared from the blood and will preferentially accumulate and sequester in the liver, up to 30-99% from those present in the blood and at much higher quantities as compared to other organs.
Studies in recent years have shown that nanomaterials can modulate and activate neutrophils and other immune cells. Nanomaterials may be considered as a particular case of danger signals that are able to trigger sterile inflammatory responses. Rapid accumulation of nanoparticles in the resident liver macrophages can change the expression of anti-inflammatory genes. Changes of genes related to detoxification and cell cycle have been observed.
Systematically administered nanoparticles may directly interact with circulating erythrocytes leading to erythrocyte aggregation and or hemolysis that is accompanied by hemoglobin release. Surface properties of the nanoparticles are known to play a critical role in nanoparticle-erythrocyte interaction. Most nanoparticles have been known to activate complements by either themselves or through serum proteins. Activation of complements and complement activation pathways could further promote tumor growth.
Nanoparticles develop a specific bio-corona comprising complex and dynamic layers of biomolecules that endow nanoparticles with a new immunological identity.
Studies on polystyrene microplastics (which can be present in facemasks and swabs) showed hepatotoxicity and dysregulation of the lipid metabolism, causing oxidative stress and inflammatory responses. This implicated a potential risk for liver steatosis, fibrosis and cancer and macrophage foam cell formation, a characteristic feature observed during atherosclerosis posing a serious threat to human health.
Another study demonstrated that fish exposed to a mixture of polyethylene with chemical pollutants bioaccumulate the chemical pollutants and suffer liver toxicity and pathology. Moreover 0.1 um microplastics could enter hepatocytes from circulation and result in liver damage even at a low concentration.
Microplastic exposure could induce DNA damage in both nucleus and mitochondria indicating a potential risk of hepatotoxicity and fibrosis. Microplastics are found in the human blood of 80 % of the people tested, in deep lung tissues and human feces.
Covid-19 mRNA vaccines use Acuitas’ PEG (Poly Ethylene Glycol) ylated lipid nanoparticles (LNP). The PEGylated lipids support prolonged circulation and shield the highly inflammatory and cytotoxic effects of the cationic lipids used. If insufficiently shielded by PEG they have been shown to mediate aggregation and interact with and damage the membranes of erythrocytes resulting in hemolysis. PEG content, surface density and conformation of the nanoparticle influence the binding of proteins to a bio corona and the uptake by immune cells.
Despite achieving high dense surface coatings of PEG, no NP formulation has been developed that can completely resist interaction with blood components. Of concern is that 22-25% of individuals who were never exposed to PEGylated therapeutics were found to have PEG antibodies, which is more than two decades ago. PEG coating can improve the penetration of biological barriers including reducing interactions with tissue extracellular matrix cellular barriers and biological fluids such as mucus leading to improved delivery.
After injection of Moderna LNP very low levels could be detected in the brain, potentially indicating that the mRNA LNP could cross the blood brain barrier and reach the Central Nervous System (CNS). Unfortunately, the potential inflammatory nature of these LNPs was not assessed.
In preclinical studies a strong induction of adaptive immune responses by CD4+ T-cell activation and protective humoral immune responses was found. The synthetic ionizable lipid is speculated to have approximately 20-30 days of half-life in humans. It has been shown that plasma protein absorption occurs very rapidly and that it affects hemolysis, thrombocyte activation, cellular uptake and endothelial cell death. The bio corona formation of the PEGylated nanoparticle may change over time.
The increasing number of side effects and reported high potency for eliciting antibody response may partially stem from the LNP’s highly inflammatory nature characterized by leukocyte infiltration and activation of different inflammatory cytokines and chemokines. Antigen-presenting cells presenting vaccine derived peptides/protein might cause tissue damage and exacerbate side effects, which have been linked to autoimmune diseases.
More severe and systemic side effects after the booster shot might be related to an amplification effect of the adaptive immune response induced by the vaccine resulting in high antibody responses. Neutrophils were found to preferentially internalize PEGylated particles in the presence of human plasma. Also, further studies of complement activation in relation to PEG nanoparticles merit rigorous evaluation for immune safe materials. Observational studies found a greater risk for complications following a positive SARS-CoV-2 test. A study of the University of Lund has indicated by in vitro studies that the BNT162b2mRNA vaccine has a fast take-up into human liver cells. In 6 hours of exposure the RNA was reverse transcribed into DNA.
Sennef et al. describes the disruption of the innate immune system by the Covid-19 mRNA vaccines caused by an impaired interferon signaling, release of large amounts of exosomes containing Spike protein, potential disturbances in regulatory control of protein synthesis and cancer surveillance of and their potential direct link to liver disease (with over 2,000 reports in VAERS December 2021) and other inflammatory diseases. The presence of Spike protein has been detected in the blood and 60 days after mRNA vaccine injection in the lymph nodes.
A functional reprogramming of the innate immune responses after BNT 162b2 injection was also observed by Fohse et al. with a lower response of innate immune cells, while the fungi-induced cytokine responses were stronger. A study on Biovrix by Nguyen et al. demonstrated an impaired lipid metabolism and increased lipotoxicity by the Spike protein. Jiang et al observed that the Spike protein localizes in the nucleus and inhibits DNA damage repair by impeding key DNA repair protein recruitment to a damaged site. A mechanism by which the spike protein might impede the adaptive immunity explaining the potential side effects. Suraswaki et al. stated that the virus itself may dysregulate the innate cellular defenses using various structural and nonstructural proteins.
Taking Back Control of Our Bodies
The European Commission Statement from May 12, 2022, announces to shorten (from 300 to 100 days) the product to market cycle to develop safe and effective vaccines, therapeutics, and diagnostics following the identification of new threats and work to make them widely available.
As discussed, the Covid-19 pandemic measures have shown to be far from safe. All materials are known to interact and bind proteins forming bio corona’s depleting the body of essentials for processes to function properly.
Subtle changes in materials and biological fluids of persons can significantly change the protein composition of the bio corona and can either lead to an excessive inflammation or resilient homeostasis. Especially in children who need more proteins, vitamins and minerals for mental, physical, and immune system development, the accumulation of toxic substances in the liver and formation of bio corona can be a serious threat to health.
At this stage, it is not known whether the mysterious rises in diseases are caused by a virus or an intoxication and/or depletion of essentials that result in impaired signaling routes. The Covid-19 routine diagnostic tests used for mass testing have major flaws which make it impossible to ensure the presence of an infectious virus as a single cause of symptoms.
An increasing number of doctors and researchers agree: the pandemic is over. All pandemic measures need to be halted immediately. The highest priority is lifting the mandates for children. Healthy children always had a very low risk for severe Covid-19 and are protected by a strong robust and long-lasting natural immunity. There is no added value to vaccinate any person with natural immunity. Moreover, the risk for side effects of the mRNA vaccine for children is high. mRNA Covid vaccine accumulates in the liver 30 minutes after it is injected.
Deep investigations on quality, reproducibility and contaminations of the materials of personal protective equipment, facemasks, tests, disinfectants and vaccines, being used with their effects on the human body and the environmental ecosystem need to be prioritized and funded.
During the past two years, the immune system of many people has been harmed and even broken. We need programs to regenerate the liver and immune system so people can face with trust and confidence any possible wave of virus attacks.
Carla Peeters is founder and managing director of COBALA Good Care Feels Better. She obtained a PhD in Immunology from the Medical Faculty of Utrecht, studied Molecular Sciences at Wageningen University and Research, and followed a four-year course in Higher Nature Scientific Education with a specialization in medical laboratory diagnostics and research. She studied at various business schools including London Business School, INSEAD and Nyenrode Business School.

By Richard Hugus | May 23, 2022
The picture above is of a sign outside a performing arts theater in Santa Barbara, California. Looks like everyone is welcome. Well, not really. It turns out that if you’re not “vaccinated” you’re not welcome. If you haven’t arrived at the ticket booth with ID and proof of being injected with two doses of an emergency use experimental gene treatment for “covid 19” — a treatment which has no efficacy and is associated with millions of serious injuries and deaths — this #LoveForAll message doesn’t actually apply to you. If you’re not “vaccinated” the only way you can get into the theater now is if you have taken a test proving you don’t have the plague. Don’t want a PCR swab up your nose? Too late for an antigen test? Tough luck. This rainbow venue welcomes EVERYONE, except for carriers of the plague.
“Who doesn’t love LOVE?” Apparently, the state of North Carolina doesn’t. The founder of Insist On Love For All which makes and sells the $60 sign displayed above, took a trip to Asheville, North Carolina a few years ago and was impressed by signs “embracing diversity.” Says Insist On Love’s founder,
shop owners started displaying these signs over two years ago [2018] to encourage tourism following the passage of the controversial House Bill 2 in North Carolina, which requires certain public bathrooms to be designated for use by males or females based on their biological sex. “The signs in Asheville moved me. Love is the only weapon we can use to fight hate . . . “
In this case, “hate” was displayed by 1) the idea that men and women should have separate bathrooms, 2) the idea that men (or men who think they’re women) don’t have a right to walk into women’s bathrooms, and vice versa, 3) the fact that other sexes besides male and female have not been acknowledged, and 4) the fact that the state of North Carolina thus discriminated against all those who don’t have male/female privilege. There is also the ‘hate’ involved in the unwillingness of North Carolina to provide separate bathrooms for a theoretically unlimited number of other genders. Unless #LoveForAll is somehow a front for a consortium of plumbing supply companies (this would actually be comforting news), there is nothing left for us to conclude but that ‘love’, as the term is being used here, is indeed a weapon, not to fight hate, but to fight reason. ‘Love’ is now a buzzword in a well-established “diversity and inclusion” narrative sent down from academic critical theory to the progressive left to the mainstream media to the culture at large. Has there ever been a time when good things have been so twisted into their opposite? This is not about love or inclusion. This is shallow virtue signaling by people who have been swallowed up by a political machine designed to turn cultural norms upside down, not for the purpose of bringing needed change, but for the purpose of creating chaos and a loss of rationality, after which new supposed norms can just be lifted into place.
“All sexual orientations”, cited in the sign, is also a topic at the current May 22-28 Davos forum, where “resilience through equity” and “inclusivity” for the “LGBTQI+ community” is on the formal agenda. Do the corporate bosses, social engineers, and preening politicians at this forum really care about equality, or are they just using the brand to create the upheaval necessary to bring in fantastic profits and power? The answer is obvious. The agenda is exclusion, not inclusion; fascism, not liberalism. Their plan is for the majority of humanity, gay or straight, to be excluded from their rights, autonomy, and independence, while the bosses enjoy their wealth and slave labor. Like #LoveForAll, everyone is welcome in the Great Reset except those who believe there are only two sexes — that is, just about everybody since the beginning of human history. Everyone is welcome in virtue-signaling countries, corporations, and institutions except those who choose not to accept a medical intervention also never heard of before in human history — that of altering the human genome on the pretext of defeating a virus. In other words, everyone is welcome except those who have chosen not to go insane. The insanity is called wokeness. Wokeness is nothing but a tool being used to effect a very ugly and very ambitious power grab. When the job is done, everyone duped into thinking they were fighting for the victims of oppression and equality for all will be swatted away like flies.
The would-be gods at Davos brought us their own version of the Apocalypse — plague, war, famine, and death became covid, Ukraine, food shortages, and vaccines. Do such people even remotely care about racial prejudice and gender dysphoria? No. They either massively exploited or completely made up these issues to create disorder. Indeed, their eugenicist predecessors had certain, ahem, opinions about people with disabilities, sexual deviants, and racial groups which they know can’t be mentioned in polite society today. So they went the other way. Not believing in God, the Davos elite see themselves as gods. The further this delusion takes them, the harder they will fall. There will also come a time of reckoning for the collaborators in this program — those who, wittingly or not, aided this monstrosity. Galling self-righteousness, ignorance, and hypocrisy were the least of the crimes in this class. The ones higher up — those who made the plans, gave the orders, and knew what they were doing — face a reckoning that perhaps we do not have words for. It may be a regular new round of guillotining such as we have seen before in history. Or it may be that this time wickedness has gone so far it will have to be ended forever. Prospects for the Davos crew do not look good.
By Michael Nevradakis, Ph.D. | The Defender | May 17, 2022
The latest release of Pfizer-BioNTech COVID-19 vaccine documents raises questions about how frequently adverse events experienced by clinical trial participants were reported as “unrelated” to the vaccine.
The 80,000-page document cache released May 2 by the U.S. Food and Drug Administration (FDA) includes an extensive set of Case Report Forms (CRFs) from Pfizer trials conducted at various locations in the U.S.
The documents also include the “third interim report” from BioNTech’s trials conducted in Germany (accompanied by a synopsis of this report and a database of adverse events from this particular set of trials).
The FDA released the documents, which pertain to the Emergency Use Authorization (EUA) of the vaccine, as part of a court-ordered disclosure schedule stemming from an expedited Freedom of Information Act (FOIA) request filed in August 2021.
Public Health and Medical Professionals for Transparency, a group of doctors and public health professionals, submitted the FOIA request.
Adverse events during Pfizer vaccine trials in the U.S. usually reported as ‘unrelated’ to vaccination
Pfizer conducted a series of vaccine trials at various locations in the U.S., including the New York University Langone Health Center, Rochester Clinical Research and Rochester General Hospital (Rochester, New York) and the J. Lewis Research, Inc. Foothill Family Clinic (Salt Lake City, Utah).
The Pfizer documents released this month by the FDA included a series of CRFs for patients who suffered some type of adverse event during their participation in the COVID-19 vaccine trials.
As the documents reveal, despite the occurrence of a wide range of symptoms, including serious cardiovascular events, almost none were identified as being “related” to the vaccine.
Such serious yet “unrelated” adverse events included:
Of the CRFs found in the documents released this month, only one adverse event is clearly specified as being related to the vaccination: a participant who suffered from psoriatic arthritis, with no prior history of the condition.
In addition, several CRFs indicated exposure during pregnancy (see here and here), or during a partner’s pregnancy (see here and here). However, the documents provided do not appear to have provided any follow-ups regarding any outcomes or potential adverse events for the participants, their partners or their newborn babies once born.
In some instances, while the CRFs claimed the adverse events suffered by patients were not related to the vaccine, their cause was unspecified, simply indicated as “other,” while in another case, a participant’s “unplanned” small bowel obstruction and panic attacks were listed as being unrelated to the vaccination despite no relevant medical history pertaining to the SAEs (severe adverse events) in question.
Did Pfizer hide critical information from regulators?
It is difficult to draw concrete conclusions about any specific case from the data provided by CRFs and vaccine trial summaries.
However, what raises eyebrows is the very large number of adverse events — often serious and often requiring the hospitalization of the patients involved — that were determined to be “unrelated” to the administration of the COVID vaccine.
Previously released Pfizer documents also included discrepancies in the recording of adverse events.
According to investigative journalist Sonia Elijah, these discrepancies include:
Many of these practices seem to appear in the trial-related documents released this month.
Medical and scientific experts who spoke to The Defender expressed similar concerns about what this month’s tranche of documents reveals, and addressed cases of “disappearing” adverse events.
Brian Hooker, chief scientific officer for Children’s Health Defense, remarked:
“I’m most concerned about ‘disappearing’ patients. One cannot conduct a valid trial and simply omit the results that they don’t like!
“With the stories about Maddie de Garay and Augusto Roux surfacing, I have to wonder how many other participants were dropped in order to hide vaccine adverse events/effects.
“If you look at the data in VAERS [Vaccine Adverse Event Reporting System], COVID-19 vaccines are the most dangerous ever introduced into the population.”
Dr. Madhava Setty, a board-certified anesthesiologist and senior science editor for The Defender, said:
“The ‘unrelated’ label the investigators use to divert attention from AEs [adverse events] is a powerful point that stands on its own. We haven’t pushed back on this enough.
“Equivalently, we can say that the meager and short-lived benefit of these shots is also ‘unrelated’ using their ‘standards.’ On what grounds can they say that their product is preventing infection (which it isn’t anymore), or death (marginally)?
“They cannot have it both ways. They cannot claim a benefit through short-term outcomes while denying that side effects of any kind are related to their product.
“That’s the whole point of doing a trial. You cannot prove causation, only statistically significant correlation.”
Setty provided further context for his remarks in an April 2022 article for The Defender and in a March 2022 presentation, in which he discussed the number of these adverse events and how Pfizer swept them away (timestamp 24:00).
In Setty‘s view:
“There’s a high likelihood of malfeasance going on. [Pfizer whistleblower] Brook Jackson says the PIs [principal investigators] were unblinded. If true, it would make it very easy for the investigators to bump up the AEs in the placebo group while ignoring some of the AEs in the vaccine group.
“Pfizer claims that 0.5% of placebo recipients suffered a serious adverse event compared to 0.6% in the vaccine group. This is how these events were obscured.”
The extant body of evidence indicates Pfizer “is hiding critical information from regulators,” Setty said:
“The clincher is in the memorandum to the VRBPAC [Vaccines and Related Biological Products Advisory Committee] (Table 2, efficacy populations), where they show us that five times more people in the vaccine group were pulled out of the trial than the placebo within seven days of their second shot for ‘important protocol deviations.’
“In a trial that big the chances that could have happened coincidentally is infinitesimally small (less than 1 in 100,000).
“Moreover, months later, the same thing happened in the pediatric trial (Table 12). This time, six times more children were pulled from the trial after their second dose.
“There are, of course, procedural differences when administering a placebo versus the mRNA vaccine, but why didn’t it happen after the first dose as well?
“Mathematically, that is about as close as you can get to eliminating any ‘shadow of doubt.’ With a formal allegation by a trial coordinator that states the same thing [referring to whistleblower Brook Jackson], we can be assured Pfizer is hiding critical information from regulators.”
BioNTech trials in Germany claim few adverse events ‘related’ to vaccine
The BioNTech trial in Germany tested various dosages of two COVID-19 vaccine formulas, labeled BNT162b1 and BNT162b2 — the latter granted EUA by the FDA.
The latest cache of Pfizer documents suggests a pattern, similar to the one in the U.S. trials, of not reporting adverse events as related to the vaccine.
According to the third interim report, dated March 20, 2021, among trial participants who were administered the BNT162b2 candidate vaccine granted EUA in the U.S.:
“The most frequently reported solicited systemic reactions of any severity were fatigue (n=40, 67%), followed by headache (n=32, 53%), malaise (n=24, 40%), and myalgia (n=23, 38%). The remaining symptom terms were less frequent.
“For nausea, headache, fatigue, myalgia, chills, arthralgia and malaise each symptom was assessed as severe in <10% of participants.”
Among trial participants who received the BNT162b1 candidate vaccine (not granted EUA):
The report states:
“The most frequently reported solicited systemic reactions of any severity were fatigue (n=68, 81%), headache (n=66, 79%), myalgia (n=51, 61%), malaise (n=50, 60%), and chills (n=47, 56%). The remaining symptom terms were less frequent.
“For nausea, vomiting, diarrhea, myalgia, arthralgia and fever each symptom was assessed as severe in ≤10% of participants.”
A total of 51 of these unsolicited TEAEs were reported as “related” to the vaccination, while 2% of participants sustained Grade 3 or higher TEAEs (four in total), “of which three events were assessed as related by the investigator.”
No unsolicited TESAEs or deaths were reported in this category.
“‘General disorders and administration site conditions’ reported by 9 participants (11%),” including influenza-like illness and injection site hematoma.
“‘Nervous system disorders’ reported by 10 participants (12%),” including presyncope, hyperaesthesia, paraesthesia, and headache.
“‘Respiratory, thoracic and mediastinal disorders’ reported by 9 participants (11%),” including cough and oropharyngeal pain.”
Other symptoms included back pain, musculoskeletal chest pain, cervicobrachial syndrome, taste disorder, sleep disorder, depression, hallucination, dysmenorrhoea, pruritus and pityriasis rosea, while one participant required the excision (removal) of a papilloma.
According to the report:
“The most frequently reported solicited systemic reactions of any severity were headache (n=29, 81%), fatigue (n=27, 75%), myalgia (n=18, 50%), and malaise (n=18, 50%). The remaining symptom terms were less frequent.”
Of the participants in this category, 11% reported TEAEs of Grade 3 or higher (four events in total), with one of these events assessed as “related” to the vaccination.
Of note, none of the participants for either vaccine candidate were pregnant, which raises questions about recommending and administering the vaccine to pregnant women despite the absence of any clinical trial data.
As the documents show, a wide range of adverse effects were reported, including cardiovascular and nervous system conditions, most of which were determined to be unrelated to the vaccination itself.
Michael Nevradakis, Ph.D., is an independent journalist and researcher based in Athens, Greece.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.

or go to
Aletho News Archives – Video-Images
By Whitney Webb | MintPress News | May 17, 2019
NEW YORK — For nearly two decades, one of the most overlooked and little known arrests made in the aftermath of the September 11 attacks was that of the so-called “High Fivers,” or the “Dancing Israelis.” However, new information released by the FBI on May 7 has brought fresh scrutiny to the possibility that the “Dancing Israelis,” at least two of whom were known Mossad operatives, had prior knowledge of the attacks on the World Trade Center. … continue
 Aletho News If Americans Knew No Tricks Zone

