What I Know and Don’t Know about SARS-CoV-2 Virus

By Edward J Curtin | June 19, 2021
After fifteen months of assiduous reading, study, observation, and research, I have come to some conclusions about what is called COVID-19. I would like to emphasize that I have done this work obsessively since it seemed so important. I have consulted information and arguments across all media, corporate and alternative, academic, medical, books, etc. I have consulted with researchers around the world. I have read the websites of the CDC, the World Health Organization, and government and non-government health organizations. In other words, I have left no stone unturned, despite the overt or covert political leanings of the sources. I have done this as a sociologist and writer, not as a medical doctor, although many of my sources have been medical doctors and medical studies.
My succinct conclusions follow without links to sources since I am not trying to persuade anyone of anything but just stating for the public record what I have concluded. Life is short. I am going to say it now.
- I know that vast numbers of people have been hypnotized by fear, threats, and bribes to accept the corporate mainstream media’s version of COVID-19. I have concluded that many millions are moving in a trance state and do not know this. They have been induced into this state by a well-organized, very sophisticated propaganda campaign that has drawn on the human fear of death and disease. Those behind this have no doubt studied the high incidence of hypochondriasis in the general population and the fear of an invisible “virus” in societies where belief in God and the spiritual invisible has been replaced by faith in science. Knowing their audience well, they have concocted a campaign of fear and confusion to induce obedience.
- I do not know but suspect that those who have been so hypnotized tend to be mainly members of the middle to the upper classes, those who have invested so much belief in the system. This includes the highly schooled.
- I know that to lockdown hundreds of millions of healthy people, to insist they wear useless masks, to tell them to avoid human contacts, to destroy the economic lives of regular people have created vast suffering that was meant to teach people a lesson about who was in control and that they better revise their understanding of human relations to adjust to the new digital unreality that the producers of this masquerade are trying to put in place of flesh and blood, face to face human reality.
- I know that the PCR test invented by Kary Mullis cannot test for the alleged virus or any virus and therefore all the numbers of cases and deaths are based on nothing. They are conjured out of thin air in a massive act of magic. I know that the belief that it can so test began with the unscientific PCR Corona protocol created by Christian Drosten in Germany in January 2020 that became the standard method for testing for SARS-CoV-2 worldwide. I am sure this was preplanned and part of a high-level conspiracy. This protocol set the cycle threshold (amplification) at 45 which could only result in false positive results. These were then called cases: An act of fraud on a massive scale.
- I do not know if the alleged virus has ever been isolated in the sense of being purified or detached from everything else aside from being cultured in a lab. Therefore I do not know if the virus exists.
- I know that the experimental mRNA “vaccines” that are being pushed on everyone are not traditional vaccines but dangerous experiments whose long-term consequences are unknown. And I know that Moderna says its messenger RNA (mRNA) non-vaccine “vaccine” functions “like an operating system on a computer” and that Dr. Robert Malone, inventor of mRNA vaccine technology, says that the lipid nanoparticles from the injections travel throughout the body and settle in large quantities in multiple organs where the spike protein, being biologically active, can cause massive damage and that the FDA has known this. Additionally, I know that tens of thousands of people have suffered adverse effects from these injections and many thousands have died from them and that these figures are greatly underestimated due to the reporting systems. I know that with this number of casualties in the past these experimental shots would have been stopped long ago or never started. That they have not, therefore, convinces me that a radically evil agenda is under way whose goal is harm not health because those in charge know what I know and much more.
- I do not know where this alleged virus originated, if it exists.
- I know that from the start of this crisis, there was a concerted effort across the world to deny access to proven effective treatments such as hydroxychloroquine, steroids, ivermectin in a planned effort to vaccinate as many people as possible. This alone reveals an agenda centered not on health but on getting as many people as possible to submit to being vaccinated and controlled. Social control is the name of this deadly game.
- I know that those pushing these vaccines – The World Economic Forum, the World Health Organization, the Gates Foundation, the Rockefeller Foundation, etc. – have a long history of wanting to drastically reduce the world’s population and that their promotion of eugenics under various names is very well known. I am convinced that the totally untested mRNA-type “gene therapy” is the key to their plan for population reduction.
- I do not know if they will succeed.
- I know they must be resisted.
- I do not know why so many good people cannot see through this evil. I can only attribute it to having been seduced by a massive hypnotic propaganda campaign that has appealed to their deepest fears and will result in those fears being realized because they thought they were free. It is a great tragedy.
- I know that all the statistics about cases and deaths “from” COVID-19 have been manipulated to create a fake pandemic. One of the most obvious proofs of this is the alleged disappearance of the flu and deaths from influenza. Only someone in a trance could fail to understand the absurd logic in the argument that this was the result of mask wearing when at the same time the air-born COVID-19 spread like wildfire until that stopped precipitously in January 2021 when a tiny number of people had been vaccinated.
- I know there has been barely any excess mortality throughout all this.
- I do not know where it will all end but hope against hope the growing opposition to this fraud will grow and defeat it despite the organized censorship that is underway against dissenting opinions. I know that when organized censorship on this scale takes place those behind it are afraid of the revelation of the truth. A simple understanding of history confirms this.
- I know that the temporary reprieve the authorities have granted to their subjects will be followed by further restrictions on fundamental freedoms, the corona virus lockdowns will likely return, “vaccine” boosters will be promoted, and the World Economic Forum’s push for a Great Reset with a Fourth Industrial Revolution will lead to the marriage of artificial intelligence, cyborgs, digital technology, and biology with the USA and other countries continuing to slip into a new form of fascist control unless people across the world stand up and resist in great numbers. I am heartened by signs that this resistance is growing.
- Finally, I know if the authoritarian forces win the immediate battle, someone will write a book with a title like that of Milton Mayer’s classic, They Thought They Were Free. It will be censored. Perhaps it will first be shared via samizdat. But in the end, after much suffering and death, the truth about this evil agenda will prevail and there will be much weeping and gnashing of teeth.
- We are in a spiritual war for the soul of the world.
Have the Great Reset Technocrats Really Thought This Through? Evil: Between Depopulation & Neuralink
By Joaquin Flores | Strategic Culture Foundation | June 19, 2021
With the UN World Food Program announcing that some 270 million people worldwide now face starvation, the ongoing debate about the real aims of the technocracy is profound. The question is whether their aim tends more towards major population reduction, or more towards a new type of slavery.
It appears that philosophical and long-term practical questions remain a mystery. We will argue that evil, not simply the influence of the base upon the superstructure, is at the core of this endeavor. We have defined evil as inflicting the highest degree of pain upon the greatest number of resisting subjects. In short, we have defined evil as sadism, inflicting evil because it brings satisfaction to those inflicting it.
Because evil is fundamentally a destructive force, it cannot create anything: nothing in it is truly novel nor of use to humanity. Its pleasures are short-lived and spurious. It is unsustainable, self-defeating, ultimately leading to self-destruction.
We have adequately assessed from any number of sources that nefarious interests are behind this process, who seek to make the process also about the exercise of power, in addition to several other aims (remaining in power, exercising power in ways consistent with their occult beliefs about evil, etc.). We understand that they are ‘evil’ because they involve a type of ‘power-over’ (as opposed to power-with/consent) which derives this power from fear-mongering and terrorism upon the population. Terrorism here is defined as the operationalized use of fear, pain, and other injury towards socio-political aims.
Had their plans not been rooted in evil, they would have used soft-power tactics like manufacturing consent, to arrive at their ends.
The aim of the Great Reset is to transition the ruling plutocratic oligarchy into a technocratic one. The basis of plutocracy is finance, and the introduction of AI and automation eliminates the basis for finance as the foundation of an economy of scale. This is because automation and deflation move in tandem, making new technologies net losers. Therefore a new paradigm accounting for this post-financial ‘Fourth Industrial Revolution’, must be introduced.

Side-by-side comparison of auto-assembly line: 1920 vs. 2020 – ‘Humans need not apply’
But the ideology of the Great Reset is based within the old financialist paradigm, which is one of cost externalization. When human beings are no longer involved in the valorization process in the production of goods and services, then humanity itself is the cost that requires externalization – elimination.
But how it is that sadism became the occult religion of the ruling class, presents a “chicken-or-the-egg” type of question. That is, did the corporate ideology mutate into occult sadism, or did occult sadism find its expression through the corporate ideology? This question will no doubt form the basis of later inquiry.
We often defer to nefarious motivations or processes in terms of ‘greed’, or ‘self-interest’, ‘power obsession’ or the ‘crisis of capital accumulation’, ‘speculative bubbles’.
And these do not suffice in the final analysis, though they provide explanatory power. The problem arises in predictive power, because while we face a crisis of diminishing returns due to automation (as the increasing tendency towards net loss on new large capital investments), the real psychological needs that motivate the present plutocracy as a power-group are actually undermined in significant and sudden population reduction, or new post-coercive technologies that eliminate human agency. This may seem counter-intuitive, but in light of an understanding of the self-defeating nature of evil, we will explore this question.
When we map out the probabilities of three intersecting policy vectors, we can understand this question even better. Those policy vectors are a.) neuralink/AI/Neural Implants/magneto proteins and related transhumanism, b.) depopulation as part of stated Agenda 2030 goals, c.) automation/roboticization, 4IR, and IoT.
This will follow from our last piece on the subject, The Great Reset Morality: Euthanization of the Inessentials:
Neural Implants
The development and introduction of neural implants, magneto proteins, etc., can go in any number of directions. Some types of these promise to give elites ‘super-human’ cognitive abilities. However, another very practical application is to mandate that these are used on the general populace as to handicap them or control their thoughts in some way.
In that sense, neural implants can work like pharmaceuticals that are used in psychiatry. In the creation of this sort of Huxleyesque ‘Brave New World’, we can easily see the continuation of a paradigm already existing today. This is one where it is common-place to find various predictable depressions, anxieties, and neuroticisms caused by contemporary social conditions, but treated psychiatrically instead of resolved socio-economically.
Neural implants can also perform a similar function, but go even further. Beyond emotions or basic effect on the re-uptake of certain hormones like serotonin, etc.; neural implants can direct thoughts or change whole cognitive processes. Beyond feelings, drives, and impulses, neural implants promise to produce actual thoughts in the minds of the subject.

LLNL engineer Vanessa Tolosa holds up a brain implant – credit: Extreme Tech Magazine, July 2014
In between these two is a hybrid form – nanotech and chemogenetics working with optogenetics. Because the delivery system to the brain can be through injection, nanolipids and other compounds can come in the form of shots. These can be delivered as part of a required ‘vaccination’ regimen (insofar as that term has been redefined), as nanotech features already in the Covid-19 shot.
Therefore, such can be included – whether disclosed to the public or not – in required vaccinations.
The development of these would seem, however, to be a technology that would support slavery, but does not rule out genocide. Certainly the ability to control the thoughts of a population would greatly mitigate risk in the view of the state apparatus, especially as it moves towards genocide.
Depopulation: Myths vs. Facts
Population control and population reduction have long been policy at various institutions and think tanks committed to global governance, from the UN to the World Economic Forum. It was a part of the UN’s Millennium goals, and since the dawn of the 21st century, has been part of UN Agenda 2030.
It is important to now introduce a framework for understanding the problem of population in light of economic development. The long standing view is that economic development leads to population stagnation, even decline. The idea here is that education and urbanization are processes which lead towards better knowledge of basic family planning, in tandem with improved access to abortion and birth control.
The underlying postulate is that people naturally do not want to be burdened with children, that children are an affront to freedom in the abstract. The formula is that as people are better educated and have more meaningful work and interesting lives, they know both how to prevent pregnancy and also no longer have ‘primitive’ inclinations towards large family building.
This mythology was built up around a notion that people are fundamentally self-interested in the narrowest sense, to the exclusion of other desires, needs, and impulses. They are presented as the norm such to furthermore create a broader culture which opposes procreation.
Instead, the real mechanism pushing population stagnation in the 1st world are increased pressures of work, and increased costs of living. Rather than ascribing population stagnation to improved conditions of life, these are more related to austere conditions imposed by late modernity. The costs of property, of rents, of food, and also because of the decline in quality of goods through increased planned obsolescence, has placed more economic pressure on individuals and couples. It has led to the requirement that both members of a household are working full-time. And even with this, home ownership in cosmopolitan centers is practically impossible for most. Austerity has also led to stagnation in life expectancy.
This truth is exposed in actual policy papers like “New strategies for slowing population growth” (1995). Here, the doublespeak is evident, with easily decipherable phrases within it; “… reduce unwanted pregnancies by expanding services that promote reproductive choice and better health, to reduce the demand for large families by creating favorable conditions for small families…”. What could possibly be meant by ‘create favorable conditions for small families’?
Economic development does not reduce population, but if we add austerity and demanding and inflexible work obligations, then we land on an answer. Economic prosperity, as it has for time immemorial, promises to greatly increase the population in the absence of a program of population reduction. Because an organic 4IR not brought in by the technocracy would decrease work obligations and increase quality of life markers, we would expect a population boom.
Consequently, projections that that population will top off at just under 10 billion by the 2060’s are as erroneous as they are linear. Without a technocracy working to actively reduce population, as they believe, an economy based on automation and AI would see a population explosion.
Conclusion
It is still likely that the would-be technocrats have indeed thought out the end-game, and that there are any number of possibilities that will allow them to harvest sadistic pleasure as an exercise of absolute power, in perpetuity. This might mean increasing fear of extermination far beyond actual population reduction. It could mean maintaining many aspects of agency for the controlled population, so that their pains are internalized in multivariate and complex fashions, that include confused feelings of self-blame, identifying with the abuser, resentment, regret, and also violations of will and dignity. Again, if will is not a factor, then all of these potential arenas of psychological pain are not present.
To frame the following, it is fundamental to understand that in a post-labor civilization, the status of humanity no longer exists upon a metric of utility. Either civilization exists to improve the human condition, or to increase human suffering. There are no trade-offs or costs. Society is either good or evil.
But evil is short lived and short-sighted, and this is why: Sudden population reduction is a fire-cracker, it explodes just once. The pleasure in the process of eradicating billions of people, and the fear, pain, and suffering this would cause, within the span of a few short years, only gets to be enjoyed once. It’s a sacrificial ritual upon the altar of Moloch that can only be performed one time.
Likewise with post-coercive technologies: Without agency, controlling people serves no purpose in terms of violating their own will or desire. Causing pain on a subject that does not resist because he has no will, gives the sadist much less pleasure than would pain on a subject against their will.
Moreover, the position of being elite is relative to a number of factors such as distribution of wealth, power, and/or privilege, and the sheer numbers in terms of population, that one possesses these advantages over.
If there are only elites remaining, then they would have merely introduced a new kind of egalitarian society on the foundation of superabundance and a miniscule human population. If living conditions of an existing humanity can be greatly reduced, then the relative privilege and luxury enjoyed by the elites grows in that proportion.
Absent some radical life-extending technology, it is conceivable that science and technology have already reached the zenith point at which privilege and luxury cannot be furthered. A reasonable solution would be to reduce living conditions for others so as to enhance their own relative privilege. The greater number of people who live in reduced conditions, the more privileged one’s position of privilege actually is.
Likewise, it would seem that maintaining some human population as ‘possessions’ would serve to augment ownership over human beings, perhaps the most valuable type of possession because they are aware that they are owned – but only if that humiliates them. For what other purpose is there for slavery, in a world without human labor?
Does it have any meaning, or is any satisfaction achieved, by governing over people without the possibility to have the will to either consent, or conversely, resent the ruler? Here we can understand it along these lines: the possibility for agency means that governing can happen with their support, or against their will.
But neural implant control over cognitive processes, eliminates the possibility for will, which would deprive technocrats of the pleasure of ruling with or against the will of the ruled.
Therefore, the destructive evil framework of those behind the Great Reset is revealed. The use of strategy, planning, and cunning to achieve their desired result is prevalent. But have they examined the foundation of their desires? Do they understand what their victory would deliver to them?
The only thing left to destroy in a world populated by elites alone, are other elites. It would seem that the desire to dominate others does not simply come to an end on its own.
For these reasons, it is likely that some elites have seen the problem in this end game. This would explain the inter-elite conflict which we have explored previously, and will return to in the near future.
An Essential Journey
My experience of international travel in Covid times
By Joanna Sharp | OffGuardian | June 19, 2021
I had not planned to travel abroad this year, especially after the UK government’s announcement in early 2021 that foreign holidays were forbidden. Even heading towards the airport with an intent to go on a foreign holiday could result in a £5000 fine or imprisonment! Surreal.
Where we live in London under a flight path to Heathrow, we notice that although there are fewer flights, they have not ceased completely. So how do people travel? It’s not something I have thought about.
One day at the end of April I receive a message that my elderly father’s condition is critical. Within an hour I am looking at flights back home in Eastern Europe and checking the UK government travel ‘advice’ webpages.
I say ‘advice’ but that word belongs to the past. Today, ‘command’ might be more appropriate. According to the government, only “essential” international travel is permitted for named valid reasons; ‘medical and compassionate’ is the category which applies to me.
I wonder whose compassion this is a reference to: mine, for wanting to be with my sick father, or the government’s for including this as a possibility. Reassured that I can go, it is now a question of buying the plane tickets, checking in and packing, right? Not quite.

WADING THROUGH THE RED TAPE
Since holiday travel has effectively been banned, the government created intricate webpages full of information on what is and what is not allowed, where citizens cannot travel, and if they must, what documents they need to prepare. So complicated travel advice alone has become that the webpage now includes a step by step flowchart with endless links within each step to be followed.
Getting through this information would take at least a day. It’s like a cross between a maze and a vortex. I soon understand that I cannot buy my tickets until I have uploaded the right Covid related paperwork onto the airline website!
First, I need to fill a Declaration for International Travel (since the 17th May it is no longer required) which asks for personal details including my date of birth, passport number, home address and destination.
The key question is the reason for international travel – and in the actual online questions, the phrase is: ‘What is your excuse for travel?’ My excuse? What kind of language is that? Am I asking a teacher to let me leave the classroom? Am I asked to explain why I haven’t done my homework?
That really shocks me, although I have already noticed my own reaction to the very idea that I need permission to leave the country, as if I was back in Eastern Europe before 1989…I read the following declaration and tick the right box out of the given options.
I hereby declare that my reason for being outside my home to travel internationally is for:
– Work
– Volunteering
– Education
– Medical or compassionate reasons
– Funeral
– Ending a temporary visit (non-UK resident)
– Allowing access to parents with children who do not live in the same country
– Other reasonable excuse – please specify
Next, I am required to sign to ‘certify that the information I have provided is true. I understand that if I provide false or misleading information, I may be issued with a fixed penalty notice and/or a direction to return home or be arrested’.
So, by signing this, and I have no choice not to if I want to get my ticket, I have given the UK authorities permission to arrest of fine me should my excuse to travel turn out to be incorrect. What if my father is not that ill, then what?
But of course, that is not enough. I now need to provide evidence of my father’s illness. How do you do that when the whole of the world is still in lockdown; imagine having to get a doctor’s note on demand. I am still just trying to get a ticket.
I want to travel tomorrow morning, my sister-in-law tells me, Dad is given a couple of days. I ask my brother to send me an email confirming the family crisis, he does that within an hour. He is also trying to copy the notes from my father’s last doctor’s visit and the most recent diagnosis.
Then, still before I buy a return ticket, I need to get a kit of two Covid tests which I will need to take upon return to UK. Another link takes me on to a list of government-approved Covid test providers. A whole list of them, each can be accessed via a separate link. I try a few. They average around £200 each. The cheapest ones are £99 but are sold out.
Why can’t I see any free NHS ones? The ones given out like sweets in schools and local pharmacies? Why are these not available? Why could I not just pick a free one at the airport?
But of course, there is no to answer these questions, I am desperate to leave so agree to this, too. No test, no flight. So, I order one of these almost £200 test kits, get an email confirming the order, upload all the documents and finally I can complete the purchase of my tickets which, as usual, turn out not so low cost after all.
I check in. My boarding card (lucky I had just bought a printer the previous week) says at the top of the page ‘Covid Documentation Uploaded’. So, now I have the boarding card and a pile of printed pages which presumably I will need to show at UK border control in order to prove my excuse for leaving the country is legitimate.
Finally, I download and fill in the compulsory Passenger Locator Form for the destination country that will enable the system to track and trace me. It is nearly bedtime and I now need to pack.
ON THE GO
My husband drives me to Stansted in the middle of the night. An early morning flight, no public transport available but at least it’s quiet and there is no traffic. The airport is still closed; a group of families with young children are waiting for the door to open.
These are not holidaymakers breaking the law to get some forbidden fun. No idea where they are travelling but they look like they are going home somewhere south, southeast perhaps? Turkey, Bulgaria or Ukraine? No idea but they do look like part of the globalised chain of workforce escaping poverty and perhaps the lockdown has pushed them to return. Better to be jobless and poor in your own village. The weather tends to be better and the environment less hostile.
Finally, the doors open. I push the scarf up over my face, my hand clutching a plastic folder with a wad of documents allowing me to leave. It is quiet, no waiting. I go through security, passport control seems non-existent, shops still closed so nothing to stop for. I wonder at which point someone will ask me to see the papers. Ask me what my excuse for leaving is. Strangely, that never happens. I am almost disappointed. I spent about four hours sorting out all that paperwork the night before and now this is not even checked!
Immediately I catch myself: why am I disappointed? Because no one will give me the all-clear? Have I been conditioned to want to be waved through the green light already?
Perhaps that is how normalising oppression works. But of course, there is no need to check, the documents have been uploaded and recorded somewhere and someone now knows everything about me, my plans, my reason (“excuse”) for leaving the country. Or perhaps the intimate details of my family crisis; my father’s terminal illness and my attempt to get to him before it’s too late have now just been converted into big data slushing around the corpo-government’s control AI machine, and turned into useful predictions.
I guess this type of authoritarianism does not even need stern looks from border control officials, no need to divulge private dramas in public. Hours of stress of getting the documents turned into a discreet but vital small print on my boarding card; the only visible proof that my travel is acceptable to the corpo-state. It is all so neat, tidy, hi-tech and invisible that we can just pretend that all is just normal.
After all, the airport trimmings look all the same; with adverts, duty-free shopping, same old queues at departure gates and same safety drills on the plane, down to the irritating Ryanair voice thanking us for choosing to fly with them (no one chooses to fly with Ryanair, just like no one chooses to go to the dentist, you do it because you have to and you hope it won’t be too unpleasant).
We can pretend nothing has changed. Except the masks on faces, of course. Slow drinking and eating is my solution. During the flight many noses protrude against the regulations, of course. People do need to breathe.
We land on time. I send a message to my father, anxious, hoping he is still there. He is not responding. I am worried. From the tarmac I can see the arrivals hall is full. There is no way of entering so the crowd from my plane stops outside and waits in the drizzle. I wonder why that is. Is that Brexit or is it that people’s papers are now checked after all?
The queue moves very slowly, twenty minutes after landing I send my father another message saying that I’m still waiting for border control. I have no idea why this is so slow; each person seems to spend a good few minutes at the control desk. Finally, an hour and a half after landing I get into the taxi. As the driver pulls away, I notice a long queue of passengers outside the arrivals hall waiting to get a Covid test. I arrive home and find my father hanging on.
MY FATHER’S ILLNESS
There is a twist to this story. My father had been treated for cancer but has been still doing quite well and had been planning to spend the summer away from his flat, in the countryside. His sudden deterioration was unexpected for me but I have not had time to think of reasons. I only learnt of this yesterday. But now I am in the flat, taking my shoes off when my brother drops the bombshell: ‘you know, Dad took the vaccine’.
I am shocked. He told me he was not going to, because he found the registration process too difficult, so he decided to stop trying. I was relieved; I had been persuading him that he should not, that being immunocompromised, his system might not cope. I told him what I knew and what I worried about. My brother tells me another family member helped organize his jab and took him there. Jesus. But I am to pretend I don’t know about it; Dad asked my brother not to tell me.
So, I learn that the day after the Pfizer jab he started to feel weak, and within ten days he was prescribed blood thinning injections, a daily drip and he became bedbound. My brother has hired a hospital-style bed and an oxygen machine, set them up in father’s bedroom and organized a private nurse for daily visits. Dad had not wanted to go to hospital: he believed that hospitals were overrun by contagious Covid patients and that going to hospital would mean certain death under a ventilator.
Luckily (I never thought I would say this), unlike the UK, this ex-communist country never managed to build up its own national health service to a level able to deliver comprehensive care, so a secondary private sector filling the gaps exists and is not beyond the means of many people. So here he is, in his own bedroom and getting care at home.
He is happy to see me but asks me not to touch him. I feel sad, guessing he might worry I am bringing contagion. That hurts. I pretend I know nothing about the jab. Later, much later, I remember this moment and think that, he might have wanted to protect me. He knew the jab made him ill and he worried he was fighting vaccine induced-Covid and did not want to give it to me.
He never told me about the vaccine, I never told him I knew.

Sunset in Quaratine
QUARANTINE ONE: THE APP
The day after arriving I receive a text message telling me I am now under statute of law obliged to download a particular app and use it during my 10-day home quarantine. I start the download but can’t complete it. Something is stuck and I have no idea how to fix it. I try for a while and then abandon it. I spend most of the time caring for my father who now slips in and out of consciousness.
The next morning I get a phone call but it stops ringing before I have time to answer it. The following day the same happens. I realise this is the local track and trace. They ring but don’t wait for me to answer. Their call is logged, the box gets ticked but the robot or a human cannot be bothered to do the job properly. Actually, it must be a human as a robot would not give up. Good. The tyranny will fail due to human error or sheer laziness.
I don’t know what possessed me but somehow, I manage to complete installing the Quarantine App. The system springs into action. I get a message from the app that I must take a selfie within the next 30 minutes and submit it. I take a selfie from the app which gives me as many times as I like to choose the best shot. I choose the worst shot.
Of course, there is a way to cheat: after doing my selfie I could leave the phone at home and go out for a walk. Trouble is, the selfie demand comes at a different time each day, usually towards the end of the day. But I have no reason to go anywhere, really, I have come here to be with him, and his condition continues to be critical. And at some point, during this journey I decided that I would do everything by the book, just to see what the new normal travel feels and looks like, and what exactly they want us to experience.
Well, here I am, in a 10-day quarantine in a flat with my dying father. We are lucky. I have my brother to get the shopping in and kind neighbours ready to help. We are lucky my father is at home. What would be the point of coming here all this way, only to be stuck in quarantine if he was in a hospital with no visitors allowed? So, all in all, we are lucky.
DIFFICULT DAYS
Days go by, my father’s condition improves a little, I am his nurse, and of course I touch him – he stopped protesting as soon as he needed a glass of water; I continue to take my selfies. We talk, I read to him, feed him, then he sleeps. He dies two days after my quarantine ends. That is good timing.
There is a lot to do now, and I will not be breaking the law trying to organize the funeral… I remember my favourite literature lesson at school when we debated who was right: Creon or Antigone. Even then, I was in team Antigone.
A doctor arrives to certify death. She is nice and takes her time. Talks a little. Does not look like a corporate bot. She is sitting at a coffee table doing the paperwork. For the cause of death, she writes ‘Thrombosis’. I ponder for a bit and then hesitatingly say: ‘Did you know he was vaccinated?’.
Her face changes and she asks: ‘No, when?’ We tell her, ‘Four weeks ago, exactly’.
‘I am not allowed to say anything,’ she says, ‘but I can tell you I have seen a lot lately. A lot!’ We try to encourage her to talk more but she is cautious. I just ask her: ‘Why would a person on cancer treatment be given a vaccine? Surely that had not been done before?’ She looks at me and says: ‘Because they want to vaccinate us all.’ So, she knows.
This kind of conversation would have been typical in the days of strict communist authoritarianism before 1989. You never knew whom you could trust so you just dropped hints and checked for people’s response. In those days careless talk was dangerous, and I am too young to remember the worst times: the Stalinist years when children were encouraged to denounce their parents; many were imprisoned, tortured and killed.
Now the threat is only a loss of income and public humiliation and yet the new order based on lies, fraud and corrupt science is already in place. Everyone is just doing their job. A perfect example of Hannah Arendt’s banality of evil in which those, following orders in this elaborate house of cards, often do not even know their active contribution to harm inflicted on others. They do not realise because they refuse to look and to know. They stopped taking responsibility for their individual part in the whole.
There is a small group of doctors in the country who are challenging the official narrative, attempt to offer treatment for Covid patients and warn against the untested ‘vaccines’, particularly now that governments want to jab children. Their voices are censored, the people get smeared, ridiculed and shamed by the professional licensing medical body. The modern-day governance in Western democracies!
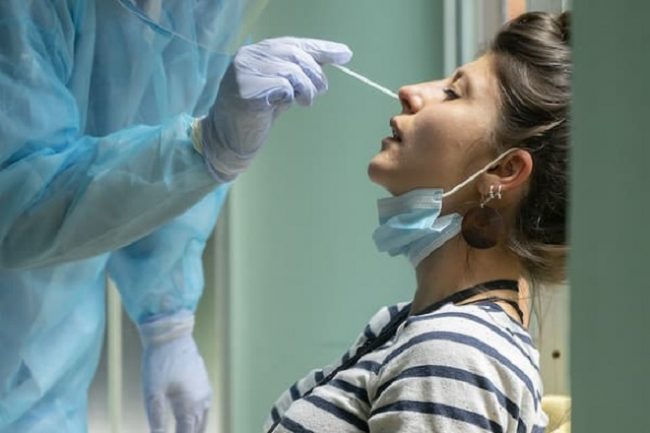
TRAVELLING HOME
As the funeral preparations get underway, I need to organise my return travel. I check the UK government website again. Travelling from an ‘amber’ coded country, I must test negative for Covid within 72 hours prior to departure. Tricky when the flight is on Monday afternoon.
I start to search for UK government-approved tests available in the city. Only a handful provide the specified UK approved antigen test with results in English. They are also open only in the mornings so if I test on Friday morning, I might be testing a few hours too early to fit within the 72 hours.
After hours of online searching, I find one that looks almost right. I pay the equivalent of £35 online and am told to come on the day, without an appointment. The laboratory website provides useful advice, how to prepare for the test. I learn that I should not brush my teeth or use mouthwash on the morning of test. So now I know what to do.
I arrive at the testing centre early, having heard that queues can be quite long. It is, and it is in the street. The lab’s waiting room only allows three people at a time so the rest stand outside. After about an hour it is my turn. I am allowed inside the surgery.
On the right, by the door, a masked man sitting at a desk behind a glass screen is checking my name and the type of test I have purchased. Then, a young tall, man in full white hazmat suit, his face covered, and in protective glasses ushers me to sit on a chair and tip my head backwards.
This is my first Covid test ever and I am terrified. I have rehearsed telling them how sensitive my face feels and asking not to go deep but there is no eye contact, no talk trying to help me feel comfortable, no attempt to put me at ease. He just tells me to tip my head back far.
I just manage to ask him to go into the left nostril as my right one is not straight. He happily obliges and shoves the long stick into my nostril. As soon as the tip enters my nose I feel shock, a feeling of something unnatural, wrong and threatening happening. The area he just touched is too soft, sensitive and the sensation so unfamiliar I involuntarily, and to my own shock, find myself pushing the man’s arm away. He moves back and looks at me, his body language (there is no face available) disapproves of my behaviour.
I say, please don’t go that deep, you already have some but he insists, tells me not to defend myself and does it again. And again, that feeling that a part of me which is vulnerable and should not be touched, gets scraped. He gets his sample and nods for me to go. I am frozen in that chair, unable to move for what seems like a while. I have tears in my eyes, and I am alone with two hazmat wearing robots. No word is uttered as I leave.
I get my negative result within hours. I recover with an old friend. By then I have a splitting headache and my left nostril is moist with a slight leak. The headache lasts for a couple of days but the leak persists for at least ten.
I arrive at the airport early because I have difficulties completing the UK Passenger Locator Form which UK needs from all passengers. I pass through a manned gate with an automatic wrist temperature check. The airport is unusually quiet, and the staff help me identify the problem which stops me from completing the form. The reference number for the double Covid test needed for the Passenger Locator Form is wrong. I ring home and ask my husband to read the reference number off the Covid test kit. Surely it has arrived now. It hasn’t. It looks like the Day 2 and 8 Test I ordered has not been paid for.
I am told I need to buy a new kit if I want to get this flight. I do as I’m told. No form, no flight. I stand next to the luggage drop off counter feeling sweats, and with my hands shaking I battle the website on my phone. Again, all the ‘cheap’ ones are sold out and somehow, at the last minute I manage to make a purchase for £180, get an email, a reference number, complete the form and have my luggage accepted.
I hurry to my gate and make it just in time as passengers are starting to board. I slow down to join the Ryanair herd waiting on the tarmac for the aircraft to be processed before we are told we can travel.
The pavement is marked with lines at 2-meter intervals. Two men behind me are joking loudly that we must stand on the lines correctly, otherwise the virus will jump on us. I turn and smile (no mask, we are still outside) and make eye contact with the fellow humans.

QUARANTINE TWO: TRACK AND TRACE
Back home in London, the following day I get my first out of ten phone calls from Track and Trace. Each time a different voice reads the same script.
I am contacting you on behalf of the NHS Test and Trace as you have recently travelled into the UK from abroad. Are you happy to continue in English?”
No idea what would happen if I said ‘no’.
Before we proceed, I need to make you aware that this call will be recorded for training and quality improvement purposes and should just take a few minutes of your time. I can confirm I have completed the necessary data security training and all information you provide today will be stored securely. NHS Test and Trace may need to share your details with other organisations including the Home Office, and further information on data security and privacy can be found on http://www.gov.uk/coronavirus. Sharing information in the call today means you consent for it to be stored in the ways I have described. Are you happy to proceed with the call?”
I wish I could say, no, I am not. Once or twice I ask how long the data is going to be stored. The caller is not sure and advises me to find this out from the government website. The call proceeds with them checking my year of birth. Then they ask if I have opted into a ‘test to release’ – I frankly don’t even know it is my option, so I say ‘no’.
I later learn that the Test to Release scheme does not replace the compulsory Day 2 and 8 test. The ten-day quarantine can be shortened to 5 days by ‘opting into’ Test to Release for an additional £99. I realise they ask this question to advertise another product!
Can you confirm that you are quarantining at the address you provided on the passenger locator form and will continue to do so for ten days starting on the day after you arrive in the UK.”
So, again, I confirm, yes. What would happen if I said no?
As part of the Covid 19 response you are legally required to take the test on Day 2 and Day 8 and a failure to do so may result in prosecution.”
That answers my previous question…
Has your test arrived? And have you taken or do you intend to take your test?”
Yes.
Then I am asked if I got my test from the NHS or from a private provider. I am confused as I had no option to get an NHS test and I tell the caller. They seem happy with my answer and continue:
If your Day 2 test is positive confirming Covid 19, you do not need to take another test on Day 8.”
I think, on one occasion, I ask how I am expected to post the test if I am not allowed to leave the house. Of course, the assumption is there is someone else in the house, and if I still have difficulties, again, the go-to place is another NHS number. Amazing what they can do these days; they can even pick up your mail for you!
The call continues:
If you develop any of the three coronavirus symptoms which are: a new continuous cough, a high temperature, or a loss or change to your sense of taste or smell, please visit http://www.gov.uk/coronavirus for further advice. You should not go to the GP, hospital or a pharmacy. If you require medical advice, please ring the NHS on 111 or in an emergency dial 999”.
So here we have the admission of medical malpractice: if I fall ill, I must not seek help from NHS, not even by going to my local pharmacy. I must stay home without help, except of course, if I qualify for 999 ie, a ventilator…
The call continues:
I must advise you that if you test positive for coronavirus or are identified as a close contact of someone who has coronavirus you will be notified by NHS Test and Trace and may be contacted again. Is there anything you would like me to repeat?”
Of course, if someone I sat next to on the (half-empty) plane gets a positive result, my quarantine will stretch to a fortnight or longer! Each time, the call ends with a friendly, youthful, ‘have a great day’. All those who have called me are young voices, all kinds of accents, probably desperate for any job in the current climate. They are trained to stick to the script and any departure from it by my questions seems to trip them up.
And most of them probably think they are doing something socially useful and valuable.

THE QUARANTINE DIY TESTS
The one I have purchased in haste at the airport is a kit with two PCR tests to be administered at home on Day 2 and Day 8. The instructions tell me that the test is run at less than a 30-cycle value threshold.
The first thing to say about the swab is that it is long. It looks like a cotton bud used for everyday use, but on closer inspection it is different. The stick itself is about 12 cm long, that’s 6”, and designed to break off after the sample is collected and put into a small tube provided. The tip itself is 2 cm long, quite thin and covered in almost translucent spiky bristles protruding outwards. It looks a bit like a miniature harsh brush designed to scratch the delicate tissue inside the mouth and nose.
I am told to swab the back of the throat for 3-5 seconds over the posterior pharynx and tonsillar areas but to avoid tongue, teeth and the sides of the mouth. Then I am told to insert the same swab to each nostril about 2 cm deep and to rotate it for 3-5 seconds each time.
The form which I have to complete for each test is yet another mandated opportunity for the corpo-government to harvest my personal data, to store it for as long as it sees fit, yet, as is often the case in abusive relationships I have to (I repeat:) I have to give my consent for all this to happen, and even consent for my possible positive test result which may include my personal details: name, date of birth, gender, home address, telephone number, occupation, place of work, ethnicity and the fact that I have tested positive for Covid 19 to be communicated to Public Health England. Luckily, both of my test results are negative.
Eleven days after arrival in the UK my quarantine is officially over. It takes me a couple of days before I venture outside, I detect a bit of agoraphobia. In the last six weeks I spent twenty days in house arrest. They say it takes six weeks to develop a new habit.
POSTSCRIPTUM
I doubt very much I will travel internationally any time soon. Not planning to take the experimental Covid jab and so will not be enjoying the privilege of freedom promised to those with the vaccine passport. At the time of writing, it is no longer illegal to leave England but the elaborate hoops and the red tape remain and the government website reminds us that “to protect public health in the UK and the vaccine rollout, you should not travel to countries or territories on the red or amber lists”.
The ‘red and amber’ lists cover most countries of the world and returning from an amber list country will involve three or four tests which could come to £240-£340 per person plus the time spent completing all the online forms.
As to the red list countries; even a short spell there ends in an expensive £1750 per person prison-like stay at an airport hotel, as can be seen here.
So whilst not forbidden, even essential travel has been made into a series of expensive, degrading and time-consuming obstacles. Vaccine passports are being rolled out precisely to convince people they will magically bring freedom back to their lives. Do they not realise, that once they have their passports, the vaccine will need regular boosters?
Those still asleep; trusting the governments and the mainstream media think that easy travel is only temporarily put on hold but once the pandemic is ‘under control’, things will get back to the way they used to be. They do not realise the plan is to make travel an exclusive and rare event beyond reach of ordinary people.
This is done to us not just by the predatory elite class. Disappointingly, the pro-lockdown left continues to cheer these restrictions on and dismiss people’s desire and need to travel, as undeserved indulgence or middle-class privilege (interestingly, unrestricted travel around Europe was, until so recently, one of the main reasons for their fierce anti-Brexit position. What happened to their cherished principle of freedom of movement?). They could not be further from the truth.
They forget that, according to official migration data for the end of 2019, the UK is home to 6.2 million people – that is 9% of the total population – who have the nationality of a different country! And that data does not even include naturalised UK citizens like me, first-generation settled migrants who have close relatives all over the world and that unrestricted travel is an essential means to family life, something which is protected by Human Rights Act 1998.
The irony for those like myself, who grew up in communist Eastern Europe, is that freedom of movement, so taken for granted in the West, the right to travel and to have your own passport at home at all times is what we did not have then. The state set limits on where ‘citizens’, treated like its property, could travel.
For many who experienced those times, even as children, a return to state-mandated travel restrictions will feel like going back into tyranny.
As for my own journey: I will never forgive those responsible and all those lockdown fanatics for stealing my Dad’s, and so many other elderly people’s, last year by locking them up in the prison of fear and isolation, and then for pushing them to take the dangerous experimental jab which – for so many – was the last straw in their already weakened bodies.
Florida gov. DeSantis declares victory as federal judge slaps down CDC ‘overreach’ on Covid-19 cruise ship rules
RT | June 19, 2021
Cruise ships may soon operate out of Florida once again, as Governor Ron DeSantis notched a court victory against the Centers for Disease Control and Prevention in an epic injunction order blasting the “authoritarian” agency.
US District Judge Steven Douglas Merryday on Friday granted Florida’s request to block the CDC “conditional sailing” order against cruise lines. The injunction won’t go into effect until July 18, however, at which point the CDC orders to cruise operators will be considered non-binding considerations, recommendations or guidelines.
“The CDC has been wrong all along, and they knew it,” said the Republican governor, announcing the decision. “The CDC and the Biden Administration concocted a plan to sink the cruise industry, hiding behind bureaucratic delay and lawsuits. Today, we are securing this victory for Florida families, for the cruise industry, and for every state that wants to preserve its rights in the face of unprecedented federal overreach.”
Florida sued the CDC for irreparable harm after some cruise lines threatened to leave the state due to the onerous and burdensome conditions imposed in October 2020 and renewed in April. Among other things, the CDC required cruise operators to build testing laboratories on board, re-do the ship ventilations systems, and have at least 98% of the crew and 95% of the passengers – including children – vaccinated in order to bypass a requirement for simulated cruises first.
Merryday’s exhaustive 124-page ruling seemed to be designed to withstand Supreme Court scrutiny, referencing multiple justices, circuit precedents, case and statutory law, and even history of the CDC and quarantines. He zeroed in on the CDC’s understanding of its authority, however, pointing out that its lawyers repeatedly defined an “outbreak” as even a single instance of human-to-human virus transmission.
By doing so, the CDC claims authority to impose nationwide any measure whatsoever, based only on its director’s discretionary finding of “necessity,” wrote Merryday, calling it “a breathtaking, unprecedented, and acutely and singularly authoritarian claim.”
“One is left to wonder,” the judge wrote, whether the CDC could have tried to “generally shut down sexual intercourse” in the US to prevent the transmission of AIDS, syphilis or herpes. “Political prudence (and difficulty of enforcement) might counsel CDC against this particular prohibition, but the statute, as understood by CDC, certainly erects no barrier,” he noted – then proceeded to reject that understanding.
Merryday’s drubbing of the CDC authority even cited the May ruling by his colleague in DC, Judge Dabney L. Friedrich, which clocked in at only 20 or so pages but disputed the agency’s right to impose a nationwide moratorium on eviction of delinquent renters.
More than 13 million cruise passengers and crew embarked or disembarked in Florida in 2019, patronizing the state’s economy. The cruise industry’s return will be “an important milestone in the fight for freedom,” DeSantis added, pointing out that Florida “continues to thrive while open for business.”
Under DeSantis, Florida has led the way in relaxing Covid-19 restrictions. He has even publicly regretted implementing any lockdowns in the first place.
How Ron Paul Stopped the US Government from Imposing a National Vaccine Passport

By Adam Dick | Ron Paul Institute | June 18, 2021
Who do Americans have to thank for the United States government not subjecting them to a national vaccine passport like those being imposed by national governments in Europe? Megan Redshaw wrote in a Wednesday article at Children’s Health Defense that the credit goes to Ron Paul who, while serving as a member of the US House of Representatives, led the effort to bar the US government from creating for each American a “unique health identifier” number.
Redshaw wrote:
So far, the Biden administration has resisted the idea of a “vaccine passport” for the U.S. On May 28, U.S. Director of Homeland Security (DHS) Alejandro Mayorkas said the U.S. was taking a “very close look” at vaccine passports for international travel. Later that day, the DHS clarified there will be no “federal mandate” for vaccine passports in the U.S.
According to the Los Angeles Times, the U.S. does not have a national database for immunization records that could act as the source of vaccination data for use in digital passes. That’s because a national system to create a unique identification number to link the health records of every American has been banned since 1998, spearheaded by then-Rep. Ron Paul (R-Texas), who said such a system would be an unwarranted privacy intrusion.
An attempt to overturn the ban passed the U.S. House in 2019, but was rejected by the Senate.
Paul left the US House in January of 2013.
Paul’s son Rand Paul has been a key person working in the US Senate to keep in place the prohibition on a unique health identifier. A September of 2019 press release from Rand Paul’s Senate office recounts the following:
Dr. Paul’s father, former Congressman Ron Paul (R-TX), introduced language to the Labor-HHS appropriations bill in 1998 to restrict the use of federal funds to develop the identifier, and such a ban has been continually renewed in each Labor-HHS appropriations bill since.
This June, however, an amendment stripped this critical protection for Americans out of the version of the Labor-HHS appropriations bill ultimately passed by the U.S. House of Representatives. Enacting the bill into law with this amendment or a similar provision would open the floodgates for a government-issued ID to be linked with the private medical history of every man, woman, and child in America.
Prior to introducing standalone legislation to repeal the original authority created under HIPAA, Dr. Paul successfully advocated this month for keeping language banning federal funding for the unique health identifier in the proposed Senate version of the Labor-HHS appropriations bill.
4 British Airways Pilots DEAD Following COVID-19 Jabs, Spain and Russia Prohibit “Vaccinated” From Air Travel

Image source from social media and on Rueters.com
By Brian Shilhavy | Health Impact News | June 18, 2021
A man claiming to be a friend with a British Airways pilot has stated that 3 pilots have just died within the past week shortly after receiving COVID-19 injections, and his recording has gone viral on social media. Here is the recording (let us know if Twitter takes it down as we have a copy.)
This brought out the usual corporate media “fact-checkers” to try and debunk the man’s claims.
Reuters responded with a “fact-check,” but in their own investigation and report they confirmed that not only did these three die, but a fourth one as well.
They gave the usual corporate media response by quoting some health “authorities” who categorically stated that their deaths had “nothing to do” with the shots, while not denying that they died, nor giving any other explanation for their deaths.
Shared in the form of a voice recording on Facebook, Instagram and Twitter, an unidentified male says he has spoken to a “friend who’s a BA pilot” and explains “things are getting crazy” after three fellow pilots passed away (here , here and here).
“They’ve had the third BA pilot die in the last seven days, yeah? Third pilot dead in the last week,” says the man heard in the recording. “The first two guys were in their forties and fifties; this guy, mid-thirties, perfectly fit, no underlying conditions. He gets his second jab and he’s dead within days, exactly the same with the first two.
“Because of this, BA are now in crisis talks with the government about whether to allow vaccinated pilots to fly. The issue with that of course is that about 80%, according to my friend in BA, 80-85% have been injected.”
The man then goes on to say only “10% of pilots will be able to fly,” branding it a “serious issue”.
Reuters presented the claims to British Airways, which said they were unfounded and that no such talks were underway with the government.
The spokesperson, however, confirmed the authenticity of the four condolence books, as four company pilots had recently passed away.
“Our thoughts are with their family and friends,” they said, adding that none of the deaths was linked to vaccines.
In a statement to Reuters, the UK’s Medicines & Healthcare products Regulatory Agency (MHRA) also denied any such crisis talks with Britain’s flagship air carrier.
“We have not been made aware of deaths of BA pilots after receiving the Covid-19 vaccine and have not had discussions with BA or other airlines, about preventing pilots from flying after receiving the COVID-19 vaccine,” said Dr. Sarah Branch, the director of vigilance and risk management of medicines for the MHRA. “There are currently no restrictions on aviation or other industries and activities post vaccination.” (Source -Emphasis added.)
Meanwhile, Sky News out of Australia is reporting that airline companies in Spain and Russia are warning COVID-19 “vaccinated” people not to travel because of the risk of blood clots.
NHS Doctor: Matt Hancock is “Not Fit for Public Office and Needs to be Removed Before He Inflicts Further Harm”
By Will Jones • Lockdown Sceptics • June 18, 2021
NHS GP Dr Helen Westwood, a member of HART, has written a letter to her MP Sir Graham Brady expressing her concerns about the possible Government plans for mandatory vaccination of healthcare workers and others. She previously wrote to him at the end of April and received a reply from Vaccines Minister Nadhim Zahawi that we published on Lockdown Sceptics offering the paper-thin reassurance that the U.K. “currently operates a system of informed consent for vaccinations”. “Why does he need to use the word ‘currently’?” she asked. “Are there plans for mandatory vaccination in future?” There were indeed, and she is not impressed – to the point of calling for Health Secretary Matt Hancock to be shown the door before he does any more damage. Here is her letter in full.
Dear Sir Graham,
I refer to my earlier correspondence dated March 2nd and April 26th regarding the concerns I have about the COVID-19 vaccination program.
I am grateful to you for raising these concerns with the Minister for COVID-19 Vaccine Deployment. Sadly Mr Zahawi seems to be either unwilling or unable to respond to my questions. Perhaps he is just delaying until the vaccine rollout has reached the whole adult population as it is due to imminently.
Mr Zahawi said in his letter to you that “the UK currently operates a system of informed consent for vaccinations”. Clearly the current proposals to make vaccinations compulsory for care home workers and possibly frontline NHS workers is completely counter to this. If a medical intervention is mandated for one group in society why not others? What about visitors to care homes? Delivery drivers? Shop workers? The list will go on and on.
I would like to draw your attention again to Article 6 of the Universal Declaration on Bioethics and Human Rights. It states that “any preventive, diagnostic and therapeutic medical intervention is only to be carried out with the prior, free and informed consent of the person concerned, based on adequate information. The consent should, where appropriate, be express and may be withdrawn by the person concerned at any time and for any reason without disadvantage or prejudice”. If an individual is being coerced into undergoing vaccination, through fear of losing their livelihood, then they are not giving “free and informed consent”. In effect, the person administering the vaccine in such circumstances is committing the criminal offence of Assault and Battery. We know that the pharmaceutical companies have been granted legal indemnity by the Government but what indemnity does the vaccinator have in this situation?
In my opinion to ask anyone to undergo a medical intervention for the benefit of others is profoundly unethical. Population immunity, achieved through high vaccine take-up, is a by-product rather than the primary reason for immunising an individual. This ethical problem is particularly pertinent to the arguments given for rolling the program out to children, but is also relevant to the majority of healthy working-age adults. The mortality risk from COVID-19 in this cohort is lower than that for seasonal influenza. People are being persuaded to have these vaccines to protect society at large. Why is nobody in Government paying attention to the significant morbidity and mortality being reported on the Yellow Card system in relation to the administration of the vaccines? Young healthy people are being exposed to risks, both known and unknown, in taking these vaccines yet have little to gain in terms of personal benefit. Dr Tess Lawrie wrote an open letter to MHRA Chief Executive Dr June Raine saying that “the MHRA now has more than enough evidence on the Yellow Card system to declare the COVID-19 vaccines unsafe for use in humans”. At the very least we should be pausing to review the data before coercing young care home workers into having this vaccine when the results of the phase 3 trials are not yet known or understood.
In my discussions with patients who have undergone vaccination I have come to realise that many are unaware that these vaccines do not yet have full marketing authorisation. Sadly, the vaccine trials have now been compromised by being unblinded and control arm participants being offered the active drug. Given that these vaccines are still in their experimental phase, surely point 1 of the Nuremberg code applies: the voluntary consent of the human subject is absolutely essential. How is this in any way compatible with mandatory vaccination?
According to Dominic Cummings, the Prime Minister referred to Matt Hancock as “fucking hopeless”. Having heard the Health Secretary say that there is a “material difference” in the duty of care owed by the state to those who have not yet been offered the vaccine compared to those that have not taken up the offer of vaccination, I would go as far as to say he is dangerous and a menace. He is not fit for public office and needs to be removed from his post before he inflicts further harm on the people of this country. The GMC’s Good Medical Practice guidance states that Doctors must “treat patients and colleagues fairly and without discrimination“. I do not think there is an exception to this based on vaccination status. Similarly the NHS constitution says that “the NHS provides a comprehensive service, available to all” and that staff has a “duty not to discriminate against patients or staff and to adhere to…human rights legislation”. With regard to patients it says “you have the right to accept or refuse treatment that is offered to you, and not to be given any…treatment unless you have given valid consent”. Perhaps the Health Secretary ought to familiarise himself with these documents.
Having read my comments you will not be surprised to learn that I still do not intend to take this vaccine currently. I refuse to be bullied into undergoing a medical intervention against my will. It is against everything I would advocate for my patients. With record waiting lists in the NHS it would seem to me to be unwise to risk losing a proportion of the workforce by forging ahead with plans for making COVID-19 vaccination compulsory.
Yours sincerely,
Dr Helen Westwood
CANCELLED: CDC’s Emergency Advisory Committee meeting tomorrow to consider myocarditis and giving Covid vaccines to our youth
By Meryl Nass, MD | June 17, 2021
CDC’s emergency meeting that was to be held June 18, called only 7 days ago to deal with bad news, was peremptorily cancelled today, at the 11th hour. In honor of Juneteenth. Really???
If the emergency they were responding to was the maiming of our youth with Covid vaccines, CDC could have called a halt to vaccinating that age group while more information was collected. They did not do that.
Had CDC’s spin doctors come up with a rationale for vaccinating young males for Covid, despite the increased risk to them (25 times the baseline rate, according to Israel’s Ministry of Health). Israel claimed the rate was 1/3,000 to 1/6,000 young male vaccine recipients. Some say, anecdotally, they have seen so many cases they think the rate is higher.
The first way this was spun was that 81% have fully recovered, and CDC is following the rest.
That sounded less good when you looked at CDC’s numbers and found they only reported data on a minority of all the cases reported to VAERS (over 800).
It sounded less good when a young woman, aged 19, just died after a heart transplant, necessitated by the myocarditis she got after a Covid 2nd dose. She was a student at Northwestern, and black. This does not bode well for mandated college vaccinations.
And now it gets even worse. Spain and Russia are advising those who were vaccinated to avoid flying due to an increased risk of blood clots.
Guess we will have to wait until CDC’s June 23-25 meeting to find out how the spin doctors explain all this.
Are the Covid-19 vaccines “safe and effective”?
Steve Kirsch | Trial Site News | June 16, 2021
A video presentation by Steve Kirsch, Executive Director of the Covid-19 Early Treatment Fund.
Watch Video at Trial Site News
Are there any risks associated with the COVID-19 vaccines currently authorized on an emergency use basis by the U.S. Food and Drug Administration (FDA)? Presently three genetic-based vaccines have been authorized via the emergency order including two mRNA-based vaccines (Moderna and Pfizer-BioNTech) as well as the adenovirus-based Johnson and Johnson product. Developed at historical speed under Operation Warp Speed, the mRNA-based technology foretells enormous implications for healthcare including the prospect of vaccines for cancer. An amazing research prowess has unfolded in response to the COVID-19 pandemic heralding profound breakthroughs that’ll benefit society for years to come. Governmental authorities have declared the vaccines both safe and effective and as TrialSite recently reported based on a change of law that waives the need for informed consent with investigational products. Both the U.S. Centers for Disease Control and Prevention (CDC) and FDA have declared that the risk-benefit analyses strongly indicate the risks of not getting a vaccination outweigh any risk of vaccination. They argue that the risks associated with COVID-19 are materially greater. Moreover, health authorities are on record that there is absolutely no correlation associated with the COVID-19 vaccines to any deaths as indicated by the CDC declaration. But have they sufficiently probed and pursued granular investigation into their own data? Have they undertaken the comprehensive analyses associated with what in the CDC VAERS is now close to 6,000 deaths. Are all of these unrelated to the vaccines? Steve Kirsch, the founder and executive director of the COVID-19 Early Treatment Fund (CETF), a regular contributor to the TrialSite recently conducted a more systematic and thorough analysis of the VAERS and CDC adverse event and death numbers reported in conjunction with the COVID-19 vaccines. The results are disturbing to say the least. TrialSite offers no opinion here other than the presentation of the highly successful MIT-trained engineer who has invested millions of his own funds into early stage treatment options targeting COVID-19. What follows is a summary of his deep dive into VAERS presented in this video.
Official CDC Position
The CDC is on the record that the now nearly 6,000 deaths reported in VAERS since December 2020, including “A review of available clinical information, including death certificates, autopsy, and medical records, has not established a causal link to COVID-19 vaccine.”
The analysis provided by Kirsch suggests that while nearly 6,000 are now entered into the voluntary system, he suggests the actual number could be undercounted by a magnitude of up to 5 times and a review of direct CDC excess death data indicates what the notable entrepreneur counts as 25,000 deaths that could be associated with the coronavirus vaccines.
The Presentation
The Kirsch presentation starts with an introduction to the CDC Vaccine Adverse Event Reporting System known as VAERS with a review of some key indicators including reported deaths. Open to the public, he reveals by June 4th the following adverse events were associated with the COVID-19 vaccines:
Reported Event #s Deaths 5,088 Hospitalizations 19,587 Urgent Care 43,891 Office Visits 58,800 Heart Attacks 2,190 Anaphylaxis 1,459 Bells Palsy 1,737 Thrombocytopenia/Low Platelet 1,564 Myocarditis/Pericarditis 1,087
A review of available clinical information, including death certificates, autopsy, and medical records, has not established a causal link to COVID-19 vaccines.
At 12:15 into the presentation Mr. Kirsch reveals a data distribution revealing a dramatic spike in deaths associated with the COVID-19. Moreover in this data analysis it’s revealed that the majority of deaths occur closer to the actual time of the vaccination event indicating a higher probability of a causal relationship.
At 12:49 he presents the data findings indicating that overwhelming the incidents of heart attacks associated with the VAERS COVID-19 vaccine spike within a day to three days after the vaccination event. He also emphasizes that the indication of Myocarditis/Pericarditis actually increases with vaccination as age decreases which is counter intuitive in that young people should have less probability of experiencing such heart related troubles. Is the vaccine causally connected to this data?
At 15:51 in the presentation Kirsch depicts again the growing numbers of deaths corresponding to the release of the vaccines under emergency use authorization by mid-December 2020. At 18:55 he reveals a corresponding increase in excess deaths reported by the CDC.
Kirsch goes on at 26:13 to discuss the imperative to consider a time out in the process to at least investigate these safety data signals. At 28:09 Kirsch raises the imperative for informed consent under the Declaration of Helsinki. Although as TrialSite reported the law was changed in 2016 thus waiving the need for informed consent with investigational products deemed safe.
At 32:22 Mr. Kirsch discusses early treatment options for COVID-19. He shares that considerable research has gone on pointing to a number of potential treatments for early onset COVID-19 that can serve to help combat COVID-19. A risk-benefit comparison at 41:50 showcases at least one argument that early stage treatments currently under study should be accelerated.
The presenter offers a plethora of other information that merits review for those interested in a debate on this topic.
Kirsch commented on the findings “The narrative is that the COVID-19 vaccines are safe and effective but the truth is that the data points to an otherwise alternative conclusion.” Kirsch declared that “if anyone was paying attention they would have picked up these safety signals by the end of January.”
Data-Driven Truth or Random Coincidence?
TrialSIte cannot advocate one position over another but rather can serve to share information that fits within the guidelines of the platform for purposes of discussion and hopefully healthy debate. This isn’t a platform for attacking others but rather one that fosters awareness, transparency and engagement. The data present in the CDC VAERS database as well as the CDC death reports do indicate a material spike in activity associated with the coronavirus vaccines. Does the CDC’s position that none of these deaths are conclusively correlated to the vaccine itself despite the data in this presentation revealing a disturbing trend of adverse events and death within a day to three days within the vaccination event? It’s not clear but TrialSite invites the CDC and others on to the platform to put forth an explanation.
The EEOC Did NOT Say Federal Law Permits Requiring a COVID-19 Vaccine
Informed Consent Action Network | June 16, 2021
In the article, “Can employers require workers to get the COVID vaccine?”, Bailey Aldridge claims that, given the updated rules of the Equal Employment Opportunity Commission (EEOC), “your employer can require you to get a COVID vaccine.” Aldridge even claims that “The EEOC says there are no federal laws that prevent an employer from requiring employees who are physically in the workplace to get the COVID-19 vaccine.”
The EEOC’s guidance, however, does not claim that an employer can legally require an emergency use COVID-19 vaccine. The EEOC guidance merely states that the “federal EEO [Equal Employment Opportunity] laws do not prevent an employer from requiring” an emergency authorized COVID-19 vaccine. That is not surprising because the EEO laws apply only to discrimination based on certain protected classes, such as race, religion and national origin.
Federal law is, of course, far broader than the narrow EEO laws. In recognizing that there are other federal laws that do prohibit an employer from requiring a COVID-19 vaccine, the EEOC’s guidance also states that, “These three vaccines were granted Emergency Use Authorizations (EUA) by the FDA” and that, “It is beyond the EEOC’s jurisdiction to discuss the legal implications of EUA or the FDA approach.”
When one reviews the FDA’s EUA and its approved labeling, a.k.a. “fact sheets,” for each COVID-19 vaccine, they each clearly provide that: “It is [the vaccine recipient’s] choice to receive or not receive the COVID-19 Vaccine.” The reason each fact sheet includes this language is because the same section of the Federal Food, Drug, and Cosmetic Act that authorizes the FDA to grant an EUA also requires the Secretary of Health and Human Services to “ensure that individuals to whom the product is administered are informed … of the option to accept or refuse administration of the product.”
That same section of the Act also authorized the Secretary, and only the Secretary, to provide the “consequences” for refusing to receive an EUA product and the EUAs for each COVID-19 vaccine do not include permission to terminate an employee for refusing the vaccine.
ICAN hopes that the Department of Justice will do its job and enforce the federal law prohibiting mandating an EUA vaccine and will continue to push it to enforce this important law.
The COVID vaccine and depopulation; the beginning of the trail

By Jon Rappoport | No More Fake News | June 14, 2021
Since the rollout of the COVID vaccines, reports of bleeding, irregular menstrual cycles, and miscarriages have surfaced.
Children’s Health Defense, February 3, 2021: “Health Officials Push Pregnant Women to Get COVID Shots, Despite Known Risks” [1]:
“… as of Feb. 12, the Vaccine Adverse Event Reporting System (VAERS) had already received 111 reports of adverse events experienced by women who were pregnant at the time of their Pfizer or Moderna injection…”
“The first such report was submitted Dec. 22, just 10 days after authorization of the Pfizer vaccine. Nearly a third (31%) of the women had miscarriages or preterm births, which occurred within as little as one day of injection — the majority after a single dose of vaccine.”
“The descriptions of miscarriages and premature births accompanying the VAERS reports are tragic and hair-raising.”
“For example, a 37-year-old who received her first dose of the Moderna vaccine at 28 weeks of pregnancy, just after an ultrasound showed a healthy placenta, was discovered to have ‘significant placenta issues just one week later.’ A repeat ultrasound showed that the placenta had ‘calcified and aged prematurely,’ leading to recommended hospitalization for the duration of her pregnancy.”
“A 35-year-old, also vaccinated at around 29 weeks of pregnancy, ‘noticed decreased motion of the baby’ two days after receiving the Pfizer injection. The following day, ‘the baby was found to not have a heartbeat’.”
“Two Pfizer vaccine recipients in earlier stages of pregnancy (first trimester) had miscarriages after experiencing ‘intolerable’ abdominal pain and uterine bleeding extensive enough, in one case, to require ‘emergency surgery and a blood transfusion’.”
“… the World Health Organization on Jan. 27 issued guidance advising against pregnant women getting Moderna’s COVID vaccine — only to reverse that guidance two days later, as The New York Times reported.”
“Documented risks of vaccination during pregnancy include miscarriage as well as neurodevelopmental problems arising from maternal immune activation (an inflammatory response in the mother that can harm fetal brain development).”
Concerning that last paragraph: Before the experimental RNA COVID vaccines were authorized, RNA technology had experienced failures and serious problems in clinical trials—because the immune system went into overdrive. It is this immune hyper-response that may be responsible for the recent reported miscarriages and pre-term births; the body basically attacks itself.
This RNA effect is documented in studies published before 2019. The vaccine makers and public health agencies are well aware of it.
But this is just the beginning of the story, because what is happening to vaccinated women now may be part of a much larger history, involving extensive research on medically induced birth control—also known as population reduction.
In the vaccine research community, it’s an open secret that the Rockefeller Fund, the UN, and other groups have been backing the development of vaccines that function as agents of population reduction. This work has been going on for decades.
What follows are examples of the evidence. They cite the Third World as the target, but no one should take that as a hideous sign that depopulation efforts are confined to one group of countries. These efforts are universal.
The late well-known journalist, Alexander Cockburn, on the op ed page of the LA Times, on September 8, 1994, in his piece “Real U.S. Policy in Third World: Sterilization: Disregard the ’empowerment’ shoe polish–the goal is to keep the natives from breeding,” [2] reviewed the infamous Kissinger-commissioned 1974 National Security Study Memorandum 200, “which addressed population issues”:
“… the true concern of Kissinger analysts [in Memorandum 200] was maintenance of US access to Third World resources. They worried that the ‘political consequences’ of population growth [in the Third World] could produce internal instability … With famine and food riots and the breakdown of social order in such countries, [the Kissinger memo warns that] ‘the smooth flow of needed materials will be jeopardized.’”
In other words, too many people equals disruption for the transnational corporations, who steal nations from those very people. Therefore, reduce the population.
Therefore, develop a vaccine that does that job.
Journalist Cockburn, in his LA Times piece, goes on to say that the writers of the Kissinger memo “favored sterilization over food aid.” He notes that, “By 1977, Reimart Ravenholt, the director of AID’s [US Agency for International Development] population program, was saying that his agency’s goal was to sterilize one-quarter of the world’s women.”
Here is an astonishing journal paper. November, 1993. FASEB Journal, volume 7, pp.1381-1385. Authors—Stephan Dirnhofer et al. Dirnhofer was a member of the Institute for Biomedical Aging Research of the Austrian Academy of Sciences.
A quote from the paper: “Our study provides insights into possible modes of action of the birth control vaccine promoted by the Task Force on Birth Control Vaccines of the WHO (World Health Organization).”
A birth control vaccine? Yes. A vaccine whose purpose is to achieve miscarriages. This particular vaccine was apparently just one of several anti-fertility vaccines the Task Force was promoting.
And yes, there is a Task Force on Birth Control Vaccines at the WHO. This journal paper focuses on a hormone called human chorionic gonadotropin B (hCG). There is a heading in the FASEB paper (p.1382) called “Ability of antibodies to neutralize the biological activity of hCG.” The authors are trying to discover whether a state of non-fertility can be achieved by blocking the normal activity of hCG.
This hormone helps sustain pregnancy. If the immune system can be trained to attack it, pregnancy will collapse and a miscarriage will occur.
Another journal paper: The British Medical Bulletin, volume 49, 1993. “Contraceptive Vaccines.” [4] The authors—RJ Aitken et al. From the MRC Reproductive Biology Unit, University of Edinburgh, Edinburgh, UK.
“Three major approaches to contraceptive vaccine development are being pursued at the present time. The most advanced approach, which has already reached the stage of phase 2 clinical trials, involves the induction of immunity against human chorionic gonadotrophin (hCG). Vaccines are being engineered … incorporating tetanus or diptheria toxoid linked to a variety of hCG-based peptides … Clinical trials have revealed that such preparations are capable of stimulating the production of anti-hCG antibodies…”
The authors are talking about creating an immune response against this female hormone. Training a woman’s body to react against one of its own secreted hormones. The authors state, “The fundamental principle behind this approach to contraceptive vaccine development is to prevent the maternal recognition of pregnancy by inducing a state of immunity against hGC, the hormone that signals the presence of the embryo to the maternal endocrine system.”
Stop the female body from recognizing a state of pregnancy. Get the body to treat the natural hormone hCG as an intruder, a disease agent, and mobilize the forces of the immune system against it. Create a synthetic effect, an engineered effect, by which the mother’s “maternal endocrine system” does not swing into gear when pregnancy occurs. The result? The embryo in the mother is swept away by her next period—since hGC, which signals the existence of the pregnancy and halts menstruation cycles, is now treated as a disease entity.
The authors put it this way: “In principle, the induction of immunity against hGC should lead to a sequence of normal, or slightly extended, menstrual cycles during which any pregnancies would be terminated…”
Miscarriage would then be the “normal” state of affairs.
“During the next decade the world’s population is set to rise by around 500 million. Moreover, because the rates of population growth in the developing countries of Africa, South America, and Asia will be so much greater than the rest of the world, the distribution of this dramatic population growth will be uneven…”
Two other vaccine methods are described. They “aim to prevent conception by interfering with the intricate cascade of interactive events that characterize the union of male and female gametes at fertilization.”
In a letter to The Lancet, p.1222, Volume 339, May 16, 1992, “Cameroon: Vaccination and politics,” [5] Peter Ndumbe and Emmanuel Yenshu report on their efforts to analyze widespread popular resistance to a tetanus vaccine given in the northwest province of Cameroon.
Two of the reasons women rejected the vaccine: it was given only to “females of childbearing age,” and people heard that a “sterilizing agent” was present in the vaccine.
Indeed, these are the charges leveled against past tetanus vaccine campaigns in Kenya and the Philippines. In Kenya (2014), an intense standoff occurred—with the Catholic Doctors Association and Kenyan Catholic Bishops on one side, and the Kenyan government Health Authority on the other.
Both sides claimed they tested vials of the tetanus vaccine. The Catholic groups’ lab report indicated the vaccine contained hCG; the Health Authority’s report indicated no hCG was present.
“Mass Sterilization: Kenyan Doctors Find Anti-Fertility Agent in UN Tetanus Vaccine,” [6] November 8, 2014, by Steve Weatherbe, earth-heal.com: “Kenya’s Catholic bishops are charging two United Nations organizations with sterilizing millions of girls and women under cover of an anti-tetanus inoculation program sponsored by the Kenyan government.”
“According to a statement released Tuesday by the Kenya Catholic Doctors Association, the organization has found an antigen that causes miscarriages in a vaccine being administered to 2.3 million girls and women by the World Health Organization and UNICEF. Priests throughout Kenya reportedly are advising their congregations to refuse the vaccine.”
“’We sent six samples from around Kenya to laboratories in South Africa. They tested positive for the HCG antigen,’ Dr. Muhame Ngare of the Mercy Medical Centre in Nairobi told LifeSiteNews. “They were all laced with HCG’.”
“Dr. Ngare, spokesman for the Kenya Catholic Doctors Association, stated in a bulletin released November 4, ‘This proved right our worst fears; that this WHO campaign is not about eradicating neonatal tetanus but a well-coordinated forceful population control mass sterilization exercise using a proven fertility regulating vaccine. This evidence was presented to the Ministry of Health before the third round of immunization but was ignored’.”
In the present situation, we have COVID vaccines. They’re being injected all over the world. Women are making reports of bleeding, disrupted menstrual cycles, miscarriages, pre-term births.
There is a long history, extending to the present day, of elite groups researching and deploying vaccines designed to terminate pregnancies, for the purpose of depopulation.
The elite groups and players behind the current “pandemic”—the WHO, UN, Bill Gates, Rockefeller Institute, etc.—are the same groups who have been developing depopulation vaccines.
This is called a clue.
It lights up like a giant sign, at the beginning of the trail of investigation into the use of COVID vaccines for depopulation.
More coming in the next article…
SOURCES:
[1] https://childrenshealthdefense.org/defender/health-officials-push-pregnant-women-covid-vaccine/
[2] https://www.latimes.com/archives/la-xpm-1994-09-08-me-35791-story.html
[3] https://faseb.onlinelibrary.wiley.com/doi/pdf/10.1096/fasebj.7.14.7693535
[4] https://academic.oup.com/bmb/article-abstract/49/1/88/279720
[5] https://www.thelancet.com/journals/lancet/article/PII0140-6736%2892%2991151-W/fulltext
Featured Video

Get ready for the big Israeli false flag cyber-attack
or go to
Aletho News Archives – Video-Images
From the Archives
Some Call It Conspiracy Theory – Part 1
BY IAIN DAVIS | SEPTEMBER 25, 2023
There are certain assumptions that are applied to anyone labelled a “conspiracy theorist”—and all of them are fallacies. Indeed, the term “conspiracy theory” is nothing more than a propaganda construct designed to silence debate and censor opinion on a range of subjects. Most particularly, it is used as a pejorative to marginalise and discredit whoever challenge the pronouncements and edicts of the State and of the Establishment—that is, the public and private entities that control the State and that profit from the State.
Those of us who have legitimate criticisms of government and its institutions and representatives, who are therefore labelled “conspiracy theorists,” face a dilemma. We can embrace the term and attempt to redefine it or we can reject it outright. Either way, it is evident that the people who weaponise the “conspiracy theory” label will continue to use it as long as it serves their propaganda purposes.
One of the most insidious aspects of the “conspiracy theory” fabrication is that the falsehoods associated with the term have been successfully seeded into the public’s consciousness. Often, propagandists need do no more than slap this label on the targeted opinion and the audience will immediately dismiss that viewpoint as a “lunatic conspiracy theory.” Sadly, this knee-jerk reaction is usually made absent any consideration or even familiarity with the evidence presented by that so-called “lunatic conspiracy theorist.”
This was the reason why “conspiracy theorist” label was created. The State and its propagandists do not want the public to even be aware of inconvenient evidence, let alone to examine it. The challenging evidence is buried under the “wild conspiracy theory” label, thereby signalling to the unsuspecting public that they should automatically reject all of the offered facts and evidence.
There are a number of components that collectively form the conspiracy theory canard. Let’s break them down. … continue
Blog Roll
 Aletho News
- ‘Stop Putting Drugs in Our Food’: Scientists Link Folic Acid in Food to Rising Rates of Colorectal Cancer
- The 14 Things That Happen to Your Newborn in the First 48 Hours
- JFK’s Forgotten Confrontation with Israel
- Trump’s Cyber Director Pick Has Deep Ties To Israeli Intelligence
- Get ready for the big Israeli false flag cyber-attack
- The Ukrainian Reset experiment: A war and surveillance state blueprint for the EU
- Pentagon fails ninth financial audit in a row, unable to account for trillions in assets
- Russia rejects Danish plot claims, vows response to expulsion
- Study of 14,000 Children Links Vaccination to Higher Rates of Chronic Illness
- Strike Iran Again, Open Pandora’s Box | Brian McGlinchey
- If Americans Knew
- Reporting Raises Fresh Questions About Israeli Role in CNN’s ‘Preposterous’ Iranian Dirty Bomb Story
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- Under the West’s watch, genocide apologism has become entirely respectable
- Israeli Diplomat Offered Iowa Attorney General Free Trip, Then Asked for Favors
- On World Children’s Day, 350 Palestinian Children Remain in Israeli Prisons
- Why Is Israel Jailing a Palestinian Student Without Trial? Because It Can
- ICJ ruling on Rohingya genocide could strengthen South Africa’s case against Israel
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- Newly nominated House Speaker funded Gaza genocide
- Leaked: How Silicon Valley Elites Bankrolled an Anti-Migrant, Pro-Israel Propaganda Machine
- No Tricks Zone
- New Study: Modern Temps Are Among The Coldest Of The Last 10,000 Years In East Central Europe
- Germany’s Renewable Energies Lead to 1.4 Billion Euro Electric Power Trade Deficit
- Argentina’s Perito Moreno Glacier Joins Antarctica and Arctic In Defying Doomsday Melt Claims
- New Study: Barents Sea Temperatures Were Warmer And Sea Ice Less Extensive In The 1700s Than Today
- German Authorities Start Initiative To Evaluate Public Register For Climate “Disinformation” Spreaders!
- Zonal Asymmetry of Temperature Change in the Antarctic Circumpolar Current
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean

