DECLARATION OF CANADIAN PHYSICIANS FOR SCIENCE AND TRUTH
The Declaration
We are a broad and diverse group of Canadian physicians from across Canada who are sending out this urgent declaration to the Colleges of Physicians and Surgeons of our various Provinces and Territories and to the Public at large, whom we serve.
On April 30, 2021, Ontario’s physician licensing body, the College of Physicians and Surgeons of Ontario (CPSO), issued a statement forbidding physicians from questioning or debating any or all of the official measures imposed in response to COVID-19. 1
The CPSO then went on to threaten physicians with punishment – investigations and disciplinary action.
We regard this recent statement of the CPSO to be unethical, anti-science and deeply disturbing.
As physicians, our primary duty of care is not to the CPSO or any other authority, but to our patients.
When we became physicians, we pledged to put our patients first and that our ethical and professional duty is always first toward our patients. The CPSO statement orders us to violate our duty and pledge to our patients in the following ways:
1. Denial of the Scientific Method itself: The CPSO is ordering physicians to put aside the scientific method and to not debate the processes and conclusions of science.
We physicians know and continue to believe that throughout history, opposing views, vigorous debate and openness to new ideas have been the bedrock of scientific progress. Any major advance in science has been arrived at by practitioners vigorously questioning “official” narratives and following a different path in the pursuit of truth.
2. Violation of our Pledge to use Evidence-Based Medicine for our patients: By ordering us not to debate and not to question, the CPSO is also asking us to violate our pledge to our patients that we will always seek the best, evidence-based scientific methods for them and advocate vigorously on their behalf.
The CPSO statement orders physicians for example, not to discuss or communicate with the public about “lockdown” measures. Lockdown measures are the subject of lively debate by world-renown and widely respected experts and there are widely divergent views on this subject. The explicitly anti-lockdown Great Barrington Declaration – https://gbdeclaration.org – was written by experts from Harvard, Stanford and Oxford Universities and more than 40,000 physicians from all over the world have signed this declaration. Several international experts including Martin Kuldorf (Harvard), David Katz (Yale), Jay Bhattacharya (Stanford) and Sunetra Gupta (Oxford) continue to strongly oppose lockdowns.
The CPSO is ordering physicians to express only pro-lockdown views, or else face investigation and discipline. This tyrannical, anti-science CPSO directive is regarded by thousands of Canadian physicians and scientists as unsupported by science and as violating the first duty of care to our patients.
3. Violation of Duty of Informed Consent: The CPSO is also ordering physicians to violate the sacred duty of informed consent – which is the process by which the patient/public is fully informed of the risks, benefits and any alternatives to the treatment or intervention, before consent is given.
The Nuremberg Code, drafted in the aftermath of the atrocities perpetrated within the Nazi concentration camps – where horrific medical experiments were performed on inmates without consent – expressly forbids the imposition of any kind of intervention without informed consent.
In the case of the lockdown intervention for example, physicians have a fiduciary duty to point out to the public that lockdowns impose their own costs on society, including in greatly increased depression and suicide rates, delayed investigation and treatment of cancer (including delayed surgery, chemotherapy and radiation therapy), ballooning surgical waiting lists (with attendant greatly increased patient suffering) and increased rates of child and domestic abuse.
We physicians believe that with the CPSO statement of 30 April 2021, a watershed moment in the assault on free speech and scientific inquiry has been reached.
By ordering physicians to be silent and follow only one narrative, or else face discipline and censure, the CPSO is asking us to violate our conscience, our professional ethics, the Nuremberg code and the scientific pursuit of truth.
We will never comply and will always put our patients first.
The CPSO must immediately withdraw and rescind its statement of 30 April 2021.
We also give notice to other Canadian and international licensing authorities for physicians and allied professions that the stifling of scientific inquiry and any order to violate our conscience and professional pledge to our patients, itself may constitute a crime against humanity.
1 College of Physicians and Surgeons of Ontario Statement on Public Health Misinformation (4/30/21). https://twitter.com/cpso_ca/status/1388211577770348544
The College is aware and concerned about the increase of misinformation circulating on social media and other platforms regarding physicians who are publicly contradicting public health orders and recommendations. Physicians hold a unique position of trust with the public and have a professional responsibility to not communicate anti-vaccine, anti-masking, anti-distancing and anti-lockdown statements and/or promoting unsupported, unproven treatments for COVID-19. Physicians must not make comments or provide advice that encourages the public to act contrary to public health orders and recommendations. Physicians who put the public at risk may face an investigation by the CPSO and disciplinary action, when warranted. When offering opinions, physicians must be guided by the law, regulatory standards, and the code of ethics and professional conduct. The information shared must not be misleading or deceptive and must be supported by available evidence and science.
Signatures
- Anne Shannon
- Andrea Roy
- Adam Salt
- Alexandre Guay
- Andrea Zaretsky
- Andrew Mahon
- annkwist@rogers.com Kwist
- Antonio Coffa
- Deno Gettas
- Beata G
- Bernard de Souza
- Beth Lindhorst
- Karen Mackey
- Bruce McKay
- Ron Bublitz
- Carla Dancey
- Deb Mair
- ROBERT PAQUETTE
- Christine Pohanka
- Cindy Create
- Claire Gosselin
- Corinne Mackenzie
- Barbara & David Schmidt
- Judith Robinson
- Donna Cuomo
- Deborah Kay
- Julia McLaren
- Dwayne Vann
- Emma Sattar
- Dave Thompson
- Elizabeth Romanowska-Konsik
- Darlene Elias
- Elizabeth Balcar
- Erin Beckman
- Richard Caviedes
- Chris Filby
- Pat Brown
- Rachel Vlietstra
- Greg Schmalz
- Gerard Lamontagne
- Freya Godard
- Ken Roberson
- Blaine Goodine
- Grazyna Sanchez
- Mary Hale
- Anja Reich
- Silvia engels
- Helke Ferrie
- Vicki Samson
- Laura Peterson
- Michelle Greenwell
- Jackie Beninato
- Jake Hoheisel
- Jan Fiss
- Jeff Graham
- Jennifer LONERGAN
- Judy Symington
- Janine Jalbert
- Jordyn Kaye
- Jeremy McKee
- Julie Montpetit
- Kathleen Perry
- Kathy Braun
- Katia Rodrigues
- Keith Baxter
- Cheryl Leite
- Larissa Flanagan
- Laurie Fetherstonhaugh
- Lauren Annez
- Sharon Leonard
- Lorraine Struyk
- larry hachey
- Linda Winger
- Luciano Perna
- Madeleine Menard
- Marissa Secord
- Marlena Murray
- Marnee Stern
- Lori McKay
- Michael Germain
- Michele Mihalik
- Michelle Losier
- Marlee Moore
- Nancy Chown
- Nikki Pulla
- Norma Ford
- Nicoline Lentze
- Nigel Bell
- Melodie VanderWal
- Colleen Roberts
- Pamela Velos
- Rick Hayter
- Rochagné Kilian
- Dale & Roeli Lutz
- ronald beaulieu
- Sarah MacInnis
- Sarah Pollard
- Sara Pahlevan
- Sabina SARGEANT
- Stephanie Cheung
- Sebastian Rozdzynski
- Sherry Lee
- Jacinthe Phillips
- Sophie Hawkins
- Steve Foget
- Sue Timmermans
- sydney felker
- Taron Puri
- Christine Simpson
- Tibor Finesz
- Lara Doucette
- Thomas J Tassé
- Thomas Russell
- Erica Tratch
- Summer Hanes
- Uwe Grunert
- Valerie Debicki
- Vladikir Gagachev
- Verna Hutchinson
- Roger Baird
Dr Mike Yeadon – “Please warn everyone not to go near top-up vaccines”
THE DAILY EXPOSE • MAY 9, 2021
We spoke to Dr Mike Yeadon about his views on the experimental Covid-19 vaccines, the medicine regulators approving them and his fears for the future.
From the outset, Dr. Yeadon said “I’m well aware of the global crimes against humanity being perpetrated against a large proportion of the worlds population.
“I feel great fear, but I’m not deterred from giving expert testimony to multiple groups of able lawyers like Rocco Galati in Canada and Reiner Fuellmich in Germany.
“I have absolutely no doubt that we are in the presence of evil (not a determination I’ve ever made before in a 40-year research career) and dangerous products.
“In the U.K., it’s abundantly clear that the authorities are bent on a course which will result in administering ‘vaccines’ to as many of the population as they can. This is madness, because even if these agents were legitimate, protection is needed only by those at notably elevated risk of death from the virus. In those people, there might even be an argument that the risks are worth bearing. And there definitely are risks which are what I call ‘mechanistic’: inbuilt in the way they work.
“But all the other people, those in good health and younger than 60 years, perhaps a little older, they don’t perish from the virus. In this large group, it’s wholly unethical to administer something novel and for which the potential for unwanted effects after a few months is completely uncharacterized.
“In no other era would it be wise to do what is stated as the intention.
“Since I know this with certainty, and I know those driving it know this too, we have to enquire: What is their motive?
“While I don’t know, I have strong theoretical answers, only one of which relates to money and that motive doesn’t work, because the same quantum can be arrived at by doubling the unit cost and giving the agent to half as many people. Dilemma solved. So it’s something else. Appreciating that, by entire population, it is also intended that minor children and eventually babies are to be included in the net, and that’s what I interpret to be an evil act.
“There is no medical rationale for it. Knowing as I do that the design of these ‘vaccines’ results, in the expression in the bodies of recipients, expression of the spike protein, which has adverse biological effects of its own which, in some people, are harmful (initiating blood coagulation and activating the immune ‘complement system’), I’m determined to point out that those not at risk from this virus should not be exposed to the risk of unwanted effects from these agents.”
The Israel Supreme Court decision last week cancelling COVID flight restrictions said: “In the future, any new restrictions on travel into or out of Israel need, in legal terms, a comprehensive, factual, data-based foundation.”
In a talk you gave four months ago, you said –
“The most likely duration of immunity to a respiratory virus like SARS CoV-2 is multiple years. Why do I say that? We actually have the data for a virus that swept through parts of the world seventeen years ago called SARS, and remember SARS CoV-2 is 80% similar to SARS, so I think that’s the best comparison that anyone can provide.
“The evidence is clear: These very clever cellular immunologists studied all the people they could get hold of who had survived SARS 17 years ago. They took a blood sample, and they tested whether they responded or not to the original SARS and they all did; they all had perfectly normal, robust T cell memory. They were actually also protected against SARS CoV-2, because they’re so similar; it’s cross immunity.
“So, I would say the best data that exists is that immunity should be robust for at least 17 years. I think it’s entirely possible that it is lifelong. The style of the responses of these people’s T cells were the same as if you’ve been vaccinated and then you come back years later to see if that immunity has been retained. So I think the evidence is really strong that the duration of immunity will be multiple years, and possibly lifelong.”
In other words, previous exposure to SARS – that is, a variant similar to SARS CoV-2 – bestowed SARS CoV-2 immunity.
The Israel government cites new variants to justify lockdowns, flight closures, restrictions, and Green Passport issuance. Given the Supreme Court verdict, do you think it may be possible to preempt future government measures with accurate information about variants, immunity, herd immunity, etc. that could be provided to the lawyers who will be challenging those future measures?
Yeadon: “What I outlined in relation to immunity to SARS is precisely what we’re seeing with SARS-CoV-2.The study is from one of the best labs in their field.” So, theoretically, people could test their T-cell immunity by measuring the responses of cells in a small sample of their blood. There are such tests, they are not “high throughput” and they are likely to cost a few hundred USD each on scale. But not thousands. The test I’m aware of is not yet commercially available, but research only in U.K.
“However, I expect the company could be induced to provide test kits “for research” on scale, subject to an agreement. If you were to arrange to test a few thousand non vaccinated Israelis, it may be a double edged sword. Based on other countries experiences, 30-50% of people had prior immunity & additionally around 25% have been infected & are now immune.
“Personally, I wouldn’t want to deal with the authorities on their own terms: that you’re suspected as a source of infection until proven otherwise. You shouldn’t need to be proving you’re not a health risk to others. Those without symptoms are never a health threat to others. And in any case, once those who are concerned about the virus are vaccinated, there is just no argument for anyone else needing to be vaccinated.”
My understanding of a “leaky vaccine” is that it only lessens symptoms in the vaccinated, but does not stop transmission; it therefore allows the spread of what then becomes a more deadly virus.
For example, in China they deliberately use leaky Avian Flu vaccines to quickly cull flocks of chicken, because the unvaccinated die within three days. In Marek’s Disease, from which they needed to save all the chickens, the only solution was to vaccinate 100% of the flock, because all unvaccinated were at high risk of death. So how a leaky vax is utilized is intention-driven, that is, it is possible that the intent can be to cause great harm to the unvaccinated.
Stronger strains usually would not propagate through a population because they kill the host too rapidly, but if the vaccinated experience only less-serious disease, then they spread these strains to the unvaccinated who contract serious disease and die.
Do you agree with this assessment? Furthermore, do you agree that if the unvaccinated become the susceptible ones, the only way forward is HCQ prophylaxis for those who haven’t already had COVID-19?
Would the Zelenko Protocol work against these stronger strains if this is the case? And if many already have the aforementioned previous “17-year SARS immunity”, would that then not protect from any super-variant?
“I think the Gerrt Vanden Bossche story is highly suspect. There is no evidence at all that vaccination is leading or will lead to ‘dangerous variants’. I am worried that it’s some kind of trick.
“As a general rule, variants form very often, routinely, and tend to become less dangerous & more infectious over time, as it comes into equilibrium with its human host. Variants generally don’t become more dangerous.
“No variant differs from the original sequence by more than 0.3%. In other words, all variants are at least 99.7% identical to the Wuhan sequence.
“It’s a fiction, and an evil one at that, that variants are likely to “escape immunity.”
“Not only is it intrinsically unlikely – because this degree of similarity of variants means zero chance that an immune person (whether from natural infection or from vaccination) will be made ill by a variant – but it’s empirically supported by high-quality research.
“The research I refer to shows that people recovering from infection or who have been vaccinated ALL have a wide range of immune cells which recognize ALL the variants.
“This paper shows WHY the extensive molecular recognition by the immune system makes the tiny changes in variants irrelevant.
“I cannot say strongly enough: The stories around variants and need for top up vaccines are FALSE. I am concerned there is a very malign reason behind all this. It is certainly not backed by the best ways to look at immunity. The claims always lack substance when examined, and utilize various tricks, like manipulating conditions for testing the effectiveness of antibodies. Antibodies are probably rather unimportant in host protection against this virus. There have been a few ‘natural experiments’, people who unfortunately cannot make antibodies, yet are able quite successfully to repel this virus. They definitely are better off with antibodies than without. I mention these rare patients because they show that antibodies are not essential to host immunity, so some contrived test in a lab of antibodies and engineered variant viruses do NOT justify need for top up vaccines.
“The only people who might remain vulnerable and need prophylaxis or treatment are those who are elderly and/or ill and do not wish to receive a vaccine (as is their right).
“The good news is that there are multiple choices available: hydroxychloroquine, ivermectin, budesonide (inhaled steroid used in asthmatics), and of course oral Vitamin D, zinc, azithromycin etc. These reduce the severity to such an extent that this virus did not need to become a public health crisis.”
Do you feel the MHRA does a good job regulating ‘big pharma’? In what ways does ‘big pharma’ get around the regulator? Do you feel they did so for the mRNA jab?
“Until recently, I had high regard for global medicines regulators. When I was in Pfizer, and later CEO of a biotech I founded (Ziarco, later acquired by Novartis), we interacted respectfully with FDA, EMA, and the MHRA.
Always good quality interactions.
“Recently, I noticed that the Bill & Melinda Gates Foundation (BMGF) had made a grant to the Medicines and Healthcare products Regulatory Agency (MHRA)! Can that ever be appropriate? They’re funded by public money. They should never accept money from a private body.
“So here is an example where the U.K. regulator has a conflict of interest.” The European Medicines Agency failed to require certain things as disclosed in the ‘hack’ of their files while reviewing the Pfizer vaccine.
“You can find examples on Reiner Fuellmich’s “Corona Committee” online.
“So I no longer believe the regulators are capable of protecting us. ‘Approval’ is therefore meaningless.
“Dr. Wolfgang Wodarg and I petitioned the EMA Dec 1, 2020 on the genetic vaccines. They ignored us.
“Recently, we wrote privately to them, warning of blood clots, they ignored us. When we went public with our letter, we were completely censored. Days later, more than ten countries paused use of a vaccine citing blood clots.
“I think the big money of pharma plus cash from BMGF creates the environment where saying no just isn’t an option for the regulator.
“I must return to the issue of ‘top up vaccines’ (booster shots) and it is this whole narrative which I fear will he exploited and used to gain unparalleled power over us.
“PLEASE warn every person not to go near top up vaccines. There is absolutely no need to them. As there’s no need for them, yet they’re being made in pharma, and regulators have stood aside (no safety testing), I can only deduce they will be used for nefarious purposes.
“For example, if someone wished to harm or kill a significant proportion of the worlds population over the next few years, the systems being put in place right now will enable it.
“It’s my considered view that it is entirely possible that this will be used for massive-scale depopulation.”
Texas Medical Doctors Testify Before State Senate to Oppose Mandatory COVID Shots
By Brian Shilhavy | Health Impact News | May 8, 2021
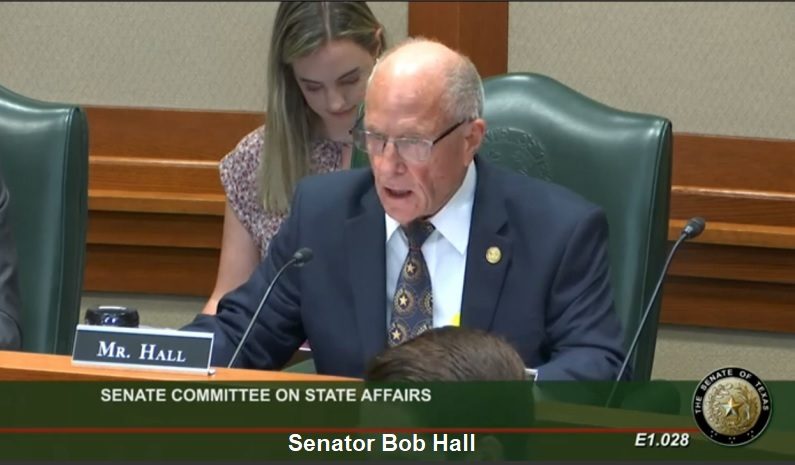
This past week the Texas Senate Committee on State Affairs took testimony from Texas physicians regarding SB 1669: Stop Forced Vaccination and Vaccine Passports in Texas.
SB 1669 was sponsored by Senator Bob Hall.
You can learn more about this bill at the National Vaccine Information Center’s Advocacy Portal (registration required.)
Here is some of the text provided to the public regarding Senate Bill 1669:
Contact your Texas State Legislators and Demand No Forced Vaccination, No Vaccine Passports, No Exceptions – Support SB 1669
Mandated vaccination in Texas with COVID-19 vaccines will be the reality unless the legislature takes decisive action now. In fact, it has already started happening.
Houston Methodist Hospital has told its 26,000 employees to get vaccinated by June 7th or get fired. Atria Senior Living, which has 16 facilities in Texas, is requiring all employees to receive 2 COVID-19 vaccines by May 1, 2021 as a condition of employment or face termination.
The city of Farmer’s Branch, Texas is requiring COVID-19 vaccination to access the city run facility called The Branch Connection. Forget taking a cruise with Royal Caribbean from Texas unless you’ve been COVID-19 vaccinated. St. Edwards University in Austin became one of the first colleges to mandate COVID-19 vaccines.
This is just the beginning.
Governor Abbott’s Executive Order Prohibiting COVID-19 Vaccine Passports Falls Short at Protection
Texas Governor Greg Abbott has been quoted saying that in Texas, COVID-19 vaccines “are always voluntary and never forced.”
The truth is Executive Order GA 35 falls short at preserving the right of law-abiding Texas citizens to be able to function normally in society without having to show proof of a COVID-19 vaccination.
EO GA 35 only prohibits the government, or public or private entities funded by the government, from requiring documentation of an individual’s COVID-19 vaccination status. This does nothing to prohibit businesses not receiving government funding from banning customers who don’t have a COVID-19 vaccine. Also, this executive order fails to give any protection to employees whose employers are requiring COVID-19 vaccination as a condition of employment.
In addition, the limited protections offered in EO GA 35 will be short lived because the order only applies to “Emergency Use Authorization” (EUA) COVID-19 vaccines. Once a vaccine has received full FDA approval, the EUA designation no longer applies and therefore neither will any protection in this executive order including the ban on forced vaccination by the government. Full FDA approval will be soon. Moderna, the manufacture of one of the 3 available COVID-19 vaccines, is already seeking full FDA approval, and Pfizer, one of the other manufacturers, announced it would seek full approval in the first half of 2021.
Governor Abbott’s executive order also falls short when compared to Florida Governor Ron DeSantis’s executive order banning vaccines passports which additionally prohibits all business from requiring COVID-19 vaccination status or post infection recovery status to gain access to or service from the business, and it applies to all COVID-19 vaccines instead of expiring after full FDA approval is achieved. It also protects personal privacy rights by prohibiting the government from publishing or sharing a person’s COVID-19 vaccination status to third parties.
Texans Need a Law Passed to Protect them From Forced Vaccination and Vaccine Passports (If you want to immediately see what you can do to help pass SB 1669 into law in Texas scroll down to “Action Needed)”
We are grateful to announce that Texas history has been made with the filing of
SB 1669 in the Texas Legislature by Senator Bob Hall.SB 1669 prohibits discrimination or segregation based on vaccination or immune status and prohibits forced vaccination in all areas of your life.
We need your help getting SB 1669 moving as the bill is currently stalled awaiting a hearing in the Senate State Affairs Committee. Legislators need to be educated about the shortcomings in Governor Abbott’s executive order and the vulnerabilities for mandated vaccination in Texas based on current law so they can pass this bill or amend parts of it onto other bills.
This is by far the most comprehensive bill prohibiting mandated vaccination in all areas that could affect your life including government orders, employment, healthcare, education, access to businesses, access to events and venues like sports and concerts, long-term care, nursing homes, insurance, and childcare.
Read more at the National Vaccine Information Center’s Advocacy Portal.
Senator Bob Hall, in his opening statements at the Senate hearing this week stated:
The chief responsibility and Constitutional role of our government is to protect the rights of the individual. Employees can take off their helmets, masks, and uniforms at the end of the work day, but they cannot remove a vaccine.

Dr. Richard Bartlett was the first physician to testify in favor of SB 1669 to Stop Forced Vaccination and Vaccine Passports in Texas.
Dr. Bartlett has over 28 years of medical practice experience and is a veteran primary care and emergency room doctor in West Texas.
Dr. Bartlett is best known since the COVID crisis started as a doctor who has cured many patients using an older, already FDA approved drug, called budesonide, which is an inhaled corticosteroid. (Learn more here.)
During his testimony, Dr. Bartlett explained that there are existing treatments already available to treat COVID patients, making it unnecessary to mandate experimental new “vaccines.”
He pointed to a recent Oxford University study just published that showed 90% success rate in using inhaled budesonide with COVID patients in preventing long-term care or hospitalization.
From the Oxford study:
The STOIC study found that inhaled budesonide given to patients with COVID-19 within seven days of the onset of symptoms also reduced recovery time. Budesonide is a corticosteroid used in the long-term management of asthma and chronic obstructive pulmonary disease (COPD).
Findings from the phase 2 randomised study, which was supported by the NIHR Oxford Biomedical Research Centre (BRC), were published on the medRxiv pre-print server.
The findings from 146 people – of whom half took 800 micrograms of the medication twice a day and half were on usual care – suggests that inhaled budesonide reduced the relative risk of requiring urgent care or hospitalisation by 90% in the 28-day study period. Participants allocated the budesonide inhaler also had a quicker resolution of fever, symptoms and fewer persistent symptoms after 28 days. (Source.)
Dr. Bartlett works in the Emergency Room, and he stated that there are very few patients coming in now with COVID, but “I am now seeing more people come in (to the ER) who are having complications from the COVID shot.”
And Dr. Bartlett points out that these are mostly younger people who were in excellent health before the shot, since Dr. Bartlett works in Lubbock, Texas, which is a college town.

Dr. Ben Edwards of Veritas Medical in Lubbock, Texas, was the next physician to give testimony in favor of SB 1669 to Stop Forced Vaccination and Vaccine Passports in Texas.
Dr. Edwards received his degree from Baylor University, and later graduated from UT-Houston Medical School. He moved to Waco to complete his training at the Waco Family Practice Residency Program where he was Chief Resident. He now operates three clinics in West Texas.
Dr. Edwards stated his concern that “the forced and coerced COVID-19 vaccinations would, in my opinion, be a violation of the Nuremberg Code,” as well as several other international codes on bioethics and human rights.
He cited the fact that the CDC is now reporting 4,178 deaths reported to VAERS, while for the previous 20 years combined there were 4,182 deaths recorded from all vaccines.
He also pointed out that a Harvard Study has previously estimated that only about 1% of all adverse reactions to vaccines are ever reported to VAERS. Two other subsequent studies showed the same thing.
In his own practice, Dr. Edwards stated that he has received “numerous reports within hours of receiving the COVID vaccines that people have suffered strokes, heart attacks, pulmonary embolisms (blood clots), and sudden death.”
Dr. Edwards went on to cite research which shows that those with natural immunity to COVID (they already had it) will see a 2 to 3 fold increase risk of adverse reactions from the COVID shots.
Over half of Texans now have this natural immunity. He stated:
On a personal note, I believe that God gave us an amazingly robust immune system, and I don’t think you can improve on God.

The next physician to testify in favor of SB 1669 to Stop Forced Vaccination and Vaccine Passports in Texas was Dr. Amy Offutt from St. Marble Falls, TX.
Dr. Offutt is trained in Integrative Medicine. She was recently appointed by Governor Greg Abbott to the Pediatric Acute-Onset Neuropsychiatric Syndrome Advisory Council. In addition, she serves on the Board of Directors for ILADS (International Lyme and Associated Diseases Society).
Dr. Offutt is another physician who has been successfully treating COVID patients with existing early treatment protocols.
She testified:
As of last Friday, my practice has treated 579 acutely ill patients as old as 98 years of age, with only ten hospitalizations and one dead.
The man who died presented on the 12th day of illness was a transplant patient and had already been to the ER multiple times before seeking care from us. This was such an unnecessary tragedy.
Dr. Offutt believes that “informed consent is the core to shared decision making in medicine.”
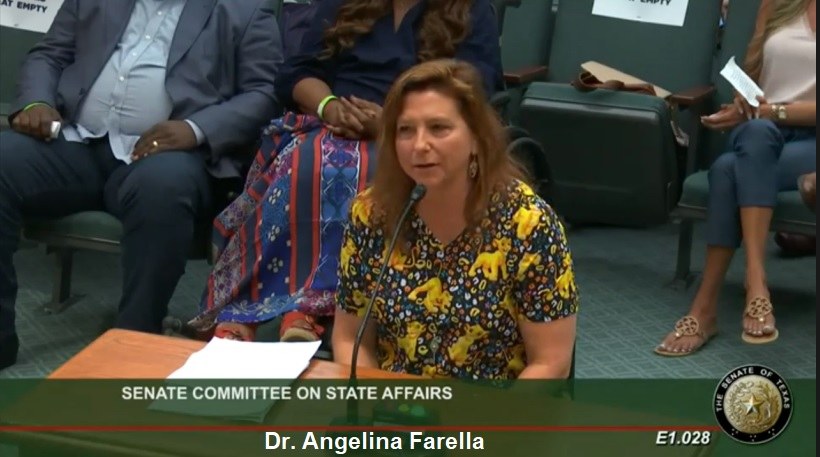
The next physician to testify in favor of SB 1669 to Stop Forced Vaccination and Vaccine Passports in Texas was Dr. Angelina Farella from Webster, TX.
Dr. Farella is a pediatrician with over 25 years experience. She started out her testimony to the Senate Committee by stating:
I am here today to protect our children in Texas. This is a very scary situation that we are in right now.
Dr. Farella stated that as a pediatrician she has given out tens of thousands of vaccines, and that she is not “anti-vaccine,” but:
I am against this COVID vaccine, if we can even call it that (a vaccine.)
What we are doing to our children with this vaccine is actually criminal.
All of these physicians are “frontline physicians” who actually treat patients, but their clinical experiences in treating COVID patients is being censored by the corporate media, and ignored by the government and Big Pharma, in favor mass vaccination instead.
Here is their testimony. This is from our Rumble Channel, and it is also on our Bitchute Channel.
Report A COVID-19 Vaccine Injury
Have you been injured by a COVID-19 vaccine?
Informed Consent Action Network
Vaccines for COVID-19 are being developed at warp speed. Potential safety issues may not be disclosed or fully disclosed to individuals receiving these experimental products.
A COVID-19 vaccine can cause injury weeks or months after injection.
If you have received a COVID-19 vaccine and suffered an adverse event thereafter, we can assist in investigating whether you have been adequately warned of the potential injury.
Informed consent is the bedrock of medical ethics and we fight every day to assure that every person is given informed consent prior to being given any drug or injected with a vaccine. We look forward to helping you.
Why are people going blind after having the Covid Vaccine?
THE DAILY EXPOSE • MAY 8, 2021
Since the first Covid-19 vaccine was authorised for use in the United Kingdom, and administered on the 8th December 2020, there have been hundreds of thousands of adverse reactions reported to the MHRA Yellow Card scheme. But there is one particular adverse reaction which is both concerning and strange, and the number of people suffering from it is increasing by the week – Blindness.
The MHRA Yellow Card scheme analysis print for the Pfizer / BioNTech mRNA jab shows that since the first jab was administered on the 9th December and up to the 28th April, thirty-three people have reported suffering blindness due to the jab. Another two people have reported central vision loss, and a further two have reported sudden visual loss.
Five people have also reported an adverse reaction known as ‘blindness transient’ due to the Pfizer vaccine. This is where a person suffers visual disturbance or loss of sight in one eye for seconds or minutes at a time. And a further six people have reported an adverse reaction known as ‘unilateral blindness’. This is where a person is blind or has extremely poor vision in one eye.

However the MHRA Yellow Card scheme analysis print for the AstraZeneca viral vector vaccine shows that recipients are at a significantly higher risk of suffering loss of vision after having the jab compared to having the Pfizer jab. Since the first AstraZeneca jab was administered on the 4th January 2021 and up to the 28th April 2021 a total of one-hundred-forty-three people have reported suffering blindness due to the jab. Another four-hundred-seventeen people have reported visual impairment, and a further three have reported sudden visual loss.
Ten people have also reported suffering transient blindness as a result of having the AstraZeneca jab, and a further thirteen have reported suffering unilateral blindness as a result of the same jab.

In all there have been 11,279 eye disorders reported as adverse reactions to both jabs, with 2,438 reported due to the Pfizer jab, and a frightening 8,841 reported due to the AstraZeneca jab. The fact-checkers alongside authorities have recently been on the case to sweep this data under the carpet and have called it unreliable. Their reasoning is that “just because someone reports the event after having the vaccine, it doesn’t necessarily mean it is due to the vaccine”.
But what they’re not telling you is that it also doesn’t necessarily mean it is not due to the vaccine, and we imagine every single person who has reported an adverse reaction would disagree with the fact checkers and authorities attempts to play down these reports. For instance one person who goes by the name of Louis has been documenting the story of his wife on Twitter since she had the AstraZeneca Covid vaccine.
Unfortunately his wife has gone completely blind in her left eye and 30-60% blind in her right eye since she had the AstraZeneca jab and the neurologist treating her has categorically told her not have the second dose. Louis states that as of the 8th May 2021 it has been 59 days since his wife had the AstraZeneca vaccine, 55 days since she went blind, 19 days since she started steroid treatment and unfortunately has seen zero improvement. In that time she has had 2 CT scans and 1 MRI. She has also seen 3 ophthalmologists, 2 opticians and had dozens of blood tests.

As you can see the misery which the fact checkers are disregarding as “not necessarily the fault of the vaccine” is very real for the people who are reporting them. But why are the Covid vaccines causing people to go blind?
Well there is another extremely concerning adverse reaction that has been reported to the MHRA Yellow Card scheme, one which has seen an astronomical increase in the number of reports in the past few weeks – stroke.
As of the 28th April 2021 the MHRA has received two-hundred-ninety-seven reports of stroke due to the Pfizer vaccine. This includes twenty-one reports of cerebral haemorrhage, 16 reports of cerebral infarction, twenty-five reports of ischaemic stroke, and a frightening 192 reports of cerebrovascular accident. Sadly this has resulted in twenty-seven deaths.

But yet again the AstraZeneca jab has caused far more misery in terms of causing a stroke compared to the Pfizer jab. As of the 28th April 2021 the MHRA Yellow Card scheme has received one-thousand-eighty-eight reports of stroke, this is almost four times the amount of reports received due to the Pfizer jab. These include eleven cerebral haematomas, forty-six cerebral infarctions, one-hundred-seven cerebral haemorrhages, and a terrifying six-hundred-seven cerebrovascular accidents.

But it doesn’t end there. The AstraZeneca jab has also caused fifteen cases of lacunar stroke, fifty-nine cases of sbarachnoid haemorrhage, and seventy-four cases of ischaemic stroke. Sadly this has resulted in eighty-five deaths.

But what does this have to do with people going blind? Well this helpful fact sheet provided by the Stroke Foundation in Australia provides the answer as to why. According to the fact sheet around one-third of stroke survivors suffer visual loss, and most sadly never fully recover their vision.
The reason strokes cause blindness is that vision depends on a healthy eye to receive information and a healthy brain to process that information. The nerves in the eye travel from the eye through the brain to the occipital cortex at the back of the brain, allowing you to see.
Most strokes affect one side of the brain. Nerves from each eye travel together in the brain, so both eyes are affected. If the right side of your brain is damaged, the left side vision in each eye may be affected. It is rare for both sides of the brain to be affected by stroke. When it does happen, it can result in blindness.
So if you’ve been wondering how on earth the experimental Covid vaccines could cause a person to go blind, you now know why. It’s the vast amount of strokes the Covid jabs are causing that is contributing to this devastating and life-changing adverse event. Strokes will not be the only contributing factor of course, but the numbers shows us they are most likely the main adverse reaction at fault.
Halt Vaccine Passports! It’s illegal, medical apartheid
By Dr Mike Yeadon | OffGuardian | May 7, 2021
It is very important that people understand what is happening here. The intention is to introduce vaccine passports everywhere. But this is a disguise. It’s a world’s first digital common-format, globally-interoperable ID system with an editable health flag (vaccinated Y or N).
It makes no one safer. If you’re vaccinated, you’re protected & are not made safer by knowing others immune status.
As in Israel, you will be compelled to present a valid VaxPass in order to access defined facilities or access services. No VaxPass, you’re denied.
This system only needs 50%+ of the adult population to start up because of its huge, coercive power on the unvaccinated.
It’s illegal, medical apartheid.
If they succeed, it won’t help you to refuse. They’ll move on, leaving that minority behind.
A VaxPass System like this will give to those controlling the database & it’s algorithms TOTALITARIAN TYRANNY over us all.
The ONLY way to stop this biosecurity nightmare is to NOT GET VACCINATED FOR NON-MEDICAL REASONS!!!
I fear that, if our adversaries gain this absolute control, they will use it to harm the population. There’s no limit to the evil which will flow from this strategic goal.
DO NOT ALLOW THIS SYSTEM TO START UP, because it’s unstoppable afterwards.
One example: your VaxPass pings, instructing you to attend for your 3rd or 4th or 5th booster or variant vaccine. If you don’t, your VaxPass will expire & you’ll become an out-person, unable to access your own life.
How much choice do you have?
It’s none. You are controlled. Forever.
PLEASE share this widely, on every platform you use.
Thank you,
Dr Mike Yeadon
Promoting and Profiting from Mass-Toxification
By Stephen Lendman | May 6, 2021
Founded in 1823, the Lancet calls itself “an independent, international weekly general medical journal (that) strive(s) (for) medicine (to) transform society, and positively impact the lives of people.”
Instead of fulfilling its pledge on all things covid, it’s been going the other way by promoting toxic mass-jabbing to be shunned, never used as directed.
In late April, the Lancet proved it can’t be trusted for falsely claiming the following:
Pfizer and AstraZeneca covid inoculations “have shown excellent safety and efficacy in phase 3 trials (sic).”
One in four people experienced mild, short-lived side effects, usually lasting one or two days (sic), it added.
Inoculations “decrease the risk of (covid) infection after 12 days (sic).”
Pharma-connected epidemiologist Tim Spector was quoted, saying:
“The data should reassure many people that in the real world, after effects of the (jab) are usually mild and short-lived, especially in the over 50’s who are most at risk of the infection (sic).”
“Rates of new disease are at a new low in the UK (sic) due to a combination of social measures and (mass-jabbing), and we need to continue this successful strategy to cover the remaining population.”
“The results also show up to 70% protection after 3 weeks following a single dose (sic), which is fantastic news for the country, especially as more people have now had their second jabs.”
Mathematician — specializing in statistical genetics — Cristina Menni defied reality by claiming that “results support the aftereffects safety of both vaccines with fewer side effects in the general population than reported in the Pfizer and AstraZeneca experimental trials and should help allay safety concerns of people willing to get” jabbed (sic).
All the above rubbish reported by the Lancet is fake news.
It’s part of relentless US-led Western mind-manipulating propaganda to get maximum numbers of unwitting people to self-inflict harm.
The Lancet allied with Western governments, their public health handmaidens, Pharma, and media press agents to all of the above in promoting what’s harmful to health, not beneficial.
There’s nothing remotely safe and beneficial from use of experimental, unapproved Pfizer/Moderna mRNA drugs or AstraZeneca/J & J vaccines for covid.
When used as directed, they risk likely irreversible harm to health or death — sooner or later.
State-sponsored coverup in the West is concealing slow-motion genocide.
According to an unnamed UK National Health Service health professional whistleblower, what’s going on is “genocide… Your children are next.”
In the US, the Pharma-connected FDA is set to OK mass-jabbing emergency use authorization for children aged 12 – 15.
If contract seasonal flu-renamed covid, their risk of serious harm or death is virtually nil.
The survival rate for flu now called covid for individuals under age-70 is 99.95% — 95% for people over age-70.
Mass-jabbing for covid should be banned.
It’s well known that toxins in experimental covid inoculations risks serious harm, nothing beneficial.
Mass-jabbing children should be criminalized, not OK’d and promoted.
State-sponsored draconian social control and depopulation hugely benefit Pharma.
Since mass-jabbing for covid began last December, Pfizer, Moderna, AstraZeneca and J & J have been cashing in big on a bonanza of huge profits.
If things go as planned, the diabolical scheme will be a gift that keeps on giving.
One or two jabs aren’t enough. Plans are for perpetual mass-toxification of unwitting people annually or semi-annually worldwide.
In Q I 2021, about one-fourth of Pfizer’s pharmaceutical revenue came from jabbing with its hazardous mRNA covid drug.
For 2021, the company projects around $26 billion in revenue from covid mass-jabbing — an annual revenue stream it aims to be permanent.
Perhaps so if countless millions of mass deceived people continue to self-inflict harm — the more covid jabs taken, the greater the harm to health near-or-longer-term.
All of the above goes on while the myth of a nonexistent pandemic persists because of the power of establishment media promoted mass deception.
Followers of my writing and likeminded others on this cutting-edge issue of our time know what’s deceptively called covid is garden variety seasonal flu.
It shows up annually without perpetual mass deception fear-mongering.
Until last year, non-beneficial/potentially harmful flu shots were promoted annually.
When for the first time ever, flu disappeared last year — because it was renamed covid — draconian mandates and recommendations have effectively manipulated the public mind in the West and elsewhere to harm health instead of protecting what’s too precious to lose.
If what’s going on continues unchecked because of public ignorance, harm to health in the West and elsewhere is highly likely to be unprecedented and suppressed — so most people will remain unaware of state-sponsored genocide.
It’s unfolding in real time below the radar — Western dark forces and their media press agents convincing most people that what’s harmful and deadly is beneficial.
I’ve stressed before and it bears repeating.
No matter how many times people have been fooled before, they’re easy marks to be duped again and again and again ad infinitum.
It’s because of the power of state-sponsored/media promoted fake news, along with the failure of most people to do minimal due diligence fact-checking.
Every literate person connected online can learn the truth on most all issues that affect their rights, health, and well-being with minimal effort.
Yet most people are easily distracted by bread and circuses.
They’re putty in the hands of manipulative dark forces and their hostile to truth-telling press agents.
We’re consistently lied to and mass deceived about all important domestic and geopolitical issues.
Yet most people are too out-of-touch with reality to notice.
My personal interfacing with individuals intelligent enough to know better but fooled like most others bears out the above reality.
COVID Vaccines: Necessity, Efficacy and Safety
Doctors for Covid Ethics | OffGuardian | May 5, 2021
This paper was originally hosted on the Doctors for Covid Ethics Medium account, but the platform censored the expert group and removed the paper, claiming the post was “under investigation”:
An archived version is still available here.
*
Abstract: COVID-19 vaccine manufacturers have been exempted from legal liability for vaccine-induced harm. It is therefore in the interests of all those authorising, enforcing and administering COVID-19 vaccinations to understand the evidence regarding the risks and benefits of these vaccines, since liability for harm will fall on them.
In short, the available evidence and science indicate that COVID-19 vaccines are unnecessary, ineffective and unsafe.
- Necessity: Immunocompetent individuals are protected against SARS-CoV-2 by cellular immunity. Vaccinating low-risk groups is therefore unnecessary. For immunocompromised individuals who do fall ill with COVID-19 there is a range of medical treatments that have been proven safe and effective. Vaccinating the vulnerable is therefore equally unnecessary. Both immunocompetent and vulnerable groups are better protected against variants of SARS-CoV-2 by naturally acquired immunity and by medication than by vaccination.
- Efficacy: Covid-19 vaccines lack a viable mechanism of action against SARS-CoV-2 infection of the airways. Induction of antibodies cannot prevent infection by an agent such as SARS-CoV-2 that invades through the respiratory tract. Moreover, none of the vaccine trials have provided any evidence that vaccination prevents transmission of the infection by vaccinated individuals; urging vaccination to “protect others” therefore has no basis in fact.
- Safety: The vaccines are dangerous to both healthy individuals and those with pre-existing chronic disease, for reasons such as the following: risk of lethal and non-lethal disruptions of blood clotting including bleeding disorders, thrombosis in the brain, stroke and heart attack; autoimmune and allergic reactions; antibody-dependent enhancement of disease; and vaccine impurities due to rushed manufacturing and unregulated production standards.
The risk-benefit calculus is therefore clear: the experimental vaccines are needless, ineffective and dangerous. Actors authorising, coercing or administering experimental COVID-19 vaccination are exposing populations and patients to serious, unnecessary, and unjustified medical risks.
1. THE VACCINES ARE UNNECESSARY
1. Multiple lines of research indicate that immunocompetent people display “robust” and lasting cellular (T cell) immunity to SARS-CoV viruses [1], including SARS-CoV-2 and its variants [2]. T cell protection stems not only from exposure to SARS-CoV-2 itself, but from cross-reactive immunity following previous exposure to common cold and SARS coronaviruses [1,3-10]. Such immunity was detectable after infections up to 17 years prior [1,3]. Therefore, immunocompetent people do not need vaccination against SARS-Cov-2.
2. Natural T-Cell immunity provides stronger and more comprehensive protection against all SARS-CoV-2 strains than vaccines, because naturally primed immunity recognises multiple virus epitopes and costimulatory signals, not merely a single (spike) protein. Thus, immunocompetent people are better protected against SARS-CoV-2 and any variants that may arise by their own immunity than by the current crop of vaccines.
3.The vaccines have been touted as a means to prevent asymptomatic infection [11], and by extension “asymptomatic transmission.” However, “asymptomatic transmission” is an artefact of invalid and unreliable PCR test procedures and interpretations, leading to high false-positive rates[12-15]. Evidence indicates that PCR-positive, asymptomatic people are healthy false-positives, not carriers. A comprehensive study of 9,899,828 people in China found that asymptomatic individuals testing positive for COVID-19 never infected others[16].
In contrast, the papers cited by the Centre for Disease Control[17,18] to justify claims of asymptomatic transmission are based on hypothetical models, not empirical studies; they present assumptions and estimates rather than evidence. Preventing asymptomatic infection is not a viable rationale for promoting vaccination of the general population.
4. In most countries, most people now have immunity to SARS-CoV-2[19]. Depending on their degree of previously acquired cross-immunity, they will have had no symptoms, mild and uncharacteristic symptoms, or more severe symptoms, possibly including anosmia (loss of sense of smell) or other somewhat characteristic signs of the COVID-19 disease. Regardless of disease severity, they will now have sufficient immunity to be protected from severe disease in the event of renewed exposure. This majority of the population will not benefit at all from being vaccinated.
5. Population survival of COVID-19 exceeds 99.8% globally[20-22]. In countries that have been intensely infected over several months, less than 0.2% of the population have died and had their deaths classified as ‘with covid19’. COVID-19 is also typically a mild to moderately severe illness. Therefore, the overwhelming majority of people are not at risk from COVID-19 and do not require vaccination for their own protection.
6. In those susceptible to severe infection, Covid-19 is a treatable illness. A convergence of evidence indicates that early treatment with existing drugs reduces hospitalisation and mortality by ~85% and 75%, respectively[23-27]. These drugs include many tried and true anti-inflammatory, antiviral, and anticoagulant medications, as well as monoclonal antibodies, zinc, and vitamins C and D.
Industry and government decisions to sideline such proven treatments through selective research support[24], regulatory bias, and even outright sanctions against doctors daring to use such treatments on their own initiative, have been out of step with existing laws, standard medical practice, and research; the legal requirement to consider real world evidence has fallen by the wayside[28].
The systematic denial and denigration of these effective therapies has underpinned the spurious justification for the emergency use authorisation of the vaccines, which requires that “no standard acceptable treatment is available”[29]. Plainly stated, vaccines are not necessary to prevent severe disease.
2. THE VACCINES LACK EFFICACY
1. At a mechanistic level, the concept of immunity to COVID-19 via antibody induction, as per COVID-19 vaccination, is medical nonsense. Airborne viruses such as SARS-CoV-2 enter the body via the airways and lungs, where antibody concentrations are too low to prevent infection. Vaccine-induced antibodies primarily circulate in the bloodstream, while concentrations on the mucous membranes of lungs and airways is low.
Given that COVID-19 primarily spreads and causes disease by infecting these mucous membranes, vaccines miss the immunological mark. The documents submitted by the vaccine manufacturers to the various regulatory bodies contain no evidence that vaccination prevents airway infection, which would be crucial for breaking the chain of transmission. Thus, vaccines are immunologically inappropriate for COVID-19.
2. Medium to long-term vaccine efficacy is unknown. Phase 3, medium-term, 24-month trials will not be complete until 2023: There is no medium-term or long term longitudinal data regarding COVID-19 vaccine efficacy.
3. Short term data has not established prevention of severe disease. The European Medicines Agency has noted of the Comirnaty (Pfizer mRNA) vaccine that severe COVID-19 cases “were rare in the study, and statistically certain conclusion cannot be drawn” from it[30]. Similarly, the Pfizer document submitted to the FDA[31] concludes that efficacy against mortality could not be demonstrated. Thus, the vaccines have not been shown to prevent death or severe disease even in the short term.
4. The correlates of protection against COVID-19 are unknown. Researchers have not yet established how to measure protection against COVID-19. As a result, efficacy studies are stabbing around in the dark. After completion of Phase 1 and 2 studies, for instance, a paper in the journal Vaccine noted that “without understanding the correlates of protection, it is impossible to currently address questions regarding vaccine-associated protection, risk of COVID-19 reinfection, herd immunity, and the possibility of elimination of SARS-CoV-2 from the human population”[32]. Thus, Vaccine efficacy cannot be evaluated because we have not yet established how to measure it.
3. THE VACCINES ARE DANGEROUS
1. Just as smoking could be and was predicted to cause lung cancer based on first principles, all gene-based vaccines can be expected to cause blood clotting and bleeding disorders [33], based on their molecular mechanisms of action. Consistent with this, diseases of this kind have been observed across age groups, leading to temporary vaccine suspensions around the world: The vaccines are not safe.
2. Contrary to claims that blood disorders post-vaccination are “rare”, many common vaccine side effects (headaches, nausea, vomiting and haematoma-like “rashes” over the body) may indicate thrombosis and other severe abnormalities. Moreover, vaccine-induced diffuse micro-thromboses in the lungs can mimic pneumonia and may be misdiagnosed as COVID-19. Clotting events currently receiving media attention are likely just the “tip of a huge iceberg”[34]: The vaccines are not safe.
3. Due to immunological priming, risks of clotting, bleeding and other adverse events can be expected to increase with each re-vaccination and each intervening coronavirus exposure. Over time, whether months or years[35], this renders both vaccination and coronaviruses dangerous to young and healthy age groups, for whom without vaccination COVID-19 poses no substantive risk. Since vaccine roll-out, COVID-19 incidence has risen in numerous areas with high vaccination rates[36-38].
Furthermore, multiple series of COVID-19 fatalities have occurred shortly after the onset vaccinations in senior homes[39,40]. These cases may have been due not only to antibody-dependent enhancement but also to a general immunosuppressive effect of the vaccines, which is suggested by the increased occurrence of Herpes zoster in certain patients[41].
Immunosuppression may have caused a previously asymptomatic infection to become clinically manifest. Regardless of the exact mechanism responsible for these reported deaths, we must expect that the vaccines will increase rather than decrease lethality of COVID-19 — the vaccines are not safe.
4. The vaccines are experimental by definition. They will remain in Phase 3 trials until 2023. Recipients are human subjects entitled to free informed consent under Nuremberg and other protections, including the Parliamentary Assembly of the Council of Europe’s resolution 2361[43] and the FDA’s terms of emergency use authorisation[29]. With respect to safety data from Phase 1 and 2 trials, in spite of initially large sample sizes the journal Vaccine reports that, “the vaccination strategy chosen for further development may have only been given to as few as 12 participants”[32].
With such extremely small sample sizes, the journal notes that, “larger Phase 3 studies conducted over longer periods of time will be necessary” to establish safety. The risks that remain to be evaluated in Phase 3 trials into 2023, with entire populations as subjects, include not only thrombosis and bleeding abnormalities, but other autoimmune responses, allergic reactions, unknown tropisms (tissue destinations) of lipid nanoparticles[35], antibody-dependent enhancement [43-46] and the impact of rushed, questionably executed, poorly regulated[47] and reportedly inconsistent manufacturing methods, conferring risks of potentially harmful impurities such as uncontrolled DNA residues[48]. The vaccines are not safe, either for recipients or for those who administer them or authorise their use.
5. Initial experience might suggest that the adenovirus-derived vaccines (AstraZeneca/Johnson & Johnson) cause graver adverse effects than the mRNA (Pfizer/Moderna) vaccines. However, upon repeated injection, the former will soon induce antibodies against the proteins of the adenovirus vector. These antibodies will then neutralize most of the vaccine virus particles and cause their disposal before they can infect any cells, thereby limiting the intensity of tissue damage.
In contrast, in the mRNA vaccines, there is no protein antigen for the antibodies to recognize. Thus, regardless of the existing degree of immunity, the vaccine mRNA is going to reach its target — the body cells. These will then express the spike protein and subsequently suffer the full onslaught of the immune system.
With the mRNA vaccines, the risk of severe adverse events is virtually guaranteed to increase with every successive injection. In the long term, they are therefore even more dangerous than the vector vaccines. Their apparent preferment over the latter is concerning in the highest degree; these vaccines are not safe.
4. ETHICS AND LEGAL POINTS TO CONSIDER
Conflicts of interest abound in the scientific literature and within organisations that recommend and promote vaccines, while demonising alternate strategies (reliance on natural immunity and early treatment). Authorities, doctors and medical personnel need to protect themselves by evaluating the sources of their information for conflicts of interest extremely closely.
Authorities, doctors and medical personnel need to be similarly careful not to ignore the credible and independent literature on vaccine necessity, safety and efficacy, given the foreseeable mass deaths and harms that must be expected unless the vaccination campaign is stopped.
Vaccine manufacturers have exempted themselves from legal liability for adverse events for a reason. When vaccine deaths and harms occur, liability will fall to those responsible for the vaccines’ authorisation, administration and/or coercion via vaccine passports, none of which can be justified on a sober, evidence-based risk-benefit analysis.
All political, regulatory and medical actors involved in COVID-19 vaccination should familiarise themselves with the Nuremberg code and other legal provisions in order to protect themselves.
References:
[1] Le Bert, N.; Tan, A.T.; Kunasegaran, K.; Tham, C.Y.L.; Hafezi, M.; Chia, A.; Chng, M.H.Y.; Lin, M.; Tan, N.; Linster, M.; Chia, W.N.; Chen, M.I.; Wang, L.; Ooi, E.E.; Kalimuddin, S.; Tambyah, P.A.; Low, J.G.; Tan, Y. and Bertoletti, A. (2020) SARS-CoV-2-specific T cell immunity in cases of COVID-19 and SARS, and uninfected controls. Nature 584:457–462. [back]
[2] Tarke, A.; Sidney, J.; Methot, N.; Zhang, Y.; Dan, J.M.; Goodwin, B.; Rubiro, P.; Sutherland, A.; da Silva Antunes, R.; Frazier, A. and al., e. (2021) Negligible impact of SARS-CoV-2 variants on CD4+ and CD8+ T cell reactivity in COVID-19 exposed donors and vaccinees. bioRxiv -:x-x.[back]
[3] Anonymous, (2020) Scientists uncover SARS-CoV-2-specific T cell immunity in recovered COVID-19 and SARS patients. [back]
[4] Beasley, D. (2020) Scientists focus on how immune system T cells fight coronavirus in absence of antibodies. Reuters, 10/07/2020. [back]
[5] Bozkus, C.C. (2020) SARS-CoV-2-specific T cells without antibodies. Nat. Rev. Immunol. 20:463. [back]
[6] Grifoni, A.; Weiskopf, D.; Ramirez, S.I.; Mateus, J.; Dan, J.M.; Moderbacher, C.R.; Rawlings, S.A.; Sutherland, A.; Premkumar, L.; Jadi, R.S. and al., e. (2020) Targets of T Cell Responses to SARS-CoV-2 Coronavirus in Humans with COVID-19 Disease and Unexposed Individuals. Cell 181:1489–1501.e15. [back]
[7] Mateus, J.; Grifoni, A.; Tarke, A.; Sidney, J.; Ramirez, S.I.; Dan, J.M.; Burger, Z.C.; Rawlings, S.A.; Smith, D.M.; Phillips, E. and al., e. (2020) Selective and cross-reactive SARS-CoV-2 T cell epitopes in unexposed humans. [back]Science 370:89–94. [back]
[8] McCurry-Schmidt, M. (2020) Exposure to common cold coronaviruses can teach the immune system to recognize SARS-CoV-2. La Jolla Institute for Immunology. [back]
[9] Palmer, S.; Cunniffe, N. and Donnelly, R. (2021) COVID-19 hospitalization rates rise exponentially with age, inversely proportional to thymic T-cell production. J. R. Soc. Interface 18:20200982. [back]
[10] Sekine, T.; Perez-Potti, A.; Rivera-Ballesteros, O.; Strålin, K.; Gorin, J.; Olsson, A.; Llewellyn-Lacey, S.; Kamal, H.; Bogdanovic, G.; Muschiol, S. and al., e. (2020) Robust T Cell Immunity in Convalescent Individuals with Asymptomatic or Mild COVID-19. Cell 183:158–168.e14. [back]
[11] Drake, J. (2021) Now We Know: Covid-19 Vaccines Prevent Asymptomatic Infection, Too.[back]
[12] Bossuyt, P.M. (2020) Testing COVID-19 tests faces methodological challenges. Journal of clinical epidemiology 126:172–176. [back]
[13] Jefferson, T.; Spencer, E.; Brassey, J. and Heneghan, C. (2020) Viral cultures for COVID-19 infectivity assessment. Systematic review. Clin. Infect. Dis. ciaa1764:x-x. [back]
[14] Borger, P.; Malhotra, R.K.; Yeadon, M.; Craig, C.; McKernan, K.; Steger, K.; McSheehy, P.; Angelova, L.; Franchi, F.; Binder, T.; Ullrich, H.; Ohashi, M.; Scoglio, S.; Doesburg-van Kleffens, M.; Gilbert, D.; Klement, R.J.; Schrüfer, R.; Pieksma, B.W.; Bonte, J.; Dalle Carbonare, B.H.; Corbett, K.P. and Kämmer, U. (2020) External peer review of the RTPCR test to detect SARS-CoV-2 reveals 10 major scientific flaws at the molecular and methodological level: consequences for false-positive results. [back]
[15] Mandavilli, A. (2020) Your Coronavirus Test Is Positive. Maybe It Shouldn’t Be.[back]
[16] Cao, S.; Gan, Y.; Wang, C.; Bachmann, M.; Wei, S.; Gong, J.; Huang, Y.; Wang, T.; Li, L.; Lu, K.; Jiang, H.; Gong, Y.; Xu, H.; Shen, X.; Tian, Q.; Lv, C.; Song, F.; Yin, X. and Lu, Z. (2020) Post-lockdown SARS-CoV-2 nucleic acid screening in nearly ten million residents of Wuhan, China. Nat. Commun. 11:5917.[back]
[17] Moghadas, S.M.; Fitzpatrick, M.C.; Sah, P.; Pandey, A.; Shoukat, A.; Singer, B.H. and Galvani, A.P. (2020) The implications of silent transmission for the control of COVID-19 outbreaks. Proc. Natl. Acad. Sci. U. S. A. 117:17513–17515.[back]
[18] Johansson, M.A.; Quandelacy, T.M.; Kada, S.; Prasad, P.V.; Steele, M.; Brooks, J.T.; Slayton, R.B.; Biggerstaff, M. and Butler, J.C. (2021) SARS-CoV-2 Transmission From People Without COVID-19 Symptoms. JAMA network open 4:e2035057.[back]
[19] Yeadon, M. (2020). What SAGE got wrong. Lockdown Skeptics.[back]
[20] Ioannidis, J.P.A. (2020) Global perspective of COVID‐19 epidemiology for a full‐cycle pandemic. Eur. J. Clin. Invest. 50:x-x. [back]
[21] Ioannidis, J.P.A. (2021) Reconciling estimates of global spread and infection fatality rates of COVID‐19: An overview of systematic evaluations. Eur. J. Clin. Invest. -:x-x. [back]
[22] CDC, (2020) Science Brief: Community Use of Cloth Masks to Control the Spread of SARS-CoV-2. [back]
[23] Orient, J.; McCullough, P. and Vliet, E. (2020) A Guide to Home-Based COVID Treatment. [back]
[24] McCullough, P.A.; Alexander, P.E.; Armstrong, R.; Arvinte, C.; Bain, A.F.; Bartlett, R.P.; Berkowitz, R.L.; Berry, A.C.; Borody, T.J.; Brewer, J.H.; Brufsky, A.M.; Clarke, T.; Derwand, R.; Eck, A.; Eck, J.; Eisner, R.A.; Fareed, G.C.; Farella, A.; Fonseca, S.N.S.; Geyer, C.E.; Gonnering, R.S.; Graves, K.E.; Gross, K.B.V.; Hazan, S.; Held, K.S.; Hight, H.T.; Immanuel, S.; Jacobs, M.M.; Ladapo, J.A.; Lee, L.H.; Littell, J.; Lozano, I.; Mangat, H.S.; Marble, B.; McKinnon, J.E.; Merritt, L.D.; Orient, J.M.; Oskoui, R.; Pompan, D.C.; Procter, B.C.; Prodromos, C.; Rajter, J.C.; Rajter, J.; Ram, C.V.S.; Rios, S.S.; Risch, H.A.; Robb, M.J.A.; Rutherford, M.; Scholz, M.; Singleton, M.M.; Tumlin, J.A.; Tyson, B.M.; Urso, R.G.; Victory, K.; Vliet, E.L.; Wax, C.M.; Wolkoff, A.G.; Wooll, V. and Zelenko, V. (2020) Multifaceted highly targeted sequential multidrug treatment of early ambulatory high-risk SARS-CoV-2 infection (COVID-19). Reviews in cardiovascular medicine 21:517–530. [back][back]
[25] Procter, {.B.C.; {APRN}, {.C.R.{.; {PA}-C, {.V.P.; {PA}-C, {.E.S.; {PA}-C, {.C.H. and McCullough, {.{.P.A. (2021) Early Ambulatory Multidrug Therapy Reduces Hospitalization and Death in High-Risk Patients with SARS-CoV-2 (COVID-19). International journal of innovative research in medical science 6:219–221. [back]
[26] McCullough, P.A.; Kelly, R.J.; Ruocco, G.; Lerma, E.; Tumlin, J.; Wheelan, K.R.; Katz, N.; Lepor, N.E.; Vijay, K.; Carter, H.; Singh, B.; McCullough, S.P.; Bhambi, B.K.; Palazzuoli, A.; De Ferrari, G.M.; Milligan, G.P.; Safder, T.; Tecson, K.M.; Wang, D.D.; McKinnon, J.E.; O’Neill, W.W.; Zervos, M. and Risch, H.A. (2021) Pathophysiological Basis and Rationale for Early Outpatient Treatment of SARS-CoV-2 (COVID-19) Infection. Am. J. Med. 134:16–22. [back]
[27] Anonymous, (2020) Real-time database and meta analysis of 588 COVID-19 studies. [back]
[28] Hirschhorn, J.S. (2021) COVID scandal: Feds ignored 2016 law requiring use of real world evidence.[back]
[29] Anonymous, (1998) Emergency Use of an Investigational Drug or Biologic: Guidance for Institutional Review Boards and Clinical Investigators. [back] [back]
[30] Anonymous, (2021) EMA assessment report: Comirnaty. [back]
[31] Anonymous, (2020) FDA briefing document: Pfizer-BioNTech COVID-19 Vaccine. [back]
[32] Giurgea, L.T. and Memoli, M.J. (2020) Navigating the Quagmire: Comparison and Interpretation of COVID-19 Vaccine Phase 1/2 Clinical Trials. Vaccines 8:746. [back][back]
[33] Bhakdi, S.; Chiesa, M.; Frost, S.; Griesz-Brisson, M.; Haditsch, M.; Hockertz, S.; Johnson, L.; Kämmerer, U.; Palmer, M.; Reiss, K.; Sönnichsen, A.; Wodarg, W. and Yeadon, M. (2021) Urgent Open Letter from Doctors and Scientists to the European Medicines Agency regarding COVID-19 Vaccine Safety Concerns. [back]
[34] Bhakdi, S. (2021) Rebuttal letter to European Medicines Agency from Doctors for Covid Ethics, April 1, 2021. [back]
[35] Ulm, J.W. (2020) Rapid response to: Will covid-19 vaccines save lives? Current trials aren’t designed to tell us. [back][back]
[36] Reimann, N. (2021) Covid Spiking In Over A Dozen States — Most With High Vaccination Rates.[back]
[37] Meredith, S. (2021) Chile has one of the world’s best vaccination rates. Covid is surging there anyway.[back]
[38] Bhuyan, A. (2021) Covid-19: India sees new spike in cases despite vaccine rollout. BMJ 372:n854. [back]
[39] Morrissey, K. (2021) Open letter to Dr. Karina Butler. [back]
[40] Anonymous, (2021) Open Letter from the UK Medical Freedom Alliance: Urgent warning re Covid-19 vaccine-related deaths in the elderly and Care Homes. [back]
[41] Furer, V.; Zisman, D.; Kibari, A.; Rimar, D.; Paran, Y. and Elkayam, O. (2021) Herpes zoster following BNT162b2 mRNA Covid-19 vaccination in patients with autoimmune inflammatory rheumatic diseases: a case series. Rheumatology -:x-x. [back]
[42] Anonymous, (2021) Covid-19 vaccines: ethical, legal and practical considerations. [back]
[43] Tseng, C.; Sbrana, E.; Iwata-Yoshikawa, N.; Newman, P.C.; Garron, T.; Atmar, R.L.; Peters, C.J. and Couch, R.B. (2012) Immunization with SARS coronavirus vaccines leads to pulmonary immunopathology on challenge with the SARS virus. PLoS One 7:e35421. [back]
[44] Bolles, M.; Deming, D.; Long, K.; Agnihothram, S.; Whitmore, A.; Ferris, M.; Funkhouser, W.; Gralinski, L.; Totura, A.; Heise, M. and Baric, R.S. (2011) A double-inactivated severe acute respiratory syndrome coronavirus vaccine provides incomplete protection in mice and induces increased eosinophilic proinflammatory pulmonary response upon challenge. J. Virol. 85:12201–15. [back]
[45] Weingartl, H.; Czub, M.; Czub, S.; Neufeld, J.; Marszal, P.; Gren, J.; Smith, G.; Jones, S.; Proulx, R.; Deschambault, Y.; Grudeski, E.; Andonov, A.; He, R.; Li, Y.; Copps, J.; Grolla, A.; Dick, D.; Berry, J.; Ganske, S.; Manning, L. and Cao, J. (2004) Immunization with modified vaccinia virus Ankara-based recombinant vaccine against severe acute respiratory syndrome is associated with enhanced hepatitis in ferrets. J. Virol. 78:12672–6. [back]
[46]Czub, M.; Weingartl, H.; Czub, S.; He, R. and Cao, J. (2005) Evaluation of modified vaccinia virus Ankara based recombinant SARS vaccine in ferrets. Vaccine 23:2273–9 [back]
[47]Tinari, S. (2021) The EMA covid-19 data leak, and what it tells us about mRNA instability. BMJ 372:n627 [back]
[48] Anonymous, (2021) Interview with Dr. Vanessa Schmidt-Krüger, Hearing #37 of German Corona Extra-Parliamentary Inquiry Committee 30 January, 2021. [back]
CDC Officially Recommends COVID Jab for Pregnant Women
By Dr. Mercola | May 3, 2021
The beyond conflicted U.S. Centers for Disease Control and Prevention has struck again: Pregnant women are now urged to get the COVID-19 gene manipulation jab, based on preliminary findings.
The postmarketing surveillance data, published in The New England Journal of Medicine,1 found “no obvious safety signals” among the 35,691 pregnant women who got either the Moderna or Pfizer shots between December 14, 2020, and February 28, 2021. The women ranged in age from 16 to 54 years old. CDC director Dr. Rochelle Walensky issued a statement saying:2
“No safety concerns were observed for people vaccinated in the third trimester or safety concerns for their babies. As such, CDC recommends pregnant people receive COVID-19 vaccines.”
Can Self-Reported Data Be Trusted?
There is more than one reason to be suspicious of this green-lighting for pregnant women. First of all, as noted by Jeremy Hammond in a recent Tweet:3
“This was NOT a randomized placebo-controlled trial. There is no data from clinical trials showing that it is safe for pregnant women to get a COVID-19 vaccine. Postmarketing surveillance is NOT a sufficient substitute for proper safety studies.”
The authors themselves state that data on mRNA “vaccines” in pregnancy are limited, and that without longitudinal follow-up of large numbers of women, it’s not possible to determine “maternal, pregnancy and infant outcomes.”4
Secondly, all postmarketing surveillance data are preliminary, so it seems incredibly foolhardy to make a blanket recommendation for all pregnant women at this early stage. Thirdly, this data is solely based on voluntary self-reporting to one of two sources:
- The Vaccine Safe (V-Safe) After Vaccination Health Checker program,5 a vaccine safety registry set up specifically for the monitoring of COVID-19 “vaccine” side effects
- The U.S. Vaccine Adverse Event Reporting System (VAERS)
By using voluntary self-reporting, we have no way of knowing how many side effects have gone unreported and cannot confirm that the data present an accurate picture. Historically, we know that voluntary reporting of vaccine side effects range from less than 1%6,7 to a maximum of 10%,8 so it’s likely we’re not getting the full story.
A hint that an enormous amount of data concerning pregnancy outcomes are being overlooked or hidden can be discerned by the fact that the paper only looked at 11% of the total number of pregnancies reported to V-Safe. While they state that a total of 35,691 pregnant women were included in the analysis, they actually only looked at 3,958 of them. Here’s how the paper reads:9
“A total of 35,691 v-safe participants 16 to 54 years of age identified as pregnant … Among 3,958 participants enrolled in the v-safe pregnancy registry, 827 had a completed pregnancy, of which 115 (13.9%) resulted in a pregnancy loss and 712 (86.1%) resulted in a live birth (mostly among participants with vaccination in the third trimester).”
If there were 35,691 pregnant V-Safe participants, why are they looking at just 11% of them?
Experimentation of the Worst Kind
Giving pregnant women unlicensed COVID-19 gene therapies is reprehensibly irresponsible experimental medicine, and to suggest that safety data are “piling up” is pure propaganda. Everything is still in the experimental stage and all data are preliminary. It’ll take years to get a clearer picture of how these injections are affecting young women and their babies.
Pregnancy is a time during which experimentation is extremely hazardous, as you’re not only dealing with potential repercussions for the mother but also for the child. Any number of things can go wrong when you introduce drugs, chemicals or foreign substances during fetal development.
The CDC has absolutely no way of gauging safety for pregnant women and babies as of yet, so to do so is reprehensible beyond words, in my opinion — especially seeing how women of childbearing age have virtually no risk of dying from COVID-19, their fatality risk being a mere 0.01%.10
Contrast this to the potential benefits of the vaccine. You can still contract the virus if immunized and you can still spread it to others.11,12,13,14 All it is designed to do is lessen your symptoms if or when you get infected. Pregnant women simply do not need this vaccine, and therefore any risk is likely excessive. I have little doubt we’ll end up with a second Nuremberg Trial over this at some point in the future.
Are These Miscarriage Ratios ‘Normal’?
Getting back to the NEJM study, the authors report the following findings, based on data collected from VAERS and V-Safe:15
“Among 3,958 participants enrolled in the v-safe pregnancy registry, 827 had a completed pregnancy, of which 115 (13.9%) resulted in a pregnancy loss and 712 (86.1%) resulted in a live birth (mostly among participants with vaccination in the third trimester). Adverse neonatal outcomes included preterm birth (in 9.4%) and small size for gestational age (in 3.2%); no neonatal deaths were reported.
Although not directly comparable, calculated proportions of adverse pregnancy and neonatal outcomes in persons vaccinated against COVID-19 who had a completed pregnancy were similar to incidences reported in studies involving pregnant women that were conducted before the COVID-19 pandemic.
Among 221 pregnancy-related adverse events reported to the VAERS, the most frequently reported event was spontaneous abortion (46 cases).”
So, in VAERS, the miscarriage rate was 20.8% (46 of 221 reports), and in V-Safe (looking at just 11% of pregnant participants), the miscarriage rate was 13.9% (115 of 827). Again, these data were reported between December 14, 2020, and February 28, 2021.
The combined miscarriage and preterm birth rate, per V-Safe, was 23.3% (13.9% + 9.4%). As of April 1, 2021, 379 VAERS reports16 had been filed by pregnant women, 110 of which involved miscarriage or premature birth, giving us an updated rate of 29%. In other words, it appears the rate of miscarriage and premature births is rising as more reports come in.
According to the authors of the NEJM report, these ratios are comparable to the miscarriage rate normally seen among unvaccinated women, while admitting that the data is “not directly comparable.”
I find that dubious, seeing how sources17 reviewing statistical data stress that the risk of miscarriage drops from an overall, average risk rate of 21.3% for the duration of the pregnancy as a whole, to just 5% between Weeks 6 and 7, all the way down to 1% between Weeks 14 and 20.
And, while the NEJM study18 report that 92.3% of spontaneous abortions occurred before 13 weeks of gestation, it specifies that very little is as yet known about the effects of the injections when given to women during the periconception period and the first and second trimesters, as “limited follow-up calls had been made at the time of this analysis.”
Now, if the miscarriage rate is normally 5% and declining after Week 6, then miscarriage rates of 13.9%, 20.87% or 29% before Week 13 is clearly excessive. As for the preterm birth rate, 9.4% does appear relatively “normal” based on historical data, which in 2019 ranged from 7.28% to 18.8% depending on the region, with an average right around 10%.19
Time will tell whether that percentage will remain within the norms as the outcomes of pregnant women are entered into databases. If preterm birth rates do rise above the norm, then that too is a significant public health issue, as the impact of premature birth on society is enormous, averaging at $26.2 billion annually, as is.20
Toxicology Expert Calls for End to mRNA Experiment
The featured video at the top of this article is the recording of a public comment by Janci Chunn Lindsay, Ph.D., director of toxicology and molecular biology for Toxicology Support Services LLC, given to the CDC Advisory Committee on Immunization Practices (ACIP), April 23, 2021.
Lindsay’s expertise is analysis of pharmacological dose-responses, mechanistic biology and complex toxicity dynamics. In her comment, Lindsay describes how she aided the development of a vaccine that caused unintended autoimmune destruction and sterility in animals which, despite careful pre-analysis, had not been predicted.
She calls for an immediate halt to COVID-19 mRNA and DNA vaccines due to safety concerns on multiple fronts. She notes there is credible concern that they will cross-react with syncytin (a retroviral envelope protein) and reproductive genes in sperm, ova and placenta in ways that may “impair fertility and reproductive outcomes.”
I’ve touched on this in previous articles, including “How COVID-19 Is Changing the Future of Vaccines” and “Pfizer Bullies Nations to Put Up Collateral for Lawsuits.” Not a single study has disproven this hypothesis, Lindsey notes.
Another theory of how these injections might impair fertility can be found in a 2006 study,21 which showed sperm can take up foreign mRNA, convert it into DNA, and release it as little pellets (plasmids) in the medium around the fertilized egg. The embryo then takes up these plasmids and carries them (sustains and clones them into many of the daughter cells) throughout its life, even passing them on to future generations.
It is possible that the pseudo-exosomes that are the mRNA contents would be perfect for supplying the sperm with mRNA for the spike protein. So, potentially, a vaccinated woman who gets pregnant with an embryo that can (via the sperms’ plasmids) synthesize the spike protein according to the instructions in the vaccine, would have an immune capacity to attack that embryo because of the “foreign” protein it displays on its cells. This then would cause a miscarriage.
“We could potentially be sterilizing an entire generation,” Lindsey warns. The fact that there have been live births following COVID-19 vaccination is not proof that these injections do not have a reproductive effect, she says.
Lindsay also points out that reports of menstrual irregularities and vaginal hemorrhaging in women who have received the injections number in the thousands,22,23,24 and this too hints at reproductive effects.
I agree with her conclusion that we simply cannot inject children and women of childbearing age with these experimental technologies until more rigorous studies have been done and we have a better understanding of their mechanisms.
Rare Blood Clotting Disorders Being Reported
Lindsay also points out there have been hundreds of reports of rare blood clotting disorders following all COVID-19 “vaccines” among people with no underlying risk factors, including immune thrombocytopenia25,26,27,28 (ITP), a rare autoimmune disease that causes your immune system to destroy your platelets (cells that help blood clot), resulting in hemorrhaging. Serious blood clots are also occurring at the same time.
Here, she points out the obvious: COVID-19 has been found to cause blood clotting disorders due to the virus’ unique spike protein. The COVID-19 “vaccines” instruct your body to make that very spike protein. Why would one assume that this spike protein cannot have similar effects when produced by your own cells?
One hypothesis that has been presented is that platelet-antagonistic antibodies are being formed against the spike antigen.29 Another novel hypothesis30 is that the lipid-coated nanoparticles, which transport the mRNA, may be carrying that mRNA into the megakaryocytes in your bone marrow.
Megakaryocytes are cells that produce platelets. According to this hypothesis, once the mRNA enters your bone marrow, the megakaryocytes would then begin to express the SARS-CoV-2 spike protein, which would tag them for destruction by cytotoxic T-cells. As your platelets are destroyed, thrombocytopenia sets in.
Avoid This Risky Milk-Sharing Practice
Women who have received the COVID-19 jab are also making what I believe is a huge mistake by sharing breast milk in a misguided effort to inoculate unvaccinated mothers’ babies. As reported by The New York Times :31
“Multiple studies32,33 show that there are antibodies in a vaccinated mother’s milk. This has led some women to try to restart breastfeeding and others to share milk with friends’ children.”
Again, there’s scarcely any data on what these gene therapies might do to infants, which is reason alone not to experiment. So far, only one suspected case34 of an infant dying has been attributed to breastfeeding. A 5-month-old infant died with a diagnosis of thrombotic thrombocytopenia purpura within days of his mother receiving her second dose of the Pfizer vaccine.35,36
But while fact checkers roundly dismiss the idea that the child could have developed thrombocytopenia from mRNA-contaminated breast milk,37 it’s important to realize they have no evidence for that. It’s pure opinion.
As of right now, we have no idea how or why the infant developed this rare blood disorder, but it would be premature and irresponsible to say that nursing children cannot be affected and that there is no risk at all. In addition to that lethal case, there are at least 20 other cases where children have had an adverse reaction to breast milk from a vaccinated mother.38
At present, all we can confidently say is that short-term harmful effects of COVID-19 vaccines are being reported at a staggering rate, and that the long-term effects are completely unknown.
In addition to the more immediate effects already discussed, there are mechanisms by which COVID-19 “vaccines” may actually worsen disease upon exposure to the wild virus, as detailed in “How COVID-19 Vaccine Can Destroy Your Immune System,” “Will Vaccinated People Be More Vulnerable to Variants?” and several other articles.
As noted in a February 4, 2021, New England Journal of Medicine paper39 reporting on the safety and effectiveness of the mRNA-1273 vaccine developed by Moderna, “Whether mRNA-1273 vaccination results in enhanced disease on exposure to the virus in the long term is unknown.”
Report All COVID-19 Vaccine Side Effects
On the whole, injecting pregnant women with novel gene therapy technology that can trigger systemic inflammation, cardiac effects and bleeding disorders (among other things), violates both the Hippocratic Oath that admonishes doctors to “First, do no harm,” and the precautionary principle that, historically, has governed health care for pregnant women.
In my view, this mass experiment is a humanitarian crime. That said, if you or someone you love — pregnant or not — has received a COVID-19 vaccine and are experiencing side effects, be sure to report it, preferably to all three of these locations.40 As we move forward, it’s absolutely crucial that people report their experiences with these vaccines, so that we can start getting a clearer idea of what their effects are.
- If you live in the U.S., file a report on VAERS
- Report the injury on VaxxTracker.com, which is a nongovernmental adverse event tracker (you can file anonymously if you like)
- Report the injury on the Children’s Health Defense website
Sources and References
- 1, 4, 9, 15, 18 NEJM April 21, 2021 DOI: 10.1056/NEJMoa2104983
- 2 CNBC April 23, 2021
- 3 Twitter Jeremy Hammond April 23, 2021
- 5 CDC V-Safe
- 6 AHRQ December 7, 2007
- 7 The Vaccine Reaction January 9, 2020
- 8 BMJ 2005;330:433
- 10 Annals of Internal Medicine September 2, 2020 DOI: 10.7326/M20-5352
- 11 Harvard Health March 25, 2021
- 12 CDC April 2, 2021
- 13 NBC Chicago April 8, 2021
- 14 The Defender April 6, 2021
- 16 The Defender April 9, 2021
- 17 Medical News Today January 12, 2020
- 19 CDC.gov Preterm births by state 2019
- 20 March of Dimes, the Impact of Premature Birth on Society
- 21 Molecular Reproduction and Development 73(10):1239-46
- 22 MSN April 10, 2021
- 23 UK Gov Yellow Card Report Unspecified Brand March 28, 2021 (PDF)
- 24 Life Site News April 19, 2021
- 25 Hopkins Medicine ITP
- 26, 29 The Defender April 13, 2021
- 27 The Defender February 9, 2021
- 28 New York Times February 8, 2021, Updated February 10, 2021 (Archived)
- 30 Medium March 19, 2021
- 31 New York Times April 8, 2021 (Archived)
- 32 Fox 4 April 7, 2021
- 33 Healio April 19, 2021
- 34, 35 Twitter Alex Berenson April 23, 2021
- 36 Twitter VAERS detail
- 37 USA Today April 9, 2021
- 38 Medalerts.org 4/16/2021 VAERS data
- 39 NEJM 2021; 384:403-416
- 40 The Defender January 25, 2021
Featured Video

Get ready for the big Israeli false flag cyber-attack
or go to
Aletho News Archives – Video-Images
From the Archives
Some Call It Conspiracy Theory – Part 1
BY IAIN DAVIS | SEPTEMBER 25, 2023
There are certain assumptions that are applied to anyone labelled a “conspiracy theorist”—and all of them are fallacies. Indeed, the term “conspiracy theory” is nothing more than a propaganda construct designed to silence debate and censor opinion on a range of subjects. Most particularly, it is used as a pejorative to marginalise and discredit whoever challenge the pronouncements and edicts of the State and of the Establishment—that is, the public and private entities that control the State and that profit from the State.
Those of us who have legitimate criticisms of government and its institutions and representatives, who are therefore labelled “conspiracy theorists,” face a dilemma. We can embrace the term and attempt to redefine it or we can reject it outright. Either way, it is evident that the people who weaponise the “conspiracy theory” label will continue to use it as long as it serves their propaganda purposes.
One of the most insidious aspects of the “conspiracy theory” fabrication is that the falsehoods associated with the term have been successfully seeded into the public’s consciousness. Often, propagandists need do no more than slap this label on the targeted opinion and the audience will immediately dismiss that viewpoint as a “lunatic conspiracy theory.” Sadly, this knee-jerk reaction is usually made absent any consideration or even familiarity with the evidence presented by that so-called “lunatic conspiracy theorist.”
This was the reason why “conspiracy theorist” label was created. The State and its propagandists do not want the public to even be aware of inconvenient evidence, let alone to examine it. The challenging evidence is buried under the “wild conspiracy theory” label, thereby signalling to the unsuspecting public that they should automatically reject all of the offered facts and evidence.
There are a number of components that collectively form the conspiracy theory canard. Let’s break them down. … continue
Blog Roll
 Aletho News
- ‘Stop Putting Drugs in Our Food’: Scientists Link Folic Acid in Food to Rising Rates of Colorectal Cancer
- The 14 Things That Happen to Your Newborn in the First 48 Hours
- JFK’s Forgotten Confrontation with Israel
- Trump’s Cyber Director Pick Has Deep Ties To Israeli Intelligence
- Get ready for the big Israeli false flag cyber-attack
- The Ukrainian Reset experiment: A war and surveillance state blueprint for the EU
- Pentagon fails ninth financial audit in a row, unable to account for trillions in assets
- Russia rejects Danish plot claims, vows response to expulsion
- Study of 14,000 Children Links Vaccination to Higher Rates of Chronic Illness
- Strike Iran Again, Open Pandora’s Box | Brian McGlinchey
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- New Study: Modern Temps Are Among The Coldest Of The Last 10,000 Years In East Central Europe
- Germany’s Renewable Energies Lead to 1.4 Billion Euro Electric Power Trade Deficit
- Argentina’s Perito Moreno Glacier Joins Antarctica and Arctic In Defying Doomsday Melt Claims
- New Study: Barents Sea Temperatures Were Warmer And Sea Ice Less Extensive In The 1700s Than Today
- German Authorities Start Initiative To Evaluate Public Register For Climate “Disinformation” Spreaders!
- Zonal Asymmetry of Temperature Change in the Antarctic Circumpolar Current
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean

