The British public’s widespread compliance with lockdown restrictions and the subsequent vaccine rollout has been the most remarkable aspect of the coronavirus crisis.
The removal of our basic freedoms — in the form of lockdowns, travel bans and mandatory mask wearing — have been passively accepted by the large majority of people. Furthermore, the proportion of the general public expressing a willingness to accept the Covid-19 vaccines has been greater in the UK than almost anywhere else in the world. But has the government achieved this widespread conformity through the unethical use of covert psychological strategies — “nudges” — in their messaging campaign?
A major contributor to the mass obedience of the British people is likely to have been the activities of government-employed psychologists working as part of the “Behavioural Insights Team” (BIT). The BIT was conceived in 2010 as “the world’s first government institution dedicated to the application of behavioural science to policy.” In collaboration with governments and other stakeholders, the team aspire to use behavioural insights to “improve people’s lives and communities”. Several members of BIT, together with other psychologists, currently sit on the Scientific Pandemic Insights Group on Behaviours (SPI-B), a subgroup of SAGE, which offers advice to the government about how to maximise the impact of its Covid-19 communications.
A comprehensive account of the psychological approaches deployed by BIT is provided by an Institute of Government document titled MINDSPACE: Influencing behaviour through public policy, where it is claimed that these strategies can achieve “low cost, low pain ways of ‘nudging’ citizens … into new ways of acting by going with the grain of how we think and act”. Several interventions of this type have been woven into the Covid-19 messaging campaign, including fear (inflating perceived threat levels), shame (conflating compliance with virtue) and peer pressure (portraying non-compliers as a deviant minority) – or “affect”, “ego” and “norms”, to use the language of behavioural science.
Behavioural scientists know that a frightened population is a compliant one, so this was exploited as a way of compelling us to abide by the coronavirus restrictions. The minutes of the SPI-B meeting on 22 March 2020 stated: “The perceived level of personal threat needs to be increased … using hard-hitting emotional messaging.” Aided by the mainstream media, the British public were subsequently bombarded with fear-inducing information, images and mantras: Covid-19 daily death counts reported without context; inflated predictions of future casualties; recurrent footage of dying patients in Intensive Care Units; and scary slogans like, “If you go out you can spread it”, or “People will die”, often accompanied by images of emergency personnel wearing PPE.
We all strive to maintain a positive view of ourselves. Utilising this human tendency, behavioural scientists have recommended messaging that equates virtue with adherence to the Covid-19 restrictions, so that following the rules preserves the integrity of our egos while any deviation evokes shame. Examples of these nudges in action include: slogans such as, “Stay home, Protect the NHS, Save lives” and “Protect yourselves, Protect your loved ones”; TV advertisements where an actor tells us, “I wear a face covering to protect my mates”; the pre-orchestrated Clap for Carers ritual; ministers telling students not to “kill your gran”; and close-up images of acutely unwell hospital patients with the voice-over, “Can you look them in the eyes and tell them you’re doing all you can to stop the spread of coronavirus?”
And then there’s what the psychologists euphemistically refer to as “normative pressure”: awareness of the prevalent views and behaviour of our fellow citizens — through peer pressure and scapegoating — can prise us into compliance. The simplest example is ministers repeatedly telling us that the vast majority of people are “obeying the rules”. But normative pressure is less effective in changing the behaviour of the deviant minority if there is no visible indicator of pro-social conformity rooted in communities. The mandating of masks in summer 2020 — in the absence of strong evidence that they reduce viral transmission in the community — enabled the rule breakers to be instantly distinguished from the followers. Appearing unmasked in public places now felt comparable to failing to display the icon of a dominant religion while being among devout followers; even if no explicit challenge ensues, the implicit demand to conform is palpable.
The same covert strategies are now being used to promote the uptake of the Covid-19 vaccines. The tactic of fear inflation is evident in a recent NHS England document that recommends healthcare staff “leverage anticipated regret” on the over-65s cohort by telling them they are “over three times more likely to die”. The recommended follow-up statement is, “Think about how you will feel if you do not get vaccinated and end up with Covid-19?” For young people — who are at vanishingly small risk of suffering serious illness should they contract Covid-19 — shame is the selected tool from the behavioural-science armoury; the recommendation is that they should be told “normality can only return, for you and others, with your vaccination.” As for the healthcare staff who will administer the jabs, the psychological experts suggest an ego boost from being hailed as the, “latest ‘NHS Heroes’”.
So, what’s wrong with using these covert psychological strategies to improve compliance with public health policy?
In comparison to the government’s traditional tools of persuasion (such as information provision and rational argument) these methods of influence differ in their nature and subconscious mode of action. Consequently, three sources of ethical concern emerge: problems with the methods per se; problems with the goals to which they are applied; and problems with the lack of consent.
It is questionable whether a civilised society should knowingly increase the emotional discomfort of its citizens as a means of gaining their compliance. State scientists deploying fear, shame and scapegoating to change minds is an ethically dubious practice that in some respects resembles the tactics used by totalitarian regimes such as China, where the state inflicts pain on a subset of its population in an attempt to eliminate beliefs and behaviour they perceive to be deviant.
Another ethical issue associated with the methods of covert nudging used in the Covid-19 communications campaign concerns the unintended consequences. Shaming and scapegoating has emboldened some people to harass those unable or unwilling to wear a face covering. More disturbingly, fear inflation has led to many people being too scared to attend hospital with non-Covid illness, while many old people, rendered housebound by fear, will have died prematurely from loneliness. Collateral damage of this sort is likely to be responsible for many of the tens of thousands of excess non-Covid deaths in private homes. In a civilised society, is it morally acceptable to use psychological strategies that are associated with this level of collateral damage?
The perceived legitimacy of using covert psychological strategies to influence people may also depend upon the behavioural goals that are being pursued. It seems likely that a higher proportion of the general public would be comfortable with the government resorting to subconscious nudges to reduce violent crime – for example, to discourage young men from stabbing each other – as compared to the purpose of imposing unprecedented and non-evidenced public-health restrictions. Would British citizens have agreed to the furtive deployment of fear, shame and peer pressure as a way of levering compliance with lockdowns and mask mandates? Maybe they should be asked before the Government considers any future imposition of these techniques.
In 2010, the authors of the MINDSPACE document — one of whom is Dr David Halpern, a member of SAGE and the SPI-B — recognised the significant ethical dilemmas arising from the use of influencing strategies that impact subconsciously on the country’s citizens and emphasised the importance of consent. Indeed, they could not be clearer: “policymakers wishing to use these tools … need the approval of the public to do so.” They go on to suggest some practical ways of acquiring this consent, including the facilitation of “deliberative forums” where a representative sample of several hundred people are brought together for a day or more to explore an issue and reach a collective decision. I am unaware of any public consultation of this type being conducted to gain the public’s permission to use covert psychological strategies.
At an individual level, obtaining a recipient’s permission prior to an intervention is a long-established principle of ethical clinical practice. Informed consent is an essential precursor to any medical procedure, including vaccination. To ensure ethical integrity, healthcare staff should be encouraging each potential recipient to, consciously and rationally, weigh up the pros and cons of accepting the Covid-19 vaccine rather than nudging them towards compliance.
The covert psychological strategies incorporated into the state’s coronavirus information campaign have achieved their aims of inducing a majority of the population to obey the draconian public health restrictions and accept vaccination. The nature of the tactics deployed — with their subconscious modes of action and the emotional discomfort generated — do, however, raise some pressing concerns about the legitimacy of using these kinds of psychological techniques for this purpose. The government, and their expert advisors, are operating in morally murky waters. An open, public-wide debate about the ethical integrity of these approaches — and the extensive collateral damage associated with them — is urgently required.
Dr Gary Sidley is a retired clinical psychologist with over 30 years’ experience working for the NHS. He is a member of the Health Advisory and Recovery Team (HART).
HART vs SAGE
HART Pathology Lead Dr John Lee appeared on Good Morning Britain this week alongside Professor Susan Michie who sits on SAGE and the Scientific Pandemic Insights Group on Behaviours (SPI-B).
Dr Lee noted the lack of evidence for asymptomatic spread of SARS-CoV-2 and also pointed out the absence of diverse scientific discussion in the media. Susanna Reid denied this, stating that the other side was being heard on social media and in the papers. However, these avenues are not the same as trusted mainstream TV programmes and the void of diverse thinking here has no doubt hampered the public’s understanding of ‘the science’.
Reid went on to say that ‘we know from the evidence that lockdown does work’. This is simply not true. Increasingly, the body of evidence points to the exact opposite as can be seen here and in dozens of published peer-reviewed papers, in stark contrast to the absence of evidence demonstrating significant benefits from lockdown when examining the real-world (as opposed to modelled) evidence. In addition, these models neglect to adequately assess the collateral harms.
Reid highlighted the figure of 126,000 COVID-19 deaths. However, there is a serious issue with excess, mainly non-Covid deaths at home which have reached over 50,000 in total. Here in the UK this figure currently sits at roughly 1,000 people each week. Perhaps many of these people would not have been put off seeking medical treatment had Michie, and her behavioural science colleagues, not terrified them into ‘staying at home’. A review of these covert, ethically questionable, psychological strategies was recently published by a member of HART here.
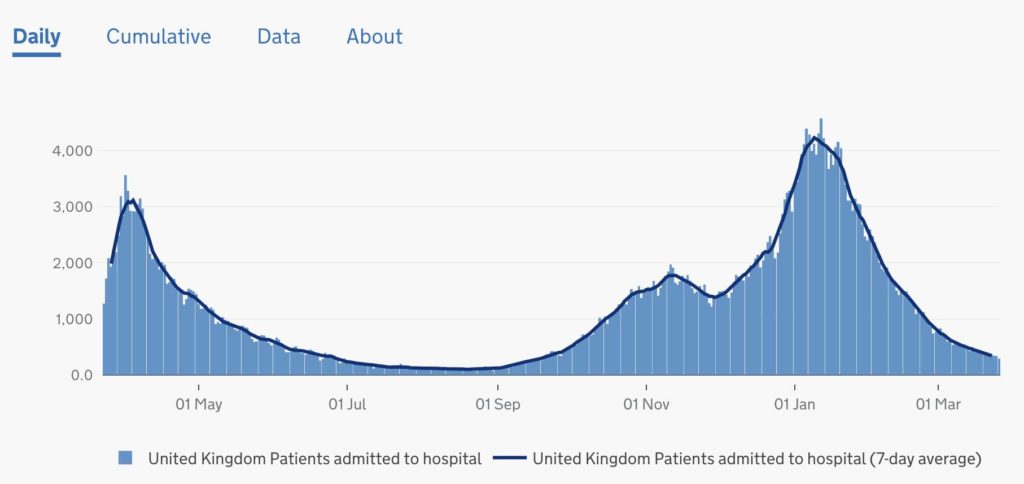
Michie also talked about mutant variants and how many people it is or is not ‘safe’ to interact with. It is a shame that these questions were addressed to a psychologist, rather than to a pathologist with medical training. No mention was made of the inevitable seasonal decline of the virus and Michie mentioned several thousand new cases a day, neglecting to outline how these figures relate to hospital statistics (currently at September levels).
Patients admitted to hospital in the UK
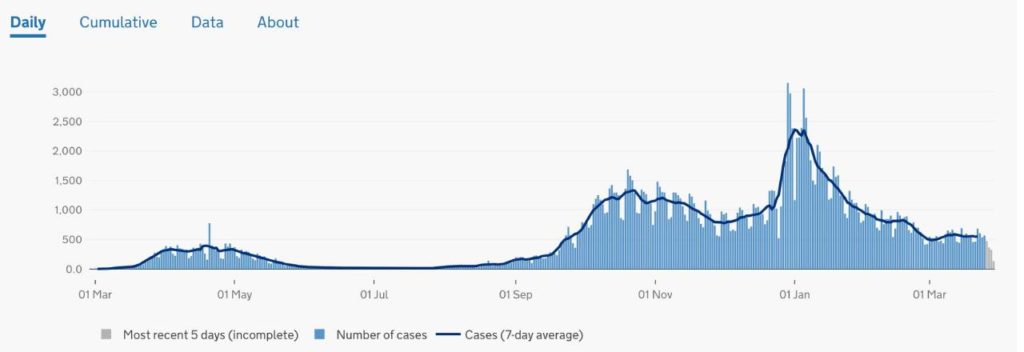
In fact, we know from numerous studies that there will be a significant number of post infectious positives at this stage with patients admitted to hospital for other reasons, incidentally testing positive. In the community, the expected surge in cases in the secondary school population has not materialised and the results of testing show that there is no active SARS-CoV-2 in that population. Overall, there is minimal evidence of residual coronavirus in the community. Mitchie went on to say cases are rising in Scotland. Again, this simply is not true.
Cases in Scotland
Michie then described the possibility of exponential growth if we remove measures too quickly, which shows a misunderstanding of the current immunity status of the population. With so many now having antibodies through natural infection or vaccination, it seems highly unlikely that this virus could now spread in an epidemic fashion. A transition into an endemic phase, as with seasonal flu in which there may be localised outbreaks, mainly in specific institutionalised settings, is much more likely.
The problems with Michie’s thesis are underpinned by the false assumption that asymptomatic spread is a major driver of transmission. There is no robust evidence for this phenomenon, and it would go against decades of understanding of respiratory viruses and how they are transmitted. By continuing to disseminate this questionable hypothesis to the British public, she is continuing to spread unnecessary fear. A far more balanced approach would be to focus on:
1. The viral season rapidly waning
2. The huge percentages of vaccinated people & those with acquired or innate immunity
3. The fact that children are not a significant driver of the disease
4. The fact that clinical symptoms are the driver of transmission of respiratory viruses
We need to stop ‘acting like we’ve got it’ and start living what is left of our finite lives.
Data not dates
It was reported this week that the weekly COVID-19-related death toll has fallen to the lowest rate since October. However, in a scenario of ever-decreasing death rates and diminishing prevalence of the virus, a comparison to the COVID mortality rate at the beginning of the winter wave seems somewhat arbitrary and of no relevance to the current situation. Once deaths reach minimal levels, this indicates that cases must have been minimal 18 days earlier.
A far more sensible metric for comparison would be the current test positivity rate. Since 21 March the PCR positivity rate has been only 2.1% i.e. only 1% higher than the baseline positivity rate we saw in summer. Including all testing, only 0.43% of 1.2 million tests were positive on 29 March. To put this in perspective, 9,957 people tested negative out of every 10,000 tests done. Remaining locked down under these circumstances indicates that the Government has adopted a “Zero Covid” strategy, despite their own admission of the futility and harm that would be caused by attempting this policy. Patrick Vallance himself said: “I think the chance of eradication, true eradication – ie zero – are in themselves close to zero.”
Tracking the success of the vaccine and maintaining confidence Last week, Sir Christopher Chope MP and William Wragg MP raised important questions in the House of Commons regarding COVID-19 deaths following coronavirus vaccination. Health Secretary Matt Hancock responded ‘I think we do have it’. Hancock also referred to the SIREN study but this only covers healthcare workers and therefore does not provide the complete information required for monitoring adverse effects, safety and efficacy. HART would urge active data capture, including a simple vaccine history taken at every unscheduled attendance at a hospital.
We must not forget that these are experimental vaccines, without full regulatory approval but issued under emergency waivers. It would be concerning in the extreme if data were not being collected or if the level of scrutiny of vaccine effects was not sufficient. The availability and rapid access to this data is vital in maintaining the public’s confidence in the vaccination programme.
US states continuing to open up Governors across the US are continuing to open up their states and remove COVID-19 restrictions. Earlier this month, Mississippi and Texas both announced the end of business restrictions and mask mandates, while North Dakota went a step further and implemented legislation to make mask mandates illegal. In Florida, Governor DeSantis is to forbid vaccine passports with an executive order.
In Texas, COVID-19 cases and hospitalisations carry on their downward trajectory despite their removal of measures being described variously as: “absolutely reckless” by California Governor Gavin Newsom, “it just is inexplicable why you would want to pull back now” by Dr Fauci and “neanderthal thinking” by President Joe Biden.
Essential viewing Nick Hudson, co-founder of the international group Pandemics ~ Data & Analytics (PANDA), has given a keynote address at the inaugural BizNews Investment Conference in South Africa. In his speech, Hudson gives a comprehensive overview of the COVID-19 pandemic and explores how instead of helping to slow the spread of the virus, lockdowns have led to infant mortality, poverty, starvation, joblessness and a major upsurge of psychological disorders. Well worth taking 30 minutes to watch in full, here. This video is currently being viewed by several thousand people per hour.
24 March 2021
There is no emergency COVID-19 cases are low and all-cause deaths are now back to normal pre-pandemic rates and falling. All vulnerable groups have been offered a vaccination. There are no longer any justifiable or ethical reasons for prolonging Covid-related statutory ‘emergency powers’.
It is anticipated that all phase 1 priority groups (approximately 32 million people) will have been offered a vaccine by 15 April, a group accounting for 99% of the deaths last spring. This will be an amazing achievement. The virus is now endemic and will circulate at very low levels this summer and is then likely to join the range of respiratory viruses circulating each winter. Talk of continuing social distancing and masks for several years is therefore unnecessary and unhelpful. We urgently need to reduce fear and increase hope as we recover from this crisis.
It is vital that we harness the benefits of the rapid vaccine rollout by acknowledging we are no longer in an emergency. We can and must reopen society. Government and SAGE will need to undo the negative messaging, after a year in restrictions many people will still be fearful to pick up their lives again. News that a £2m Government contract has just been awarded for a COVID Public Information Campaign over the next two years is concerning. The repeal of the coronavirus emergency legislation would give a very positive message of confidence and hope to the British public. Therefore, HART continues to urge all MPs to vote against the renewal of the Coronavirus Act this week in Parliament.
No evidence of SARS-CoV-2 in schools HART predicted 24,000 false positive results in children in the first week of mass testing based on 4 million children being tested twice. In the week of 4 March, only 2.7 million tests were carried out on secondary school children and 0.05% of them were positive. Our previous prediction was based on the estimated false positive rate for the adult population of 0.3%. Testing of university students prior to Christmas showed a very low false positive rate of at or below 0.06% including Newcastle, Hull, Exeter and Birmingham. Testing among school children is demonstrating a similar rate. The good news is that these numbers are so low that no-one can be left in any doubt that they represent only false positive results and that there is no SARS-CoV-2 at present in the secondary school population. The ONS estimated that there would be SARS-CoV-2 in 0.4% (1 in 250) 12-24 year olds, so this is another instance of failed testing with PCR. With no virus in schools, there is now no justification for the mask mandate or mass testing.
Is mask wearing benign? This week, Dr Mary Ramsay from Public Health England told the BBC that face coverings were a ‘lower level restriction’ that ‘people can live with’ and they should continue to be worn ‘for a few years’. Her words are similar to those used by politicians to justify the introduction of the mask mandate in summer 2020, when it was portrayed as an extra layer of protection, a precautionary measure, a nothing-to-lose restriction.
While there is no evidence that masks significantly reduce transmission when worn routinely in real-world settings, there is recognition that they may constitute an infection hazard, particularly when used incorrectly. Masks potentially cause physical harms, while the social and psychological cost of concealing our faces from other people is considerable. Face coverings impair all forms of communication and human connection, make lip-reading impossible for the deaf and constitute a gross impediment to children’s social development.
A highly visible reminder that danger is supposedly all around, face coverings are fuelling widespread, irrational fear at a time when the current viral threat is very low and the vulnerable have been vaccinated. As we look to re-activate the economy and reopen our society, this mask-induced fear will act as a major obstacle. HART believes the Government should now lift the mandate and allow people to decide for themselves whether to wear one. It is time to trust the public with their own personal risk-based decision making.
The futility of border closures Summer holidays are in doubt again, with the news that a £5,000 fine will come into force for anyone trying to travel abroad without a ‘reasonable excuse’. Matt Hancock has said the restrictions are to ‘guard against’ new variants that might put the vaccine rollout at risk. Professor Neil Ferguson was also quoted as saying we ‘should be planning on summer holidays in the UK not overseas’. Closing international borders to keep out ‘foreign mutants’ of an already endemic virus is neither useful nor possible. It is worth noting that mutant variants from abroad pose no extra threat compared with any homegrown variants and are likely to have very similar sequences. Mutant variants, emerging overseas or domestically, are an inevitable biological reality once a virus is in the population, as is the case in the UK. The virus will mutate slowly over time, irrespective of borders.
Mandatory vaccination for care home workers The news that the government is considering making COVID-19 vaccination a legal requirement for all care workers is concerning and against international law. This would create a precedent of eroding informed consent, and is difficult to justify when the vulnerable population have themselves already been offered at least one dose of vaccine, especially in the light of Scottish data that suggests the Oxford-AstraZeneca vaccine reduces risk of hospitalisation by up to 94%. If this is case, would it be better to prioritise second doses for all vulnerable groups, thus rendering the vaccination of our younger, healthy population unnecessary?
And some good news… The number of patients admitted per day to intensive care units is now close to normal, pre-pandemic levels for the time of year. It appears we are well beyond the risk of overwhelming the NHS – further highlighting that now is the time to lift restrictions and allow the NHS to begin rapidly addressing the backlog of postponed appointments and operations. There is no sign of a virus resurgence in American states such as Florida and Texas which have lifted restrictions.
In 2000, everything about Bill Gates’ public persona changed. He morphed from a hardnosed and ruthless technology monopolizer into a soft, fuzzy and incredibly generous philanthropist when he and his wife launched the Bill & Melinda Gates Foundation.1
It was a public relations coup. May 18, 1998, the U.S. Justice Department, in collaboration with 20 state attorneys, filed an antitrust lawsuit against Microsoft.2 At that time, the company was 23 years old and was ruling the personal computer market. The Seattle Times described the fallout from the antitrust lawsuit:3
“The company barely escaped being split up after it was ruled an unlawful monopolist in 2000 for using its stranglehold on the PC market with its Windows operating system to cripple competitors, such as Netscape’s Navigator Web browser.”
How would the world be different today if the company had been split? Yale law professor George Priest described the antitrust lawsuit as “one of the most important antitrust cases of its generation.”4 In 2002, a court settlement placed restrictions on Microsoft to curb some of its practices for five years.
It was later extended twice and then expired May 12, 2011. The lawsuit had a dramatic effect on “the emergence of an entirely new field called IP (intellectual property) antitrust,” Iowa law professor Herbert Hovenkamp told the Seattle Times.5
Later, large sums donated from the foundation made the news multiple times, including $9.5 million to GAVI (Global Alliance for Vaccines), a second $7.5 million to GAVI and $6.8 million to the World Health Organization in 2017.6
By June 2020, in the middle of a global pandemic, the Gates Foundation’s donations totaled 45% of WHO’s funding from nongovernmental sources.7 Once mainstream media’s attention was no longer on Gates’ antitrust activities and focused on the philanthropist actions of the foundation, Gates publicly turned his attention to vaccinating the world, long before COVID-19.8
Event 201: A Preplanned Pandemic
In a deep dive into the Gates Foundation’s charitable donations, The Nation found there were $250 million in grants to companies where the foundation held corporate stocks, including Novartis, GlaxoSmithKline, Merck, Sanofi and Medtronic. The money was directed at supporting projects “like developing new drugs and health monitoring systems and creating mobile banking services.”9
What Gates had discovered was an easy path to political power, allowing him to shape public policy without being elected to office. In other words, favorable headlines could be bought with charitable contributions.10 One event that Gates has personally supported and participated in was Event 201.11
Writing in The Defender, Robert Kennedy Jr. describes the exercise that Gates organized in October 2019. Many high-ranking men and women with governmental authority participated in Event 201, which coincidentally simulated a worldwide pandemic triggered by a novel coronavirus, just months before SARS-CoV-2, the virus that causes COVID-19, changed the world.12
They included representatives from the World Economic Forum, the Centers for Disease Control and Prevention, Johns Hopkins University Population Center, the World Bank, the Chinese government and vaccine maker Johnson & Johnson. During the event, the group developed strategies to control a pandemic, the population and the narrative surrounding the event.
At no time did they investigate using current therapeutic drugs and vitamins or communicating information about building immune systems. Instead, the aim was to develop and distribute patentable antiviral medications and a new wave of vaccines.
As Kennedy reports, Gates spoke to the BBC13 April 12, 2020, and claimed these types of simulations had not occurred, saying “Now here we are. You know we didn’t simulate this; we didn’t practice, so both the health policies and economic policies … we find ourselves in uncharted territories.”
Yet, videos of the event are available14 and Johns Hopkins Center for Health Security released a statement naming the Gates Foundation as a partner in sponsoring the pandemic simulation.15 It seems strange and alarming that a man with the responsibility of running the Gates Foundation and the powerful influence he has over global public policy decisions had forgotten an exercise he organized only six months before the interview.16 Or was it deception?
Uncanny Prediction or Planned Event?
During the pandemic exercise, the global experts “modeled a fictional coronavirus pandemic.”17 After questions arose about whether the exercise had “predicted the outbreak in China,” Johns Hopkins Center for Health Security released a thinly supported statement, saying:18
“… the exercise served to highlight preparedness and response challenges that would likely arise in a very severe pandemic … Although our tabletop exercise included a mock novel coronavirus, the inputs we use for modeling the potential impact of that fictional virus are not similar to nCoV-2019.”
Kennedy characterizes the fourth simulation in Event 201, writing that “the participants primarily focused on planning industry-centric, fear-mongering, police-state strategies for managing an imaginary global coronavirus contagion culminating in mass censorship of social media.”19
The transcript of the fourth simulation shows that the participants discussed communication strategies using dissemination of information and censorship on social media.20,21 Communication strategist Hasti Taghi, who works for a major media company and leads strategic initiatives with the World Economic Forum,22 said:
“So, I think a couple of things we have to consider are even before this began, the anti-vaccine movement was very strong and this is something specifically through social media that has spread.
So, as we do the research to come up with the right vaccines to help prevent the continuation of this, how do we get the right information out there? How do we communicate the right information to ensure that the public has trust in these vaccines that we’re creating?”
The question the group undertook wasn’t how to communicate the truth about the vaccine development, manufacture and distribution, but rather how to “communicate the right information to ensure the public has trust in these vaccines that we’re creating?”
The issue of gaining public trust to take a vaccine was significant in this simulation, even though the U.S. population is well indoctrinated in the perceived value of annual flu shots and childhood vaccinations. In fact, the Centers for Disease Control and Prevention has a list of 26 different types of vaccines currently in use in the U.S.
In addition to the long list of recommended childhood vaccinations, there are adult vaccines against shingles, tetanus and pneumococcal pneumonia that are routinely given. Why, then, did the global experts in communication and control believe communicating the “right information” would be necessary to “ensure the public trust”?
Group Calls for Social Media Censorship
This was only one of the highly predictive conversations during Event 201 that played out in 2020 as the global COVID-19 pandemic unfolded. George Gao, director-general, Chinese Center for Disease Control and Prevention,23 predicted:24
“By and long, we have more cases in China and also death cases reported. And also, my staff told me that before there’s misinformation and there’s some belief. People believe, ‘This is a manmade … some pharmaceutical company made the virus,’ so there’s some violations of human … That is because of this misinformation.”
Others agreed with the need for social media censorship as it may pertain to the spread of “disinformation” about the pandemic or vaccines and vaccine injury, without regard to the source. The idea was to remove any information that did not align with the government’s mandates and ideas. Kevin McAleese, who is a communications officer with a Gates-funded agricultural project, said:25
“To me, it is clear countries need to make strong efforts to manage both mis- and disinformation … If the solution means controlling and reducing access to information, I think it’s the right choice.”
During the ensuing conversation, Tom Inglesby, director of the Johns Hopkins Center for Health Security,26 replied, “In this case, do you think governments are at the point where they need to require social media companies to operate in a certain way?”27
At each step of the simulation, the global “experts” agreed that information censorship through media platforms would be necessary to control the flow of the “right information” in order for people to willingly follow the leader.
What is interesting about the transcript from Event 201 is that what was planned and shared was frighteningly close to what has happened since January 2020. It may have been a coincidence to predict one or two major public health decisions, but it appears that the group was either phenomenally prophetic or they shaped the decisions and events of 2020 from behind the scenes.
Framing the Vaccine Message to Trigger Action
From the outside, the driving force behind economically devastating lockdowns, warp speed vaccine development and population control and surveillance strategies has been to “flatten the curve” and lower the death rate of SARS-CoV-2. Yet, as I and others have exposed, when these strategies are analyzed, it’s apparent there is more than what meets the eye.
In July 2020, Yale University28 announced a study of the trigger words and phrases that would have a higher likelihood of promoting an otherwise individualistic society to quietly follow mandates (not laws) to control behavior. The phrases tested were believed to be most successful at conveying feelings about health, helping others and fear.
The hope was to manipulate behavior in such a way that it lowered the governmental risk for riots and dissidence. The study was conducted by Yale University using 4,000 participants who were randomized to receive one of 12 different messages. After the message, they were then evaluated to “compare the reported willingness to get a COVID-19 vaccine at three and six months of it becoming available.”29
The primary outcome of the study was to find the right combination of phrases and messaging that would increase the number of people who got the vaccine. The study began July 3, 2020, and the last participant underwent testing by July 8, 2020.30 To date, the results of the study have not been published.
The president of the U.S. announced in July 2020 that there would be an “overwhelming” vaccine campaign launched by November 2020.31 In December 2020, the National Institutes of Health released a COVID-19 vaccination communication recommending behavioral and social science actions that might address vaccine hesitancy and increase the number who take the vaccine, including:32
Framing accepting a vaccine as a social norm including “promotional materials that induced peer pressure to vaccinate.”
Encouraging those who vaccinate to share their positive experience on social media.
Nudging a person into accepting the vaccine by making it convenient and easy, leveraging electronic portals to send messages and using competition, gamification and incentives to encourage behavioral changes.
Assessing the values of the target audience and then embedding those values into messages about vaccinations. Examples might include being a protector of the community, building on desires to go back to normal activities or as a way of enacting equality and social justice by protecting vulnerable people.
In other words, many of the messages that you’ve been seeing in the media and your doctor’s office have been designed to trigger emotions that would lead you to take the vaccine. These same pressure tactics are not routinely used in the media for some of the more common adult vaccinations including pneumococcal, tetanus, hepatitis or shingles vaccines.
It’s Time to Speak With One Voice and Fight for Freedom
As I’ve written before, what we lose as a society when we acquiesce to these mandates and controls will be exponentially harder to get back. One of the freedoms we give away is allowing our thoughts and beliefs to be censored on social media without fighting back.
It is essential to safeguard your constitutional rights and civil liberties against unlawful overreach, and yet many appear to be willing to give up easily. Although the government has a duty to protect the health and welfare of its citizens, this must be balanced against the loss of civil rights and liberties.
We’re currently facing a battle of freedom versus tyranny. For example, multiple studies have demonstrated that long-term lockdowns are clearly not in the public’s best interest.33,34 Instead, it’s tantamount to abuse. And yet many have gone along with these mandates, which were not laws.
It’s vital to understand that the vast majority of information you consume in mainstream media is carefully designed propaganda that has been crafted from nearly two decades of personal data collected from you.
Although Yale University undertook a study with 4,000 participants for a COVID-19 messaging campaign, that data had been gathered and collated through your use of social media.
As I have carefully identified in many previous articles, this plan will result in a progressive loss of your freedom and liberty that eventually results in tyranny and slavery. It is crucial to be vigilant and seek the truth so that you can understand how to distinguish between fact and a fictional narrative that promises you liberation but eventually enslaves you.
My newest book, “The Truth About COVID-19,” will be available April 29, 2021, on Amazon. In it, I investigate the origins of the virus and how the elite has used it to slowly erode your personal liberty and freedom. In addition, I’ll also show you how to protect yourself against the disease and what you can do to fight back against the technocratic overlords.
The country of Nicaragua never instituted a lockdown, never required masks, and yet crushed the Corona virus? Major protests in Germany, Switzerland, and the UK as people are saying ‘no’ to more lockdowns.
—————-
Support Truth in Media by visiting our sponsors:
Pulse Cellular: Use code “TRUTH” for 10% every plan for life. https://truthinmedia.com/phone
WHO updated “Therapeutics and COVID-19” on March 31, 2021 to include a recommendation on ivermectin. The recommendation was:
“We recommend not to use ivermectin in patients with COVID-19 except in the context of a clinical trial.”
The recommendation was made by the Guideline Development Group; 63 members consisting of “content experts, clinicians, patients, ethicists and methodologists”.
WHO explained that a vote on the recommendation was not necessary:
“While a priori voting rules informed procedures if the panel failed to reach consensus, these procedures proved unnecessary for this recommendation.”
Two questions:
Was there an “a priori” system in place for deciding when and how to abandon the “a priori” voting rules?
How was consensus determined?
Is it too late to take a vote?
WHO explained how they reached their “transparent and trustworthy recommendations”. They need to understand that bypassing a vote on the recommendation is the opposite of transparent and trustworthy.
According to the latest figures derived from the European Medicines Agency’s database of Covid-19 vaccine adverse reactions, 162,610 injurious events and 3,964 deaths have now been reported. Among the three major vaccines approved and deployed in Europe, Pfizer-Biontech’s vaccine accounts for over two-thirds of reported injuries and mortalities, or 102,100 and 2,540 events respectively. Curiously, women disproportionately account for 77% of adverse events; this greater than 1:4 gender ratio is also being observed for Moderna’s and AstraZeneca’s vaccines. So far there seems to be no scientific explanation to account for this gender disparity.
Recently, we have been alerted that AZ’s adenovirus vaccine is particularly worrisome. It has been less than two months since its administration in the EU commenced; already there have been over 54,000 injuries and 451 deaths registered. Consequently, many European nations, which are more committed to protecting their citizens than increasing pharmaceutical profits, have placed moratoriums on administering AZ’s Covid vaccine. In the UK, over 114,000 adverse reactions from AZ’s product or 4.6 reactions per 1,000 recipients have been reported.
However, the EU’s vaccine injury statistics are disturbing for another reason. It seems very apparent in our review of government and institutional figures that the EU has a far more robust and accurate vaccine injury reporting system in place. Given that the US started vaccinating adults against SARS-CoV-2 before the EU, we would expect to observe the number of reported adverse effects higher or at least proportionate. However, this is not the case. Since December 14, 2020, the CDC’s Vaccine Adverse Event Reporting System (VAERS) has only reported 44,606 adverse events and 2,050 deaths – a small fraction compared to Europe and where the average European citizen is generally healthier and where far fewer doses have been administered.
Consider two other anomalies. According to Oxford University’s global Covid-19 vaccine tracker, as of March 27th, the US has administered over 136 million doses, which accounts for about 25 percent of all Covid-19 vaccines administered worldwide. On the other hand, the EU nations have only administered 66 million doses — less than a half compared to the US. In addition, the US vaccination rate is now approximately 41 per 100 Americans. EU nations have individually vaccinated 17 per 100 citizens or less. Therefore, why is there such an enormous discrepancy of adverse vaccine reactions between the US and EU? The EU is reporting a 0.2 percent adverse reaction rate whereas the US is claiming only 0.03 percent, almost a ten-fold difference.
Various studies have estimated that only between 1 to 10 percent of vaccine injuries are reported in VAERS. In the past, the CDC has relied upon the conservative 10 percent estimate, which may account for the ten-fold discrepancy in adverse Covid-19 vaccine events in the EU and US. A 2011 Harvard study in collaboration with the Federal Agency for Health Care Research has estimated actual adverse event reporting may be as low as 1 percent. The study states,
“Adverse events from drugs and vaccines are common, but underreported. Although 25% of ambulatory patients experience an adverse drug event, less than 0.3% of all adverse drug events and 1-13% of serious events are reported to the Food and Drug Administration (FDA). Likewise, fewer than 1% of vaccine adverse events are reported.”
If we assume the European Medicines Agency’s statistics are relatively accurate, we would therefore expect that the actual number of US adverse reactions should be in the neighborhood of 335,000 injuries and over 8,100 deaths.
Something is very seriously amiss with this scenario.
First, we can surely agree that Covid vaccines do not hold a personal vendetta against Europeans. Nor does owning an EU passport make one more susceptible to a serious vaccine reaction.
Although anyone can report an adverse reaction to VAERS, very few Americans know it exists. The CDC notes that reporting vaccine injuries and deaths in the database is completely voluntary. Consequently, there is no requirement for a vaccine administering physician or health professional to report an injury or death. In fact, many doctors and healthcare workers are largely ignorant about VAERS’ existence as is the public. Because VAERS is an extremely flawed passive surveillance system, it provides an extremely inaccurate picture for risks associated with every approved vaccine, let alone those against the SARS-CoV-2 virus. The CDC’s National Immunization Program has acknowledged VAERS’ glaring limitations for over 25 years, but nothing has fundamentally changed in mandating its use throughout the medical establishment. As millions of Americans are rushing to get their shots, our health officials have been relying upon “a patchwork of existing programs that they acknowledge are inadequate because of small sample size, missing critical data or other problems.” Anthony Fauci and the heads of our health agencies have known for many months that these vaccines were forthcoming. However they have been utterly negligent, according to a New York Times article, to put in place a robust monitoring system to record adverse vaccine reactions and to undertake appropriate analysis.
VAERS has served as a highly successful propaganda tool to mask and hide actual vaccine risks instead of a reliable monitoring system. Anyone can access the database, and it is the most common resource for those who follow and report adverse vaccine reaction trends.
Yet, the CDC also relies upon other monitoring sources, notably the Vaccine Safety Datalink (VSD), a database controlled in a collaboration between the CDC and nine large managed healthcare organizations. In fact, the CDC states that it relies upon VSD “to evaluate vaccine safety issues.” The Institute of Medicine ranks VSD as the best resource for conducting necessary analysis on vaccine safety and contains the electronic records of over 9 million Americans. It is also relied upon for comparing the health status of vaccinated versus unvaccinated groups and for investigating long-term adverse vaccine risks. However, despite our tax dollars going towards the funding of VSD, the database’s content is inaccessible to the public. Federal agencies have assured that its data remain the proprietary property of the private healthcare organizations to prevent it being used by independent researchers and journalists.
Given the CDC’s and FDA’s long history of secrecy and lack of transparency, and its long public relations arm that infiltrates every mainstream media source, it is not surprising that we never hear public service announcements notifying viewers and readership that the CDC has a system in place to report any adverse effects from Covid-vaccination. Now that the vaccines are being rolled en masse, we would expect our government to enforce due diligence to track vaccine injuries in the public interest. But we will never hear this information coming from the lips of the pharmaceutical media shills such as Sanjay Gupta and George Stephanopoulos. Not even during flu seasons when the media follows its marching orders from federal health agencies to persuade the public to roll up their sleeves.
In the meantime, the medical establishment gives lukewarm condolences towards those unfortunate to have become seriously ill or have died from the virus. But think of all the others, Fauci and his federal colleagues consistently tell us over the media waves, who have been lucky enough to be vaccinated and can return to a normal life. Just take these experimental vaccines despite the shoddy evidence to convince any objective reviewer that they prevent transmission or protect anyone from contracting the virus. Nor were they tested to determine rates of hospitalization or deaths. Yet the media makes every effort to assure us that we are being given the best information science can provide. And sadly, all this science is preferentially cherry picked to strengthen the false narrative to increase vaccination compliance. And since lockdowns, masks, social distancing and quarantining remain in place, it is near impossible to conduct any vigorous scientific study to determine how much or how little these vaccines are contributing to the rise and fall of infectious rates. Is it vaccination or all of the mandatory social restrictions that is the major contributing factor?
“The greatest enemy of knowledge,” wrote renowned historian Daniel Boorstein, “is not ignorance, it is the illusion of knowledge.” Today, this illusion of authoritative knowledge pervades the medical establishment and brainwashes the sleeping media. In our opinion, it is becoming a dangerous collective mental disorder. The good news is that more and more scientists, researchers and doctors within the towering medical citadel are exiting rapidly in order to publicly speak out against the litany of falsehoods, lies and corruption spewed from the orifices of the CDC, the FDA, World Health Organization and Big Pharma.
Gary Null is an internationally recognized thought leader and activist who holds a Ph.D. in human nutrition and public health science and Richard Gall is the Executive Producer for the Progressive Radio Network.
Disclaimer: This article is not intended to provide medical advice, diagnosis or treatment.
“Wow. But don’t those cost a fortune? How can you afford them, with just the Universal Basic Income?”
“Well, duh. I didn’t buy them, dude. I’m just renting them from Amazon Prime, of course. All of my clothes are rented, including the original Calvin Klein underwear.”
“Nothing, just remembering an old joke here. So, what’s new? What are your plans for next week?”
“Not sure. Maybe I’ll go to the City Hall Yearly Masked Ball. You want to come? The masks are all N95 compliant, so it’s safe.”
“No, thanks. I thought you were travelling to Italy for the holidays?”
“Nah, I can’t board a plane this month. I didn’t get my Moderna monthly booster shots. I wanted to, but the lines were so big, the next appointment available for me is only next month.”
“This Covid-29 is really pesky, isn’t it?”
“You bet. But I’m sure the vaccine is working. Just give it time. It takes a few years to achieve full immunization, but of course, with the new variants and viruses that appear every month, it’s always a game of catching up. We got to be patient. So, yeah, no travel this month for me.”
“Well, you know, you could always travel around your own room.”
“What?”
“Oh. I just got reminded of an old 18th century novel. ‘Voyage around my room,’ by Xavier de Maistre.”
“What it’s about?”
“It’s about a guy who, well, travels around his room.”
“18th century? Man, that’s like, old. When was that exactly? I guess that’s when the first lockdowns happened, right? In the first Covid era?”
“Yeah, sort of… Anyway, forget it, you just reminded me of that book. But I guess reading is not really your thing.”
“Nah. Is there a YouTube version? You are funny, you’re one of those guys who still read, right? You’re really old-fashioned. I bet you don’t even have a microchip in your brain, L.O.L.”
“Thankfully not…”
“…”
“What’s wrong?”
“Don’t get close to me.”
“What? Why? Who are you calling?”
“Who am I calling? Who am I calling? The police, dude. Not having a brain chip is a felony, and it’s my duty as a citizen to report you, sorry. I know you’re a friend and neighbour and all, but, that’s just sick, dude. That’s really fucked-up.”
“No, No… Wait, stop! I meant that I don’t have the latest version of he chip. But I still have the 2029 model. As you said, I’m old-fashioned…”
“Ah… Ok… But… I don’t see the scar in your head…”
“Oh, it’s there, trust me. It’s just that I got a hair implant on top of it, so, it’s not visible.”
“Ah, OK. That’s cool. You were starting to scare me, dude. I mean, not having a brain chip, in this day and age… I was starting to think you were a radical or something…”
“Well…”
“Oh man, it’s getting late. It was nice seeing you, but, sorry, I got to go now. I have a Zoom meeting with my family. But, see you another time, I guess. Should we do an elbow bump, or a foot shake?”
“…”
“What’s up dude? What’s wrong with you?”
“Nothing, you know, memories. I’m kind of old now, and sometimes I get flashes of images from previous times. And now I was thinking of an old movie I saw once, long ago…“The Flowers of Saint Francis”, it was called. By Roberto Rossellini, about Saint Francis of Assisi. There is one scene in which a leper comes, ringing a bell… You know, at that time, in the Middle Ages, lepers were forced to wear bells on their clothes to announce their arrival… And so this leper comes, his little bell ringing, asking for some money, but all people move away from him, and he’s there all alone, looking so forlorn. So Saint Francis sees this, and he is so overcome with pity, that he approaches the leper and hugs him. A long hug, for several minutes. And when the poor leper goes away, he starts to cry.”
“Eew… That’s sick, man. I mean, hugging someone. That’s just gross! What’s a leper?”
“Oh… it’s a… Leprosy was a disease that existed a long time ago. I mean, it still exists, but it was more common then.”
“Oh. I guess mRNA vaccines cured it, right? Man, viruses are evil. But thankfully we have those magic vaccines today.”
“Sort of. It’s not really caused by a virus, and the treatment is not a vaccine. But anyway, I was just reminded of that scene, I don’t know why…”
“OK. So, elbow bump or foot shake, then?”
“Honestly, I prefer neither.”
“Sure, that’s the safest way. See you around then, man. And get that 2030 brain chip, bro, for Satan’s sake. I mean, we’re in 2030, dude. We are not in the Middle Ages anymore.”
A bizarre Covid-19 conspiracy theory appears to have taken root among the epidemiologists and public health officials who still support lockdowns. According to their claims, the UK government’s pandemic response was secretly captured at some point in the fall of 2020 by lockdown critics including Great Barrington Declaration co-author Sunetra Gupta, her Oxford colleague Carl Heneghan, and Sweden’s state epidemiologist Anders Tegnell.
Seizing on an article in the Times of London, supporters of this theory allege that Gupta and her colleagues convinced UK Prime Minister Boris Johnson and Chancellor Rishi Sunak to abandon a so-called “circuit breaker” lockdown during an audience in late September. Had the UK gone back into lockdown around the beginning of October instead of a month later – proponents of this theory maintain – it would have avoided its disastrous second wave over the fall and winter months.
Even the basic narrative flies in the face of empirical reality. In November 2020 and again in January 2021, the UK went through two successive rounds of draconian lockdowns of the exact type that Gupta and her colleagues advised against. Championed by Johnson as a way to avert the second wave, these policies utterly failed at their stated purpose. On November 5th, the date the second lockdown took effect, the UK’s death toll stood at 48,000. Over the next four months, three of them spent under recurring lockdowns, the UK’s fatality numbers exploded to over 120,000.
Equally telling, the timing of the UK’s fall/winter wave almost perfectly matched that of Sweden, which remained open throughout the same period – except the UK’s results under lockdowns were visibly worse. As a growing body of scientific literature attests, lockdowns did practically nothing to contain the pandemic. Instead, the performance of this policy shows no discernible advantage over states and countries that opted against suspending the basic operations of daily life, and in many cases lockdown countries actually did worse than those that remained open.
Still, proponents of the newest UK conspiracy theory hold that something very different would have happened if only Johnson had enacted an earlier lockdown around the beginning of October instead of November 5th. Its underlying narrative has gained an unusually intense following among public health activists and pundits in the UK.
Deepti Gurdasani, an epidemiologist at Queen Mary University in London and a principal organizer of the pro-lockdown John Snow Memorandum, has aggressively promoted the alleged wresting of pandemic policy away from the lockdowners as an explanation for why the UK’s second and third lockdowns failed. As early as December, Gurdasani blasted Downing Street for supposedly listening to the “dangerous ideology” of Gupta, Heneghan, and Tegnell, which “has cost thousands of lives” and sought to replicate the “dangerous” Swedish strategy. Never mind that Sweden, without lockdowns, has a much lower deaths-per-million residents total (1,303 as of April 1st) than the UK (1,890) under three harsh lockdowns.
The same narrative has become a favorite of Devi Sridhar, an anthropologist and Snow Memorandum co-signer who frequently appears in the UK media to advocate the fringe “Zero Covid” strategy (the same one that claims we need more lockdowns to prevent future lockdowns, apparently unaware of the contradiction that entails). Attempting to explain why her own lockdown approach did not work, Sridhar wrote on January 5th that “Chancellor Sunak invited Heneghan, Gupta & Tegnell to advise on strategy. That says it all.”
Other variants of the same conspiracy theory permeate the UK’s pundit ranks. Far-left Guardian columnist Owen Jones repeated it in a December column targeting Sunak and the scientists for allegedly delaying the lockdowns until it was “too late to bring coronavirus rates down to anywhere near the level needed to suppress the virus.”
A little over a month later, Sam Bowman, a right-leaning self-described “neoliberal,” penned an almost identical argument to Jones in the same newspaper, writing “Sunak was reported as having been the decisive voice in government against an autumn lockdown that might have brought cases low enough to make things like test-and-trace viable,” all because of “Sunetra Gupta, Carl Heneghan and Anders Tegnell being invited to speak via Zoom at Downing Street.”
Note that none of these commentators are even willing to consider the possibility that lockdowns do not deliver on their promises, or that Britain’s dismal performance under the policies they advocated is a direct testament to their failure as public health measures. The validity of lockdowns has become an axiom to them, and the only conceivable reason they do not work must be some form of malfeasance preventing them from working the way the epidemiology models claim they should. Sunak and the three dissenting scientists accordingly became a natural scapegoat for Britain’s dismal public health performance over the winter months.
Is there even a kernel of truth behind the lockdowner’s UK conspiracy theory? Gupta, Heneghan, and Tegnell did meet with Downing Street via Zoom on September 20th to voice their opposition to lockdowns in general – a position they have consistently held throughout the pandemic. Unfortunately, as Gupta has explained and as the next four months repeatedly demonstrated, the Prime Minister largely ignored their advice.
The conspiracists’ alleged “smoking gun” is a series of minutes from the UK government’s SAGE advisory committee on September 21st, which included a “circuit-breaker lockdown” among a “short-list” of policies “that should be considered” in response to rising Covid-19 cases. Apparently in their minds, being “considered” equates to adoption, and the fact that Johnson did not lock down the very next day is proof that the dissenting scientists had wrested the reins of the UK’s pandemic policy from those who advocated lockdowns, delaying the necessary response until November 5th after which it was too late.
There are multiple immediate problems with this narrative. First off, Wales tried a “circuit breaker” lockdown that almost exactly followed the proposal being considered by the SAGE committee, announcing it on October 19and implementing it a few days later. Although it had a lead of almost two weeks before the rest of Britain went into lockdown in November, Wales’s per capita case numbers followed the same trajectory as the rest of the country, including the sharp spike in late December and early January. Far from working as intended, Wales’s “circuit breaker” lockdown only slightly shifted the timing of this pattern. Its maximum daily peak of 87 cases per 100,000 residents nearly matched England’s peak of 96, and its curve for Covid-19 fatalities followed the same pattern as the rest of Britain.
Equally telling, a number of the conspiracy theory adherents themselves were singing a very different tune when these events were unfolding. Gurdasani, Sridhar, and other lockdown advocates of the John Snow Memorandum crowd want you to believe that they were patiently counseling the government to adopt an early lockdown between the end of September and mid-October, only to see their advice deflected by Downing Street due to the interference of Gupta and the other dissenting scientists. The record reveals a very different story.
On September 24, only three days after the SAGE meeting minutes, an interesting editorial appeared in the leading British medical journal. Written by Karl Friston, a frequent collaborator with Gurdasani and fellow John Snow Memorandum organizer, the editorial advocated a “third way beyond lockdown or herd immunity” premised on implementing a contact tracing regime over the next few weeks. Far from raising alarms about the immediate need for another lockdown, Friston attempted to assure calm.
“We have already developed a substantial population immunity (around 8% in the UK) and our physical distancing policies remain adaptive and effective,” he explained, arguing that a contact tracing regime could synergistically harness and augment their effectiveness. As far as the fall case surge went, he predicted a comparatively mild trajectory: “When one models what is likely to happen…in terms of viral spread and our responses to it—a plausible worst-case scenario is a peak in daily deaths in the tens (e.g., 50 to 60) not hundreds, in November.” As it happens, the UK topped 400 deaths per day during the November lockdown, and surged to 1,200 deaths per day at the peak of the January lockdown.
Just over two months later, Friston joined Gurdasani and several other Snow Memorandum signers in an letter to the Lancet that blamed the UK’s second wave on failing to heed pro-lockdown advice that they now claimed as their own, even as it conflicted with their public messaging from September that downplayed the very same recommendation. Writing in hindsight and with a liberal amount of revisionism, they recast themselves as proponents of an earlier lockdown all along: “On Sept 21, 2020, the Scientific Advisory Group for Emergencies (SAGE) advised the UK Government to institute a circuit breaker in England to suppress the epidemic. Instead, the government opted for several weeks of ineffective local tiered restrictions, and cases continued to rise exponentially.”
A similar messaging came from the “Independent SAGE” group – a private organization of scientists who now generally support the lockdown approach, but also spent the early fall advocating less-restrictive measures that would supposedly avoid another lockdown. On September 20th, the same day that Gupta and the other scientists met with Downing Street, the Independent SAGE group (not to be confused with the official SAGE group despite their shared name) released a 10-point plan “to avoid a national lockdown.”
The scheme warned of a point “when the situation is so far out of control that the only possible response will be a second national lockdown,” but advised “we can only avoid it if we take urgent action” as recommended by the group. They sought a variety of restaurant restrictions limited to outdoor dining, plus the same testing and contact tracing programs espoused by Friston. Six months later, Independent SAGE member Kit Yates is now faulting the anti-lockdown scientists for Johnson’s failure to implement a policy last September that his own group purported to oppose and sought to forestall.
Indeed, what we see when we look to the words of these lockdowner scientists and pundits is nothing short of a conscious attempt to rewrite their own positions from the time period when the conspiracy theory that they’ve now adopted was allegedly playing out. As I documented last fall, the overwhelming media narrative from late September and early October explicitly deflected attention away from the prospect of a second lockdown. Scientists such as Gupta, Heneghan, and the Great Barrington Declaration (GBD) signers, they vigorously maintained, were arguing with a “strawman” of renewed lockdowns that nobody was seriously proposing or considering anymore.
A typical version of this narrative appeared inWired UKon October 7th as part of a media attack on the GBD. “The kind of lockdown that the Great Barrington Declaration seems to be railing against hasn’t been in place in the UK since mid-June,” argued the magazine’s science editor Matt Reynolds. Even in UK cities that were under local restrictions, “pubs, restaurants and schools are still open and it’s hard to find people who are advocating for a return to the lockdown we saw in March.” Reynolds continued: “When the Great Barrington Declaration authors declare their opposition to lockdowns, they are quite literally arguing with the past.”
Similar messages appeared throughout the UK media at the time, each insisting that lockdowns were no longer on the table. On October 11th, Guardian columnist Sonia Sodha wrote “The [Great Barrington] declaration sets itself up against a straw proposal that nobody is arguing for – a full-scale national lockdown until a vaccine is made available.” By October 30th, Sodha was already contradicting herself and revising her own history, tweeting “Wish we’d had a circuit breaker lockdown when SAGE first recommended it.” By mid-December, she was touting the conspiracy theory about Gupta, Heneghan, and Tegnell’s Zoom meeting with Downing Street. More recently, she’s become an advocate of de-platforming the same scientists from British media channels for their anti-lockdown heresies.
Sridhar’s own navigation of the lockdown question followed a similar course. Although she now chastises opponents of the “circuit breaker” lockdown proposal from the events of September 20-21 and faults them for Britain’s second wave, Sridhar wrote a bizarre op-ed in the Guardian on October 10th purporting to oppose “continual lockdowns.” Much like the Zero Covid messaging she would later adopt, its argument is confused and self-contradictory, meandering from touting the model of Taiwan, which never locked down, to New Zealand, which continues to use aggressive lockdowns to suppress even the slightest outbreak. But it also sought to signal her opposition to the specter of renewed lockdowns, which could be avoided – she insisted – by adopting less-stringent localized restrictions and an extensive contact tracing regime.
Sridhar would doubtless insist that her own re-adoption of lockdown advocacy about a month later arose from a failure to heed her earlier advice, as opposed to a more fundamental error with the lockdown approach. Even then, it’s difficult to square her mid-October position with her newfound claim to have recognized the wisdom of a national lockdown some 2 to 3 weeks earlier than the October 10th op-ed, only to see it derailed by the scientists who spoke to Downing Street. Like the Independent SAGE group’s September 20th manifesto, Sridhar was either far less attached to a second lockdown at that point in time than she now insists, or she was engaging in deception about her intentions.
The most astounding attempt at revisionism, however, came from Gurdasani – the Snow Memorandum organizer who has since tried to scapegoat the UK’s Covid failures on Gupta, Heneghan, and Tegnell over the September Zoom conference. She now depicts herself as an early lockdown advocate whose advice from September was shoved aside and ignored. Yet as late as October 26, Gurdasani was still pushing the same “lockdowns are a strawman” line that had dominated the previous month of UK media coverage.
Writing for the Byline Times, a London-based blog that has pushed multiple unhinged conspiracy theories of its own about the Great Barrington Declaration, Gurdasani described lockdowns as “a strawman that the science is not only not advocating for, but very keen to avoid.”
Gurdasani was in the middle of a publicity campaign for the John Snow Memorandum at the time, its own language having been carefully crafted to present its recommendations as a strategy “to prevent future lockdowns” by relying on nondescript localized “restrictions” and a contact tracing regime. As Gurdasani and another Snow Memorandum signer told the Byline Times’ readership, “Unfortunately, the proponents of herd immunity have had a huge impact on responses to the pandemic, effectively creating the lockdown strawman,” insisting that this presented a “dangerous false dichotomy.”
With Gurdasani stressing that she was keen to avoid future lockdowns – a “strawman” in her own words – as late as October 26th, one begins to wonder how she could have supported the very same “strawman” over a month earlier on September 20th, the date on which the dissenting scientists allegedly wrested control of the UK’s pandemic response. Perhaps the lockdowners’ latest conspiracy theory has another as of yet undisclosed twist to it, this one involving a time machine.
Update:Gript ran a piece on March 11 criticising the inferences of our article below, and here’s our recently published rebuttal. After reading the below ask yourself, why are Gript not going after St James’s hospital for what they did?
Freepress.ie can exclusively reveal that Irish hospitals were never under strain throughout 2020, based on newly released official health system hospital data arising from our freedom of information request. If you’re in a hurry, scroll to the section on St. James’s hospital.
The contradiction between the official data and representations that the health service has been under dangerous strain is obviously extremely important. The charts below will show you just how how busy Irish hospitals have been.
The new data directly contradicts the reporting and statements of Irish politicians, RTE and other Irish mainstream media, and the Irish Health Service Executive (HSE) covid-body NPHET. These Irish establishment bodies have consistently told the public that the hospital system was at breaking point since the Covid issue surfaced. Their own HSE data completely contradicts that contention.
We requested a specific dataset from the HSE on the 2nd of February. We asked for:
‘the full occupancy rates for all Irish hospitals under the direction of the HSE for the past four years broken down by month. Specifically, only people who were admitted to hospitals should be included and not outpatients who were on a waiting list: only people who were in the hospital for treatment should be included.’ – Our February 2nd FOI Request to HSE
It took five weeks, but we now have that data. It shows conclusively that hospitals were never at breaking point and they were operating far below capacity all year.
The idea of an extremely stressed health service is still one of the key pillars used to justify the Irish Government’s unscientific lockdowns and mask mandates, both of which have no basis in science and have been argued to be examples of crimes against humanity.
The HSE Hospital Bed Data – Available For You To Download
We have included both the FOI request letter from the HSE and the actual data release here for download to verify everything for yourself with the HSE if you need to.
We encourage everyone to examine and use it for your own content to spread awareness – a link back to this site at the top of your material is all we ask. Make a chart for your local hospital and share it in your area! If you can’t use excel hit the comments below and I will make one for you. Feel free to use anything in this report in your own material for free, including all chart images below. The spreadsheet data we received from the HSE breaks down hospital bed occupancy for the past four years, with tabs for each year from 2017 to 2020.
The figures are given for the entire country at the top of the list, and then each of the seven hospital groups are given, along with each individual hospital within each of those groups. In all, there are fifty-six lines of data per year, broken down by month. Each of the charts below have the corresponding data shown used to generate each chart.
For each chart we took the four consecutive years for that specific group or hospital and charted it to show the comparison between the year of the ‘pandemic’, and the three previous years.
The National Picture Is One Of Half Empty Hospitals
Let’s first take a look at the national picture. For the year of Covid-19 2020 in blue, the graph shows that National Hospital occupancy levels were starkly below those of the previous years. Click each image to enlarge and to see the yearly figures.
All Irish hospital bed occupancy by month, from 2017 (Yellow) to 2020 (Blue). Click each image to enlarge
It seems they flattened the curve alright – but maybe not the one we thought they meant. This data incorporates all hospital beds in the country (the first line of data on the excel sheet). As you can see, the system was never under strain.
To check if the National picture is reproduced in a subset of that data, the Ireland East Hospital Group (IEHG), is the largest and most complex of Ireland’s hospital groups. Comprising 11 hospitals (6 voluntary and 5 statutory), IEHG spans eight eastern counties and works with four Community Healthcare Organisation (CHO) partners. The Mater hospital and National Maternity Hospital are members of this group.
Ireland East Hospital group, 11 hospital on most populous East Coast of Ireland
Still the same picture. Remember: according to official government figures, between March 1 and May 6, a total of 534 sick elderly patients who had tested positive for Covid were discharged from hospitals in Ireland and moved to nursing homes, under instructions from the Irish Government and senior HSE & NPHET officials. This was ordered under the auspices of ‘protecting hospitals under strain’. We included this period in the graph above.
We have written extensively about the Nursing home actions of the the government and NPHET in Freepress.ie. These new hospital figures show conclusively that the hospitals were half empty. Those covid-positive elderly people should have been kept in hospital where sick people are normally treated, not sent back into vulnerable mortally ill nursing home populations to cause havoc. The HSE and Irish Government knew this at the time, and they knew the hospitals were the best place to treat these people.
Here’s Ireland’s largest hospital, St James’s hospital – which is not part of the previous Ireland East hospital group.
St James’s hospital, Ireland’s largest, and four years of bed occupancy levels. Never under strain in 2020.
Same picture. Indeed, you will see the same picture across all Irish hospitals if you chart them yourself in excel or give the numbers a brief examination across all four years. Fifty-four elderly sick Covid patients were transferred from St James’s hospital to understaffed nursing homes by decree.
Why were they discharged if St James’s was almost empty as their own figures show us (at 58%), when they could have received the best acute care in hospital for what the HSE & Government said at the time was a deadly life-threatening disease? This is proof positive of medical negligence resulting in death by St James’s hospital.
Let’s now take a look at a Cancer hospital, St Luke’s Oncology and radiation network. Remember, cancer diagnosis, treatment & detection services were shut down across the country on the basis that Covid was a bigger threat to life (despite the Irish Government and HSE having access to data from Italy in March 2020, whichshowed conclusively that Covid was not a major pandemic threat – we reported on that here.
St Lukes Cancer network, Ireland’s largest. Cancer rates did not half because of Covid.
I think we can all agree that Cancer in Ireland has probably not reduced because of covid, and you can see the steady levels of treatment in this cancer hospital for the previous three years. This shows that people with cancer (a real killer in Ireland, with real mortality figures) was not being treated in the usual numbers. This also means that those cancers will be much worse when eventually treated or detected.
The Irish government and HSE know that screenings for cancer and other killer diseases have been stopped, yet continue into 2021 to advocate for unscientific and devastating lockdowns, despite Covid having killed a relatively small number of people who were not already dying of underlying conditions like Cancer. This is not an insensitive declaration – we are advocating here for hospitals to fully open up so that people can get screened for diseases that are guaranteed to kill more people than Covid. All data shows that Covid has been massively overblown, is not the threat as presented, and the mitigation and protection measures like masks and isolation are total overkill.
Skeptics may say that this data is proof that lockdowns work, but given that global locations without lockdowns have had less mortality than those with lockdowns, their contention will not hold up to any kind of scientific scrutiny. Take Sweden, Florida & North Dakota – there were no lockdowns or mask mandates there and they had less Covid death than all other lockdown states. Like everything about Covid, the actual science proves the Irish Government got everything wrong. The only question is how deliberate it was.
The Covid hysteria pushed by Irish politicians and Government meant that regular hospital admissions were drastically reduced due to appointments being cancelled, and people being afraid to visit the hospitals they pay for via taxation. The Irish government and HSE deliberately withdrew healthcare from the population. What more do the quiet people need to see in order to voice their opposition to what the Irish Government are doing?
The Lasting Health Impact Of Closed Hospitals
No rocket science degree required to figure this one out – even the brainwashed know that stopping hospital treatment on such a wide scale is disastrous. Many people unfortunately still believe the government messaging on Covid, through the spell of Irish mainstream media repetition and paralysis by fear. They are still having trouble understanding the scale of what they have done.
We are facing the biggest existential crisis our people have ever faced due to lockdowns and the suspension of healthcare & democracy in Ireland.
As Per Dr Scott Atlas late last year, “The harms to children of suspending in-person schooling are dramatic, including poor learning, school dropouts, social isolation, and suicidal ideation, most of which are far worse for lower income groups. A recent study confirms that up to 78 percent of cancers were never detected due to missed screening over a three-month period. If one extrapolates to the entire country, 750,000 to over a million new cancer cases over a nine-month period will have gone undetected… Beyond hospital care, the CDC reported four-fold increases in depression, three-fold increases in anxiety symptoms, and a doubling of suicidal ideation, particularly among young adults after the first few months of lockdowns, echoing American Medical Association reports of drug overdoses and suicides… Finally, the unemployment shock from lockdowns, according to a recent National Bureau of Economic Research study, will generate a three percent increase in the mortality rate and a 0.5 percent drop in life expectancy over the next 15 years, disproportionately affecting African Americans and women. That translates into what the study refers to as a “staggering” 890,000 additional U.S. deaths.”
Ireland has roughly the same cancer & disease rates per capita as the United States, which has sixty-seven times the population of Ireland (328 million versus 4.9 million). Dividing Atlas’s 890,000 additional US excess deaths caused by lockdowns by 67 gives you 13,263 additional Irish deaths due to disastrous unscientific lockdowns and shuttering of our health service in Ireland. This doesn’t even take into account suicides because the Irish Government are hiding those figures from the public, or the bigger unemployment rate we face.
Compare these projected death numbers with the 369 people who died with Covid and no underlying conditions for the past 12 months according to HSE, numbers which came via an FOI request C150/71 in February 2020, linked here. You can immediately see that crimes against humanity are occurring, perpetrated by Irish politicians, the HSE, and a complicit media who are legally mandated to investigate these matters in Ireland yet refuse to do so.
The Irish Government have the statistics and are not acting on them by opening up society immediately. At this stage, things have gone well beyond political arse-covering. People are dying unnecessarily and politicians know it. And they’re not dying not from Covid.
There Never Was A Pandemic
Based on this official data there never was a pandemic. Our hospitals were never under strain – not once. Even by the now changed WHO definition of a Pandemic, as reported by the British Medical Journal, there never was one. We see now with certainty how so many doctors and nurses had so much time to make dance videos, while the elderly of the country were wrongly made to fear for their lives.
We see now how they could make those comedy sketches and movie parody videos in full PPE on hospital trolleys, while the lives of our children were so devastatingly impacted by masks that continue to cause fear, erode their sense of self, and cause incredible feelings of guilt and helplessness along with suicidal-ideation.
We showed you that the Government & RTE knew that Covid was not the killer they said it was as early as March of 2020, yet still embarked on this ruinous path deliberately. They really must pay for the death and suffering they have caused, or this wound will fester for decades. We must continue to push for accountability. It will not be easy: so many institutions are so heavily invested in the idea of a pandemic that they cannot let go because of status repercussions, loss of trust issues (for that segment of the population that still believes their lies), and real legal liabilities. Politicians & NPHET operatives know that if the public at large fully understood the scale of what they have done, many would be dangling from lamp posts.
Get out of your echo chambers and put material like this in front of people who are still under the spell of media and political repetition. Each one of you reading this is important. Create your own content, use the excel data we received to make your own comparisons and inferences. Share it.
Lockdowns, and the quarantining of healthy populations, and the deliberate withdrawal of healthcare for a fraudulent pandemic, are crimes against humanity.
These are crimes that the Irish Government, politicians, and various civil servants are clearly guilty of. The evidence is clear now for the currently complicit police to redeem themselves and prosecute this psychopathic Irish establishment.
Michael Martin, Leo Varadkar, Tony Holohan and Stephen Donnelly are the murderous ringleaders: we await their arrest and trial by jury.
New variants are of no concern. There is no need to cancel summer holidays. Millions vaccinated, coupled with immunity from millions of prior infections means we can surf on the crest of the third wave, rather than being remotely concerned about it. In fact, the UK should open now. And vaccine passports, certificates, or whatever name they are being given, will do nothing to improve the health of the population – all headlines we have read and heard over the past week or so.
Except, we haven’t. We have heard and read the opposite. And we are instilled with fear from TV and radio adverts, complete with ‘that scary voice’ all too eager to give listeners nightmares, be it your impressionable primary-school-aged daughter, or a frail older lady now terrified into wearing a mask outside while waiting for a bus with no one within a 50-metre radius. But the reality is that the above headlines could have been written – and all based on science. Jayanta Bhattacharya is a Professor of Medicine at Stanford University and one of the co-authors of the Great Barrington Declaration, the report that called for the focused protection of the vulnerable and no lockdowns, signed by almost 14,000 medical and public health scientists, nearly 42,000 medical practitioners and close to 765,000 concerned citizens.
I interviewed him by email and he remains a staunch lockdown sceptic.
Why have the media, politicians and many scientists sought to panic the populace about SARS-CoV-2 far beyond what the evidence would warrant? The incentives include financial motives, political goals, the desire to protect professional reputations and many other factors.
The virus is seasonal and late fall/winter is its season. It is very unlikely, given that this is the case, that the virus will spread very widely during the summer months. It is also the case that a large fraction of the UK population has already been infected or vaccinated and is immune, which will greatly reduce hospitalisation and mortality from the virus in coming months.
There are tens of thousands of mutations of the SARS-CoV-2 virus. They mutate because the replication mechanisms they induce involve very little error checking. Most of the mutations either do not change the virulence of the virus, or weaken it. There are a few mutations that provide the virus with a selective advantage in infectivity and may increase its lethality very slightly, though the evidence on this latter point is not solid.
We should not be particularly concerned about the variants that have arisen to date. First, prior infection with the wild type virus and vaccination provide protection against severe outcomes arising from reinfection with the mutated virus. Second, though the mutants have taken over the few remaining cases, their rise has coincided with a sharp drop in cases and deaths, even in countries where they have come to dominate. Their selective infectivity advantage has not been enough to cause a resurgence in cases. Third, the age gradient in mortality is the same for the mutant and wild-type virus. Thus a focused protection policy is still warranted. If lockdowns could not stop the less infectious wild type virus, why would we expect them to stop the more infectious mutant virus?
According to the three authors of the Great Barrington Declaration which, other than Dr Bhattacharya, include Dr Martin Kulldorff, Professor of Medicine at Harvard Medical School, and Dr Sunetra Gupta, Professor of Theoretical Epidemiology at the University of Oxford, the UK Government is creating unfounded hysteria around SARS-CoV-2. Dr Bhattacharya said:
According to a meta-analysis by Dr John Ioannidis [Professor of Medicine at Stanford University] of every seroprevalence study conducted to date of publication with a supporting scientific paper (74 estimates from 61 studies and 51 different localities around the world), the median infection survival rate from COVID-19 infection is 99.77 per cent. For COVID-19 patients under 70, the meta-analysis finds an infection survival rate of 99.95 per cent.
The CDC’s [Centres for Disease Control] and Prevention] best estimate of infection fatality rate for people ages 70 plus years is 5.4 per cent, meaning seniors have a 94.6 per cent survivability rate. For children and people in their 20s/30s, it poses less risk of mortality than the flu. For people in their 60s and above, it is much more dangerous than the flu.
Even so, this hardly warrants a new Government drive urging families to carry out tests on their children twice a week in the hope of unearthing asymptomatic cases. Especially, as the vulnerable have already been vaccinated.
The scientific evidence now strongly suggests that COVID-19 infected individuals who are asymptomatic are more than an order of magnitude less likely to spread the disease to even close contacts than symptomatic COVID-19 patients. A meta-analysis of 54 studies from around the world found that within households – where none of the safeguards that restaurants are required to apply are typically applied – symptomatic patients passed on the disease to household members in 18 per cent of instances, while asymptomatic patients passed on the disease to household members in 0.7 per cent of instances. A separate, smaller meta-analysis similarly found that asymptomatic patients are much less likely to infect others than symptomatic patients.
Asymptomatic individuals are an order of magnitude less likely to infect others than symptomatic individuals, even in intimate settings such as people living in the same household where people are much less likely to follow social distancing and masking practices that they follow outside the household. Spread of the disease in less intimate settings by asymptomatic individuals – including religious services, in-person restaurant visits, gyms, and other public settings – are likely to be even less likely than in the household.
What about mask mandates?
The evidence that mask mandates work to slow the spread of the disease is very weak. The only randomised evaluation of mask efficacy in preventing Covid infection found very small, statistically insignificant effects [Danish mask study]. And masks are deleterious to the social and educational development of children, especially young children. They are not needed to address the epidemic. In Sweden, for instance, children have been in school maskless almost the whole of the epidemic, with no child Covid deaths and teachers contracting Covid at rates that are lower than the average of other workers.
In light of this, what conclusion can we draw from the fact that the UK Government wants the entire adult population to be injected against the virus, instead of just the vulnerable? And the possibility that we’ll need to produce vaccine certificates to access hospitality and sports venues or travel overseas?
Vaccine passports are a terrible idea that will diminish trust in public health and do nothing to improve the health of the population. Vaccine certificates are not needed as a public health measure. The Government had it right previously. The country should open up now that the older, vulnerable population has been vaccinated. The rest of the population is at much greater health risk from the lockdown than they are from the virus.
The author is a staff journalistat a national newspaper group.Oliver May is a pseudonym.
UNESCO says it is seriously concerned about the increase in “disinformation” and “conspiracy theories”. And they plan to put an end to it through a network of informants.
“Conspiracy theories can be dangerous,” the UN agency warned. “Often they ignore scientific evidence and polarize society with dire consequences. This has to stop.”
Unesco’s director-general warned that “conspiracy theories” could cause damage to people as well as to their health. “They reinforce misconceptions about the pandemic, reinforcing stereotypes that can fuel violence and violent, extremist ideologies,” said Audrey Azoulay.
The UN agency has launched a campaign to help people identify, debunk and report “conspiracy theories” to prevent them from spreading further.
This campaign is being carried out in collaboration with the European Commission, Twitter and the World Jewish Congress. The UN has created a toolkit to “debunk” such theories and smear anyone who dares to claim that governments are not fair and transparent.
The UN also warned that George Soros, the Rothschilds and Israel should not be linked to “alleged conspiracies”.
World events “are not secretly manipulated behind the scenes by powerful players with malicious intent,” the UN agency maintained.
And if anyone therefore comes across someone who believes that the world elite is plotting to consolidate power or direct events, then that person needs to take action. According to the UN agency, when meeting a “conspiracy theorist”, under no circumstances should one enter into a discussion. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.