Is this the smoking gun that proves hospital neglect and malfeasance, in the midst of a drummed up crisis environment, killed covid patients?
Daniel Horowitz recently interviewed Scott Schara, whose 19-year-old Down syndrome daughter Grace died of “covid” in Ascension’s St. Elizabeth’s Hospital.
In this stunning interview, Scott laid out the real-life horror movie of Grace’s experience in the hospital as a mentally disabled individual, culminating in her being sedated to death by hospital staff. According to him, the cruel indifference of the hospital was at least in part because Grace had Down Syndrome. (Scott created a website that contains all of his meticulously documented evidence and research where you can get all the sordid details for yourself.)
This “anecdote” aligns with the numerous and widely reported instances of the shocking descent of some hospital administrators and healthcare staff into depravity reminiscent of medical war crimes, one of the defining atrocities of the pandemic.
However, while vignettes of individual cases abound, there had not yet been any published data suggesting a direct link from hospital neglect to covid outcomes that would effectively be a smoking gun that hospital malfeasance was and is systematically killing patients.
“Of 2,311,282 people included in the study, 164,046 (7.1%) were admitted and 53,156 (2.3%) died within 28 days of a positive Covid-19 test. We found significant variation in the case hospitalisation and mortality risk over time, which remained after accounting for the underlying risk of those infected. Older age groups, males, those resident in areas of greater socioeconomic deprivation, and those with obesity had higher odds of admission and death. People with severe mental illness and learning disability had the highest odds of admission and death.”
In plain English, they discovered that having a “severe mental illness or learning disability” was a stronger predictor than age and obesity of becoming hospitalized and dying from covid.
It is less clear why there should be higher rates of hospital admission for mentally incapacitated individuals. Regardless, even if there is a completely separate reason for higher hospitalization rates for mentally disabled people, the most plausible explanation why having a learning disability is a greater “comorbidity” than age or obesity is that hospitals/LTC’s are ‘treating them to death’ whether by oversedation or using other inappropriate medical interventions; or utter neglect.
To be fair, the authors noted that obesity “had higher risk of admission than those of a healthy weight, but mortality risk was lower in those overweight, which may indicate higher perceived risk amongst clinicians and a lower threshold for admission.”)
Anyone reading this is undoubtedly well aware that age and obesity have consistently been the two most lethal comorbid factors for covid outcomes. So how can having a severe mental illness or *learning disability* be more lethal than being 258 lbs or 87 years of age?
Now, it is theoretically possible that ‘severe mental illness’ is in reality catching underlying conditions that are the real culprit of the increased hospital admissions and deaths and not the mental illness itself, as people with severe mental illness often are also suffering from severe physiological problems (which are also sometimes contributing to their psychological impairments).
It is not remotely plausible that “learning disabilities” have a physiological connection or influence on the pathological course of covid infection or disease, certainly not en masse that would show up as a stronger safety signal than both age and obesity. The proposition that an otherwise perfectly healthy individual with a learning disability is at a higher risk from covid than your 83-year-old grandma is so absurd that it should call the entire study into doubt.
It is plausible though that hospitals were systematically taking advantage of patients who were mentally incapacitated and therefore especially susceptible to utter neglect, and/or unable to resist adverse “treatment” by medical providers.
The implications of this finding are significant. Although this particular study is analyzing UK data, considering what we know about the general scene in US hospitals, it is overwhelmingly likely that this finding would be replicable using US data (by honest researchers). Consider that it was widely reported by the mainstream media that there were already plans made to triage care away from disabled patients and not just the elderly, e.g. this NBC report.
More importantly, this is another datapoint in the broad mosaic of evidence pointing to the complicity of hospitals and other healthcare provider institutions in the deaths of perhaps hundreds of thousands of covid patients.
In a truly ironic twist, the study authors unwittingly captured the root issue quite accurately, concluding that “People with severe mental illness and learning disability were amongst those with the highest odds of both admission and mortality, indicating the need for proactive care in these groups.”
Is there evidence of similar behavior in the UK?
This is relevant insofar as showing that the mindset, willingness and the means to essentially euthanize patients exists independently of the allegations regarding mentally incapacitated patients in the UK, which would be powerful evidence affirming that the reason that mental disabilities are the most lethal ‘comorbidity’ is that they were selectively discriminated against on an institutional level to receive potentially lethal medical interventions.
CARE homes have been accused of using powerful sedatives to make coronavirus victims die more quickly. Prescriptions for the drug midazolam rocketed during the height of the pandemic, with some claiming it has “turned end-of-life care into euthanasia.”
That elderly nursing home residents represent a large proportion of Covid-19 fatalities is a familiar if sad fact to most Canadians. Even sadder and more disturbing would be if many of those deaths were avoidable. And if some were deliberate, it would be shocking and outrageous. In this investigative piece, Anna Farrow explores the widespread use of “population triage” in several jurisdictions during the pandemic’s early months. While healthcare establishments seemed woefully unprepared in nearly all respects, Farrow found they were lightning-quick to adopt what amounted to killer protocols on thousands of elderly and vulnerable citizens. This included not merely the withholding of advanced care but end-of-life measures using fatal drug cocktails.
Several establishments in Quebec have already suspended the application of protocols, developed at the start of the COVID-19 pandemic, which aimed to relieve patients suffering from respiratory distress.
Canadians heard about it when the military were sent into elderly care homes in late April 2020. “To read Brigadier General C.J.J. Mialkowski’s report about the Ontario homes is to read a document that conveys in the precise, meticulous language of a soldier the horror the military personnel felt. It reads as dispatches from a new kind of battlefield,” Farrow states.
“There were common themes across the five facilities: lack of permanent, trained, and coordinated staff; misuse of narcotics; shortage of supplies; inadequate nutrition and hydration of residents.”
At risk of rehashing what I stated above, these scandals are a solid indication of the following:
The medical profession is capable of sedating or otherwise ‘treating’ patients to death, both morally and practically.
Medical institutions had developed protocols to systematically implement treatment regiments that result in the deaths of patients.
Medical practitioner and healthcare worker whistleblowers claiming that hospitals and nursing homes were committing negligence or outright causing patient deaths are credible as a general matter.
This neatly fits in with the hypothesis that hospitals were systematically taking advantage of mentally disabled patients to withhold treatment, or worse, recklessly administer sedatives and ventilate them.
COVID-19 is much less deadly in the non-elderly population than previously thought, a major new study of antibody prevalence surveys has concluded.
The study was led by Dr. John Ioannidis, Professor of Medicine and Epidemiology at Stanford University, who famously sounded an early warning on March 17th 2020 with a widely-read article in Stat News, presciently arguing that “we are making decisions without reliable data” and “with lockdowns of months, if not years, life largely stops, short-term and long-term consequences are entirely unknown, and billions, not just millions, of lives may be eventually at stake”.
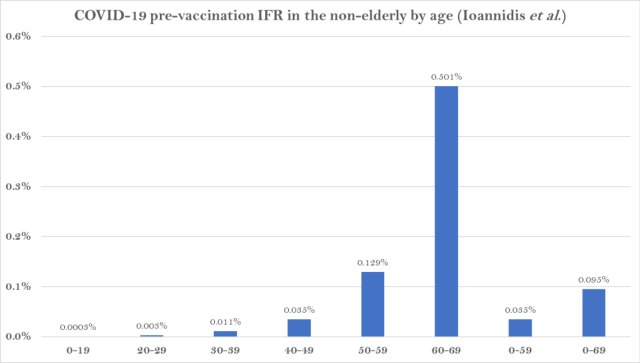
In the new study, which is currently undergoing peer-review, Prof. Ioannidis and colleagues found that across 31 national seroprevalence studies in the pre-vaccination era, the average (median) infection fatality rate of COVID-19 was estimated to be just 0.035% for people aged 0-59 years people and 0.095% for those aged 0-69 years. A further breakdown by age group found that the average IFR was 0.0003% at 0-19 years, 0.003% at 20-29 years, 0.011% at 30-39 years, 0.035% at 40-49 years, 0.129% at 50-59 years, and 0.501% at 60-69 years.
The study states that it shows a “much lower pre-vaccination IFR in non-elderly populations than previously suggested”.
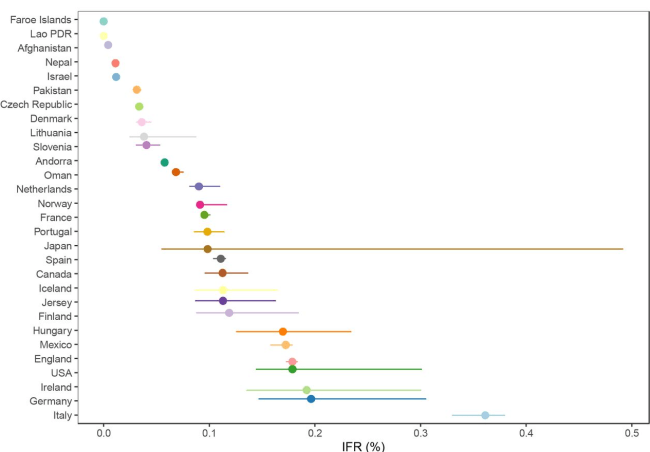
A breakdown by country reveals the wide range of IFR values across different populations.
The significantly higher values for the top seven suggest some of the difference may be an artefact of, for example, the way Covid deaths are counted, particularly where excess death levels are similar. Note also that the antibody studies date from various points during the first year of the pandemic, most of them prior to the large winter wave of 2020-21, when levels of spread and numbers of deaths were more varied than later in the pandemic as subsequent waves caused countries to converge.
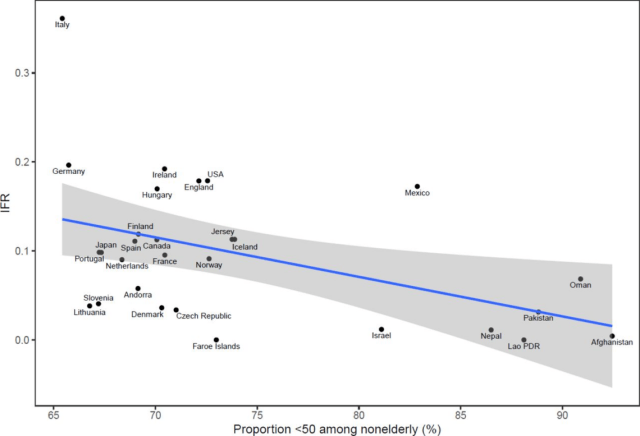
The reason some countries had much lower values and some much higher is not completely clear. The authors suggest that “much of the diversity in IFR across countries is explained by differences in age structure”, as per the plot below.
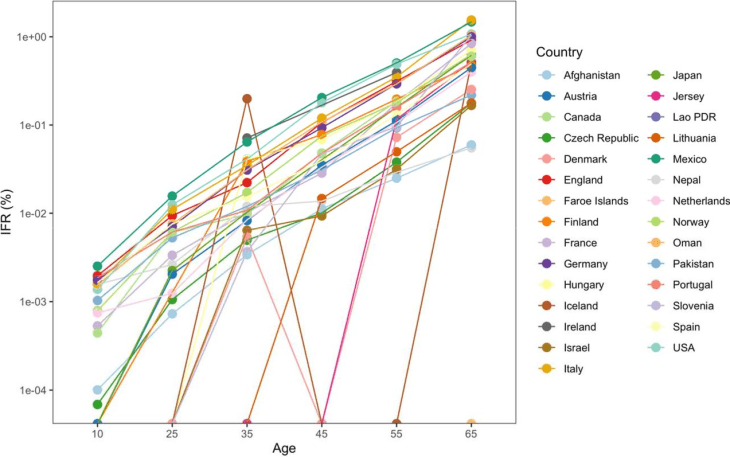
However, the age breakdown by country suggests that the IFR differed for each age group in each country, casting doubt on that suggestion. (In the chart below, note the logarithmic scale, and ignore the zig-zag lines, which are due to small countries having low numbers of deaths.)
Why are countries seeing differing IFRs even for the same age groups? The authors suggest a number of explanations, including data artefacts (e.g. if the number of deaths or seroprevalence are not accurately measured), presence and severity of comorbidities (for example, obesity affects 42% of the U.S. population, but the proportion of obese adults is only 2% in Vietnam, 4% in India and under 10% in most African countries, though it affects almost 40% of South African women), the presence of frail individuals in nursing homes and differences in management, healthcare, overall societal support and levels of drug problems.
Prof. Ioannidis has previously published a number ofpapers estimating COVID-19’s IFR using seroprevalence surveys. He and his team conclude that their new estimates provide a baseline from which to assess further IFR declines following the widespread use of vaccination, prior infections and evolution of new variants such as Omicron.
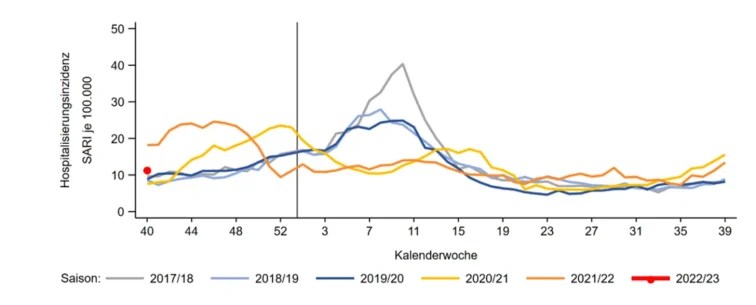
If you look at hospitalisations, though, you’ll have a hard time finding any crisis at all. Here, for example, are hospitalisations for severe acute respiratory infections since 2017, as published last week by the Robert Koch Institut:
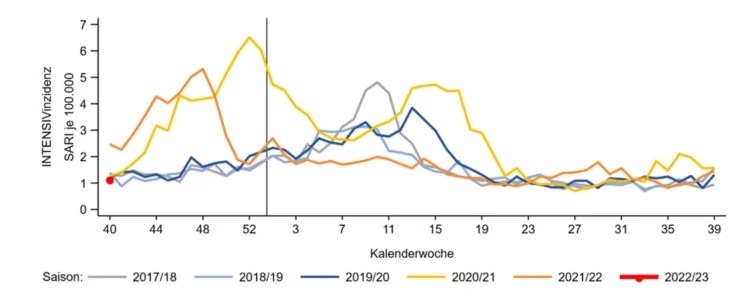
The red dot is where we are right now. Admissions are totally in line with the pre-pandemic era. The ICU admissions tell exactly the same story:
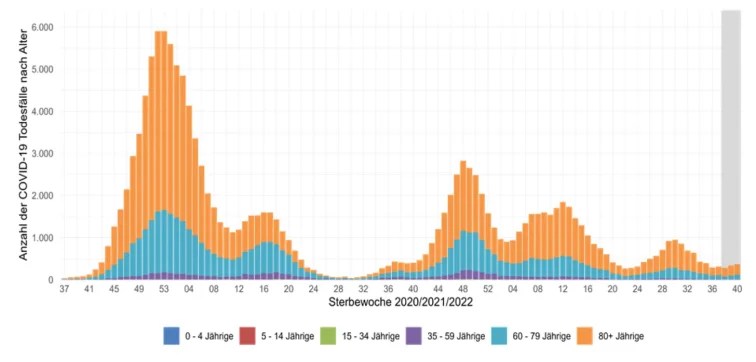
Nor is anybody really dying at the moment:
To the extent that there is any crisis at all here, it’s of our own making. Hospital patients with Corona diagnoses have to be treated according to strict isolation protocols, in special wards. These rituals are staff-intensive, and they effectively reduce across-the-board hospital capacity. It’s the same as our quarantine laws, which induce worker shortages by forcing millions of otherwise healthy Germans into isolation whenever they test positive. We could declare a rhinovirus pandemic tomorrow and suffer all the same problems from the common cold, and by the same token we could end all of this ourselves in an instant, by abolishing our foolishness and choosing to ignore SARS-2. Instead, we insist that this virus is dangerous and through our own behaviour we make it so.
The most onerous part of all this, is the inability of the German press to find a new narrative, ask new questions, or to change their reporting in any way at all — despite the totally different behaviour of Omicron and the near-universal levels of immune exposure to SARS-2. I know some of you complain that I repeat the same themes and arguments overmuch, but Germany has descended into some kind of purgatorial alternate reality, where it’s always March 2020, and our hospitals are always on the verge of melting down, and we never have enough information, so we just have to try masking and social distancing and hope for the best. They’re wrong about everything and they just keep telling the same lies over and over.
Dr. Jeff Barke, a founding member of America’s Frontline Doctors, joins Del to discuss California’s new law enacted with the passage of AB2098, which effectively makes it illegal for doctors to disagree with politicians.
Pictured is the Federal President of Germany, Frank-Walter Steinmeier, violating the Infection Protection Act, which requires masks in all local and long-distance trains. He pleads that he only took his mask off for a few seconds for the purposes of a short video message and some publicity photographs. Alas, the law provides for no such exception, and why should it? The official position of the German government is that unmasked people are a danger to themselves and others, particularly when they are on trains.
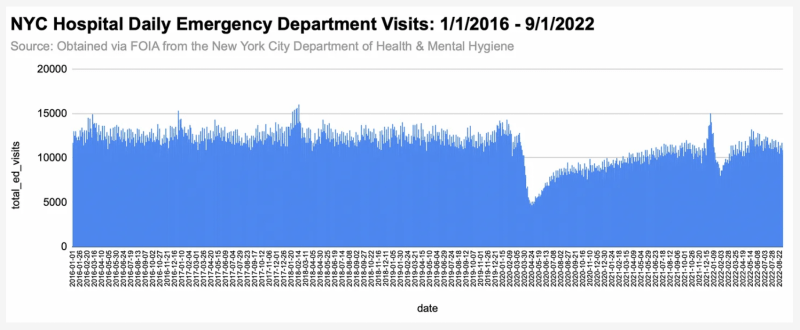
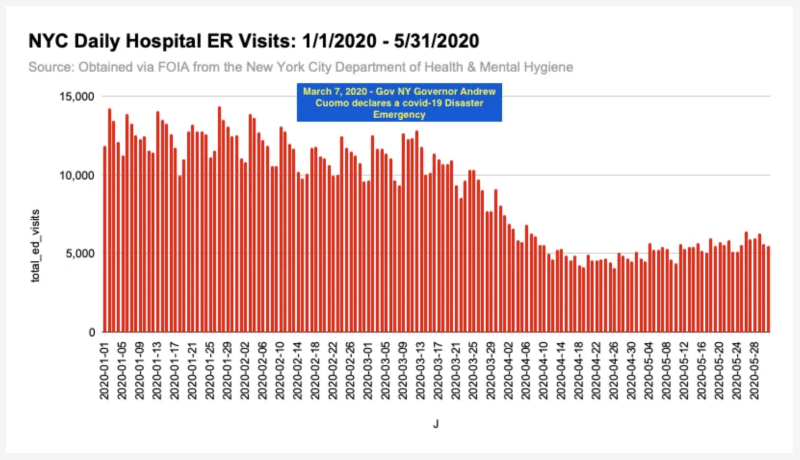
Repeat after me: New York City’s emergency rooms were not overwhelmed by visits in spring 2020. In fact, they were busier during the 2017-2018 flu season than they were at any point between lockdown orders and January 2022’s “omicron surge.”
Data from the New York City Department of Health & Hygiene, provided via FOIA request, tell a different story from the one told by elected officials, news media, dancing nurses, and aspiring celebrity doctors.
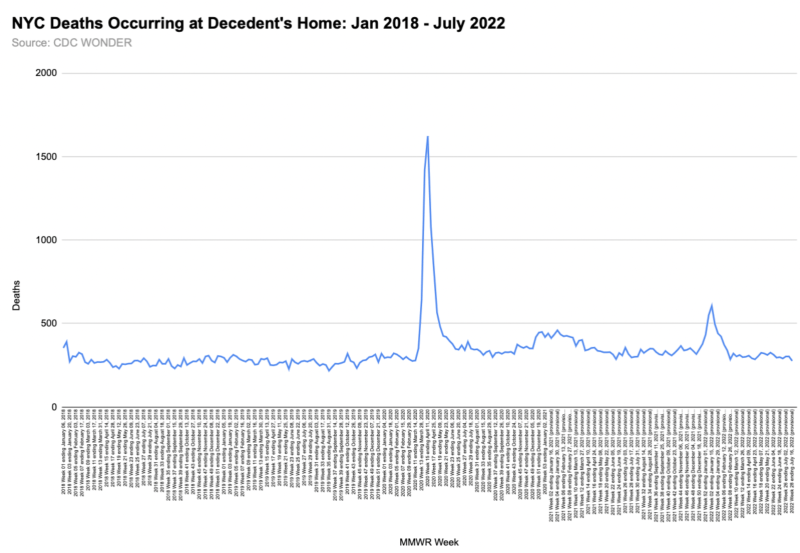
Contrary to The Narrative, Governor Cuomo’s stay-home orders didn’t come “just in time” to save NYC’s healthcare system from collapse. They triggered a staggering 60%+ decline in the number of people coming or being brought to ERs. (NYC’s spring 2020 emergency visit decline was even greater than Chicago’s.) That’s a hard truth to handle given the city’s record high number of EMS calls and hospital, outpatient facility, & ER deaths in spring 2020.
It’s likewise a hard, if predictable, truth to handle for those of us who were/are anti-lockdown.
We remember how selected images of & video from NYC hospitals scaring people across the country about how dangerous covid must be.
We remember being told, implicitly if not explicitly, that in order to avoid what was happening in New York, we must be content with Zoom church, screen school, carryout, & minimal in-person contact with humans outside our own household.
We remember that anyone who questioned the wisdom of these directives – or wondered whether NYC hospitals were truly any busier than during a bad flu season – was a grandma killer. (Meanwhile, grandma was being killed by the very policies & protocols put in place to *save hospitals* and *slow the spread,* not only in the hospital and at the long-term care facility, but also at home.
NYC deaths occurring at decedent’s home (all causes)
No one denies that thousands of New Yorkers died needlessly in March – May 2020. Now we know it wasn’t because the city’s ERs were overrun.
I want to talk about Dr Aseem Malhotra. After the press conference on 27 September, there were concerns from some circles that World Council for Health was associating itself with Dr Malhotra. While some regard him as ‘controlled opposition’, others object to his lack of questioning vaccines in general, given Covid-19 “vaccine” and pharmaceutical industry corruption revelations.
We are living through interesting times. As the institutions entrusted with public service and care, reveal themselves to have betrayed our trust, as vaccine harms become ever harder to shove under the carpet, and as governments become ever more incompetent and unaccountable, we find ourselves apparently cast adrift on a turbulent sea, understandably wondering who is our enemy and who is our friend.
What helps me stay centred and free from fear, is the 7 Principles of A Better Way. They came out of the collective wisdom shared in May’s Better Way Conference, and they are a lodestar in these times of extreme pressure.
One of the Principles is:
We value different perspectives.
We celebrate respectful discussion as the means to ever more refined knowledge, compassion and wisdom.
It is in the spirit of this noble principle that we hosted Dr Malhotra’s press conference. Not all of us agree with his view that traditional vaccines are safe and effective. But we do agree that the Covid-19 vaccine roll-out should be halted immediately, and this is something that World Council for Health has been calling for almost since its inception. Dr Malhotra’s press conference has been viewed well over 100,000 times. Many wrote to us to say that they would be sharing it with their loved ones as it was just the thing that would reach them and get them thinking.
My hope is that his courageous efforts will, in particular, reach doctors and other medical professionals – those who are questioning the ‘safe and effective’ narrative but are afraid to speak up. They are certainly under the cosh: on Friday, California’s Governor Gavin Newsome signed a bill that means any doctor can lose their licence for sharing ‘misinformation’ or ‘disinformation’ about Covid-19. In Queensland, Australia, a similar bill is being presented to Parliament next week that goes even further, prohibiting doctors from giving any advice or opinion that goes against public health edict. Governments are going out of their way to shut doctors up, and while that may be terrifying for doctors – and their patients – it is also an indication of the power doctors hold. Governments know that if enough doctors speak up, the ‘safe and effective’ narrative will quickly crumble.
How we treat Dr Malhotra may be a deciding factor as to whether other doctors follow suit to stand up for medical ethics and their patients. Will we welcome them with gratitude and compassion, or shun them for not having spoken up sooner? This is a personal question for each of us, and one that we will all have to reckon with at some point. Is it for us to judge and does it serve the highest good of all to do so?
There are those who benefit from us dividing ourselves and each other into the binary camps of friend or foe. Of debating whether this or that person is controlled opposition, or bona fide. In this endless speculation we exhaust our precious life force, and find ourselves lacking the energy to create a better way.
If we can just relax and remember ourselves and why we are here, we can reclaim the broader view: that humanity is inherently fallible and yet capable of the most extraordinary acts of redemption. That we are all beings of light, but that we each have our own darkness as well. And, that we are all redeemed in the light of compassion for ourselves and each other.
This Saturday 15th October, we are holding a UK Doctors Conference in London. Our wish is for every doctor and health professional to feel they are welcome. It will be a safe and private space for people to ask questions, learn more about what’s really going on, and speak freely with each other. Please watch NHS Consultant Dr Julia Wilkens’ invitation (click on the image to view) – she could not have put the value of being there any better:
Please share this event widely: there is still space and we want as many people as possible to come together and realise that they are not a sole dissenter but one of many ready to question, to inquire, and understand.
‘Winning Doctors Back One at a Time’ Hearts of Oak podcast
I recently returned to the highly informative Heart of Oak podcast to speak about doctors, health, and of course the doctors conference. I really enjoyed our conversation – if you’d like to tune in, you’ll find it on the Hearts of Oak home page here.
Title says it all – the evil of Mandates, when they had to know they served no purpose but… totalitarianism and control! Great one to share with normies, as all the data is packed in here too.
NOTE: My extensive research and interviewing / video/sound editing, business travel and much more does require support – please consider helping if you can with monthly donation to support me directly, or one-off payment: https://www.paypal.com/donate?hosted_button_id=69ZSTYXBMCN3W – alternatively join up with my Patreon: https://www.patreon.com/IvorCummins
I’ve just been included in a nonsense propaganda publication! A book no less – publishing tomorrow Oct 6th – “Web of Lies”. Unbelievable deceit dripping through the piece they decided to share with me before publication – and stunningly incorrect throughout. Btw if referring to this book or sharing thoughts, always use the hashtag #WebOfLies – and PLEASE don’t comment if talking depopulation, radio waves or any other such stuff – always stick to the pandemic response ‘science’, and to published science/data – I never associate with anything other than the latter, as you should well know… 😠
That said, this vid will give you and your friends/family an invaluable education on how these guys craft propaganda. Enjoy, while I blow their deceit out of the water with trivial ease – directly from the published data – as always 😉 p.s. the white paper I sent them – a key resource to download and share: https://thefatemperor.com/wp-content/uploads/2022/09/Evidence-For-and-Against-the-Effectiveness-of-Lockdown-Policies-DRAFT-RevC.pdf
Almost three years ago science entered a new dark age.
Jay Bhattacharya, a professor of medicine at Stanford University and co-author of the Great Barrington Declaration, seems to agree. He has been compiling a list of the examples of anti-science we have unfortunately become used to.
I have listed his thoughts so far but the list is continually expanding.
Insinuating that the lab leak hypothesis is a racist conspiracy theory is anti-science;
Closing international borders to keep a virus out when the virus is already established in-country is anti-science;
Panicked killing of Danish mink was anti-science. Public health apologizing for the mistake is pro-science;
Redefining herd immunity to exclude immunity conferred by disease recovery is anti-science;
Sending covid infected patients back to nursing homes to keep hospital beds empty was anti-science;
Lockdowns and other trickle down epidemiology are anti-science;
Science bureaucrats using their power to smear scientists who disagree with them is anti-science;
Instituting lockdowns & restrictions on the basis of overly-simplistic covid models is anti-science;
Pretending there is a scientific consensus on lockdown and so much else when there is not a scientific consensus (Especially while censoring sceptical voices) is anti-science;
Arbitrarily dividing society into essential and non-essential is anti-science;
Ignoring the obvious and devastating economic costs of policy is anti-science;
Censorship of scientific debate is anti-science. Literally.
Zoom school is anti-science;
Politically partisan public health is anti-science;
Not permitting healthy people to leave home for more than an hour, even for exercise, is anti-science;
Jumping off the sidewalk to avoid the breath of an unmasked person walking by is anti-science;
Shutting down kids’ sports is anti-science;
Public health shaming people for not following public health diktats is anti-science;
Forcing school kids to eat six feet apart from each other, outdoors and in silence was anti-science;
Redefining health to be synonymous with the avoidance of a single infectious disease is anti-science;
Six-foot social distancing is anti-science;
Not letting family members visit dying relatives is anti-science;
Contact tracing to contain a highly infectious and aerosolized respiratory virus is anti-science;
Zero covid is anti-science;
Mask mandates are anti-science;
White washing the harm done to children by school closures by glibly asserting that ‘kids are resilient’ is anti-science;
Institutionalized hypochondria is anti-science;
Masking toddlers is anti-science;
Requiring waiters to mask to serve unmasked patrons is anti-science;
Noble lies are bad public health practice and anti-science;
Pharmaceutical company funding of on-air news media and professional medical organizations is anti-science;
Policing private doctor patient communication for non-CDC approved content is anti-science;
Science & medicine are the common inheritance of all, regardless of party. Medical and scientific professional societies officially endorsing political candidates and thereby alienating half the population is anti-science;
Not rapidly running randomized trials to evaluate off-patent early treatment options and denigrating doctors and patients who tried them (“horse paste”) when better options were not available is anti-science;
Ignoring age-stratification in risk in determining pandemic policy and vaccine recommendations is anti-science;
Vaccine discrimination is socially divisive and is anti-science;
Public health experts have an obligation to speak respectfully with everyone, including people who oppose their recommendations (such as on vaccines). Guilt-by-association attacks on experts who fulfil this obligation are anti-science;
Asserting that a vaccine stops transmission when it does not stop transmission is anti-science;
Ignoring immunity after covid recovery is anti-science;
Vaccine mandates have demolished public trust and are anti-science;
Pausing childhood vaccination programs and tuberculosis treatment in poor countries because of fear of covid led to many unnecessary deaths and is anti-science;
Ignoring legitimate vaccine injury is anti-science;
Declaring oneself to be The Science itself is anti-science;
On the day she was sworn in as Alberta’s new Premier, Danielle Smith said unvaccinated individuals have been the most discriminated against in the country since last year.
“I don’t think I’ve ever experienced a situation in my lifetime where a person was fired from their job, or not allowed to watch their kids play hockey, or not allowed to go visit a loved one in long-term care or a hospital, or not allowed to get on a plane to either go across the country to see family or even travel across the border.”
“So they have been the most discriminated group I have ever witnessed in my lifetime. That’s a pretty extreme level of discrimination that we have seen…”
Smith added that she isn’t dismissing the seriousness of other forms of historical discrimination. But over the past year, she says not one group experienced it worse than unvaccinated individuals.
“We are not going to segregate a society on the basis of a medical choice.”
Smith also noted that she will fire the province’s health minister, Deena Hinshaw.
“I appreciate the work that Dr. Deena Hinshaw has done, but I think that we are in a new phase where we are now talking about treating coronavirus as endemic, as we do influenza,” Smith said.
In August, The Counter Signalreported that during the height of lockdowns and mandates, when Albertans were fed daily fear propaganda, CMOH Deena Hinshaw received hundreds of thousands of dollars as a cash bonus.
Smith said she’ll assemble a team of health advisors in Hinshaw’s place. One issue she said will be improved are wait times for people in need of emergency help. Ambulance patient offloading times, and emergency room wait times are far too long, Smith said.
The Department of Health and Human Services (HHS) and the Centers For Disease Control and Prevention (CDC) have been exposed running the most disturbing and elaborate propaganda campaign in living memory. Screen writers, comedians, influencers and church leaders, among others, were recruited and paid to promote Covid-19 vaccines to the masses, while ridiculing and shaming those who refuse the jab.
Judicial Watch has nailed it yet again, suing HHS to acquire a treasure trove of documents that reveal the world’s most exhaustive and heavily funded propaganda campaign to try to convince the oblivious masses to be injected with an experimental mRNA concoction.
“Judicial Watch Uncovers Biden Administration Propaganda Plan to Push COVID Vaccine,” reads the Judicial Watch press release: Judicial Watch announced today that it received 249 pages of records from the Department of Health and Human Services (HHS) detailing the extensive media plans for a propaganda campaign to push the COVID-19 vaccine. One document in the released records was entitled, “PEC (Public Education Campaign) Plan April 19 – May 31 2021” and featured all the following bullet points and more:
Vaccine engagement package to all entertainment talent and management agencies
Vaccine engagement package to all media companies and show producers
Outreach to major culture event producers
Produce HHS question-and-answer videos featuring local Black doctors discussing the vaccines, how they work, and why the public should get vaccinated
Request that Tom Brady create a video with his parents encouraging vaccination
Create custom partnerships with the social media platforms with algorithms to hit the audience
Launch Hollywood comedy writers video content
Work with YouTube on an original special about vaccinations targeted to young people
Work with Instagram to produce a series about vaccines for @Instagram (the largest social media account in the world, 387 million followers)
Request major TikTok, Snapchat and Instagram influences to create videos of themselves being vaccinated
Request a vaccination special on Christian Broadcast Network featur[ing] Evangelical leaders
Request that the major live TV entertainment shows feature hosts being vaccinated on air (ex: the hosts of The Voice)
Request that the TV morning and daytime talk shows feature special vaccination reunion moments with everyday Americans
Convene an editorial meeting with the publishers of Catholic newspapers and newsletters across the country
Place a trusted messenger on the Joe Rogan Show and Barstool Sports to promote vaccination
Work with the NFL, NASCAR, MLB, CMA to request they create content with their talent and release through their broadcast and social channels
As Judicial Watch President Tom Fitton stated, “These records show a disturbing and massive campaign by the Biden administration to propagandize and politicize the controversial COVID vaccine. It seems as if the entire entertainment industry was an agent for the government!”
CONFIRMED: HHS and CDC paid comedians and screen writers to mock the unvaccinated
These documents confirm what many of us have long suspected: That HHS and CDC paid stand-up comedians to mock the unvaccinated in their comedy routines. Screen writers and production companies were also bribed to push vaccine propaganda in their episodes, and social media influencers were paid off to pimp the untested jabs.
Part of the Covid-19 stimulus push included a cool $1 billion to the CDC for propaganda payoffs and bribes. They used this money to flood tech platforms, Hollywood writers and influencers with dark money, and in return they had to sell their soul by promoting the mRNA jabs.
Hollywood has always been in on the depopulation agenda
This was all taxpayer money, used to brainwash Americans with a monstrous, coordinated vaccine propaganda campaign coordinated by HHS and the CDC.
At the same time, Big Tech targeted anyone who disagreed with the propaganda, banning them from platforms and destroying their reputations. All because they dared to take a stand against the propaganda.
The media was in on it the whole time, of course, and they refuse to report on this bombshell HHS document even now. They’ve been complicit the entire time. Watch:
“This bill would designate the dissemination of misinformation or disinformation related to the SARS-CoV-2 coronavirus, or ‘COVID-19,’ as unprofessional conduct. The bill would also make findings and declarations in this regard.”
Any information doctors give that publicly contradicts state messaging on the COVID-19 virus, COVID vaccines, and prevention and treatment information is now “unprofessional conduct.”
Misinformation, as defined by the bill, refers to “false information that is contradicted by contemporary scientific consensus contrary to the standard of care.”
In other words, the state now has legal grounds to strip doctors of their medical licenses if they publicly disagree with its COVID related messaging.
In response to Newsom’s new law, the Liberty Justice Center quickly filed a lawsuit against the state’s Medical Board and Attorney General on behalf of two doctors.
“Science is not static. By its very nature science is constantly evolving and the subject of unending debate,” the Justice Center states.
“Throughout the COVID-19 pandemic, the Centers for Disease Control and other public health authorities have constantly shifted their public presentation of the scientific data. Governor Newsom himself closed schools and even outdoor spaces— policies now widely acknowledged as unscientific and harmful.”
Last month, in another bizarre display of scientific tyranny, the UN’s Global Communications representative Melissa Fleming said, “We own the science.”
Fleming was speaking to the World Economic Forum’s “disinformation” panel.
“We’re becoming much more proactive. We own the science, and we think that the world should know it, and the platforms themselves also do,” she said.
In Canada, provincial health boards have threatened medical professionals who go against their messaging.
Earlier this year, 40 doctors from Ontario were under “investigation” for COVID-19 related decisions that went outside the province’s orders.
Almost immediately after the proxy war erupted, ISIS-tier footage of the torture and murder of Russians in Ukrainian custody emerged.
On July 6th, the New York Times published an astonishing investigation: In Ukraine, Killings of Surrendering Russians Divide an American-Led Unit. The article documents in grim detail how Chosen Company, an international volunteer battalion for Kiev, routinely executes Russian prisoners of war. It is the very first mainstream admission that this practice – a brazen breach of the Geneva Conventions, and a grave war crime – is widespread among Ukraine’s fighters, both foreign and homegrown. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.