New Study Blames COVID on NIH, University of North Carolina — Finds Fauci and Baric’s Fingerprints on Pandemic Bug

By Robert F. Kennedy, Jr., J. Jay Couey, Ph.D., and Charles Rixey | The Defender | October 21, 2022
Critics have long questioned why the National Institutes of Health (NIH) would fund experiments by University of North Carolina of Chapel Hill (UNC) professor Ralph Baric to develop a technique for hiding evidence of human tampering in laboratory-created super viruses.
Aided by some $220.5 million in National Institute of Allergy and Infectious Diseases (NIAID) funding, Baric developed a so-called “Seamless Ligation” technique, which he boasted could perfectly conceal all evidence of human tampering in laboratory-created viruses. Baric nicknamed his invention the “no-see’m” method.
Now a new study, “Endonuclease fingerprint indicates a synthetic origin of SARS-CoV2,” published on the preprint server bioRxiv, shows that — apparently unbeknownst to Baric — the “seamless ligation” concealment gimmick leaves its own minute but legible signature.
Most momentously, these same researchers have discovered that damning signature in the genome of the virus that causes COVID-19.
Baric’s technique has long been controversial. “It’s the artist that doesn’t sign his name to the painting; the virologist that doesn’t put his signature into the virus to let us know whether or not it is emerging naturally or whether it is produced in a laboratory,” said Jeffrey Sachs, chair of The Lancet COVID-19 Commission, a task force that investigated the origins of COVID-19.
“All of it says, my God, there was really a big, very risky research agenda underway.”
This month, Sachs published the results of his 22-month investigation in The Lancet, including the damaging conclusion that COVID-19 was probably laboratory-generated and that the technology probably came from NIH-funded science.
Referring to Baric’s seamless ligation methodology, evolutionary biologist Bret Weinstein observed:
“It’s the exact opposite of what you would do if your interest was public health. Public health scientists would be marking their enhancements with red flags — not devising ways to hide them. The only reason you would want a concealer is to advance a sinister purpose — such as illegal bioweapons development — some mischief that the scientist didn’t want traceable back to his lab.”
Baric taught his “no-see’m” method to the Wuhan Institute of Virology’s (WIV) “Bat Lady” Shi Zhengli in 2016. In return, Baric received Chinese coronaviruses collected by Shi from bats in Yunnan province. (Scientists have linked the COVID-19 genome’s pedigree to closely related bats.)
Shi and her colleagues at the Wuhan Institute subsequently demonstrated their mastery of Baric’s high-risk technique in a series of published — and highly controversial — gain-of-function experiments at the Wuhan lab. It has been even more puzzling to his critics that Baric, again with NIAID funding, chose to share this dangerous technique for weaponizing pathogens with Chinese scientists who have clear links to the Chinese military.
Experts say that the implications of this new study could be far-reaching. By pointing the finger at Baric, the study raises the possibility of potentially devastating liability for the NIAID and the University of North Carolina and other parties.
Scientists, including those close to Dr. Anthony Fauci, have repeatedly pointed out that SARS-CoV-2, the virus that causes COVID-19, has genomic sequences that appear inconsistent with natural evolution: The COVID-19 virus is no longer infectious in bats, and its spiked protein feature — which is unknown in this family of coronavirus — includes numerous mutations that make it ideally infectious in humans.
The closest known coronavirus relative — a coronavirus from the Wuhan lab — is 96.2% identical to SARS-CoV-2. The peculiar spike accounts almost completely for the entire 3.8% difference. Oddly, there are multiple novel mutations in the spike and almost none in the rest of the genome.
Natural evolution would be expected to leave mutations distributed evenly across the genome. The fact that virtually all the mutations occur on the spike led these scientists to suspect that that particular Wuhan lab coronavirus collected by Shi Zhengli is the direct progenitor of SARS-CoV-2 and that its new spike was implanted through engineering.
However, the unmistakable fingerprints of lab engineering were absent — leaving many experts wondering whether Baric’s technique was used to assemble a novel coronavirus with the engineered spike while removing the evidence of lab generation.
This new study connects the biological breadcrumbs that link federally funded research to a global pandemic. That trail leads directly to UNC and NIAID.
The authors of the study — a team of researchers from Duke University, University Clinics of Würzburg and an industry group — identified a characteristic signature in the amino acid code. That indelible artifact could only have emerged from Baric’s “no-see’m” methodology.
In an interview last spring, Baric himself confessed, that at the time the pandemic began, only two or three labs in the world were using his protocol – including his UNC lab and the WIV.
The study’s authors’ conclusions rest on the presence of unique sites in the COVID-19 virus. These sites allow special enzymes called “restriction enzymes” to cut the DNA into building blocks of unique size that then can be “stitched together in the correct order of the viral genome,” according to the study’s authors.
Essentially, Baric’s technique leaves behind unique spellings in the “genetic vocabulary.” The new words include “odd spelling choices” subtly distinguishing them from typical viral vocabulary.
The magic of Baric’s “no-see’m” technique is to invisibly weave these telltale “spelling” changes into the viral sequence between relevant genes without altering the viral protein. This is like changing the “spelling” of the word without changing its meaning; the casual listener will never notice the difference.
The research team used forensic tools to drill down on minute “spelling differences” in the SARS-CoV2 genome that betray laboratory tampering using the “no-see’m” technique.
Consider how a Brit would spell “colour,” “manoeuvre” or “paediatric.” The choice to spell a word in a certain way can reveal your nation of origin. Similarly, these nearly imperceptible changes in the viral sequence give away the laboratory origins of this virus.
In sharing his seamless ligation technique with Shi Zhengli, Baric assured that the WIV possessed all the required elements of the assembly process. EcoHealth Alliance’s infamous DEFUSE proposal describes the same techniques in detail. (submitted to The Defense Advanced Research Projects Agency, or DARPA, in 2018).
The world now has proof positive that SARS-CoV2 is an engineered laboratory creation generated with technology developed by Ralph Baric with U.S. government funding.
Prosecutors and private attorneys representing clients injured by the COVID-19 pandemic now have a smoking gun. The gun points at humanity. Forensic scientists have now successfully lifted faint but precise fingerprints from the lethal pistol’s grip and trigger. Those fingerprints belong to the NIAID and the University of North Carolina.
Baric is Fauci’s favorite gain-of-function scientist. The cascade of NIAID funding to Baric and his UNC lab has financed 152 studies approaching a quarter-billion dollars.
Those federal grants have made Baric the global kingpin of gain-of-function science. In conformance with standard practice, it is probable that UNC pockets one-quarter to one-half of NIH’s financial felicities to Baric for “administrative costs.”
These monumental payments have probably incentivized UNC to turn a blind eye to Baric’s reckless experiments and to his controversial decision to transfer his dangerous technologies to a Chinese military laboratory known to suffer from deficient safety protocols and shoddy construction that make it, in the words of Congressional investigators, less secure than a “dentist’s office.”
UNC’s role in enabling the questionable conduct may have precipitated a global pandemic that could easily give rise to liability for negligence.
UNC and NIAID’s liability is now clear. But do we have positive proof that the Wuhan lab created the monstrosity that caused COVID-19?
The cumulative evidence strongly suggests that the Wuhan lab used Baric’s methodologies to cobble together the chimeric virus that caused the COVID-19 pandemic. But a few missing puzzle pieces still prevent us from definitively proving that this dangerous construction project occurred at the Wuhan lab.
As The Lancet Commission report concluded, the released emails show that NIH’s Dr. Francis Collins, NIAID’s Fauci and EcoHealth Alliance’s Peter Daszak, and others are continuing to collaborate with Shi Zhengli and Chinese officials to suppress the public release of information that would allow us to complete this picture. Stay tuned!
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Fauci forced to testify on social media censorship
Samizdat | October 22, 2022
The White House’s chief medical advisor, Anthony Fauci, and other senior officials are set to be deposed under oath as part of a lawsuit claiming the government worked alongside social media platforms to create a “massive censorship enterprise” throughout the Covid-19 outbreak.
In a Friday ruling, Judge Terry Doughty granted a joint request from the attorneys general of Missouri and Louisiana to compel several current and former officials to testify in the suit, among them Fauci, ex-White House press secretary Jen Psaki, Director of White House Digital Strategy Rob Flaherty, Surgeon General Vivek Murthy and two high-level figures from the FBI and Department of Homeland Security (DHS).
“After finding documentation of a collusive relationship between the [Joe] Biden administration and social media companies to censor free speech, we immediately filed a motion to get these officials under oath,” Missouri AG Eric Schmitt said in a statement. “It is high time we shine a light on this censorship enterprise and force these officials to come clean to the American people, and this ruling will allow us to do just that. We’ll keep pressing for the truth.”
While the defense insisted that senior officials can only be called to testify about their actions in office under “extraordinary circumstances,” Judge Doughty said the personnel in question met that standard. He added that the two GOP-led states “have proven that Dr. Fauci has personal knowledge about the issue concerning censorship across social media as it related to Covid-19,” ordering him to cooperate with a deposition.
Requests to depose the other officials were granted on similar grounds, as the judge concluded all either held direct meetings with social media firms about the purported censorship, or had close knowledge of those discussions.
Jen Easterly, who heads up the DHS’s Cybersecurity and Infrastructure Security Agency (CISA) was also ordered to testify. She played a “central role” in “flagging misinformation to social-media companies for censorship,” the plaintiffs argued, describing the cyber agency the “nerve center” of “the federal government’s efforts to censor social media users.” The same official was said to be involved in the DHS’ now-defunct ‘Disinformation Governance Board’ – dubbed the ‘Ministry of Truth’ by critics – which would have created a new mechanism to facilitate cooperation between the White House and social media sites.
Initially filed last May by Schmitt and Louisiana Attorney General Jeff Landry, the lawsuit claims the federal government encouraged online platforms to censor, delete or ban certain speech about the pandemic, including discussion of the “lab leak theory of Covid-19’s origin,” as well as questions about the effectiveness of face masks, vaccines or lockdown policies, among other issues. The two AGs have largely relied on documents obtained through subpoenas of YouTube, Twitter and Facebook’s parent firm Meta, which detail regular communications between the government and social media sites.
The White House, as well as the eight officials ordered to testify, have yet to comment on Friday’s ruling. The depositions must take place within 30 days of the order, though it remains unclear whether the defense intends to appeal the decision.
NEW EVIDENCE PROVES BIDEN ADMINISTRATION PRESSURED FACEBOOK AND TWITTER TO CENSOR AMERICANS
Liberty Justice Center | October 21, 2022
Yesterday, author and data analyst Justin Hart filed new evidence in his federal lawsuit against Facebook, Twitter, and U.S. President Joe Biden. The evidence documents collusion between social media companies and the federal government to silence Americans online on the Internet — a public forum the Supreme Court has determined is the most important place for the exchange of ideas. Hart sued the social media giants and Biden administration in August 2021 for violating his First Amendment right to free speech for working together to monitor, flag, suspend, and delete social media posts it deems “misinformation.”
Hart is represented by attorneys from the Liberty Justice Center, a national public-interest law firm that fights to protect fundamental constitutional rights. Since filing the federal lawsuit, Liberty Justice Center, other nonprofit law firms, and state attorneys general have uncovered communications and documents proving collusion between Big Tech and Biden administration officials at every level. Hart’s attorneys have submitted this evidence gained through public records requests with an amended complaint.
“New evidence confirms what we have long known: our federal government is working directly with Big Tech to silence Americans,” said Daniel Suhr, managing attorney at the Liberty Justice Center. “The government is directing private companies to violate Americans’ free speech rights. Censorship may have started with what they call ‘COVID misinformation,’ but it opens the door for any administration to define any message they don’t like as ‘misinformation.’ This is unconscionable and illegal.”
Justin Hart is the author of Gone Viral: How COVID Drove the World Insane and founder of RationalGround.com. Over the last two years, his Facebook and Twitter accounts were suspended multiple times for sharing data and scientific research about COVID. At the time Hart’s statements and valid public health messages were censored, the facts were deemed “misinformation” by the Biden administration and Big Tech. However, much of what he shared about the detrimental effects of masking, lockdowns, and school closures are now widely accepted as true.
“The depth of the collusion between Big Government and Big Tech is alarming and reveals a sinister plot to undermine the rights of Americans by fully removing certain ideas and people from public discourse,” said Justin Hart, author and plaintiff. “The government does not have a monopoly on truth. By directing and pressuring social media companies to censor Americans, our government is silencing critical discussions and, most importantly, violating our most sacred rights.”
New evidence proves that prior to Justin Hart’s deplatforming in July 2021, the federal government and Big Tech coordinated regularly:
- Facebook offered the federal government, and it accepted, $15 million in free COVID-19 public health advertising to promote its public health message on the Internet.
- The Centers for Disease Control and Prevention (CDC) and Biden administration officials coordinated its COVID “misinformation” response with Facebook and Twitter by holding regular “be-on-the-lookout” meetings and by providing examples of the types of messages that contradicted the government’s message and it wanted censored.
- Facebook used proprietary tools to monitor social media posts that contradicted the federal government’s COVID-19 narrative and reported such posts to the federal government.
- Facebook adjusted its policies and algorithms to align with misinformation policies set by the federal government.
The lawsuit, Hart v. Facebook, was filed Aug. 31, 2021, and is being heard in the U.S. District Court for the Northern District of California, San Francisco Division. Case filings are available here.
The crushing of dissent throughout the covid era
Orwellian parallels worsen by the week
Health Advisory & Recovery Team | October 8, 2022
The recent actions of the financial technology company, PayPal, to close the accounts of subscribers expressing political opinions of which they disapprove, represents the latest example of censorship within so-called liberal democracies. Their strategic decisions to block the online monetary activities of the Free Speech Union, the Daily Sceptic website and the Us For Them campaign group – although later reversed – signal the willingness of powerful global big-tech companies to collude with governments in the crushing of activities that challenge the dominant narratives. But no one should be surprised; we have all been manipulated by top-down censorship and state propaganda for many years, a dystopian process that accelerated during the covid era.
Since the emergence of the novel coronavirus in early 2020, there has been widespread censorship of views that do not support the two mantras of covid-19 orthodoxy: namely that, ‘Lockdowns and other restrictions were appropriate responses’ and ‘The mRNA vaccines are safe and effective’. Indeed, the unprecedented and non-evidenced covid restrictions could not have been so successfully imposed without propaganda in all its forms. Contrary to popular opinion, techniques of manipulation do not only characterise recognised totalitarian regimes, but are now endemic within contemporary liberal democracies. And three, overlapping, forms of non-consensual persuasion have been widely deployed throughout the covid era to control the narrative and subsequent behaviour of citizens:
1. Control through emotional manipulation
The covert influencing of people’s emotions via use of behavioural-science ‘nudges’ has been well documented. Based on the advice of state-employed psychological experts, the covid-19 communication strategy has relied heavily on evoking uncomfortable feelings in the populace as a way of inducing them to ‘do the right thing’, where what is ‘right’ is solely determined by government-appointed officials. In particular, the manipulation of fear, shame and scapegoating – or ‘affect’, ‘ego’ and ‘norms’, to use the euphemisms of behavioural science – has been conducted for this purpose via the broadcasting of selective statistics, alarming images and emotional messaging. Furthermore, the decision to impose mask mandates was most likely informed by the knowledge that face coverings enhance the power of each of these three nudges, thereby increasing people’s compliance with government diktats.
Despite escalating concerns about the ethical basis of the state’s deployment of behavioural science, there has been a stark reluctance of anyone in authority to accept responsibility for this form of manipulation. The British Psychological Society (the formal guardians of ethical application of psychological interventions) is of the view that covertly inflicting emotional distress on people so as to promote compliance with covid restrictions and the vaccine rollout is acceptable as it is encouraging ‘social responsibility’, thereby colluding – along with other professional bodies – with the state’s mission to silence dissent and eliminate contrary behaviour. Meanwhile the Government show a reluctance to explore the ethics underpinning their deployment of nudges as evidenced by their ‘Public Administration and Public Affairs Committee’ ignoring a request for an independent inquiry and the omission of any mention of behavioural science in the draft terms of reference for the Inquiry into the covid-19 pandemic.
2. Control through modulating the flow of information
A second way of controlling dissent – used at unprecedentedly high levels throughout the covid event – has been via the regulation of information flow within our TV, radio, newspaper and social media outlets. Ease of access to facts, data and opinion (including that of scientific experts) has been mainly determined by the degree to which the information corresponds with the dominant narratives: write or speak words supportive of lockdowns, masking and vaccination and they will typically receive preferential treatment within the media’s editorial processes, gaining prominence and ease of access; in contrast, say or print something contrarian and it will most likely be submerged in the quagmire of daily media output.
The seeds of this system of selective information flow had been sown prior to 2020 with the formation of the ‘Trusted News Initiative’ (a coalition of mainstream media, publishers and big-tech companies) aspiring to ‘create a global alliance of integrity in news’ by countering ‘misinformation’ and ‘bias’. Furthermore, at the start of the pandemic, Ofcom – the UK’s communications regulator – instructed broadcasters not to cover anything that went against the Government’s narrative. This censorial alliance ensured that voices expressing dissent about covid restrictions and the vaccine rollout were disadvantaged, displaced to the inaccessible fringes of media output.
In the UK, there has even been military involvement in the form of the 77th Brigade with their explicit mission to create and spread material ‘in support of designated tasks’ while also ‘supporting counter-adversarial information activity’. Internationally, the WHO has effectively modulated the flow of information via the use of fact-checking organisations and collaborations with Facebook, Twitter, WhatsApp and YouTube, so as to guarantee that ‘science-based health messages from official sources’ (aka the dominant narrative) appear first when one searches for covid information.
Specific examples of the impact of this – seemingly global – operation to control information flow are numerous. They include: Professor Gupta (an epidemiological expert) being instructed not to mention the Great Barrington Declaration prior to appearing on a BBC discussion programme about lockdowns; academic journals blocking the peer-reviewed covid research of Dr Peter McCullough and the suppression of trial findings that had concluded that Ivermectin was an effective treatment; the removal of Dr Robert Malone (the inventor of mRNA technology) from Twitter; and the removal of MPs Sir Christopher Chope and David Davies from YouTube for, respectively, raising concerns about vaccine damage and vaccine effectiveness.
One fundamental consequence of this selective regulation of information was that our Western media – a supposed pillar of democracy – failed us all in their refusal to scrutinise and evaluate the actions of public officials.
3. Control through erasing dissenting voices
Presumably based on the assumption that eliminating people before dissent is expressed is a more effective censorial method than controlling their information output, throughout the covid era there appears to have been a systematic state-driven attempt to discredit or cancel those brave individuals expressing views that are inconsistent with the dominant restrict-and-jab narrative.
Since March 2020, anyone who has expressed a contrarian covid opinion in a public space will likely have attracted criticism involving accusations of being ‘right wing’, fascist or a ‘conspiracy theorist’. Efforts by powerful players to destroy reputations and livelihoods through smearing and character assassination have been commonplace. Arguably the most high-profile example of this egregious practice is in regards to the targeting of the main authors of the Great Barrington Declaration, a multi-signatory document arguing for an alternative to the blanket lockdowns. In leaked emails between Anthony Fauci (Chief Medical Advisor to the US president) and Francis Collins (the Director of the US National Institute of Health), these powerful state officials refer to the illustrious authors of the document as ‘fringe epidemiologists’ while describing the need for a ‘quick and devastating public takedown’ of their arguments. Furthermore, the extremely popular US podcaster, Joe Rogan, was smeared as a transphobe and racist in the aftermath of him giving a platform to experts expressing views at odds with the dominant covid narrative.
A threat of imminent loss of earnings – actual or implied – is another tactic that has been commonly deployed to cancel those criticising the approach of Western governments to pandemic management. Many academics have suffered in this way, including Canadian professor Julie Ponesse who lost her job after she challenged the vaccine mandates. Of course, such a draconian sanction serves as a warning to many other university scholars who might also be considering expressing dissent.
The recent actions of PayPal suggest that our medico-technocratic powerhouses are not satisfied with inflicting emotional distress, censorship and character assassination on the Western population, but now seek to control how we spend our money. Manipulation by means of regulating access to our finances may be the new front in the war on freedom of verbal and behavioural expression. It raises the spectre of the imposition of a totalitarian social credit system, mediated via a Central Bank Digital Currency, a world where unelected global bureaucrats determine our monthly spend based on the degree to which our behaviour conforms to their version of what constitutes the ‘greater good’.
In the words of Piers Robinson (an expert on global propaganda), ‘That the censorship, smearing and coercion … has come to be tolerated is a clear indicator of how far our democracies have slipped into an authoritarian abyss’. And the imminent Online Harms Bill, with its ‘legal but harmful’ category, may further restrict our basic human right to freedom of expression. But there is still hope. As more and more people become aware of the associated collateral damage, the dominant narratives on the benefits of lockdowns, school closures, masks and ‘safe-and-effective’ covid vaccines are beginning to crumble. As awareness of ubiquitous state-funded manipulation and censorship grows, increasing numbers of citizens are turning to independent sources of expert information – such as HART and PANDA – for reliable covid updates. The basic human right of freedom of expression within Western democracies must be protected; once lost, it is unlikely to be restored within our lifetimes.
US scientists create new lethal Covid variant
Samizdat | October 17, 2022
Scientists at Boston University claim to have created a new variant of Covid-19 with an 80% mortality rate, by combining the highly-transmissible Omicron variant of the coronavirus with the original Wuhan strain. The research, which echoes experiments thought to have created the virus in the first place, has caused outrage.
In a research paper published last week, the scientists explained that they isolated the spike protein of the Omicron variant and combined it with the “backbone” of the original strain that circulated in early 2020. This created a virus that “robustly escapes vaccine-induced… immunity” and inflicts “serious disease” on laboratory mice, 80% of whom died during testing, the paper stated.

While the team admitted that their mutant strain would likely be less deadly in humans than mice, they found that it produced five times as many virus particles in lab-grown human lung cells when compared to the Omicron variant.
The paper has yet to be peer reviewed.
 News of the research caused outrage online, as it is widely believed that similar ‘gain-of-function’ research – a term describing the alteration of a pathogen to enhance its potency – at the Wuhan Institute of Virology in China led to the global Covid-19 pandemic. The US funded such research at the Wuhan Institute, although it is still unclear whether the specific coronavirus that caused the pandemic originated in the lab.
“This should be totally forbidden, it’s playing with fire,” former Israel Institute for Biological Research head Shmuel Shapira said of the Boston experiments. “How many times did virologists say they were not making chimeric SARS viruses more deadly? How many???” reporter Paul Thaker tweeted.
The Boston team aren’t the only scientists returning to potentially dangerous research in the aftermath of the pandemic. EcoHealth Alliance, the private company responsible for much of the Wuhan Institute’s pre-2020 gain-of-function research, was awarded a $650,000 grant by the US last month to study “the potential for future bat coronavirus emergence in Myanmar, Laos, and Vietnam.”
Those Demonising the Unvaccinated Need to Look in the Mirror

BY NICK RENDELL | THE DAILY SCEPTIC | OCTOBER 17, 2022
It’s been known since the outbreak of Covid that obesity leads to higher rates of hospitalisations and deaths. Despite this, very few resources were deployed to encourage healthier eating and lifestyles. This article argues that this was a disastrous decision for the long term health of the nation and the short to medium term capacity of the NHS.
Boris Johnson (BMI 34; healthy is under 25) in his New Year message broadcast on December 31st 2020 said: “Get a vaccine, it’s far easier than losing weight” (see video from two minutes in). Well, the people of the U.K. took him at his word: we’ve had 30 months to galvanise the population into losing weight and getting fitter, 30 months entirely squandered.
First, let’s just look at how effective spending £25bn injecting 150 million vaccines into the U.K. population has been. As the NHS continues to struggle to meet demand, perhaps Covid hospital admissions are the key metric. For the vaccine programme to have been a success we should expect the unvaccinated to be disproportionately admitted to hospital. They’re not. These figures come from the latest UKHSA Weekly Vaccine Surveillance Report; table 12a on page 49 gives us the figures for hospital admissions between March 21st and August 28th of this year. In each age cohort the unvaccinated are proportionately less likely to be hospitalised than the vaccinated. As an example, in the 50-64 year-olds, 129 of the 1,342 admissions were unvaccinated, that’s 9.6%. Yet, about 14% of that age group are unvaccinated. If the unvaccinated were more likely to be hospitalised we would expect the figures to be reversed, to see a higher proportion of the unvaccinated hospitalised than the total proportion of people unvaccinated.

Demonstrably, despite the Government’s claims that vaccines have reduced hospital admissions, this can’t be true. Something has reduced hospital admissions from the peaks in the first two waves, but if the rate of admission is much the same for the vaccinated and the unvaccinated I struggle to see how vaccines can explain it. Surely, far more likely are the twin benefits of immunity brought about by prior infection and a less virulent variant. Figure 2 shows the peaks and troughs of Covid hospital admissions since the start of the pandemic.

Also worth noting, the seven-day average number of hospital admissions for Covid is currently 132% higher than it was on October 7th 2020, before anyone anywhere had been vaccinated, and 86% higher than on October 7th 2021 when most people had been vaccinated – though it should be noted that over half of Covid hospital admissions since Omicron have been primarily being treated for something else.
Despite my deep scepticism of the efficacy of the mRNA vaccines and the real world evidence presented above, to avoid any accusations of dogmatism I’m going to indulge the vaccine zealots’ figures for vaccine effectiveness. Again, with the data taken from the Government’s week 40 vaccine surveillance report, figure 3 suggests that the UKHSA thinks that the best protection a fourth dose of vaccine can offer is about 50%, soon falling to 20%.

Now let’s compare that vaccine efficacy with the impact of obesity on severe Covid outcomes by turning to a fascinating study published in June in the Lancet that looked at how BMI affects Covid outcomes. What made this latest study particularly interesting was that it used real, though anonymised, data from about 20% of the U.K. population. The data, from QResearch had over 12 million patient records but about 3 million couldn’t be used, mainly because BMI data were missing, but that still left 9,171,524 patient records to be analysed. So, again, we’re looking at real-world evidence whereas the UKHSA vaccine efficacy rates are estimates.
The data related to the period from December 2020 to November 2021. This was the period covering the initial rollout through to booster doses in older people. Part of the summary table is reproduced in Figure 4. I’ve highlighted in red hospital admissions.

There were 3,509,213 people of a healthy weight in the study, of whom 8,315 were hospitalised with Covid, that’s 0.23%. Of the 3,062,925 overweight people, 10,653 or 0.35% were hospitalised. That means the overweight were 50% more likely to end up in hospital than those classed as healthy weight.
Of the 2,278,649 obese people 13,044 or 0.57% were hospitalised. This means they were 150% more likely require hospital treatment than the healthy weight group.
Let’s now compare the relative risk of being vaccinated with that of being obese. The obese get hospitalised at a rate 150% greater than those of a healthy weight while the best you can hope for from your fourth vaccine is a 50% reduction in the likelihood of being admitted to hospital, dropping to 20% after about four months. And that’s another key point, keep the weight off and that risk reduction remains in contrast to any benefit from vaccination that soon wanes to nothing (assuming it ever existed in the first place).
But of course, it’s not just Covid where the overweight and obese have worse outcomes. The Lancet study goes on to list some of the other health outcomes for other conditions. The obese are almost six times more likely to have type 2 diabetes, more than twice as likely to suffer cardiovascular disease and over three times more likely to suffer hypertension.

Lose weight and many of these rates of disease would fall. The burden on the NHS would be reduced, the people losing weight, in most cases, would feel better and no doubt their mental health would, in the round, be improved.
I was interested in a piece by Michael P. Senger in the Daily Sceptic on October 14th 2022 highlighting the demonisation of the unvaccinated. I really don’t recall anyone in the mainstream media or in Government objecting to this vilification at the time yet it was evident from the Week 35 2021 Vaccine Surveillance Report that in each of the age groups from 40 to 80 the double dosed were testing positive for the virus at a higher rate than the unvaccinated (see an article I wrote back in June that goes into some detail on this point), so it was evident that the unvaccinated represented less of a threat than the vaccinated. Likewise, it’s been known since the Covid outbreak on the Diamond Princess back in February 2020 that obesity was a risk factor. However, can you imagine the furore that would result if people were to suggest that the obese were denied hospital treatment?
It’s not the unvaccinated who are clogging up the NHS, it’s disproportionately the obese and overweight – some of whom have been particularly vocal in vilifying the unvaccinated or in failing to promote healthier lifestyles:
- Andrew Neil (estimated BMI 32) argued for restrictions on the freedoms of the unvaccinated.
- Piers Morgan (estimated BMI 29) argued for the unvaccinated to be denied NHS care if they caught Covid.
- Boris Johnson (estimated BMI 34) attempted to bring in vaccine passports.
- Michael Gove (estimated BMI 28) was a keen advocate of vaccine passports.
- Therese Coffey (estimated BMI 30), the new Health Minister appears to be far keener on promoting vaccines rather than healthy lifestyles.
The Government spent about £12bn vaccinating the under 50s, largely a pointless exercise. As an advocate of lower taxes and a smaller state I don’t argue that this money should have been spent on schemes to subsidise healthier living. Such schemes invariably fail. What’s more, I would object just as fiercely to coercing people to lose weight as I do to coercing people to get vaccinated. However, I would like to see them campaign to raise people’s awareness of the risks associated with a high BMI. In rough terms, there appears to be about a 10% Covid hospitalisation risk reduction for each BMI point reduction and associated risk reductions for various cancers, diabetes, heart conditions, muscular/skeletal problems and mental health.
Body positivity is all well and good but being overweight is neither risk or cost free. If Andrew Neil, Piers Morgan, Boris Johnson et al. want target a group to be censorious of perhaps they should follow Jordan Peterson’s advice and go tidy their own room first.
COVID-19 Much Less Deadly Than Previously Thought, Major Study Finds

BY WILL JONES | THE DAILY SCEPTIC | OCTOBER 17, 2022
COVID-19 is much less deadly in the non-elderly population than previously thought, a major new study of antibody prevalence surveys has concluded.
The study was led by Dr. John Ioannidis, Professor of Medicine and Epidemiology at Stanford University, who famously sounded an early warning on March 17th 2020 with a widely-read article in Stat News, presciently arguing that “we are making decisions without reliable data” and “with lockdowns of months, if not years, life largely stops, short-term and long-term consequences are entirely unknown, and billions, not just millions, of lives may be eventually at stake”.
In the new study, which is currently undergoing peer-review, Prof. Ioannidis and colleagues found that across 31 national seroprevalence studies in the pre-vaccination era, the average (median) infection fatality rate of COVID-19 was estimated to be just 0.035% for people aged 0-59 years people and 0.095% for those aged 0-69 years. A further breakdown by age group found that the average IFR was 0.0003% at 0-19 years, 0.003% at 20-29 years, 0.011% at 30-39 years, 0.035% at 40-49 years, 0.129% at 50-59 years, and 0.501% at 60-69 years.
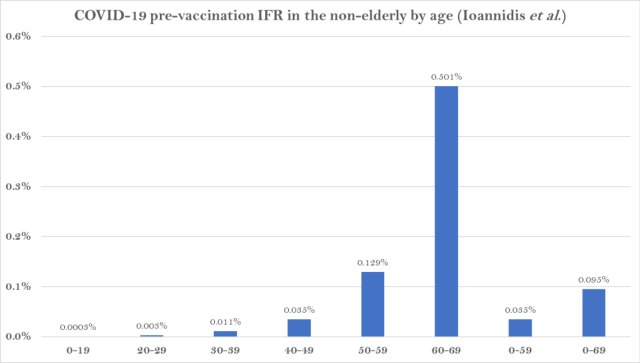
The study states that it shows a “much lower pre-vaccination IFR in non-elderly populations than previously suggested”.
A breakdown by country reveals the wide range of IFR values across different populations.
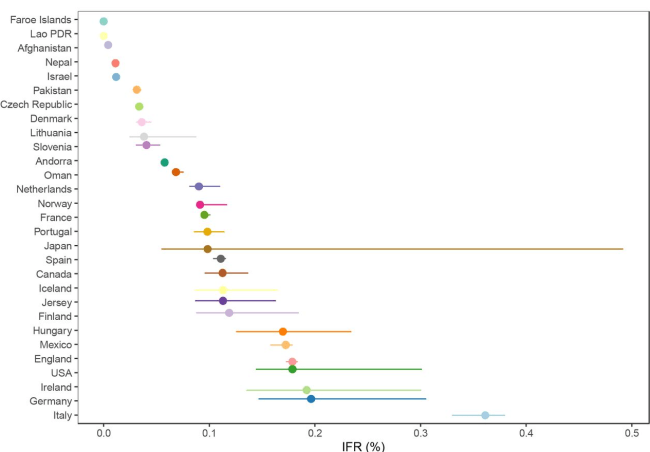
The significantly higher values for the top seven suggest some of the difference may be an artefact of, for example, the way Covid deaths are counted, particularly where excess death levels are similar. Note also that the antibody studies date from various points during the first year of the pandemic, most of them prior to the large winter wave of 2020-21, when levels of spread and numbers of deaths were more varied than later in the pandemic as subsequent waves caused countries to converge.
The reason some countries had much lower values and some much higher is not completely clear. The authors suggest that “much of the diversity in IFR across countries is explained by differences in age structure”, as per the plot below.
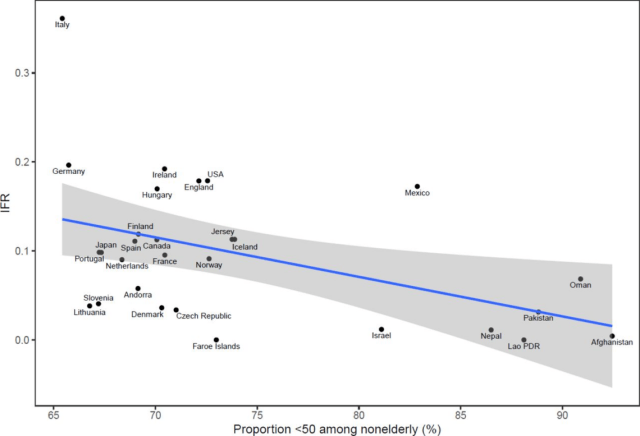
However, the age breakdown by country suggests that the IFR differed for each age group in each country, casting doubt on that suggestion. (In the chart below, note the logarithmic scale, and ignore the zig-zag lines, which are due to small countries having low numbers of deaths.)
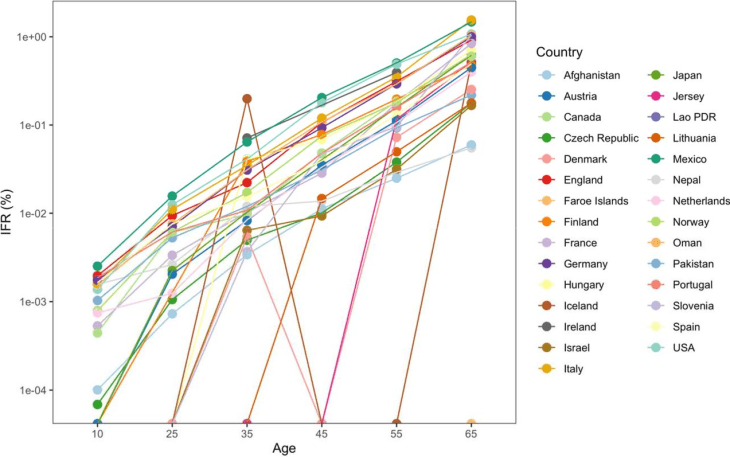
Why are countries seeing differing IFRs even for the same age groups? The authors suggest a number of explanations, including data artefacts (e.g. if the number of deaths or seroprevalence are not accurately measured), presence and severity of comorbidities (for example, obesity affects 42% of the U.S. population, but the proportion of obese adults is only 2% in Vietnam, 4% in India and under 10% in most African countries, though it affects almost 40% of South African women), the presence of frail individuals in nursing homes and differences in management, healthcare, overall societal support and levels of drug problems.
Prof. Ioannidis has previously published a number of papers estimating COVID-19’s IFR using seroprevalence surveys. He and his team conclude that their new estimates provide a baseline from which to assess further IFR declines following the widespread use of vaccination, prior infections and evolution of new variants such as Omicron.
Corona is a Flat Circle
For the third autumn in a row, the German press screeches about overwhelmed hospitals, and there’s no reason to think they’ll ever stop.
eugyppius | October 15, 2022
It’s virus season, and the headlines are already here: Many New Corona Infections: Hospitals Demand Indoor Mask Mandate — Lauterbach Already Hopes for Corona Restrictions — High Covid Incidences: Medical Association Wants Compulsory FFP2 Masks Indoors — Corona: Baden-Württemberg Health Minister Considers Mask Mandate Possible. I could add a dozen more, but you get the idea. It’s the same reheated pablum from last year. Hospital staff have their backs against the wall; a new tide of Corona patients threatens to overwhelm their meagre resources; the Apocalypse threatens if we don’t immediately return to indoor plastic face coverings.
If you look at hospitalisations, though, you’ll have a hard time finding any crisis at all. Here, for example, are hospitalisations for severe acute respiratory infections since 2017, as published last week by the Robert Koch Institut:
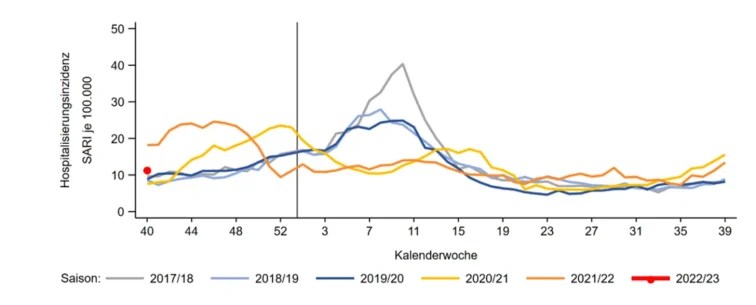
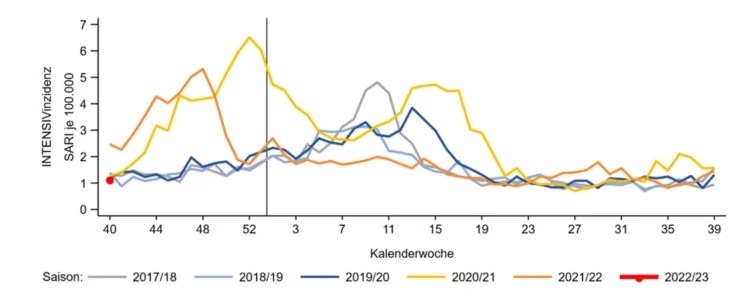
The red dot is where we are right now. Admissions are totally in line with the pre-pandemic era. The ICU admissions tell exactly the same story:
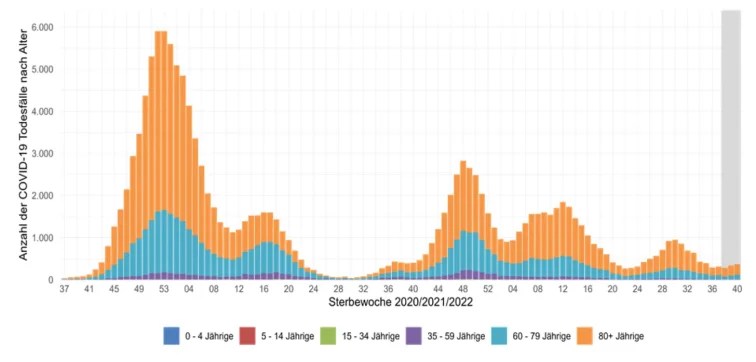
Nor is anybody really dying at the moment:
To the extent that there is any crisis at all here, it’s of our own making. Hospital patients with Corona diagnoses have to be treated according to strict isolation protocols, in special wards. These rituals are staff-intensive, and they effectively reduce across-the-board hospital capacity. It’s the same as our quarantine laws, which induce worker shortages by forcing millions of otherwise healthy Germans into isolation whenever they test positive. We could declare a rhinovirus pandemic tomorrow and suffer all the same problems from the common cold, and by the same token we could end all of this ourselves in an instant, by abolishing our foolishness and choosing to ignore SARS-2. Instead, we insist that this virus is dangerous and through our own behaviour we make it so.
The most onerous part of all this, is the inability of the German press to find a new narrative, ask new questions, or to change their reporting in any way at all — despite the totally different behaviour of Omicron and the near-universal levels of immune exposure to SARS-2. I know some of you complain that I repeat the same themes and arguments overmuch, but Germany has descended into some kind of purgatorial alternate reality, where it’s always March 2020, and our hospitals are always on the verge of melting down, and we never have enough information, so we just have to try masking and social distancing and hope for the best. They’re wrong about everything and they just keep telling the same lies over and over.
CA DOCTORS FIGHT BACK AGAINST ‘MEDICAL MISINFORMATION’ BILL
The Highwire with Del Bigtree | October 14, 2022
Dr. Jeff Barke, a founding member of America’s Frontline Doctors, joins Del to discuss California’s new law enacted with the passage of AB2098, which effectively makes it illegal for doctors to disagree with politicians.
Masks For Thee But Not For Me

eugyppius – October 13, 2022
Pictured is the Federal President of Germany, Frank-Walter Steinmeier, violating the Infection Protection Act, which requires masks in all local and long-distance trains. He pleads that he only took his mask off for a few seconds for the purposes of a short video message and some publicity photographs. Alas, the law provides for no such exception, and why should it? The official position of the German government is that unmasked people are a danger to themselves and others, particularly when they are on trains.
Now this is merely the latest in a string of similar incidents, including these barefaced mask mandate-happy Greens at Oktoberfest and German Chancellor Olaf Scholz’s unmasked government flight to Canada. It’s long become clear that nobody—not even the politicians most in favour of mandates—believes that masking is worth the trouble. And when you think about it, that’s depressing indeed, because how can we ever get rid of these rules if they are this discredited, and yet they persist?
Featured Video

Macgregor: We Haven’t Seen the Worst of the Iran War Yet
or go to
Aletho News Archives – Video-Images
From the Archives
15 Saudi ‘hijackers’ were CIA agents working for US: Scholar
Press TV – April 13, 2016
Fifteen of the 9/11 “hijackers” from Saudi Arabia were CIA agents working for the United States government, which was seeking to destroy the Middle East for Israel and to double the American military budget, says Dr. Kevin Barrett, an American academic who has been studying the events of 9/11 since late 2003…. continue
Blog Roll
 Aletho News
- Breast Cancer: Before You Consent
- Iran’s Plan to Shut Down AI in the Persian Gulf
- Israel seeks ‘compensation’ from Washington over Saudi F-35 sale
- Saudi crown prince seeks dialogue with Ansarullah after Yemeni blows: Report
- Damascus rejects Saudi request for Syrian fighters to counter Yemen: Report
- South Korea says will not send troops to join terrorist US war on Iran
- Russia Just Struck the Eyes of NATO’s War Machine in Ukraine
- Russia summons UK charge d’affaires over Kiev drone support
- NATO member warns bloc seeking pretext for war with Russia
- Macgregor: We Haven’t Seen the Worst of the Iran War Yet
- If Americans Knew
- Debunking The Claim That Macklemore Has A “History Of Antisemitism”
- CPJ demands release of arrested Palestinian-US journalist near Bethlehem
- Robert Kraft: The Billionaire Friend of Netanyahu Pulling The Strings Behind the Macklemore/Ed Sheeran Blow Up
- Columbia Administered Fund Gives Big Money to Pro-Israel Groups
- Deportation Case of Palestinian Activist Salah Sarsour Tests First Amendment
- ‘We Will Not Forget’: Palestinians Mark 44 Years since Sabra and Shatila
- Why do we let Zionists decide what we can and can’t say?
- US welcomes Israeli, Iranian delegations to UN, but not Palestinians – Daily Update
- Biden’s Genocide Accomplices Targeted by New Accountability Campaign
- AIPAC’s Network Has Already Spent $67.2 Million to Shape the Midterm Elections
- No Tricks Zone
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
- Fear Of Debate: Alarmist German Climate Scientist Calls On Mainstream Media To Discredit Skeptic Voices
- End-Of-August Arctic Sea Ice Extent Hasn’t Fallen In 20 Years, Official Data Show!
 Aletho News
