A recent New York Times/Siena College poll showing 64 percent of Democrats preferring a new standard-bearer in 2024 rocked the White House and the political landscape, but it should not have come as a big surprise. After all, President Joe Biden continues to fall short of the promises that drew many Democrats, including myself, to his candidacy in 2020: his pledge for a new strategy combatting Covid-19.
Consider the Food and Drug Administration’s recent decision allowing pharmacists to play doctor and prescribe Pfizer’s anti-viral treatment Paxlovid, which Biden himself, having contracted Covid-19, is now taking. The agency claims this is meant to increase access to the medicine, which must be taken as soon as symptoms arise. But the drug’s fact sheet is a tangled web of restrictions that will make it impractical for most pharmacies to take the risk. Why is the FDA encouraging this?
The answer is plain to anyone who has been following the plight of independent doctors during the pandemic. Our public health agencies — heavily influenced by the pharmaceutical industry and beholden to Biden’s “vaccine first” approach — are committed to diminishing the medical profession and centralizing authority with bureaucrats in Washington, D.C. They have prosecuted a relentless campaign to reduce physicians to cogs in a health care system that is aggressively transforming all medical professionals from providers to prescribers.
The problems with Paxlovid are no secret. FDA granted Pfizer emergency use authorization for the drug after a single trial with questionable results. The medicine has many contraindications, meaning it can’t be taken by someone who simultaneously would be taking certain anti-depressants, anti-seizure, anti-psychotic, cholesterol, or blood pressure medications. Furthermore, many Americans cannot take Paxlovid, given that nearly half of adults have cardiovascular disease.
The risks are plain to see in FDA’s guidance, which recommends referring the patient to a doctor if “sufficient information is not available to assess renal and hepatic function” or “potential drug interactions.” Numerous contraindications are listed, and caution is advised throughout. The burden is on the patient to furnish medical records to prove that he or she doesn’t have any significant kidney or liver disease, drug sensitivities, or other medications that could cause serious adverse events.
Nevertheless, pharmacies have spent months and millions of dollars lobbying for the right to play doctor and prescribe Paxlovid. The economic motives of such a move are clearly in their favor, as, unlike doctors, they profit directly from dispensing drugs. It’s no surprise the National Community Pharmacists Association celebrated the win as a “course correction.” Its CEO said, “Pharmacists are the drug therapy and drug interaction experts. This move opening up their ability to assess the need for and prescribe Paxlovid will improve patients’ timely access to treatments that will help keep them out of the hospital and alive.”
This may be as absurd a statement by a health organization as any I have heard in the pandemic. No pharmacist could ever safely dispense a novel medicine with an unprecedented amount of drug interactions without in-depth knowledge of the severity of the patient’s medical problems or the critical necessity of each of their other medicines. This fact was not lost on the American Medical Association, which temporarily snapped out of its woke-activist-induced coma to offer qualified criticism.
“While the majority of COVID-19 positive patients will benefit from Paxlovid, it is not for everyone, and prescribing it requires knowledge of a patient’s medical history, as well as clinical monitoring for side effects and follow-up care to determine whether a patient is improving—requirements far beyond a pharmacist’s scope and training,” American Medical Association President Jack Resneck Jr. said in a statement.
The tell is right there, though. The AMA is fine with Paxlovid as long as physicians are doing the prescribing. Ceding authority is the problem, which is why the agency previously called the idea “dangerous in practice and precedent” when the Biden administration first proposed it in the Test to Treat initiative.
Covid cases and deaths are down massively from their last peak in January. Most states have lifted restrictions and returned to normal. Yet just days after the FDA made this announcement, the Biden administration again extended the Covid public health emergency — because the president can’t lose the specter of Covid as a political tool.
Vaccination rates have leveled off, and Paxlovid sales bottomed out in April due to a combination of supply problems and sinking demand. Pfizer pushed expectations for the drug sky high, and now it needs to deliver on that promise. The FDA’s move shows how deftly the company has used the pandemic to influence government and public health agencies to serve its shareholders.
The pharmaceutical industry, led by Pfizer and in league with the Biden administration, is waging war against independent doctors who refuse to cede control over patient well-being — and they are winning. If there is any hope for change, it will come in November.
The red wave forming off our political shores is a culmination of many factors. Inflation and gas prices are hitting all-time highs, and just 13 percent of Americans believe the country is heading in the right direction. But relying on scare tactics to distract voters back to Biden is a strategy not supported by medical conditions on the ground.
Let’s hope whoever rides into Washington on that red wave will take on this fight with integrity.
Pierre Kory, MD, is president and chief medical officer of the Front-Line COVID-19 Critical Care Alliance.
In 2021, HART published a review of the evidence for asymptomatic transmission.
The concept of asymptomatic transmission formed the foundation for the belief that lockdown was necessary and might work and for mask wearing and amplified the atmosphere of fear with the idea that anyone could be a threat.
Key points from that article include the fact that:
Presymptomatic people account for only 7% of spread in an outbreak
People who are immune and healthy can test positive but, because of how testing has been calibrated, this is not evidence of either disease or infectiousness
The medical literature contained multiple meta analyses where evidence from the same handful of poorly designed studies had been recycled to create the illusion of a body of evidence
The only three instances of people becoming ill having allegedly been infected by someone who never developed symptoms were two cases of a “mild cough for one day” and one baby with a runny nose.
At the time it was possible to conclude that the global evidence of transmission from people who never had symptoms amounted to only three people with very mild symptoms, calling into question the idea that there should be any concern around the apparently healthy.
In the last year there have been two reports which have increased knowledge in this area. The first was a study of thoroughly tested marine recruits and the second was a carefully reported outbreak in Japan. Both studies failed to provide answers to critical questions – the key question being whether someone who tested positive after contact with a never symptomatic individual, ever developed symptoms themselves. This question has been repeatedly omitted from such studies of asymptomatic spread.
Marine study
Although this study got a lot of traction, it is ultimately the story of five young people with mild cold symptoms and the ubiquitous nature of viruses. Before the advent of molecular biology this would hardly be newsworthy! A total of 1,847 trainee marines were included in the study. The thrust of the study was in tracking different genomic sequences detected from swabbing people within platoons. The results were not clear at all about who had symptoms. In fact the failure to report on symptoms is a glaring weakness in the claim that they are diagnosing anything meaningful.
The marines were made to isolate for two weeks, before arriving at the training camp and then quarantined for a further two weeks (but in shared rooms) with constant mask wearing, social distancing, hand washing, daily temperature and symptom monitoring, banning of electronic devices, and repeated testing. They claim they diagnosed 46 asymptomatic positives. The PCR results were strong positives in the few marines with symptoms (a median Ct value of 22-23) but were weak in the asymptomatic (a median Ct value of 25-27 meaning there was 100 times less viral RNA present). A third of them had too little material present to carry out successful sequencing at all. For those that did, there was a pattern of clustering of genome sequences within platoons. Unsurprisingly, if there was virus in the air shared by the platoon then it would be detectable in the respiratory tracts of those people breathing that air.
The paper never reports on whether there was any instance of a person sharing a room with an asymptomatic positive person and becoming symptomatic. As a paper which set out to investigate the problem of asymptomatic positives, the failure to mention symptoms suggests either that spread with resulting symptoms did not happen or that the scientists involved were incompentent.
A paper demonstrating that asymptomatic people may be contaminated with enough virus that others in their platoon test positive, asymptomatically is of no clinical interest. If no-one developed symptoms due to exposure to someone who was asymptomatic then there was no meaningful asymptomatic spread. Every morning the marines had temperature checks and symptom checks and yet none of the symptomatic positive marines were detected this way. Nevertheless the claim is made that a total of five of these young people did develop symptoms during the week before a positive test result.
Japanese study
The Japanese study reported on an outbreak in Japan in January 2020. The outbreak began in Tokyo at a party attended by someone from Wuhan showed 36 people who tested positive over a period of 48 days. 25 of the supposedly infected did not spread it to anyone. Despite this being the entirety of covid in Japan at the time they failed to trace one link in the chain who was the source of a small outbreak in a remote part of Kanagawa, a coastal town south of Tokyo. The authors assume that there must have been a person from the Tokyo outbreak who was responsible for this infection as they seem unable to think beyond person to person spread as the only possible mechanism of spread.
The article makes a big point of the fact that a woman in her 80s died. The woman in question had pneumonia and had been ill from January before dying on 13th February. The diagnosis was made post mortem and the ministry of health tried to impress upon people that it was not clear that the virus had been the cause of her death.
Why is there still confusion on this issue?
The evidence that supports the belief in asymptomatic transmission appears to come from a combination of two factors:
Positive test results in the absence of symptoms (without evidence of transmission of disease)
The fact people become infected without a traceable source
The former is explainable through poor testing and a failure to acknowledge immunity. PCR testing has been set up to detect 3 or 4 virus particles per sample where 5,000 particles would be needed to indicate someone with infectious potential. Detecting virus in the air in someone’s respiratory tract is of no consequence if they have immunity and will never become an infection risk or develop symptoms themselves. Even where relatively large amounts of virus have been detected on testing, in the absence of evidence of transmission that results in a person with more than fleeting mild symptoms, this is also of no consequence.
The fact people become infected when there is no discernable source can be attributed to long distant aerosol transmission. Despite WHO officially acknowledging this mode of transmission there seems to be continuing total denial of the implications of that from most authorities. In Australia, the Delta wave began with a tourist from Sri Lanka who was quarantined after landing. During his stay in quarantine a total of 44 genetically similar cases were identified in the Melbourne community. Rather than acknowledge airborne spread, James Merlino, the acting premier of Victoria, said transmission had occurred due to “being in the same place, at the same time, for mere moments.”
Conclusion
Our ability to test and detect minute, irrelevant quantities of virus has created an utterly distorted view of reality. A test which when positive does not demonstrate pre-symptomatic infection, infectiousness or disease is of no use to anyone and should be replaced. The myth that apparently healthy people are a potential threat to others needs to be quashed for good so that people can stop treating each other primarily as potential vectors of disease.
Top-ranking Biden administration officials — including Dr. Anthony Fauci — and five social media giants have 30 days to respond to subpoenas and discovery requests in a lawsuit alleging the government colluded with social media companies to suppress freedom of speech “under the guise of combatting misinformation.”
Missouri Attorney General Eric Schmitt and Louisiana Attorney General Jeff Landry on Wednesday served third-party subpoenas on Twitter, Meta (Facebook’s parent company), Youtube, Instagram and LinkedIn.
“In May, Missouri and Louisiana filed a landmark lawsuit against top-ranking Biden Administration officials for allegedly colluding with social media giants to suppress free speech on topics like COVID-19 and election security,” Schmitt said in Tuesday’s press release.
Schmitt added:
“Earlier this month, a federal court granted our motion for expedited discovery, allowing us to collect important documents from Biden Administration officials. Yesterday, we served discovery requests and today served third-party subpoenas to do exactly that.
“We will fight to get to the bottom of this alleged collusion and expose the suppression of freedom of speech by social media giants at the behest of top-ranking government officials.”
Schmitt announced in a July 12 statement that Terry Doughty, a judge in the U.S. District Court for the Western District of Louisiana, ruled in favor of a June 17 motion for expedited preliminary injunction-related discovery and set a timetable with specific deadlines for depositions.
According to Schmitt, government officials “both pressured and colluded with social media giants Meta, Twitter and Youtube to censor free speech in the name of combating so-called ‘disinformation’ and ‘misinformation,’ which led to the suppression and censorship of truthful information on several topics, including COVID-19.”
“The Court’s decision cleared the way for Missouri and Louisiana to gather discovery and documents from Biden Administration officials and social media companies,” Schmitt said in a press release on Tuesday.
“The order states, ‘The First Amendment obviously applies to the citizens of Missouri and Louisiana, so Missouri and Louisiana have the authority to assert those rights,’” he said.
Children’s Health Defense (CHD) President Mary Holland, who also serves as CHD general counsel, praised the ruling:
“CHD welcomes this groundbreaking ruling from Judge Doughty of the Western District of Louisiana to discover whether the Biden administration has violated the First Amendment through censorship.
“For two years, CHD and many other media outlets have not been able to comprehend the mechanisms whereby our major media platforms have ruthlessly censored, suppressed and distorted our information.
“Now, through the discovery process that the judge has allowed, we’ll find out how Meta, Instagram, Twitter and YouTube have been colluding with the federal government to curb so-called ‘disinformation’ and ‘misinformation.’ This is a new day.”
Fauci, CDC, White House press secretary and more must turn over documents
According to the press release, Fauci, chief medical advisor to President Biden and director of the NIAID, was asked to turn over any communications with social media platforms related to content modulation and/or misinformation, and to disclose all meetings with any social media platform related to the subject and to provide all communications with Mark Zuckerberg from Jan. 1, 2020, to the present.
Fauci also must turn over all communications with any social media platform related to the Great Barrington Declaration; the authors and original signers of the Great Barrington Declaration; Dr. Jay Bhattacharya; Martin Kulldorff, Ph.D.; Dr. Aaron Kheriaty, Sunetra Gupta, Ph.D.; Dr. Scott Atlas; Alex Berenson; Peter Daszak, Ph.D.; Shi Zhengli, Ph.D.; the Wuhan Institute of Virology; EcoHealth Alliance; and/or any member of the so-called “Disinformation Dozen,” including CHD chairman and chief legal counsel Robert F. Kennedy, Jr.
White House Press Secretary Karine Jean-Pierre is required to identify every officer, official, employee, staff member, personnel, contractor or any other person associated with the White House communications team who communicated or is communicating with any social media platform related to content modulation and/or misinformation — and to turn over those communications.
Jean-Pierre also must identify all persons who “engage[s] regularly with all social media platforms about steps that can be taken” to address misinformation on social media, which engagement “has continued, and … will continue,” as stated during an April 25 White House press briefing — and turn over all communications with any social media platform involved in such engagement.
Defendant Nina Jankowicz, who was tasked with heading up the Biden administration’s “Disinformation Governance Board” must provide all documents related to communications with social media platforms and content modulation and/or misinformation.
Jankowicz is required to identify the nature, purpose, participants, topics to be discussed and topics actually discussed at the meeting between DHS personnel and Twitter executives Nick Pickles and Yoel Roth scheduled on or around April 28.
The CDC is required to provide the names of every officer, official, employee, staff member, personnel, contractor or agent of CDC or any other federal official or agency who communicated or is communicating with any social media platform regarding content modulation and/or misinformation.
The CDC must disclose communications with any social media platform related to content modulation or misinformation, any meetings that took place with social media platforms related to content modulation and/or misinformation, and must identify all “members of our senior staff” and/or “members of our COVID-19 team” who are “in regular touch with … social media platforms,” as “Jennifer Psaki [former White House press secretary] stated at a White House press briefing on or around July 15, 2021.”
The agency must also disclose all “government experts” who are federal officers, officials, agents, employees or contractors, who have “partnered with” Facebook or any other social media platform to address misinformation and/or content modulation, including all communications relating to such partnerships.
Like Fauci, the CDC must turn over information and communications on the “so-called disinformation dozen,” Great Barrington Declaration, alternative news outlets and key experts and scientists who have spoken out against the government’s approach to treating COVID-19 or mandating face masks and lockdowns.
Meta (Facebook) was “commanded” to produce all communications with any federal official relating to misinformation and/or content modulation, to produce all documents and communications-related actions taken based in whole or in part on information received, directly or indirectly, from any federal official and to produce all communications and documents related to a list of search terms that include Kennedy’s name and/or the names of prominent doctors and physicians who were censored for their views on COVID-19.
Facebook also must disclose meetings, communications and documents related to remarks made by Psaki, who said the White House is “in regular touch with these social media platforms, and those engagements typically happen through members of our senior staff, but also members of our COVID-19 team,” and regarding the White House’s efforts to flag “problematic posts for Facebook that spread disinformation.”
Similar requests were made to other government officials and social media platforms, including Twitter, YouTube, Instagram and LinkedIn.
Lawsuit alleges collusion to suppress disfavored speakers and viewpoints
Attorneys general of Louisiana and Missouri in May filed a lawsuit alleging government defendants “colluded with and/or coerced social media companies to suppress disfavored speakers, viewpoints, and content on social media platforms by labeling the content ‘disinformation,’ ‘misinformation’ and ‘malinformation.’”
The court lawsuit alleges social media companies falsely labeled truthful content “disinformation” and “misinformation” and contends the suppression constitutes government action, violating free speech protected by the U.S. constitution.
The complaint also alleges that DHS’ Disinformation Governance Board was created “to induce, label, and pressure the censorship of disfavored content, viewpoints and speakers on social-media platforms,” and that HHS and DHS violated the Administrative Procedure Act to “hold unlawful and set aside final agency actions” that are deemed to be an abuse of power and arbitrary and capricious.
The lawsuit provides several examples of truthful information that was censored by social media companies who later admitted the content was truthful or credible.
According to The Epoch Times, the lawsuit could help bring to light the Biden administration’s “behind-the-scenes efforts” to discourage the dissemination of information related to the lab-leak theory of COVID-19’s origins and the efficiency of masks and lockdowns.
I’ve been looking again at Covid’s origins and the start of the pandemic. Last time I wrote on it I argued that Italy brought in China-style lockdowns on March 8th and 10th 2020 mainly as a result of panic owing to the leap in the death rate, with it being clear from the hospital situation there were many more deaths to come. I still believe that that was the immediate trigger for imposing lockdowns at the time. However, I now recognise that that is far from the full story. What it leaves out is the backdrop of who was pushing for lockdowns throughout the preceding two months, and why.
Two key pieces of data have emerged in the last few months that help to bring the picture into clearer focus. The first is that with the arrival of Omicron the Chinese have continued fanatically to pursue lockdowns, crippling their economy as they do it. To my mind, this is convincing evidence that the Chinese are sincere about their belief in the radical new disease management strategy they inaugurated on January 23rd 2020 in Wuhan. I initially (in 2020) thought it may be an elaborate ruse to convince the world to do something monumentally and pointlessly self-destructive. But it appears they really do think lockdowns are highly effective and the right way to fight a disease like COVID-19. I’m aware some suggest it could just be a cunning strategy to strengthen the grip of the ruling party on the population, but all the evidence indicates to me that they actually are trying to fight the disease in this way.
If this is accepted then one of the key pieces of the puzzle snaps into place: the global Covid narrative has, both behind closed doors and in front of them, been driven in part by the Chinese Government’s commitment to its extreme suppression strategy and its desire for other countries to adopt it as well. It’s been suggested this derives from a sense of national pride and seeking vindication of their efforts and ideas, and is part of a wider aim of achieving global Chinese cultural supremacy, which sounds plausible to me.
The second key piece of data are emails sent by White House Chief Medical Advisor Dr. Anthony Fauci, which reveal that behind closed doors as late as February 26th 2020, Dr. Fauci was still, as he had been consistently up to that point, advising people not to panic. But as of February 27th his approach suddenly changed and, from that moment on, he began consistently pushing restrictions.
On February 26th he wrote to CBS News that Americans should not yield to fear:
You cannot avoid having infections since you cannot shut off the country from the rest of the world… Do not let the fear of the unknown… distort your evaluation of the risk of the pandemic to you relative to the risks that you face every day… do not yield to unreasonable fear.
But by the next day he was writing to actress Morgan Fairchild that the American public should prepare for pandemic restrictions:
It would be great if you could tweet to your many Twitter followers that although the current risk of coronavirus to the American public is low, the fact that there is community spread of virus in a number of countries besides China… poses a risk that we may progress to a global pandemic of COVID-19… And so for that reason, the American public should not be frightened, but should be prepared to mitigate an outbreak in this country by measures that include social distancing, teleworking, temporary closure of schools, etc. There is nothing to be done right now since there are so few cases in this country and these cases are being properly isolated, and so go about your daily business. However, be aware that behavioural adjustments may need to be made if a pandemic occurs.
Interestingly, February 27th was also the day the media narrative in the U.S. shifted, with the New York Times leading the way with its first alarmist piece, by Peter Daszak of the EcoHealth Alliance, and also an alarmist podcast with science and health reporter Donald G. McNeil Jr., which quoted directly from China a 2% mortality rate for the virus.
The context for this shift was a WHO press briefing on February 24th by Bruce Aylward, who had just concluded a WHO-China Joint Mission on COVID-19 and told the world that lockdown worked and “you have to do this. If you do it, you can save lives and prevent thousands of cases of what is a very difficult disease.”
The timing obviously suggests the events are connected, but crucially it also implies that Fauci and those around him were not part of the behind-the-scenes decision of Aylward to throw the WHO’s weight behind the Chinese approach. This leaves, then, the question of why Fauci & Co flipped from their previous position of playing down the threat from the virus and not supporting extreme Chinese-style interventions to going all in with the panic.
The picture being painted here is of at least two ‘conspiracies’ going on – the Chinese one, seeking to push lockdowns as part of Chinese vindication and cultural supremacy, and the Fauci & Co one, the potential motives for which are discussed below. I am pretty confident these are not the same ‘conspiracy’, as I assume that Fauci and Co are not motivated by vindicating China and advancing its cultural supremacy (I’ve seen no evidence this should be the case).
A further element to throw into the mix is that the first Western lockdown occurred three days before the Aylward WHO briefing, on February 21st 2020, in a region of 50,000 people in Lombardy. Oddly, it seems to have been an isolated local initiative in response to the first identified ‘cases’ led by the regional health chief Giulio Gallera, with no clear links to the WHO or any other known lockdown protagonists. It would be interesting to ask Mr. Gallera why he decided to follow such a radical course of action that day.
Italy locked down on March 8th and 10th, a response it seems to the climbing death rate, and most of the rest of the world followed in the ensuing two weeks. The U.S. Government was persuaded by Deborah Birx and others to back lockdowns on March 16th. On March 12th-14th, U.K. Government ministers and officials did a media round promoting the idea of aiming for herd immunity and keeping calm and carrying on. However, that strategy soon collapsed in the face of shifting public opinion and alarmist models from scientists like Imperial’s Neil Ferguson. After March 23rd, Sweden was the only holdout among Western Governments.
Such a mess of uncoordinated action confirms to my mind a picture of different groups driven by different motives and agendas which sometimes overlap, catalysed by groupthink and hysteria, rather than any grand behind-the-scenes conspiracy involving all in a coordinated fashion.
The Chinese Communist Party is a crucial actor, of course. It invented lockdowns and since then has persistently pushed them to the rest of the world, including through an all too willing WHO. However, that doesn’t mean that all who promote panic and lockdowns do so because they are in thrall to China or doing its bidding.
So what was the deal with Fauci & Co – why did they oppose panic and lockdowns until February 27th, then flip to become among their most eager and high-powered proponents?
Fauci’s emails show that, starting at the end of January and into February 2020, he organised a series of secretive video conferences and phone calls because he and his associates suspected the virus may have been genetically modified and leaked from a lab. Yet despite these suspicions, on February 19th the group wrote a letter to the Lancet denouncing the lab leak as a “conspiracy theory”. The organiser of the letter was Peter Daszak of the EcoHealth Alliance, one of Fauci’s associates who it later turned out had been funding gain of function research at the Wuhan Institute of Virology of exactly the kind that was suspected as being responsible for creating COVID-19. Biologist Nick Patterson notes a grant application from EcoHealth Alliance to DARPA (the research agency of the U.S. Department of Defence), of which he says, “as far as I can make out, the plan here was for WIV to collect live virus, ship it to the USA, have U.S. scientists genetically modify the virus, and then ship modified virus… back to China”.
In light of information like this and Fauci and Co’s preoccupation during February 2020 with the origin of the virus, culminating in their cynical effort to suppress the claims of lab leak and genetic modification, I surmise that their major motivation was to cover themselves for the possibility that they and their research fields would be held responsible for the virus. Initially this took the form of suppressing the lab leak theory while also playing down the threat from the virus, which they would have been keen to be as uneventful as possible. But why then the flip to panic mode after February 27th? Did the WHO backing lockdowns on February 24th change the equation, so it was no longer deemed viable or good cover to oppose the new approach? The path of least resistance in other words. A related question is whether they were genuinely persuaded that the measures would be effective or if they retained an unspoken scepticism. If they did retain any scepticism there’s been precious little sign of it since March 2020.
Overall, I see no indication of a grand plan from the earliest days in which all are working from a common script to a common goal. Instead, I see various groups with their own agendas, interests and fears. It’s clear that, following Aylward’s team’s visit, China managed to capture the WHO and bring it on board with championing lockdowns. However, the motives of everyone besides China are largely opaque. Why did Aylward become China’s biggest fan – was he threatened or bribed or just duped and naïve? Why exactly did Lombardy regional health chief Giulio Gallera respond to the first cases in his region by imposing a Chinese-style lockdown even before the WHO had backed them? Why did Fauci flip on February 27th? What about curious figures like Deputy National Security Advisor Matt Pottinger, highlighted by Michael Senger, who despite being a known China critic, was a major alarmist influence within the White House from the get-go, drawing on mysterious ‘contacts in China’ to call for panic and restrictions as early as January?
What drove each of these people to get behind the closing down of society as the ‘solution’ to a respiratory virus? We can largely see now who did what and when. What’s mainly missing is the why.
In a watershed moment for lockdown sceptics, Prime Minister candidate Rishi Sunak has said his opposition to lockdown is a reason that Conservative members should vote for him to lead the country.
In an interview with Andrew Marr on LBC, the former Chancellor said that last December he cut short an overseas trip and flew back to London to intervene and “stop us sleepwalking into a national lockdown”.
“We were hours away from a press conference that was going to lock this country down again because of Omicron,” he said. “And I came back and fought very hard against the system, because I believe that would be the wrong thing for this country, with all the damage it would have done to businesses, to children’s education, to people’s lives.”
It is the first time a leading politician, whether from the Government or opposition, has suggested that being opposed to lockdown is a reason to vote for him or favour him for office. It is indicative of a significant shift in public opinion about Covid restrictions, particularly that Sunak felt able to be so bold in trumpeting his opposition to lockdown and his role in defeating it without a need to couch it in careful language about taking the virus seriously and being cautious. That his interviewer, Andrew Marr, didn’t challenge him on it is further indication of how opinion has changed. This is despite a number of recent high profile calls for restrictions to be reintroduced, most recently by the editors of the BMJ and HSJ.
It offers hope that the future lies with politicians willing to turn their back on the ruinous and illiberal restrictions of 2020 and 2021.
Here is what Rishi said in full.
I’ll tell you what I was doing in December, though, because I still remember it quite vividly. You know what I did in December was fly back from a Government trip I was on overseas and I flew back to this country to stop us sleepwalking into a national lockdown. Because we were hours away from a press conference that was going to lock this country down again because of Omicron. And I came back and fought very hard against the system, because I believe that would be the wrong thing for this country, with all the damage it would have done to businesses, to children’s education, to people’s lives.
That’s really important in December Andrew because we were hours away, we were hours away from a national lockdown, but I came back and challenged the system, and said this is not right and we don’t need to do this and I’m glad I won the argument. But it should give people some confidence that in the same way I stood up for Brexit, in the same way I did that, I am prepared to push hard and fight for the things that I believe in even when that’s difficult.
Once upon a time, news that a top-level COBRA meeting was held at Downing Street – in the midst of a government re-shuffle – would stir a flicker of alarm or excitement (depending on one’s temperament). Now, when COBRA meetings are called due to a spike in positive tests for a strain of flu, we know that the government is more interested in showing it is responding rather than actually responding or indeed having anything worth responding to.
The reason for the cabinet-level emergency meeting was the arrival of summer. You might have thought that aides could have briefed senior government figures privately on a brief period of warm-to-hot weather that some years occurs over July and August in the British Isles. No doubt the aides had been watching weather maps on television news which have been showing the country seared scarlet, despite the fact that the temperature has been as expected. The establishment, which has been both pushing the idea of a climate crisis and has come to believe its own alarmism, takes the normal heatwaves as evidence of a climate emergency. To be fair, if you consume mainstream television news and radio – plus factual programmes – at high levels, your residual belief in climate emergency will have reached near unbreakable levels.
The Met Office – an arm of the scientific-governmental-media complex – has issued amber and red alerts for sunny days last week. Even GBNews has been running a chyron of dire warnings advising against unnecessary travel. The gleeful doomsayers of the mainstream media have been playing up the dangers of hot weather, adding obligatory comments about anthropogenic global warming. Some exaggerate for tactical effect – to scare people into new types of behaviour – while others simply follow the herd, led by untested assumptions and a climate of fear.
COVID hysteria is not as potent a tool of control and fear as it once was. News reports of a rise in positive tests (caused due to COVID becoming an endemic, mild infection) – which were notably not accompanied by data suggesting increased deaths – generated only a brief uptick in mask-wearing by the “doing their part” crowd. There will be another push to impose a COVID lockdown this winter, but the government, NGOs and international bodies wanting to use lockdown as a tool for restricting the freedom and independence of people are looking for extra excuses. Marburg virus and Monkey Pox have both been pitched as potential reasons to restrict freedom but seem to have been met with muted responses.
So, while authorities worldwide tinker with their systems of control, climate emergency looks like a viable route. It has already been used to promote green policies, lower vehicle emissions, stringent insulation regulations, phasing out of gas boilers. The aim is to restrict means of private travel, monitor energy consumption and use digital identities and social-credit systems to micromanage people, using all-pervading systems to instil fear and obedience. It seems likely that air-quality readings may be used to restrict non-electric vehicle use in cities. Expect this winter to see more “stay at home” advisory notices due to cold weather – essentially for any days with road ice – but a big push next summer for not only advisory notices but action. This may include local or national government imposing fines on businesses which “irresponsibly” remain open during hot weather, as well as more vehicle restrictions.
The government and its medical-environmental partners use fear and coddling to direct a compliant population away from free choice and towards authoritarianism. The exaggerated heat warnings have been a feature of British mainstream news and activist press releases for many years, mainly as a means of reinforcing the necessity of environmental measures. However, the government and its partners have seen how compliant and fearful the population is and are ready to use weather as a tool for population suppression via the means of lockdown.
Be watchful and notice how the mass-media, establishment science, giant corporations and government work together to knit ever tighter the control of the managerial elite in order to remove your ability to judge risk for yourself, travel independently and run your businesses.
In this interview we spoke with Dr. Peter McCullough, an American cardiologist and outspoken critic of the questionable handling of the COVID-19 “pandemic.” He is one of the most notable and credentialed voices speaking out in the United States and is a wealth of information. He was vice chief of internal medicine at Baylor University Medical Center and a professor at Texas A&M University, and one of the largest donors to the school, leading to a scholarship named after him. Upon speaking out the university shamelessly attacked him. He is articulate, balanced and a voice of reason.
In this interview he clarifies the following points:
– PR testing methodology
– Therapeutic Nihilism
– Myocarditis amongst the vaccinated
– Early treatment suppression prior to the pandemic
– Persecution of medical personnel for exercising their licensed authority
– The upside down irrational nature of COVID-19 policies including vaccine mandates
– The efficacy of a global, indiscriminate mass vax campaign, in contrast to vaccination of mainly at-risk patients
Many of my readers had one Covid a long time ago, or never had Covid, are not having another Covid so far, and may not realize how badly are things going in Covid-land in Europe and highly vaccinated areas of USA.
More than one out of 15 Brits is having COVID today (Jul 19, 2022). This is higher than ever before. An “unexpected” largest-ever wave of a yet-another variant Ba.5 is reinfecting highly-vaccinated countries one more time. Hospitals are strained, because sick, force-injected health care workers are staying home due to their Covid reinfections, and patients are hospitalized at record rates. Excess mortality is rising.
People are, naturally, becoming worried as they or their relatives have two-week-long bouts of Covid reinfections that do not feel mild to them and leave them exhausted. My own opinion is that we are on the verge of significant increases in overall mortality. I am quite worried about that.
Rumblings of discontent are appearing. The powers-to-be are wondering what to do.
So, the so-called “Independent SAGE” just came up with a “seven-point plan” to combat COVID. The plan is so spectacularly stupid that it reads like a parody. Here it is, from the British Medical Journal no less.
This plan is the product of supposedly the “best Covid minds”, the leading thinkers of UK science, whose recommendations influence UK policy. What did these minds produce? Let’s look.
They are proposing to do more of same!
The “clear and consistent messaging” is a theme of the pandemic, it relates to a bad idea that all officials should parrot one line during a so-called “emergency”, to avoid confusing the public. The result of this policy was a lack of independent thinking, as well as censorship of any dissenting voices, that led to groupthink. What message, pray tell, should such “clear and consistent messaging” convey? The seven-point plan?
The efforts to promote “vaccine uptake” are particularly laughable in July of 2022. Here’s how vaccine uptake looks in the UK:
Of special interest is a need to have a “clear long-term plan to address waning immunity and immune escape”. What they are saying is that they do not have such a plan. They merely want to have a plan, which they do not have, as of now.
The concept of “air filtration” refers to a sincerely expressed, but misguided idea that retrofitting buildings with “air filtration devices” will stop the pandemic. While I personally like almost all people who advocate it, I also recognize that it is largely futile, for many reasons having to do with physics and gas dynamics.
Air filtration that could effectively capture airborne virions, would need to turn over enormous volumes of air every minute, through the finest filters, continuously. This is not compatible with existing buildings’ HVAC systems. It would also cost a fortune in electric bills and create a lot of heat. I do not want to get into this discussion too much, but “air filtration” of that kind is not possible in most establishments or homes.
The “FFP3 masks” are obvious non-starters because of difficulties wearing them. Making the public wear such masks in 2022 is impossible.
The worst part of this proposal is the so-called “equitable global provision of vaccines”. This is a code word for bribing governments of poor countries into forcing their citizens to take “vaccines” that these wise but poor people refuse to take voluntarily. The countries with unvaccinated majorities are the future of humanity, in my opinion. They are largely at herd immunity precisely because they refused to vaccinate. Yet, Independent SAGE wants to inject them with non-working “vaccines” in the name of “equity”. Why?
The crazy “Independent SAGE” advisers are anything but sage, are actually stupid, and I am very sorry that they have been UK’s thought leaders since 2020.
Here’s a clip from “Idiocracy”. While it is funny, it shows President Camacho actually solving his country’s problem of dying plants, with his three-point plan of hiring the smartest person in the world named Not Sure. Not Sure figured out the problem and proceeded to stop using Brawndo to water plants.
Brawndo’, which owned the FDA, went bankrupt. The plants started growing, given clean water. Any parallels with the present?
P.S. Please do not think that I am badmouthing the UK by criticizing British Covid experts: Covid experts in the USA are so much worse and could not even come up with a “seven-point plan”. So there is no “USA Covid plan” that I could criticize.
The medical establishment professes to know an awful lot. A few days before lockdown in March 2020, it knew that covid was not a High Consequence Infectious Disease and downgraded it accordingly. Exhibiting an Orwellian capacity for doublethink, it also knew that societies ought to be bludgeoned with lockdowns to prevent the spread of the not so highly consequential, and therefore downgraded, pathogen. In addition, it somehow just knew, without being able to explain why, that a cost-benefit analysis would be superfluous, so none was done. Until July 2020, it knew, based on decades of established science, that masking in community settings was useless in preventing the spread of respiratory illnesses. Then, with no new science to support a 180-degree turn, it just knew that masks had to be mandated.
It was so certain that mass vaccination with the experimental injections was the only course of action to take in the face of the not so highly consequential covid disease that it suppressed alternative cheap, safe and effective treatments. It was also quite sure that it had to censor and threaten doctors like Sam White with debarment because he expressed concerns about mass vaccination with the shoddily tested and hastily marketed novel ‘vaccines’. It somehow reasoned that doctors expressing genuine concern for patient safety was a threat to patient safety and that the only way to guarantee patient safety was for every single doctor, journalist and media outlet to sing from the same Big Pharma-sponsored hymn sheet.
Granted, the medical establishment’s stance during covid has not been underpinned by rational considerations, but that is precisely what has given it so much latitude to respond to ‘the crisis’. There is no limit to what you can know and do when you don’t have to prove rationally how you came to know it. Life is a never-ending carousel of trade-offs. You can either plod through things methodically and get it right or you can blast ahead at Warp Speed with the misplaced confidence of Joe Biden on a bicycle.
So, given the medical establishment’s boundless knowledge in times of crisis, it’s more than a little odd that it does not know why young and apparently healthy adults all over the world are dying in unprecedentedly large numbers. It is uncharacteristically stumped: it professes that there are simply no clues whatsoever to this disturbing phenomenon.
It is in the grip of such uncharacteristic knowledge paralysis that it seems incapable of exploring obvious lines of enquiry, such as asking questions like: when was the last time that governments all over world put a jackboot on the neck of every adult citizen to inject them with novel ‘vaccines’ employing an experimental gene-based technology tested under quality control conditions that would have run-of-the-mill crack dealers shaking their heads in disbelief?
What’s in a name?
Once you unlock the mystery of the medical establishment’s peculiar brand of epistemology, you begin to understand that how it comes to ‘know’ things is directly related to how it defines the problems it is trying to solve. For people who think in straitjackets, the problem of young people dying inexplicably is a medical problem. But, for the unbounded thinkers in charge of the medical establishment, it is a Public Relations problem. Through that lens, the obvious line of enquiry into experimental mass vaccination gets ruled out because it is too rational, too much of a threat to its reputation and too unprofitable.
The solution to this PR problem is to repackage it in such a way that it is seen as an insoluble medical mystery, as insoluble as the mystery of life itself – a mystery that one can debate in philosophical terms but never get to grips with in any practical way. The most insoluble mysteries are those that have been around since the dawn of time and yet continue to evade unravelling. This is axiomatic to the quality of insolubility – Plato, Seneca, Aquinas, Voltaire and Heidegger will have all given it their best shot and yet here we are today, none the wiser. The seed must be sown in the public mind that this is not a new problem that arose coterminously with mass global experimental covid vaccination but has been ‘a thing’ since the dawn of medical things.
The key to all successful narrative management is naming the problem. When Edward Bernays, the father of propaganda, was tasked by the tobacco industry in the early 20th century with breaking the taboo against women smoking cigarettes, he didn’t call them cancer sticks. He called them torches of freedom. With one ingenious stroke of the naming pen, the tobacco industry doubled its market overnight and women won the right to lung cancer.
In a similar vein, society must understand that young adults inexplicably dying before their time is the result of a bona fide disease of unfathomable cause – a mysterious and yet proper medical thing – and not a possible crime against humanity.
At first glance, the name they’ve hit on does not fill you with confidence that the best medical minds were enlisted in the brainstorming session. But it certainly has an air of does-what-it-says-on-the-tin. It is partly for that reason that Sudden Adult Death Syndrome (“SADS”) is a stroke of marketing genius. It’s got an easy acronym that chimes flippantly with the tragic outcome and yet is also readily accessible to authoritative tones after three pints in the pub. This is 90 per cent of the battle in getting the public to understand in no uncertain terms that SADS is ‘a thing’. A serious thing. It trips off the tongue very easily and yet is not so silly that it sounds like the lead-in to a crazy story developed by a contestant in an episode of BBC One’s Would I Lie to You.
As far as the medical establishment is concerned, the perception that SADS on this scale is a recent global phenomenon must be resisted on the grounds that it could become associated with a big new event – like mass global experimental covid vaccination. So no, SADS is not new. It’s been a thing for eons. And for sure, a Google search seems to suggest that SADS has been around for as long as cancer. But Allan Stevo’s investigation using his “8.6 pound Webster’s Encyclopaedic Unabridged Dictionary of the English Language from 1992” – which is impervious to algorithmic re-engineering – reveals that the term did not exist in 1992. But who are you going to trust – the colourful, digital pages of Google or the crumbling ancient parchments of Webster’s Encyclopaedic Unabridged Dictionary of the English Language?
I’m not saying there have never been mysterious unexplained deaths of young and apparently healthy adults. They were just so rare that they weren’t on the radar, even of dictionaries whose job it is to define all things known to the vast bulk of humanity. Surely this merits delving into a little deeper?
Whatever you do, don’t solve the problem – autopsies die a sudden death
One way to solve the apparently insoluble problem of sudden adult death would be to conduct autopsies on as many sudden adult deaths as resources will allow. It turns out that the Chief Pathologist at the University of Heidelberg, Dr. Peter Schirmacher, was doing just that very thing. In the summer of 2021, his team had just finished conducting 40 autopsies on people who had died within two weeks of vaccination and concluded that 30-40% of them died from the vaccine. He was pushing for many more autopsies of vaccinated people.
His claims were naturally dismissed by the German Government. From Dr. Schirmacher’s perspective, the dismissal by bureaucrats of his professional autopsy findings must have felt like being an army private in the battlefield reporting by radio to a lieutenant that he’d just been shot in the leg, only to have the lieutenant ask, “How can you be sure?”. But the powerful bureaucrats must have had good reason to dismiss his professional work although these reasons weren’t made clear.
Calls by the Federal Association of German Pathologists pushing for more autopsies of vaccinated people were also treated with disdain. No other autopsies have been performed apart from 15 done by Dr. Arne Burkhardt towards the end of 2021, which found “clear evidence of vaccine-induced autoimmune-like pathology in multiple organs” in 14 of 15 cases, all of which were ignored by all health authorities and mainstream media. No further autopsies have been reported and Dr. Schirmacher and his colleagues have gone quiet, after being so emphatic about the risks and the need for as many autopsies as possible.
On the face of it, the only way to prove what is causing the uptick in mysterious sudden deaths has died a sudden death. But the sensible and mature conclusion to draw from the silence of the autopsy doctors is that they have realised they were wrong and that the powerful bureaucrats and MSM journalists, who know nothing about autopsies, were right. Only a ‘conspiracy theorist’ would think there was a cover-up going on, right?
Public Relations – The Mail Online takes a proper gander at SADS
In any case, why bother with autopsies when, according to this article in the Mail Online, the best medical minds in Australia are getting to grips with the problem by “opening up a new national register”. Yes, that’s right, they’re at the cutting edge of the Fourth Industrial Revolution (4IR) in which all our problems will be solved by data, algorithms, AI and registers. We’re leaving behind the grime of autopsies, post-mortems and diagnosing diseased patients by prodding them with stethoscopes and asking them time-wasting questions. We’ve got registers now.
Now, at first glance it might seem that the article would not be out of place in The Onion or the Babylon Bee because of idiotic tautologies like this one:
But pointing out that SADS, a death syndrome, is fatal is not cheap satire. It is a reminder that contained in SADS is both the disease and its inescapable prognosis of death.
Another reason why SADS is more of a thing than any other medical thing is that a diagnosis of SADS can never be wrong. It can only be given after death has occurred and only three boxes need to be ticked – did the deceased die without warning; was the deceased an adult in the prime of life and, crucially; do we intend to follow 4IR protocols to establish cause of death by doing nothing other than entering some data in a register? Yes, to all three? Job done. The clever cardiologist who is quoted extensively in the article jokes that SADS is a “diagnosis of nothing” but, once she has taken her tongue out of her cheek, I’m sure she is only too aware of how clever a diagnosis this is.
After correctly informing the reader that this particular death syndrome is fatal, the article recounts how a typical sudden death unfolds. The victim doesn’t come down for breakfast, but no one is concerned because we (white-collar workers at least) all work from home these days so having a lie-in is par for the course. The whole tone of the description of the tragic death of a young person in the peak of life is bizarrely deadpan. Again, you would be wrong to interpret this apparently tasteless approach as cheap satire. The banal tone is deliberately intended to drive home the point that SADS is just another puzzle in the countless puzzles that the universe, with its twisted sense of humour, flings at humanity on a regular basis.
The article contains pictures of very young actors clutching at their hearts with distressed expressions. Again, you would be wrong to think this is cheap and tasteless. How else are we to understand that SADS really is a thing? I think the visual message here is that if you’re under 40 and find yourself clutching at your heart while out jogging, be appropriately but not overly distressed because, while your heart may stop beating and no-one will ever know exactly why, SADS is definitely a thing. And the national register will never forget you.
Because the article is intended to be as informative as possible, it shares some very helpful warning ‘signs’ of SADS. Top warning sign number one is a family history of a SADS diagnosis. The happy smiley cardiologist who was selected to educate the public about SADS advises that your SADS clock might be silently ticking down if any of the following things have happened to you: fainting from exercise, over-excitement or just being ‘startled’. If you are one of those people who faints at the mere thought of exercise, you would have obviously been on the SADS register a very long time ago, had it been in operation. Your continued existence is actually more of a mystery than SADS itself, but let’s not complicate things any further. Suffice to say your clock is ticking down and your housemates should not be too surprised if you don’t come down for breakfast in the next couple of weeks. At least the Mail Online has prepared them. And you, come to think of it.
If you are wondering why I refer to the cardiologist as “the happy smiley doctor”, click the link to the article and it will be as clear to you as her sparkling eyes and teeth. There is a photo of her beaming as though she has just been awarded the Nobel Prize for medicine when in fact, she is being quizzed about the grizzly business of young people dying for reasons that cannot be fathomed by the best brains in medicine. Why is she happy and smiley instead of sombre and uneasy? Is this another tactless error by the Mail Online inadvertently making the whole article look like cheap satire? Not at all. World War II propaganda used the very same technique to placate the masses in times of great uncertainty. Here is a WWII poster of a woman exuding the same brand of devil-may-care insouciance in the face of adversity:
Ok, so I’ve chosen a Nazi propaganda poster to compare with the happy smiley Australian doctor. Is this in bad taste? Personally, I don’t think so. Today’s brave new world of forced masking, forced lockdowns and forced medical experimentation must be met head-on with bold comparisons. Yesterday’s Nazis weren’t big on bodily autonomy and nor are today’s Australians (or Canadians, or Austrians, or French for that matter). Am I saying, rather unsubtly, that the Western world is becoming the very thing it fought 75 years ago? Only if you believe that people were robbed of the human right to voluntary informed consent by being coerced into taking the ‘vaccines’. ‘Vaccines’ which, let’s be clear, have absolutely nothing to do with the current spate of sudden adult deaths all over the world.
Am I unsubtly hinting that the Mail Online’s proper gander at SADS is actually propaganda for the medical establishment? Only if you believe that the responsible thing to do would be to show a picture of a doctor holding her head in her hands, tears of shame flowing from her eyes for failing to at least consider one potential and obvious cause of the mysterious deaths. I think we’re all in agreement here – that would not be responsible journalism. Far better to show a happy beaming doctor exuding the confidence of someone who is certain that SADS really is a thing, that it’s been a big thing for quite some time and that, while getting a ‘diagnosis’ of SADS is indeed the end of the world for you, you will die knowing that we are getting on top of this very real thing because we’re fighting it with a register and not with futile autopsies.
There’s a mention in the article about the role of genes because you can’t have a totally mysterious and fatal death syndrome (if the Mail Online can get away with this clever tautology, why can’t I?) without genes playing a role. Of course they haven’t, and never will, find a SADS gene, but that’s beside the point when proffering genes causality. Genes are the building blocks of life; your life ends suddenly without warning, ergo there must have been something wrong with your building blocks.
The ‘best advice’ the happy smiley cardiologist can give is: if you’re related to anyone who’s had an unexplained death, ‘it’s extremely recommended you see a cardiologist.’ Which seems pointless because a SADS diagnosis rests entirely on you having no detectable condition right up to the point you clutch your heart in desperation and keel over. If the condition was a recognised detectable one, mitigation strategies would likely kick in pre-heart clutching and, even if you ended up dying from that condition, your death would be labelled something other than SADS by virtue of its having been detected. SADS is the ultimate catch-22 – the doctors don’t know what’s wrong with the patient before they die and there’s no way of knowing afterwards (autopsies now being off the table) so the patient gets a posthumous SADS ‘diagnosis’, and is successfully entered on a register.
The Mail Online article is perfect except for that flawed bit of advice which seems to fail to recognise the complex circular nature of SADS. Telling people to have a thorough check-up before SADS threatens the very existence of SADS. Being cynical, I would say this advice is a ruse to give a boost to the happy smiley doctor’s billings.
As I’ve repeated ad nauseum here at the Daily Sceptic, excess mortality provides a far better measure of the pandemic’s impact on mortality than the ‘official’ Covid death rate.
When it comes to cross-country comparisons, the ‘official’ Covid death rates are particularly deficient. Testing and diagnosis vary dramatically, so two countries with the same actual death tolls may still have very different ‘official’ death tolls – just because one tested more or had broader criteria for diagnosis.
Excess mortality, as most readers are no-doubt aware, is the difference between the number of deaths observed during the pandemic and the number that were expected, based on previous years. A five-year average is often used for the number of expected deaths – though one can use a linear trend or more complicated extrapolation instead.
Here’s a very simple example. Suppose a country had roughly 100,000 deaths per year in 2015, 2016, 2017, 2018 and 2019. Then in 2020, it records 120,000 deaths. In that case, excess mortality would be 20,000 deaths.
But of course, if we want to compare this country to other countries, the ‘20,000 deaths’ isn’t very useful. Larger countries will have more excess deaths just because there are more people at risk of death. And this is something we need to account for when making comparisons, or else we’ll conclude that all the small countries did well and all the large ones did badly.
So why not just divide the ‘20,000 deaths’ figure by the country’s population, thereby obtaining ‘excess deaths per 100,000 people’? Indeed, that’s exactly what the WHO did for its recent estimates of excess deaths associated with the pandemic (which were widely covered in the media).
Well, there’s a problem with this method of adjustment: countries have different age structures. And this matters because the risk of death (from both Covid and everything else) is far higher in older age-groups than in younger age-groups.
Consider two countries with the same number of excess deaths, say 20,000. One has a population of 10 million and one has a population of 12 million. Suppose the 2 million ‘extra’ people in the second country are all under the age of 40. So above the age of 40, the two countries have identical age structures.
Using the WHO’s method of adjustment, excess mortality would be 200 per 100,000 in the first country, but only 167 per 100,000 in the second country. Yet this clearly ‘rewards’ the second country. Why? Very few deaths occur among people under 40, so including them in the denominator artificially pulls down the rate of excess mortality.
Rather than dividing by the country’s population, there’s a much better way of making excess mortality figures comparable: divide by the number of expected deaths. This gives you a percentage, which is neither biased against large countries, nor against countries with aging populations.
As a matter of fact, the WHO’s decision to divide by the country’s population may help to explain its widely-reported (but almost certainly wrong) finding that Britain had less excess mortality than Germany. Estimates based on percentages clearly show that Britain had more excess mortality. Yet because Germany’s population pyramid has a narrower base, the denominator in the WHO’s calculation will have been smaller.
Having said that, I doubt the WHO’s estimates are substantially different from those based on percentages. But that’s not the point. The point is they used a bad method of adjustment, when an equally simple and better one was available.
What would be your prediction for those who are both unvaccinated against COVID-19 and never previously infected? Let’s say those of working age(20 – 55) in fairly good health.
Should they be worried about Avian Flu and Monkeypox, since they have not experienced an infection by SARS-CoV-2?
Are they at risk for serious illness from these more infectious (and future more virulent) SARS-CoV-2 mutants?
Answer:
It would be quite unbelievable that they didn’t get exposed to SC-2 given the high infectiousness of previously and currently circulating variants. Ideally, they should have their Abs tested (anti-S would be sufficient since they’re not vaccinated). They can also have their Abs tested against Flu. If all this is negative (which would point to poor activation of natural immunity), they can just take one shot of a live attenuated measles or mumps or rubella or varicella vaccine (or all together in one shot) to boost their innate immune response. (However, they should only do so if they got MMR(V)-vaccinated in the past. The better their innate immune status, the lower the likelihood they are going to catch severe disease from these viruses. But anyhow, for a person in good health, it is highly unlikely to develop severe disease from Monkeypox (as it is – for now(!) – not highly infectious) or from Avian Flu as they must at least have had contact with Flu viruses in the past and hence, have some ‘Flu-trained’ innate immunity.)
Unvaccinated can now largely forget about contracting severe C-19 disease as the next big mutation will most likely make the unvaccinated resistant to the virus. However, if they have not yet been infected at all by any of these highly infectious variants, they could still contract C-19 disease (before that new variant emerges) and become seriously ill (but not ‘severely ill’ as longas they are in good health with no comorbidities and predisposing factors). To avoid this, they should either prevent risky contacts (difficult) till the next variant appears (in my opinion, just a matter of weeks) or take Ivermectin or HCQ as soon as symptoms manifest (but not prophylactically).
The BBC is either the worst media organisation on Earth or the best, depending upon your perspective. On the one hand it is a truly world-class propaganda machine. On the other it is completely incapable of challenging government narratives or power because it is effectively a branch of the UK government and is itself beholden to power.
As an agency of the state, the BBC has actively sought to destabilise overseas governments around the world. It is a master of propaganda and frequently lies to the public, either overtly or by omission, with the goal of convincing the people to accept whatever falsehood or agenda it has been tasked to sell.
From top to bottom, the BBC’s commitment to journalistic integrity is missing. It is simply a mouthpiece for the ruling cartel. It comprehensively fails to deliver the most crucial social function of journalism: holding power to account.
According to the corporation’s published values, “trust is the foundation of the BBC.” The Oxford English Dictionary offers a pejorative meaning of the word “trust”: “acceptance of the truth of a statement without evidence or investigation.”
This definition of “trust” seems appropriate for the BBC. While it declares itself to be “independent, impartial and truthful,” it routinely trots out claimed “facts” that lack supporting evidence and produces investigative reports absent any real investigation. Indeed, the BBC broadcasts appalling lies as a matter of course.
And so it is with a certain degree of mirth that we now learn from the BBC that it intends to air a “documentary” about a phenomenon it has already opted to call “vaccine hesitancy.” (Bear in mind: A “documentary” is “a film or television or radio programme that gives facts and information about a subject.”)
The producer of the upcoming programme, due to air on the 20th of July, Craig Hunter, explains:
Moving beyond the often misrepresented debate, this programme reveals why some people remain vaccine hesitant.
The deprecatory word “hesitant” means “tentative, unsure, or slow in acting.” There is no room in the programme-maker’s minds for the possibility that people who chose to remain “unvaccinated” have considered the risk-benefit of these shots, have looked at the available evidence and have decisively concluded that they don’t want a COVID-19 jab.
Hunter’s statement absolutely “misrepresents” the debate. As Craig is the producer of the forthcoming BBC documentary, it seems the chance of the programme delivering a balanced exploration of the issue is remote to non-existent. There is little reason to expect the BBC to provide anything that is “independent, impartial and truthful.”
Indeed, objectively discussing any facet of the alleged pandemic is way beyond the reach of the BBC. As a state propaganda operation, all it can do is parrot the official narrative spouted by the government and its partners, who are, in this instance, the pharmaceutical corporations.
. . . confronting the latest science and statistics to emerge in the field and dissecting how misinformation spreads on social media.
The BBC cannot succeed in this task because the science and the statistics rarely support the disinformation it has been commissioned to spread. Consequently, it must deceive and misdirect its audience to make sure they believe its propagandist tripe. More to the point, the BBC is itself one of the most prolific distributors of online misinformation.
For example, in its press release the BBC says:
After multiple lockdowns and more than 197,000 deaths, experts are warning we’re now entering a fifth wave of the pandemic. So why are five million adults in the UK still yet to receive a single dose of the vaccine?
Putting aside for the moment that there are actually more than eleven million UK adults yet to receive a single dose of the vaccine and the fact that the BBC itself reported that there were just three million less than a week later, the rest of this claim assumes, without good reason, that there was a “pandemic” in the first place. We now know there is very little evidence that a genuine pandemic ever occurred, yet the BBC keeps up its charade by omitting key facts.
Here is one such key fact: In 2009 the World Health Organisation (WHO) suddenly and radically changed its long-time definition of the word “pandemic.” It removed the defining phrase “several, simultaneous epidemics worldwide with enormous numbers of deaths and illness,” replacing it with reference to a disease for which “most people do not have immunity.” Under this definition, practically any new disease can be declared a pandemic. But the BBC won’t inform its audience of the WHO’s changed definition nor the fact that under the original, and more valid, definition, COVID-19 disease could never have been described as a pandemic.
The BBC has left its audience in the dark about a number of other important facts: (1) as of the 19th of March 2020, UK public health authorities did not consider COVID-19 to be “a high-consequence infectious disease” due to its low mortality; (2) all-cause mortality (the overall death rate) in 2020, the year of the so-called “outbreak,” ranked as only the 9th highest death rate in the first two decades of the 21st century; (3) people with injured limbs and stomach pain were being admitted to hospital as registered COVID-19 patients, thus giving an entirely false impression of a severe pandemic disease; (4) there is no statistical evidence of any beneficial effect from any supposed COVID-19 vaccine; and (5) many deaths have been caused, not by any single disease, but by the policy response to an alleged pandemic.
In the press release for its upcoming “documentary,” the BBC refers to the figure of 197,000 UK deaths from COVID-19 as if that figure is scientifically or statistically indisputable. Not only can it be questioned, it has been! So why doesn’t the BBC mention this?
By deliberately using the largest possible figure, the BBC is attempting to elicit an emotional reaction to the highly questionable number of supposed COVID deaths. The BBC is playing on people’s emotions in order to avoid any objective analysis of the data. Its intention is to manipulate its audience into unquestioning acceptance of a story about a severe pandemic which does not stand up to scrutiny.
Let’s pause to make an important point: The collection, analysis and reporting of COVID-19 mortality data has been deliberately altered and manipulated by governments around the world, all of which worked and continue to work in partnership with the WHO. Nowhere has this manipulation been more pronounced than in the UK, where the engineering of COVID-19 mortality statistics has been quite remarkable.
Mainstream media outlets, especially the BBC, have perpetuated baseless fearmongering. For example, for the first time in the history of reporting deaths from a respiratory disease, propagandists like the BBC are reporting cumulative deaths instead of the annual mortality rates or the more common seasonal variation in these figures. If the same were done for, say, influenza, total flu deaths would be measured in millions, depending on the chosen start date for the accumulation of the mortality data.
Another example: The BBC has chosen to report what the government claims to be “deaths with COVID-19 on the death certificate.” While some of these likely were genuine COVID-19 deaths, the expansive, all-encompassing methodology that the government and the WHO created to attribute as many deaths as possible to COVID-19 renders the bulk of these statistics virtually meaningless. In truth, we don’t know how many people in the UK have died as a direct consequence of COVID-19, though estimates in the region of 20,000 – 25,000 seem reasonable.
The BBC never questions the mortality statistics. It simply takes the figures from the government and reports them without any investigation or analysis. This is essentially the BBC’s purpose: to report whatever it is told to report.
In announcing its faux documentary, the BBC says:
In this timely, eye-opening investigation [. . .] Professor Hannah Fry seeks to understand why eight percent of the population remain unvaccinated against Covid-19.
In reality, more than twenty percent of adults in the UK are “unvaccinated.” The BBC can’t even write a press release for its forthcoming documentary without publishing deceptive statistics. So it is safe to say the “documentary” itself will be little more than a marketing promotion for the jabs.
Statistics from the UK Health Security Agency (UKHSA) on vaccine coverage in England show that the actual percentage of the “unvaccinated” population is very close to thirty percent, not the eight percent the BBC alleges. The English figures are broadly representative of the UK as a whole and can be extrapolated.
Jab uptake increases with age. Thus, if we exclude children under 18, then more than twenty percent of the UK adult population are unvaccinated.
The subsequent uptake of booster jabs has declined markedly from the one-and-two dose uptake. Millions of Brits decided, for whatever reason, that two shots was their limit. Only fifty-two percent have elected to have the first booster (the third jab).
Speaking in December 2021, then-Health Secretary Sajid Javid said that, in order to be considered fully vaccinated for the proposed “covid pass,” one would need to have three jabs. If three becomes the definition of “fully vaccinated,” which seems unlikely given the lack of interest, then currently forty-eight percent of the total UK population, and more than thirty-five percent of the adult population, are not “fully vaccinated.”
The BBC launched its “documentary” by trying to deceive its audience into believing that there is only a tiny fringe minority of indecisive folk who don’t want the COVID jabs. In point of fact, it is nearly half of the UK population.
Not only has the BBC lied about the statistics in its press release, it has even misrepresented the debate it proposed to examine by calling the millions of people who made an informed decision not to have the jabs “hesitant.” But that’s because the BBC is all about propaganda, not journalism.
When some diligent independent researchers did what real journalists are supposed to do and picked up on the BBC’s deception, the BBC simply changed its press release. Since citing real statistics was a bit too tricky for the BBC—after all, it only has an annual budget of around £5 billion—the revisedweb page now reads:
In this timely, eye-opening investigation [. . .] Professor Hannah Fry seeks to understand why a portion of the population remain unvaccinated against Covid-19.
Despite there being no reason to trust anything the BBC ever says, the broadcaster implores its viewers to “trust” it simply by pronouncing its own trustworthiness. For the BBC, your “trust” demonstrates your “faith,” allowing it to tell you stories without the need for investigative journalism or even supporting evidence. By contrast, the evidence invariably reveals that the BBC is completely untrustworthy.
According to BBC, its so-called “documentary” is going to be based on bombarding seven hapless unvaccinated lay people with a barrage of pro-vaccine “experts.” Once browbeaten into submission by these authoritative opinions, the victims will then be subject to the BBC’s logical fallacy tactic of appeal to authority. In other words, these high priests of “the science” will explain how the BBC’s seven victims have been misled by “anti-vaxxer” propaganda.
It is highly likely that even if the seven subjects cogently explain why they have decided not to be injected with experimental concoctions, the BBC will edit out any and all valid points they make—and/or deny whatever evidence they cite. We can make these predictions with relative ease, simply by noting the extraordinary level of deceit already present in the BBC’s press release announcing its “programme.”
We can make still further forecasts about the BBC’s alleged “investigation.” For one thing, it won’t honestly report on the current status of the vaccine trials.
Namely, it will neglect to inform its audience that the NCT04368728 trial of the Pfizer-BioNTech jab isn’t finished. And it will not reveal that neither the NCT04470427 trial of Moderna’s mRNA jab nor Johnson & Johnson’s NCT04614948 Jansen trials have posted any results, because these trials, too, are incomplete. Moreover, the BBC will strenuously avoid pointing out the implication of these facts—probably by not reporting them.
Unless the recipients of these drugs were told that the jabs they were about to receive were experimental, they couldn’t possibly have given their informed consent. Consequently, whenever they weren’t informed, administration of the jab contravened nearly every known medical ethic, including those outlined in the Nuremberg Code. But the BBC won’t mention this, either.
It is also safe to say that the BBC will not tell its audience that AstraZeneca concluded the NCT04516746 trial of its AZD1222 adenovirus jab more than a year before schedule by not bothering to conduct a quality control review, rendering its so-called vaccine trial results practically meaningless.
The BBC will not tell anyone that the British Medical Journal (BMJ)disclosed that both Moderna and Jansen (J&J) confirmed that they had given the jabs to their placebo control groups, ending any prospect of their trials ever meeting the basic standards for randomised controlled studies. When the BMJ asked Pfizer if it had done the same, Pfizer declined comment.
Instead, the BBC will almost certainly claim that the jabs have been through extensive clinical trials. It will just omit the part about them having failed to properly complete any.
The BBC will not acknowledge the freedom of information requests and subsequent court ruling in the US that overturned the Food and Drug Administration’s (FDA) decision to delay release of Pfizer’s primary safety monitoring data for 75 years. The Federal Court forced the FDA to release the damning results of Pfizer’s own early monitoring of adverse reactions following the jab rollout in the US and Europe.
In the space of just a couple of months, there were approximately 42,000 adverse reactions to the Pfizer mRNA jab alone, with just over 25,000 of those confirmed by medical exam and the other 16,000+ unconfirmed. Of these, more than 1,200 injuries resulted in death. More than 11,000 of the injured had not recovered from their serious adverse event at the time of reporting.
The BBC certainly won’t report the Israeli study, the results of which indicate that the Pfizer jab prompts a marked decline in male fertility.
Nor will the BBC mention that Pfizer’s own research shows that, contrary to all of Pfizer’s marketing claims, the corporation knew during the trial phase that the lipid nanoparticles used in its jabs found their way into the liver, adrenal glands and spleen and, in particular, accumulated in female recipients’ ovaries.
The BBC may well have to acknowledge the more-than-38,000 possible vaccine deaths reported to the US VAERS system, the 2,200 deaths reported in the UK and the 46,000 deaths recorded by the European Medicines Agency. Its “experts” will point out that there is no evidence that these deaths are caused by the vaccines and will say that the risk of the disease COVID-19 is far higher than any known risks from the COVID-19 jabs.
The BBC will almost certainly make extraordinary and extremely silly claims about how many lives the jabs have allegedly saved. Again these claims will be based upon nothing but baseless assumptions about what could have happened according to some spurious “predictive model.” Rather like claiming your anti-unicorn spray has stopped a million unicorns from grazing your lawn because you don’t have any unicorns in your garden.
As we have just discussed, the risks of harm from COVID-19 claimed by the government and its propaganda outlets—the BBC foremost—are so implausible they verge on absurd. Yet the BBC will not inform its audience that, to date, not one of the regulators has produced a comprehensive risk-benefit analysis for any of the jabs. So the inevitable BBC claims that the jab benefits outweigh the risks will literally be based upon nothing at all.
The BBC will not go anywhere near reporting the findings of a team of eminent German pathologists who performed autopsies on 40 corpses of people who died within two weeks of vaccination—and who identified the vaccine as the likely cause of death in one-third of the cases.
Nor will the BBC report statements like those from the UK regulator, the MHRA, that adverse reactions, including deaths, are significantly undereported, with just ten percent of serious reactions and between two percent and four percent of non-serious reactions recorded.
What the BBC will do instead is rely upon carefully cherry-picked scientific papers, a narrow band of selected “expert opinion,” speculative statistics and emotionally charged anecdotes to convince its audience that the seven victims of its hit piece, though well meaning, are all hopelessly deluded due to the scourge of online disinformation. It may well try to squeeze in reference to the proposed Online Safety Act and suggest that this government policy is essential to tackle the disinformation problem fabricated in its documentary.
Of course, if the BBC were serious about its professed wish to “fully explore this complex and deeply divisive debate,” it wouldn’t simply subject a group of ordinary men and women to a tirade of unchallenged claims from its hand-picked group of “experts.” If it really wanted to tackle the debate with any objectivity or journalistic integrity, it would also report the views of some of the many eminently qualified scientists and physicians who do question the COVID-19 narrative and the alleged safety and efficacy of the vaccines.
It would be genuinely interesting to see people like Professor Sucharit Bhakdi, Dr. Mike Yeadon, Professor Carl Heneghan and Professor Arne Burkhardt explain some of their reservations. Perhaps other scientists, physicians and experts who have questioned the vaccines and the COVID-19 pandemic could be heard.
Maybe the statistician and Nobel Laureate Professor Michael Levitt; epidemiologists like Professor John Ioannidis or Professor Knut Wittkowski; experts in clinical drug development such as Alexandra (Sasha) Latypova; or physicians such as Dr. Peter McCullough or Dr. Roger Hodkinson could be invited to challenge the BBC’s preferred experts.
The audience and the seven subjects of the BBC’s attack could then hear both sides of the argument. But that won’t happen.
Alas, many won’t get to see the BBC’s vaccine marketing programme because they have already decided that they will no longer pay for its propaganda to be beamed into their heads. These numbers are swelling all the time, hence the deceptive plan to allegedly end the BBC license fee while a desperate workaround is conjured up to make sure the BBC’s coffers remain stuffed with gargantuan amounts of public money.
Still, we might get to watch “Unvaccinated, with Professor Hannah Fry” when it finds its way on to Odysee, BitChute, Rumble or some other worthy video-sharing platform. If so, it will perhaps be interesting for some to see how accurate or inaccurate this article is.
In the meantime, let’s give the Beeb the benefit of the doubt and hope this post is way off the mark. Instead of the awful propagandist drivel we might expect, let’s hope the BBC proves that these suspicions are born of nothing but unfounded, anti-BBC bias.
Peter Gøtzsche reviewed every randomised mammography screening trial ever conducted for the Cochrane Collaboration. Cochrane’s headline is that, assuming a 15% mortality reduction, one woman in 2000 avoids dying of breast cancer over ten years. Ten are overdiagnosed and treated. Two hundred experience false alarms.
But that headline assumes the reduction. When Gøtzsche looked only at the trials with adequate randomisation — the higher-quality ones — the reduction disappeared. No effect on breast cancer mortality. No effect on all-cause mortality.
This is the Cochrane finding, published in the establishment’s own database of systematic reviews.
No woman being asked to consent to a mammogram this week knows it.
That is why the new Unbekoming paperback exists. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.
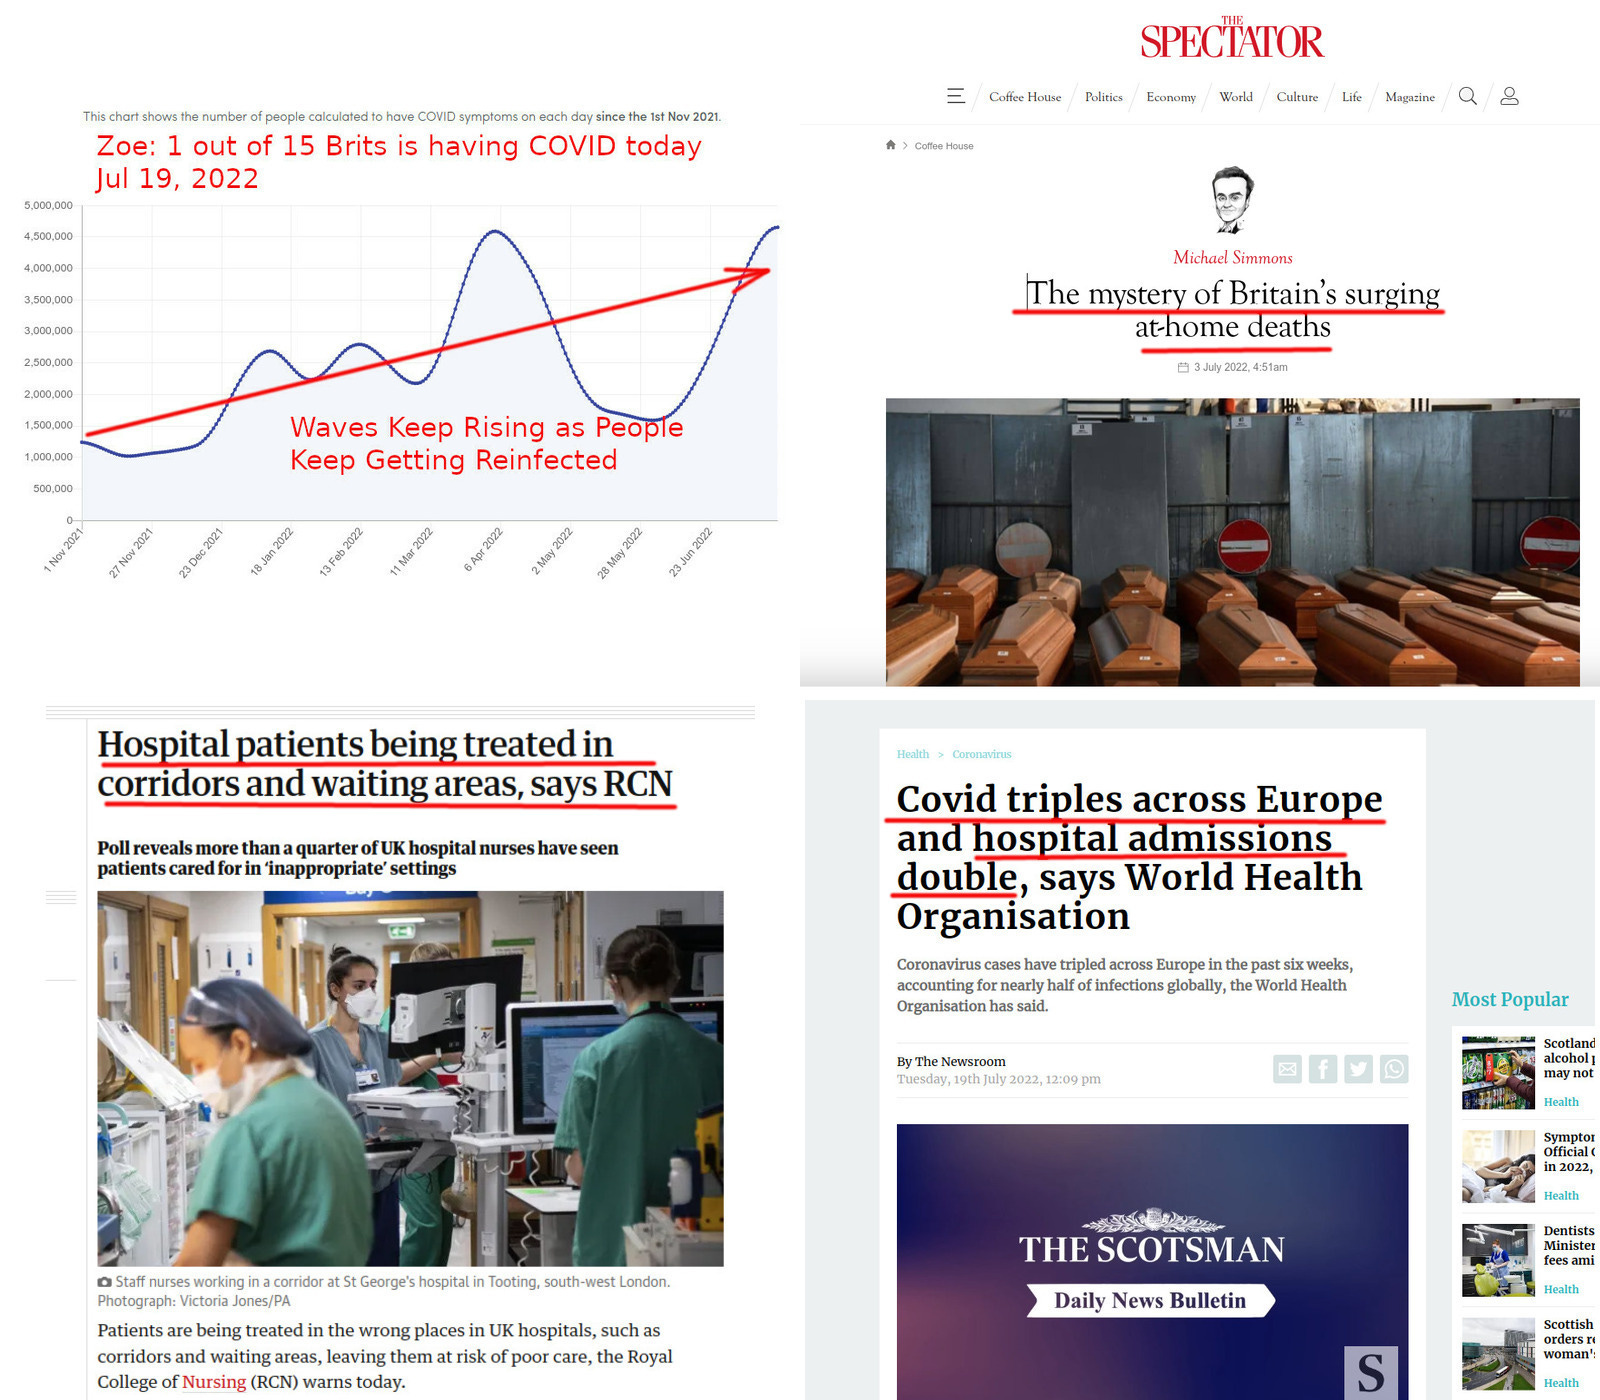

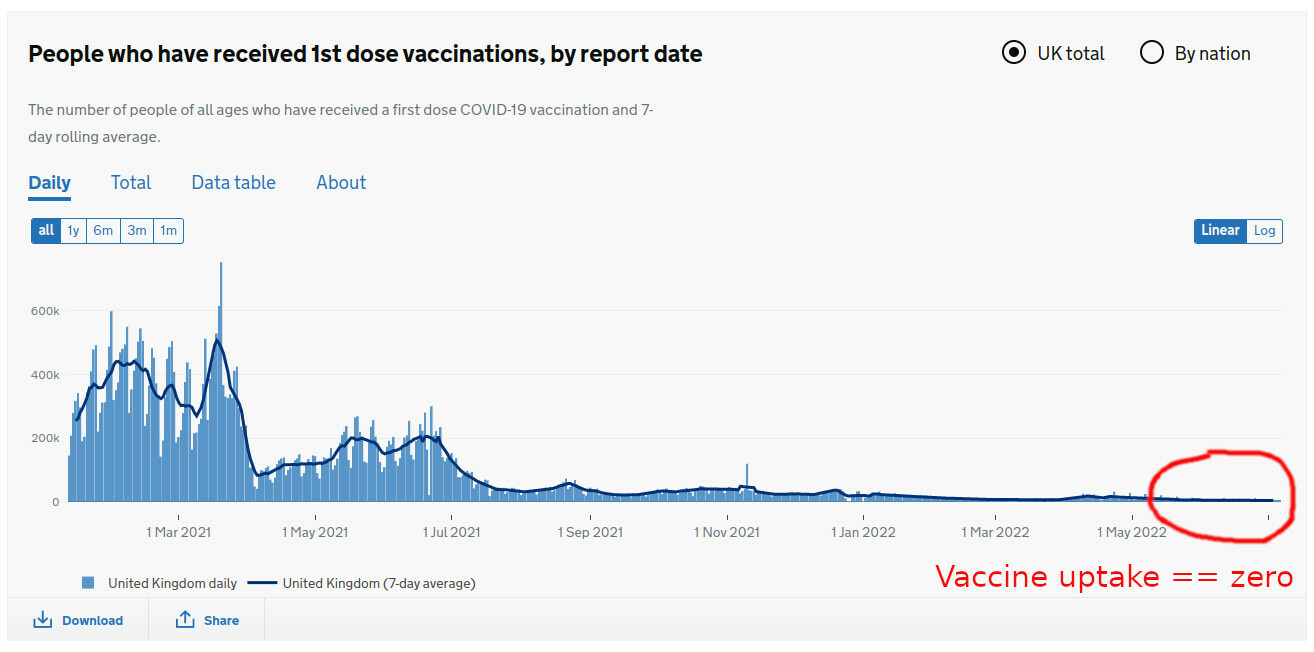





 Aletho News
